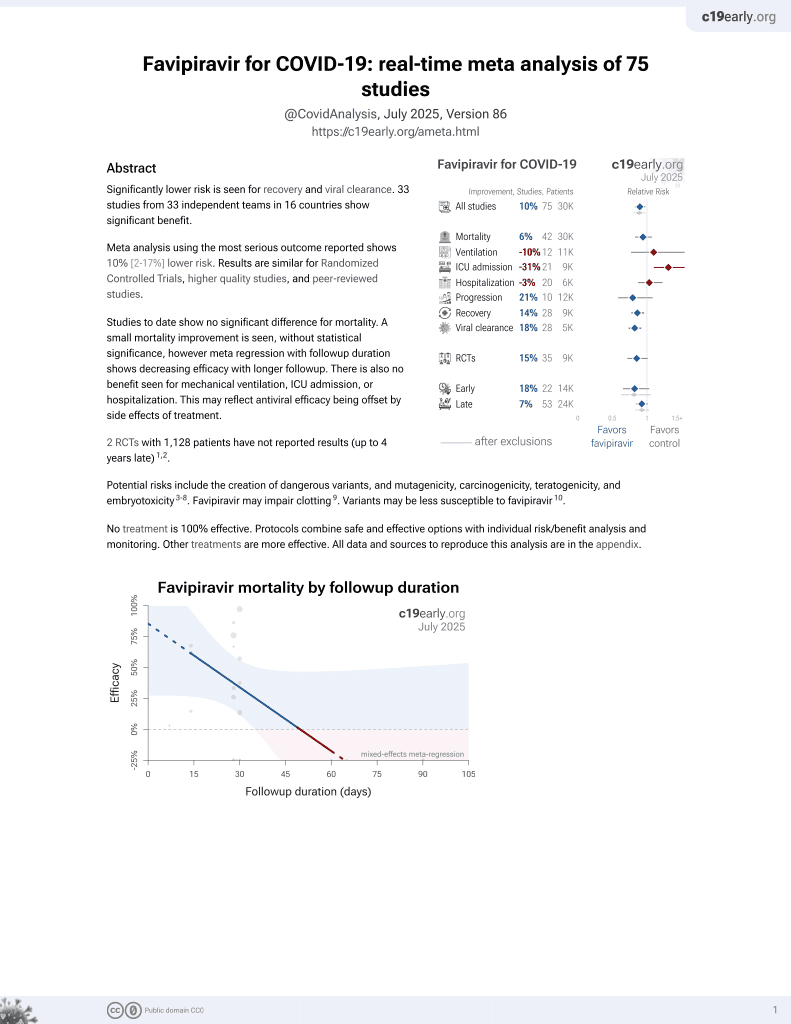
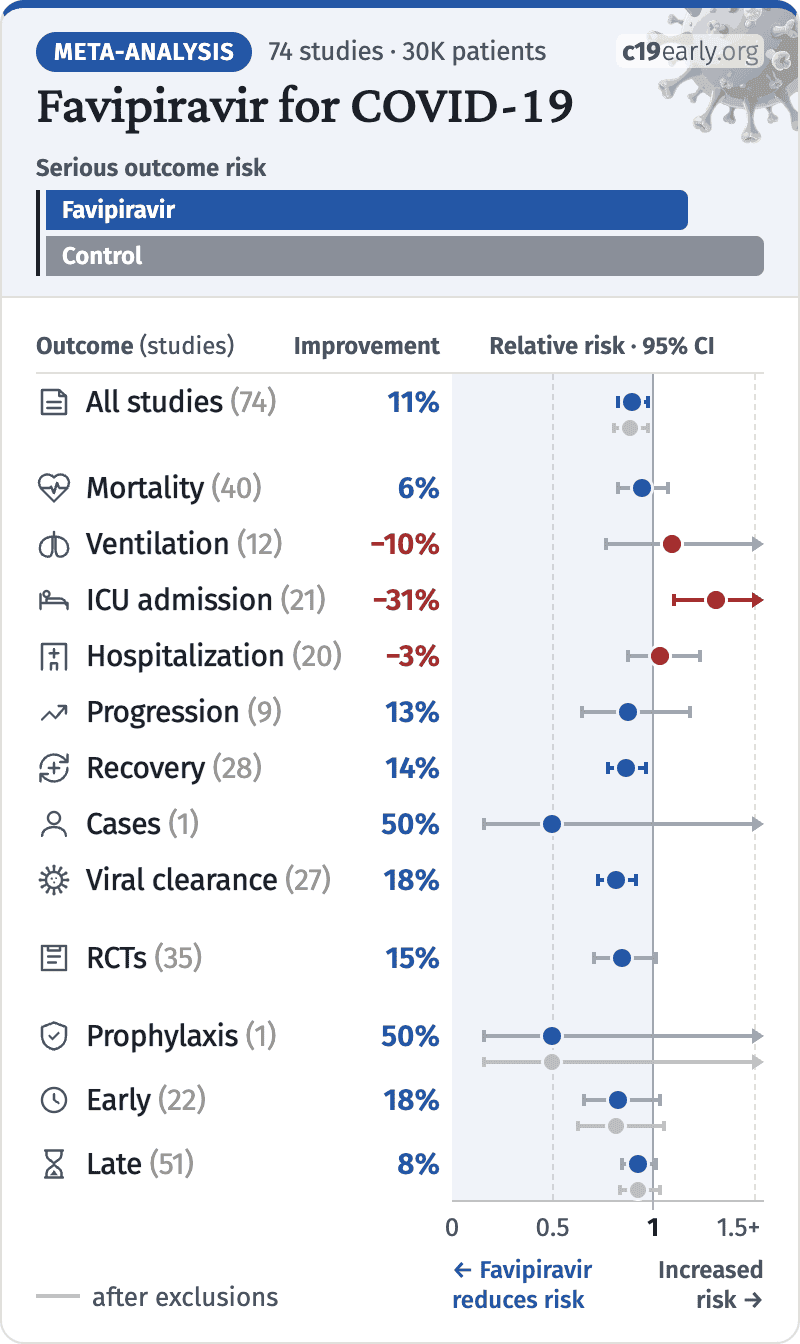
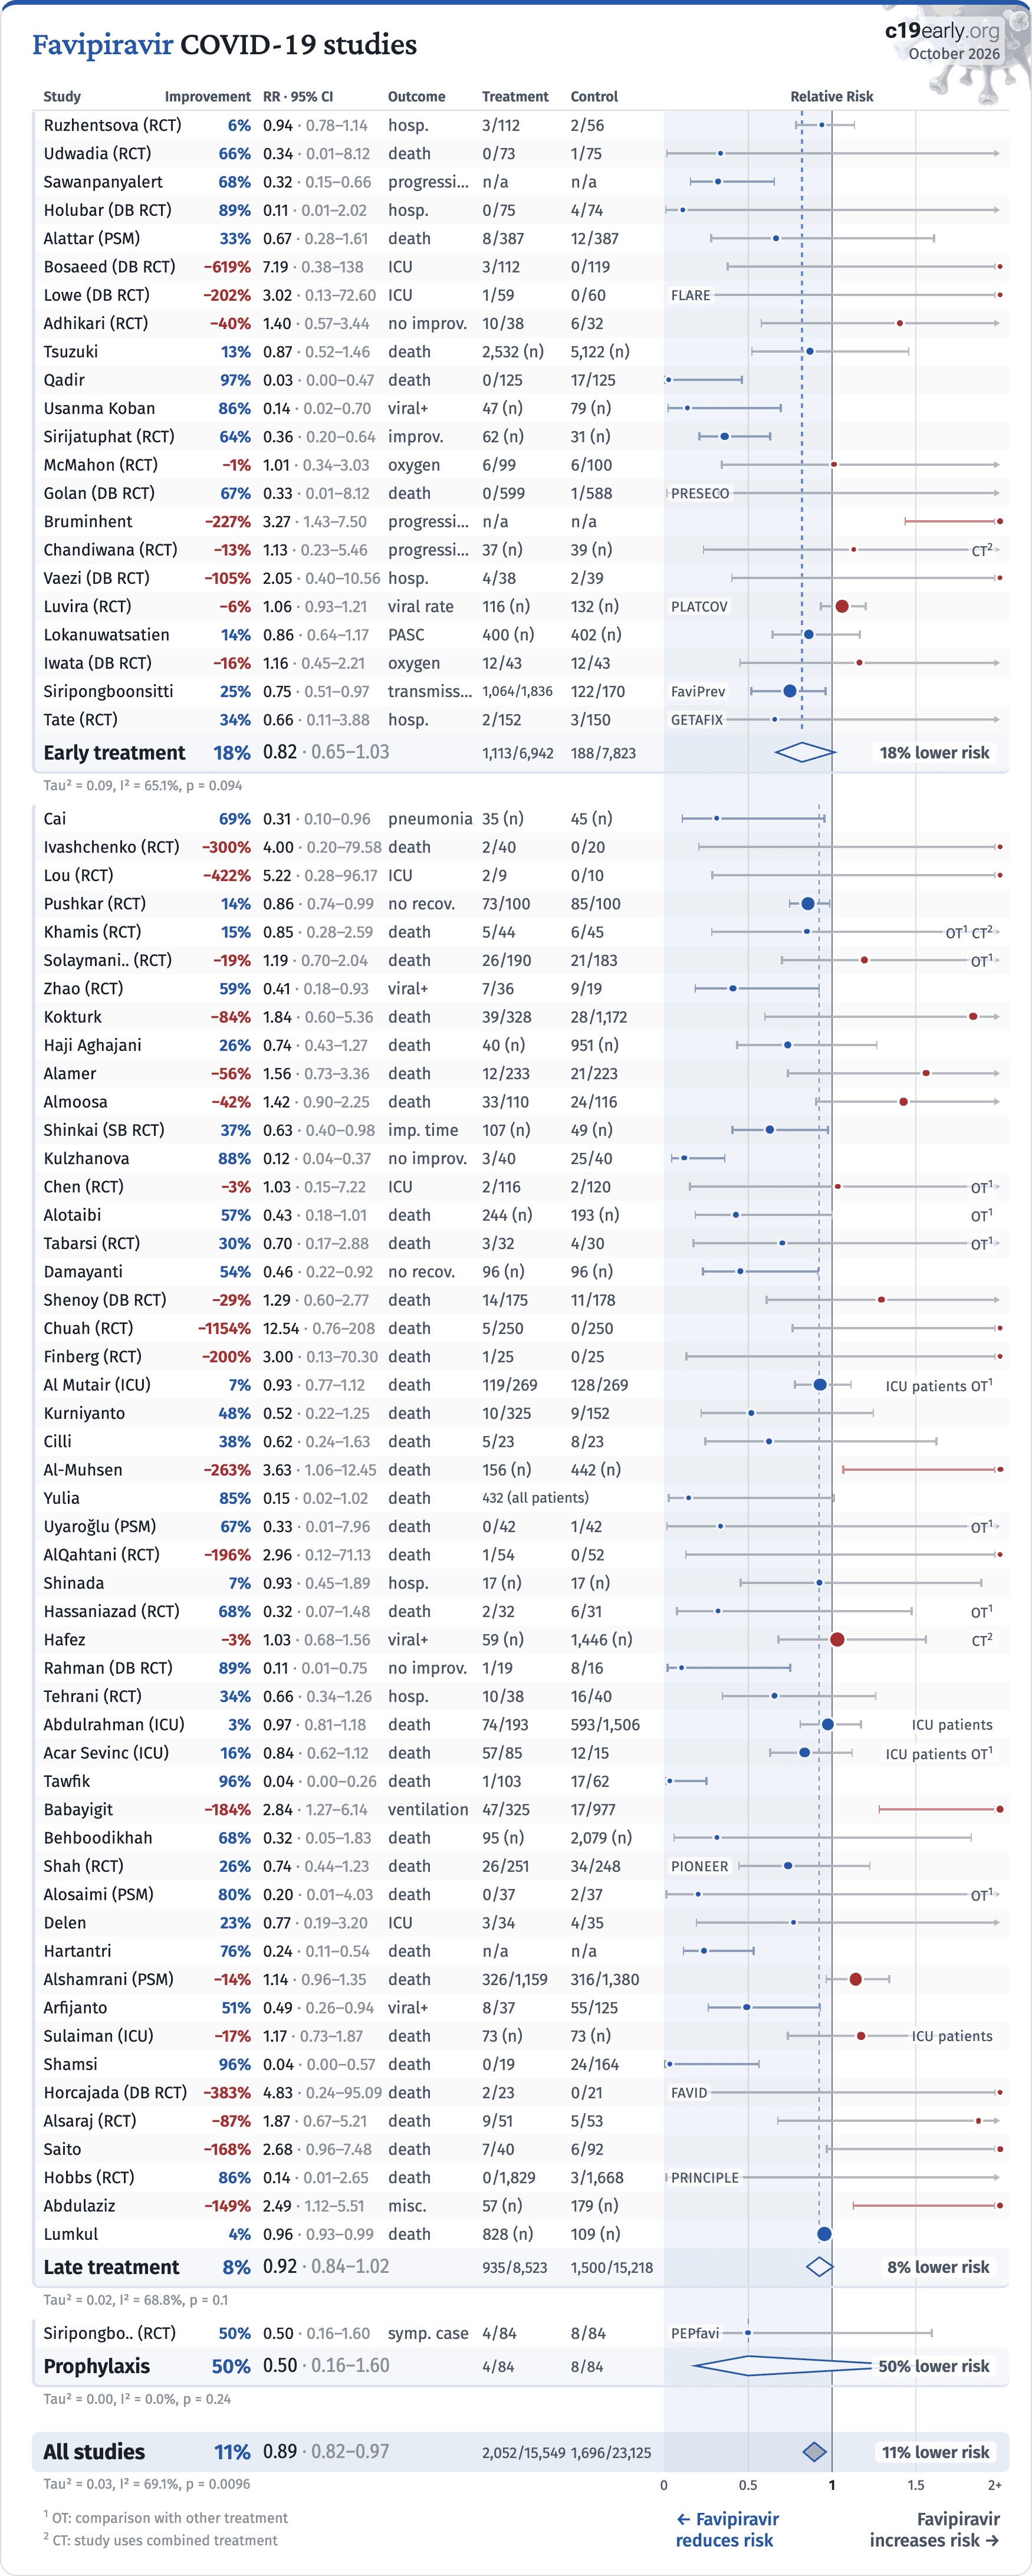
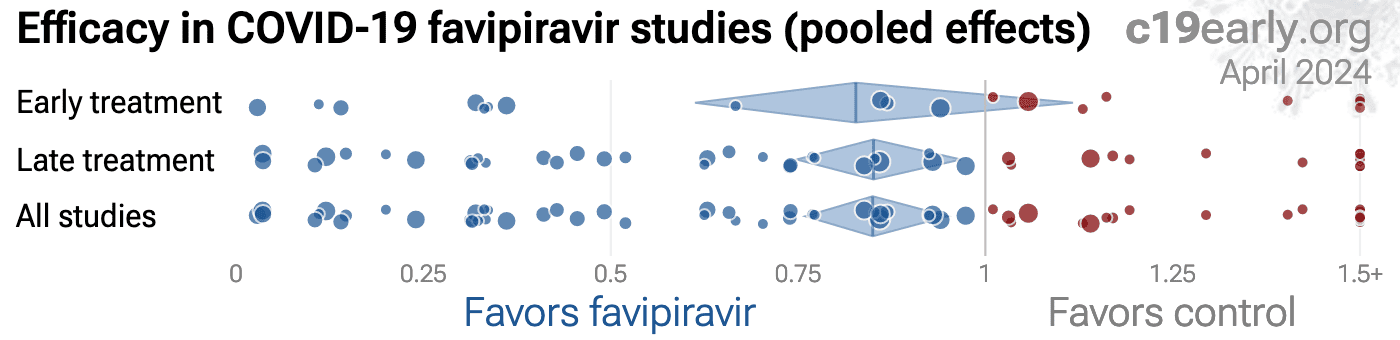
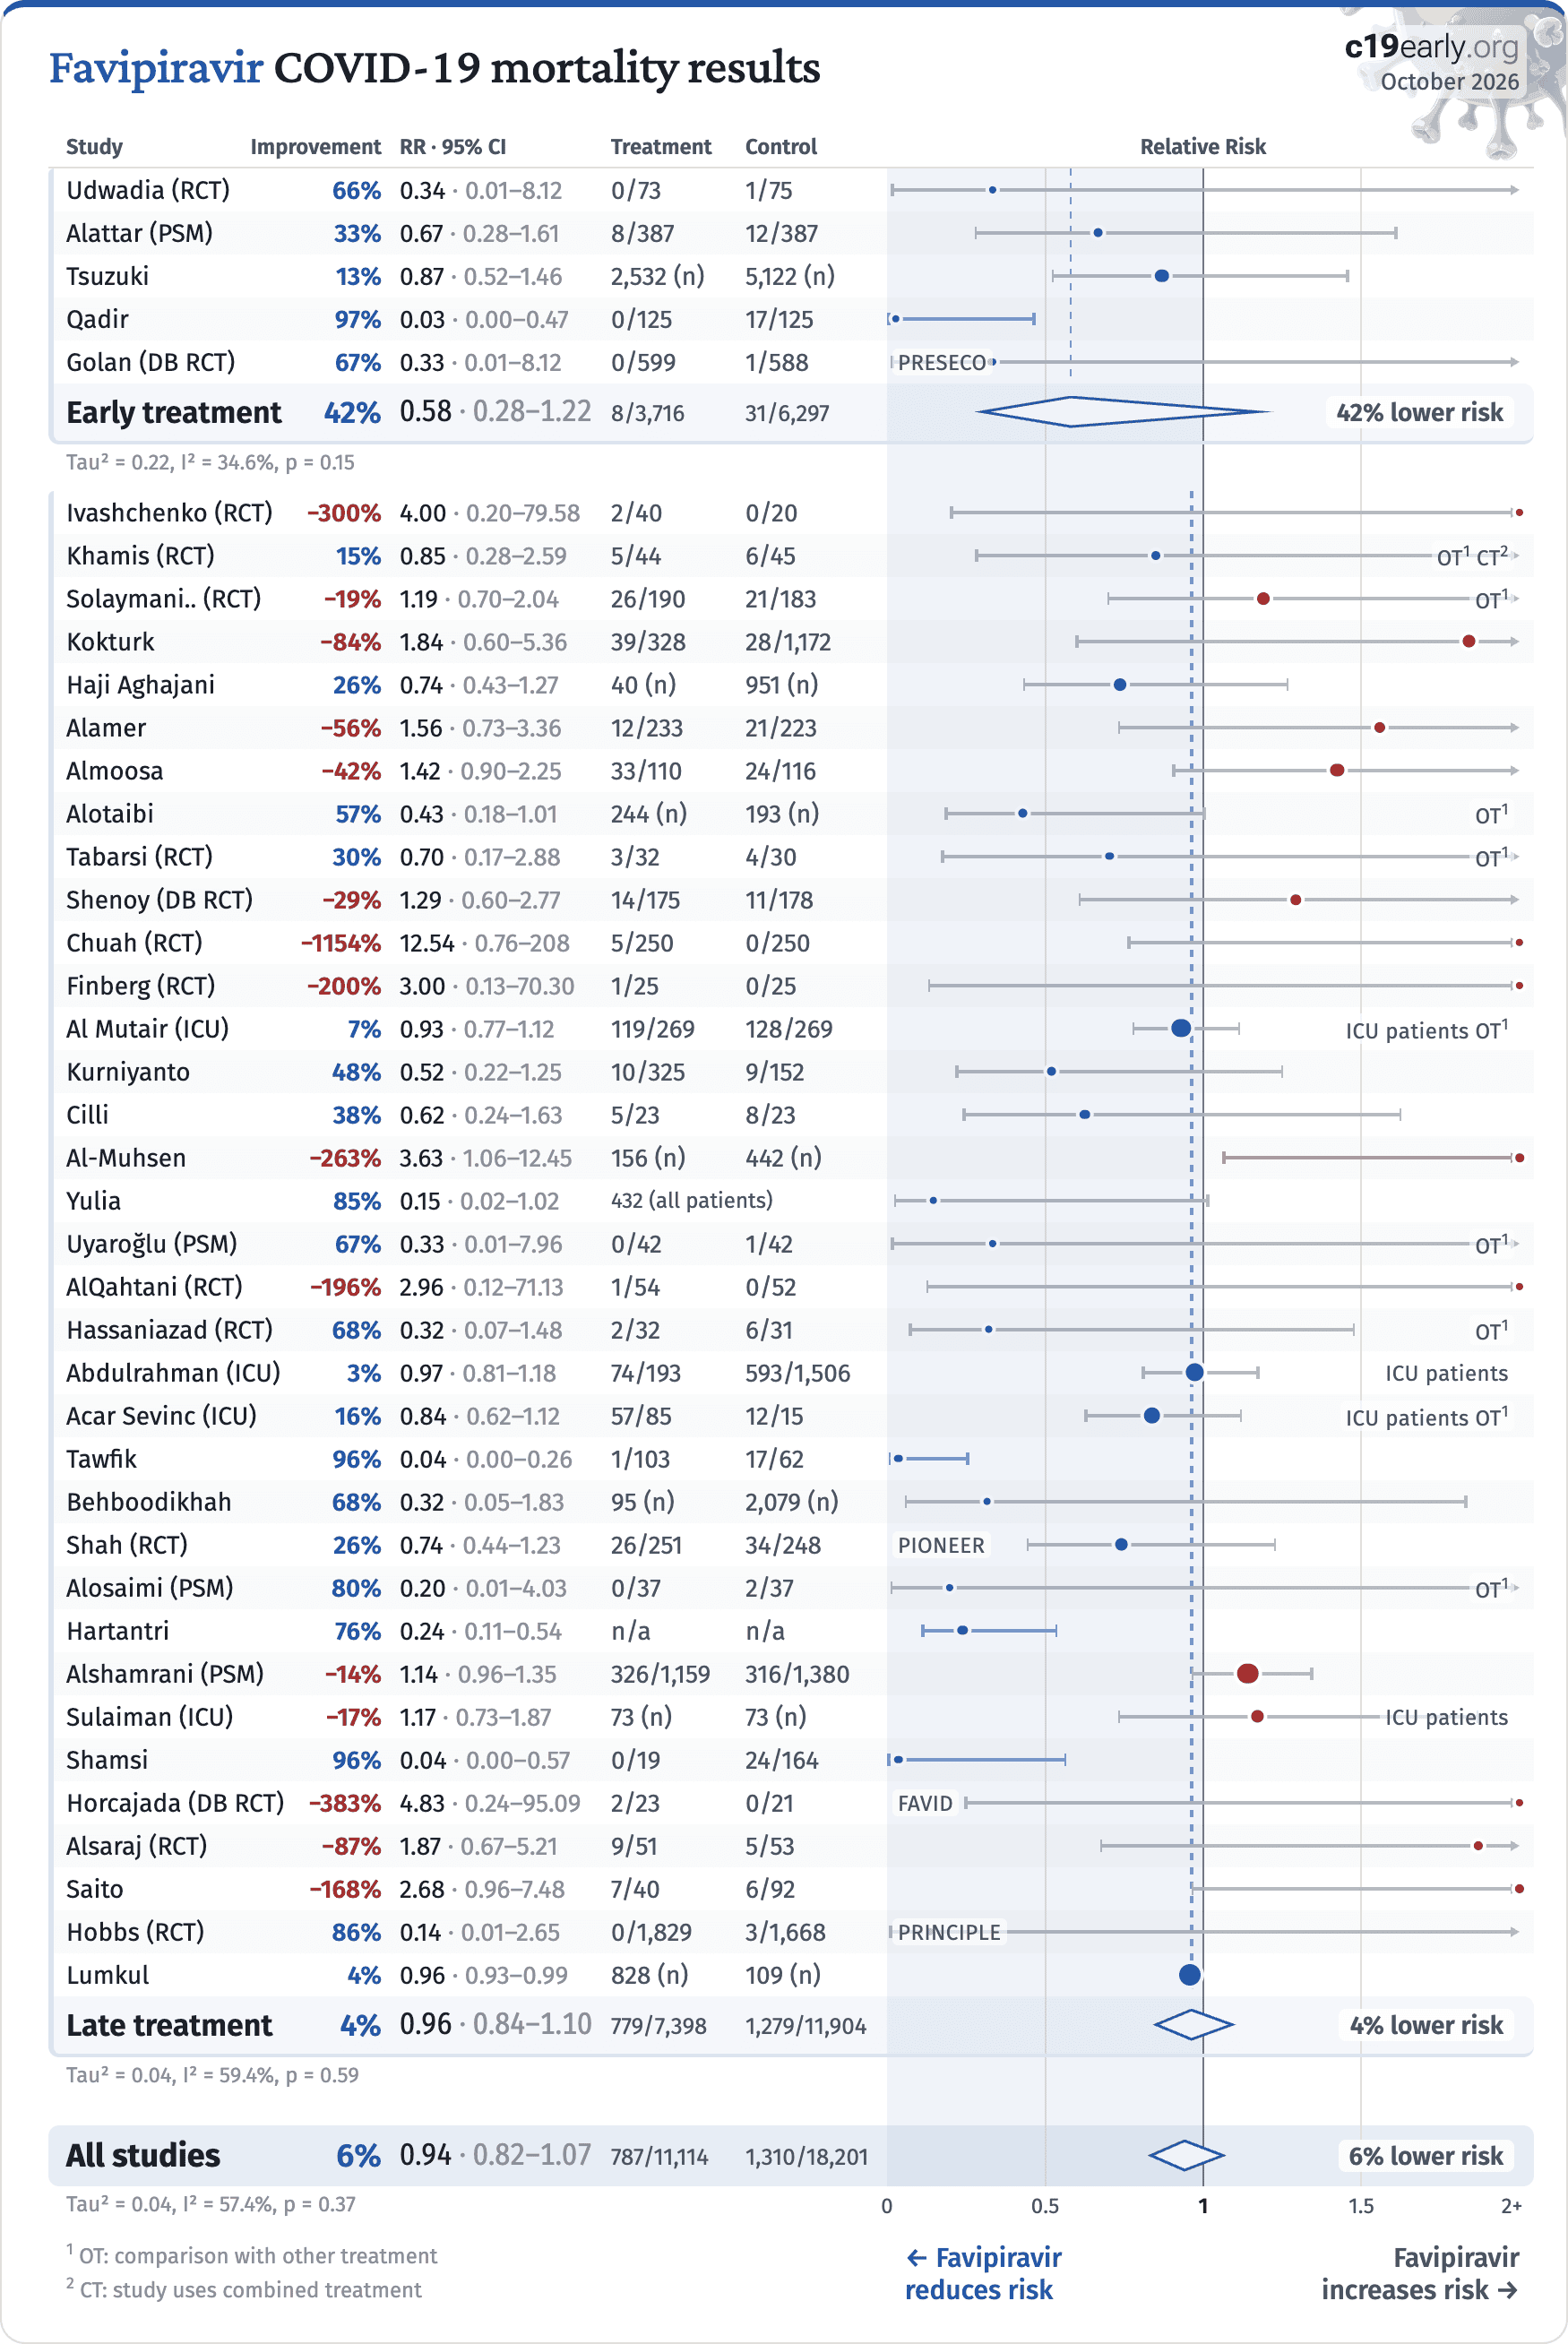
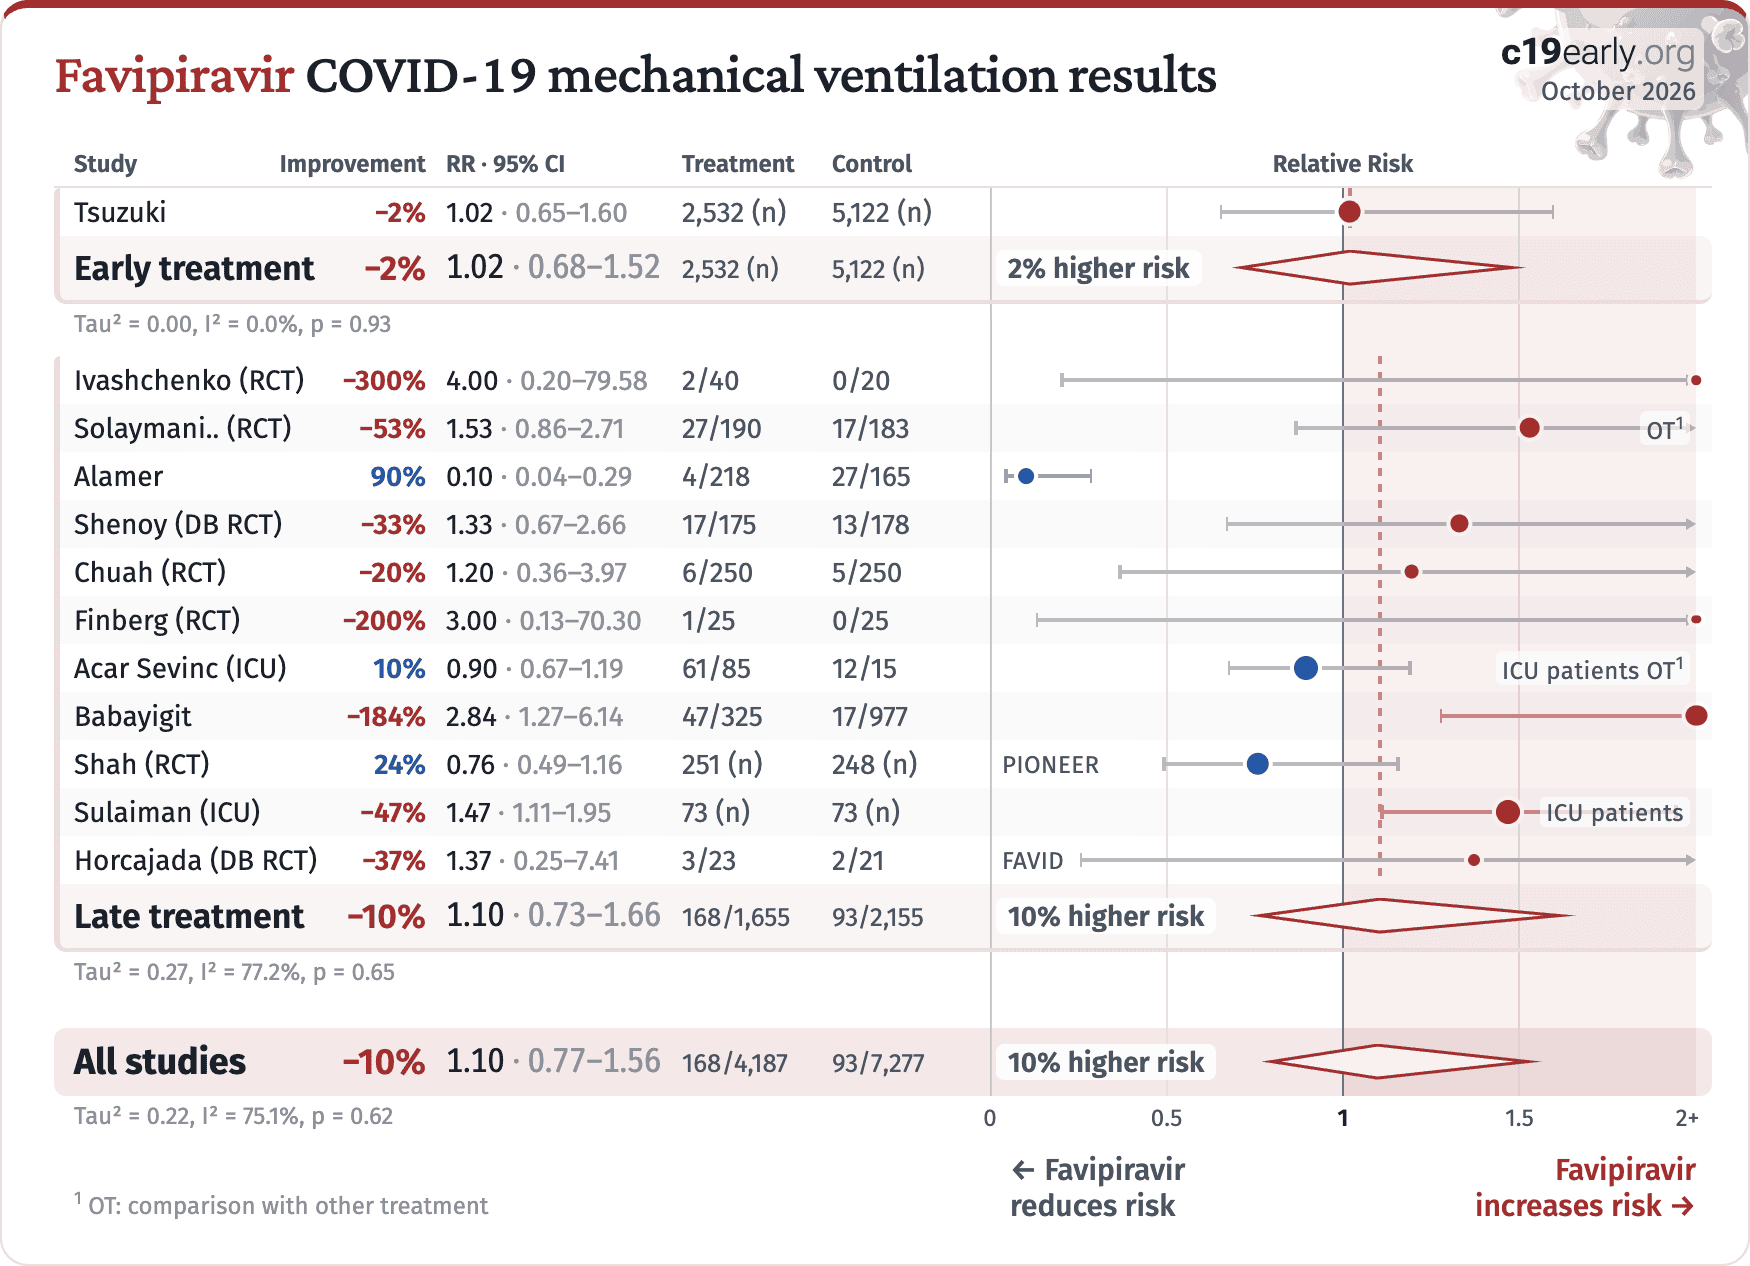
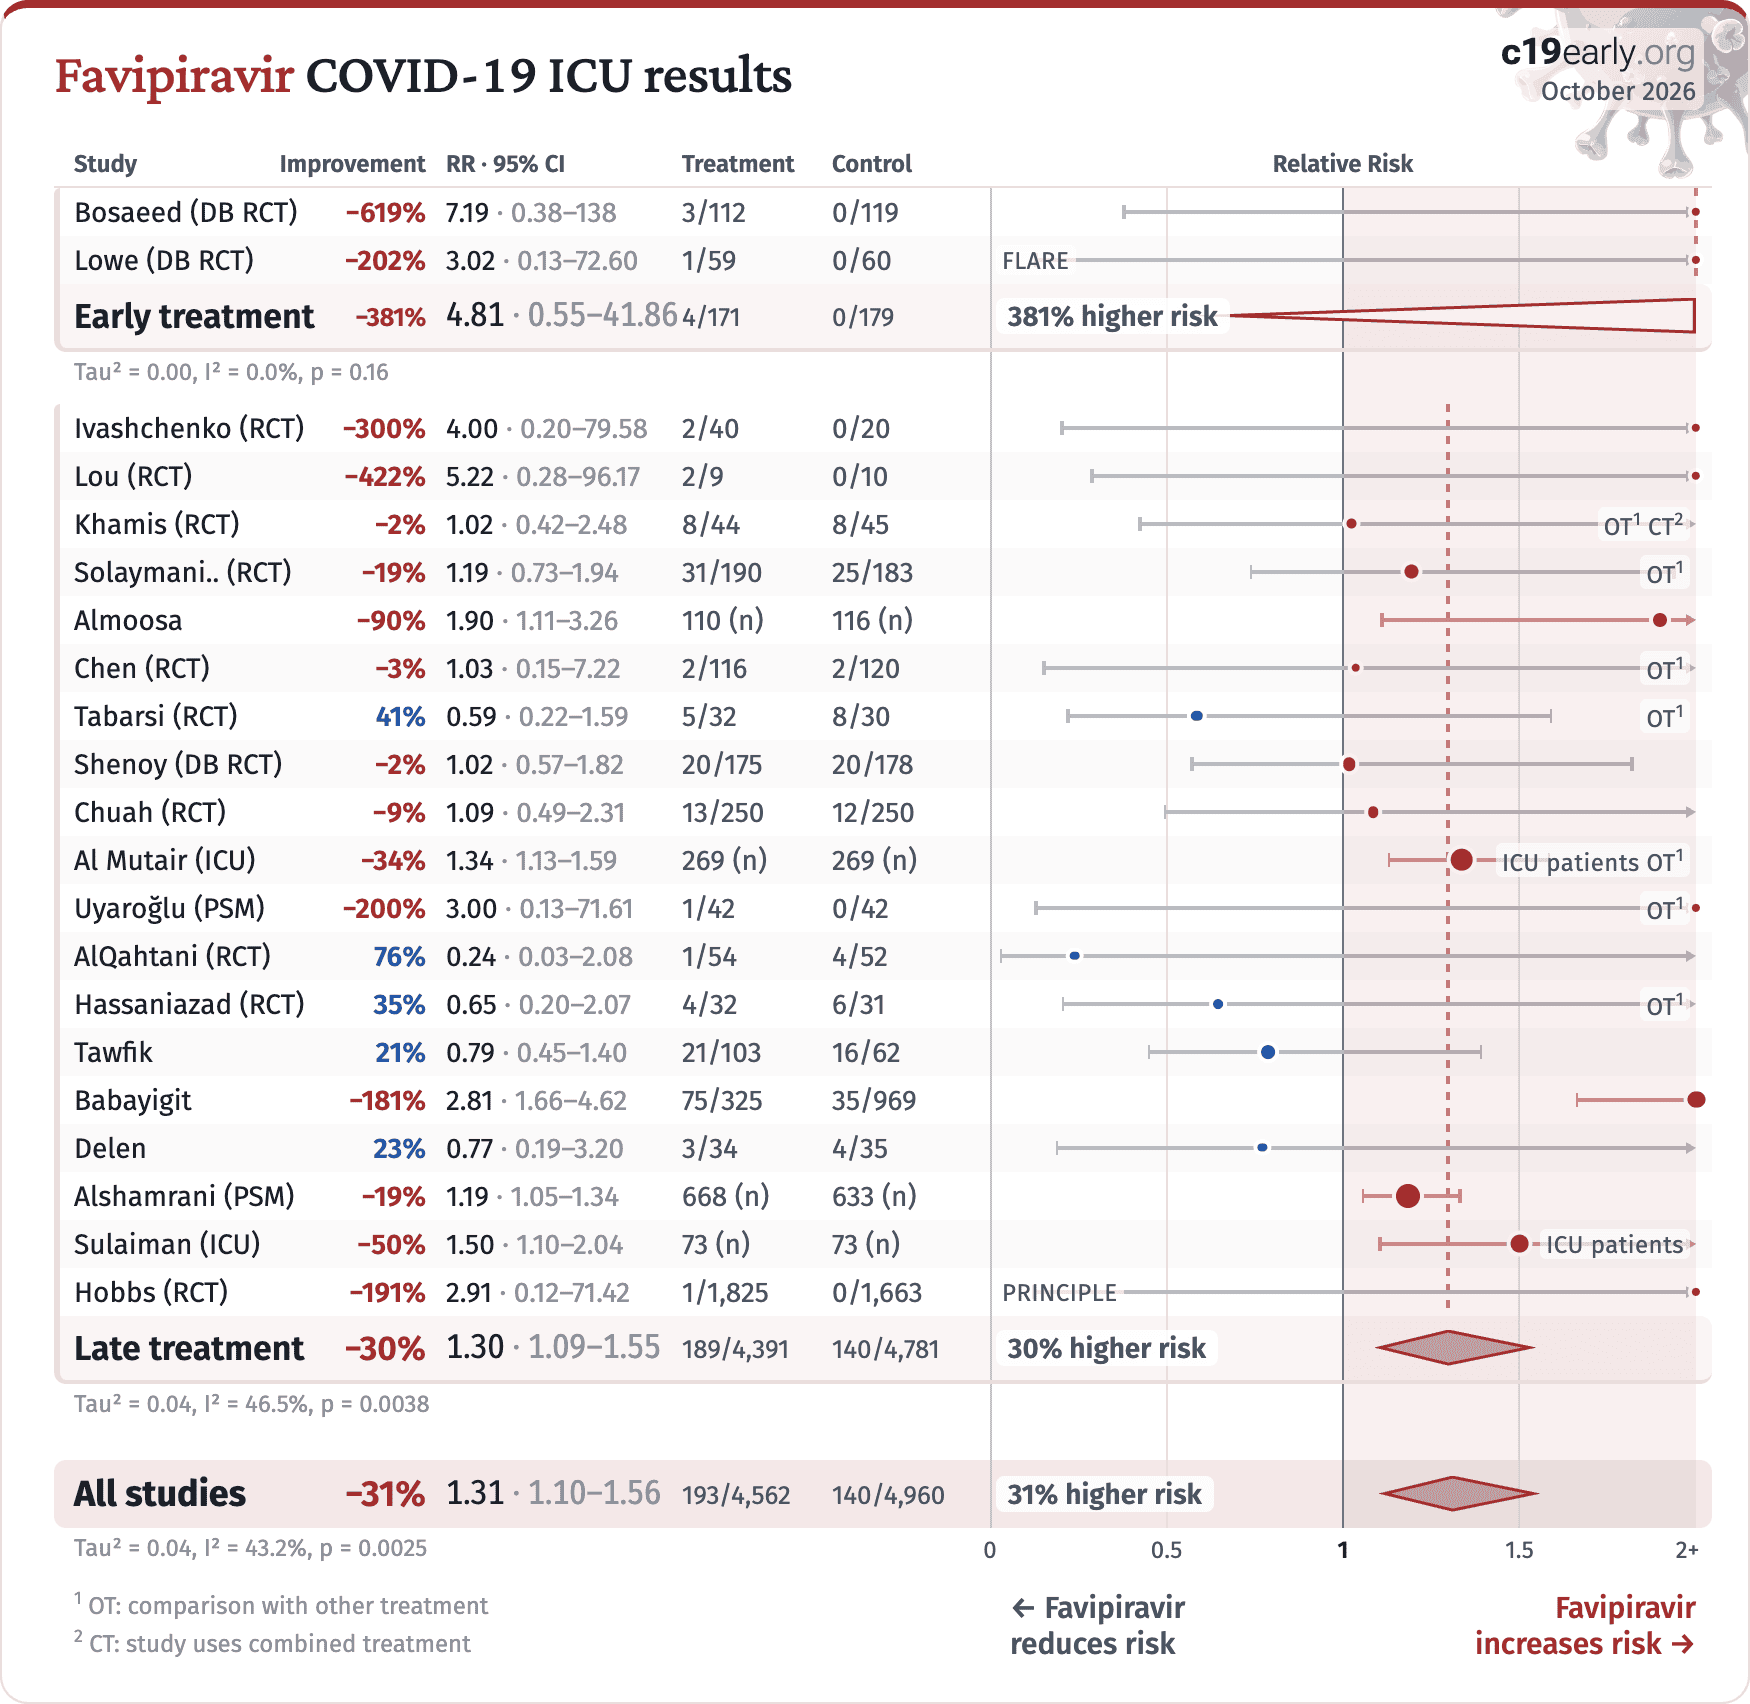
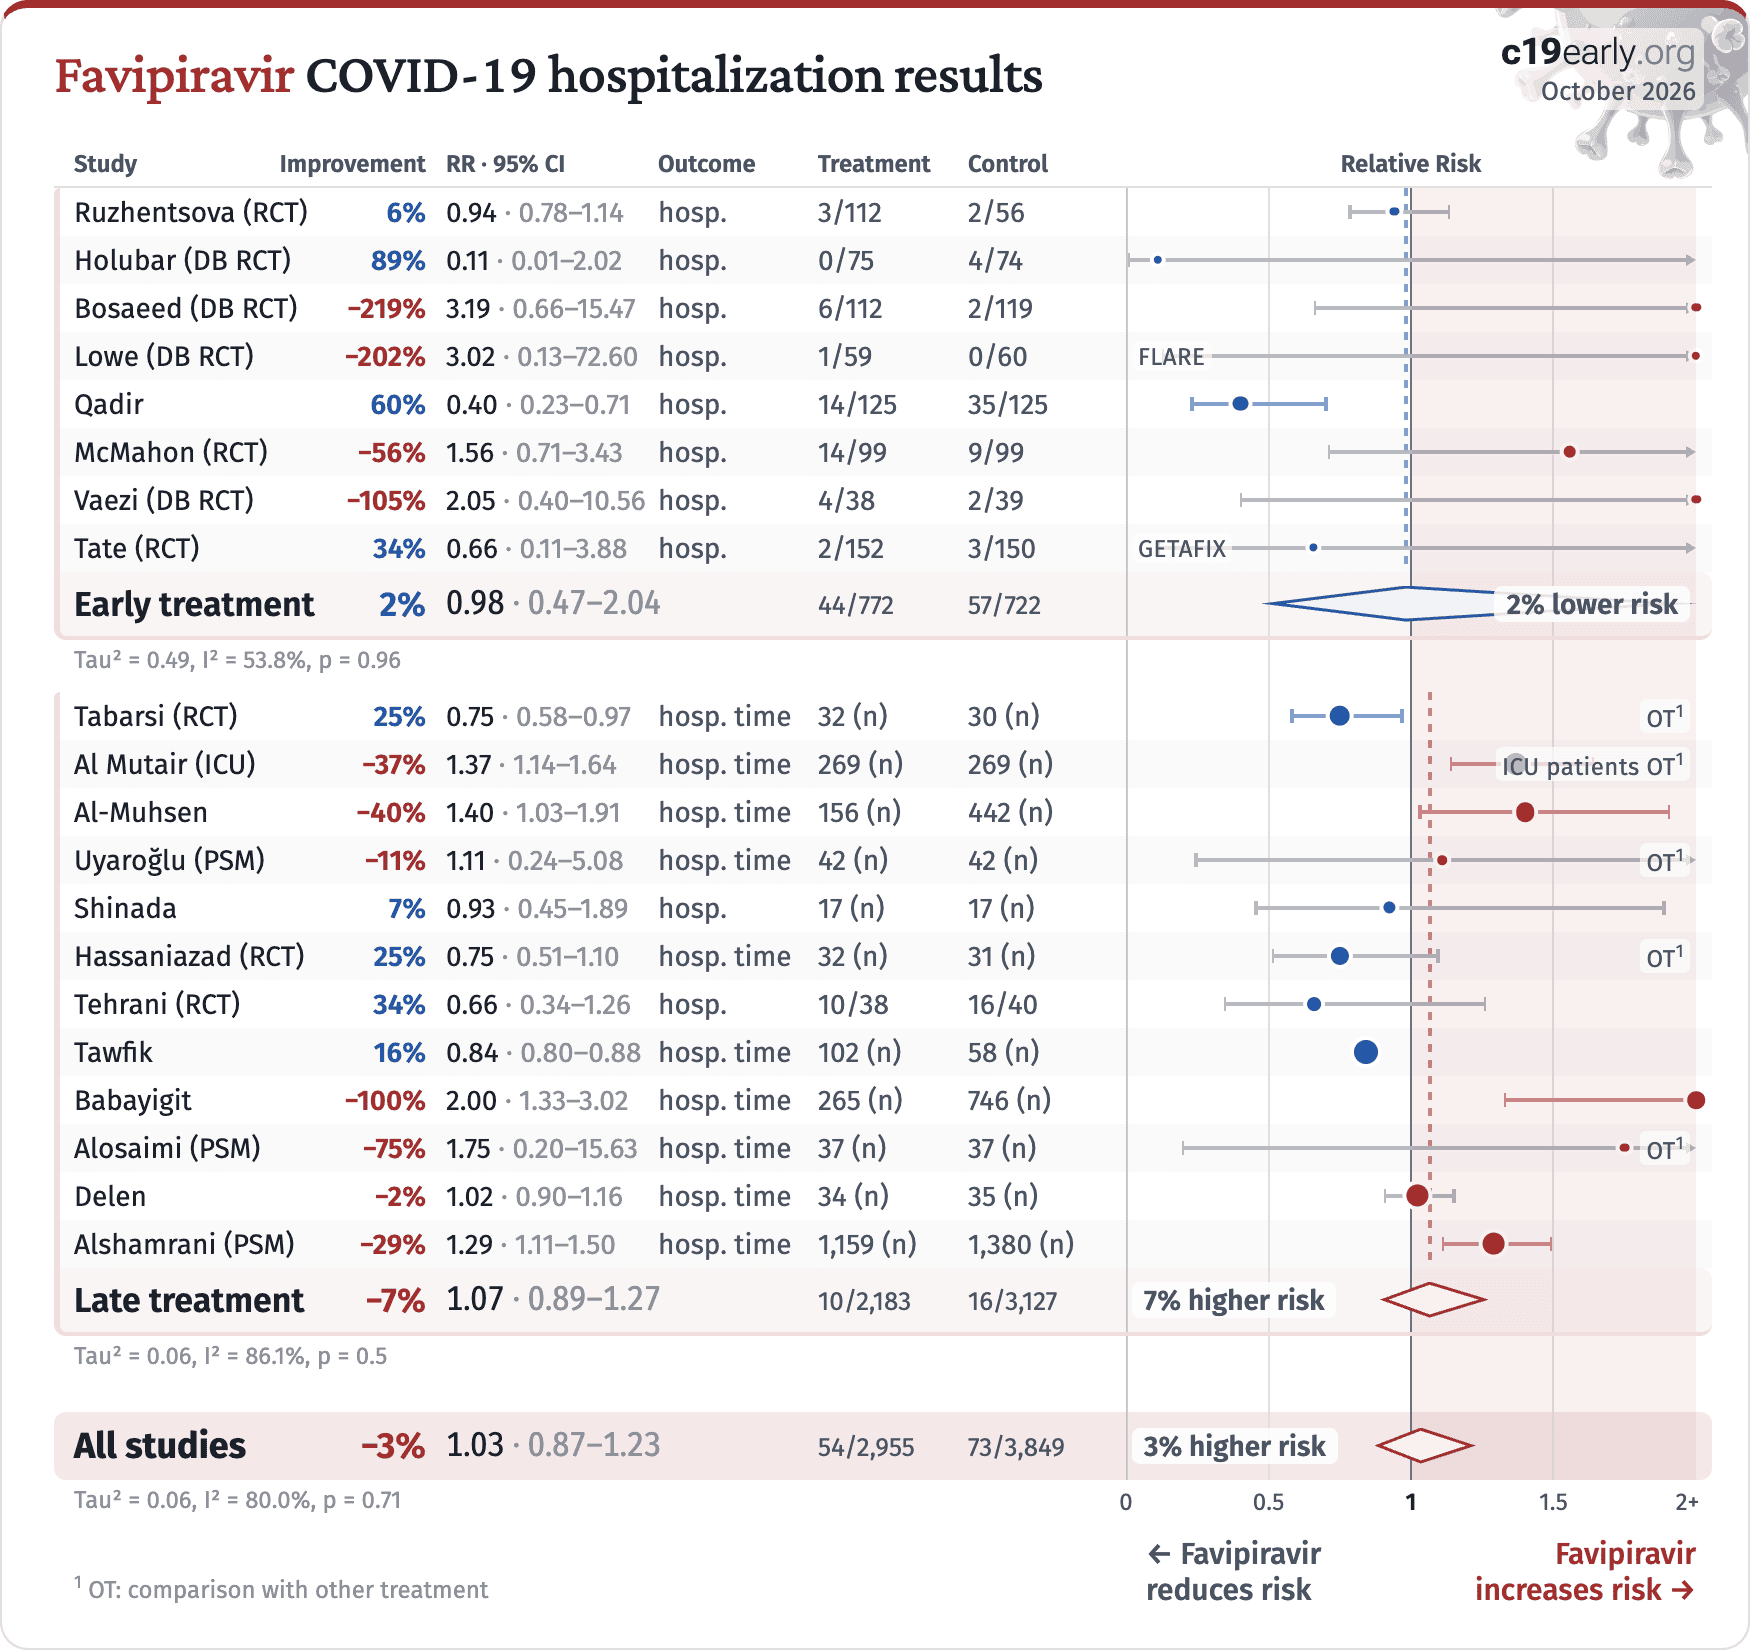
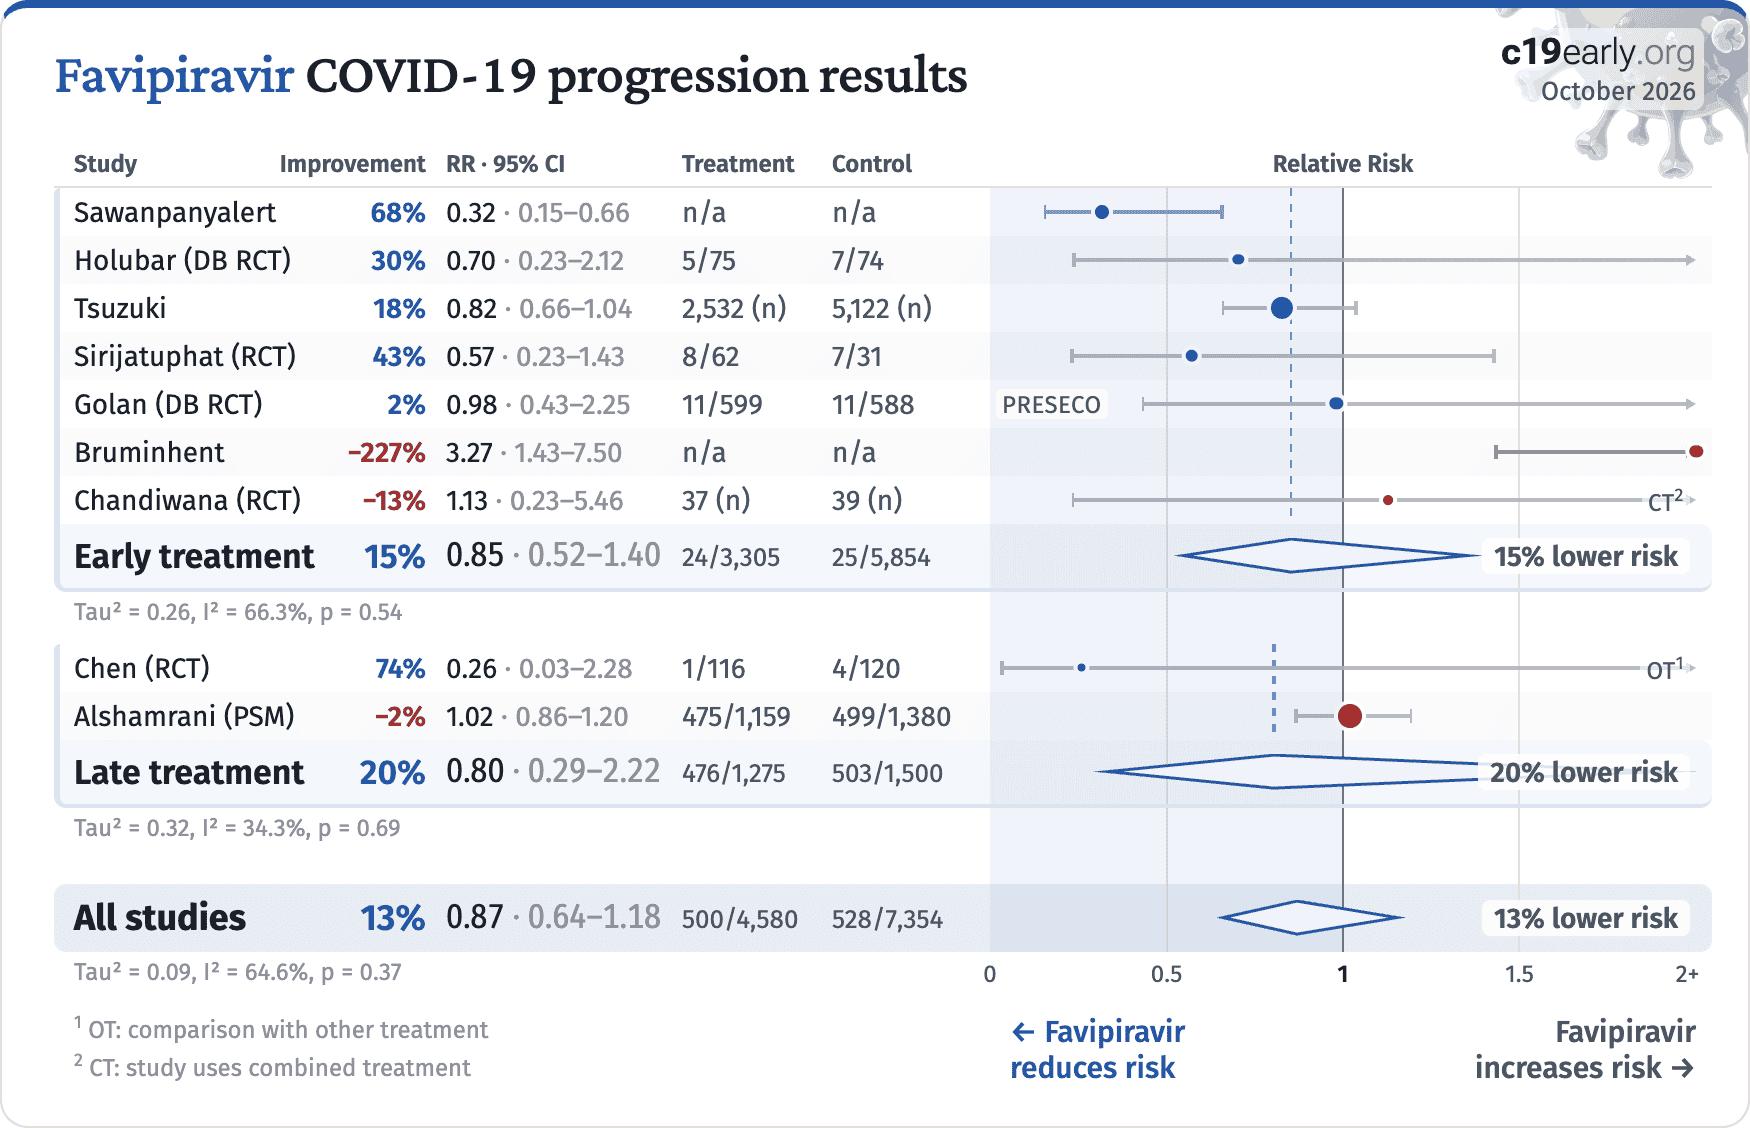
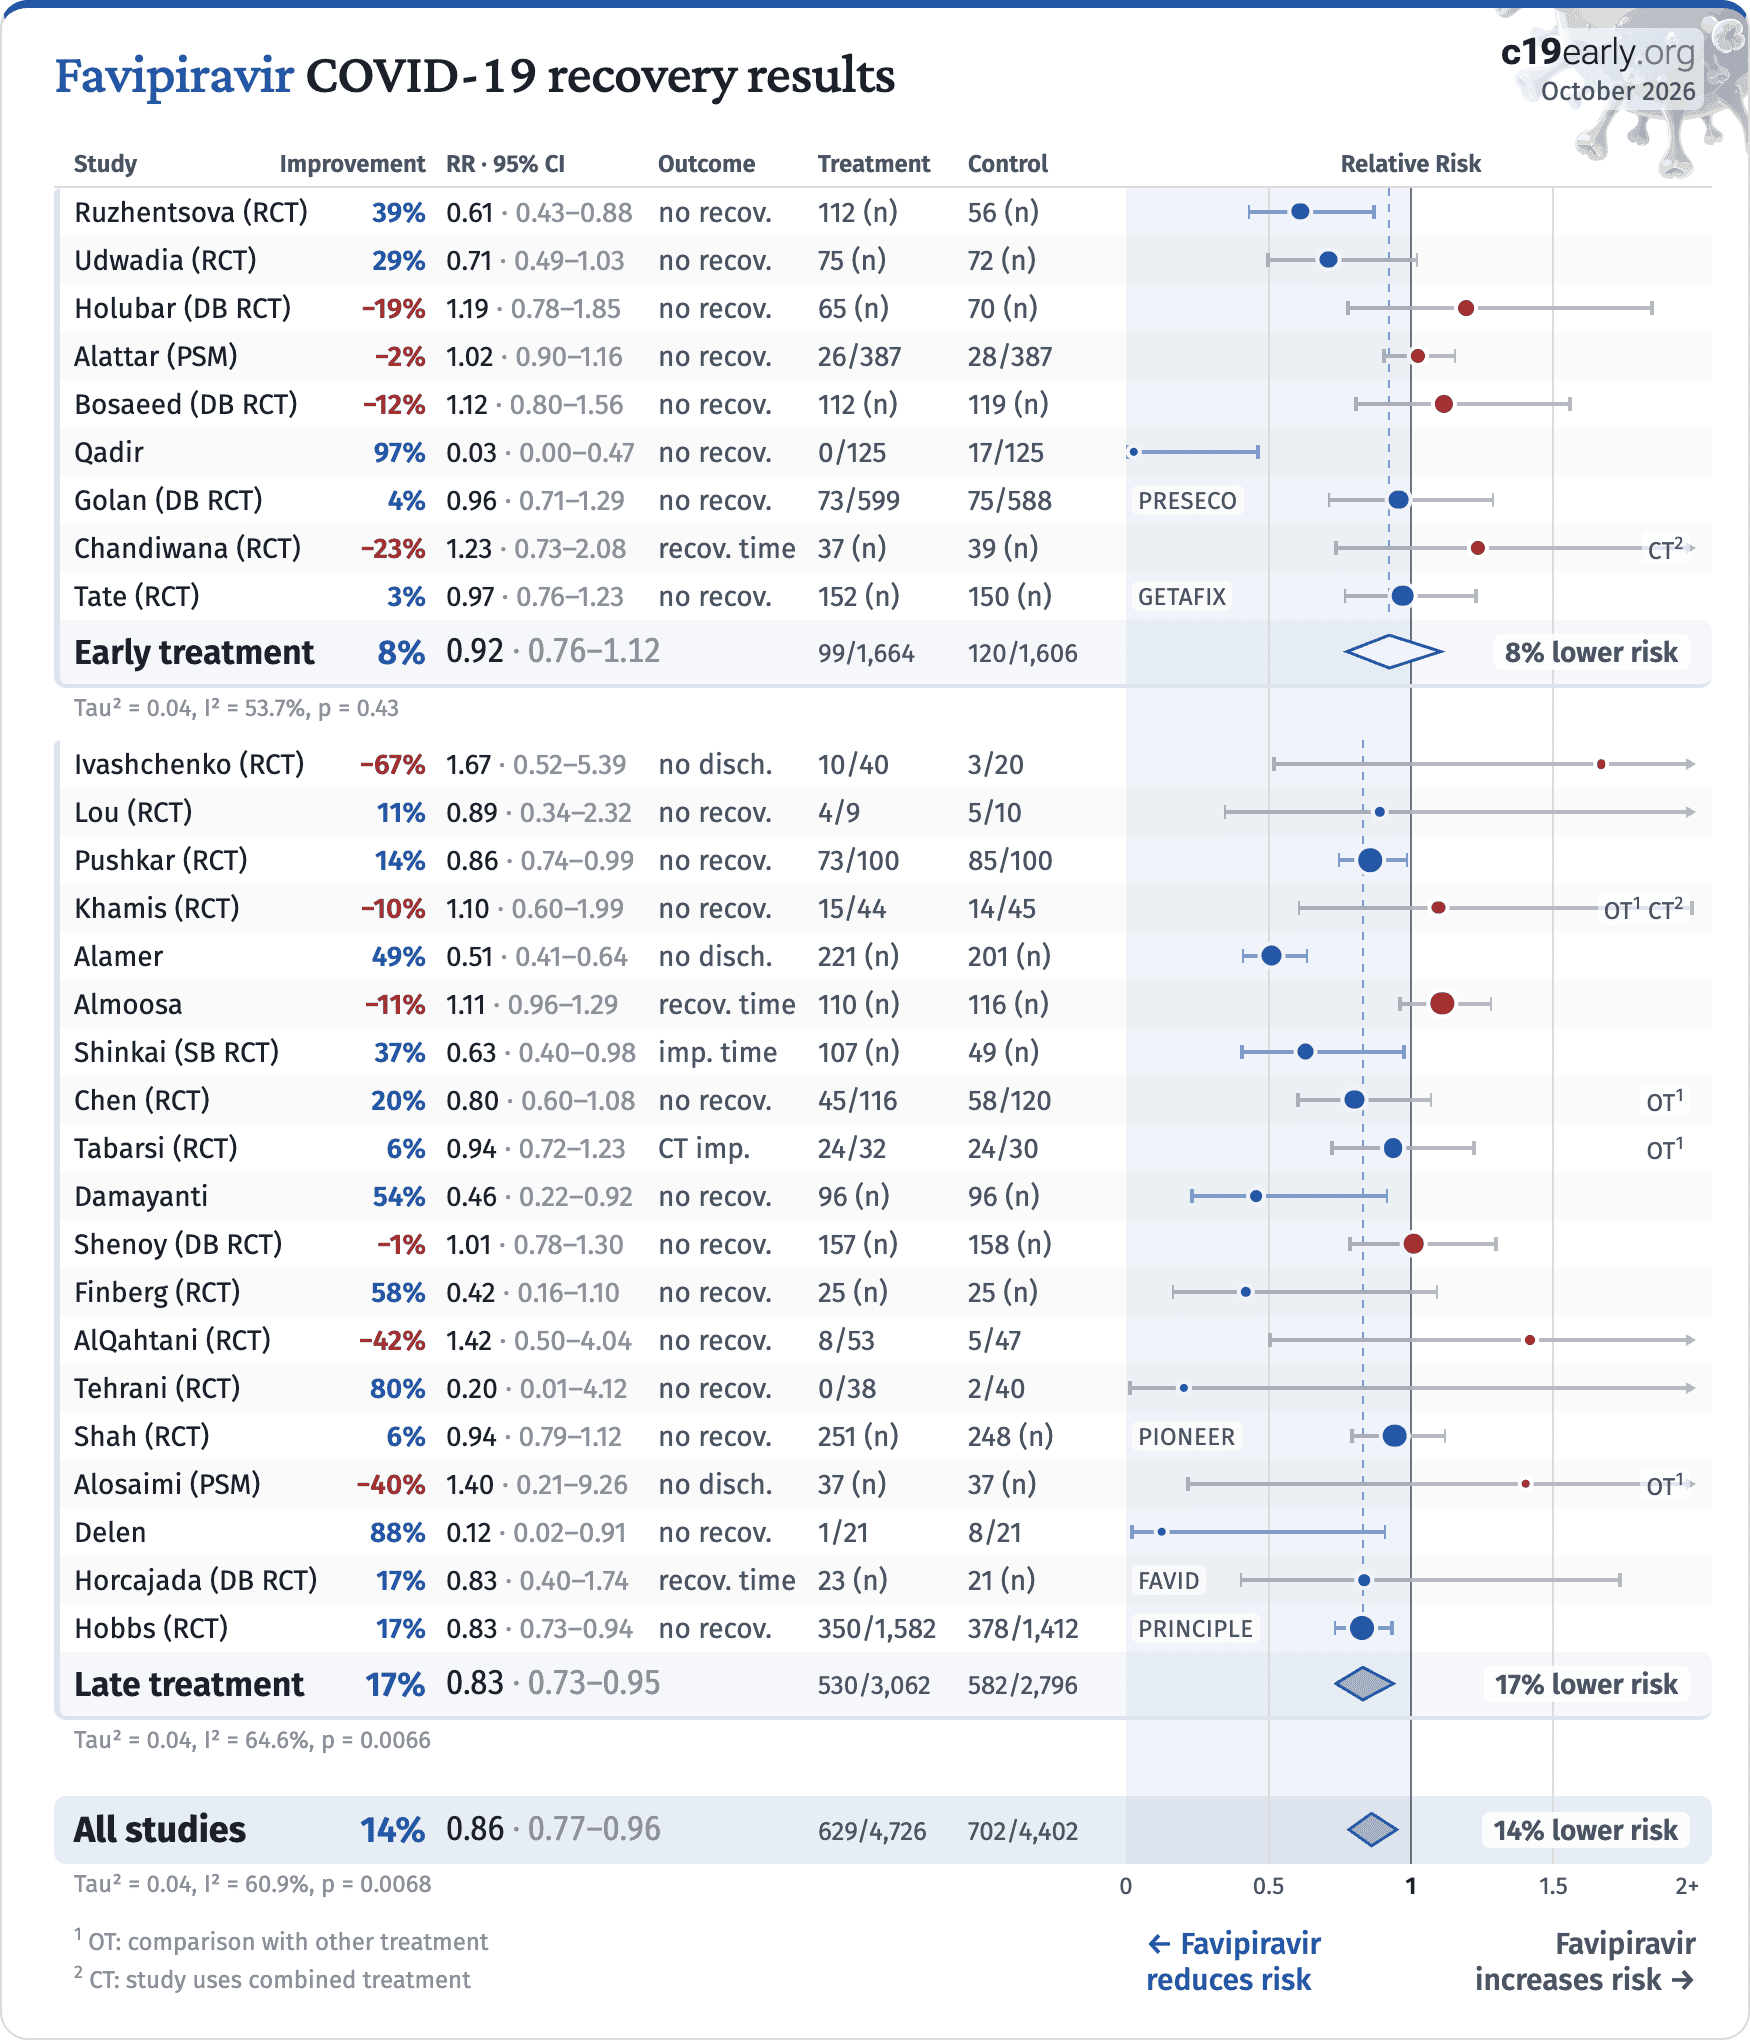
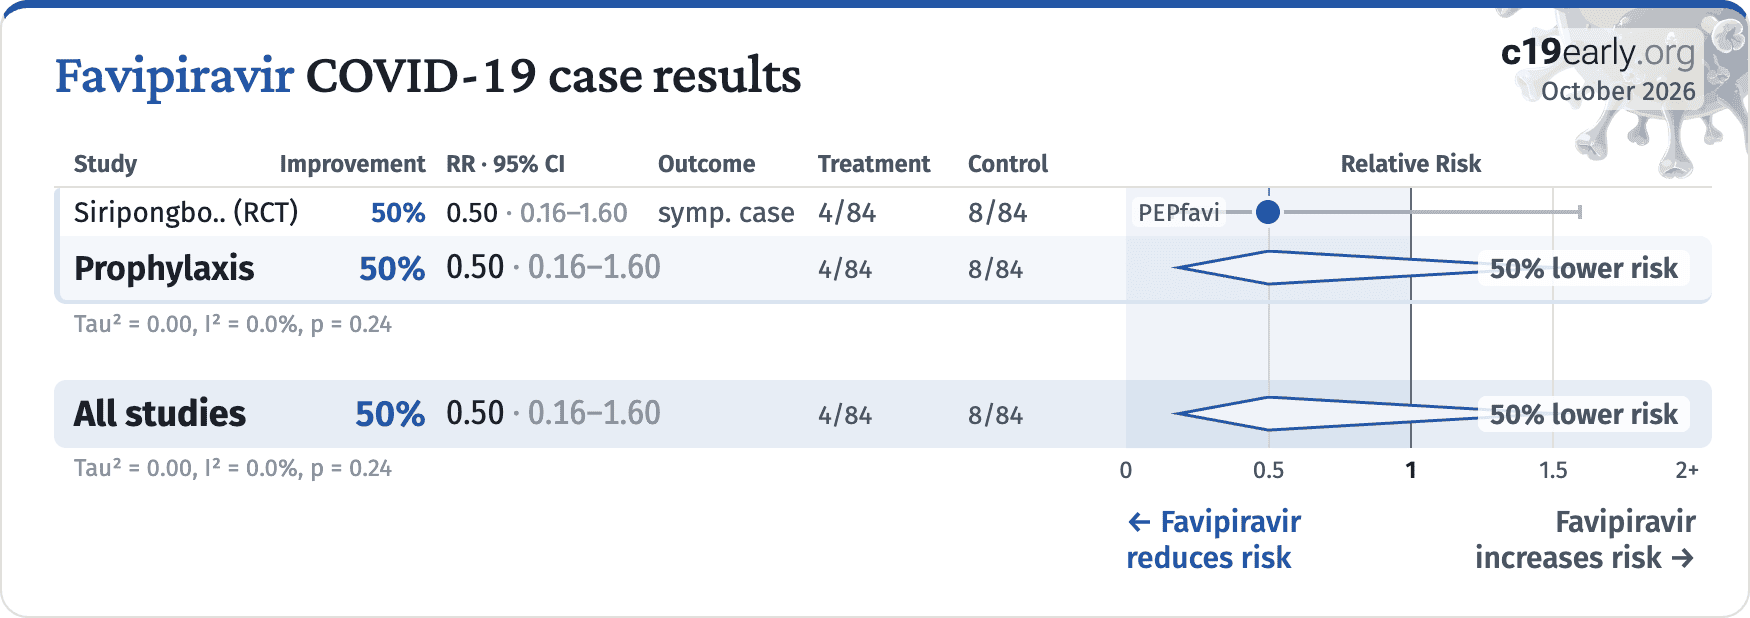
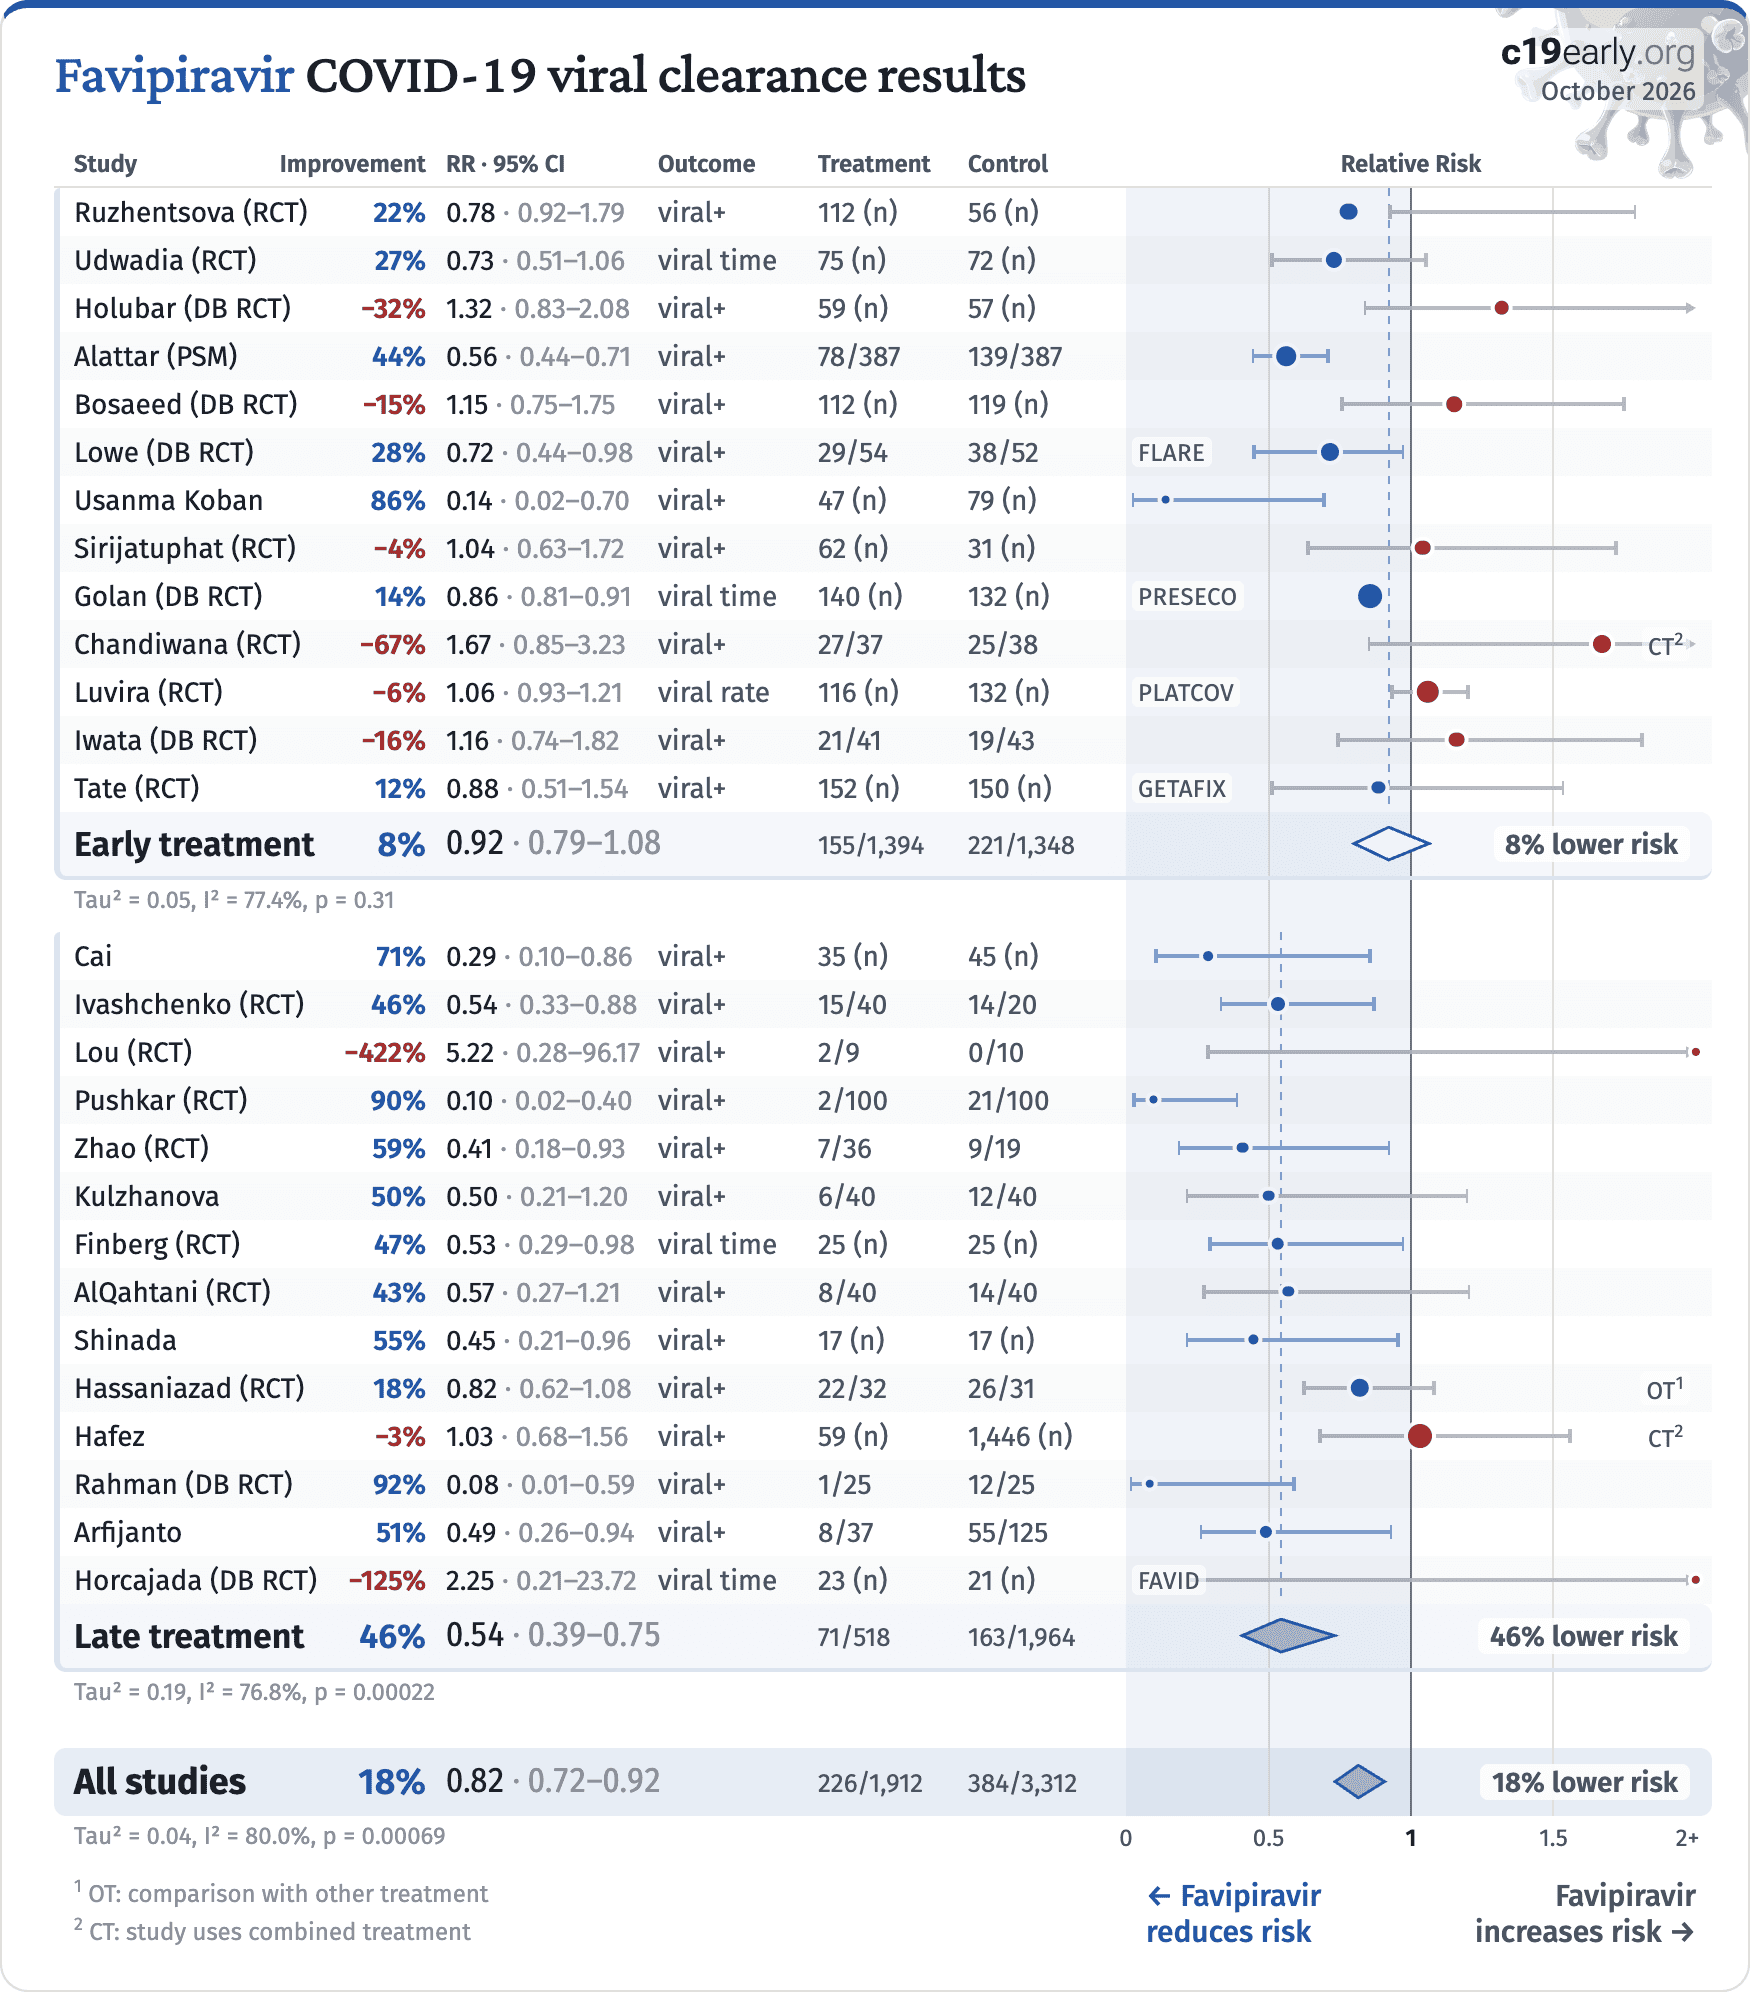
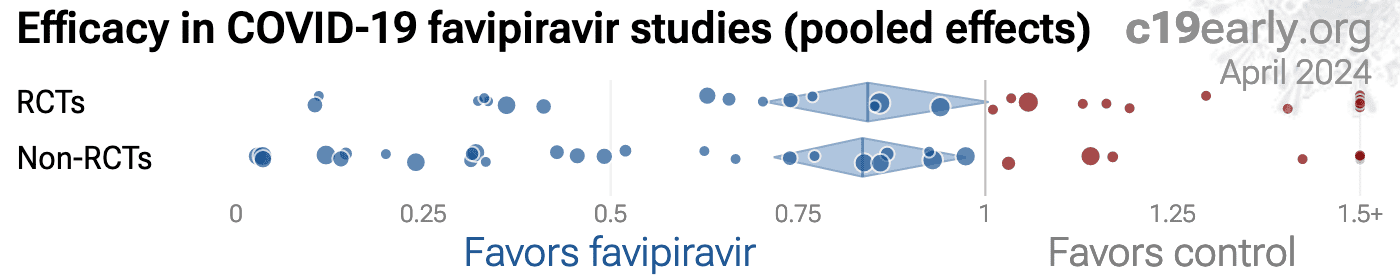
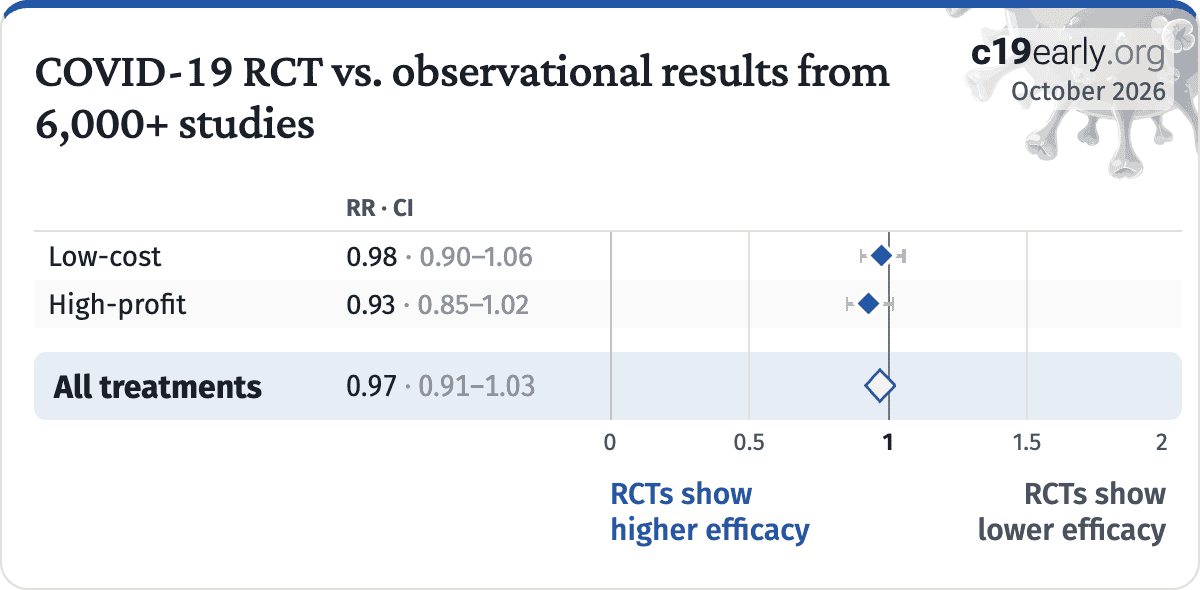
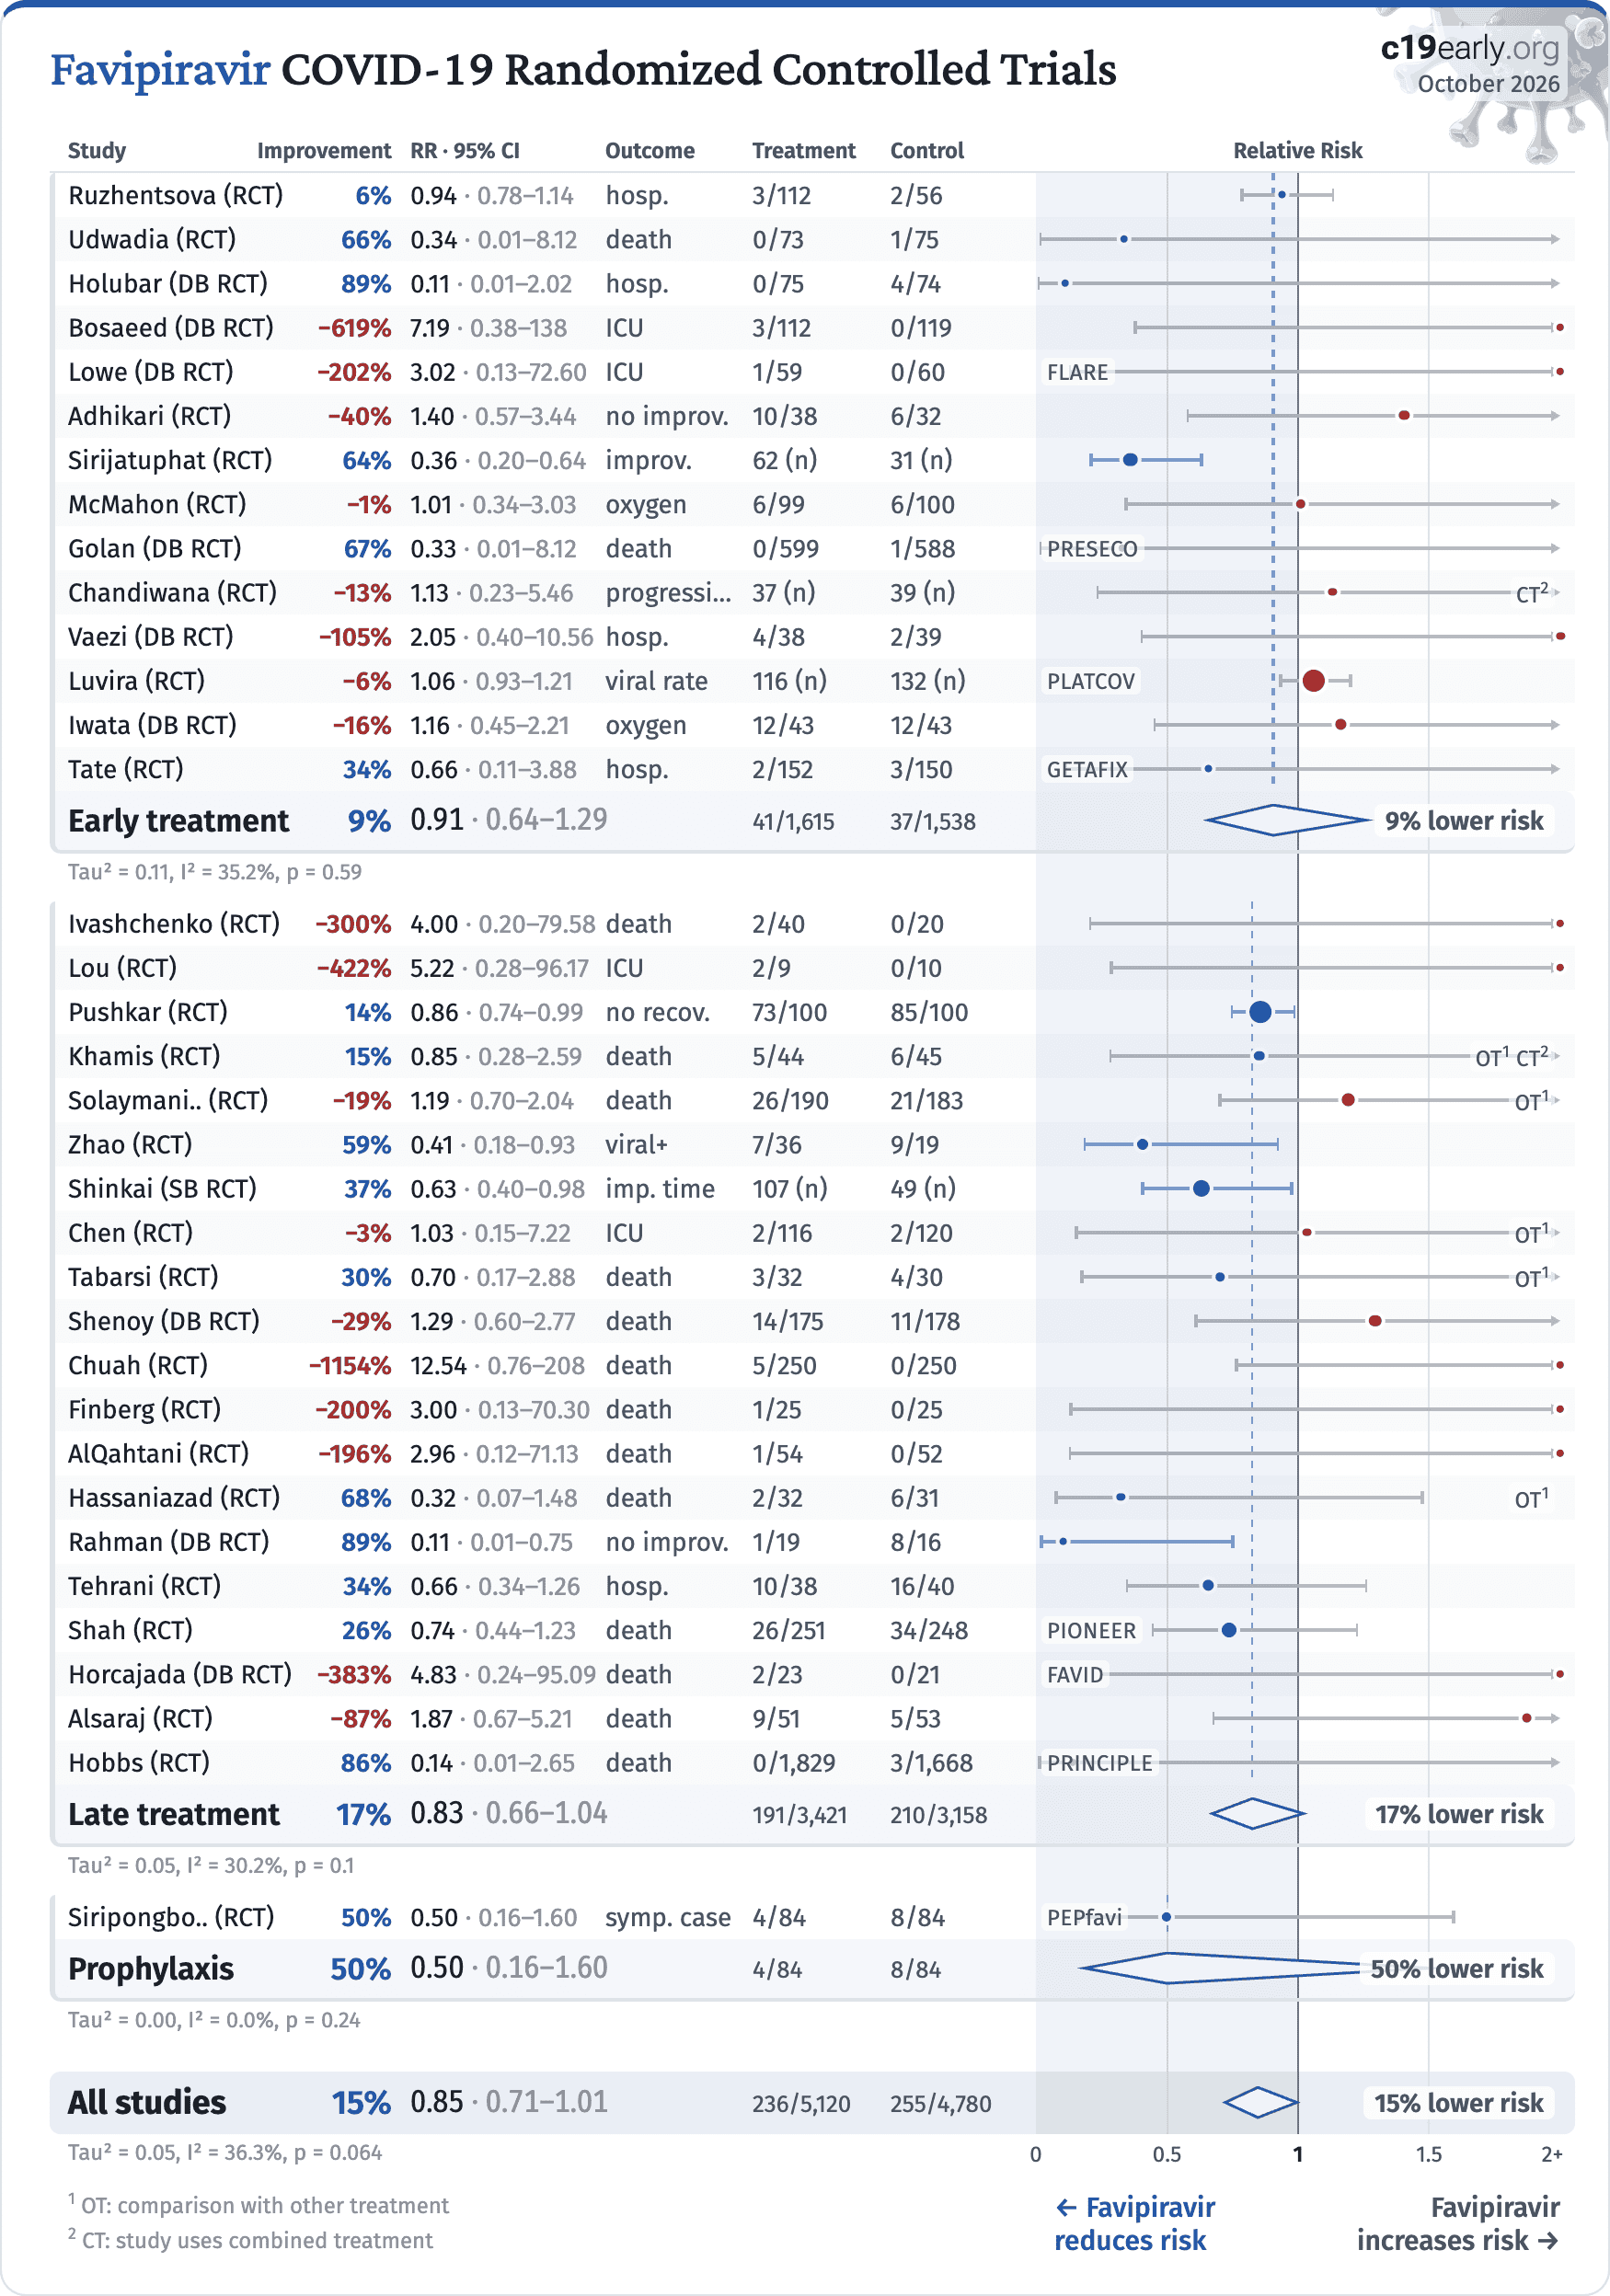
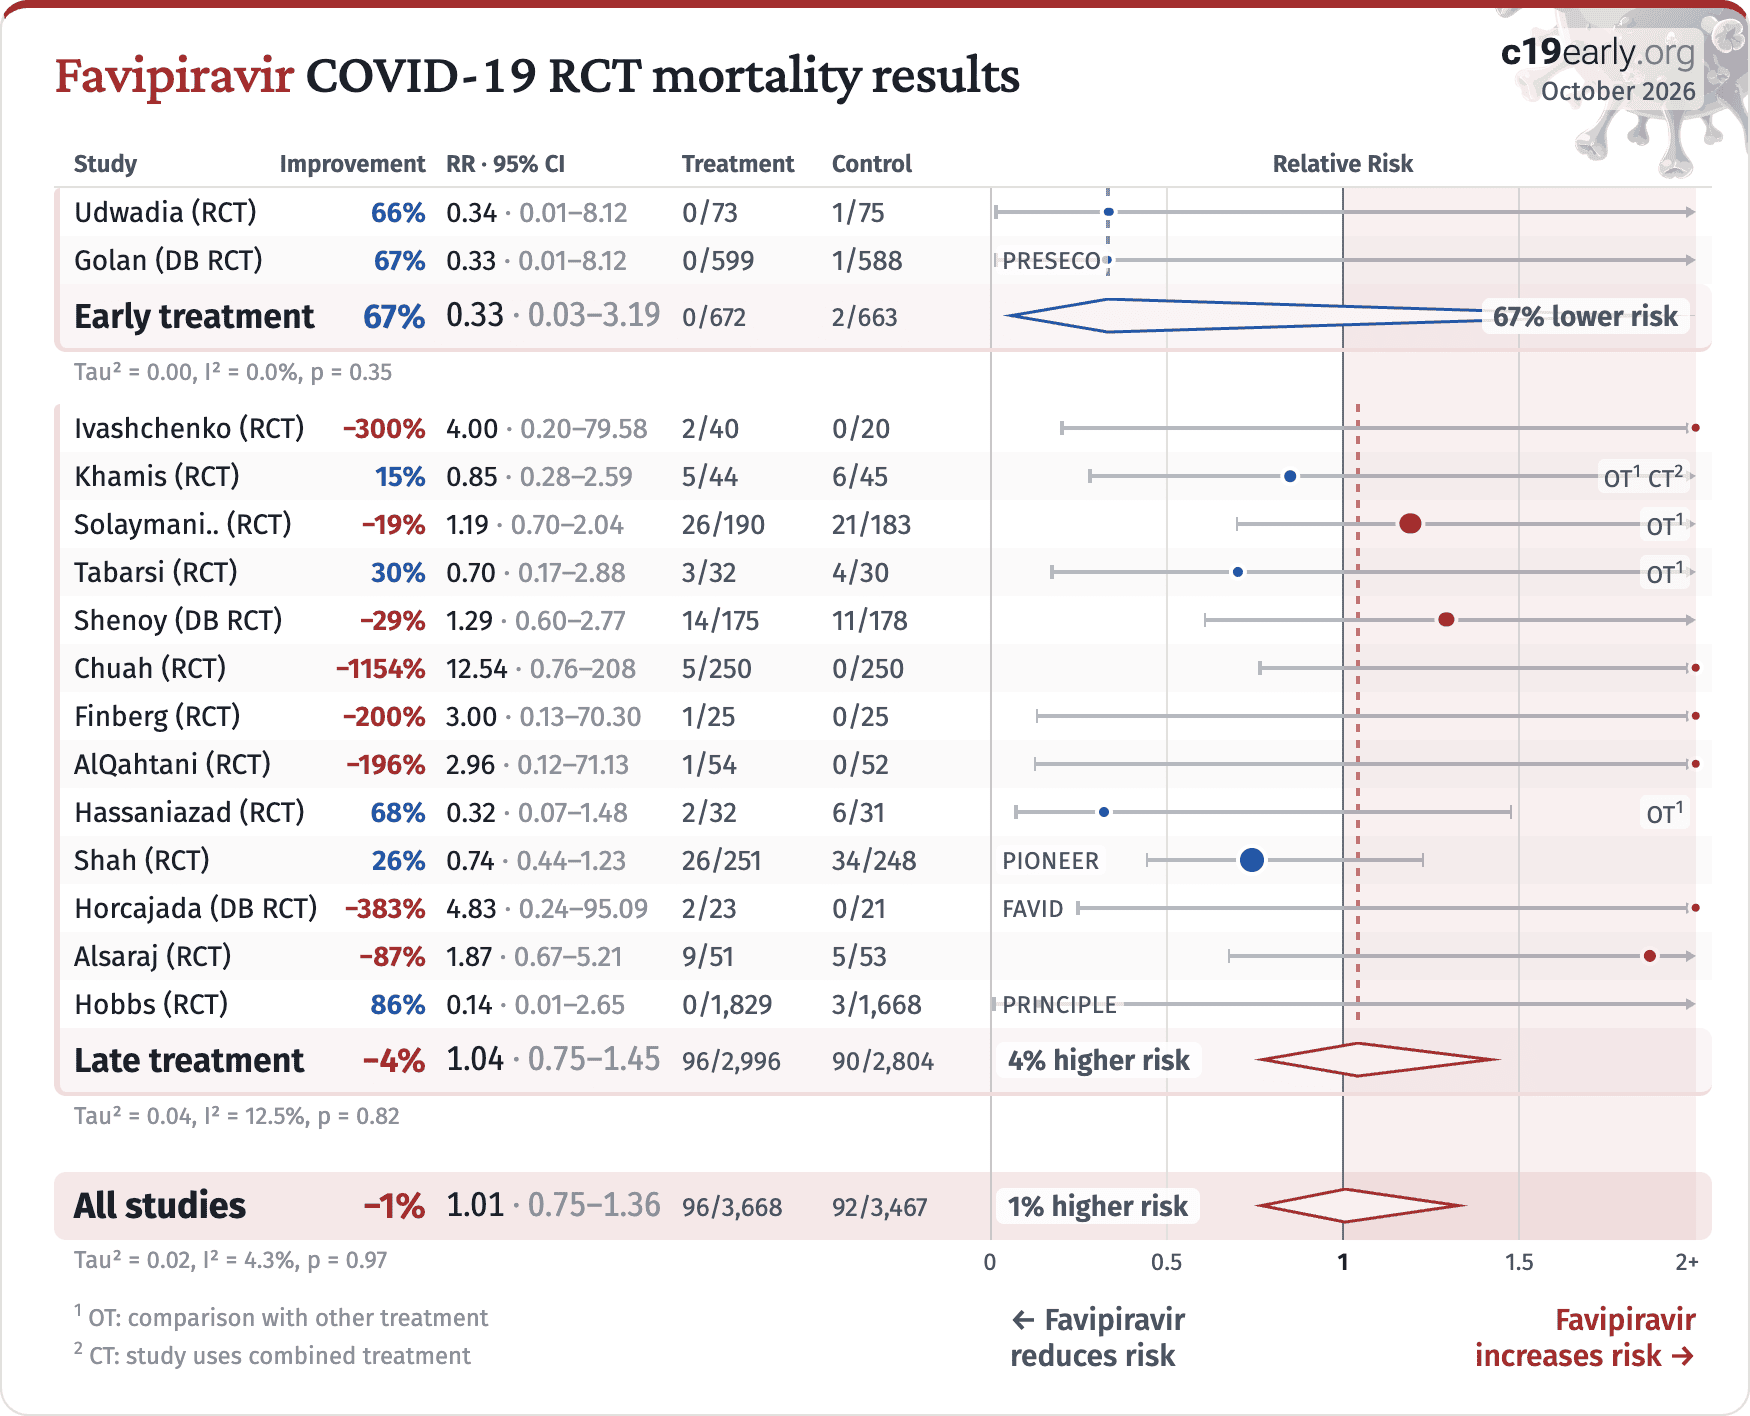
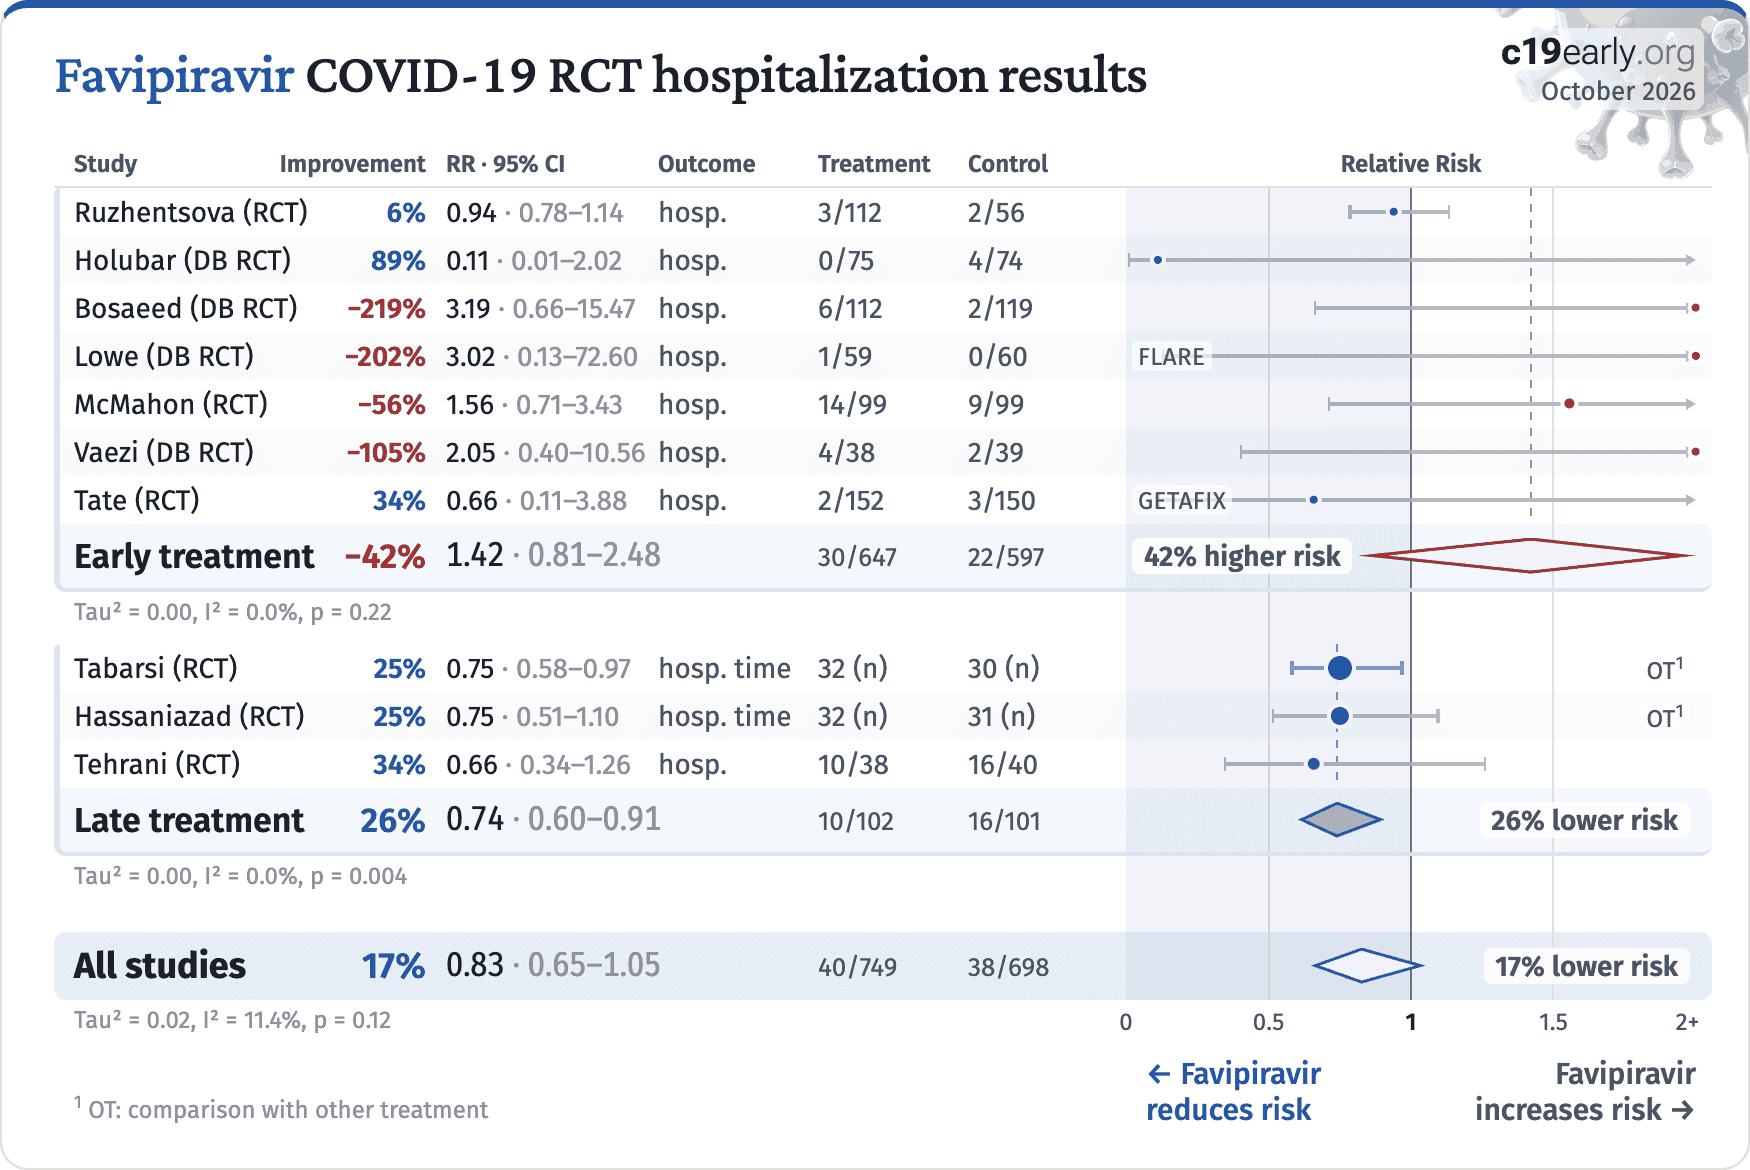
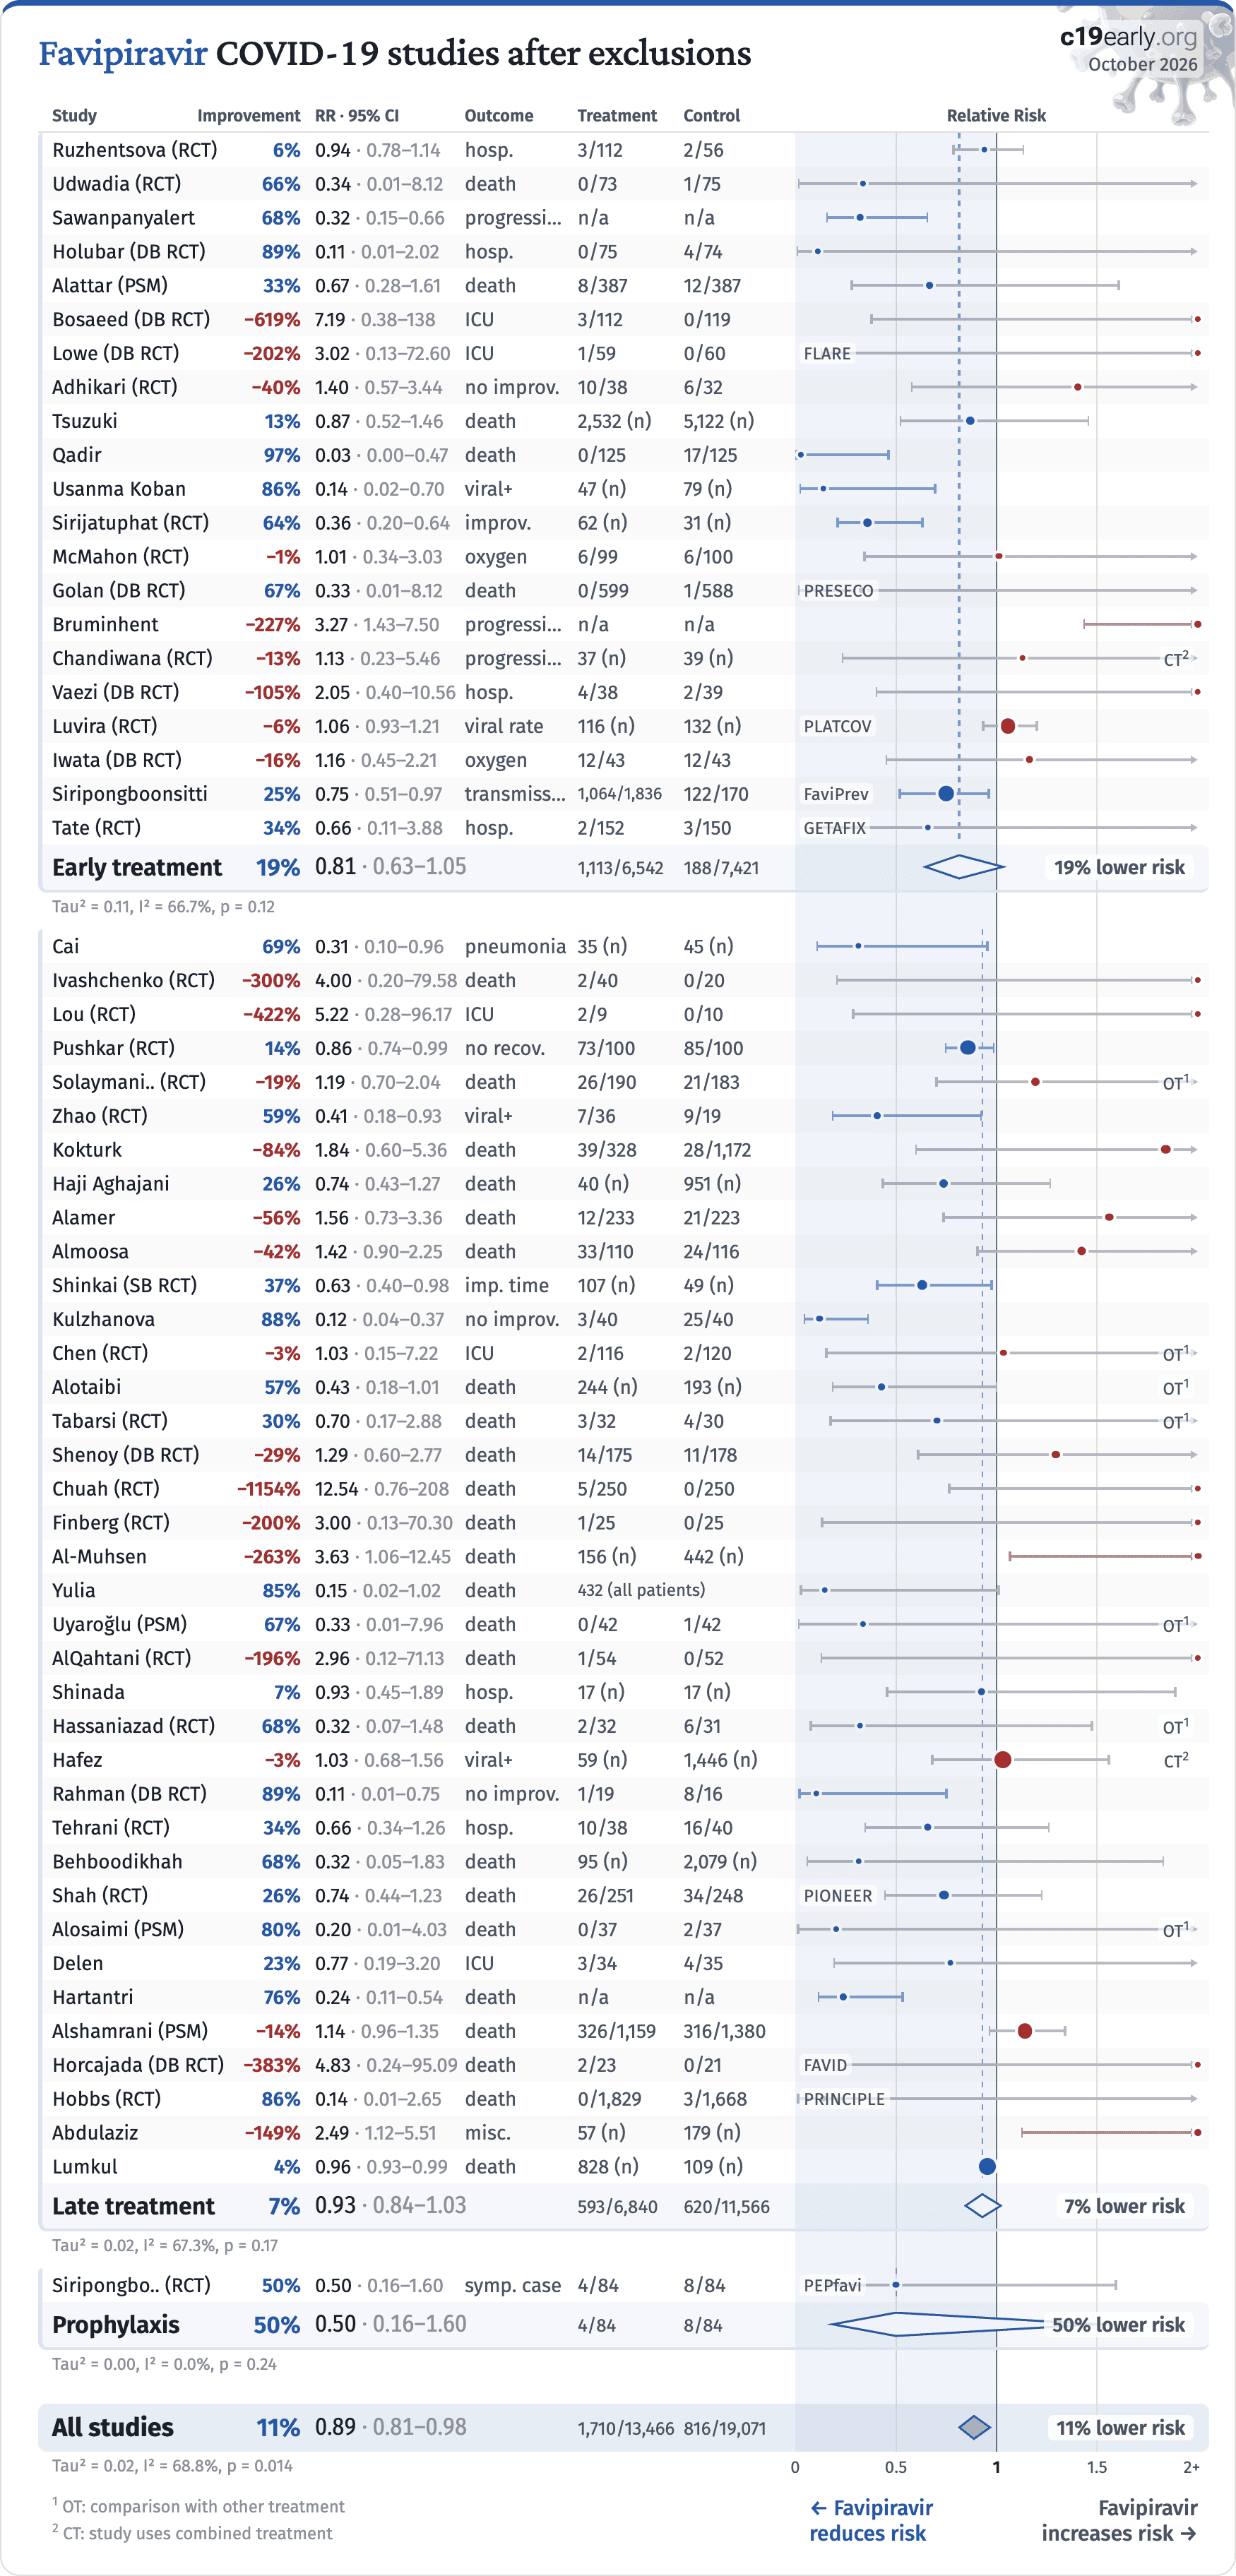
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
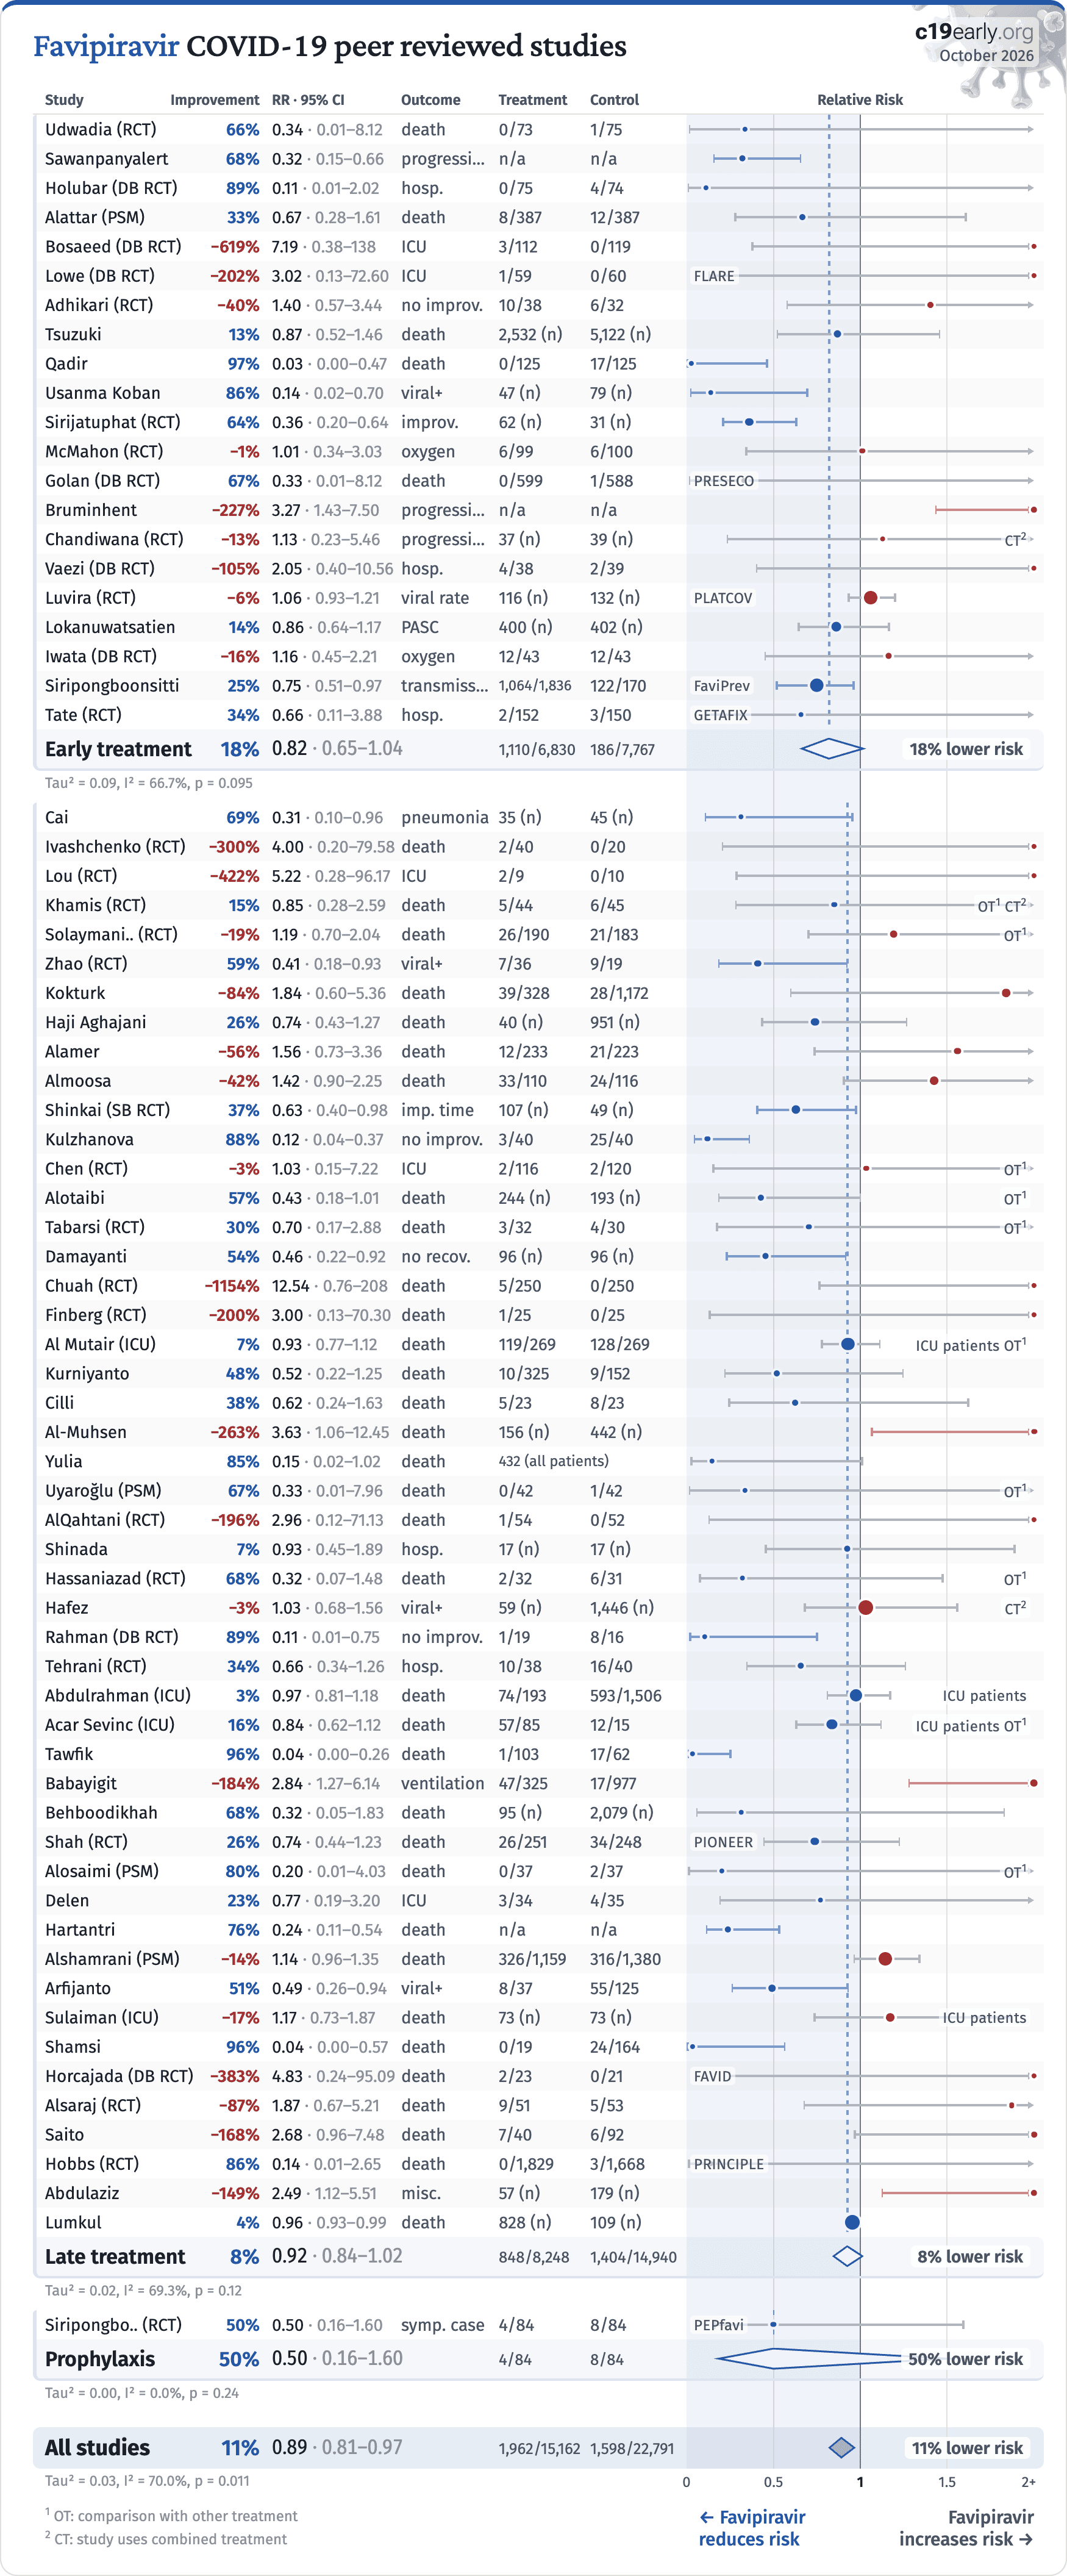
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/ameta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Adhikari, 3/1/2022, Randomized Controlled Trial, Nepal, peer-reviewed, 12 authors, study period May 2020 - October 2020.
|
risk of no improvement, 40.4% higher, RR 1.40, p = 0.57, treatment 10 of 38 (26.3%), control 6 of 32 (18.8%), all.
|
|
risk of no improvement, 36.3% higher, RR 1.36, p = 0.75, treatment 8 of 27 (29.6%), control 5 of 23 (21.7%), mild cases.
|
|
risk of no improvement, 63.6% higher, RR 1.64, p = 1.00, treatment 2 of 11 (18.2%), control 1 of 9 (11.1%), moderate cases.
|
|
Alattar, 11/30/2021, retrospective, Qatar, peer-reviewed, median age 46.0, 25 authors, study period 23 May, 2020 - 18 July, 2020, average treatment delay 5.0 days.
|
risk of death, 33.3% lower, RR 0.67, p = 0.50, treatment 8 of 387 (2.1%), control 12 of 387 (3.1%), NNT 97, propensity score matching, day 28.
|
|
risk of no clinical improvement, 2.2% higher, RR 1.02, p = 0.73, treatment 26 of 387 (6.7%), control 28 of 387 (7.2%), NNT 194, adjusted per study, inverted to make RR<1 favor treatment, day 28, Cox proportional hazards, propensity score matching, primary outcome.
|
|
days to clinical improvement, 6.2% higher, relative time 1.06, p = 0.07, treatment 387, control 387, propensity score matching.
|
|
risk of no viral clearance, 43.9% lower, RR 0.56, p < 0.001, treatment 78 of 387 (20.2%), control 139 of 387 (35.9%), NNT 6.3, propensity score matching.
|
|
Bosaeed, 1/11/2022, Double Blind Randomized Controlled Trial, Saudi Arabia, peer-reviewed, 31 authors, study period 23 July, 2020 - 4 August, 2021, average treatment delay 3.0 days, trial NCT04464408 (history).
|
risk of ICU admission, 618.8% higher, RR 7.19, p = 0.11, treatment 3 of 112 (2.7%), control 0 of 119 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 218.8% higher, RR 3.19, p = 0.16, treatment 6 of 112 (5.4%), control 2 of 119 (1.7%).
|
|
time to clinical improvement, 11.9% higher, HR 1.12, p = 0.51, treatment 112, control 119, adjusted per study, inverted to make HR<1 favor treatment.
|
|
time to viral clearance, 14.9% higher, HR 1.15, p = 0.51, treatment 112, control 119, adjusted per study, inverted to make HR<1 favor treatment, primary outcome.
|
|
Bruminhent, 9/10/2022, retrospective, Thailand, peer-reviewed, 6 authors, study period 26 April, 2021 - 27 May, 2021.
|
risk of progression, 227.0% higher, OR 3.27, p = 0.005, adjusted per study, multivariable, RR approximated with OR.
|
|
Chandiwana, 11/1/2022, Randomized Controlled Trial, South Africa, peer-reviewed, mean age 34.9, 16 authors, study period 3 September, 2020 - 23 August, 2021, average treatment delay 2.6 days, this trial uses multiple treatments in the treatment arm (combined with nitazoxanide) - results of individual treatments may vary, trial NCT04532931 (history).
|
risk of progression, 13.0% higher, OR 1.13, p = 0.89, treatment 37, control 39, adjusted per study, day 28, Table S9, RR approximated with OR.
|
|
time to WHO zero score, 23.5% higher, HR 1.23, p = 0.42, treatment 37, control 39, inverted to make HR<1 favor treatment, Cox proportional hazards, Table S10.
|
|
risk of no viral clearance, 66.7% higher, RR 1.67, p = 0.13, treatment 27 of 37 (73.0%), control 25 of 38 (65.8%), adjusted per study, inverted to make RR<1 favor treatment.
|
|
Golan, 9/6/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 9 authors, study period November 2020 - October 2021, trial NCT04600895 (history) (PRESECO).
|
risk of death, 66.9% lower, RR 0.33, p = 0.50, treatment 0 of 599 (0.0%), control 1 of 588 (0.2%), NNT 588, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
|
|
risk of progression, 1.8% lower, RR 0.98, p = 1.00, treatment 11 of 599 (1.8%), control 11 of 588 (1.9%), NNT 2911, narrow definition.
|
|
risk of progression, 7.1% lower, RR 0.93, p = 0.44, treatment 159 of 599 (26.5%), control 168 of 588 (28.6%), NNT 49, broad definition.
|
|
risk of no recovery, 4.5% lower, RR 0.96, p = 0.79, treatment 73 of 599 (12.2%), control 75 of 588 (12.8%), NNT 176.
|
|
time to viral-, 14.3% lower, relative time 0.86, p < 0.001, treatment median 6.0 IQR 2.0 n=140, control median 7.0 IQR 2.0 n=132, 50% conversion.
|
|
Holubar, 11/24/2021, Double Blind Randomized Controlled Trial, USA, peer-reviewed, 26 authors, study period 8 July, 2020 - 23 March, 2021, average treatment delay 5.0 days, conflicts of interest:
Pfizer, Gates Foundation, Gilead, Regeneron, Janssen.
|
risk of hospitalization, 89.0% lower, RR 0.11, p = 0.06, treatment 0 of 75 (0.0%), control 4 of 74 (5.4%), NNT 18, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of ER visit, 29.5% lower, RR 0.70, p = 0.56, treatment 5 of 75 (6.7%), control 7 of 74 (9.5%), NNT 36.
|
|
risk of no recovery, 19.0% higher, RR 1.19, p = 0.43, treatment 65, control 70, inverted to make RR<1 favor treatment, initial resolution of symptoms.
|
|
viral shedding, 31.6% higher, RR 1.32, p = 0.24, treatment 59, control 57, inverted to make RR<1 favor treatment, primary outcome.
|
|
Iwata, 10/12/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Japan, peer-reviewed, 13 authors, trial jRCT2041210004.
|
risk of oxygen therapy, 16.2% higher, RR 1.16, p = 0.73, treatment 12 of 43 (27.9%), control 12 of 43 (27.9%), adjusted per study, odds ratio converted to relative risk, multivariable, day 28.
|
|
risk of oxygen therapy, 18.5% lower, RR 0.81, p = 0.77, treatment 5 of 24 (20.8%), control 6 of 22 (27.3%), NNT 16, adjusted per study, odds ratio converted to relative risk, patients with onset ≤48 hours, multivariable, day 28.
|
|
risk of no viral clearance, 15.9% higher, RR 1.16, p = 0.66, treatment 21 of 41 (51.2%), control 19 of 43 (44.2%), day 15.
|
|
risk of no viral clearance, 6.0% lower, RR 0.94, p = 0.82, treatment 26 of 41 (63.4%), control 29 of 43 (67.4%), NNT 25, day 10.
|
|
risk of no viral clearance, 0.9% lower, RR 0.99, p = 1.00, treatment 34 of 41 (82.9%), control 36 of 43 (83.7%), NNT 126, day 7.
|
|
risk of no viral clearance, 5.6% lower, RR 0.94, p = 0.48, treatment 36 of 41 (87.8%), control 40 of 43 (93.0%), NNT 19, day 4.
|
Kara, 6/1/2021, Randomized Controlled Trial, Turkey, peer-reviewed, trial NCT04411433 (history).
|
1,008 patient RCT with results unknown and over 5 years late.
|
|
Lokanuwatsatien, 5/24/2023, prospective, Thailand, peer-reviewed, 8 authors, study period September 2021 - March 2022, excluded in exclusion analyses:
unadjusted results with no group details.
|
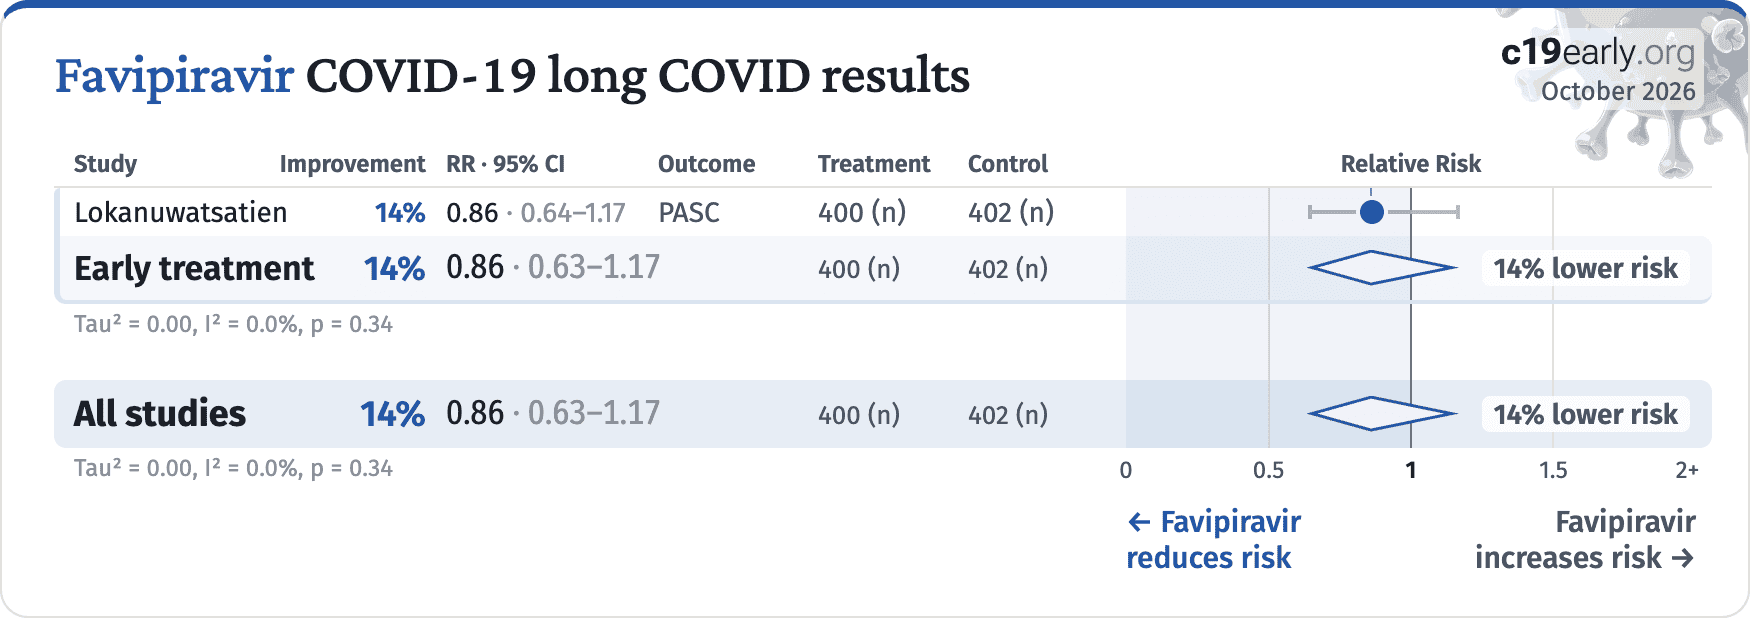
risk of long COVID, 14.0% lower, OR 0.86, p = 0.34, treatment 400, control 402, RR approximated with OR.
|
|
Lowe, 2/15/2022, Double Blind Randomized Controlled Trial, placebo-controlled, United Kingdom, peer-reviewed, 18 authors, study period 6 October, 2020 - 4 November, 2021, trial NCT04499677 (history) (FLARE).
|
risk of ICU admission, 201.7% higher, RR 3.02, p = 0.50, treatment 1 of 59 (1.7%), control 0 of 60 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 201.7% higher, RR 3.02, p = 0.50, treatment 1 of 59 (1.7%), control 0 of 60 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of no viral clearance, 28.4% lower, RR 0.72, p = 0.03, treatment 29 of 54 (53.7%), control 38 of 52 (73.1%), NNT 5.2, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, day 5, primary outcome.
|
|
Luvira, 4/5/2023, Randomized Controlled Trial, multiple countries, peer-reviewed, median age 30.1, 36 authors, study period 30 September, 2021 - 31 October, 2022, trial NCT05041907 (history) (PLATCOV).
|
relative clearance rate, 5.7% worse, RR 1.06, p = 0.42, treatment median 16.6 IQR 10.0 n=116, control median 15.7 IQR 13.0 n=132, primary outcome.
|
|
McMahon, 6/14/2022, Randomized Controlled Trial, placebo-controlled, Australia, peer-reviewed, median age 36.0, 33 authors, study period 31 July, 2020 - 19 September, 2021, trial NCT04445467 (history).
|
risk of oxygen therapy, 1.0% higher, RR 1.01, p = 1.00, treatment 6 of 99 (6.1%), control 6 of 100 (6.0%).
|
|
risk of hospitalization, 55.6% higher, RR 1.56, p = 0.38, treatment 14 of 99 (14.1%), control 9 of 99 (9.1%).
|
|
Qadir, 5/23/2022, prospective, Iraq, peer-reviewed, 3 authors, study period 22 June, 2020 - 25 October, 2021.
|
risk of death, 97.1% lower, RR 0.03, p < 0.001, treatment 0 of 125 (0.0%), control 17 of 125 (13.6%), NNT 7.4, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 30.
|
|
risk of hospitalization, 60.0% lower, RR 0.40, p = 0.001, treatment 14 of 125 (11.2%), control 35 of 125 (28.0%), NNT 6.0.
|
|
risk of no recovery, 97.1% lower, RR 0.03, p < 0.001, treatment 0 of 125 (0.0%), control 17 of 125 (13.6%), NNT 7.4, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 30, primary outcome.
|
|
risk of no recovery, 70.8% lower, RR 0.29, p < 0.001, treatment 14 of 125 (11.2%), control 48 of 125 (38.4%), NNT 3.7, day 15.
|
|
risk of no recovery, 78.8% lower, RR 0.21, p < 0.001, treatment 14 of 125 (11.2%), control 66 of 125 (52.8%), NNT 2.4, day 10.
|
|
risk of no recovery, 70.6% lower, RR 0.29, p < 0.001, treatment 32 of 125 (25.6%), control 109 of 125 (87.2%), NNT 1.6, day 5.
|
|
recovery time, 58.1% lower, relative time 0.42, p < 0.001, treatment 125, control 125.
|
|
Ruzhentsova, 10/26/2020, Randomized Controlled Trial, Russia, preprint, 31 authors, study period 23 May, 2020 - 30 June, 2020, average treatment delay 3.55 days.
|
risk of hospitalization, 6.0% lower, RR 0.94, p = 0.49, treatment 3 of 112 (2.7%), control 2 of 56 (3.6%), adjusted per study.
|
|
HR for time to clinical improvement, 38.7% lower, HR 0.61, p = 0.007, treatment 112, control 56, inverted to make HR<1 favor treatment.
|
|
risk of no viral clearance, 21.9% lower, RR 0.78, p = 0.16, treatment 112, control 56, inverted to make RR<1 favor treatment, day 5 mid-recovery.
|
|
Sawanpanyalert, 9/9/2021, retrospective, Thailand, peer-reviewed, 11 authors.
|
risk of death, ICU, intubation, or high-flow oxygen, 68.0% lower, OR 0.32, p = 0.003, within 4 days of symptom onset, RR approximated with OR.
|
|
Sirijatuphat, 6/8/2022, Randomized Controlled Trial, Thailand, peer-reviewed, 9 authors, study period December 2020 - July 2021, trial TCTR20200514001.
|
time to clinical improvement, 63.9% lower, HR 0.36, p < 0.001, treatment 62, control 31, inverted to make HR<1 favor treatment, primary outcome.
|
|
clinical improvement, 89.9% lower, OR 0.10, p < 0.001, treatment 62, control 31, inverted to make OR<1 favor treatment, logistic regression, day 14, RR approximated with OR.
|
|
risk of mild pneumonia, 42.9% lower, RR 0.57, p = 0.25, treatment 8 of 62 (12.9%), control 7 of 31 (22.6%), NNT 10.
|
|
risk of no viral clearance, 4.2% higher, HR 1.04, p = 0.87, treatment 62, control 31, adjusted per study, inverted to make HR<1 favor treatment.
|
|
Siripongboonsitti, 12/12/2024, retrospective, Thailand, peer-reviewed, 11 authors, study period 1 April, 2021 - 31 May, 2022, FaviPrev trial.
|
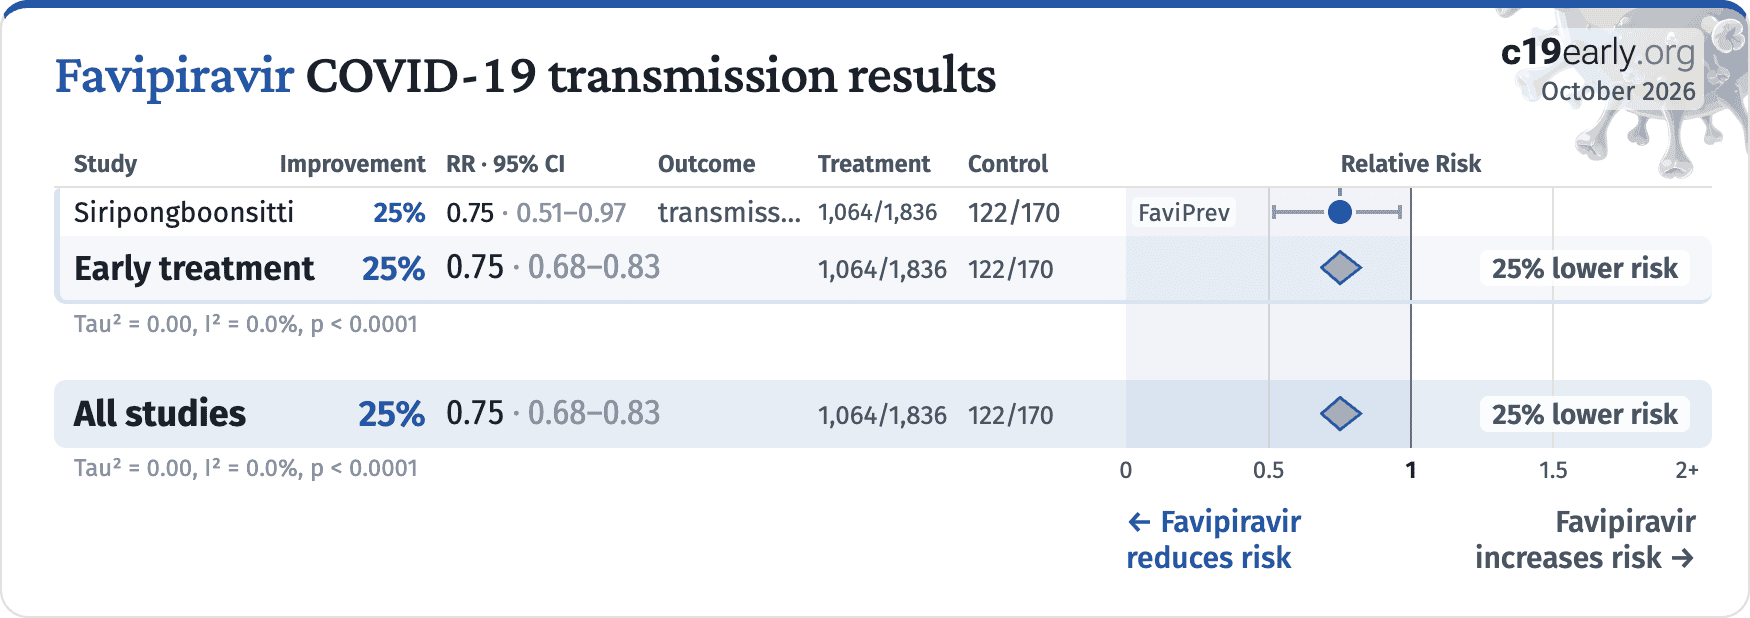
risk of transmission, 24.9% lower, RR 0.75, p = 0.05, treatment 1,064 of 1,836 (58.0%), control 122 of 170 (71.8%), NNT 7.2, adjusted per study, odds ratio converted to relative risk.
|
Smith, 3/21/2023, Double Blind Randomized Controlled Trial, Mexico, trial NCT04918927 (history) (FANTAZE).
|
120 patient RCT with results unknown and over 3 years late.
|
|
Tate, 6/24/2025, Randomized Controlled Trial, United Kingdom, peer-reviewed, mean age 47.2, 39 authors, study period December 2020 - July 2022, average treatment delay 3.84 days, trial ISRCTN31062548 (GETAFIX).
|
risk of hospitalization, 34.2% lower, RR 0.66, p = 0.68, treatment 2 of 152 (1.3%), control 3 of 150 (2.0%), NNT 146.
|
|
risk of 7-point scale, 20.6% lower, OR 0.79, p = 0.61, treatment 152, control 150, adjusted per study, inverted to make OR<1 favor treatment, clinical status to day 15, RR approximated with OR.
|
|
risk of no recovery, 2.9% lower, HR 0.97, p = 0.82, treatment 152, control 150, inverted to make HR<1 favor treatment, time to symptom resolution.
|
|
risk of no viral clearance, 11.5% lower, HR 0.88, p = 0.68, treatment 152, control 150, inverted to make HR<1 favor treatment, time to viral clearance.
|
|
Tsuzuki, 3/21/2022, retrospective, Japan, peer-reviewed, 21 authors, average treatment delay 4.0 days.
|
risk of death, 13.1% lower, HR 0.87, p = 0.59, treatment 2,532, control 5,122, adjusted per study, day 30.
|
|
risk of mechanical ventilation, 2.0% higher, HR 1.02, p = 0.93, treatment 2,532, control 5,122, adjusted per study, IMV/ECMO.
|
|
risk of progression, 17.5% lower, HR 0.82, p = 0.10, treatment 2,532, control 5,122, adjusted per study, oxygen requirement.
|
|
Udwadia, 11/16/2020, Randomized Controlled Trial, India, peer-reviewed, 11 authors, study period 14 May, 2020 - 3 July, 2020, trial CTRI/2020/05/025114.
|
risk of death, 66.4% lower, RR 0.34, p = 1.00, treatment 0 of 73 (0.0%), control 1 of 75 (1.3%), NNT 75, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
time to discharge, 28.9% lower, HR 0.71, p = 0.07, treatment 75, control 72, inverted to make HR<1 favor treatment.
|
|
time to clinical cure, 42.8% lower, HR 0.57, p = 0.02, treatment 75, control 72, inverted to make HR<1 favor treatment.
|
|
time to viral clearance, 26.8% lower, HR 0.73, p = 0.10, treatment 75, control 72, inverted to make HR<1 favor treatment.
|
|
Usanma Koban, 6/7/2022, retrospective, Turkey, peer-reviewed, 3 authors, study period 1 March, 2020 - 30 September, 2020.
|
risk of no viral clearance, 86.0% lower, OR 0.14, p = 0.03, treatment 47, control 79, adjusted per study, multivariable, day 14, RR approximated with OR.
|
|
Vaezi, 1/28/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, 6 authors, study period 5 December, 2020 - 31 March, 2021, trial IRCT20171219037964N3.
|
risk of hospitalization, 105.3% higher, RR 2.05, p = 0.43, treatment 4 of 38 (10.5%), control 2 of 39 (5.1%), day 28.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Abdulaziz, 1/1/2025, retrospective, Egypt, peer-reviewed, median age 68.5, 3 authors, study period September 2020 - February 2021.
|
AKI, 148.7% higher, OR 2.49, p = 0.03, treatment 57, control 179, RR approximated with OR.
|
|
Abdulrahman, 6/21/2022, retrospective, Saudi Arabia, peer-reviewed, 15 authors, study period June 2020 - August 2020, excluded in exclusion analyses:
very late stage, ICU patients.
|
risk of death, 2.6% lower, RR 0.97, p = 0.81, treatment 74 of 193 (38.3%), control 593 of 1,506 (39.4%), NNT 97.
|
|
Acar Sevinc, 6/28/2022, retrospective, Turkey, peer-reviewed, mean age 65.6, 1 author, study period 10 March, 2020 - 10 May, 2020, this trial compares with another treatment - results may be better when compared to placebo, trial NCT04645433 (history), excluded in exclusion analyses:
very late stage, ICU patients.
|
risk of death, 16.2% lower, RR 0.84, p = 0.38, treatment 57 of 85 (67.1%), control 12 of 15 (80.0%), NNT 7.7.
|
|
risk of mechanical ventilation, 10.3% lower, RR 0.90, p = 0.75, treatment 61 of 85 (71.8%), control 12 of 15 (80.0%), NNT 12.
|
|
Al Mutair, 2/15/2022, retrospective, Saudi Arabia, peer-reviewed, 14 authors, study period April 2020 - March 2021, this trial compares with another treatment - results may be better when compared to placebo, excluded in exclusion analyses:
very late stage, ICU patients.
|
risk of death, 7.0% lower, RR 0.93, p = 0.49, treatment 119 of 269 (44.2%), control 128 of 269 (47.6%), NNT 30.
|
|
risk of ARDS, 8.6% higher, RR 1.09, p = 0.63, treatment 76 of 269 (28.3%), control 70 of 269 (26.0%), severe ARDS.
|
|
ICU time, 33.7% higher, relative time 1.34, p = 0.001, treatment 269, control 269.
|
|
hospitalization time, 36.6% higher, relative time 1.37, p = 0.001, treatment 269, control 269.
|
|
Al-Muhsen, 3/4/2022, prospective, Saudi Arabia, peer-reviewed, 11 authors, study period June 2020 - January 2021.
|
risk of death, 263.0% higher, HR 3.63, p = 0.04, treatment 156, control 442, Cox proportional hazards, day 65.
|
|
risk of oxygen therapy, 40.6% lower, RR 0.59, p < 0.001, treatment 52 of 156 (33.3%), control 248 of 442 (56.1%), NNT 4.4.
|
|
hospitalization time, 40.0% higher, relative time 1.40, p = 0.03, treatment 156, control 442.
|
|
Alamer, 5/19/2021, retrospective, Saudi Arabia, peer-reviewed, 18 authors.
|
risk of death, 56.0% higher, HR 1.56, p = 0.26, treatment 12 of 233 (5.2%), control 21 of 223 (9.4%), adjusted per study, day 90.
|
|
risk of mechanical ventilation, 90.0% lower, HR 0.10, p < 0.001, treatment 4 of 218 (1.8%), control 27 of 165 (16.4%), NNT 6.9, adjusted per study.
|
|
adjusted discharge ratio, 49.0% lower, RR 0.51, p < 0.001, treatment 221, control 201, adjusted per study, inverted to make RR<1 favor treatment.
|
|
Almoosa, 8/24/2021, retrospective, Saudi Arabia, peer-reviewed, 14 authors.
|
risk of death, 42.3% higher, RR 1.42, p = 0.10, treatment 33 of 110 (30.0%), control 24 of 116 (20.7%), adjusted per study, odds ratio converted to relative risk, overall mortality, multivariate binary logistic regression.
|
|
risk of death, 149.3% higher, RR 2.49, p = 0.006, treatment 26 of 110 (23.6%), control 11 of 116 (9.5%), day 28.
|
|
risk of death, 61.7% lower, RR 0.38, p = 0.11, treatment 4 of 110 (3.6%), control 11 of 116 (9.5%), NNT 17, day 14.
|
|
risk of ICU admission, 90.0% higher, OR 1.90, p = 0.02, treatment 110, control 116, adjusted per study, multivariate binary logistic regression, RR approximated with OR.
|
|
recovery time, 10.9% higher, relative time 1.11, p = 0.17, treatment 110, control 116.
|
|
Alosaimi, 11/24/2022, retrospective, Saudi Arabia, peer-reviewed, 13 authors, study period April 2020 - March 2021, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 80.0% lower, RR 0.20, p = 0.49, treatment 0 of 37 (0.0%), control 2 of 37 (5.4%), NNT 18, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), propensity score matching.
|
|
hospitalization time, 75.0% higher, relative time 1.75, p = 0.63, treatment 37, control 37, propensity score matching.
|
|
time to discharge, 40.0% higher, relative time 1.40, p = 0.74, treatment 37, control 37, propensity score matching.
|
|
Alotaibi, 9/14/2021, retrospective, Saudi Arabia, peer-reviewed, 11 authors, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 57.2% lower, RR 0.43, p = 0.05, treatment 244, control 193, inverted to make RR<1 favor treatment, multivariate, day 30.
|
|
AlQahtani, 3/23/2022, Randomized Controlled Trial, Bahrain, peer-reviewed, 14 authors, study period August 2020 - March 2021, trial NCT04387760 (history).
|
risk of death, 196.3% higher, RR 2.96, p = 1.00, treatment 1 of 54 (1.9%), control 0 of 52 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 30.
|
|
risk of ICU admission, 75.9% lower, RR 0.24, p = 0.20, treatment 1 of 54 (1.9%), control 4 of 52 (7.7%), NNT 17.
|
|
risk of no recovery, 41.9% higher, RR 1.42, p = 0.51, treatment 8 of 53 (15.1%), control 5 of 47 (10.6%).
|
|
risk of no viral clearance, 42.9% lower, RR 0.57, p = 0.21, treatment 8 of 40 (20.0%), control 14 of 40 (35.0%), NNT 6.7.
|
|
Alsaraj, 1/8/2024, Randomized Controlled Trial, Iraq, peer-reviewed, 6 authors, study period September 2021 - February 2022, excluded in exclusion analyses:
potential data issue.
|
risk of death, 87.1% higher, HR 1.87, p = 0.26, treatment 9 of 51 (17.6%), control 5 of 53 (9.4%), adjusted per study, multivariable, Cox proportional hazards, day 30.
|
|
Alshamrani, 2/15/2023, retrospective, Saudi Arabia, peer-reviewed, 3 authors, study period March 2020 - January 2021.
|
risk of death, 14.0% higher, RR 1.14, p = 0.13, treatment 326 of 1,159 (28.1%), control 316 of 1,380 (22.9%), adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable.
|
|
risk of progression, 1.9% higher, RR 1.02, p = 0.83, treatment 475 of 1,159 (41.0%), control 499 of 1,380 (36.2%), adjusted per study, odds ratio converted to relative risk, AKI, ARDS, multi-organ failure, or mortality, propensity score matching, multivariable.
|
|
ICU time, 18.6% higher, relative time 1.19, p = 0.005, treatment 668, control 633, propensity score matching.
|
|
hospitalization time, 28.8% higher, relative time 1.29, p < 0.001, treatment 1,159, control 1,380, propensity score matching.
|
|
Arfijanto, 5/4/2023, retrospective, Indonesia, peer-reviewed, 8 authors, study period June 2021 - December 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
delayed viral clearance, 50.9% lower, RR 0.49, p = 0.02, treatment 8 of 37 (21.6%), control 55 of 125 (44.0%), NNT 4.5.
|
|
Babayigit, 8/31/2022, retrospective, Turkey, peer-reviewed, mean age 51.9, 68 authors, study period 11 March, 2020 - 18 July, 2020, excluded in exclusion analyses:
substantial unadjusted confounding by indication possible.
|
risk of mechanical ventilation, 184.4% higher, RR 2.84, p = 0.01, treatment 47 of 325 (14.5%), control 17 of 977 (1.7%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of ICU admission, 181.5% higher, RR 2.81, p = 0.001, treatment 75 of 325 (23.1%), control 35 of 969 (3.6%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
hospitalization time, 100% higher, relative time 2.00, p = 0.001, treatment 265, control 746.
|
|
Behboodikhah, 9/15/2022, retrospective, Iran, peer-reviewed, 8 authors.
|
risk of death, 68.5% lower, OR 0.32, p = 0.20, treatment 95, control 2,079, adjusted per study, multivariable, RR approximated with OR.
|
|
Cai, 3/18/2020, retrospective, China, peer-reviewed, 26 authors.
|
risk of no improvement in CT, 68.7% lower, OR 0.31, p = 0.04, treatment 35, control 45, inverted to make OR<1 favor treatment, multivariate, RR approximated with OR.
|
|
risk of no viral clearance, 70.9% lower, HR 0.29, p = 0.03, treatment 35, control 45, inverted to make HR<1 favor treatment, multivariate.
|
|
Chen (B), 9/2/2021, Randomized Controlled Trial, China, peer-reviewed, 14 authors, average treatment delay 9.0 days, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of ICU admission, 3.4% higher, RR 1.03, p = 1.00, treatment 2 of 116 (1.7%), control 2 of 120 (1.7%).
|
|
risk of respiratory failure, 74.1% lower, RR 0.26, p = 0.37, treatment 1 of 116 (0.9%), control 4 of 120 (3.3%), NNT 40.
|
|
risk of oxygen therapy, 19.5% lower, RR 0.80, p = 0.42, treatment 21 of 116 (18.1%), control 27 of 120 (22.5%), NNT 23.
|
|
risk of progression to dyspnea, 70.4% lower, RR 0.30, p = 0.03, treatment 4 of 116 (3.4%), control 14 of 120 (11.7%), NNT 12.
|
|
risk of dyspnea, 10.3% lower, RR 0.90, p = 0.84, treatment 13 of 116 (11.2%), control 15 of 120 (12.5%), NNT 77.
|
|
risk of no recovery, 19.7% lower, RR 0.80, p = 0.15, treatment 45 of 116 (38.8%), control 58 of 120 (48.3%), NNT 10, day 7, primary outcome.
|
|
Chuah, 11/19/2021, Randomized Controlled Trial, Malaysia, peer-reviewed, 18 authors, study period February 2021 - July 2021.
|
risk of death, 1154.0% higher, RR 12.54, p = 0.08, treatment 5 of 250 (2.0%), control 0 of 250 (0.0%), odds ratio converted to relative risk, continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of mechanical ventilation, 19.5% higher, RR 1.20, p = 0.76, treatment 6 of 250 (2.4%), control 5 of 250 (2.0%), odds ratio converted to relative risk.
|
|
risk of ICU admission, 8.5% higher, RR 1.09, p = 0.84, treatment 13 of 250 (5.2%), control 12 of 250 (4.8%), odds ratio converted to relative risk.
|
|
Cilli, 3/3/2022, retrospective, Turkey, peer-reviewed, 10 authors, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 37.5% lower, RR 0.62, p = 0.51, treatment 5 of 23 (21.7%), control 8 of 23 (34.8%), NNT 7.7, day 30.
|
|
Damayanti, 11/1/2021, retrospective, Indonesia, peer-reviewed, 4 authors, excluded in exclusion analyses:
minimal details provided.
|
risk of no recovery, 54.5% lower, RR 0.46, p = 0.03, treatment 96, control 96, adjusted per study, inverted to make RR<1 favor treatment.
|
|
Delen, 12/31/2022, retrospective, Turkey, peer-reviewed, mean age 60.1, 8 authors, study period March 2020 - July 2020.
|
risk of ICU admission, 22.8% lower, RR 0.77, p = 1.00, treatment 3 of 34 (8.8%), control 4 of 35 (11.4%), NNT 38.
|
|
risk of no recovery, 87.5% lower, RR 0.12, p = 0.02, treatment 1 of 21 (4.8%), control 8 of 21 (38.1%), NNT 3.0, day 5, fever.
|
|
hospitalization time, 2.2% higher, relative time 1.02, p = 0.74, treatment 34, control 35.
|
|
risk of no hospital discharge, 2.9% higher, RR 1.03, p = 1.00, treatment 31 of 34 (91.2%), control 31 of 35 (88.6%).
|
|
Finberg, 12/7/2021, Randomized Controlled Trial, USA, peer-reviewed, 10 authors, study period 17 April, 2020 - 30 October, 2020, average treatment delay 8.4 days, trial NCT04358549 (history).
|
risk of death, 200.0% higher, RR 3.00, p = 1.00, treatment 1 of 25 (4.0%), control 0 of 25 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 60.
|
|
risk of mechanical ventilation, 200.0% higher, RR 3.00, p = 1.00, treatment 1 of 25 (4.0%), control 0 of 25 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of no recovery, 58.1% lower, OR 0.42, p = 0.08, treatment 25, control 25, inverted to make OR<1 favor treatment, day 8 mid-recovery, 6-point ordinal scale, RR approximated with OR.
|
|
risk of no recovery, 46.2% higher, OR 1.46, p = 0.54, treatment 25, control 25, inverted to make OR<1 favor treatment, day 15, 6-point ordinal scale, RR approximated with OR.
|
|
time to viral-, 46.7% lower, relative time 0.53, p = 0.04, treatment 25, control 25, primary outcome.
|
|
Hafez, 4/8/2022, retrospective, United Arab Emirates, peer-reviewed, 6 authors, this trial uses multiple treatments in the treatment arm (combined with HCQ) - results of individual treatments may vary.
|
viral clearance time, 3.1% higher, HR 1.03, p = 0.09, treatment 59, control 1,446, inverted to make HR<1 favor treatment, HCQ + favipiravir, Cox proportional hazards.
|
|
viral clearance time, 58.7% lower, HR 0.41, p = 0.09, treatment 4, control 1,446, inverted to make HR<1 favor treatment, HCQ + favipiravir + lopinavir/ritonavir, Cox proportional hazards.
|
|
Haji Aghajani, 4/29/2021, retrospective, Iran, peer-reviewed, 7 authors.
|
risk of death, 26.1% lower, HR 0.74, p = 0.28, treatment 40, control 951, univariate Cox proportional regression.
|
|
Hartantri, 2/9/2023, retrospective, Indonesia, peer-reviewed, 10 authors, study period 1 March, 2020 - 31 December, 2020.
|
risk of death, 76.0% lower, HR 0.24, p < 0.001, adjusted per study, mild/moderate, multivariable, Cox proportional hazards, day 28.
|
|
risk of death, 60.0% lower, HR 0.40, p = 0.04, adjusted per study, severe, multivariable, Cox proportional hazards, day 28.
|
|
Hassaniazad, 3/24/2022, Randomized Controlled Trial, Iran, peer-reviewed, mean age 53.8, 7 authors, this trial compares with another treatment - results may be better when compared to placebo, trial IRCT20200506047323N3.
|
risk of death, 67.7% lower, RR 0.32, p = 0.15, treatment 2 of 32 (6.2%), control 6 of 31 (19.4%), NNT 7.6, day 14.
|
|
risk of death, 3.1% lower, RR 0.97, p = 1.00, treatment 1 of 32 (3.1%), control 1 of 31 (3.2%), NNT 992, day 7.
|
|
risk of ICU admission, 35.4% lower, RR 0.65, p = 0.51, treatment 4 of 32 (12.5%), control 6 of 31 (19.4%), NNT 15, day 14.
|
|
hospitalization time, 25.0% lower, relative time 0.75, p = 0.14, treatment 32, control 31.
|
|
risk of no viral clearance, 18.0% lower, RR 0.82, p = 0.24, treatment 22 of 32 (68.8%), control 26 of 31 (83.9%), NNT 6.6, day 7.
|
|
Hobbs (B), 8/31/2024, Randomized Controlled Trial, United Kingdom, peer-reviewed, median age 54.1, 26 authors, study period 8 April, 2021 - 1 July, 2022, average treatment delay 5.1 days, trial ISRCTN86534580 (PRINCIPLE).
|
risk of death, 86.3% lower, RR 0.14, p = 0.11, treatment 0 of 1,829 (0.0%), control 3 of 1,668 (0.2%), NNT 556, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
|
|
risk of ICU admission, 191.1% higher, RR 2.91, p = 1.00, treatment 1 of 1,825 (0.1%), control 0 of 1,663 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of death/hospitalization, 1.0% lower, HR 0.99, p = 0.51, treatment 1,829, control 3,256, adjusted per study.
|
|
not fully recovered, 17.4% lower, RR 0.83, p = 0.003, treatment 350 of 1,582 (22.1%), control 378 of 1,412 (26.8%), NNT 22, day 365, Table 3.
|
|
not fully recovered, 12.2% lower, RR 0.88, p = 0.04, treatment 378 of 1,503 (25.1%), control 384 of 1,340 (28.7%), NNT 29, day 180, Table 3.
|
|
not fully recovered, 17.2% lower, RR 0.83, p < 0.001, treatment 418 of 1,507 (27.7%), control 459 of 1,370 (33.5%), NNT 17, day 90, Table 3.
|
|
ongoing persistent symptoms at 3, 6, 12 months, 29.0% lower, RR 0.71, p = 0.02, treatment 1,829, control 1,668, Table 3.
|
|
time to first reported recovery, 18.7% lower, HR 0.81, p < 0.001, treatment 1,829, control 3,256, adjusted per study, inverted to make HR<1 favor treatment, primary outcome.
|
|
early sustained recovery, 34.2% lower, RR 0.66, p < 0.001, treatment 1,828, control 1,666, adjusted per study, inverted to make RR<1 favor treatment.
|
|
sustained recovery, 24.8% lower, RR 0.75, p < 0.001, treatment 1,829, control 1,668, adjusted per study, inverted to make RR<1 favor treatment.
|
|
alleviation of all symptoms, 12.3% lower, RR 0.88, p < 0.001, treatment 1,562, control 1,407, adjusted per study, inverted to make RR<1 favor treatment.
|
|
sustained alleviation of all symptoms, 20.6% lower, RR 0.79, p < 0.001, treatment 1,562, control 1,407, adjusted per study, inverted to make RR<1 favor treatment.
|
|
initial reduction of severity, 23.1% lower, RR 0.77, p < 0.001, treatment 1,828, control 1,667, adjusted per study, inverted to make RR<1 favor treatment.
|
|
Horcajada, 8/24/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, peer-reviewed, 30 authors, study period November 2020 - October 2021, trial EudraCT2020-002753-22 (FAVID).
|
risk of death, 382.6% higher, RR 4.83, p = 0.49, treatment 2 of 23 (8.7%), control 0 of 21 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 28.
|
|
risk of mechanical ventilation, 37.0% higher, RR 1.37, p = 1.00, treatment 3 of 23 (13.0%), control 2 of 21 (9.5%), day 28.
|
|
dischage or NEWS <3, 16.7% lower, relative time 0.83, p = 0.64, treatment 23, control 21.
|
|
time to viral-, 125.0% higher, relative time 2.25, p = 0.51, treatment 23, control 21.
|
|
Ivashchenko, 8/9/2020, Randomized Controlled Trial, Russia, peer-reviewed, 21 authors, study period April 2020 - May 2020, average treatment delay 6.7 days.
|
risk of death, 300.0% higher, RR 4.00, p = 0.55, treatment 2 of 40 (5.0%), control 0 of 20 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 29.
|
|
risk of mechanical ventilation, 300.0% higher, RR 4.00, p = 0.55, treatment 2 of 40 (5.0%), control 0 of 20 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of ICU admission, 300.0% higher, RR 4.00, p = 0.55, treatment 2 of 40 (5.0%), control 0 of 20 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of no viral clearance, 46.4% lower, RR 0.54, p = 0.03, treatment 15 of 40 (37.5%), control 14 of 20 (70.0%), NNT 3.1, mid-recovery day 5.
|
|
risk of no viral clearance, 62.5% lower, RR 0.37, p = 0.21, treatment 3 of 40 (7.5%), control 4 of 20 (20.0%), NNT 8.0, day 10.
|
|
risk of no discharge and WHO-OSC>2, 66.7% higher, RR 1.67, p = 0.51, treatment 10 of 40 (25.0%), control 3 of 20 (15.0%).
|
|
Khamis, 11/9/2020, Randomized Controlled Trial, Oman, peer-reviewed, 11 authors, study period 22 June, 2020 - 13 August, 2020, this trial compares with another treatment - results may be better when compared to placebo, this trial uses multiple treatments in the treatment arm (combined with interferon beta-1b) - results of individual treatments may vary, excluded in exclusion analyses:
study compares against another treatment showing significant efficacy.
|
risk of death, 14.8% lower, RR 0.85, p = 1.00, treatment 5 of 44 (11.4%), control 6 of 45 (13.3%), NNT 51, day 14.
|
|
risk of ICU admission, 2.3% higher, RR 1.02, p = 1.00, treatment 8 of 44 (18.2%), control 8 of 45 (17.8%).
|
|
risk of no recovery, 9.6% higher, RR 1.10, p = 0.82, treatment 15 of 44 (34.1%), control 14 of 45 (31.1%).
|
|
Kokturk, 4/28/2021, retrospective, database analysis, Turkey, peer-reviewed, 68 authors.
|
risk of death, 84.1% higher, RR 1.84, p = 0.29, treatment 39 of 328 (11.9%), control 28 of 1,172 (2.4%), adjusted per study, odds ratio converted to relative risk.
|
|
Kulzhanova, 8/31/2021, retrospective, Kazakhstan, peer-reviewed, 10 authors, average treatment delay 6.45 days.
|
risk of no improvement, 88.0% lower, RR 0.12, p < 0.001, treatment 3 of 40 (7.5%), control 25 of 40 (62.5%), NNT 1.8, mid-recovery day 7.
|
|
risk of no improvement, 88.9% lower, RR 0.11, p = 0.12, treatment 0 of 40 (0.0%), control 4 of 40 (10.0%), NNT 10.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 14.
|
|
risk of no viral clearance, 50.0% lower, RR 0.50, p = 0.18, treatment 6 of 40 (15.0%), control 12 of 40 (30.0%), NNT 6.7.
|
|
Kurniyanto, 2/28/2022, retrospective, Indonesia, peer-reviewed, 11 authors, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 48.0% lower, RR 0.52, p = 0.21, treatment 10 of 325 (3.1%), control 9 of 152 (5.9%), NNT 35.
|
|
Lou, 10/25/2020, Randomized Controlled Trial, China, peer-reviewed, 13 authors, average treatment delay 8.5 days, trial ChiCTR2000029544.
|
risk of ICU admission, 422.2% higher, RR 5.22, p = 0.21, treatment 2 of 9 (22.2%), control 0 of 10 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of no recovery, 11.1% lower, RR 0.89, p = 1.00, treatment 4 of 9 (44.4%), control 5 of 10 (50.0%), NNT 18, day 14.
|
|
risk of no recovery, 13.6% lower, RR 0.86, p = 0.58, treatment 7 of 9 (77.8%), control 9 of 10 (90.0%), NNT 8.2, day 7.
|
|
risk of no viral clearance, 422.2% higher, RR 5.22, p = 0.21, treatment 2 of 9 (22.2%), control 0 of 10 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 14.
|
|
risk of no viral clearance, 11.1% higher, RR 1.11, p = 1.00, treatment 5 of 9 (55.6%), control 5 of 10 (50.0%), day 7.
|
|
Lumkul, 6/4/2025, retrospective, Thailand, peer-reviewed, 5 authors, study period 14 May, 2021 - 20 September, 2021.
|
survival time, 4.5% lower, relative time 0.96, p = 0.004, treatment 29.46 [29.22-29.71] n=828, control 28.14 [26.51-29.76] n=109.
|
|
Pushkar, 11/5/2020, Randomized Controlled Trial, Russia, preprint, mean age 50.0, 1 author.
|
risk of no clinical status improvement of 2+ WHO-OSCI at ~10 days, 14.1% lower, RR 0.86, p = 0.06, treatment 73 of 100 (73.0%), control 85 of 100 (85.0%), NNT 8.3.
|
|
relative time to clinical improvement, 33.3% lower, relative time 0.67, p < 0.001, treatment 100, control 100.
|
|
risk of no fever reduction by day 3, 45.2% lower, RR 0.55, p < 0.001, treatment 40 of 100 (40.0%), control 73 of 100 (73.0%), NNT 3.0.
|
|
relative time to resolution of fever, 20.0% lower, relative time 0.80, p = 0.05, treatment 100, control 100.
|
|
risk of no discharge at day 10, 69.7% lower, RR 0.30, p < 0.001, treatment 10 of 100 (10.0%), control 33 of 100 (33.0%), NNT 4.3.
|
|
risk of no full recovery at day 10, 26.7% lower, RR 0.73, p < 0.001, treatment 66 of 100 (66.0%), control 90 of 100 (90.0%), NNT 4.2.
|
|
risk of no improvement in lung CT, 33.3% lower, RR 0.67, p = 0.007, treatment 40 of 100 (40.0%), control 60 of 100 (60.0%), NNT 5.0.
|
|
risk of no viral clearance, 90.5% lower, RR 0.10, p < 0.001, treatment 2 of 100 (2.0%), control 21 of 100 (21.0%), NNT 5.3.
|
|
Rahman, 5/13/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Bangladesh, peer-reviewed, mean age 37.8, 10 authors, study period May 2020 - July 2020, trial NCT04402203 (history).
|
risk of no chest x-ray improvement, 89.5% lower, RR 0.11, p = 0.005, treatment 1 of 19 (5.3%), control 8 of 16 (50.0%), NNT 2.2, day 10.
|
|
risk of no chest x-ray improvement, 64.9% lower, RR 0.35, p = 0.007, treatment 5 of 19 (26.3%), control 12 of 16 (75.0%), NNT 2.1, day 7.
|
|
risk of no chest x-ray improvement, 47.4% lower, RR 0.53, p = 0.001, treatment 10 of 19 (52.6%), control 16 of 16 (100.0%), NNT 2.1, day 4.
|
|
risk of no viral clearance, 91.7% lower, RR 0.08, p < 0.001, treatment 1 of 25 (4.0%), control 12 of 25 (48.0%), NNT 2.3, day 10.
|
|
risk of no viral clearance, 62.5% lower, RR 0.38, p = 0.010, treatment 6 of 25 (24.0%), control 16 of 25 (64.0%), NNT 2.5, day 7.
|
|
risk of no viral clearance, 48.0% lower, RR 0.52, p < 0.001, treatment 13 of 25 (52.0%), control 25 of 25 (100.0%), NNT 2.1, day 4.
|
|
Saito, 1/28/2024, retrospective, Japan, peer-reviewed, 6 authors, study period February 2020 - June 2021, average treatment delay 6.9 days, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 168.3% higher, RR 2.68, p = 0.06, treatment 7 of 40 (17.5%), control 6 of 92 (6.5%).
|
|
Shah, 9/22/2022, Randomized Controlled Trial, placebo-controlled, multiple countries, peer-reviewed, median age 58.9, 120 authors, study period 5 May, 2020 - 26 May, 2021, average treatment delay 8.9 days, trial NCT04373733 (history) (PIONEER).
|
risk of death, 26.0% lower, HR 0.74, p = 0.24, treatment 26 of 251 (10.4%), control 34 of 248 (13.7%), NNT 30, day 28.
|
|
risk of mechanical ventilation, 24.0% lower, HR 0.76, p = 0.21, treatment 251, control 248.
|
|
risk of no recovery, 5.7% lower, HR 0.94, p = 0.53, treatment 251, control 248, inverted to make HR<1 favor treatment.
|
|
Shamsi, 7/17/2023, retrospective, Iran, peer-reviewed, 4 authors, study period 1 March, 2020 - 1 August, 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 96.4% lower, RR 0.04, p = 0.14, treatment 0 of 19 (0.0%), control 24 of 164 (14.6%), NNT 6.8, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Shenoy, 11/9/2021, Double Blind Randomized Controlled Trial, Kuwait, preprint, 8 authors, study period 22 August, 2020 - 27 January, 2021, average treatment delay 6.3 days, trial NCT04529499 (history).
|
risk of death, 29.5% higher, RR 1.29, p = 0.54, treatment 14 of 175 (8.0%), control 11 of 178 (6.2%), day 28.
|
|
risk of mechanical ventilation, 33.0% higher, RR 1.33, p = 0.54, treatment 17 of 175 (9.7%), control 13 of 178 (7.3%).
|
|
risk of ICU admission, 1.7% higher, RR 1.02, p = 0.54, treatment 20 of 175 (11.4%), control 20 of 178 (11.2%).
|
|
time to resolution of hypoxia, 1.0% higher, HR 1.01, p = 0.94, treatment 157, control 158, inverted to make HR<1 favor treatment, primary outcome.
|
|
time to hospital discharge, 5.7% lower, HR 0.94, p = 0.60, treatment 175, control 178, inverted to make HR<1 favor treatment.
|
|
time to resolution of hypoxia, 17.4% lower, HR 0.83, p = 0.29, treatment 157, control 158, inverted to make HR<1 favor treatment, earlier treatment subgroup, primary outcome.
|
|
time to hospital discharge, 32.0% lower, HR 0.68, p = 0.01, treatment 175, control 178, inverted to make HR<1 favor treatment, earlier treatment subgroup.
|
|
Shinada, 3/24/2022, retrospective, Japan, peer-reviewed, 11 authors, study period 28 May, 2020 - 26 September, 2020, average treatment delay 8.9 days.
|
hospitalization time, 7.5% lower, HR 0.93, p = 0.84, treatment 17, control 17.
|
|
viral clearance time, 55.2% lower, HR 0.45, p = 0.04, treatment 17, control 17.
|
|
Shinkai, 8/27/2021, Single Blind Randomized Controlled Trial, Japan, peer-reviewed, 39 authors, average treatment delay 4.8 days.
|
time to improvement, 37.1% lower, HR 0.63, p = 0.01, treatment 107, control 49, adjusted per study, inverted to make HR<1 favor treatment, Cox proportional hazards, composite time to improvement in temperature, SpO2, CT findings, and recovery to PCR-.
|
|
time to improvement, 58.5% lower, HR 0.41, p = 0.01, treatment 47, control 13, adjusted per study, inverted to make HR<1 favor treatment, <5 days from onset of fever, Cox proportional hazards, composite time to improvement in temperature, SpO2, CT findings, and recovery to PCR-.
|
|
Solaymani-Dodaran, 3/11/2021, Randomized Controlled Trial, Iran, peer-reviewed, 44 authors, study period 4 February, 2020 - 8 March, 2020, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 19.2% higher, RR 1.19, p = 0.54, treatment 26 of 190 (13.7%), control 21 of 183 (11.5%).
|
|
risk of mechanical ventilation, 53.0% higher, RR 1.53, p = 0.15, treatment 27 of 190 (14.2%), control 17 of 183 (9.3%).
|
|
risk of ICU admission, 19.4% higher, RR 1.19, p = 0.56, treatment 31 of 190 (16.3%), control 25 of 183 (13.7%).
|
|
Sulaiman, 6/14/2023, retrospective, Saudi Arabia, peer-reviewed, mean age 60.1, 20 authors, study period 1 March, 2020 - 31 July, 2021, excluded in exclusion analyses:
very late stage, ICU patients.
|
risk of death, 17.0% higher, HR 1.17, p = 0.51, treatment 73, control 73, in-hospital, propensity score matching.
|
|
risk of death, 14.0% lower, HR 0.86, p = 0.53, treatment 73, control 73, propensity score matching, day 30.
|
|
ventilation time, 46.7% higher, relative time 1.47, p = 0.008, treatment 73, control 73, propensity score matching.
|
|
ICU time, 50.0% higher, relative time 1.50, p = 0.01, treatment 73, control 73, propensity score matching.
|
|
Tabarsi, 9/30/2021, Randomized Controlled Trial, Iran, peer-reviewed, 27 authors, study period 4 April, 2020 - 7 May, 2020, average treatment delay 7.0 days, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 29.7% lower, RR 0.70, p = 0.70, treatment 3 of 32 (9.4%), control 4 of 30 (13.3%), NNT 25.
|
|
risk of ICU admission, 41.4% lower, RR 0.59, p = 0.36, treatment 5 of 32 (15.6%), control 8 of 30 (26.7%), NNT 9.1.
|
|
risk of <50% improvement in chest CT, 6.2% lower, RR 0.94, p = 0.76, treatment 24 of 32 (75.0%), control 24 of 30 (80.0%), NNT 20.
|
|
hospitalization time, 25.0% lower, relative time 0.75, p = 0.03, treatment 32, control 30.
|
|
Tawfik, 6/29/2022, retrospective, Saudi Arabia, peer-reviewed, mean age 60.1, 8 authors, study period 3 June, 2020 - 3 November, 2020, excluded in exclusion analyses:
unadjusted results with minimal group details.
|
risk of death, 96.5% lower, RR 0.04, p < 0.001, treatment 1 of 103 (1.0%), control 17 of 62 (27.4%), NNT 3.8.
|
|
risk of ICU admission, 21.0% lower, RR 0.79, p = 0.45, treatment 21 of 103 (20.4%), control 16 of 62 (25.8%), NNT 18.
|
|
hospitalization time, 15.8% lower, relative time 0.84, p < 0.001, treatment mean 9.6 (±1.2) n=102, control mean 11.4 (±1.7) n=58.
|
|
Tehrani, 6/15/2022, Randomized Controlled Trial, Iran, peer-reviewed, mean age 52.5, 5 authors, study period April 2021 - September 2021, average treatment delay 5.29 days, trial IRCT20211004052664N1.
|
risk of hospitalization, 34.2% lower, RR 0.66, p = 0.24, treatment 10 of 38 (26.3%), control 16 of 40 (40.0%), NNT 7.3.
|
|
risk of no recovery, 79.6% lower, RR 0.20, p = 0.49, treatment 0 of 38 (0.0%), control 2 of 40 (5.0%), NNT 20, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 7, dyspnea.
|
|
risk of no recovery, 57.9% lower, RR 0.42, p = 0.010, treatment 8 of 38 (21.1%), control 20 of 40 (50.0%), NNT 3.5, day 5, dyspnea.
|
|
risk of no recovery, 47.4% lower, RR 0.53, p = 1.00, treatment 1 of 38 (2.6%), control 2 of 40 (5.0%), NNT 42, day 7, fever.
|
|
risk of no recovery, 47.4% lower, RR 0.53, p = 0.25, treatment 5 of 38 (13.2%), control 10 of 40 (25.0%), NNT 8.4, day 5, fever.
|
|
risk of no recovery, 66.1% lower, RR 0.34, p = 1.00, treatment 0 of 38 (0.0%), control 1 of 40 (2.5%), NNT 40, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 7, sore throat.
|
|
risk of no recovery, 47.4% lower, RR 0.53, p = 0.68, treatment 2 of 38 (5.3%), control 4 of 40 (10.0%), NNT 21, day 5, sore throat.
|
|
risk of no recovery, 29.8% lower, RR 0.70, p = 0.17, treatment 16 of 38 (42.1%), control 24 of 40 (60.0%), NNT 5.6, day 7, cough.
|
|
risk of no recovery, 7.1% lower, RR 0.93, p = 0.56, treatment 30 of 38 (78.9%), control 34 of 40 (85.0%), NNT 17, day 5, cough.
|
|
risk of no recovery, 21.1% lower, RR 0.79, p = 0.77, treatment 6 of 38 (15.8%), control 8 of 40 (20.0%), NNT 24, day 7, myalgia.
|
|
risk of no recovery, 38.1% lower, RR 0.62, p = 0.16, treatment 10 of 38 (26.3%), control 17 of 40 (42.5%), NNT 6.2, day 5, myalgia.
|
|
Uyaroğlu, 3/17/2022, retrospective, propensity score matching, Turkey, peer-reviewed, 6 authors, study period 20 March, 2020 - 30 September, 2020, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 66.7% lower, RR 0.33, p = 1.00, treatment 0 of 42 (0.0%), control 1 of 42 (2.4%), NNT 42, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of ICU admission, 200.0% higher, RR 3.00, p = 1.00, treatment 1 of 42 (2.4%), control 0 of 42 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
hospitalization time, 10.8% higher, relative time 1.11, p = 0.90, treatment 42, control 42.
|
|
Yulia, 3/7/2022, retrospective, Indonesia, peer-reviewed, median age 46.0, 10 authors, study period July 2020 - December 2020.
|
risk of death, 85.3% lower, OR 0.15, p = 0.05, inverted to make OR<1 favor treatment, RR approximated with OR.
|
|
Zhao, 4/21/2021, Randomized Controlled Trial, China, peer-reviewed, 25 authors, study period 27 March, 2020 - 9 May, 2020.
|
risk of no viral clearance, 59.0% lower, RR 0.41, p = 0.06, treatment 7 of 36 (19.4%), control 9 of 19 (47.4%), NNT 3.6.
|
|
time to viral-, 52.4% lower, relative time 0.48, p = 0.04, treatment 36, control 19, inverted to make RR<1 favor treatment.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.