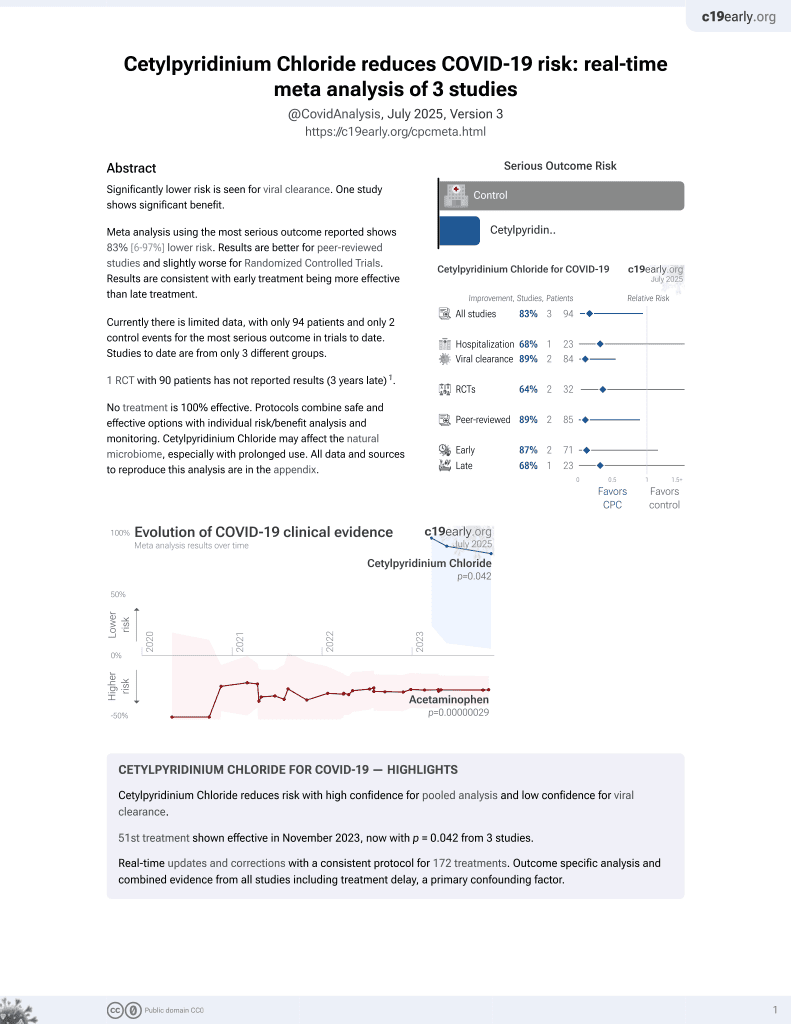
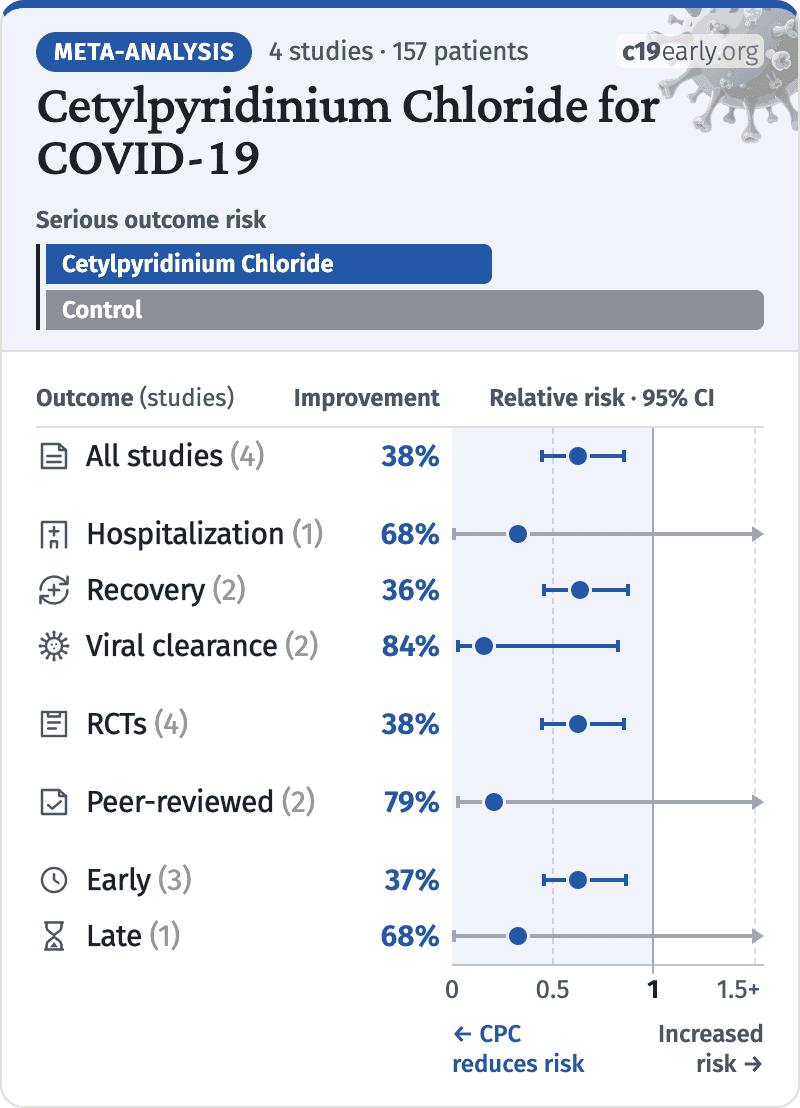
Currently there is limited data, with only 157 patients and only 44 control events for the most serious outcome in trials to date.
1 RCT
with 90 patients has not reported results (4 years late)1.
No treatment is 100%
effective. Protocols combine safe and effective options with individual
risk/benefit analysis and monitoring.
Other treatments are more effective.
Cetylpyridinium Chloride may affect the natural microbiome, especially with prolonged use.
All data and sources to reproduce this analysis are in the appendix.
58th treatment shown effective in September 2025, now with p = 0.0035 from 4 studies.
Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
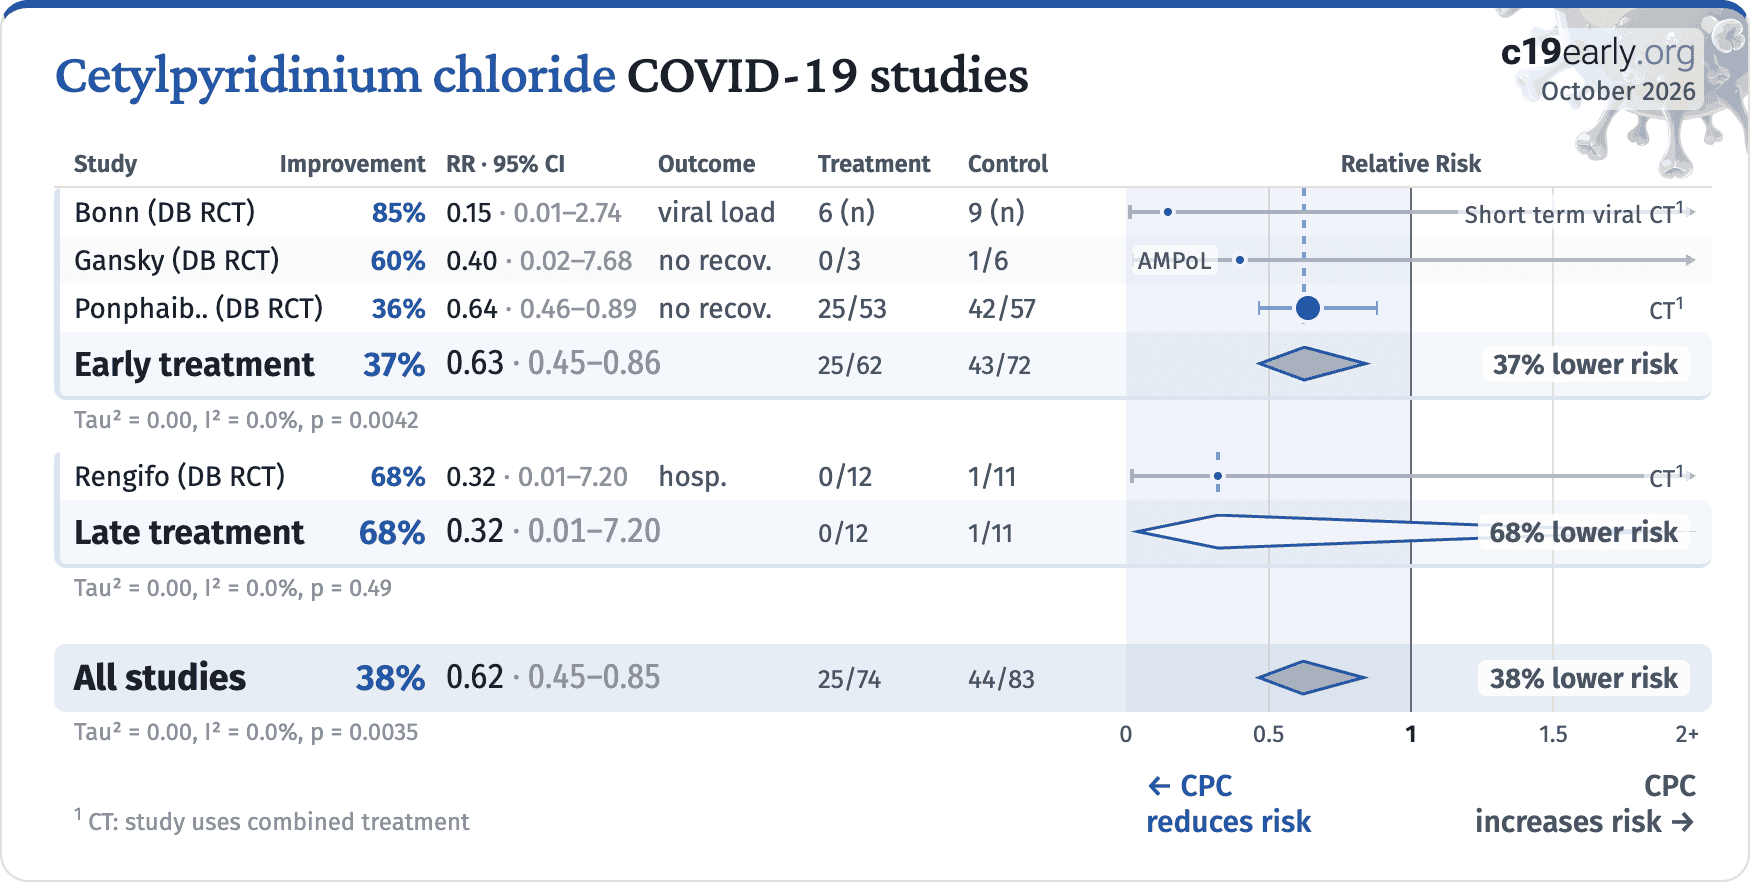
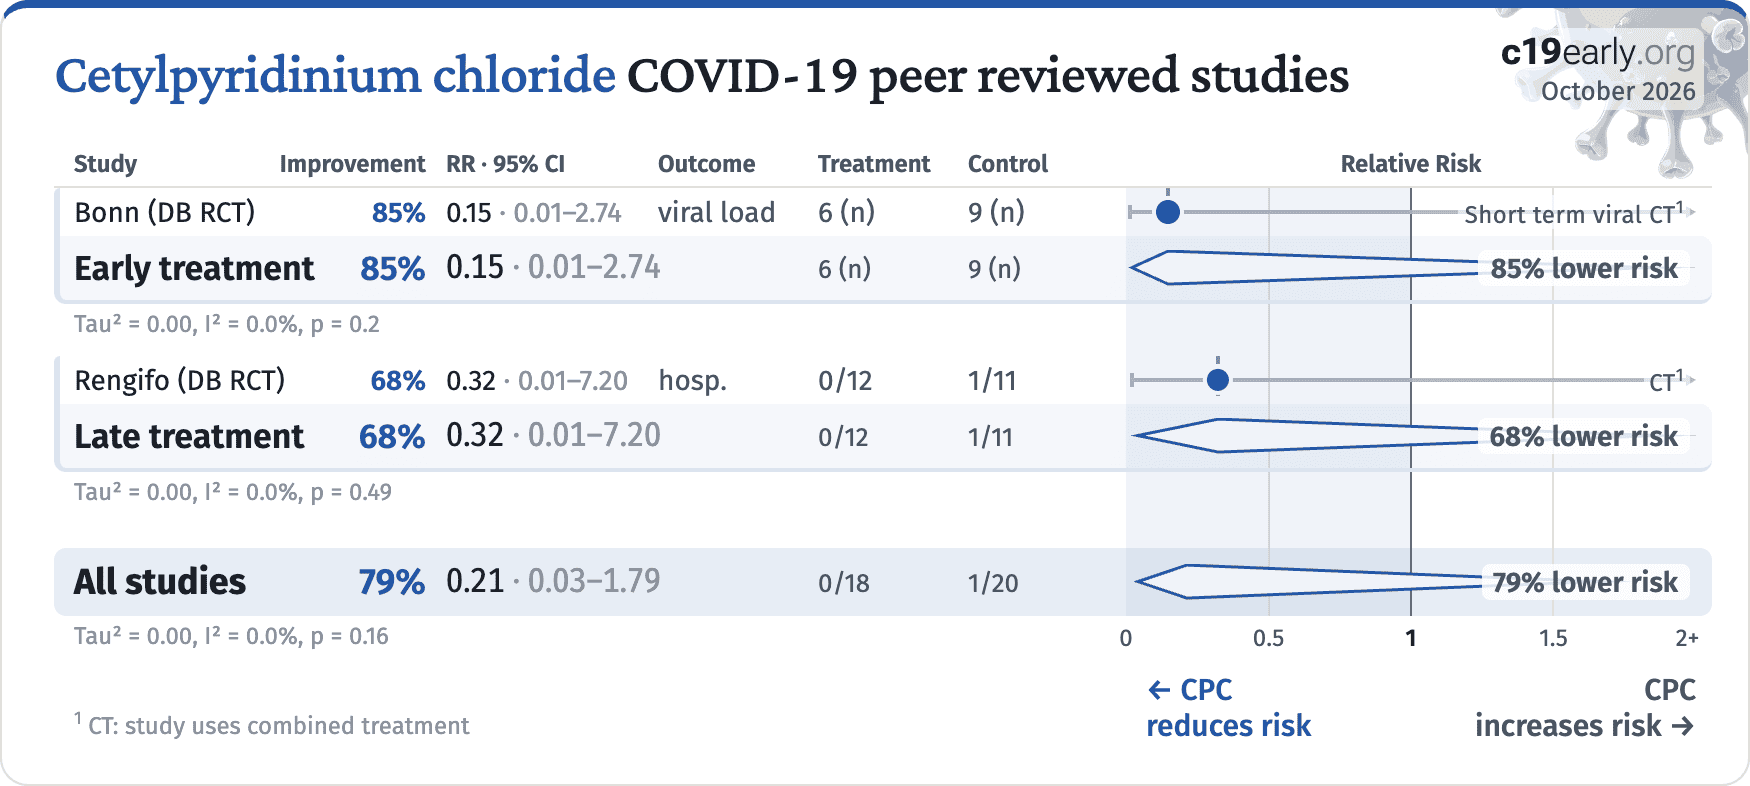
Late treatment68%0.32 · 0.01–7.200/121/1168% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.49
All studies38%0.62 · 0.45–0.8525/7444/8338% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.003500.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← CPC reduces riskCPC increases risk →
B
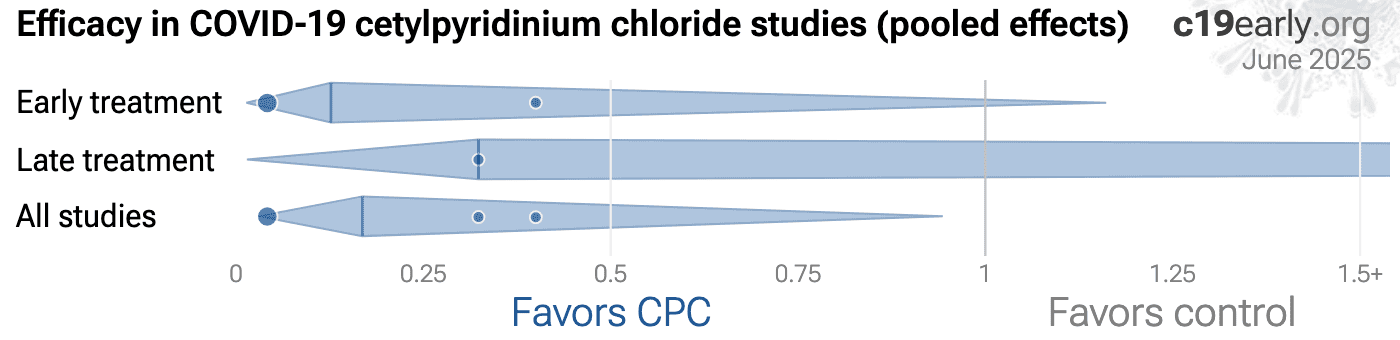
Fig. 1.A. Random-effects meta-analysis. This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
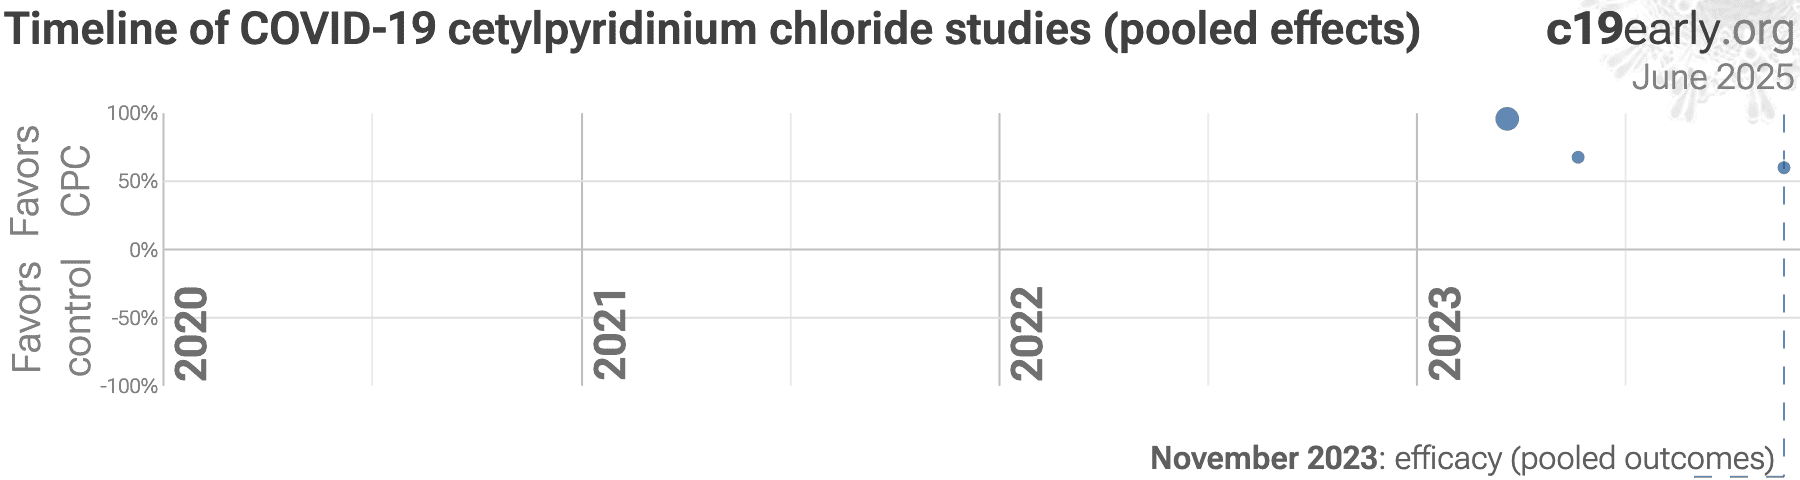
B. Timeline of results in cetylpyridinium chloride studies. The marked dates indicate the time when efficacy was known with a statistically significant improvement of ≥10% from ≥3 studies for pooled outcomes and pooled outcomes in RCTs.
SARS-CoV-2 infection typically starts in the upper respiratory
tract, and specifically the nasal respiratory epithelium. Entry via the eyes
and gastrointestinal tract is possible, but less common, and entry via other
routes is rare.
Infection may progress to the lower respiratory tract, other tissues, and the
nervous and cardiovascular systems. The primary initial route for entry into
the central nervous system is thought to be the olfactory nerve in the nasal
cavity3.
Progression may lead to cytokine storm, pneumonia, ARDS, neurological
injury4-20 and cognitive
deficits7,12, cardiovascular
complications21-27, DNA
damage28-31, organ failure, and death.
Even mild untreated infections may result in persistent cognitive
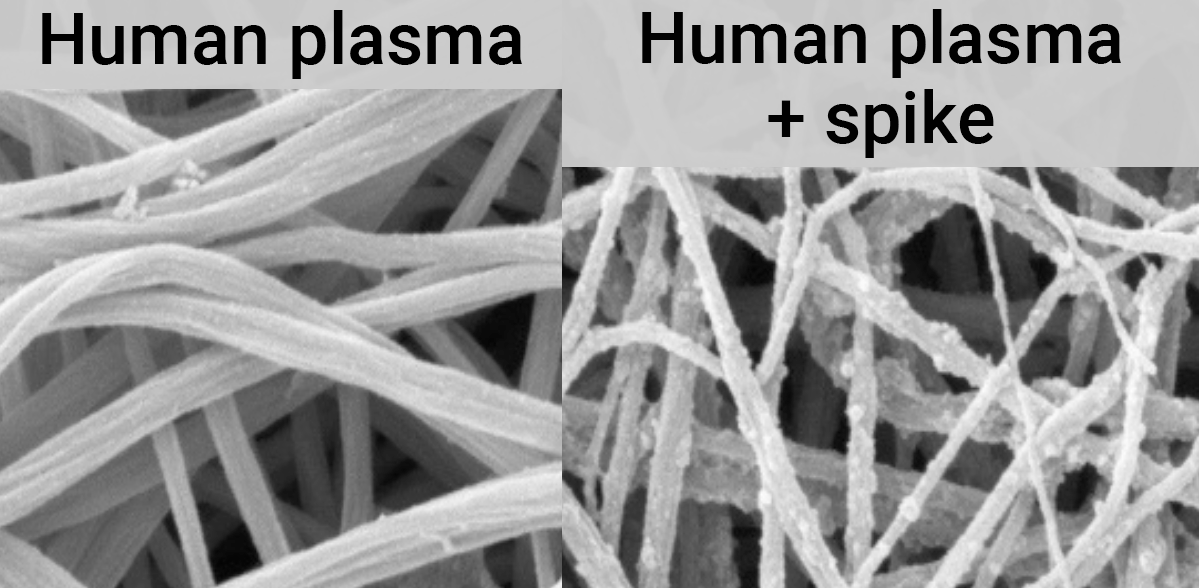
deficits32—the spike protein binds to fibrin leading to
fibrinolysis-resistant blood clots, thromboinflammation, and
neuropathology.
Systemic treatments may be insufficient to prevent
neurological damage11.
Minimizing replication as early as possible is recommended.
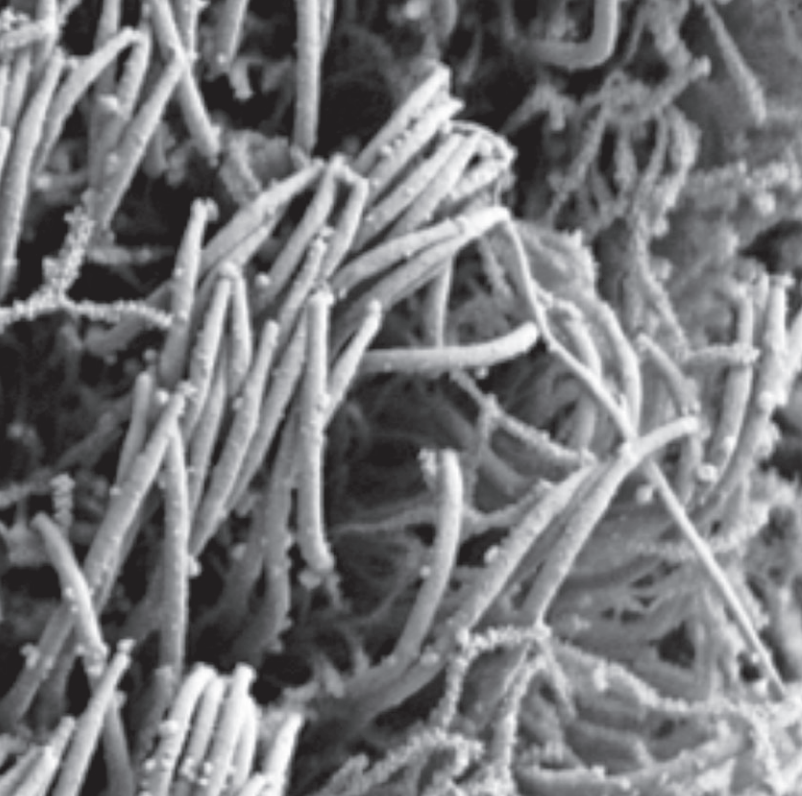
Fig. 3.
SARS-CoV-2 virions attached to cilia of nasal epithelial cells,
from Chien-Ting Wu33,34.
Logically, stopping replication in the upper respiratory tract should be
simpler and more effective.
Wu et al., using an airway organoid model incorporating many in
vivo aspects, show that SARS-CoV-2 initially attaches to cilia—hair-like
structures responsible for moving the mucus layer and where ACE2 is
localized in nasal epithelial cells35. The mucus layer and the
need for ciliary transport slow down infection, providing more time for
localized treatments33,34.
Early or prophylactic nasopharyngeal/oropharyngeal treatment may avoid the
consequences of viral replication in other tissues, and avoid the requirement
for systemic treatments with greater potential for side effects.
SARS-CoV-2 infection and replication involves the complex interplay of 500+
host and viral proteins and other factorsA,36-43, providing many
therapeutic targets for which many existing compounds have known activity.
Scientists have predicted that over 12,000 compounds may
reduce COVID-19 risk44, either by
directly minimizing infection or replication, by supporting immune system
function, or by minimizing secondary complications.
We analyze all significant
controlled studies of
cetylpyridinium chloride
for COVID-19.
Search methods, inclusion criteria, effect extraction criteria (more serious
outcomes have priority), all individual study data, PRISMA answers, and
statistical methods are detailed in Appendix 1. We present random-effects
meta-analysis results for all studies, studies within each treatment stage, individual outcomes, peer-reviewed studies, and Randomized Controlled Trials (RCTs).
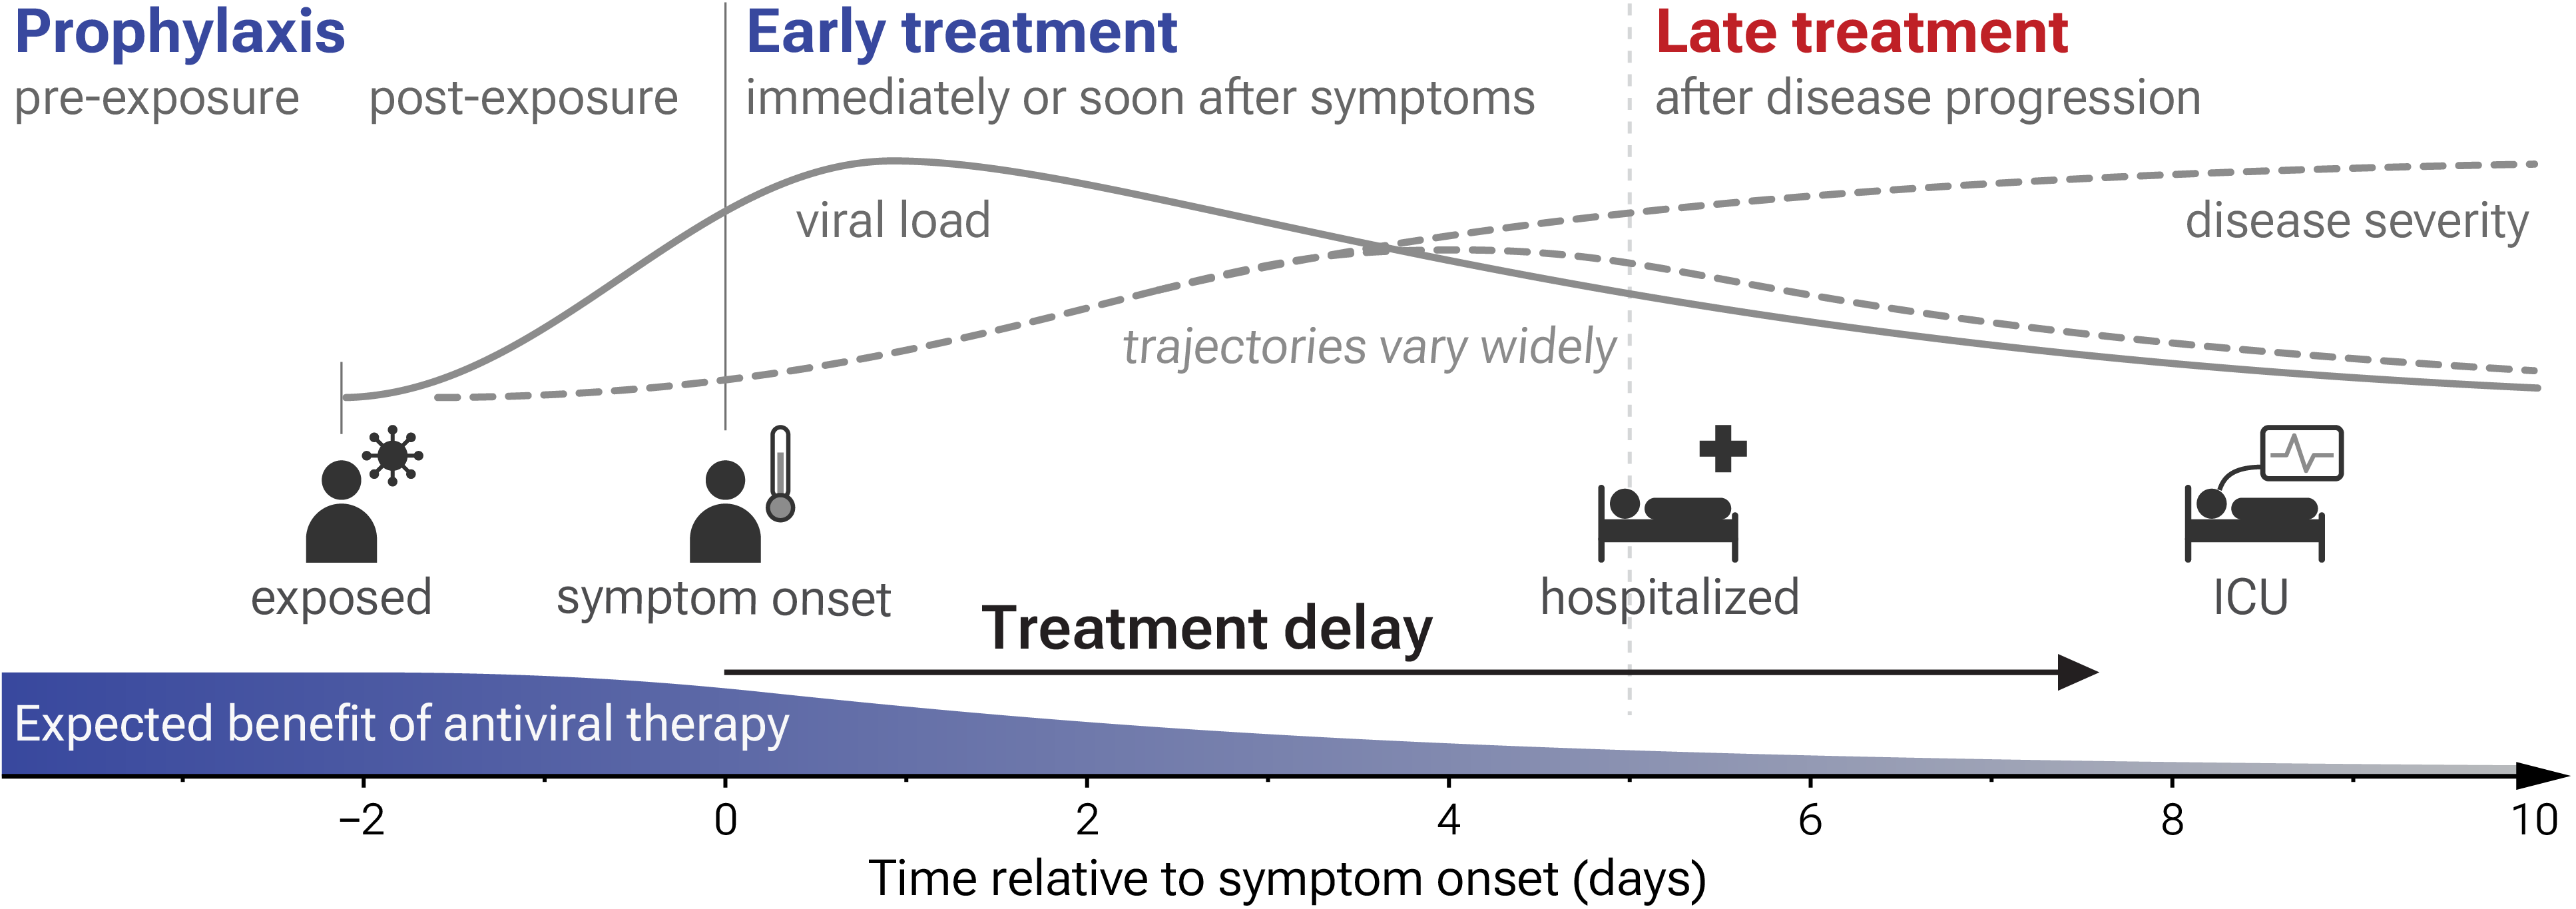
Fig. 4 shows stages of possible treatment for
COVID-19. Prophylaxis refers to regularly taking medication before
becoming sick, in order to prevent or minimize infection. Early
treatment refers to treatment immediately or soon after symptoms appear,
while late treatment refers to more delayed treatment.
2 in vitro studies support the efficacy of cetylpyridinium chloride54,55.
Preclinical research is an important part of the development of
treatments, however results may be very different in clinical trials.
Preclinical results are not used in this paper.
Table 1 summarizes the results for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, and for specific outcomes.
Table 2 shows results by treatment stage.
Fig. 5 plots individual results by treatment stage.
Fig. 6, 7, 8, 9, and 10
show forest plots for random-effects meta-analysis of
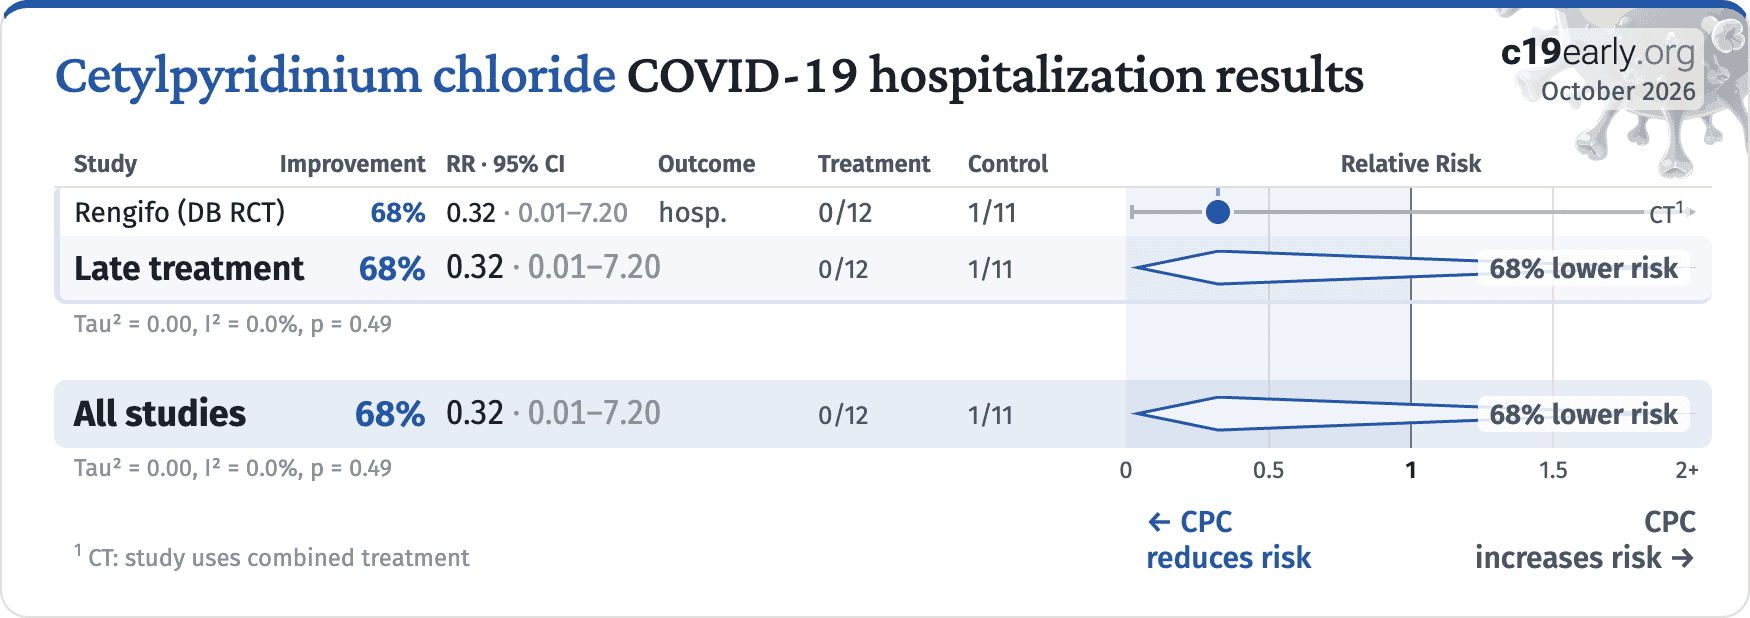
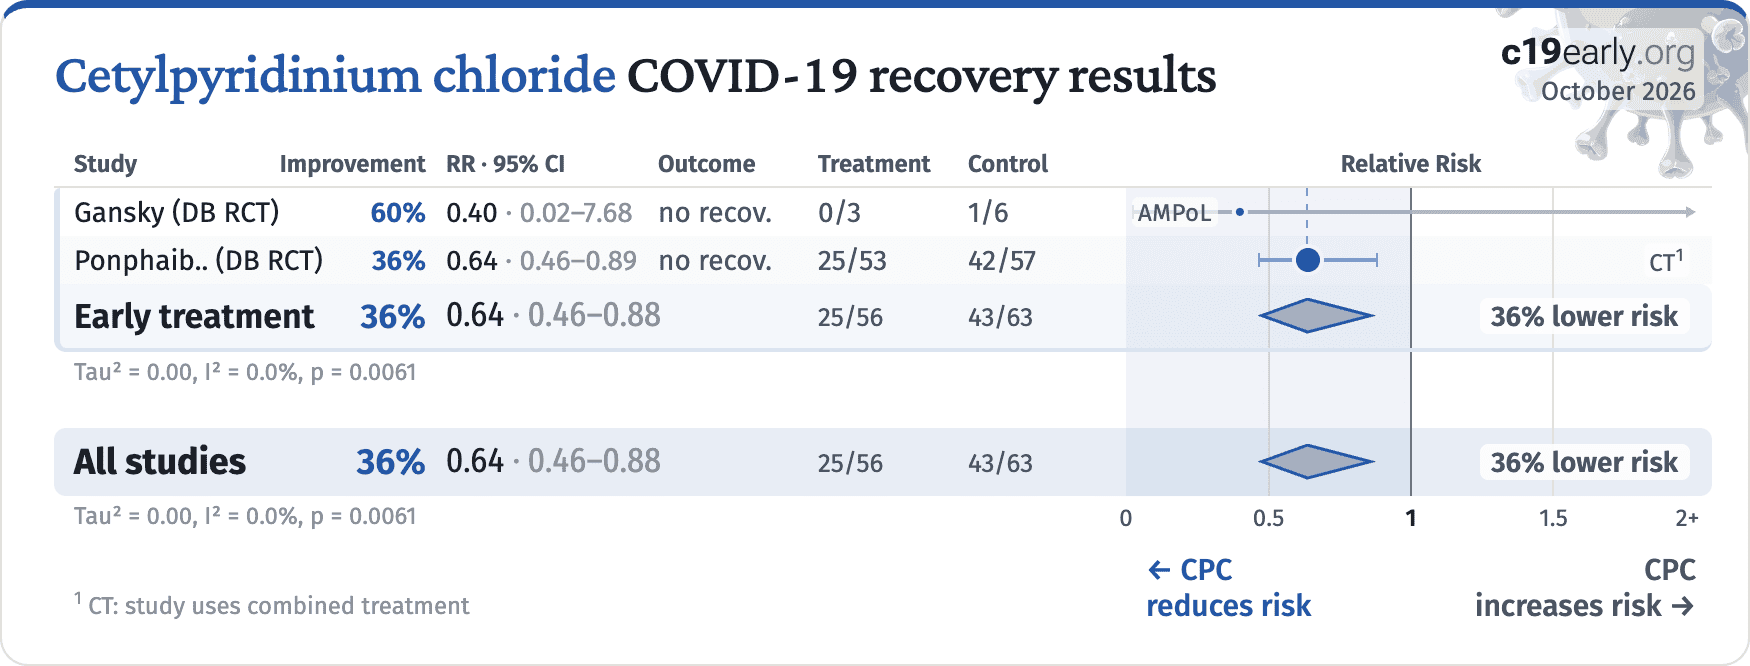
all studies with pooled effects, hospitalization, recovery, viral clearance, and peer reviewed studies.
Table 1. Random-effects meta-analysis for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, and for specific outcomes.
Results show the relative risk with treatment and the
95% confidence interval. **p<0.01.
Table 2. Random-effects meta-analysis results by treatment stage. Results show the relative risk with treatment and the 95% confidence interval.treatment and the 95%
confidence interval.**p<0.01.
Fig. 5. Scatter plot showing the most serious outcome in all studies, and for studies within each stage. Diamonds shows the results of random-effects meta-analysis.
Late treatment68%0.32 · 0.01–7.200/121/1168% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.49
All studies38%0.62 · 0.45–0.8525/7444/8338% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.003500.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← CPC reduces riskCPC increases risk →
Fig. 6. Random-effects meta-analysis for all studies.
This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
Late treatment68%0.32 · 0.01–7.200/121/1168% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.49
All studies79%0.21 · 0.03–1.790/181/2079% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.1600.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← CPC reduces riskCPC increases risk →
Fig. 10. Random-effects meta-analysis for peer reviewed studies.
Zeraatkar et al. analyze 356 COVID-19 trials, finding no significant
evidence that preprint results are inconsistent with peer-reviewed studies.
They also show extremely long peer-review delays, with a median of 6 months to
journal publication. A six month delay was equivalent to around 1.5 million
deaths during the first two years of the pandemic. Authors recommend using
preprint evidence, with appropriate checks for potential falsified data, which
provides higher certainty much earlier. Davidson et al. also showed no
important difference between meta-analysis results of preprints and
peer-reviewed publications for COVID-19, based on 37 meta-analyses including
114 trials.
Effect extraction is pre-specified, using the most serious outcome reported,
see the appendix for details.
Analysis validating pooled outcomes for
COVID-19 can be found below.
In addition to the dosage and frequency
of administration, efficacy for nasopharyngeal/oropharyngeal treatments may depend on
many other details. For example considering sprays, viscosity, mucoadhesion, sprayability,
droplet size58,59, dispersion59, and application
angle58 are important.
Akash et al. performed a computational fluid dynamics study
of nasal spray administration showing 100x improvement in nasopharyngeal drug
delivery using a new spray placement protocol, which involves holding the spay
nozzle close to horizontal at the nostril, with a slight tilt towards
the cheeks. The study also found the optimal droplet size range for
nasopharyngeal deposition was ~7-17µm.
1 cetylpyridinium chloride
RCT has not reported results1.
The trial reports
report an estimated total of 90 patients.
The result is delayed over 4 years.
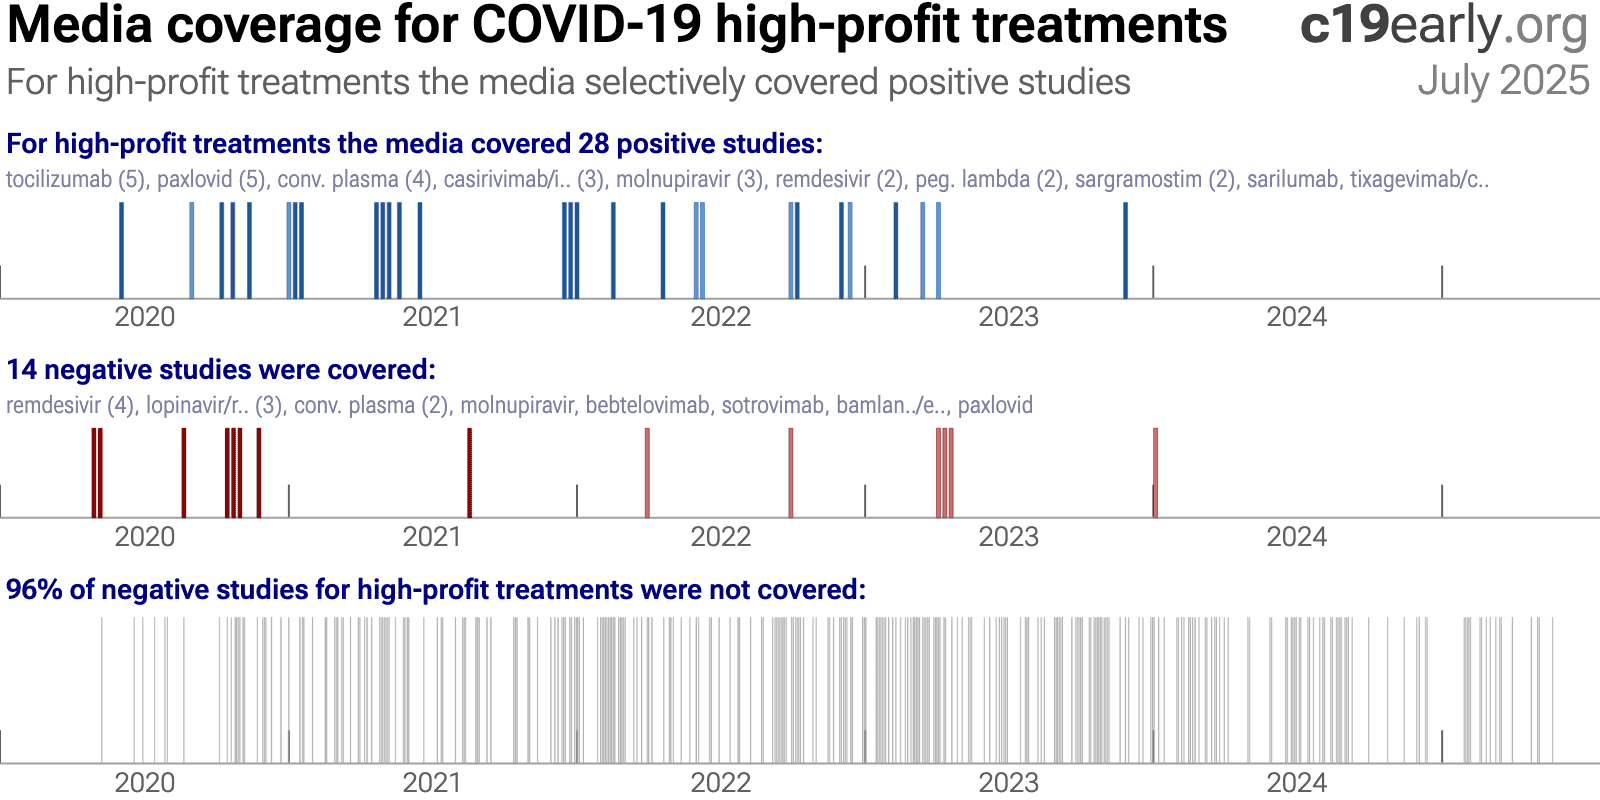
Low-cost treatments were subject to bias and censorship during the pandemic.
Scientific bias is seen in the design, analysis, presentation, and selective
reporting of studies, which often favored negative results. A similar bias is seen in the media
coverage for low-cost treatments.
While broadly seen, bias was particularly notable for ivermectin and hydroxychloroquine, e.g., Scott Alexander noted that "if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."47.
We analyze media coverage for the 227 treatments we cover using
Altmetric60, which reports the number of ~12,000 tracked news outlets that covered each study61. Studies are considered to have received significant media coverage if they were covered by at least 0.5% of the tracked news outlets.
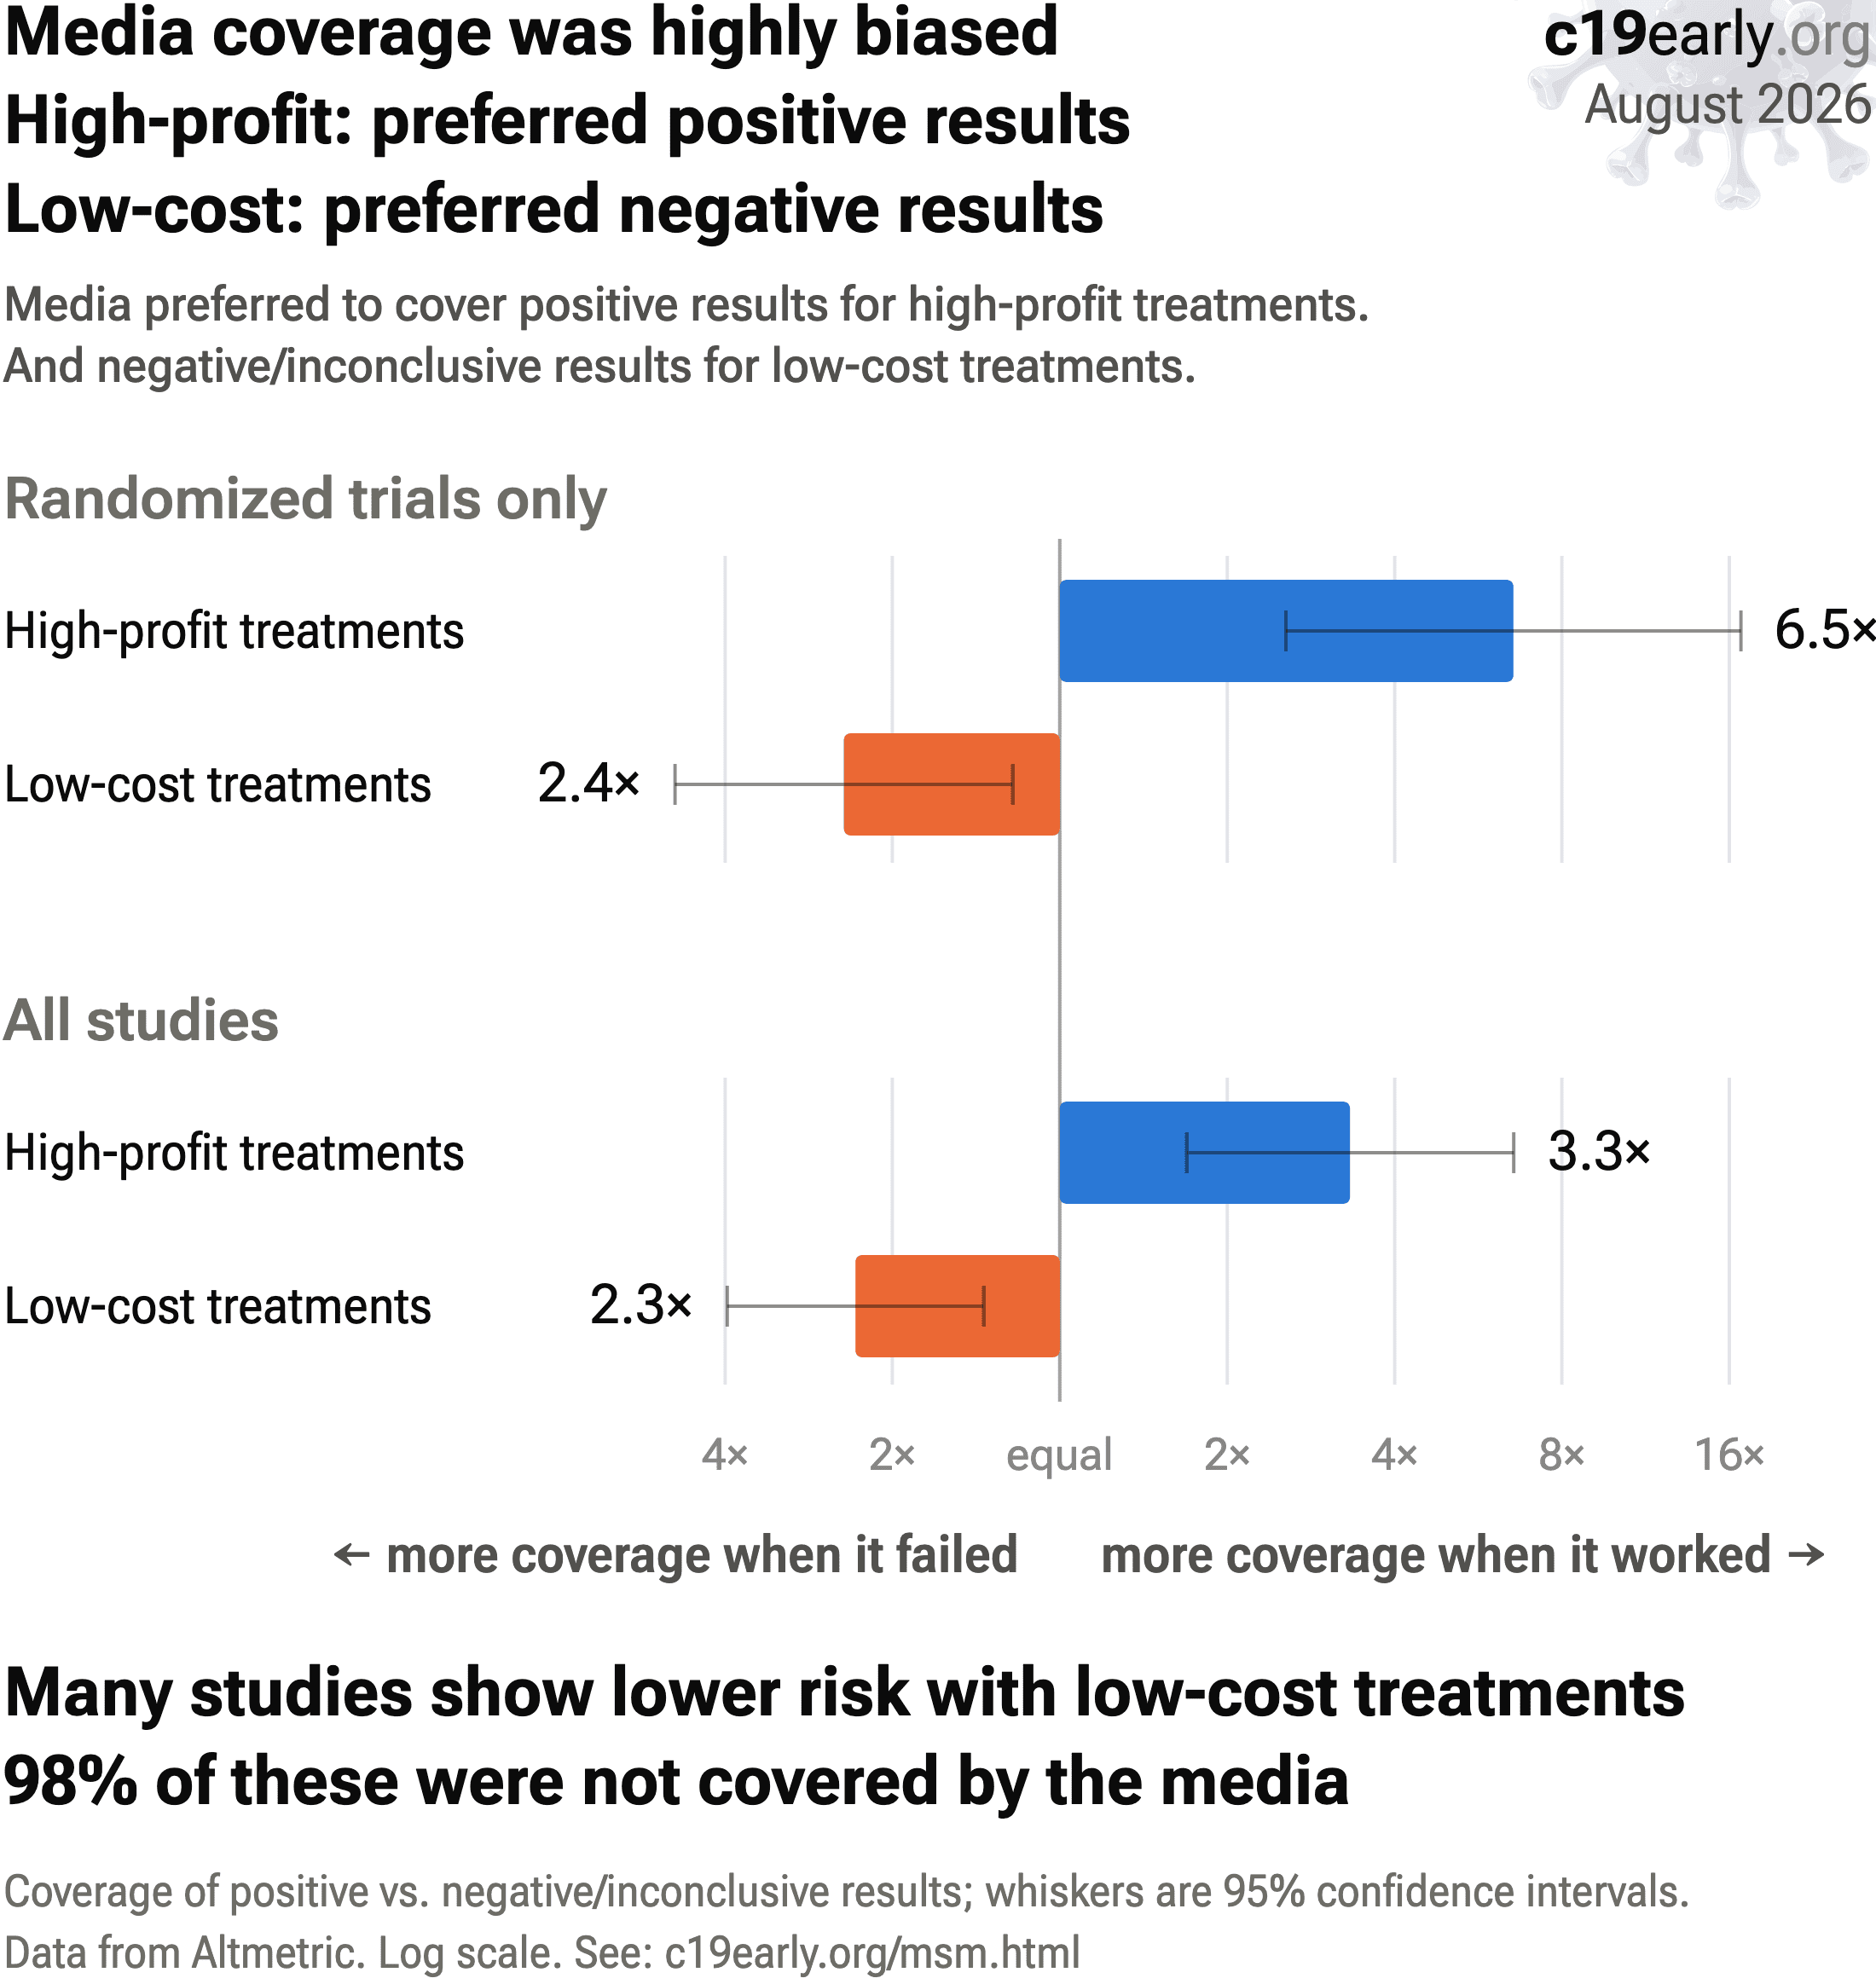
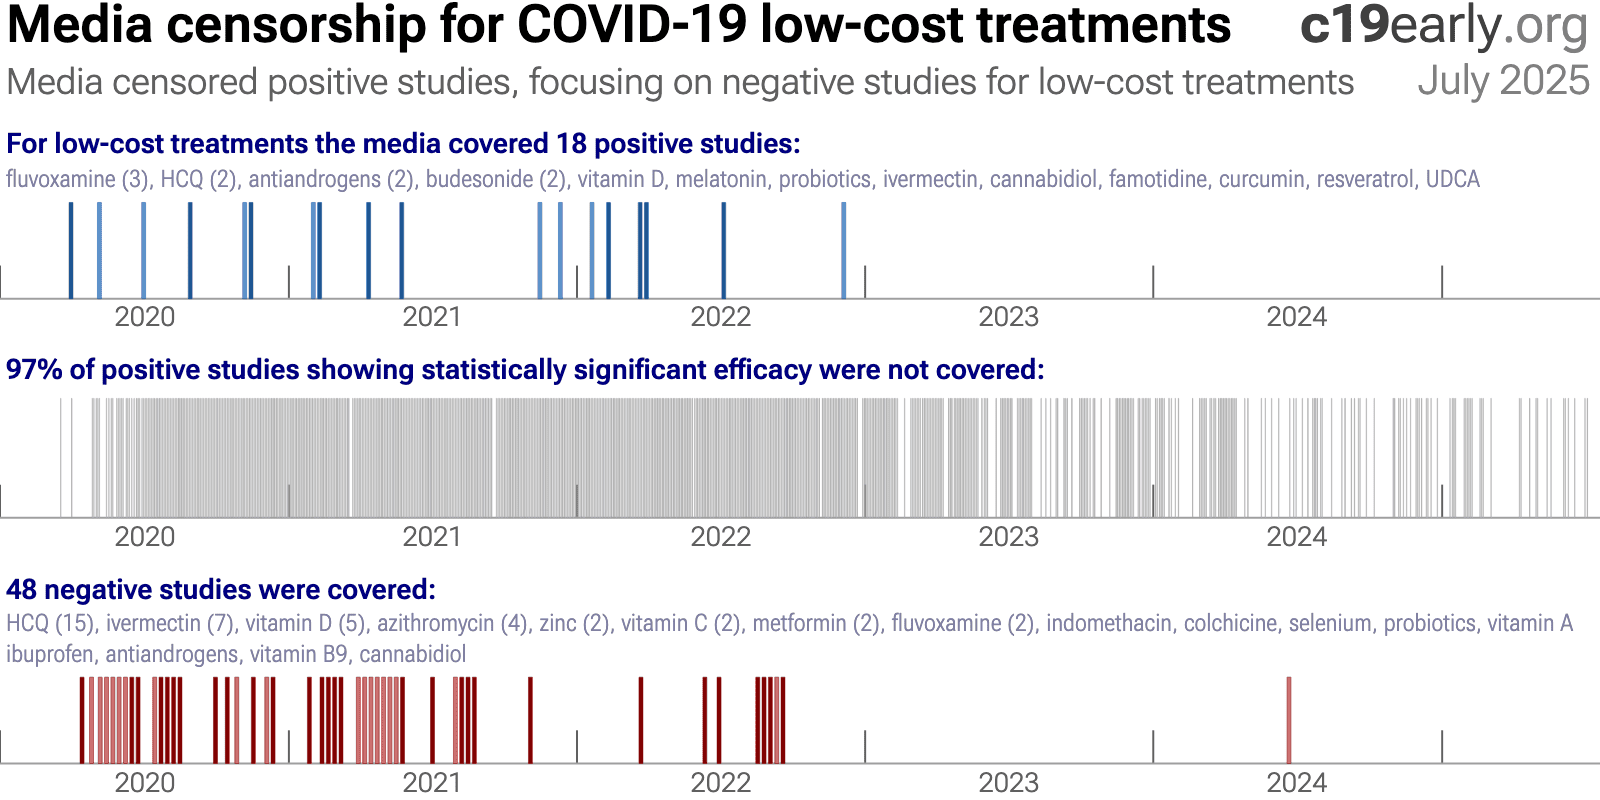
Fig. 12, 13, and 14 show the bias toward negative results for low-cost treatments, in contrast to the opposite bias for high-profit treatments.
This may result in widespread incorrect perceptions on the relative efficacy of high-profit and low-cost treatments. The impact is significant—increased cost limits the use of high-profit
treatments and treatment equity, and high-profit treatments were also more difficult to access, especially for earlier treatment which improves efficacy and minimizes community transmission.
Loading..
Fig. 12. Media was more likely to cover negative or inconclusive results for low-cost treatments, and positive results for high-profit treatments.
Loading..
Loading..
Fig. 13. Mainstream media was biased against positive results for low-cost treatments.
Loading..
Loading..
Fig. 14. In contrast to the results for low-cost treatments, mainstream media was biased towards positive results for high-cost treatments.
A combination of factors may have led to the media's suppression of low-cost treatments:
•
Politicization
led to a media environment where coverage was often framed to support a political
narrative rather than to provide objective scientific information. As Scott Alexander
said:
"if you say anything in favor of ivermectin you will be cast out
of civilization and thrown into the circle of social hell reserved for Klan members and
1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!'
at you and compare you to Josef Mengele."
There was strong social pressure to
discredit low-cost treatments.
•
Censorship
of
information conflicting with selected authorities. For example, individuals and
organizations presenting conflicting science were often banned on Twitter and
YouTube.
•
FDA requires "no
adequate, approved, and available alternatives"
in order to grant an EUA for
novel high-profit interventions, creating a strong incentive for authorities to ignore or
downplay existing low-cost treatments.
•
Regulatory
capture
biases authorities towards high-profit interventions.
•
Authorities ignored
most evidence for low-cost treatments
, for example the NIH references only 2% of
studies in delayed, rarely-updated, biased commentaries with no quantitive analysis.
•
Media coverage of
science is often not very accurate
, e.g., misunderstanding confounding issues. For
example the media widely considered the RECOVERY HCQ RCT to be conclusive on efficacy, but
very late treatment of late stage patients (mostly on oxygen already) with an excessive
toxic dose (shown dangerous in a dose comparison RCT) provides no information on the
recommended early/prophylactic treatment. With difficulting in understanding basic
confounders like treatment delay and dose, the media may favor deferring to authorities.
Many studies for low-cost treatments require greater expertise to analyze. Relatively few
journalists have a strong ability to analyze clinical trials and are outnumbered by the
rest.
•
Substantial funding
from pharmaceutical advertising
biases editorial decisions towards high-profit
interventions.
•
PR power
-
companies/teams with strong PR presence are favored in the media, which correlates with
high-profit and high conflict of interest studies.
•
The media was very
negative in general
, inflating risk, fear, and anxieties. A negative bias may
improve ratings and revenue, increasing motivation to continue watching coverage. A
combination of low-cost treatments greatly reducing risk conflicts with the negative
narrative.
25 low-cost treatments were approved in one
or more countries, yet many countries approved no low-cost treatments.
The countries that did adopt low-cost treatments analyzed the evidence early and made
timely approvals. With few exceptions, authorities did not change their initial views,
regardless of how much evidence accumulated showing either efficacy or harm. Why?
The harms of smoking here hidden for 25 yearsC. Authorities did not analyze the data in real-time, failing to act when
harm was known.
Widespread acknowledgement of harm came only after attempts by two new surgeon generals,
along with pressure from health advocates and a new president, and a review of 7,000 studies.
Similarly for COVID-19, most authorities and experts did not proactively
analyze data in real-time. This guarantees delayed recognition of efficacy or harm, by
which time moral, legal, career, and reputational liabilities strongly disincentivize any
admission of error. Claims of no efficacy (for effective treatments) or safety (for
harmful treatments) were often made prior to strong data being available. Correction
would require admitting to errors that increased mortality, which is unlikely with the
same generation of officials.
Analysis of potential treatments was rarely done, and when done these were
typically minimal efforts.
For example, NIH reviews were highly delayed, cover only a tiny fraction of treatments,
reference only 2% of studies for the treatments covered, and include no
quantitative analysis.
They appear as rarely updated side projects from
external panels implicitly tasked with justifying prior failures.
As with smoking, the thousands of studies could (and should)
have been analyzed and acted on in real-time.
A key structural improvement, applicable to all current and future
diseases, is for authorities to implement real-time proactive analysis of clinical
evidence. This does not remove all bias, but does make it possible to act on evidence,
whereas delayed action may be unlikely due to moral, legal, career, and reputational
liabilities.
c19early.org
Delayed public health acknowledgments
Official acknowledgment of efficacy or harm is often delayed—legal, career, and status risks disincentivize admission of error.
Evidence
Official Acknowledgment
Approx. Delay
Citrus Fruit (vitamin C) for Scurvy (effectiveness)
1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors.
1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease.
48 years
Handwashing (lower mortality)
1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%.
~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death).
~20+ years
Helicobacter pylori (bacteria causes ulcers)
1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food.
1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy.
~12 years
Asbestos (causes asbestosis & cancer)
1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers.
1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it.
~47 years
Leaded Gasoline (neurotoxicity)
~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning.
1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996.
~49 years
Harms of Smoking (causes lung cancer)
1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s.
1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease.
The time between infection or the onset of symptoms and
treatment may critically affect how well a treatment works. For example an
antiviral may be very effective when used early but may not be effective in
late stage disease, and may even be harmful. Oseltamivir, for example, is
generally only considered effective for influenza when used within 0-36 or
0-48 hours62,63. Baloxavir marboxil studies for influenza
also show that treatment delay is critical — Ikematsu et al. report
an 86% reduction in cases for post-exposure prophylaxis, Hayden et al.
show a 33 hour reduction in the time to alleviation of symptoms for treatment
within 24 hours and a reduction of 13 hours for treatment within 24-48 hours,
and Kumar et al. report only 2.5 hours improvement for inpatient
treatment.
Table 3. Studies of baloxavir marboxil for influenza
show that early treatment is more effective.
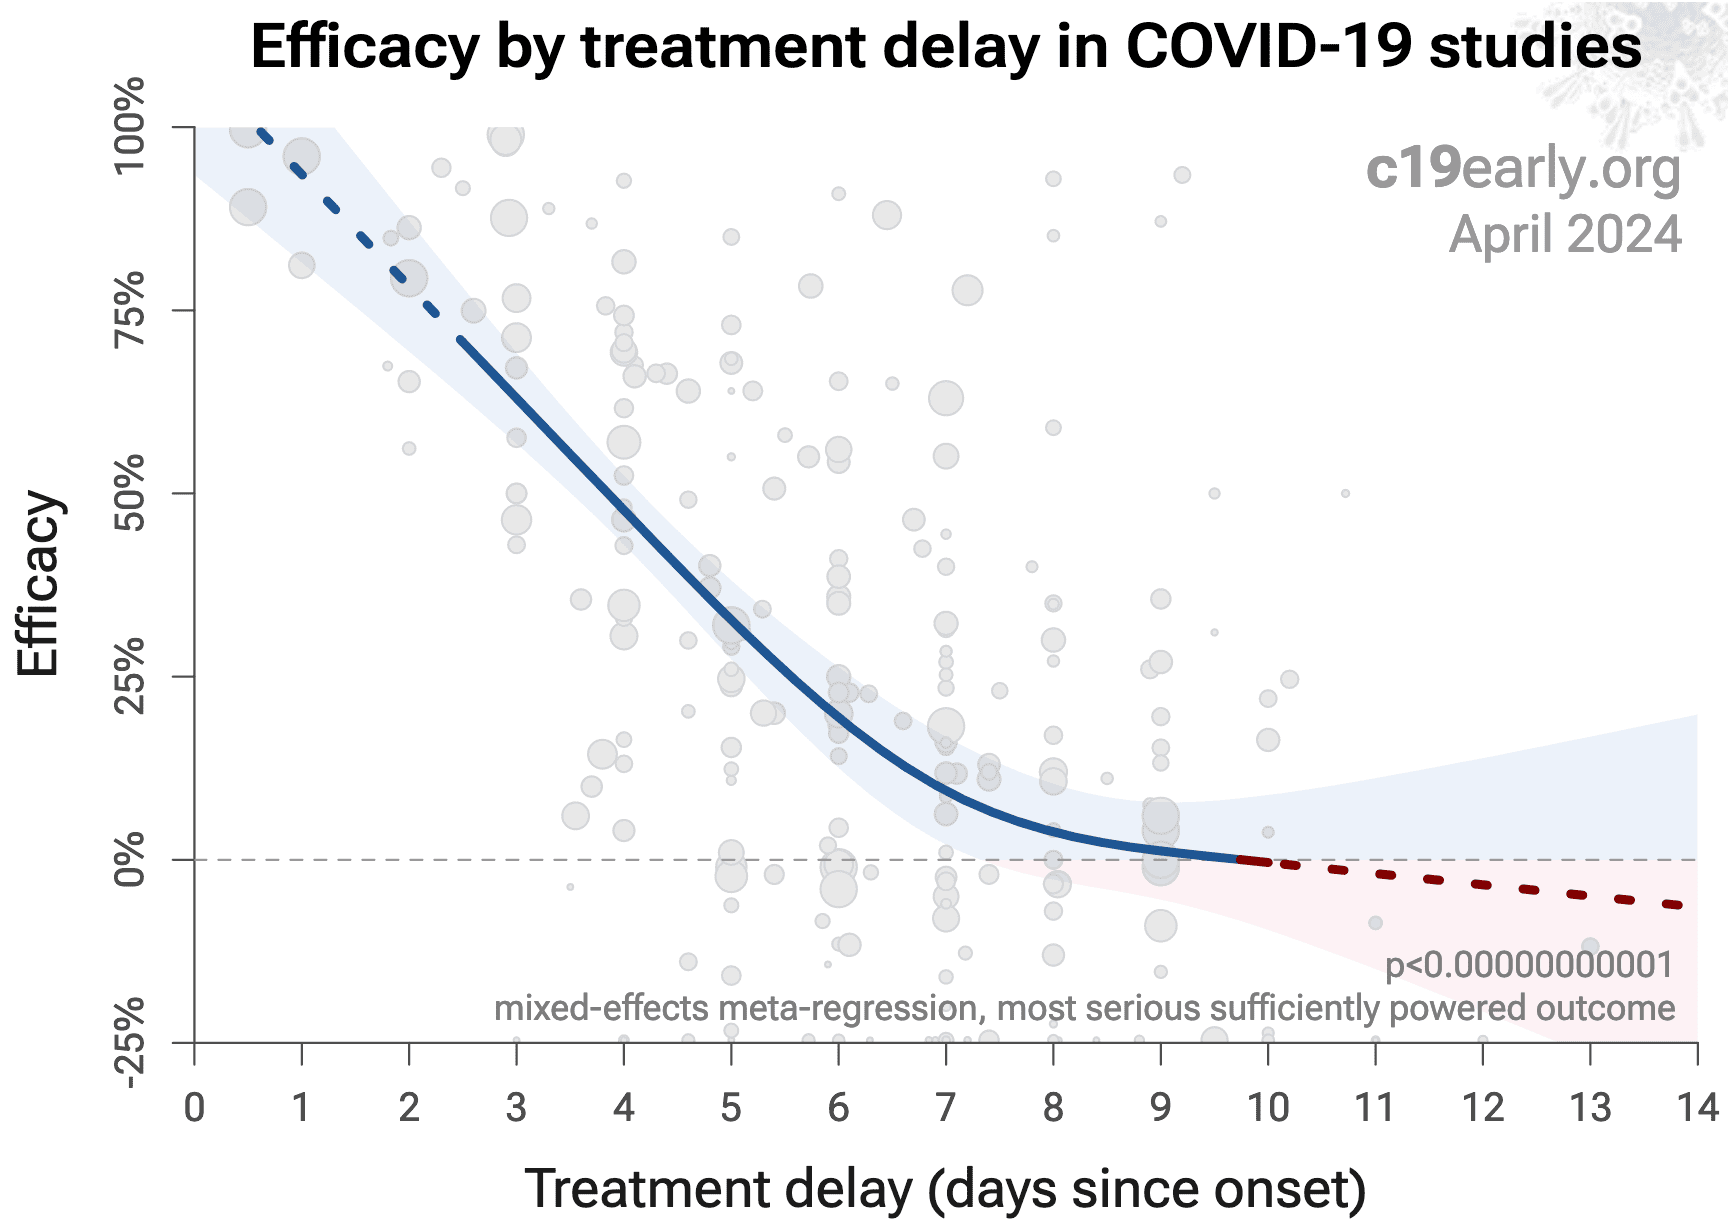
Fig. 15 shows a mixed-effects meta-regression for
efficacy as a function of treatment delay in COVID-19 studies from 227 treatments, showing that efficacy
declines rapidly with treatment delay. Early treatment is critical for COVID-19.
Loading..
Fig. 15. Early treatment is more effective. Meta-regression showing efficacy as a function of treatment delay in COVID-19 studies from 227 treatments.
Details of the patient population including age and comorbidities may
critically affect how well a treatment works. For example, many COVID-19
studies with relatively young low-comorbidity patients show all patients
recovering quickly with or without treatment. In such cases, there is little
room for an effective treatment to improve results, for example as in
López-Medina et al.
Efficacy may depend critically on the distribution of
SARS-CoV-2 variants encountered by patients. Risk varies significantly across
variants68, for example the Gamma variant shows significantly
different characteristics69-72. Different
mechanisms of action may be more or less effective depending on variants, for
example the degree to which TMPRSS2 contributes to viral entry can differ
across variants73,74.
The quality of medications may vary significantly between
manufacturers and production batches, which may significantly affect efficacy
and safety. Williams et al. analyze ivermectin from 11 different sources,
showing highly variable antiparasitic efficacy across different manufacturers.
Xu et al. analyze a treatment from two different manufacturers, showing 9
different impurities, with significantly different concentrations for each
manufacturer.
The use
of other treatments may significantly affect outcomes, including supplements,
other medications, or other interventions such as prone positioning.
Treatments may be synergistic77-101, therefore
efficacy may depend strongly on combined treatments.
Across all
studies there is a strong association between different outcomes, for example
improved recovery is strongly associated with lower mortality. However,
efficacy may differ depending on the effect measured, for example a treatment
may be more effective against secondary complications and have minimal effect
on viral clearance.
The
distribution of studies will alter the outcome of a meta-analysis. Consider a
simplified example where everything is equal except for the treatment delay,
and effectiveness decreases to zero or below with increasing delay. If there
are many studies using very late treatment, the outcome may be negative, even
though early treatment is very effective.
All meta-analyses combine heterogeneous studies, varying in population,
variants, and potentially all factors above, and therefore may obscure
efficacy by including studies where treatment is less effective. Generally, we
expect the estimated effect size from meta-analysis to be less than that for
the optimal case.
Looking at all studies is valuable for providing an overview of all research,
important to avoid cherry-picking, and informative when a positive result is
found despite combining less-optimal situations. However, the resulting
estimate does not apply to specific cases such as
early treatment in high-risk populations.
While we present results for all studies, we also present treatment time and
individual outcome analyses, which may be more informative for specific use
cases.
For COVID-19, delay in clinical results translates into
additional death and morbidity, as well as additional economic and societal
damage. Combining the results of studies reporting different outcomes is
required.
There may be no mortality in a trial with low-risk patients,
however a reduction in severity or improved viral clearance may translate
into lower mortality in a high-risk population.
Different studies may report lower severity, improved recovery, and lower mortality,
and the significance may be very high when combining the results.
"The studies reported different outcomes" is not a good reason for
disregarding results.
Pooling the results of studies reporting different outcomes allows us to use
more of the available information. Logically we should, and do, use additional
information when evaluating treatments—for example dose-response and
treatment delay-response relationships provide additional evidence of efficacy
that is considered when reviewing the evidence for a treatment.
We present both specific outcome and pooled analyses.
In order to combine the results of studies reporting different outcomes we use
the most serious outcome reported in each study, based on the thesis that
improvement in the most serious outcome provides comparable measures of
efficacy for a treatment. A critical advantage of this approach is
simplicity and transparency.
There are many other ways to combine evidence for different outcomes, along
with additional evidence such as dose-response relationships, however these
increase complexity.
Trials with high-risk patients may be restricted due to ethics for treatments
that are known or expected to be effective, and they increase difficulty for
recruiting. Using less severe outcomes as a proxy for more serious outcomes
allows faster and safer collection of evidence.
For many COVID-19 treatments, a reduction in mortality logically
follows from a reduction in hospitalization, which follows from a reduction in
symptomatic cases, which follows from a reduction in PCR positivity. We can
directly test this for COVID-19.
Analysis of the the association between different outcomes across studies from
all 227
treatments we cover confirms the validity of pooled outcome analysis for COVID-19.
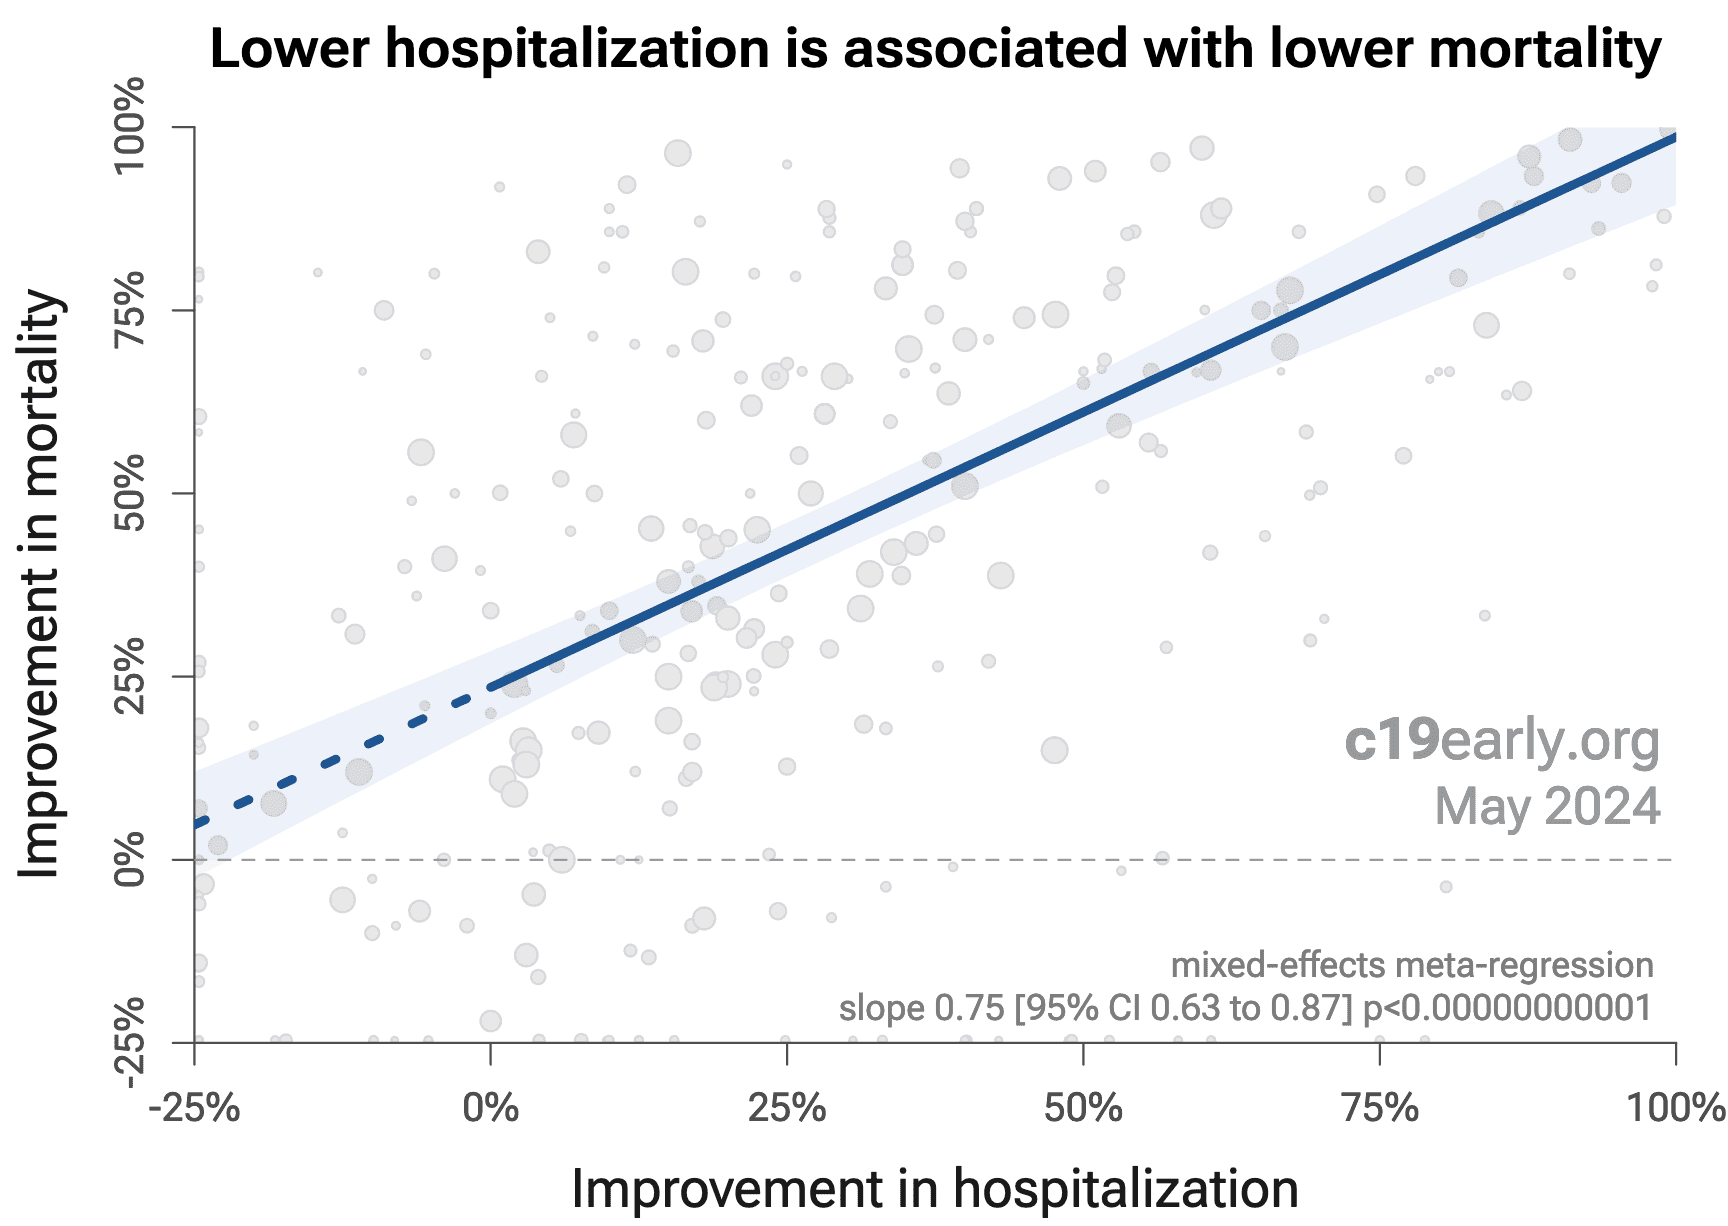
Fig. 16 shows that lower hospitalization is very strongly associated
with lower mortality (p < 0.0000000001).
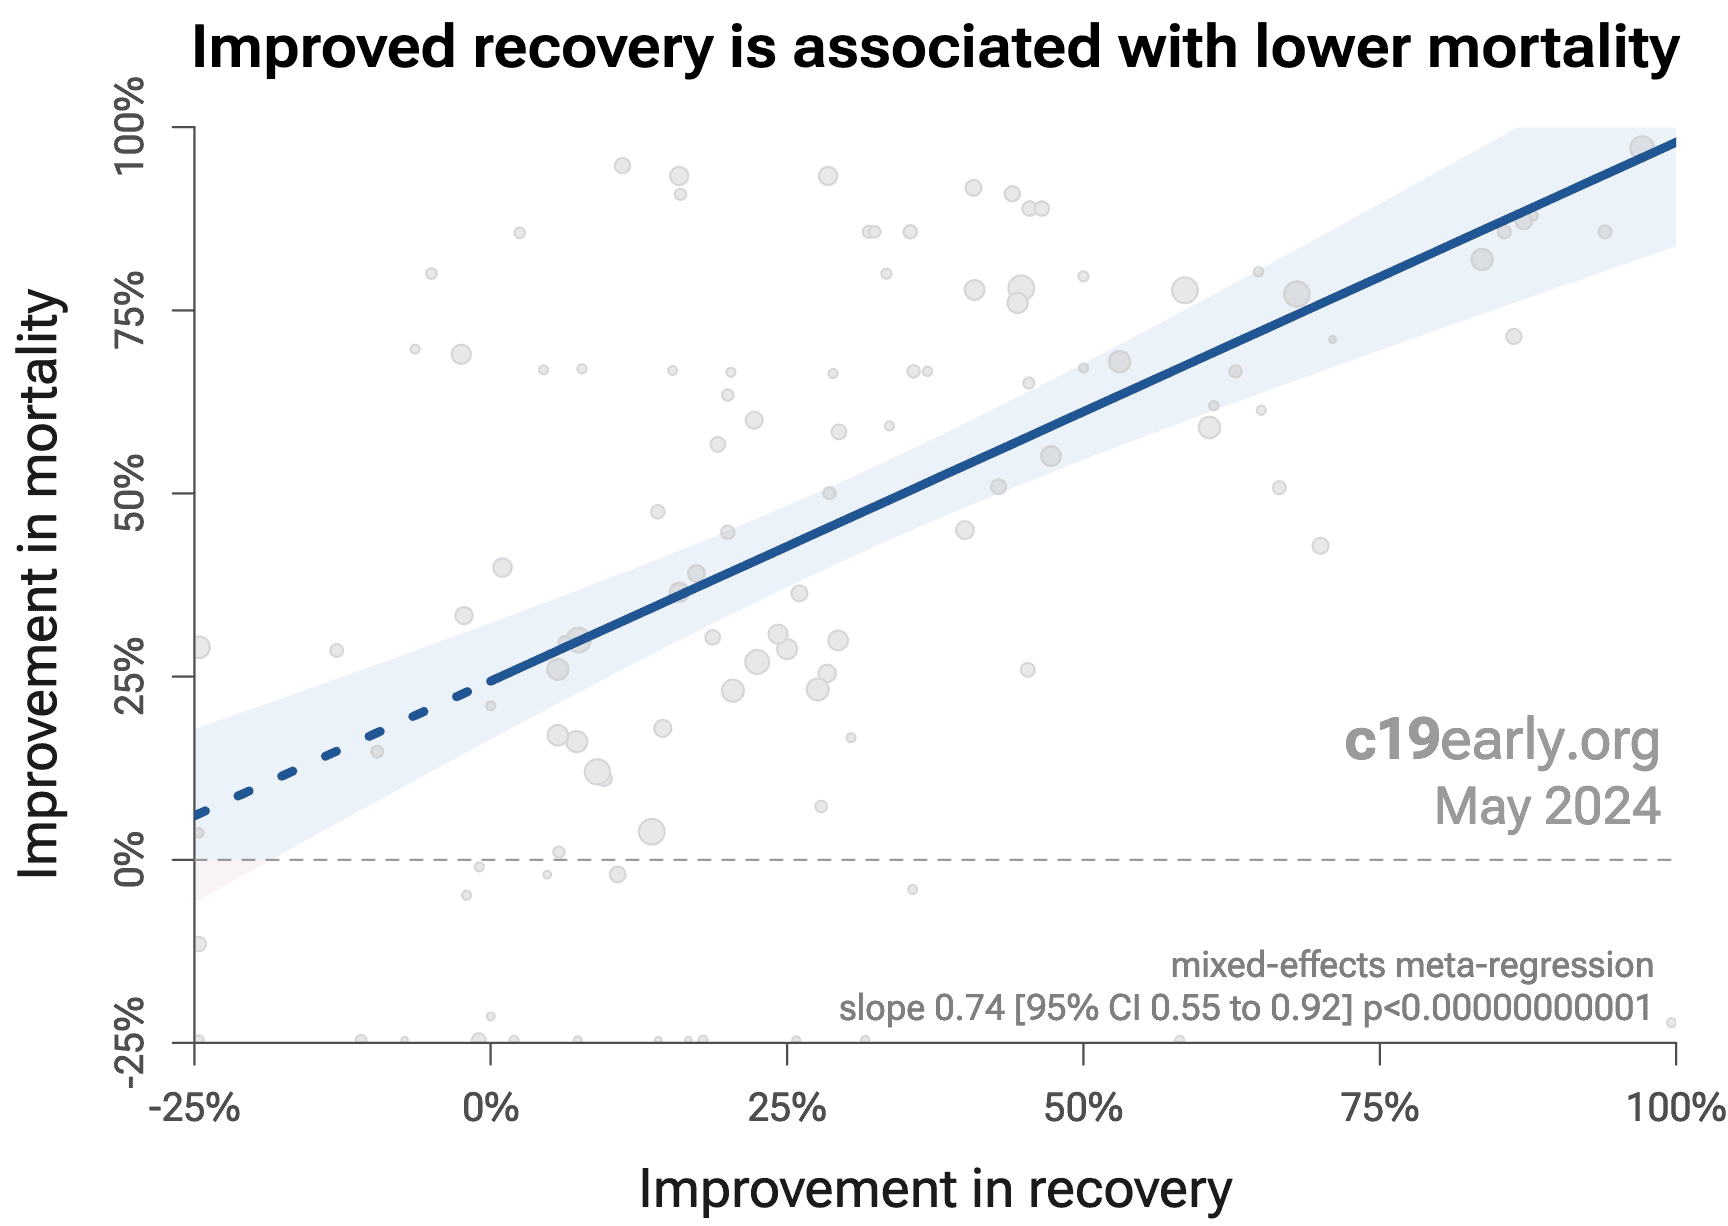
Similarly, Fig. 17 shows that improved recovery is very strongly associated
with lower mortality (p < 0.0000000001).
Considering the extremes, Singh et al. show an association between viral clearance and
hospitalization or death, with p = 0.003 after excluding one large
outlier from a mutagenic treatment, and based on 44 RCTs including 52,384
patients.
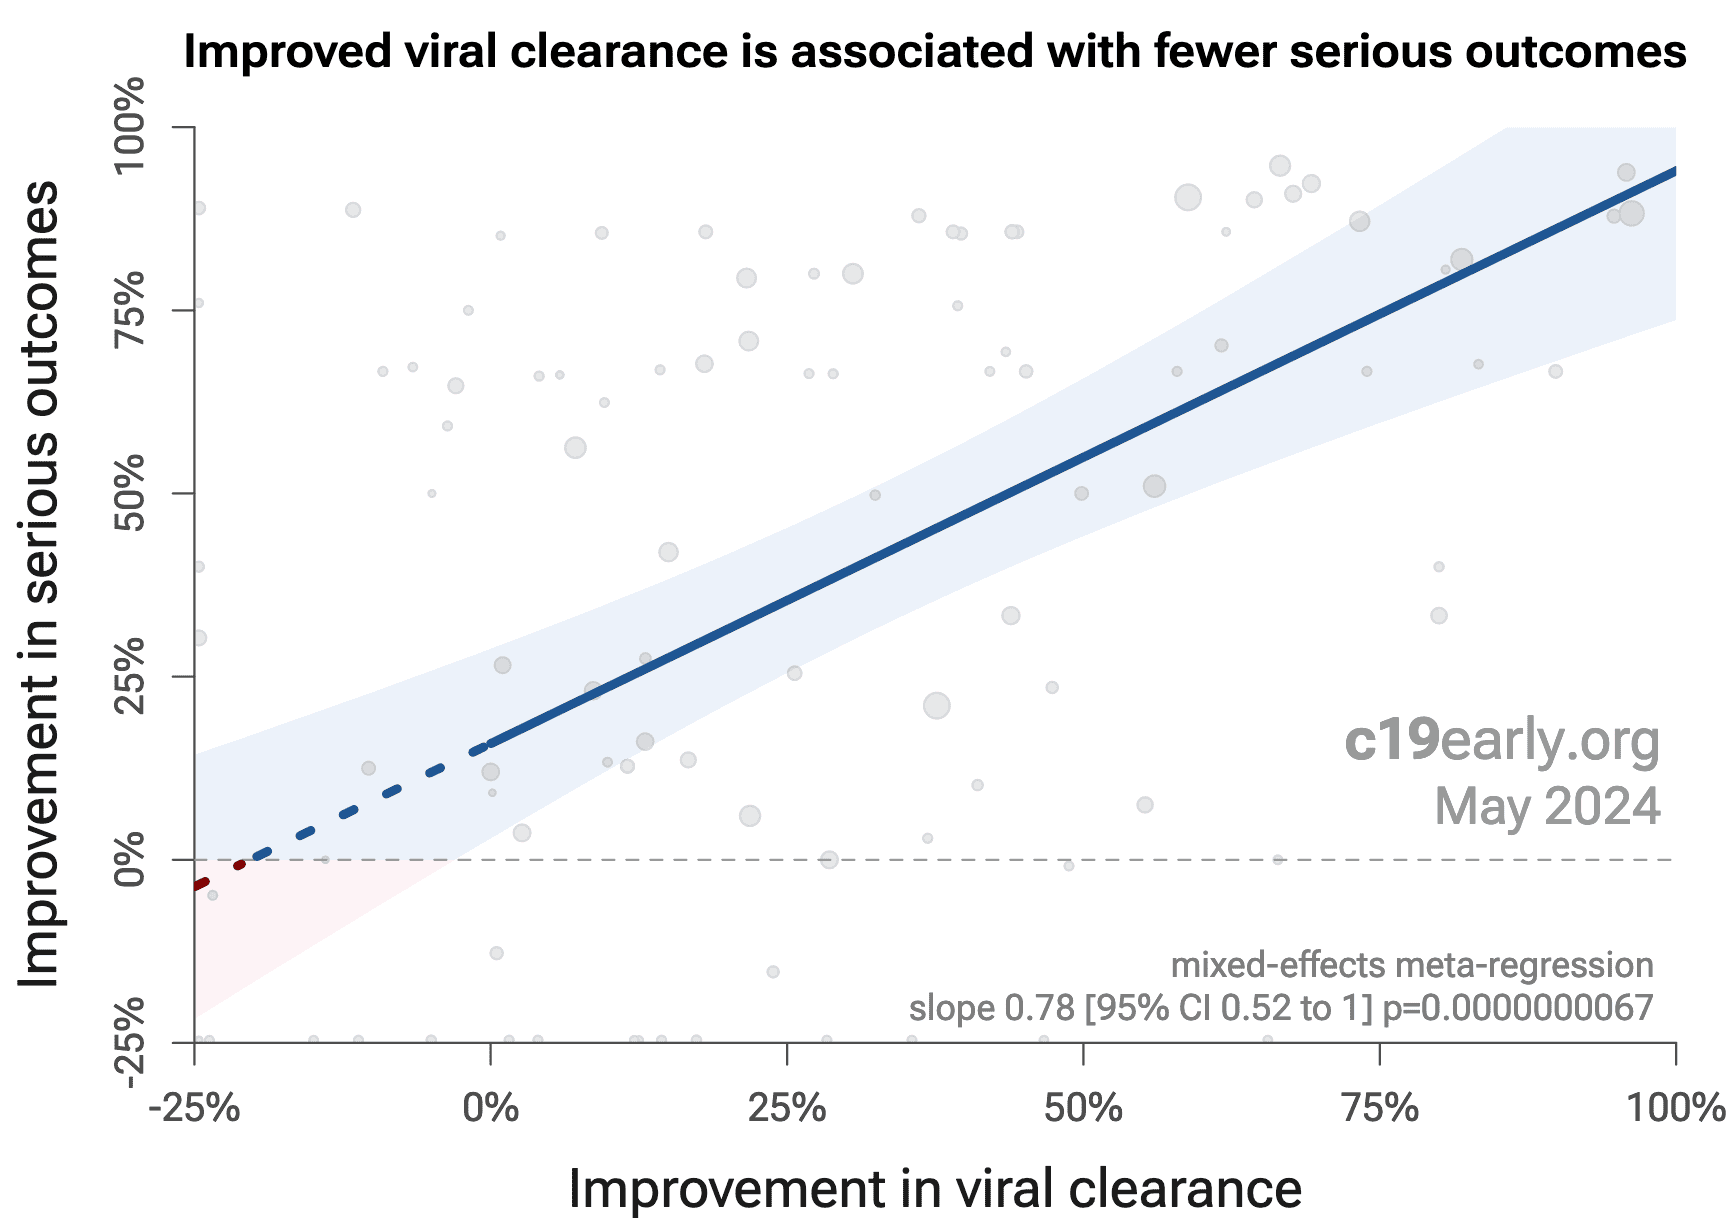
Fig. 18 shows that improved viral clearance is strongly associated
with fewer serious outcomes. The association is very similar to
Singh et al., with higher confidence due to the larger number of
studies. As with Singh et al., the confidence increases
when excluding the outlier treatment, from p = 0.0000000074 to p = 0.00000000015.
Loading..
Fig. 16. Lower hospitalization is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 17. Improved recovery is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 16. Improved viral clearance is associated with fewer serious outcomes, supporting pooled outcome analysis.
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. 85% of these have been confirmed with one or more specific outcomes, with a mean delay of 4.6 months. When restricting to RCTs only, 53% of treatments showing statistically significant efficacy/harm with pooled effects have been confirmed with one or more specific outcomes, with a mean delay of 7.5 months.
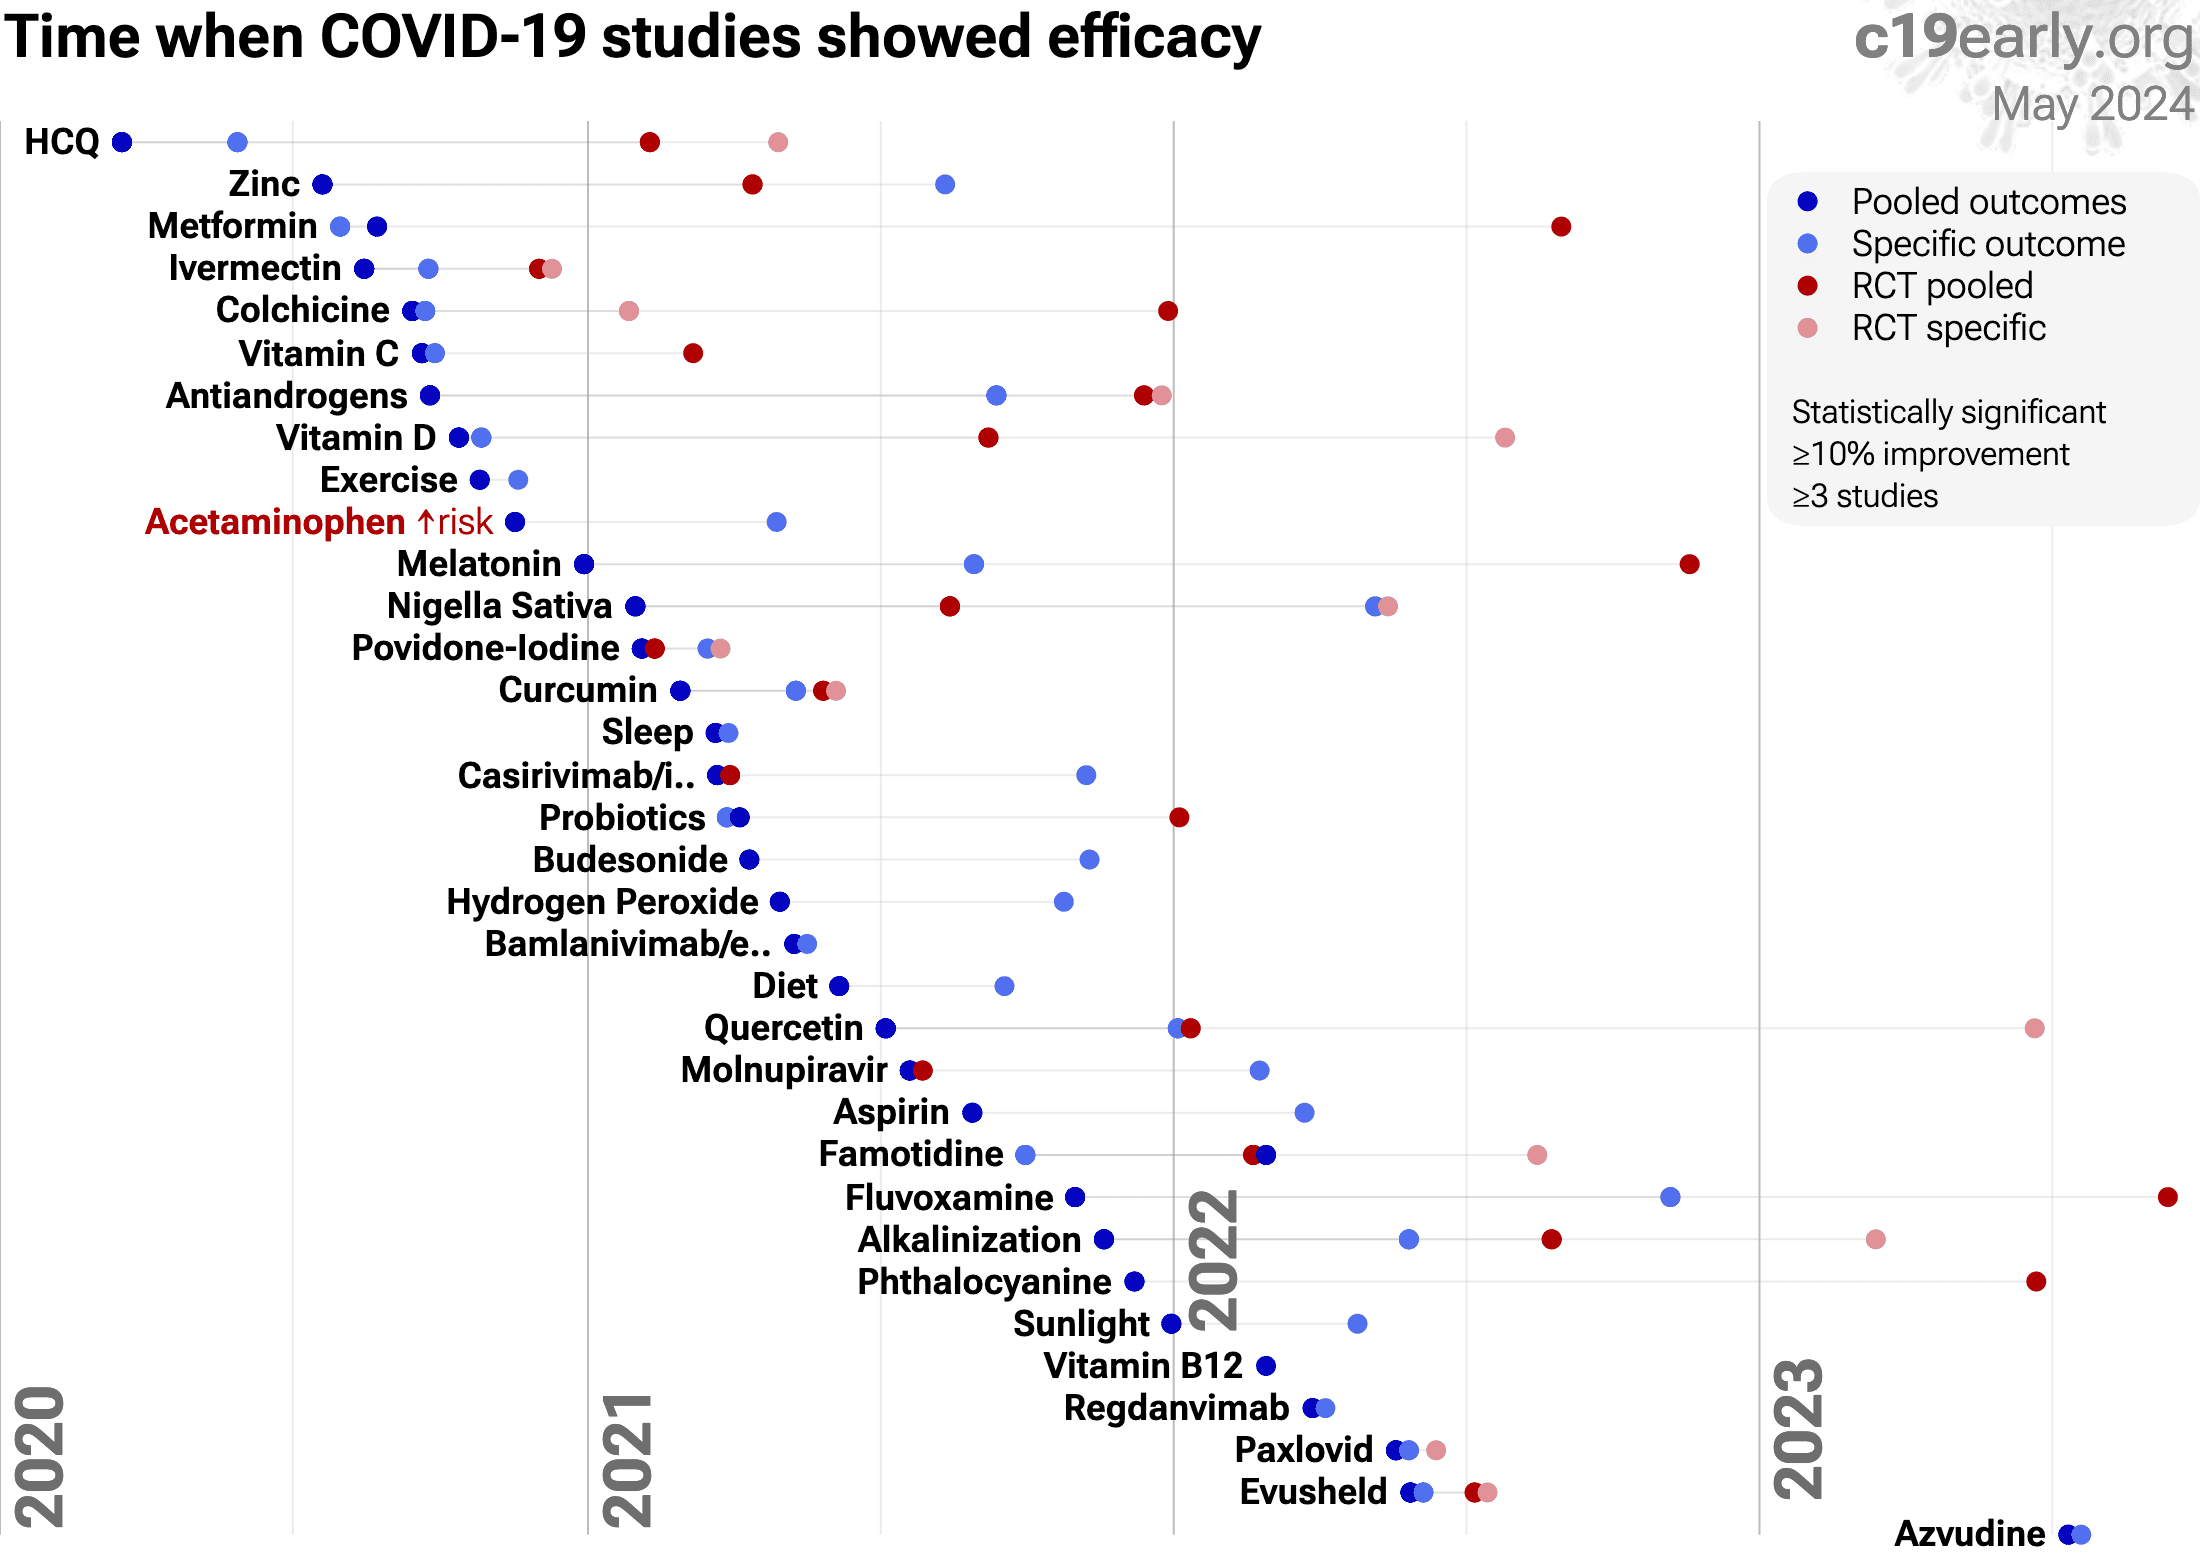
Fig. 19 shows when treatments were found effective during the
pandemic. Pooled outcomes often resulted in earlier detection of efficacy.
Loading..
Loading..
Fig. 19. The time when studies showed that
treatments were effective, defined as statistically significant improvement of
≥10% from ≥3 studies.
Pooled results typically show efficacy earlier than specific
outcome results. Results from all studies often shows efficacy much earlier
than when restricting to RCTs.
Results reflect conditions as used in trials to date, these depend on the
population treated, treatment delay, and treatment regimen.
Pooled analysis could hide efficacy, for example a treatment that is
beneficial for late stage patients but has no effect on viral clearance may
show no efficacy if most studies only examine viral clearance. In practice, it
is rare for a non-antiviral treatment to report viral clearance and to not
report clinical outcomes; and in practice other sources of heterogeneity such
as differences in treatment delay are more likely to hide efficacy.
Analysis validates the use of pooled effects and shows significantly faster
detection of efficacy on average.
However, as with all meta-analyses, it is important to review the different
studies included. We also present individual outcome analyses, which may be
more informative for specific use cases.
Efficacy with cetylpyridinium chloride has also been shown for upper respiratory tract infections45.Preclinical studies have also shown efficacy with cetylpyridinium chloride for influenza A virus46 and respiratory syncytial virus46.
Analysis of short-term changes in viral load using PCR may not detect
effective treatments because PCR is unable to differentiate between intact
infectious virus and non-infectious or destroyed virus particles. For example
Tarragó-Gil, Alemany perform RCTs with cetylpyridinium chloride
(CPC) mouthwash that show no difference in PCR viral load, however there was
significantly increased detection of SARS-CoV-2 nucleocapsid protein,
indicating viral lysis. CPC inactivates SARS-CoV-2 by degrading its membrane,
exposing the nucleocapsid of the virus. To better estimate changes in viral
load and infectivity, methods like viral culture that can
differentiate intact vs. degraded virus are preferred.
Studies to date use a variety of administration methods to the
respiratory tract, including nasal and oral sprays, nasal irrigation, oral
rinses, and inhalation. Table 4 shows the relative efficacy for
nasal, oral, and combined administration. Combined administration shows the
best results, and nasal administration is more effective than oral. Precise
efficacy depends on the details of administration, e.g., mucoadhesion and
sprayability for sprays.
c19early.org
Combined nasal and oral administration is most effective
Across all nasopharyngeal/oropharyngeal treatments we cover, combined nasal and oral administration shows the highest efficacy, followed by nasal administration, with oral administration alone showing the lowest efficacy.
Administration
Improvement
Studies
Nasal & oral
88%[72‑95%]
10
Nasal spray/rinse
59%[50‑66%]
21
Oral spray/rinse
38%[25‑49%]
11
Table 4. Respiratory tract administration efficacy. Relative efficacy of nasal, oral, and combined nasal/oral administration for treatments administered directly to the respiratory tract. Results show random-effects meta-analysis for the most serious outcome reported for all prophylaxis and early treatment studies.
Nasopharyngeal/oropharyngeal treatments work via different methods.
Some are drugs with other primary uses and have a greater potential for side effects and drug interactions, for example azelastine and chlorpheniramine are antihistamines. Table 5 summarizes the primary classes of mechanisms of action, and Table 6 shows mechanisms of action for specific treatments.
c19early.org
Nasal/oral sprays and rinses—primary mechanisms
Primary mechanisms of action for nasopharyngeal/oropharyngeal sprays and rinses. Note: sequenced application is possible to maximize efficacy—for example, using a virucidal spray/wash first (to clean), followed by a barrier spray (to protect), with a 5-10 minute drying window in between.
Virucidal action
Chemically inactivating or destroying the structure of viral particles
Blocking attachment
Binding to the virus or host cells to prevent viral attachment to host cells
Physical barrier
Forming a physical layer over the nasal mucosa preventing viral access to host cells
Physical removal
Mechanical washout/flushing of viral particles and mucus (e.g., large volume irrigation)
Mucociliary clearance
Stimulating the natural beating of nasal cilia to accelerate the clearing of trapped pathogens
Table 5. Primary classes for mechanisms of action for nasopharyngeal/oropharyngeal treatments.
c19early.org
Nasal/oral sprays and rinses—mechanisms of action
Nasopharyngeal/oropharyngeal treatments have many different mechanisms of action. Specific treatments may have significant systemic effects or significantly alter the microbiome.
Antiviral: binds to viral spike protein to block entry Antiviral: high affinity for viral transport proteins Other: H1-receptor antagonist (1st generation antihistamine) Other: anticholinergic activity
Antihistamine. Stronger systemic risks than azelastine. Known to cause significant sedation/drowsiness and cognitive impairment.
Virucidal: oxidizes viral proteins, causing aggregation and loss of function. Impairs spike-ACE2 binding Antiseptic: broad-spectrum antimicrobial activity via oxidative damage to microbial proteins and membranes
Chemical virucide. Activity depends on concentration, pH, and contact time. Saliva may reduce activity.
Virucidal: physically damages viral structure via nitrosylation Other: vasodilator (relaxes blood vessels) in systemic use
Virucide/drug hybrid. In nasal spray form, it acts primarily as a topical disinfectant. Rapidly cleared, so systemic vasodilation risks are low but present.
Nasopharyngeal/oropharyngeal treatments may not be highly selective. In
addition to inhibiting or disabling SARS-CoV-2, they may also be harmful to
beneficial microbes, disrupting the natural microbiome in the oral cavity and
nasal passages that have important protective and metabolic roles117,118. This may be
especially important for prolonged use or overuse.
Table 7 summarizes the potential for common
nasopharyngeal/oropharyngeal treatments to affect the natural
microbiome.
c19early.org
Nasal/oral sprays and rinses may affect the microbiome
Nasopharyngeal/oropharyngeal treatments may significantly alter the microbiome. These effects may be more important with longer-term prophylaxis.
Publishing is often biased
towards positive results, however evidence suggests that there may be a negative bias for
inexpensive treatments for COVID-19. Both negative and positive results are
very important for COVID-19, media in many countries prioritizes negative
results for inexpensive treatments (inverting the typical incentive for
scientists that value media recognition), and there are many reports of
difficulty publishing positive results120-123.
For cetylpyridinium chloride, there is currently not
enough data to evaluate publication bias with high confidence.
Pharmaceutical drug
trials often have conflicts of interest whereby sponsors or trial staff have a
financial interest in the outcome being positive. Cetylpyridinium Chloride for COVID-19
lacks this because it is off-patent, has multiple manufacturers, and is very low cost.
In contrast, most COVID-19 cetylpyridinium chloride trials have been run by
physicians on the front lines with the primary goal of finding the best
methods to save human lives and minimize the collateral damage caused by
COVID-19. While pharmaceutical companies are careful to run trials under
optimal conditions (for example, restricting patients to those most likely to
benefit, only including patients that can be treated soon after onset when
necessary, and ensuring accurate dosing), not all cetylpyridinium chloride trials
represent the optimal conditions for efficacy.
Summary statistics from
meta-analysis necessarily lose information. As with all meta-analyses, studies
are heterogeneous, with differences
in treatment delay, treatment regimen, patient demographics, variants,
conflicts of interest, standard of care, and other factors. We provide analyses for specific
outcomes and by treatment delay, and we aim to identify key characteristics in
the forest plots and summaries. Results should be viewed in the context of
study characteristics.
Some analyses classify treatment based on early or late
administration, as done here, while others distinguish between mild, moderate,
and severe cases. Viral load does not indicate degree of symptoms — for
example patients may have a high viral load while being asymptomatic. With
regard to treatments that have antiviral properties, timing of treatment is
critical — late administration may be less helpful regardless of
severity.
Details of treatment delay per patient is often not available.
For example, a study may treat 90% of patients relatively early, but the
events driving the outcome may come from 10% of patients treated very late.
Our 5 day cutoff for early treatment may be too conservative, 5 days may be too late in many cases.
Comparison across treatments is confounded by differences in
the studies performed, for example dose, variants, and conflicts of interest.
Trials with conflicts of interest may use designs better suited to the
preferred outcome.
In some cases, the most serious outcome has very few events,
resulting in lower confidence results being used in pooled analysis, however
the method is simpler and more transparent. This is less critical as the
number of studies increases. Restriction to outcomes with sufficient power may
be beneficial in pooled analysis and improve accuracy when there are few
studies, however we maintain our pre-specified method to avoid any
retrospective changes.
Studies show that combinations of treatments can be highly
synergistic and may result in many times greater efficacy than individual
treatments alone77-101.
Therefore standard of care may be critical and benefits may diminish or
disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on
submissions. Accuracy benefits from widespread review and submission of
updates and corrections from reviewers. Less popular treatments may receive
fewer reviews.
No treatment or intervention is 100% available and
effective for all current and future variants. Efficacy may vary significantly
with different variants and within different populations. All treatments have
potential side effects. Propensity to experience side effects may be predicted
in advance by qualified physicians. We do not provide medical advice. Before
taking any medication, consult a qualified physician who can compare all
options, provide personalized advice, and provide details of risks and
benefits based on individual medical history and situations.
Multiple reviews cover cetylpyridinium chloride for COVID-19, presenting additional
background on mechanisms and related results, including118,124-127.
Additional preclinical or review papers suggesting potential
benefits of cetylpyridinium chloride for COVID-19 include132-136. We have not
reviewed these studies in detail.
SARS-CoV-2 infection and replication involves a complex
interplay of 500+ host and viral proteins and other
factors36-43, providing many therapeutic
targets.
Over 12,000 compounds have been predicted to reduce COVID-19
risk44, either by directly
minimizing infection or replication, by supporting immune system function, or
by minimizing secondary complications.
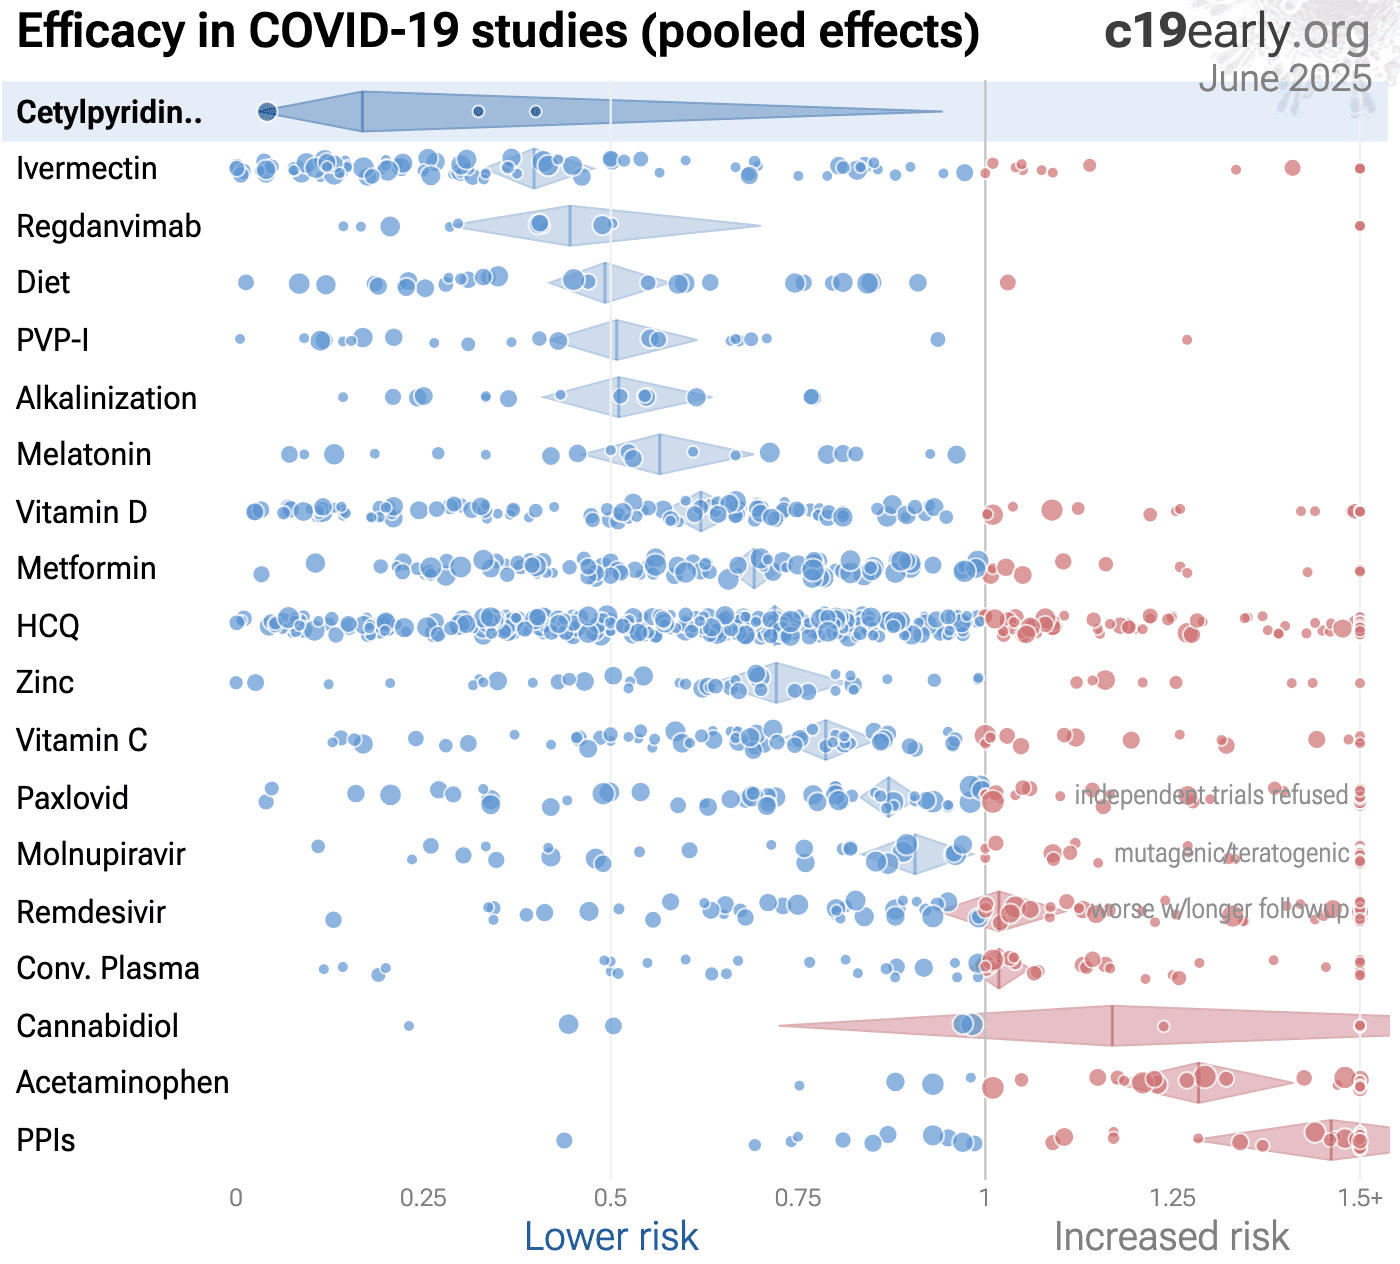
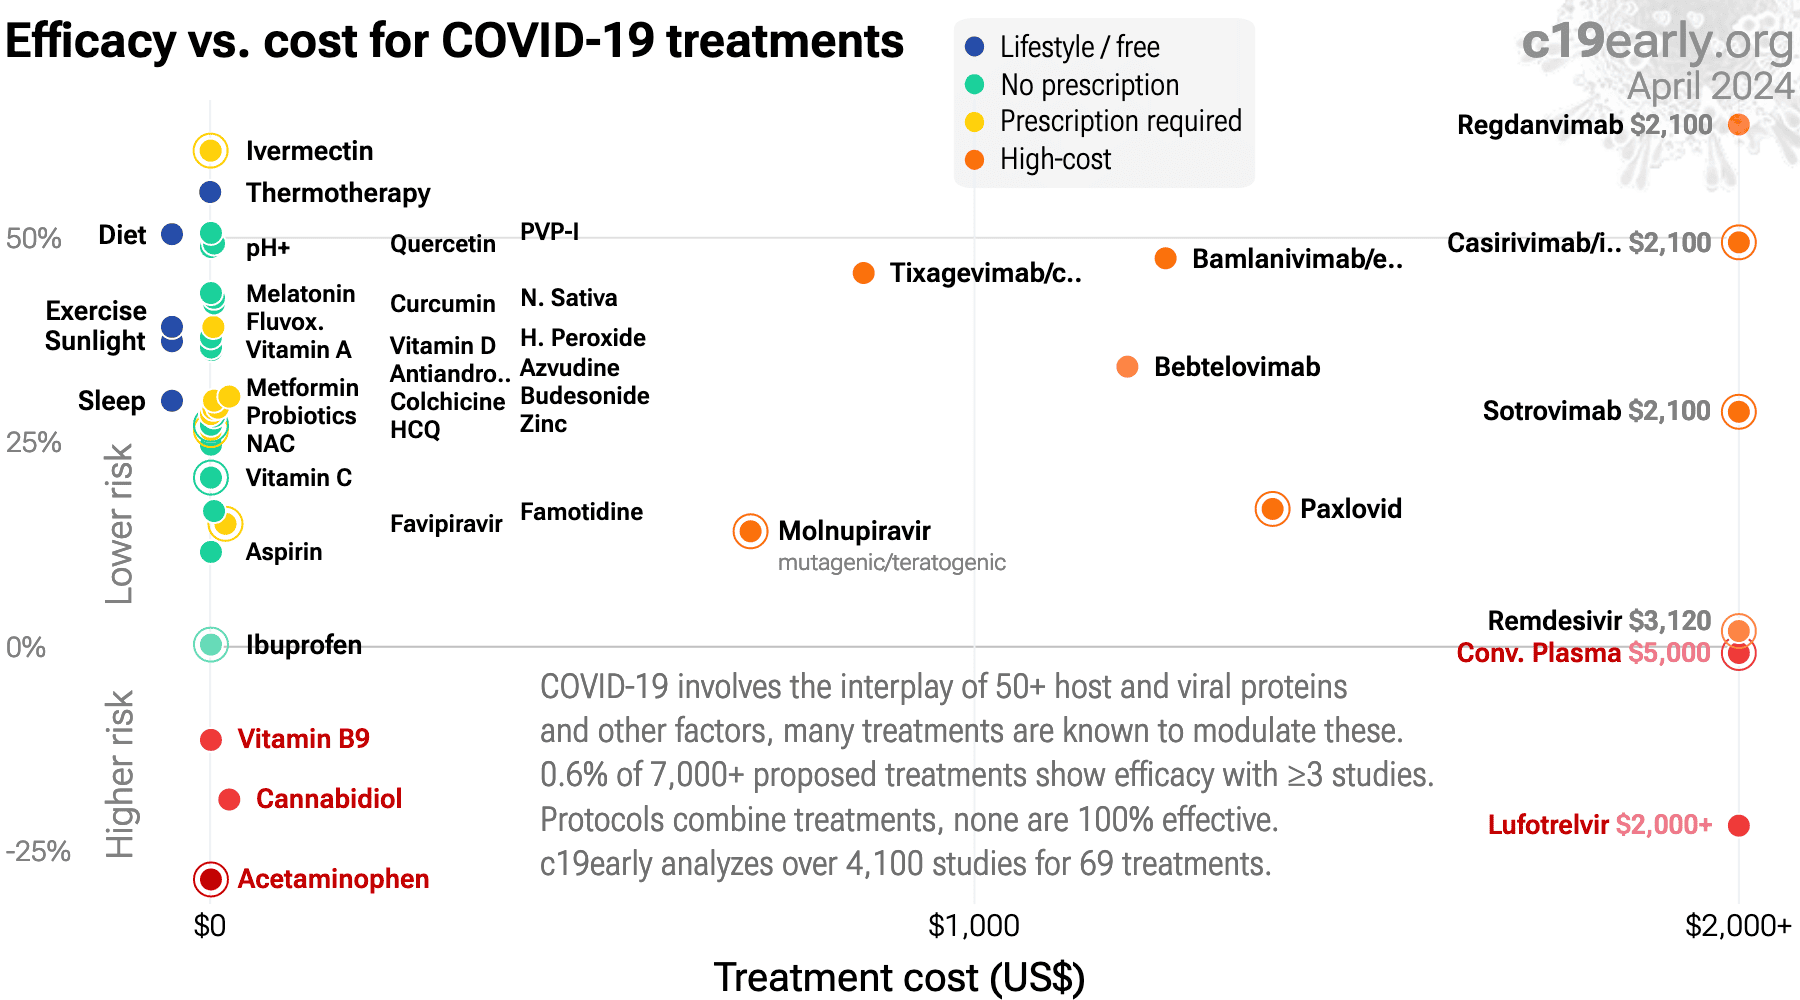
Fig. 20 shows an overview of the results for cetylpyridinium chloride
in the context of multiple COVID-19 treatments, and Fig. 21 shows a plot
of efficacy vs. cost for COVID-19 treatments.
Loading..
Fig. 20.
Scatter plot showing results within the context of multiple COVID-19 treatments.
Diamonds shows the results of random-effects meta-analysis.
0.5% of 12,000+ proposed treatments show efficacy137.
Loading..
Loading..
Fig. 21. Efficacy vs. cost for COVID-19 treatments.
SARS-CoV-2 infection typically starts in the upper respiratory tract.
Progression may lead to cytokine storm, pneumonia, ARDS, neurological issues,
organ failure, and death. Stopping replication in the upper respiratory tract,
via early or prophylactic nasopharyngeal/oropharyngeal treatment, can avoid
the consequences of progression to other tissues, and avoid the requirement
for systemic treatments with greater potential for side effects.
Studies to date show that cetylpyridinium chloride is
an effective treatment for COVID-19.
Significantly lower risk is seen for recovery and viral clearance. One study shows significant benefit.
Meta-analysis using the most serious outcome reported shows
38% [15‑55%] lower risk. Results are better for peer-reviewed studies.
Currently all studies are RCTs.
Currently there is limited data, with only 157 patients and only 44 control events for the most serious outcome in trials to date.
Efficacy with cetylpyridinium chloride has also been shown for upper respiratory tract infections45.
Cetylpyridinium Chloride may affect the natural microbiome, especially with prolonged use.
Contact.
Contact us on X at @CovidAnalysis.
Funding.
We have received no funding or
compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest.
We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
AI.
We use AI models (Gemini, Grok, Claude, and
ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest
improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.
Updates.
Our COVID-19 meta-analyses involve the extraction of over 228,000
datapoints from thousands of papers for 227 treatments. We thank the
thousands of scientists, physicians, and other contributors that have provided updates,
suggestions, feedback, and corrections. These are all welcome and can be submitted
at https://c19early.org/cpcmeta.html.
Dedication.
This work is dedicated to top
evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce
mortality and morbidity during the pandemic. In alphabetical order:
Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty,
Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr.
Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch,
Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work
distributed in accordance with the Creative Commons CC0 1.0 Universal license, which
dedicates the work to the public domain by waiving all rights worldwide under copyright law.
You can distribute, remix, adapt, and build upon this work in any medium or format,
including for commercial purposes, without asking permission. Referenced material and
third-party images retain any original copyrights or restrictions.
See: https://creativecommons.org/publicdomain/zero/1.0/.
RCT 61 COVID+ patients showing improved reduction in viral infectivity with a mouthwash containing 0.05% cetylpyridinium chloride (CPC) and 0.05% chlorhexidine digluconate (CHX), compared to 0.9% NaCl. The study only analyzes short-term changes in viral load 30 minutes after treatment.
Submit Corrections or Updates.
Early terminated RCT with very limited information reported in the registry and only one patient showing symptoms. There is not enough information to assess the viral load results in the registry - the protocol indicates right-censoring for patients with undetectable viral load which may be the majority of patients at 4 weeks.
Submit Corrections or Updates.
RCT 120 low-risk COVID-19 patients showing improved recovery with nasal and oral formulations containing cetylpyridinium chloride, D-limonene, and monolaurin (the nasal formulation contained D-limonene and cetylpyridinium chloride, while the oral formulation contained D-limonene, monolaurin, and cetylpyridinium chloride). No patients progressed to severe disease. No adverse events were reported in either group during the 7 day treatment period or 1 month followup. Placebo contents are not specified - authors note only "a homogenized liquid carrier", however any liquid rinse may have some efficacy via mechanical clearance.
Submit Corrections or Updates.
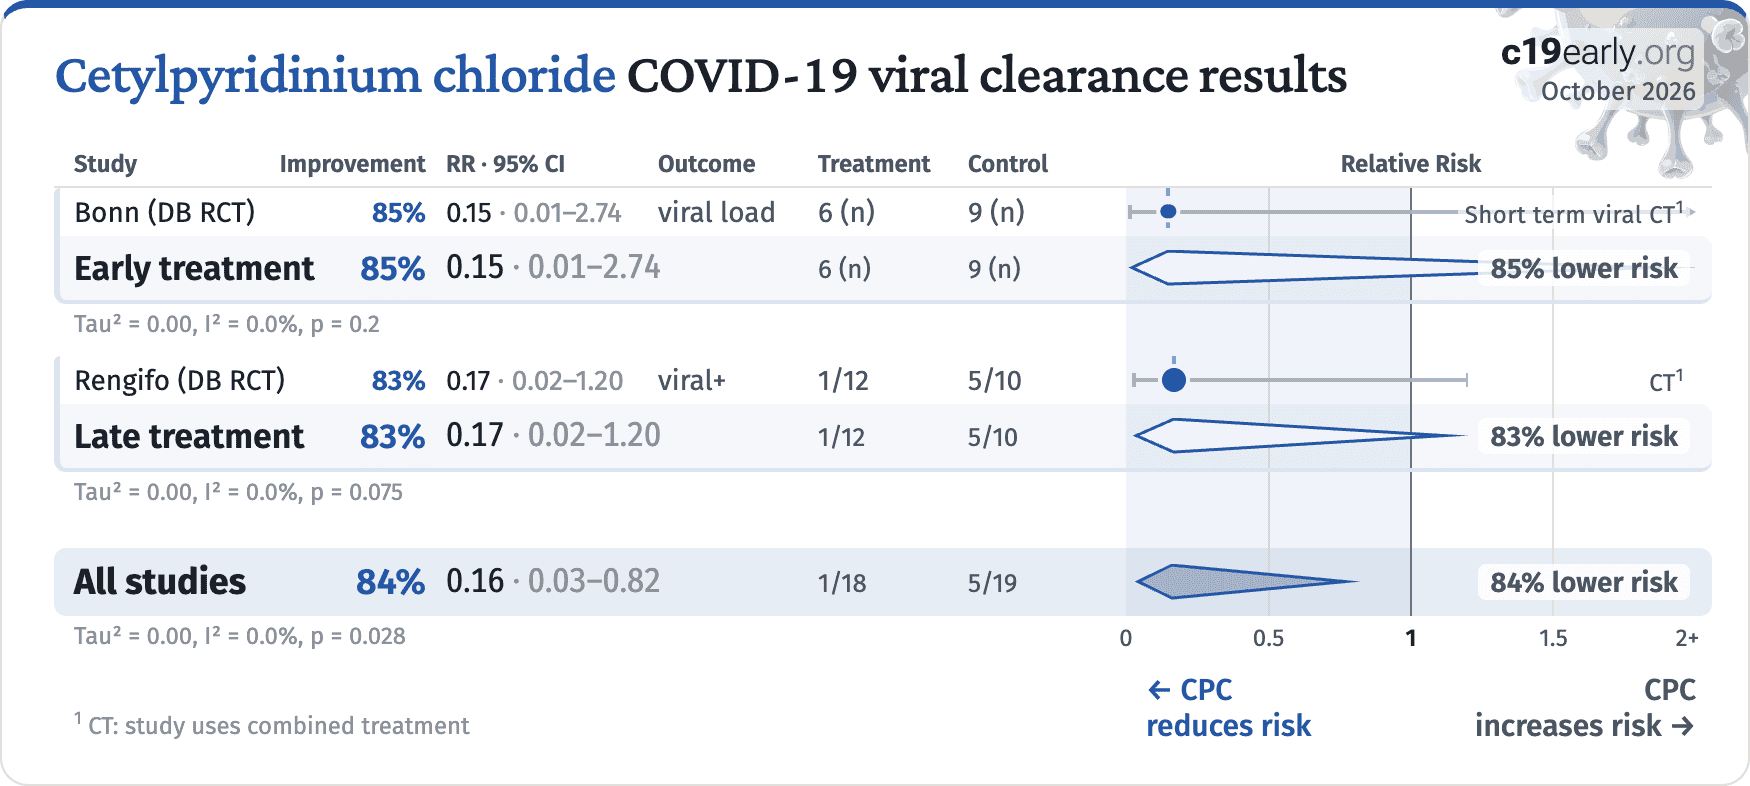
Lower hospitalization and improved viral clearance
Not statistically significant · p = 0.48 (hospitalization) and p = 0.056 (viral clearance)
RCT 23 patients in Colombia, showing improved viral clearance with cetylpyridinium chloride plus chlorhexidine mouthwash.
Submit Corrections or Updates.
Estimated 90 patient cetylpyridinium chloride early treatment RCT with results not reported over 4 years after estimated completion.
Submit Corrections or Updates.
We perform ongoing searches of PubMed, medRxiv, Europe PMC, ClinicalTrials.gov, The Cochrane
Library, Google Scholar, Research Square, ScienceDirect, Oxford University Press, the
reference lists of other studies and meta-analyses, and submissions to the site c19early.org, which regularly receives notification of studies upon
publication.
Search terms are cetylpyridinium chloride and COVID-19 or SARS-CoV-2. Automated searches are performed twice daily, with all matches reviewed for inclusion.
All studies regarding the use of cetylpyridinium chloride for COVID-19 that report a comparison with a
control group are included in the main analysis.
Studies with major unexplained data issues, for example major outcome data that is
impossible to be correct with no response from the authors, are excluded.
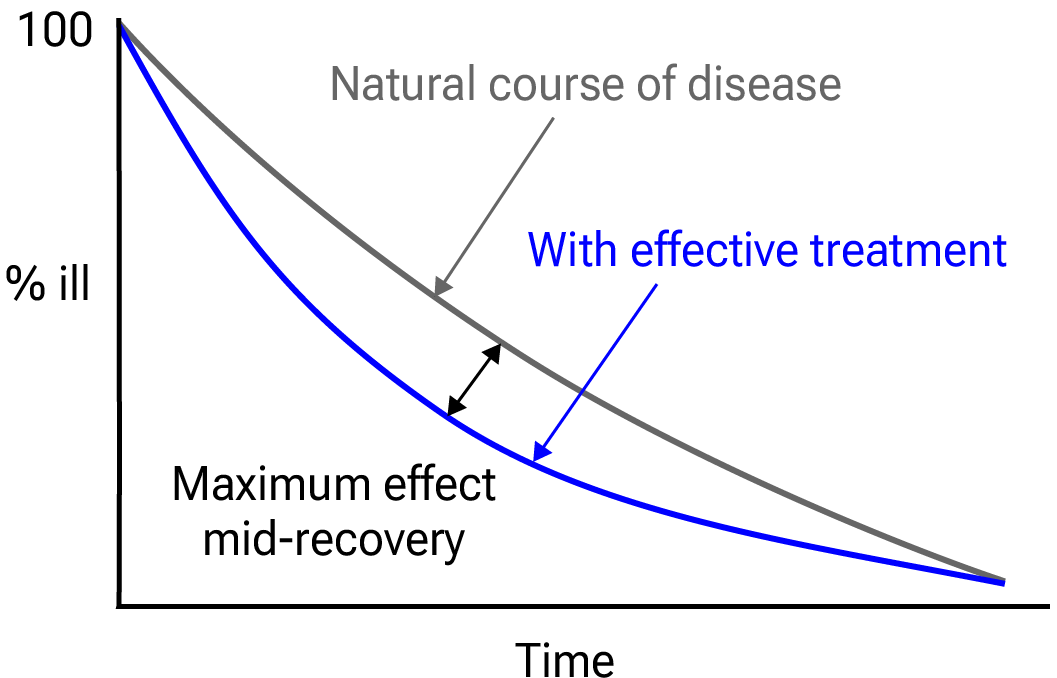
Fig. 22.
Mid-recovery results can more accurately reflect efficacy when almost all patients
recover. Mateja et al. confirm that intermediate viral load results more accurately
reflect hospitalization/death.
We extracted effect sizes and associated data from all studies. If studies report multiple
kinds of effects then the most serious outcome is used in pooled analysis, while
other outcomes are included in the outcome-specific analyses. For example, if effects for
mortality and cases are reported then they are both used in specific outcome analyses,
while mortality is used for pooled analysis.
If symptomatic results are reported at multiple times, we use the latest time, for example
if mortality results are provided at 14 days and 28 days, the results at 28 days have
preference. Mortality alone is preferred over combined outcomes.
Outcomes with zero events in both arms are not used, the next most serious outcome with
one or more events is used. For example, in low-risk populations with no mortality, a
reduction in mortality with treatment is not possible, however a reduction in
hospitalization, for example, is still valuable.
Clinical outcomes are considered more important than viral outcomes.
When basically all patients recover in both treatment and control groups, preference for
viral clearance and recovery is given to results mid-recovery where available. After most
or all patients have recovered there is little or no room for an effective treatment to do
better, however faster recovery is valuable.
An IPD meta-analysis confirms that intermediate viral load reduction is more closely
associated with hospitalization/death than later viral load reduction138.
If only individual symptom data is available, the most serious symptom has
priority, for example difficulty breathing or low SpO2 is more
important than cough.
Forest plots are computed using PythonMeta139 with the DerSimonian and
Laird random-effects model (the fixed effect assumption is not plausible in this case) and
inverse variance weighting.
Results are presented with 95% confidence intervals. Heterogeneity among studies was
assessed using the I2 statistic.
When results provide an odds ratio, we compute the relative risk when possible, or convert
to a relative risk according to Zhang et al.
Reported confidence intervals and p-values are used when available, and adjusted
values are used when provided. If multiple types of adjustments are reported propensity
score matching and multivariable regression has preference over propensity score matching
or weighting, which has preference over multivariable regression. Adjusted results have
preference over unadjusted results for a more serious outcome when the adjustments
significantly alter results.
When needed, conversion between reported p-values and confidence intervals followed
Altman, Altman (B), and Fisher's exact test was used to calculate
p-values for event data. If continuity correction for zero values is required, we
use the reciprocal of the opposite arm with the sum of the correction factors equal to
1143.
Results are expressed with RR < 1.0 favoring treatment, and using the risk of a negative
outcome when applicable (for example, the risk of death rather than the risk of survival).
If studies only report relative continuous values such as relative times, the ratio of the
time for the treatment group versus the time for the control group is used. Calculations
are done in Python (3.14.8) with
scipy (1.18.1), pythonmeta (1.26), numpy (2.5.3), statsmodels (0.15.0), and plotly (6.9.0).
Mixed-effects meta-regression results are computed with R (4.4.0) using the metafor
(4.6-0) and rms (6.8-0) packages, and using the most serious sufficiently powered outcome.
For all statistical tests, a p-value less than 0.05 was considered statistically
significant.
Grobid 0.8.2 is used to parse PDF documents.
When evaluating potential effect modification across groups, we use an
interaction test as described by Altman (C) et al. We compared the log-transformed
relative risks using a z-test, deriving the standard error of the difference from
the 95% confidence intervals. A two-sided interaction p-value of < 0.05 was
considered a statistically significant difference in treatment effect between the
groups.
Cochrane RoB 2/ROBINS-I are often used to evaluate studies, and have the advantage of
providing standardized rules that can be applied with minimal understanding of the domain
and study. However, the rules do not account for many real-world issues, often
overemphasize or underemphasize others, and studies show low inter-rater
reliability151.
Certain domains are more applicable for these tools, however the time-sensitive nature of
a pandemic, with significant mortality for every day of delay in evidence assessment, and
the characteristics of COVID-19 make them inappropriate for this domain.
This can be demonstrated with examples where expert RoB 2/ROBINS-I ratings do not match
reality for COVID-19. Popp et al. use RoB 2 to classify Reis et al. as low
risk of bias, however this is the opposite of reality—the trial not only has very
high risk of bias, but has very high actual known bias, refusing to release data despite
pledging to, reporting multiple impossible numbers, having blinding and randomization
failure, and many other issues153.
Axfors et al. use RoB 2 to classify Horby et al. as low risk of bias, however
this is the opposite of reality—the very late treatment and excessive dosage used
produces results with no relevance to recommended usage.
HCQ shows poor results with
late treatment and excessive dosage, and the combination shows harmD.
Hempenius et al. use ROBINS-I to classify 33 studies for HCQ. The two rated as having
the lowest risk of bias149,150 are far from the most informative. Both
involve very late treatment, providing no information on recommended usage, and ROBINS-I
does a very poor job of accounting for the impact of confounding factorsE.
Our quality evaluation focuses on known issues and bias, and the potential
impact on outcomes, rather than just the risk of bias.
The estimated potential impact of each confounding factor, and the direction of the impact
is considered. For example, consider a study that shows significantly lower risk, the
value of the study varies significantly if confounding points to an underestimate or an
overestimate of efficacy. In one case, the real effect may be null, while the other case
provides stronger evidence of efficacy (which may be greater than the study shows).
Analysis focusing on the risk of bias, while simpler, may penalize studies for theoretical
or technical issues that have no or minimal impact on outcomes. Analysis also depends on
the outcome, for example certain issues are less relevant for objective outcomes such as
mortality.
Inaccurate penalization, and inaccurate high-quality evaluation in the face of known major
issues affecting outcomes, increases in significance during a pandemic when immediate
recognition of new evidence is critical, and when considering all global studies, as
required during a pandemic. Investigators in other countries may have different customs
for design, analysis, and reporting, and different English language skills, however they
may not be less diligent or have greater bias.
Investigators in lower-pharmaceutical-profit countries may have lower bias towards
profitable interventions.
We have classified studies as
early treatment if most patients are not already at a severe stage at the time of
treatment (for example based on oxygen status or lung involvement), and treatment started
within 5 days of the onset of symptoms. If studies contain a mix of early treatment and
late treatment patients, we consider the treatment time of patients contributing most to
the events (for example, consider a study where most patients are treated early but late
treatment patients are included, and all mortality events were observed with late
treatment patients).
We note that a shorter time may be preferable. Antivirals are typically only considered
effective when used within a shorter timeframe, for example 0-36 or 0-48 hours for
oseltamivir, with longer delays not being effective62,63.
This is a living analysis and is updated regularly.
Submit updates or corrections with the form below.
We received no funding, this research is done in our spare time.
We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/cpcmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Bonn, 3/21/2023, Double Blind Randomized Controlled Trial, Germany, peer-reviewed, 14 authors, study period 4 January, 2022 - 22 February, 2022, this trial uses multiple treatments in the treatment arm (combined with CHX) - results of individual treatments may vary, trial DRKS00027812.
viral load, 85.3% lower, relative load 0.15, p = 0.20, treatment 6, control 9, relative reduction in infectious viral load, 30 min vs. baseline, CPC+CHX.
risk of no recovery, 60.0% lower, RR 0.40, p = 1.00, treatment 0 of 3 (0.0%), control 1 of 6 (16.7%), NNT 6.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
Ponphaiboon (B), 9/19/2025, Double Blind Randomized Controlled Trial, placebo-controlled, Thailand, preprint, 12 authors, study period 17 May, 2022 - 16 May, 2023, this trial uses multiple treatments in the treatment arm (combined with limonene and monolaurin) - results of individual treatments may vary, trial TCTR20240803002.
risk of no recovery, 36.0% lower, RR 0.64, p = 0.006, treatment 25 of 53 (47.2%), control 42 of 57 (73.7%), NNT 3.8, day 7, fever and headache.
risk of no recovery, 24.5% lower, RR 0.76, p < 0.001, treatment 43 of 59 (72.9%), control 55 of 57 (96.5%), NNT 4.2, day 7, sore throat.
risk of no recovery, 13.7% lower, RR 0.86, p = 0.02, treatment 50 of 59 (84.7%), control 56 of 57 (98.2%), NNT 7.4, day 7, cough and mucus.
risk of no recovery, 29.7% lower, RR 0.70, p < 0.001, treatment 40 of 59 (67.8%), control 55 of 57 (96.5%), NNT 3.5, day 7, runny nose and nasal congestion.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Rengifo, 5/22/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Colombia, peer-reviewed, 13 authors, study period July 2020 - September 2020, average treatment delay 5.5 days, this trial uses multiple treatments in the treatment arm (combined with chlorhexidine) - results of individual treatments may vary, trial NCT04563689(history).
risk of hospitalization, 67.6% lower, RR 0.32, p = 0.48, treatment 0 of 12 (0.0%), control 1 of 11 (9.1%), NNT 11, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of no viral clearance, 83.3% lower, RR 0.17, p = 0.06, treatment 1 of 12 (8.3%), control 5 of 10 (50.0%), NNT 2.4, day 5.
Viral infection and replication involves attachment, entry, uncoating and release, genome replication and transcription, translation and protein processing, assembly and budding, and release. Each step can be disrupted by therapeutics.
Monoclonal antibodies were
previously included. Other treatments such as dexamethasone, tocilizumab, and baricitinib
were recommended for late stage hospitalized patients.
Smoking was
known to cause lung cancer since at least 1939, but this was not widely recognized in the
US until 1964, 25 years later. Surgeon general Leroy Burney tried publicizing the danger
starting in 1957, with limited success. Surgeon general Luther Terry, appointed in 1961,
prompted by President Kennedy in 1962 amid pressure from health advocates, finally got
recognition in 1964. The 1964 report reviewed 7,000+ studies, but these could (and should)
have been reviewed and acted upon in real-time as they were published.
Historians attribute the 25 year delay to an industry campaign to manufacture doubt and
controversy, through tactics like funding biased and fraudulent research from
"independent" organizations, attacking scientists, and political lobbying.
The success of the industry campaign is only possible because officials did not analyze
the research in detail. Fraudulent industry research supported prior failures, but would
have been called out as fraudulent by officials that analyzed and understood the research
in real-time.
When administered late in infection, HCQ may enhance viral egress by further increasing
lysosomal pH beyond the effect of ORF3a's water channel activity, thereby promoting
lysosomal exocytosis, inactivating degradative enzymes, and facilitating the release of
SARS-CoV-2 particles into the extracellular environment145,146.
Research also suggests potential cardioprotective effects at lower doses, but
cardiotoxicity with excessive dosage147. Bobrowski et al. also
indicate negative effects if HCQ and remdesivir are combined.
Peters et al. is subject to confounding by calendar-time (SOC evolved rapidly early in
the pandemic, the linear covariate does not reflect non-linear SOC changes and hospital
specific effects), hospital type (non-treatment hospitals were tertiary university
centers), confounding by indication (4/7 hospitals initiated treatment on deterioration),
immortal-time bias for as-treated (exposure assigned after baseline), significant
differences for other experimental treatments, potential overadjustment from collider bias
(steroid use and indication bias), limited baseline severity information, differences in
hospice referral propensity across hospitals, unadjusted difference in time from onset to
admission, difference in PCR positivity, and other factors.
Mahévas et al. is subject to confounding by hospital (treatment highly dependent on
the hospital, different SOC/ICU transfer practices, not included in PS), immortal time
(only partly addressed in sensitivity analysis), co-treatment differences, calendar-time
(SOC evolved rapidly early in the pandemic), binary coding for age (age ≥65 despite steep
age-risk gradient), residual imbalance (variables dropped from PS), a composite outcome
dependent on hospital triage/capacity, and other factors.