Media covered none of the 4 studies showing significantly lower risk
No positive sodium bicarbonate studies were covered
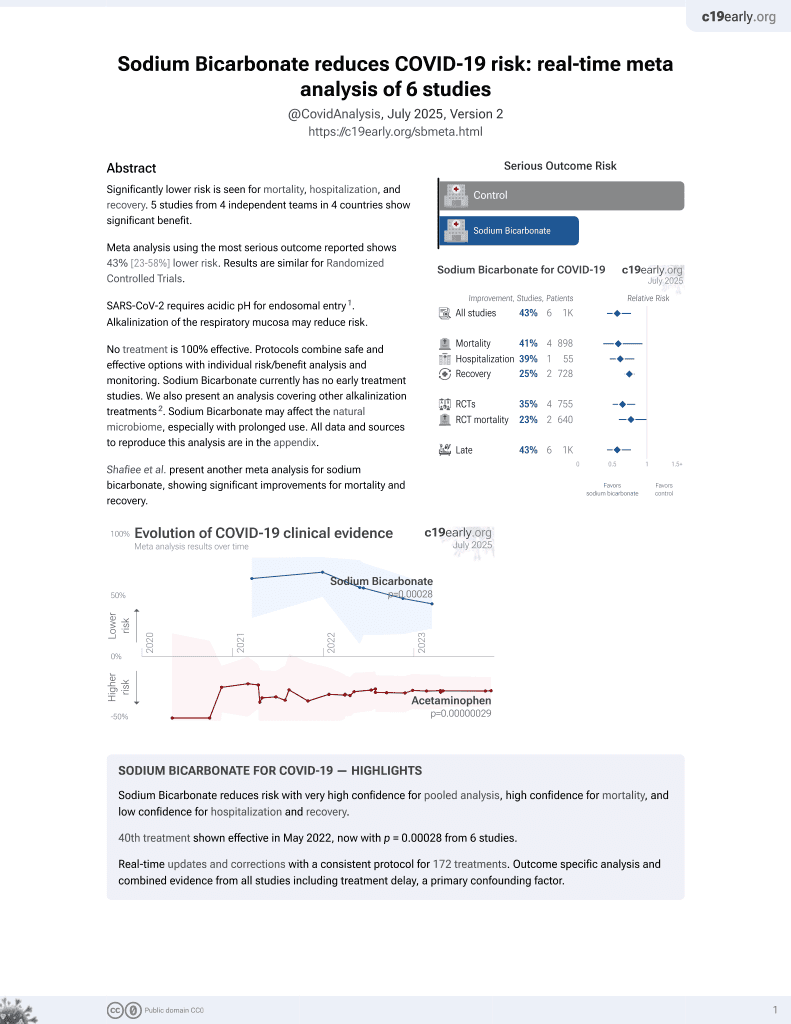
Sodium Bicarbonate for COVID-19
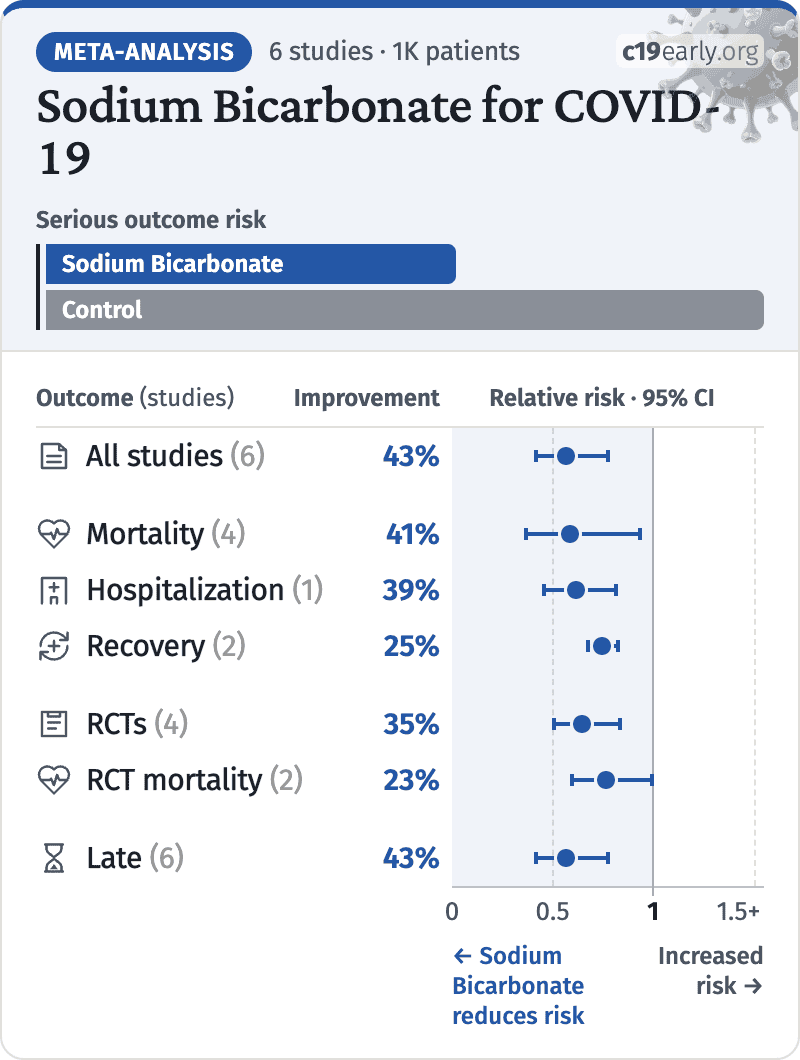
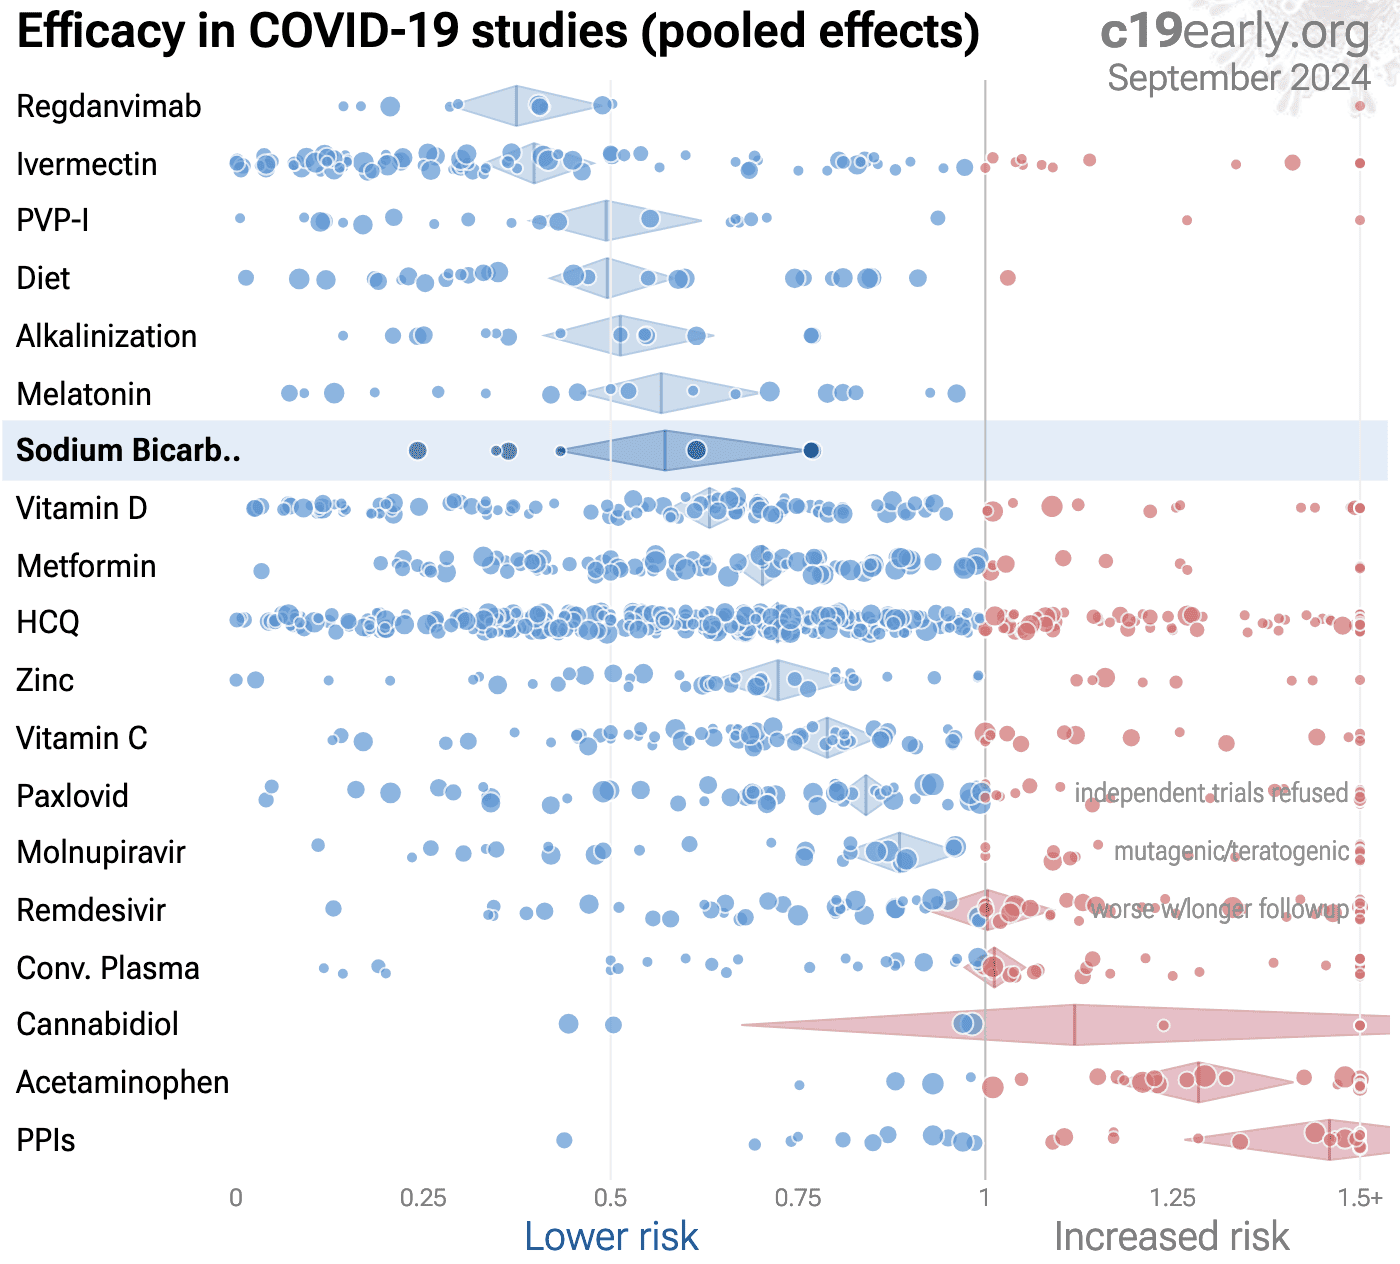
Highlights- Sodium Bicarbonate reduces risk with very high confidence for pooled analysis, high confidence for mortality, and low confidence for hospitalization and recovery.
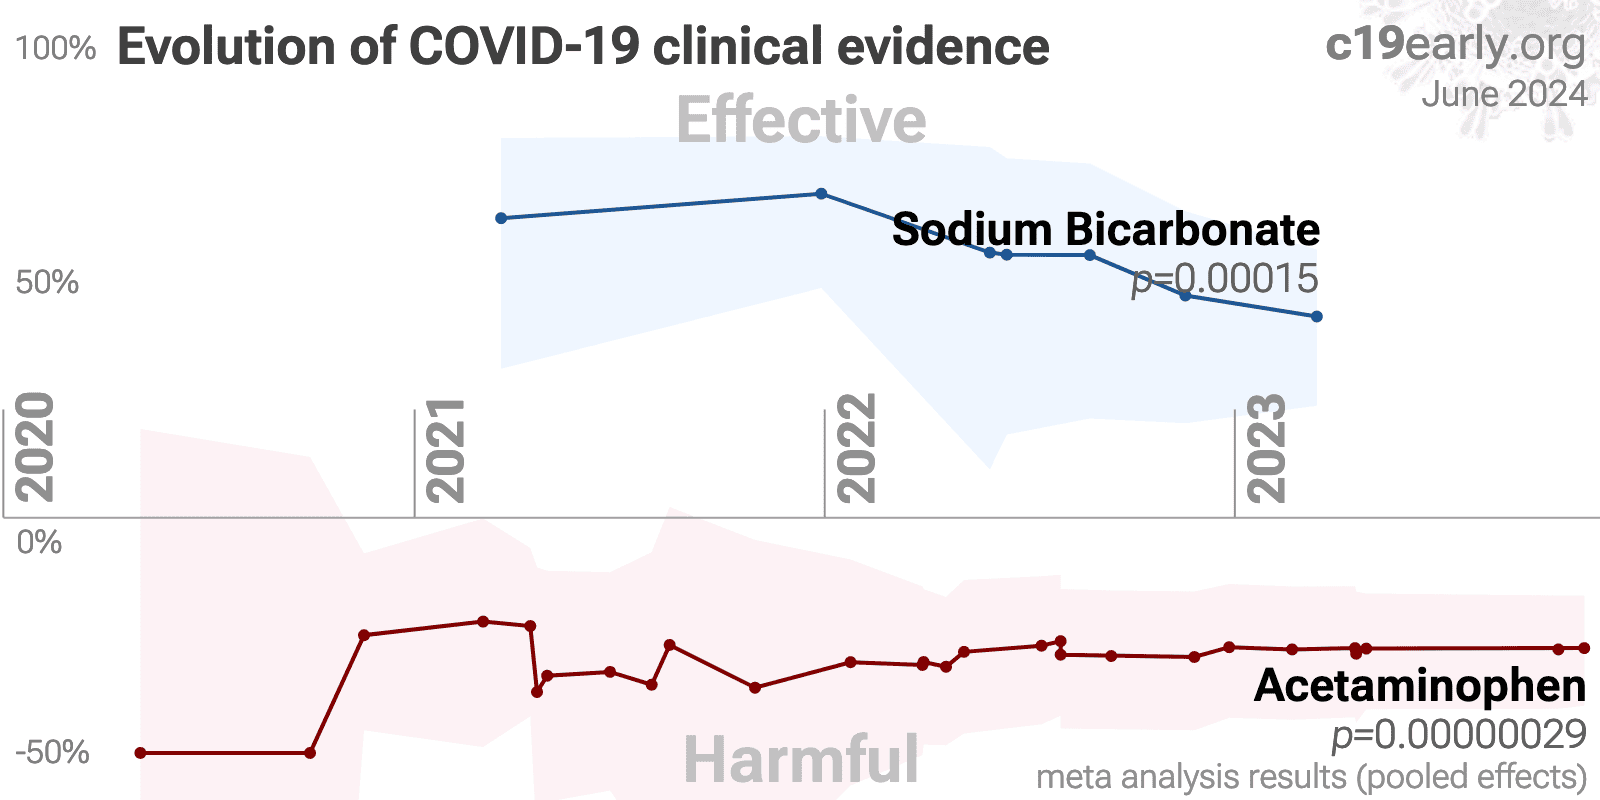
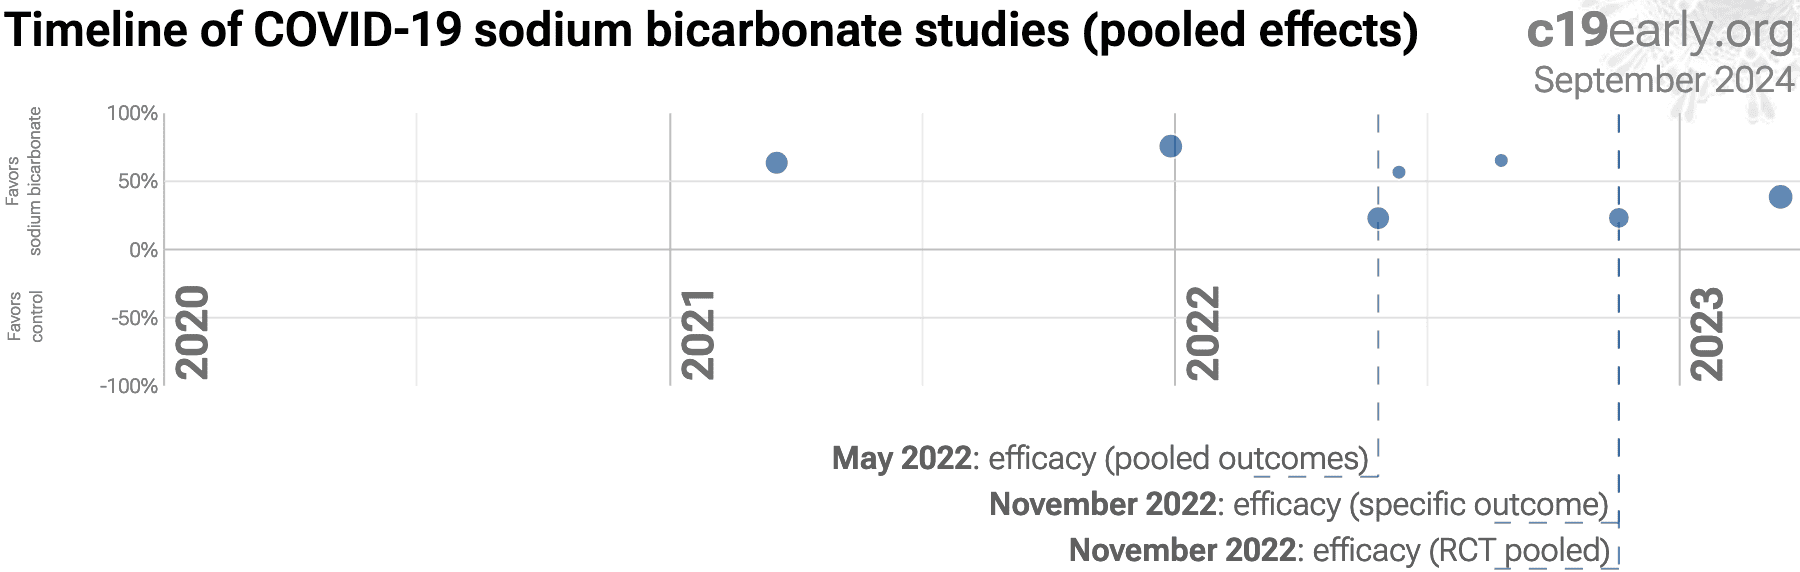
- 41st treatment shown effective in May 2022, now with p = 0.00028 from 6 studies.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
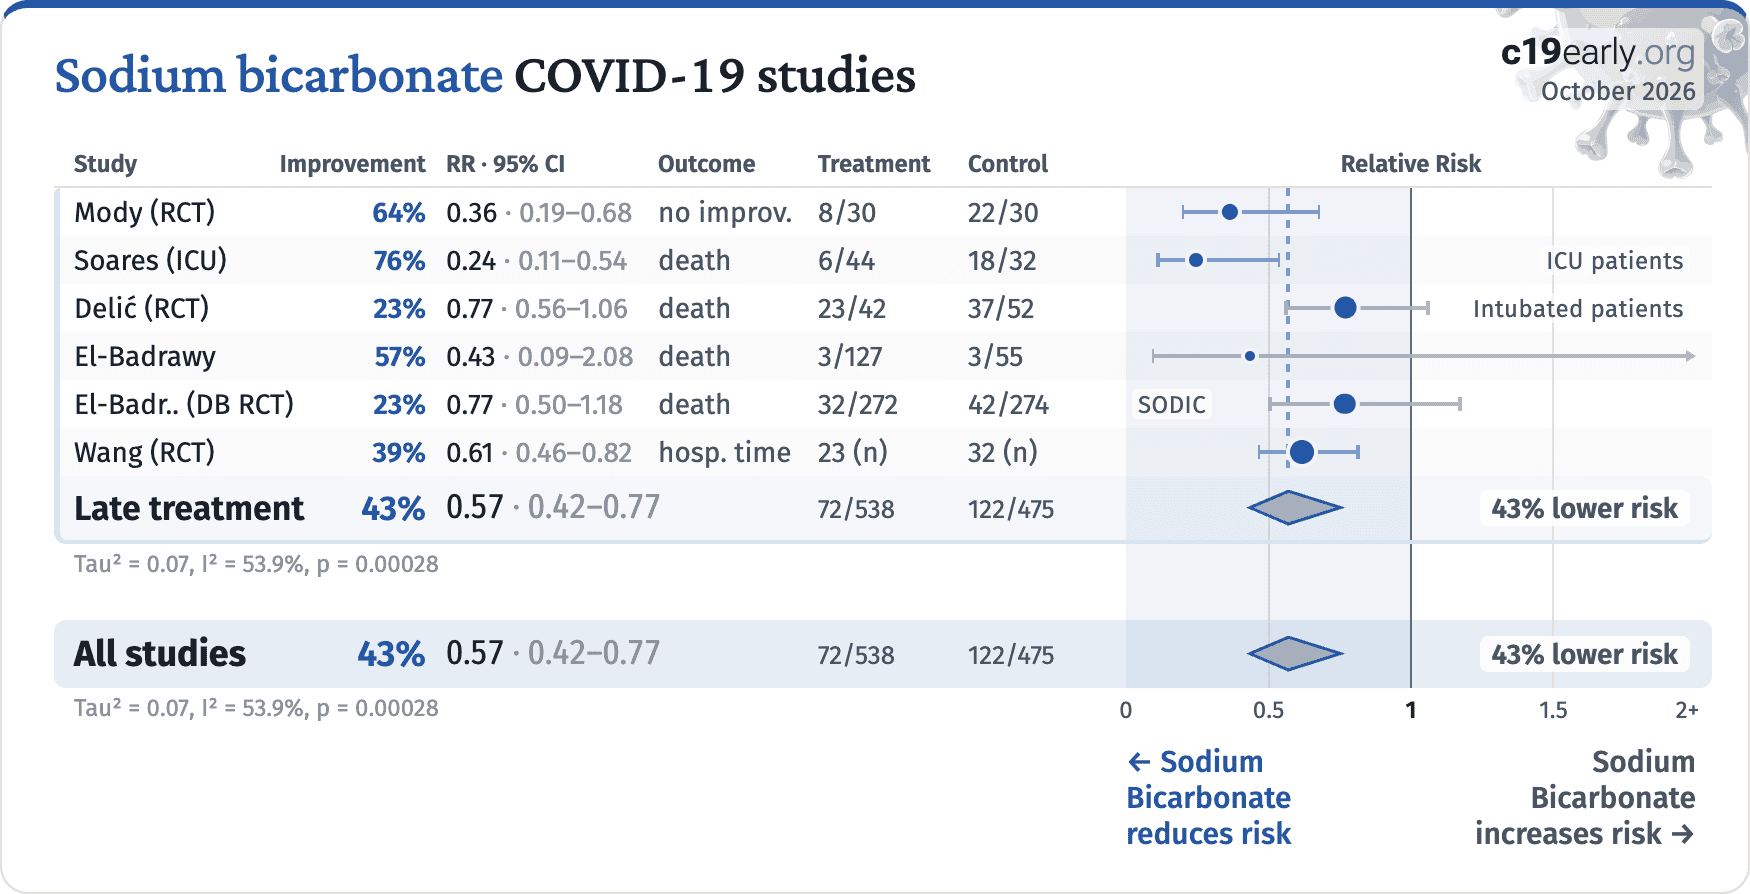
Sodium bicarbonate COVID-19 studies
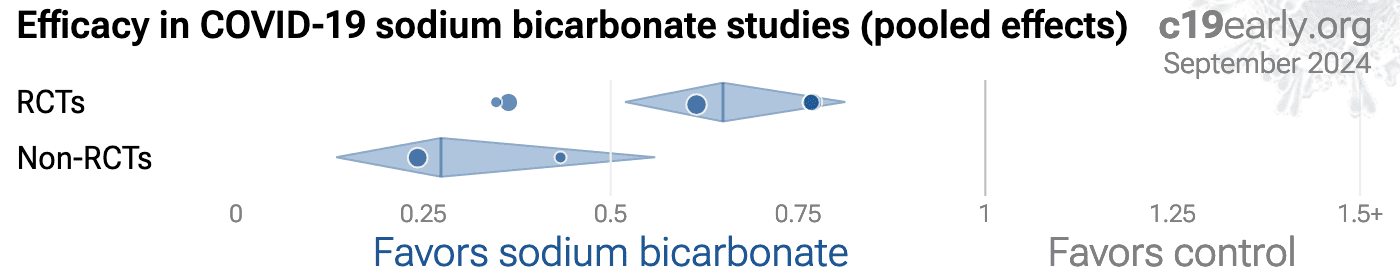
Sodium Bicarbonate for COVID-19: meta-analysis results
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Sodium bicarbonate COVID-19 studies
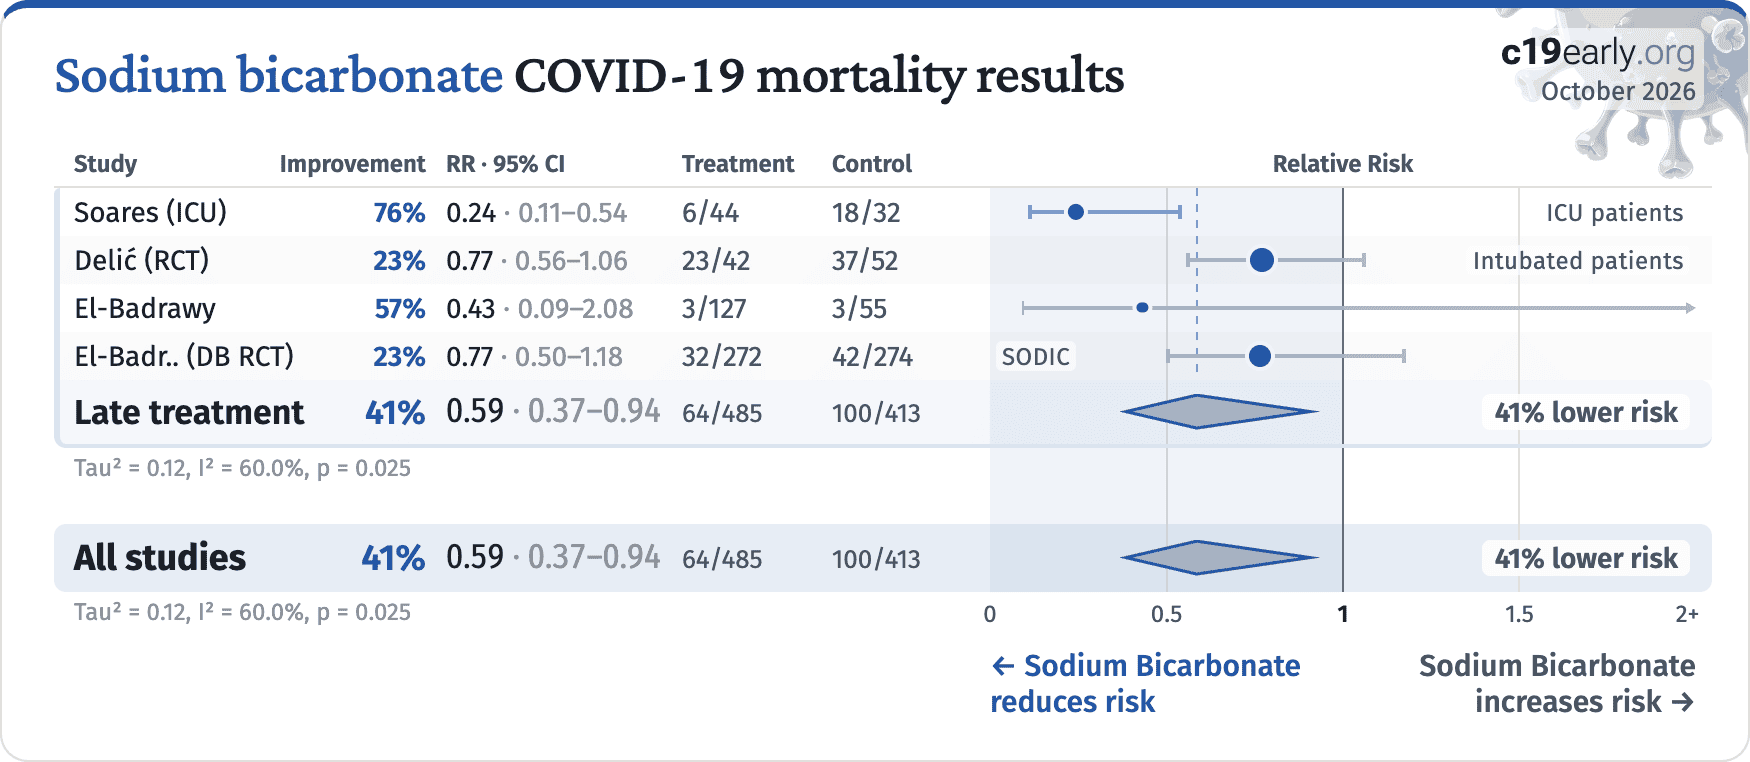
Sodium bicarbonate COVID-19 mortality results
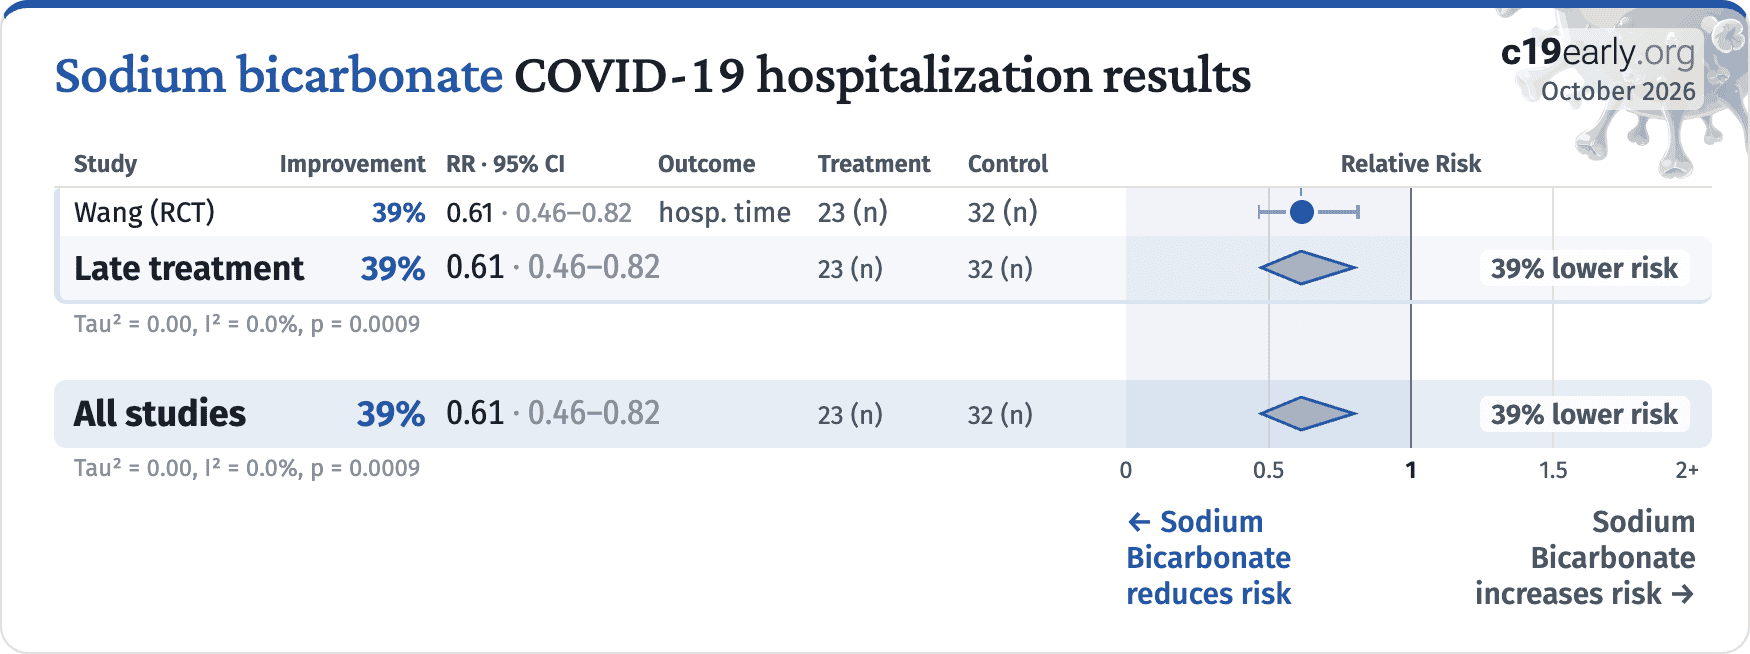
Sodium bicarbonate COVID-19 hospitalization results
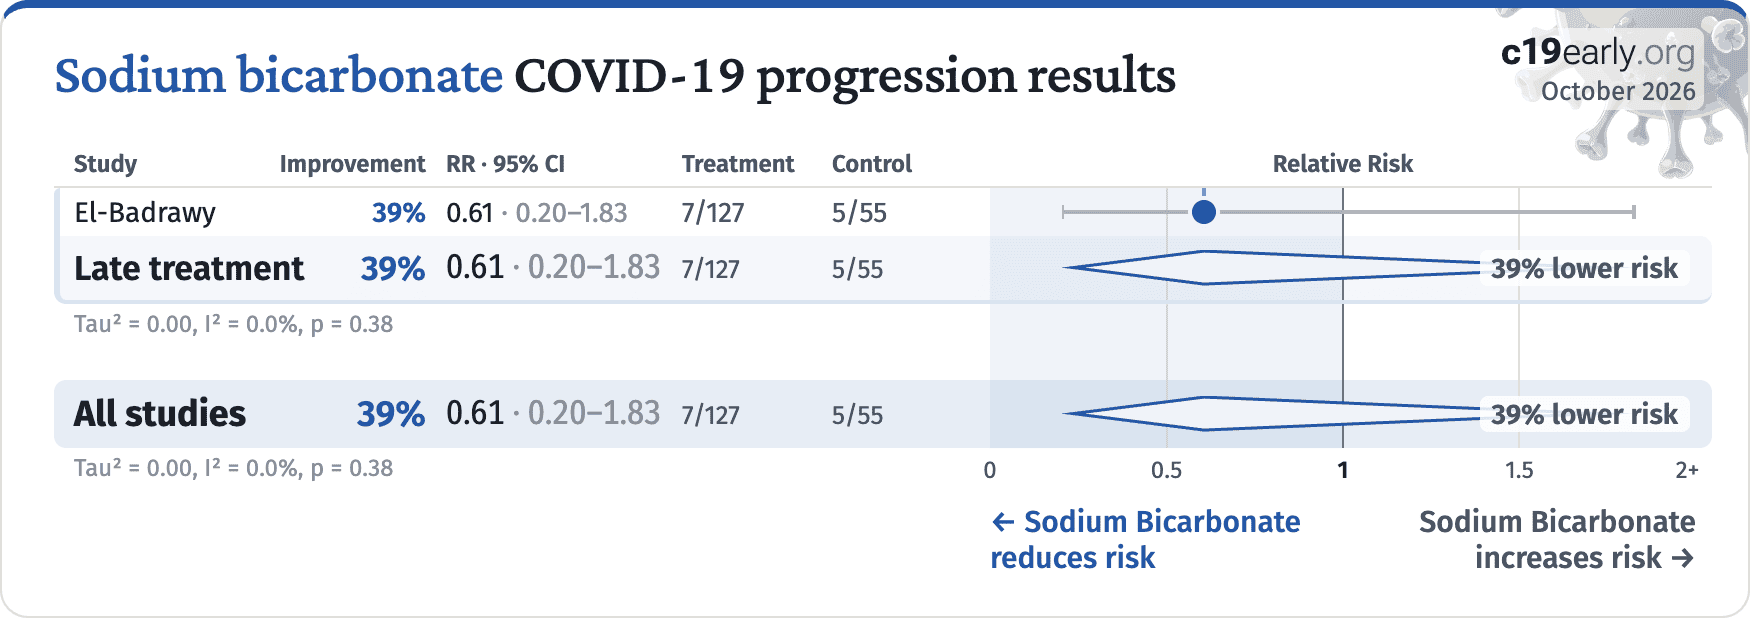
Sodium bicarbonate COVID-19 progression results
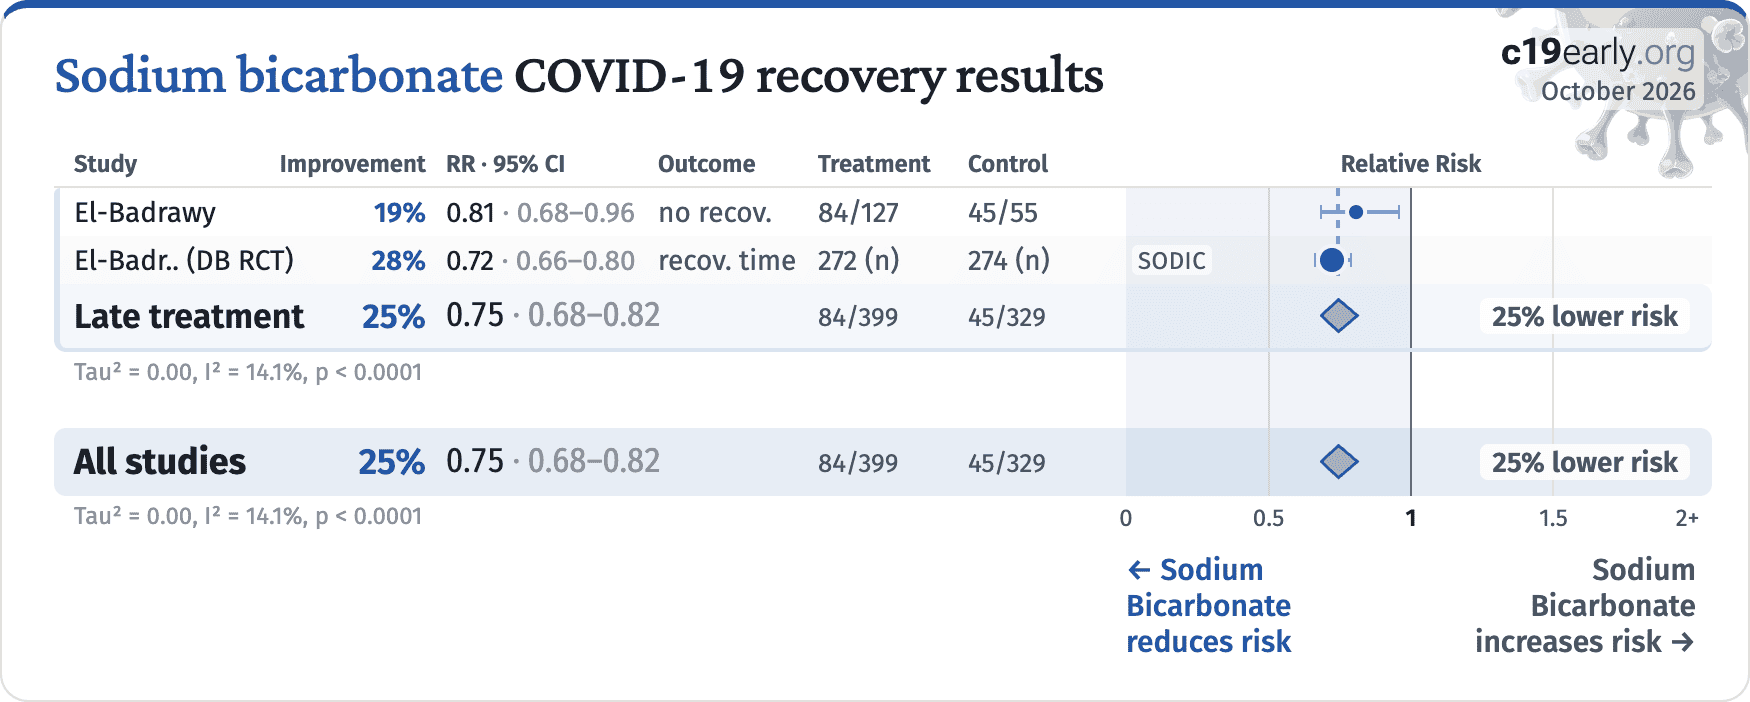
Sodium bicarbonate COVID-19 recovery results
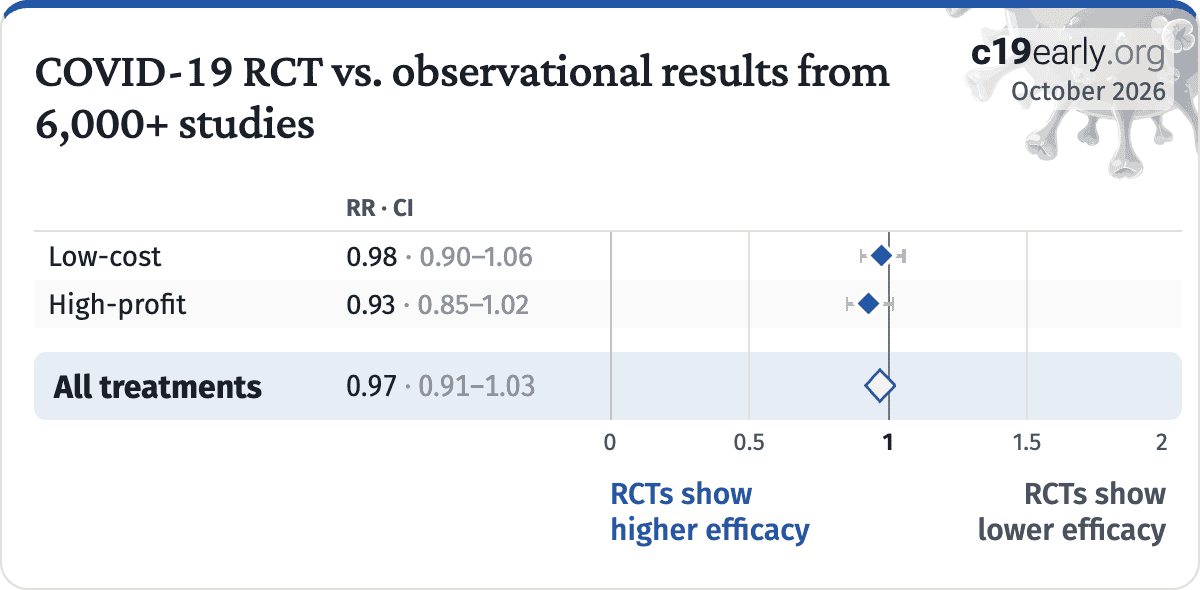
COVID-19 RCT vs. observational results from 6,000+ studies
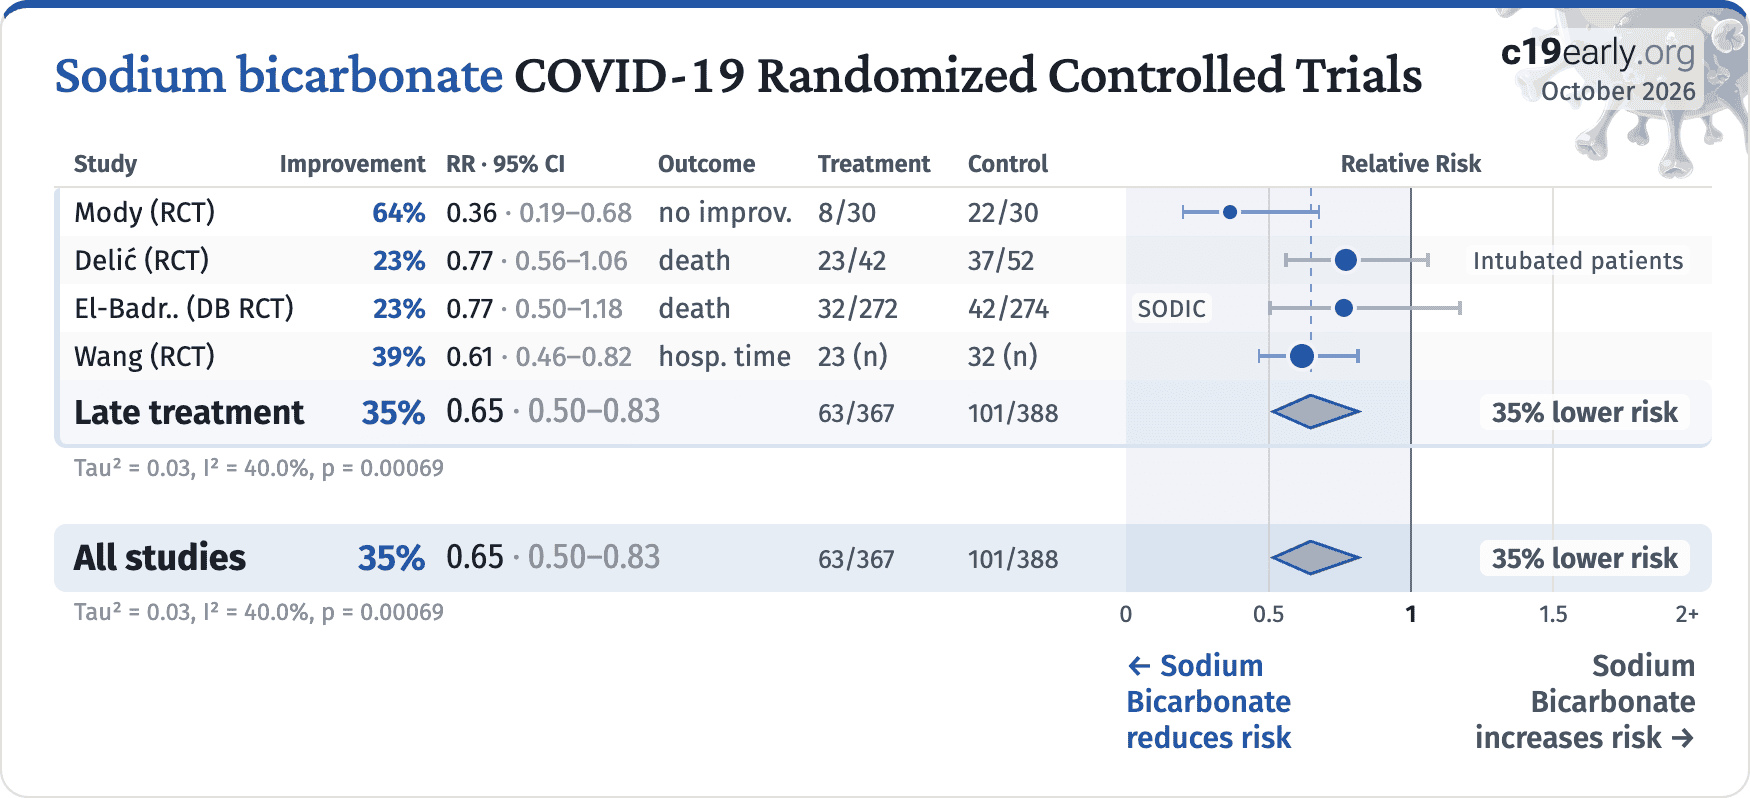
Sodium bicarbonate COVID-19 Randomized Controlled Trials
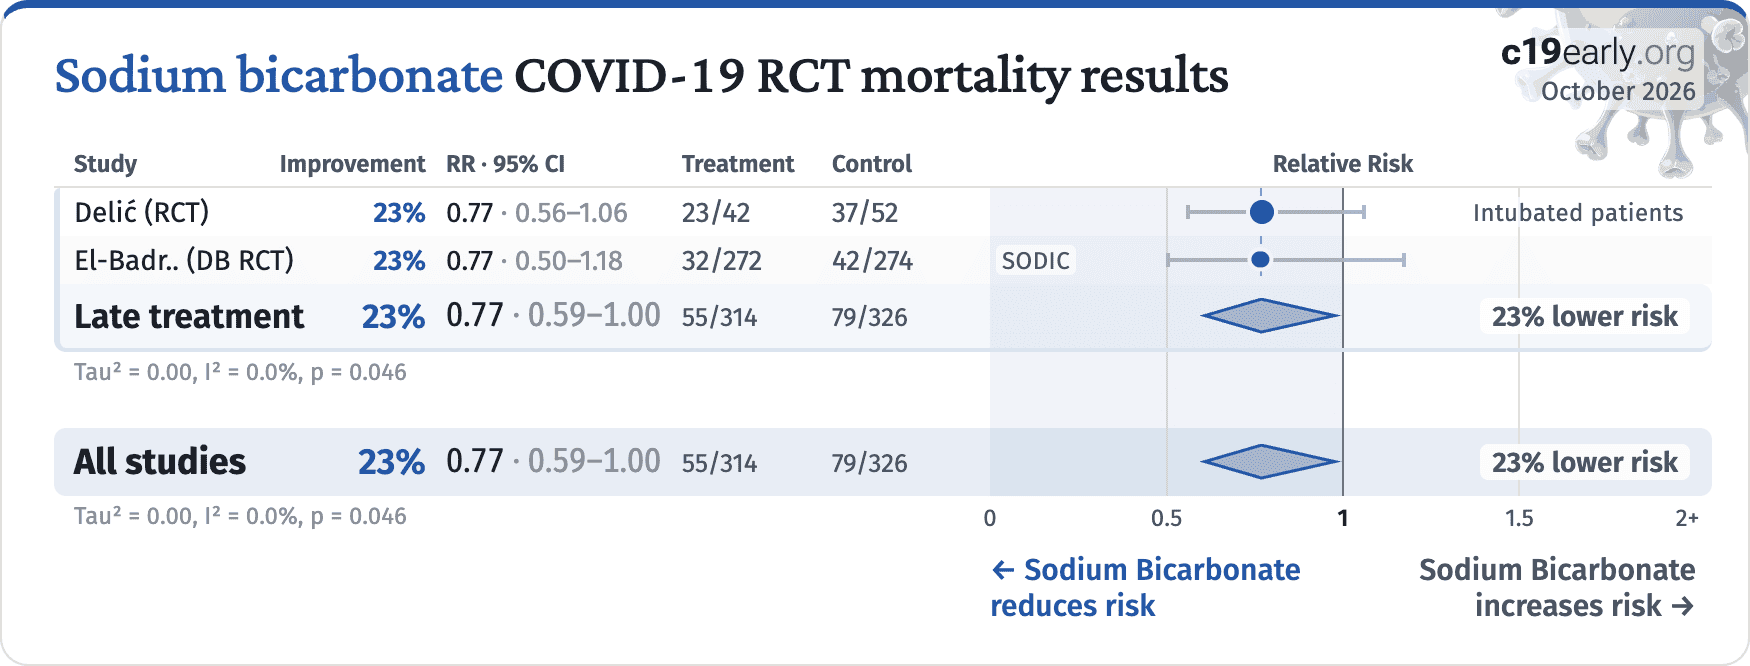
Sodium bicarbonate COVID-19 RCT mortality results
Media covered none of the 4 studies showing significantly lower risk
No positive sodium bicarbonate studies were covered
Media bias for low-cost COVID‑19 treatments
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
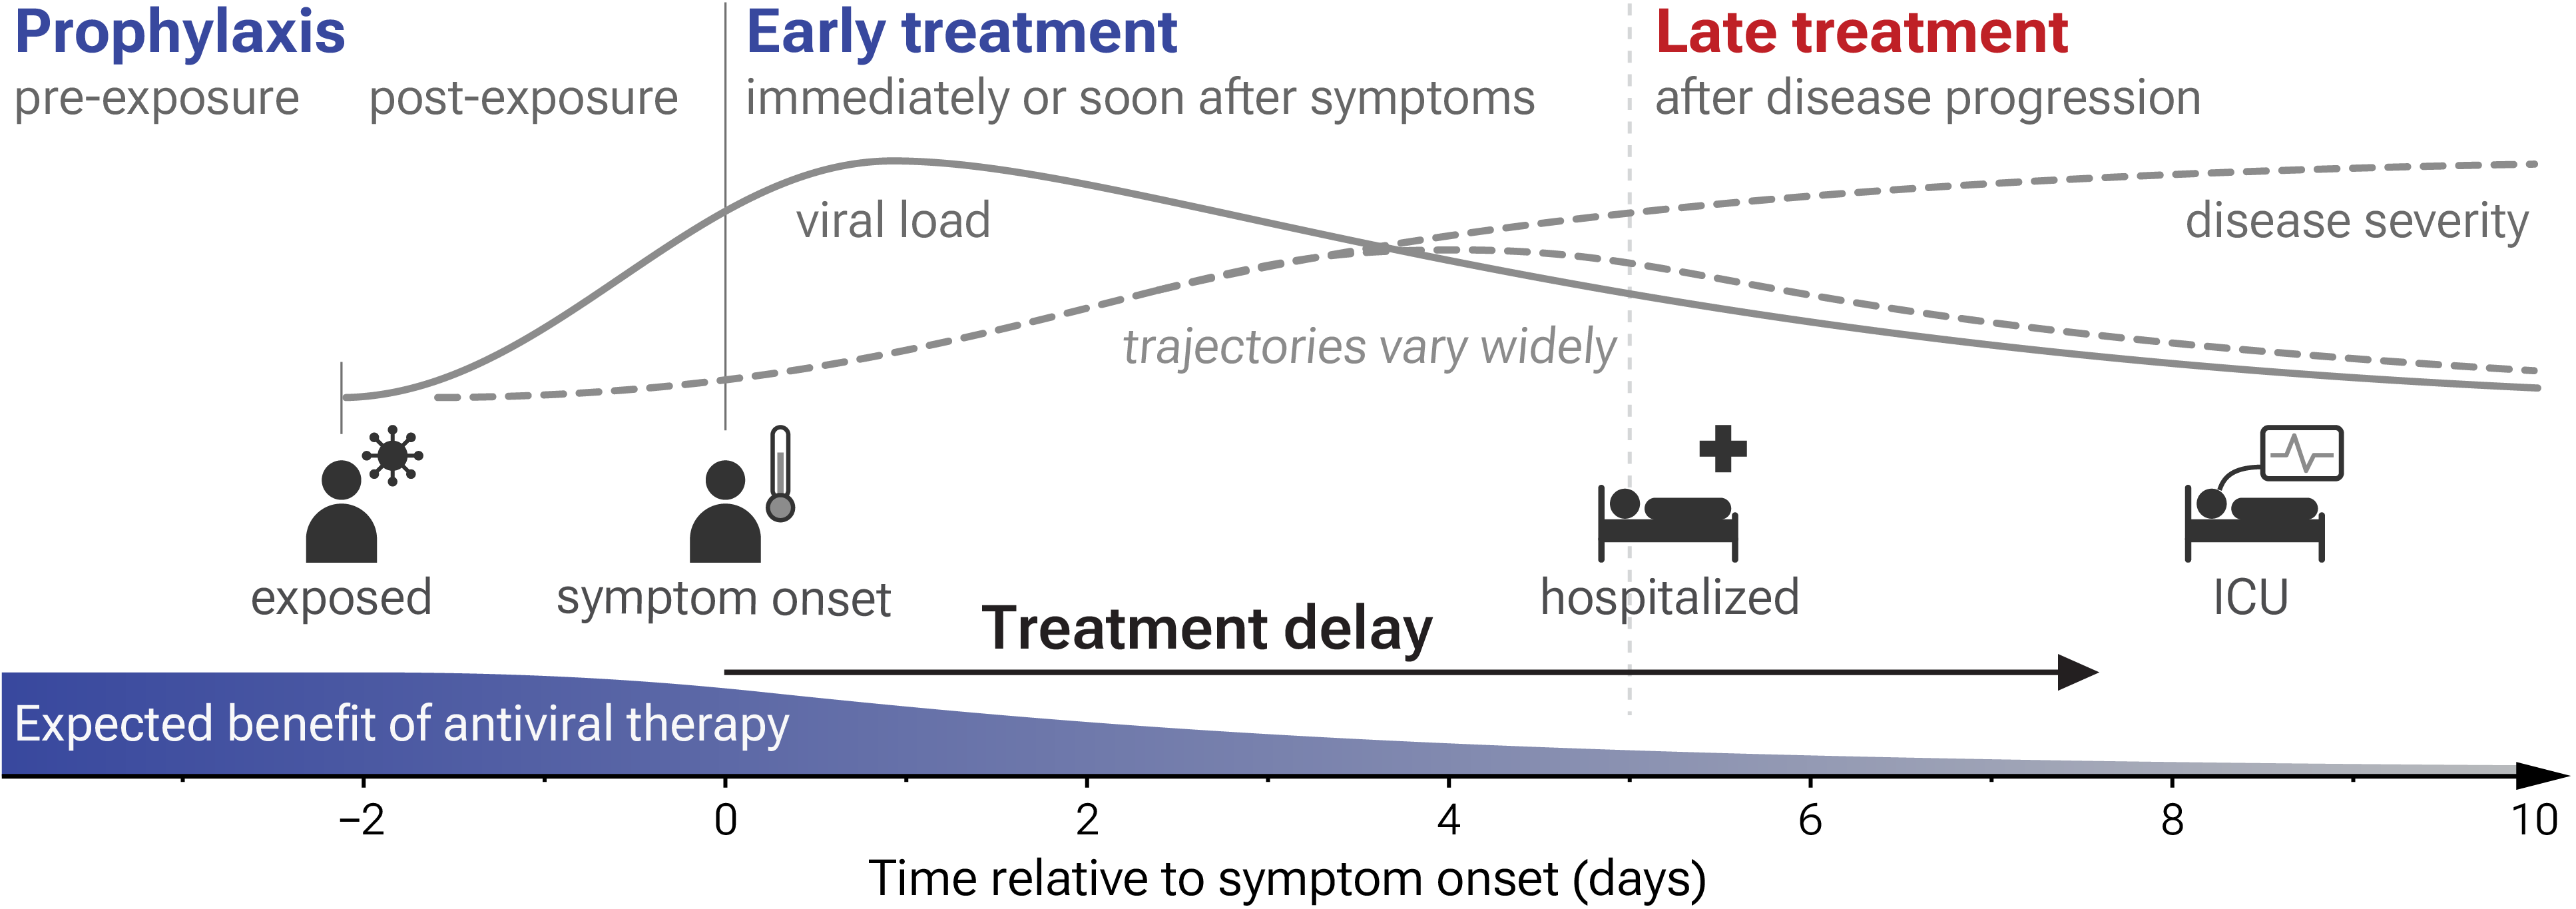
Early treatment is more effective: baloxavir marboxil
| Administration | Improvement | Studies |
|---|---|---|
| Nasal & oral | 88% [72‑95%] | 10 |
| Nasal spray/rinse | 59% [50‑66%] | 21 |
| Oral spray/rinse | 38% [25‑49%] | 11 |
| Virucidal action | Chemically inactivating or destroying the structure of viral particles |
| Blocking attachment | Binding to the virus or host cells to prevent viral attachment to host cells |
| Physical barrier | Forming a physical layer over the nasal mucosa preventing viral access to host cells |
| Physical removal | Mechanical washout/flushing of viral particles and mucus (e.g., large volume irrigation) |
| Mucociliary clearance | Stimulating the natural beating of nasal cilia to accelerate the clearing of trapped pathogens |
| Treatment | Mechanisms | Notes |
|---|---|---|
| Azelastine115 |
Antiviral: inhibits interaction between spike protein and ACE2 Antiviral: potential inhibition of viral protease (Mpro) Other: H1-receptor antagonist (antihistamine) Other: mast cell stabilizer |
Antihistamine. Designed to affect human receptors. Risks include dysgeusia, drowsiness, and nasal burning. |
| Cetylpyridinium Chloride116 |
Virucidal: disrupts viral lipid envelope Antiseptic: quaternary ammonium compound |
Chemical virucide. Common in mouthwashes. Can cause temporary staining of teeth or tongue irritation if used frequently. |
| Chlorhexidine117 |
Virucidal: disrupts viral lipid membranes Antiseptic: cationic polybiguanide |
Chemical virucide. May cause tooth staining and altered taste. |
| Chlorpheniramine118 |
Antiviral: binds to viral spike protein to block entry Antiviral: high affinity for viral transport proteins Other: H1-receptor antagonist (1st generation antihistamine) Other: anticholinergic activity |
Antihistamine. Stronger systemic risks than azelastine. Known to cause significant sedation/drowsiness and cognitive impairment. |
| Hydrogen Peroxide119 |
Virucidal: oxidizing agent that destroys viral parts Other: tissue debridement |
Chemical virucide. Can be toxic to healthy tissue if concentration is too high (>1%). Long-term safety on nasal mucosa is debated. |
| Hypochlorous Acid120 |
Virucidal: oxidizes viral proteins, causing aggregation and loss of function. Impairs spike-ACE2 binding Antiseptic: broad-spectrum antimicrobial activity via oxidative damage to microbial proteins and membranes |
Chemical virucide. Activity depends on concentration, pH, and contact time. Saliva may reduce activity. |
| Inhaled Heparin121 |
Antiviral: acts as a decoy receptor (mimics heparan sulfate) Antiviral: anti-inflammatory effects on lung tissue Other: Anticoagulant |
Anticoagulant. Use requires caution regarding bleeding risks. |
| Iota-carrageenan122 |
Barrier: forms a viscous physical layer on mucosa Trap: electrostatistically traps virus particles (mimics cell surface) |
Physical barrier. High safety profile for daily use. |
| NaCl123 |
Cleaning: physically washes away viral particles Support: moisturizes mucosa to support natural immune barrier |
Physical wash. High degree of safety, reduces viral load via physical removal. |
| Nitric Oxide124 |
Virucidal: physically damages viral structure via nitrosylation Other: vasodilator (relaxes blood vessels) in systemic use |
Virucide/drug hybrid. In nasal spray form, it acts primarily as a topical disinfectant. Rapidly cleared, so systemic vasodilation risks are low but present. |
| Phthalocyanine125 |
Virucidal: generates reactive oxygen species (ROS) when exposed to light to kill virus Other: photosensitizer |
Chemical virucide. A synthetic compound often used in photodynamic therapy. Works by creating an oxidative environment hostile to the virus. |
| Povidone-Iodine126 |
Virucidal: oxidizes viral proteins and destabilizes membrane structures Antiseptic: broad-spectrum bacterial/fungal killer |
Chemical virucide. Highly effective but risk of thyroid absorption with chronic use. Can be irritating to mucous membranes. |
| Sodium Bicarbonate |
Environment: raises pH to inhibit viral fusion Cleaning: improves mucociliary clearance (washing) |
Physical/chemical environment. Changes the environment rather than attacking the virus directly. High degree of safety. |
| Treatment | Microbiome disruption potential | Notes |
|---|---|---|
| Iota-carrageenan122 | Low | Primarily antiviral, however extended use may mildly affect the microbiome |
| Nitric Oxide124 | Low to moderate | More selective towards pathogens, however excessive concentrations or prolonged use may disrupt the balance of bacteria |
| Alkalinization2 | Moderate | Increases pH, negatively impacting beneficial microbes that thrive in a slightly acidic environment |
| Cetylpyridinium Chloride116 | Moderate | Quaternary ammonium broad-spectrum antiseptic that can disrupt beneficial and harmful bacteria |
| Hypochlorous Acid120 | Moderate | Broad-spectrum oxidizing antiseptic that may affect beneficial and harmful bacteria |
| Phthalocyanine125 | Moderate to high | Photodynamic compound with antimicrobial activity, likely to affect the microbiome |
| Chlorhexidine117 | High | Potent antiseptic with broad activity, significantly disrupts the microbiome |
| Hydrogen Peroxide119 | High | Strong oxidizer, harming both beneficial and harmful microbes |
| Povidone-Iodine126 | High | Potent broad-spectrum antiseptic harmful to beneficial microbes |
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →
Inhalation of nebulized sodium bicarbonate 8.4% (5ml every 4h) 7:00am to 23:00pm every day for 30 days together with 8.4% nasal drops 4 times daily (three drops for each nostril).
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →
Authors note that contacts of index cases also received sodium bicarbonate treatment, with none reporting COVID-19.
Inhalation of nebulized sodium bicarbonate 8.4% (5ml every 4h) 7:00am to 23:00pm every day for 30 days together with 8.4% nasal drops 4 times daily (three drops for each nostril).
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →
Nasal and oral inhalation of nebulized 50ml 8.4% sodium bicarbonate for 5 minutes twice daily for 5 days.
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →
Bronchoalveolar lavage with 10ml of sodium bicarbonate solution directly into the tube (closed circuit), 500μl for each lung segment, followed by aspiration of the solution, performed every 6 hours for 7 days.
Bicarbonate
reduces riskSodium Bicarbonate
increases risk →

| Delić, 5/28/2022, Randomized Controlled Trial, Croatia, peer-reviewed, 12 authors, study period October 2020 - June 2021, trial NCT04755972 (history). | risk of death, 23.0% lower, RR 0.77, p = 0.13, treatment 23 of 42 (54.8%), control 37 of 52 (71.2%), NNT 6.1, ICU mortality. |
| risk of death, 20.1% lower, RR 0.80, p = 0.30, treatment 20 of 42 (47.6%), control 31 of 52 (59.6%), NNT 8.3, 28 day mortality. | |
| El-Badrawy, 11/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Egypt, peer-reviewed, 8 authors, study period 2 September, 2021 - 30 April, 2022, trial NCT05035524 (history) (SODIC). | risk of death, 23.2% lower, RR 0.77, p = 0.26, treatment 32 of 272 (11.8%), control 42 of 274 (15.3%), NNT 28, all cases. |
| risk of death, 54.8% lower, RR 0.45, p = 0.02, treatment 12 of 247 (4.9%), control 27 of 251 (10.8%), NNT 17, mild/moderate/severe cases. | |
| risk of death, 79.2% lower, RR 0.21, p = 0.21, treatment 1 of 125 (0.8%), control 5 of 130 (3.8%), NNT 33, moderate cases. | |
| risk of death, 53.2% lower, RR 0.47, p = 0.02, treatment 11 of 63 (17.5%), control 22 of 59 (37.3%), NNT 5.0, severe cases. | |
| risk of death, 22.7% higher, RR 1.23, p = 0.33, treatment 20 of 25 (80.0%), control 15 of 23 (65.2%), critical cases. | |
| recovery time, 27.6% lower, relative time 0.72, p < 0.001, treatment mean 4.2 (±2.5) n=272, control mean 5.8 (±3.1) n=274, time to clinical improvement. | |
| CT score, 33.3% lower, RR 0.67, p = 0.001, treatment 238, control 229, CT score, day 30. | |
| El-Badrawy (B), 6/12/2022, prospective, Egypt, peer-reviewed, 7 authors, study period 15 April, 2020 - 31 August, 2020, trial NCT04374591 (history). | risk of death, 56.7% lower, RR 0.43, p = 0.37, treatment 3 of 127 (2.4%), control 3 of 55 (5.5%), NNT 32. |
| risk of progression, 39.4% lower, RR 0.61, p = 0.52, treatment 7 of 127 (5.5%), control 5 of 55 (9.1%), NNT 28, deterioration or death, day 30. | |
| risk of no recovery, 19.2% lower, RR 0.81, p = 0.03, treatment 84 of 127 (66.1%), control 45 of 55 (81.8%), NNT 6.4, day 30. | |
| relative CT score, 72.7% better, RR 0.27, p < 0.001, treatment 127, control 55, day 30. | |
| recovery time, 66.2% lower, relative time 0.34, p < 0.001, treatment mean 3.31 (±0.99) n=127, control mean 9.79 (±6.29) n=55, time to clinical improvement. | |
| Mody, 3/19/2021, Randomized Controlled Trial, India, peer-reviewed, 1 author, study period July 2020 - September 2020, trial CTRI/2020/07/026535. | risk of no improvement, 63.6% lower, RR 0.36, p < 0.001, treatment 8 of 30 (26.7%), control 22 of 30 (73.3%), NNT 2.1. |
| Soares, 12/29/2021, prospective, Brazil, peer-reviewed, 17 authors, study period December 2020 - May 2021. | risk of death, 75.8% lower, RR 0.24, p < 0.001, treatment 6 of 44 (13.6%), control 18 of 32 (56.2%), NNT 2.3. |
| Wang (B), 3/15/2023, Randomized Controlled Trial, China, peer-reviewed, 13 authors. | hospitalization time, 38.5% lower, relative time 0.61, p < 0.001, treatment mean 7.7 (±4.15) n=23, control mean 12.53 (±5.56) n=32. |