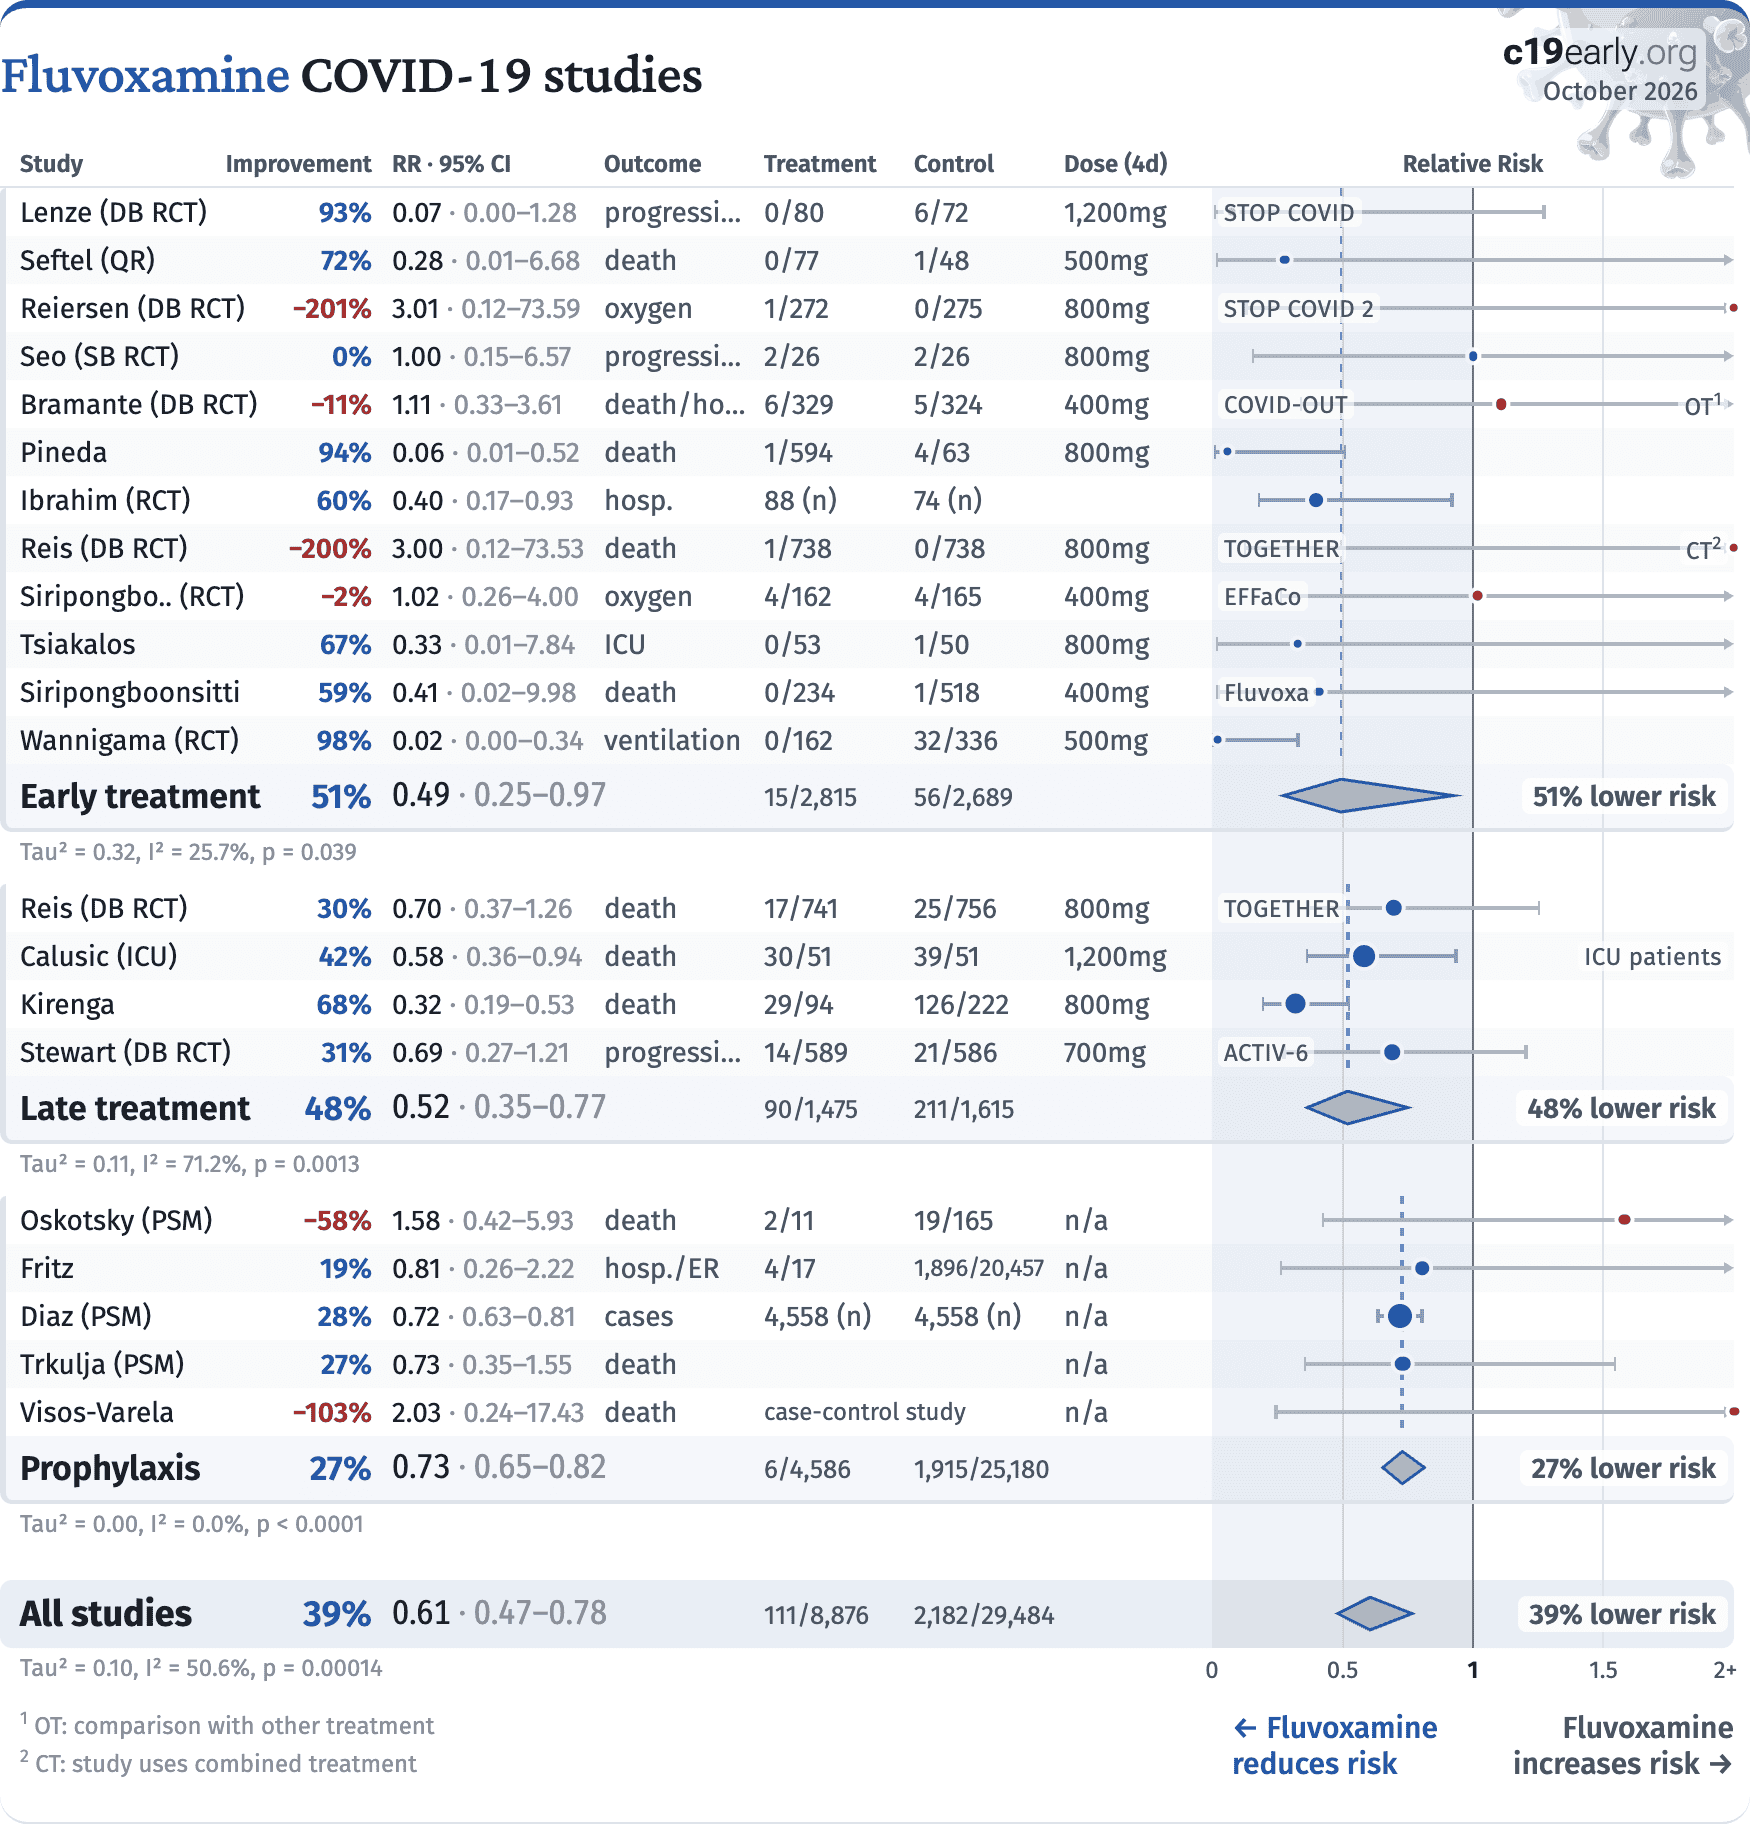
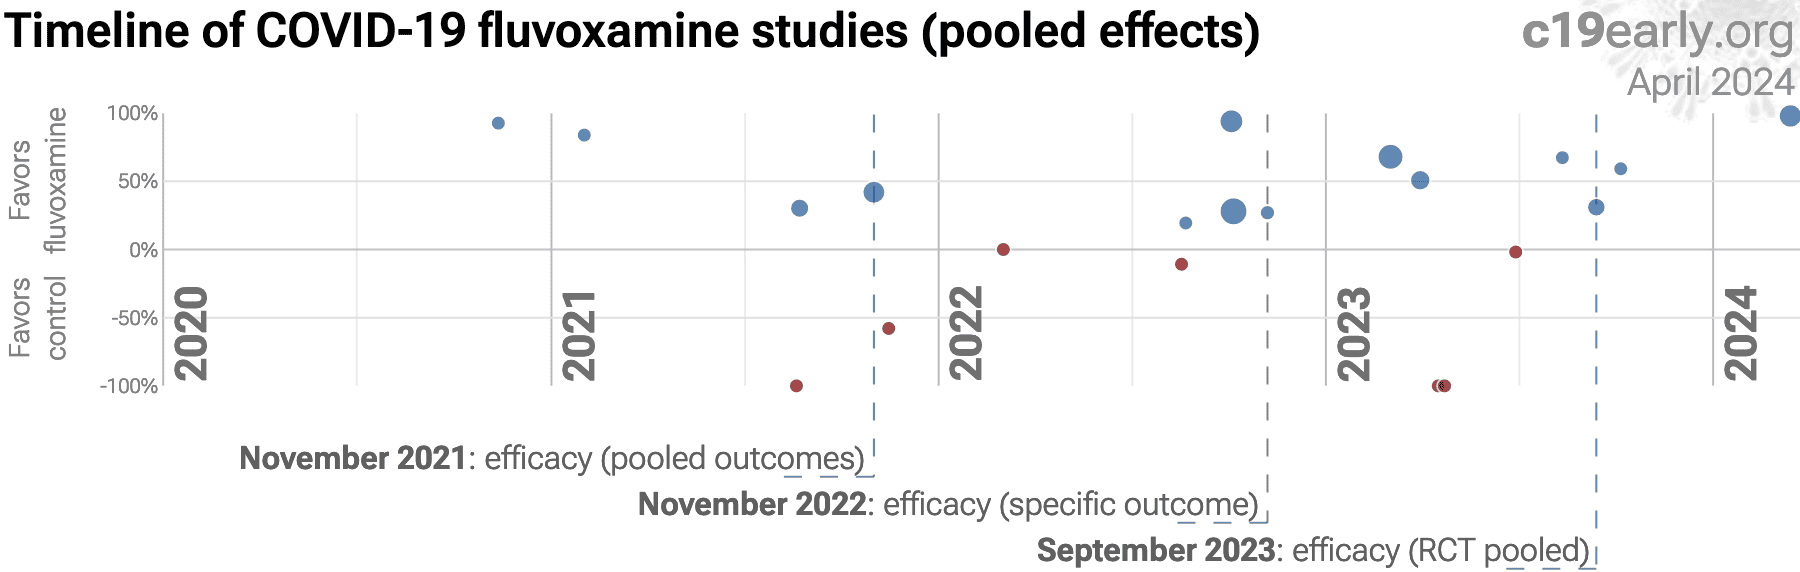
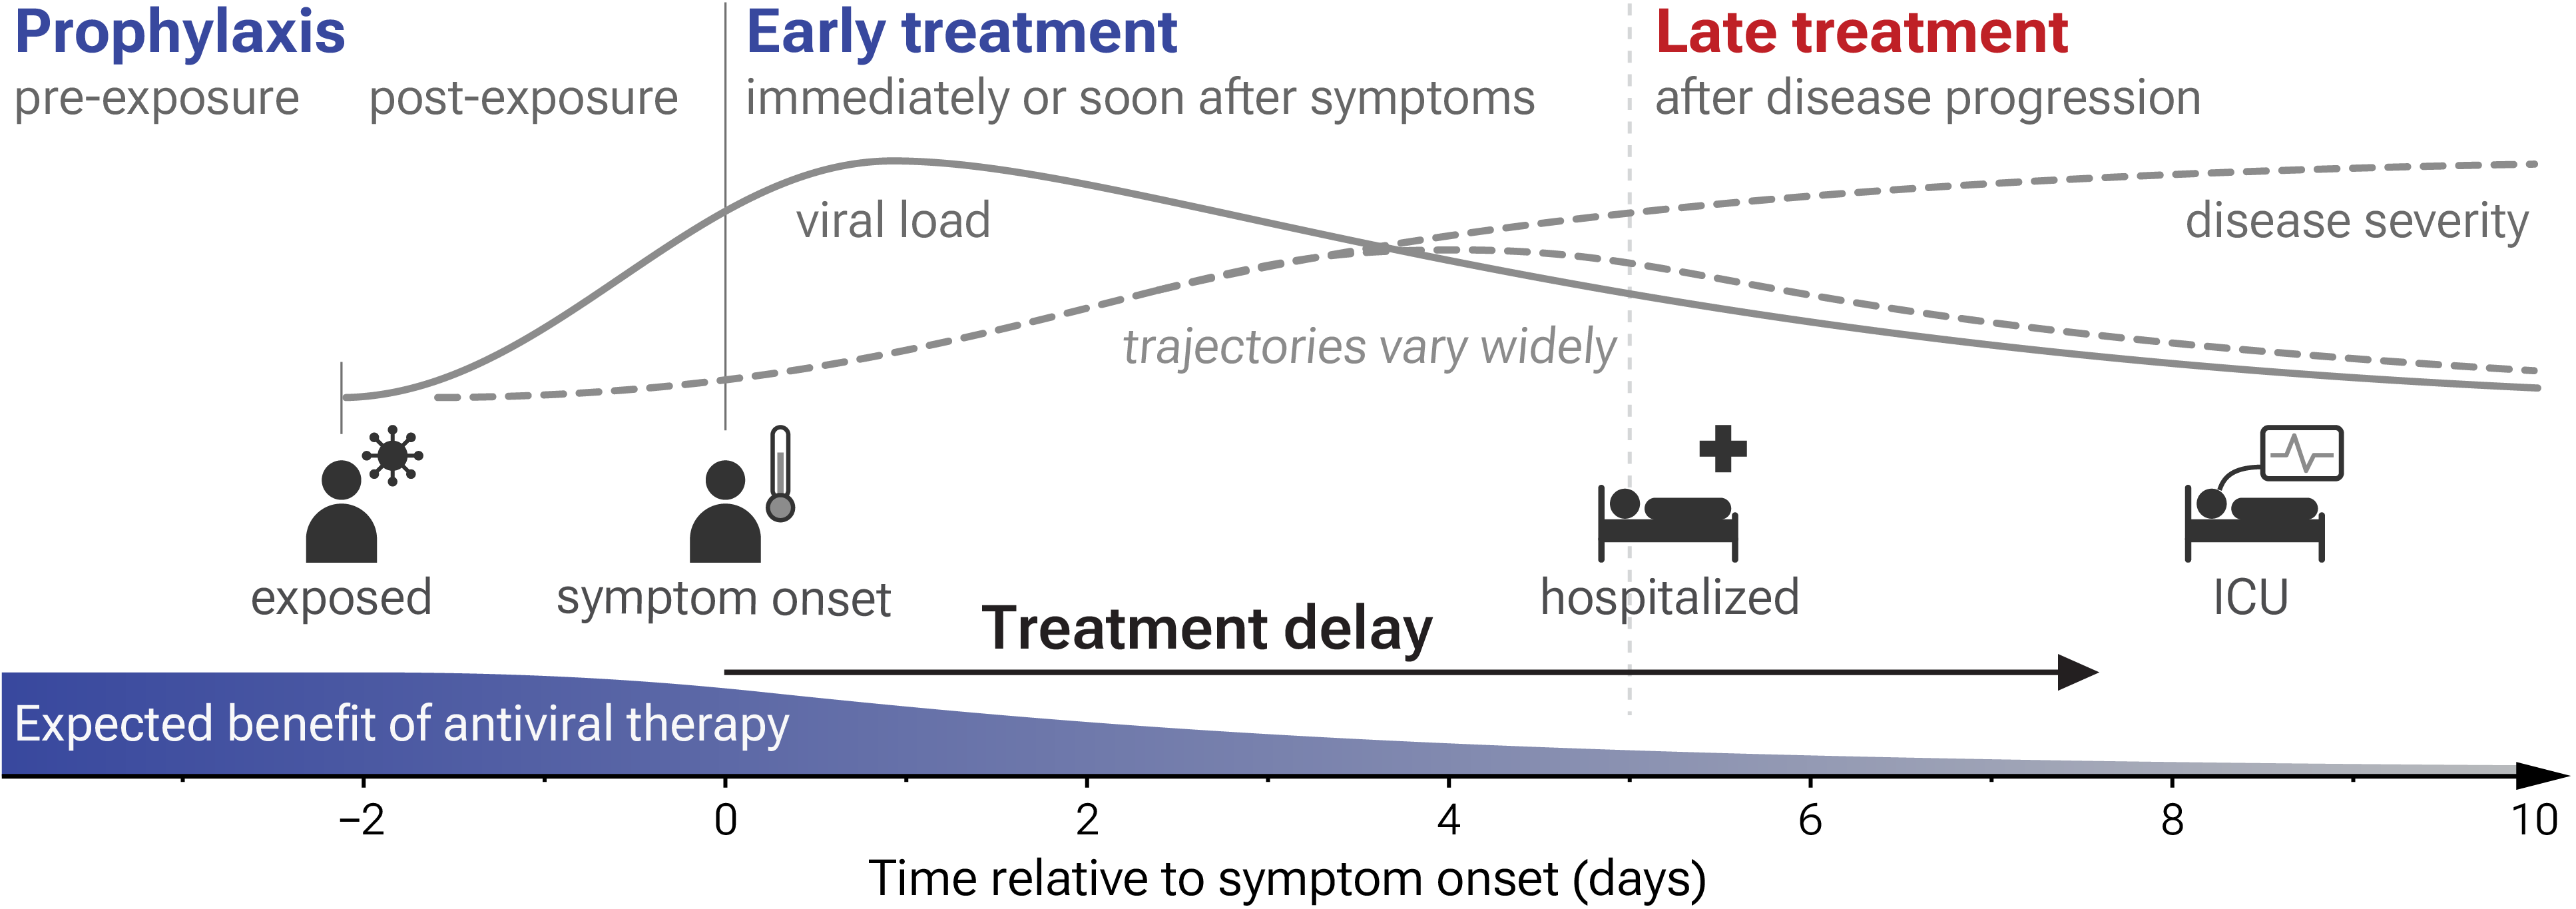
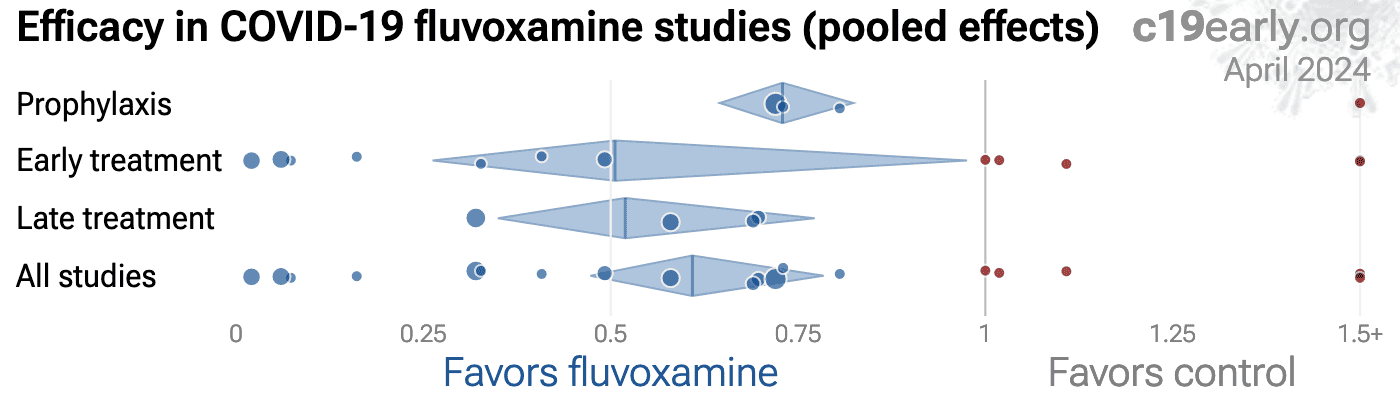
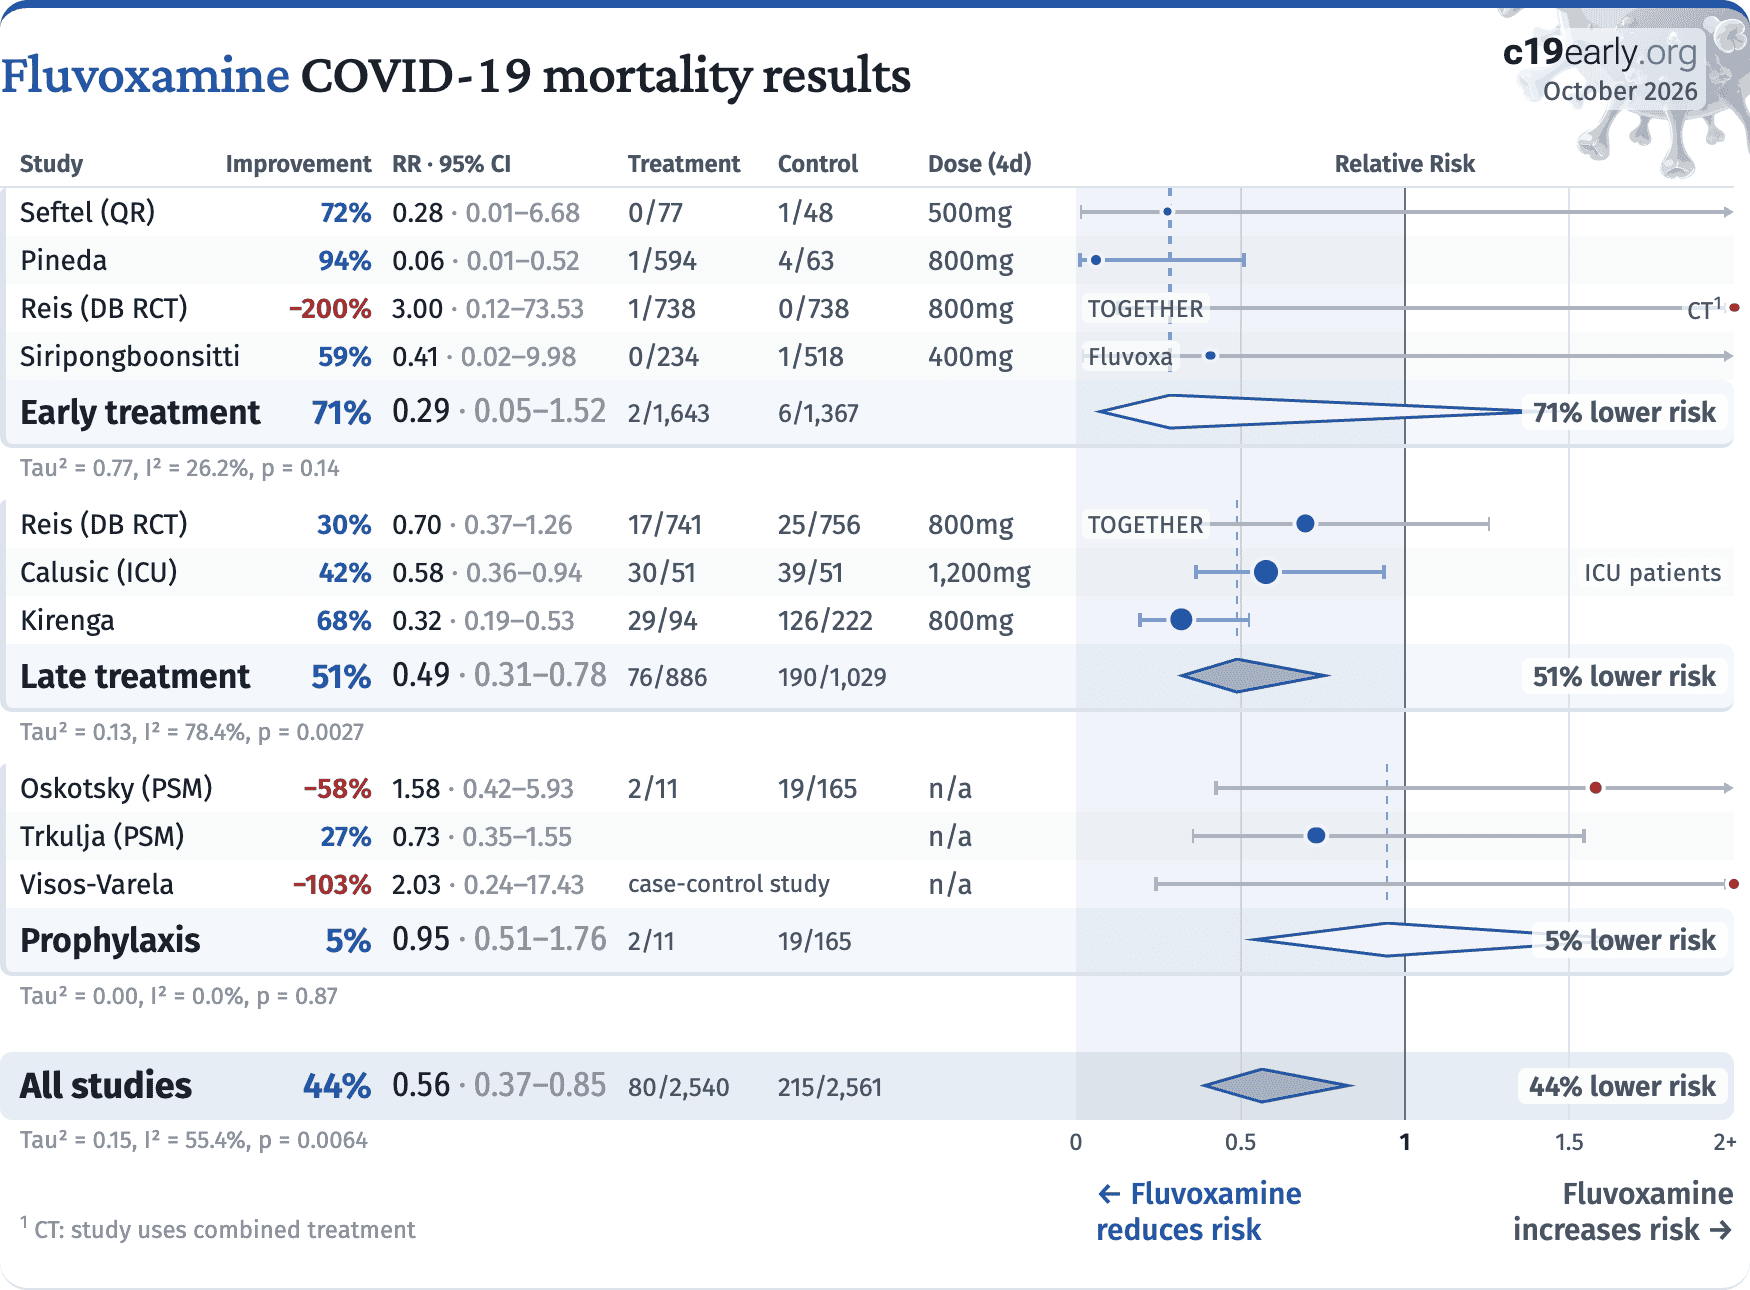
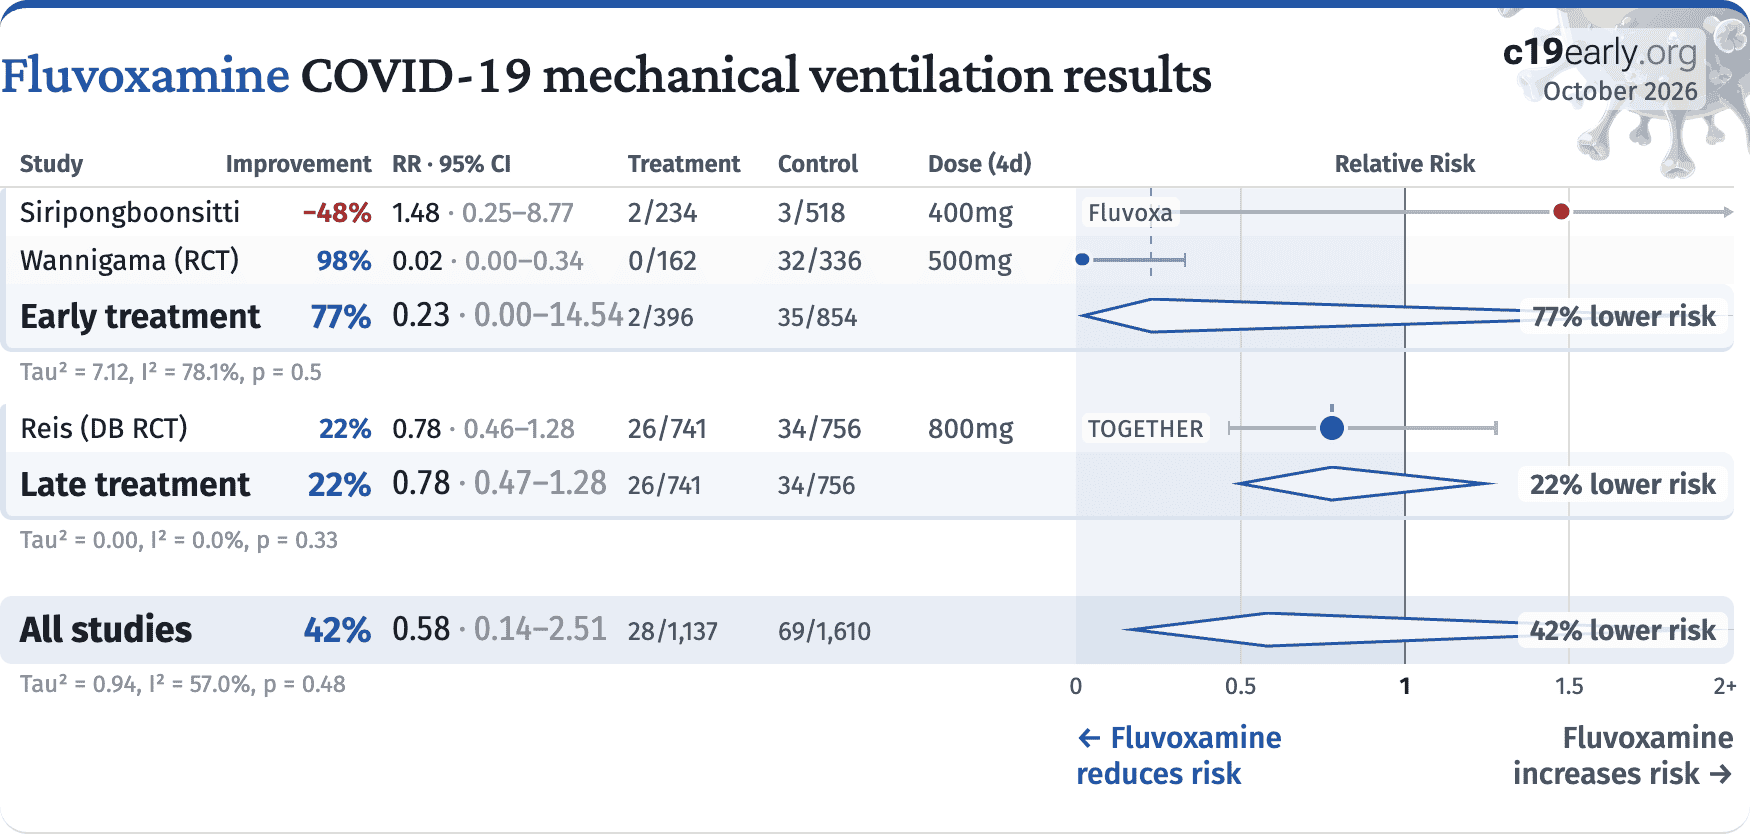
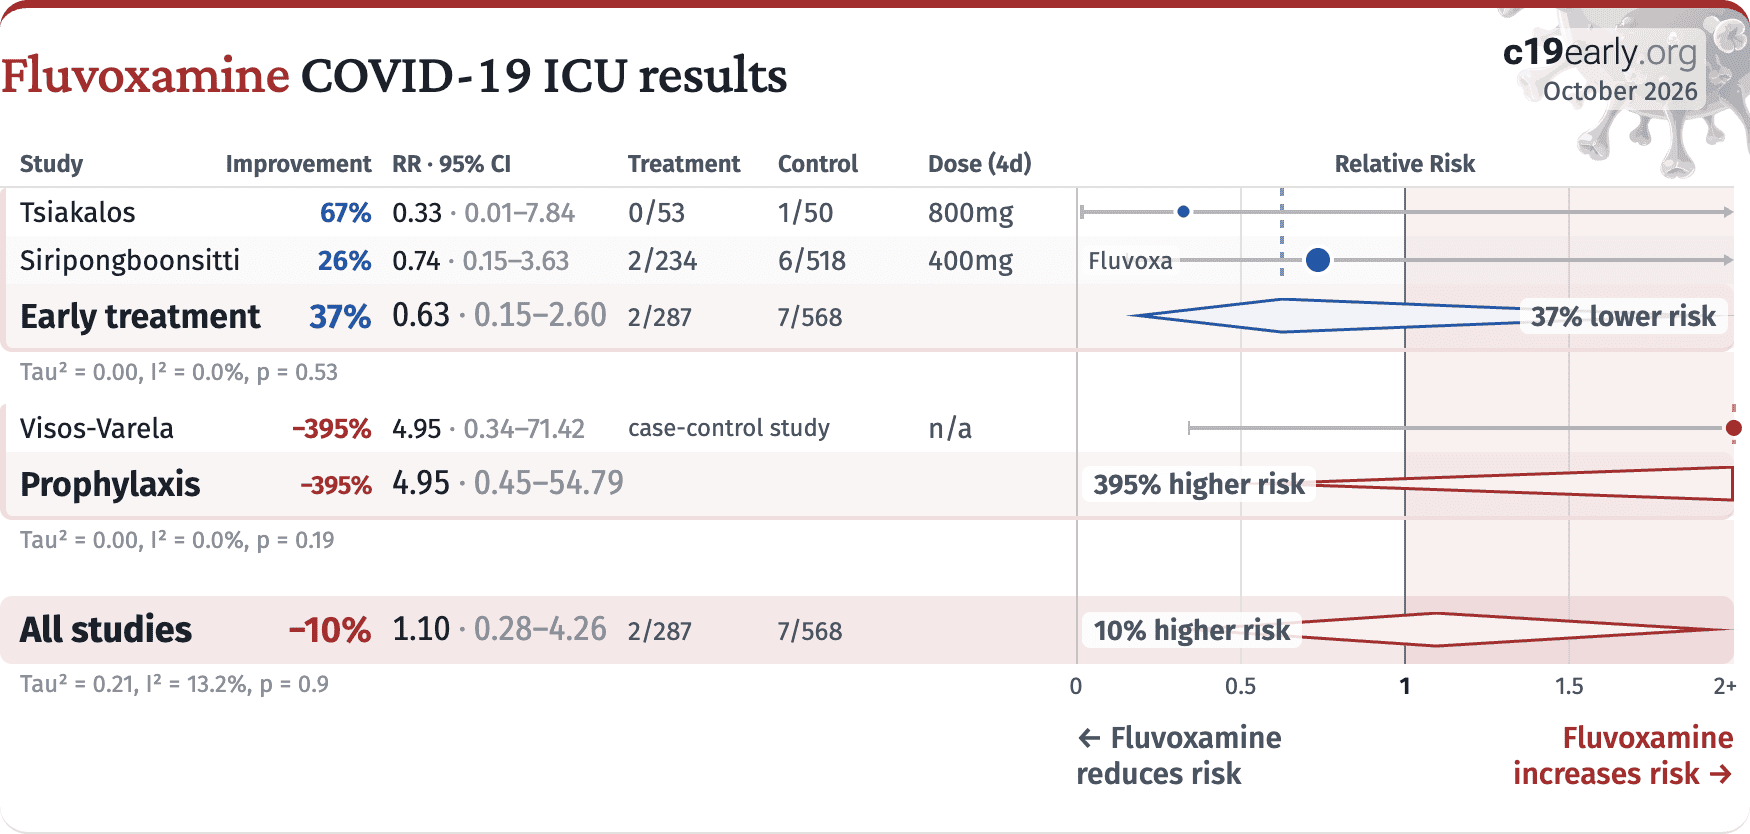
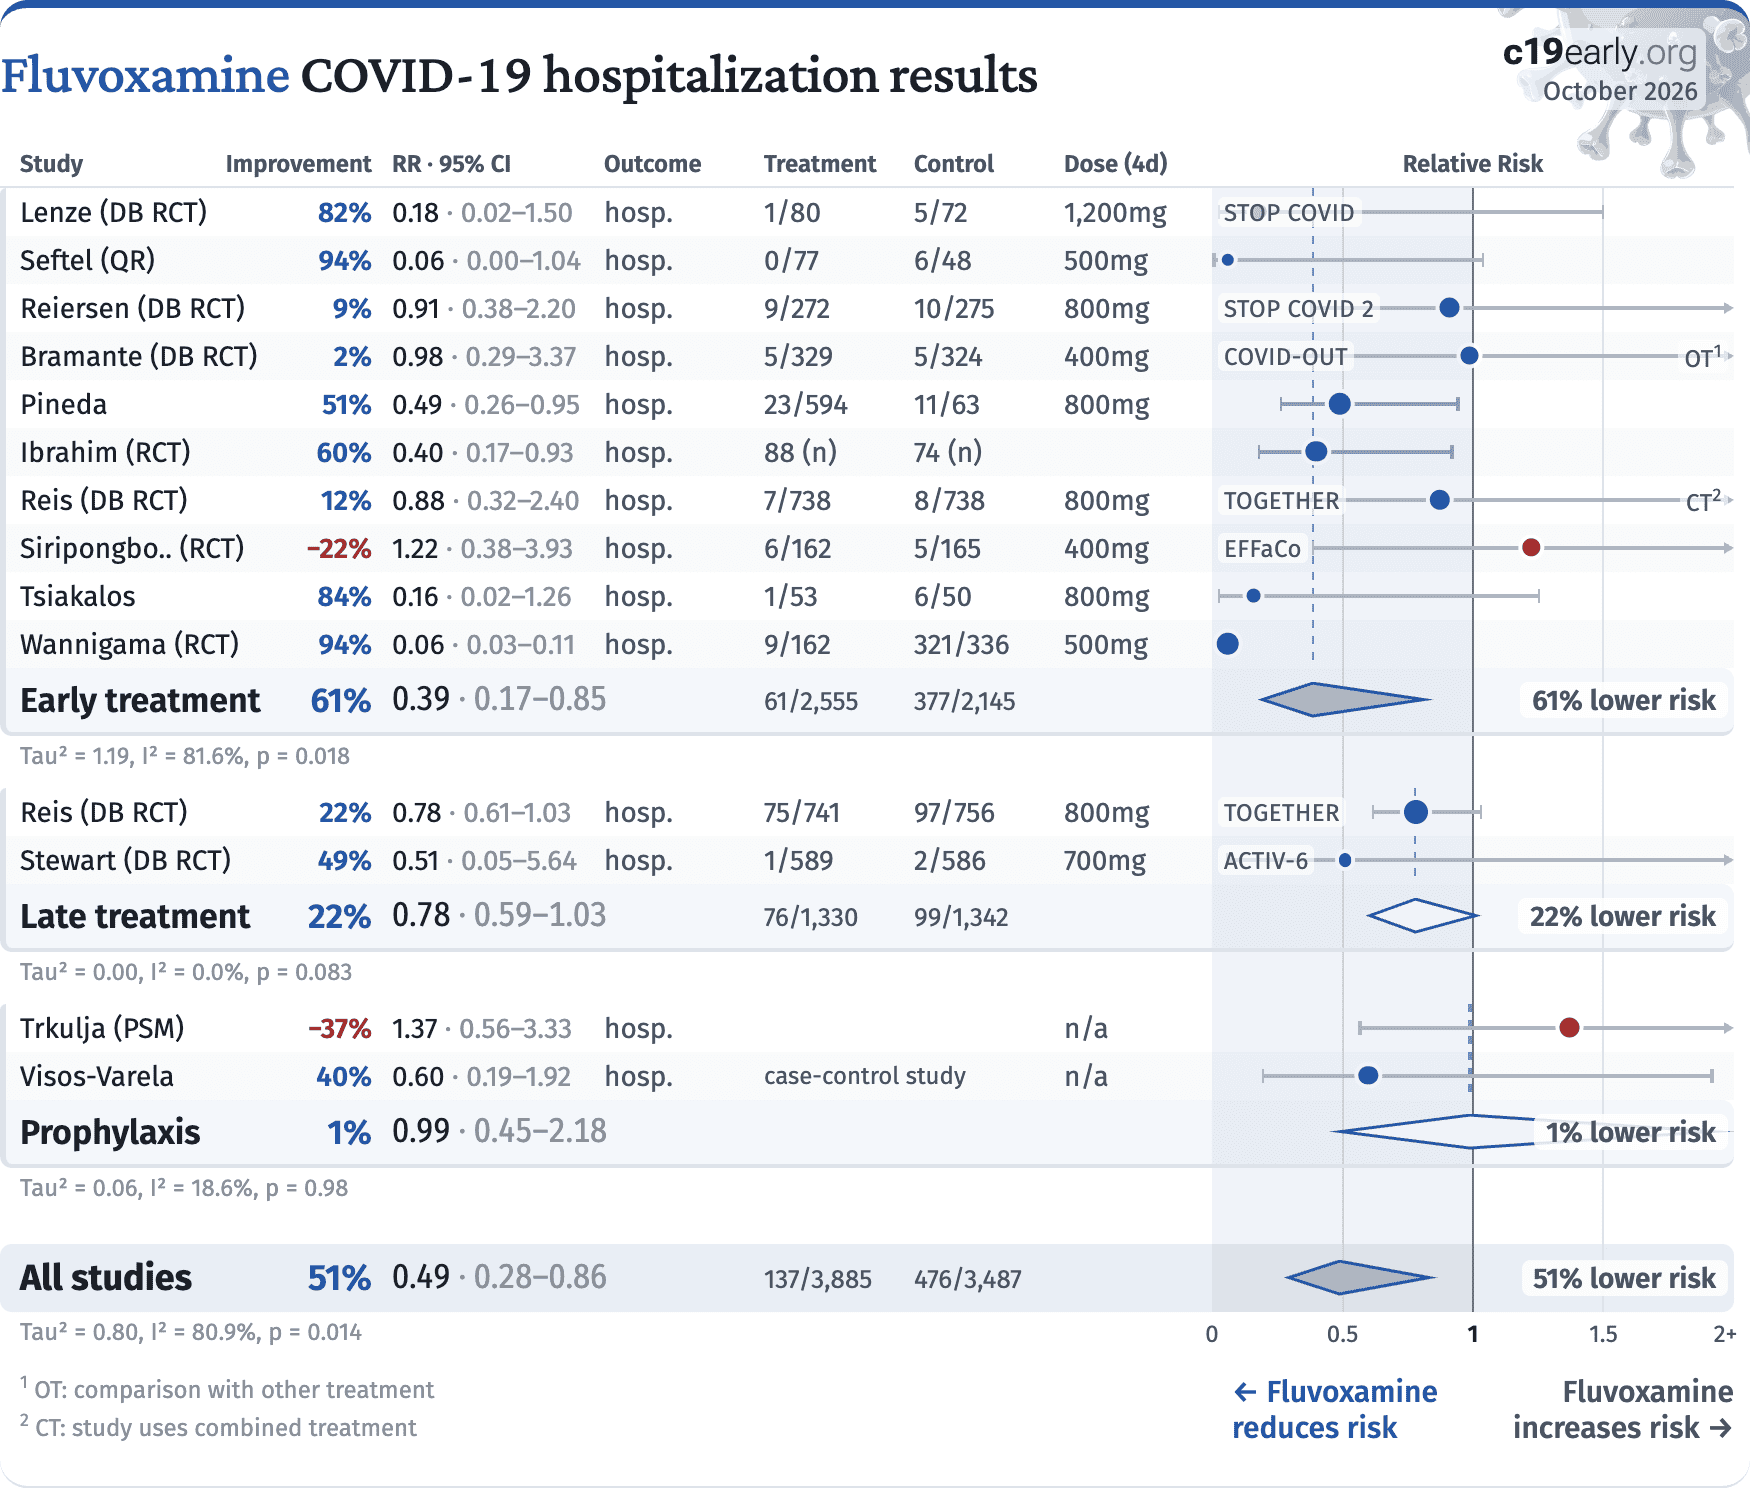
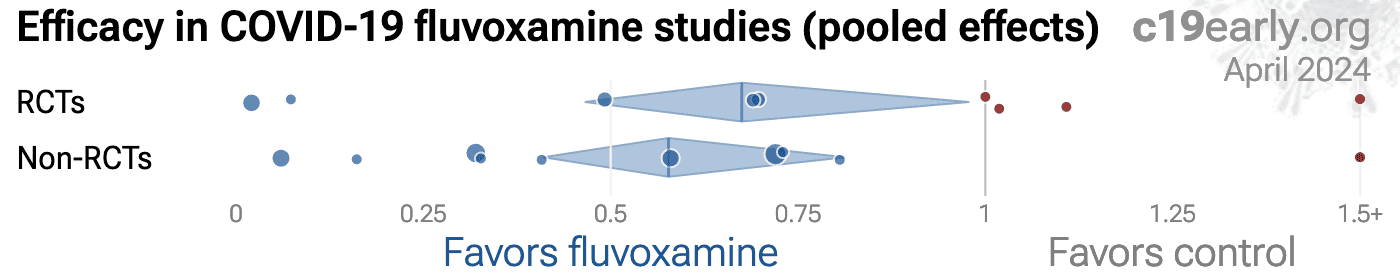
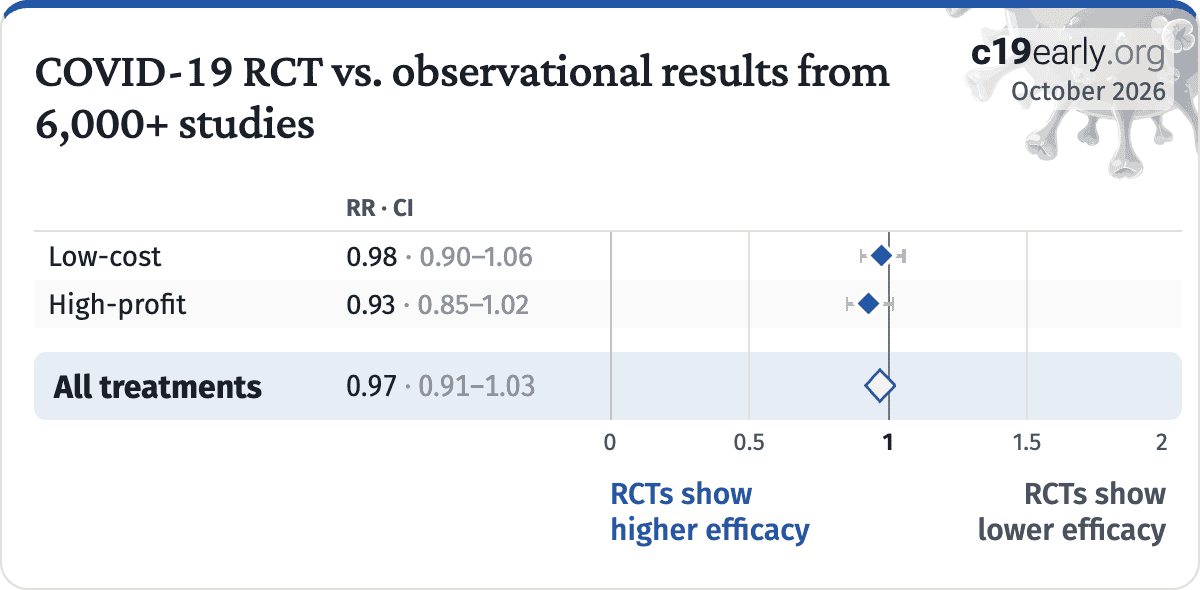
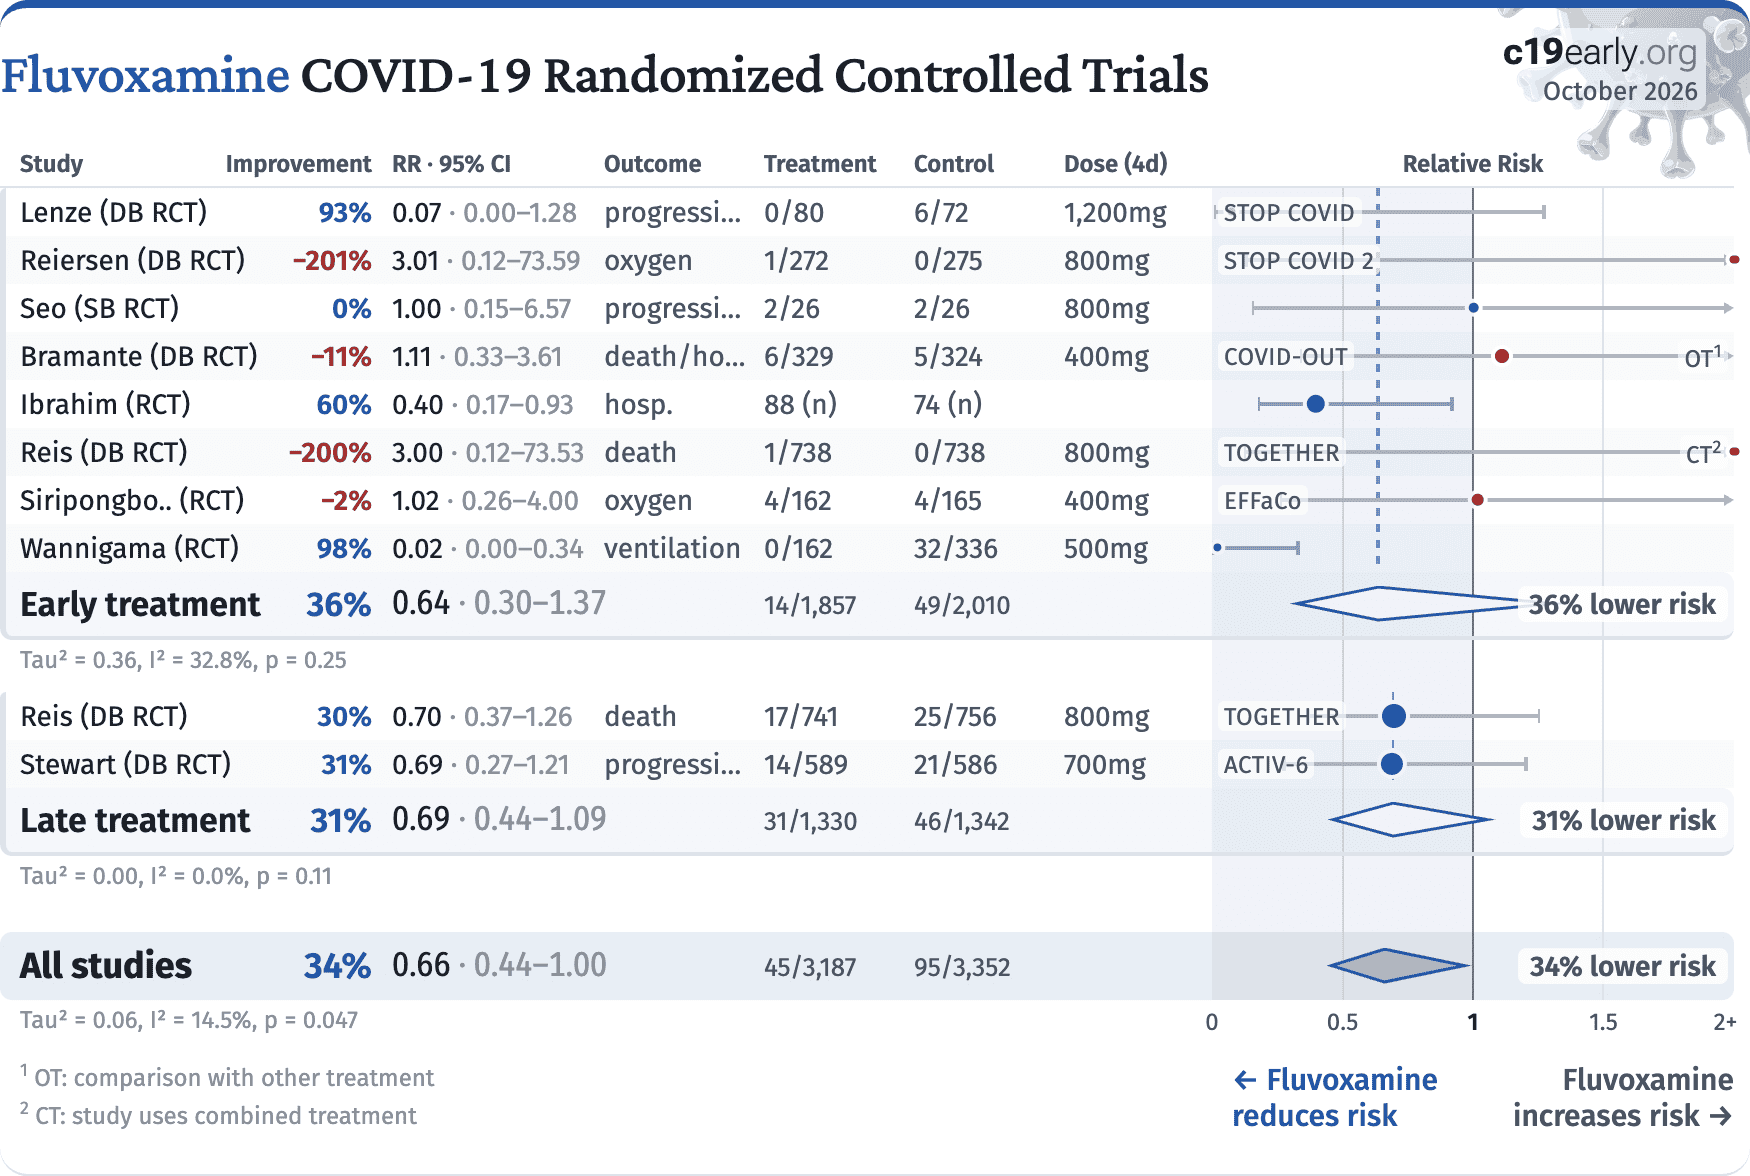
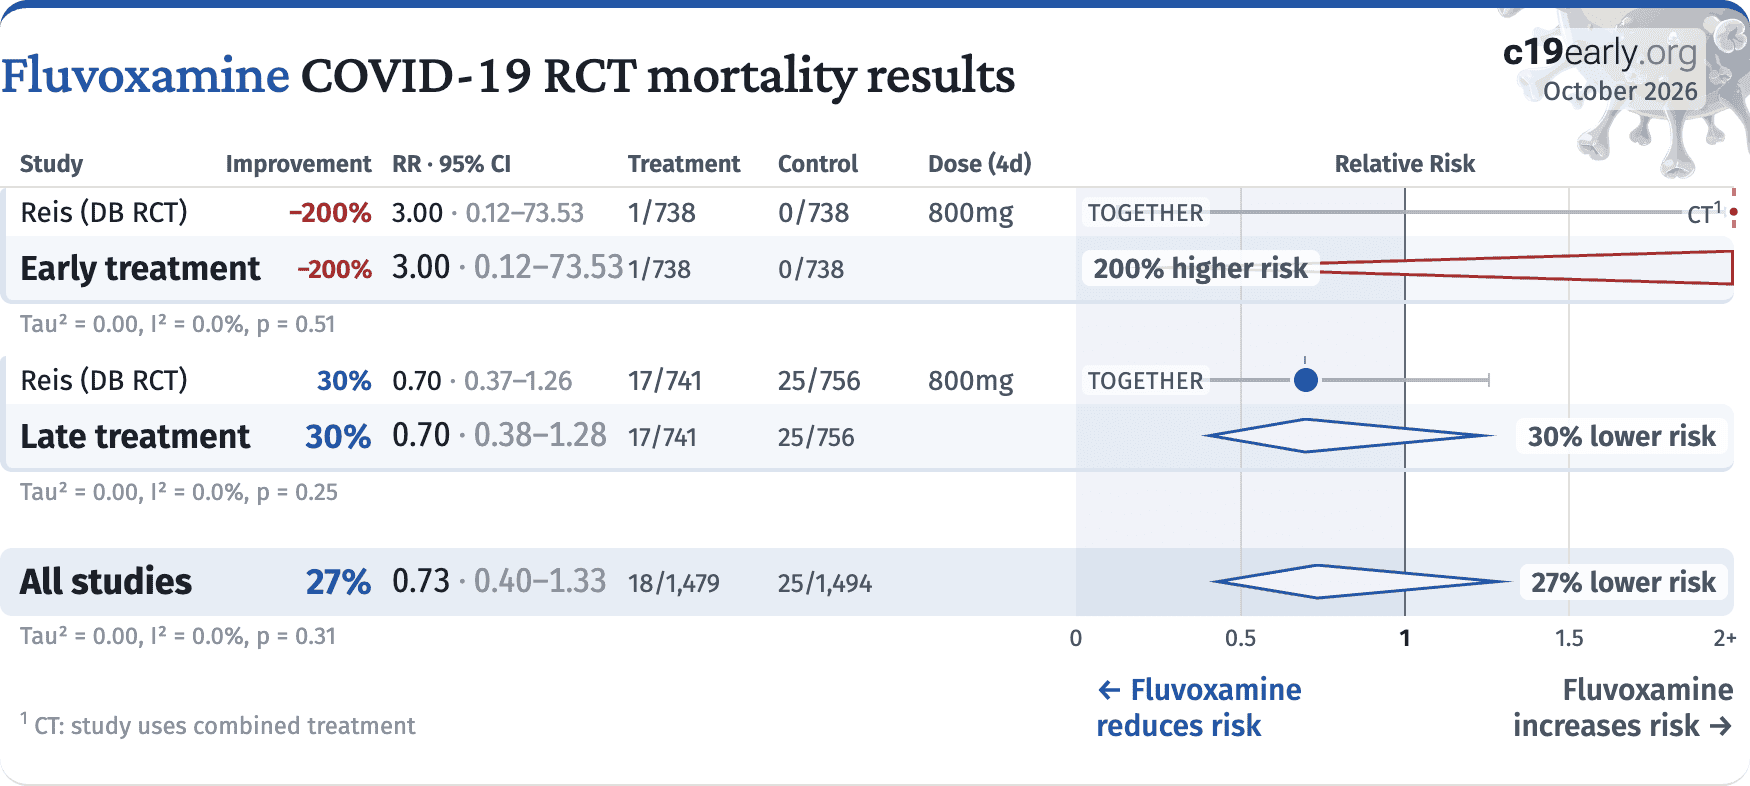
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/fmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
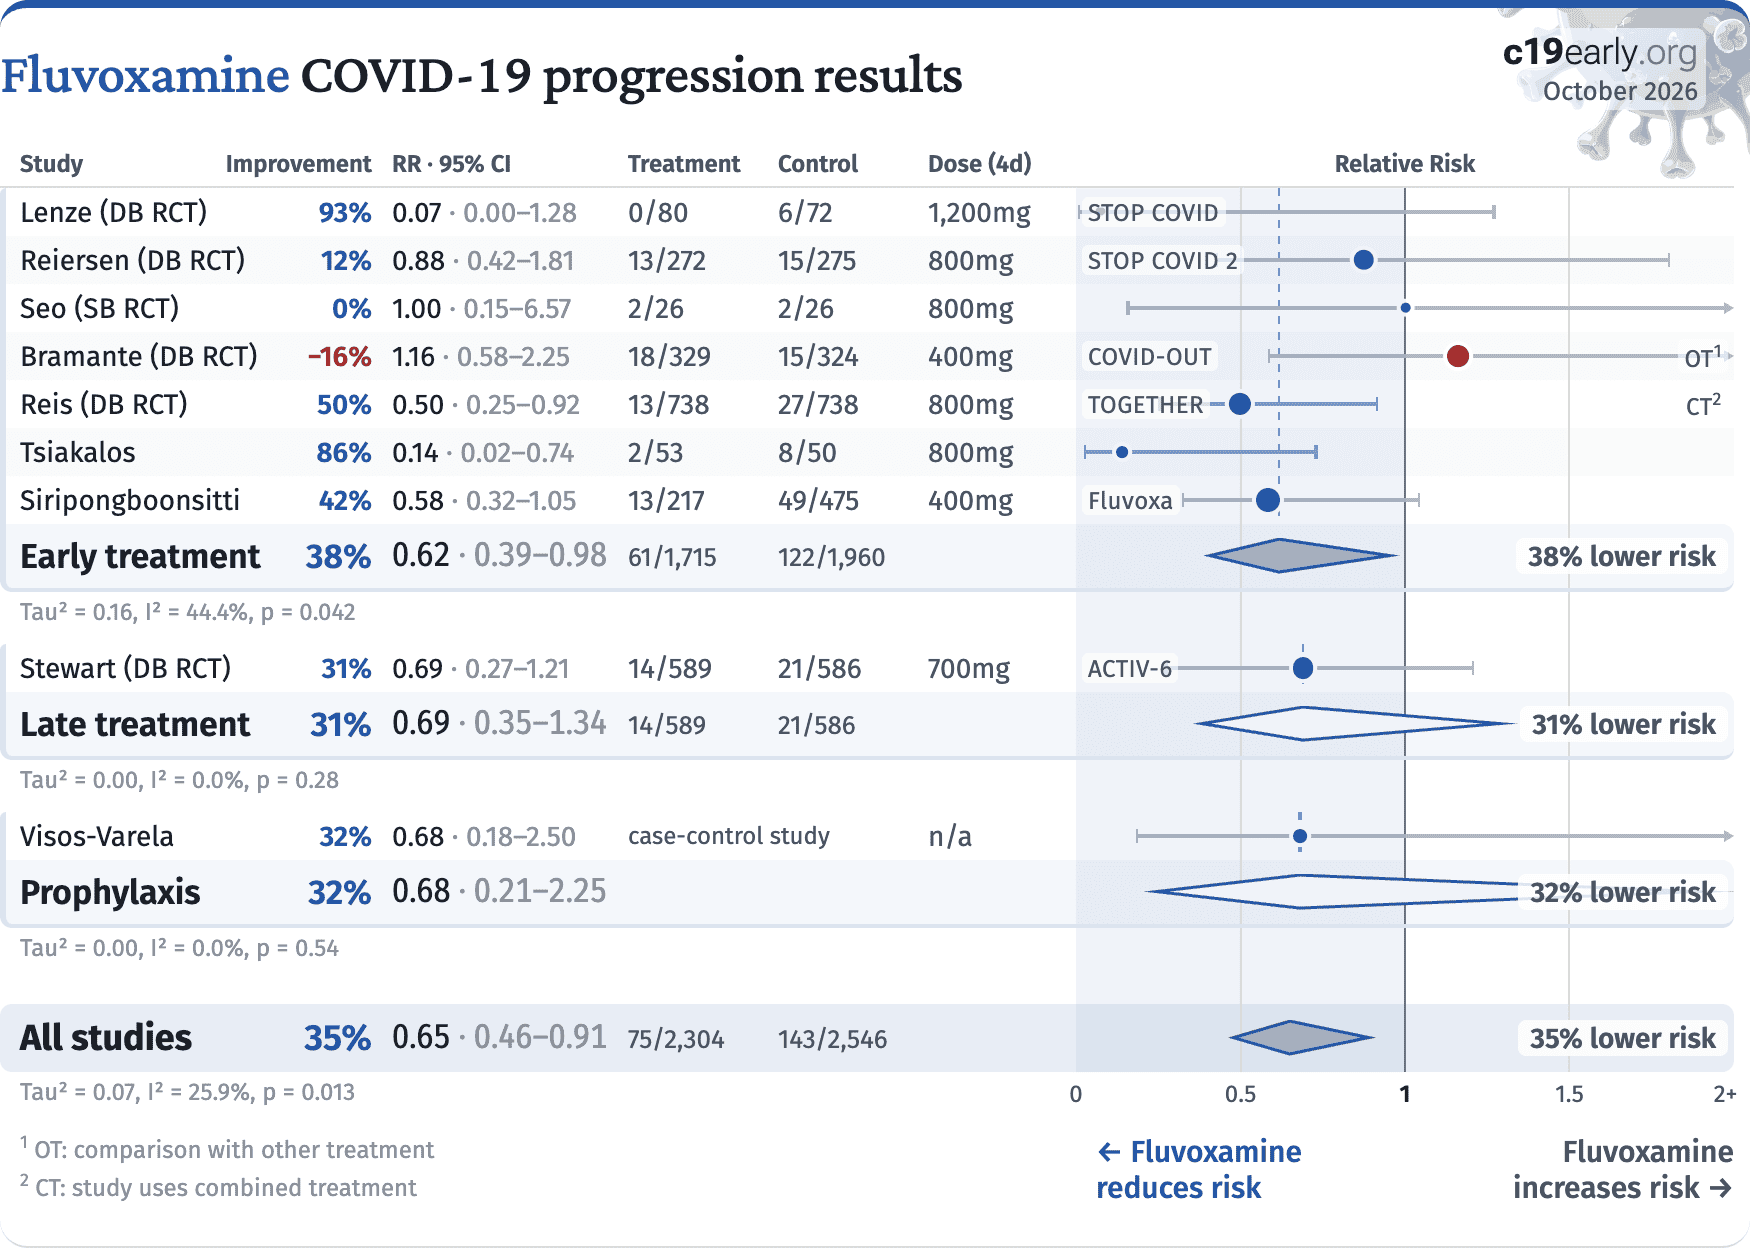
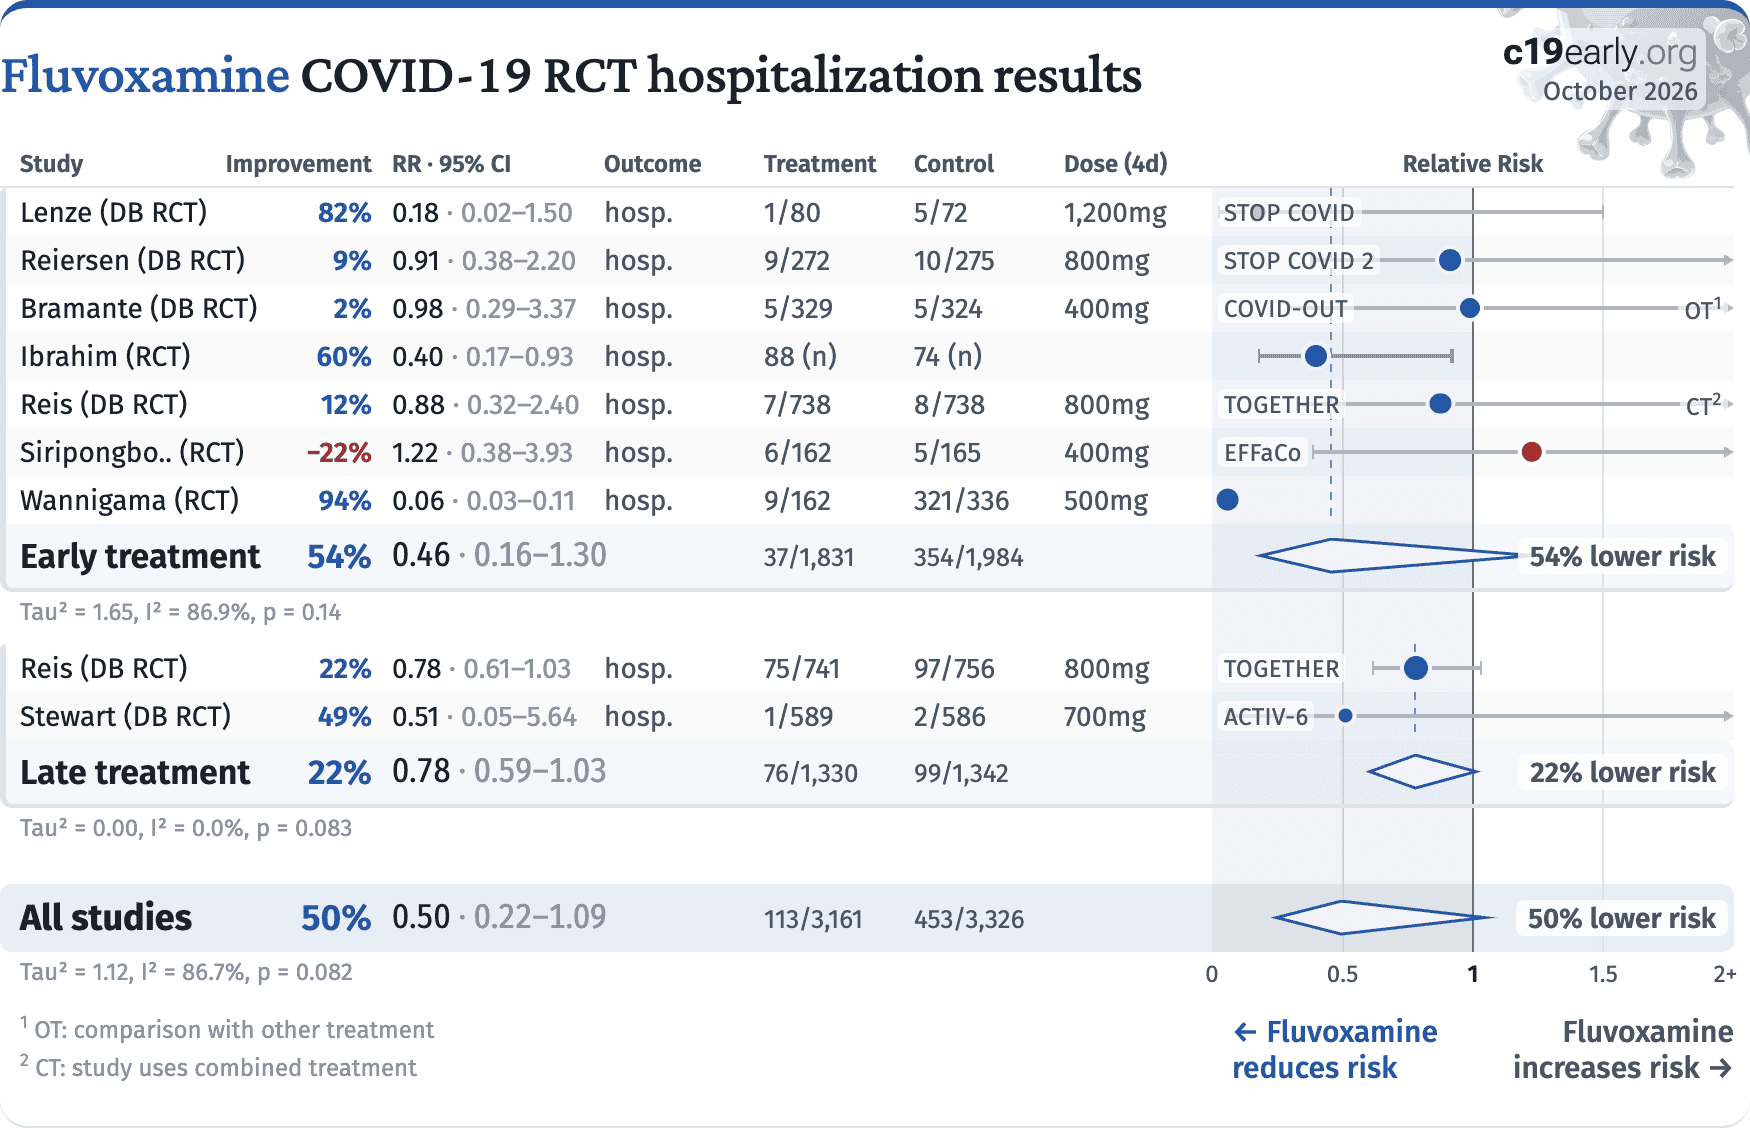
Bramante, 8/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 37 authors, average treatment delay 5.0 days, this trial compares with another treatment - results may be better when compared to placebo, trial NCT04510194 (history) (COVID-OUT).
|
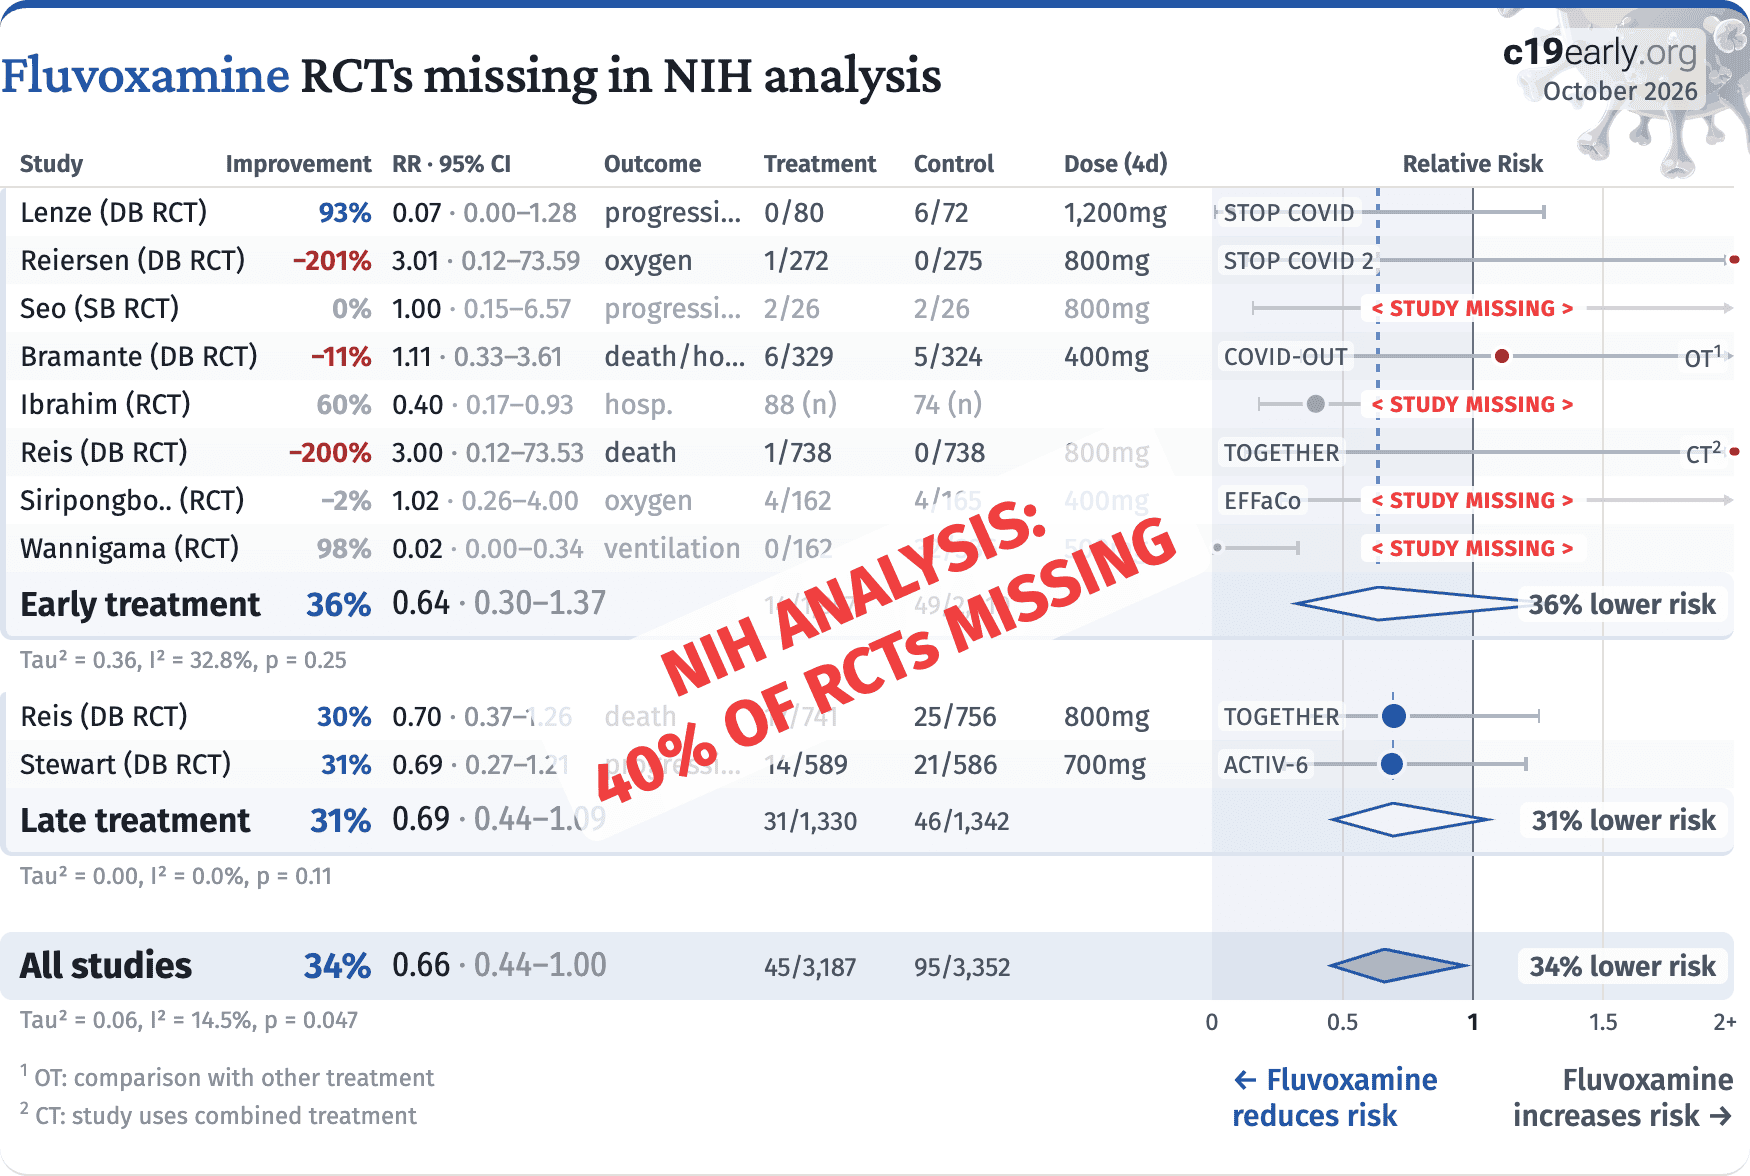
risk of death/hospitalization, 10.8% higher, RR 1.11, p = 0.88, treatment 6 of 329 (1.8%), control 5 of 324 (1.5%), odds ratio converted to relative risk.
|
|
risk of progression, 16.1% higher, RR 1.16, p = 0.68, treatment 18 of 329 (5.5%), control 15 of 324 (4.6%), odds ratio converted to relative risk, combined ER, hospitalization, death.
|
|
risk of hospitalization, 1.5% lower, RR 0.98, p = 1.00, treatment 5 of 329 (1.5%), control 5 of 324 (1.5%), NNT 4264, Figure S8, day 28.
|
|
risk of hospitalization, 1.5% lower, RR 0.98, p = 1.00, treatment 5 of 329 (1.5%), control 5 of 324 (1.5%), NNT 4264, Figure S7, day 14.
|
|
risk of progression, 4.6% lower, RR 0.95, p = 0.75, treatment 79 of 329 (24.0%), control 80 of 321 (24.9%), NNT 110, odds ratio converted to relative risk, combined hypoxemia, ER, hospitalization, death, primary outcome.
|
|
Ibrahim, 1/31/2023, Randomized Controlled Trial, placebo-controlled, Egypt, peer-reviewed, 2 authors.
|
risk of hospitalization, 59.9% lower, RR 0.40, p = 0.03, treatment 88, control 74, all patients.
|
|
risk of hospitalization, 58.3% lower, RR 0.42, p = 0.06, treatment 6 of 51 (11.8%), control 11 of 39 (28.2%), NNT 6.1, moderate cases.
|
|
risk of hospitalization, 68.5% lower, RR 0.32, p = 0.35, treatment 1 of 37 (2.7%), control 3 of 35 (8.6%), NNT 17, mild cases.
|
|
Lenze, 11/12/2020, Double Blind Randomized Controlled Trial, USA, peer-reviewed, 11 authors, study period 10 April, 2020 - 5 August, 2020, average treatment delay 4.0 days, trial NCT04342663 (history) (STOP COVID).
|
risk of progression, 92.7% lower, RR 0.07, p = 0.009, treatment 0 of 80 (0.0%), control 6 of 72 (8.3%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), clinical deterioration over 15 days.
|
|
risk of hospitalization, 82.0% lower, RR 0.18, p = 0.009, treatment 1 of 80 (1.2%), control 5 of 72 (6.9%), NNT 18, COVID-19 hospitalization within 15 days, see supplemental appendix for details.
|
|
Pineda, 10/4/2022, prospective, Honduras, peer-reviewed, mean age 48.1, 24 authors, study period November 2020 - January 2022.
|
risk of death, 94.0% lower, RR 0.06, p = 0.01, treatment 1 of 594 (0.2%), control 4 of 63 (6.3%), NNT 16, adjusted per study.
|
|
risk of oxygen therapy, 73.0% lower, RR 0.27, p < 0.001, treatment 15 of 594 (2.5%), control 13 of 63 (20.6%), NNT 5.5, adjusted per study.
|
|
risk of hospitalization, 51.0% lower, RR 0.49, p = 0.04, treatment 23 of 594 (3.9%), control 11 of 63 (17.5%), NNT 7.4, adjusted per study.
|
|
hospitalization time, 71.4% higher, relative time 1.71, p = 0.08, treatment 23, control 11.
|
|
Reiersen, 8/20/2021, Double Blind Randomized Controlled Trial, USA, peer-reviewed, median age 47.0 (treatment) 48.0 (control), 24 authors, study period 22 December, 2020 - 21 May, 2021, average treatment delay 5.0 days, trial NCT04668950 (history) (STOP COVID 2).
|
risk of oxygen therapy, 201.1% higher, RR 3.01, p = 0.50, treatment 1 of 272 (0.4%), control 0 of 275 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), non-invasive ventilation.
|
|
risk of oxygen therapy, 32.6% lower, RR 0.67, p = 0.60, treatment 6 of 272 (2.2%), control 9 of 275 (3.3%), NNT 94.
|
|
risk of oxygen therapy, 37.5% lower, RR 0.62, p = 0.74, treatment 3 of 164 (1.8%), control 6 of 205 (2.9%), NNT 91, per-protocol.
|
|
risk of hospitalization, 9.0% lower, RR 0.91, p = 1.00, treatment 9 of 272 (3.3%), control 10 of 275 (3.6%), NNT 305.
|
|
risk of progression, 12.4% lower, RR 0.88, p = 0.85, treatment 13 of 272 (4.8%), control 15 of 275 (5.5%), NNT 148, primary outcome.
|
|
Reis (B), 4/17/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Brazil, peer-reviewed, 35 authors, study period 15 January, 2022 - 6 July, 2022, average treatment delay 3.0 days, this trial uses multiple treatments in the treatment arm (combined with budesonide) - results of individual treatments may vary, trial NCT04727424 (history) (TOGETHER).
|
risk of death, 200.0% higher, RR 3.00, p = 1.00, treatment 1 of 738 (0.1%), control 0 of 738 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 12.5% lower, RR 0.88, p = 1.00, treatment 7 of 738 (0.9%), control 8 of 738 (1.1%), NNT 738.
|
|
hospitalization or ER >6hrs, 50.0% lower, RR 0.50, p = 0.04, treatment 13 of 738 (1.8%), control 27 of 738 (3.7%), NNT 53, adjusted per study, day 28, primary outcome.
|
|
Seftel, 2/1/2021, prospective quasi-randomized (patient choice), USA, peer-reviewed, 2 authors.
|
risk of death, 72.3% lower, RR 0.28, p = 0.38, treatment 0 of 77 (0.0%), control 1 of 48 (2.1%), NNT 48, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of death/ICU, 83.9% lower, RR 0.16, p = 0.15, treatment 0 of 77 (0.0%), control 2 of 48 (4.2%), NNT 24, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 94.0% lower, RR 0.06, p = 0.003, treatment 0 of 77 (0.0%), control 6 of 48 (12.5%), NNT 8.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
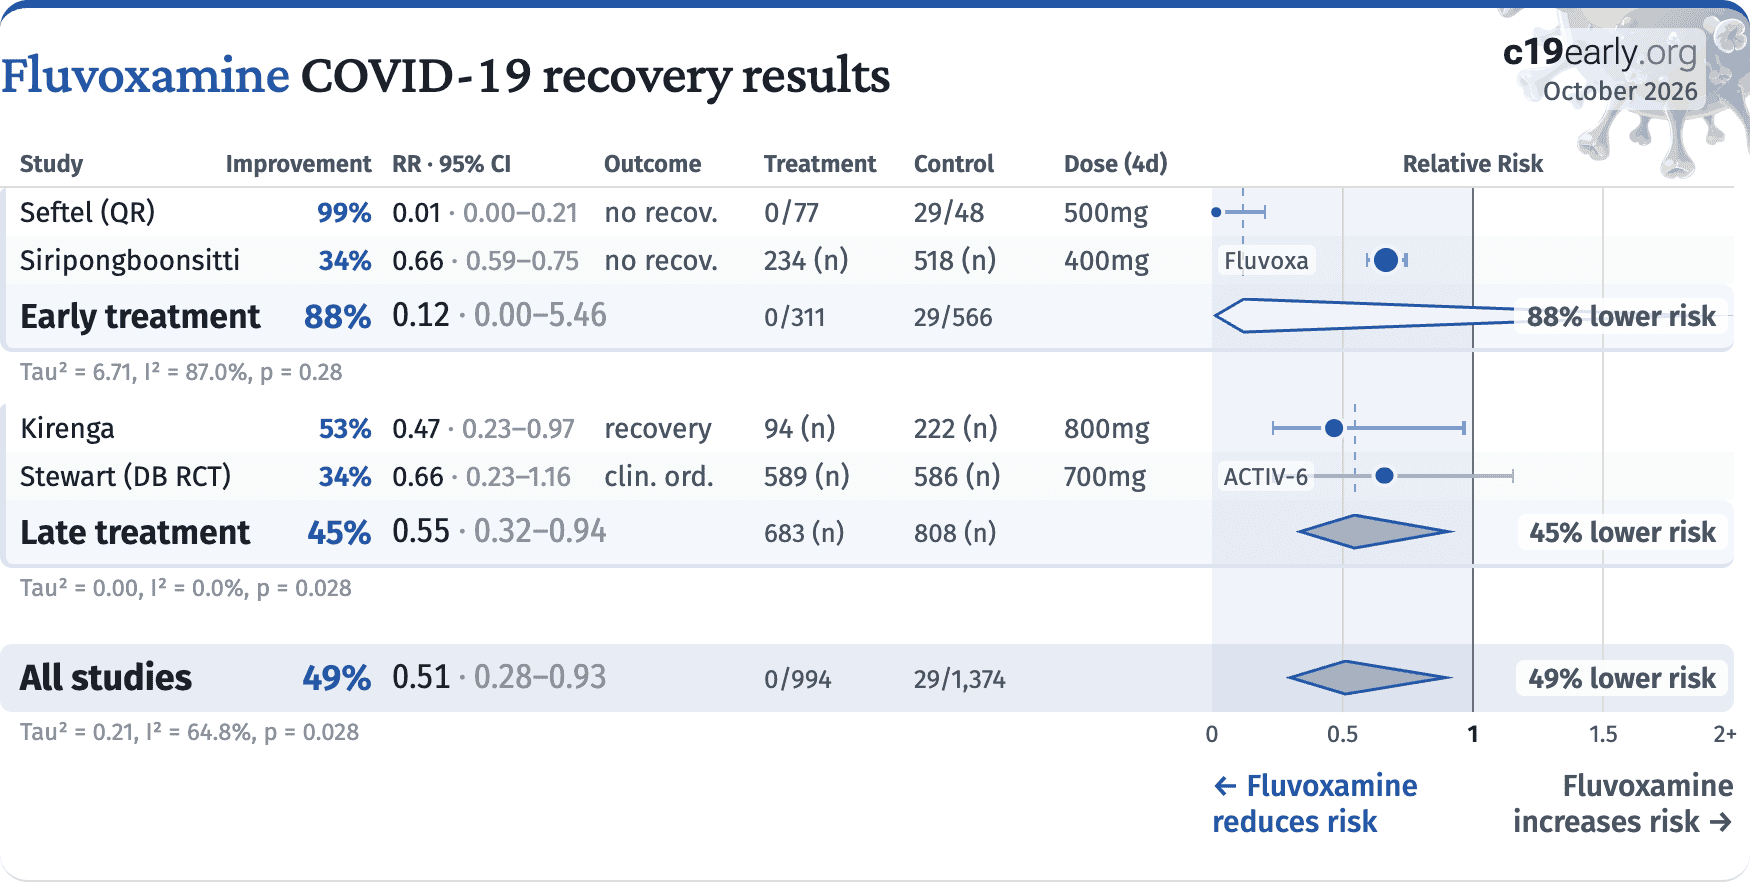
risk of no recovery, 98.7% lower, RR 0.01, p < 0.001, treatment 0 of 77 (0.0%), control 29 of 48 (60.4%), NNT 1.7, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Seo, 3/3/2022, Single Blind Randomized Controlled Trial, placebo-controlled, South Korea, peer-reviewed, median age 53.5, 14 authors, study period 15 January, 2021 - 19 February, 2021.
|
risk of progression, no change, RR 1.00, p = 1.00, treatment 2 of 26 (7.7%), control 2 of 26 (7.7%).
|
|
risk of progression, 34.2% lower, RR 0.66, p = 1.00, treatment 1 of 19 (5.3%), control 2 of 25 (8.0%), NNT 37, PP.
|
|
time to progression, 13.3% lower, relative time 0.87, p = 0.16, treatment mean 6.5 (±0.7) n=26, control mean 7.5 (±3.5) n=26.
|
|
Siripongboonsitti (B), 10/6/2023, retrospective, Thailand, peer-reviewed, 4 authors, study period 16 April, 2021 - 24 July, 2021, trial TCTR20230401001 (Fluvoxa).
|
risk of death, 59.2% lower, RR 0.41, p = 1.00, treatment 0 of 234 (0.0%), control 1 of 518 (0.2%), NNT 518, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
|
|
risk of mechanical ventilation, 47.6% higher, RR 1.48, p = 0.65, treatment 2 of 234 (0.9%), control 3 of 518 (0.6%).
|
|
risk of ICU admission, 26.2% lower, RR 0.74, p = 1.00, treatment 2 of 234 (0.9%), control 6 of 518 (1.2%), NNT 329.
|
|
risk of oxygen therapy, 67.3% higher, RR 1.67, p = 0.02, treatment 34 of 234 (14.5%), control 45 of 518 (8.7%).
|
|
risk of deterioration, 41.9% lower, RR 0.58, p = 0.08, treatment 13 of 217 (6.0%), control 49 of 475 (10.3%), NNT 23, day 14.
|
|
risk of deterioration, 35.0% lower, RR 0.65, p = 0.047, treatment 23 of 166 (13.9%), control 88 of 413 (21.3%), NNT 13, day 5.
|
|
risk of deterioration, 32.9% lower, RR 0.67, p = 0.004, treatment 51 of 217 (23.5%), control 132 of 377 (35.0%), NNT 8.7, day 2.
|
|
risk of progression, 47.6% higher, RR 1.48, p = 0.65, treatment 2 of 234 (0.9%), control 3 of 518 (0.6%), ARDS.
|
|
WHO-CPS, 33.6% lower, RR 0.66, p < 0.001, treatment mean 0.73 (±0.67) n=234, control mean 1.1 (±0.75) n=518, WHO-CPS score, day 14.
|
|
WHO-CPS, 7.9% higher, RR 1.08, p = 0.06, treatment mean 2.06 (±1.07) n=234, control mean 1.91 (±0.98) n=518, WHO-CPS score, day 5.
|
|
WHO-CPS, 3.3% higher, RR 1.03, p = 0.43, treatment mean 2.21 (±1.25) n=234, control mean 2.14 (±1.06) n=518, WHO-CPS score, day 2.
|
|
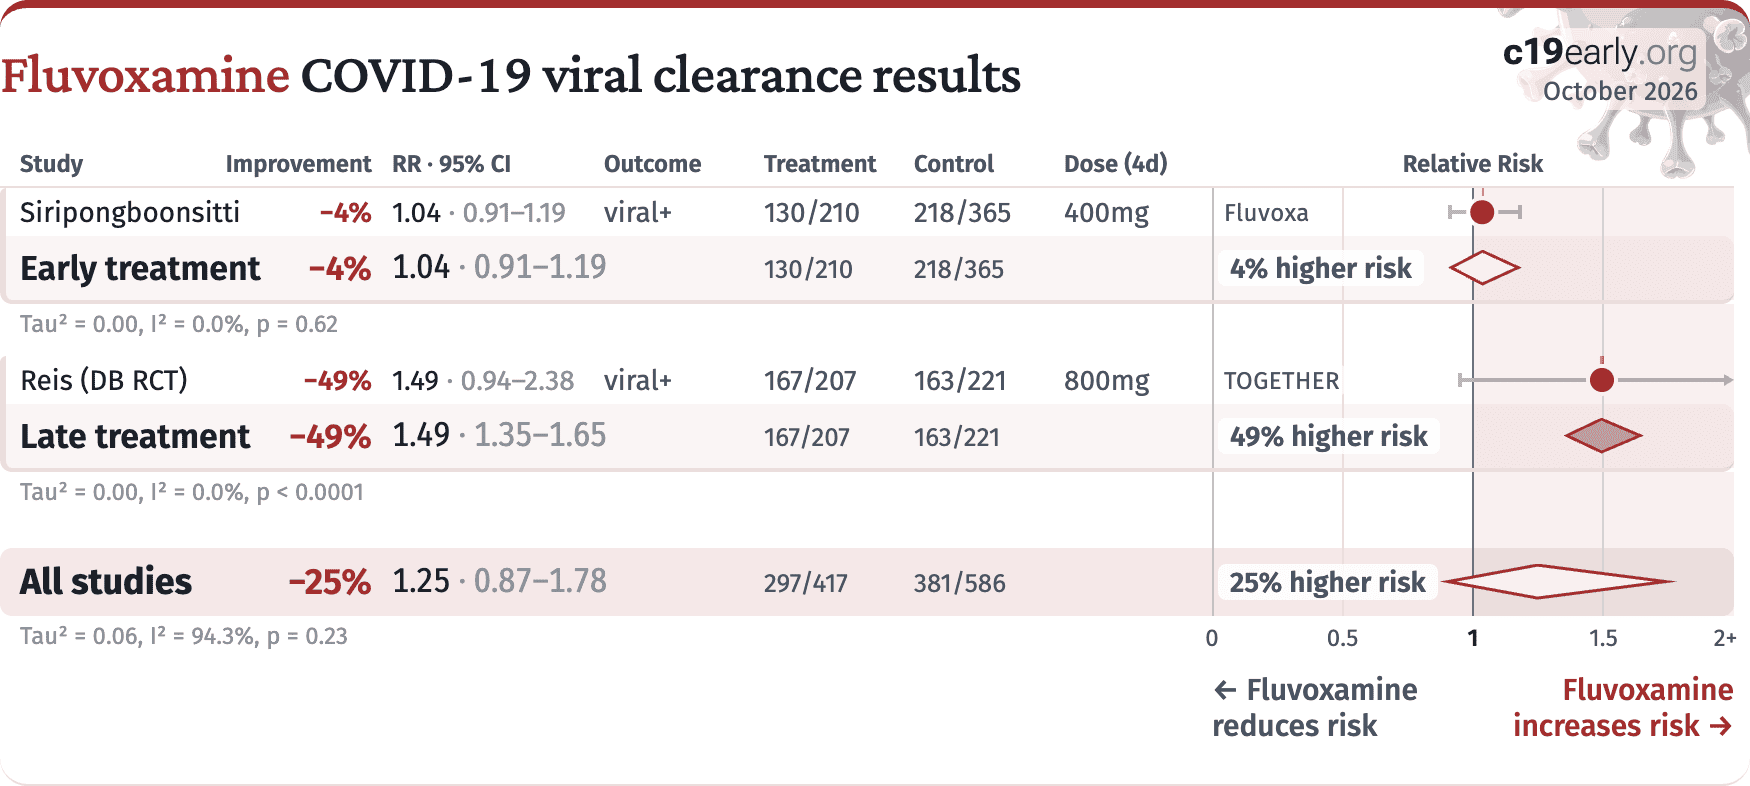
risk of no viral clearance, 3.6% higher, RR 1.04, p = 0.66, treatment 130 of 210 (61.9%), control 218 of 365 (59.7%), day 14.
|
|
Siripongboonsitti, 6/29/2023, Randomized Controlled Trial, Thailand, peer-reviewed, 9 authors, study period 26 June, 2021 - 22 February, 2022, trial TCTR20210615002 (EFFaCo).
|
risk of oxygen therapy, 1.9% higher, RR 1.02, p = 1.00, treatment 4 of 162 (2.5%), control 4 of 165 (2.4%).
|
|
risk of hospitalization, 22.2% higher, RR 1.22, p = 0.77, treatment 6 of 162 (3.7%), control 5 of 165 (3.0%), day 28.
|
|
Tsiakalos, 8/12/2023, retrospective, Greece, peer-reviewed, 5 authors, study period 1 September, 2021 - 31 December, 2021.
|
risk of ICU admission, 67.3% lower, RR 0.33, p = 0.49, treatment 0 of 53 (0.0%), control 1 of 50 (2.0%), NNT 50, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 84.3% lower, RR 0.16, p = 0.06, treatment 1 of 53 (1.9%), control 6 of 50 (12.0%), NNT 9.9.
|
|
risk of progression, 86.0% lower, RR 0.14, p = 0.02, treatment 2 of 53 (3.8%), control 8 of 50 (16.0%), NNT 8.2, adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Wannigama, 3/14/2024, Randomized Controlled Trial, Thailand, peer-reviewed, 29 authors, study period 1 October, 2021 - 21 June, 2022, average treatment delay 0.5 days, trial NCT05087381 (history).
|
risk of mechanical ventilation, 97.9% lower, RR 0.02, p < 0.001, treatment 0 of 162 (0.0%), control 32 of 336 (9.5%), NNT 10, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
|
|
risk of mechanical ventilation, 97.6% lower, RR 0.02, p < 0.001, treatment 0 of 162 (0.0%), control 27 of 336 (8.0%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 14.
|
|
risk of mechanical ventilation, 96.6% lower, RR 0.03, p < 0.001, treatment 0 of 162 (0.0%), control 19 of 336 (5.7%), NNT 18, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 9.
|
|
risk of oxygen therapy, 89.1% lower, RR 0.11, p < 0.001, treatment 9 of 162 (5.6%), control 171 of 336 (50.9%), NNT 2.2, day 28.
|
|
risk of oxygen therapy, 99.6% lower, RR 0.004, p < 0.001, treatment 0 of 162 (0.0%), control 150 of 336 (44.6%), NNT 2.2, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 14.
|
|
risk of oxygen therapy, 99.4% lower, RR 0.006, p < 0.001, treatment 0 of 162 (0.0%), control 117 of 336 (34.8%), NNT 2.9, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 9.
|
|
risk of hospitalization, 94.2% lower, RR 0.06, p < 0.001, treatment 9 of 162 (5.6%), control 321 of 336 (95.5%), NNT 1.1, day 28.
|
|
risk of hospitalization, 97.6% lower, RR 0.02, p < 0.001, treatment 0 of 162 (0.0%), control 27 of 336 (8.0%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 14.
|
|
risk of hospitalization, 96.6% lower, RR 0.03, p < 0.001, treatment 0 of 162 (0.0%), control 19 of 336 (5.7%), NNT 18, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 9.
|
|
risk of long COVID, 40.1% lower, RR 0.60, p < 0.001, treatment 97 of 162 (59.9%), control 336 of 336 (100.0%), NNT 2.5, day 90.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Calusic, 11/1/2021, prospective, propensity score matching, Croatia, peer-reviewed, 7 authors, study period 1 April, 2021 - 31 May, 2021.
|
risk of death, 42.0% lower, HR 0.58, p = 0.03, treatment 30 of 51 (58.8%), control 39 of 51 (76.5%), NNT 5.7, adjusted per study, propensity score matching.
|
|
Kirenga, 3/3/2023, prospective, Uganda, peer-reviewed, 19 authors, study period December 2021 - February 2022.
|
risk of death, 68.0% lower, HR 0.32, p < 0.001, treatment 29 of 94 (30.9%), control 126 of 222 (56.8%), NNT 3.9, adjusted for unbalanced covariates, propensity score weighting, Cox proportional hazards.
|
|
symptom resolution, 53.1% lower, HR 0.47, p = 0.04, treatment 94, control 222, inverted to make HR<1 favor treatment, propensity score weighting, Cox proportional hazards, RR approximated with OR.
|
|
Reis, 8/23/2021, Double Blind Randomized Controlled Trial, Brazil, peer-reviewed, 27 authors, study period 20 January, 2021 - 5 August, 2021, trial NCT04727424 (history) (TOGETHER).
|
risk of death, 30.3% lower, RR 0.70, p = 0.24, treatment 17 of 741 (2.3%), control 25 of 756 (3.3%), NNT 99, odds ratio converted to relative risk, ITT.
|
|
risk of death, 90.8% lower, RR 0.09, p = 0.02, treatment 1 of 548 (0.2%), control 12 of 618 (1.9%), NNT 57, odds ratio converted to relative risk, per protocol.
|
|
risk of mechanical ventilation, 22.2% lower, RR 0.78, p = 0.33, treatment 26 of 741 (3.5%), control 34 of 756 (4.5%), NNT 101, odds ratio converted to relative risk, ITT.
|
|
risk of hospitalization, 21.6% lower, RR 0.78, p = 0.10, treatment 75 of 741 (10.1%), control 97 of 756 (12.8%), NNT 37, odds ratio converted to relative risk, ITT.
|
|
extended ER observation or hospitalization, 32.0% lower, RR 0.68, p = 0.004, treatment 79 of 741 (10.7%), control 119 of 756 (15.7%), NNT 20, ITT, primary outcome.
|
|
extended ER observation or hospitalization, 31.0% lower, RR 0.69, p = 0.006, treatment 78 of 740 (10.5%), control 115 of 752 (15.3%), NNT 21, mITT.
|
|
extended ER observation or hospitalization, 66.0% lower, RR 0.34, p < 0.001, treatment 541, control 609, per protocol.
|
|
risk of no viral clearance, 49.3% higher, RR 1.49, p = 0.09, treatment 167 of 207 (80.7%), control 163 of 221 (73.8%), adjusted per study, inverted to make RR<1 favor treatment.
|
|
Stewart, 9/13/2023, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 32 authors, study period 5 August, 2022 - 20 January, 2023, average treatment delay 5.0 days, trial NCT04885530 (history) (ACTIV-6).
|
risk of progression, 31.0% lower, RR 0.69, p = 0.34, treatment 14 of 589 (2.4%), control 21 of 586 (3.6%), NNT 83, adjusted per study, urgent or emergency care visits, hospitalizations, or death.
|
|
clinical progression, 34.0% lower, OR 0.66, p = 0.32, treatment 589, control 586, mid-recovery, day 14, RR approximated with OR.
|
|
clinical progression, 15.0% higher, OR 1.15, p = 0.68, treatment 589, control 586, day 7, RR approximated with OR.
|
|
clinical progression, 6.0% lower, OR 0.94, p = 0.90, treatment 589, control 586, day 28, RR approximated with OR.
|
|
risk of no recovery, 1.0% higher, HR 1.01, p = 0.86, treatment 589, control 586, inverted to make HR<1 favor treatment, post-hoc primary outcome.
|
|
risk of hospitalization, 49.0% lower, RR 0.51, p = 0.59, treatment 1 of 589 (0.2%), control 2 of 586 (0.3%), NNT 583, non-COVID-19 hospitalization, day 28.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Diaz, 10/6/2022, retrospective, USA, peer-reviewed, 2 authors.
|
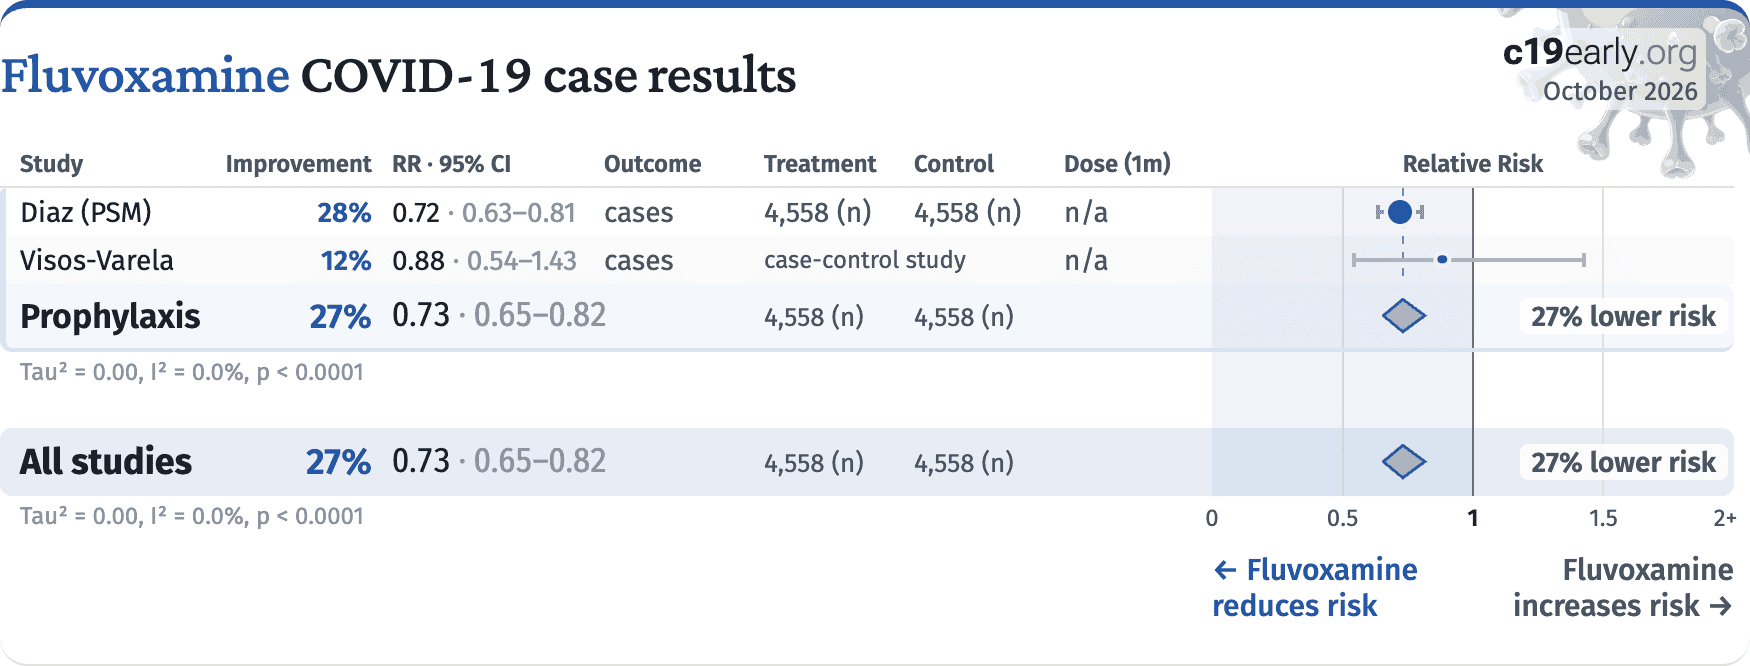
risk of case, 28.0% lower, OR 0.72, p < 0.001, treatment 4,558, control 4,558, propensity score matching, RR approximated with OR.
|
|
Fritz, 8/22/2022, retrospective, USA, peer-reviewed, 5 authors, study period 1 March, 2020 - 16 May, 2021.
|
risk of hospitalization/ER, 19.4% lower, RR 0.81, p = 0.69, treatment 4 of 17 (23.5%), control 1,896 of 20,457 (9.3%), adjusted per study, odds ratio converted to relative risk, fluvoxamine, multivariable.
|
|
risk of hospitalization/ER, 11.9% lower, RR 0.88, p = 0.03, treatment 707 of 3,414 (20.7%), control 1,896 of 20,457 (9.3%), adjusted per study, odds ratio converted to relative risk, FIASMA, multivariable.
|
|
risk of hospitalization/ER, 11.9% lower, RR 0.88, p = 0.04, treatment 559 of 2,744 (20.4%), control 1,896 of 20,457 (9.3%), adjusted per study, odds ratio converted to relative risk, SSRI, multivariable.
|
|
risk of hospitalization/ER, 10.1% lower, RR 0.90, p = 0.04, treatment 971 of 4,577 (21.2%), control 1,896 of 20,457 (9.3%), adjusted per study, odds ratio converted to relative risk, all antidepressants, multivariable.
|
|
Oskotsky, 11/15/2021, retrospective, propensity score matching, USA, peer-reviewed, 8 authors.
|
risk of death, 57.9% higher, RR 1.58, p = 0.62, treatment 2 of 11 (18.2%), control 19 of 165 (11.5%), fluvoxamine.
|
|
risk of death, 26.0% lower, RR 0.74, p = 0.04, treatment 48 of 481 (10.0%), control 956 of 7,215 (13.3%), NNT 31, fluoxetine.
|
|
Trkulja, 11/7/2022, retrospective, Croatia, peer-reviewed, 2 authors.
|
risk of death, 27.0% lower, RR 0.73, p = 0.41, treatment 749, control 31,336, cohort A vs. B, propensity score matching.
|
|
risk of hospitalization, 37.0% higher, RR 1.37, p = 0.50, treatment 749, control 31,336, cohort A vs. B, COVID-related, propensity score matching.
|
|
Visos-Varela, 4/23/2023, retrospective, Spain, peer-reviewed, 8 authors.
|
risk of death, 103.0% higher, OR 2.03, p = 0.52, treatment 1 of 413 (0.2%) cases,
7 of 7,408 (0.1%) controls, adjusted per study, case control OR.
|
|
risk of ICU admission, 395.0% higher, OR 4.95, p = 0.24, treatment 1 of 228 (0.4%) cases,
2 of 4,398 (0.0%) controls, adjusted per study, case control OR.
|
|
risk of hospitalization, 40.0% lower, OR 0.60, p = 0.39, treatment 3 of 3,060 (0.1%) cases,
69 of 56,785 (0.1%) controls, adjusted per study, case control OR.
|
|
risk of progression, 32.0% lower, OR 0.68, p = 0.56, treatment 3 of 3,060 (0.1%) cases,
25 of 26,757 (0.1%) controls, adjusted per study, case control OR.
|
|
risk of case, 12.0% lower, OR 0.88, p = 0.60, treatment 28 of 29,817 (0.1%) cases,
69 of 56,785 (0.1%) controls, adjusted per study, case control OR.
|