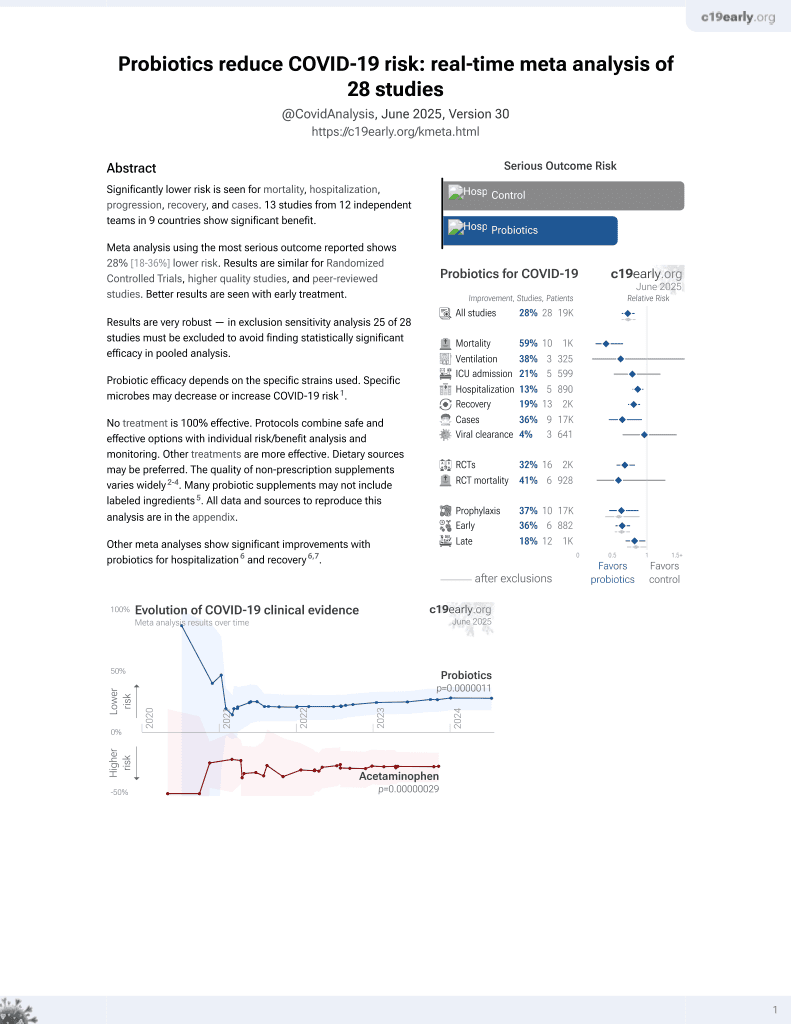
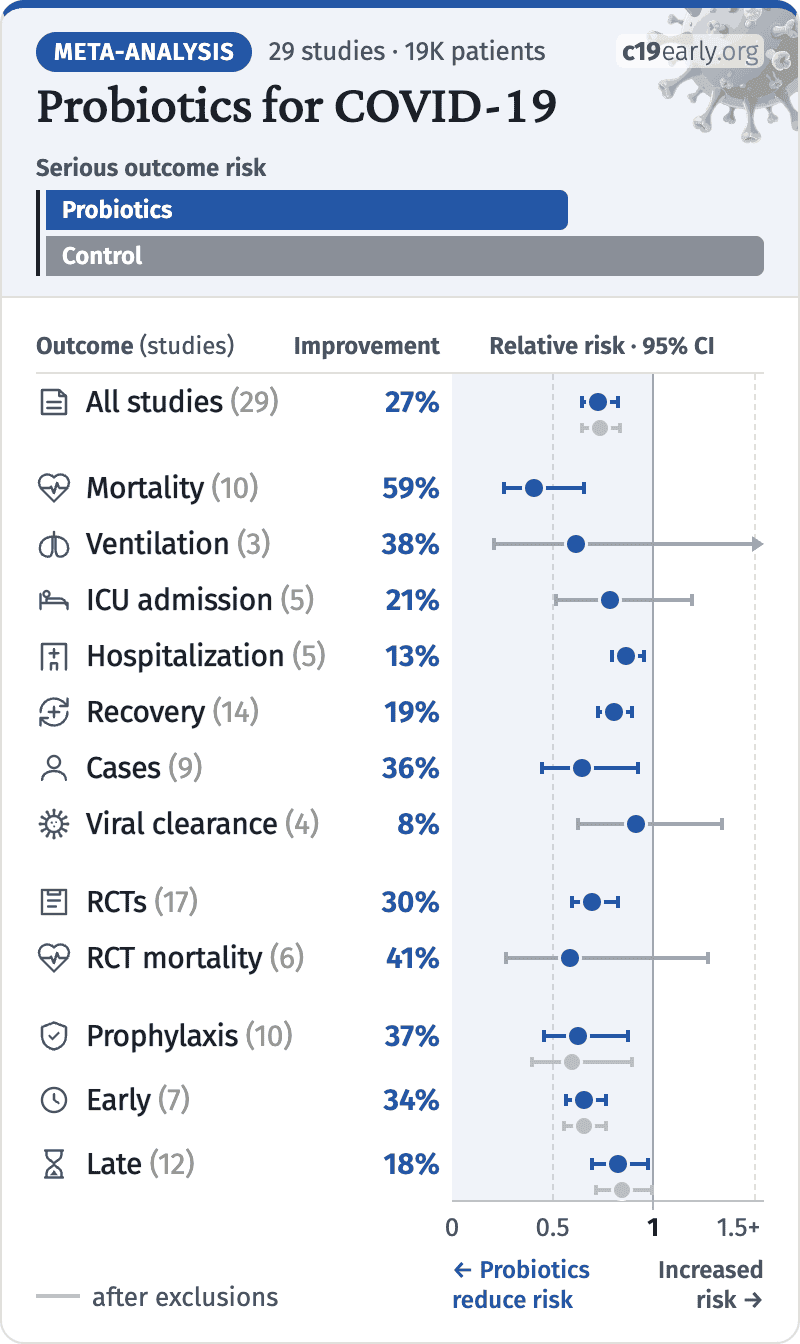
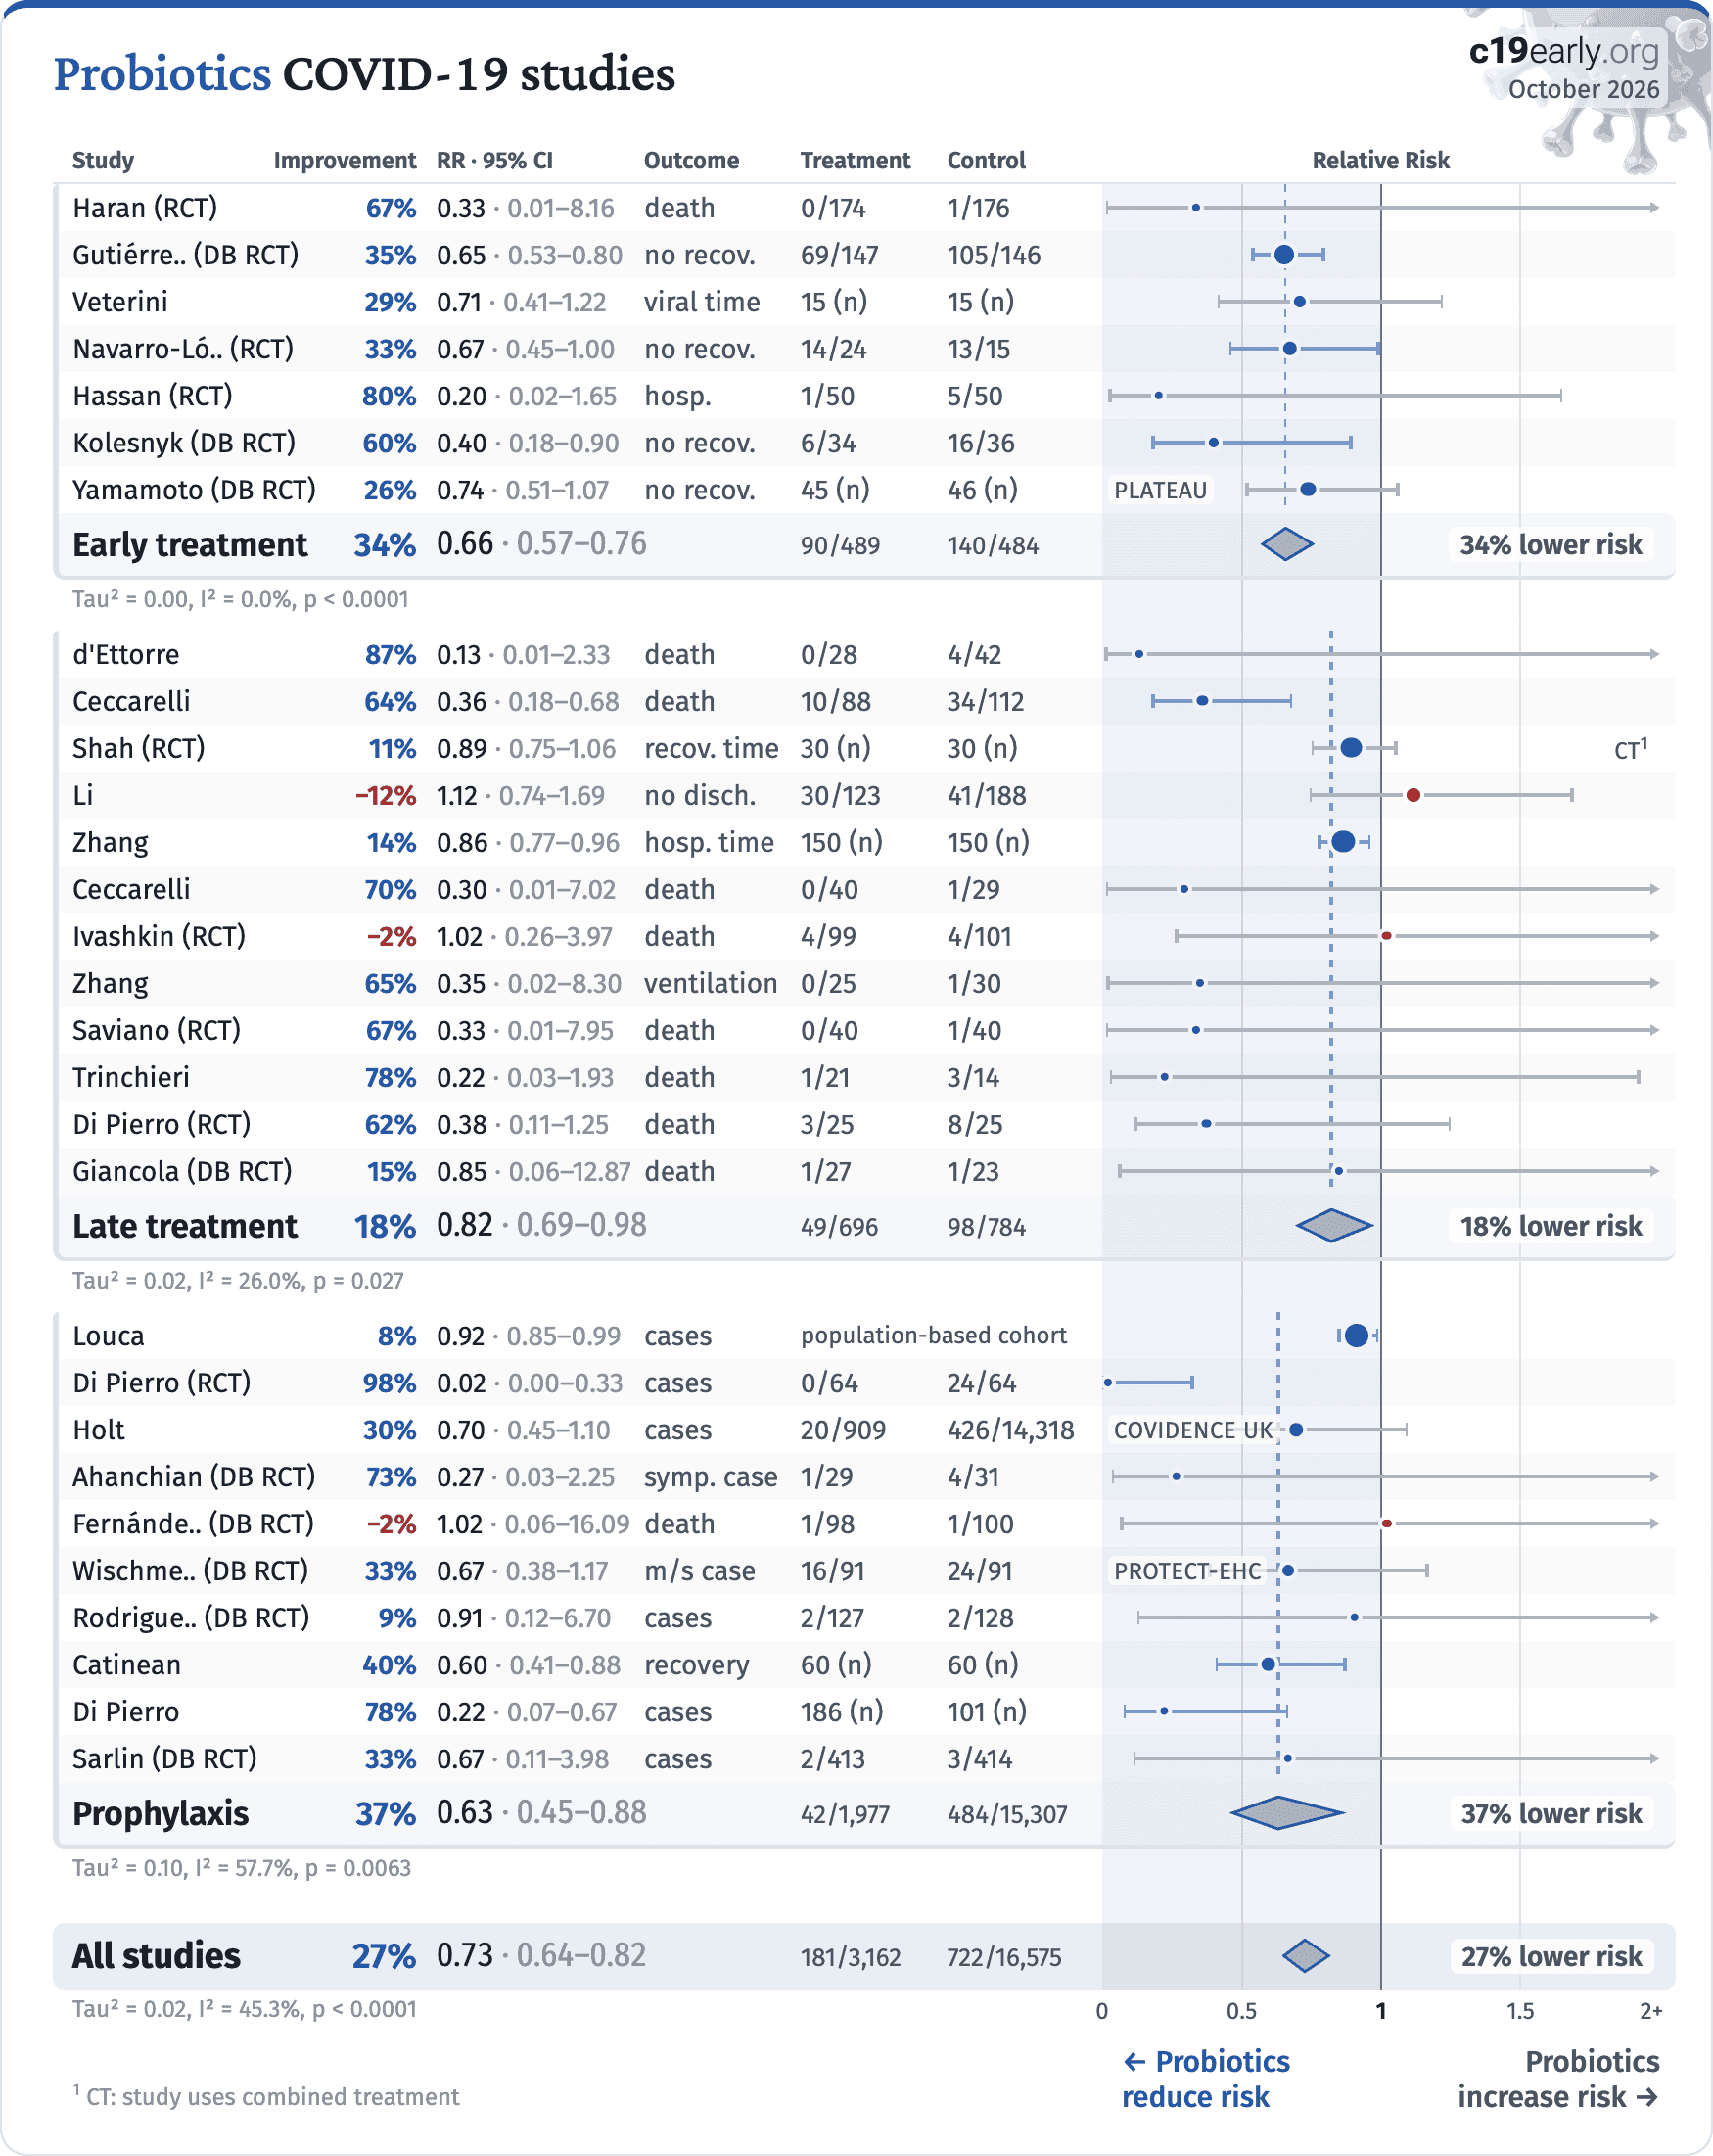
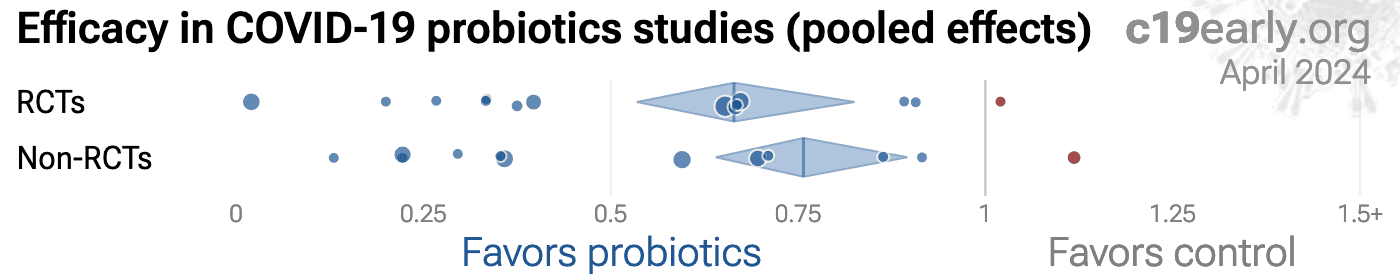
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/kmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
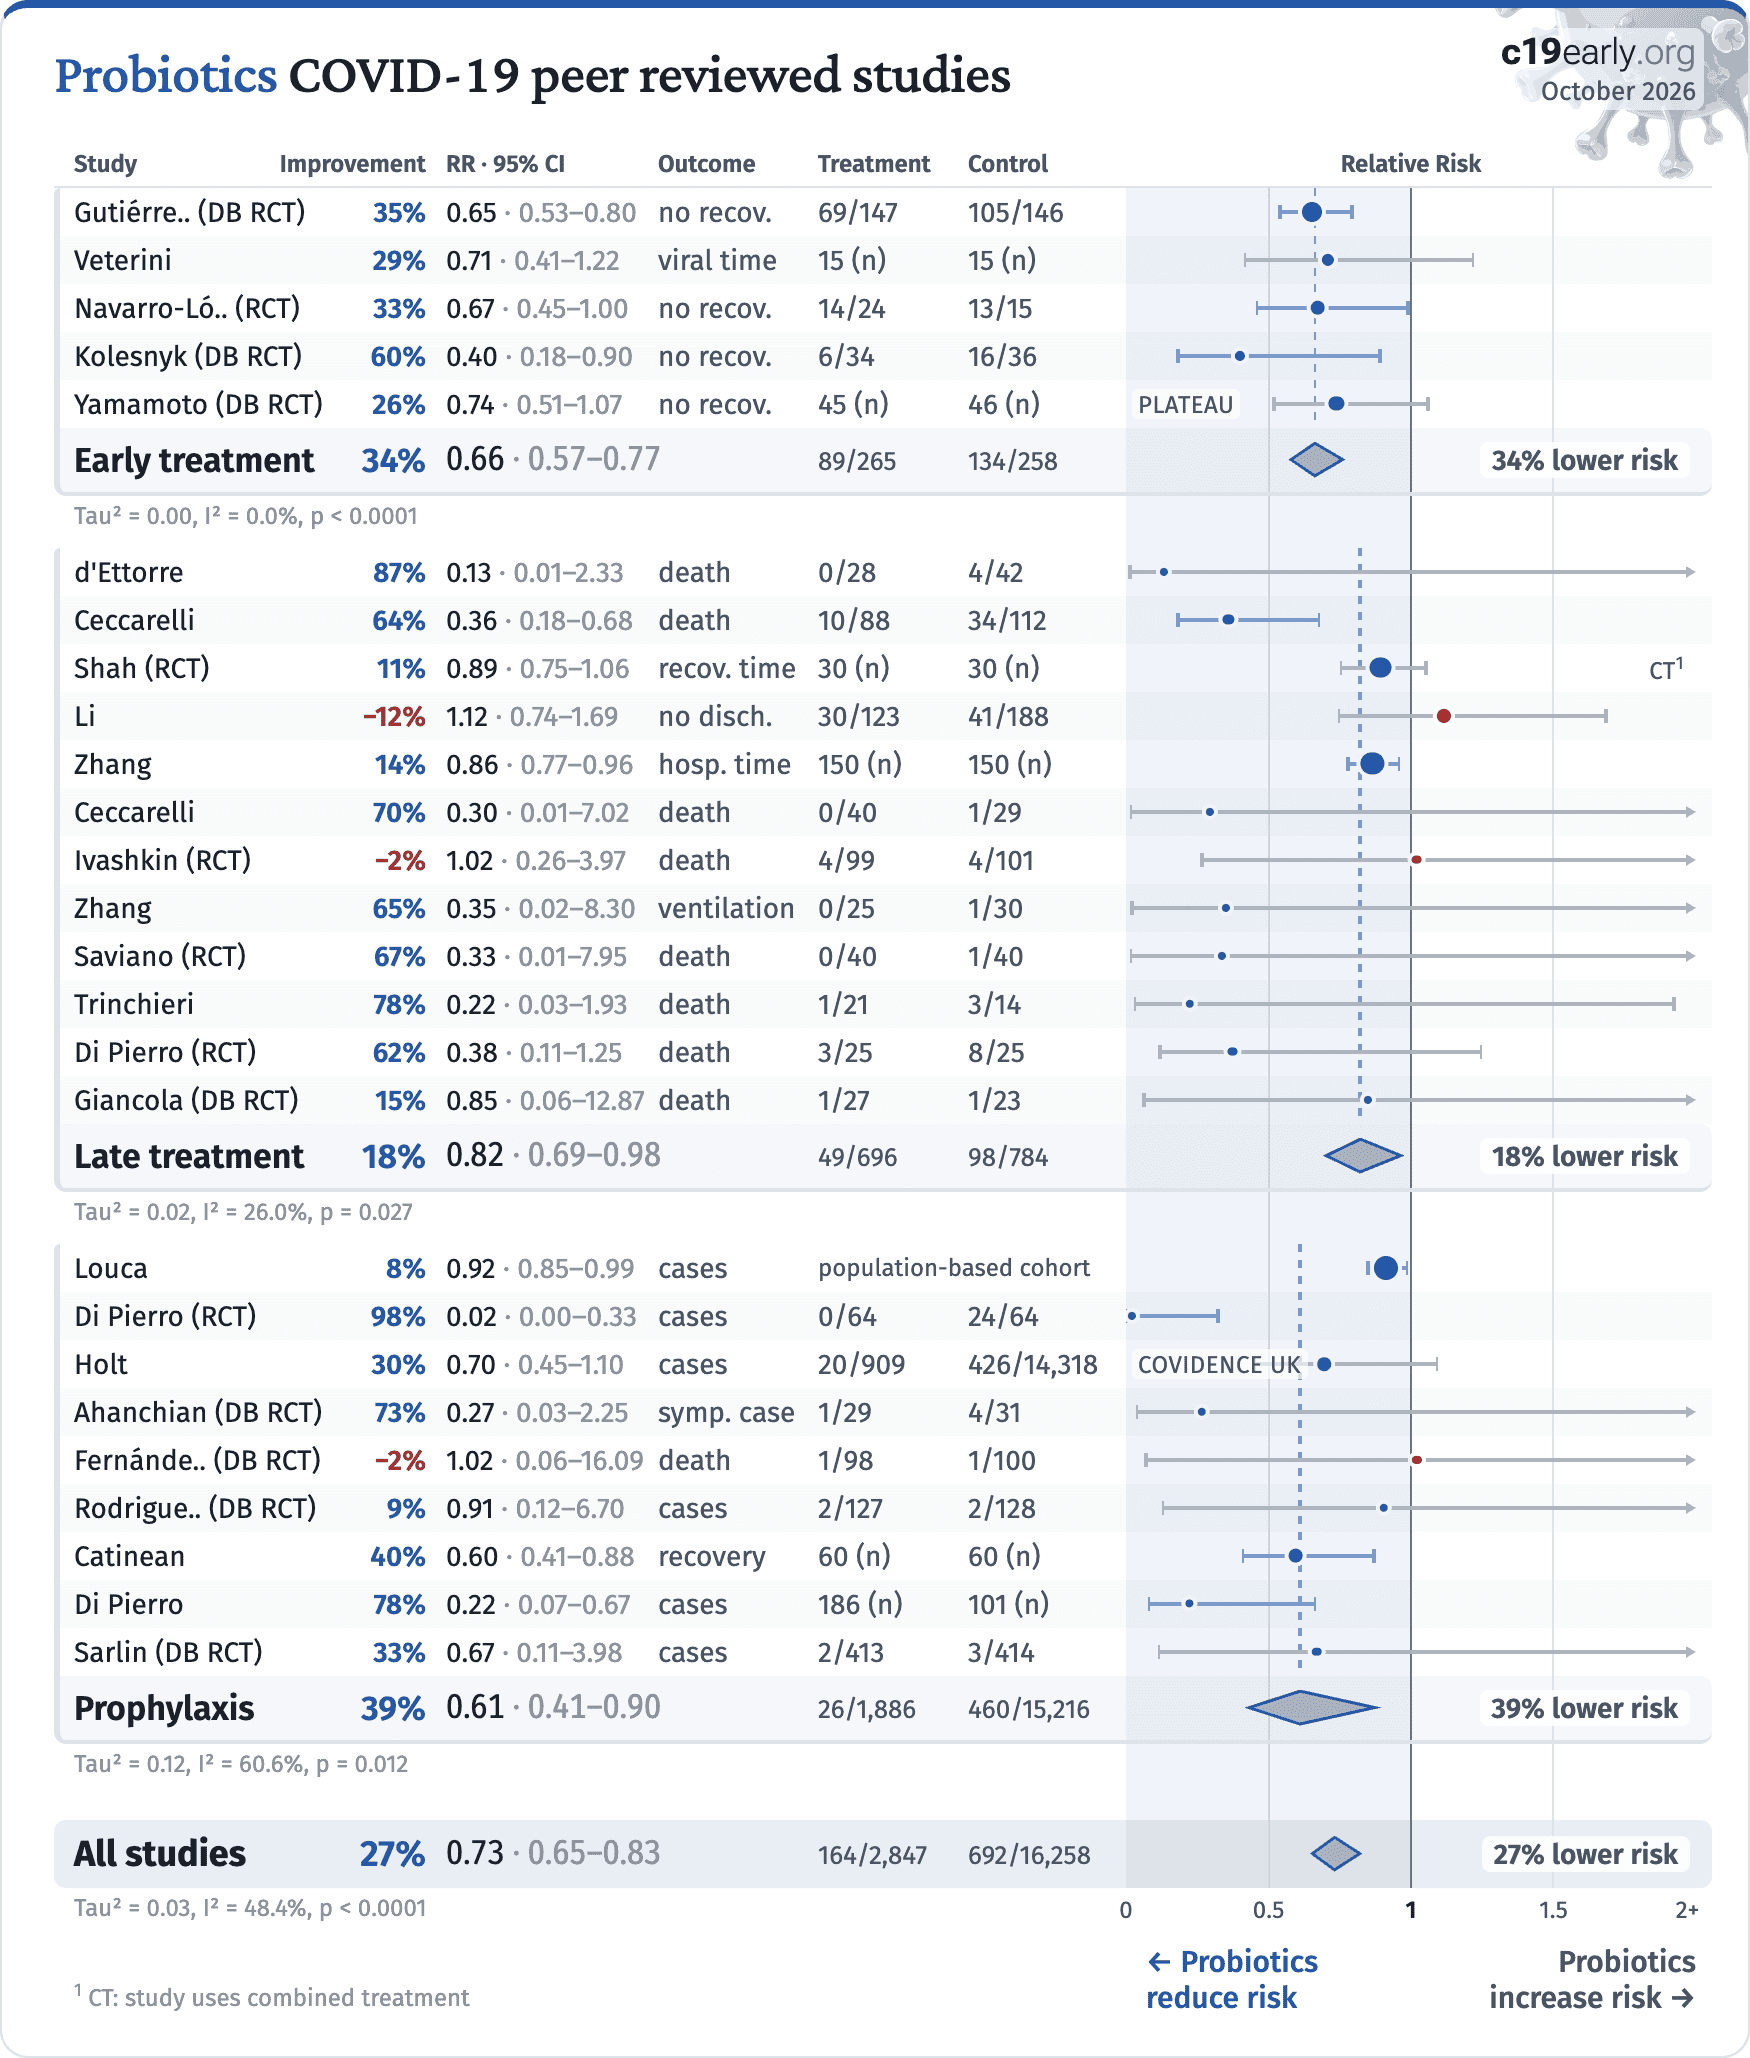
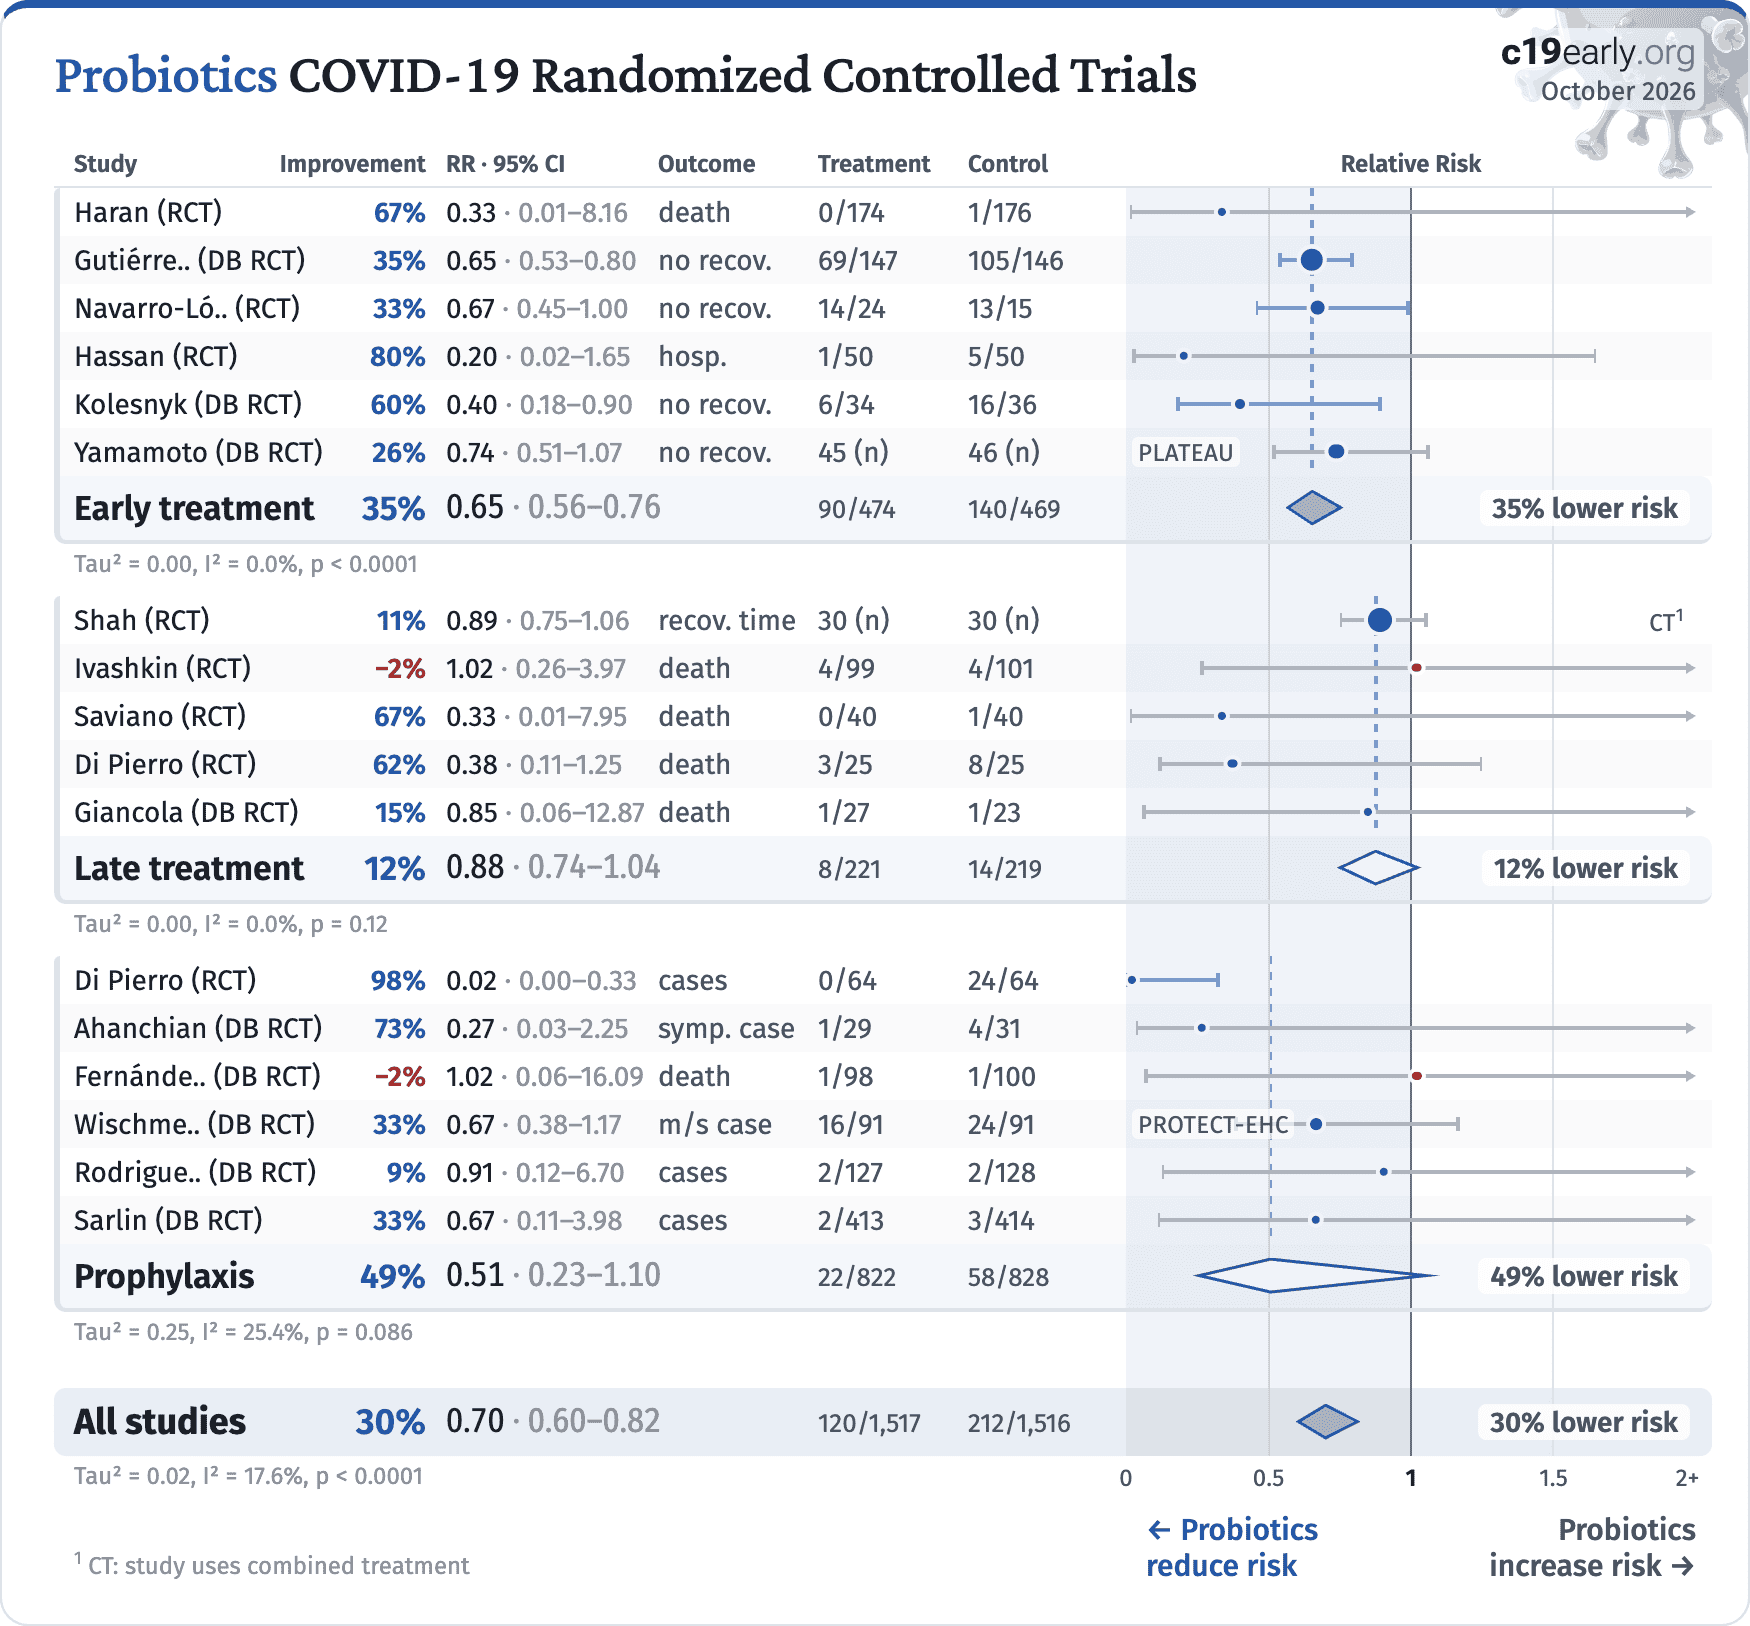
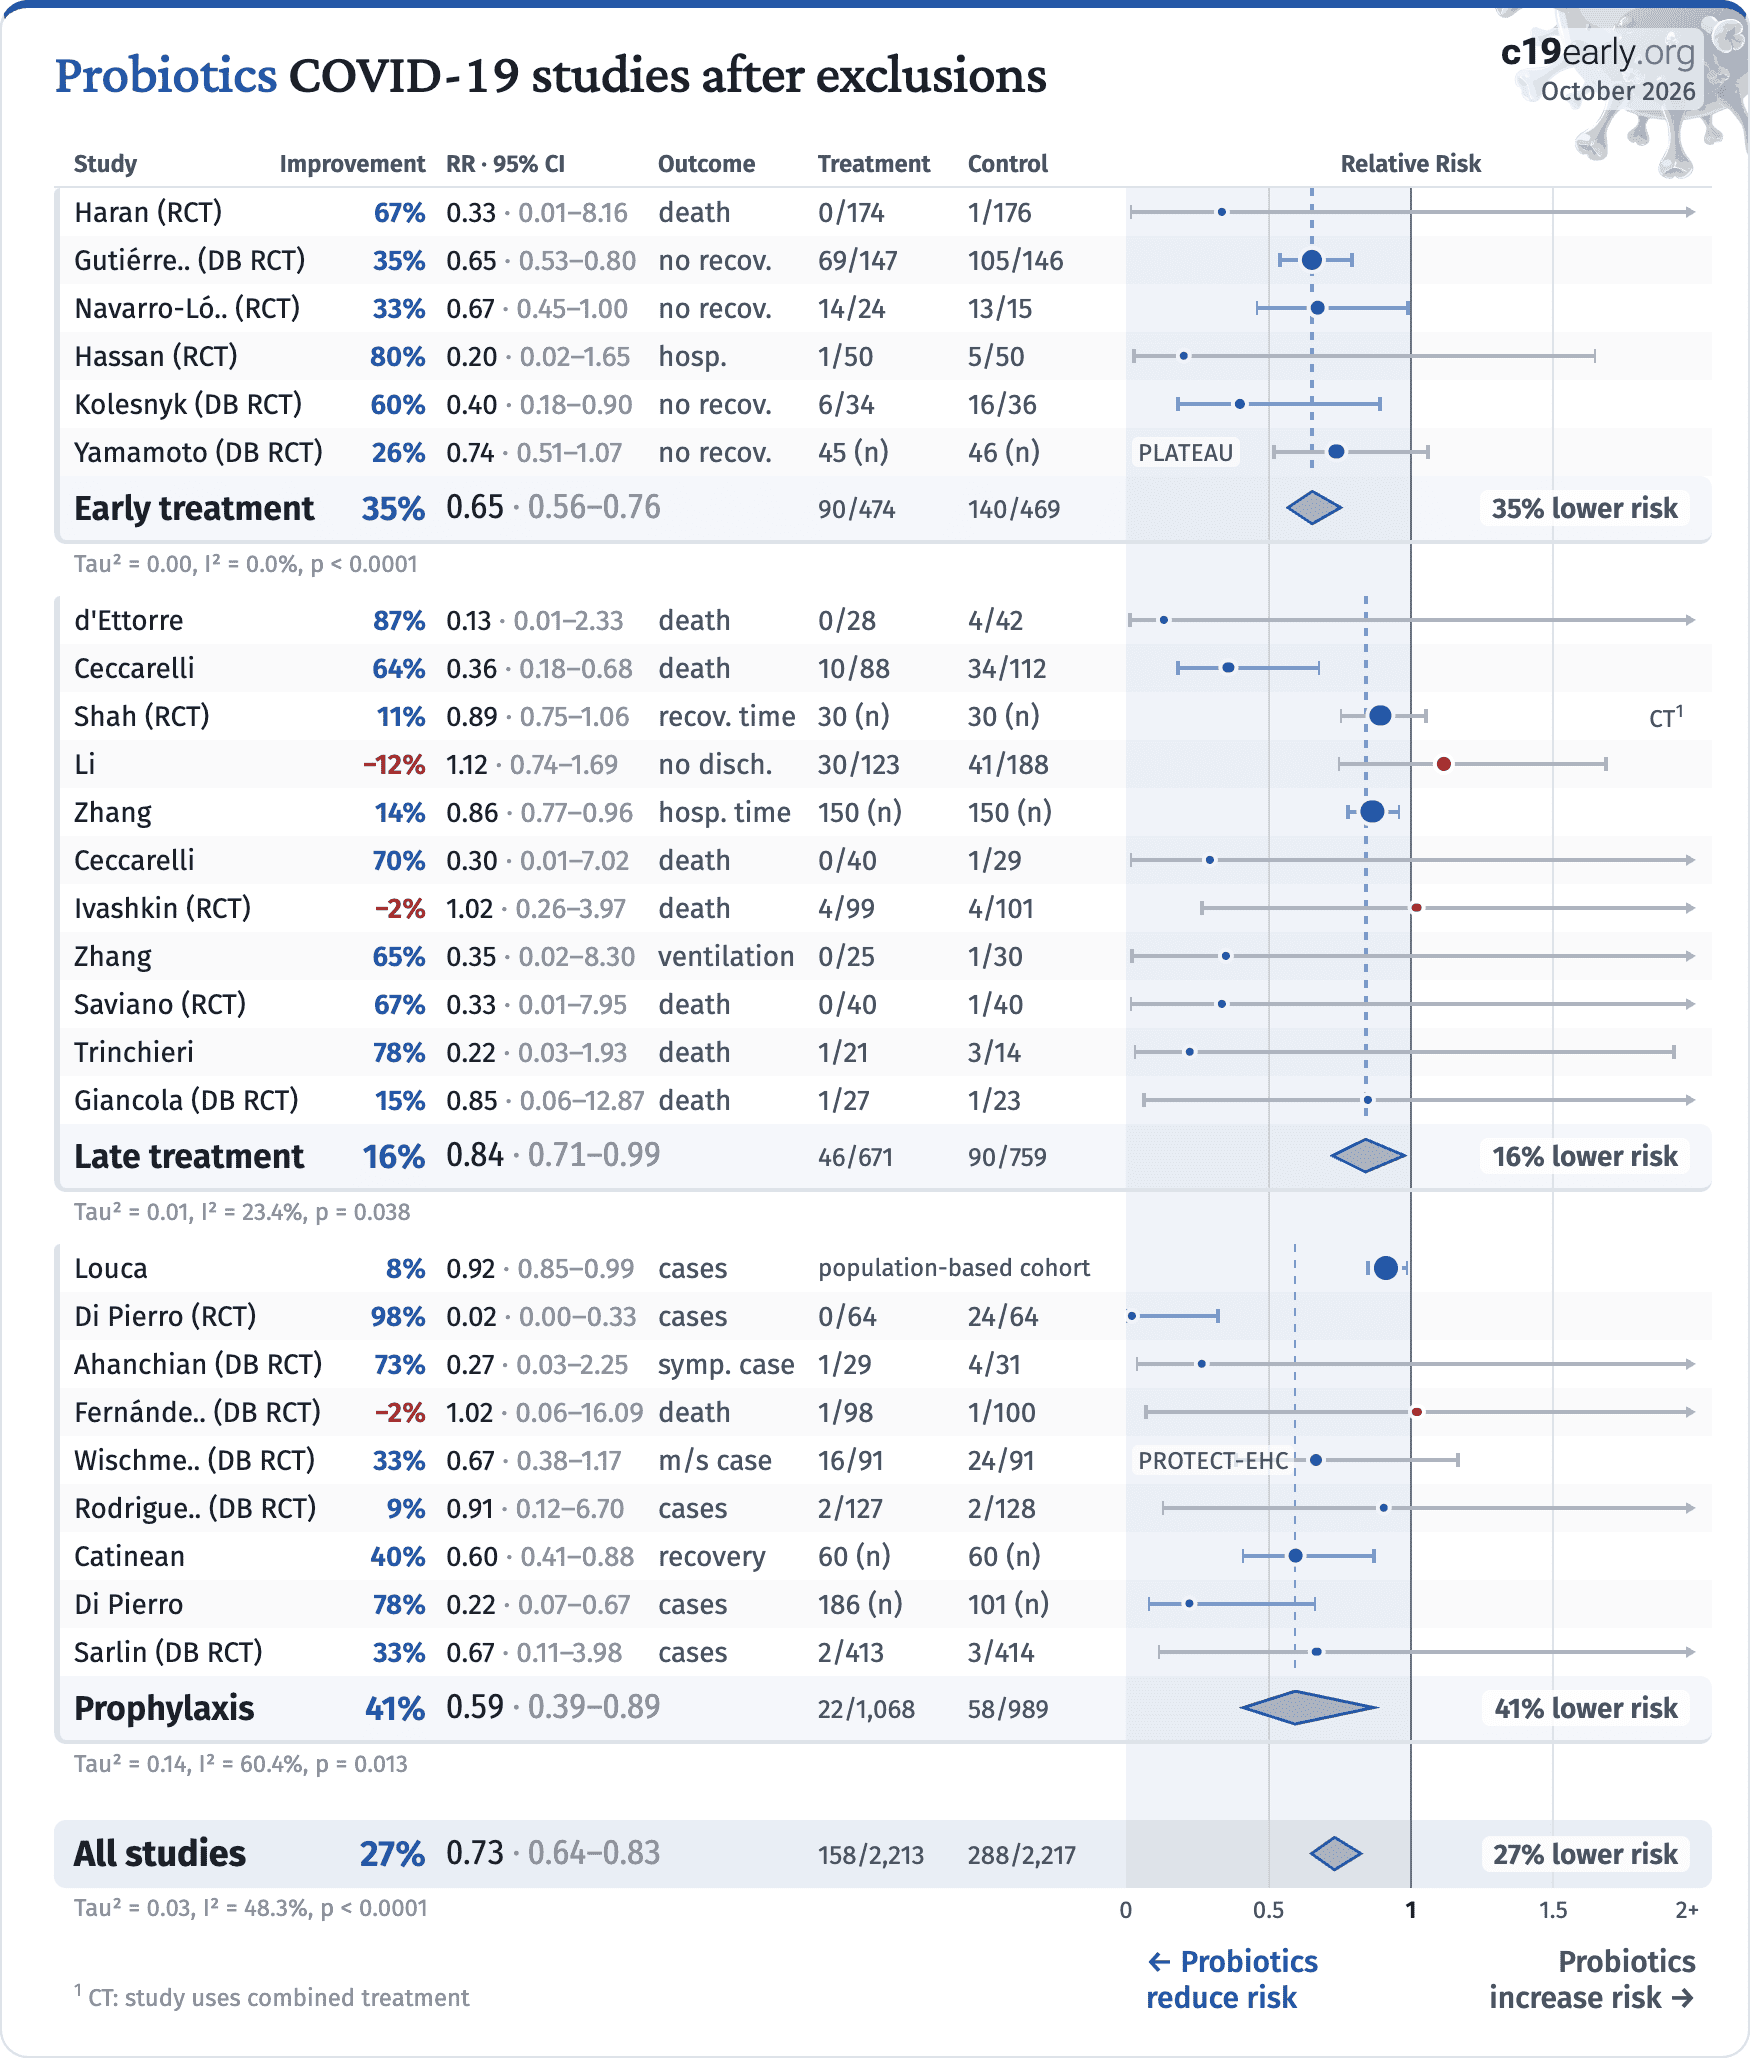
Gutiérrez-Castrellón, 5/24/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Mexico, peer-reviewed, 9 authors, study period 19 August, 2020 - 2 February, 2021, average treatment delay 4.0 days, trial NCT04517422 (history).
|
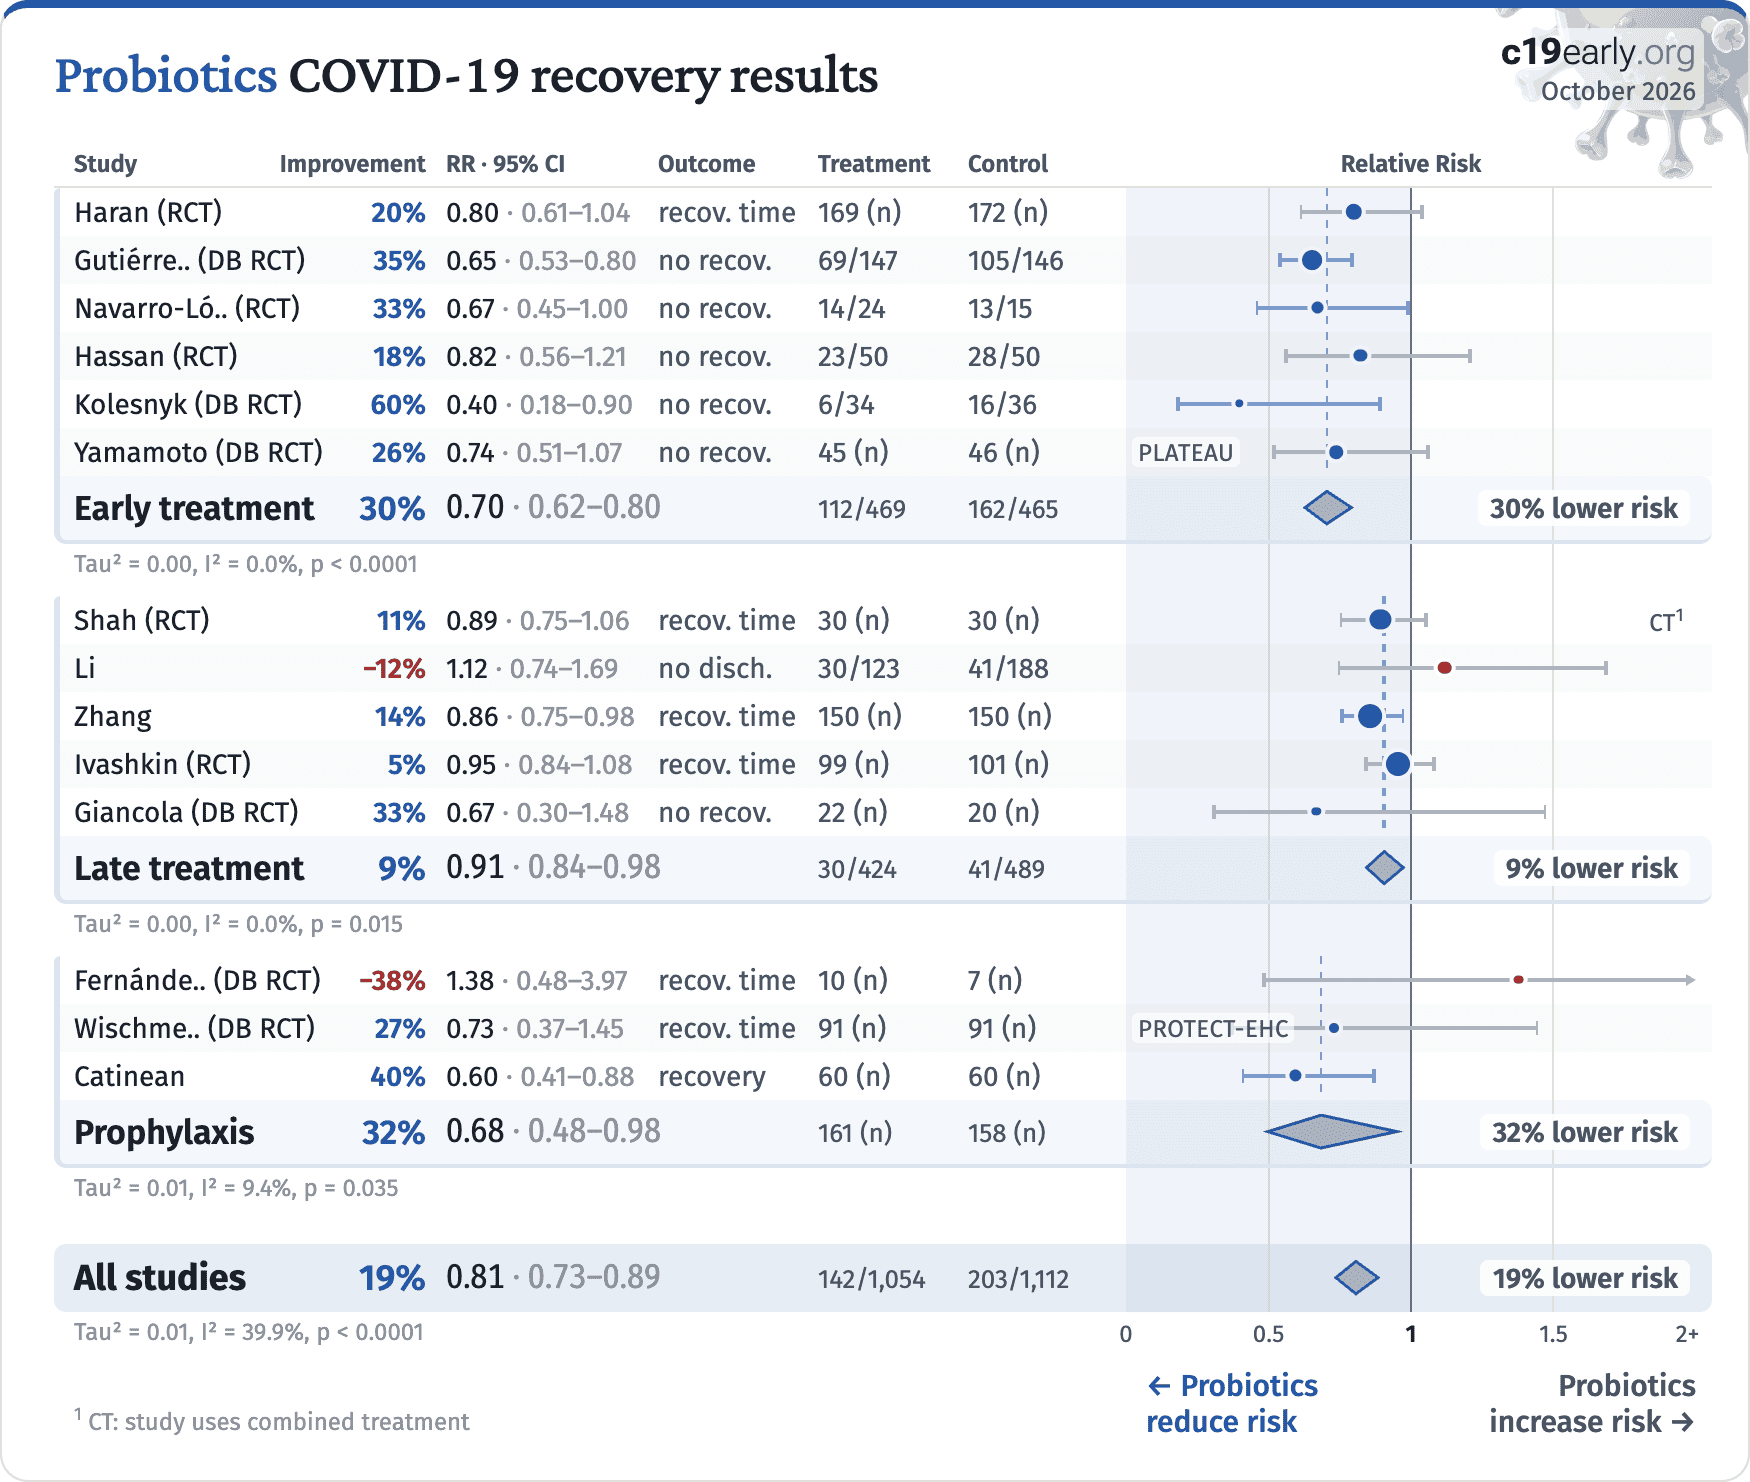
risk of no recovery, 34.7% lower, RR 0.65, p < 0.001, treatment 69 of 147 (46.9%), control 105 of 146 (71.9%), NNT 4.0.
|
|
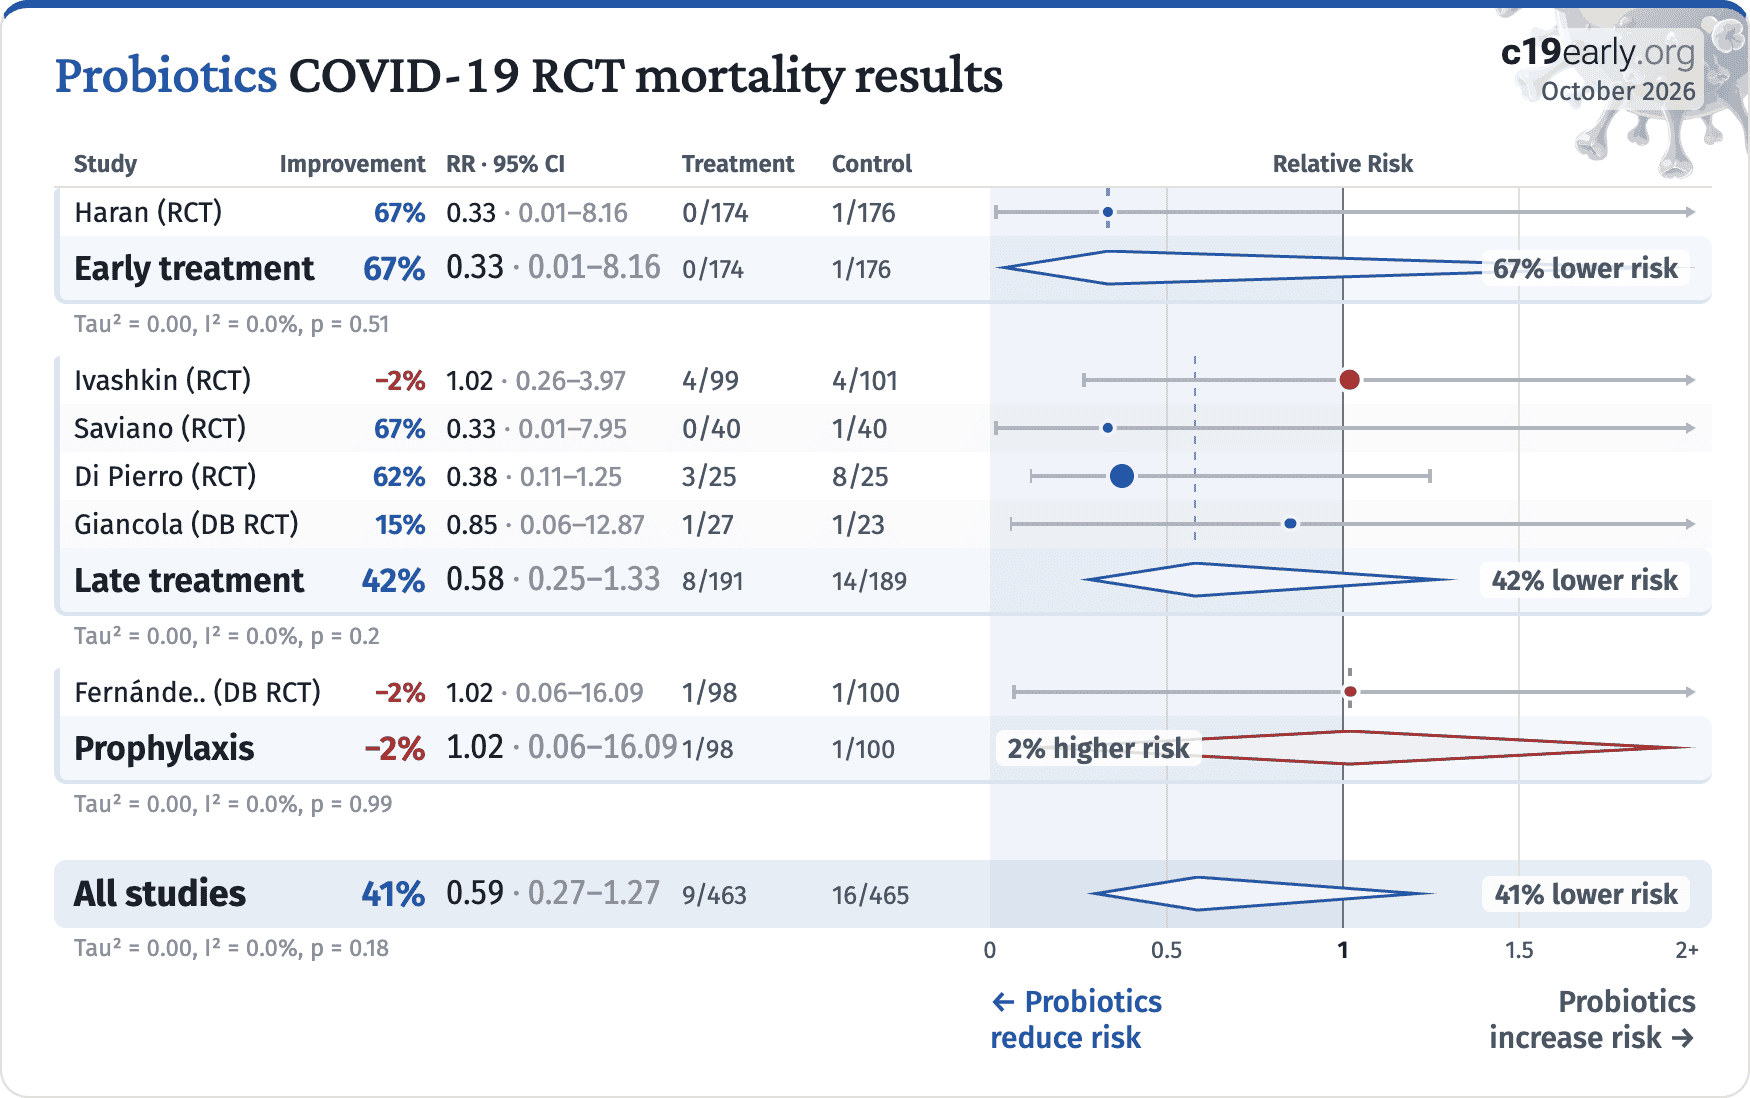
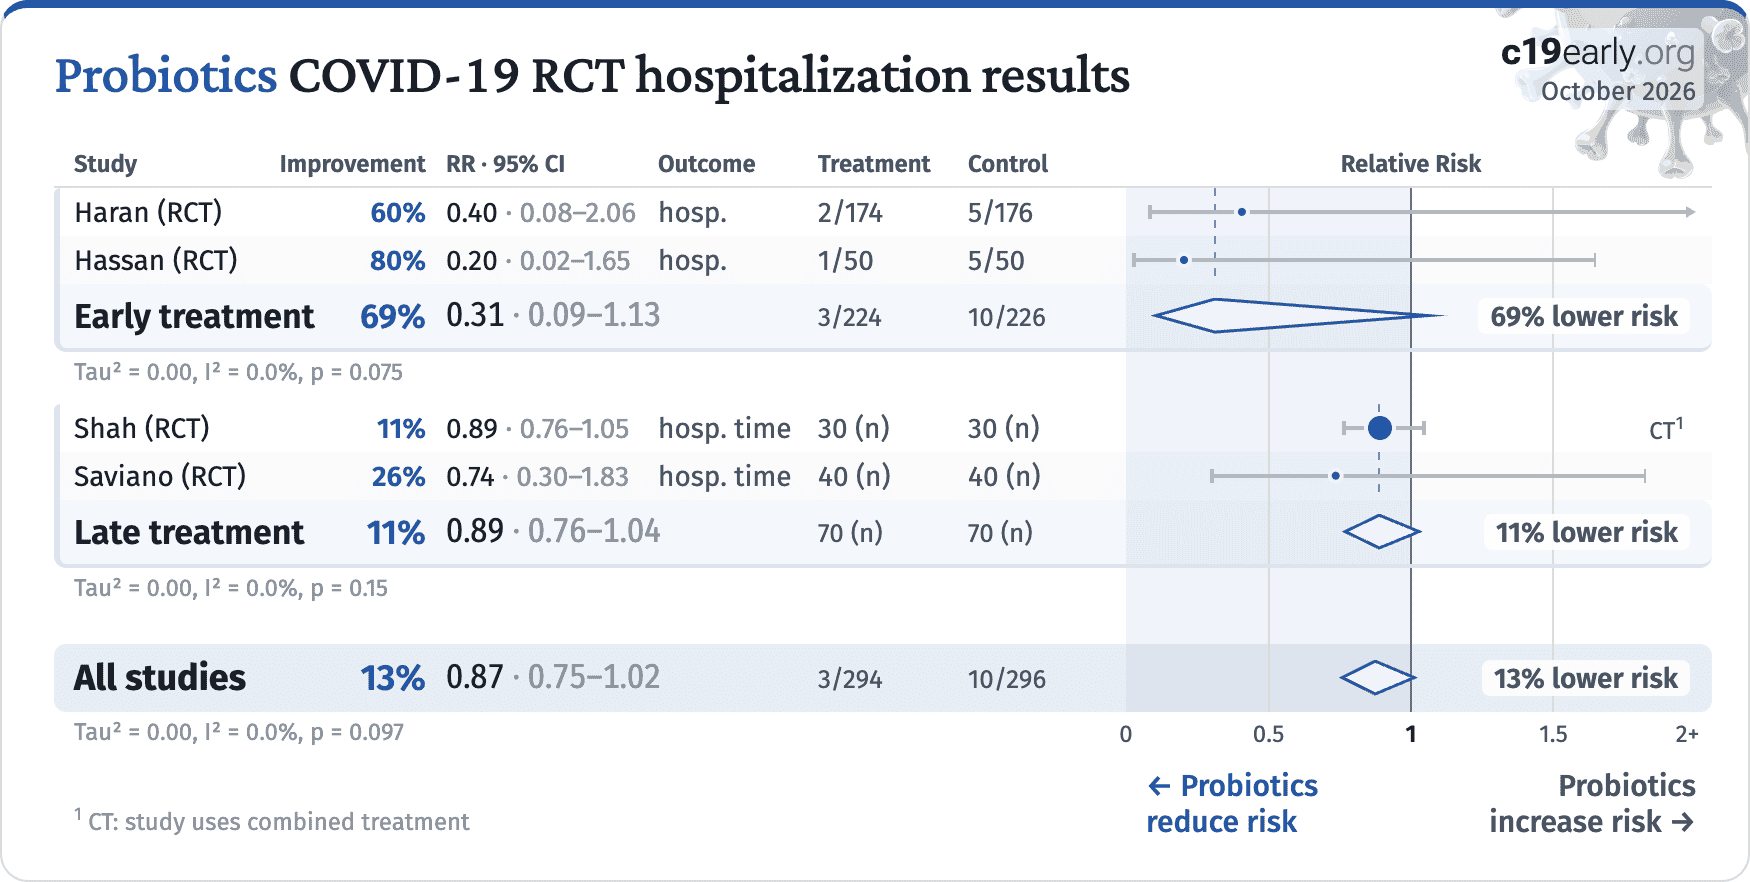
Haran, 3/29/2021, Randomized Controlled Trial, USA, preprint, 6 authors, study period 2 July, 2020 - 23 December, 2020, trial NCT04414124 (history).
|
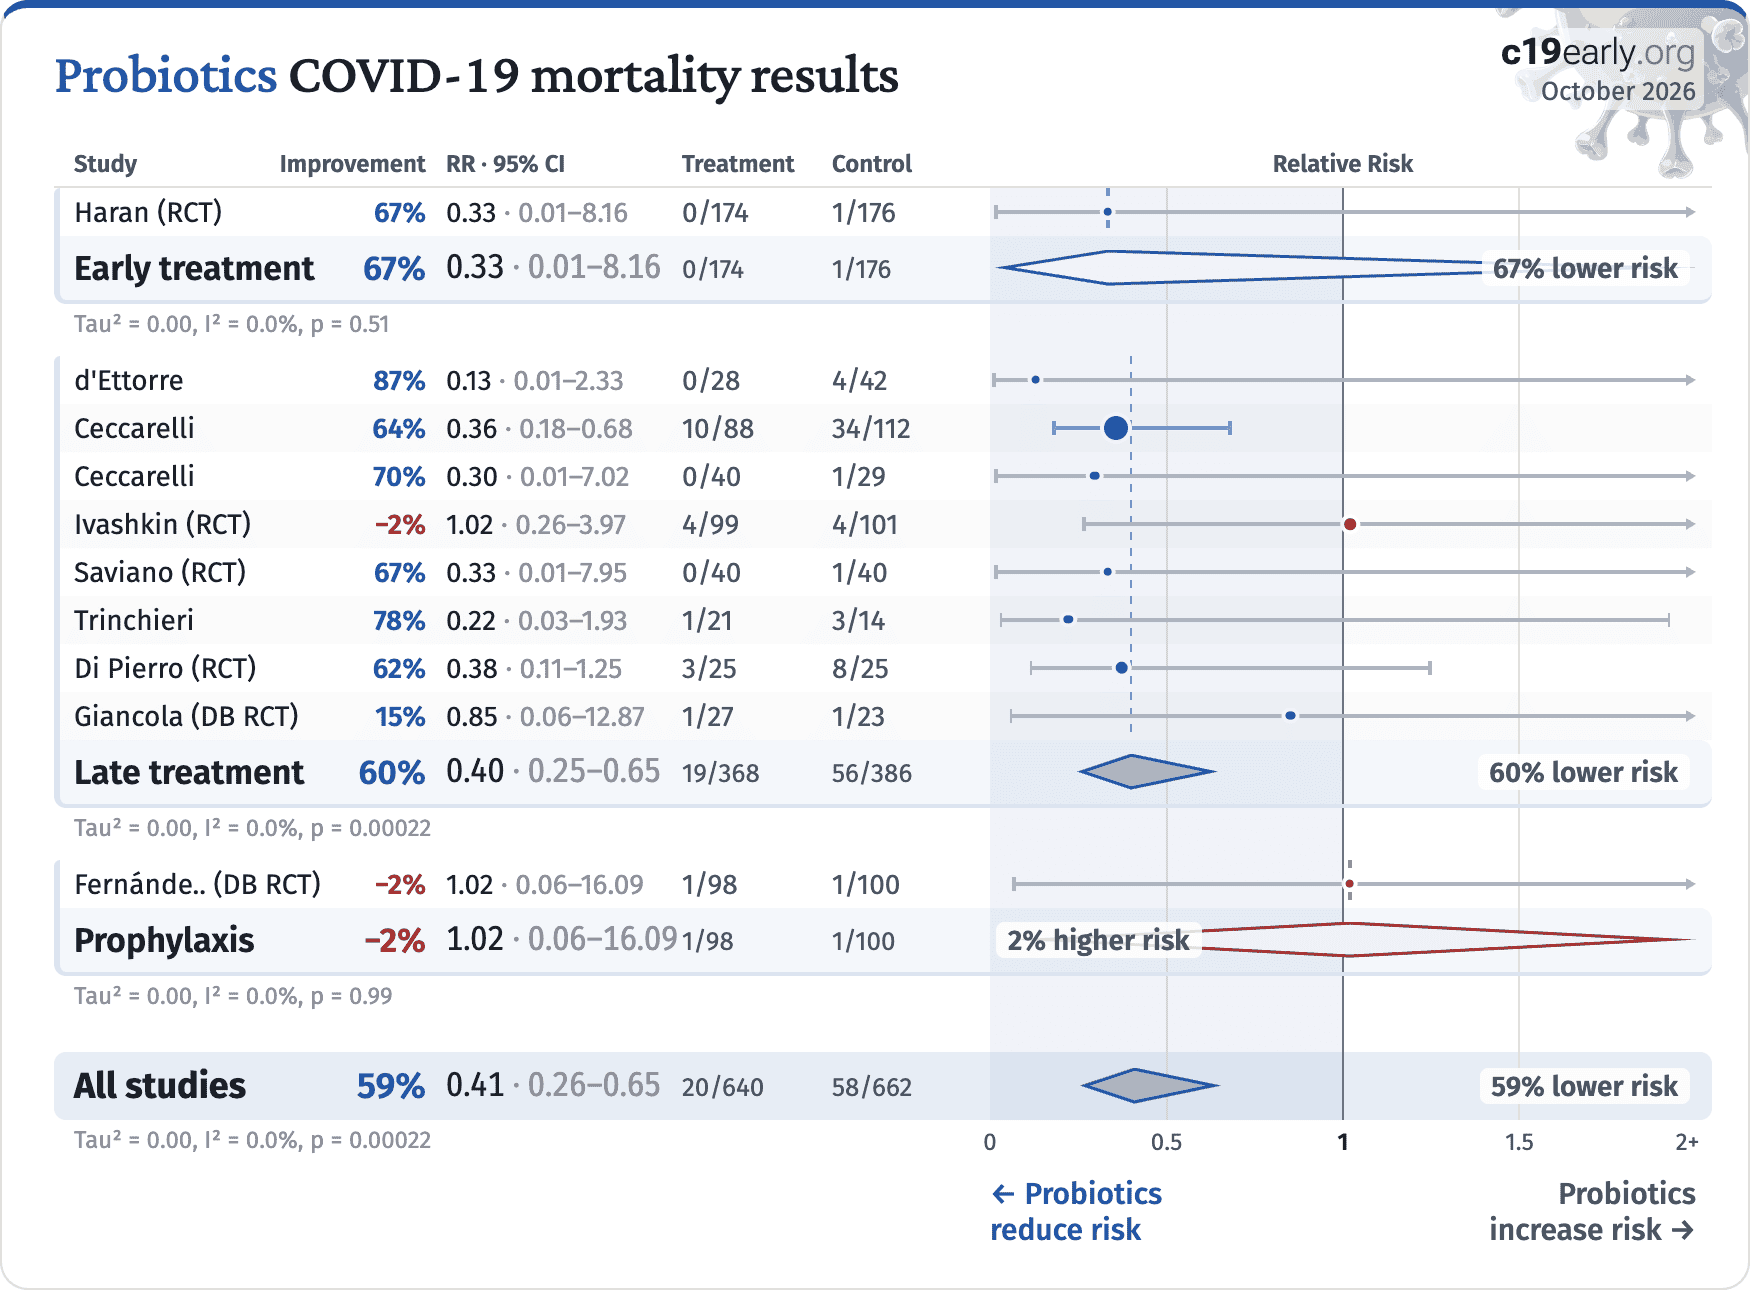
risk of death, 66.5% lower, RR 0.33, p = 1.00, treatment 0 of 174 (0.0%), control 1 of 176 (0.6%), NNT 176, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), death two weeks after study withdrawal.
|
|
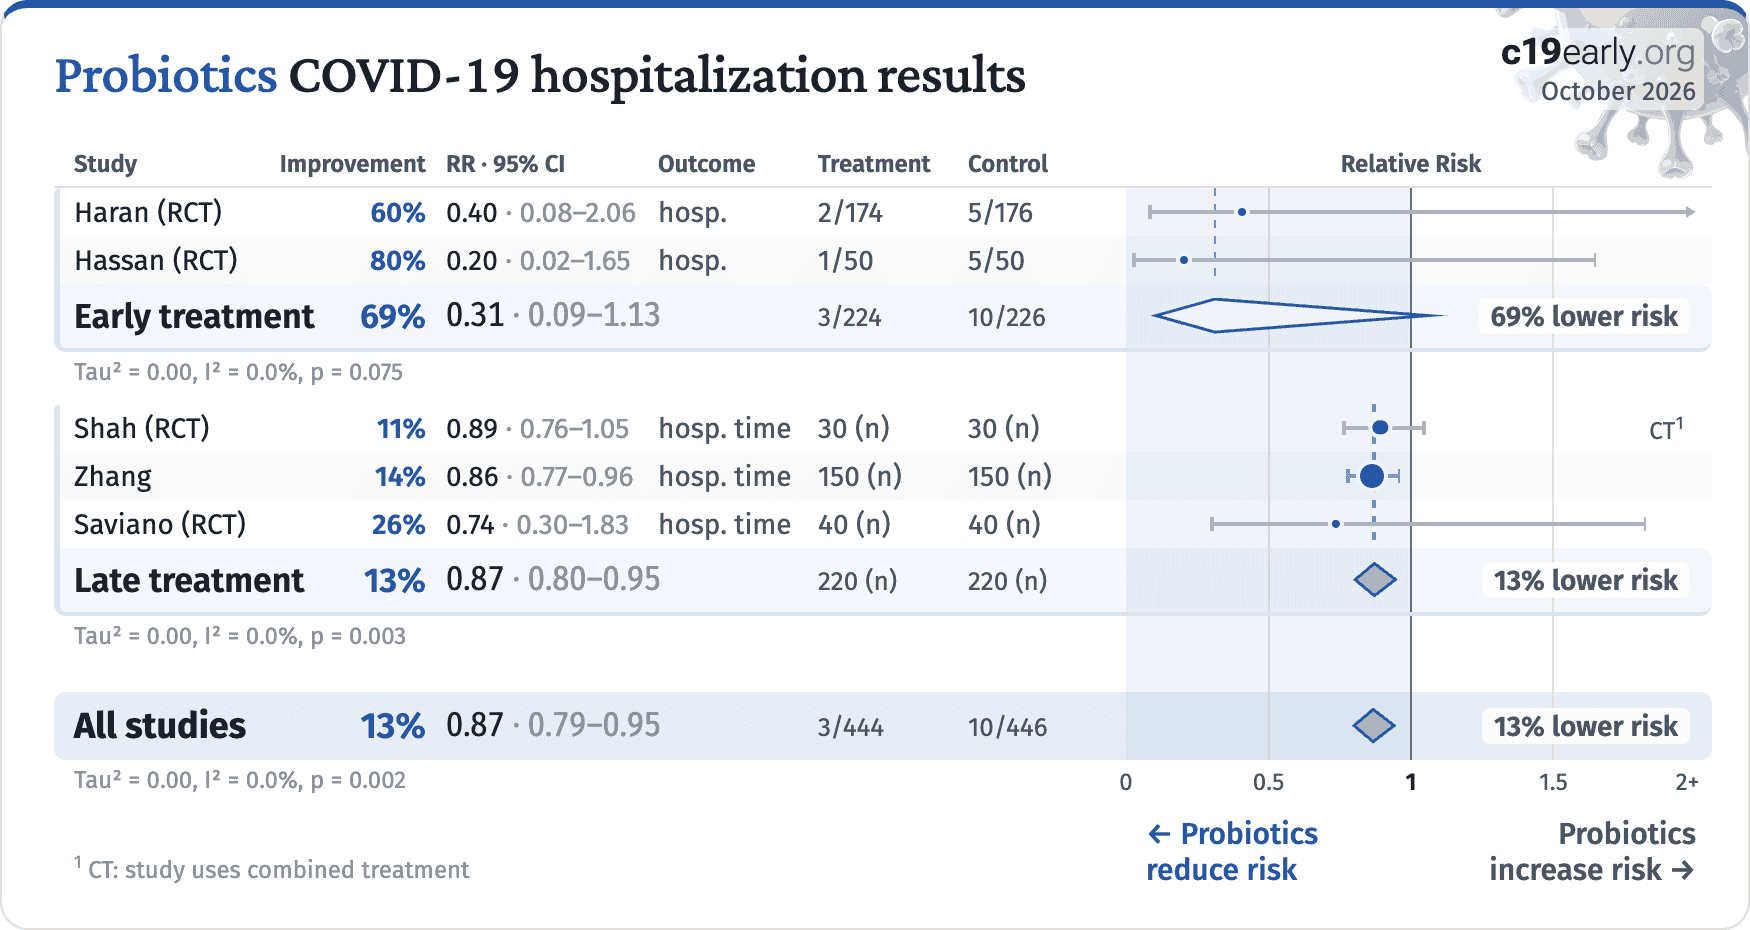
risk of hospitalization, 59.5% lower, RR 0.40, p = 0.45, treatment 2 of 174 (1.1%), control 5 of 176 (2.8%), NNT 59, including treatment period.
|
|
risk of hospitalization/ER/urgent care, 50.0% lower, RR 0.50, p = 0.13, treatment 7 of 169 (4.1%), control 15 of 181 (8.3%), NNT 24.
|
|
time to resolution of symptoms, 20.3% lower, relative time 0.80, p = 0.10, treatment 169, control 172, inverted to make RR<1 favor treatment.
|
|
Hassan, 6/13/2023, Randomized Controlled Trial, Egypt, preprint, 6 authors, study period July 2021 - August 2022.
|
risk of hospitalization, 80.0% lower, RR 0.20, p = 0.20, treatment 1 of 50 (2.0%), control 5 of 50 (10.0%), NNT 12.
|
|
risk of no recovery, 17.9% lower, RR 0.82, p = 0.42, treatment 23 of 50 (46.0%), control 28 of 50 (56.0%), NNT 10.0.
|
|
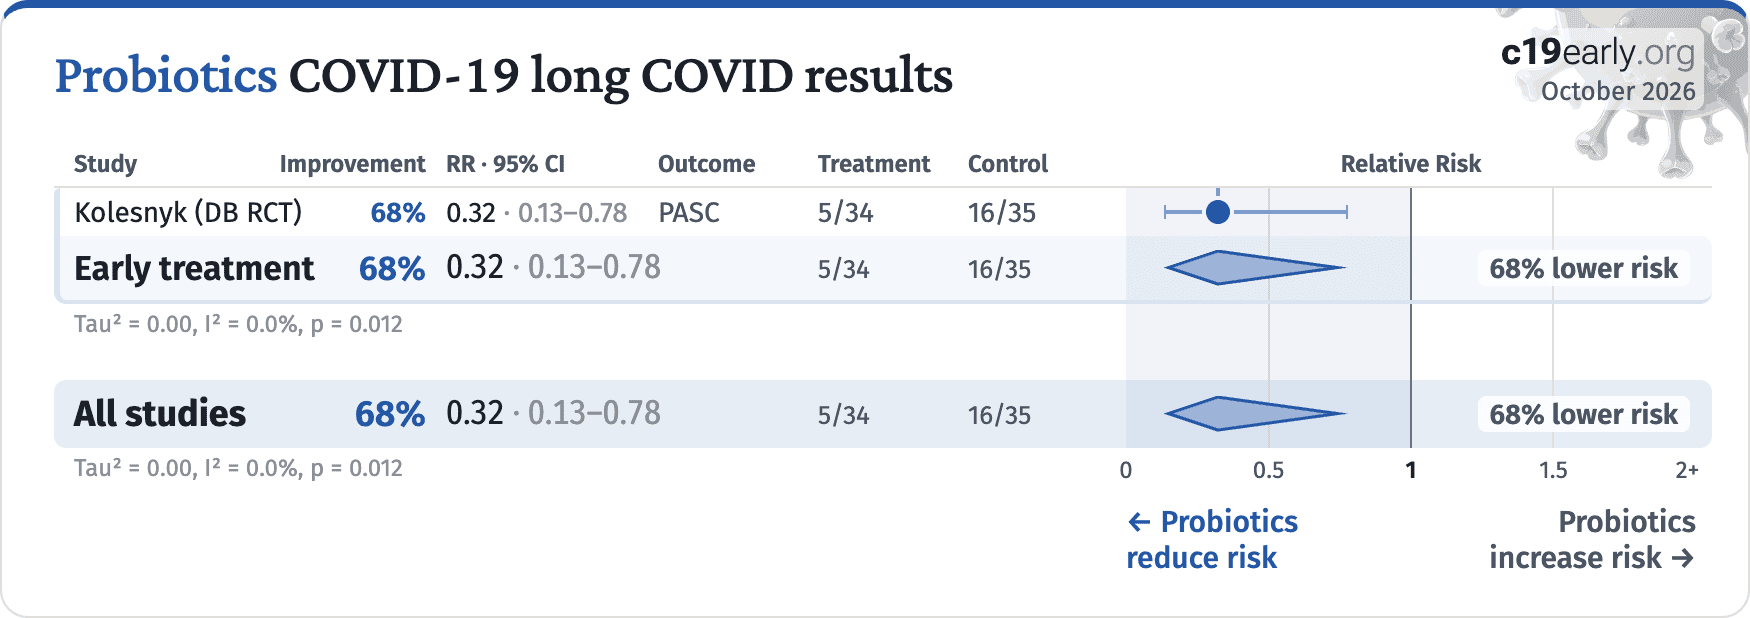
Kolesnyk, 1/4/2024, Double Blind Randomized Controlled Trial, placebo-controlled, Ukraine, peer-reviewed, 10 authors, study period November 2021 - June 2022, trial NCT04907877 (history).
|
WHO score >1, 60.3% lower, RR 0.40, p = 0.02, treatment 6 of 34 (17.6%), control 16 of 36 (44.4%), NNT 3.7.
|
|
recovery time, 21.4% lower, relative time 0.79, p = 0.04, treatment 34, control 36.
|
|
PCFS ≥1, 67.8% lower, RR 0.32, p = 0.008, treatment 5 of 34 (14.7%), control 16 of 35 (45.7%), NNT 3.2, long COVID, Supplementary Table 1.
|
|
Navarro-López, 8/24/2022, Randomized Controlled Trial, Spain, peer-reviewed, 13 authors, study period December 2020 - February 2021, trial NCT04390477 (history).
|
risk of no recovery, 32.7% lower, RR 0.67, p = 0.08, treatment 14 of 24 (58.3%), control 13 of 15 (86.7%), NNT 3.5, day 30.
|
|
risk of no recovery, 53.1% lower, RR 0.47, p = 0.10, treatment 6 of 24 (25.0%), control 8 of 15 (53.3%), NNT 3.5, digestive symptoms, day 30.
|
|
relative recovery, 20.0% better, RR 0.80, p = 0.03, treatment 24, control 15, relative symptom improvement, day 30.
|
|
relative recovery, 26.1% better, RR 0.74, p = 0.06, treatment 24, control 15, relative improvement for digestive symptoms, day 30.
|
|
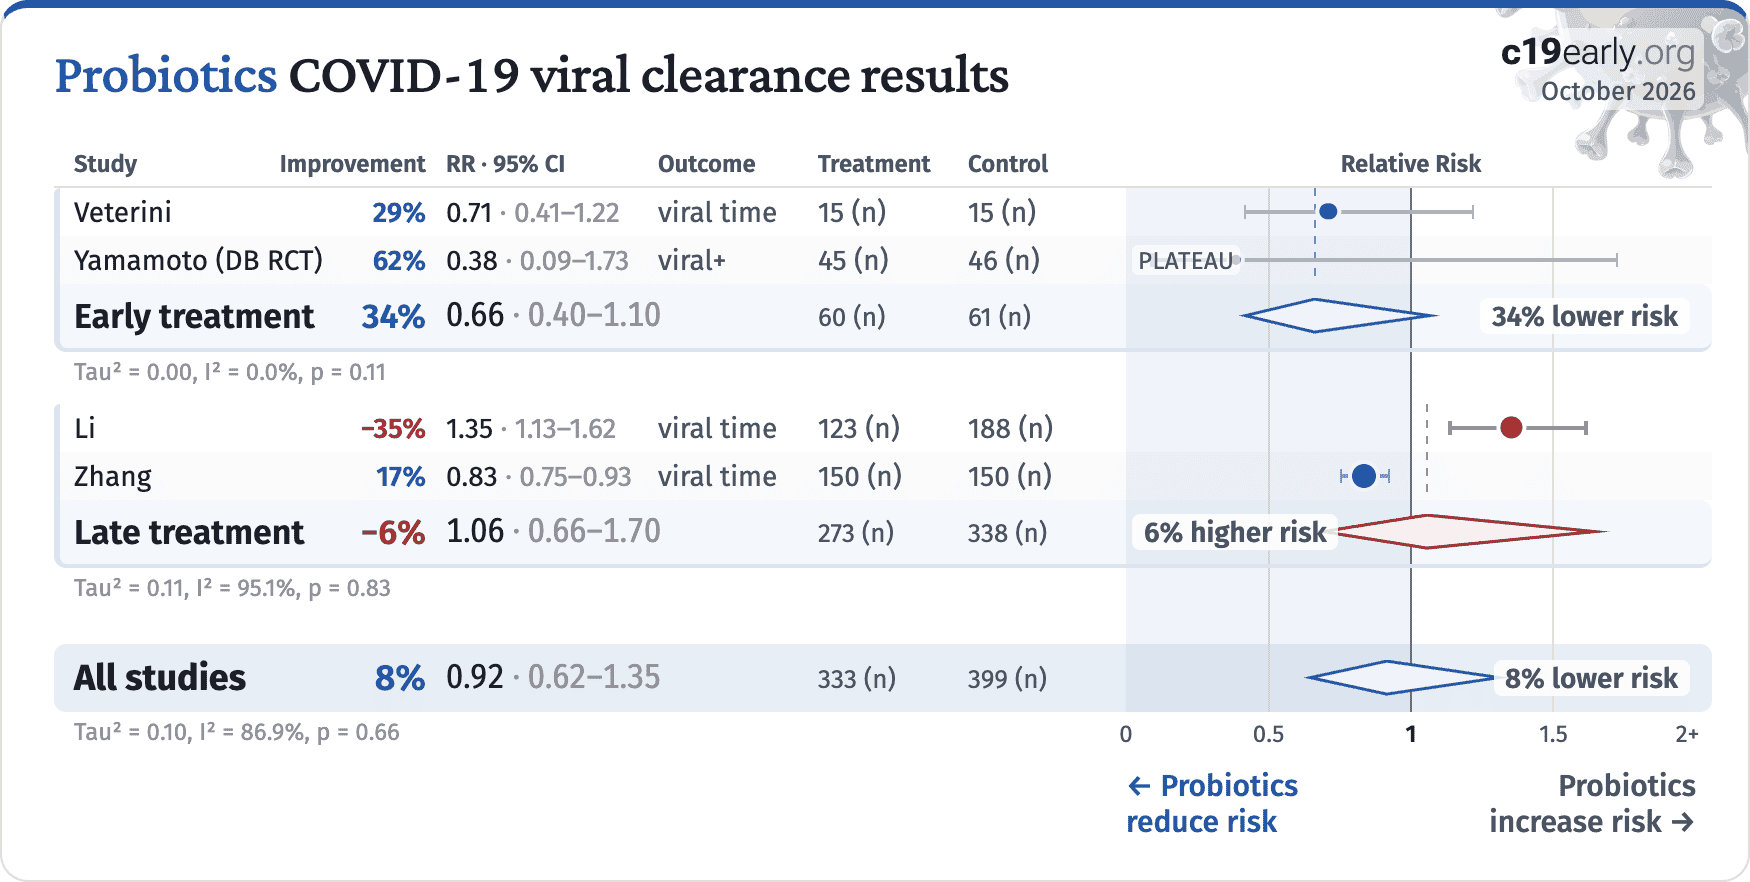
Veterini, 6/30/2021, retrospective, Indonesia, peer-reviewed, 6 authors, excluded in exclusion analyses:
the observered difference in duration could be caused by the baseline difference in Ct values.
|
time to viral-, 29.0% lower, relative time 0.71, p = 0.22, treatment 15, control 15.
|
|
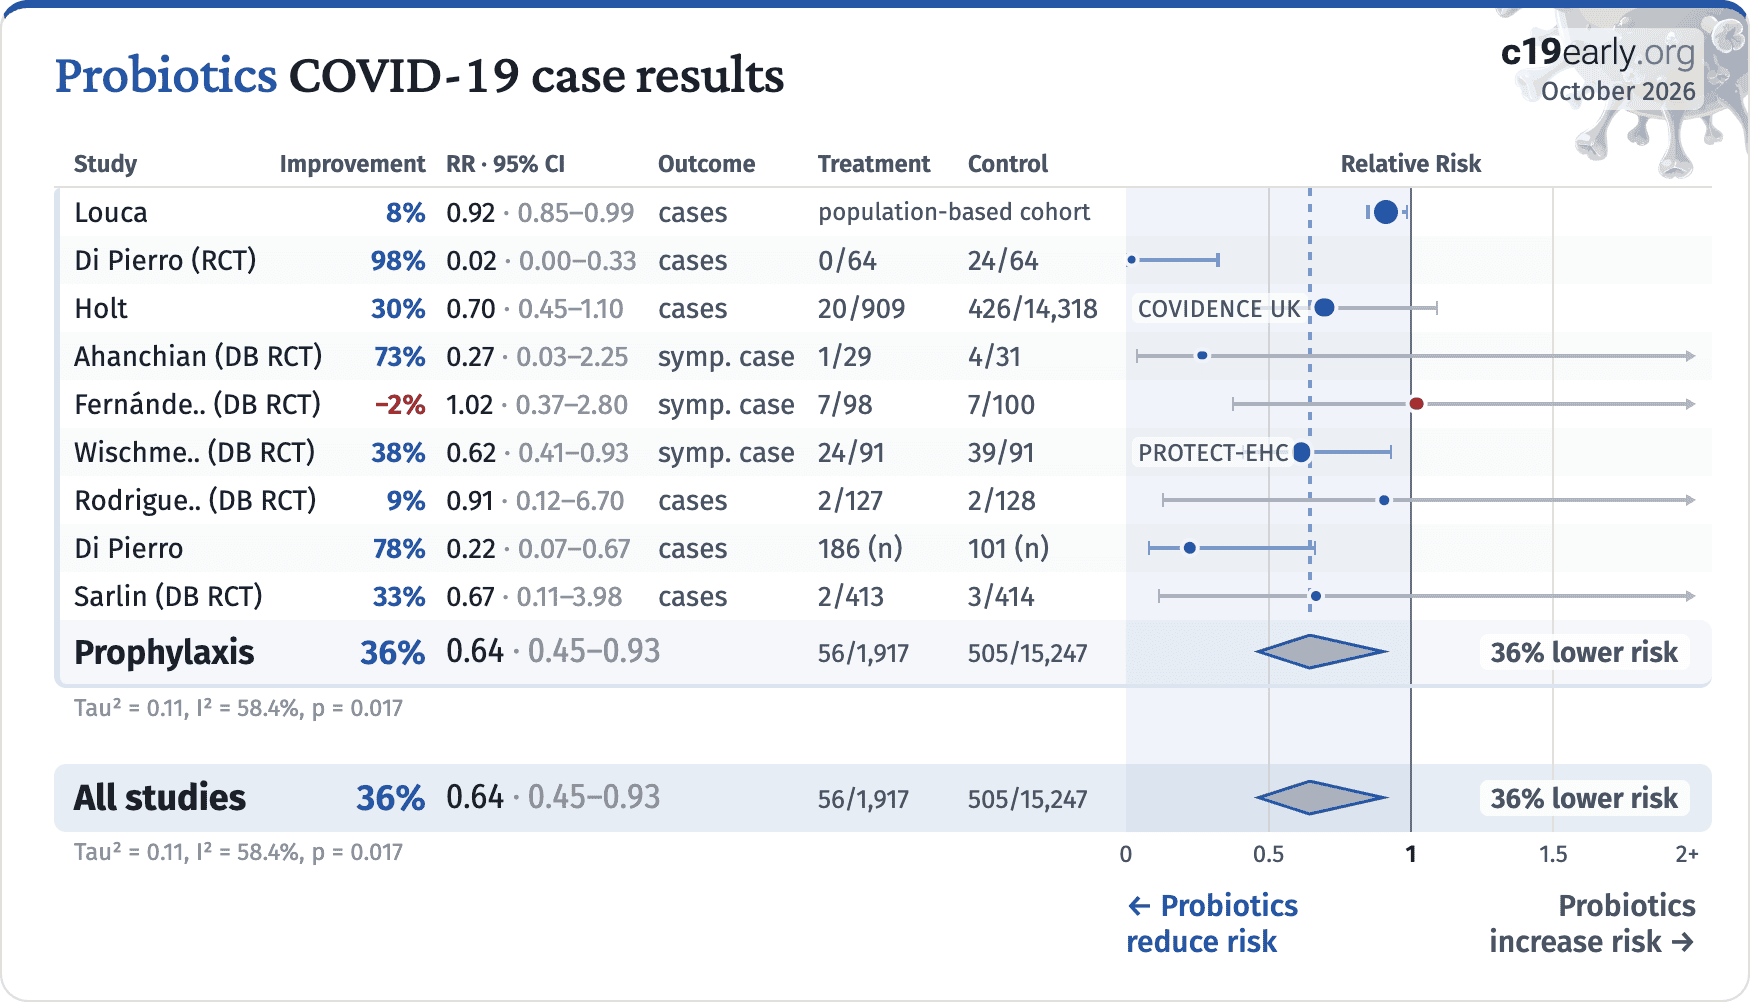
Yamamoto, 10/25/2025, Double Blind Randomized Controlled Trial, placebo-controlled, Japan, peer-reviewed, 29 authors, study period December 2021 - April 2022, trial jRCTs071210097 (PLATEAU).
|
risk of no recovery, 26.0% lower, RR 0.74, p < 0.001, treatment mean 0.76 (±0.18) n=45, control mean 1.02 (±0.3) n=46, relative total severity score, day 14.
|
|
risk of no viral clearance, 61.6% lower, RR 0.38, p = 0.21, treatment 27.9 [19.3-36.4] n=45, control 10.7 [-14.6-36.0] n=46, relative decrease in viral load, mid-recovery, day 4.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Ceccarelli, 8/23/2021, prospective, Italy, peer-reviewed, 10 authors.
|
risk of death, 70.4% lower, RR 0.30, p = 0.42, treatment 0 of 40 (0.0%), control 1 of 29 (3.4%), NNT 29, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
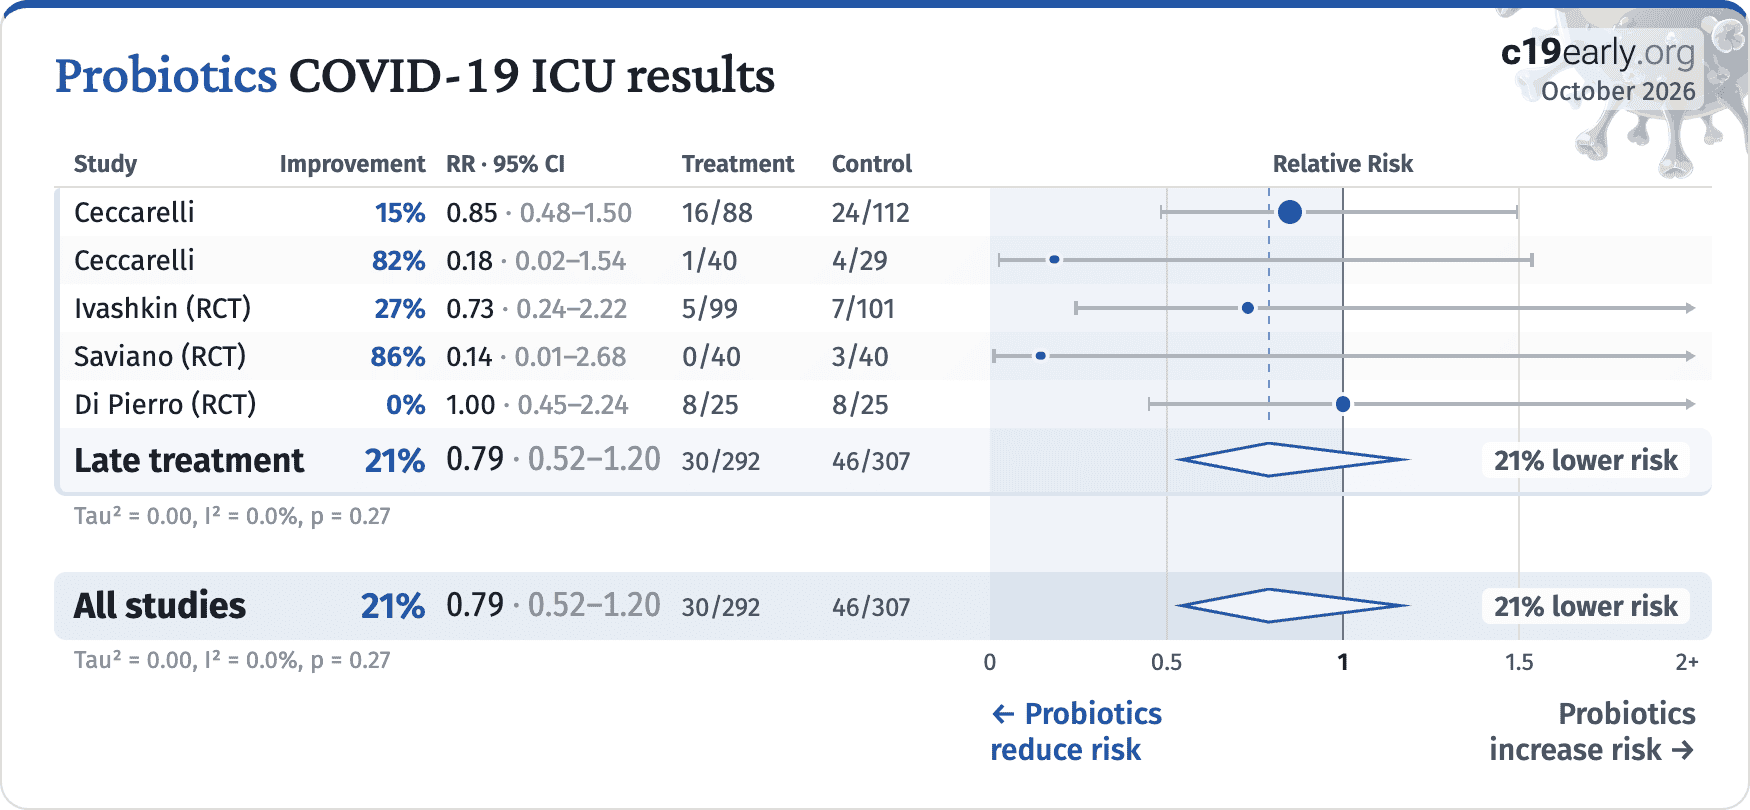
risk of ICU admission, 81.9% lower, RR 0.18, p = 0.15, treatment 1 of 40 (2.5%), control 4 of 29 (13.8%), NNT 8.9.
|
|
Ceccarelli (B), 1/11/2021, retrospective, Italy, peer-reviewed, 14 authors.
|
risk of death, 64.2% lower, RR 0.36, p = 0.003, treatment 10 of 88 (11.4%), control 34 of 112 (30.4%), NNT 5.3, adjusted per study, odds ratio converted to relative risk.
|
|
risk of ICU admission, 15.2% lower, RR 0.85, p = 0.60, treatment 16 of 88 (18.2%), control 24 of 112 (21.4%), NNT 31.
|
|
d'Ettorre, 7/7/2020, retrospective, Italy, peer-reviewed, 17 authors.
|
risk of death, 87.0% lower, RR 0.13, p = 0.14, treatment 0 of 28 (0.0%), control 4 of 42 (9.5%), NNT 10, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
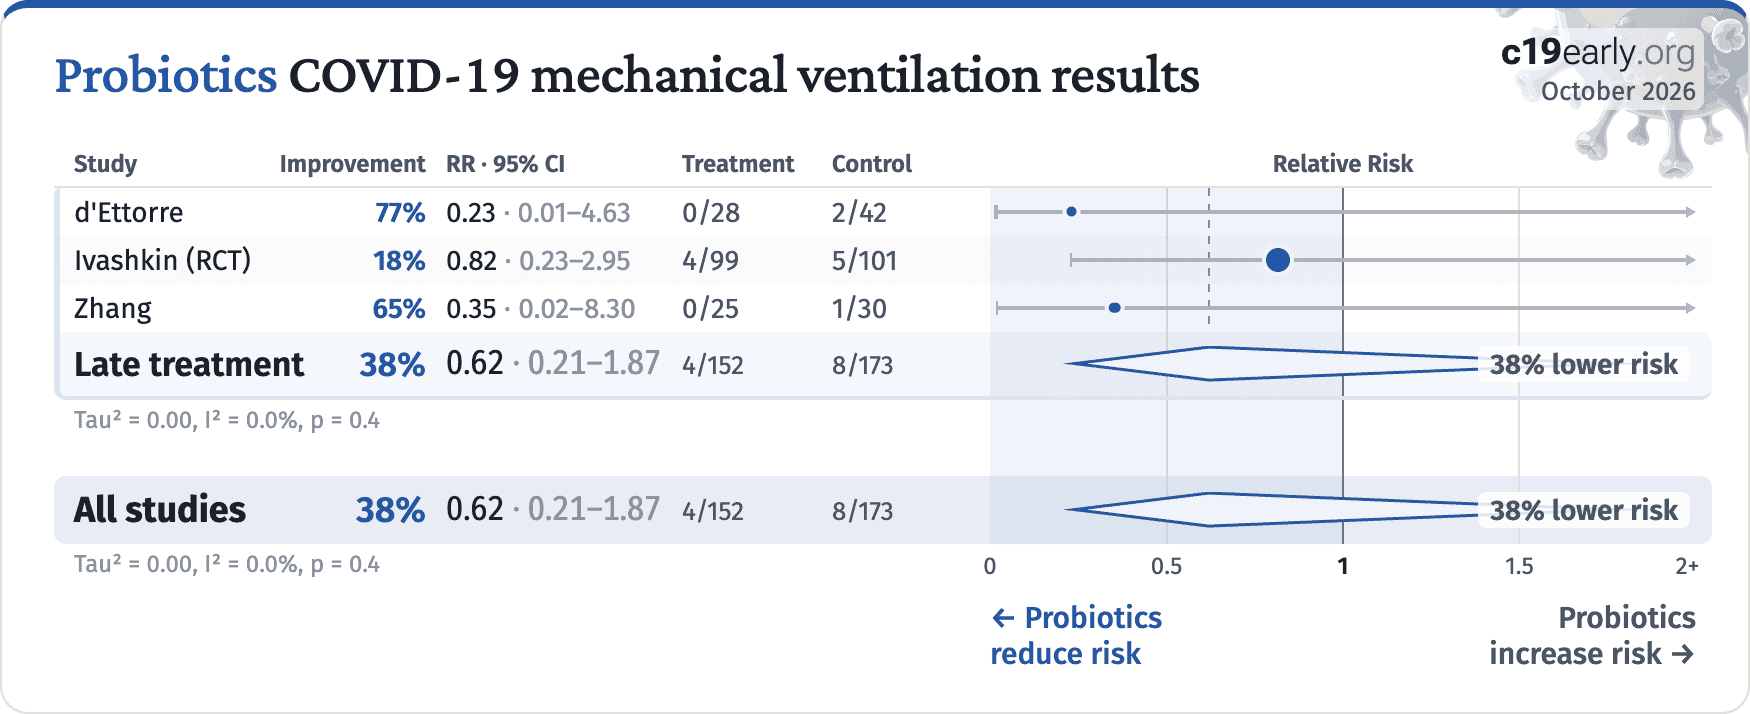
risk of mechanical ventilation, 76.9% lower, RR 0.23, p = 0.51, treatment 0 of 28 (0.0%), control 2 of 42 (4.8%), NNT 21, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
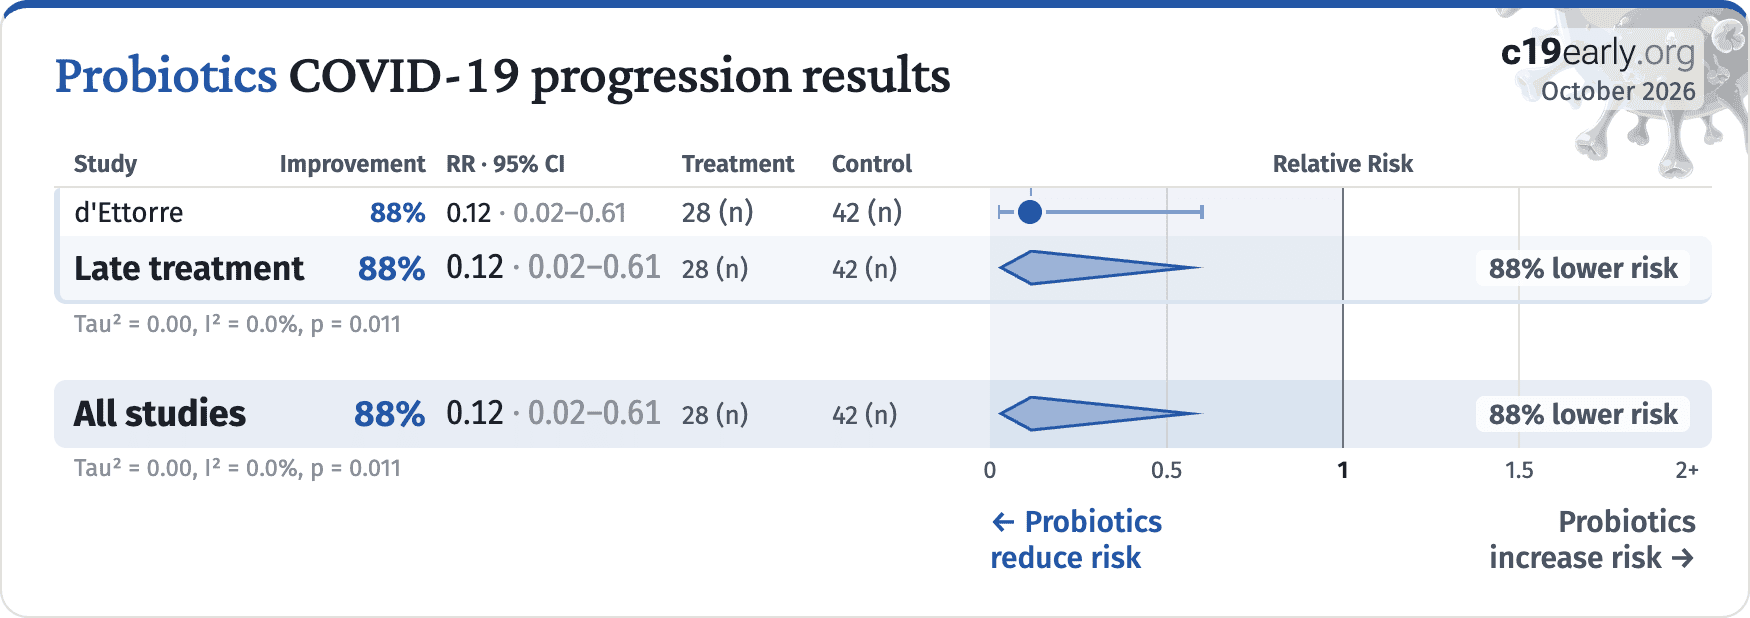
respiratory failure, 88.4% lower, OR 0.12, p = 0.01, treatment 28, control 42, inverted to make OR<1 favor treatment, RR approximated with OR.
|
|
Di Pierro, 9/28/2022, Randomized Controlled Trial, Pakistan, peer-reviewed, mean age 48.5, 7 authors, study period 11 August, 2021 - 18 November, 2021, trial NCT05043376 (history), excluded in exclusion analyses:
unadjusted differences between groups.
|
risk of death, 62.5% lower, RR 0.38, p = 0.17, treatment 3 of 25 (12.0%), control 8 of 25 (32.0%), NNT 5.0.
|
|
risk of ICU admission, no change, RR 1.00, p = 1.00, treatment 8 of 25 (32.0%), control 8 of 25 (32.0%).
|
|
Giancola, 7/16/2024, Double Blind Randomized Controlled Trial, placebo-controlled, Italy, peer-reviewed, 16 authors, study period 18 January, 2022 - 21 March, 2023.
|
risk of death, 14.8% lower, RR 0.85, p = 1.00, treatment 1 of 27 (3.7%), control 1 of 23 (4.3%), NNT 155.
|
|
risk of moderate/severe symptoms, 33.2% lower, RR 0.67, p = 0.32, treatment 22, control 20, combined.
|
|
risk of moderate/severe symptoms, 21.2% higher, RR 1.21, p = 1.00, treatment 4 of 22 (18.2%), control 3 of 20 (15.0%), moderate/severe symptoms, day 180, cardio-respiratory symptoms.
|
|
risk of moderate/severe symptoms, 69.7% lower, RR 0.30, p = 0.12, treatment 2 of 22 (9.1%), control 6 of 20 (30.0%), NNT 4.8, moderate/severe symptoms, day 180, digestive symptoms.
|
|
risk of moderate/severe symptoms, 74.0% lower, RR 0.26, p = 0.06, treatment 2 of 22 (9.1%), control 7 of 20 (35.0%), NNT 3.9, moderate/severe symptoms, day 180, neurological/neurocognitive symptoms.
|
|
risk of moderate/severe symptoms, 13.6% higher, RR 1.14, p = 0.76, treatment 10 of 22 (45.5%), control 8 of 20 (40.0%), moderate/severe symptoms, day 180, systemic symptoms.
|
|
Ivashkin, 10/13/2021, Randomized Controlled Trial, Russia, peer-reviewed, 11 authors, study period December 2020 - March 2021, average treatment delay 8.0 days, trial NCT04854941 (history).
|
risk of death, 2.0% higher, RR 1.02, p = 1.00, treatment 4 of 99 (4.0%), control 4 of 101 (4.0%).
|
|
risk of mechanical ventilation, 18.4% lower, RR 0.82, p = 1.00, treatment 4 of 99 (4.0%), control 5 of 101 (5.0%), NNT 110.
|
|
risk of ICU admission, 27.1% lower, RR 0.73, p = 0.77, treatment 5 of 99 (5.1%), control 7 of 101 (6.9%), NNT 53.
|
|
recovery time, 4.8% lower, relative time 0.95, p = 0.47, treatment 99, control 101.
|
|
Li (B), 3/5/2021, retrospective, China, peer-reviewed, 7 authors, average treatment delay 13.0 days.
|
risk of no hospital discharge, 11.8% higher, RR 1.12, p = 0.68, treatment 30 of 123 (24.4%), control 41 of 188 (21.8%).
|
|
time to discharge, 60.0% higher, relative time 1.60, p < 0.001, treatment 123, control 188.
|
|
time to viral-, 35.3% higher, relative time 1.35, p < 0.001, treatment 123, control 188.
|
|
Saviano, 6/28/2022, Randomized Controlled Trial, Italy, peer-reviewed, mean age 59.8, 9 authors.
|
risk of death, 66.7% lower, RR 0.33, p = 1.00, treatment 0 of 40 (0.0%), control 1 of 40 (2.5%), NNT 40, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of ICU admission, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 40 (0.0%), control 3 of 40 (7.5%), NNT 13, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
hospitalization time, 26.3% lower, relative time 0.74, p = 0.52, treatment mean 14.0 (±6.0) n=40, control mean 19.0 (±10.0) n=40.
|
|
Shah, 2/2/2021, Randomized Controlled Trial, India, peer-reviewed, 3 authors, this trial uses multiple treatments in the treatment arm (combined with multi-enzyme formulation) - results of individual treatments may vary.
|
time to clinical improvement, 10.8% lower, relative time 0.89, p = 0.19, treatment 30, control 30.
|
|
hospitalization time, 10.6% lower, relative time 0.89, p = 0.18, treatment 30, control 30.
|
|
risk of no clinical improvement, 83.3% lower, RR 0.17, p = 0.005, treatment 2 of 30 (6.7%), control 12 of 30 (40.0%), NNT 3.0, day 10 mid-recovery.
|
|
risk of no clinical improvement, 3.7% lower, RR 0.96, p = 1.00, treatment 26 of 30 (86.7%), control 27 of 30 (90.0%), NNT 30, day 7.
|
|
Trinchieri, 8/1/2022, retrospective, Italy, peer-reviewed, 10 authors, study period November 2020 - March 2021.
|
risk of death, 77.8% lower, RR 0.22, p = 0.28, treatment 1 of 21 (4.8%), control 3 of 14 (21.4%), NNT 6.0.
|
|
risk of miscellaneous, 77.8% lower, RR 0.22, p < 0.001, treatment 4 of 21 (19.0%), control 12 of 14 (85.7%), NNT 1.5, CPAP, day 7.
|
|
risk of miscellaneous, 9.5% lower, RR 0.90, p = 0.51, treatment 19 of 21 (90.5%), control 14 of 14 (100.0%), NNT 10, CPAP, day 3.
|
|
Zhang (B), 3/2/2022, retrospective, China, peer-reviewed, 12 authors, trial NCT04581018 (history).
|
risk of mechanical ventilation, 64.7% lower, RR 0.35, p = 1.00, treatment 0 of 25 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of no antibody formation, 67.3% lower, RR 0.33, p = 0.06, treatment 3 of 25 (12.0%), control 11 of 30 (36.7%), NNT 4.1.
|
|
Zhang (C), 8/4/2021, retrospective, China, peer-reviewed, 14 authors.
|
hospitalization time, 13.6% lower, relative time 0.86, p = 0.009, treatment 150, control 150, PSM.
|
|
time to clinical improvement, 14.3% lower, relative time 0.86, p = 0.02, treatment 150, control 150, PSM.
|
|
time to viral-, 16.7% lower, relative time 0.83, p < 0.001, treatment 150, control 150, PSM.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Ahanchian, 5/31/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, 14 authors, study period July 2020 - August 2020, trial IRCT20101020004976N6.
|
respiratory symptoms, 73.3% lower, RR 0.27, p = 0.35, treatment 1 of 29 (3.4%), control 4 of 31 (12.9%), NNT 11.
|
|
risk of case, 85.3% lower, RR 0.15, p = 0.24, treatment 0 of 29 (0.0%), control 3 of 31 (9.7%), NNT 10, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Catinean, 1/17/2023, retrospective, Romania, peer-reviewed, 4 authors, study period 15 September, 2020 - 15 February, 2021.
|
symptom resolution, 40.5% lower, HR 0.60, p = 0.008, treatment 60, control 60, inverted to make HR<1 favor treatment.
|
|
resolution of fever, 37.5% lower, HR 0.62, p = 0.02, treatment 60, control 60, inverted to make HR<1 favor treatment, fever.
|
|
Di Pierro (C), 9/30/2023, retrospective, Italy, peer-reviewed, 10 authors, study period January 2022 - March 2022, trial NCT05840926 (history).
|
risk of case, 77.8% lower, RR 0.22, p = 0.007, treatment mean 0.02 (±0.15) n=186, control mean 0.09 (±0.29) n=101.
|
|
Di Pierro (D), 3/12/2021, Randomized Controlled Trial, Italy, peer-reviewed, 2 authors, study period September 2020 - December 2020.
|
risk of case, 98.0% lower, RR 0.02, p < 0.001, treatment 0 of 64 (0.0%), control 24 of 64 (37.5%), NNT 2.7, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Fernández-Ferreiro, 1/5/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, peer-reviewed, mean age 83.1, 9 authors, study period January 2021 - April 2021, trial NCT04756466 (history).
|
risk of death, 2.0% higher, RR 1.02, p = 1.00, treatment 1 of 98 (1.0%), control 1 of 100 (1.0%).
|
|
recovery time, 37.8% higher, relative time 1.38, p = 0.56, treatment mean 8.45 (±9.69) n=10, control mean 6.13 (±4.22) n=7.
|
|
risk of severe case, 27.6% higher, RR 1.28, p = 0.75, treatment 5 of 98 (5.1%), control 4 of 100 (4.0%).
|
|
risk of symptomatic case, 2.0% higher, RR 1.02, p = 1.00, treatment 7 of 98 (7.1%), control 7 of 100 (7.0%).
|
|
risk of case, 35.1% higher, RR 1.35, p = 0.53, treatment 11 of 98 (11.2%), control 8 of 100 (8.0%), adjusted per study.
|
|
Holt, 3/30/2021, prospective, United Kingdom, peer-reviewed, 34 authors, study period 1 May, 2020 - 5 February, 2021, trial NCT04330599 (history) (COVIDENCE UK), excluded in exclusion analyses:
significant unadjusted confounding possible.
|
risk of case, 30.4% lower, RR 0.70, p = 0.11, treatment 20 of 909 (2.2%), control 426 of 14,318 (3.0%), NNT 129, adjusted per study, odds ratio converted to relative risk, minimally adjusted, group sizes approximated.
|
|
Louca, 11/30/2020, retrospective, United Kingdom, peer-reviewed, 26 authors.
|
risk of case, 8.5% lower, RR 0.92, p = 0.03, odds ratio converted to relative risk, United Kingdom, all adjustment model.
|
|
Rodriguez-Blanque, 8/3/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, peer-reviewed, 7 authors, study period 24 April, 2020 - 20 July, 2020, trial NCT04366180 (history).
|
risk of case, 9.3% lower, RR 0.91, p = 0.92, treatment 2 of 127 (1.6%), control 2 of 128 (1.6%), adjusted per study, multivariable.
|
|
Sarlin, 11/2/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Finland, peer-reviewed, 7 authors, study period 1 August, 2020 - 31 May, 2021.
|
risk of case, 33.2% lower, RR 0.67, p = 1.00, treatment 2 of 413 (0.5%), control 3 of 414 (0.7%), NNT 416.
|
|
Wischmeyer, 1/5/2022, Double Blind Randomized Controlled Trial, USA, preprint, 21 authors, study period 24 June, 2020 - 8 July, 2021, trial NCT04399252 (history) (PROTECT-EHC).
|
risk of moderate/severe case, 33.3% lower, RR 0.67, p = 0.15, treatment 16 of 91 (17.6%), control 24 of 91 (26.4%), NNT 11.
|
|
risk of symptomatic case, 38.5% lower, RR 0.62, p = 0.02, treatment 24 of 91 (26.4%), control 39 of 91 (42.9%), NNT 6.1, primary outcome.
|
|
recovery time, 27.3% lower, relative time 0.73, p = 0.37, treatment 91, control 91.
|
|
risk of case, 42.9% lower, RR 0.57, p = 0.17, treatment 8 of 91 (8.8%), control 14 of 91 (15.4%), NNT 15.
|