Convalescent Plasma for COVID-19: real-time meta-analysis of 58 studies

Abstract
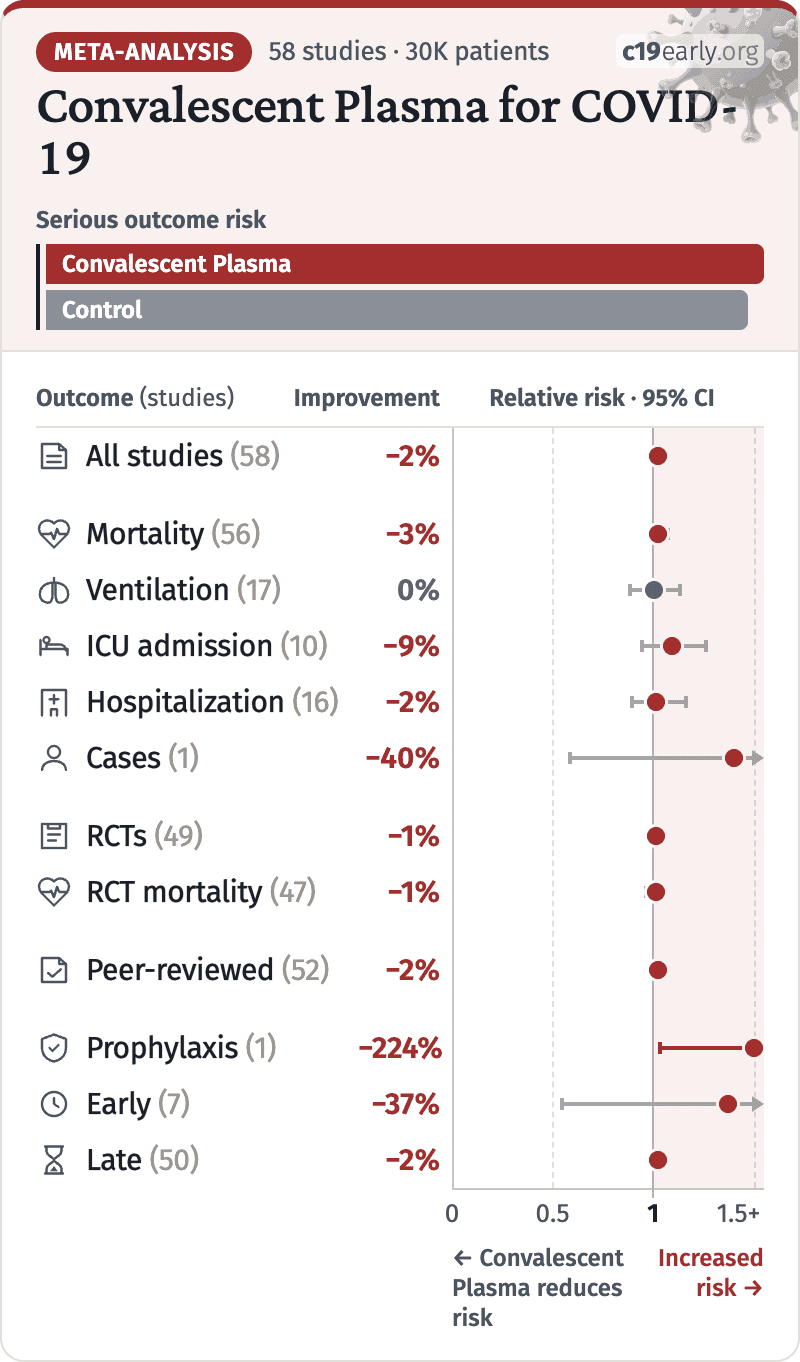
Meta-analysis using the most serious outcome reported shows 2% [-2‑6%] higher risk, without reaching statistical significance.
29 RCTs with 3,534 patients have not reported results (up to 6 years late).
All data and sources to reproduce this analysis are in the appendix.
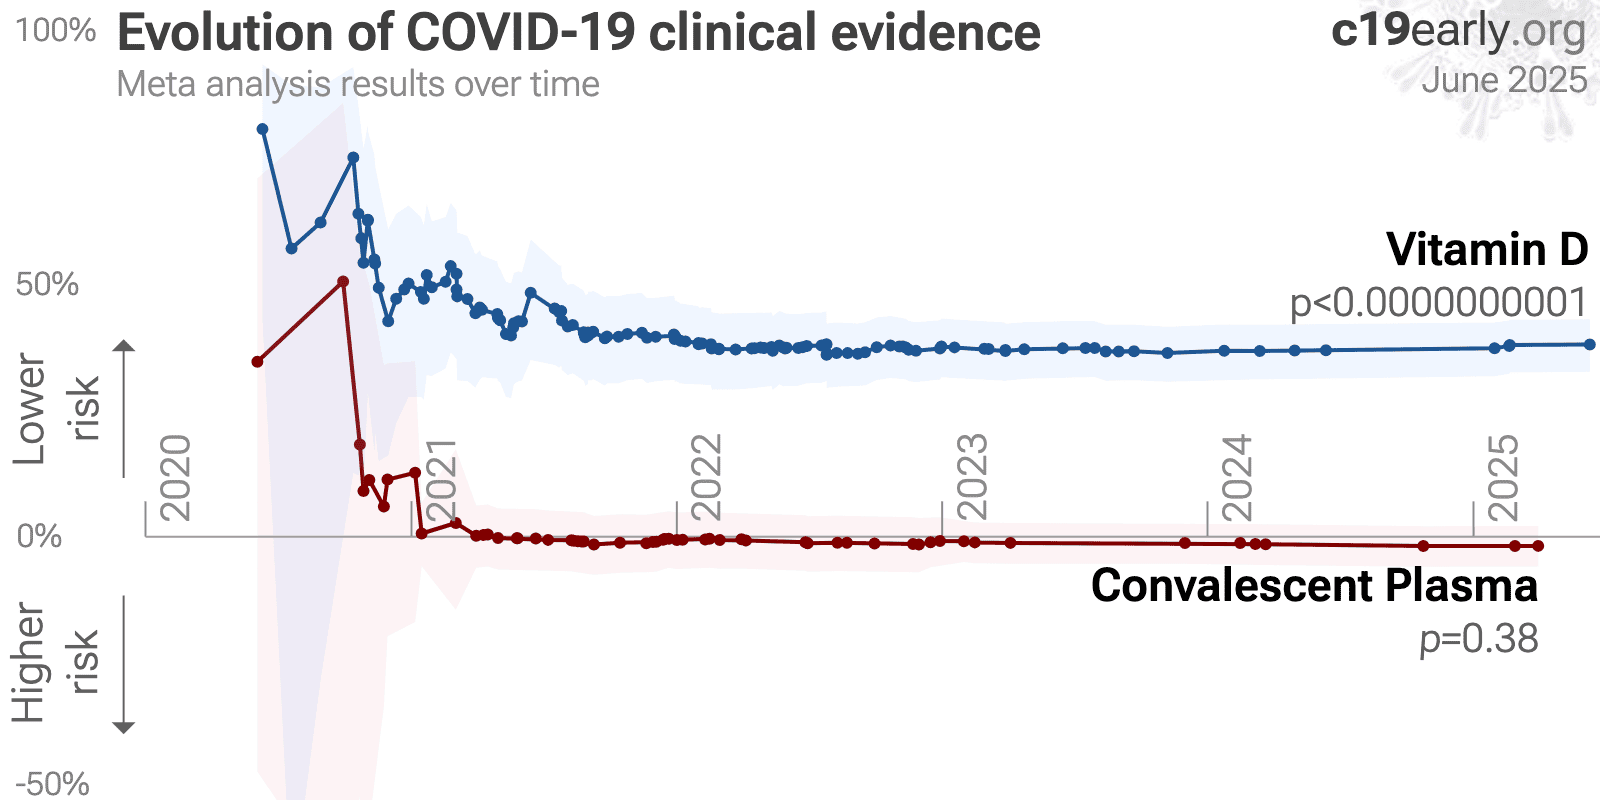
Evolution of COVID-19 clinical evidence Meta-analysis results over time Convalescent Plasma p=0.26 Vitamin D p<0.0000000001 2020 2021 2022 2023 2024 2025 2026 Lowerrisk Higherrisk c19early.org October 2026 50% 0% -50%
Convalescent Plasma for COVID-19 — Highlights
Meta-analysis of studies to date shows no significant improvements with convalescent plasma.
Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
October 2026

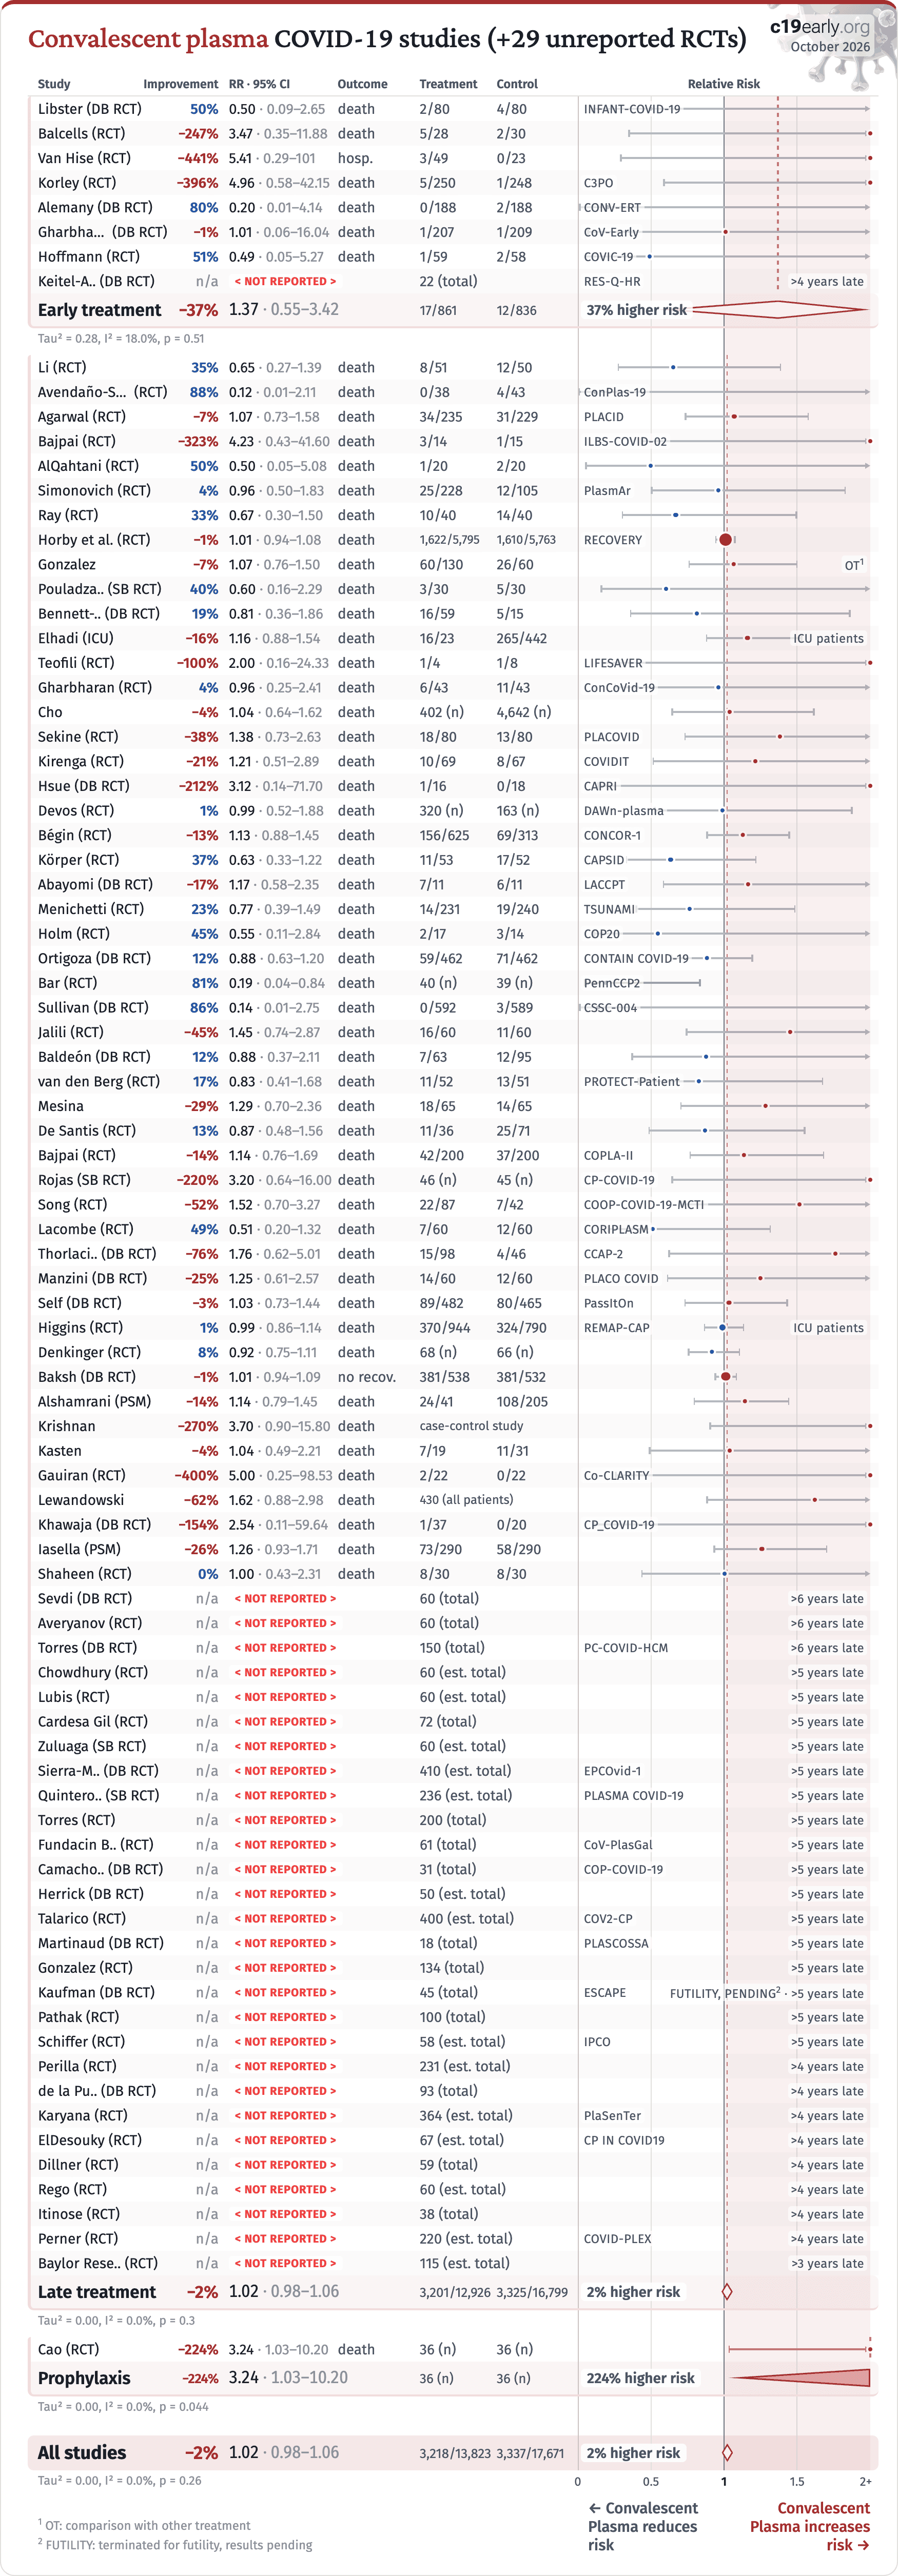
Convalescent plasma COVID-19 studies (+29 unreported RCTs)

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment−37%1.37 · 0.55–3.4217/86112/83637% higher risk
Tau² = 0.28, I² = 18.0%, p = 0.51
Li (RCT)35%0.65 · 0.27–1.39death8/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.11death0/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.58death34/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.60death3/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.08death1/202/20 Simonovich (RCT)4%0.96 · 0.50–1.83death25/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.50death10/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.08death1,622/5,7951,610/5,763RECOVERY Gonzalez−7%1.07 · 0.76–1.50death60/13026/60OT1 Pouladza.. (SB RCT)40%0.60 · 0.16–2.29death3/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.86death16/595/15 Elhadi (ICU)−16%1.16 · 0.88–1.54death16/23265/442ICU patients Teofili (RCT)−100%2.00 · 0.16–24.33death1/41/8LIFESAVER Gharbharan (RCT)4%0.96 · 0.25–2.41death6/4311/43ConCoVid-19 Cho−4%1.04 · 0.64–1.62death402 (n)4,642 (n) Sekine (RCT)−38%1.38 · 0.73–2.63death18/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.89death10/698/67COVIDIT Hsue (DB RCT)−212%3.12 · 0.14–71.70death1/160/18CAPRI Devos (RCT)1%0.99 · 0.52–1.88death320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45death156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.22death11/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.35death7/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.49death14/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.84death2/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.20death59/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.84death40 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.75death0/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.87death16/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.11death7/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.68death11/5213/51PROTECT-Patient Mesina−29%1.29 · 0.70–2.36death18/6514/65 De Santis (RCT)13%0.87 · 0.48–1.56death11/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.69death42/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.00death46 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.27death22/877/42COOP-COVID-19-MCTI Lacombe (RCT)49%0.51 · 0.20–1.32death7/6012/60CORIPLASM Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.01death15/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.57death14/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.44death89/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14death370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.11death68 (n)66 (n) Baksh (DB RCT)−1%1.01 · 0.94–1.09no recov.381/538381/532 Alshamrani (PSM)−14%1.14 · 0.79–1.45death24/41108/205 Krishnan−270%3.70 · 0.90–15.80deathcase-control study Kasten−4%1.04 · 0.49–2.21death7/1911/31 Gauiran (RCT)−400%5.00 · 0.25–98.53death2/220/22Co-CLARITY Lewandowski−62%1.62 · 0.88–2.98death430 (all patients) Khawaja (DB RCT)−154%2.54 · 0.11–59.64death1/370/20CP_COVID-19 Iasella (PSM)−26%1.26 · 0.93–1.71death73/29058/290 Shaheen (RCT)0%1.00 · 0.43–2.31death8/308/30 Sevdi (DB RCT)n/a< NOT REPORTED >60 (total)>6 years late Averyanov (RCT)n/a< NOT REPORTED >60 (total)>6 years late Torres (DB RCT)n/a< NOT REPORTED >150 (total)PC-COVID-HCM>6 years late Chowdhury (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Lubis (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Cardesa Gil (RCT)n/a< NOT REPORTED >72 (total)>5 years late Zuluaga (SB RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Sierra-M.. (DB RCT)n/a< NOT REPORTED >410 (est. total)EPCOvid-1>5 years late Quintero.. (SB RCT)n/a< NOT REPORTED >236 (est. total)PLASMA COVID-19>5 years late Torres (RCT)n/a< NOT REPORTED >200 (total)>5 years late Fundacin B.. (RCT)n/a< NOT REPORTED >61 (total)CoV-PlasGal>5 years late Camacho.. (DB RCT)n/a< NOT REPORTED >31 (total)COP-COVID-19>5 years late Herrick (DB RCT)n/a< NOT REPORTED >50 (est. total)>5 years late Talarico (RCT)n/a< NOT REPORTED >400 (est. total)COV2-CP>5 years late Martinaud (DB RCT)n/a< NOT REPORTED >18 (total)PLASCOSSA>5 years late Gonzalez (RCT)n/a< NOT REPORTED >134 (total)>5 years late Kaufman (DB RCT)n/a< NOT REPORTED >45 (total)ESCAPEFUTILITY, PENDING2 · >5 years late Pathak (RCT)n/a< NOT REPORTED >100 (total)>5 years late Schiffer (RCT)n/a< NOT REPORTED >58 (est. total)IPCO>5 years late Perilla (RCT)n/a< NOT REPORTED >231 (est. total)>4 years late de la Pu.. (DB RCT)n/a< NOT REPORTED >93 (total)>4 years late Karyana (RCT)n/a< NOT REPORTED >364 (est. total)PlaSenTer>4 years late ElDesouky (RCT)n/a< NOT REPORTED >67 (est. total)CP IN COVID19>4 years late Dillner (RCT)n/a< NOT REPORTED >59 (total)>4 years late Rego (RCT)n/a< NOT REPORTED >60 (est. total)>4 years late Itinose (RCT)n/a< NOT REPORTED >38 (total)>4 years late Perner (RCT)n/a< NOT REPORTED >220 (est. total)COVID-PLEX>4 years late Baylor Rese.. (RCT)n/a< NOT REPORTED >115 (est. total)>3 years late
Late treatment−2%1.02 · 0.98–1.063,201/12,9263,325/16,7992% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.3
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−2%1.02 · 0.98–1.063,218/13,8233,337/17,6712% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.2600.511.52+
1 OT: comparison with other treatment
2 FUTILITY: terminated for futility, results pending
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
B
Loading..
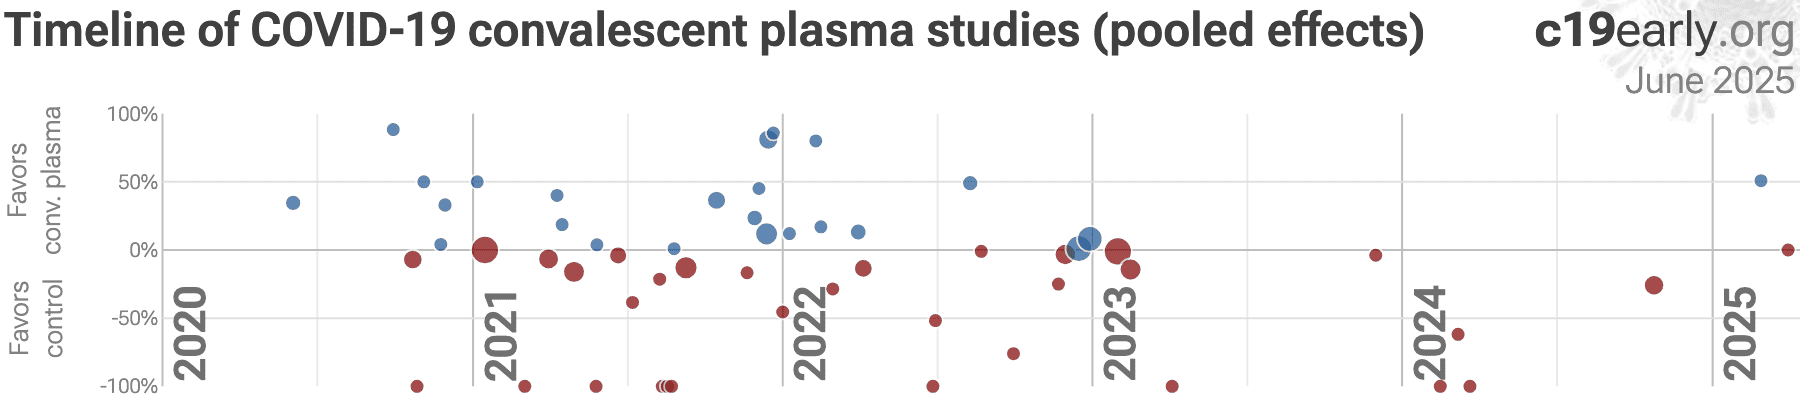
Fig. 1. A. Random-effects meta-analysis. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix. B. Timeline of results in convalescent plasma studies.
Fig. 2. SARS-CoV-2 spike protein fibrin binding leads to thromboinflammation and neuropathology, from1.
SARS-CoV-2 infection primarily begins in the upper respiratory tract and may progress to the lower respiratory tract, other tissues, and the nervous and cardiovascular systems, which may lead to cytokine storm, pneumonia, ARDS, neurological injury2-18 and cognitive deficits5,10, cardiovascular complications19-25, DNA damage26-29, organ failure, and death. Even mild untreated infections may result in persistent cognitive deficits30—the spike protein binds to fibrin leading to fibrinolysis-resistant blood clots, thromboinflammation, and neuropathology. Minimizing replication as early as possible is recommended.
SARS-CoV-2 infection and replication involves the complex interplay of 500+ host and viral proteins and other factorsA,31-38, providing many therapeutic targets for which many existing compounds have known activity. Scientists have predicted that over 12,000 compounds may reduce COVID-19 risk39, either by directly minimizing infection or replication, by supporting immune system function, or by minimizing secondary complications.
We analyze all significant controlled studies of convalescent plasma for COVID-19. Search methods, inclusion criteria, effect extraction criteria (more serious outcomes have priority), all individual study data, PRISMA answers, and statistical methods are detailed in Appendix 1. We present random-effects meta-analysis results for all studies, studies within each treatment stage, individual outcomes, peer-reviewed studies, and Randomized Controlled Trials (RCTs).
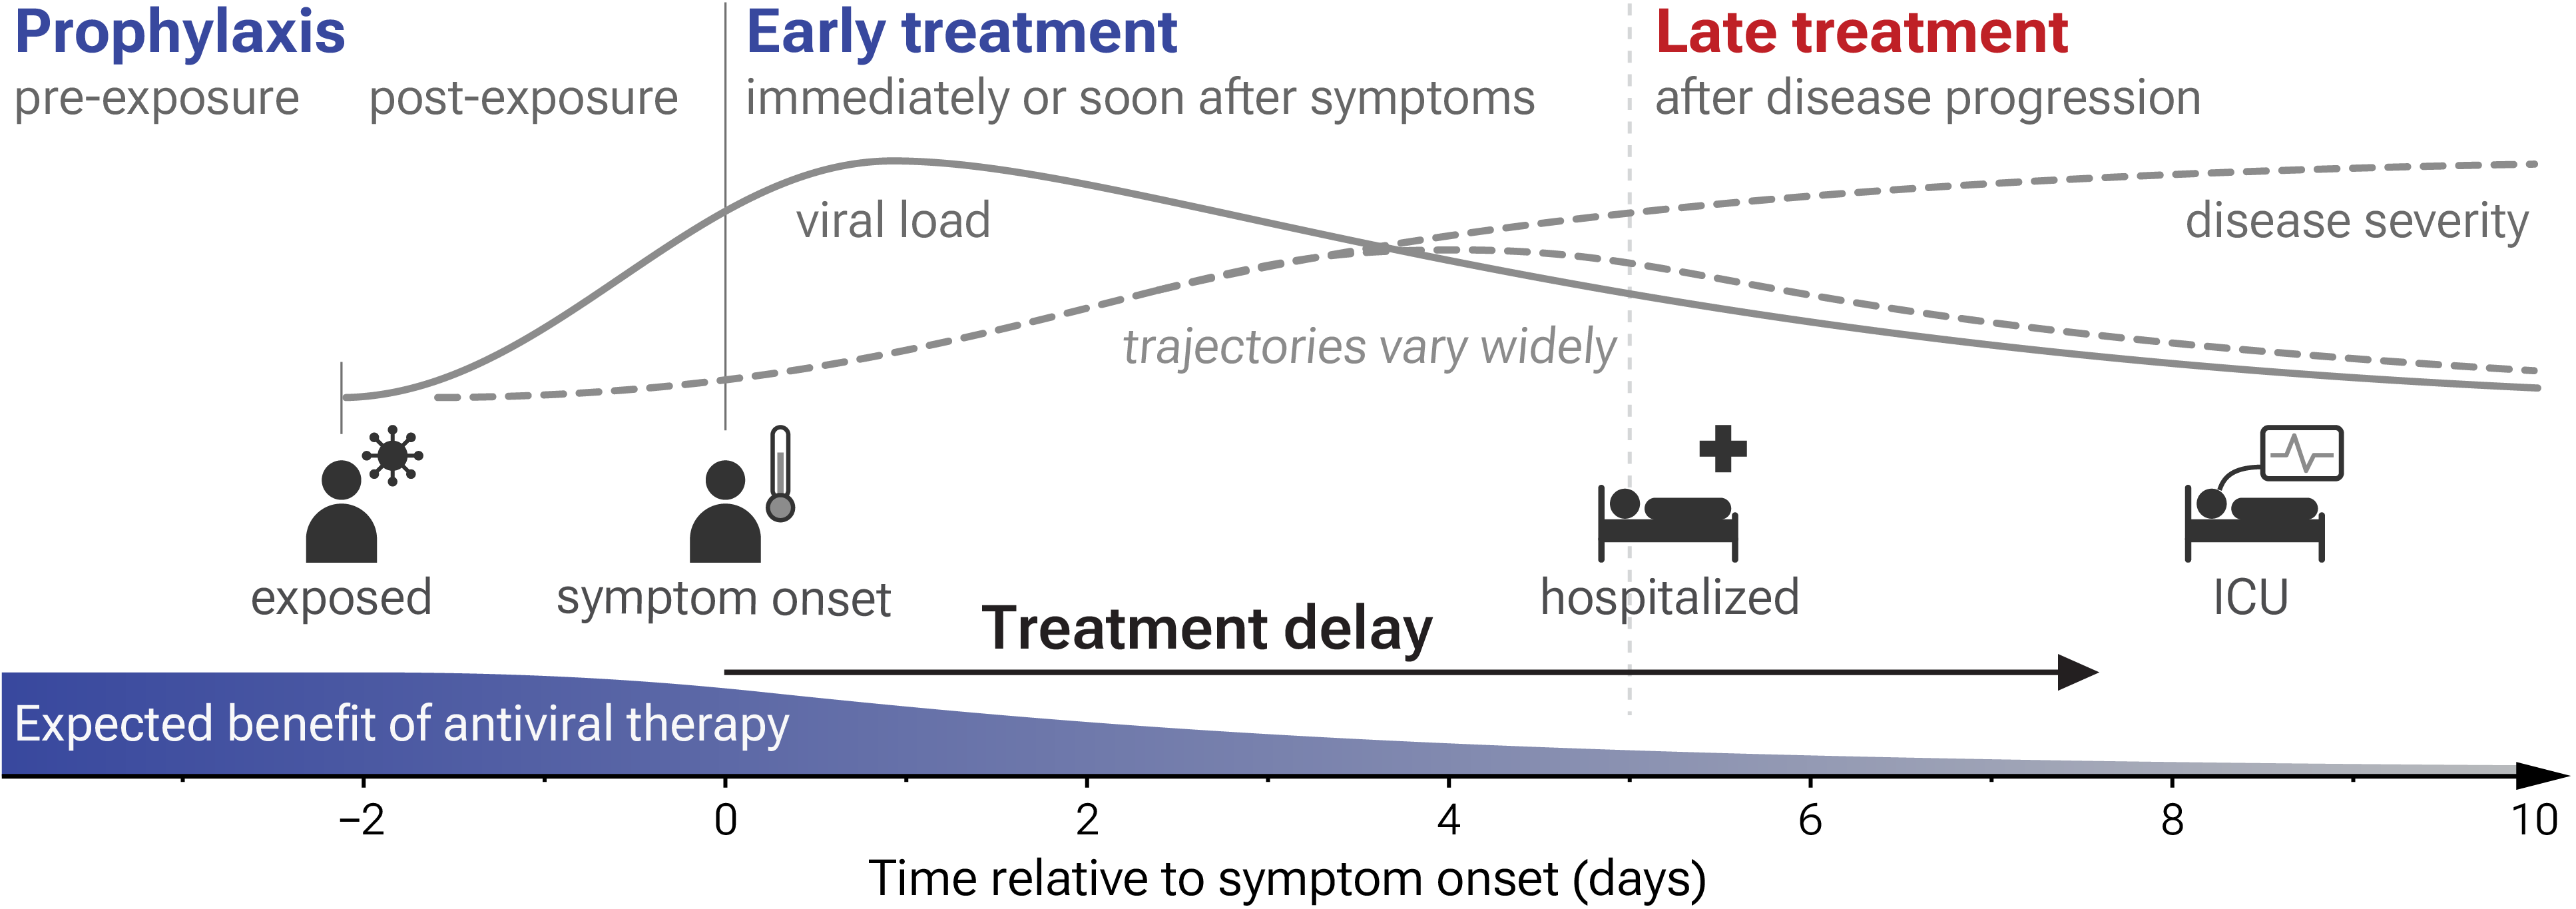
Fig. 3 shows stages of possible treatment for COVID-19. Prophylaxis refers to regularly taking medication before becoming sick, in order to prevent or minimize infection. Early treatment refers to treatment immediately or soon after symptoms appear, while late treatment refers to more delayed treatment.
Prophylaxis pre-exposure post-exposure Early treatment Late treatment Treatment delay viral load disease severity exposed symptom onset hospitalized ICU Expected benefit of antiviral therapy −2 0 2 4 6 8 10 Time relative to symptom onset (days) trajectories vary widely immediately or soon after symptoms after disease progression
Fig. 3. Treatment stages.
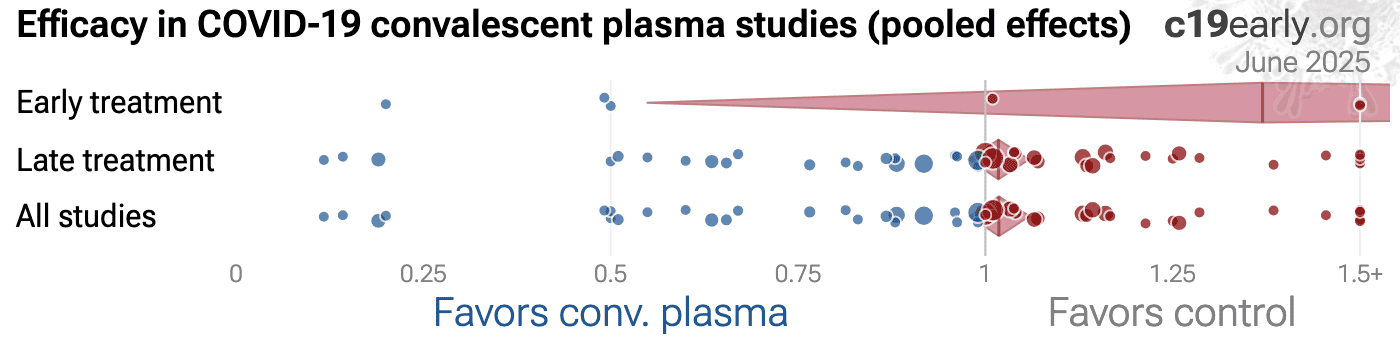
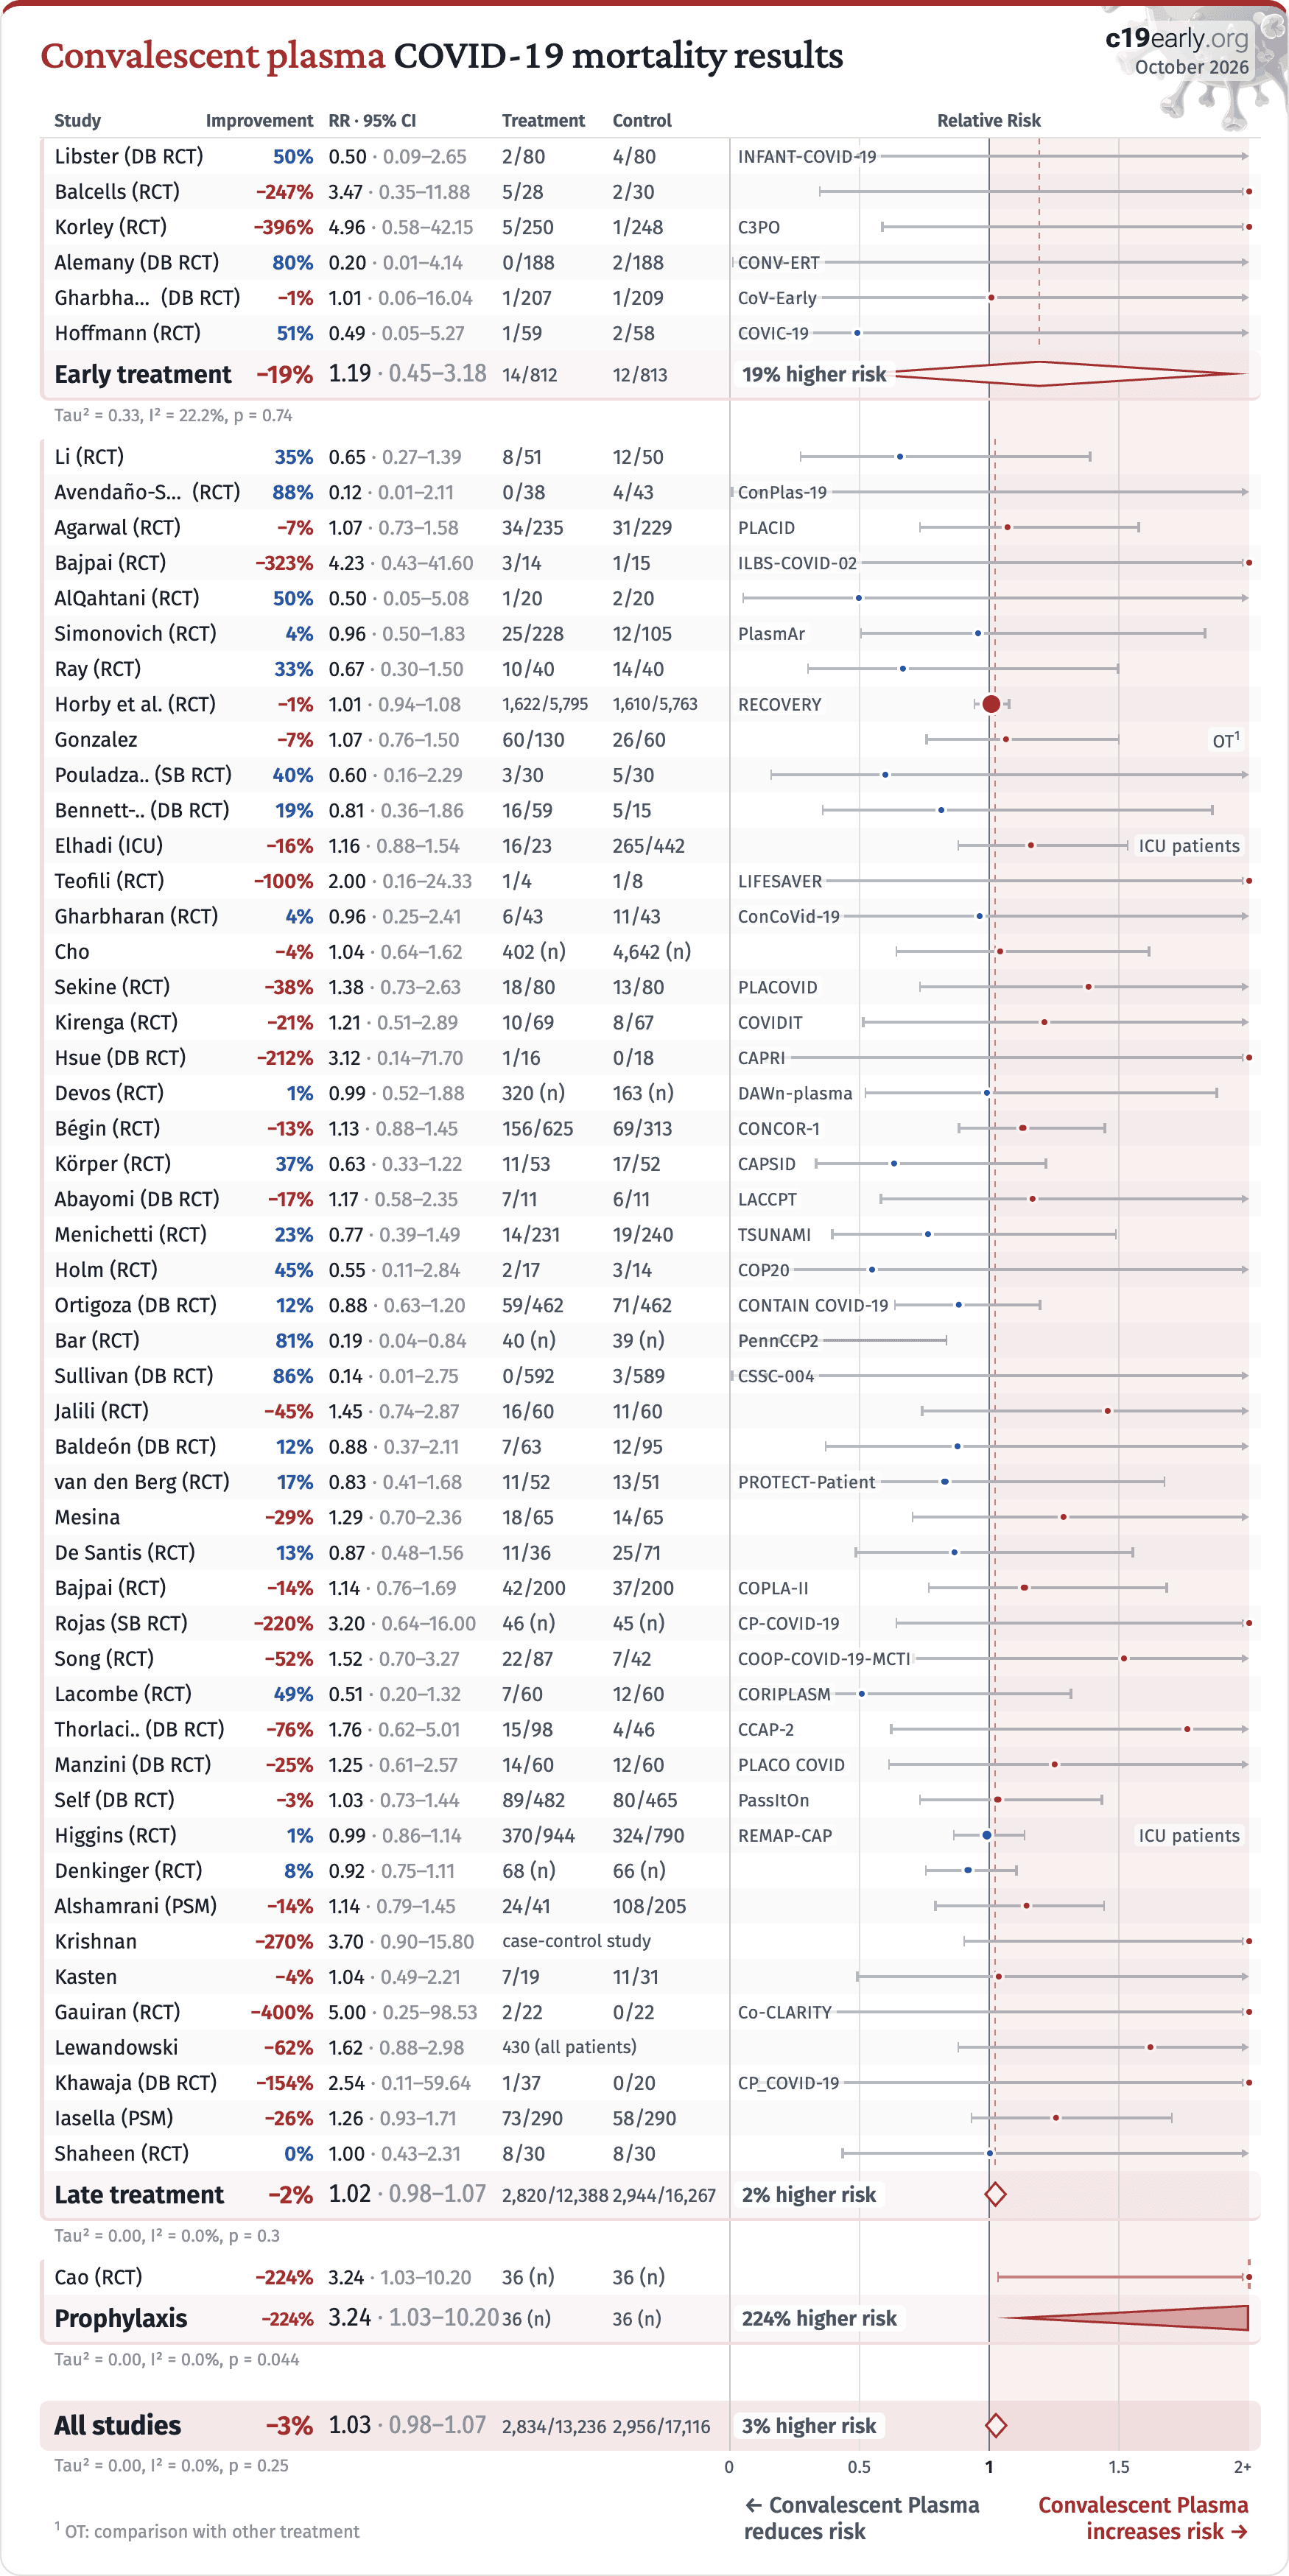
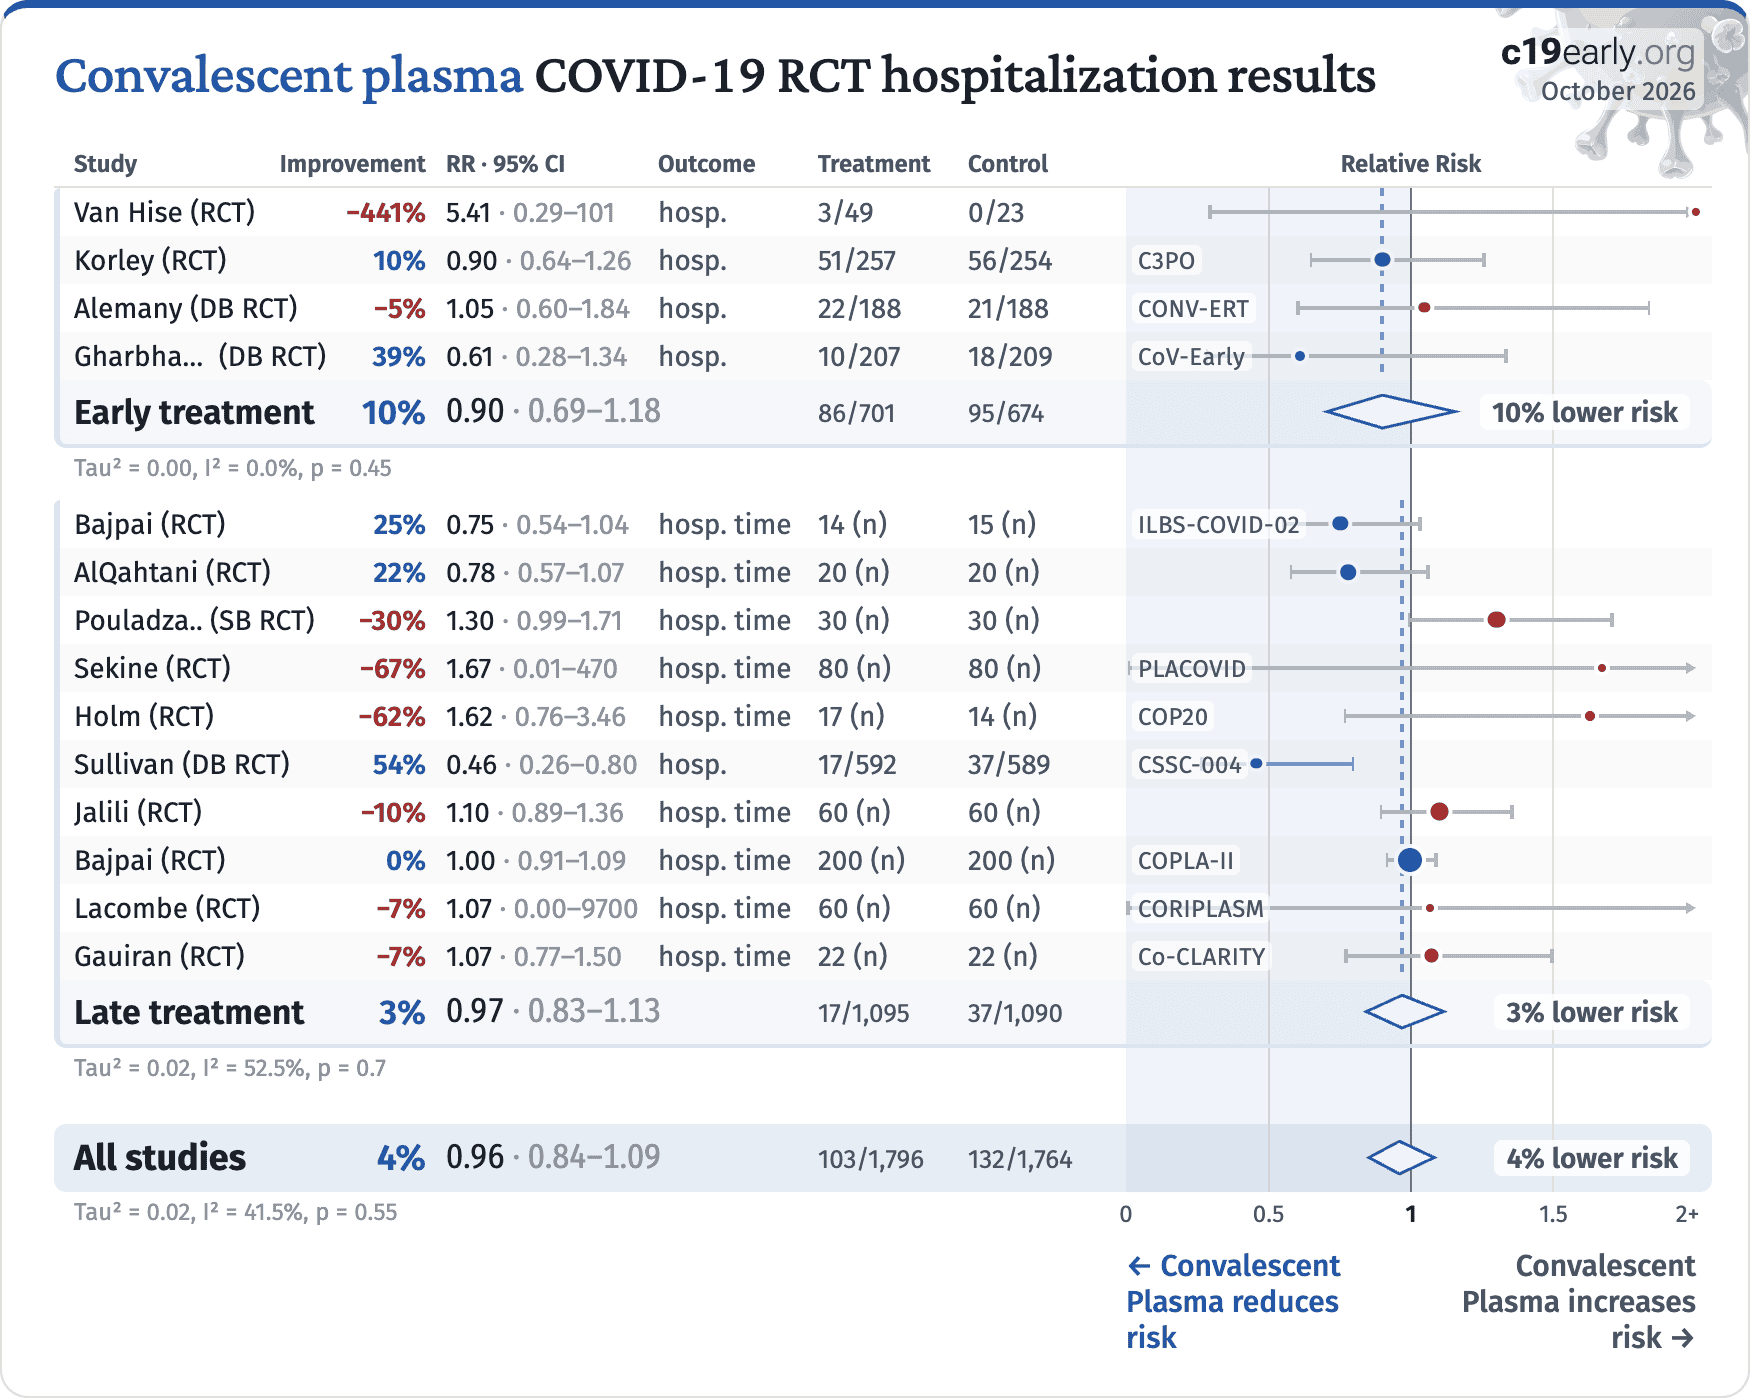
Table 1 summarizes the results for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, and for specific outcomes. Table 2 shows results by treatment stage. Fig. 4 plots individual results by treatment stage. Fig. 5, 6, 7, 8, 9, 10, 11, 12, 13, 14, and 15 show forest plots for random-effects meta-analysis of all studies with pooled effects, mortality results, ventilation, ICU admission, hospitalization, progression, recovery, cases, viral clearance, peer reviewed studies, and long COVID.
Table 1. Random-effects meta-analysis for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, and for specific outcomes. Results show the relative risk with treatment and the 95% confidence interval. * p<0.05.
Relative Risk Studies Patients
All studies1.02 [0.98‑1.06]5830K
Peer-reviewedPeer-reviewed1.02 [0.98‑1.06]5230K
RCTsRCTs1.01 [0.97‑1.05]4920K
Mortality1.03 [0.98‑1.07]5630K
VentilationVent.1.00 [0.89‑1.14]173,663
ICU admissionICU1.09 [0.95‑1.26]102,893
HospitalizationHosp.1.02 [0.89‑1.16]163,936
Recovery1.00 [0.96‑1.04]910K
Viral0.96 [0.85‑1.07]81,541
RCT mortality1.01 [0.96‑1.06]4720K
RCT hospitalizationRCT hosp.0.96 [0.84‑1.09]143,560
Table 2. Random-effects meta-analysis results by treatment stage. Results show the relative risk with treatment and the 95% confidence interval.treatment and the 95% confidence interval. * p<0.05.
Early treatment Late treatment Prophylaxis
All studies1.37 [0.55‑3.42]1.37
[0.55‑3.42]
1.02 [0.98‑1.06]1.02
[0.98‑1.06]
3.24 [1.03‑10.20]*3.24*
[1.03‑10.20]
Peer-reviewedPeer-reviewed1.19 [0.45‑3.18]1.19
[0.45‑3.18]
1.02 [0.98‑1.06]1.02
[0.98‑1.06]
3.24 [1.03‑10.20]*3.24*
[1.03‑10.20]
RCTsRCTs1.37 [0.55‑3.42]1.37
[0.55‑3.42]
1.01 [0.97‑1.05]1.01
[0.97‑1.05]
3.24 [1.03‑10.20]*3.24*
[1.03‑10.20]
Mortality1.19 [0.45‑3.18]1.19
[0.45‑3.18]
1.02 [0.98‑1.07]1.02
[0.98‑1.07]
3.24 [1.03‑10.20]*3.24*
[1.03‑10.20]
VentilationVent.1.00 [0.28‑3.54]1.00
[0.28‑3.54]
1.00 [0.88‑1.14]1.00
[0.88‑1.14]
ICU admissionICU0.33 [0.08‑1.35]0.33
[0.08‑1.35]
1.10 [0.97‑1.25]1.10
[0.97‑1.25]
HospitalizationHosp.0.90 [0.69‑1.18]0.90
[0.69‑1.18]
1.04 [0.89‑1.20]1.04
[0.89‑1.20]
Recovery1.02 [0.91‑1.15]1.02
[0.91‑1.15]
1.00 [0.96‑1.04]1.00
[0.96‑1.04]
Viral1.04 [0.97‑1.11]1.04
[0.97‑1.11]
0.87 [0.67‑1.12]0.87
[0.67‑1.12]
RCT mortality1.19 [0.45‑3.18]1.19
[0.45‑3.18]
1.01 [0.96‑1.05]1.01
[0.96‑1.05]
3.24 [1.03‑10.20]*3.24*
[1.03‑10.20]
RCT hospitalizationRCT hosp.0.90 [0.69‑1.18]0.90
[0.69‑1.18]
0.97 [0.83‑1.13]0.97
[0.83‑1.13]
Loading..
Fig. 4. Scatter plot showing the most serious outcome in all studies, and for studies within each stage. Diamonds shows the results of random-effects meta-analysis.
October 2026

Convalescent plasma COVID-19 studies (+29 unreported RCTs)

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment−37%1.37 · 0.55–3.4217/86112/83637% higher risk
Tau² = 0.28, I² = 18.0%, p = 0.51
Li (RCT)35%0.65 · 0.27–1.39death8/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.11death0/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.58death34/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.60death3/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.08death1/202/20 Simonovich (RCT)4%0.96 · 0.50–1.83death25/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.50death10/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.08death1,622/5,7951,610/5,763RECOVERY Gonzalez−7%1.07 · 0.76–1.50death60/13026/60OT1 Pouladza.. (SB RCT)40%0.60 · 0.16–2.29death3/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.86death16/595/15 Elhadi (ICU)−16%1.16 · 0.88–1.54death16/23265/442ICU patients Teofili (RCT)−100%2.00 · 0.16–24.33death1/41/8LIFESAVER Gharbharan (RCT)4%0.96 · 0.25–2.41death6/4311/43ConCoVid-19 Cho−4%1.04 · 0.64–1.62death402 (n)4,642 (n) Sekine (RCT)−38%1.38 · 0.73–2.63death18/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.89death10/698/67COVIDIT Hsue (DB RCT)−212%3.12 · 0.14–71.70death1/160/18CAPRI Devos (RCT)1%0.99 · 0.52–1.88death320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45death156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.22death11/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.35death7/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.49death14/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.84death2/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.20death59/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.84death40 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.75death0/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.87death16/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.11death7/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.68death11/5213/51PROTECT-Patient Mesina−29%1.29 · 0.70–2.36death18/6514/65 De Santis (RCT)13%0.87 · 0.48–1.56death11/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.69death42/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.00death46 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.27death22/877/42COOP-COVID-19-MCTI Lacombe (RCT)49%0.51 · 0.20–1.32death7/6012/60CORIPLASM Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.01death15/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.57death14/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.44death89/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14death370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.11death68 (n)66 (n) Baksh (DB RCT)−1%1.01 · 0.94–1.09no recov.381/538381/532 Alshamrani (PSM)−14%1.14 · 0.79–1.45death24/41108/205 Krishnan−270%3.70 · 0.90–15.80deathcase-control study Kasten−4%1.04 · 0.49–2.21death7/1911/31 Gauiran (RCT)−400%5.00 · 0.25–98.53death2/220/22Co-CLARITY Lewandowski−62%1.62 · 0.88–2.98death430 (all patients) Khawaja (DB RCT)−154%2.54 · 0.11–59.64death1/370/20CP_COVID-19 Iasella (PSM)−26%1.26 · 0.93–1.71death73/29058/290 Shaheen (RCT)0%1.00 · 0.43–2.31death8/308/30 Sevdi (DB RCT)n/a< NOT REPORTED >60 (total)>6 years late Averyanov (RCT)n/a< NOT REPORTED >60 (total)>6 years late Torres (DB RCT)n/a< NOT REPORTED >150 (total)PC-COVID-HCM>6 years late Chowdhury (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Lubis (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Cardesa Gil (RCT)n/a< NOT REPORTED >72 (total)>5 years late Zuluaga (SB RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Sierra-M.. (DB RCT)n/a< NOT REPORTED >410 (est. total)EPCOvid-1>5 years late Quintero.. (SB RCT)n/a< NOT REPORTED >236 (est. total)PLASMA COVID-19>5 years late Torres (RCT)n/a< NOT REPORTED >200 (total)>5 years late Fundacin B.. (RCT)n/a< NOT REPORTED >61 (total)CoV-PlasGal>5 years late Camacho.. (DB RCT)n/a< NOT REPORTED >31 (total)COP-COVID-19>5 years late Herrick (DB RCT)n/a< NOT REPORTED >50 (est. total)>5 years late Talarico (RCT)n/a< NOT REPORTED >400 (est. total)COV2-CP>5 years late Martinaud (DB RCT)n/a< NOT REPORTED >18 (total)PLASCOSSA>5 years late Gonzalez (RCT)n/a< NOT REPORTED >134 (total)>5 years late Kaufman (DB RCT)n/a< NOT REPORTED >45 (total)ESCAPEFUTILITY, PENDING2 · >5 years late Pathak (RCT)n/a< NOT REPORTED >100 (total)>5 years late Schiffer (RCT)n/a< NOT REPORTED >58 (est. total)IPCO>5 years late Perilla (RCT)n/a< NOT REPORTED >231 (est. total)>4 years late de la Pu.. (DB RCT)n/a< NOT REPORTED >93 (total)>4 years late Karyana (RCT)n/a< NOT REPORTED >364 (est. total)PlaSenTer>4 years late ElDesouky (RCT)n/a< NOT REPORTED >67 (est. total)CP IN COVID19>4 years late Dillner (RCT)n/a< NOT REPORTED >59 (total)>4 years late Rego (RCT)n/a< NOT REPORTED >60 (est. total)>4 years late Itinose (RCT)n/a< NOT REPORTED >38 (total)>4 years late Perner (RCT)n/a< NOT REPORTED >220 (est. total)COVID-PLEX>4 years late Baylor Rese.. (RCT)n/a< NOT REPORTED >115 (est. total)>3 years late
Late treatment−2%1.02 · 0.98–1.063,201/12,9263,325/16,7992% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.3
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−2%1.02 · 0.98–1.063,218/13,8233,337/17,6712% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.2600.511.52+
1 OT: comparison with other treatment
2 FUTILITY: terminated for futility, results pending
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 5. Random-effects meta-analysis for all studies. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
October 2026

Convalescent plasma COVID-19 mortality results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Early treatment−19%1.19 · 0.45–3.1814/81212/81319% higher risk
Tau² = 0.33, I² = 22.2%, p = 0.74
Li (RCT)35%0.65 · 0.27–1.398/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.110/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.5834/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.603/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.081/202/20 Simonovich (RCT)4%0.96 · 0.50–1.8325/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.5010/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.081,622/5,7951,610/5,763RECOVERY Gonzalez−7%1.07 · 0.76–1.5060/13026/60OT1 Pouladza.. (SB RCT)40%0.60 · 0.16–2.293/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.8616/595/15 Elhadi (ICU)−16%1.16 · 0.88–1.5416/23265/442ICU patients Teofili (RCT)−100%2.00 · 0.16–24.331/41/8LIFESAVER Gharbharan (RCT)4%0.96 · 0.25–2.416/4311/43ConCoVid-19 Cho−4%1.04 · 0.64–1.62402 (n)4,642 (n) Sekine (RCT)−38%1.38 · 0.73–2.6318/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.8910/698/67COVIDIT Hsue (DB RCT)−212%3.12 · 0.14–71.701/160/18CAPRI Devos (RCT)1%0.99 · 0.52–1.88320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.2211/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.357/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.4914/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.842/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.2059/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.8440 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.750/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.8716/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.117/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.6811/5213/51PROTECT-Patient Mesina−29%1.29 · 0.70–2.3618/6514/65 De Santis (RCT)13%0.87 · 0.48–1.5611/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.6942/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.0046 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.2722/877/42COOP-COVID-19-MCTI Lacombe (RCT)49%0.51 · 0.20–1.327/6012/60CORIPLASM Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.0115/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.5714/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.4489/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.1168 (n)66 (n) Alshamrani (PSM)−14%1.14 · 0.79–1.4524/41108/205 Krishnan−270%3.70 · 0.90–15.80case-control study Kasten−4%1.04 · 0.49–2.217/1911/31 Gauiran (RCT)−400%5.00 · 0.25–98.532/220/22Co-CLARITY Lewandowski−62%1.62 · 0.88–2.98430 (all patients) Khawaja (DB RCT)−154%2.54 · 0.11–59.641/370/20CP_COVID-19 Iasella (PSM)−26%1.26 · 0.93–1.7173/29058/290 Shaheen (RCT)0%1.00 · 0.43–2.318/308/30
Late treatment−2%1.02 · 0.98–1.072,820/12,3882,944/16,2672% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.3
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−3%1.03 · 0.98–1.072,834/13,2362,956/17,1163% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.2500.511.52+
1 OT: comparison with other treatment
Rotate screen for more detailsIncrease width for more details
← Convalescent Plasma
reduces risk
Convalescent Plasma
increases risk →
Fig. 6. Random-effects meta-analysis for mortality results.
October 2026

Convalescent plasma COVID-19 mechanical ventilation results

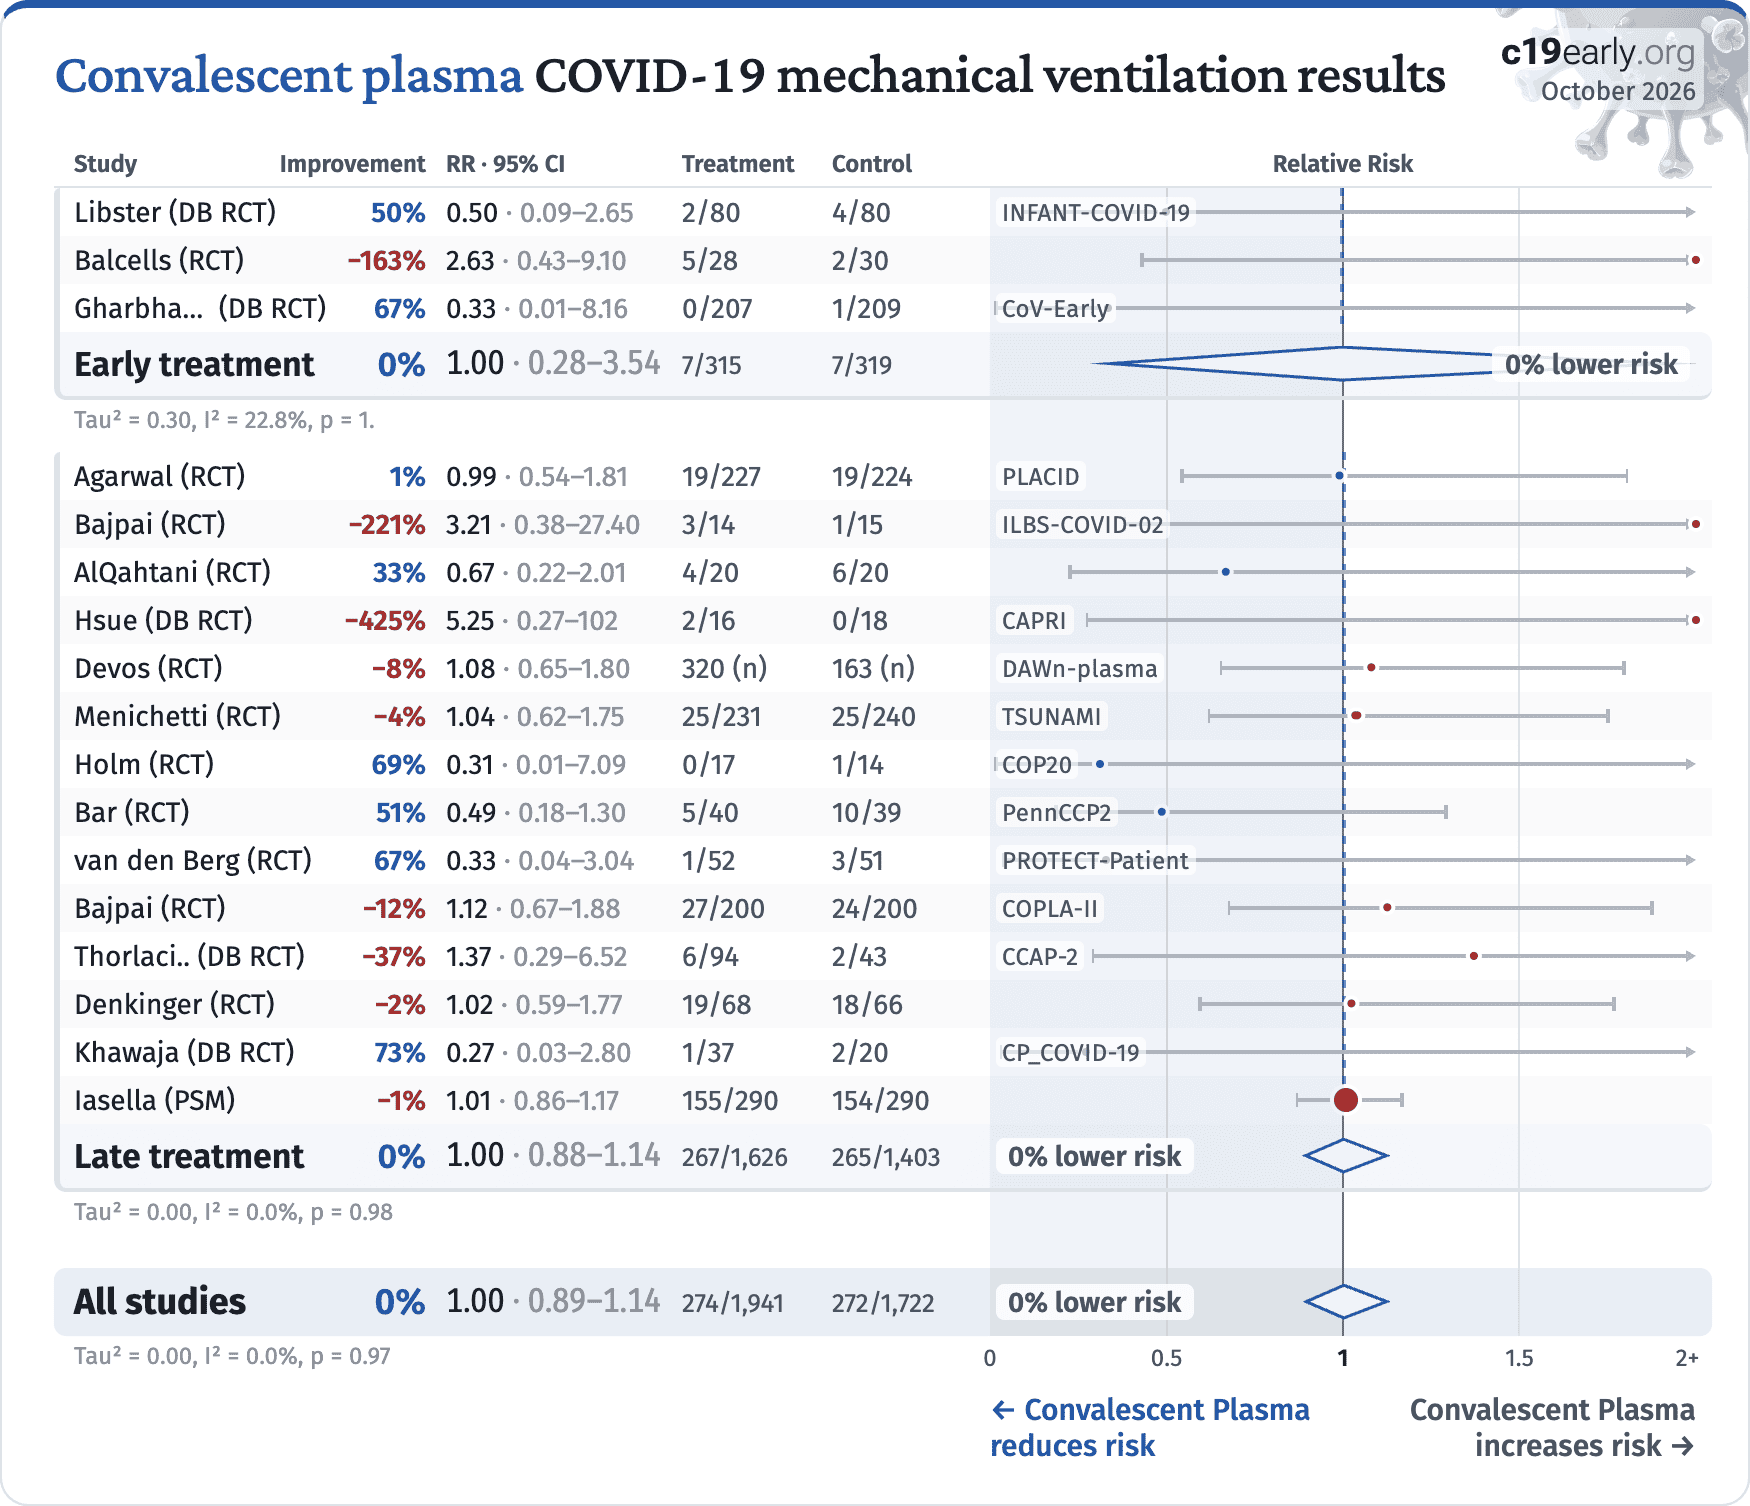
Fig. 7. Random-effects meta-analysis for ventilation.
October 2026

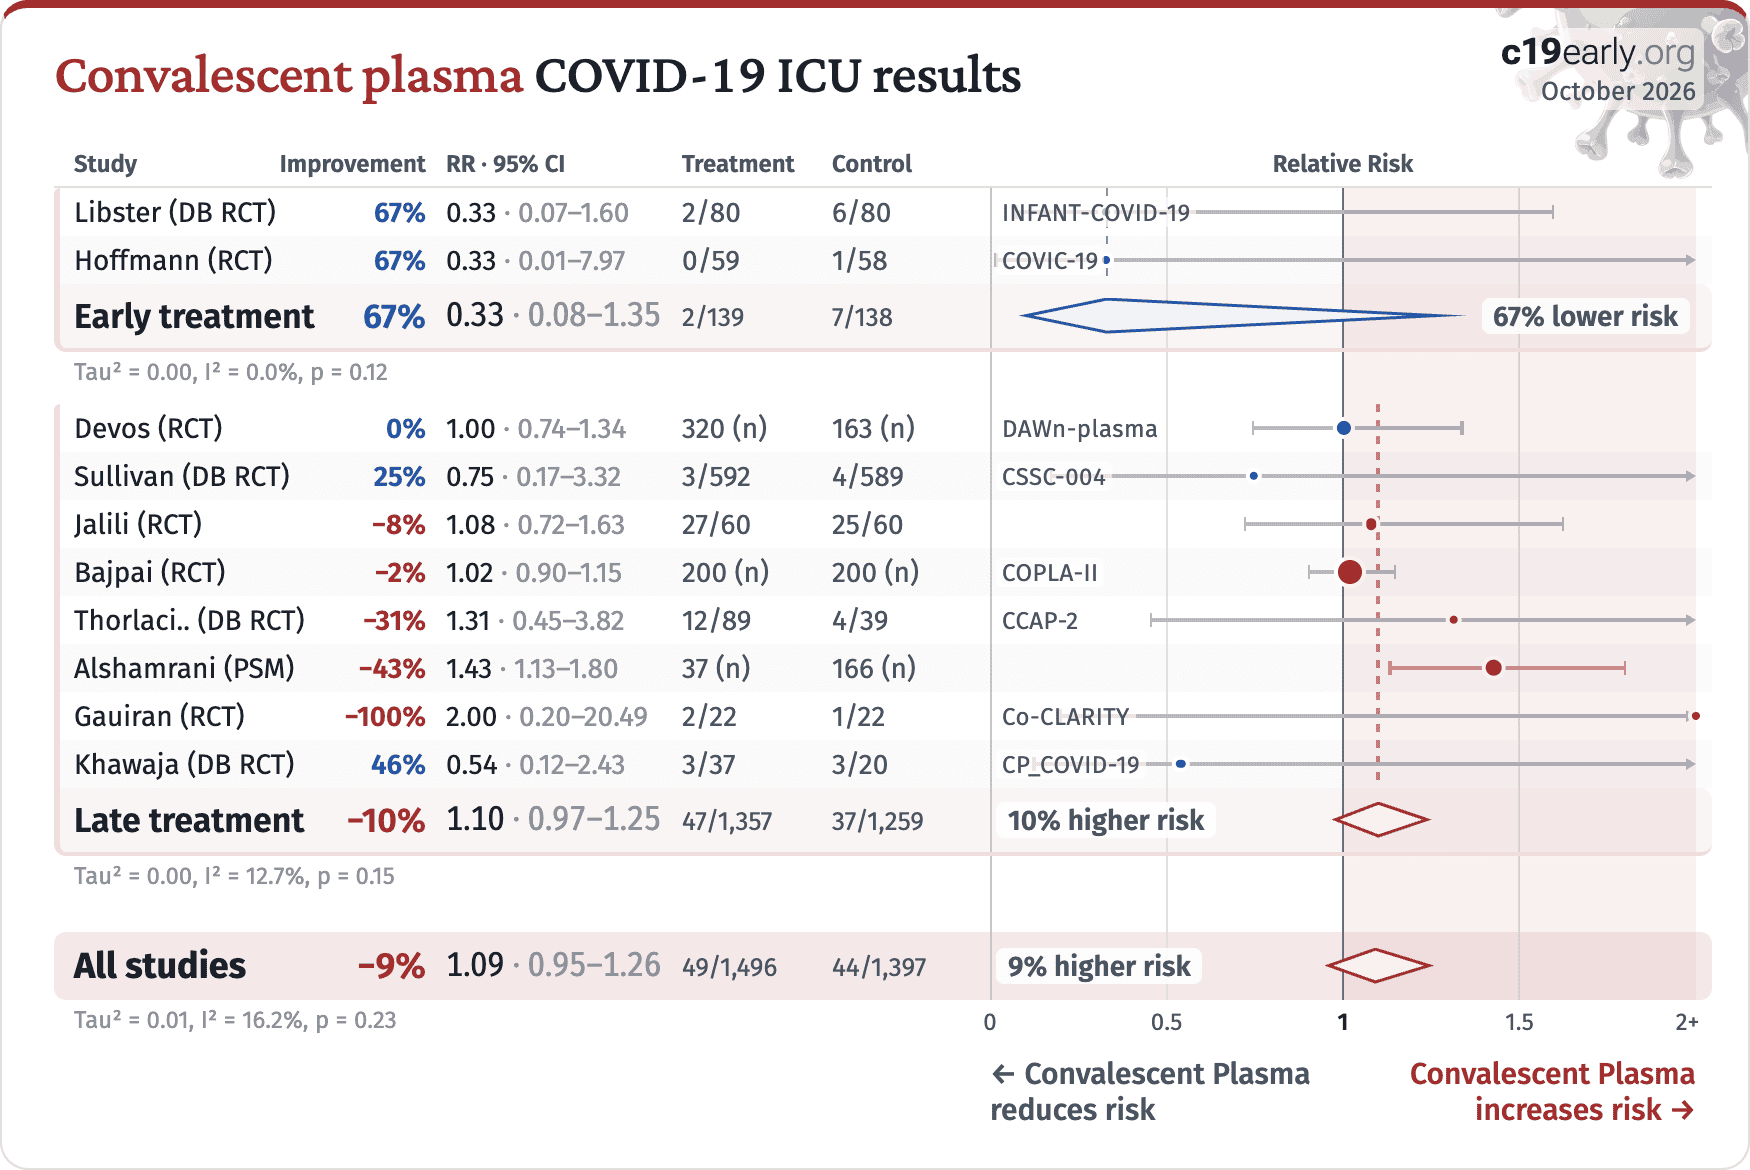
Convalescent plasma COVID-19 ICU results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Early treatment67%0.33 · 0.08–1.352/1397/13867% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.12
Late treatment−10%1.10 · 0.97–1.2547/1,35737/1,25910% higher risk
Tau² = 0.00, I² = 12.7%, p = 0.15
All studies−9%1.09 · 0.95–1.2649/1,49644/1,3979% higher risk
Tau² = 0.01, I² = 16.2%, p = 0.2300.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent Plasma
reduces risk
Convalescent Plasma
increases risk →
Fig. 8. Random-effects meta-analysis for ICU admission.
October 2026

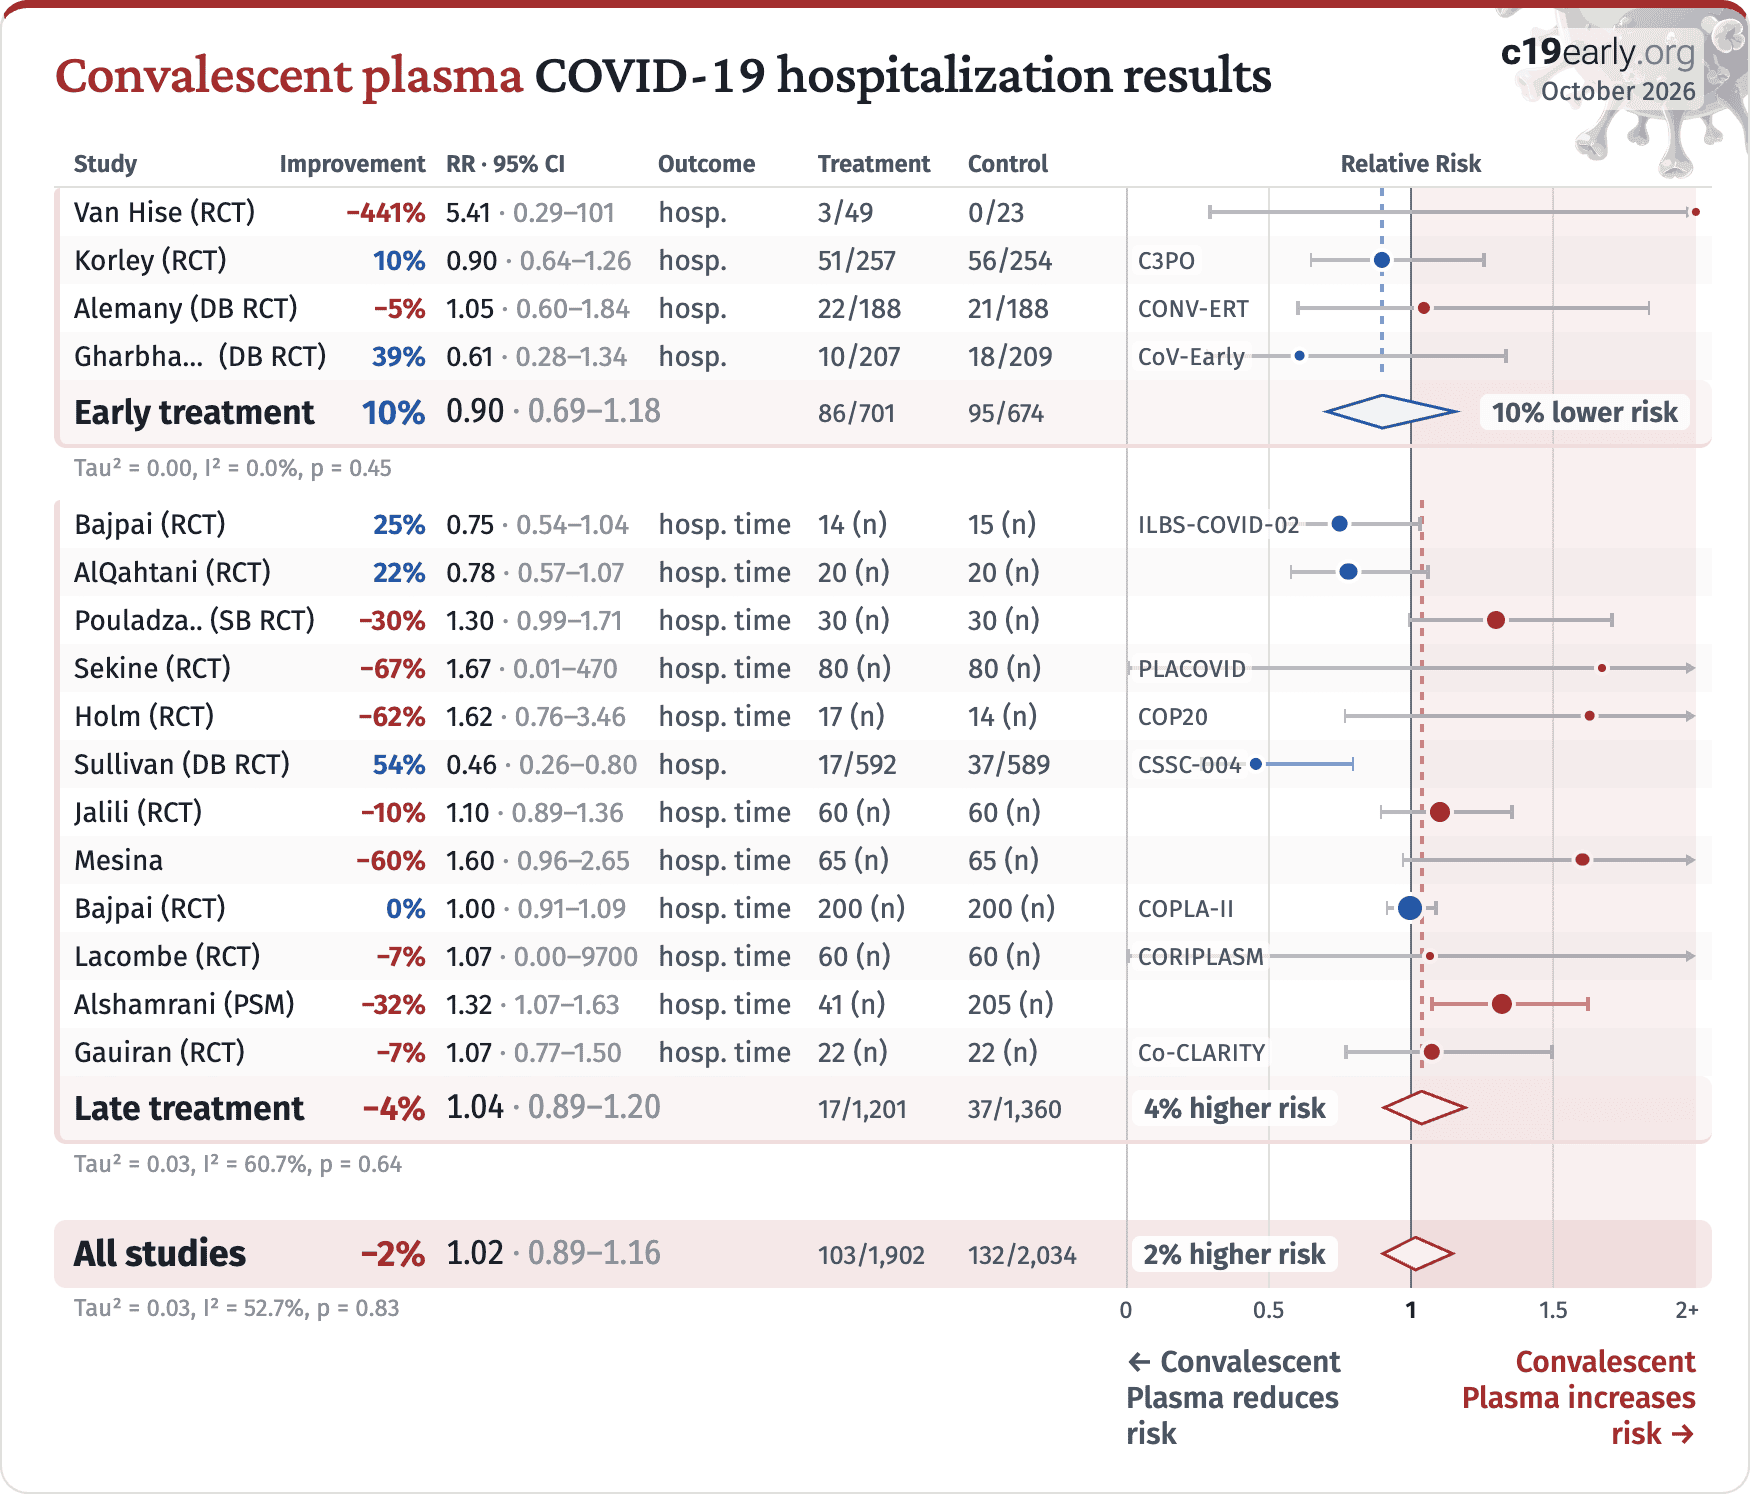
Convalescent plasma COVID-19 hospitalization results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment10%0.90 · 0.69–1.1886/70195/67410% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.45
Late treatment−4%1.04 · 0.89–1.2017/1,20137/1,3604% higher risk
Tau² = 0.03, I² = 60.7%, p = 0.64
All studies−2%1.02 · 0.89–1.16103/1,902132/2,0342% higher risk
Tau² = 0.03, I² = 52.7%, p = 0.8300.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 9. Random-effects meta-analysis for hospitalization.
October 2026

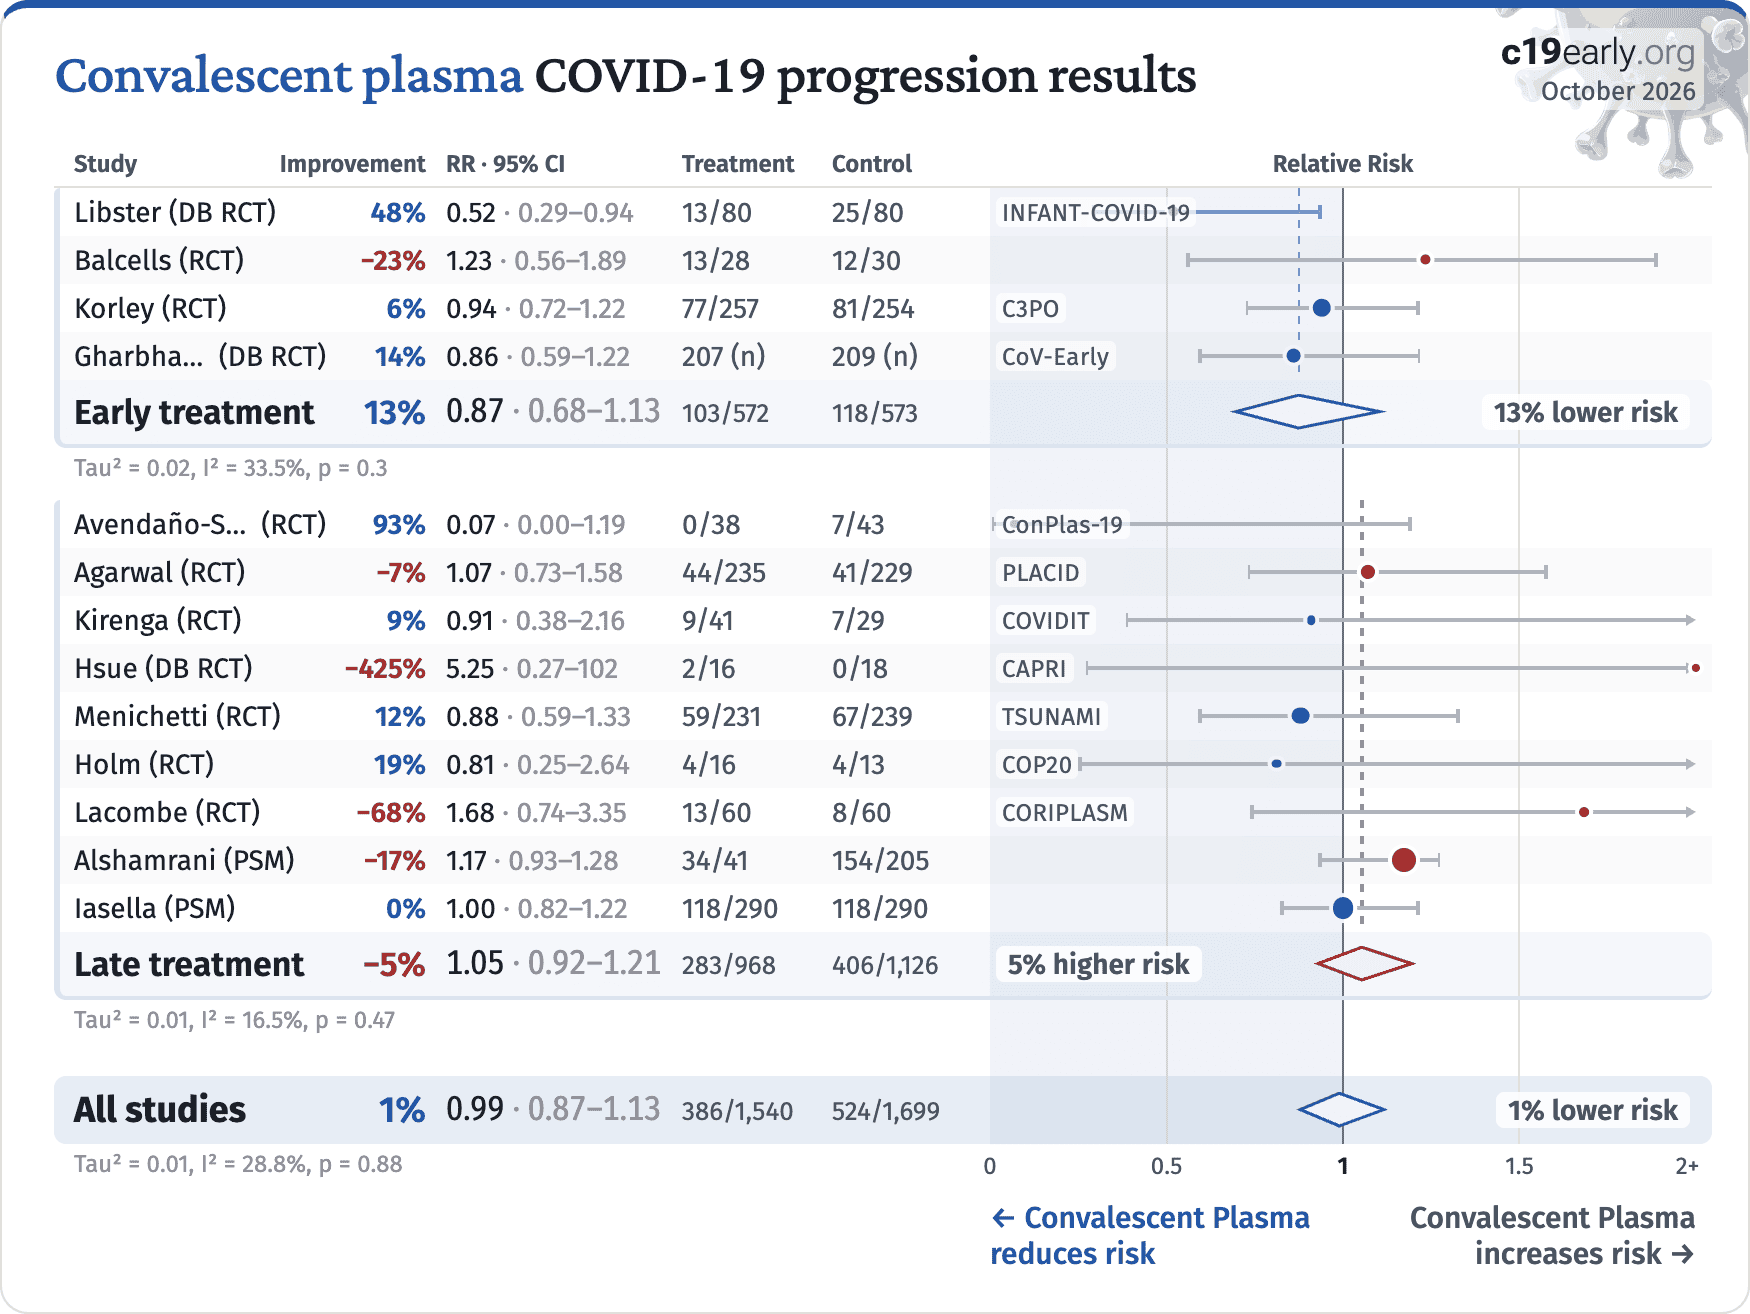
Convalescent plasma COVID-19 progression results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Early treatment13%0.87 · 0.68–1.13103/572118/57313% lower risk
Tau² = 0.02, I² = 33.5%, p = 0.3
Late treatment−5%1.05 · 0.92–1.21283/968406/1,1265% higher risk
Tau² = 0.01, I² = 16.5%, p = 0.47
All studies1%0.99 · 0.87–1.13386/1,540524/1,6991% lower risk
Tau² = 0.01, I² = 28.8%, p = 0.8800.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent Plasma
reduces risk
Convalescent Plasma
increases risk →
Fig. 10. Random-effects meta-analysis for progression.
October 2026

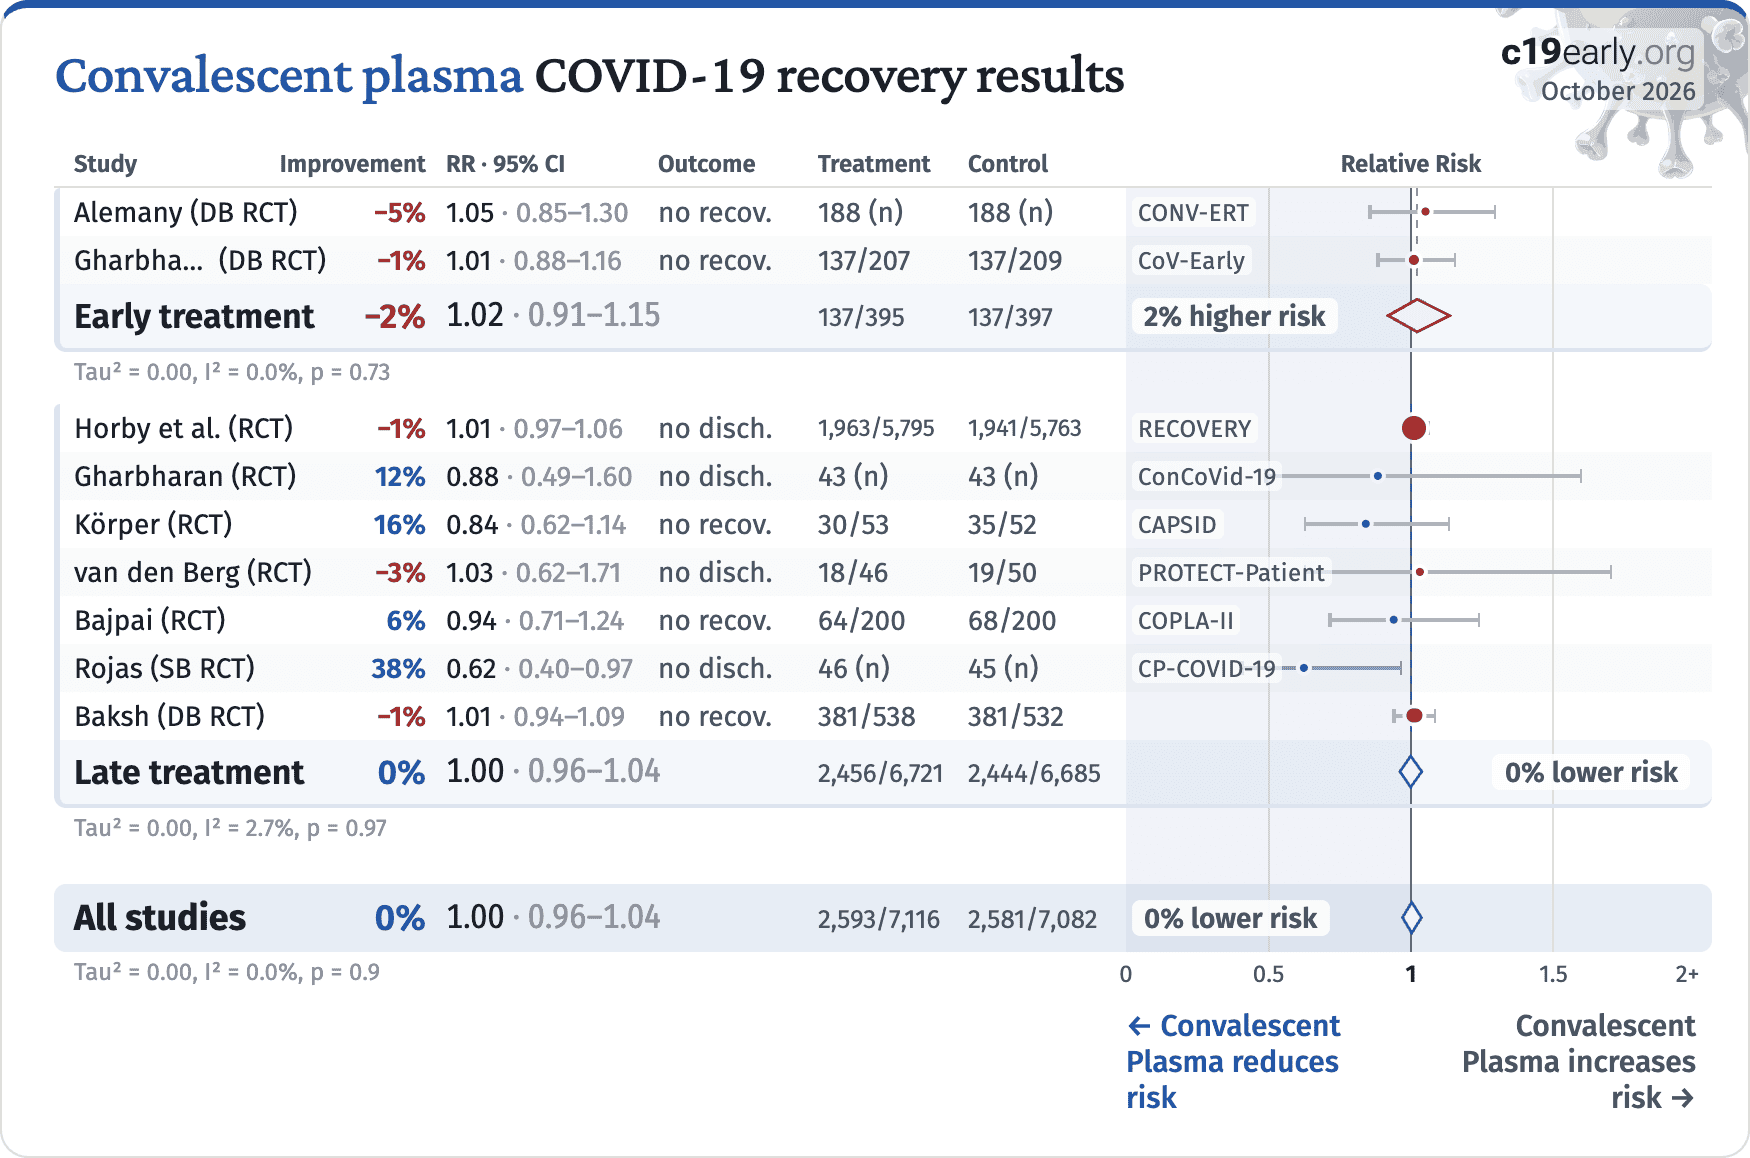
Convalescent plasma COVID-19 recovery results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment−2%1.02 · 0.91–1.15137/395137/3972% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.73
Late treatment0%1.00 · 0.96–1.042,456/6,7212,444/6,6850% lower risk
Tau² = 0.00, I² = 2.7%, p = 0.97
All studies0%1.00 · 0.96–1.042,593/7,1162,581/7,0820% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.900.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 11. Random-effects meta-analysis for recovery.
October 2026

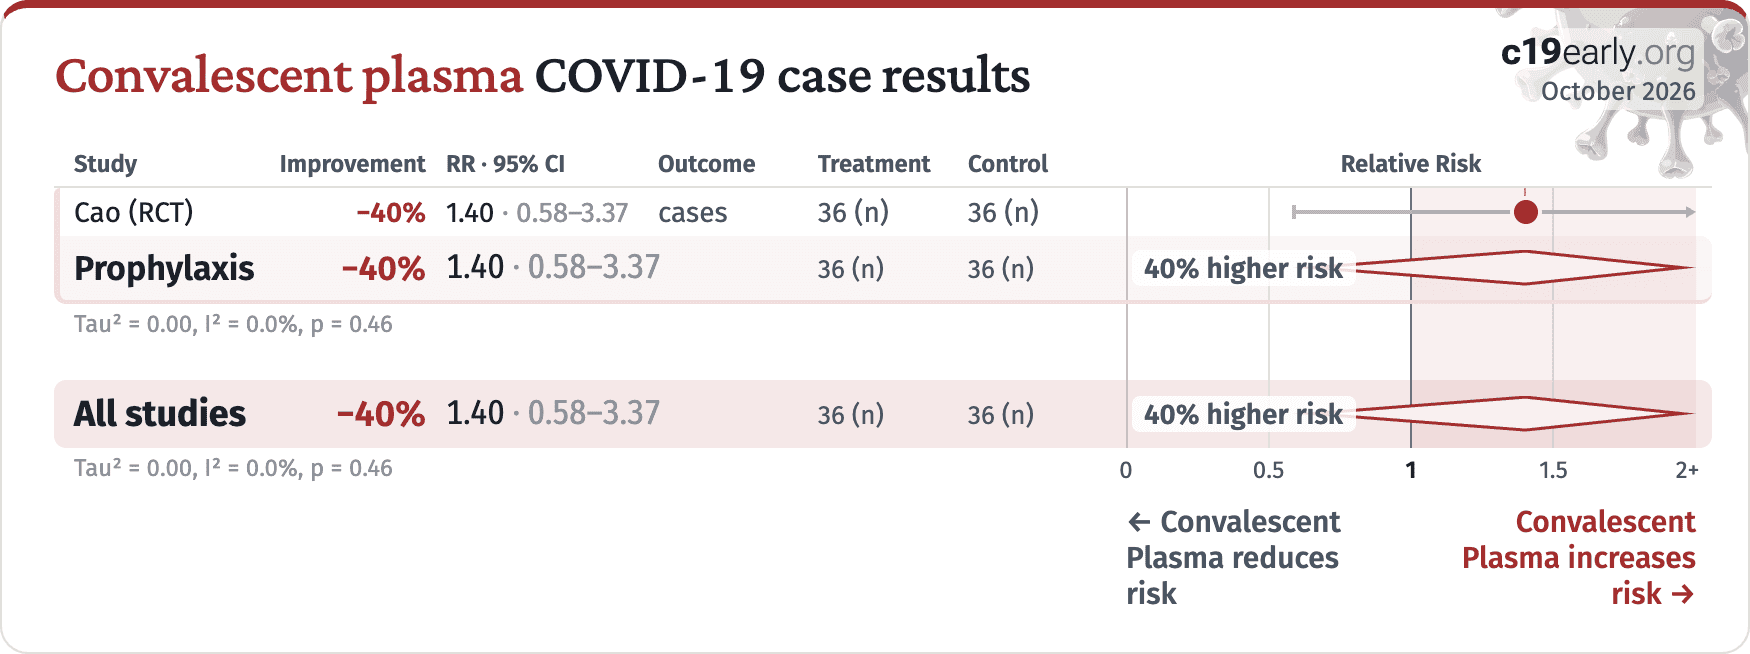
Convalescent plasma COVID-19 case results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Prophylaxis−40%1.40 · 0.58–3.3736 (n)36 (n)40% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.46
All studies−40%1.40 · 0.58–3.3736 (n)36 (n)40% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.4600.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 12. Random-effects meta-analysis for cases.
October 2026

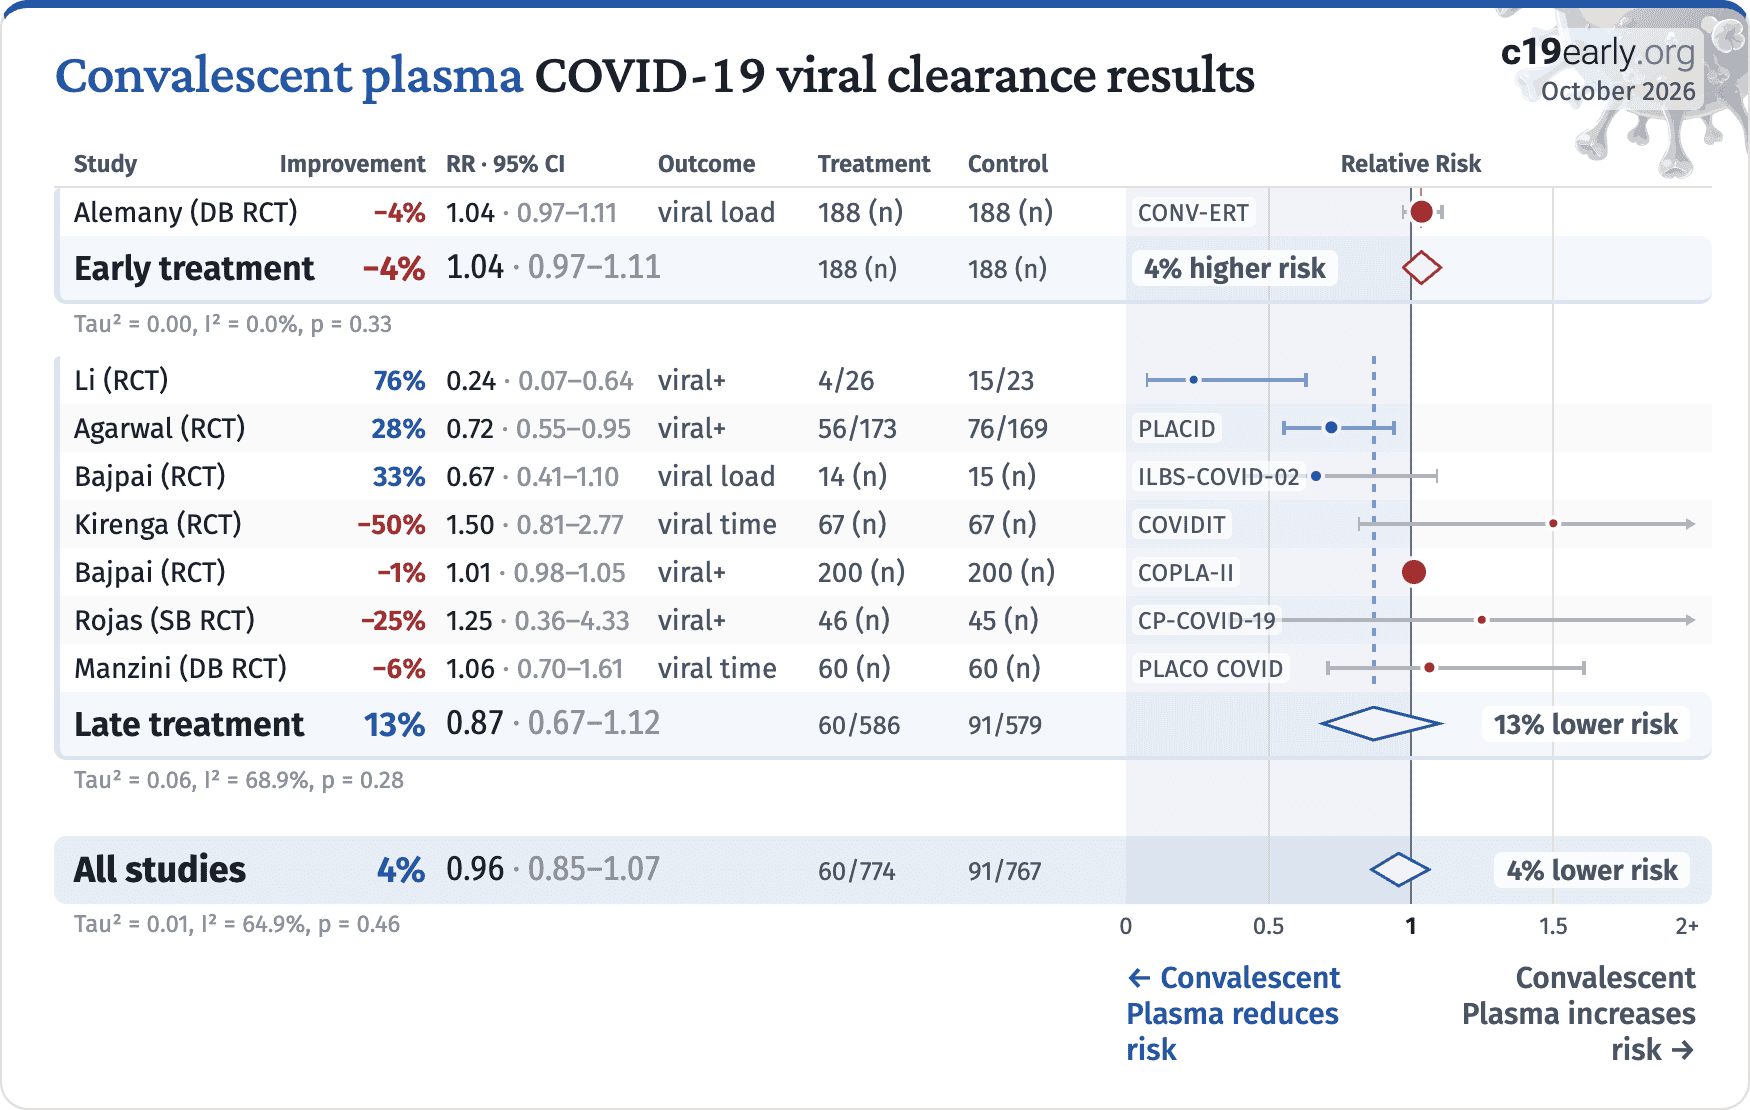
Convalescent plasma COVID-19 viral clearance results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment−4%1.04 · 0.97–1.11188 (n)188 (n)4% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.33
Late treatment13%0.87 · 0.67–1.1260/58691/57913% lower risk
Tau² = 0.06, I² = 68.9%, p = 0.28
All studies4%0.96 · 0.85–1.0760/77491/7674% lower risk
Tau² = 0.01, I² = 64.9%, p = 0.4600.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 13. Random-effects meta-analysis for viral clearance.
October 2026

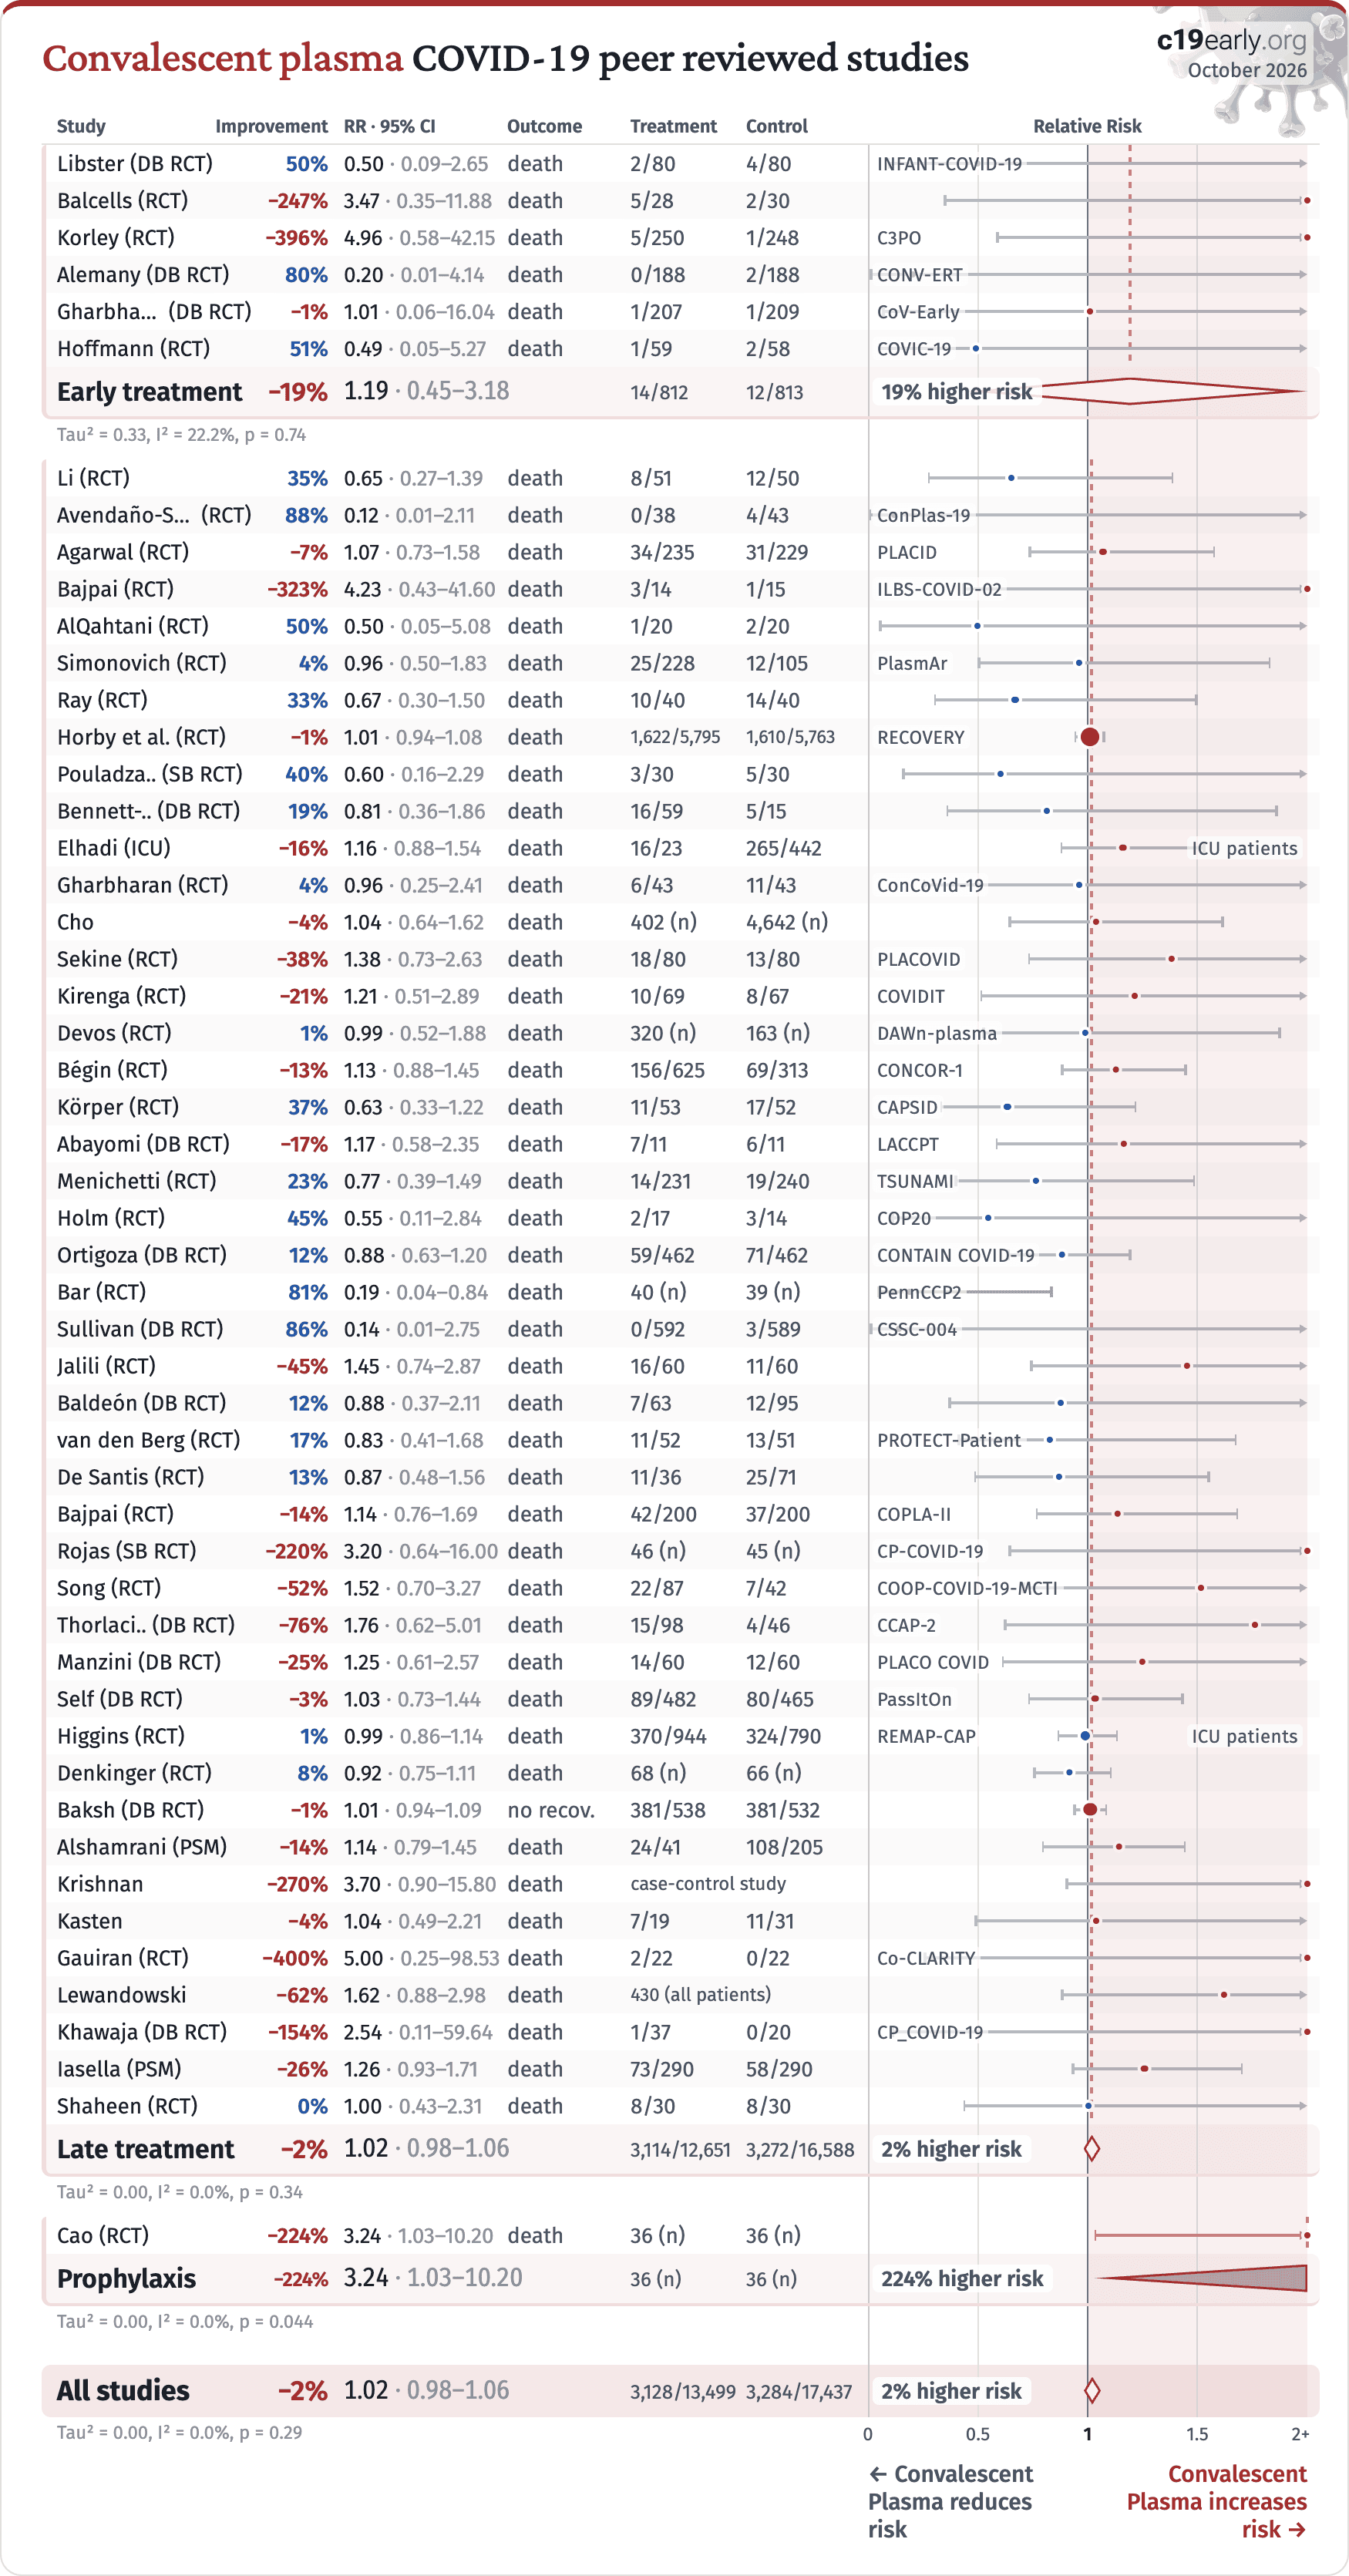
Convalescent plasma COVID-19 peer reviewed studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment−19%1.19 · 0.45–3.1814/81212/81319% higher risk
Tau² = 0.33, I² = 22.2%, p = 0.74
Li (RCT)35%0.65 · 0.27–1.39death8/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.11death0/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.58death34/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.60death3/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.08death1/202/20 Simonovich (RCT)4%0.96 · 0.50–1.83death25/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.50death10/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.08death1,622/5,7951,610/5,763RECOVERY Pouladza.. (SB RCT)40%0.60 · 0.16–2.29death3/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.86death16/595/15 Elhadi (ICU)−16%1.16 · 0.88–1.54death16/23265/442ICU patients Gharbharan (RCT)4%0.96 · 0.25–2.41death6/4311/43ConCoVid-19 Cho−4%1.04 · 0.64–1.62death402 (n)4,642 (n) Sekine (RCT)−38%1.38 · 0.73–2.63death18/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.89death10/698/67COVIDIT Devos (RCT)1%0.99 · 0.52–1.88death320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45death156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.22death11/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.35death7/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.49death14/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.84death2/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.20death59/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.84death40 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.75death0/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.87death16/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.11death7/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.68death11/5213/51PROTECT-Patient De Santis (RCT)13%0.87 · 0.48–1.56death11/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.69death42/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.00death46 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.27death22/877/42COOP-COVID-19-MCTI Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.01death15/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.57death14/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.44death89/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14death370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.11death68 (n)66 (n) Baksh (DB RCT)−1%1.01 · 0.94–1.09no recov.381/538381/532 Alshamrani (PSM)−14%1.14 · 0.79–1.45death24/41108/205 Krishnan−270%3.70 · 0.90–15.80deathcase-control study Kasten−4%1.04 · 0.49–2.21death7/1911/31 Gauiran (RCT)−400%5.00 · 0.25–98.53death2/220/22Co-CLARITY Lewandowski−62%1.62 · 0.88–2.98death430 (all patients) Khawaja (DB RCT)−154%2.54 · 0.11–59.64death1/370/20CP_COVID-19 Iasella (PSM)−26%1.26 · 0.93–1.71death73/29058/290 Shaheen (RCT)0%1.00 · 0.43–2.31death8/308/30
Late treatment−2%1.02 · 0.98–1.063,114/12,6513,272/16,5882% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.34
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−2%1.02 · 0.98–1.063,128/13,4993,284/17,4372% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.2900.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 14. Random-effects meta-analysis for peer reviewed studies. Zeraatkar et al. analyze 356 COVID-19 trials, finding no significant evidence that preprint results are inconsistent with peer-reviewed studies. They also show extremely long peer-review delays, with a median of 6 months to journal publication. A six month delay was equivalent to around 1.5 million deaths during the first two years of the pandemic. Authors recommend using preprint evidence, with appropriate checks for potential falsified data, which provides higher certainty much earlier. Davidson et al. also showed no important difference between meta-analysis results of preprints and peer-reviewed publications for COVID-19, based on 37 meta-analyses including 114 trials. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
October 2026

Convalescent plasma COVID-19 long COVID results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
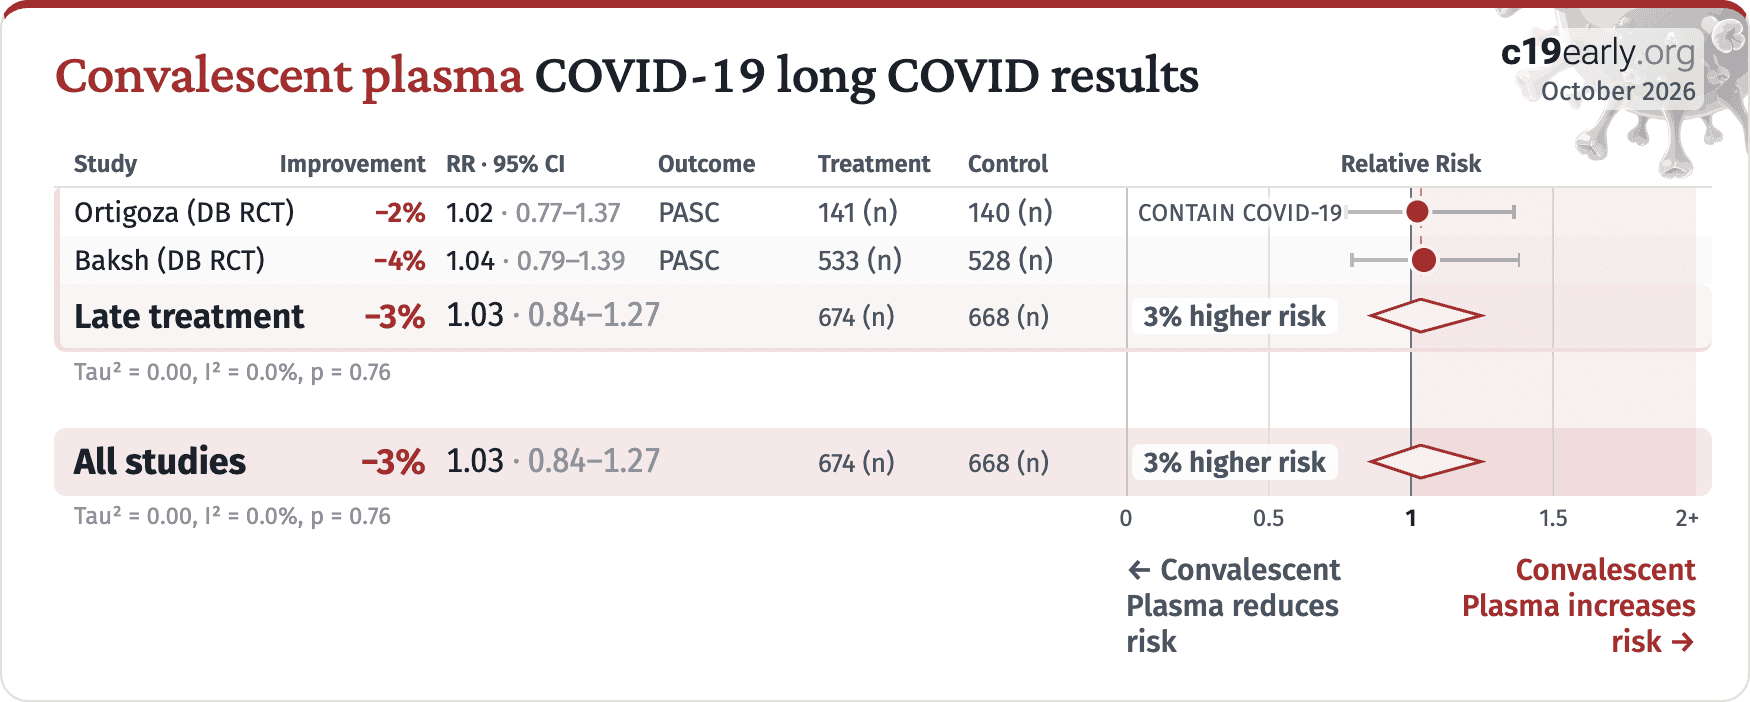
Late treatment−3%1.03 · 0.84–1.27674 (n)668 (n)3% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.76
All studies−3%1.03 · 0.84–1.27674 (n)668 (n)3% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.7600.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 15. Random-effects meta-analysis for long COVID. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
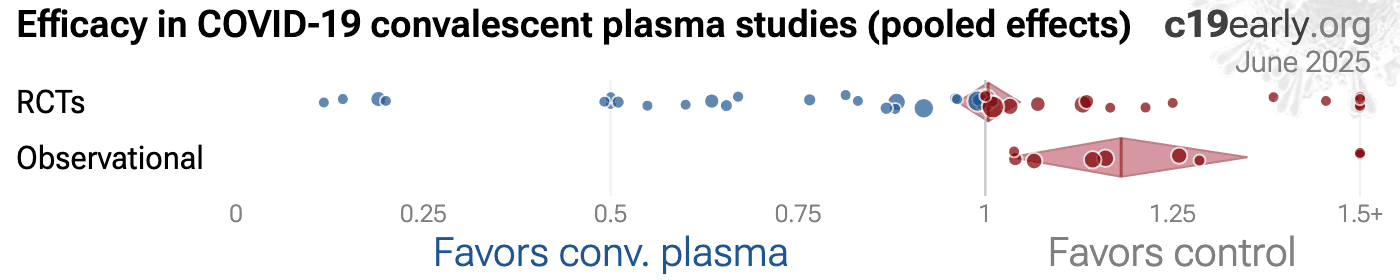
Fig. 16 shows a comparison of results for RCTs and observational studies. Fig. 17, 18, and 19 show forest plots for random-effects meta-analysis of all Randomized Controlled Trials, RCT mortality results, and RCT hospitalization results. RCT results are included in Table 1 and Table 2.
Loading..
Fig. 16. Results for RCTs and observational studies.
RCTs help to make study groups more similar and can provide a higher level of evidence, however they are subject to many biases42, and analysis of double-blind RCTs has identified extreme levels of bias43. For COVID-19, the overhead may delay treatment, dramatically compromising efficacy; they may encourage monotherapy for simplicity at the cost of efficacy which may rely on combined or synergistic effects; the participants that sign up may not reflect real world usage or the population that benefits most in terms of age, comorbidities, severity of illness, or other factors; standard of care may be compromised and unable to evolve quickly based on emerging research for new diseases; errors may be made in randomization and medication delivery; and investigators may have hidden agendas or vested interests influencing design, operation, analysis, reporting, and the potential for fraud. All of these biases have been observed with COVID-19 RCTs. There is no guarantee that a specific RCT provides a higher level of evidence.
RCTs are expensive and many RCTs are funded by pharmaceutical companies or other organizations with conflicts of interest, for example governments that previously denied treatment with the study drug. For COVID-19, this creates an incentive to show efficacy for patented commercial products, and an incentive to show a lack of efficacy for inexpensive treatments. The bias is expected to be significant, for example Als-Nielsen et al. analyzed 370 RCTs from Cochrane reviews, showing that trials funded by for-profit organizations were 5 times more likely to recommend the experimental drug compared with those funded by nonprofit organizations. Bekelman et al. and Lundh et al. show that industry-sponsored studies are more likely to be favorable. For COVID-19, some major philanthropic organizations are largely funded by investments with extreme conflicts of interest for and against specific COVID-19 interventions.
High quality RCTs for novel acute diseases are more challenging, with increased ethical issues due to the urgency of treatment, increased risk due to enrollment delays, and more difficult design with a rapidly evolving evidence base. For COVID-19, the most common site of initial infection is the upper respiratory tract. Immediate treatment is likely to be most successful and may prevent or slow progression to other parts of the body. For a non-prophylaxis RCT, it makes sense to provide treatment in advance and instruct patients to use it immediately on symptoms, just as some governments have done by providing medication kits in advance. Unfortunately, no RCTs have been done in this way. Every treatment RCT to date involves delayed treatment. Among the 227 treatments we have analyzed, 67% of RCTs involve very late treatment 5+ days after onset. No non-prophylaxis COVID-19 RCTs match the potential real-world use of early treatments. They may more accurately represent results for treatments that require visiting a medical facility, e.g., those requiring intravenous administration.
Concato et al. report a paradoxical finding—RCT results had higher variability, and only RCTs were found to sometimes report significant results the opposite of the overall result. The same trend is seen for the most popular (most politicized) COVID-19 treatments—considering all statistically significant results reported in studies, RCTs are slightly more likely to report a result in the opposite direction. In other words, for these COVID-19 treatments and for the topics covered by Concato et al., assuming causality from a single study is more likely to result in an incorrect conclusion for RCTs.
Increased risk of inconsistent results for RCTs suggests higher prevalence of bias, which may arise due to many issues including design bias, conflicts of interest, treatment differences by physicians aware of allocation, attrition bias, ascertainment bias, randomization failures, errors, or fraud.
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. Of these, 54% have been confirmed in RCTs, with a mean delay of 7.8 months (62% with 8.7 months delay for low-cost treatments). The remaining treatments either have no RCTs, or the point estimate is consistent.
Neither observational studies nor RCTs prove causation—any study can be flawed or fraudulent. We need much more, for example a combination of results from many independent teams, detailed understanding of each study, knowledge of conflicts/team reliability, dose-response relationships, delay-response relationships, logical results across outcomes, or details consistent with preclinical expectations.
All studies must be evaluated individually. RCTs for a given medication and disease may be more reliable, however they may also be less reliable. For off-patent medications, very high conflict of interest trials may be more likely to be RCTs, and more likely to be large trials that dominate meta-analyses.
October 2026

Convalescent plasma COVID-19 Randomized Controlled Trials

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
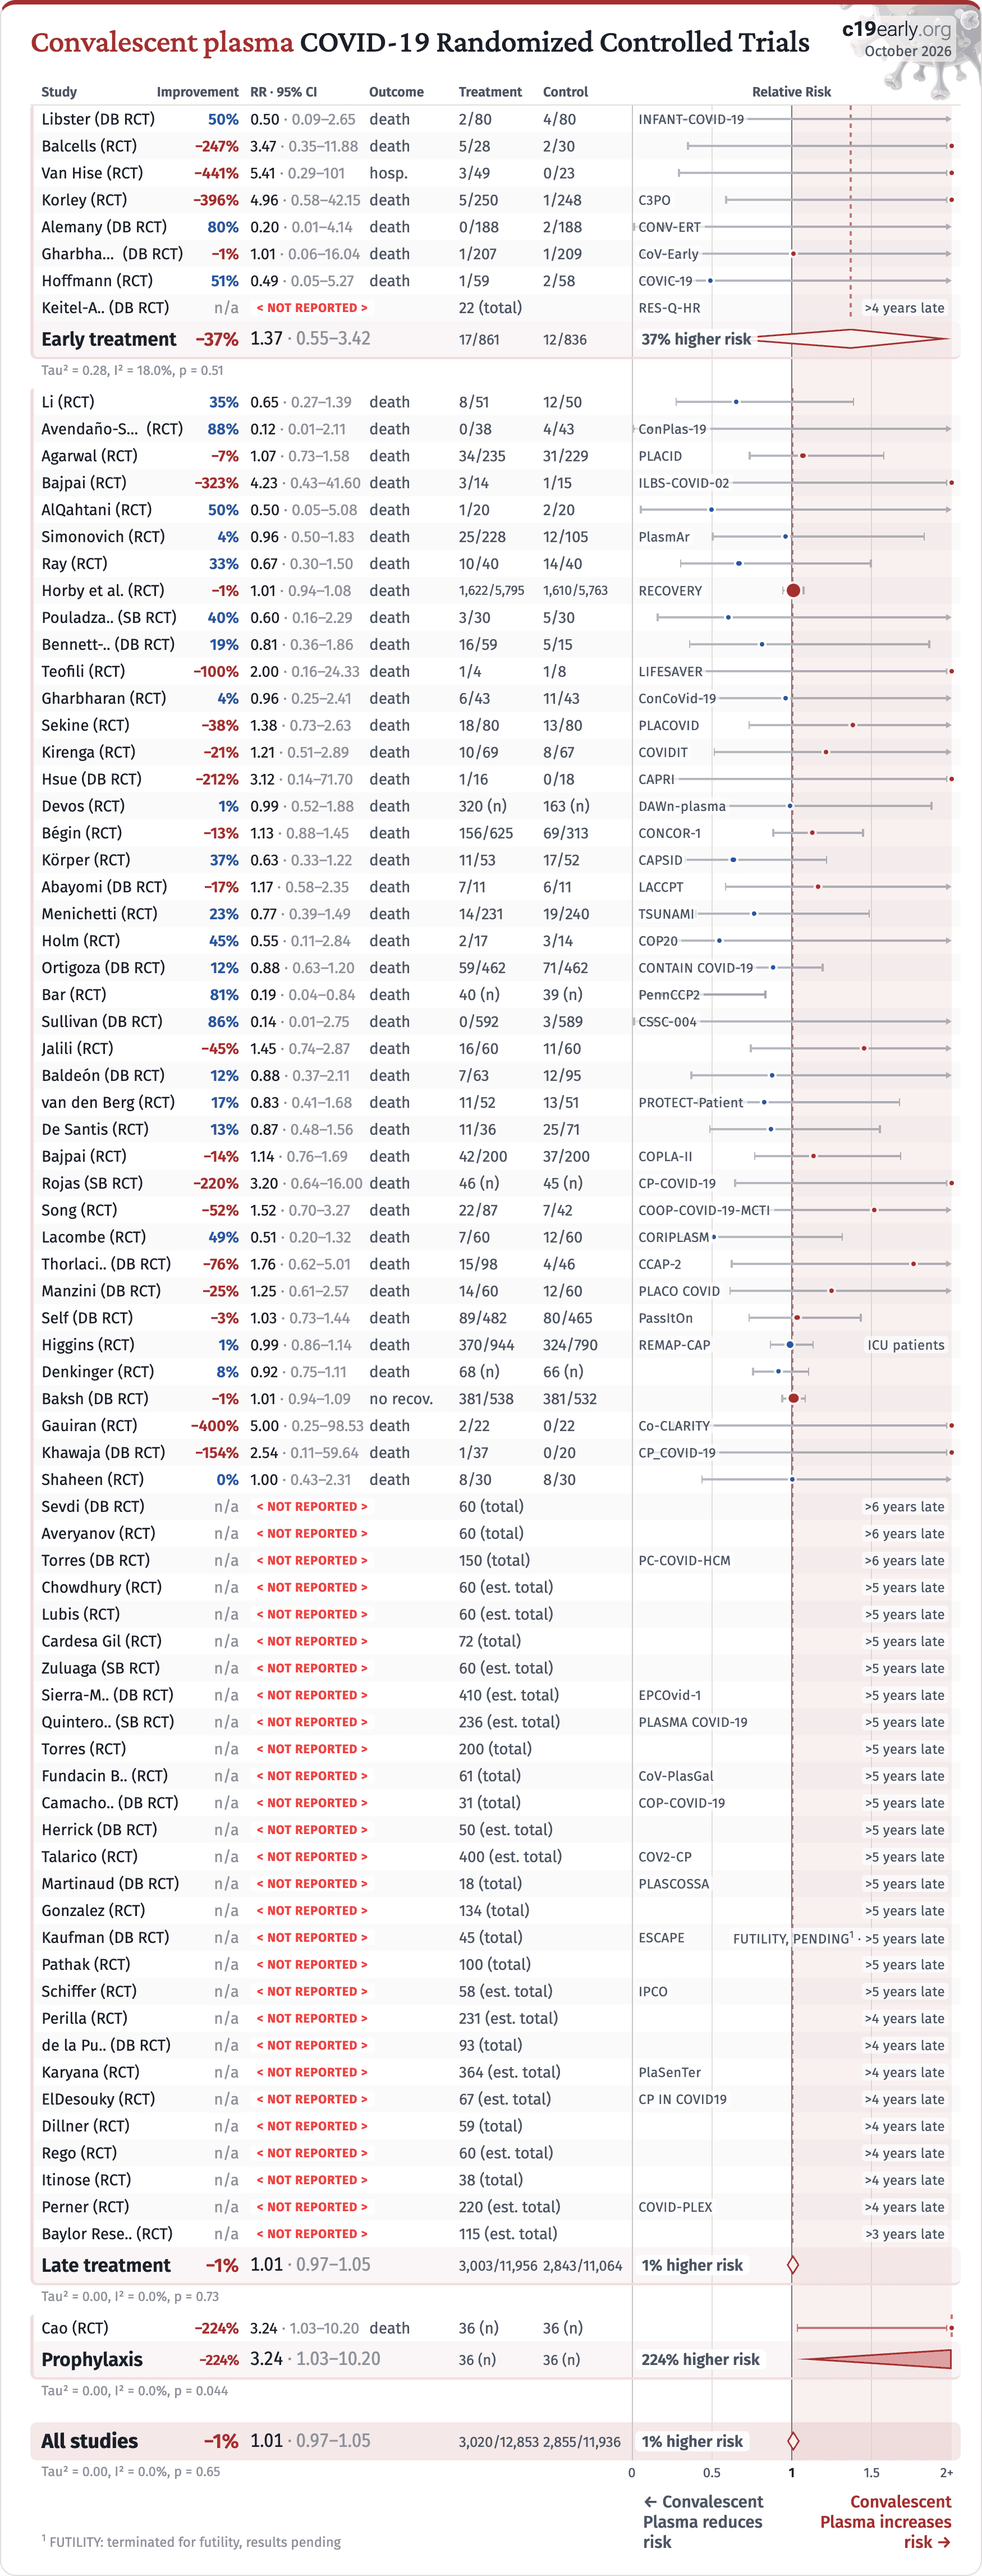
Early treatment−37%1.37 · 0.55–3.4217/86112/83637% higher risk
Tau² = 0.28, I² = 18.0%, p = 0.51
Li (RCT)35%0.65 · 0.27–1.39death8/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.11death0/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.58death34/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.60death3/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.08death1/202/20 Simonovich (RCT)4%0.96 · 0.50–1.83death25/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.50death10/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.08death1,622/5,7951,610/5,763RECOVERY Pouladza.. (SB RCT)40%0.60 · 0.16–2.29death3/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.86death16/595/15 Teofili (RCT)−100%2.00 · 0.16–24.33death1/41/8LIFESAVER Gharbharan (RCT)4%0.96 · 0.25–2.41death6/4311/43ConCoVid-19 Sekine (RCT)−38%1.38 · 0.73–2.63death18/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.89death10/698/67COVIDIT Hsue (DB RCT)−212%3.12 · 0.14–71.70death1/160/18CAPRI Devos (RCT)1%0.99 · 0.52–1.88death320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45death156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.22death11/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.35death7/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.49death14/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.84death2/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.20death59/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.84death40 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.75death0/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.87death16/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.11death7/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.68death11/5213/51PROTECT-Patient De Santis (RCT)13%0.87 · 0.48–1.56death11/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.69death42/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.00death46 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.27death22/877/42COOP-COVID-19-MCTI Lacombe (RCT)49%0.51 · 0.20–1.32death7/6012/60CORIPLASM Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.01death15/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.57death14/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.44death89/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14death370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.11death68 (n)66 (n) Baksh (DB RCT)−1%1.01 · 0.94–1.09no recov.381/538381/532 Gauiran (RCT)−400%5.00 · 0.25–98.53death2/220/22Co-CLARITY Khawaja (DB RCT)−154%2.54 · 0.11–59.64death1/370/20CP_COVID-19 Shaheen (RCT)0%1.00 · 0.43–2.31death8/308/30 Sevdi (DB RCT)n/a< NOT REPORTED >60 (total)>6 years late Averyanov (RCT)n/a< NOT REPORTED >60 (total)>6 years late Torres (DB RCT)n/a< NOT REPORTED >150 (total)PC-COVID-HCM>6 years late Chowdhury (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Lubis (RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Cardesa Gil (RCT)n/a< NOT REPORTED >72 (total)>5 years late Zuluaga (SB RCT)n/a< NOT REPORTED >60 (est. total)>5 years late Sierra-M.. (DB RCT)n/a< NOT REPORTED >410 (est. total)EPCOvid-1>5 years late Quintero.. (SB RCT)n/a< NOT REPORTED >236 (est. total)PLASMA COVID-19>5 years late Torres (RCT)n/a< NOT REPORTED >200 (total)>5 years late Fundacin B.. (RCT)n/a< NOT REPORTED >61 (total)CoV-PlasGal>5 years late Camacho.. (DB RCT)n/a< NOT REPORTED >31 (total)COP-COVID-19>5 years late Herrick (DB RCT)n/a< NOT REPORTED >50 (est. total)>5 years late Talarico (RCT)n/a< NOT REPORTED >400 (est. total)COV2-CP>5 years late Martinaud (DB RCT)n/a< NOT REPORTED >18 (total)PLASCOSSA>5 years late Gonzalez (RCT)n/a< NOT REPORTED >134 (total)>5 years late Kaufman (DB RCT)n/a< NOT REPORTED >45 (total)ESCAPEFUTILITY, PENDING1 · >5 years late Pathak (RCT)n/a< NOT REPORTED >100 (total)>5 years late Schiffer (RCT)n/a< NOT REPORTED >58 (est. total)IPCO>5 years late Perilla (RCT)n/a< NOT REPORTED >231 (est. total)>4 years late de la Pu.. (DB RCT)n/a< NOT REPORTED >93 (total)>4 years late Karyana (RCT)n/a< NOT REPORTED >364 (est. total)PlaSenTer>4 years late ElDesouky (RCT)n/a< NOT REPORTED >67 (est. total)CP IN COVID19>4 years late Dillner (RCT)n/a< NOT REPORTED >59 (total)>4 years late Rego (RCT)n/a< NOT REPORTED >60 (est. total)>4 years late Itinose (RCT)n/a< NOT REPORTED >38 (total)>4 years late Perner (RCT)n/a< NOT REPORTED >220 (est. total)COVID-PLEX>4 years late Baylor Rese.. (RCT)n/a< NOT REPORTED >115 (est. total)>3 years late
Late treatment−1%1.01 · 0.97–1.053,003/11,9562,843/11,0641% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.73
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−1%1.01 · 0.97–1.053,020/12,8532,855/11,9361% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.6500.511.52+
1 FUTILITY: terminated for futility, results pending
Rotate screen for more detailsIncrease width for more details
← Convalescent
Plasma reduces
risk
Convalescent
Plasma increases
risk →
Fig. 17. Random-effects meta-analysis for all Randomized Controlled Trials. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
October 2026

Convalescent plasma COVID-19 RCT mortality results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
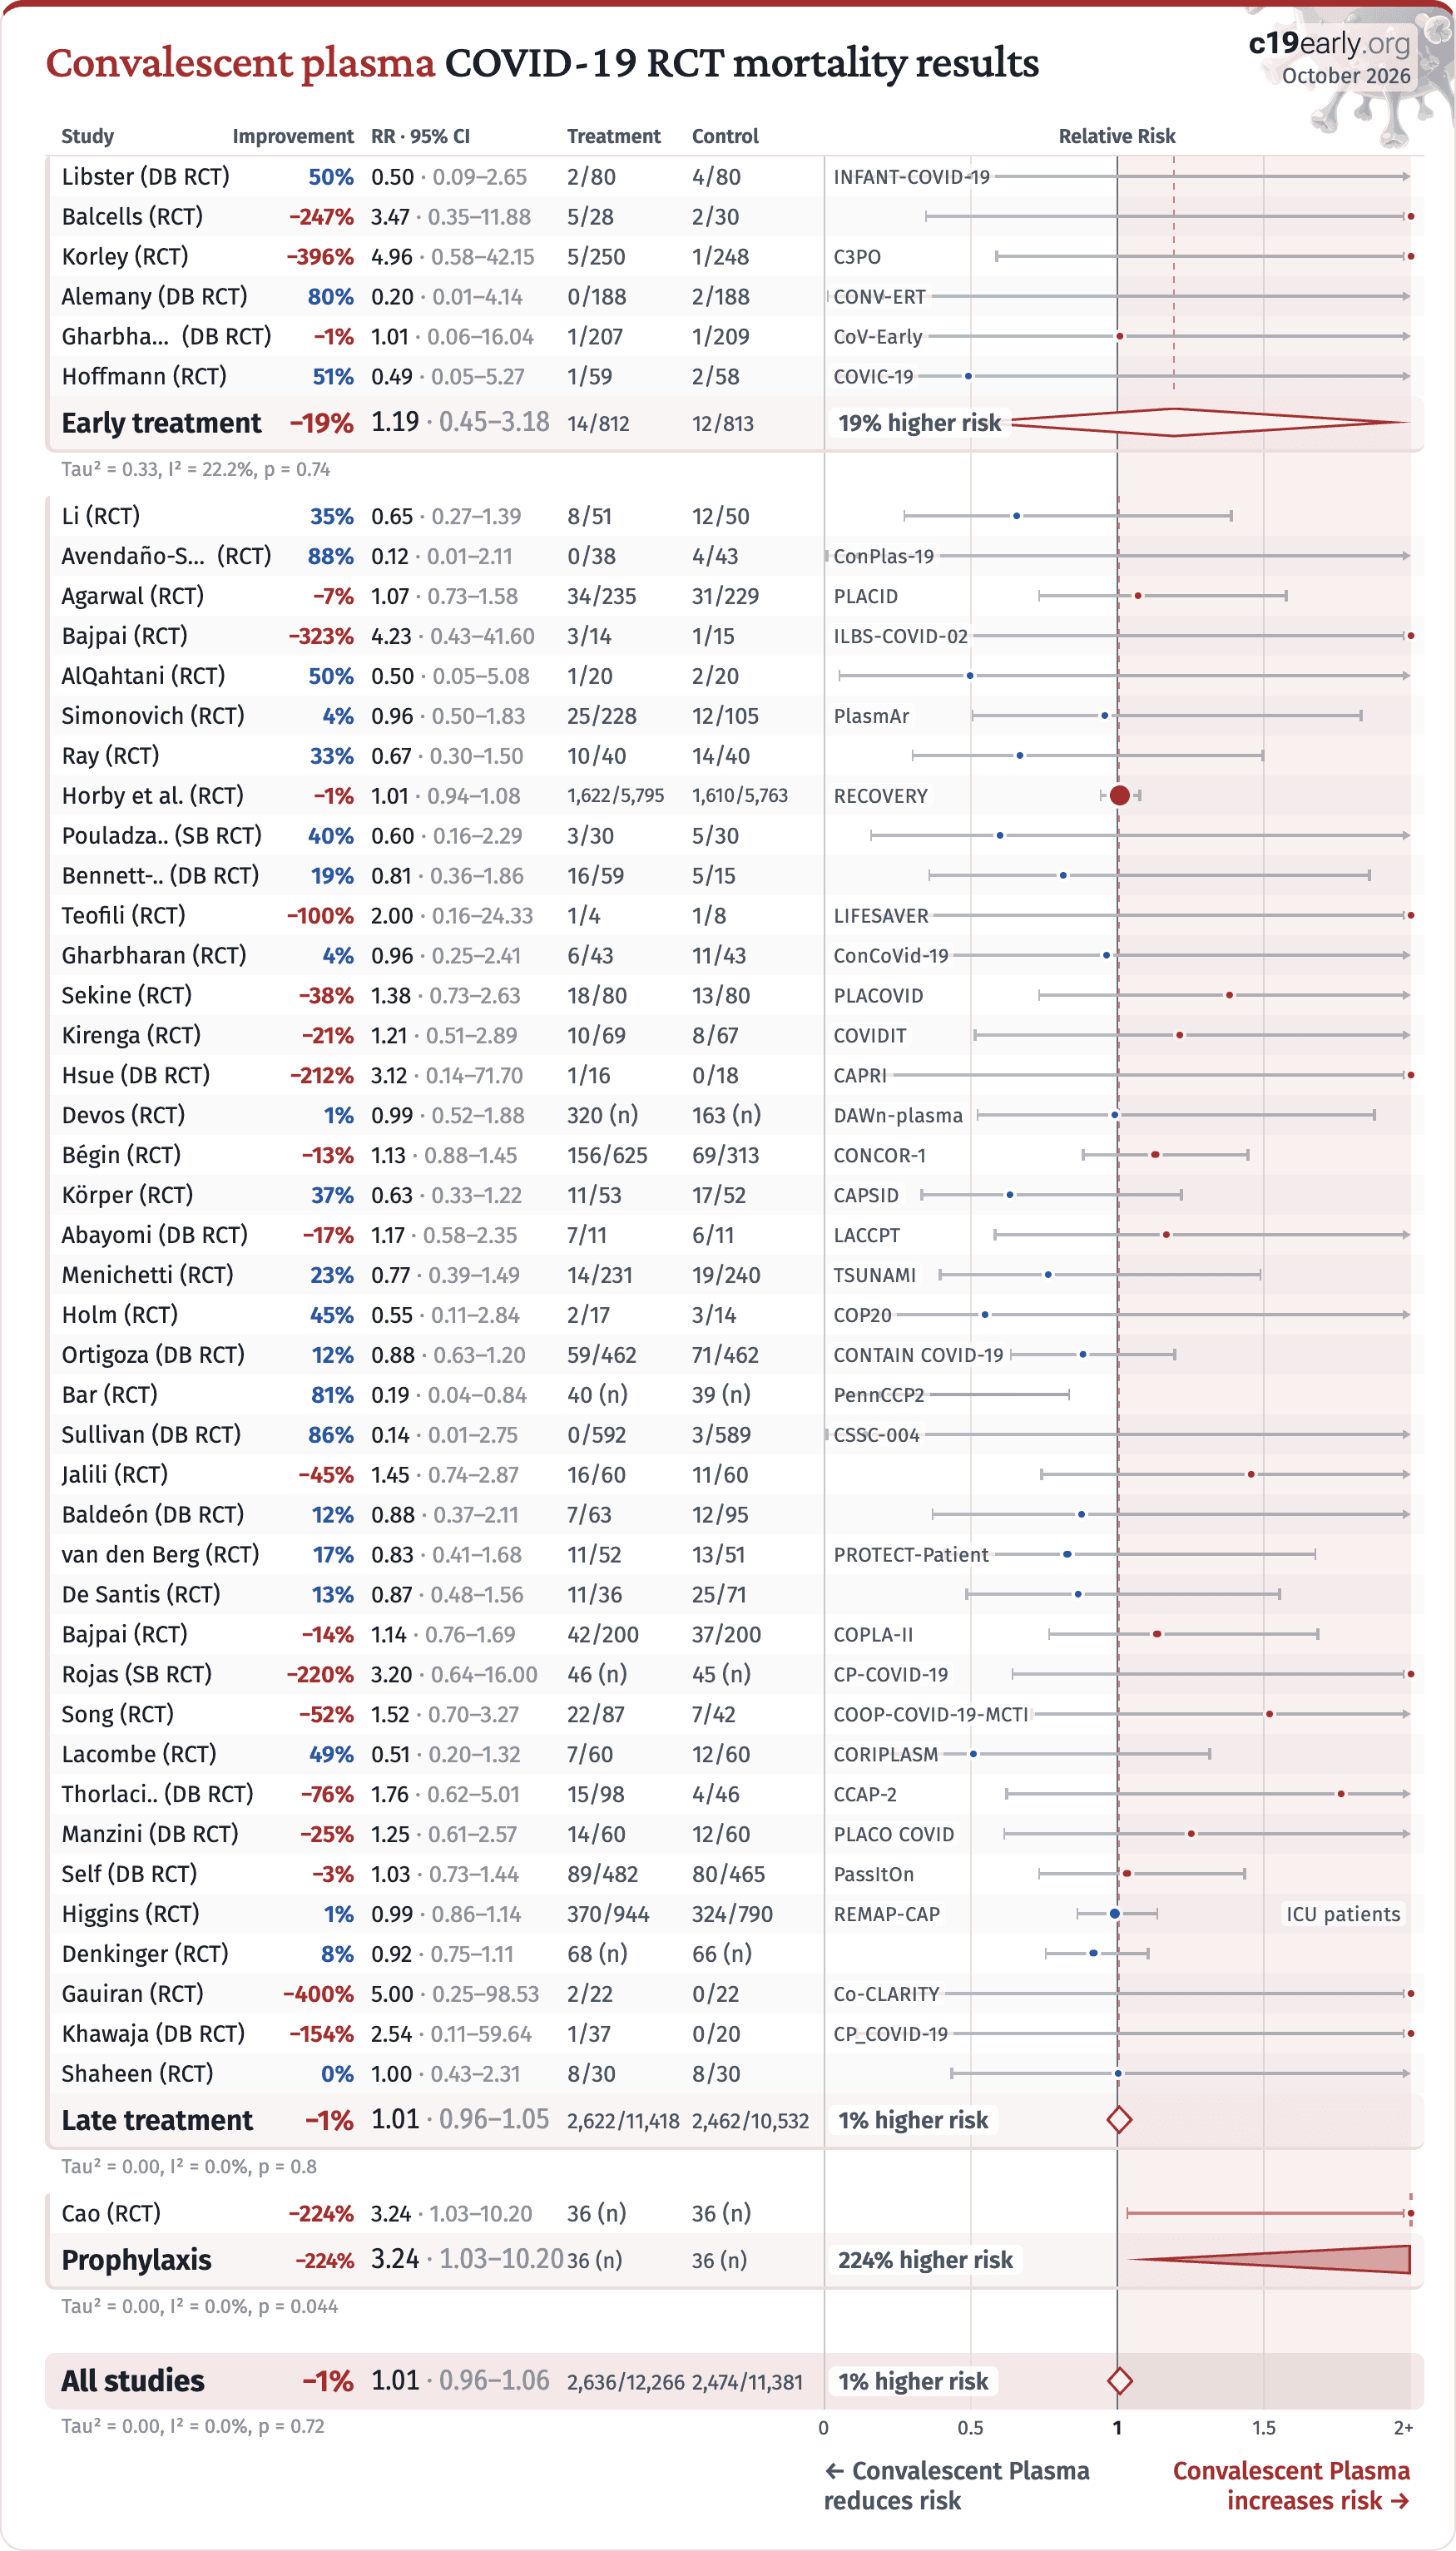
Early treatment−19%1.19 · 0.45–3.1814/81212/81319% higher risk
Tau² = 0.33, I² = 22.2%, p = 0.74
Li (RCT)35%0.65 · 0.27–1.398/5112/50 Avendaño-Solà (RCT)88%0.12 · 0.01–2.110/384/43ConPlas-19 Agarwal (RCT)−7%1.07 · 0.73–1.5834/23531/229PLACID Bajpai (RCT)−323%4.23 · 0.43–41.603/141/15ILBS-COVID-02 AlQahtani (RCT)50%0.50 · 0.05–5.081/202/20 Simonovich (RCT)4%0.96 · 0.50–1.8325/22812/105PlasmAr Ray (RCT)33%0.67 · 0.30–1.5010/4014/40 Horby et al. (RCT)−1%1.01 · 0.94–1.081,622/5,7951,610/5,763RECOVERY Pouladza.. (SB RCT)40%0.60 · 0.16–2.293/305/30 Bennett-.. (DB RCT)19%0.81 · 0.36–1.8616/595/15 Teofili (RCT)−100%2.00 · 0.16–24.331/41/8LIFESAVER Gharbharan (RCT)4%0.96 · 0.25–2.416/4311/43ConCoVid-19 Sekine (RCT)−38%1.38 · 0.73–2.6318/8013/80PLACOVID Kirenga (RCT)−21%1.21 · 0.51–2.8910/698/67COVIDIT Hsue (DB RCT)−212%3.12 · 0.14–71.701/160/18CAPRI Devos (RCT)1%0.99 · 0.52–1.88320 (n)163 (n)DAWn-plasma Bégin (RCT)−13%1.13 · 0.88–1.45156/62569/313CONCOR-1 Körper (RCT)37%0.63 · 0.33–1.2211/5317/52CAPSID Abayomi (DB RCT)−17%1.17 · 0.58–2.357/116/11LACCPT Menichetti (RCT)23%0.77 · 0.39–1.4914/23119/240TSUNAMI Holm (RCT)45%0.55 · 0.11–2.842/173/14COP20 Ortigoza (DB RCT)12%0.88 · 0.63–1.2059/46271/462CONTAIN COVID-19 Bar (RCT)81%0.19 · 0.04–0.8440 (n)39 (n)PennCCP2 Sullivan (DB RCT)86%0.14 · 0.01–2.750/5923/589CSSC-004 Jalili (RCT)−45%1.45 · 0.74–2.8716/6011/60 Baldeón (DB RCT)12%0.88 · 0.37–2.117/6312/95 van den Berg (RCT)17%0.83 · 0.41–1.6811/5213/51PROTECT-Patient De Santis (RCT)13%0.87 · 0.48–1.5611/3625/71 Bajpai (RCT)−14%1.14 · 0.76–1.6942/20037/200COPLA-II Rojas (SB RCT)−220%3.20 · 0.64–16.0046 (n)45 (n)CP-COVID-19 Song (RCT)−52%1.52 · 0.70–3.2722/877/42COOP-COVID-19-MCTI Lacombe (RCT)49%0.51 · 0.20–1.327/6012/60CORIPLASM Thorlaci.. (DB RCT)−76%1.76 · 0.62–5.0115/984/46CCAP-2 Manzini (DB RCT)−25%1.25 · 0.61–2.5714/6012/60PLACO COVID Self (DB RCT)−3%1.03 · 0.73–1.4489/48280/465PassItOn Higgins (RCT)1%0.99 · 0.86–1.14370/944324/790REMAP-CAPICU patients Denkinger (RCT)8%0.92 · 0.75–1.1168 (n)66 (n) Gauiran (RCT)−400%5.00 · 0.25–98.532/220/22Co-CLARITY Khawaja (DB RCT)−154%2.54 · 0.11–59.641/370/20CP_COVID-19 Shaheen (RCT)0%1.00 · 0.43–2.318/308/30
Late treatment−1%1.01 · 0.96–1.052,622/11,4182,462/10,5321% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.8
Prophylaxis−224%3.24 · 1.03–10.2036 (n)36 (n)224% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.044
All studies−1%1.01 · 0.96–1.062,636/12,2662,474/11,3811% higher risk
Tau² = 0.00, I² = 0.0%, p = 0.7200.511.52+
Rotate screen for more detailsIncrease width for more details
← Convalescent Plasma
reduces risk
Convalescent Plasma
increases risk →
Fig. 18. Random-effects meta-analysis for RCT mortality results.
Fig. 19. Random-effects meta-analysis for RCT hospitalization results.
29 convalescent plasma RCTs have not reported results48-76. The trials report a total of 3,534 patients, with 15 trials having actual enrollment of 1,143, and the remainder estimated. The results are delayed from 3 years to over 6 years.
Heterogeneity in COVID-19 studies arises from many factors including:
The time between infection or the onset of symptoms and treatment may critically affect how well a treatment works. For example an antiviral may be very effective when used early but may not be effective in late stage disease, and may even be harmful. Oseltamivir, for example, is generally only considered effective for influenza when used within 0-36 or 0-48 hours77,78. Baloxavir marboxil studies for influenza also show that treatment delay is critical — Ikematsu et al. report an 86% reduction in cases for post-exposure prophylaxis, Hayden et al. show a 33 hour reduction in the time to alleviation of symptoms for treatment within 24 hours and a reduction of 13 hours for treatment within 24-48 hours, and Kumar et al. report only 2.5 hours improvement for inpatient treatment.
Table 3. Studies of baloxavir marboxil for influenza show that early treatment is more effective.
Treatment delayResult
Post-exposure prophylaxis86% fewer cases79
<24 hours-33 hours symptoms80
24-48 hours-13 hours symptoms80
Inpatients-2.5 hours to improvement81
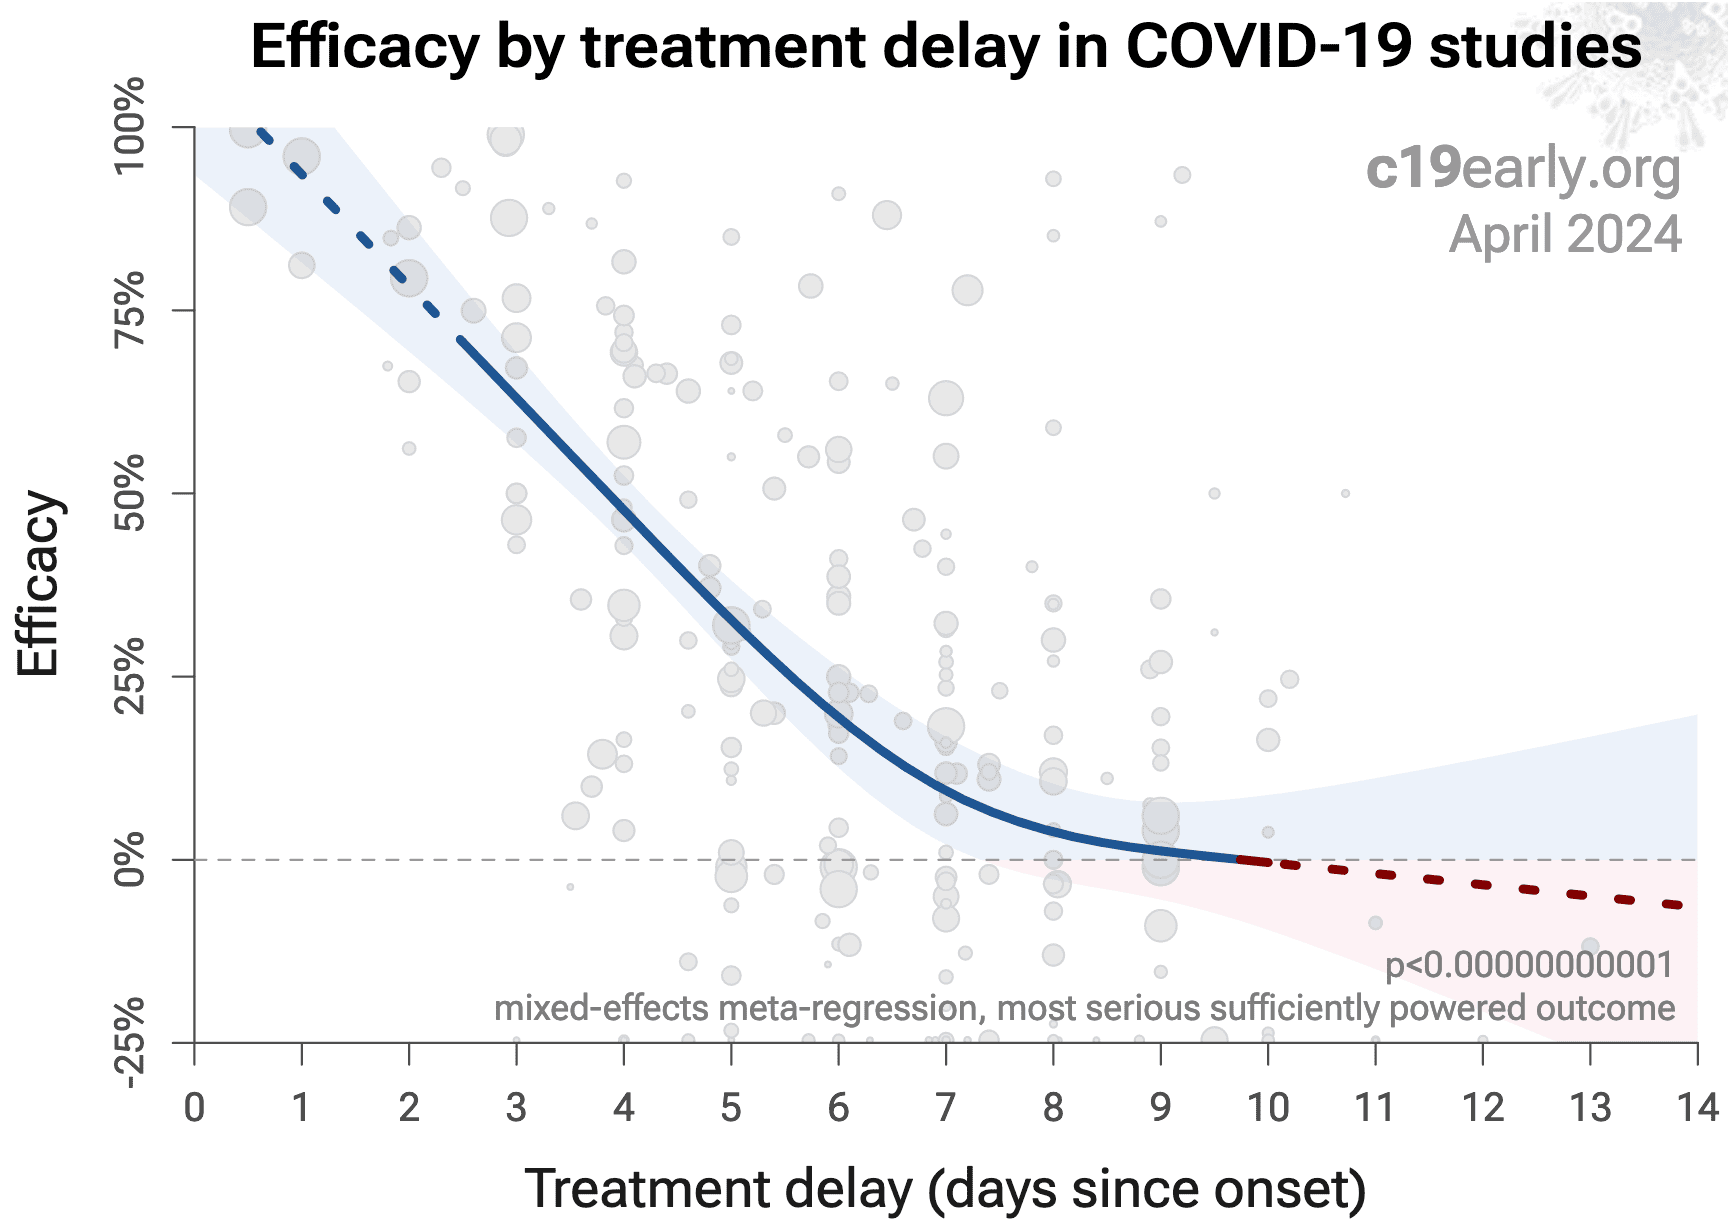
Fig. 20 shows a mixed-effects meta-regression for efficacy as a function of treatment delay in COVID-19 studies from 227 treatments, showing that efficacy declines rapidly with treatment delay. Early treatment is critical for COVID-19.
Loading..
Fig. 20. Early treatment is more effective. Meta-regression showing efficacy as a function of treatment delay in COVID-19 studies from 227 treatments.
Details of the patient population including age and comorbidities may critically affect how well a treatment works. For example, many COVID-19 studies with relatively young low-comorbidity patients show all patients recovering quickly with or without treatment. In such cases, there is little room for an effective treatment to improve results, for example as in López-Medina et al.
Efficacy may depend critically on the distribution of SARS-CoV-2 variants encountered by patients. Risk varies significantly across variants83, for example the Gamma variant shows significantly different characteristics84-87. Different mechanisms of action may be more or less effective depending on variants, for example the degree to which TMPRSS2 contributes to viral entry can differ across variants88,89.
Effectiveness may depend strongly on the dosage and treatment regimen.
The quality of medications may vary significantly between manufacturers and production batches, which may significantly affect efficacy and safety. Williams et al. analyze ivermectin from 11 different sources, showing highly variable antiparasitic efficacy across different manufacturers. Xu et al. analyze a treatment from two different manufacturers, showing 9 different impurities, with significantly different concentrations for each manufacturer.
The use of other treatments may significantly affect outcomes, including supplements, other medications, or other interventions such as prone positioning. Treatments may be synergistic92-116, therefore efficacy may depend strongly on combined treatments.
Across all studies there is a strong association between different outcomes, for example improved recovery is strongly associated with lower mortality. However, efficacy may differ depending on the effect measured, for example a treatment may be more effective against secondary complications and have minimal effect on viral clearance.
The distribution of studies will alter the outcome of a meta-analysis. Consider a simplified example where everything is equal except for the treatment delay, and effectiveness decreases to zero or below with increasing delay. If there are many studies using very late treatment, the outcome may be negative, even though early treatment is very effective. All meta-analyses combine heterogeneous studies, varying in population, variants, and potentially all factors above, and therefore may obscure efficacy by including studies where treatment is less effective. Generally, we expect the estimated effect size from meta-analysis to be less than that for the optimal case. Looking at all studies is valuable for providing an overview of all research, important to avoid cherry-picking, and informative when a positive result is found despite combining less-optimal situations. However, the resulting estimate does not apply to specific cases such as early treatment in high-risk populations. While we present results for all studies, we also present treatment time and individual outcome analyses, which may be more informative for specific use cases.
For COVID-19, delay in clinical results translates into additional death and morbidity, as well as additional economic and societal damage. Combining the results of studies reporting different outcomes is required. There may be no mortality in a trial with low-risk patients, however a reduction in severity or improved viral clearance may translate into lower mortality in a high-risk population. Different studies may report lower severity, improved recovery, and lower mortality, and the significance may be very high when combining the results. "The studies reported different outcomes" is not a good reason for disregarding results. Pooling the results of studies reporting different outcomes allows us to use more of the available information. Logically we should, and do, use additional information when evaluating treatments—for example dose-response and treatment delay-response relationships provide additional evidence of efficacy that is considered when reviewing the evidence for a treatment.
We present both specific outcome and pooled analyses. In order to combine the results of studies reporting different outcomes we use the most serious outcome reported in each study, based on the thesis that improvement in the most serious outcome provides comparable measures of efficacy for a treatment. A critical advantage of this approach is simplicity and transparency. There are many other ways to combine evidence for different outcomes, along with additional evidence such as dose-response relationships, however these increase complexity.
Trials with high-risk patients may be restricted due to ethics for treatments that are known or expected to be effective, and they increase difficulty for recruiting. Using less severe outcomes as a proxy for more serious outcomes allows faster and safer collection of evidence.
For many COVID-19 treatments, a reduction in mortality logically follows from a reduction in hospitalization, which follows from a reduction in symptomatic cases, which follows from a reduction in PCR positivity. We can directly test this for COVID-19.
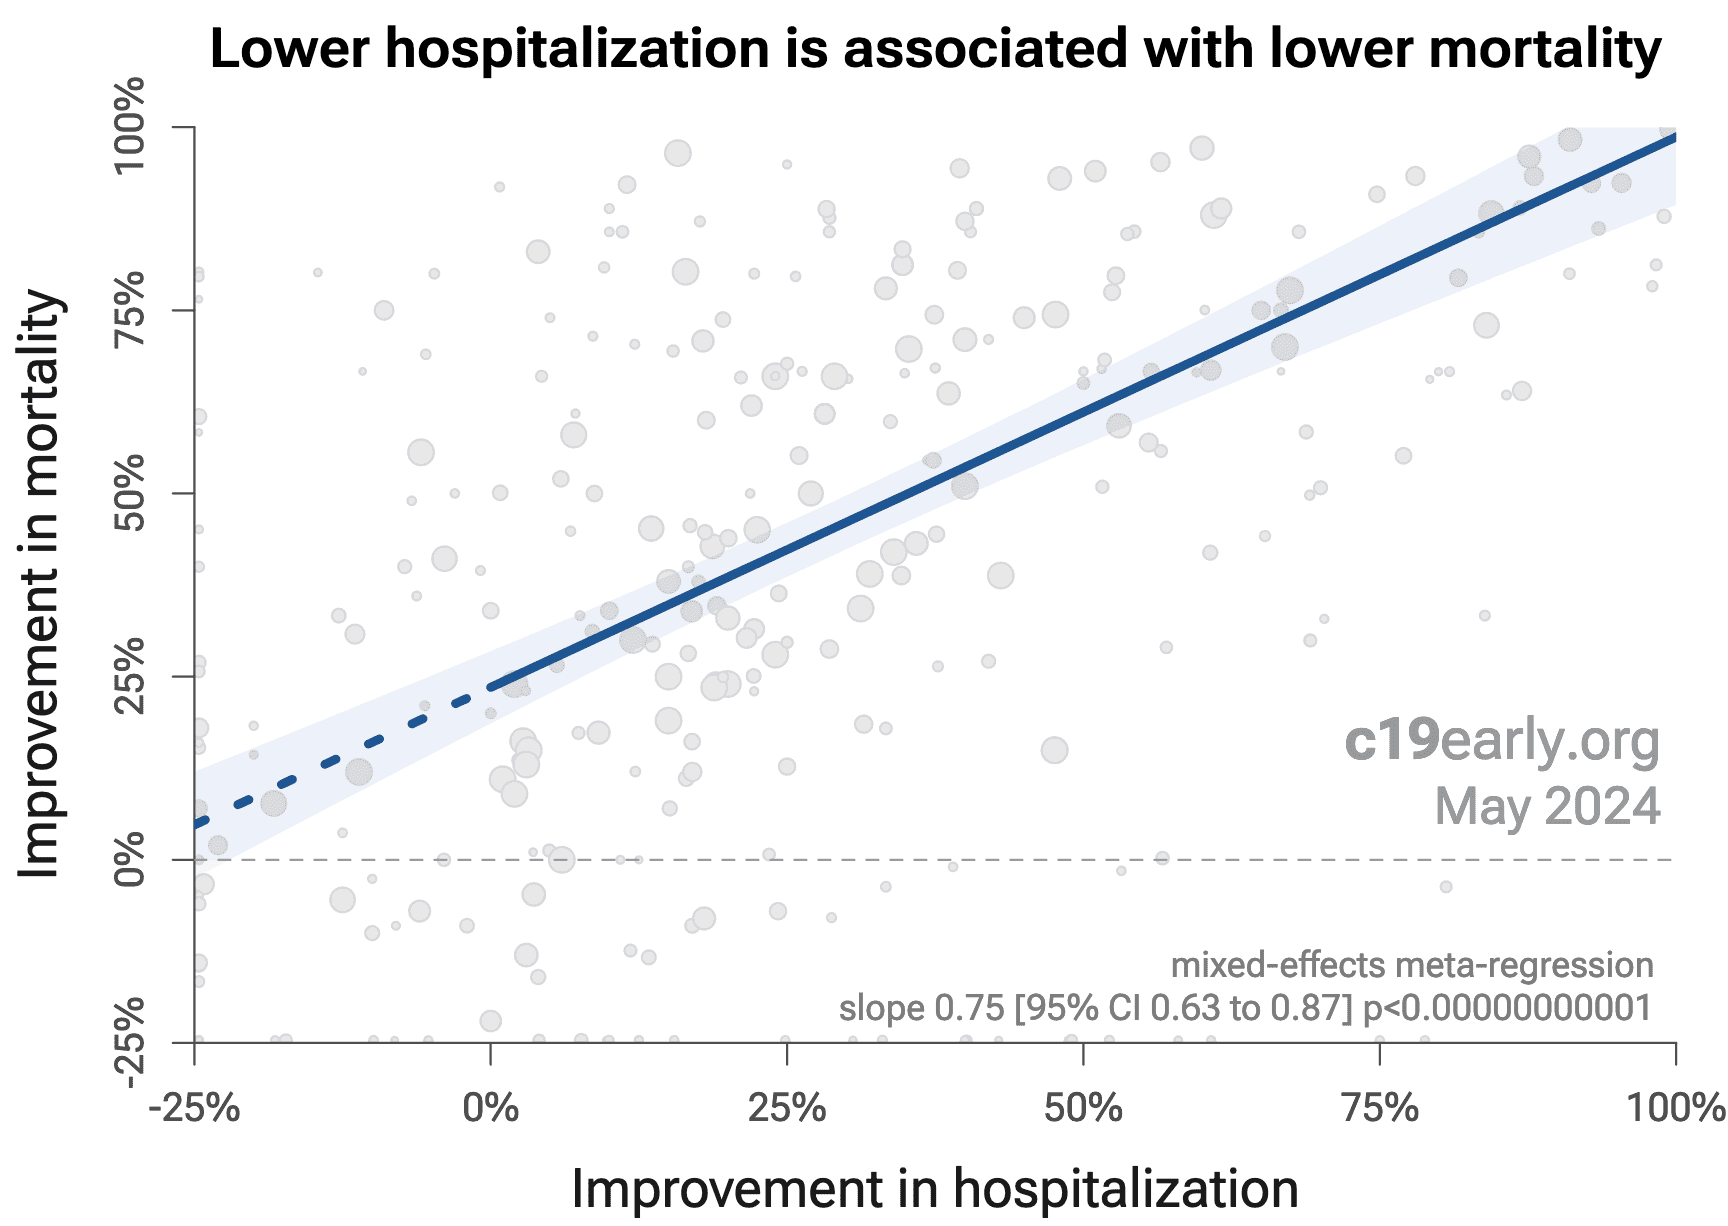
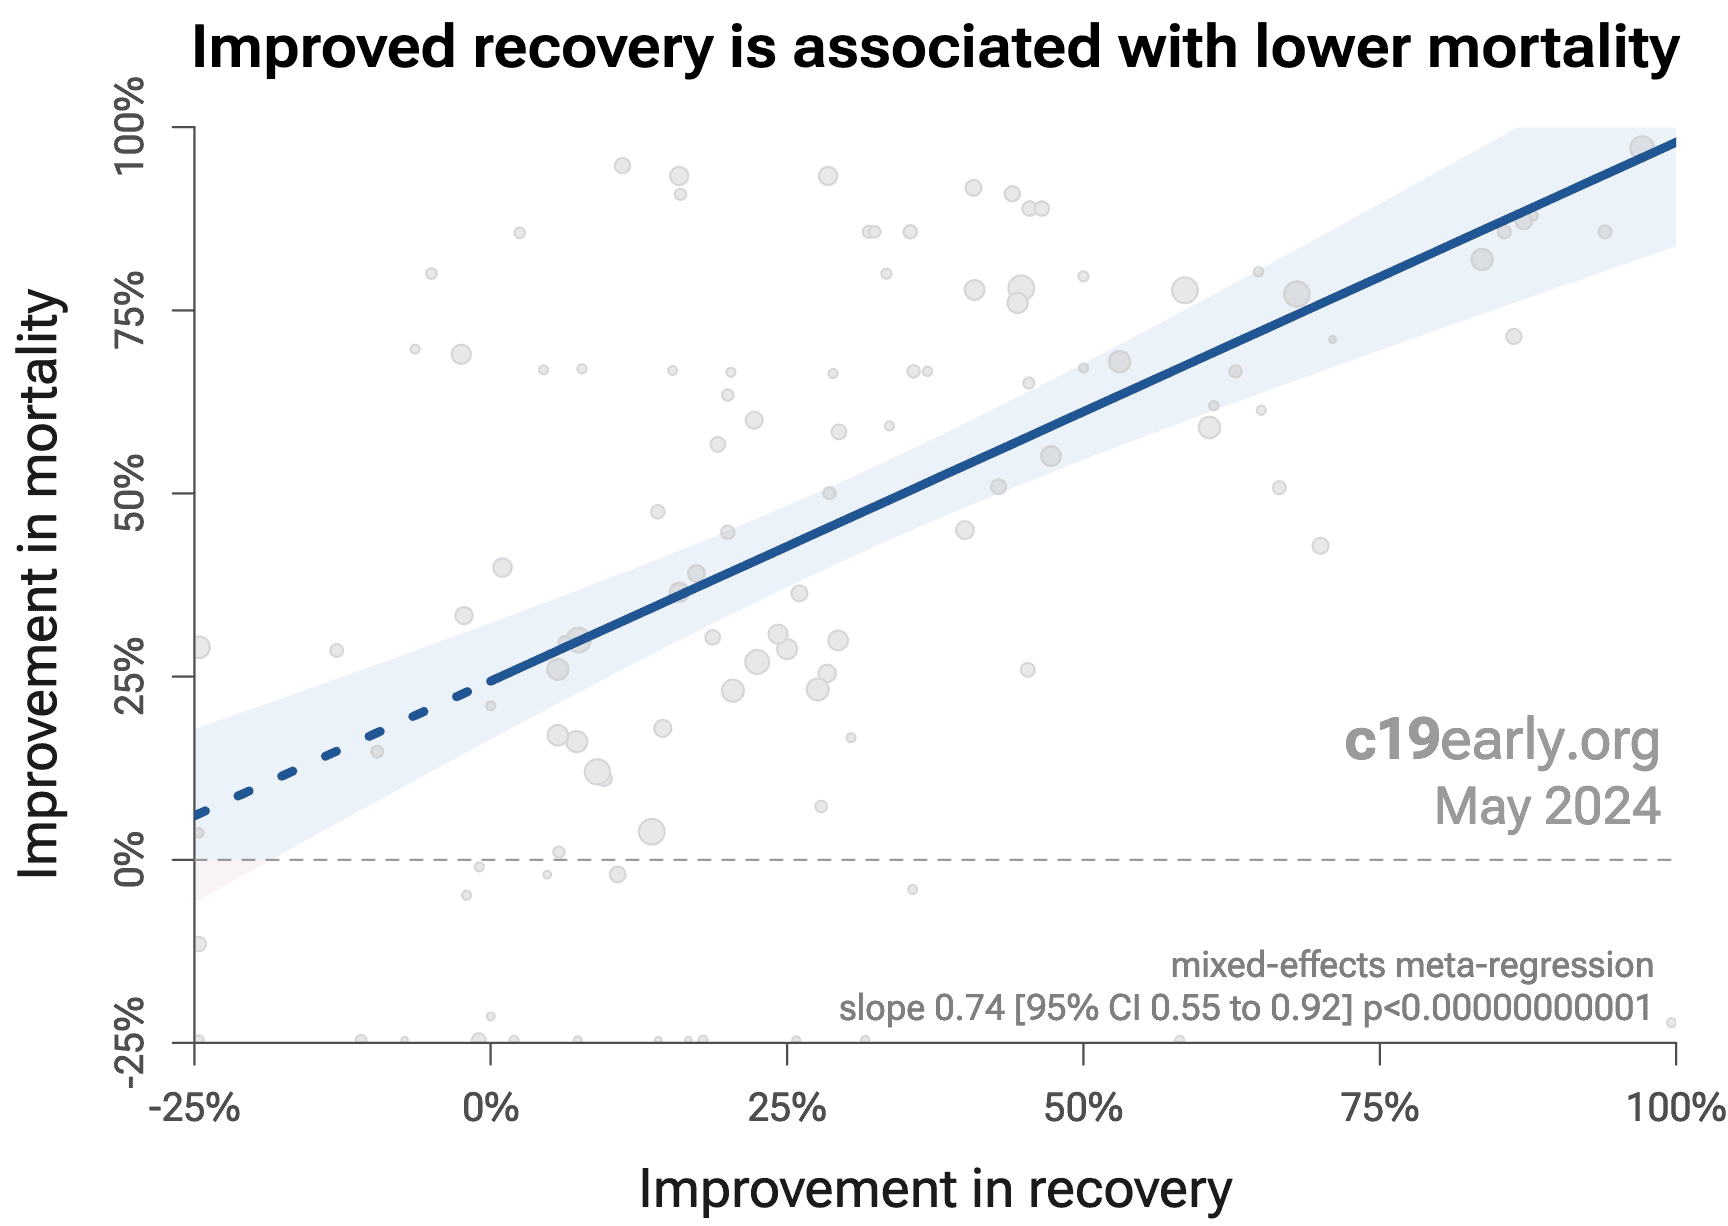
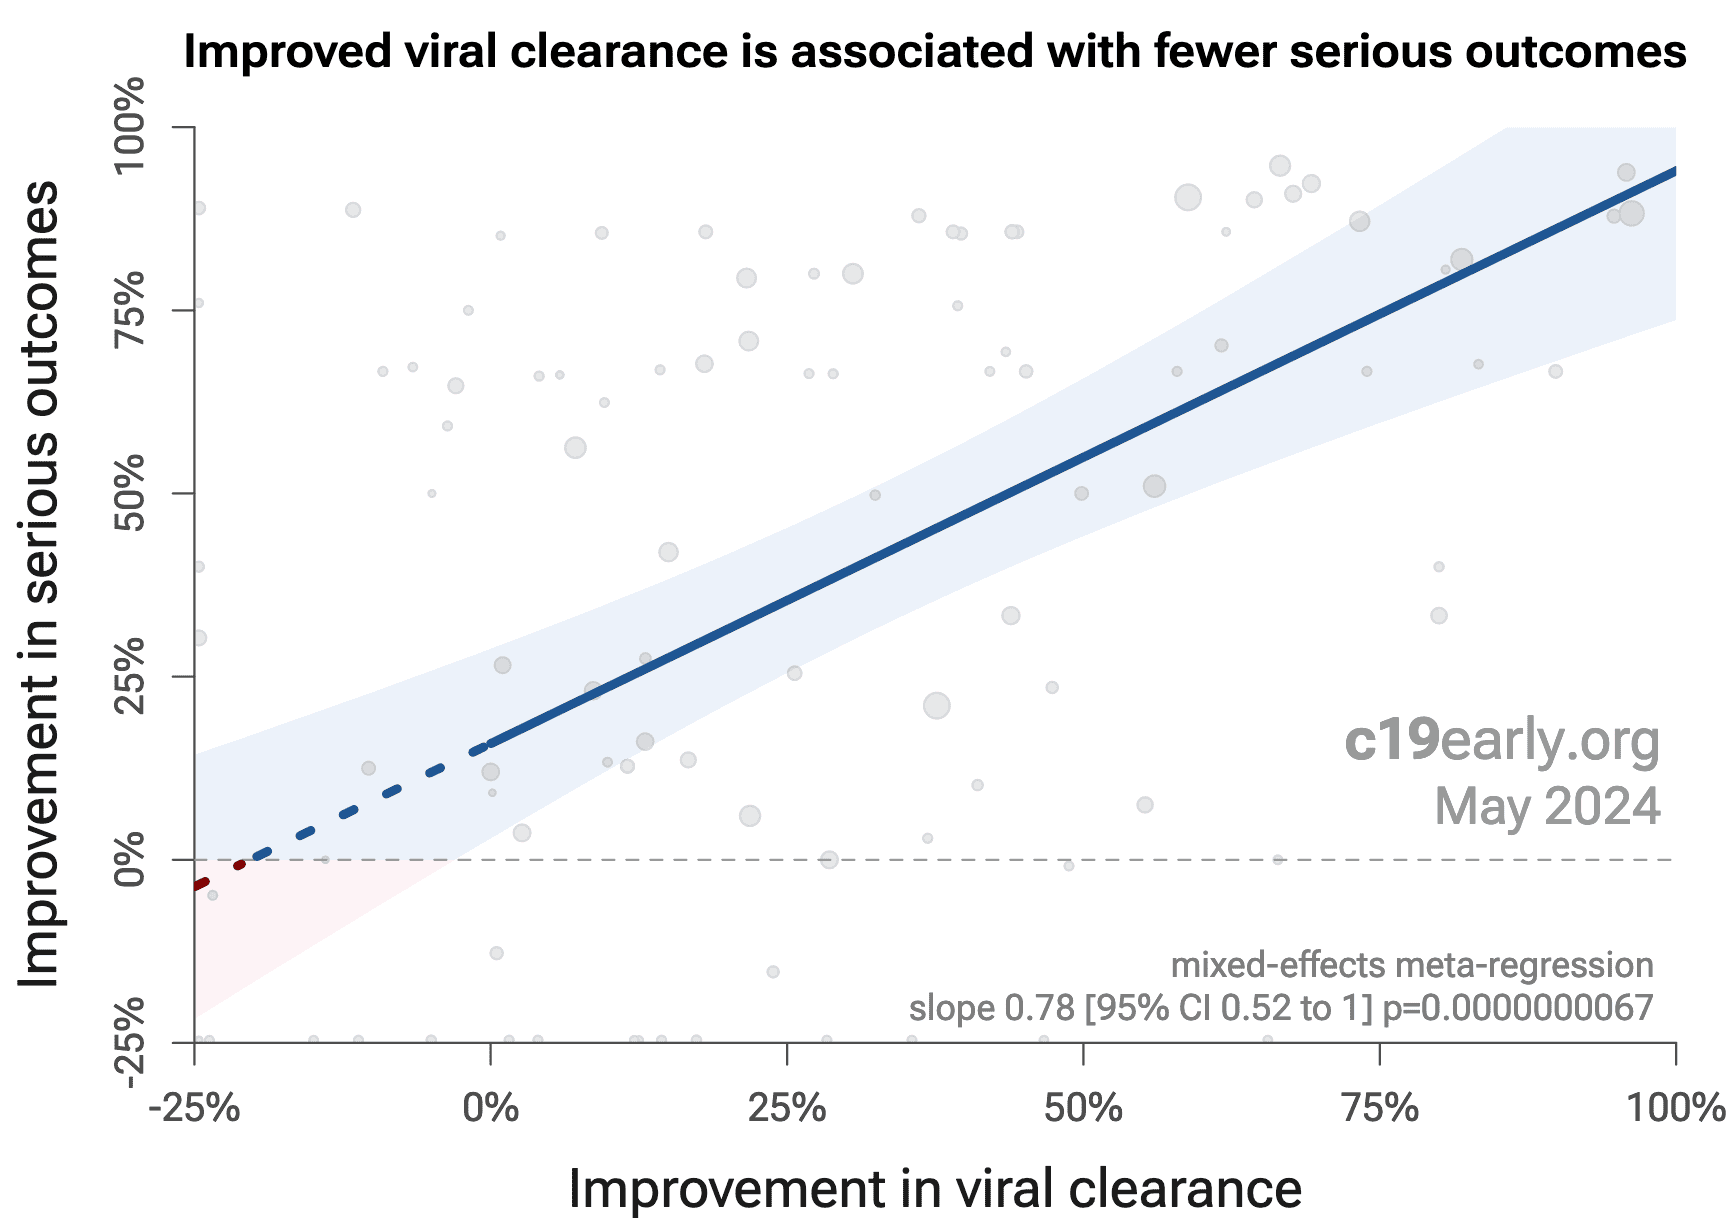
Analysis of the the association between different outcomes across studies from all 227 treatments we cover confirms the validity of pooled outcome analysis for COVID-19. Fig. 21 shows that lower hospitalization is very strongly associated with lower mortality (p < 0.0000000001). Similarly, Fig. 22 shows that improved recovery is very strongly associated with lower mortality (p < 0.0000000001). Considering the extremes, Singh et al. show an association between viral clearance and hospitalization or death, with p = 0.003 after excluding one large outlier from a mutagenic treatment, and based on 44 RCTs including 52,384 patients. Fig. 23 shows that improved viral clearance is strongly associated with fewer serious outcomes. The association is very similar to Singh et al., with higher confidence due to the larger number of studies. As with Singh et al., the confidence increases when excluding the outlier treatment, from p = 0.0000000074 to p = 0.00000000015.
Loading..
Fig. 21. Lower hospitalization is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 22. Improved recovery is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 21. Improved viral clearance is associated with fewer serious outcomes, supporting pooled outcome analysis.
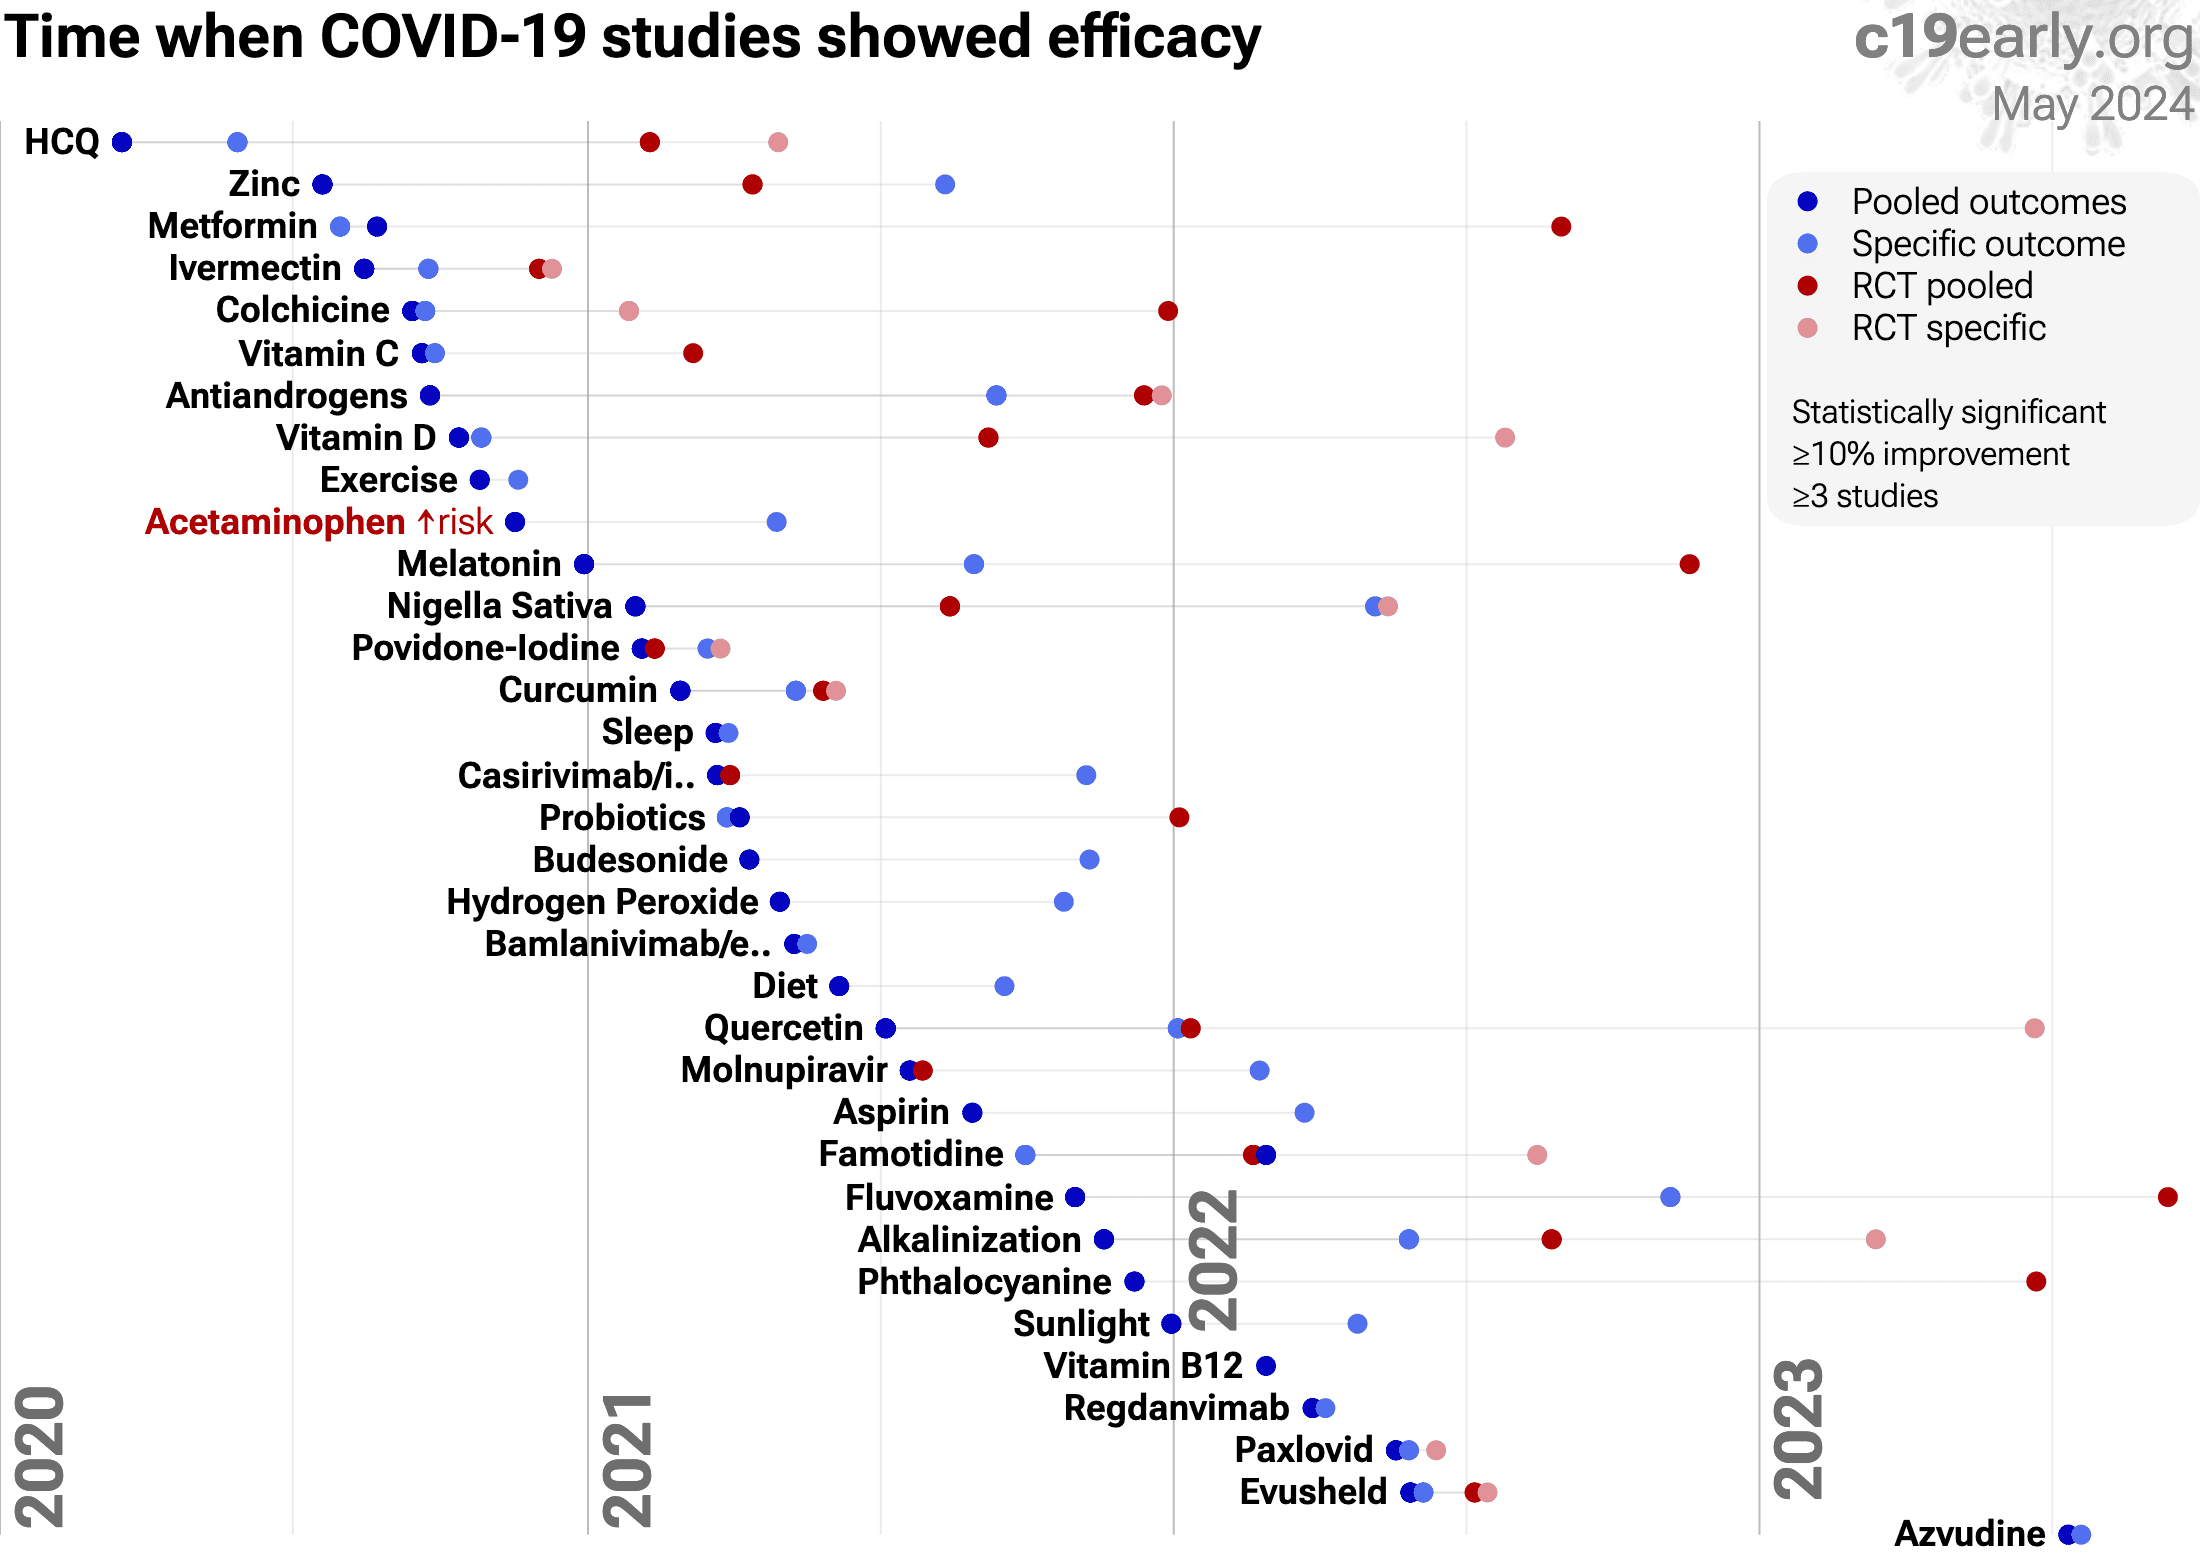
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. 85% of these have been confirmed with one or more specific outcomes, with a mean delay of 4.6 months. When restricting to RCTs only, 53% of treatments showing statistically significant efficacy/harm with pooled effects have been confirmed with one or more specific outcomes, with a mean delay of 7.5 months. Fig. 24 shows when treatments were found effective during the pandemic. Pooled outcomes often resulted in earlier detection of efficacy.
Loading..
Loading..
Fig. 24. The time when studies showed that treatments were effective, defined as statistically significant improvement of ≥10% from ≥3 studies. Pooled results typically show efficacy earlier than specific outcome results. Results from all studies often shows efficacy much earlier than when restricting to RCTs. Results reflect conditions as used in trials to date, these depend on the population treated, treatment delay, and treatment regimen.
Pooled analysis could hide efficacy, for example a treatment that is beneficial for late stage patients but has no effect on viral clearance may show no efficacy if most studies only examine viral clearance. In practice, it is rare for a non-antiviral treatment to report viral clearance and to not report clinical outcomes; and in practice other sources of heterogeneity such as differences in treatment delay are more likely to hide efficacy.
Analysis validates the use of pooled effects and shows significantly faster detection of efficacy on average. However, as with all meta-analyses, it is important to review the different studies included. We also present individual outcome analyses, which may be more informative for specific use cases.
Publishing is often biased towards positive results. Trials with patented drugs may have a financial conflict of interest that results in positive studies being more likely to be published, or bias towards more positive results. For example with molnupiravir, trials with negative results remain unpublished to date (CTRI/2021/05/033864 and CTRI/2021/08/0354242). For convalescent plasma, there is currently not enough data to evaluate publication bias with high confidence.
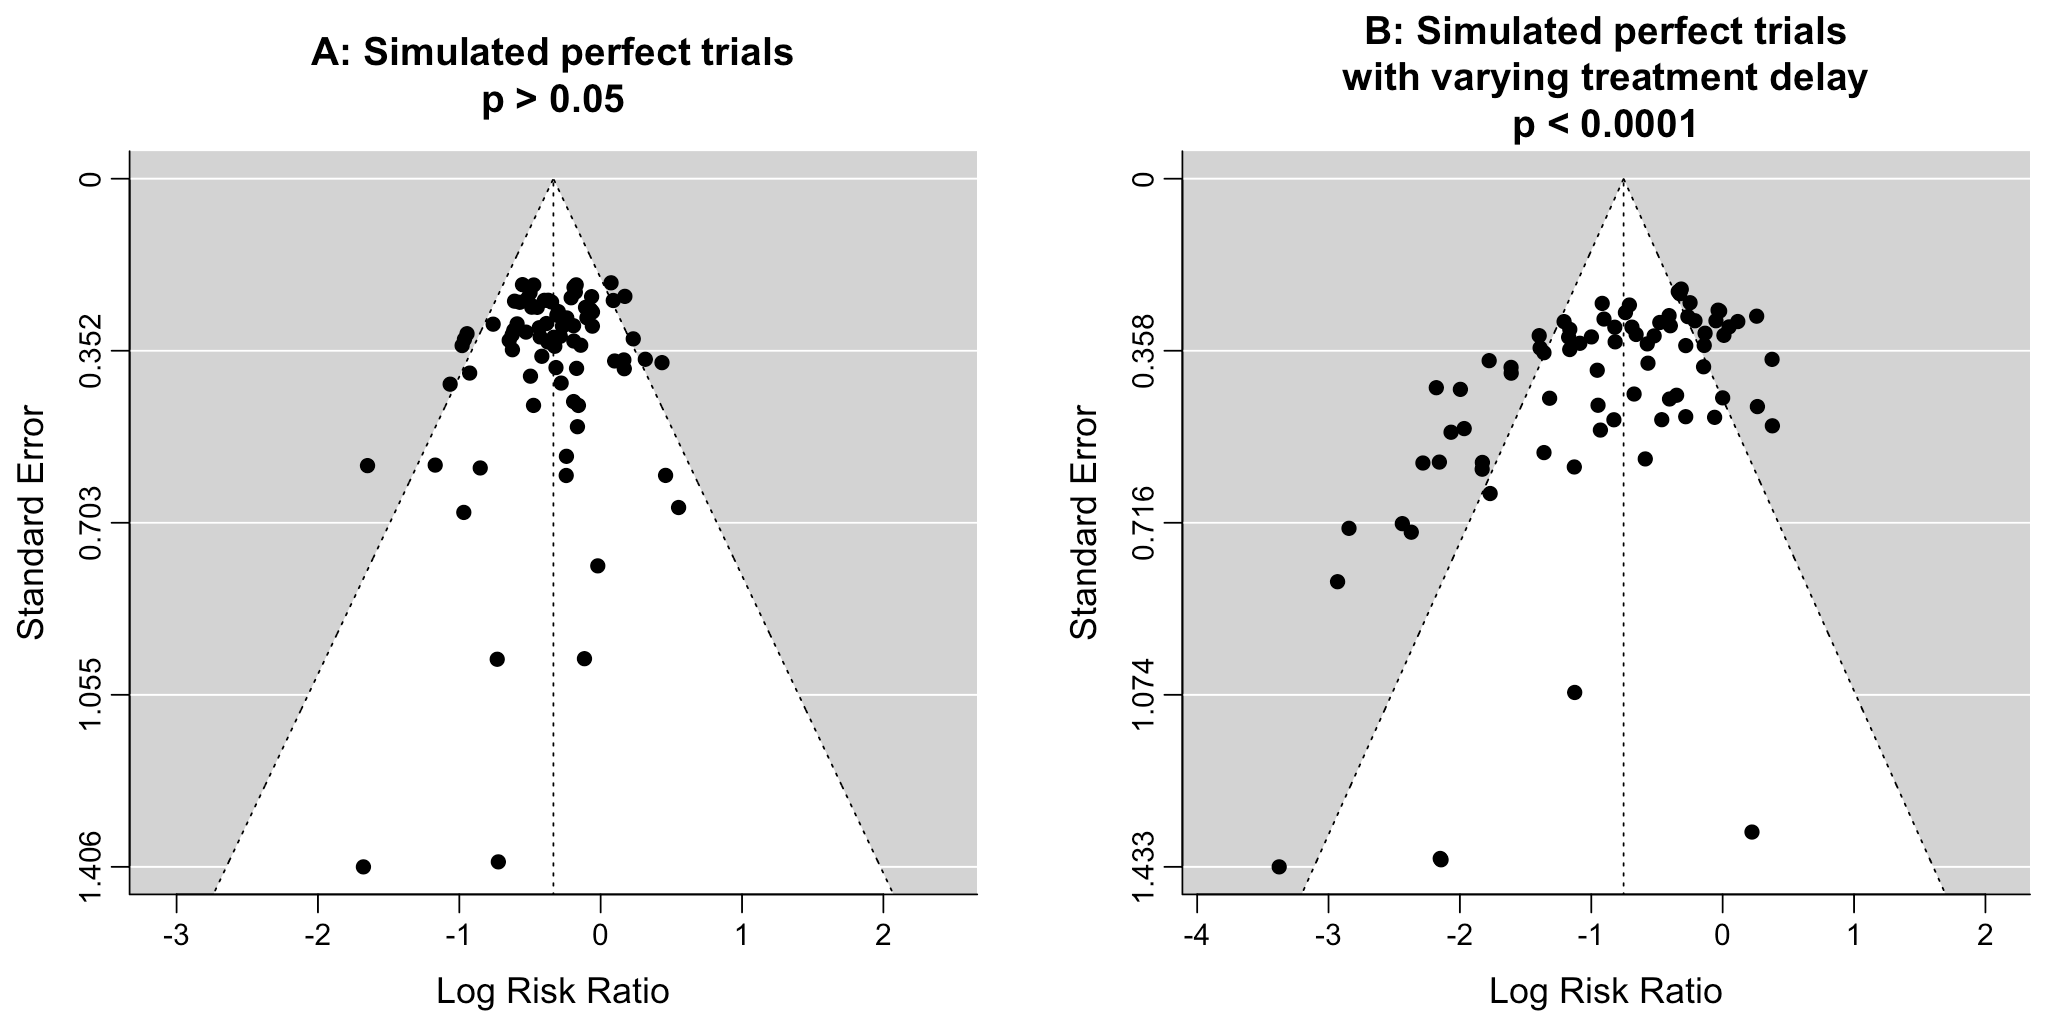
Funnel plots have traditionally been used for analyzing publication bias. This is invalid for COVID-19 acute treatment trials — the underlying assumptions are invalid, which we can demonstrate with a simple example. Consider a set of hypothetical perfect trials with no bias. Fig. 25 plot A shows a funnel plot for a simulation of 80 perfect trials, with random group sizes, and each patient's outcome randomly sampled (10% control event probability, and a 30% effect size for treatment). Analysis shows no asymmetry (p > 0.05). In plot B, we add a single typical variation in COVID-19 treatment trials — treatment delay. Consider that efficacy varies from 90% for treatment within 24 hours, reducing to 10% when treatment is delayed 3 days. In plot B, each trial's treatment delay is randomly selected. Analysis now shows highly significant asymmetry, p < 0.0001, with six variants of Egger's test all showing p < 0.05118-125. Note that these tests fail even though treatment delay is uniformly distributed. In reality treatment delay is more complex — each trial has a different distribution of delays across patients, and the distribution across trials may be biased (e.g., late treatment trials may be more common). Similarly, many other variations in trials may produce asymmetry, including dose, administration, duration of treatment, differences in SOC, comorbidities, age, variants, and bias in design, implementation, analysis, and reporting.
Log Risk Ratio Standard Error 1.406 1.055 0.703 0.352 0 -3 -2 -1 0 1 2 A: Simulated perfect trials p > 0.05 Log Risk Ratio Standard Error 1.433 1.074 0.716 0.358 0 -4 -3 -2 -1 0 1 2 B: Simulated perfect trials with varying treatment delay p < 0.0001
Fig. 25. Example funnel plot analysis for simulated perfect trials.
Summary statistics from meta-analysis necessarily lose information. As with all meta-analyses, studies are heterogeneous, with differences in treatment delay, treatment regimen, patient demographics, variants, conflicts of interest, standard of care, and other factors. We provide analyses for specific outcomes and by treatment delay, and we aim to identify key characteristics in the forest plots and summaries. Results should be viewed in the context of study characteristics.
Some analyses classify treatment based on early or late administration, as done here, while others distinguish between mild, moderate, and severe cases. Viral load does not indicate degree of symptoms — for example patients may have a high viral load while being asymptomatic. With regard to treatments that have antiviral properties, timing of treatment is critical — late administration may be less helpful regardless of severity.
Details of treatment delay per patient is often not available. For example, a study may treat 90% of patients relatively early, but the events driving the outcome may come from 10% of patients treated very late. Our 5 day cutoff for early treatment may be too conservative, 5 days may be too late in many cases.
Comparison across treatments is confounded by differences in the studies performed, for example dose, variants, and conflicts of interest. Trials with conflicts of interest may use designs better suited to the preferred outcome.
In some cases, the most serious outcome has very few events, resulting in lower confidence results being used in pooled analysis, however the method is simpler and more transparent. This is less critical as the number of studies increases. Restriction to outcomes with sufficient power may be beneficial in pooled analysis and improve accuracy when there are few studies, however we maintain our pre-specified method to avoid any retrospective changes.
Studies show that combinations of treatments can be highly synergistic and may result in many times greater efficacy than individual treatments alone92-116. Therefore standard of care may be critical and benefits may diminish or disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on submissions. Accuracy benefits from widespread review and submission of updates and corrections from reviewers. Less popular treatments may receive fewer reviews.
No treatment or intervention is 100% available and effective for all current and future variants. Efficacy may vary significantly with different variants and within different populations. All treatments have potential side effects. Propensity to experience side effects may be predicted in advance by qualified physicians. We do not provide medical advice. Before taking any medication, consult a qualified physician who can compare all options, provide personalized advice, and provide details of risks and benefits based on individual medical history and situations.
1 of the 58 studies compare against other treatments, which may reduce the effect seen.
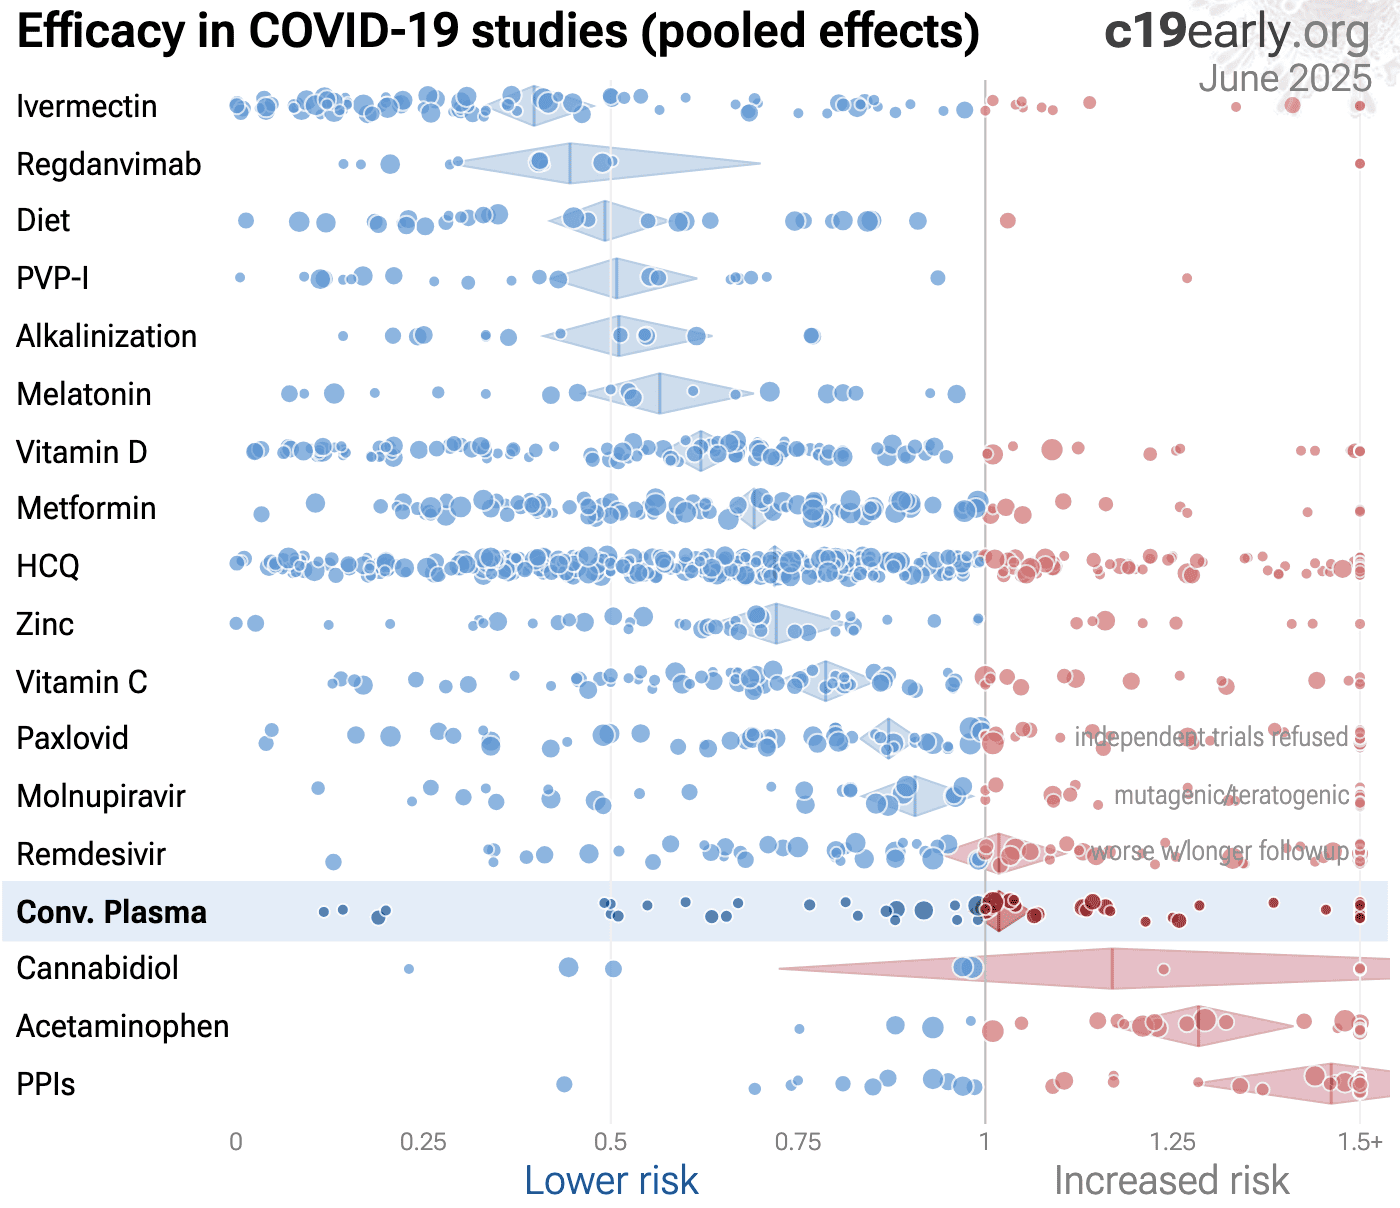
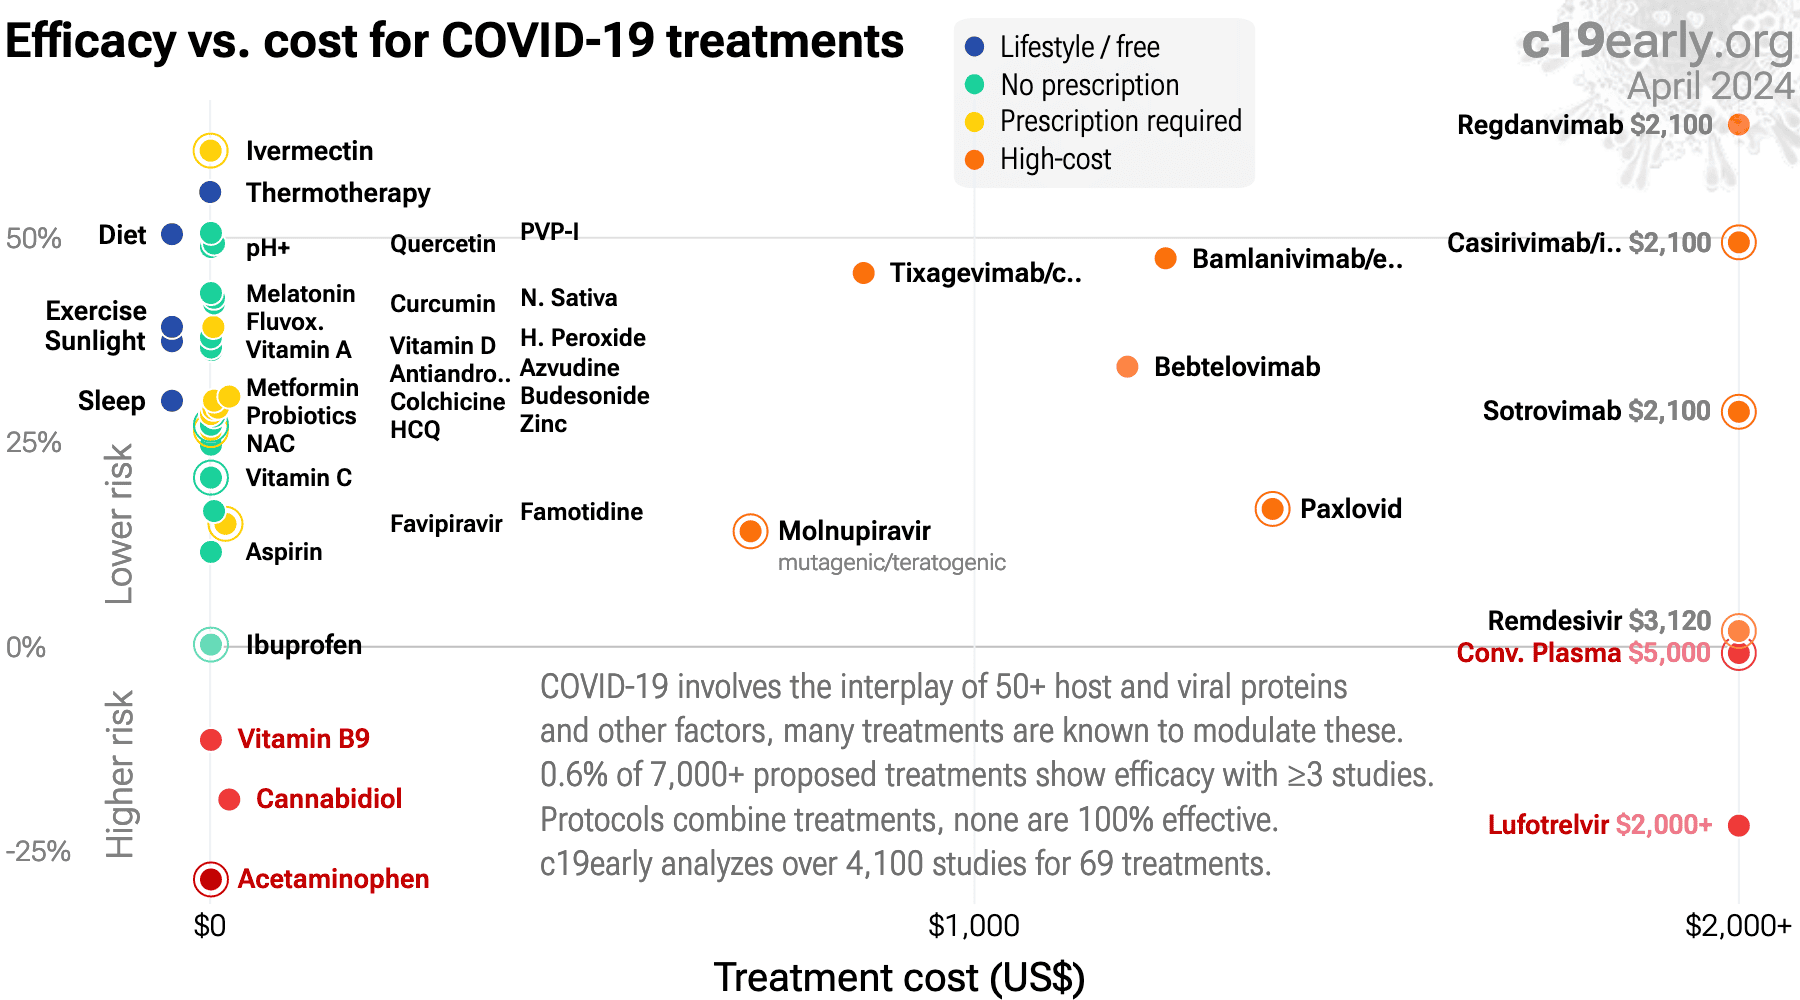
SARS-CoV-2 infection and replication involves a complex interplay of 500+ host and viral proteins and other factors31-38, providing many therapeutic targets. Over 12,000 compounds have been predicted to reduce COVID-19 risk39, either by directly minimizing infection or replication, by supporting immune system function, or by minimizing secondary complications. Fig. 26 shows an overview of the results for convalescent plasma in the context of multiple COVID-19 treatments, and Fig. 27 shows a plot of efficacy vs. cost for COVID-19 treatments.
Loading..
Fig. 26. Scatter plot showing results within the context of multiple COVID-19 treatments. Diamonds shows the results of random-effects meta-analysis. 0.5% of 12,000+ proposed treatments show efficacy126.
Loading..
Loading..
Fig. 27. Efficacy vs. cost for COVID-19 treatments.
Meta-analysis using the most serious outcome reported shows 2% [-2‑6%] higher risk, without reaching statistical significance.
 
Contact.
Contact us on X at @CovidAnalysis.
Funding.
We have received no funding or compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
AI.
We use AI models (Gemini, Grok, Claude, and ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.
Updates.
Our COVID-19 meta-analyses involve the extraction of over 228,000 datapoints from thousands of papers for 227 treatments. We thank the thousands of scientists, physicians, and other contributors that have provided updates, suggestions, feedback, and corrections. These are all welcome and can be submitted at https://c19early.org/cpmeta.html.
Dedication.
This work is dedicated to top evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce mortality and morbidity during the pandemic. In alphabetical order: Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty, Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr. Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch, Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work distributed in accordance with the Creative Commons CC0 1.0 Universal license, which dedicates the work to the public domain by waiving all rights worldwide under copyright law. You can distribute, remix, adapt, and build upon this work in any medium or format, including for commercial purposes, without asking permission. Referenced material and third-party images retain any original copyrights or restrictions. See: https://creativecommons.org/publicdomain/zero/1.0/.
RCT 22 hospitalized patients, show no significant difference in mortality with convalescent plasma. Results are from Axfors et al.. Submit Corrections or Updates.
Late treatmentRCT · 464 patients · India · Apr – Jul 2020
Conv. Plasma for COVID-19
Improved viral clearance with convalescent plasma
p = 0.02
RCT 464 hospitalized patients in India, 235 treated with convalescent plasma, showing no improvement in combined death at 28 days or progression to severe disease. Submit Corrections or Updates.
Early treatmentRCT · 376 patients · Spain · Nov 2020 – Jul 2021
Conv. Plasma for COVID-19
Lower mortality with convalescent plasma
Not statistically significant · p = 0.5
RCT 188 convalescent plasma and 188 control patients, showing no significant difference in outcomes. Submit Corrections or Updates.
Late treatmentRCT · NCT04356534 · 40 patients · Bahrain · Apr – Jul 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and ventilation
Not statistically significant · p = 0.55 (mortality) and p = 0.47 (ventilation)
Small RCT with 40 hospitalized patients in Bahrain, 20 treated with convalescent plasma, not showing significant differences. Submit Corrections or Updates.
Late treatmentPSM retrospective · 246 patients · Mar 2020 – Jan 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Longer ICU admission and hospitalization
p = 0.003 (ICU admission) and p = 0.01 (hospitalization)
PSM retrospective 29 hospitals in Saudi Arabia, showing longer ICU and hospitalization time with convalescent plasma, but no significant difference in mortality. Submit Corrections or Updates.
Late treatmentRCT · NCT04345523 · 81 patients · Spain · Apr – Jul 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower progression with convalescent plasma
p = 0.013
Early terminated RCT with 81 hospitalized patients, 38 treated with convalescent plasma, showing lower progression with treatment. Submit Corrections or Updates.
60 patient convalescent plasma late treatment RCT with results not reported over 6 years after completion. Submit Corrections or Updates.
Late treatmentRCT · NCT04425915 · 400 patients · India · Jun – Dec 2020
Conv. Plasma for COVID-19
RCT 400 hospitalized severe COVID-19 patients in India showing no significant difference in time to clinical improvement, mortality, or other outcomes with convalescent plasma compared to standard treatment. In a subgroup analysis, results were better for patients receiving plasma within 3 days of admission. There was no difference in outcomes based on patient baseline antibody levels. Submit Corrections or Updates.
Late treatmentRCT · NCT04346446 · 29 patients · India
Conv. Plasma for COVID-19
Higher mortality and ventilation
Not statistically significant · p = 0.22 (mortality) and p = 0.33 (ventilation)
RCT 29 severe COVID-19 patients showing no significant differences with convalescent plasma compared to fresh frozen plasma. Submit Corrections or Updates.
Late treatmentRCT · 1,070 patients · USA · Jun 2020 – Oct 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
No significant difference in outcomes seen
RCT 1,070 outpatients in the USA, showing no significant difference in recovery with convalescent plasma treatment. Long COVID results are from Gebo et al. Submit Corrections or Updates.
Early treatmentRCT · NCT04375098 · 58 patients · Chile · May – Jul 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality and ventilation
Not statistically significant · p = 0.17 (mortality) and p = 0.22 (ventilation)
Small RCT with 28 early and 30 deferred (treated according to prespecified deterioration criteria) convalescent plasma patients, not showing significant differences. "Early" is relative, with a median of 5 days from symptom onset. 13 patients in the deferred group received plasma. Submit Corrections or Updates.
RCT 158 patients in Ecuador, showing no significant difference in mortality with convalescent plasma. Authors note indications of improved results for earlier treatment. Submit Corrections or Updates.
Late treatmentRCT · NCT04397757 · 79 patients · USA · May 2020 – Jan 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality with convalescent plasma
p = 0.029
RCT 79 hospitalized patients in the USA, showing significant benefit in clinical severity score and 28-day mortality with convalescent plasma treatment. Submit Corrections or Updates.
Estimated 115 patient convalescent plasma late treatment RCT with results not reported over 3 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · NCT04344535 · 74 patients · USA · Apr 2020 – Feb 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Trial underpowered for serious outcomes
RCT 74 hospitalized patients in the USA, showing no significant difference with convalescent plasma treatment. Submit Corrections or Updates.
Late treatmentRCT · 938 patients · multinational · May 2020 – Jan 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher death/intubation with treatment
Not statistically significant · p = 0.18
RCT 940 hospitalized patients, 614 assigned to convalescent plasma, showing no significant differences. Submit Corrections or Updates.
31 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
ProphylaxisRCT · 72 patients · China · Jun 2023 – Feb 2024
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality with convalescent plasma
p = 0.044
RCT 72 hematopoietic stem cell transplantation (HSCT) recipients, showing higher one-year mortality with COVID-19 convalescent plasma prophylaxis treatment. Submit Corrections or Updates.
72 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
Target trial emulation with 4,755 patients showing no significant difference in 30-day mortality with convalescent plasma. Submit Corrections or Updates.
Estimated 60 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
93 patient convalescent plasma late treatment RCT with results not reported over 4 years after completion. Submit Corrections or Updates.
RCT 110 hospitalized patients in Brazil, showing no significant difference in outcomes with high-dose convalescent plasma. Submit Corrections or Updates.
Late treatmentRCT · 134 patients · Germany · Sep 2020 – Jan 2022
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Improved 7-point scale results with treatment
Not statistically significant · p = 0.22
RCT 134 hospitalized patients showing no significant difference in outcomes with convalescent plasma for all patients, however significantly improved mortality and time to improvement was seen for patients with cancer. Submit Corrections or Updates.
Late treatmentRCT · 483 patients · Belgium · May 2020 – Jan 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
No significant difference in outcomes seen
RCT 489 hospitalized COVID-19 patients in Belgium, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
59 patient convalescent plasma late treatment RCT with results not reported over 4 years after completion. Submit Corrections or Updates.
Estimated 67 patient convalescent plasma late treatment RCT with results not reported over 4 years after estimated completion. Submit Corrections or Updates.
Prospective study of 465 COVID-19 ICU patients in Libya showing no significant differences with treatment. Submit Corrections or Updates.
61 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
Late treatmentRCT · 44 patients · Philippines · Sep 2020 – May 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality with convalescent plasma
Not statistically significant · p = 0.49
Early terminated RCT 44 hospitalized COVID-19 patients showing no significant differences with convalescent plasma treatment. Submit Corrections or Updates.
Early treatmentRCT · 416 patients · Netherlands · Nov 2020 – Jul 2021
Conv. Plasma for COVID-19
Lower progression and hospitalization
Not statistically significant · p = 0.42 (progression) and p = 0.22 (hospitalization)
RCT 416 outpatients in the Netherlands, showing no significant difference with convalesent plasma treatment. Hospitalization was lower, and improved results were seen with ≤5 days of symptoms, without statistical significance. Submit Corrections or Updates.
RCT 86 hospitalized patients, 43 treated with convalescent plasma, showing no significant differences with treatment. Authors conclude that the most likely explanation was already high antibody titers on the day of inclusion, and they recommend treating patients early. Submit Corrections or Updates.
134 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
Late treatmentRetrospective · 190 patients · Mexico · May – Oct 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
No significant difference in mortality
Study compares with IVIg, results vs. placebo may differ
RCT 190 hospitalized severe condition patients in Mexico, showing no significant difference between convalescent plasma and human immunoglobulin treatment. Submit Corrections or Updates.
Estimated 50 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
Long-term followup for the REMAP-CAP very late stage ICU trial, showing no significant difference with convalescent plasma treatment. Submit Corrections or Updates.
Early treatmentRCT · 117 patients · multinational · Apr 2022 – Nov 2023
Conv. Plasma for COVID-19
Lower death/hosp. with convalescent plasma
p = 0.027
RCT 117 immunocompromised patients with mild COVID-19 showing lower hospitalization or death with early administration of very high-titre COVID-19 convalescent plasma (CCP). The trial was terminated early due to declining enrollment. Submit Corrections or Updates.
Late treatmentRCT · 31 patients · Sweden · Jun 2020 – Jan 2021
Conv. Plasma for COVID-19
Lower ventilation and higher oxygen therapy
Not statistically significant · p = 0.45 (ventilation) and p = 0.43 (oxygen)
RCT 31 hospitalized patients requiring supplemental oxygen in Sweden, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
Late treatmentRCT · NCT04381936 · 11,558 patients · UK
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
No significant difference in outcomes seen
RCT 16,287 hospitalized patients in the UK, showing no significant differences with convalescent plasma treatment. Subgroup analysis shows better results for those treated ≤7 days from symptom onset. 6-month results are from Horby et al. Submit Corrections or Updates.
Late treatmentRCT · NCT04421404 · 34 patients · USA · Jun 2020 – Apr 2021
Conv. Plasma for COVID-19
Higher mortality and ventilation
Not statistically significant · p = 0.47 (mortality) and p = 0.21 (ventilation)
RCT 34 hospitalized patients in the USA, showing no significant difference with convalescent plasma treatment. Submit Corrections or Updates.
Late treatmentPSM retrospective · 580 patients · USA · Mar 2020 – Jun 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality with convalescent plasma
Not statistically significant · p = 0.14
Retrospective propensity-matched analysis of 290 hospitalized COVID-19 patients who received convalescent plasma (CCP) compared to 290 controls, showing no significant difference in 30-day mortality, ECMO/mechanical ventilation, or hospital length of stay. Submit Corrections or Updates.
38 patient convalescent plasma late treatment RCT with results not reported over 4 years after completion. Submit Corrections or Updates.
Late treatmentRCT · 120 patients · Iran · May – Jul 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality and ARDS
Not statistically significant · p = 0.38 (mortality) and p = 0.16 (ARDS)
RCT 120 hospitalized patients in Iran, showing no significant differences with convalescent plasma treatment. Submit Corrections or Updates.
Estimated 364 patient convalescent plasma late treatment RCT with results not reported over 4 years after estimated completion. Submit Corrections or Updates.
Late treatmentRetrospective · 50 patients · USA · Sep 2020 – Feb 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
Study underpowered to detect differences
Retrospective 144 immunocompromised patients treated with anti-CD20 therapy prior to contracting COVID-19. Among 50 patients hospitalized within 14 days, administration of high-titer convalescent plasma in the first 14 days was not associated with improved outcomes. Submit Corrections or Updates.
45 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
22 patient convalescent plasma early treatment RCT with results not reported over 4 years after completion. Submit Corrections or Updates.
Late treatmentRCT · 57 patients · Finland · Feb 2021 – Jan 2022
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Trial underpowered to detect differences
RCT 57 hospitalized COVID-19 patients showing no significant difference in outcomes with convalescent plasma treatment. Submit Corrections or Updates.
Late treatmentRCT · NCT04542941 · 136 patients · Uganda · Jun – Dec 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Slower viral clearance with treatment
Not statistically significant · p = 0.2
RCT 136 hospitalized COVID-19 patients in Uganda, showing no significant benefit with convalescent plasma treatment. Submit Corrections or Updates.
Early treatmentRCT · 511 patients · USA · Aug 2020 – Feb 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality with convalescent plasma
Not statistically significant · p = 0.22
RCT 511 emergency department patients, 257 assigned to convalescent plasma, showing no significant difference in outcomes. Submit Corrections or Updates.
Case control study with 2,431 hospitalized COVID-19 patients in India, showing higher mortality with convalescent plasma treatment, without statistical significance. Submit Corrections or Updates.
Late treatmentRCT · 105 patients · Germany · Aug – Dec 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and improved recovery
Not statistically significant · p = 0.19 (mortality) and p = 0.32 (recovery)
RCT 105 hospitalized patients in Germany, 53 treated with convalescent plasma, showing no significant difference in mortality or the primary composite outcome of survival and no longer fulfilling criteria for severe COVID-19 on day 21. Submit Corrections or Updates.
Late treatmentRCT · 120 patients · France · Apr 2020 – Apr 2021
Conv. Plasma for COVID-19
Lower mortality and higher progression
Not statistically significant · p = 0.16 (mortality) and p = 0.18 (progression)
RCT 120 hospitalized patients in France, showing no significant difference in outcomes with convalescent plasma treatment, with the exception of lower mortality in the subgroup of immunosuppressed patients. Submit Corrections or Updates.
Retrospective 430 hospitalized COVID-19 patients with type 2 diabetes in Poland showing lower mortality with metformin and higher mortality with remdesivir, convalescent plasma, and aspirin in univariable analysis. These results were not statistically significant except for aspirin, and no baseline information per treatment is provided to assess confounding. Submit Corrections or Updates.
Small RCT 103 severe condition patients, 52 treated with convalescent plasma, showing improved viral clearance but no statistically significant improvements in mortality or clinical improvement. ChiCTR2000029757. Submit Corrections or Updates.
Early treatmentRCT · 160 patients · Argentina · Jun – Oct 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower progression with convalescent plasma
p = 0.029
RCT 160 patients ≥65 with symptom onset <72 hours, 80 treated with convalescent plasma, showing lower progression to severe disease with treatment. Submit Corrections or Updates.
Estimated 60 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · 120 patients · Italy · Jun 2020 – Aug 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Higher mortality with convalescent plasma
Not statistically significant · p = 0.54
RCT 180 hospitalized COVID-19 patients with respiratory impairment in Italy showing no significant improvement in mortality or mechanical ventilation with either standard plasma or COVID-19 convalescent plasma compared to standard of care. Submit Corrections or Updates.
86 patient convalescent plasma late treatment study with results not reported over 3 years after completion. Submit Corrections or Updates.
18 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
Late treatmentRCT · NCT04716556 · 471 patients · Italy · Jul – Dec 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
primary
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
Lower mortality and progression
Not statistically significant · p = 0.47 (mortality) and p = 0.54 (progression)
RCT 487 patients in Italy, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
Late treatmentProspective · 130 patients · Philippines · Apr 2020 – Mar 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
Higher mortality and longer hospitalization
Not statistically significant · p = 0.54 (mortality) and p = 0.068 (hospitalization)
Prospective study of 65 hospitalized COVID-19 patients in the Philippines treated with convalescent plasma and 65 matched controls showing no significant difference in mortality and longer hospitalization with treatment. Submit Corrections or Updates.
Late treatmentRCT · 941 patients · USA · Apr 2020 – Mar 2021
Conv. Plasma for COVID-19
Lower mortality with convalescent plasma
Not statistically significant · p = 0.45
RCT 941 hospitalized patients in the USA, showing no significant difference with convalescent plasma treatment. PASC results are from Yoon et al. Submit Corrections or Updates.
100 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
Estimated 231 patient convalescent plasma late treatment RCT with results not reported over 4 years after estimated completion. Submit Corrections or Updates.
Estimated 220 patient convalescent plasma late treatment RCT with results not reported over 4 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · 60 patients · multinational · Mar – May 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
Longer hospitalization with treatment
Not statistically significant · p = 0.06
RCT 62 hospitalized patients in Iran, showing no significant difference in mortality and length of stay with convalescent plasma. Submit Corrections or Updates.
Estimated 236 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
RCT 80 severe COVID-19 patients in India showing no significant difference in 30-day mortality with convalescent plasma therapy (CPT). Patients receiving CPT had greater reduction in inflammatory cytokines, but this did not translate to clinical benefit in terms of survival or duration of hospital stay. Submit Corrections or Updates.
Estimated 60 patient convalescent plasma late treatment RCT with results not reported over 4 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · NCT04332835 · 91 patients · Colombia · Aug – Nov 2020
Conv. Plasma for COVID-19
Higher discharge with convalescent plasma
p = 0.038
RCT 91 hospitalized patients in Colombia showing shorter time to discharge with convalescent plasma, but higher mortality (without statistical significance). Submit Corrections or Updates.
Estimated 58 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · NCT04547660 · 160 patients · Brazil · Jul – Dec 2020
Conv. Plasma for COVID-19
Higher mortality with convalescent plasma
Not statistically significant · p = 0.42
RCT 160 hospitalized patients in Brazil, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
Late treatmentRCT · 960 patients · USA · Apr 2020 – Jun 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
No significant difference in outcomes seen
RCT 947 hospitalized patients in the USA, showing no signficant difference with convalescent plasma treatment. Submit Corrections or Updates.
60 patient convalescent plasma late treatment RCT with results not reported over 6 years after completion. Submit Corrections or Updates.
RCT 60 severe COVID-19 patients showing no benefit with convalescent plasma. Submit Corrections or Updates.
Estimated 410 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
Late treatmentRCT · 333 patients · Argentina · May – Aug 2020
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Convalescent
Plasma reduces risk
Increased risk →
Improved 7-point scale results with treatment
Not statistically significant · p = 0.4
RCT 333 hospitalized patients in Argentina, 228 treated with convalescent plasma, showing no significant differences in clinical status or mortality. Submit Corrections or Updates.
RCT 129 severe COVID-19 patients in Brazil, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
Late treatmentRCT · 1,181 patients · USA · Jun 2020 – Oct 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower hospitalization with convalescent plasma
p = 0.0052
RCT 1,181 outpatients in the USA, mean 6 days from symptom onset, showing lower hospitalization with treatment. Submit Corrections or Updates.
Estimated 400 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
RCT 12 patients in Italy, showing no significant difference with convalescent plasma treatment. Results are from Axfors et al.. Submit Corrections or Updates.
Late treatmentRCT · 144 patients · Denmark · Jun 2020 – Mar 2021
Conv. Plasma for COVID-19
Higher mortality and worse 7-point scale results
Not statistically significant · p = 0.43 (mortality) and p = 0.32 (7-point scale results)
RCT 147 patients in Denmark, showing no significant difference in outcomes with convalescent plasma. The trial was terminated due to futility. Submit Corrections or Updates.
200 patient convalescent plasma late treatment RCT with results not reported over 5 years after completion. Submit Corrections or Updates.
150 patient convalescent plasma late treatment RCT with results not reported over 6 years after completion. Submit Corrections or Updates.
Late treatmentRCT · 103 patients · South Africa · Sep 2020 – Jan 2021
Conv. Plasma for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower ventilation with convalescent plasma
Not statistically significant · p = 0.36
RCT 103 hospitalized patients in South Africa, showing no significant difference in outcomes with convalescent plasma. Submit Corrections or Updates.
RCT 72 outpatients in the USA showing no significant difference with convalescent plasma treatment. Submit Corrections or Updates.
Estimated 60 patient convalescent plasma late treatment RCT with results not reported over 5 years after estimated completion. Submit Corrections or Updates.
We perform ongoing searches of PubMed, medRxiv, Europe PMC, ClinicalTrials.gov, The Cochrane Library, Google Scholar, Research Square, ScienceDirect, Oxford University Press, the reference lists of other studies and meta-analyses, and submissions to the site c19early.org, which regularly receives notification of studies upon publication. Search terms are convalescent plasma and COVID-19 or SARS-CoV-2. Automated searches are performed twice daily, with all matches reviewed for inclusion. All studies regarding the use of convalescent plasma for COVID-19 that report a comparison with a control group are included in the main analysis. Studies with major unexplained data issues, for example major outcome data that is impossible to be correct with no response from the authors, are excluded.
Fig. 28. Mid-recovery results can more accurately reflect efficacy when almost all patients recover. Mateja et al. confirm that intermediate viral load results more accurately reflect hospitalization/death.
We extracted effect sizes and associated data from all studies. If studies report multiple kinds of effects then the most serious outcome is used in pooled analysis, while other outcomes are included in the outcome-specific analyses. For example, if effects for mortality and cases are reported then they are both used in specific outcome analyses, while mortality is used for pooled analysis. If symptomatic results are reported at multiple times, we use the latest time, for example if mortality results are provided at 14 days and 28 days, the results at 28 days have preference. Mortality alone is preferred over combined outcomes. Outcomes with zero events in both arms are not used, the next most serious outcome with one or more events is used. For example, in low-risk populations with no mortality, a reduction in mortality with treatment is not possible, however a reduction in hospitalization, for example, is still valuable. Clinical outcomes are considered more important than viral outcomes. When basically all patients recover in both treatment and control groups, preference for viral clearance and recovery is given to results mid-recovery where available. After most or all patients have recovered there is little or no room for an effective treatment to do better, however faster recovery is valuable. An IPD meta-analysis confirms that intermediate viral load reduction is more closely associated with hospitalization/death than later viral load reduction131. If only individual symptom data is available, the most serious symptom has priority, for example difficulty breathing or low SpO2 is more important than cough.
Forest plots are computed using PythonMeta132 with the DerSimonian and Laird random-effects model (the fixed effect assumption is not plausible in this case) and inverse variance weighting. Results are presented with 95% confidence intervals. Heterogeneity among studies was assessed using the I2 statistic. When results provide an odds ratio, we compute the relative risk when possible, or convert to a relative risk according to Zhang et al. Reported confidence intervals and p-values are used when available, and adjusted values are used when provided. If multiple types of adjustments are reported propensity score matching and multivariable regression has preference over propensity score matching or weighting, which has preference over multivariable regression. Adjusted results have preference over unadjusted results for a more serious outcome when the adjustments significantly alter results. When needed, conversion between reported p-values and confidence intervals followed Altman, Altman (B), and Fisher's exact test was used to calculate p-values for event data. If continuity correction for zero values is required, we use the reciprocal of the opposite arm with the sum of the correction factors equal to 1136. Results are expressed with RR < 1.0 favoring treatment, and using the risk of a negative outcome when applicable (for example, the risk of death rather than the risk of survival). If studies only report relative continuous values such as relative times, the ratio of the time for the treatment group versus the time for the control group is used. Calculations are done in Python (3.14.8) with scipy (1.18.1), pythonmeta (1.26), numpy (2.5.3), statsmodels (0.15.0), and plotly (6.9.0). Mixed-effects meta-regression results are computed with R (4.4.0) using the metafor (4.6-0) and rms (6.8-0) packages, and using the most serious sufficiently powered outcome. For all statistical tests, a p-value less than 0.05 was considered statistically significant. Grobid 0.8.2 is used to parse PDF documents.
When evaluating potential effect modification across groups, we use an interaction test as described by Altman (C) et al. We compared the log-transformed relative risks using a z-test, deriving the standard error of the difference from the 95% confidence intervals. A two-sided interaction p-value of < 0.05 was considered a statistically significant difference in treatment effect between the groups.
Cochrane RoB 2/ROBINS-I are often used to evaluate studies, and have the advantage of providing standardized rules that can be applied with minimal understanding of the domain and study. However, the rules do not account for many real-world issues, often overemphasize or underemphasize others, and studies show low inter-rater reliability144. Certain domains are more applicable for these tools, however the time-sensitive nature of a pandemic, with significant mortality for every day of delay in evidence assessment, and the characteristics of COVID-19 make them inappropriate for this domain. This can be demonstrated with examples where expert RoB 2/ROBINS-I ratings do not match reality for COVID-19. Popp et al. use RoB 2 to classify Reis et al. as low risk of bias, however this is the opposite of reality—the trial not only has very high risk of bias, but has very high actual known bias, refusing to release data despite pledging to, reporting multiple impossible numbers, having blinding and randomization failure, and many other issues146. Axfors (B) et al. use RoB 2 to classify Horby (B) et al. as low risk of bias, however this is the opposite of reality—the very late treatment and excessive dosage used produces results with no relevance to recommended usage. HCQ shows poor results with late treatment and excessive dosage, and the combination shows harmB. Hempenius et al. use ROBINS-I to classify 33 studies for HCQ. The two rated as having the lowest risk of bias142,143 are far from the most informative. Both involve very late treatment, providing no information on recommended usage, and ROBINS-I does a very poor job of accounting for the impact of confounding factorsC.
Our quality evaluation focuses on known issues and bias, and the potential impact on outcomes, rather than just the risk of bias. The estimated potential impact of each confounding factor, and the direction of the impact is considered. For example, consider a study that shows significantly lower risk, the value of the study varies significantly if confounding points to an underestimate or an overestimate of efficacy. In one case, the real effect may be null, while the other case provides stronger evidence of efficacy (which may be greater than the study shows). Analysis focusing on the risk of bias, while simpler, may penalize studies for theoretical or technical issues that have no or minimal impact on outcomes. Analysis also depends on the outcome, for example certain issues are less relevant for objective outcomes such as mortality. Inaccurate penalization, and inaccurate high-quality evaluation in the face of known major issues affecting outcomes, increases in significance during a pandemic when immediate recognition of new evidence is critical, and when considering all global studies, as required during a pandemic. Investigators in other countries may have different customs for design, analysis, and reporting, and different English language skills, however they may not be less diligent or have greater bias. Investigators in lower-pharmaceutical-profit countries may have lower bias towards profitable interventions.
We have classified studies as early treatment if most patients are not already at a severe stage at the time of treatment (for example based on oxygen status or lung involvement), and treatment started within 5 days of the onset of symptoms. If studies contain a mix of early treatment and late treatment patients, we consider the treatment time of patients contributing most to the events (for example, consider a study where most patients are treated early but late treatment patients are included, and all mortality events were observed with late treatment patients). We note that a shorter time may be preferable. Antivirals are typically only considered effective when used within a shorter timeframe, for example 0-36 or 0-48 hours for oseltamivir, with longer delays not being effective77,78.
This is a living analysis and is updated regularly. Submit updates or corrections with the form below. We received no funding, this research is done in our spare time. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
A summary of study results is below. Please submit updates and corrections at the bottom of this page.
A summary of study results is below. Please submit updates and corrections at https://c19early.org/cpmeta.html.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
Alemany, 2/9/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, peer-reviewed, median age 56.0, 108 authors, study period 10 November, 2020 - 28 July, 2021, trial NCT04621123 (history) (CONV-ERT). risk of death, 80.0% lower, RR 0.20, p = 0.50, treatment 0 of 188 (0.0%), control 2 of 188 (1.1%), NNT 94, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of hospitalization, 4.8% higher, RR 1.05, p = 1.00, treatment 22 of 188 (11.7%), control 21 of 188 (11.2%).
risk of no recovery, 5.0% higher, HR 1.05, p = 0.67, treatment 188, control 188, time to symptom resolution.
viral load, 3.6% higher, relative load 1.04, p = 0.33, treatment 188, control 188, relative change in viral load, day 28.
viral load, 3.7% lower, relative load 0.96, p = 0.42, treatment 188, control 188, relative change in viral load, day 7.
Balcells, 3/3/2021, Randomized Controlled Trial, Chile, peer-reviewed, 32 authors, study period 10 May, 2020 - 18 July, 2020, average treatment delay 5.0 days, trial NCT04375098 (history). risk of death, 247.4% higher, RR 3.47, p = 0.17, treatment 5 of 28 (17.9%), control 2 of 30 (6.7%), adjusted per study, odds ratio converted to relative risk, logistic regression, early vs. deferred.
risk of mechanical ventilation, 163.3% higher, RR 2.63, p = 0.22, treatment 5 of 28 (17.9%), control 2 of 30 (6.7%), adjusted per study, odds ratio converted to relative risk, logistic regression, early vs. deferred.
risk of progression, 23.3% higher, RR 1.23, p = 0.51, treatment 13 of 28 (46.4%), control 12 of 30 (40.0%), adjusted per study, odds ratio converted to relative risk, logistic regression, early vs. deferred.
Gharbharan, 8/23/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Netherlands, peer-reviewed, 59 authors, study period November 2020 - July 2021, average treatment delay 5.0 days, trial NCT04589949 (history) (CoV-Early). risk of death, 1.0% higher, RR 1.01, p = 1.00, treatment 1 of 207 (0.5%), control 1 of 209 (0.5%), day 28.
risk of mechanical ventilation, 66.6% lower, RR 0.33, p = 1.00, treatment 0 of 207 (0.0%), control 1 of 209 (0.5%), NNT 209, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
risk of progression, 14.0% lower, OR 0.86, p = 0.42, treatment 207, control 209, adjusted per study, improved severity score, RR approximated with OR.
risk of progression, 42.0% lower, OR 0.58, p = 0.06, treatment 123, control 103, adjusted per study, improved severity score, ≤5 days, RR approximated with OR.
risk of hospitalization, 39.0% lower, HR 0.61, p = 0.22, treatment 10 of 207 (4.8%), control 18 of 209 (8.6%), NNT 26, adjusted per study, day 28.
hospitalization time, 50.0% higher, relative time 1.50, p = 0.56, treatment 207, control 209.
risk of no recovery, 1.0% higher, RR 1.01, p = 0.92, treatment 137 of 207 (66.2%), control 137 of 209 (65.6%), continued COVID-19 symptoms, day 27.
recovery time, 8.3% higher, relative time 1.08, p = 0.99, treatment 207, control 209.
Hoffmann, 2/27/2025, Randomized Controlled Trial, multiple countries, peer-reviewed, median age 57.0, 33 authors, study period 11 April, 2022 - 27 November, 2023, average treatment delay 4.0 days, trial NCT05271929 (history) (COVIC-19). risk of death, 50.8% lower, RR 0.49, p = 0.62, treatment 1 of 59 (1.7%), control 2 of 58 (3.4%), NNT 57, day 180.
risk of death/hospitalization, 91.0% lower, RR 0.09, p = 0.03, treatment 0 of 59 (0.0%), control 5 of 58 (8.6%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
risk of death/hospitalization, 89.0% lower, RR 0.11, p = 0.06, treatment 0 of 59 (0.0%), control 4 of 58 (6.9%), NNT 14, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 14.
risk of ICU admission, 66.9% lower, RR 0.33, p = 0.50, treatment 0 of 59 (0.0%), control 1 of 58 (1.7%), NNT 58, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28.
Keitel-Anselmino, 10/29/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Germany, trial NCT04681430 (history) (RES-Q-HR). 22 patient RCT with results unknown and over 4 years late.
Korley, 8/18/2021, Randomized Controlled Trial, USA, peer-reviewed, 28 authors, study period August 2020 - February 2021, average treatment delay 3.7 days, trial NCT04355767 (history) (C3PO). risk of death, 396.0% higher, RR 4.96, p = 0.22, treatment 5 of 250 (2.0%), control 1 of 248 (0.4%).
risk of hospitalization, 10.0% lower, RR 0.90, p = 0.59, treatment 51 of 257 (19.8%), control 56 of 254 (22.0%), NNT 45.
risk of progression, 6.0% lower, RR 0.94, p = 0.70, treatment 77 of 257 (30.0%), control 81 of 254 (31.9%), NNT 52.
Libster, 1/6/2021, Double Blind Randomized Controlled Trial, Argentina, peer-reviewed, 56 authors, study period 4 June, 2020 - 25 October, 2020, average treatment delay 1.825 days, trial NCT04479163 (history) (INFANT-COVID-19). risk of death, 50.0% lower, RR 0.50, p = 0.43, treatment 2 of 80 (2.5%), control 4 of 80 (5.0%), NNT 40.
risk of mechanical ventilation, 50.0% lower, RR 0.50, p = 0.43, treatment 2 of 80 (2.5%), control 4 of 80 (5.0%), NNT 40.
risk of ICU admission, 67.0% lower, RR 0.33, p = 0.17, treatment 2 of 80 (2.5%), control 6 of 80 (7.5%), NNT 20.
risk of progression, 48.0% lower, RR 0.52, p = 0.03, treatment 13 of 80 (16.2%), control 25 of 80 (31.2%), NNT 6.7.
Van Hise, 8/12/2021, Randomized Controlled Trial, USA, preprint, 1 author, trial NCT04438057 (history). risk of hospitalization, 440.8% higher, RR 5.41, p = 0.55, treatment 3 of 49 (6.1%), control 0 of 23 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
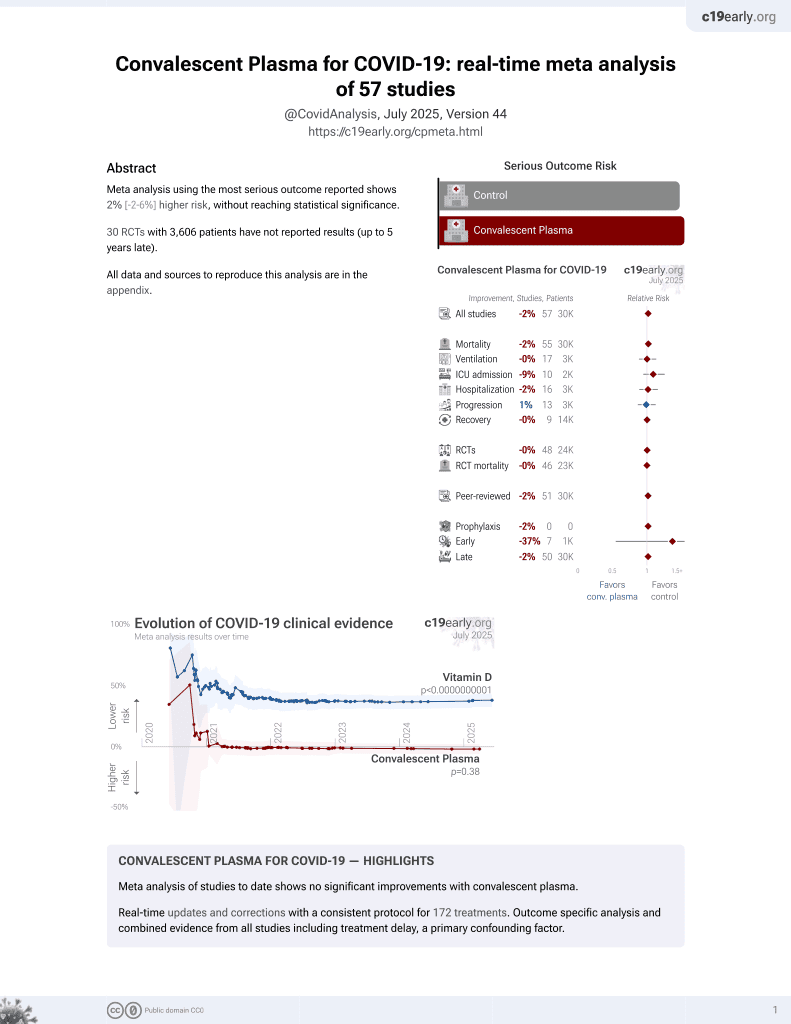
Abayomi, 11/20/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Nigeria, peer-reviewed, 1 author, trial PACTR202006760881890 (LACCPT). risk of death, 16.7% higher, RR 1.17, p = 1.00, treatment 7 of 11 (63.6%), control 6 of 11 (54.5%).
Agarwal, 10/22/2020, Randomized Controlled Trial, India, peer-reviewed, 6 authors, study period 22 April, 2020 - 14 July, 2020, average treatment delay 8.0 days, trial CTRI/2020/04/024775 (PLACID). risk of death, 7.0% higher, RR 1.07, p = 0.74, treatment 34 of 235 (14.5%), control 31 of 229 (13.5%).
combined death at 28 days or progression to severe disease, 7.0% higher, RR 1.07, p = 0.74, treatment 44 of 235 (18.7%), control 41 of 229 (17.9%).
risk of mechanical ventilation, 1.0% lower, RR 0.99, p = 0.98, treatment 19 of 227 (8.4%), control 19 of 224 (8.5%), NNT 892.
risk of no viral clearance, 28.0% lower, RR 0.72, p = 0.02, treatment 56 of 173 (32.4%), control 76 of 169 (45.0%), NNT 7.9, day 7.
AlQahtani, 11/4/2020, Randomized Controlled Trial, Bahrain, peer-reviewed, 11 authors, study period 19 April, 2020 - 9 July, 2020, trial NCT04356534 (history). risk of death, 50.0% lower, RR 0.50, p = 0.55, treatment 1 of 20 (5.0%), control 2 of 20 (10.0%), NNT 20.
noninvasive or mechanical ventilation, 33.3% lower, RR 0.67, p = 0.47, treatment 4 of 20 (20.0%), control 6 of 20 (30.0%), NNT 10, primary outcome.
hospitalization time, 21.9% lower, relative time 0.78, p = 0.12, treatment 20, control 20.
Alshamrani, 2/15/2023, retrospective, Saudi Arabia, peer-reviewed, 3 authors, study period March 2020 - January 2021. risk of death, 14.3% higher, RR 1.14, p = 0.39, treatment 24 of 41 (58.5%), control 108 of 205 (52.7%), adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable.
risk of progression, 17.3% higher, RR 1.17, p = 0.047, treatment 34 of 41 (82.9%), control 154 of 205 (75.1%), adjusted per study, odds ratio converted to relative risk, AKI, ARDS, multi-organ failure, or mortality, propensity score matching, multivariable.
ICU time, 42.6% higher, relative time 1.43, p = 0.003, treatment 37, control 166, propensity score matching.
hospitalization time, 31.8% higher, relative time 1.32, p = 0.01, treatment 41, control 205, propensity score matching.
Avendaño-Solà, 9/29/2020, Randomized Controlled Trial, Spain, peer-reviewed, 38 authors, study period 4 April, 2020 - 10 July, 2020, average treatment delay 8.0 days, trial NCT04345523 (history) (ConPlas-19). risk of death, 88.3% lower, RR 0.12, p = 0.12, treatment 0 of 38 (0.0%), control 4 of 43 (9.3%), NNT 11, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 29.
risk of progression, 93.0% lower, RR 0.07, p = 0.01, treatment 0 of 38 (0.0%), control 7 of 43 (16.3%), NNT 6.1, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 29, progression to categories 5-7.
risk of progression, 91.9% lower, RR 0.08, p = 0.03, treatment 0 of 38 (0.0%), control 6 of 43 (14.0%), NNT 7.2, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 15, progression to categories 5-7, primary outcome.
Averyanov, 9/23/2020, Randomized Controlled Trial, placebo-controlled, Russia, trial NCT04392414 (history). 60 patient RCT with results unknown and over 6 years late.
Bajpai, 4/6/2022, Randomized Controlled Trial, India, peer-reviewed, mean age 55.5, 23 authors, study period June 2020 - December 2020, trial NCT04425915 (history) (COPLA-II). risk of death, 13.5% higher, RR 1.14, p = 0.62, treatment 42 of 200 (21.0%), control 37 of 200 (18.5%), day 28.
risk of death, 19.0% higher, RR 1.19, p = 0.64, treatment 25 of 200 (12.5%), control 21 of 200 (10.5%), day 7.
risk of mechanical ventilation, 12.5% higher, RR 1.13, p = 0.76, treatment 27 of 200 (13.5%), control 24 of 200 (12.0%), day 7.
ICU time, 1.7% higher, relative time 1.02, p = 0.80, treatment mean 11.1 (±7.77) n=200, control mean 10.91 (±6.96) n=200.
hospitalization time, 0.1% lower, relative time 1.00, p = 0.98, treatment mean 13.8 (±7.03) n=200, control mean 13.82 (±7.19) n=200.
risk of no recovery, 5.9% lower, RR 0.94, p = 0.75, treatment 64 of 200 (32.0%), control 68 of 200 (34.0%), NNT 50, day 28.
relative mean Ct, 1.1% worse, RR 1.01, p = 0.54, treatment mean 34.31 (±6.61) n=200, control mean 34.7 (±6.2) n=200, day 7.
Bajpai (B), 10/27/2020, Randomized Controlled Trial, India, peer-reviewed, mean age 48.2, 17 authors, trial NCT04346446 (history) (ILBS-COVID-02). risk of death, 323.0% higher, HR 4.23, p = 0.22, treatment 3 of 14 (21.4%), control 1 of 15 (6.7%), adjusted per study, 28 days, Cox proportional hazards.
risk of death, 114.3% higher, RR 2.14, p = 0.60, treatment 2 of 14 (14.3%), control 1 of 15 (6.7%), 7 days.
risk of mechanical ventilation, 221.4% higher, RR 3.21, p = 0.33, treatment 3 of 14 (21.4%), control 1 of 15 (6.7%), 7 days.
hospitalization time, 24.9% lower, relative time 0.75, p = 0.08, treatment 14, control 15.
relative improvement in Ct value, 33.1% better, RR 0.67, p = 0.11, treatment 14, control 15.
Baksh, 1/31/2023, Double Blind Randomized Controlled Trial, USA, peer-reviewed, 26 authors, study period 3 June, 2020 - 1 October, 2021, average treatment delay 6.0 days, trial NCT04373460 (history). risk of no recovery, 1.0% higher, RR 1.01, p = 0.62, treatment 381 of 538 (70.8%), control 381 of 532 (71.6%), NNT 125, inverted to make RR<1 favor treatment, day 14.
risk of long COVID, 4.4% higher, RR 1.04, p = 0.78, treatment 533, control 528, all patients.
risk of long COVID, 9.0% lower, OR 0.91, p = 0.67, treatment 232, control 234, ≤5 days, full population, RR approximated with OR.
risk of long COVID, 18.0% higher, OR 1.18, p = 0.41, treatment 301, control 294, >5 days, full population, RR approximated with OR.
Baldeón, 1/9/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Ecuador, peer-reviewed, 17 authors, study period May 2020 - January 2021, average treatment delay 10.6 days. risk of death, 12.0% lower, RR 0.88, p = 1.00, treatment 7 of 63 (11.1%), control 12 of 95 (12.6%), NNT 66.
Bar, 12/15/2021, Randomized Controlled Trial, USA, peer-reviewed, median age 63.0, 40 authors, study period 18 May, 2020 - 8 January, 2021, trial NCT04397757 (history) (PennCCP2). risk of death, 81.0% lower, HR 0.19, p = 0.03, treatment 40, control 39, Cox proportional hazards, day 28.
risk of no improvement, 43.8% lower, OR 0.56, p = 0.18, treatment 40, control 39, WHO8 score, day 28, RR approximated with OR.
risk of mechanical ventilation, 51.2% lower, RR 0.49, p = 0.16, treatment 5 of 40 (12.5%), control 10 of 39 (25.6%), NNT 7.6.
Baylor Research Institute, 12/31/2022, Randomized Controlled Trial, placebo-controlled, USA, trial NCT04333251 (history). Estimated 115 patient RCT with results unknown and over 3 years late.
Bennett-Guerrero, 4/16/2021, Double Blind Randomized Controlled Trial, USA, peer-reviewed, 18 authors, study period 8 April, 2020 - 1 February, 2021, average treatment delay 9.0 days, trial NCT04344535 (history). risk of death, 18.6% lower, RR 0.81, p = 0.75, treatment 16 of 59 (27.1%), control 5 of 15 (33.3%), NNT 16, day 90.
risk of death, 11.0% lower, RR 0.89, p = 1.00, treatment 14 of 59 (23.7%), control 4 of 15 (26.7%), NNT 34, day 28.
risk of no improvement, 0.4% lower, RR 1.00, p = 1.00, treatment 47 of 59 (79.7%), control 12 of 15 (80.0%), NNT 295.
Bégin, 9/9/2021, Randomized Controlled Trial, multiple countries, peer-reviewed, 33 authors, study period 14 May, 2020 - 29 January, 2021, average treatment delay 8.0 days, trial NCT04348656 (history) (CONCOR-1). risk of death, 13.0% higher, RR 1.13, p = 0.33, treatment 156 of 625 (25.0%), control 69 of 313 (22.0%), day 90.
risk of death, 12.0% higher, RR 1.12, p = 0.40, treatment 141 of 614 (23.0%), control 63 of 307 (20.5%), day 30.
risk of death/intubation, 16.0% higher, RR 1.16, p = 0.18, treatment 199 of 614 (32.4%), control 86 of 307 (28.0%), primary outcome.
Camacho-Ortiz, 5/1/2021, Double Blind Randomized Controlled Trial, Mexico, trial NCT04358783 (history) (COP-COVID-19). 31 patient RCT with results unknown and over 5 years late.
Cardesa Gil, 12/30/2020, Randomized Controlled Trial, Spain, trial NCT04366245 (history). 72 patient RCT with results unknown and over 5 years late.
Cho, 6/21/2021, retrospective, USA, peer-reviewed, 24 authors, trial NCT04545047 (history). risk of death, 4.0% higher, HR 1.04, p = 0.88, treatment 402, control 4,642.
Chowdhury, 10/30/2020, Randomized Controlled Trial, Bangladesh, trial NCT04403477 (history). Estimated 60 patient RCT with results unknown and over 5 years late.
de la Puerta Rueda, 12/31/2021, Double Blind Randomized Controlled Trial, Spain, trial NCT05247307 (history). 93 patient RCT with results unknown and over 4 years late.
De Santis, 3/31/2022, Randomized Controlled Trial, Brazil, peer-reviewed, 23 authors, average treatment delay 9.0 days. risk of death, 13.2% lower, RR 0.87, p = 0.67, treatment 11 of 36 (30.6%), control 25 of 71 (35.2%), NNT 21, day 60.
risk of death, 12.3% lower, RR 0.88, p = 0.81, treatment 8 of 36 (22.2%), control 18 of 71 (25.4%), NNT 32, day 30.
Denkinger, 12/29/2022, Randomized Controlled Trial, Germany, peer-reviewed, 54 authors, study period 3 September, 2020 - 20 January, 2022, average treatment delay 7.0 days. risk of death, 8.2% lower, RR 0.92, p = 0.39, treatment 68, control 66, inverted to make RR<1 favor treatment, day 84.
risk of mechanical ventilation, 2.5% higher, RR 1.02, p = 1.00, treatment 19 of 68 (27.9%), control 18 of 66 (27.3%).
risk of 7-point scale, 22.5% lower, HR 0.78, p = 0.22, treatment 68, control 66, inverted to make HR<1 favor treatment, primary outcome.
Devos, 8/26/2021, Randomized Controlled Trial, Belgium, peer-reviewed, 26 authors, study period 2 May, 2020 - 26 January, 2021, average treatment delay 7.0 days, trial NCT04429854 (history) (DAWn-plasma). risk of death, 1.0% lower, HR 0.99, p = 0.98, treatment 320, control 163.
risk of mechanical ventilation, 8.0% higher, HR 1.08, p = 0.78, treatment 320, control 163.
risk of ICU admission, no change, HR 1.00, p = 1.00, treatment 320, control 163.
Dillner, 1/26/2022, Randomized Controlled Trial, Sweden, trial NCT04649879 (history). 59 patient RCT with results unknown and over 4 years late.
ElDesouky, 12/31/2021, Randomized Controlled Trial, Egypt, trial NCT04438694 (history) (CP IN COVID19). Estimated 67 patient RCT with results unknown and over 4 years late.
Elhadi, 4/30/2021, prospective, Libya, peer-reviewed, 21 authors, study period 29 May, 2020 - 30 December, 2020. risk of death, 16.0% higher, RR 1.16, p = 0.39, treatment 16 of 23 (69.6%), control 265 of 442 (60.0%).
Fundacin Biomedica Galicia Sur, 3/31/2021, Randomized Controlled Trial, Spain, trial NCT05578391 (history) (CoV-PlasGal). 61 patient RCT with results unknown and over 5 years late.
Gauiran, 2/15/2024, Randomized Controlled Trial, Philippines, peer-reviewed, median age 60.0, 26 authors, study period 28 September, 2020 - 31 May, 2021, average treatment delay 8.0 days, trial NCT04567173 (history) (Co-CLARITY). risk of death, 400.0% higher, RR 5.00, p = 0.49, treatment 2 of 22 (9.1%), control 0 of 22 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
risk of ICU admission, 100% higher, RR 2.00, p = 1.00, treatment 2 of 22 (9.1%), control 1 of 22 (4.5%).
hospitalization time, 7.1% higher, relative time 1.07, p = 0.70, treatment 22, control 22.
Gharbharan (B), 5/27/2021, Randomized Controlled Trial, Netherlands, peer-reviewed, 32 authors, study period 8 April, 2020 - 14 June, 2020, average treatment delay 10.0 days, trial NCT04342182 (history) (ConCoVid-19). risk of death, 3.8% lower, RR 0.96, p = 0.95, treatment 6 of 43 (14.0%), control 11 of 43 (25.6%), NNT 8.6, adjusted per study, odds ratio converted to relative risk, multivariable logistic regression, primary outcome.
time to discharge, 11.7% lower, relative time 0.88, p = 0.68, treatment 43, control 43, adjusted per study, multivariable Fine and Gray regression.
Gonzalez, 6/19/2021, Randomized Controlled Trial, Argentina, trial NCT04468009 (history). 134 patient RCT with results unknown and over 5 years late.
Gonzalez (B), 3/31/2021, retrospective, Mexico, preprint, 17 authors, study period 5 May, 2020 - 17 October, 2020, this trial compares with another treatment - results may be better when compared to placebo, trial NCT04381858 (history). risk of death, 6.5% higher, RR 1.07, p = 0.76, treatment 60 of 130 (46.2%), control 26 of 60 (43.3%), day 28, intention-to-treat.
risk of death, 1.0% higher, RR 1.01, p = 1.00, treatment 70 of 130 (53.8%), control 32 of 60 (53.3%), followup, day 28, intention-to-treat.
Herrick, 5/5/2021, Double Blind Randomized Controlled Trial, placebo-controlled, USA, trial NCT04442191 (history). Estimated 50 patient RCT with results unknown and over 5 years late.
Higgins, 12/16/2022, Randomized Controlled Trial, multiple countries, peer-reviewed, 66 authors, study period 9 March, 2020 - 22 June, 2021, trial NCT02735707 (history) (REMAP-CAP). risk of death, 1.0% lower, HR 0.99, p = 0.90, treatment 370 of 944 (39.2%), control 324 of 790 (41.0%), NNT 55, adjusted per study, day 180.
Holm, 12/4/2021, Randomized Controlled Trial, Sweden, peer-reviewed, 14 authors, study period June 2020 - January 2021, average treatment delay 7.0 days, trial NCT04600440 (history) (COP20). risk of death, 45.1% lower, RR 0.55, p = 0.64, treatment 2 of 17 (11.8%), control 3 of 14 (21.4%), NNT 10.
risk of mechanical ventilation, 68.9% lower, RR 0.31, p = 0.45, treatment 0 of 17 (0.0%), control 1 of 14 (7.1%), NNT 14, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of progression, 18.8% lower, RR 0.81, p = 1.00, treatment 4 of 16 (25.0%), control 4 of 13 (30.8%), NNT 17, progression to HFNC.
oxygen time, 57.1% higher, relative time 1.57, p = 0.43, treatment 17, control 14.
hospitalization time, 62.5% higher, relative time 1.62, p = 0.21, treatment 17, control 14.
Horby et al., 1/15/2021, Randomized Controlled Trial, United Kingdom, peer-reviewed, 36 authors, average treatment delay 9.0 days, trial NCT04381936 (history) (RECOVERY). risk of death, 1.0% higher, RR 1.01, p = 0.78, treatment 1,622 of 5,795 (28.0%), control 1,610 of 5,763 (27.9%), day 180.
risk of death, no change, RR 1.00, p = 0.95, treatment 1,399 of 5,795 (24.1%), control 1,408 of 5,763 (24.4%), NNT 345, day 28, primary outcome.
risk of no hospital discharge, 1.0% higher, RR 1.01, p = 0.57, treatment 1,963 of 5,795 (33.9%), control 1,941 of 5,763 (33.7%), inverted to make RR<1 favor treatment, day 28.
Hsue, 8/23/2021, Double Blind Randomized Controlled Trial, placebo-controlled, USA, preprint, 1 author, study period 9 June, 2020 - 30 April, 2021, trial NCT04421404 (history) (CAPRI). risk of death, 212.5% higher, RR 3.12, p = 0.47, treatment 1 of 16 (6.2%), control 0 of 18 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 28.
risk of death, 12.5% higher, RR 1.12, p = 1.00, treatment 1 of 16 (6.2%), control 1 of 18 (5.6%), all cause, day 28.
risk of mechanical ventilation, 425.0% higher, RR 5.25, p = 0.21, treatment 2 of 16 (12.5%), control 0 of 18 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 28.
risk of progression, 425.0% higher, RR 5.25, p = 0.21, treatment 2 of 16 (12.5%), control 0 of 18 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), death or mechanical ventilation, day 28, primary outcome.
risk of progression, 425.0% higher, RR 5.25, p = 0.21, treatment 2 of 16 (12.5%), control 0 of 18 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), death or mechanical ventilation, day 14, primary outcome.
Iasella, 10/24/2024, retrospective, USA, peer-reviewed, 30 authors, study period March 2020 - June 2021. risk of death, 25.9% higher, RR 1.26, p = 0.14, treatment 73 of 290 (25.2%), control 58 of 290 (20.0%), propensity score matching, day 30.
risk of mechanical ventilation, 0.6% higher, RR 1.01, p = 1.00, treatment 155 of 290 (53.4%), control 154 of 290 (53.1%), MV/ECMO, propensity score matching, day 30.
oxygen, no change, RR 1.00, p = 1.00, treatment 118 of 290 (40.7%), control 118 of 290 (40.7%), propensity score matching, day 30.
Itinose, 4/7/2022, Randomized Controlled Trial, Brazil, trial NCT05077930 (history). 38 patient RCT with results unknown and over 4 years late.
Jalili, 1/1/2022, Randomized Controlled Trial, Iran, peer-reviewed, 15 authors, study period May 2020 - July 2020. risk of death, 45.5% higher, RR 1.45, p = 0.38, treatment 16 of 60 (26.7%), control 11 of 60 (18.3%).
risk of ICU admission, 8.0% higher, RR 1.08, p = 0.85, treatment 27 of 60 (45.0%), control 25 of 60 (41.7%).
risk of ARDS, 250.0% higher, RR 3.50, p = 0.16, treatment 7 of 60 (11.7%), control 2 of 60 (3.3%).
hospitalization time, 9.9% higher, relative time 1.10, p = 0.39, treatment 60, control 60.
Karyana, 12/31/2021, Randomized Controlled Trial, Indonesia, trial NCT04873414 (history) (PlaSenTer). Estimated 364 patient RCT with results unknown and over 4 years late.
Kasten, 12/1/2023, retrospective, USA, peer-reviewed, median age 63.6, 13 authors, study period 1 September, 2020 - 28 February, 2021, trial NCT04884477 (history). risk of death, 3.8% higher, RR 1.04, p = 1.00, treatment 7 of 19 (36.8%), control 11 of 31 (35.5%), day 90.
risk of death, 16.5% higher, RR 1.17, p = 1.00, treatment 5 of 19 (26.3%), control 7 of 31 (22.6%), day 30.
Kaufman, 6/30/2021, Double Blind Randomized Controlled Trial, placebo-controlled, USA, trial NCT04361253 (history) (ESCAPE). 45 patient RCT with results unknown and over 5 years late.
Khawaja, 3/21/2024, Double Blind Randomized Controlled Trial, placebo-controlled, Finland, peer-reviewed, mean age 51.7, 23 authors, study period 2 February, 2021 - 19 January, 2022, average treatment delay 8.0 days, trial NCT04730401 (history) (CP_COVID-19). risk of death, 154.1% higher, RR 2.54, p = 1.00, treatment 1 of 37 (2.7%), control 0 of 20 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
risk of mechanical ventilation, 73.0% lower, RR 0.27, p = 0.28, treatment 1 of 37 (2.7%), control 2 of 20 (10.0%), NNT 14.
risk of ICU admission, 45.9% lower, RR 0.54, p = 0.65, treatment 3 of 37 (8.1%), control 3 of 20 (15.0%), NNT 15.
Kirenga, 8/9/2021, Randomized Controlled Trial, Uganda, peer-reviewed, median age 50.0, 30 authors, study period 16 June, 2020 - 31 December, 2020, average treatment delay 7.0 days, trial NCT04542941 (history) (COVIDIT). risk of death, 21.4% higher, RR 1.21, p = 0.80, treatment 10 of 69 (14.5%), control 8 of 67 (11.9%).
risk of progression, 9.1% lower, RR 0.91, p = 1.00, treatment 9 of 41 (22.0%), control 7 of 29 (24.1%), NNT 46.
time to viral-, 50.0% higher, relative time 1.50, p = 0.20, treatment 67, control 67.
Krishnan, 4/5/2023, retrospective, India, peer-reviewed, mean age 52.8, 48 authors, study period March 2020 - March 2021. risk of death, 270.0% higher, OR 3.70, p = 0.07, adjusted per study, case control OR, multivariable.
Körper, 10/15/2021, Randomized Controlled Trial, Germany, peer-reviewed, median age 60.0, 27 authors, study period 30 August, 2020 - 24 December, 2020, trial NCT04433910 (history) (CAPSID). risk of death, 36.5% lower, RR 0.63, p = 0.19, treatment 11 of 53 (20.8%), control 17 of 52 (32.7%), NNT 8.4, day 60.
risk of death, 14.2% lower, RR 0.86, p = 0.79, treatment 7 of 53 (13.2%), control 8 of 52 (15.4%), NNT 46, day 21.
risk of no recovery, 15.9% lower, RR 0.84, p = 0.32, treatment 30 of 53 (56.6%), control 35 of 52 (67.3%), NNT 9.3, composite outcome of survival and no longer fulfilling criteria for severe COVID-19, day 21, primary outcome.
Lacombe, 8/10/2022, Randomized Controlled Trial, France, preprint, 33 authors, study period 16 April, 2020 - 21 April, 2021, average treatment delay 7.0 days, trial NCT04345991 (history) (CORIPLASM). risk of death, 49.0% lower, HR 0.51, p = 0.16, treatment 7 of 60 (11.7%), control 12 of 60 (20.0%), NNT 12, adjusted per study, day 28.
risk of death, 64.0% lower, HR 0.36, p = 0.04, treatment 4 of 22 (18.2%), control 11 of 27 (40.7%), NNT 4.4, adjusted per study, day 28, immunocompromised.
risk of progression, 68.3% higher, RR 1.68, p = 0.18, treatment 13 of 60 (21.7%), control 8 of 60 (13.3%), adjusted per study, odds ratio converted to relative risk, WHO-CPS ≥6, day 4, primary outcome.
risk of progression, 4.0% higher, HR 1.04, p = 0.89, treatment 19 of 60 (31.7%), control 20 of 60 (33.3%), NNT 60, adjusted per study, ventilation, additional immunomodulators, or death, day 14, primary outcome.
hospitalization time, 6.7% higher, relative time 1.07, p = 0.99, treatment 60, control 60.
Lewandowski, 3/7/2024, retrospective, Poland, peer-reviewed, 15 authors. risk of death, 61.8% higher, OR 1.62, p = 0.12, RR approximated with OR.
Li, 6/3/2020, Randomized Controlled Trial, China, peer-reviewed, 34 authors, study period 14 February, 2020 - 1 April, 2020. risk of death, 34.6% lower, RR 0.65, p = 0.30, treatment 8 of 51 (15.7%), control 12 of 50 (24.0%), NNT 12, odds ratio converted to relative risk, 28 days.
risk of no improvement, 15.3% lower, RR 0.85, p = 0.37, treatment 25 of 52 (48.1%), control 29 of 51 (56.9%), NNT 11, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, 28 days.
risk of no viral clearance, 76.4% lower, RR 0.24, p = 0.01, treatment 4 of 26 (15.4%), control 15 of 23 (65.2%), NNT 2.0, inverted to make RR<1 favor treatment, odds ratio converted to relative risk.
Lubis, 10/31/2020, Randomized Controlled Trial, Indonesia, trial NCT04380935 (history). Estimated 60 patient RCT with results unknown and over 5 years late.
Manzini, 11/22/2022, Double Blind Randomized Controlled Trial, Italy, peer-reviewed, median age 66.6, 54 authors, study period June 2020 - August 2021, trial NCT04428021 (history) (PLACO COVID). risk of death, 25.0% higher, RR 1.25, p = 0.54, treatment 14 of 60 (23.3%), control 12 of 60 (20.0%), adjusted per study, day 30.
risk of death/intubation, 10.0% higher, RR 1.10, p = 0.76, treatment 17 of 59 (28.8%), control 14 of 56 (25.0%), day 30.
time to viral-, 6.4% higher, relative time 1.06, p = 0.76, treatment 60, control 60, inverted to make RR<1 favor treatment.
Marshall, 3/23/2023, USA, trial NCT04412486 (history). 86 patient study with results unknown and over 3 years late.
Martinaud, 6/1/2021, Double Blind Randomized Controlled Trial, France, trial NCT04372979 (history) (PLASCOSSA). 18 patient RCT with results unknown and over 5 years late.
Menichetti, 11/29/2021, Randomized Controlled Trial, Italy, peer-reviewed, 110 authors, study period 15 July, 2020 - 8 December, 2020, average treatment delay 7.0 days, trial NCT04716556 (history) (TSUNAMI). risk of death, 23.4% lower, RR 0.77, p = 0.47, treatment 14 of 231 (6.1%), control 19 of 240 (7.9%), NNT 54.
risk of mechanical ventilation, 3.9% higher, RR 1.04, p = 1.00, treatment 25 of 231 (10.8%), control 25 of 240 (10.4%), mechanical ventilation or death.
risk of progression, 12.0% lower, RR 0.88, p = 0.54, treatment 59 of 231 (25.5%), control 67 of 239 (28.0%), NNT 40, PaO2/FiO2 <150 mm Hg or death, primary outcome.
Mesina, 3/1/2022, prospective, Philippines, preprint, median age 60.0, 7 authors, study period April 2020 - March 2021. risk of death, 28.6% higher, RR 1.29, p = 0.54, treatment 18 of 65 (27.7%), control 14 of 65 (21.5%).
hospitalization time, 60.0% higher, relative time 1.60, p = 0.07, treatment mean 16.0 (±25.08) n=65, control mean 10.0 (±7.87) n=65.
Ortigoza, 12/13/2021, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, median age 63.0, 268 authors, study period 17 April, 2020 - 15 March, 2021, average treatment delay 7.0 days, trial NCT04364737 (history) (CONTAIN COVID-19). risk of death, 11.8% lower, RR 0.88, p = 0.45, treatment 59 of 462 (12.8%), control 71 of 462 (15.4%), NNT 39, odds ratio converted to relative risk, day 28.
risk of death, 1.3% lower, RR 0.99, p = 0.95, treatment 35 of 463 (7.6%), control 39 of 463 (8.4%), NNT 116, odds ratio converted to relative risk, day 14.
WHO scale, 7.6% lower, OR 0.92, p = 0.50, treatment 468, control 473, day 28, RR approximated with OR.
WHO scale, 6.4% lower, OR 0.94, p = 0.58, treatment 468, control 473, day 14, primary outcome, RR approximated with OR.
risk of long COVID, 2.4% higher, RR 1.02, p = 0.88, treatment 141, control 140, all categories combined.
risk of long COVID, 5.0% lower, OR 0.95, p = 0.87, treatment 141, control 140, general, RR approximated with OR.
risk of long COVID, 15.0% higher, OR 1.15, p = 0.70, treatment 141, control 140, gastrointestinal, RR approximated with OR.
risk of long COVID, 18.0% lower, OR 0.82, p = 0.54, treatment 141, control 140, neurological, RR approximated with OR.
risk of long COVID, 18.0% higher, OR 1.18, p = 0.53, treatment 141, control 140, respiratory, RR approximated with OR.
Pathak, 8/9/2021, Randomized Controlled Trial, India, trial NCT04374487 (history). 100 patient RCT with results unknown and over 5 years late.
Perilla, 12/1/2021, Randomized Controlled Trial, Colombia, trial NCT04391101 (history). Estimated 231 patient RCT with results unknown and over 4 years late.
Perner, 6/30/2022, Randomized Controlled Trial, Denmark, trial NCT04634422 (history) (COVID-PLEX). Estimated 220 patient RCT with results unknown and over 4 years late.
Pouladzadeh, 4/10/2021, Single Blind Randomized Controlled Trial, multiple countries, peer-reviewed, mean age 53.5, 17 authors, study period March 2020 - May 2020, trial IRCT20200310046736N1. risk of death, 40.0% lower, RR 0.60, p = 0.71, treatment 3 of 30 (10.0%), control 5 of 30 (16.7%), NNT 15.
hospitalization time, 30.0% higher, relative time 1.30, p = 0.06, treatment 30, control 30.
Quintero-Vega, 2/1/2021, Single Blind Randomized Controlled Trial, Colombia, trial NCT04425837 (history) (PLASMA COVID-19). Estimated 236 patient RCT with results unknown and over 5 years late.
Ray, 11/29/2020, Randomized Controlled Trial, India, peer-reviewed, mean age 26.0, 38 authors, study period 31 May, 2020 - 12 October, 2020, trial CTRI/2020/05/025209. risk of death, 33.0% lower, HR 0.67, p = 0.34, treatment 10 of 40 (25.0%), control 14 of 40 (35.0%), NNT 10, adjusted per study, Mantel-Haenszel, primary outcome.
Rego, 1/30/2022, Randomized Controlled Trial, Brazil, trial NCT04528368 (history). Estimated 60 patient RCT with results unknown and over 4 years late.
Rojas, 6/27/2022, Single Blind Randomized Controlled Trial, Colombia, peer-reviewed, 45 authors, study period 8 August, 2020 - 13 November, 2020, average treatment delay 11.0 days, trial NCT04332835 (history) (CP-COVID-19). risk of death, 220.0% higher, HR 3.20, p = 0.16, treatment 46, control 45, Cox proportional hazards.
risk of no hospital discharge, 37.5% lower, HR 0.62, p = 0.04, treatment 46, control 45, inverted to make HR<1 favor treatment, Cox proportional hazards.
risk of no viral clearance, 25.0% higher, OR 1.25, p = 0.72, treatment 46, control 45, adjusted per study, mid-recovery, day 4, RR approximated with OR.
risk of no viral clearance, 16.0% higher, OR 1.16, p = 0.82, treatment 46, control 45, adjusted per study, day 7, RR approximated with OR.
risk of no viral clearance, 51.0% higher, OR 1.51, p = 0.60, treatment 46, control 45, adjusted per study, day 14, RR approximated with OR.
risk of no viral clearance, 12.0% higher, OR 1.12, p = 0.91, treatment 46, control 45, adjusted per study, day 28, RR approximated with OR.
Schiffer, 9/1/2021, Randomized Controlled Trial, Germany, trial NCT04712344 (history) (IPCO). Estimated 58 patient RCT with results unknown and over 5 years late.
Sekine, 7/8/2021, Randomized Controlled Trial, Brazil, peer-reviewed, 28 authors, study period 15 July, 2020 - 10 December, 2020, average treatment delay 10.0 days, trial NCT04547660 (history) (PLACOVID). risk of death, 38.5% higher, RR 1.38, p = 0.42, treatment 18 of 80 (22.5%), control 13 of 80 (16.2%), day 28.
risk of death, 100% higher, RR 2.00, p = 0.28, treatment 10 of 80 (12.5%), control 5 of 80 (6.2%), day 14.
risk of no improvement, 10.7% higher, RR 1.11, p = 0.74, treatment 31 of 80 (38.8%), control 28 of 80 (35.0%), day 28.
hospitalization time, 66.7% higher, relative time 1.67, p = 0.87, treatment 80, control 80.
Self, 11/30/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 51 authors, study period 28 April, 2020 - 1 June, 2021, average treatment delay 8.0 days, trial NCT04362176 (history) (PassItOn). risk of death, 3.3% higher, RR 1.03, p = 0.86, treatment 89 of 482 (18.5%), control 80 of 465 (17.2%), odds ratio converted to relative risk, day 28.
risk of death, 26.1% higher, RR 1.26, p = 0.29, treatment 63 of 482 (13.1%), control 48 of 465 (10.3%), odds ratio converted to relative risk, day 14.
risk of 7-point scale, 4.0% higher, OR 1.04, p = 0.76, treatment 487, control 473, day 14, primary outcome, RR approximated with OR.
Sevdi, 6/17/2020, Double Blind Randomized Controlled Trial, Turkey, trial NCT04442958 (history). 60 patient RCT with results unknown and over 6 years late.
Shaheen, 3/31/2025, Randomized Controlled Trial, Bangladesh, peer-reviewed, mean age 51.7, 9 authors, study period June 2020 - July 2021. risk of death, no change, RR 1.00, p = 1.00, treatment 8 of 30 (26.7%), control 8 of 30 (26.7%).
Sierra-Madero, 12/31/2020, Double Blind Randomized Controlled Trial, placebo-controlled, Mexico, trial NCT04388410 (history) (EPCOvid-1). Estimated 410 patient RCT with results unknown and over 5 years late.
Simonovich, 11/24/2020, Randomized Controlled Trial, Argentina, peer-reviewed, 39 authors, study period 28 May, 2020 - 27 August, 2020, average treatment delay 8.0 days, trial NCT04383535 (history) (PlasmAr). risk of death, 4.1% lower, RR 0.96, p = 1.00, treatment 25 of 228 (11.0%), control 12 of 105 (11.4%), NNT 216.
risk of 7-point scale, 19.0% lower, OR 0.81, p = 0.40, treatment 228, control 105, RR approximated with OR.
Song, 6/30/2022, Randomized Controlled Trial, Brazil, peer-reviewed, median age 61.0, 20 authors, study period 2 June, 2020 - 18 November, 2020, average treatment delay 8.0 days, trial NCT04415086 (history) (COOP-COVID-19-MCTI). risk of death, 51.7% higher, RR 1.52, p = 0.37, treatment 22 of 87 (25.3%), control 7 of 42 (16.7%).
Sullivan, 12/21/2021, Double Blind Randomized Controlled Trial, USA, peer-reviewed, 58 authors, study period 3 June, 2020 - 1 October, 2021, average treatment delay 6.0 days, trial NCT04373460 (history) (CSSC-004). risk of death, 85.7% lower, RR 0.14, p = 0.12, treatment 0 of 592 (0.0%), control 3 of 589 (0.5%), NNT 196, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of ICU admission, 25.4% lower, RR 0.75, p = 0.73, treatment 3 of 592 (0.5%), control 4 of 589 (0.7%), NNT 580.
risk of hospitalization, 54.3% lower, RR 0.46, p = 0.005, treatment 17 of 592 (2.9%), control 37 of 589 (6.3%), NNT 29.
Talarico, 5/15/2021, Randomized Controlled Trial, Italy, trial NCT04385043 (history) (COV2-CP). Estimated 400 patient RCT with results unknown and over 5 years late.
Teofili, 5/26/2021, Randomized Controlled Trial, Italy, preprint, 1 author, trial NCT04374526 (history) (LIFESAVER). risk of death, 100% higher, RR 2.00, p = 1.00, treatment 1 of 4 (25.0%), control 1 of 8 (12.5%).
Thorlacius-Ussing, 9/30/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Denmark, peer-reviewed, 27 authors, study period 13 June, 2020 - 16 March, 2021, average treatment delay 11.0 days, trial NCT04345289 (history) (CCAP-2). risk of death, 76.0% higher, RR 1.76, p = 0.43, treatment 15 of 98 (15.3%), control 4 of 46 (8.7%), day 90.
risk of death, 87.8% higher, RR 1.88, p = 0.39, treatment 12 of 98 (12.2%), control 3 of 46 (6.5%), day 28.
risk of death, 72.1% higher, RR 1.72, p = 0.55, treatment 11 of 98 (11.2%), control 3 of 46 (6.5%), day 21.
risk of death, 64.3% higher, RR 1.64, p = 0.72, treatment 7 of 98 (7.1%), control 2 of 46 (4.3%), day 14.
risk of death, 734.7% higher, RR 8.35, p = 0.18, treatment 5 of 98 (5.1%), control 0 of 46 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 7.
risk of mechanical ventilation, 37.2% higher, RR 1.37, p = 1.00, treatment 6 of 94 (6.4%), control 2 of 43 (4.7%), day 28.
risk of ICU admission, 31.5% higher, RR 1.31, p = 0.77, treatment 12 of 89 (13.5%), control 4 of 39 (10.3%), day 28.
risk of 7-point scale, 41.0% higher, OR 1.41, p = 0.32, treatment 98, control 46, day 14, primary outcome, RR approximated with OR.
Torres, 2/4/2021, Randomized Controlled Trial, Spain, trial NCT04547127 (history). 200 patient RCT with results unknown and over 5 years late.
Torres (B), 9/30/2020, Double Blind Randomized Controlled Trial, Mexico, trial NCT04542967 (history) (PC-COVID-HCM). 150 patient RCT with results unknown and over 6 years late.
van den Berg, 2/15/2022, Randomized Controlled Trial, placebo-controlled, South Africa, peer-reviewed, 30 authors, study period 30 September, 2020 - 14 January, 2021, average treatment delay 9.0 days, trial NCT04516811 (history) (PROTECT-Patient). risk of death, 17.0% lower, RR 0.83, p = 0.65, treatment 11 of 52 (21.2%), control 13 of 51 (25.5%), NNT 23, day 28.
risk of mechanical ventilation, 67.3% lower, RR 0.33, p = 0.36, treatment 1 of 52 (1.9%), control 3 of 51 (5.9%), NNT 25.
risk of no improvement, 5.4% lower, RR 0.95, p = 1.00, treatment 16 of 47 (34.0%), control 18 of 50 (36.0%), NNT 51, day 28.
risk of no hospital discharge, 3.0% higher, RR 1.03, p = 1.00, treatment 18 of 46 (39.1%), control 19 of 50 (38.0%), day 28.
Zuluaga, 12/30/2020, Single Blind Randomized Controlled Trial, Colombia, trial NCT04385186 (history). Estimated 60 patient RCT with results unknown and over 5 years late.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
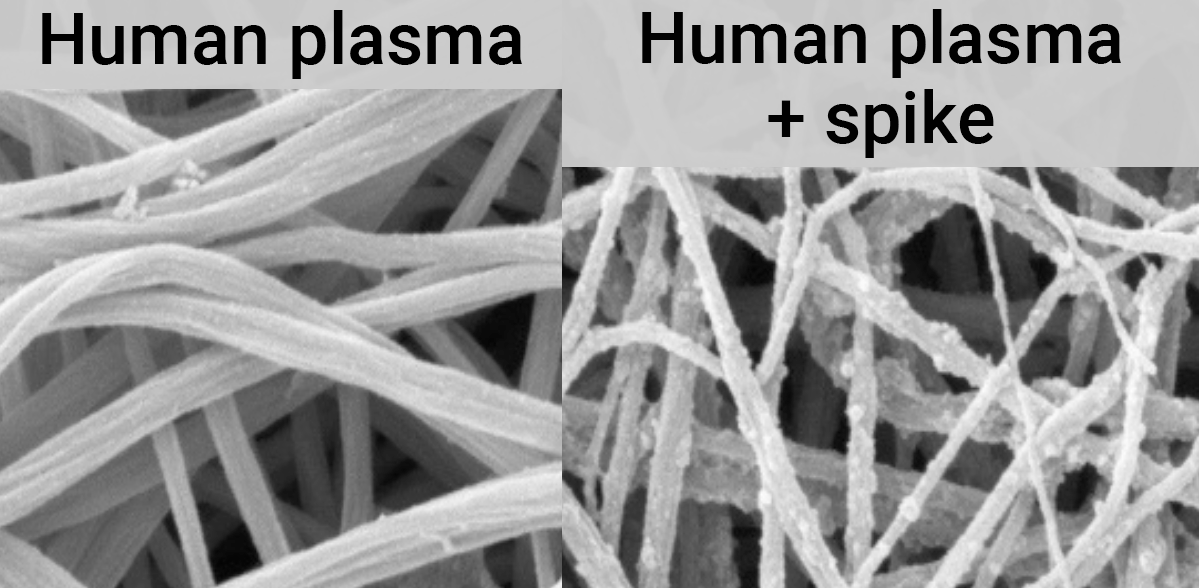
Cao, 11/11/2025, Randomized Controlled Trial, China, peer-reviewed, 22 authors, study period June 2023 - February 2024. risk of death, 224.1% higher, RR 3.24, p = 0.04, treatment 36, control 36, day 365.
risk of severe case, no change, RR 1.00, p = 1.00, treatment 1 of 36 (2.8%), control 1 of 36 (2.8%), day 120.
risk of case, 40.2% higher, RR 1.40, p = 0.46, treatment 36, control 36, day 120.
Viral infection and replication involves attachment, entry, uncoating and release, genome replication and transcription, translation and protein processing, assembly and budding, and release. Each step can be disrupted by therapeutics.
When administered late in infection, HCQ may enhance viral egress by further increasing lysosomal pH beyond the effect of ORF3a's water channel activity, thereby promoting lysosomal exocytosis, inactivating degradative enzymes, and facilitating the release of SARS-CoV-2 particles into the extracellular environment138,139. Research also suggests potential cardioprotective effects at lower doses, but cardiotoxicity with excessive dosage140. Bobrowski et al. also indicate negative effects if HCQ and remdesivir are combined.
Peters (B) et al. is subject to confounding by calendar-time (SOC evolved rapidly early in the pandemic, the linear covariate does not reflect non-linear SOC changes and hospital specific effects), hospital type (non-treatment hospitals were tertiary university centers), confounding by indication (4/7 hospitals initiated treatment on deterioration), immortal-time bias for as-treated (exposure assigned after baseline), significant differences for other experimental treatments, potential overadjustment from collider bias (steroid use and indication bias), limited baseline severity information, differences in hospice referral propensity across hospitals, unadjusted difference in time from onset to admission, difference in PCR positivity, and other factors. Mahévas et al. is subject to confounding by hospital (treatment highly dependent on the hospital, different SOC/ICU transfer practices, not included in PS), immortal time (only partly addressed in sensitivity analysis), co-treatment differences, calendar-time (SOC evolved rapidly early in the pandemic), binary coding for age (age ≥65 despite steep age-risk gradient), residual imbalance (variables dropped from PS), a composite outcome dependent on hospital triage/capacity, and other factors.