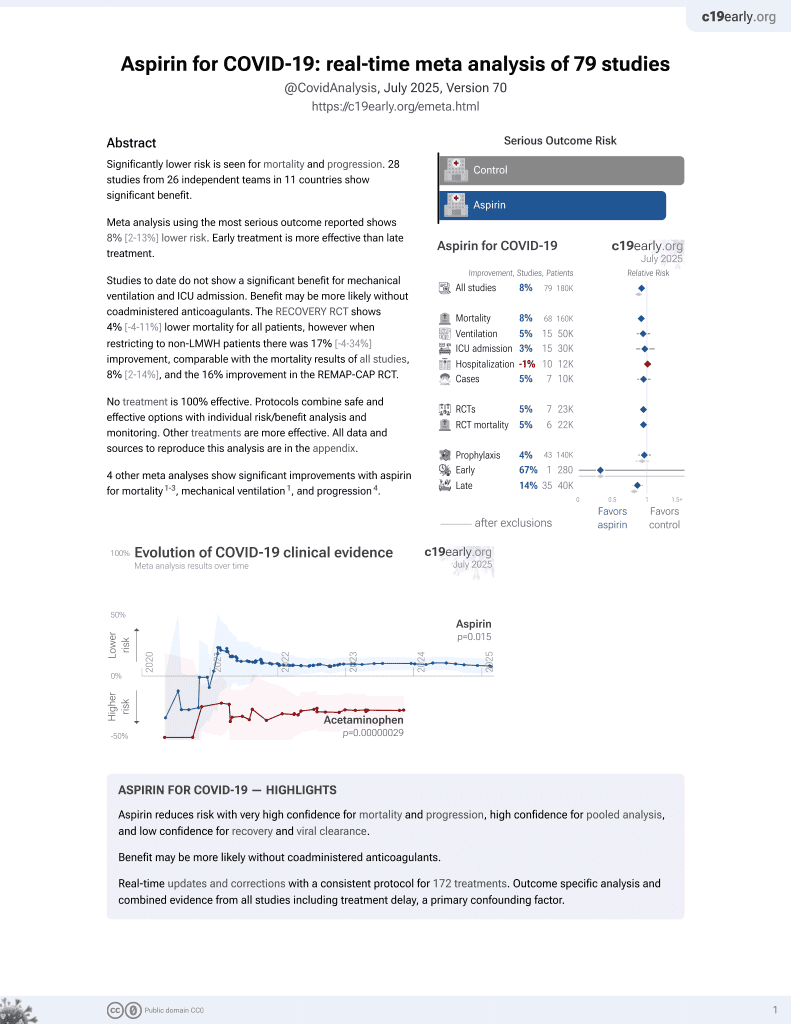
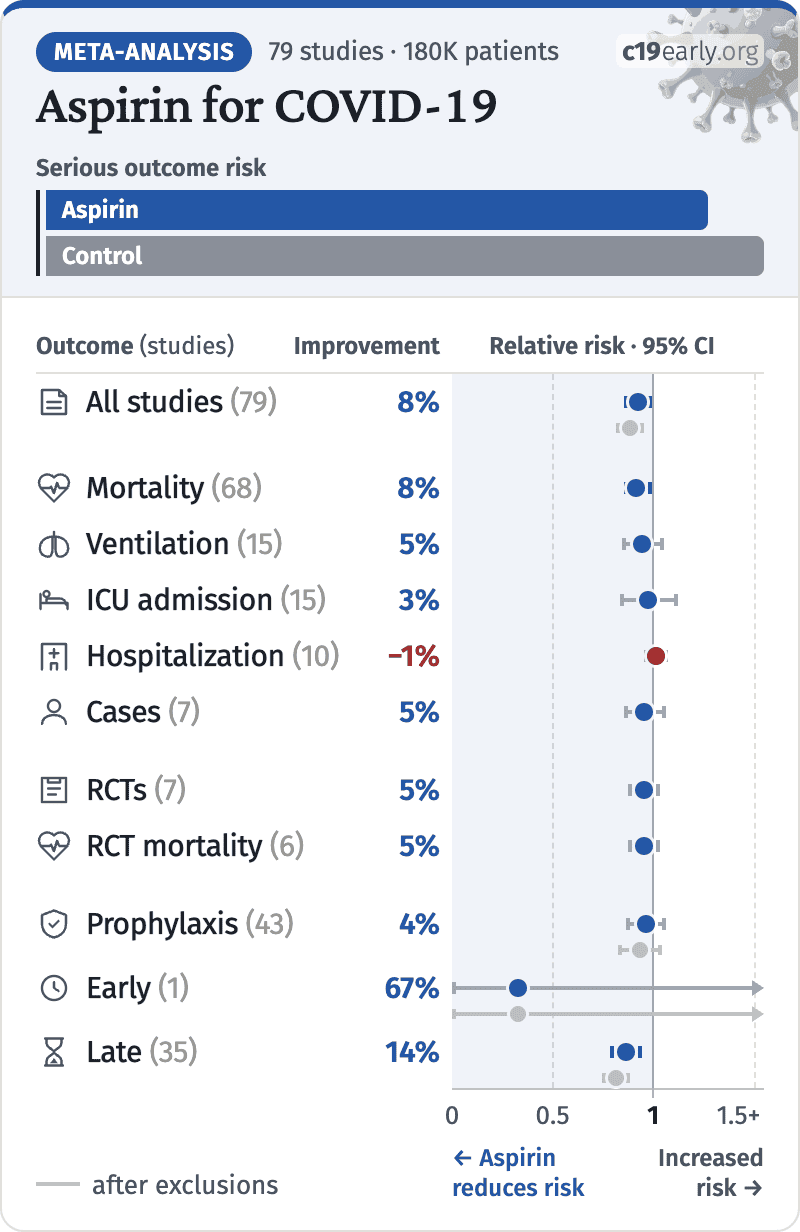
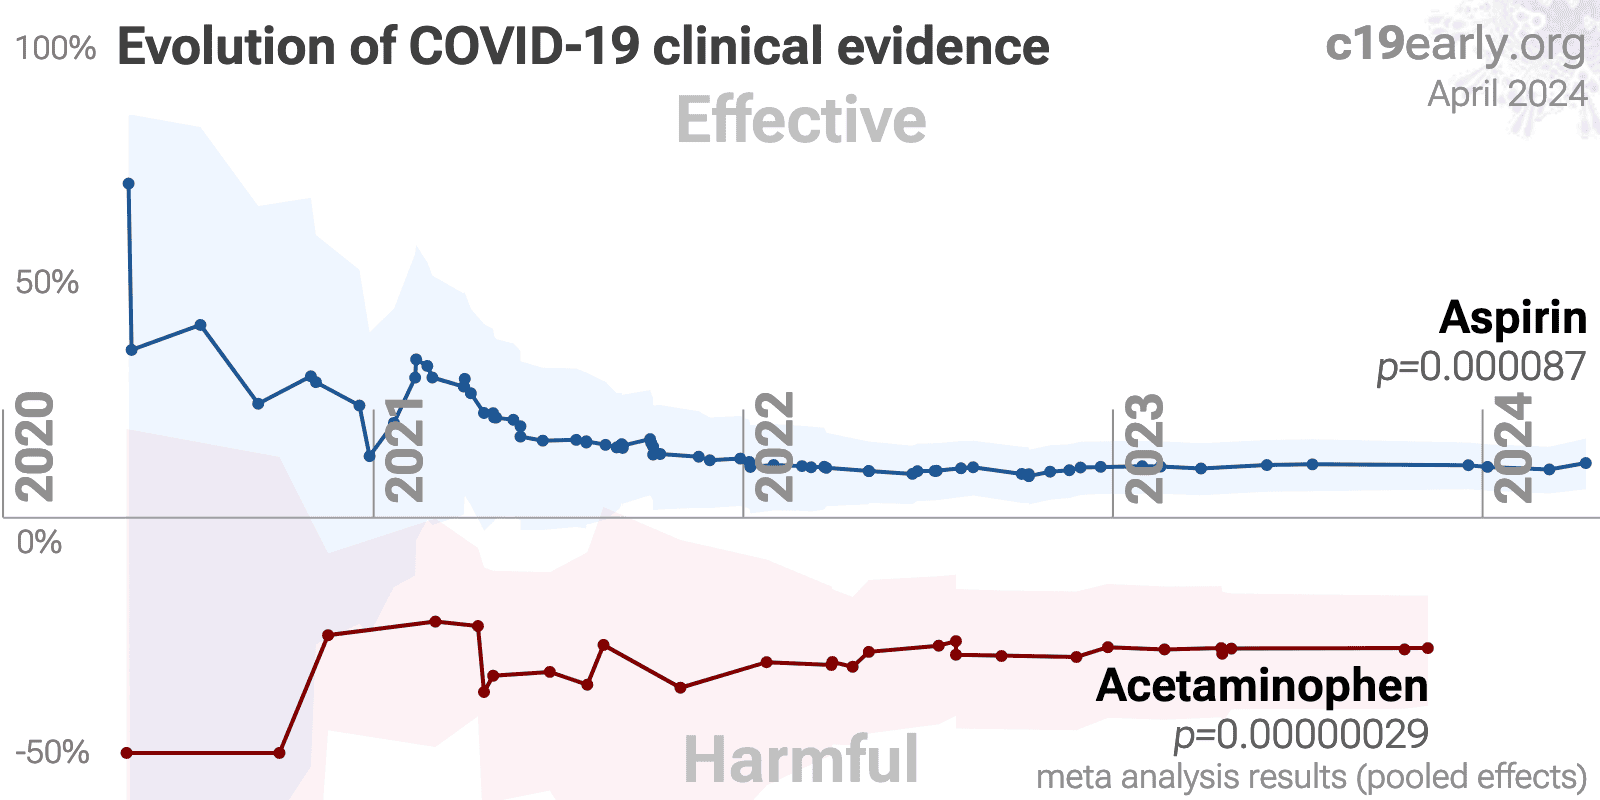
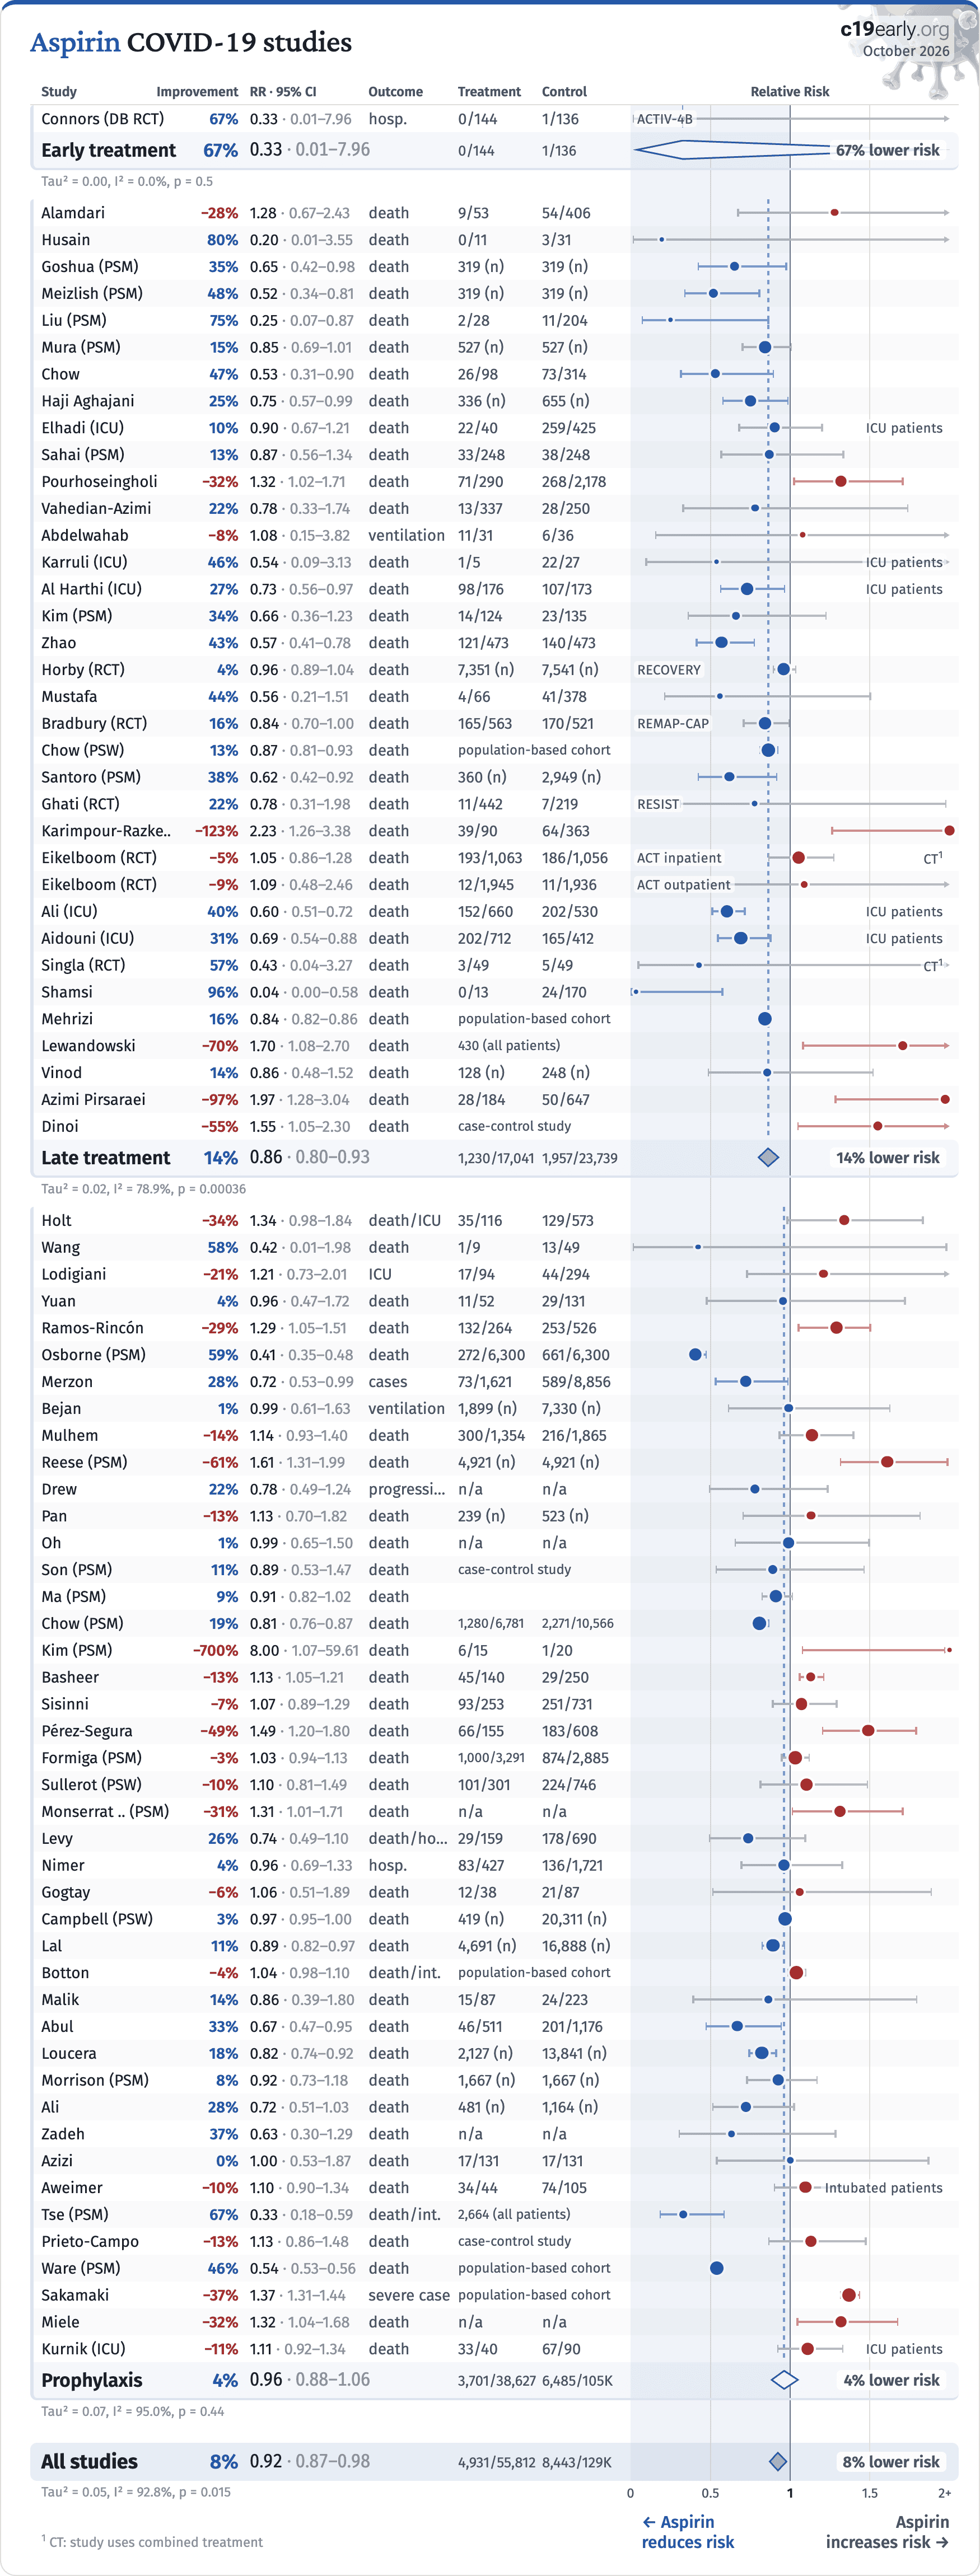
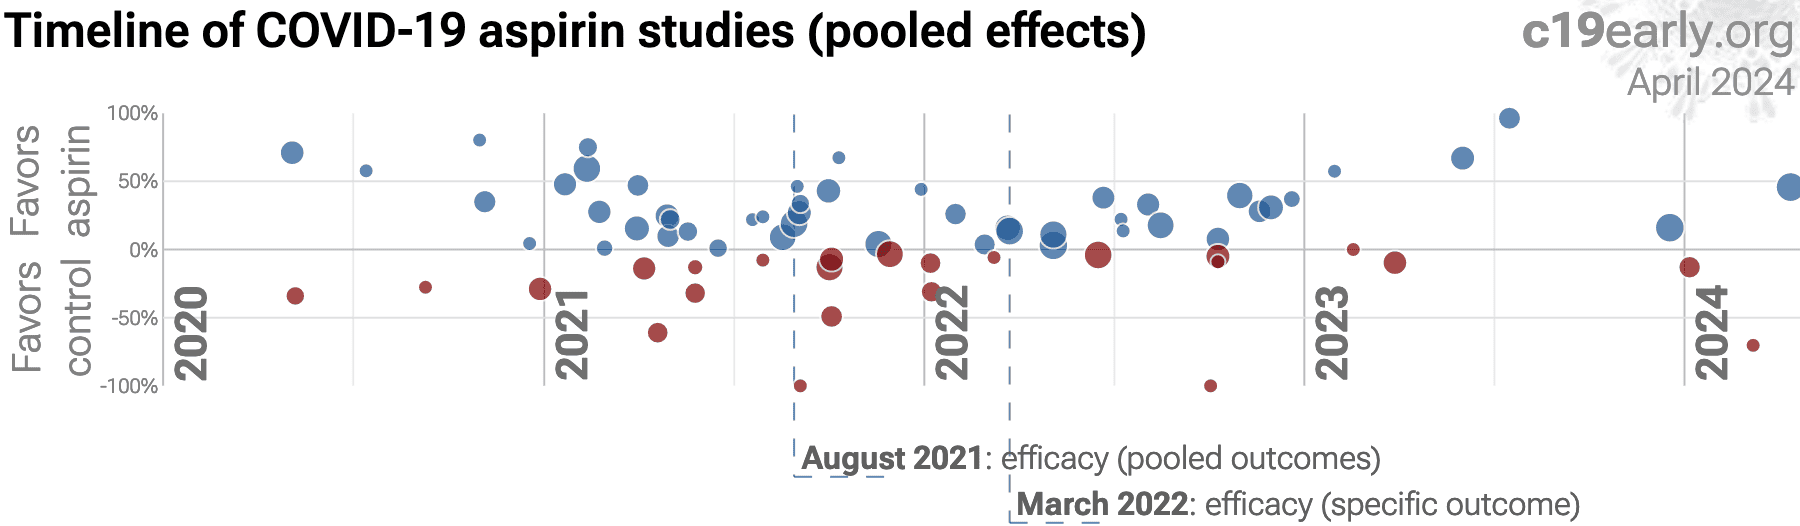
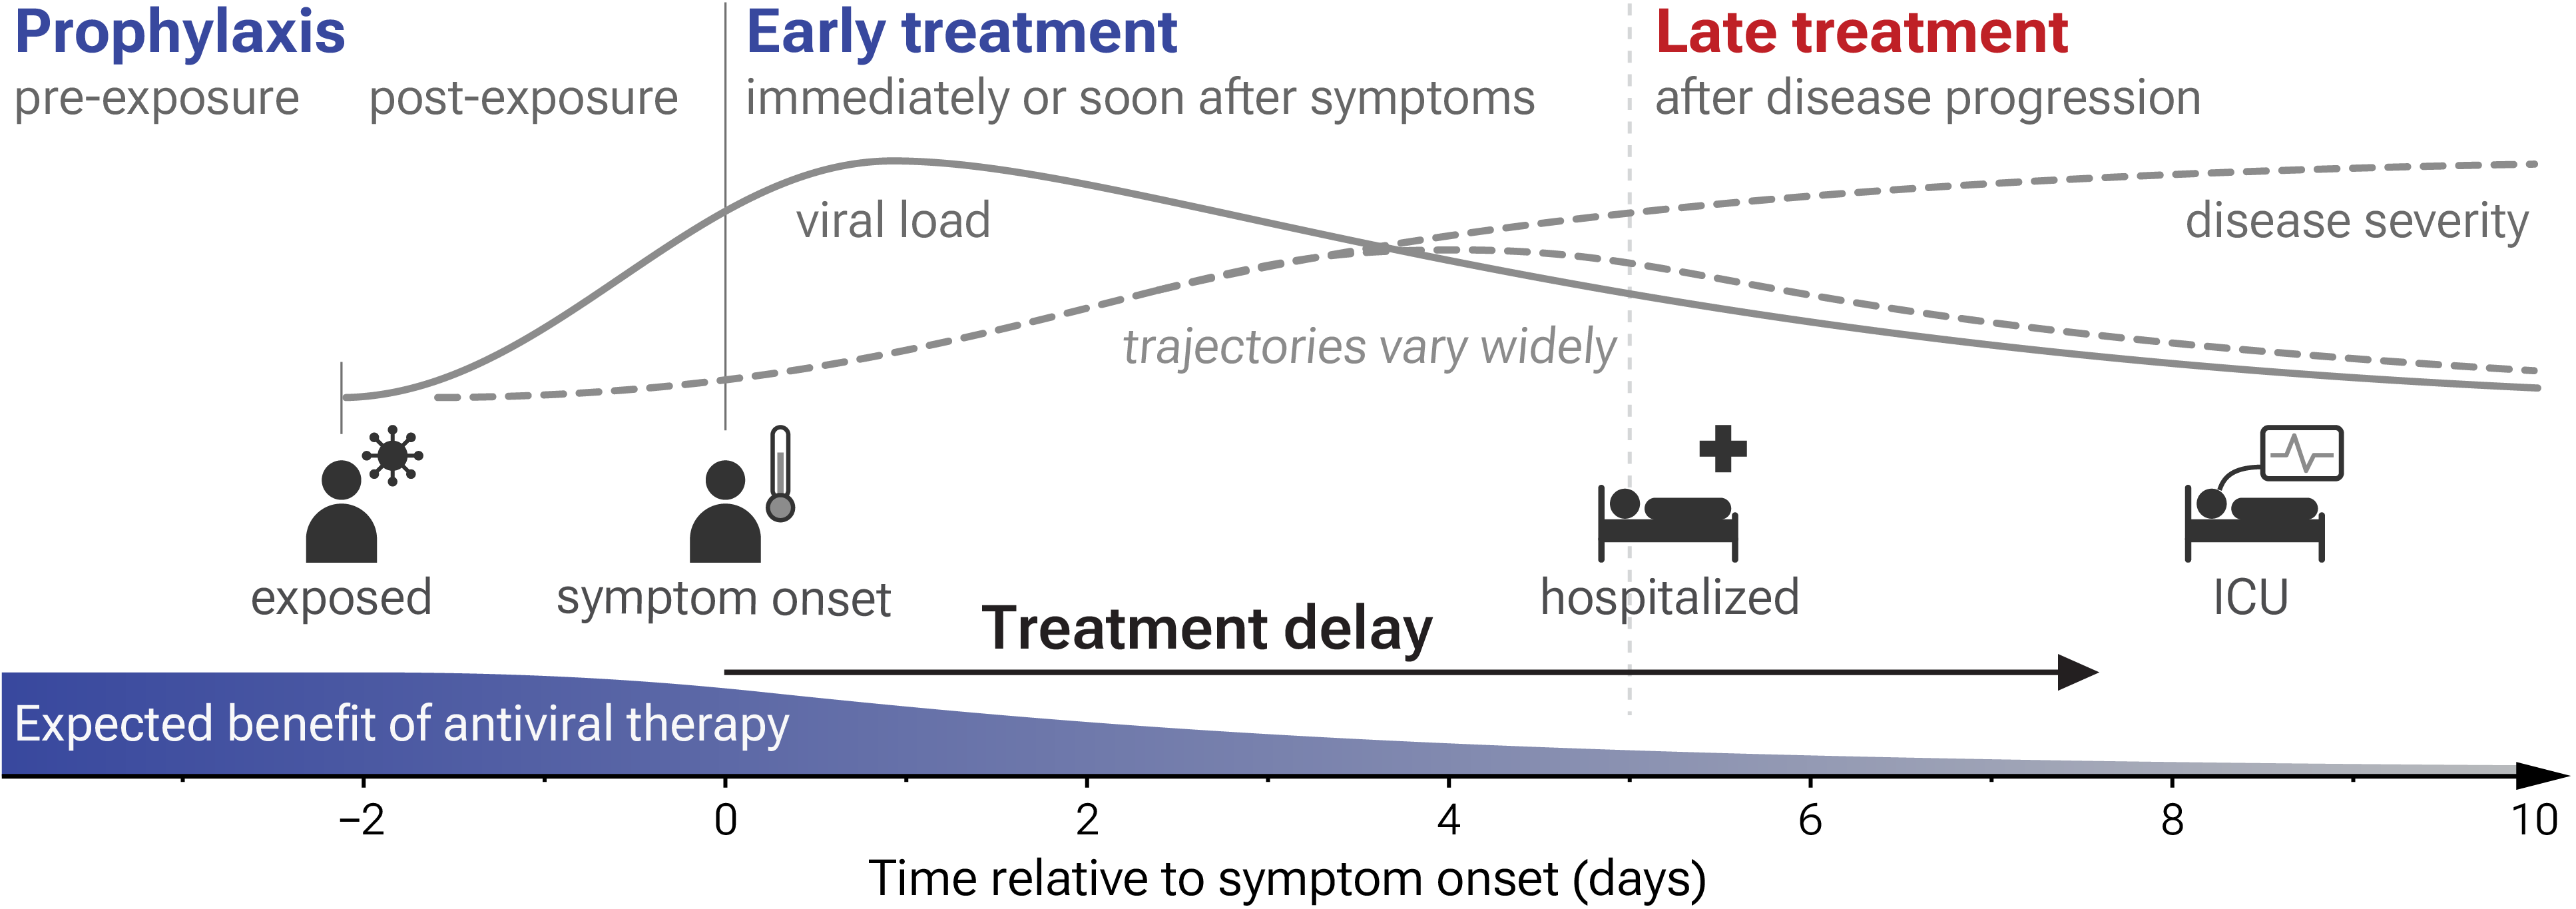
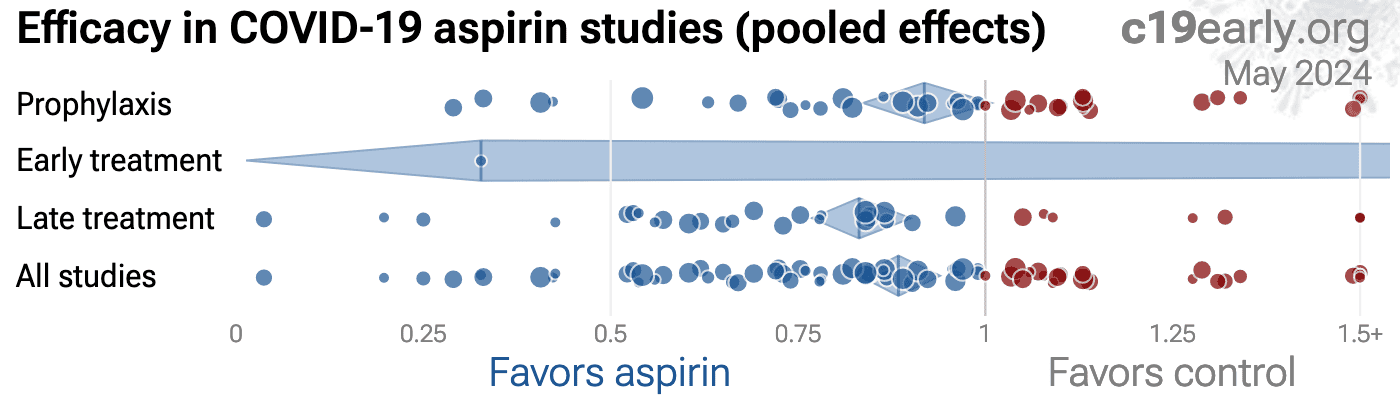
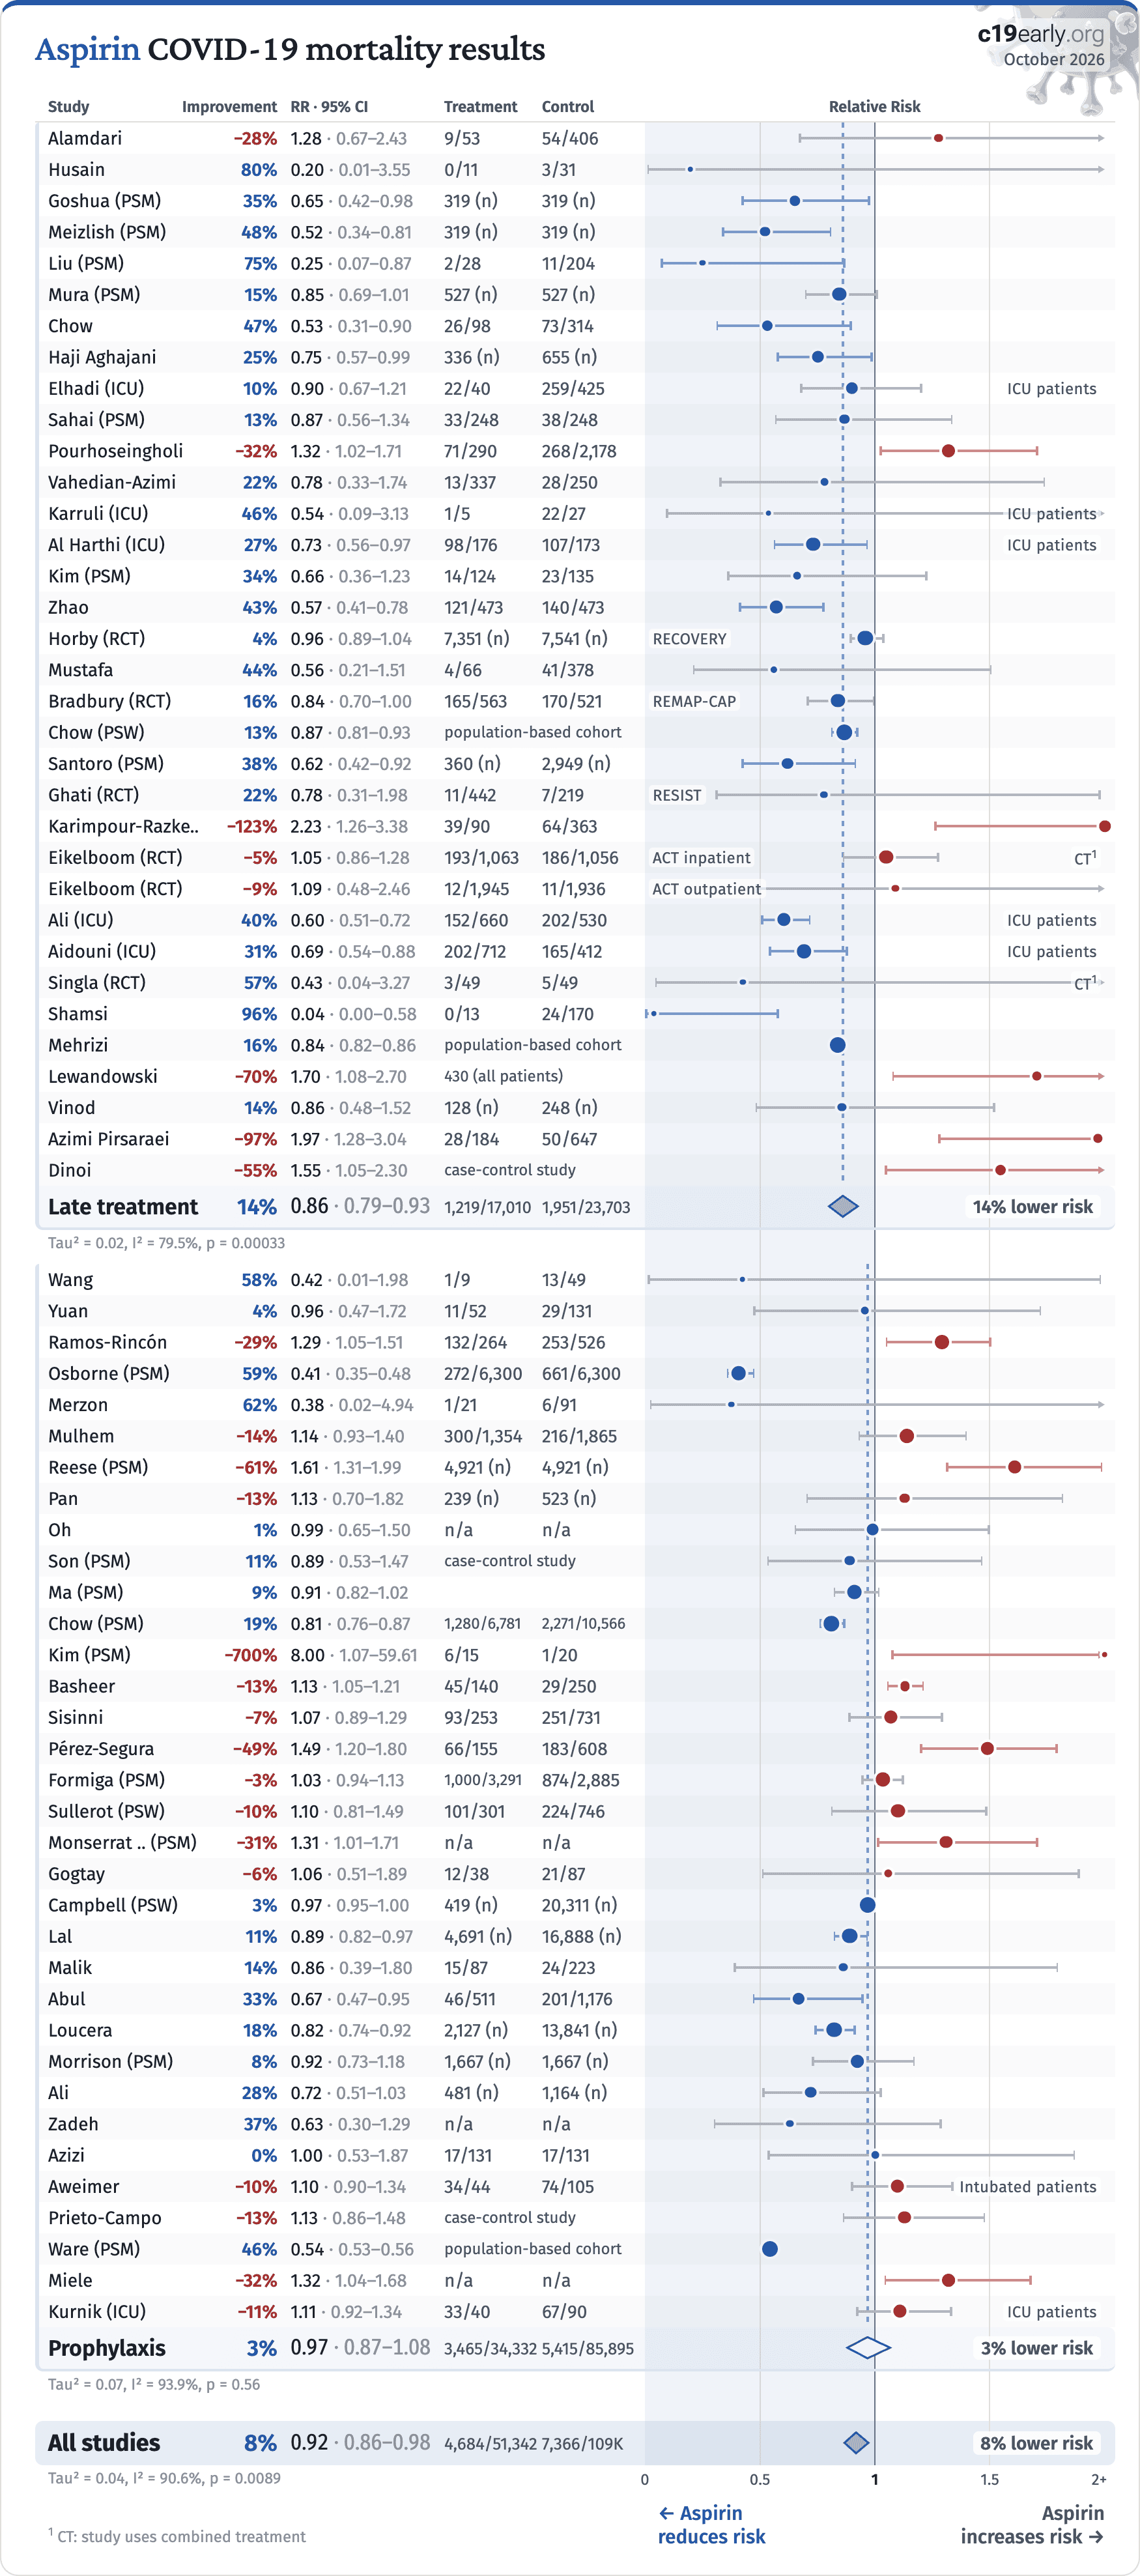
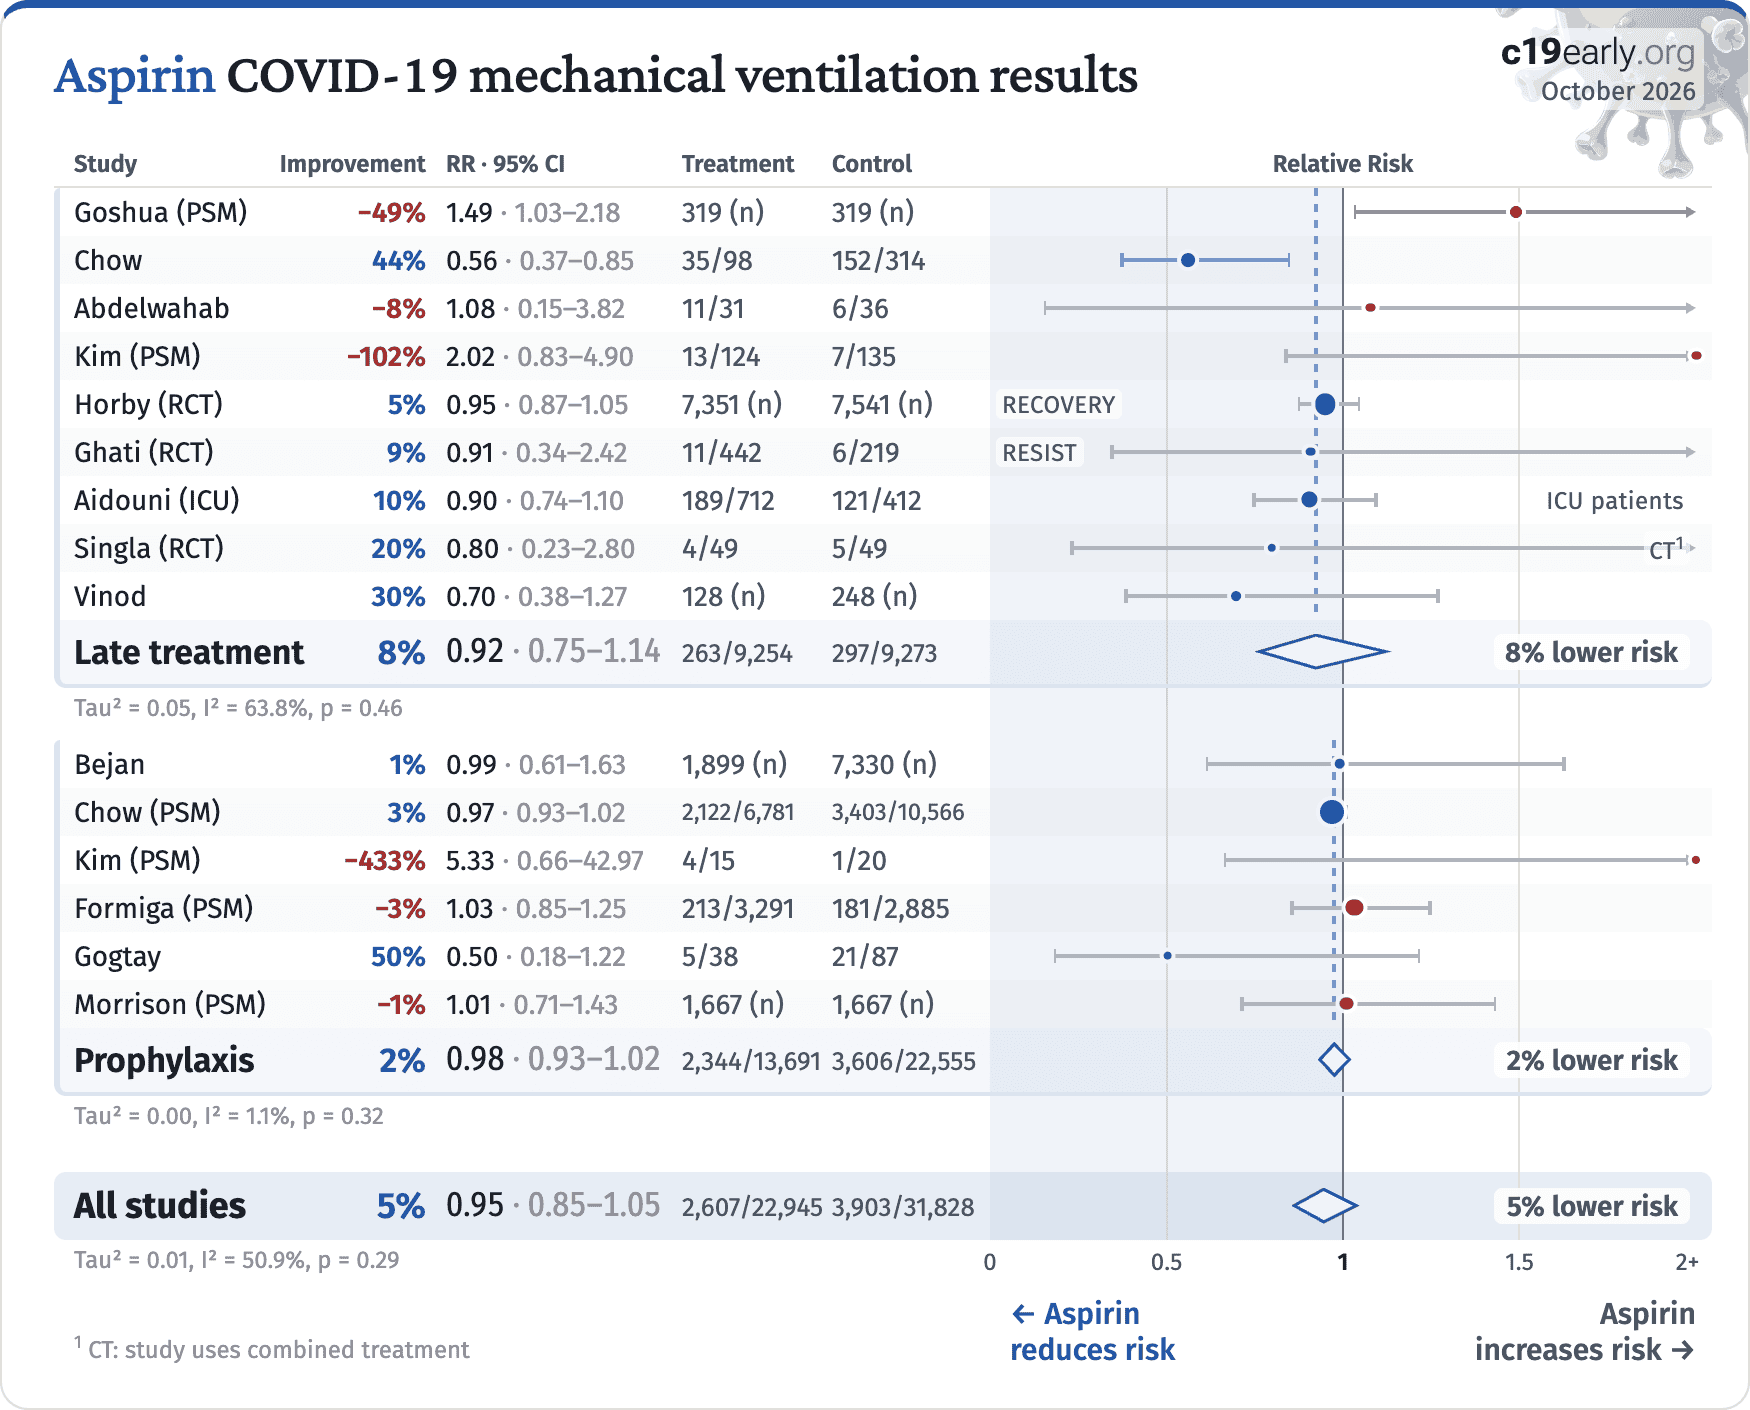
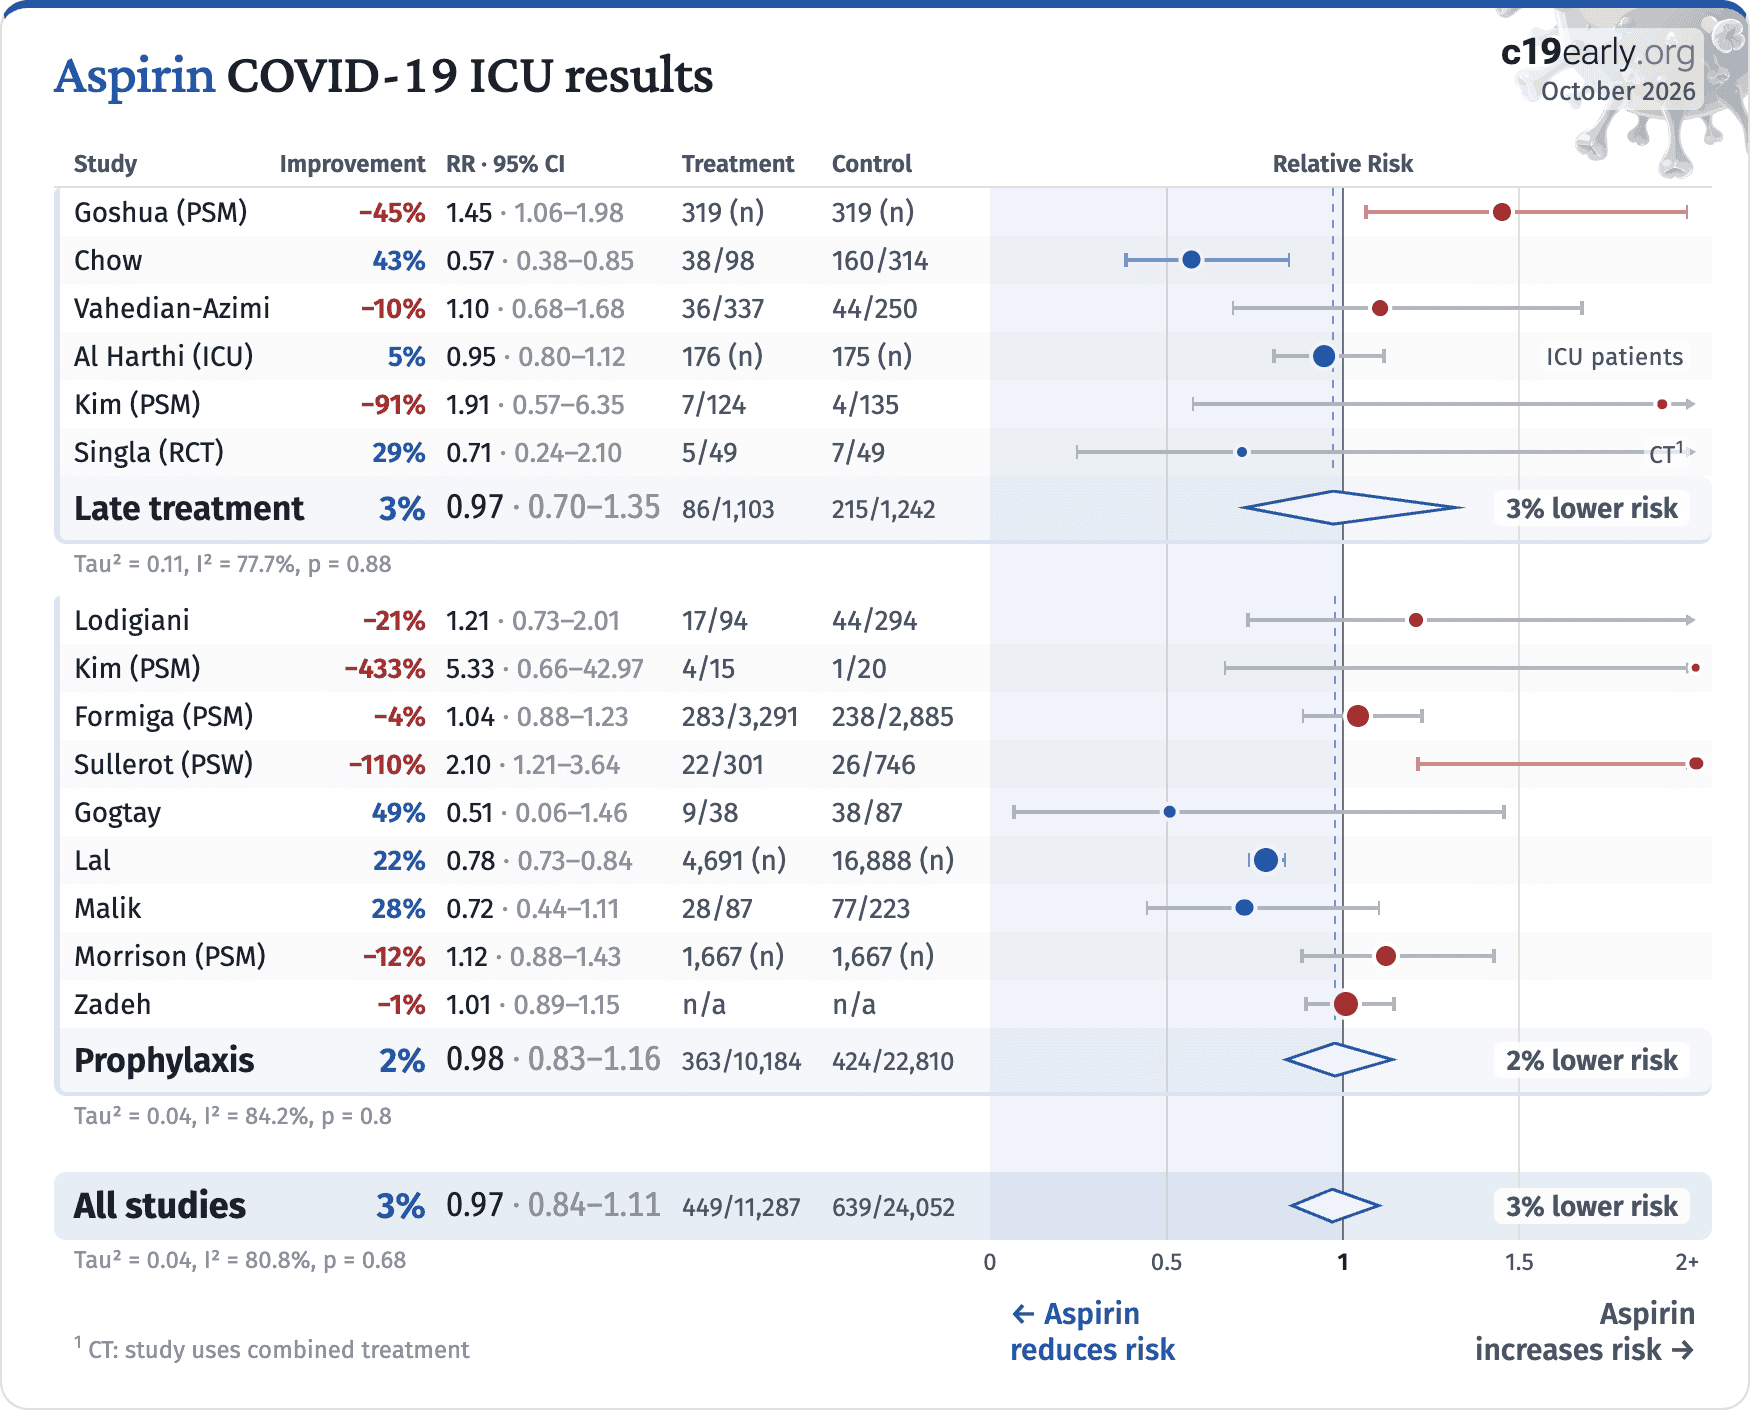
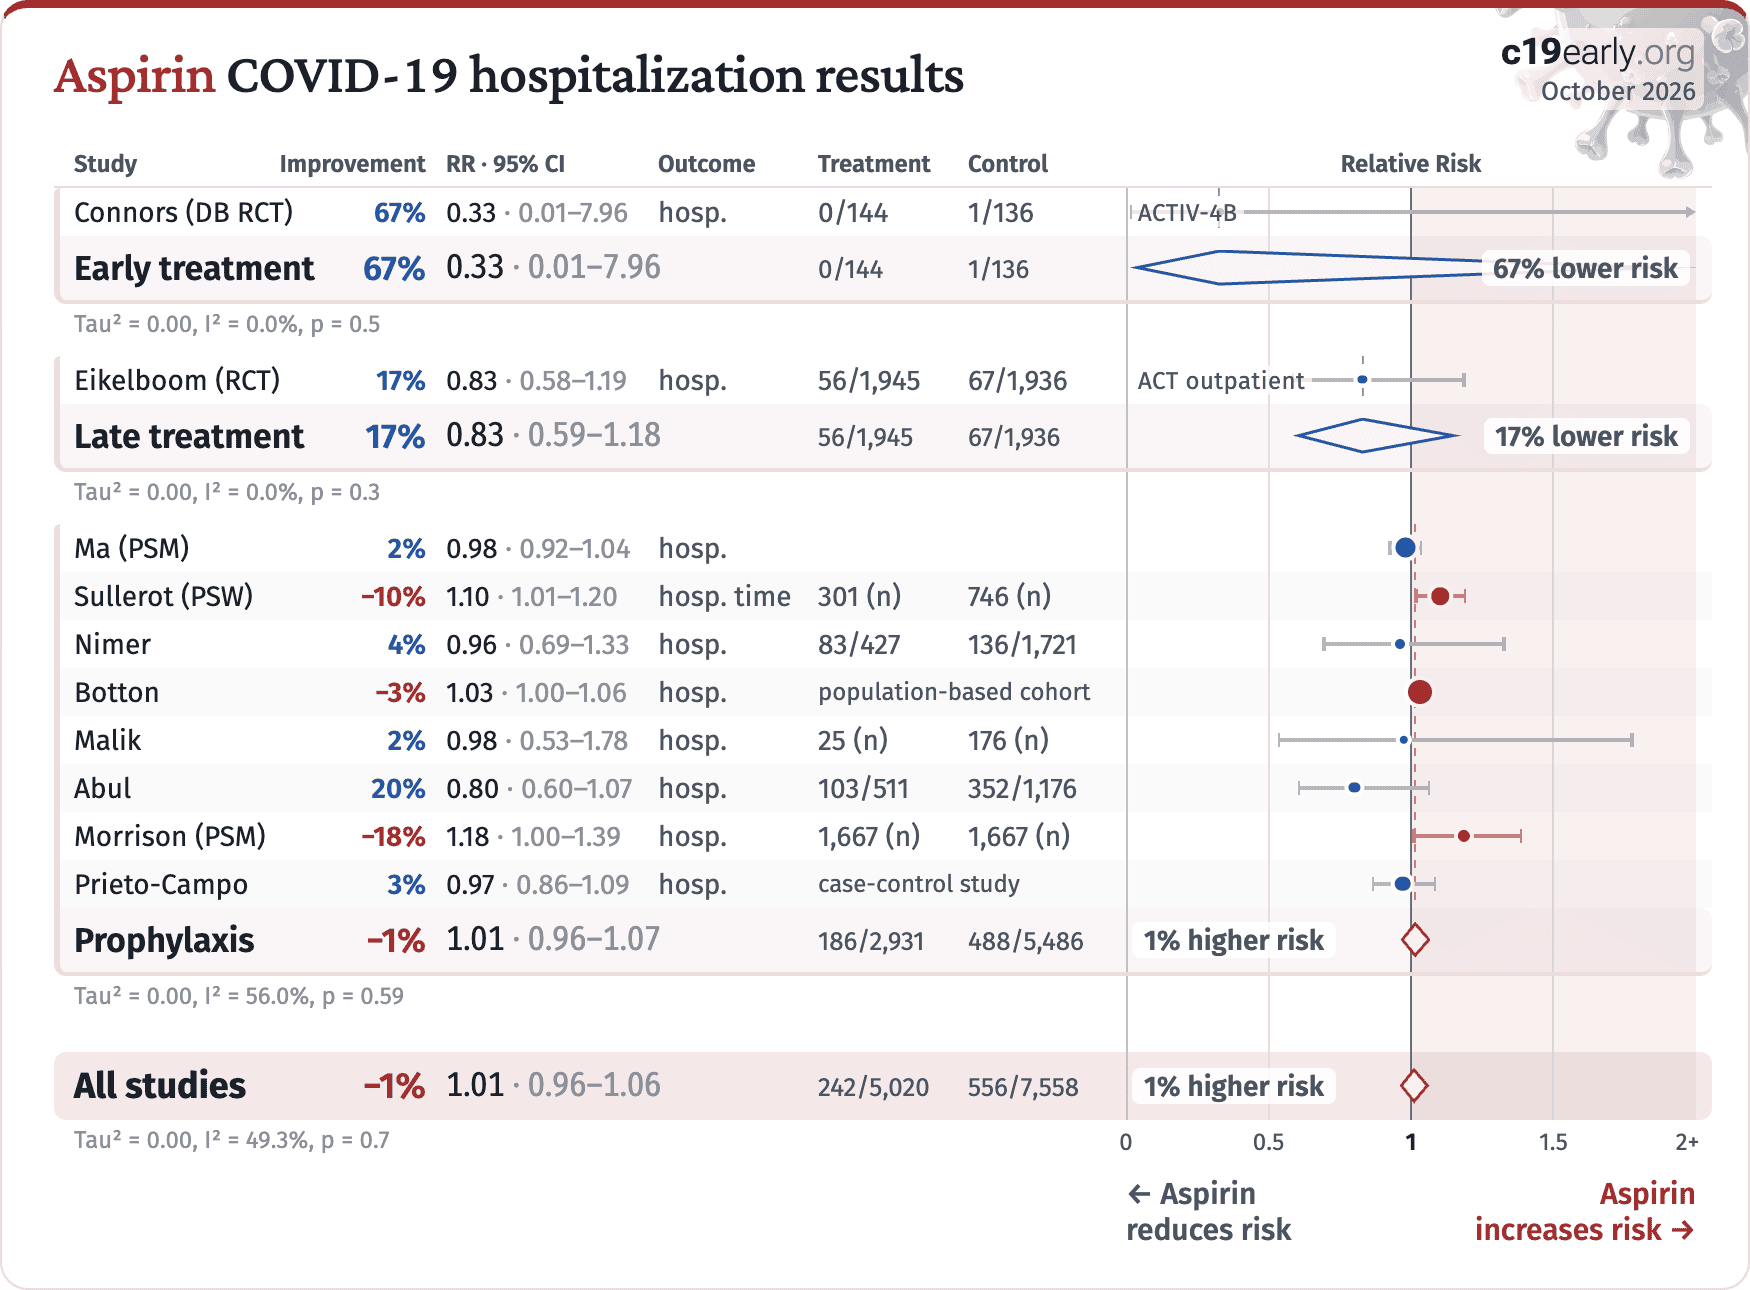
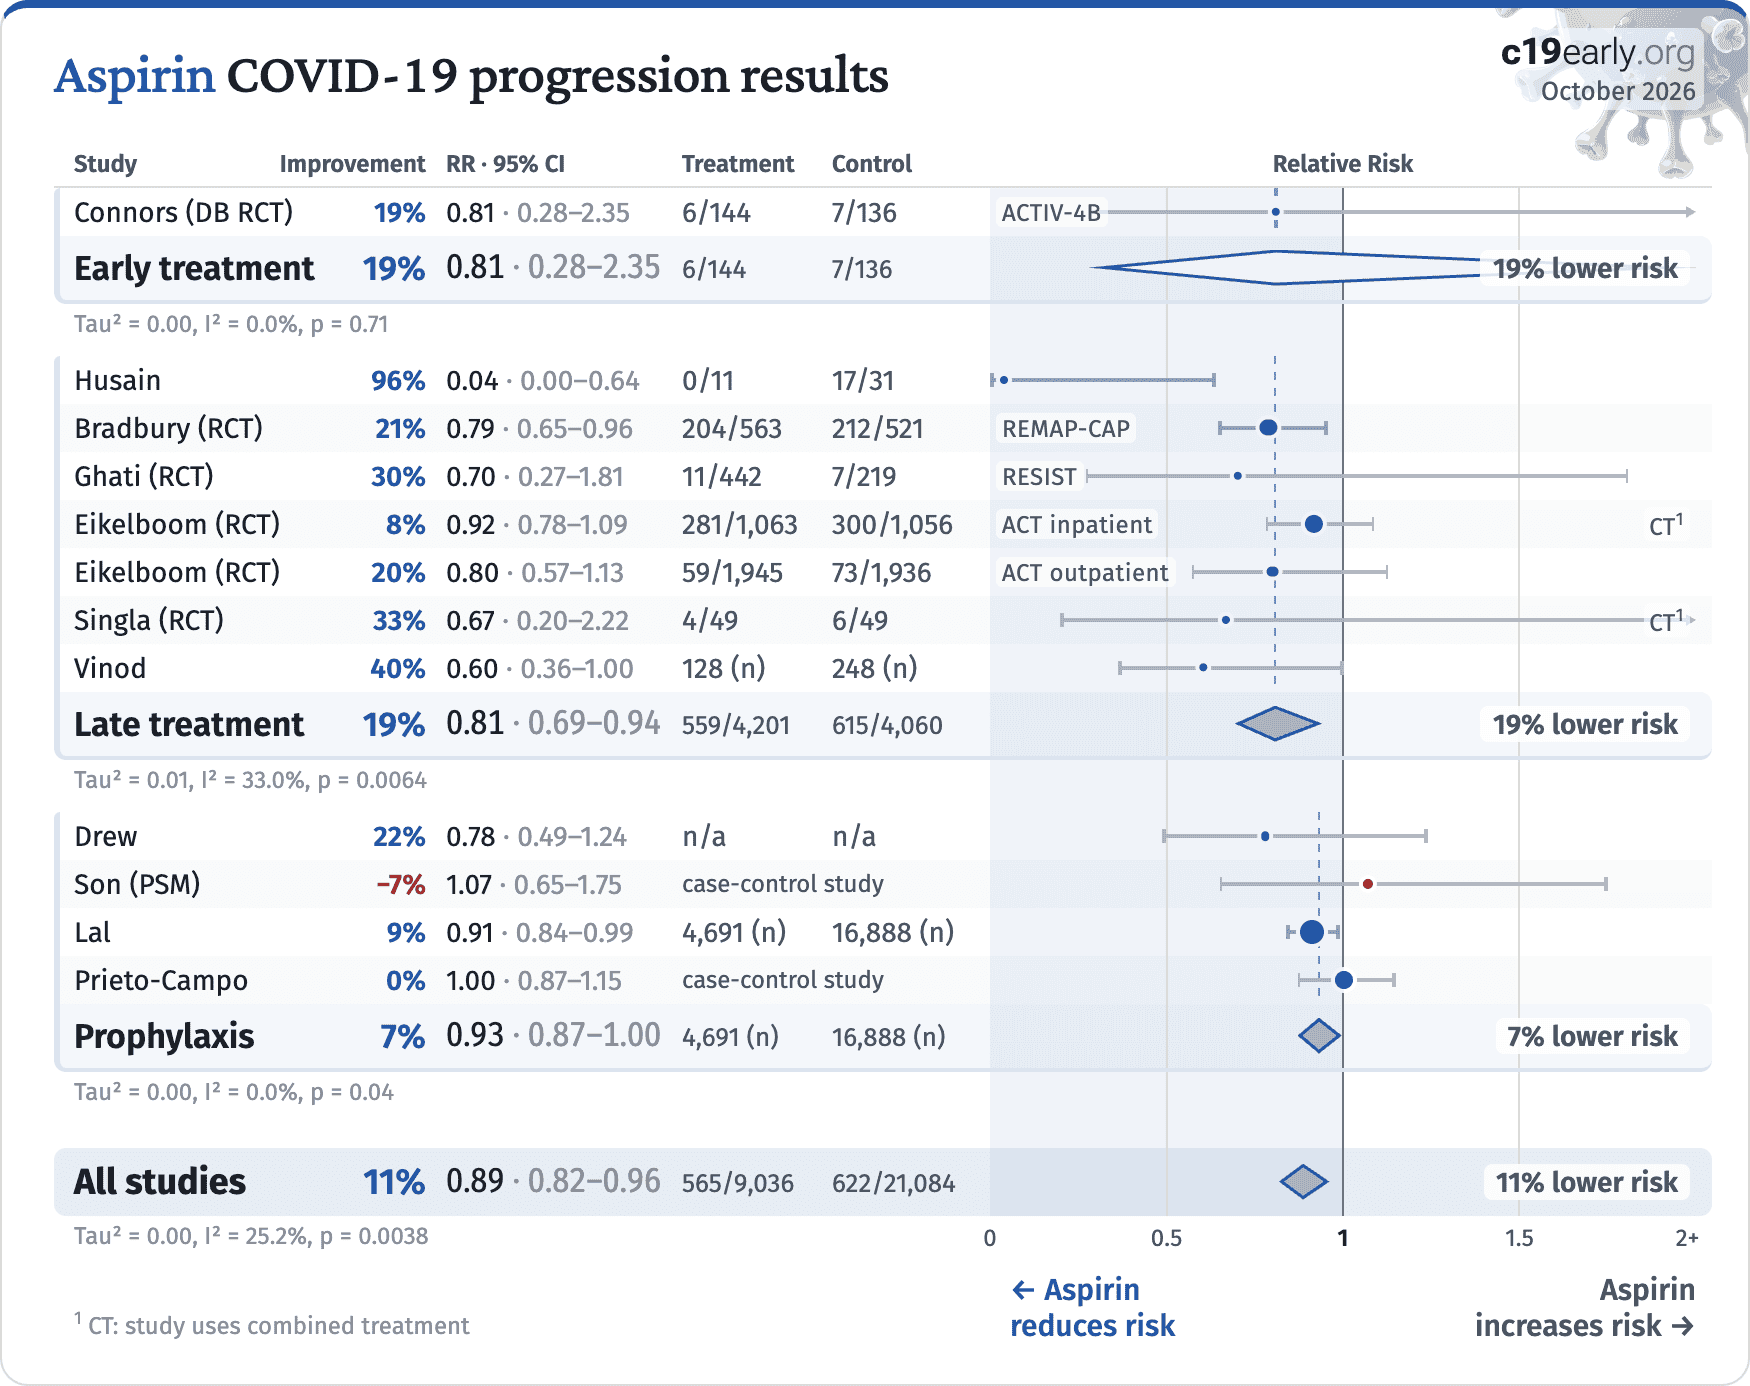
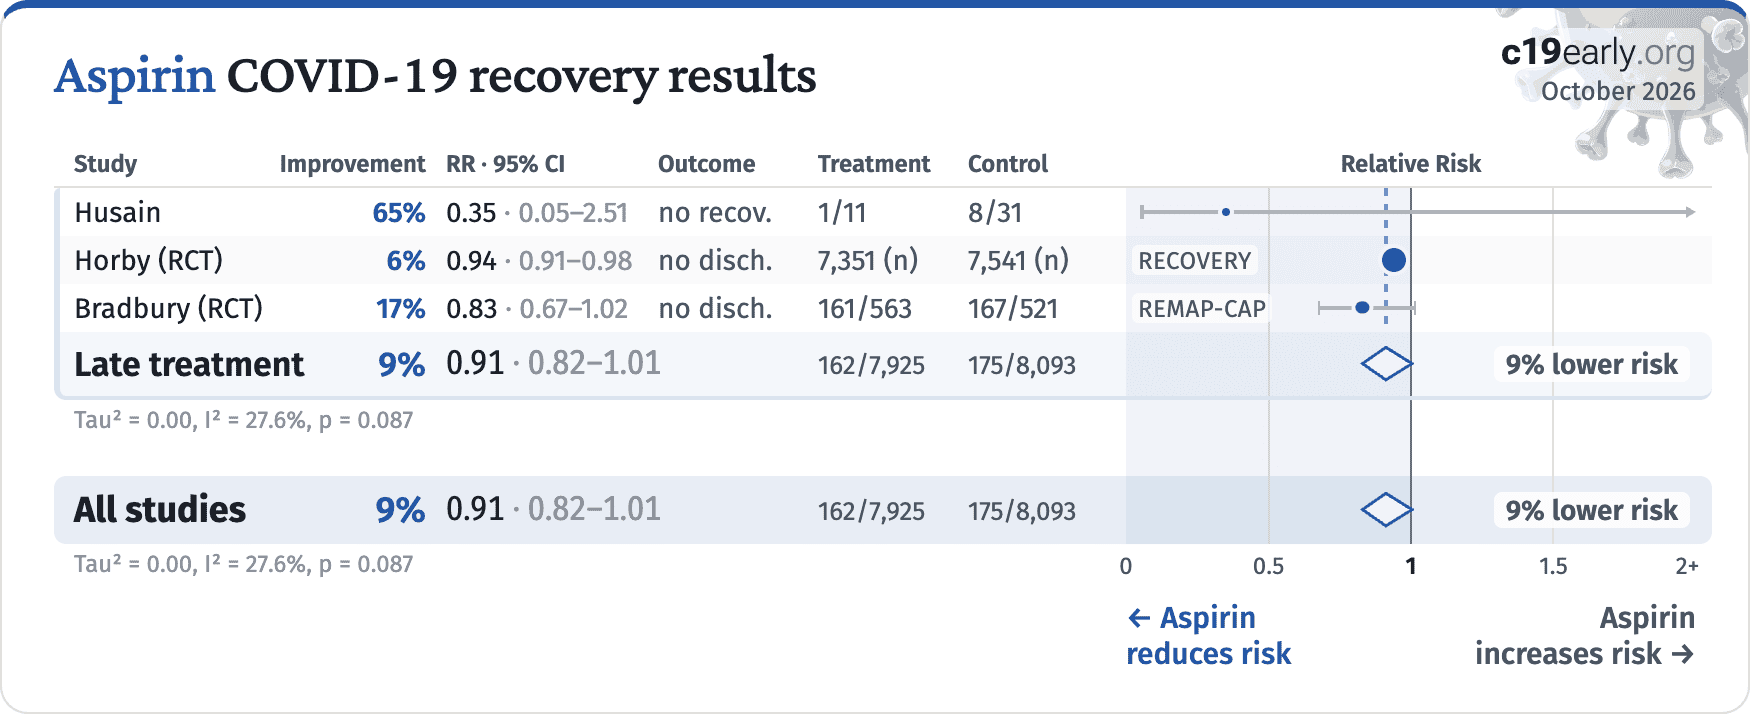
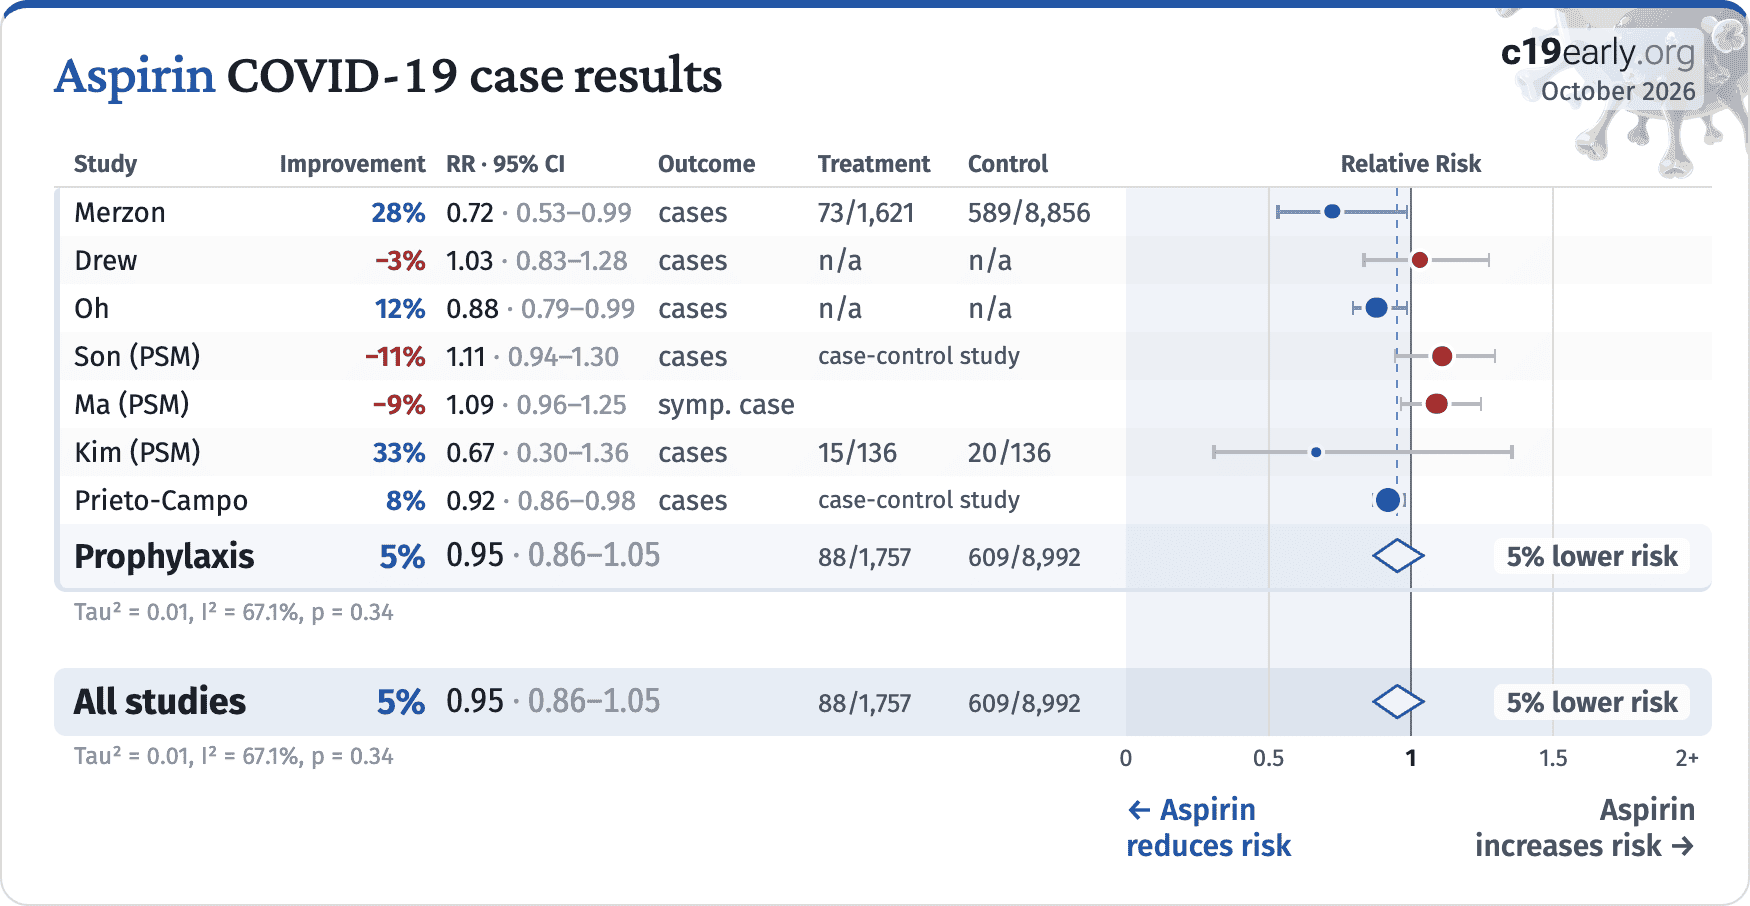
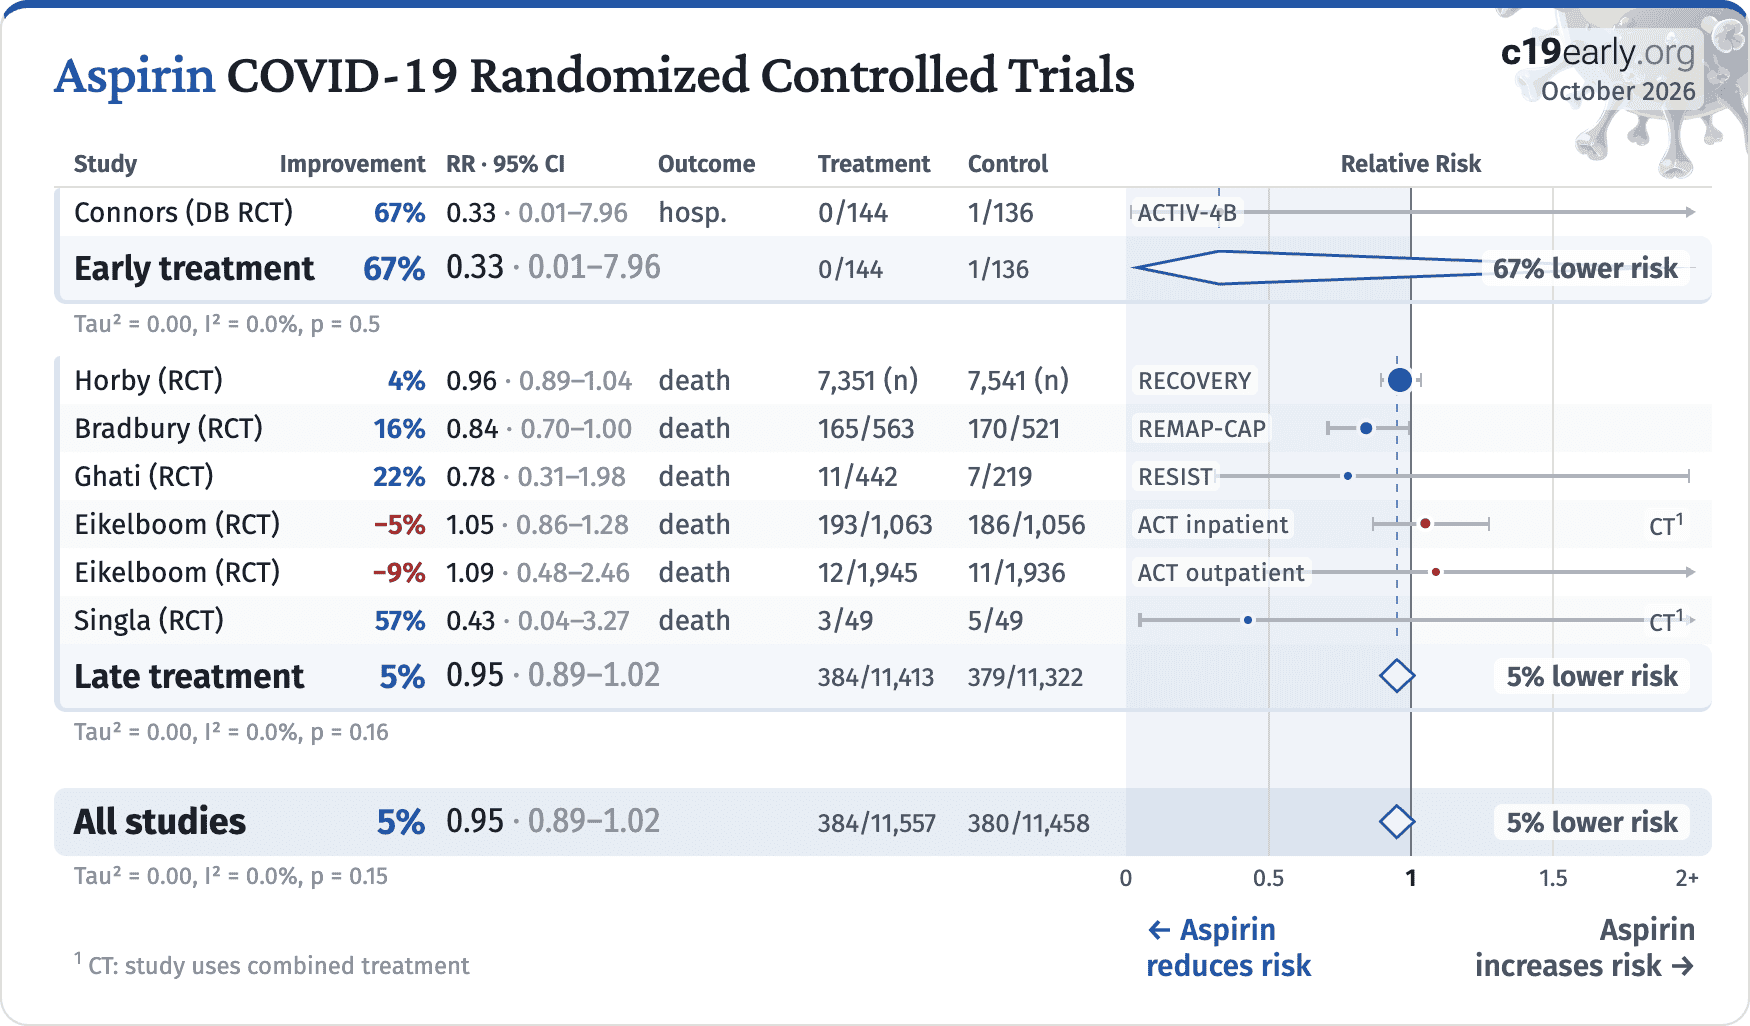
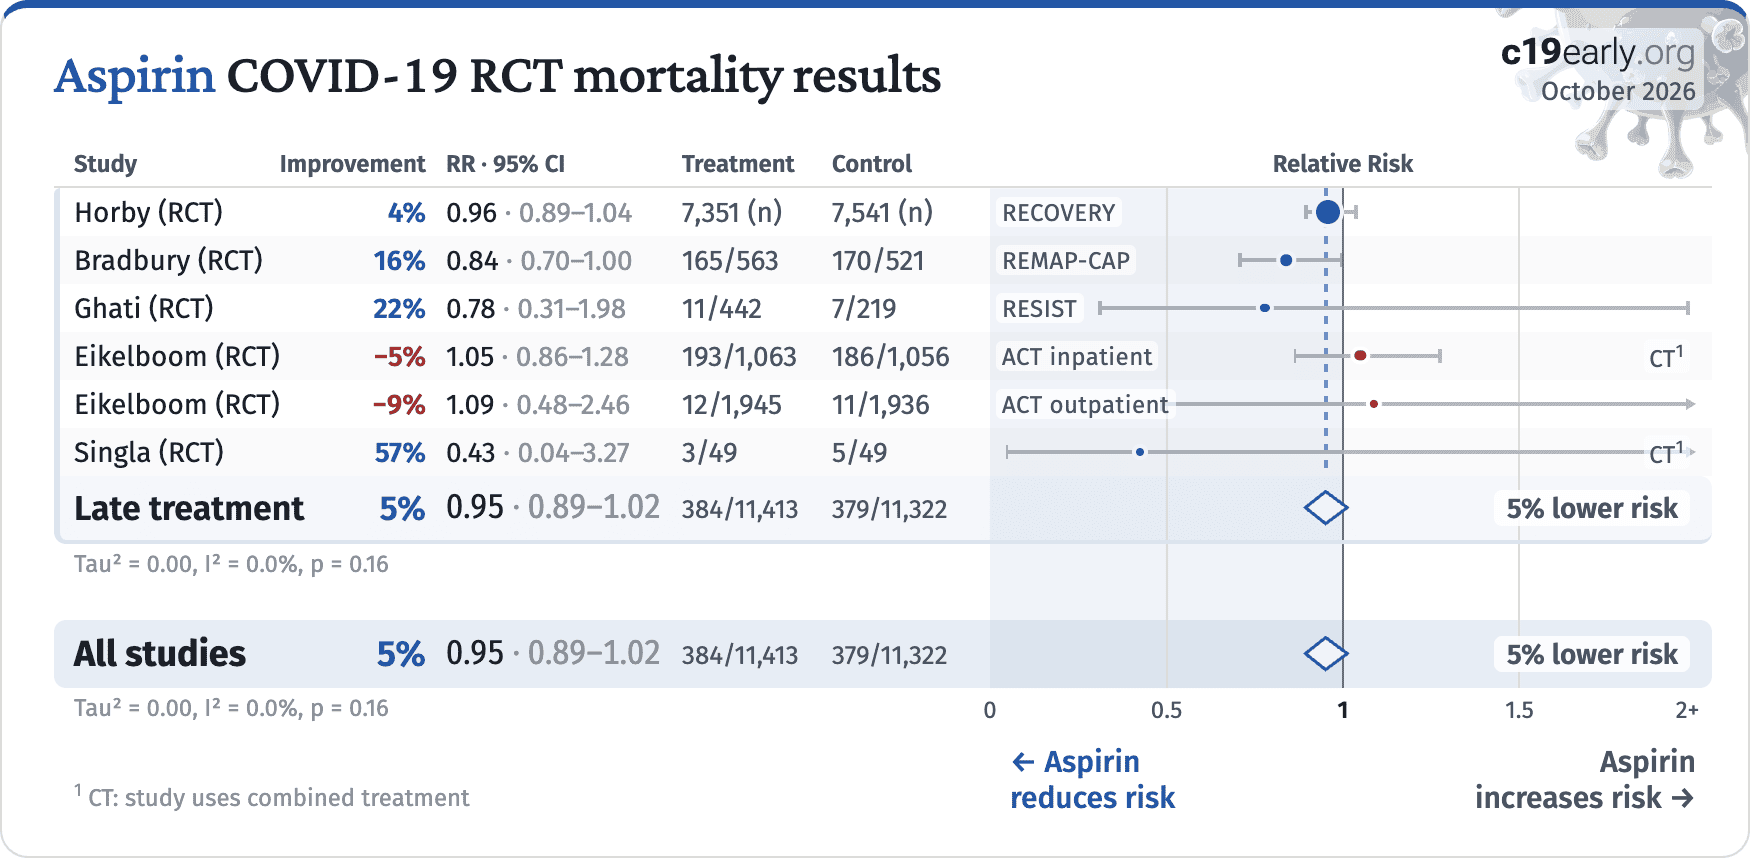
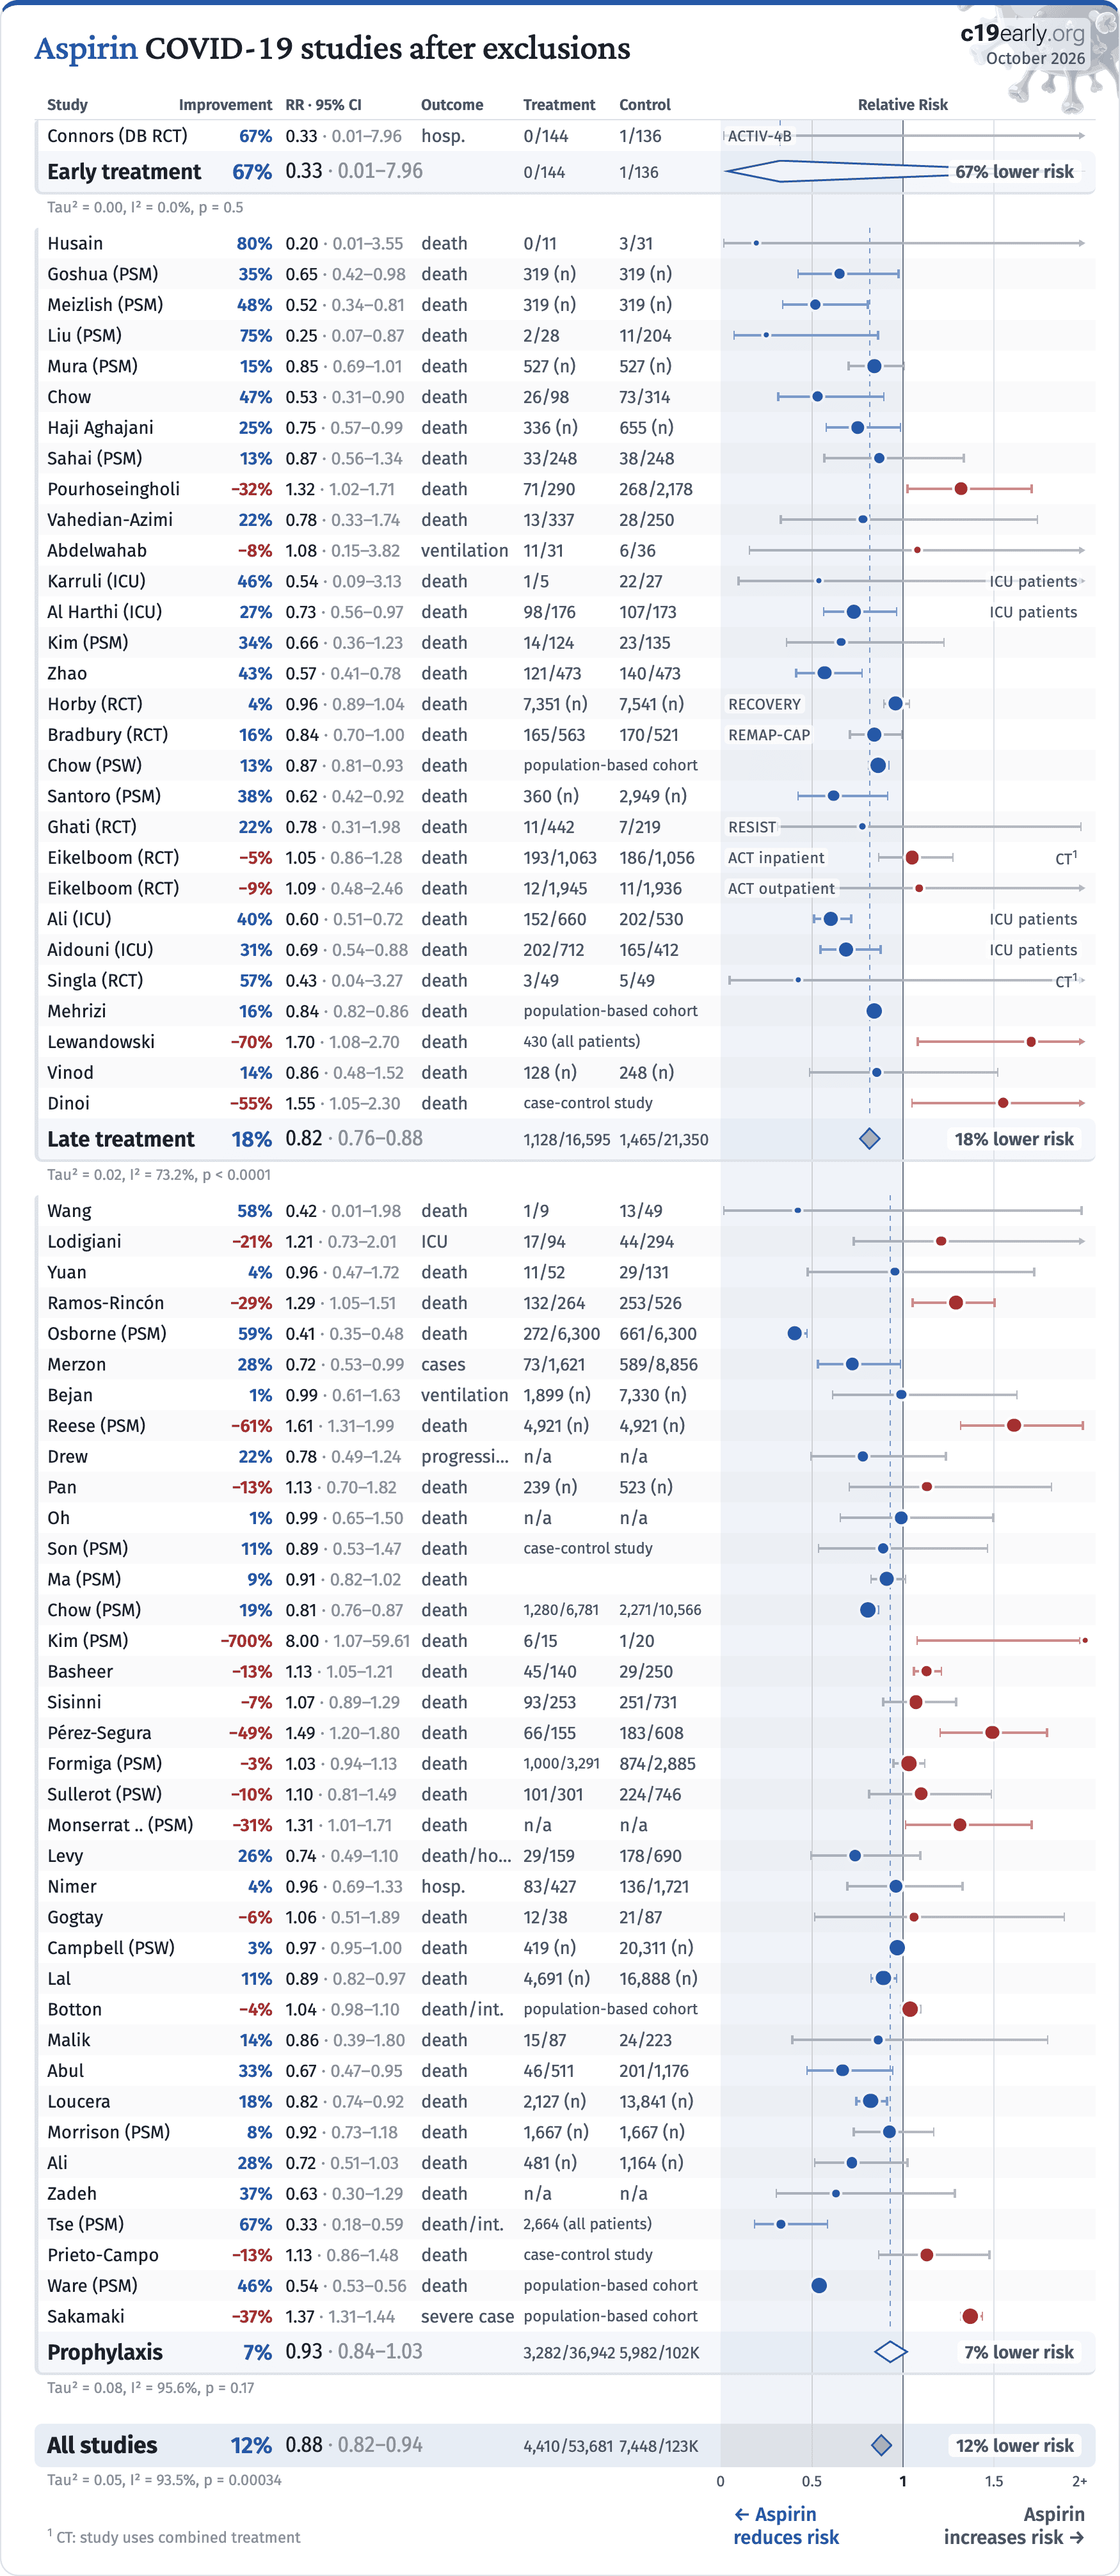
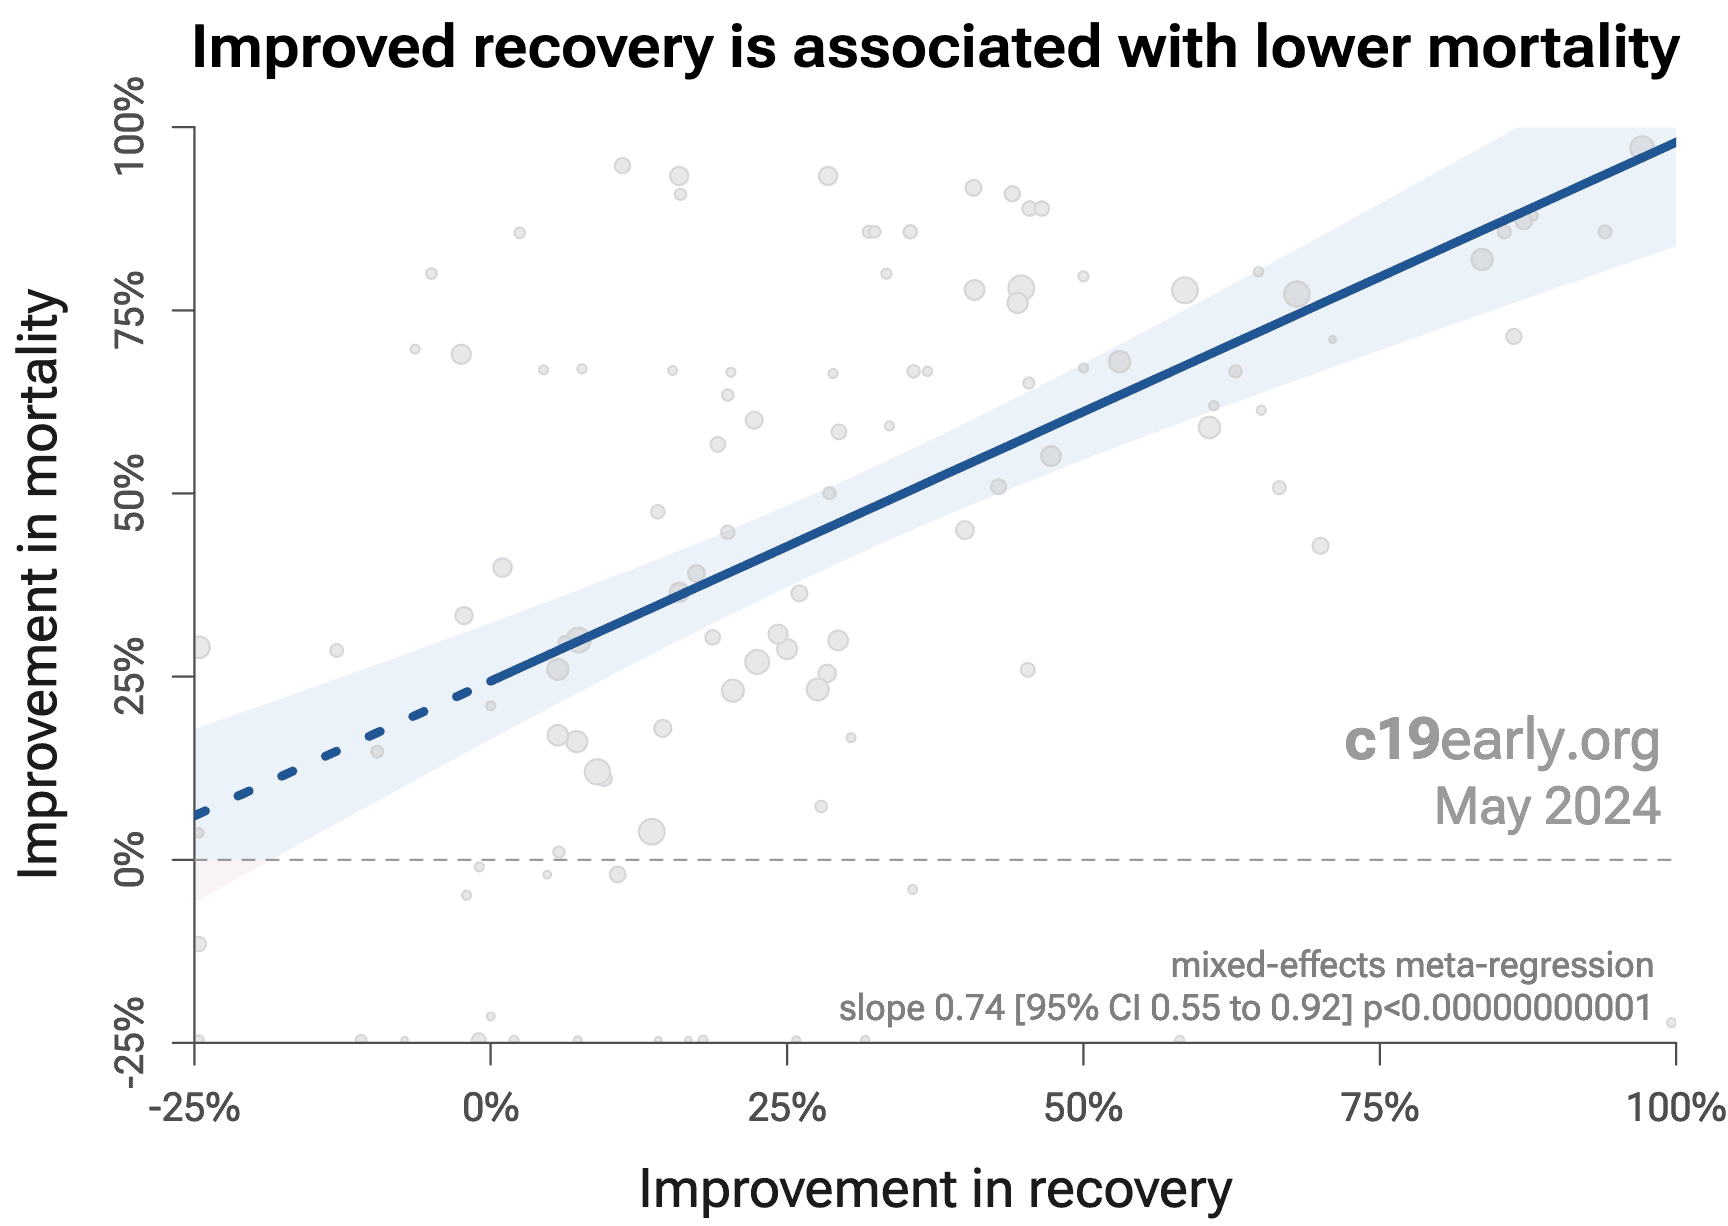
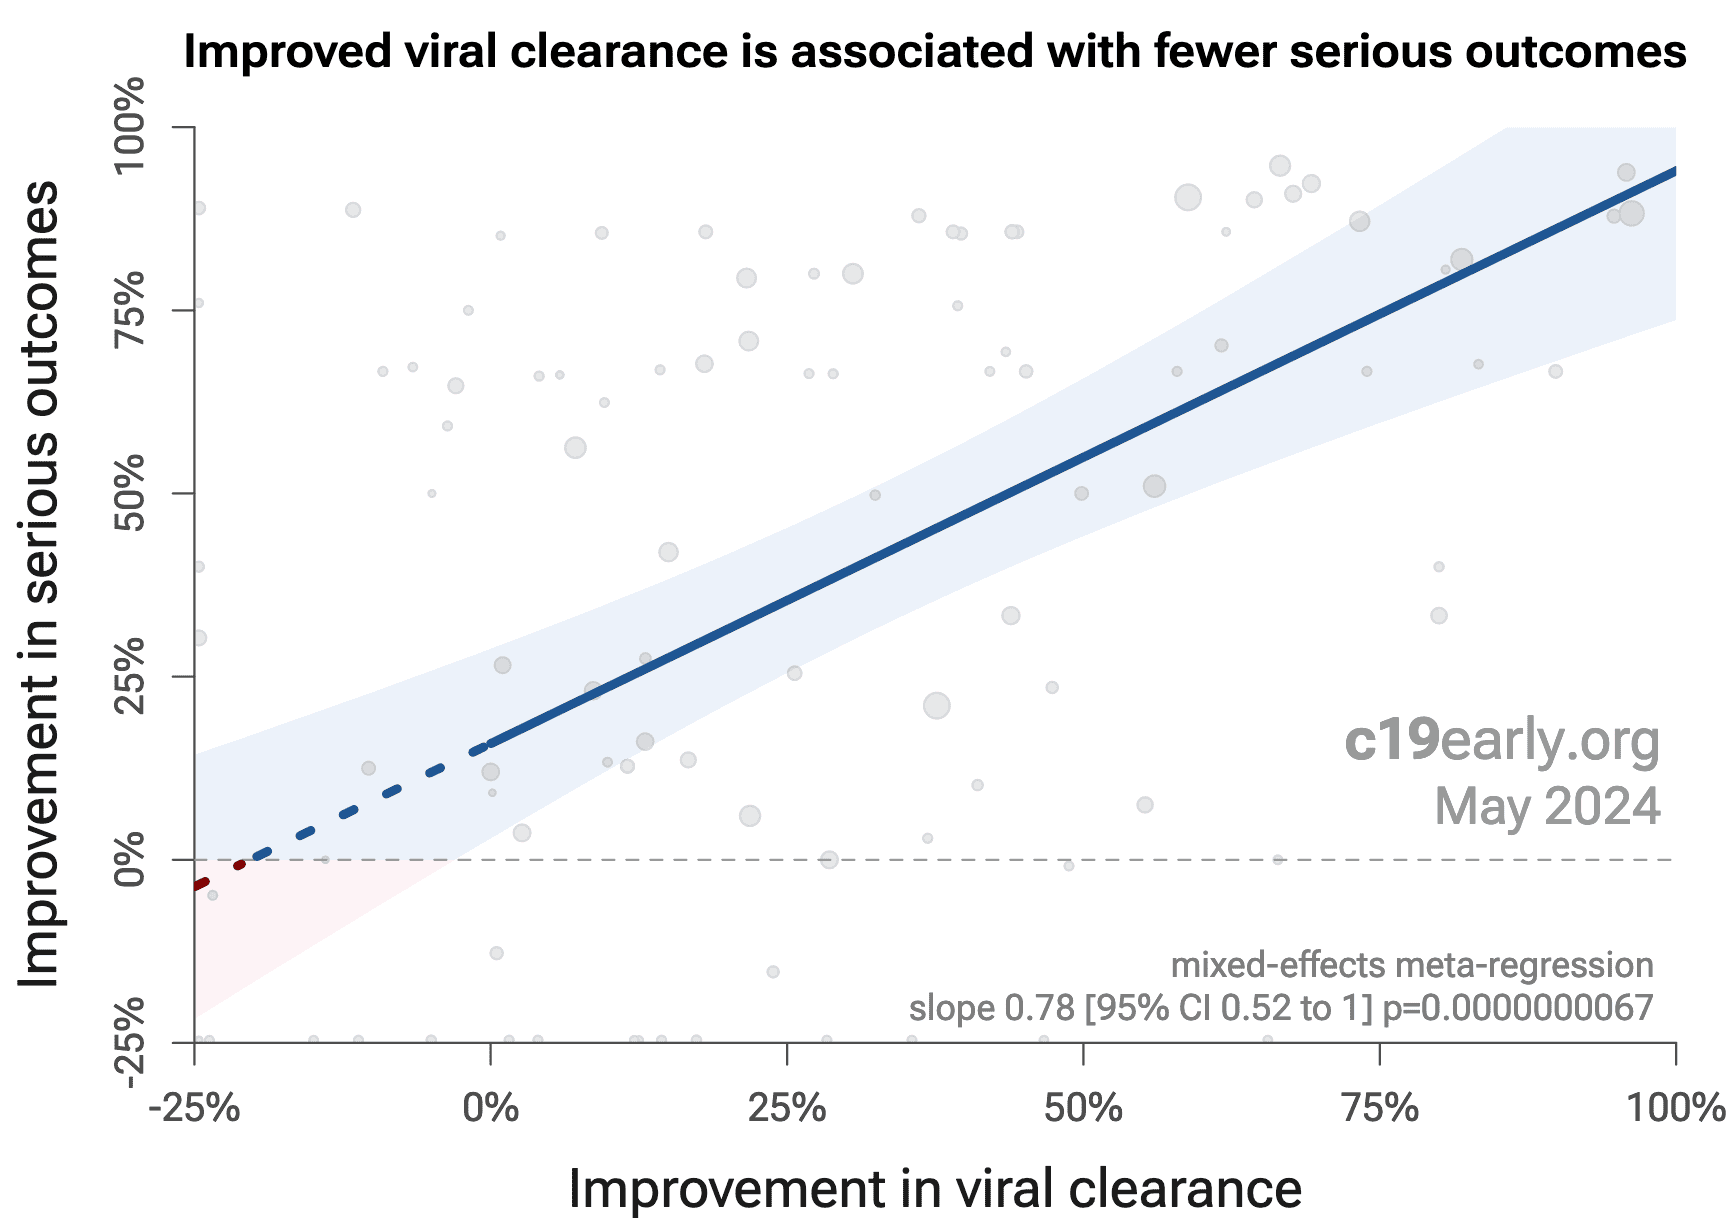
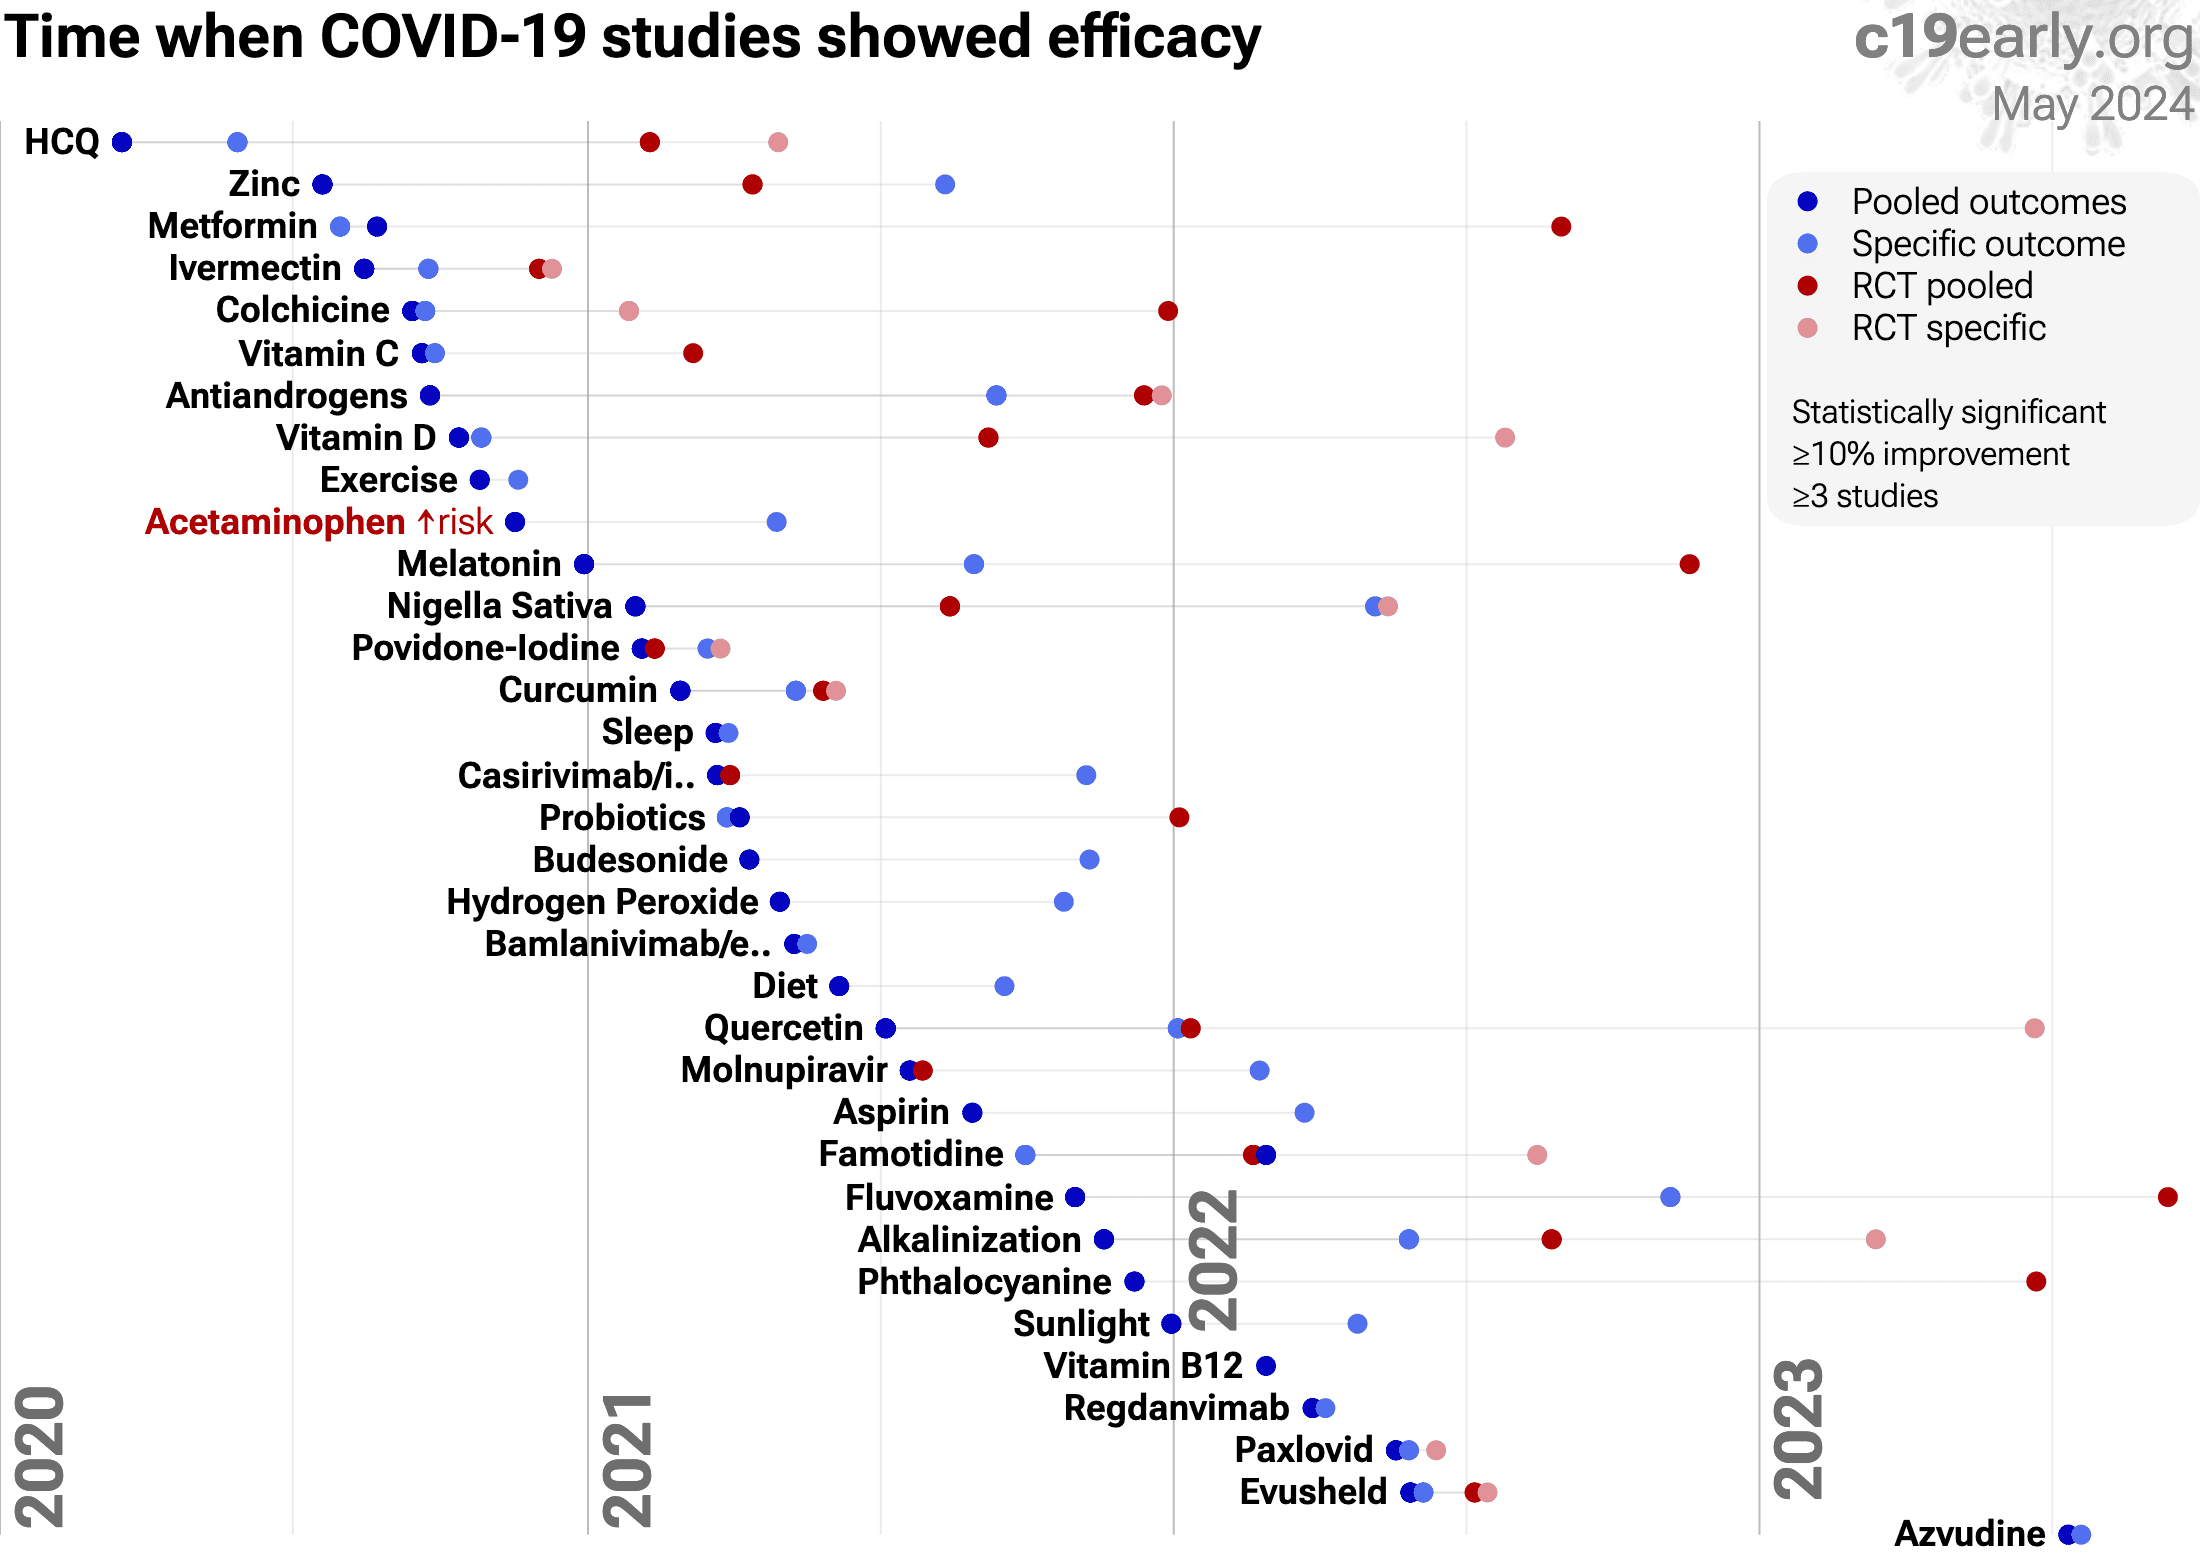
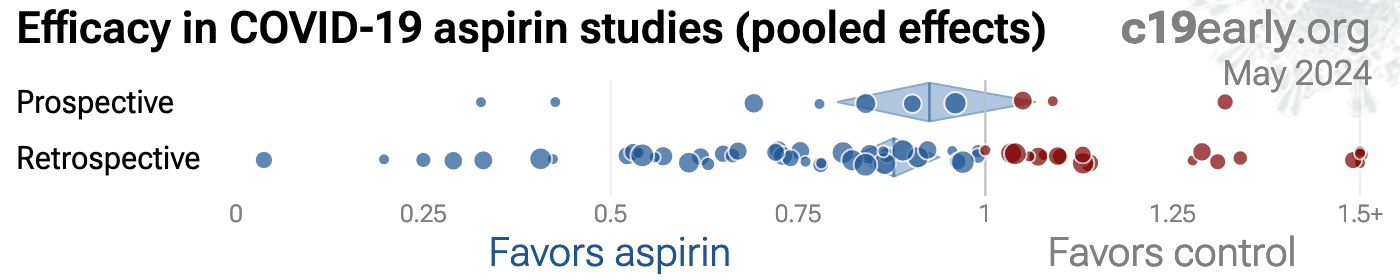
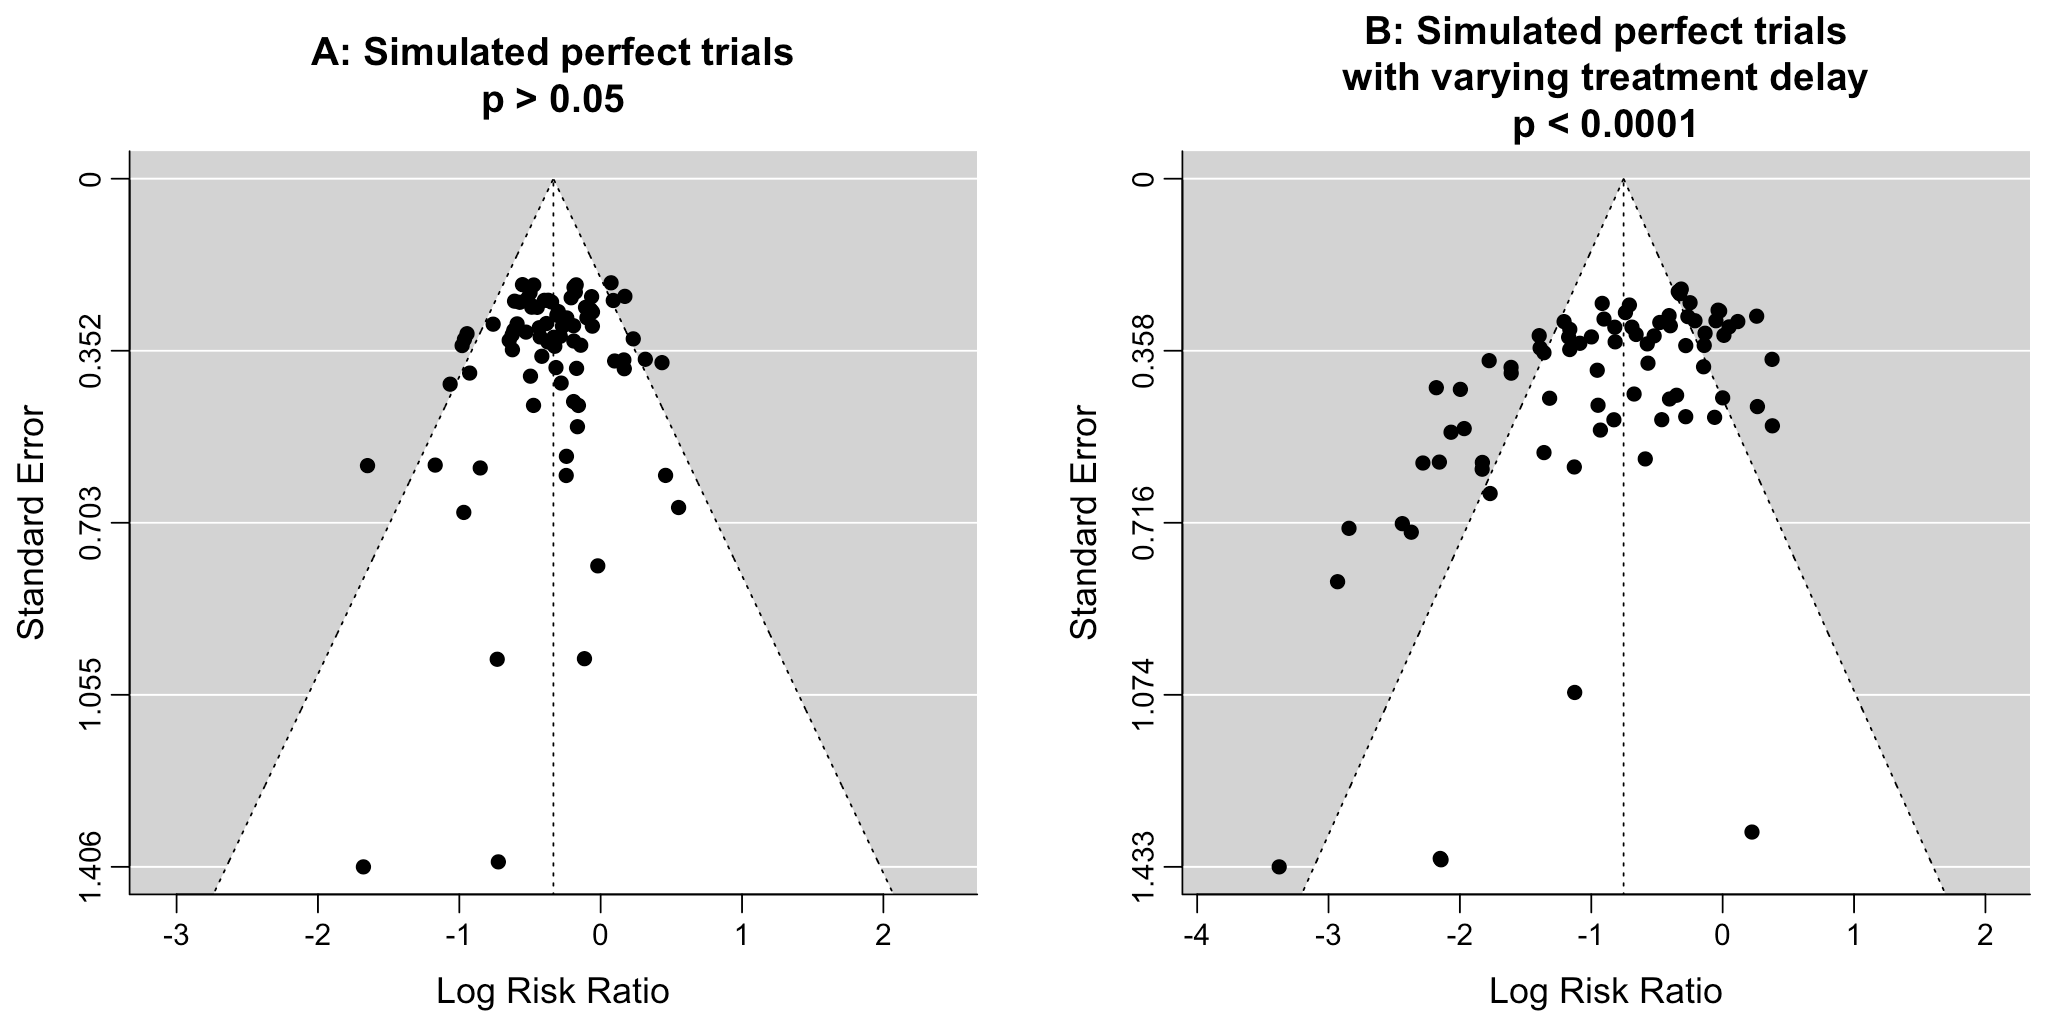
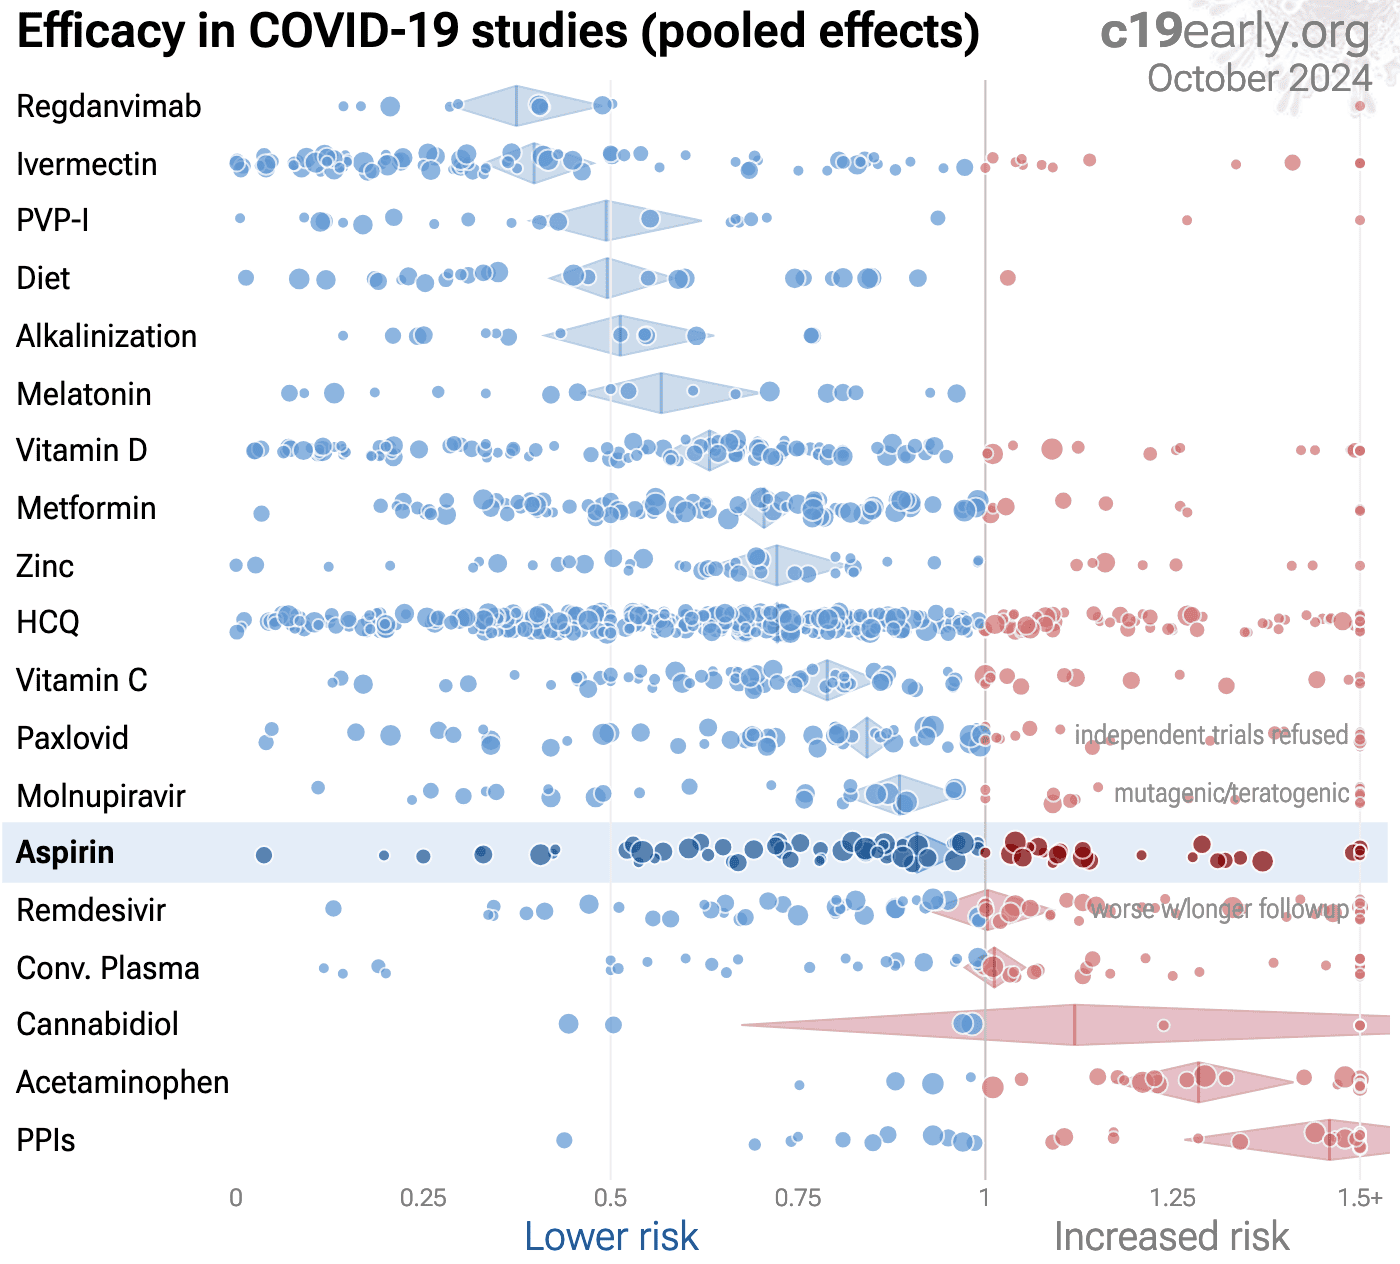
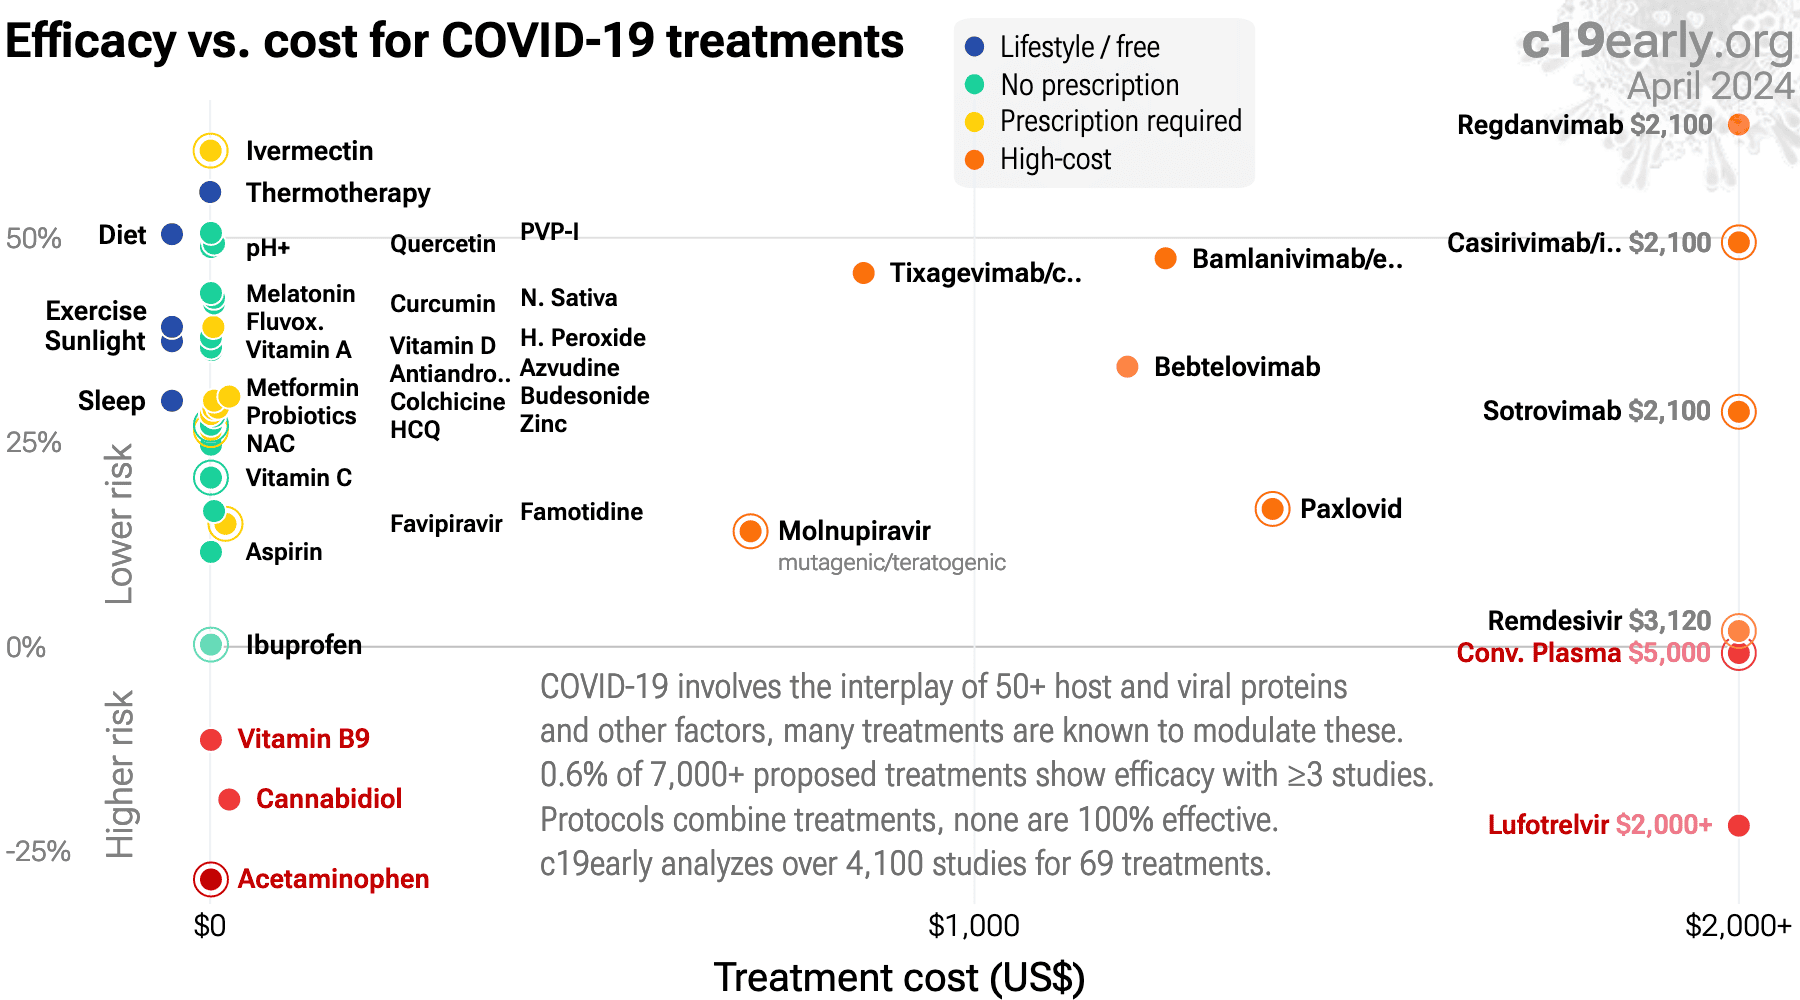
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/emeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
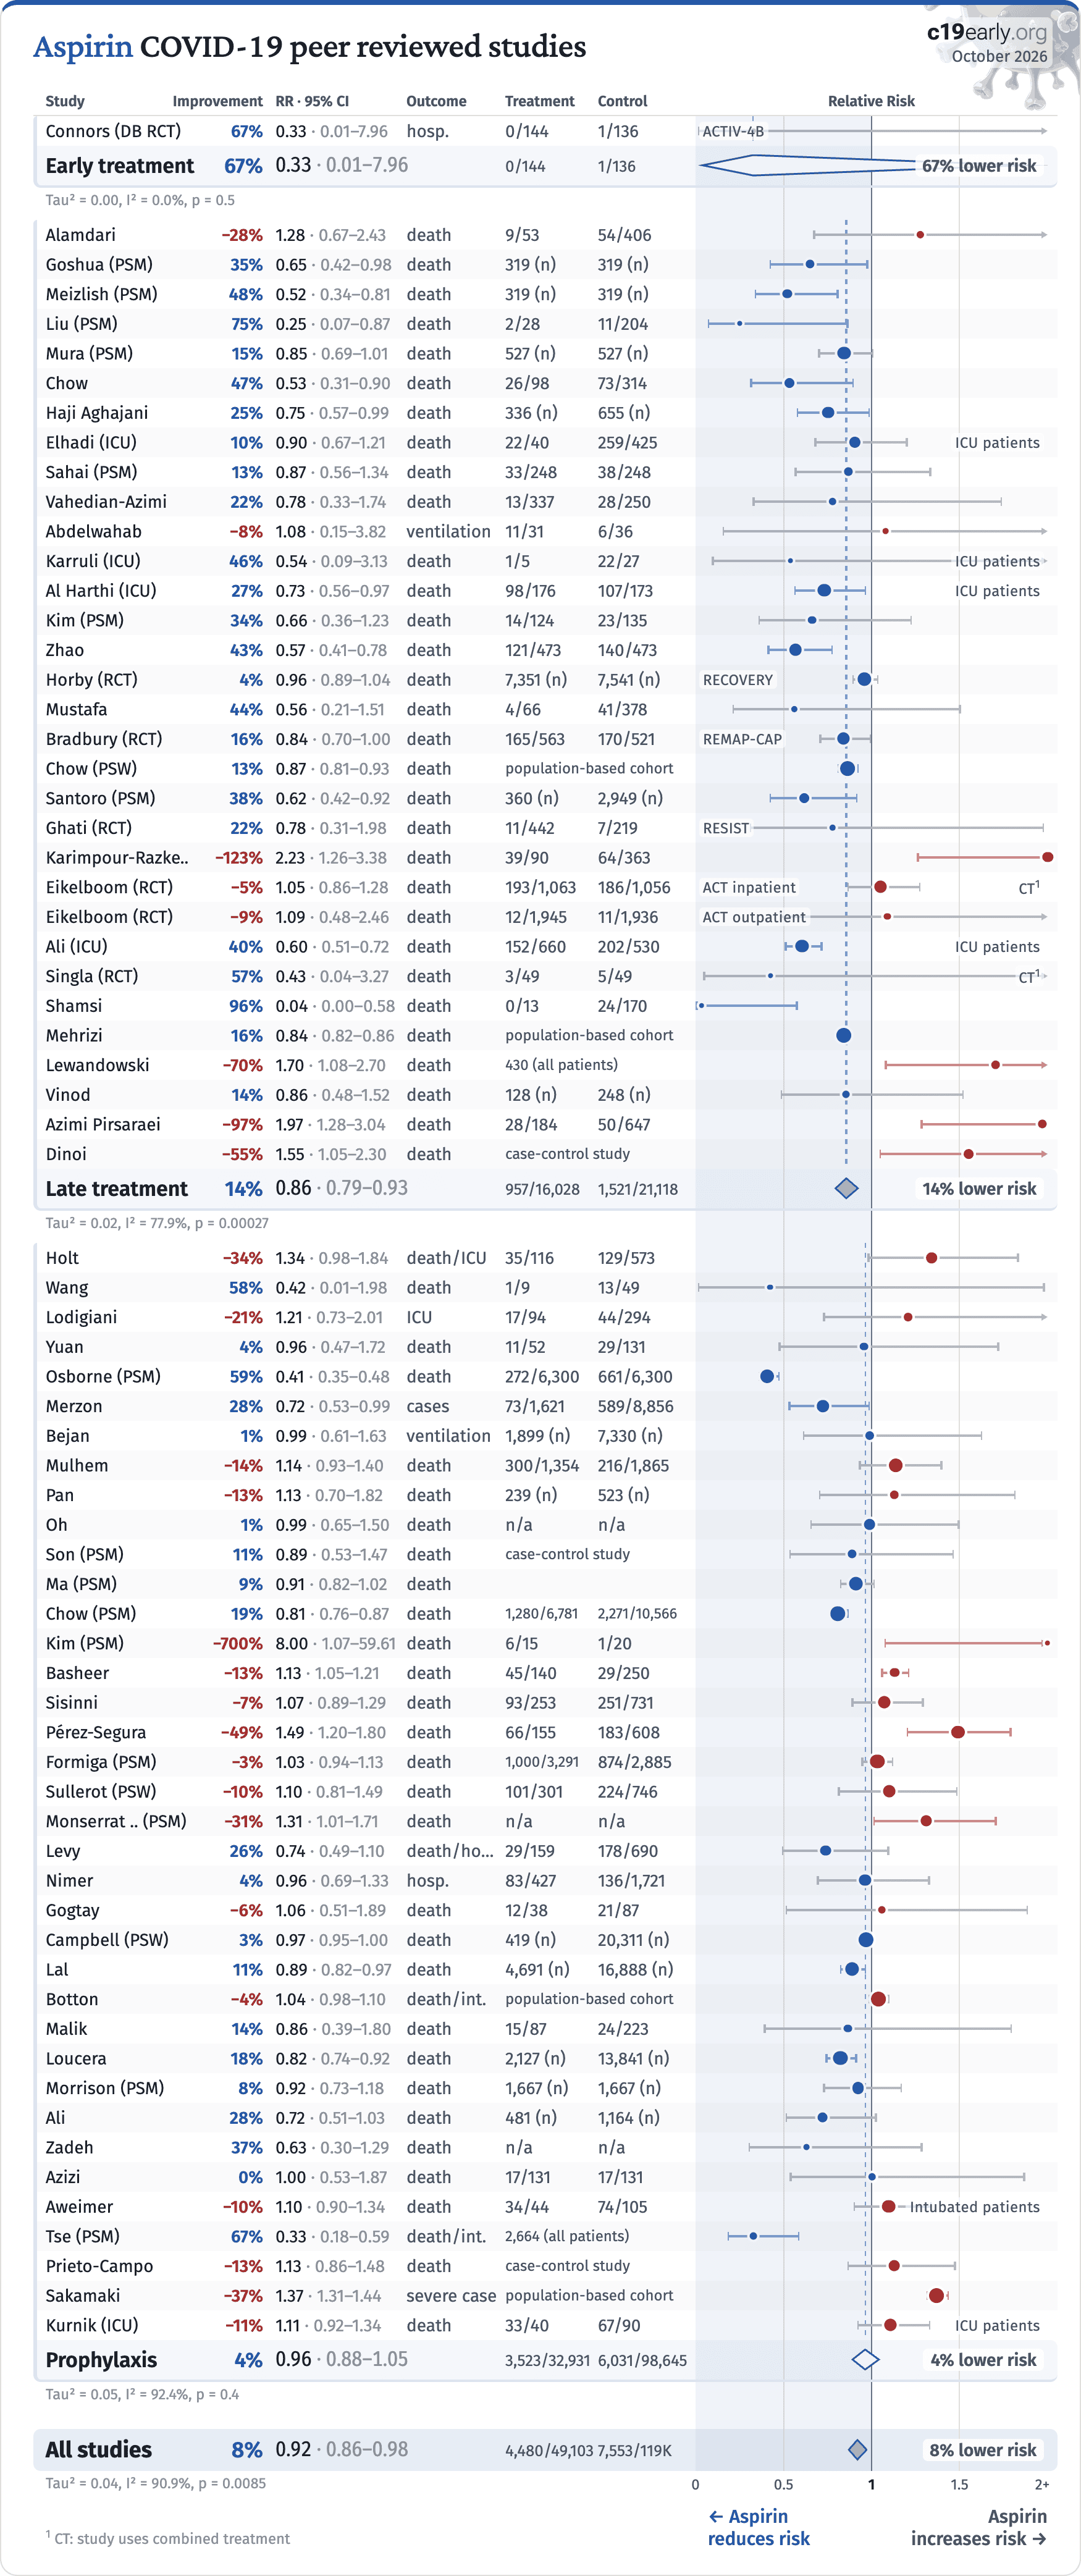
Abdelwahab, 7/30/2021, retrospective, Egypt, peer-reviewed, 17 authors.
|
risk of mechanical ventilation, 7.8% higher, RR 1.08, p = 0.93, treatment 11 of 31 (35.5%), control 6 of 36 (16.7%), adjusted per study, odds ratio converted to relative risk.
|
|
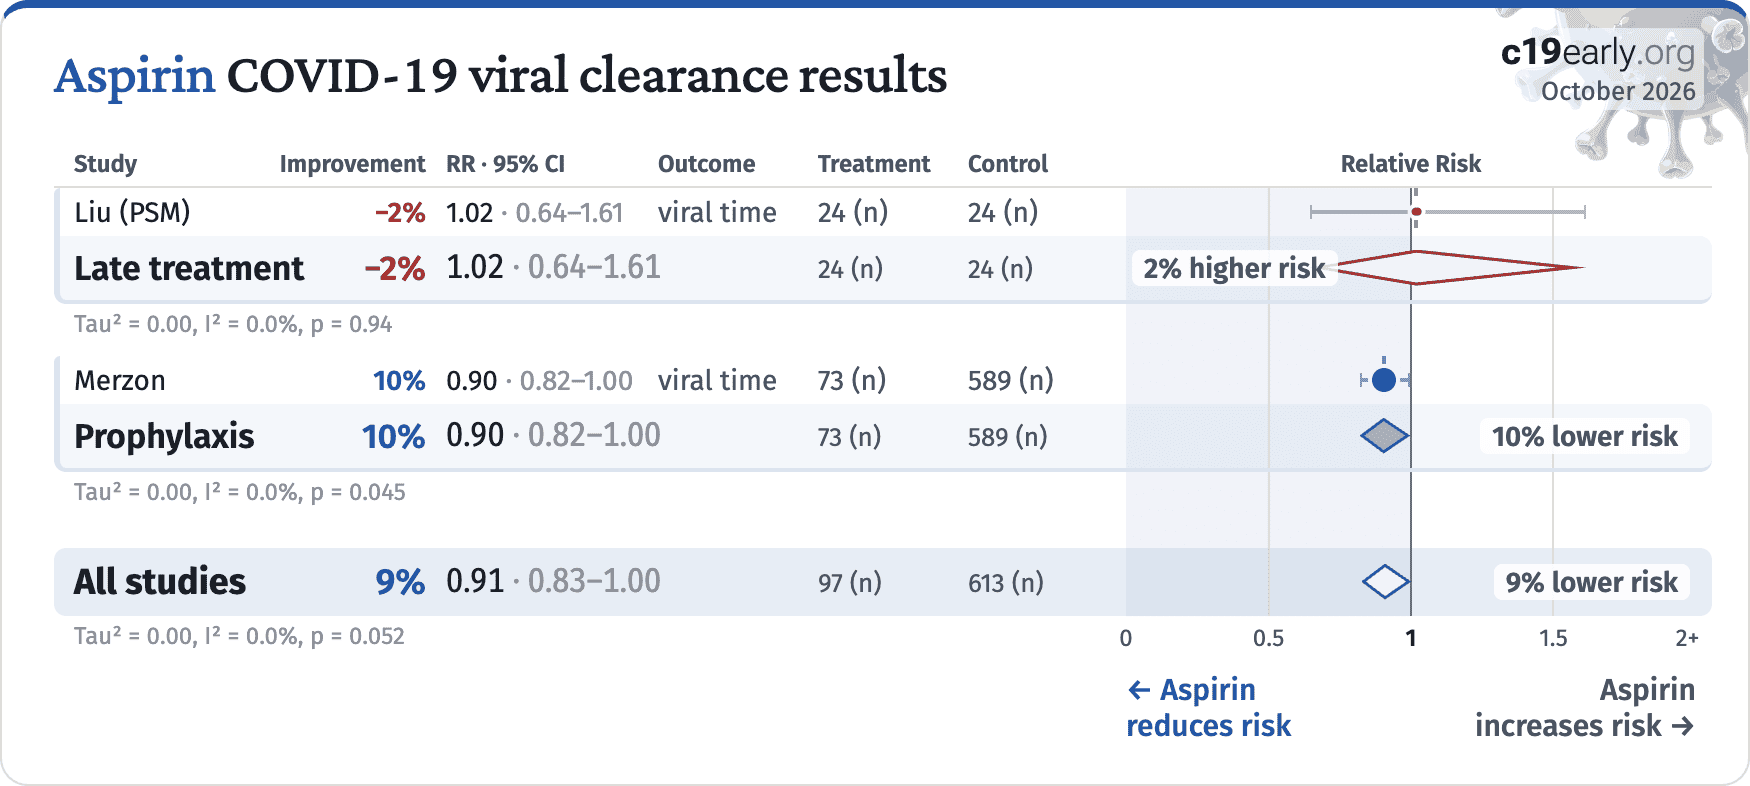
Aidouni, 11/30/2022, prospective, Morocco, preprint, mean age 64.0, 6 authors, study period March 2020 - March 2022.
|
risk of death, 30.9% lower, HR 0.69, p = 0.003, treatment 202 of 712 (28.4%), control 165 of 412 (40.0%), NNT 8.6, adjusted per study, multivariable, Cox proportional hazards.
|
|
risk of mechanical ventilation, 9.6% lower, RR 0.90, p = 0.33, treatment 189 of 712 (26.5%), control 121 of 412 (29.4%), NNT 35.
|
|
Al Harthi, 9/3/2021, retrospective, propensity score matching, Saudi Arabia, peer-reviewed, 21 authors.
|
risk of death, 27.0% lower, HR 0.73, p = 0.03, treatment 98 of 176 (55.7%), control 107 of 173 (61.8%), adjusted per study, in-hospital mortality, multivariable Cox proportional hazards.
|
|
risk of death, 14.0% lower, HR 0.86, p = 0.30, treatment 95 of 176 (54.0%), control 97 of 175 (55.4%), adjusted per study, day 30, multivariable Cox proportional hazards.
|
|
ICU time, 5.3% lower, relative time 0.95, p = 0.54, treatment median 9.0 IQR 11.0 n=176, control median 9.5 IQR 11.0 n=175.
|
|
Alamdari, 9/9/2020, retrospective, Iran, peer-reviewed, 14 authors, average treatment delay 5.72 days, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely.
|
risk of death, 27.7% higher, RR 1.28, p = 0.52, treatment 9 of 53 (17.0%), control 54 of 406 (13.3%).
|
|
Ali (B), 10/31/2022, retrospective, Egypt, peer-reviewed, 3 authors.
|
risk of death, 39.6% lower, RR 0.60, p < 0.001, treatment 152 of 660 (23.0%), control 202 of 530 (38.1%), NNT 6.6.
|
|
risk of ARDS, 37.4% lower, RR 0.63, p = 0.001, treatment 74 of 660 (11.2%), control 95 of 530 (17.9%), NNT 15.
|
|
Azimi Pirsaraei, 8/13/2024, retrospective, Iran, peer-reviewed, mean age 57.2, 5 authors, study period 20 March, 2020 - 20 June, 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 96.9% higher, RR 1.97, p = 0.002, treatment 28 of 184 (15.2%), control 50 of 647 (7.7%).
|
|
Bradbury, 3/22/2022, Randomized Controlled Trial, multiple countries, peer-reviewed, 73 authors, study period 30 October, 2020 - 23 June, 2021, trial NCT02735707 (history) (REMAP-CAP).
|
risk of death, 16.0% lower, HR 0.84, p = 0.05, treatment 165 of 563 (29.3%), control 170 of 521 (32.6%), NNT 30, inverted to make HR<1 favor treatment, Kaplan-Meier, day 90.
|
|
risk of no hospital discharge, 16.9% lower, RR 0.83, p = 0.08, treatment 161 of 563 (28.6%), control 167 of 521 (32.1%), NNT 29, adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk.
|
|
risk of progression, 21.0% lower, RR 0.79, p = 0.02, treatment 204 of 563 (36.2%), control 212 of 521 (40.7%), adjusted per study, odds ratio converted to relative risk, combined death/thrombosis.
|
|
risk of progression, 4.8% lower, OR 0.95, p = 0.67, treatment 563, control 521, adjusted per study, inverted to make OR<1 favor treatment, support-free days, primary outcome, RR approximated with OR.
|
|
Chow, 3/24/2022, retrospective, USA, peer-reviewed, median age 63.0, 89 authors.
|
risk of death, 13.5% lower, RR 0.87, p < 0.001, treatment 1,410 of 13,795 (10.2%), control 11,577 of 98,275 (11.8%), NNT 64, adjusted per study, odds ratio converted to relative risk, propensity score weighting.
|
|
Chow (B), 4/1/2021, retrospective, USA, peer-reviewed, 38 authors.
|
risk of death, 47.0% lower, HR 0.53, p = 0.02, treatment 26 of 98 (26.5%), control 73 of 314 (23.2%), adjusted per study, Cox proportional hazards.
|
|
risk of mechanical ventilation, 44.0% lower, HR 0.56, p = 0.007, treatment 35 of 98 (35.7%), control 152 of 314 (48.4%), NNT 7.9, adjusted per study, Cox proportional hazards.
|
|
risk of ICU admission, 43.0% lower, HR 0.57, p = 0.007, treatment 38 of 98 (38.8%), control 160 of 314 (51.0%), NNT 8.2, adjusted per study, Cox proportional hazards.
|
|
Dinoi, 2/20/2025, retrospective, Italy, peer-reviewed, 11 authors, study period 17 March, 2020 - 15 June, 2021.
|
risk of death, 54.9% higher, OR 1.55, p = 0.03, treatment 82 of 247 (33.2%) cases,
60 of 247 (24.3%) controls, case control OR.
|
|
Eikelboom, 10/10/2022, Randomized Controlled Trial, Canada, peer-reviewed, mean age 45.0, 31 authors, study period 27 August, 2020 - 10 February, 2022, average treatment delay 5.4 days, trial NCT04324463 (history) (ACT outpatient).
|
risk of death, 9.0% higher, HR 1.09, p = 0.84, treatment 12 of 1,945 (0.6%), control 11 of 1,936 (0.6%).
|
|
risk of progression, 20.0% lower, HR 0.80, p = 0.21, treatment 59 of 1,945 (3.0%), control 73 of 1,936 (3.8%), NNT 136, major thrombosis, hospitalisation, or death, primary outcome.
|
|
risk of hospitalization, 17.0% lower, HR 0.83, p = 0.31, treatment 56 of 1,945 (2.9%), control 67 of 1,936 (3.5%), NNT 172.
|
|
Eikelboom (B), 10/10/2022, Randomized Controlled Trial, multiple countries, peer-reviewed, mean age 56.0, 29 authors, study period 2 October, 2020 - 10 February, 2022, average treatment delay 7.0 days, this trial uses multiple treatments in the treatment arm (combined with rivaroxaban) - results of individual treatments may vary, trial NCT04324463 (history) (ACT inpatient).
|
risk of death, 5.0% higher, HR 1.05, p = 0.66, treatment 193 of 1,063 (18.2%), control 186 of 1,056 (17.6%).
|
|
risk of progression, 8.0% lower, HR 0.92, p = 0.32, treatment 281 of 1,063 (26.4%), control 300 of 1,056 (28.4%), NNT 51, major thrombosis, high-flow oxygen, ventilation, or death.
|
|
risk of progression, 11.0% lower, HR 0.89, p = 0.27, treatment 191 of 1,063 (18.0%), control 210 of 1,056 (19.9%), NNT 52, high-flow oxygen or ventilation.
|
|
Elhadi, 4/30/2021, prospective, Libya, peer-reviewed, 21 authors, study period 29 May, 2020 - 30 December, 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 9.7% lower, RR 0.90, p = 0.50, treatment 22 of 40 (55.0%), control 259 of 425 (60.9%), NNT 17.
|
|
Ghati, 7/9/2022, Randomized Controlled Trial, India, peer-reviewed, 14 authors, study period 28 July, 2020 - 27 January, 2021, average treatment delay 6.0 days, trial CTRI/2020/07/026791 (RESIST).
|
risk of death, 22.1% lower, RR 0.78, p = 0.62, treatment 11 of 442 (2.5%), control 7 of 219 (3.2%), NNT 141, aspirin and aspirin/atorvastatin vs. control, modified intention-to-treat.
|
|
risk of death, 57.5% lower, RR 0.42, p = 0.22, treatment 3 of 221 (1.4%), control 7 of 219 (3.2%), NNT 54, aspirin vs. control, modified intention-to-treat.
|
|
risk of mechanical ventilation, 9.2% lower, RR 0.91, p = 0.80, treatment 11 of 442 (2.5%), control 6 of 219 (2.7%), NNT 398, aspirin and aspirin/atorvastatin vs. control, modified intention-to-treat.
|
|
risk of mechanical ventilation, 50.5% lower, RR 0.50, p = 0.34, treatment 3 of 221 (1.4%), control 6 of 219 (2.7%), NNT 72, aspirin vs. control, modified intention-to-treat.
|
|
risk of progression, 30.0% lower, HR 0.70, p = 0.46, treatment 11 of 442 (2.5%), control 7 of 219 (3.2%), NNT 141, aspirin and aspirin/atorvastatin vs. control, Cox proportional hazards, modified intention-to-treat, primary outcome.
|
|
risk of progression, 60.0% lower, HR 0.40, p = 0.18, treatment 3 of 221 (1.4%), control 7 of 219 (3.2%), NNT 54, aspirin vs. control, Cox proportional hazards, modified intention-to-treat, primary outcome.
|
|
Goshua, 11/5/2020, retrospective, USA, peer-reviewed, 15 authors.
|
risk of death, 35.0% lower, OR 0.65, p = 0.04, treatment 319, control 319, propensity score matching, RR approximated with OR.
|
|
risk of mechanical ventilation, 49.0% higher, OR 1.49, p = 0.04, treatment 319, control 319, propensity score matching, RR approximated with OR.
|
|
risk of ICU admission, 45.0% higher, OR 1.45, p = 0.02, treatment 319, control 319, propensity score matching, RR approximated with OR.
|
|
Haji Aghajani, 4/29/2021, retrospective, Iran, peer-reviewed, 7 authors.
|
risk of death, 24.7% lower, HR 0.75, p = 0.04, treatment 336, control 655, adjusted per study, Cox proportional hazards, RR approximated with OR.
|
|
Horby, 11/18/2021, Randomized Controlled Trial, multiple countries, peer-reviewed, 35 authors, study period 1 November, 2020 - 21 March, 2021, average treatment delay 9.0 days, RECOVERY trial.
|
risk of death, 4.0% lower, RR 0.96, p = 0.35, treatment 7,351, control 7,541, day 28.
|
|
risk of death, 17.0% lower, RR 0.83, p = 0.35, treatment 7,351, control 7,541, non-LMWH, day 28.
|
|
risk of mechanical ventilation, 5.0% lower, RR 0.95, p = 0.32, treatment 7,351, control 7,541, day 28.
|
|
risk of no hospital discharge, 5.7% lower, RR 0.94, p = 0.006, treatment 7,351, control 7,541, inverted to make RR<1 favor treatment, day 28.
|
|
risk of no hospital discharge, 16.0% lower, RR 0.84, p = 0.04, treatment 7,351, control 7,541, inverted to make RR<1 favor treatment, non-LMWH, day 28.
|
|
Husain, 10/31/2020, retrospective, Bangladesh, preprint, 4 authors.
|
risk of death, 80.3% lower, RR 0.20, p = 0.55, treatment 0 of 11 (0.0%), control 3 of 31 (9.7%), NNT 10, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of no recovery, 64.8% lower, RR 0.35, p = 0.40, treatment 1 of 11 (9.1%), control 8 of 31 (25.8%), NNT 6.0.
|
|
complications, 95.8% lower, RR 0.04, p = 0.001, treatment 0 of 11 (0.0%), control 17 of 31 (54.8%), NNT 1.8, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Karimpour-Razkenari, 10/3/2022, retrospective, Iran, peer-reviewed, median age 58.5, 9 authors, study period 23 February, 2020 - 23 May, 2020, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely.
|
risk of death, 123.2% higher, RR 2.23, p = 0.008, treatment 39 of 90 (43.3%), control 64 of 363 (17.6%), adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, multivariable.
|
|
Karruli, 9/1/2021, retrospective, Italy, peer-reviewed, 13 authors, study period March 2020 - May 2020.
|
risk of death, 46.3% lower, RR 0.54, p = 0.63, treatment 1 of 5 (20.0%), control 22 of 27 (81.5%), NNT 1.6, adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Kim, 9/4/2021, retrospective, propensity score matching, South Korea, peer-reviewed, 7 authors.
|
risk of death, 33.7% lower, RR 0.66, p = 0.22, treatment 14 of 124 (11.3%), control 23 of 135 (17.0%), NNT 17, PSM.
|
|
risk of mechanical ventilation, 102.2% higher, RR 2.02, p = 0.16, treatment 13 of 124 (10.5%), control 7 of 135 (5.2%), PSM.
|
|
risk of ICU admission, 90.5% higher, RR 1.91, p = 0.36, treatment 7 of 124 (5.6%), control 4 of 135 (3.0%), PSM.
|
|
Lewandowski, 3/7/2024, retrospective, Poland, peer-reviewed, 15 authors.
|
risk of death, 70.3% higher, OR 1.70, p = 0.02, RR approximated with OR.
|
|
Liu, 2/12/2021, retrospective, propensity score matching, China, peer-reviewed, 8 authors.
|
risk of death, 75.0% lower, HR 0.25, p = 0.03, treatment 2 of 28 (7.1%), control 11 of 204 (5.4%), adjusted per study, 60 days, KM, PSM.
|
|
risk of death, 81.0% lower, HR 0.19, p = 0.02, treatment 1 of 28 (3.6%), control 9 of 204 (4.4%), adjusted per study, 30 days, KM, PSM.
|
|
time to viral-, 1.9% higher, relative time 1.02, p = 0.94, treatment 24, control 24, PSM.
|
|
Mehrizi, 12/18/2023, retrospective, Iran, peer-reviewed, 10 authors, study period 1 February, 2020 - 20 March, 2022.
|
risk of death, 16.0% lower, OR 0.84, p < 0.001, RR approximated with OR.
|
|
Meizlish, 1/21/2021, retrospective, propensity score matching, USA, peer-reviewed, 22 authors.
|
risk of death, 47.8% lower, HR 0.52, p = 0.004, treatment 319, control 319, PSM.
|
|
Mura, 3/31/2021, retrospective, database analysis, multiple countries, peer-reviewed, 6 authors.
|
risk of death, 15.4% lower, RR 0.85, p = 0.08, treatment 527, control 527, odds ratio converted to relative risk, aspirin only, control prevalence approximated with treatment prevalence, propensity score matching.
|
|
risk of death, 37.3% lower, RR 0.63, p = 0.001, treatment 305, control 305, odds ratio converted to relative risk, famotidine and aspirin, control prevalence approximated with treatment prevalence, propensity score matching.
|
|
Mustafa, 12/29/2021, retrospective, Pakistan, peer-reviewed, 7 authors, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 44.1% lower, RR 0.56, p = 0.28, treatment 4 of 66 (6.1%), control 41 of 378 (10.8%), NNT 21.
|
|
Pourhoseingholi, 5/26/2021, prospective, Iran, preprint, mean age 57.9, 11 authors, study period 2 February, 2020 - 20 July, 2020, average treatment delay 7.4 days.
|
risk of death, 32.0% higher, HR 1.32, p = 0.04, treatment 71 of 290 (24.5%), control 268 of 2,178 (12.3%), adjusted per study, multivariable, Cox proportional hazards.
|
|
Sahai, 5/19/2021, retrospective, propensity score matching, USA, peer-reviewed, 18 authors.
|
risk of death, 13.2% lower, RR 0.87, p = 0.53, treatment 33 of 248 (13.3%), control 38 of 248 (15.3%), NNT 50.
|
|
Santoro, 6/22/2022, retrospective, propensity score matching, multivariable, multiple countries, peer-reviewed, 31 authors, study period 16 January, 2020 - 30 May, 2020.
|
risk of death, 38.0% lower, HR 0.62, p = 0.02, treatment 360, control 2,949.
|
|
Shamsi, 7/17/2023, retrospective, Iran, peer-reviewed, 4 authors, study period 1 March, 2020 - 1 August, 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 96.3% lower, RR 0.04, p = 0.22, treatment 0 of 13 (0.0%), control 24 of 170 (14.1%), NNT 7.1, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Singla, 1/30/2023, Randomized Controlled Trial, USA, peer-reviewed, 26 authors, study period 1 October, 2020 - 30 April, 2021, this trial uses multiple treatments in the treatment arm (combined with dipyridamole) - results of individual treatments may vary, trial NCT04410328 (history).
|
risk of death, 57.4% lower, RR 0.43, p = 0.44, treatment 3 of 49 (6.1%), control 5 of 49 (10.2%), adjusted per study, odds ratio converted to relative risk, multivariable, day 28.
|
|
risk of death, 15.0% lower, OR 0.85, p = 0.87, treatment 49, control 49, adjusted per study, multivariable, day 14, RR approximated with OR.
|
|
risk of mechanical ventilation, 20.0% lower, RR 0.80, p = 1.00, treatment 4 of 49 (8.2%), control 5 of 49 (10.2%), NNT 49.
|
|
risk of ICU admission, 28.6% lower, RR 0.71, p = 0.76, treatment 5 of 49 (10.2%), control 7 of 49 (14.3%), NNT 25.
|
|
risk of progression, 33.3% lower, RR 0.67, p = 0.74, treatment 4 of 49 (8.2%), control 6 of 49 (12.2%), NNT 24, day 28.
|
|
risk of progression, 76.3% lower, RR 0.24, p = 0.22, treatment 4 of 49 (8.2%), control 7 of 49 (14.3%), odds ratio converted to relative risk, respiratory failure, day 28.
|
|
risk of progression, 44.4% lower, RR 0.56, p = 0.39, treatment 5 of 49 (10.2%), control 9 of 49 (18.4%), NNT 12, AKI.
|
|
risk of progression, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 49 (0.0%), control 3 of 49 (6.1%), NNT 16, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), DIC.
|
|
risk of progression, 25.0% lower, RR 0.75, p = 0.62, treatment 9 of 49 (18.4%), control 12 of 49 (24.5%), NNT 16, liver dysfunction.
|
|
Vahedian-Azimi, 7/20/2021, retrospective, Iran, peer-reviewed, 9 authors.
|
risk of death, 21.9% lower, RR 0.78, p = 0.56, treatment 13 of 337 (3.9%), control 28 of 250 (11.2%), adjusted per study, odds ratio converted to relative risk, multivariable, primary outcome.
|
|
risk of ICU admission, 10.5% higher, RR 1.10, p = 0.67, treatment 36 of 337 (10.7%), control 44 of 250 (17.6%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Vinod, 6/24/2024, retrospective, USA, peer-reviewed, mean age 66.8, 8 authors, study period March 2020 - October 2020.
|
risk of death, 14.4% lower, OR 0.86, p = 0.61, treatment 128, control 248, adjusted per study, multivariable, RR approximated with OR.
|
|
risk of mechanical ventilation, 30.3% lower, OR 0.70, p = 0.24, treatment 128, control 248, adjusted per study, multivariable, RR approximated with OR.
|
|
hypoxia, 39.6% lower, OR 0.60, p = 0.0497, treatment 128, control 248, adjusted per study, multivariable, RR approximated with OR.
|
|
readmisson, 5.8% higher, OR 1.06, p = 0.88, treatment 128, control 248, adjusted per study, multivariable, RR approximated with OR.
|
|
DVT/PE, 17.7% lower, OR 0.82, p = 0.77, treatment 128, control 248, adjusted per study, multivariable, RR approximated with OR.
|
|
Zhao, 10/1/2021, retrospective, USA, peer-reviewed, 6 authors.
|
risk of death, 43.0% lower, HR 0.57, p < 0.001, treatment 121 of 473 (25.6%), control 140 of 473 (29.6%), adjusted per study, PSM.
|
|
risk of death, 28.0% lower, HR 0.72, p = 0.03, treatment 473, control 1,597, adjusted per study, multivariable.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Abul, 8/4/2022, retrospective, USA, preprint, mean age 72.3, 10 authors, study period 13 December, 2020 - 18 September, 2021.
|
risk of death, 33.0% lower, HR 0.67, p = 0.03, treatment 46 of 511 (9.0%), control 201 of 1,176 (17.1%), Cox proportional hazards, day 56.
|
|
risk of death, 40.0% lower, HR 0.60, p = 0.01, treatment 33 of 511 (6.5%), control 154 of 1,176 (13.1%), Cox proportional hazards, day 30.
|
|
risk of hospitalization, 20.0% lower, HR 0.80, p = 0.13, treatment 103 of 511 (20.2%), control 352 of 1,176 (29.9%), Cox proportional hazards.
|
|
Ali (C), 11/19/2022, retrospective, USA, peer-reviewed, 8 authors.
|
risk of death, 28.0% lower, HR 0.72, p = 0.07, treatment 481, control 1,164, Cox proportional hazards.
|
|
Aweimer, 3/29/2023, retrospective, Germany, peer-reviewed, median age 67.0, 19 authors, study period 1 March, 2020 - 31 August, 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 9.6% higher, RR 1.10, p = 0.43, treatment 34 of 44 (77.3%), control 74 of 105 (70.5%).
|
|
Azizi, 2/17/2023, retrospective, Iran, peer-reviewed, 6 authors, excluded in exclusion analyses:
age matching based on only two categories, matching may be very poor given the relationship between age and COVID-19 risk; inconsistent data.
|
risk of death, no change, RR 1.00, p = 1.00, treatment 17 of 131 (13.0%), control 17 of 131 (13.0%).
|
|
Basheer, 10/2/2021, retrospective, Israel, peer-reviewed, 4 authors.
|
risk of death, 13.0% higher, RR 1.13, p < 0.001, treatment 45 of 140 (32.1%), control 29 of 250 (11.6%), adjusted per study, odds ratio converted to relative risk, group sizes approximated (only percentages provided).
|
|
Bejan, 2/28/2021, retrospective, USA, peer-reviewed, mean age 42.0, 6 authors.
|
risk of mechanical ventilation, 1.0% lower, OR 0.99, p = 0.97, treatment 1,899, control 7,330, adjusted per study, RR approximated with OR.
|
|
Botton, 6/17/2022, retrospective, France, peer-reviewed, 7 authors.
|
risk of death/intubation, 4.0% higher, HR 1.04, p = 0.18, Cox proportional hazards.
|
|
risk of hospitalization, 3.0% higher, HR 1.03, p = 0.046, Cox proportional hazards.
|
|
Campbell, 5/5/2022, retrospective, USA, peer-reviewed, 4 authors, study period 2 March, 2020 - 14 December, 2020.
|
risk of death, 3.0% lower, OR 0.97, p = 0.06, treatment 419, control 20,311, adjusted per study, propensity score weighting, multivariable, day 60, RR approximated with OR.
|
|
risk of death, 2.0% lower, OR 0.98, p = 0.10, treatment 419, control 20,311, adjusted per study, propensity score weighting, multivariable, day 30, RR approximated with OR.
|
|
Chow (C), 8/29/2021, retrospective, propensity score matching, USA, peer-reviewed, 12 authors.
|
risk of death, 19.0% lower, HR 0.81, p < 0.005, treatment 1,280 of 6,781 (18.9%), control 2,271 of 10,566 (21.5%), NNT 38, adjusted per study, Kaplan Meier.
|
|
risk of mechanical ventilation, 2.8% lower, HR 0.97, p = 0.21, treatment 2,122 of 6,781 (31.3%), control 3,403 of 10,566 (32.2%), NNT 109.
|
|
Drew, 5/2/2021, retrospective, multiple countries, preprint, 25 authors, study period 24 March, 2020 - 8 May, 2020.
|
risk of progression, 22.0% lower, HR 0.78, p = 0.30, adjusted per study, seen in hospital/clinic, comorbidity and symptom adjusted, multivariable.
|
|
risk of case, 3.0% higher, HR 1.03, p = 0.80, adjusted per study, comorbidity and symptom adjusted, multivariable.
|
|
Formiga, 11/29/2021, retrospective, USA, peer-reviewed, 24 authors, study period 1 March, 2020 - 1 May, 2021.
|
risk of death, 3.4% higher, RR 1.03, p = 0.48, treatment 1,000 of 3,291 (30.4%), control 874 of 2,885 (30.3%), odds ratio converted to relative risk, propensity score matching.
|
|
risk of mechanical ventilation, 3.2% higher, RR 1.03, p = 0.75, treatment 213 of 3,291 (6.5%), control 181 of 2,885 (6.3%), propensity score matching.
|
|
risk of ICU admission, 4.2% higher, RR 1.04, p = 0.65, treatment 283 of 3,291 (8.6%), control 238 of 2,885 (8.2%), propensity score matching.
|
|
Gogtay, 3/9/2022, retrospective, USA, peer-reviewed, 4 authors, study period March 2020 - April 2020.
|
risk of death, 5.9% higher, RR 1.06, p = 0.87, treatment 12 of 38 (31.6%), control 21 of 87 (24.1%), adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, multivariable.
|
|
risk of mechanical ventilation, 49.8% lower, RR 0.50, p = 0.16, treatment 5 of 38 (13.2%), control 21 of 87 (24.1%), NNT 9.1, adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of ICU admission, 49.2% lower, RR 0.51, p = 0.41, treatment 9 of 38 (23.7%), control 38 of 87 (43.7%), NNT 5.0, adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Holt, 5/7/2020, retrospective, Denmark, peer-reviewed, median age 70.0, 4 authors, study period 1 March, 2020 - 1 April, 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death/ICU, 34.0% higher, RR 1.34, p = 0.09, treatment 35 of 116 (30.2%), control 129 of 573 (22.5%).
|
|
Kim (B), 9/4/2021, retrospective, propensity score matching, South Korea, peer-reviewed, 7 authors.
|
risk of death, 700.0% higher, RR 8.00, p = 0.03, treatment 6 of 15 (40.0%), control 1 of 20 (5.0%), PSM, prior aspirin use.
|
|
risk of mechanical ventilation, 433.3% higher, RR 5.33, p = 0.14, treatment 4 of 15 (26.7%), control 1 of 20 (5.0%), PSM, prior aspirin use.
|
|
risk of ICU admission, 433.3% higher, RR 5.33, p = 0.14, treatment 4 of 15 (26.7%), control 1 of 20 (5.0%), PSM, prior aspirin use.
|
|
risk of case, 33.4% lower, RR 0.67, p = 0.29, treatment 15 of 136 (11.0%), control 20 of 136 (14.7%), NNT 27, adjusted per study, odds ratio converted to relative risk, PSM, logistic regression, prior aspirin use.
|
|
risk of death, 33.7% lower, RR 0.66, p = 0.22, treatment 14 of 124 (11.3%), control 23 of 135 (17.0%), NNT 17, PSM, aspirin treatment after diagnosis.
|
|
risk of mechanical ventilation, 102.2% higher, RR 2.02, p = 0.16, treatment 13 of 124 (10.5%), control 7 of 135 (5.2%), PSM, aspirin treatment after diagnosis.
|
|
risk of ICU admission, 90.5% higher, RR 1.91, p = 0.36, treatment 7 of 124 (5.6%), control 4 of 135 (3.0%), PSM, aspirin treatment after diagnosis.
|
|
Kurnik, 2/11/2025, retrospective, Slovenia, peer-reviewed, mean age 76.8, 3 authors, study period October 2020 - April 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 10.8% higher, RR 1.11, p = 0.37, treatment 33 of 40 (82.5%), control 67 of 90 (74.4%), day 1000.
|
|
Lal, 5/5/2022, retrospective, USA, peer-reviewed, 20 authors, study period 15 February, 2020 - 30 September, 2021, trial NCT04323787 (history).
|
risk of death, 11.0% lower, HR 0.89, p = 0.01, treatment 4,691, control 16,888, adjusted per study, multivariable.
|
|
risk of ICU admission, 22.0% lower, HR 0.78, p < 0.001, treatment 4,691, control 16,888, adjusted per study, multivariable.
|
|
risk of progression, 9.0% lower, HR 0.91, p = 0.02, treatment 4,691, control 16,888, adjusted per study, multivariable.
|
|
Levy, 1/31/2022, retrospective, Israel, peer-reviewed, 10 authors.
|
risk of death/hospitalization, 26.0% lower, HR 0.74, p = 0.13, treatment 29 of 159 (18.2%), control 178 of 690 (25.8%), NNT 13, adjusted per study, multivariable, Cox proportional hazards, day 40.
|
|
Lodigiani, 7/31/2020, retrospective, Italy, peer-reviewed, median age 66.0, 12 authors, study period 13 February, 2020 - 10 April, 2020.
|
risk of ICU admission, 20.8% higher, RR 1.21, p = 0.52, treatment 17 of 94 (18.1%), control 44 of 294 (15.0%).
|
|
Loucera, 8/16/2022, retrospective, Spain, peer-reviewed, 8 authors, study period January 2020 - November 2020.
|
risk of death, 17.7% lower, HR 0.82, p < 0.001, treatment 2,127, control 13,841, Cox proportional hazards, day 30.
|
|
Ma (B), 8/18/2021, retrospective, propensity score matching, United Kingdom, peer-reviewed, 9 authors.
|
risk of death, 9.0% lower, OR 0.91, p = 0.12, treatment 12,471, control 64,750, RR approximated with OR.
|
|
risk of hospitalization, 2.0% lower, OR 0.98, p = 0.47, treatment 12,471, control 64,750, RR approximated with OR.
|
|
risk of symptomatic case, 9.0% higher, OR 1.09, p = 0.18, treatment 12,471, control 64,750, RR approximated with OR.
|
|
risk of case, 7.0% higher, OR 1.07, p = 0.09, treatment 12,471, control 64,750, RR approximated with OR.
|
|
Malik, 7/11/2022, retrospective, USA, peer-reviewed, 16 authors, study period 1 March, 2020 - 1 December, 2020.
|
risk of death, 13.6% lower, RR 0.86, p = 0.72, treatment 15 of 87 (17.2%), control 24 of 223 (10.8%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of ICU admission, 27.8% lower, RR 0.72, p = 0.17, treatment 28 of 87 (32.2%), control 77 of 223 (34.5%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of ARDS, 25.1% lower, RR 0.75, p = 0.39, treatment 13 of 87 (14.9%), control 40 of 223 (17.9%), NNT 33, adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of hospitalization, 2.4% lower, OR 0.98, p = 0.94, treatment 25, control 176, adjusted per study, multivariable, RR approximated with OR.
|
|
Merzon, 2/23/2021, retrospective, Israel, peer-reviewed, 8 authors.
|
risk of case, 27.6% lower, RR 0.72, p = 0.04, treatment 73 of 1,621 (4.5%), control 589 of 8,856 (6.7%), NNT 47, adjusted per study, odds ratio converted to relative risk.
|
|
risk of death, 62.4% lower, RR 0.38, p = 0.51, treatment 1 of 21 (4.8%), control 6 of 91 (6.6%), adjusted per study, odds ratio converted to relative risk.
|
|
time to viral-, 9.6% lower, relative time 0.90, p = 0.045, treatment 73, control 589, time to 2nd negative test.
|
|
time to viral-, 14.8% lower, relative time 0.85, p = 0.005, treatment 73, control 589, time to 1st negative test.
|
|
Miele, 12/8/2024, retrospective, USA, preprint, 12 authors, study period 1 January, 2020 - 31 March, 2021, excluded in exclusion analyses:
substantial unadjusted confounding by indication possible.
|
risk of death, 32.0% higher, OR 1.32, p = 0.02, RR approximated with OR.
|
|
Monserrat Villatoro, 1/8/2022, retrospective, propensity score matching, Spain, peer-reviewed, 18 authors.
|
risk of death, 31.0% higher, OR 1.31, p = 0.04, RR approximated with OR.
|
|
Morrison, 10/10/2022, retrospective, USA, peer-reviewed, mean age 62.5, 3 authors, study period March 2020 - March 2021.
|
risk of death, 7.7% lower, OR 0.92, p = 0.52, treatment 1,667, control 1,667, propensity score matching, RR approximated with OR.
|
|
risk of mechanical ventilation, 0.9% higher, OR 1.01, p = 0.96, treatment 1,667, control 1,667, propensity score matching, RR approximated with OR.
|
|
risk of ICU admission, 12.2% higher, OR 1.12, p = 0.36, treatment 1,667, control 1,667, propensity score matching, RR approximated with OR.
|
|
risk of hospitalization, 18.3% higher, OR 1.18, p = 0.04, treatment 1,667, control 1,667, propensity score matching, RR approximated with OR.
|
|
Mulhem, 4/7/2021, retrospective, database analysis, USA, peer-reviewed, 3 authors, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely; substantial confounding by time likely due to declining usage over the early stages of the pandemic when overall treatment protocols improved dramatically.
|
risk of death, 13.9% higher, RR 1.14, p = 0.21, treatment 300 of 1,354 (22.2%), control 216 of 1,865 (11.6%), adjusted per study, odds ratio converted to relative risk, Table S1, logistic regression.
|
|
Nimer, 2/28/2022, retrospective, Jordan, peer-reviewed, survey, 4 authors, study period March 2021 - July 2021.
|
risk of hospitalization, 3.7% lower, RR 0.96, p = 0.08, treatment 83 of 427 (19.4%), control 136 of 1,721 (7.9%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of severe case, 17.8% higher, RR 1.18, p = 0.28, treatment 98 of 427 (23.0%), control 162 of 1,721 (9.4%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Oh, 6/17/2021, retrospective, database analysis, South Korea, peer-reviewed, 4 authors.
|
risk of death, 1.0% lower, OR 0.99, p = 0.95, adjusted per study, multivariable, RR approximated with OR.
|
|
risk of case, 12.0% lower, RR 0.88, p = 0.04, adjusted per study, odds ratio converted to relative risk, multivariable, control prevalance approximated with overall prevalence.
|
|
Osborne, 2/11/2021, retrospective, propensity score matching, USA, peer-reviewed, 6 authors.
|
risk of death, 59.4% lower, RR 0.41, p < 0.001, treatment 272 of 6,300 (4.3%), control 661 of 6,300 (10.5%), NNT 16, odds ratio converted to relative risk, 30 days, PSM.
|
|
risk of death, 60.5% lower, RR 0.40, p < 0.001, treatment 170 of 6,814 (2.5%), control 427 of 6,814 (6.3%), NNT 27, odds ratio converted to relative risk, 14 days, PSM.
|
|
Pan, 5/26/2021, retrospective, USA, peer-reviewed, 11 authors, study period 1 March, 2020 - 9 April, 2020.
|
risk of death, 13.0% higher, OR 1.13, p = 0.63, treatment 239, control 523, adjusted per study, MOS 6 vs. <6, multivariable, RR approximated with OR.
|
|
risk of death/intubation, 2.0% higher, OR 1.02, p = 0.93, treatment 239, control 523, adjusted per study, MOS 5+ vs. <5, multivariable, RR approximated with OR.
|
|
Prieto-Campo, 1/6/2024, retrospective, Spain, peer-reviewed, 6 authors.
|
risk of death, 13.0% higher, OR 1.13, p = 0.38, adjusted per study, case control OR.
|
|
risk of hospitalization, 3.0% lower, OR 0.97, p = 0.64, adjusted per study, case control OR.
|
|
risk of progression, no change, OR 1.00, p = 0.98, adjusted per study, case control OR.
|
|
risk of case, 8.0% lower, OR 0.92, p = 0.02, adjusted per study, case control OR.
|
|
Pérez-Segura, 10/4/2021, retrospective, multiple countries, peer-reviewed, 23 authors.
|
risk of death, 49.1% higher, RR 1.49, p < 0.001, treatment 66 of 155 (42.6%), control 183 of 608 (30.1%), odds ratio converted to relative risk.
|
|
Ramos-Rincón, 12/28/2020, retrospective, Spain, preprint, 25 authors, study period 1 March, 2020 - 29 May, 2020.
|
risk of death, 28.9% higher, RR 1.29, p = 0.02, treatment 132 of 264 (50.0%), control 253 of 526 (48.1%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Reese, 4/20/2021, retrospective, USA, preprint, 23 authors.
|
risk of death, 61.0% higher, HR 1.61, p < 0.001, treatment 4,921, control 4,921, propensity score matching, Cox proportional hazards, Table S55.
|
|
risk of severe case, 309.0% higher, OR 4.09, p < 0.001, treatment 4,921, control 4,921, propensity score matching, Table S47, RR approximated with OR.
|
|
Sakamaki, 9/27/2024, retrospective, Japan, peer-reviewed, mean age 52.1, 3 authors, study period 15 January, 2020 - 31 December, 2022.
|
risk of severe case, 37.0% higher, OR 1.37, p < 0.001, adjusted per study, multivariable, RR approximated with OR.
|
|
Sisinni, 10/4/2021, retrospective, Italy, peer-reviewed, 18 authors.
|
risk of death, 7.1% higher, RR 1.07, p = 0.65, treatment 93 of 253 (36.8%), control 251 of 731 (34.3%).
|
|
risk of death or respiratory support upgrade, 30.3% lower, RR 0.70, p = 0.01, treatment 253, control 731, multivariate.
|
|
Son, 7/30/2021, retrospective, propensity score matching, South Korea, peer-reviewed, 6 authors.
|
risk of death, 11.0% lower, OR 0.89, p = 0.67, treatment 58 of 210 (27.6%) cases,
54 of 210 (25.7%) controls, adjusted per study, case control OR, group 2, model 1, multivariable.
|
|
risk of death, 24.0% lower, OR 0.76, p = 0.52, treatment 37 of 128 (28.9%) cases,
31 of 128 (24.2%) controls, adjusted per study, case control OR, group 1, model 2, multivariable.
|
|
risk of progression, 7.0% higher, OR 1.07, p = 0.80, treatment 77 of 339 (22.7%) cases,
58 of 339 (17.1%) controls, adjusted per study, case control OR, complications, group 1, model 2, multivariable.
|
|
risk of progression, 9.0% lower, OR 0.91, p = 0.61, treatment 77 of 339 (22.7%) cases,
58 of 339 (17.1%) controls, adjusted per study, case control OR, complications, group 2, model 1, multivariable.
|
|
risk of case, 11.0% higher, OR 1.11, p = 0.21, treatment 313 of 3,825 (8.2%) cases,
531 of 7,650 (6.9%) controls, adjusted per study, case control OR, group 1, PSM 1, model 2, multivariable.
|
|
risk of case, 1.0% higher, OR 1.01, p = 0.90, treatment 431 of 7,223 (6.0%) cases,
752 of 14,446 (5.2%) controls, adjusted per study, case control OR, group 2, PSM 1, model 1, multivariable.
|
|
Sullerot, 1/7/2022, retrospective, propensity score weighting, multiple countries, peer-reviewed, 15 authors, study period 1 March, 2020 - 31 December, 2020.
|
risk of death, 10.0% higher, RR 1.10, p = 0.52, treatment 101 of 301 (33.6%), control 224 of 746 (30.0%).
|
|
risk of ICU admission, 109.7% higher, RR 2.10, p = 0.007, treatment 22 of 301 (7.3%), control 26 of 746 (3.5%).
|
|
hospitalization time, 10.0% higher, relative time 1.10, p = 0.02, treatment 301, control 746.
|
|
Tse, 6/2/2023, retrospective, China, peer-reviewed, 12 authors, study period 1 January, 2020 - 8 December, 2020.
|
risk of death/intubation, 67.0% lower, OR 0.33, p < 0.001, adjusted per study, propensity score matching, multivariable, day 30, RR approximated with OR.
|
|
Wang (B), 7/14/2020, retrospective, USA, peer-reviewed, 13 authors.
|
risk of death, 57.7% lower, RR 0.42, p = 0.43, treatment 1 of 9 (11.1%), control 13 of 49 (26.5%), NNT 6.5, odds ratio converted to relative risk.
|
|
Ware, 4/12/2024, retrospective, propensity score matching, USA, preprint, 7 authors, study period 2 March, 2020 - 13 June, 2022.
|
risk of death, 45.8% lower, RR 0.54, p = 0.001, treatment 7,531 of 81,830 (9.2%), control 13,890 of 81,830 (17.0%), NNT 13, propensity score matching, day 365.
|
|
Yuan, 12/18/2020, retrospective, China, peer-reviewed, 6 authors.
|
risk of death, 4.4% lower, RR 0.96, p = 0.89, treatment 11 of 52 (21.2%), control 29 of 131 (22.1%), NNT 102, odds ratio converted to relative risk, mutivariate.
|
|
Zadeh, 12/20/2022, retrospective, USA, peer-reviewed, mean age 62.2, 8 authors.
|
risk of death, 37.0% lower, RR 0.63, p = 0.28.
|
|
risk of ICU admission, 1.0% higher, RR 1.01, p = 0.79.
|