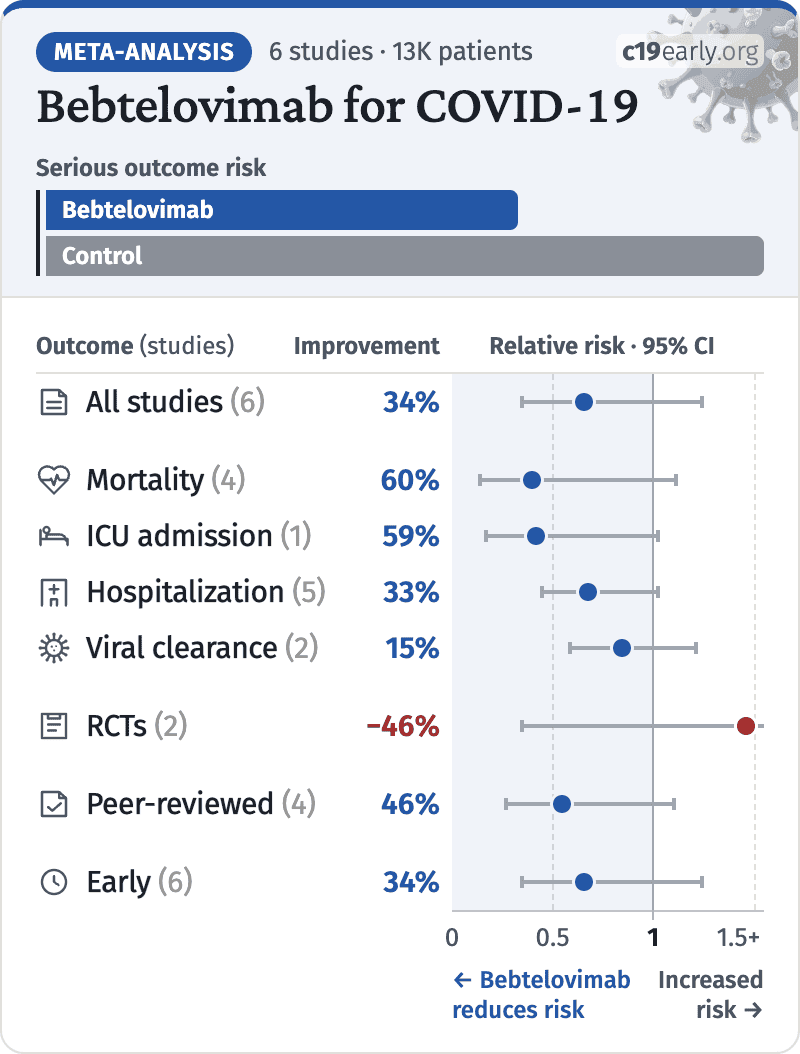
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/btmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
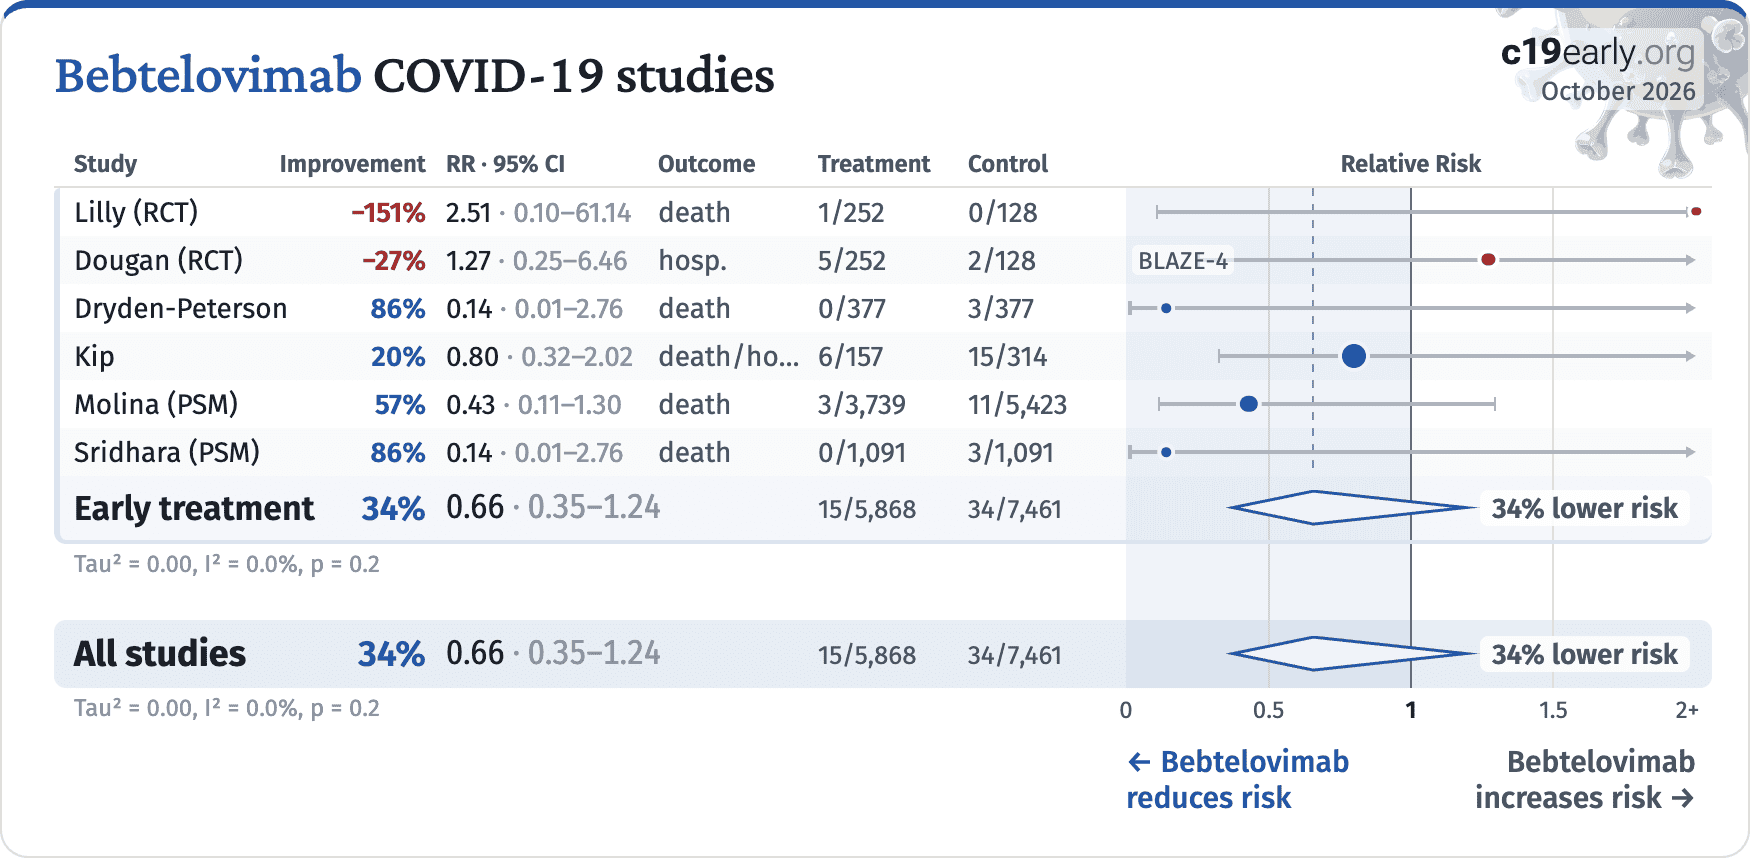
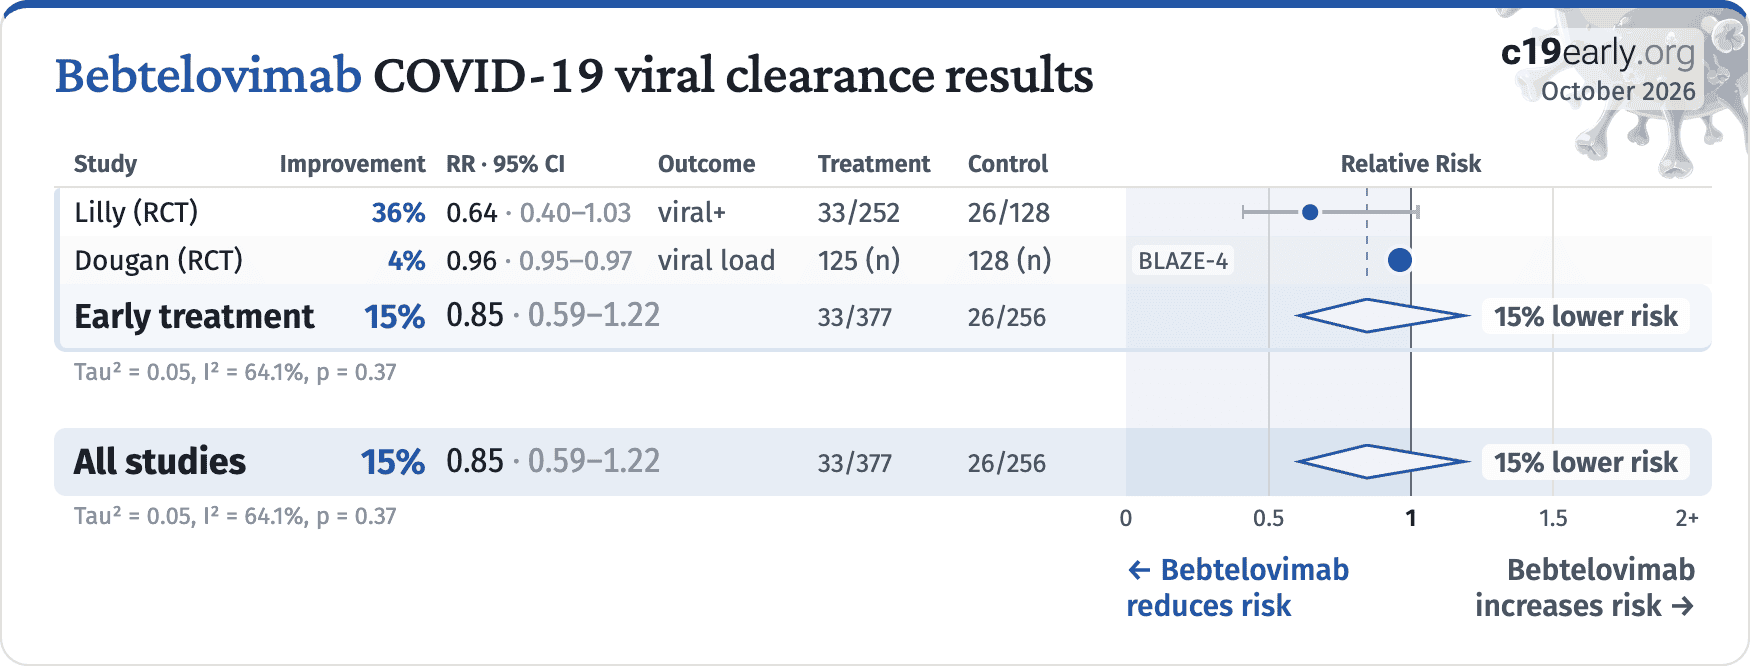
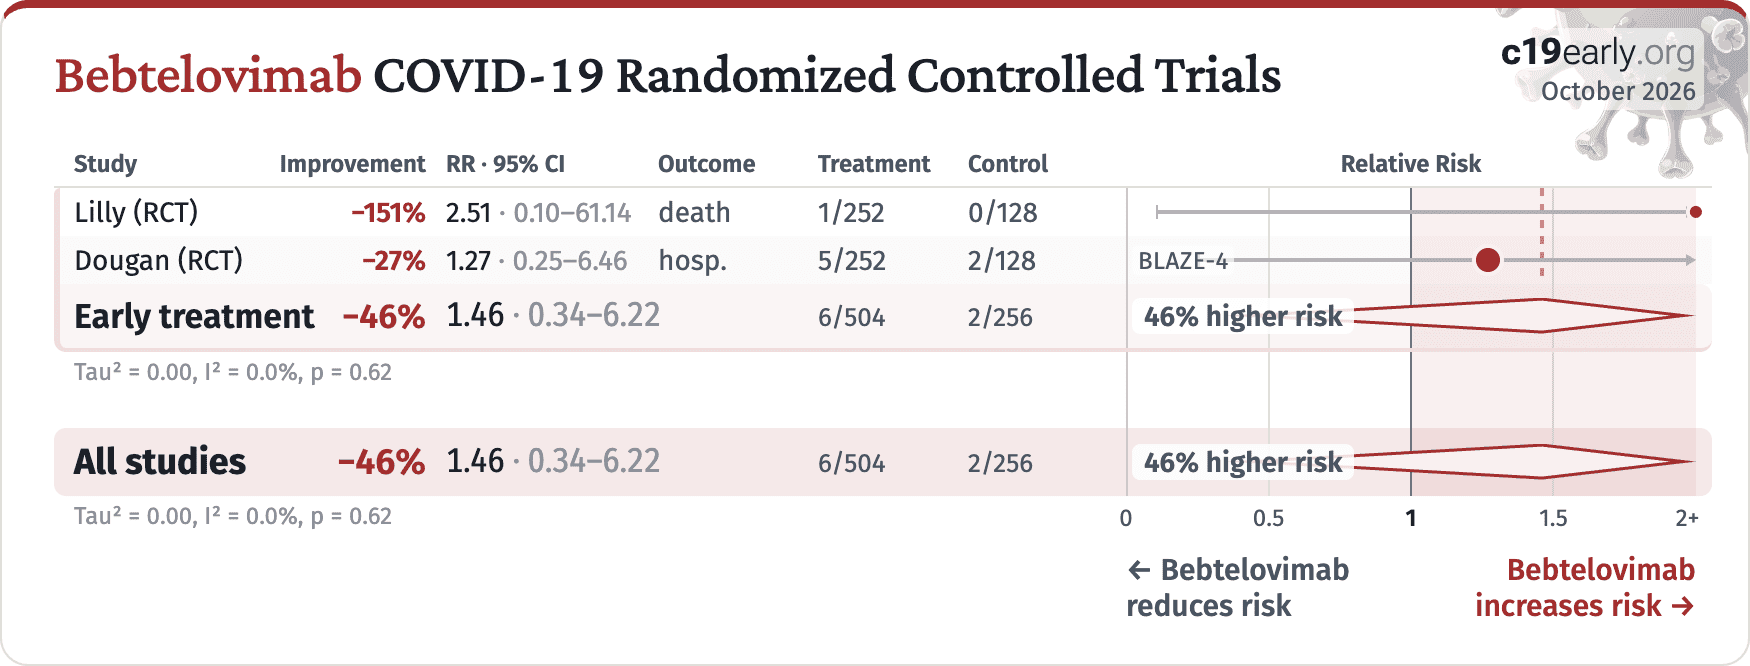
Dougan, 3/12/2022, Randomized Controlled Trial, USA, preprint, 22 authors, study period 19 April, 2021 - 19 July, 2021, average treatment delay 3.0 days, trial NCT04634409 (history) (BLAZE-4).
|
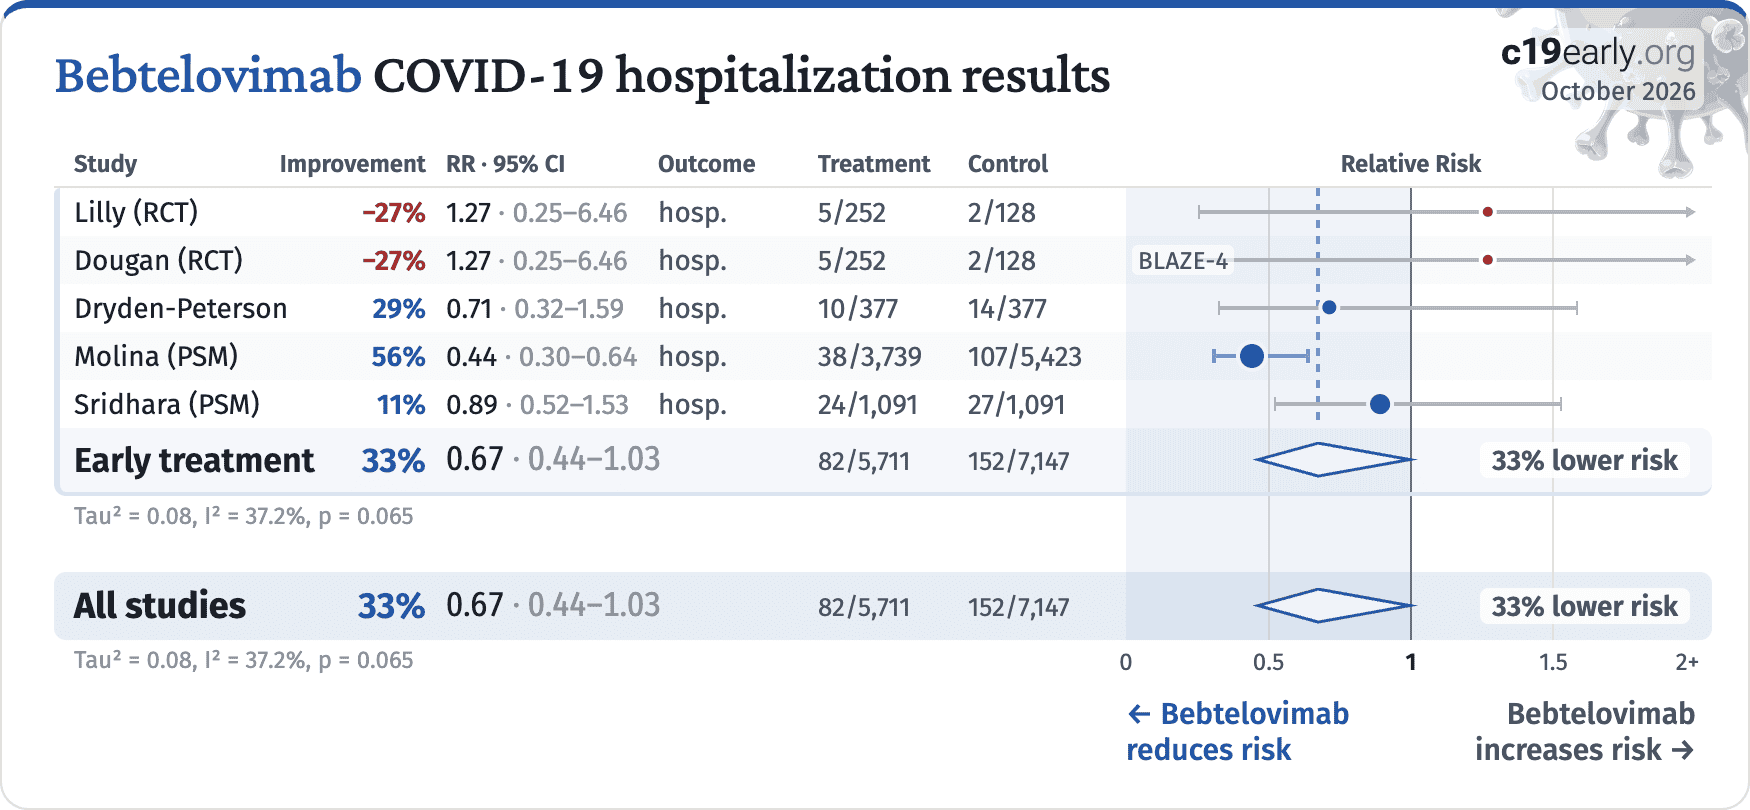
risk of hospitalization, 27.0% higher, RR 1.27, p = 1.00, treatment 5 of 252 (2.0%), control 2 of 128 (1.6%), combined bebtelovimab arms.
|
|
risk of hospitalization, 2.4% higher, RR 1.02, p = 1.00, treatment 2 of 125 (1.6%), control 2 of 128 (1.6%), bebtelovimab only.
|
|
relative viral load reduction, 4.0% better, RR 0.96, p < 0.001, treatment mean 3.77 (±0.21) n=125, control mean 3.62 (±0.2) n=128, day 7.
|
|
relative viral load reduction, 29.7% better, RR 0.70, p < 0.001, treatment mean 3.03 (±0.19) n=125, control mean 2.13 (±0.19) n=128, day 5.
|
|
relative viral load reduction, 15.4% better, RR 0.85, p < 0.001, treatment mean 1.43 (±0.2) n=125, control mean 1.21 (±0.2) n=128, day 3.
|
|
risk of no viral clearance, 38.6% lower, RR 0.61, p = 0.12, treatment 15 of 125 (12.0%), control 25 of 128 (19.5%), NNT 13, persistently high viral load, day 7, primary outcome.
|
|
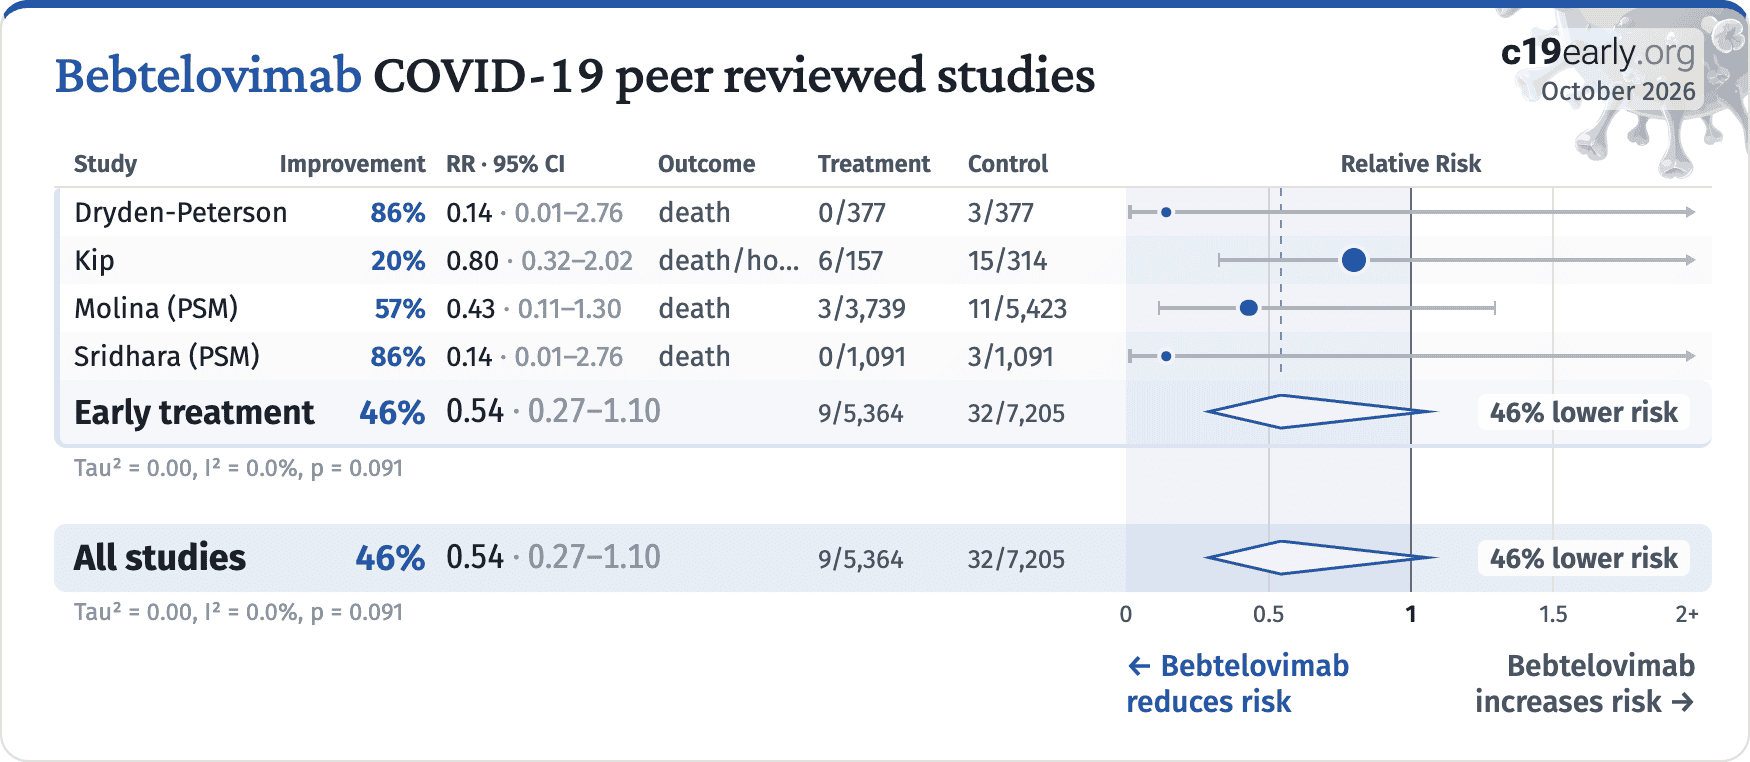
Dryden-Peterson, 10/27/2022, retrospective, USA, peer-reviewed, 7 authors, study period 16 March, 2022 - 31 May, 2022, average treatment delay 3.0 days.
|
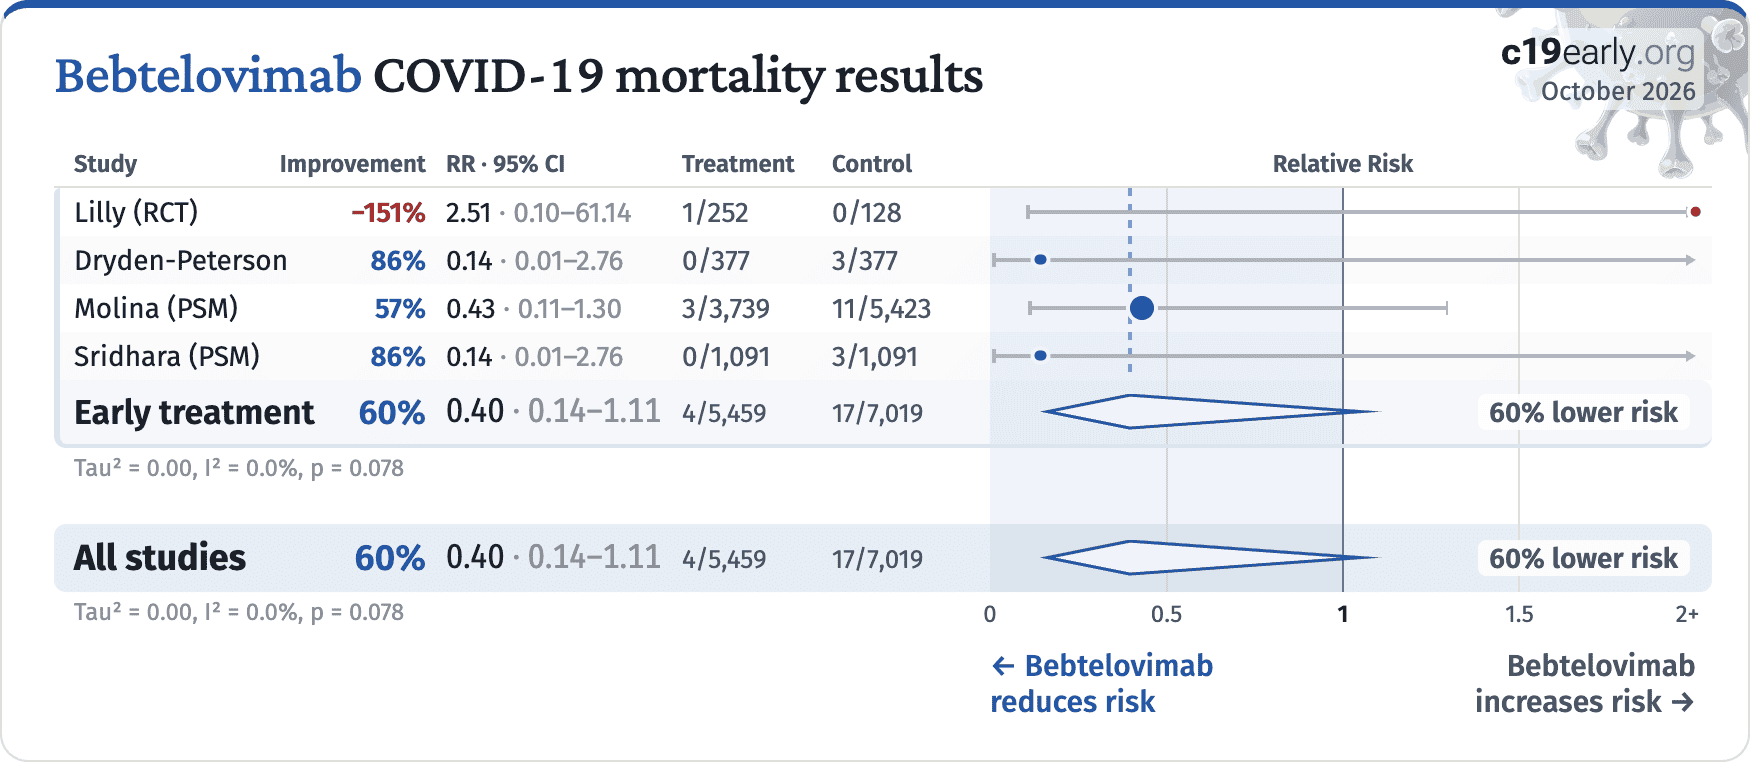
risk of death, 85.7% lower, RR 0.14, p = 0.25, treatment 0 of 377 (0.0%), control 3 of 377 (0.8%), NNT 126, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of death/hospitalization, 43.0% lower, RR 0.57, p = 0.14, treatment 10 of 377 (2.7%), control 17 of 377 (4.5%), NNT 54.
|
|
risk of hospitalization, 28.6% lower, RR 0.71, p = 0.53, treatment 10 of 377 (2.7%), control 14 of 377 (3.7%), NNT 94.
|
|
Kip, 4/4/2023, retrospective, USA, peer-reviewed, 16 authors, study period 8 December, 2020 - 31 August, 2022.
|
risk of death/hospitalization, 20.0% lower, RR 0.80, p = 0.65, treatment 6 of 157 (3.8%), control 15 of 314 (4.8%), NNT 105, omicron variant, day 28.
|
|
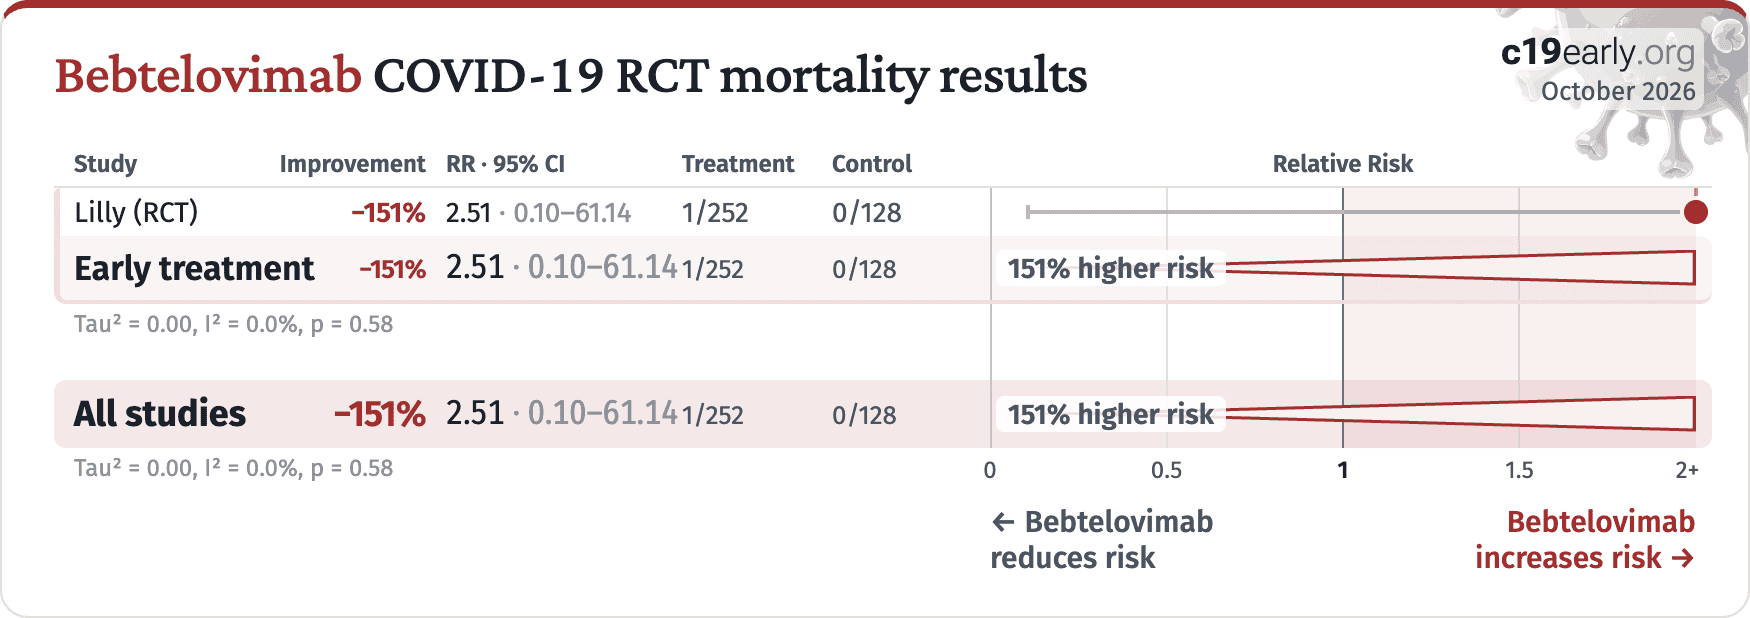
Lilly, 2/12/2022, Randomized Controlled Trial, USA, preprint, 1 author, study period 29 October, 2020 - 18 October, 2021, average treatment delay 3.6 days, trial NCT04634409 (history).
|
risk of death, 150.8% higher, RR 2.51, p = 1.00, treatment 1 of 252 (0.4%), control 0 of 128 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), combined bebtelovimab arms.
|
|
risk of death, 200.8% higher, RR 3.01, p = 0.50, treatment 1 of 127 (0.8%), control 0 of 128 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), bamlanivimab, etesevimab, and bebtelovimab.
|
|
risk of hospitalization, 27.0% higher, RR 1.27, p = 1.00, treatment 5 of 252 (2.0%), control 2 of 128 (1.6%), combined bebtelovimab arms.
|
|
risk of hospitalization, 51.2% higher, RR 1.51, p = 0.68, treatment 3 of 127 (2.4%), control 2 of 128 (1.6%), bamlanivimab, etesevimab, and bebtelovimab.
|
|
risk of hospitalization, 2.4% higher, RR 1.02, p = 1.00, treatment 2 of 125 (1.6%), control 2 of 128 (1.6%), bebtelovimab.
|
|
risk of no viral clearance, 35.5% lower, RR 0.64, p = 0.07, treatment 33 of 252 (13.1%), control 26 of 128 (20.3%), NNT 14, day 7 persistently high viral load, combined bebtelovimab arms, primary outcome.
|
|
risk of no viral clearance, 38.0% lower, RR 0.62, p = 0.13, treatment 16 of 127 (12.6%), control 26 of 128 (20.3%), NNT 13, day 7 persistently high viral load, bamlanivimab, etesevimab, and bebtelovimab, primary outcome.
|
|
risk of no viral clearance, 33.0% lower, RR 0.67, p = 0.18, treatment 17 of 125 (13.6%), control 26 of 128 (20.3%), NNT 15, day 7 persistently high viral load, bebtelovimab, primary outcome.
|
|
Molina, 4/16/2023, retrospective, USA, peer-reviewed, 11 authors, study period 6 April, 2022 - 11 October, 2022.
|
risk of death, 57.0% lower, RR 0.43, p = 0.14, treatment 3 of 3,739 (0.1%), control 11 of 5,423 (0.2%), NNT 816, adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable.
|
|
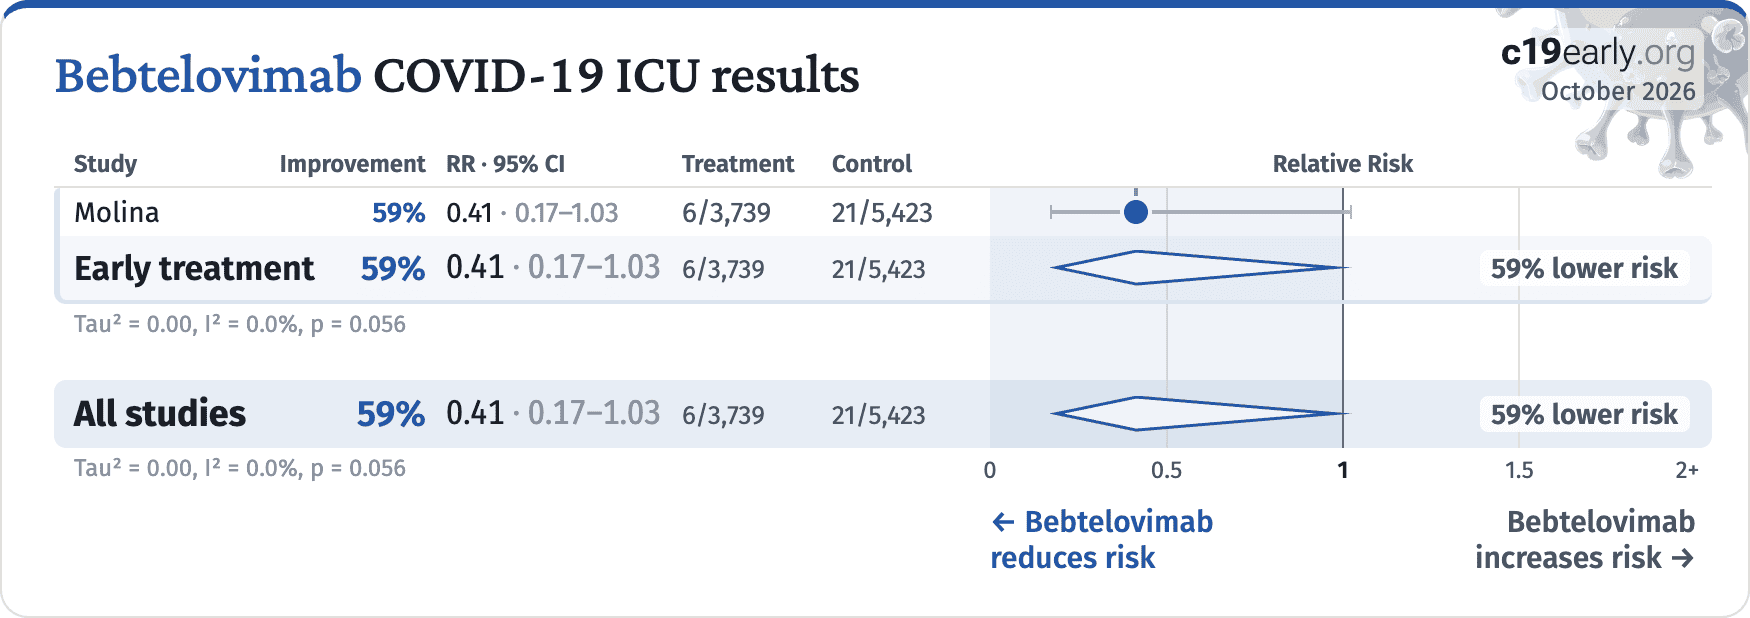
risk of ICU admission, 58.6% lower, RR 0.41, p = 0.05, treatment 6 of 3,739 (0.2%), control 21 of 5,423 (0.4%), NNT 441.
|
|
risk of hospitalization, 55.5% lower, RR 0.44, p < 0.001, treatment 38 of 3,739 (1.0%), control 107 of 5,423 (2.0%), NNT 105, adjusted per study, odds ratio converted to relative risk, COVID-19, propensity score matching, multivariable.
|
|
risk of hospitalization, 46.5% lower, RR 0.54, p < 0.001, treatment 48 of 3,739 (1.3%), control 116 of 5,423 (2.1%), NNT 117, adjusted per study, odds ratio converted to relative risk, all cause, propensity score matching, multivariable.
|
|
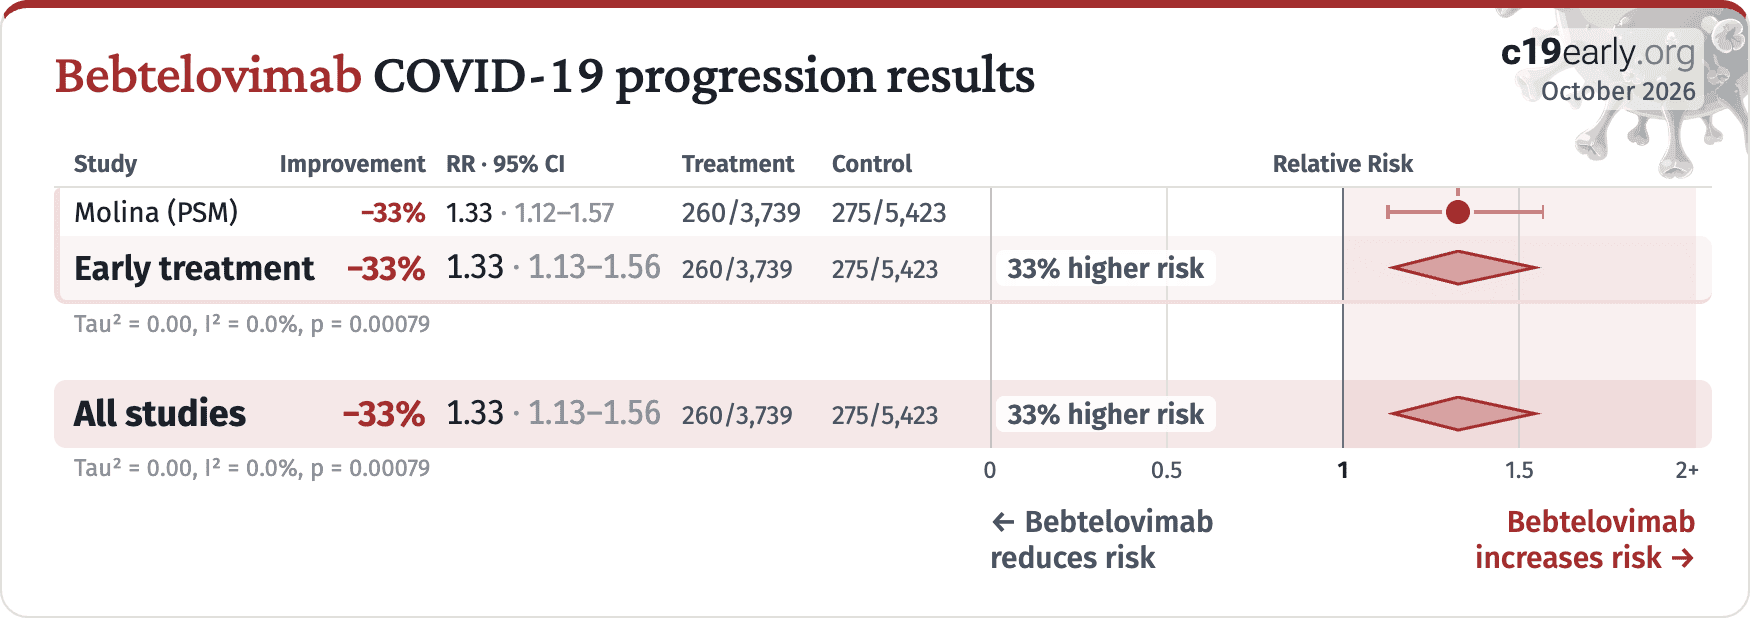
risk of progression, 32.6% higher, RR 1.33, p = 0.001, treatment 260 of 3,739 (7.0%), control 275 of 5,423 (5.1%), adjusted per study, odds ratio converted to relative risk, ED visit, propensity score matching, multivariable.
|
|
Sridhara, 4/28/2023, retrospective, USA, peer-reviewed, 13 authors, study period 5 April, 2022 - 1 August, 2022.
|
risk of death, 85.7% lower, RR 0.14, p = 0.25, treatment 0 of 1,091 (0.0%), control 3 of 1,091 (0.3%), NNT 364, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), propensity score matching, day 30.
|
|
risk of death/hospitalization, 25.0% lower, HR 0.75, p = 0.31, treatment 24 of 1,091 (2.2%), control 28 of 1,091 (2.6%), adjusted per study, propensity score matching, multivariable, Cox proportional hazards.
|
|
risk of hospitalization, 11.1% lower, RR 0.89, p = 0.78, treatment 24 of 1,091 (2.2%), control 27 of 1,091 (2.5%), NNT 364, propensity score matching, day 30RETRO.
|