Publishing is often biased
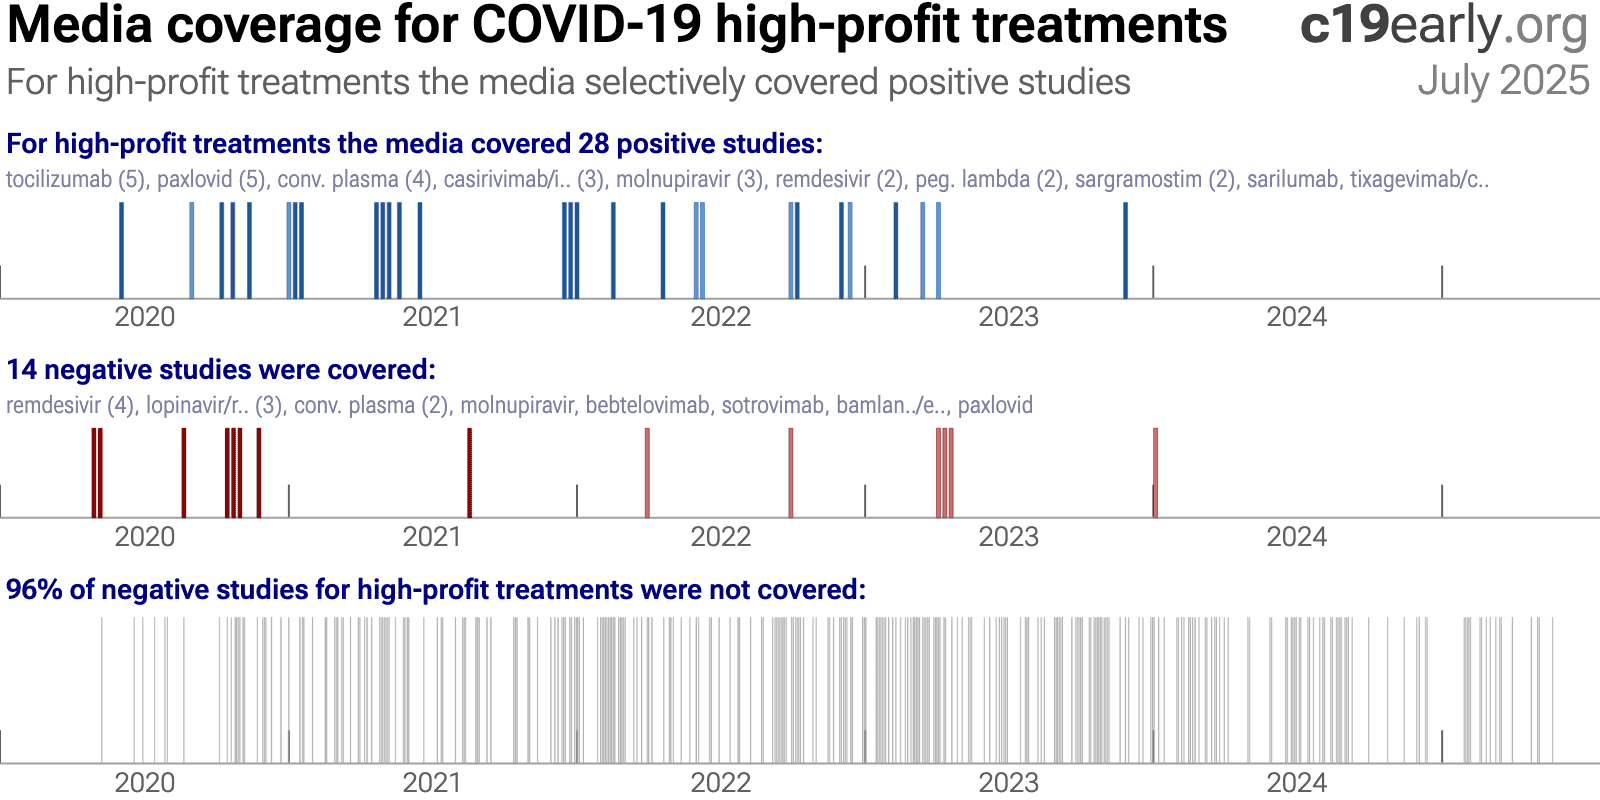
towards positive results, however evidence suggests that there may be a negative bias for
inexpensive treatments for COVID-19. Both negative and positive results are
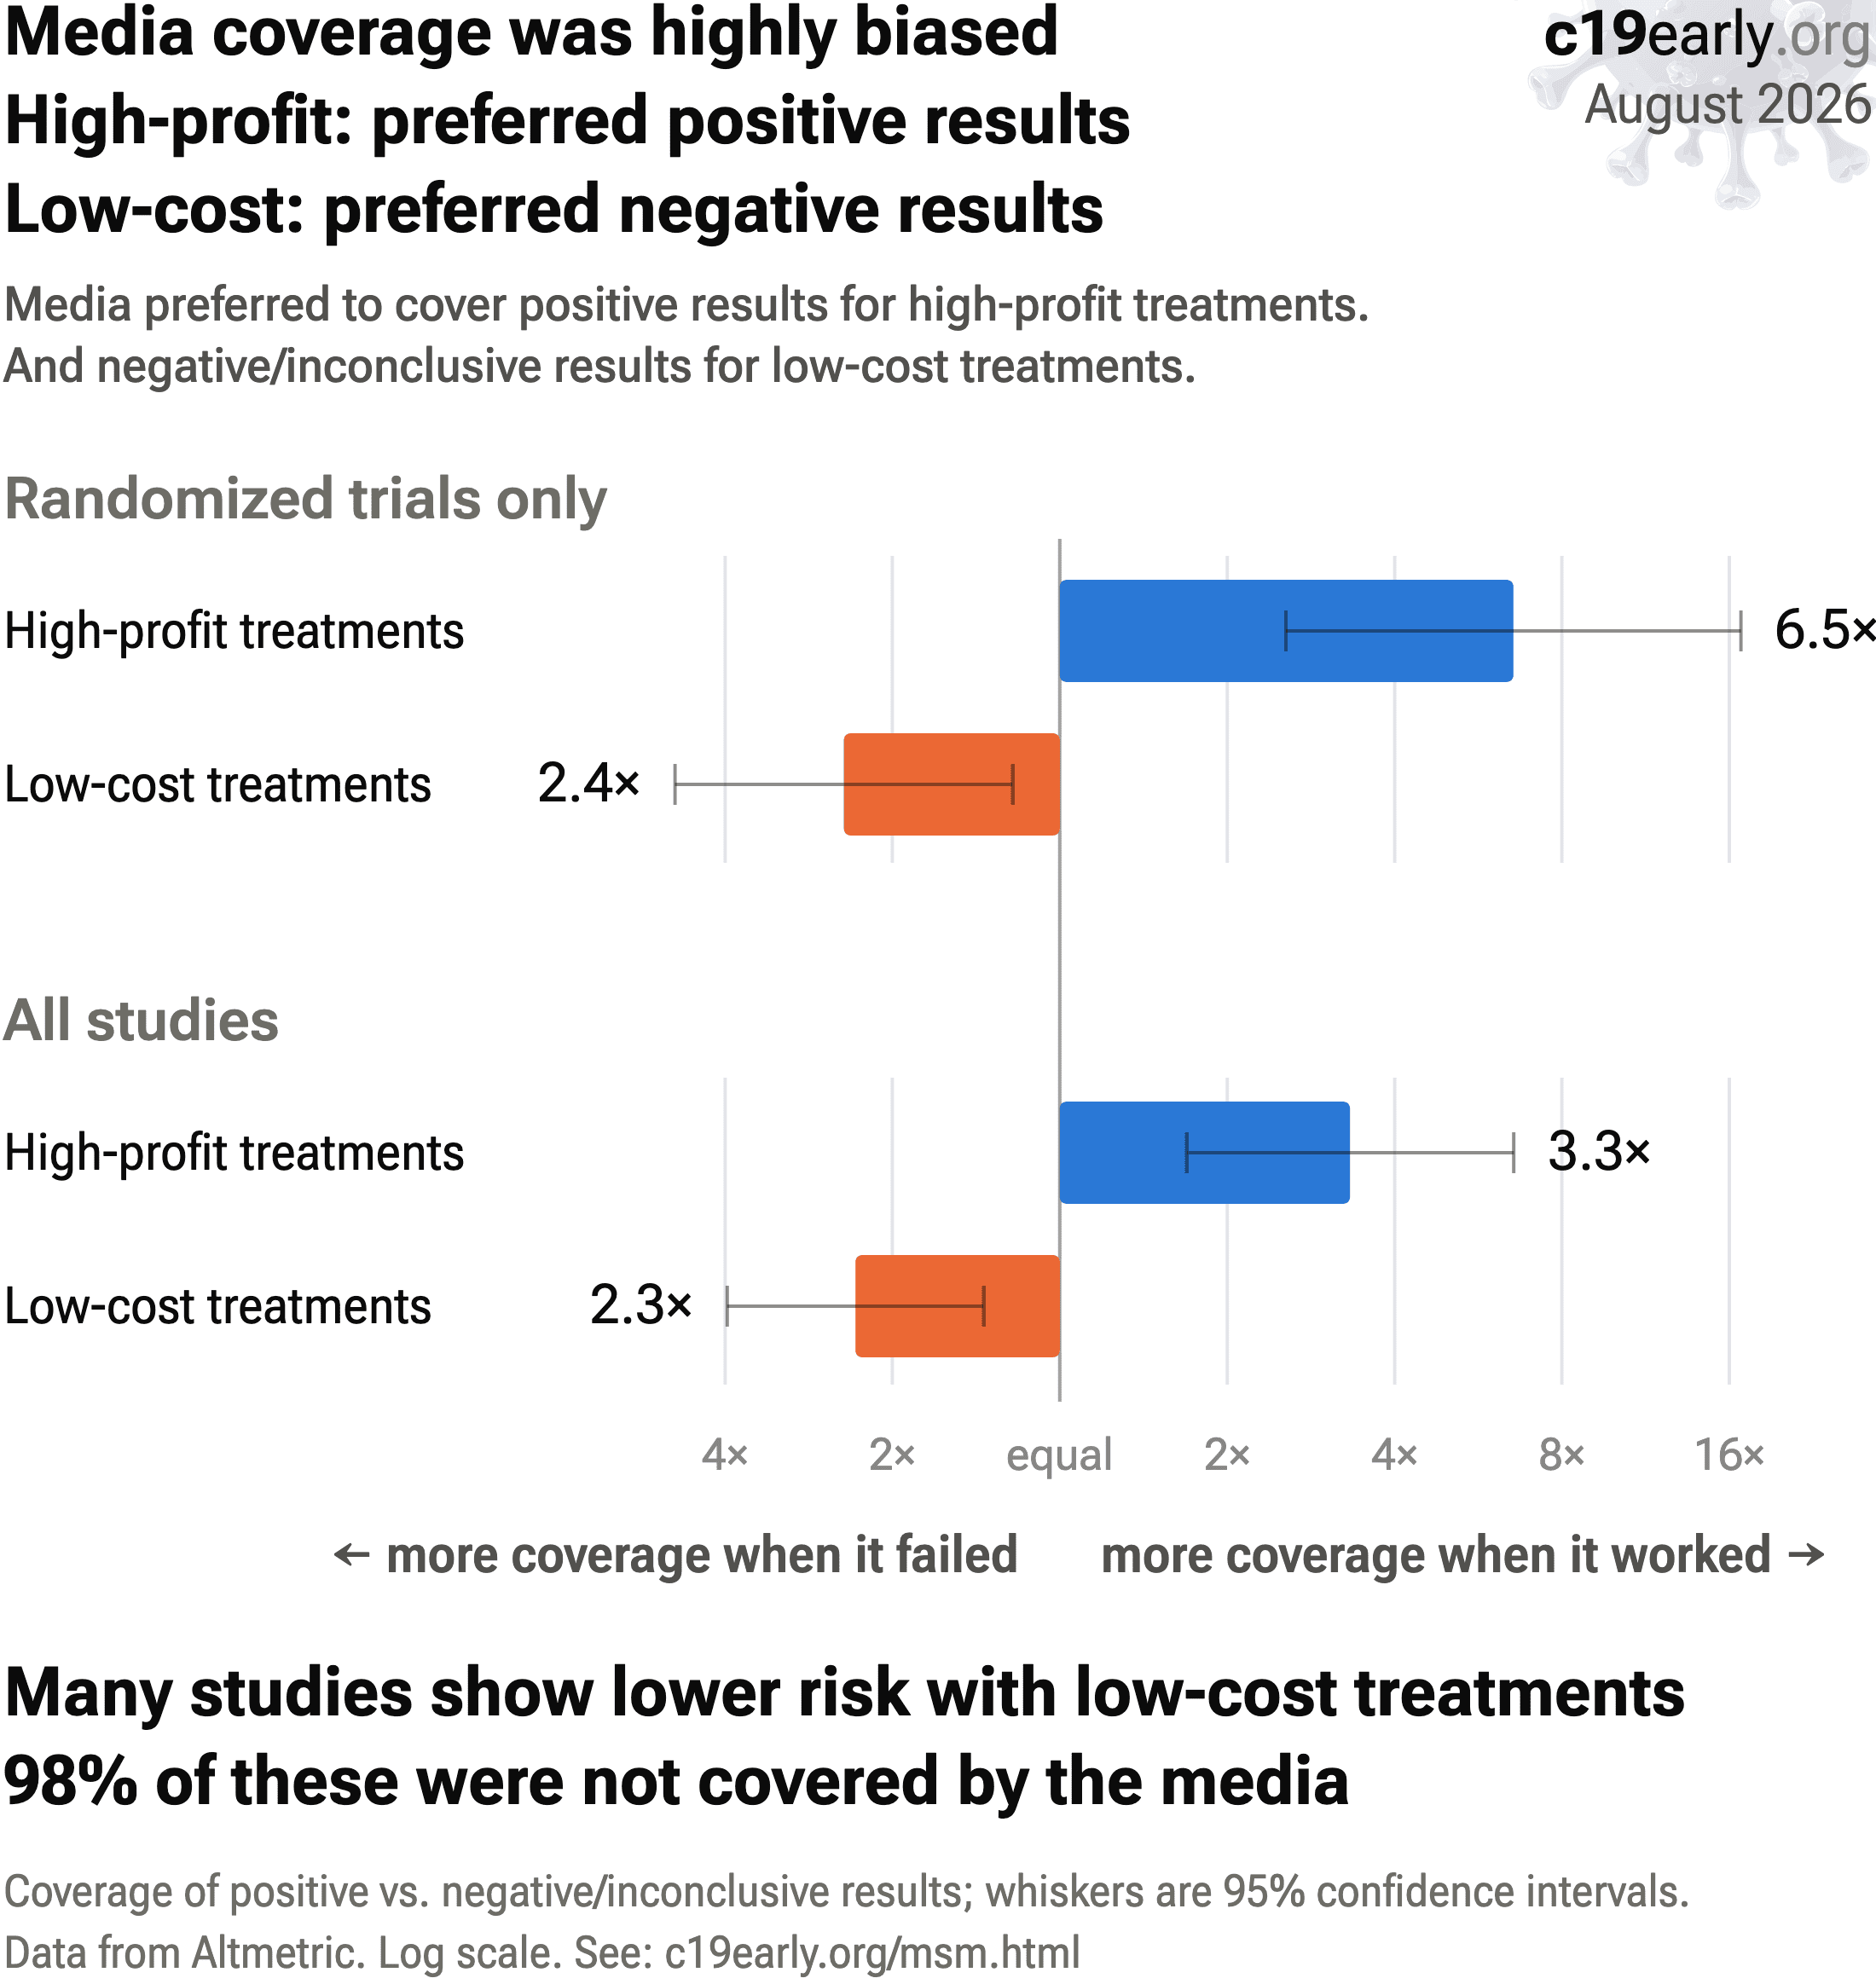
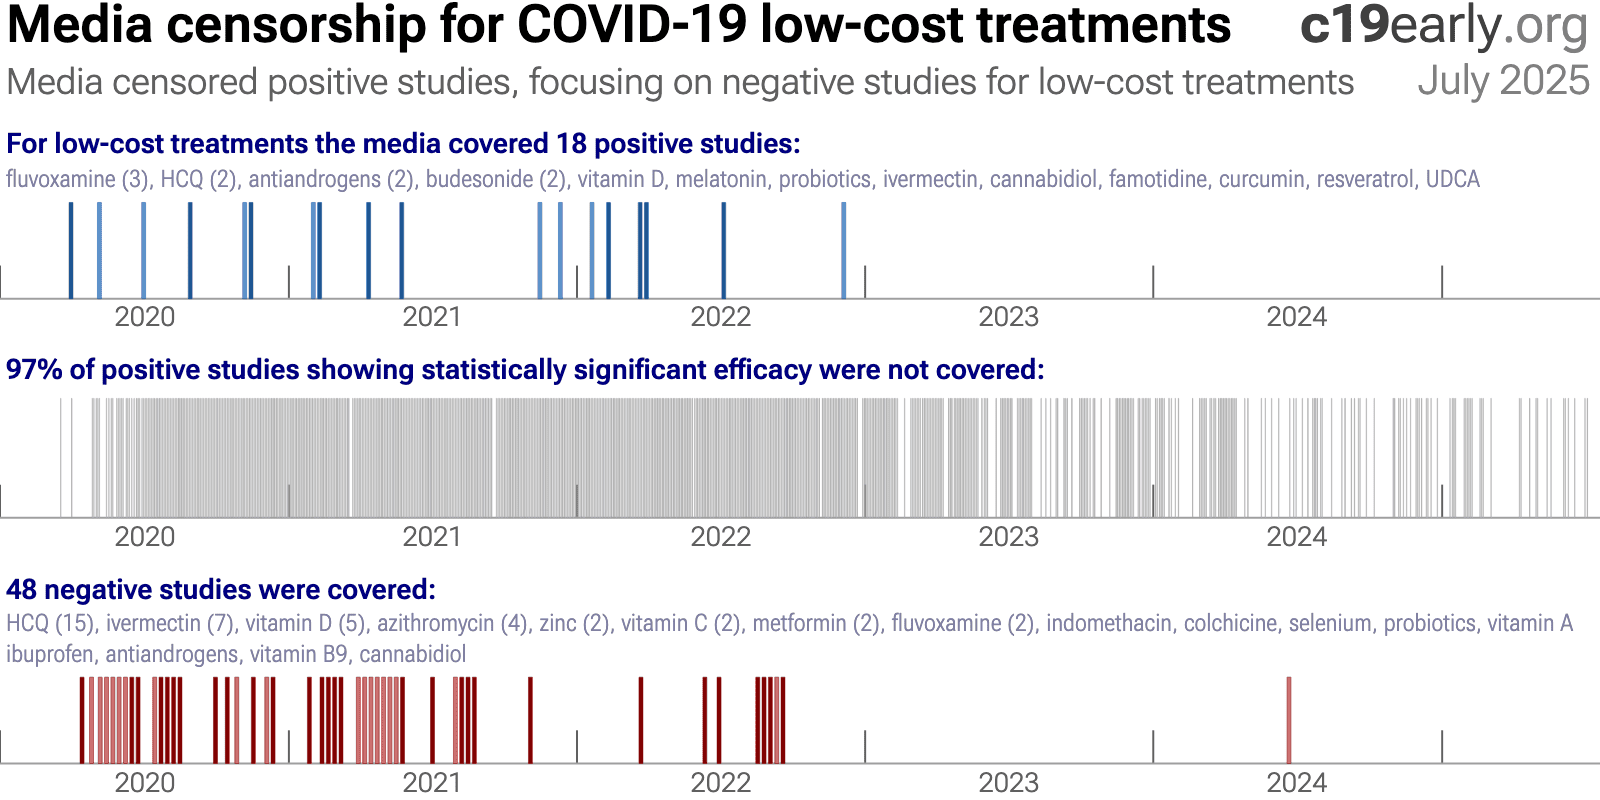
very important for COVID-19, media in many countries prioritizes negative
results for inexpensive treatments (inverting the typical incentive for
scientists that value media recognition), and there are many reports of
difficulty publishing positive results
106-.
For resveratrol, there is currently not
enough data to evaluate publication bias with high confidence.
One method to evaluate bias is to compare prospective vs.
retrospective studies. Prospective studies are more likely to be published
regardless of the result, while retrospective studies are more likely to
exhibit bias. For example, researchers may perform preliminary analysis with
minimal effort and the results may influence their decision to continue.
Retrospective studies also provide more opportunities for the specifics of
data extraction and adjustments to influence results.
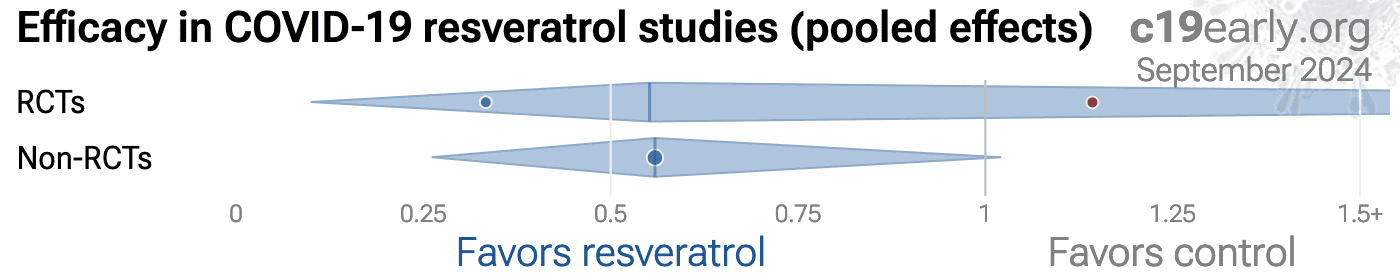
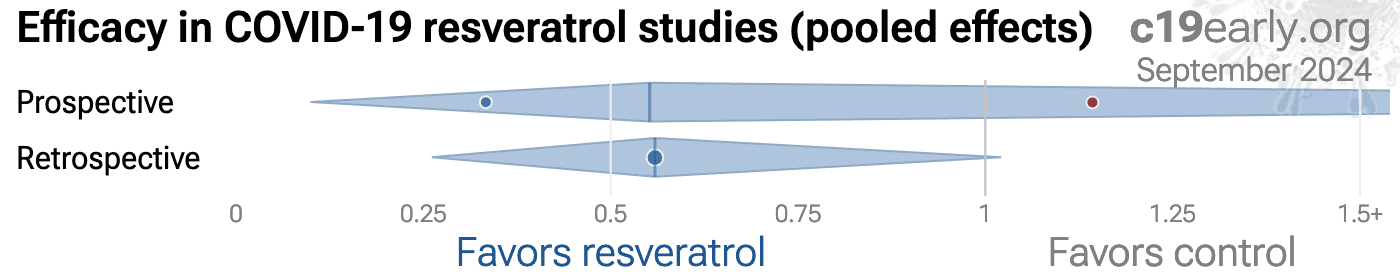
Fig. 23 shows a scatter plot of
results for prospective and retrospective studies.
100% of retrospective studies
report positive effects, compared to
50% of prospective studies, consistent with a bias toward publishing positive results.
The median effect size for
retrospective studies is 44% improvement,
compared to 26% for prospective
studies, suggesting a potential bias towards publishing results showing higher efficacy.
Fig. 23. Prospective vs. retrospective studies.
The diamonds show the results of random-effects meta-analysis.
Pharmaceutical drug
trials often have conflicts of interest whereby sponsors or trial staff have a
financial interest in the outcome being positive. Resveratrol for COVID-19
lacks this because it is off-patent, has multiple manufacturers, and is very low cost.
In contrast, most COVID-19 resveratrol trials have been run by
physicians on the front lines with the primary goal of finding the best
methods to save human lives and minimize the collateral damage caused by
COVID-19. While pharmaceutical companies are careful to run trials under
optimal conditions (for example, restricting patients to those most likely to
benefit, only including patients that can be treated soon after onset when
necessary, and ensuring accurate dosing), not all resveratrol trials
represent the optimal conditions for efficacy.
Summary statistics from
meta-analysis necessarily lose information. As with all meta-analyses, studies
are
heterogeneous, with differences
in treatment delay, treatment regimen, patient demographics, variants,
conflicts of interest, standard of care, and
other factors. We provide analyses for specific
outcomes and by treatment delay, and we aim to identify key characteristics in
the forest plots and summaries. Results should be viewed in the context of
study characteristics.
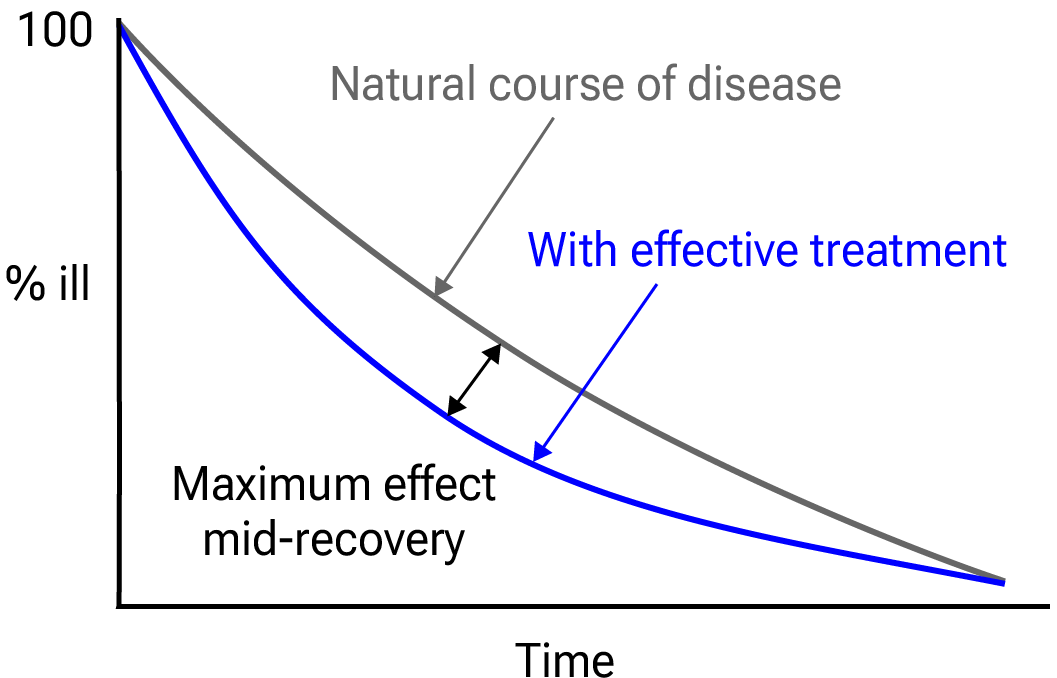
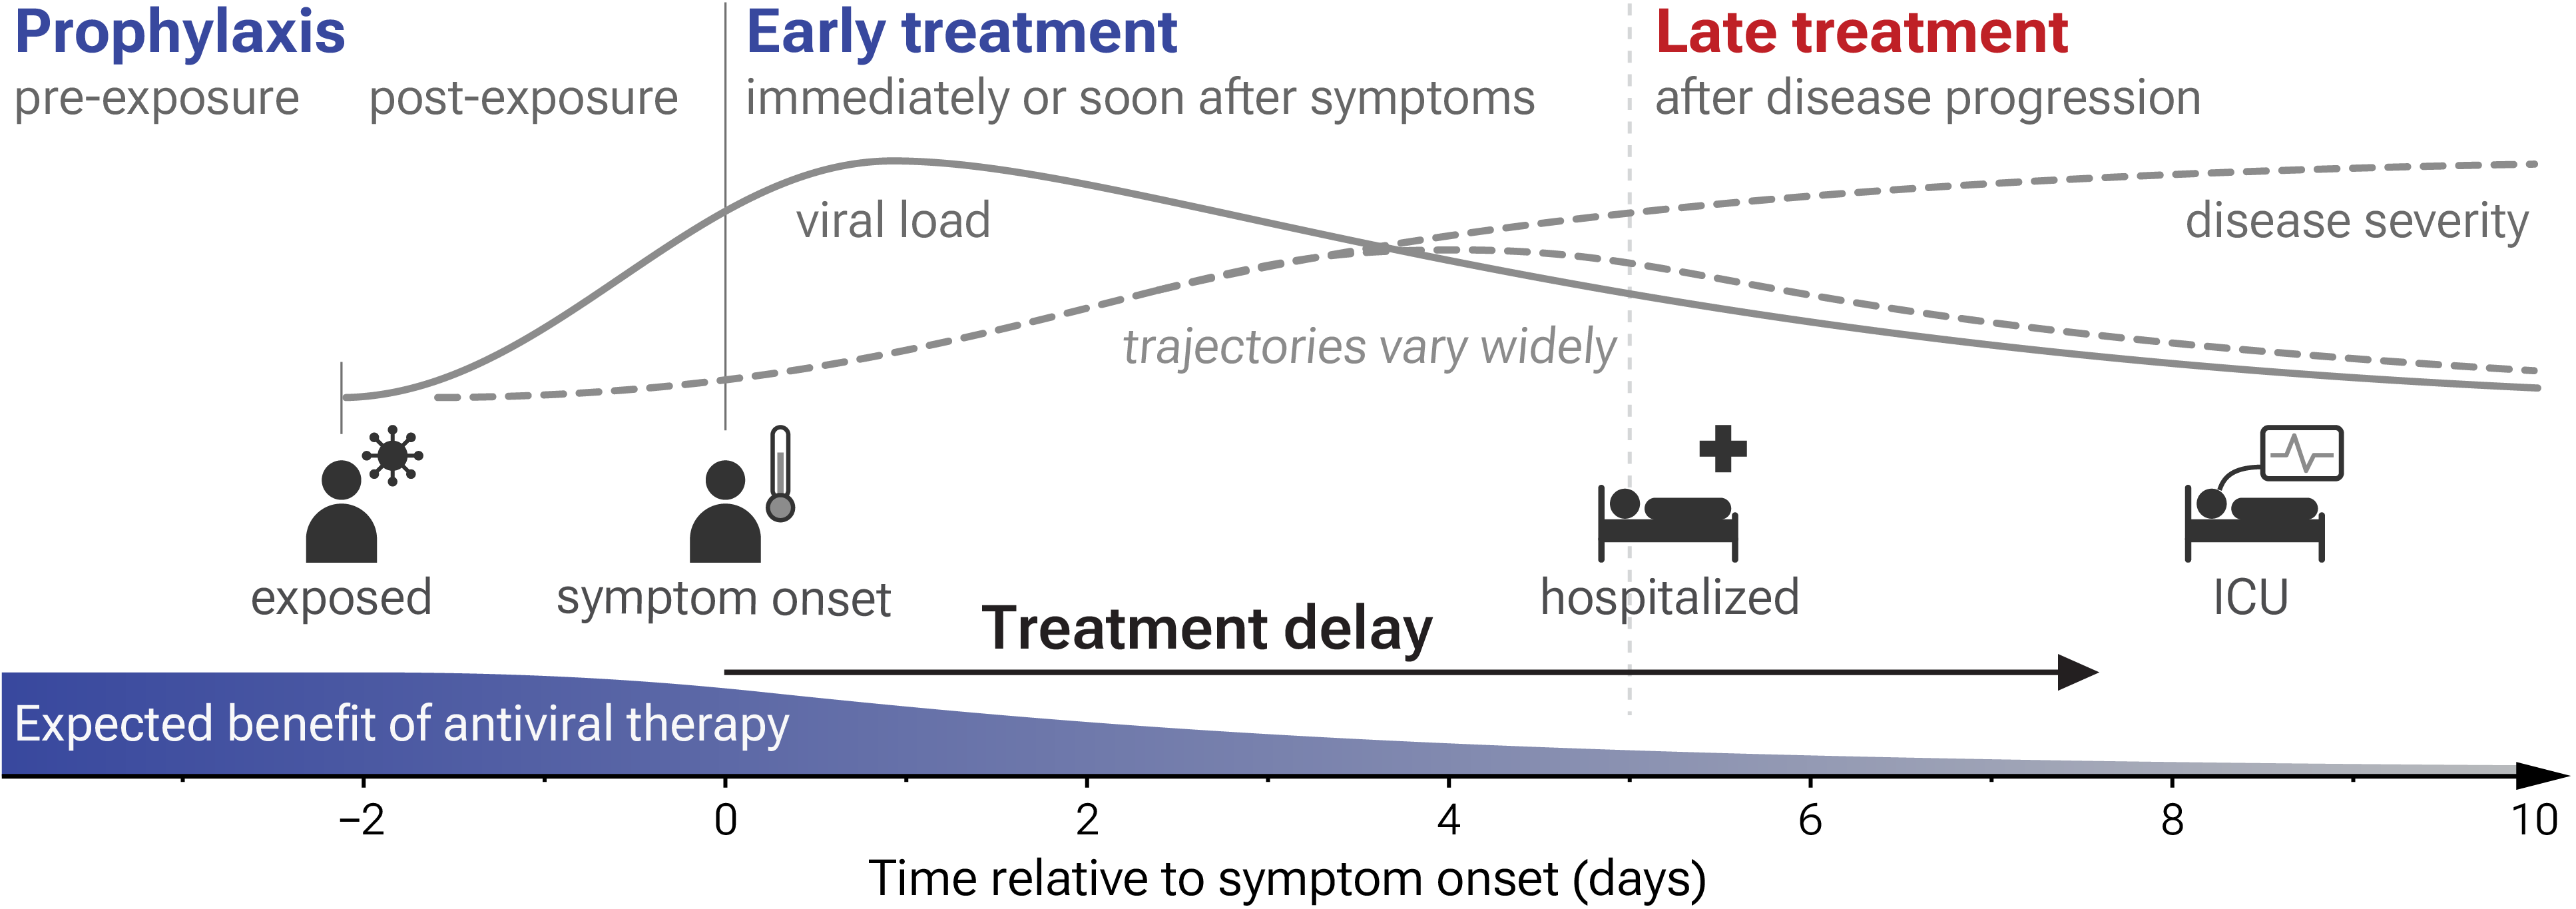
Some analyses classify treatment based on early or late
administration, as done here, while others distinguish between mild, moderate,
and severe cases. Viral load does not indicate degree of symptoms — for
example patients may have a high viral load while being asymptomatic. With
regard to treatments that have antiviral properties, timing of treatment is
critical — late administration may be less helpful regardless of
severity.
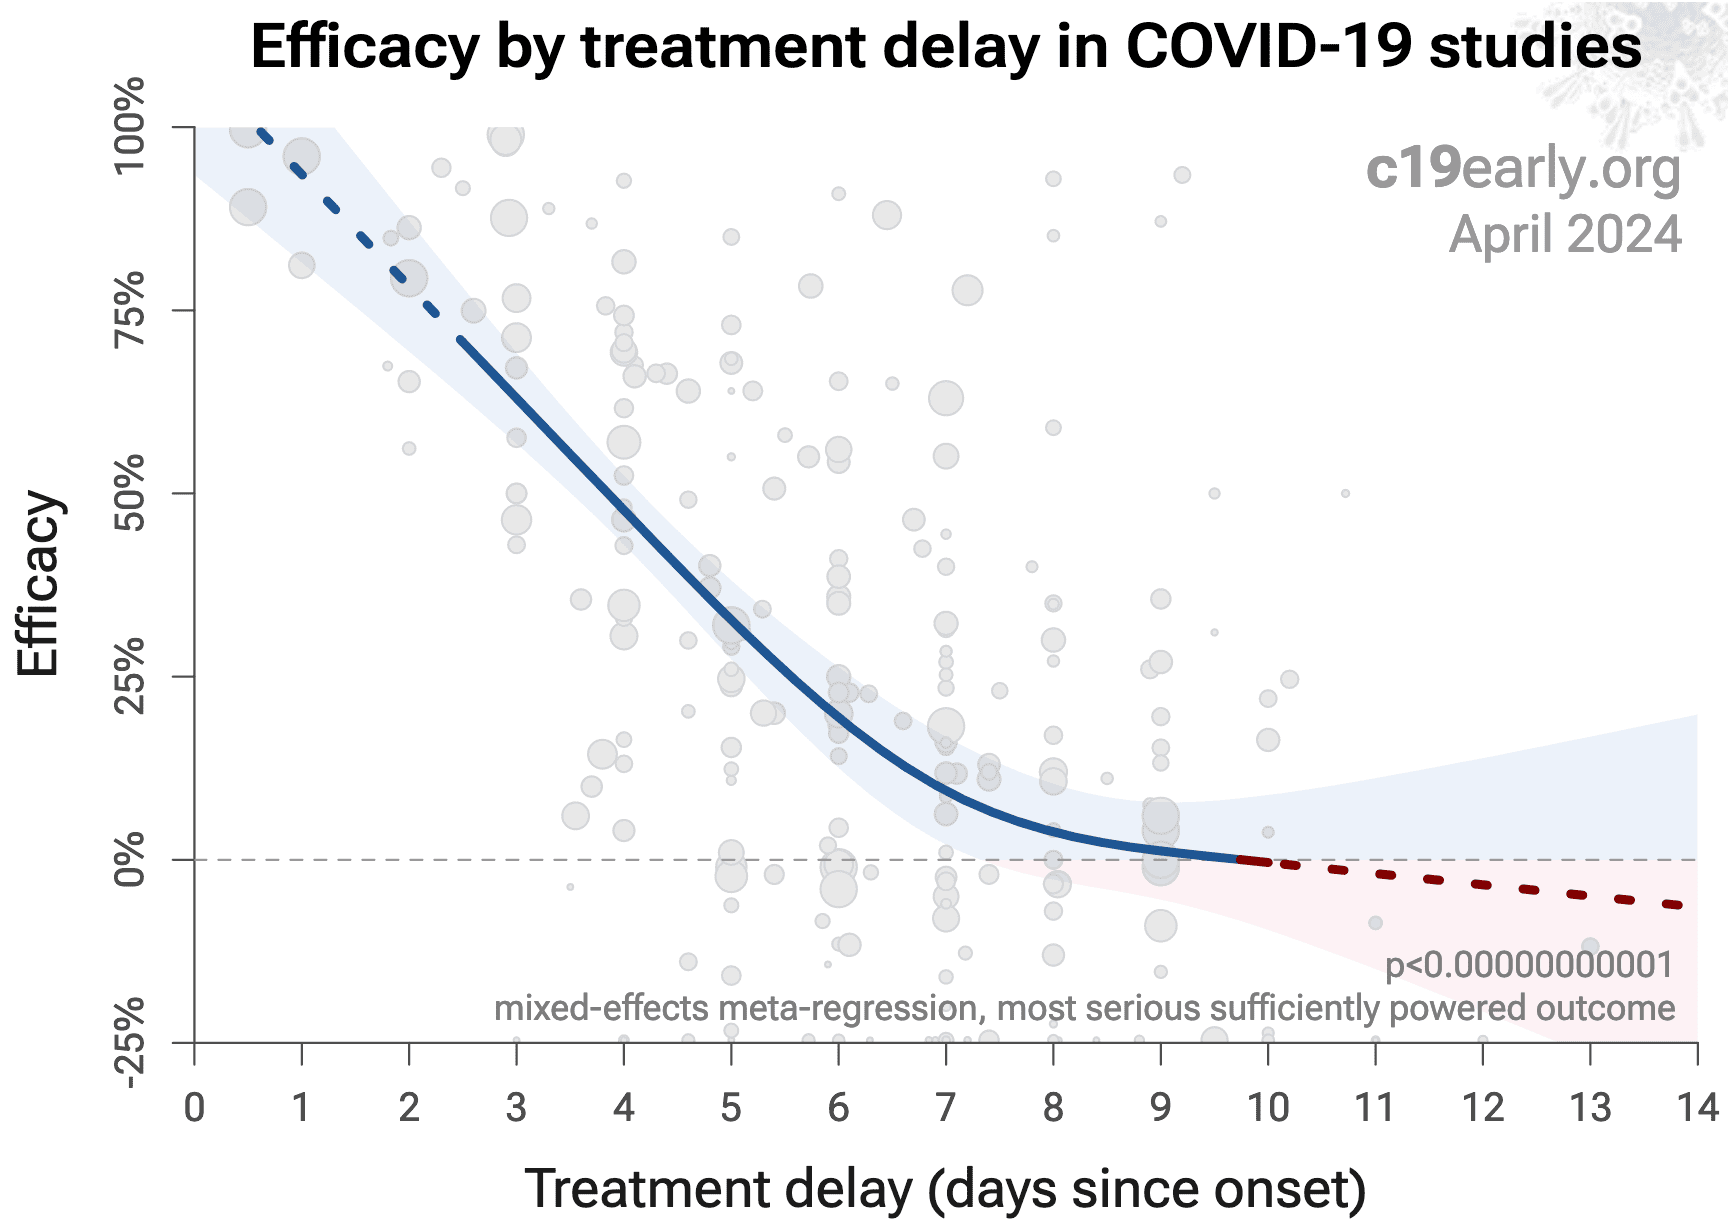
Details of treatment delay per patient is often not available.
For example, a study may treat 90% of patients relatively early, but the
events driving the outcome may come from 10% of patients treated very late.
Our 5 day cutoff for early treatment may be too conservative,
5 days may be too late in many cases.
Comparison across treatments is confounded by differences in
the studies performed, for example dose, variants, and conflicts of interest.
Trials with conflicts of interest may use designs better suited to the
preferred outcome.
In some cases, the most serious outcome has very few events,
resulting in lower confidence results being used in pooled analysis, however
the method is simpler and more transparent. This is less critical as the
number of studies increases. Restriction to outcomes with sufficient power may
be beneficial in pooled analysis and improve accuracy when there are few
studies, however we maintain our pre-specified method to avoid any
retrospective changes.
Studies show that combinations of treatments can be highly
synergistic and may result in many times greater efficacy than individual
treatments alone
80-104.
Therefore standard of care may be critical and benefits may diminish or
disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on
submissions. Accuracy benefits from widespread review and submission of
updates and corrections from reviewers. Less popular treatments may receive
fewer reviews.
No treatment or intervention is 100% available and
effective for all current and future variants. Efficacy may vary significantly
with different variants and within different populations. All treatments have
potential side effects. Propensity to experience side effects may be predicted
in advance by qualified physicians. We do not provide medical advice. Before
taking any medication, consult a qualified physician who can compare all
options, provide personalized advice, and provide details of risks and
benefits based on individual medical history and situations.