Montelukast reduces COVID-19 risk: real-time meta-analysis of 9 studies
Serious outcome risk
Outcome (studies)
Improvement
Relative risk · 95% CI
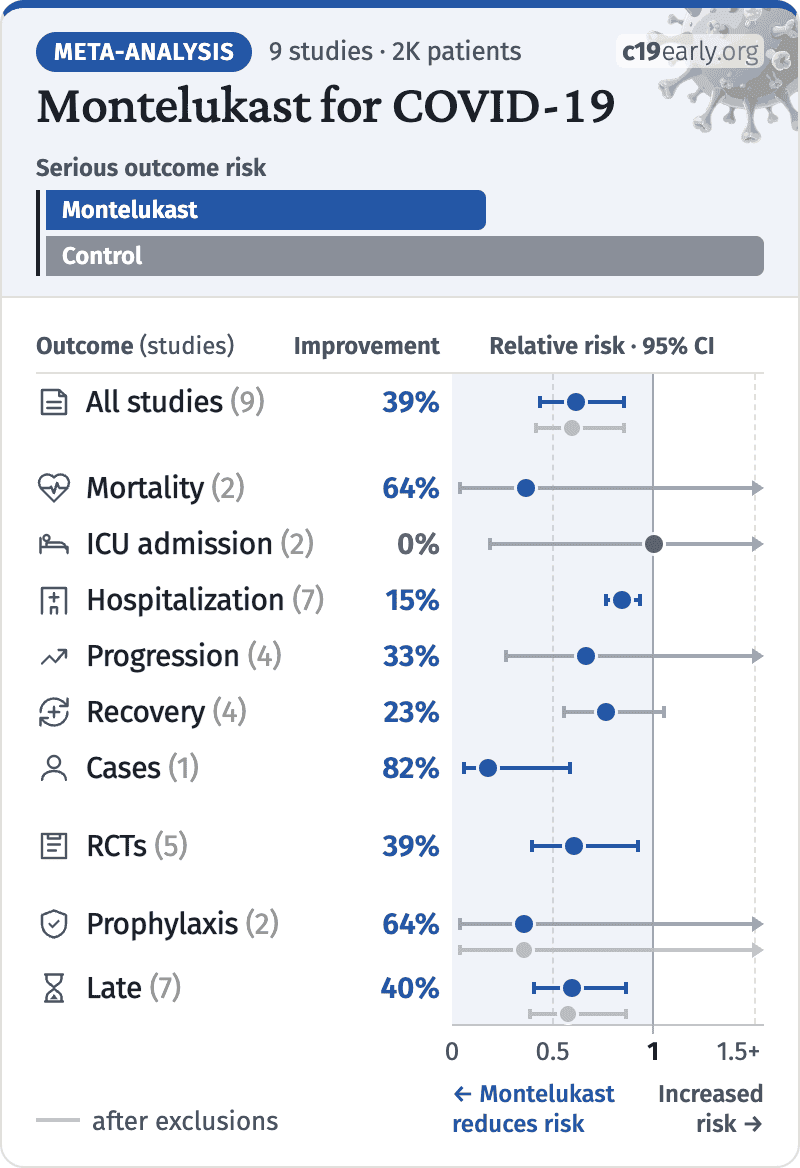
All studies (9)39%
Mortality (2)64%
ICU admission (2)0%
Hospitalization (7)15%
Progression (4)33%
Recovery (4)23%
Cases (1)82%
RCTs (5)39%
Prophylaxis (2)64%
Late (7)40%
Abstract
Significantly lower risk is seen for hospitalization and cases. 4 studies from 4 independent teams in 4 countries show significant
benefit.
Meta-analysis using the most serious outcome reported shows
39% [14‑56%] lower risk. Results are similar for Randomized Controlled Trials and higher quality studies.
Montelukast for COVID-19
Serious outcome risk
Outcome (studies)
Improvement
Relative risk · 95% CI
All studies (9)39%
Mortality (2)64%
ICU admission (2)0%
Hospitalization (7)15%
Progression (4)33%
Recovery (4)23%
Cases (1)82%
RCTs (5)39%
Prophylaxis (2)64%
Late (7)40%
Currently there is limited data, with only 37 control events for the most serious outcome in trials to date.
Montelukast has a boxed warning for neuropsychiatric side effects3.
No treatment is 100%
effective. Protocols combine safe and effective options with individual
risk/benefit analysis and monitoring.
Other treatments are more effective.
Montelukast currently has no early treatment studies.
All data and sources to reproduce this analysis are in the appendix.
Montelukast for COVID-19
Highlights- Montelukast reduces risk with very high confidence for hospitalization and in pooled analysis, and low confidence for recovery and cases.
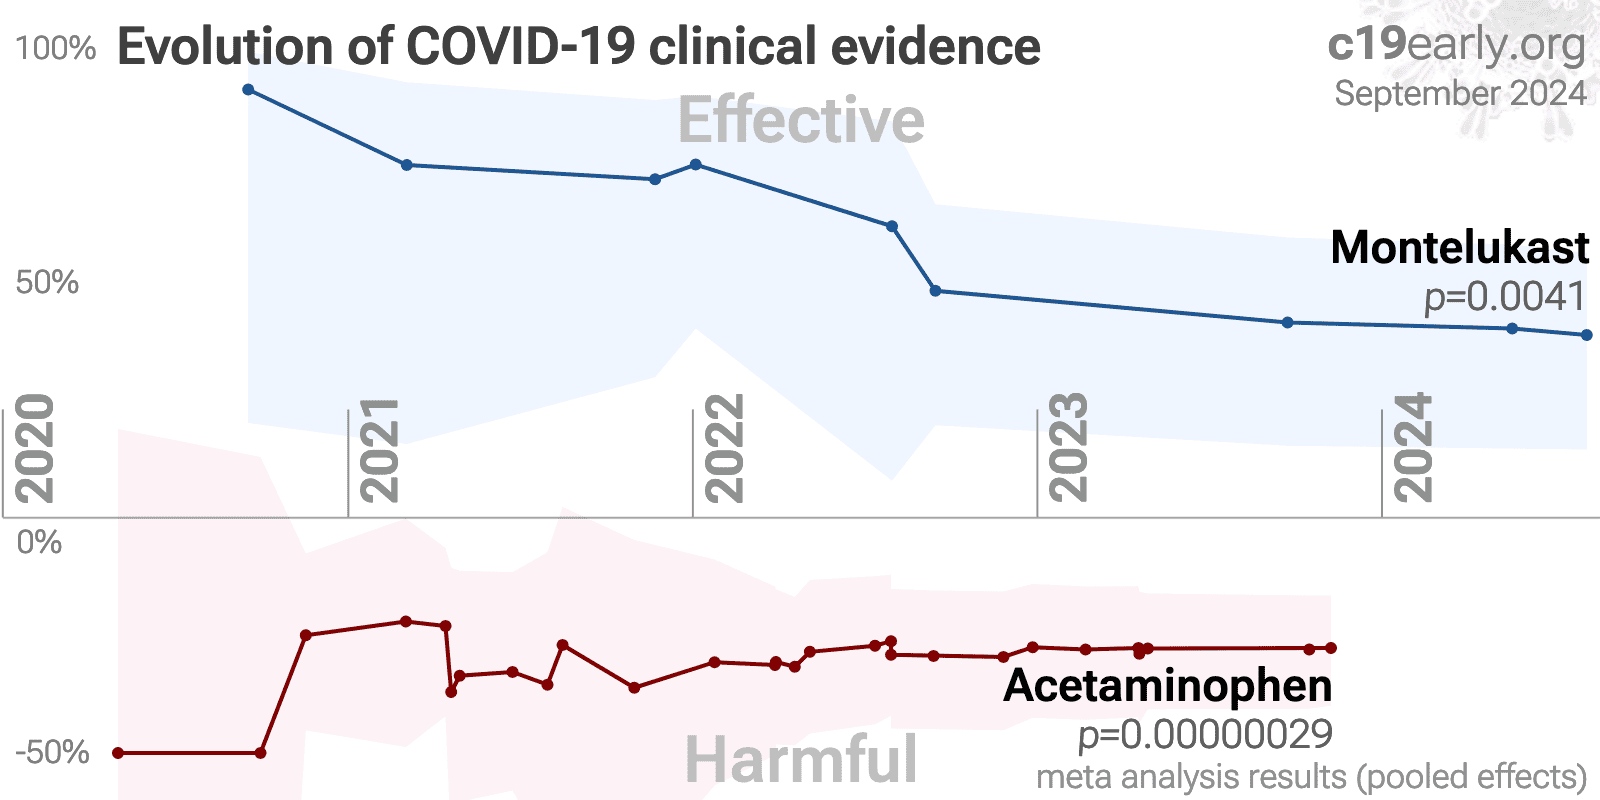
- 32nd treatment shown effective in November 2021, now with p = 0.0041 from 9 studies.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
A
Montelukast COVID-19 studies
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
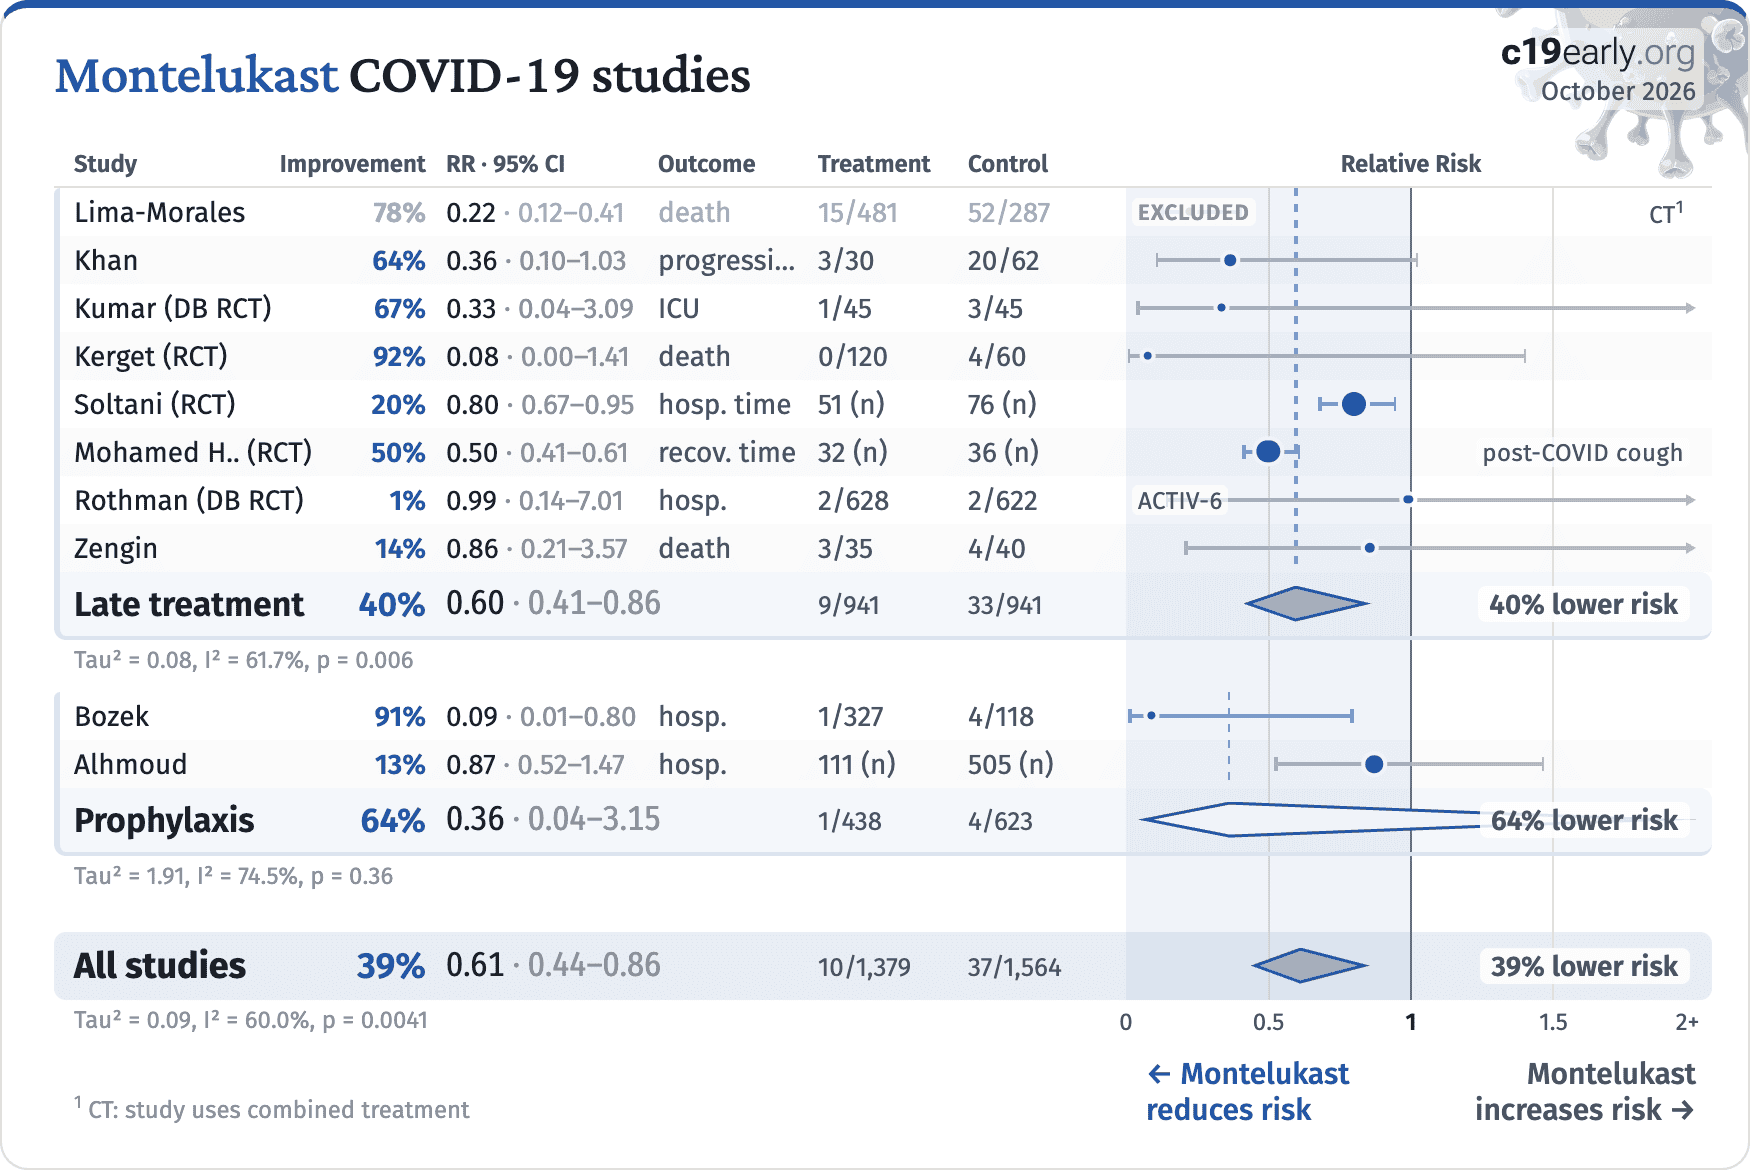
Lima-Morales78%0.22 · 0.12–0.41death15/48152/287EXCLUDEDCT1
Khan64%0.36 · 0.10–1.03progression3/3020/62
Kumar (DB RCT)67%0.33 · 0.04–3.09ICU1/453/45
Kerget (RCT)92%0.08 · 0.00–1.41death0/1204/60
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Mohamed H.. (RCT)50%0.50 · 0.41–0.61recov. time32 (n)36 (n)post-COVID cough
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Zengin14%0.86 · 0.21–3.57death3/354/40
Late treatment40%0.60 · 0.41–0.869/94133/94140% lower risk
Tau² = 0.08, I² = 61.7%, p = 0.006
Prophylaxis64%0.36 · 0.04–3.151/4384/62364% lower risk
Tau² = 1.91, I² = 74.5%, p = 0.36
All studies39%0.61 · 0.44–0.8610/1,37937/1,56439% lower risk
Tau² = 0.09, I² = 60.0%, p = 0.004100.511.52+
B
Loading..
Fig. 1. A. Random-effects meta-analysis. This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
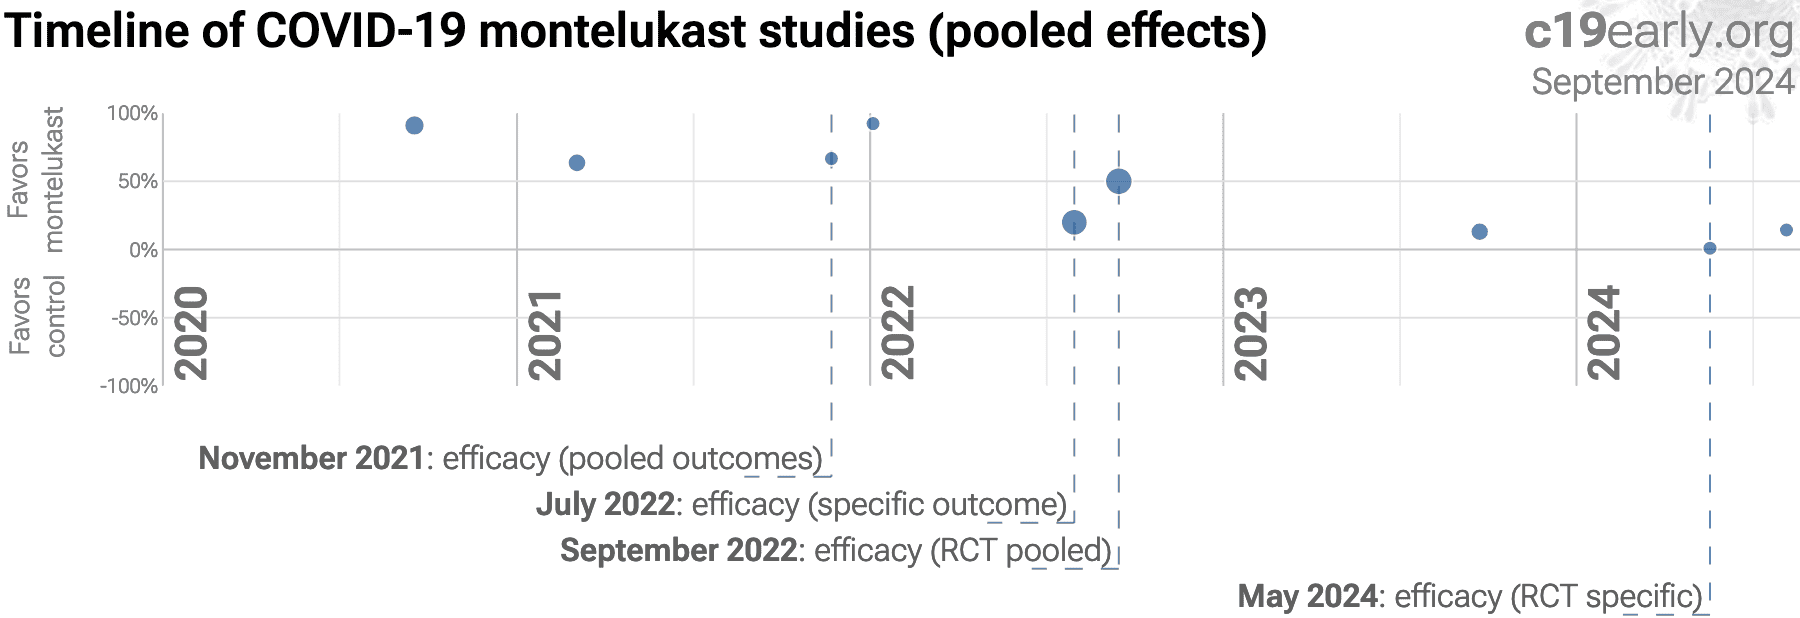
B. Timeline of results in montelukast studies. The marked dates indicate the time when efficacy was known with a statistically significant improvement of ≥10% from ≥3 studies for pooled outcomes, one or more specific outcome, pooled outcomes in RCTs, and one or more specific outcome in RCTs. Efficacy based on RCTs only was delayed by 9.8 months, compared to using all studies. Efficacy based on specific outcomes was delayed by 8.2 months, compared to using pooled outcomes. Efficacy based on specific outcomes in RCTs was delayed by 20.1 months, compared to using pooled outcomes in RCTs.
SARS-CoV-2 infection primarily begins in the upper respiratory
tract and may progress to the lower respiratory tract, other tissues, and the
nervous and cardiovascular systems, which may lead to cytokine storm,
pneumonia, ARDS, neurological injury5-21 and
cognitive deficits8,13, cardiovascular
complications22-28, DNA
damage29-32, organ failure, and death.
Even mild untreated infections may result in persistent cognitive
deficits33—the spike protein binds to fibrin leading to
fibrinolysis-resistant blood clots, thromboinflammation, and
neuropathology.
Minimizing replication as early as possible is recommended.
SARS-CoV-2 infection and replication involves the complex interplay of 500+
host and viral proteins and other factorsA,34-41 , providing many
therapeutic targets for which many existing compounds have known activity.
Scientists have predicted that over 12,000 compounds may
reduce COVID-19 risk42, either by
directly minimizing infection or replication, by supporting immune system
function, or by minimizing secondary complications.
In silico studies predict inhibition of SARS-CoV-2 with montelukast or metabolites via binding to the spikeB,43 (and specifically the receptor binding domainC,44), MproD,43, RNA-dependent RNA polymeraseE,43,45 , PLproF,43, nucleocapsidG,43, and helicaseH,43 proteins.
Montelukast inhibits SARS-CoV-2 omicron infection in Vero cells
at 1μM44 and inhibits platelet activation induced by plasma from
COVID-19 patients46.
We analyze all significant
controlled studies of
montelukast
for COVID-19.
Search methods, inclusion criteria, effect extraction criteria (more serious
outcomes have priority), all individual study data, PRISMA answers, and
statistical methods are detailed in Appendix 1. We present random-effects
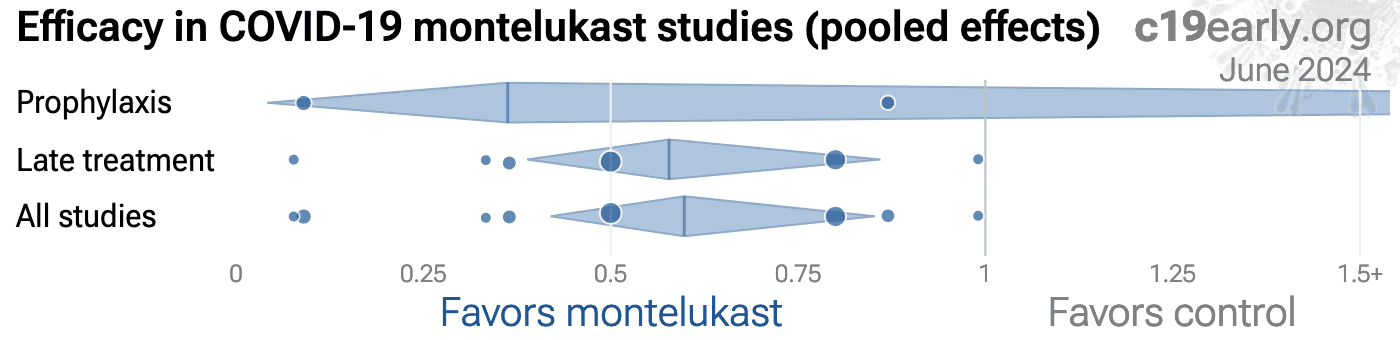
meta-analysis results for all studies, studies within each treatment stage, individual outcomes, Randomized Controlled Trials (RCTs), and higher quality studies.
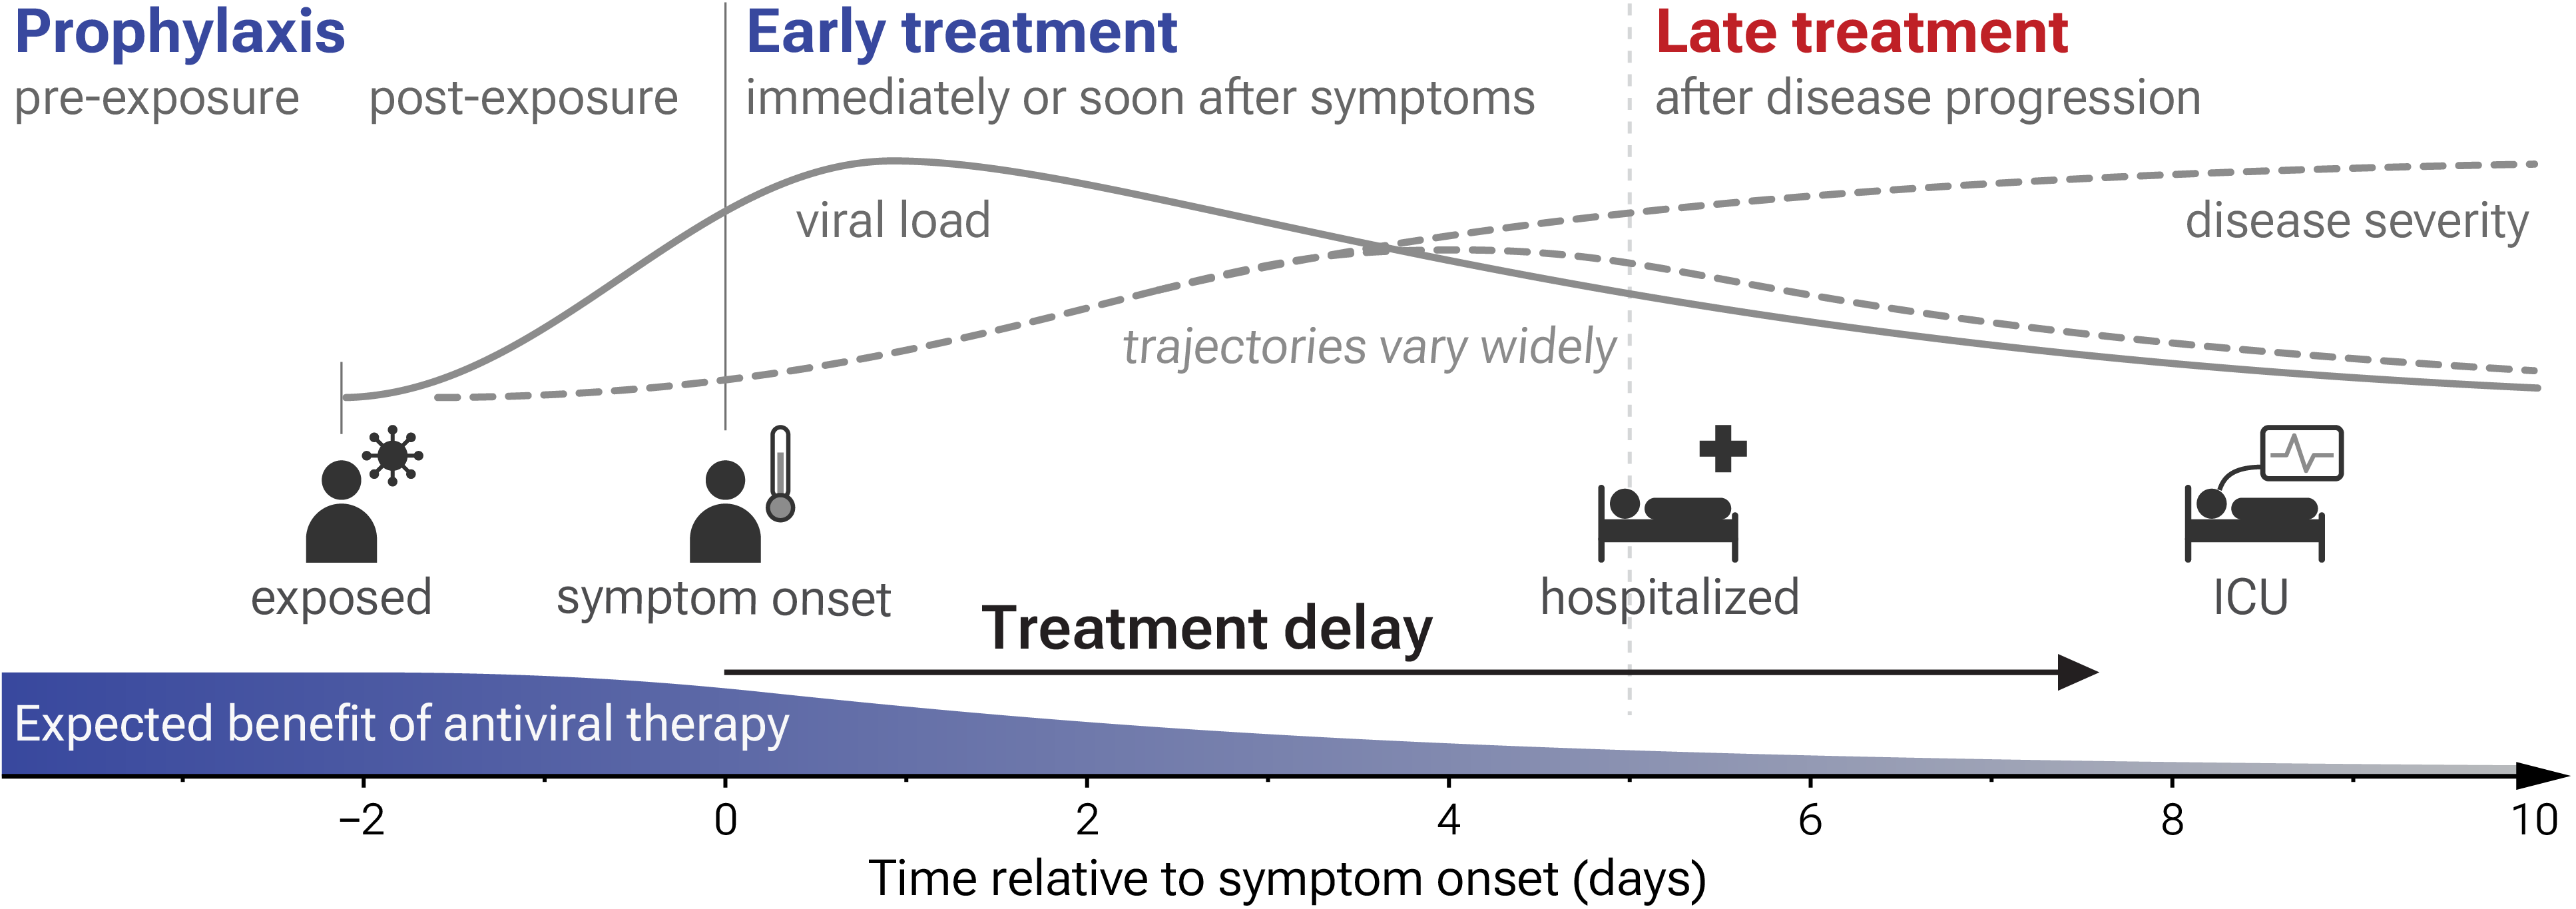
Fig. 3 shows stages of possible treatment for
COVID-19. Prophylaxis refers to regularly taking medication before
becoming sick, in order to prevent or minimize infection. Early
treatment refers to treatment immediately or soon after symptoms appear,
while late treatment refers to more delayed treatment.
Fig. 3. Treatment stages.
In silico studies predict inhibition of SARS-CoV-2 with montelukast or metabolites via binding to the spikeB,43 (and specifically the receptor binding domainC,44), MproD,43, RNA-dependent RNA polymeraseE,43,45 , PLproF,43, nucleocapsidG,43, and helicaseH,43 proteins.
Montelukast inhibits SARS-CoV-2 omicron infection in Vero cells
at 1μM44 and inhibits platelet activation induced by plasma from
COVID-19 patients46.
Preclinical research is an important part of the development of
treatments, however results may be very different in clinical trials.
Preclinical results are not used in this paper.
Table 1 summarizes the results for all studies, for Randomized Controlled Trials, after exclusions, for specific outcomes, and by treatment stage.
Fig. 4 plots individual results by treatment stage.
Fig. 5, 6, 7, 8, 9, 10, and 11
show forest plots for random-effects meta-analysis of
all studies with pooled effects, mortality results, ICU admission, hospitalization, progression, recovery, and cases.
Montelukast for COVID-19: meta-analysis results
November 2026
All stages
Prophylaxis
Late treatment
All studies9 studies · 2,943 patients
All stages0.61** 0.44–0.8639% lower risk
Prophylaxis0.36 0.04–3.1564% lower risk
Late treatment0.60** 0.41–0.8640% lower risk
After exclusions8 studies · 2,868 patients
All stages0.60** 0.42–0.8540% lower risk
Prophylaxis0.36 0.04–3.1564% lower risk
Late treatment0.58** 0.39–0.8642% lower risk
RCTs5 studies · 1,715 patients
All stages0.61* 0.40–0.9339% lower risk
Prophylaxis—
Late treatment0.61* 0.40–0.9339% lower risk
Mortality2 studies · 255 patients
All stages0.36 0.04–3.4964% lower risk
Prophylaxis—
Late treatment0.36 0.04–3.4964% lower risk
ICU admission2 studies · 165 patients
All stages1.00 0.19–5.210% lower risk
Prophylaxis—
Late treatment1.00 0.19–5.210% lower risk
Hospitalization7 studies · 2,725 patients
All stages0.85*** 0.77–0.9315% lower risk
Prophylaxis0.36 0.04–3.1564% lower risk
Late treatment0.85** 0.77–0.9415% lower risk
Recovery4 studies · 1,535 patients
All stages0.77 0.56–1.0623% lower risk
Prophylaxis—
Late treatment0.77 0.56–1.0623% lower risk
RCT hospitalization3 studies · 1,497 patients
All stages0.82** 0.73–0.9318% lower risk
Prophylaxis—
Late treatment0.82** 0.73–0.9318% lower risk
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Table 1. Random-effects meta-analysis results for montelukast. Results show the relative risk and 95% confidence interval.
Fig. 4. Scatter plot showing the most serious outcome in all studies, and for studies within each stage. Diamonds shows the results of random-effects meta-analysis.
Montelukast COVID-19 studies
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Lima-Morales78%0.22 · 0.12–0.41death15/48152/287EXCLUDEDCT1
Khan64%0.36 · 0.10–1.03progression3/3020/62
Kumar (DB RCT)67%0.33 · 0.04–3.09ICU1/453/45
Kerget (RCT)92%0.08 · 0.00–1.41death0/1204/60
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Mohamed H.. (RCT)50%0.50 · 0.41–0.61recov. time32 (n)36 (n)post-COVID cough
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Zengin14%0.86 · 0.21–3.57death3/354/40
Late treatment40%0.60 · 0.41–0.869/94133/94140% lower risk
Tau² = 0.08, I² = 61.7%, p = 0.006
Prophylaxis64%0.36 · 0.04–3.151/4384/62364% lower risk
Tau² = 1.91, I² = 74.5%, p = 0.36
All studies39%0.61 · 0.44–0.8610/1,37937/1,56439% lower risk
Tau² = 0.09, I² = 60.0%, p = 0.004100.511.52+
Fig. 5. Random-effects meta-analysis for all studies.
This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
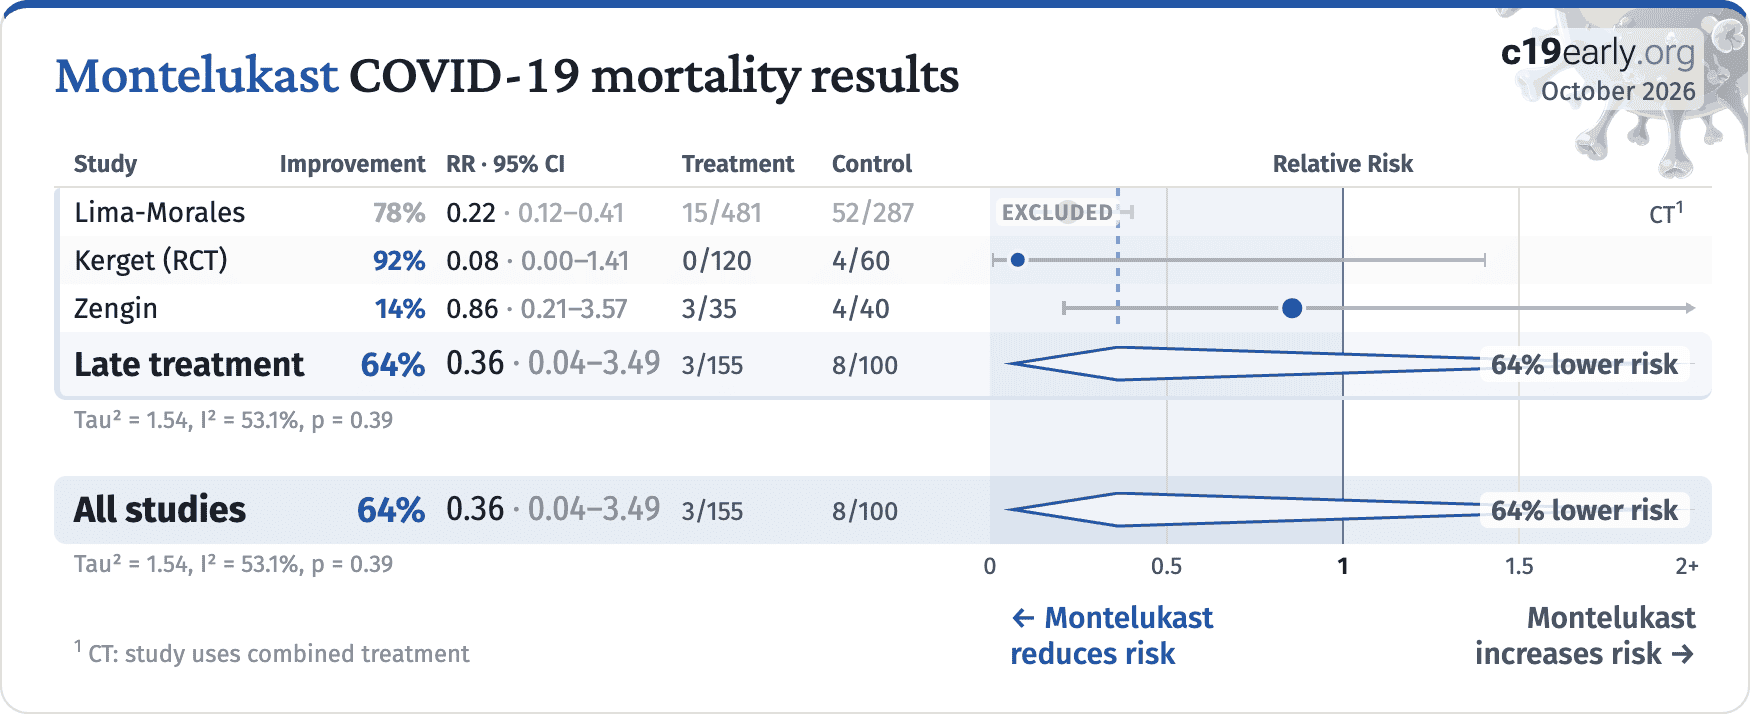
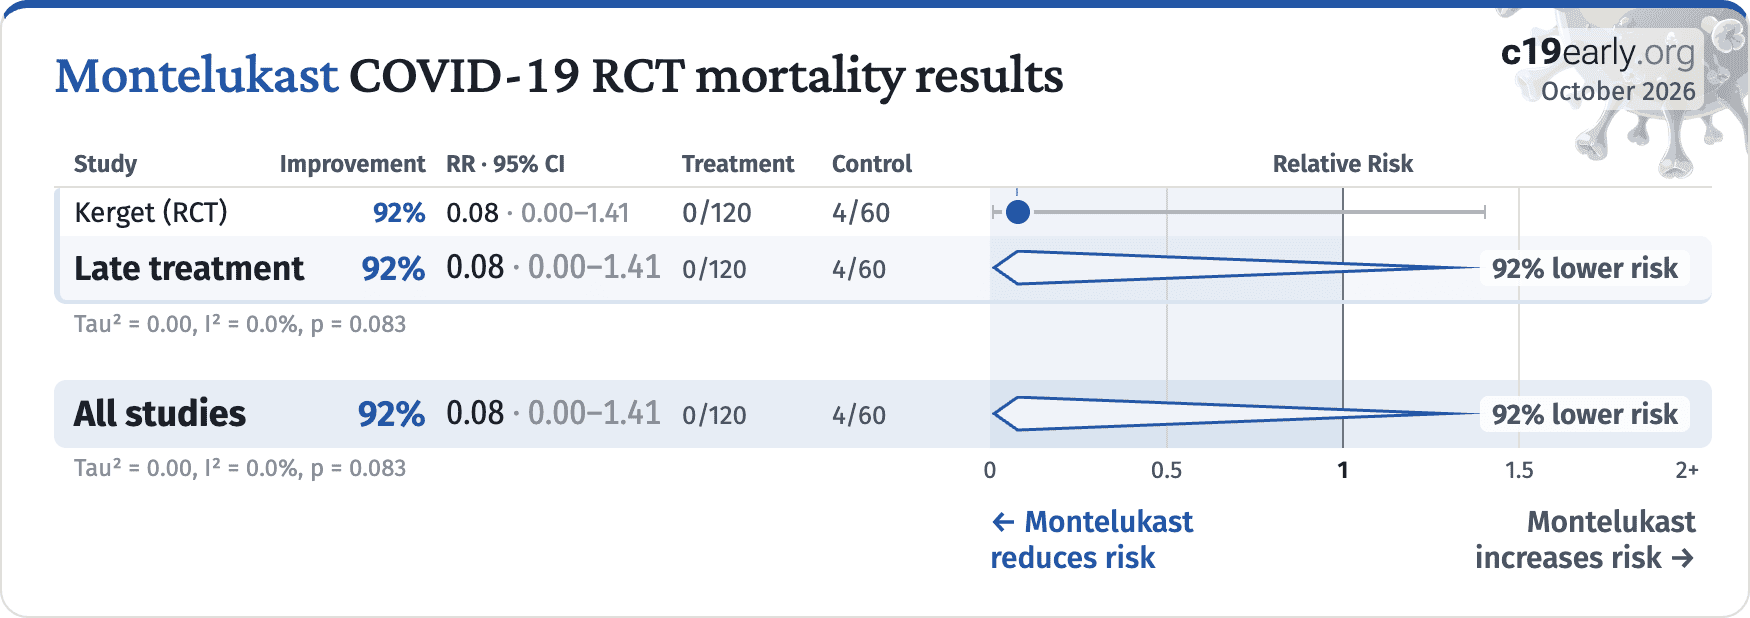
Montelukast COVID-19 mortality results
November 2026
StudyImprovementRR · 95% CITreatmentControlRelative Risk
Lima-Morales78%0.22 · 0.12–0.4115/48152/287EXCLUDEDCT1
Kerget (RCT)92%0.08 · 0.00–1.410/1204/60
Zengin14%0.86 · 0.21–3.573/354/40
Late treatment64%0.36 · 0.04–3.493/1558/10064% lower risk
Tau² = 1.54, I² = 53.1%, p = 0.39
All studies64%0.36 · 0.04–3.493/1558/10064% lower risk
Tau² = 1.54, I² = 53.1%, p = 0.3900.511.52+
Fig. 6. Random-effects meta-analysis for mortality results.
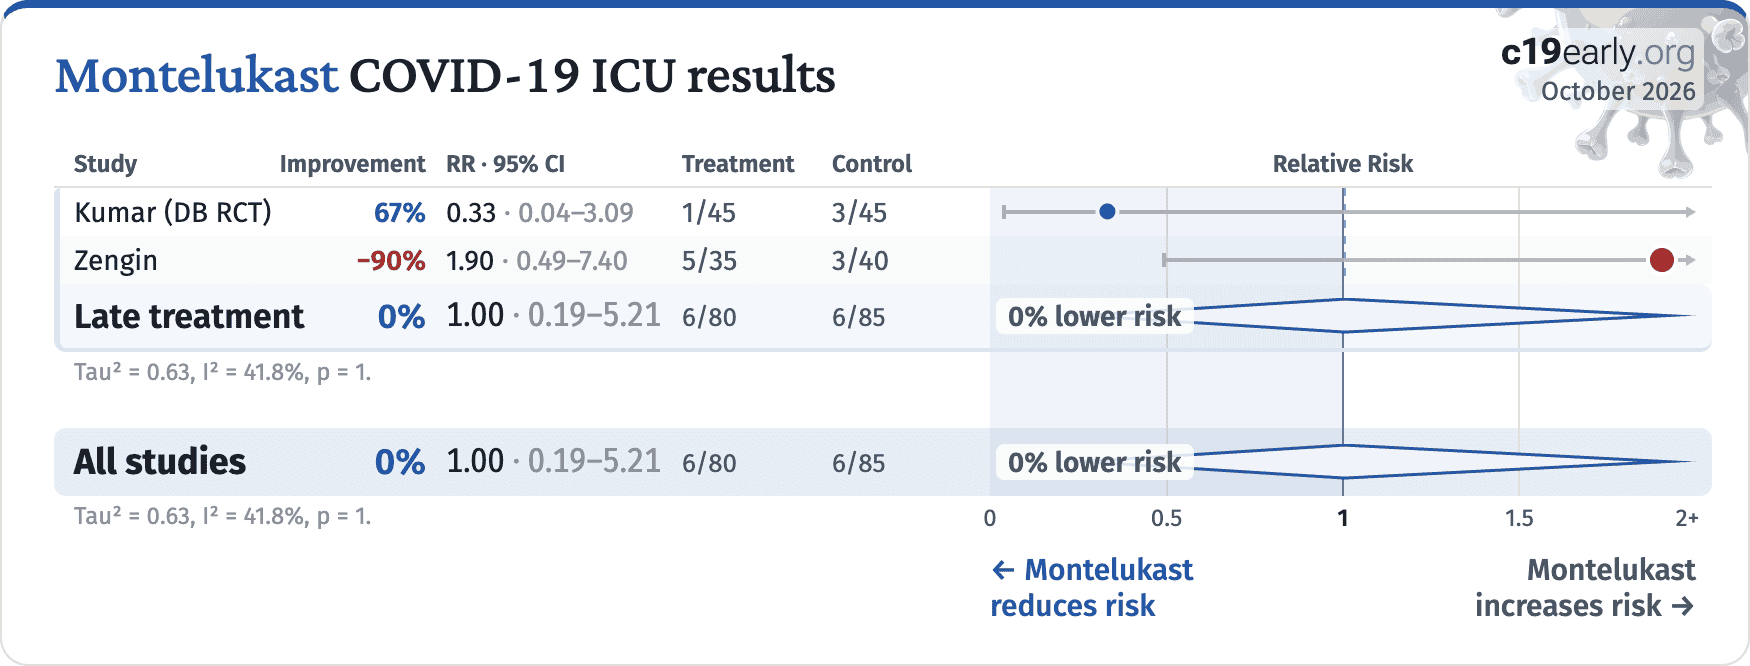
Montelukast COVID-19 ICU results
November 2026
StudyImprovementRR · 95% CITreatmentControlRelative Risk
Late treatment0%1.00 · 0.19–5.216/806/850% lower risk
Tau² = 0.63, I² = 41.8%, p = 1.
All studies0%1.00 · 0.19–5.216/806/850% lower risk
Tau² = 0.63, I² = 41.8%, p = 1.00.511.52+
Fig. 7. Random-effects meta-analysis for ICU admission.
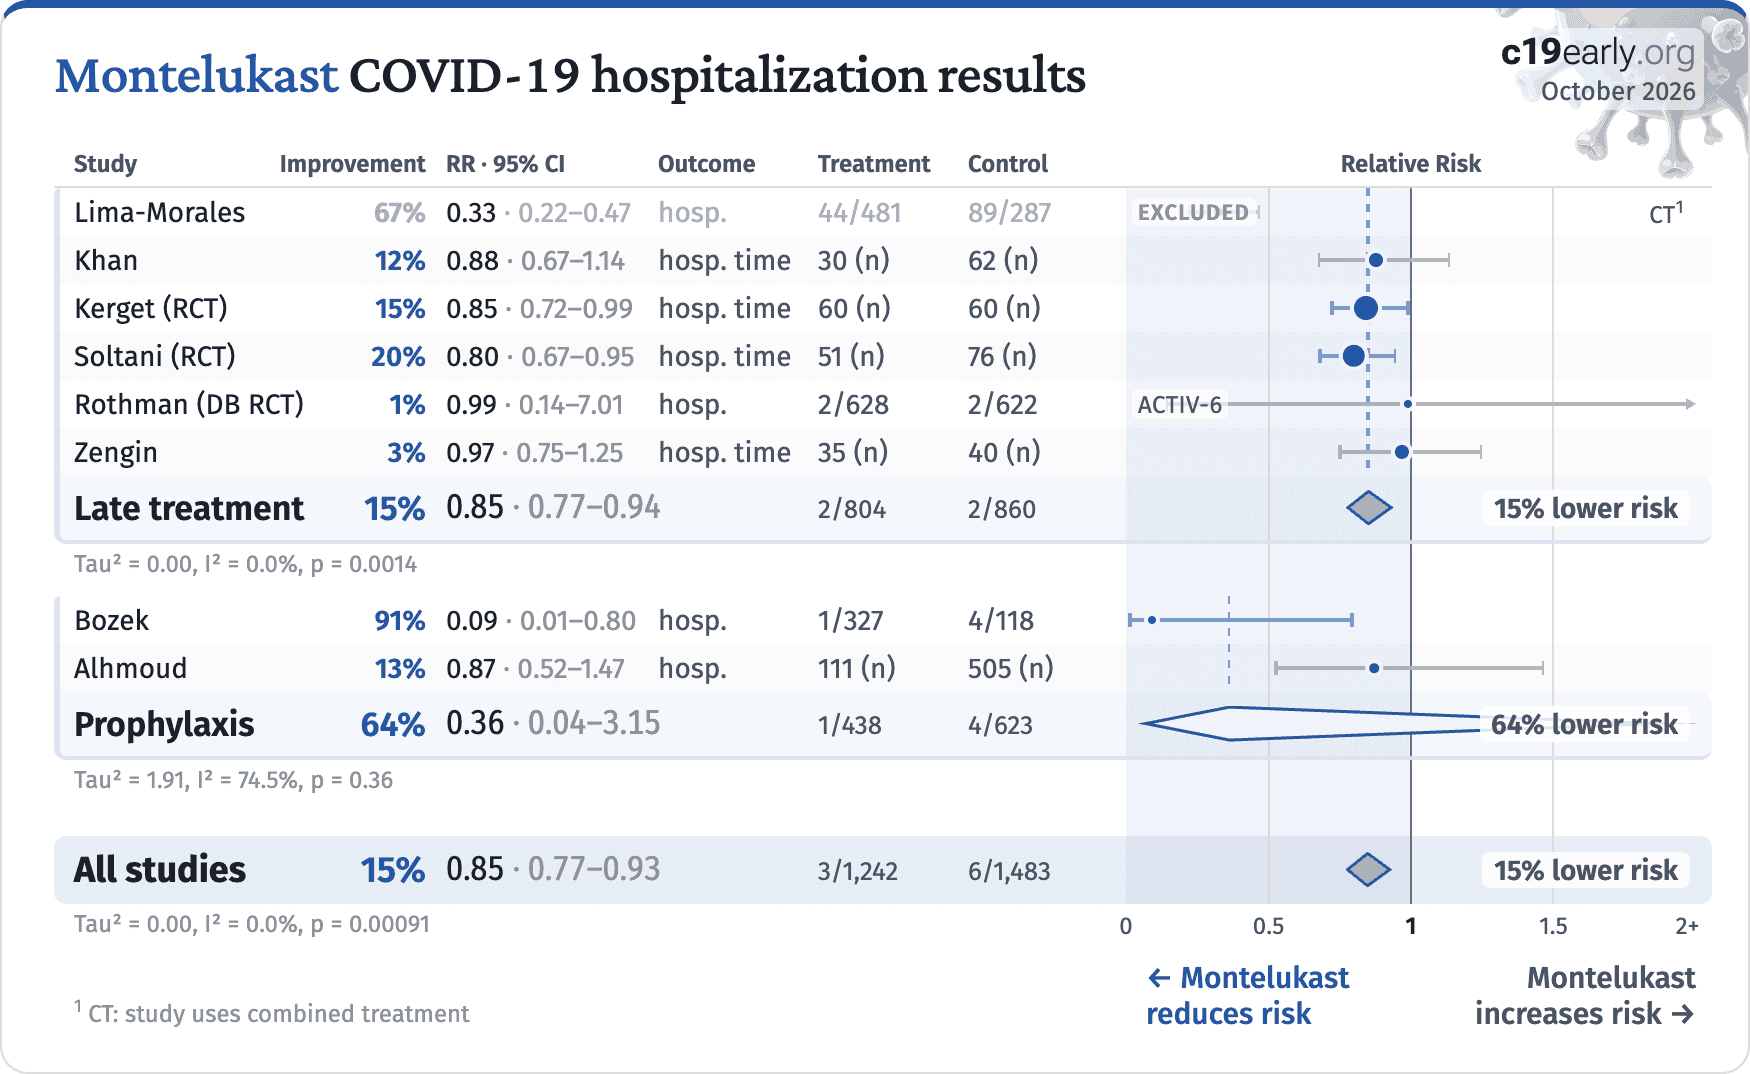
Montelukast COVID-19 hospitalization results
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Lima-Morales67%0.33 · 0.22–0.47hosp.44/48189/287EXCLUDEDCT1
Khan12%0.88 · 0.67–1.14hosp. time30 (n)62 (n)
Kerget (RCT)15%0.85 · 0.72–0.99hosp. time60 (n)60 (n)
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Zengin3%0.97 · 0.75–1.25hosp. time35 (n)40 (n)
Late treatment15%0.85 · 0.77–0.942/8042/86015% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0014
Prophylaxis64%0.36 · 0.04–3.151/4384/62364% lower risk
Tau² = 1.91, I² = 74.5%, p = 0.36
All studies15%0.85 · 0.77–0.933/1,2426/1,48315% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0009100.511.52+
Fig. 8. Random-effects meta-analysis for hospitalization.
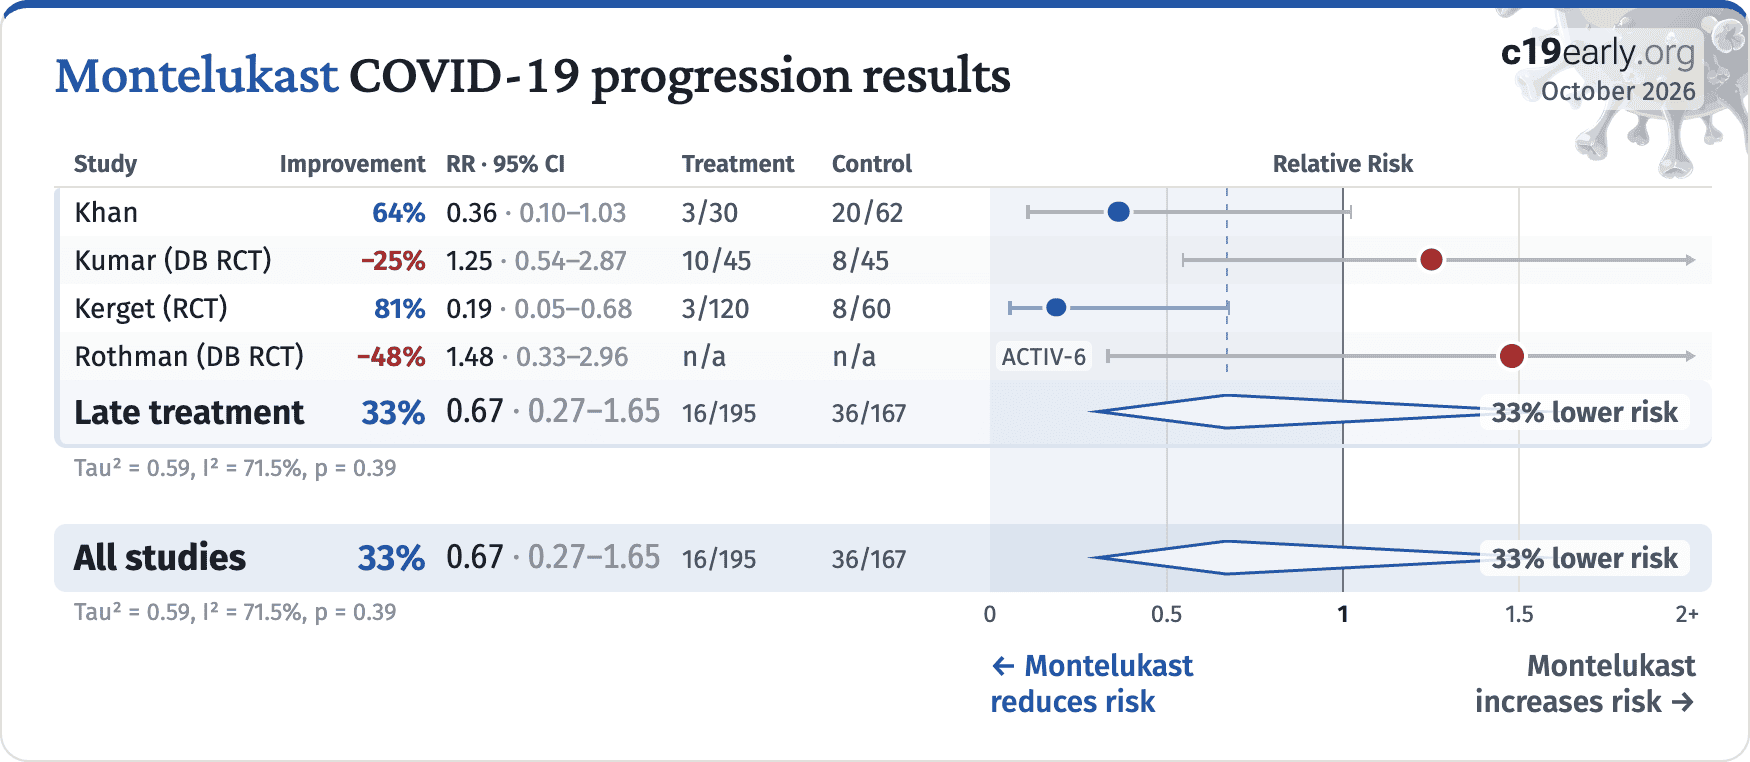
Montelukast COVID-19 progression results
November 2026
StudyImprovementRR · 95% CITreatmentControlRelative Risk
Khan64%0.36 · 0.10–1.033/3020/62
Kumar (DB RCT)−25%1.25 · 0.54–2.8710/458/45
Kerget (RCT)81%0.19 · 0.05–0.683/1208/60
Rothman (DB RCT)−48%1.48 · 0.33–2.96n/an/aACTIV-6
Late treatment33%0.67 · 0.27–1.6516/19536/16733% lower risk
Tau² = 0.59, I² = 71.5%, p = 0.39
All studies33%0.67 · 0.27–1.6516/19536/16733% lower risk
Tau² = 0.59, I² = 71.5%, p = 0.3900.511.52+
Fig. 9. Random-effects meta-analysis for progression.
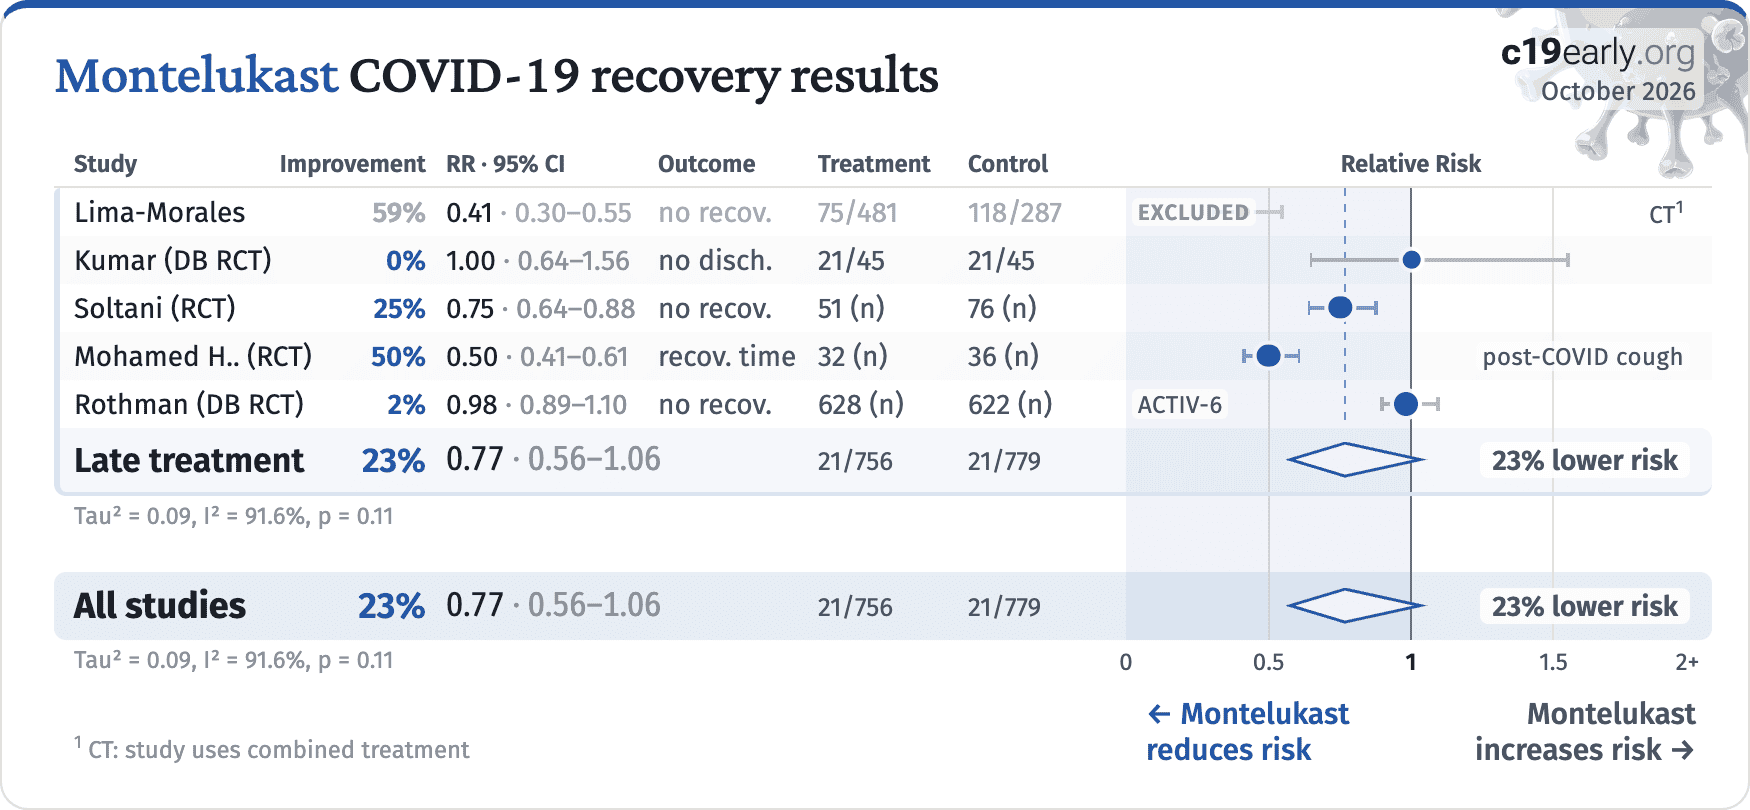
Montelukast COVID-19 recovery results
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Lima-Morales59%0.41 · 0.30–0.55no recov.75/481118/287EXCLUDEDCT1
Kumar (DB RCT)0%1.00 · 0.64–1.56no disch.21/4521/45
Soltani (RCT)25%0.75 · 0.64–0.88no recov.51 (n)76 (n)
Mohamed H.. (RCT)50%0.50 · 0.41–0.61recov. time32 (n)36 (n)post-COVID cough
Rothman (DB RCT)2%0.98 · 0.89–1.10no recov.628 (n)622 (n)ACTIV-6
Late treatment23%0.77 · 0.56–1.0621/75621/77923% lower risk
Tau² = 0.09, I² = 91.6%, p = 0.11
All studies23%0.77 · 0.56–1.0621/75621/77923% lower risk
Tau² = 0.09, I² = 91.6%, p = 0.1100.511.52+
Fig. 10. Random-effects meta-analysis for recovery.
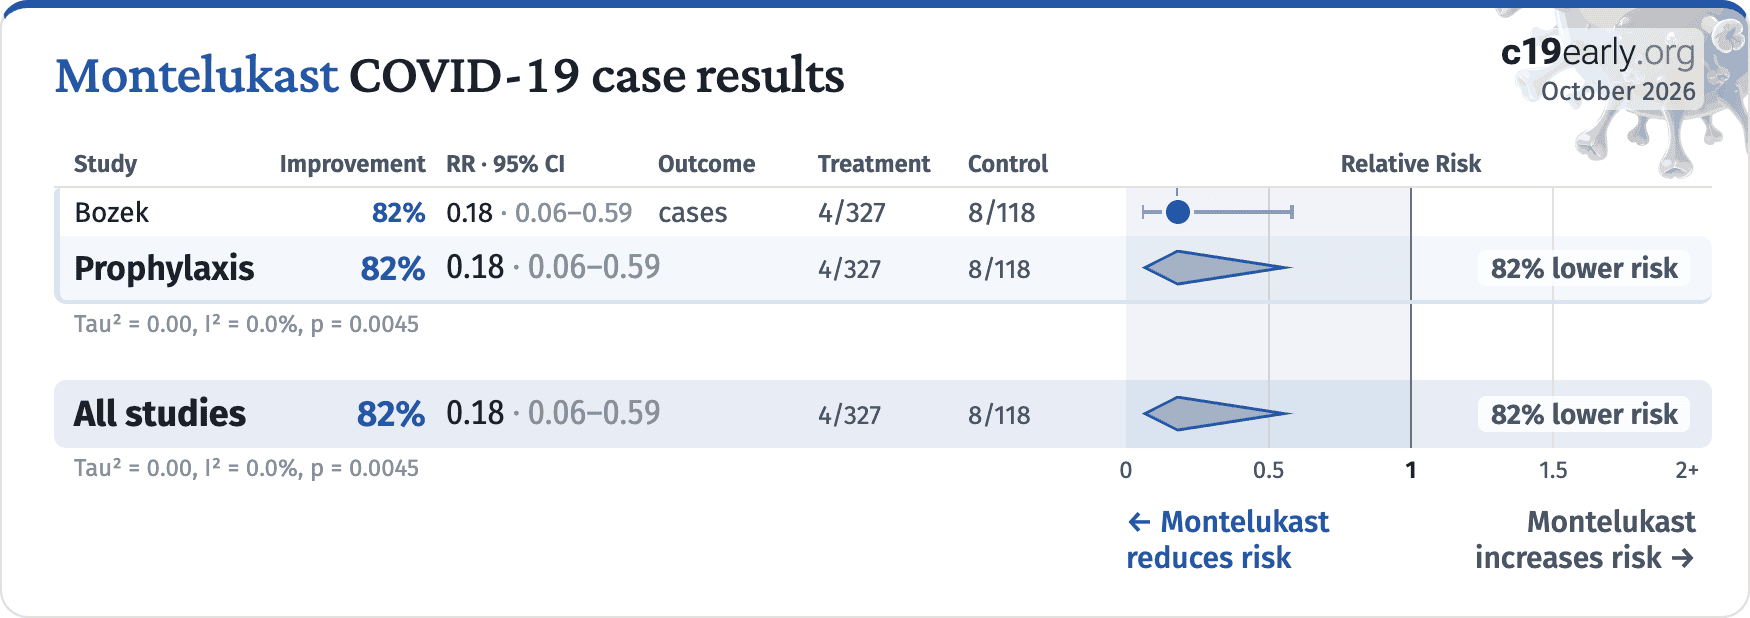
Montelukast COVID-19 case results
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Prophylaxis82%0.18 · 0.06–0.594/3278/11882% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0045
All studies82%0.18 · 0.06–0.594/3278/11882% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.004500.511.52+
Fig. 11. Random-effects meta-analysis for cases.
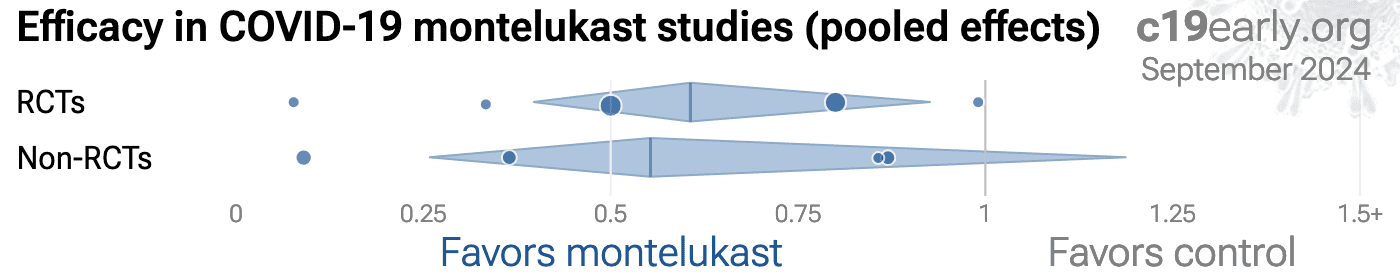
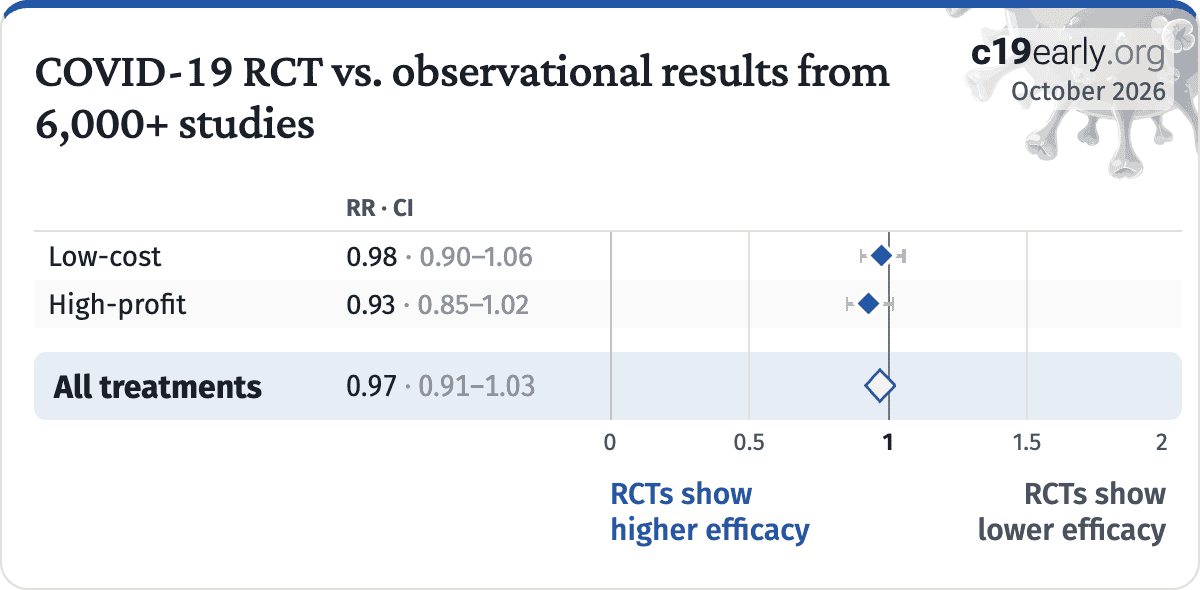
Fig. 12 shows a comparison of results for RCTs and observational studies.
Fig. 13, 14, and 15
show forest plots for random-effects meta-analysis of
all Randomized Controlled Trials, RCT mortality results, and RCT hospitalization results.
RCT results are included in Table 1.
Fig. 12. Results for RCTs and observational studies.
RCTs help to make study groups more similar and can provide a higher level of
evidence, however they are subject to many biases54, and
analysis of double-blind RCTs has identified extreme levels of bias55.
For COVID-19, the overhead may delay treatment, dramatically compromising
efficacy; they may encourage monotherapy for simplicity at the cost of
efficacy which may rely on combined or synergistic effects; the participants
that sign up may not reflect real world usage or the population that benefits
most in terms of age, comorbidities, severity of illness, or other factors;
standard of care may be compromised and unable to evolve quickly based on
emerging research for new diseases; errors may be made in randomization and
medication delivery; and investigators may have hidden agendas or vested
interests influencing design, operation, analysis, reporting, and the
potential for fraud. All of these biases have been observed with COVID-19
RCTs. There is no guarantee that a specific RCT provides a higher level of
evidence.
RCTs are expensive and many RCTs are funded
by pharmaceutical companies or other organizations with conflicts of interest, for example
governments that previously denied treatment with the study drug.
For COVID-19, this creates an incentive to show efficacy for
patented commercial products, and an incentive to show a lack of efficacy for
inexpensive treatments. The bias is expected to be significant, for example
Als-Nielsen et al. analyzed 370 RCTs from Cochrane reviews, showing that
trials funded by for-profit organizations were 5 times more likely to
recommend the experimental drug compared with those funded by nonprofit
organizations. Bekelman et al. and Lundh et al. show that
industry-sponsored studies are more likely to be favorable.
For COVID-19, some major philanthropic organizations are
largely funded by investments with extreme conflicts of interest for and
against specific COVID-19 interventions.
High quality RCTs for novel acute diseases are more challenging, with
increased ethical issues due to the urgency of treatment, increased risk due
to enrollment delays, and more difficult design with a rapidly evolving
evidence base. For COVID-19, the most common site of initial infection is the
upper respiratory tract. Immediate treatment is likely to be most successful
and may prevent or slow progression to other parts of the body. For a
non-prophylaxis RCT, it makes sense to provide treatment in advance and
instruct patients to use it immediately on symptoms, just as some governments
have done by providing medication kits in advance. Unfortunately, no RCTs have
been done in this way. Every treatment RCT to date involves delayed treatment.
Among the 227 treatments we have analyzed,
67% of RCTs involve very late treatment 5+ days after
onset. No non-prophylaxis COVID-19 RCTs match the potential real-world use of
early treatments. They may more accurately represent results for treatments
that require visiting a medical facility, e.g., those requiring intravenous
administration.
RCTs have a bias against finding an effect for interventions
that are widely available—patients that believe they need the
intervention are more likely to decline participation and take the
intervention. RCTs for montelukast are more likely to enroll low-risk
participants that do not need treatment to recover, making the results less
applicable to clinical practice. This bias is likely to be greater for widely
known treatments, and may be greater when the risk of a serious outcome is
overstated. This bias does not apply to the typical pharmaceutical trial of a
new drug that is otherwise unavailable.
COVID-19 RCT vs. observational results from 6,000+ studies
November 2026
RR · CI
All treatments0.97 · 0.91–1.03
00.511.52
Evidence shows that observational studies
can also provide reliable results. Concato et al. found that well-designed
observational studies do not systematically overestimate the magnitude of the
effects of treatment compared to RCTs. Anglemyer et al. analyzed reviews
comparing RCTs to observational studies and found little evidence for
significant differences in effect estimates.
We performed a similar analysis across the 227 treatments
we cover, showing no significant difference in the results of RCTs compared to
observational studies, RR 0.97 [0.91‑1.03]51. Similar results are found for all low-cost treatments, RR
0.98 [0.90‑1.06]. High-cost treatments
show a non-significant trend towards RCTs showing greater efficacy,
RR 0.92 [0.84‑1.02].
Details can be found in the
supplementary data.
Lee et al. showed that only 14% of the guidelines of the Infectious
Diseases Society of America were based on RCTs. Evaluation of studies relies
on an understanding of the study and potential biases. Limitations in an RCT
can outweigh the benefits, for example excessive dosages, excessive treatment
delays, or remote survey bias may have a greater effect on results. Ethical
issues may also prevent running RCTs for known effective treatments. For more
on issues with RCTs see63,64.
Concato et al. report a paradoxical finding—RCT results had higher
variability, and only RCTs were found to sometimes report significant results the opposite
of the overall result. The same trend is seen for the most popular (most politicized)
COVID-19 treatments—considering all statistically significant results reported in
studies, RCTs are slightly more likely to report a result in the opposite direction. In
other words, for these COVID-19 treatments and for the topics covered by Concato et al., assuming causality from a single study is more likely to result in an incorrect conclusion for
RCTs.
Increased risk of inconsistent results for RCTs suggests higher prevalence of
bias, which may arise due to many issues including design bias, conflicts of interest,
treatment differences by physicians aware of allocation, attrition bias, ascertainment
bias, randomization failures, errors, or fraud.
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. Of these, 54% have been confirmed in RCTs, with a mean delay of 7.8 months (62% with 8.7 months delay for low-cost treatments). The remaining treatments either have no RCTs, or the point estimate is consistent.
Neither observational studies nor RCTs prove causation—any study can be
flawed or fraudulent. We need much more, for example a combination of results from many
independent teams, detailed understanding of each study, knowledge of conflicts/team
reliability, dose-response relationships, delay-response relationships, logical results across outcomes, or details consistent with preclinical expectations.
All studies must be evaluated individually. RCTs for a
given medication and disease may be more reliable, however they may also be
less reliable. For off-patent medications, very high conflict of interest
trials may be more likely to be RCTs, and more likely to be large trials that
dominate meta-analyses.
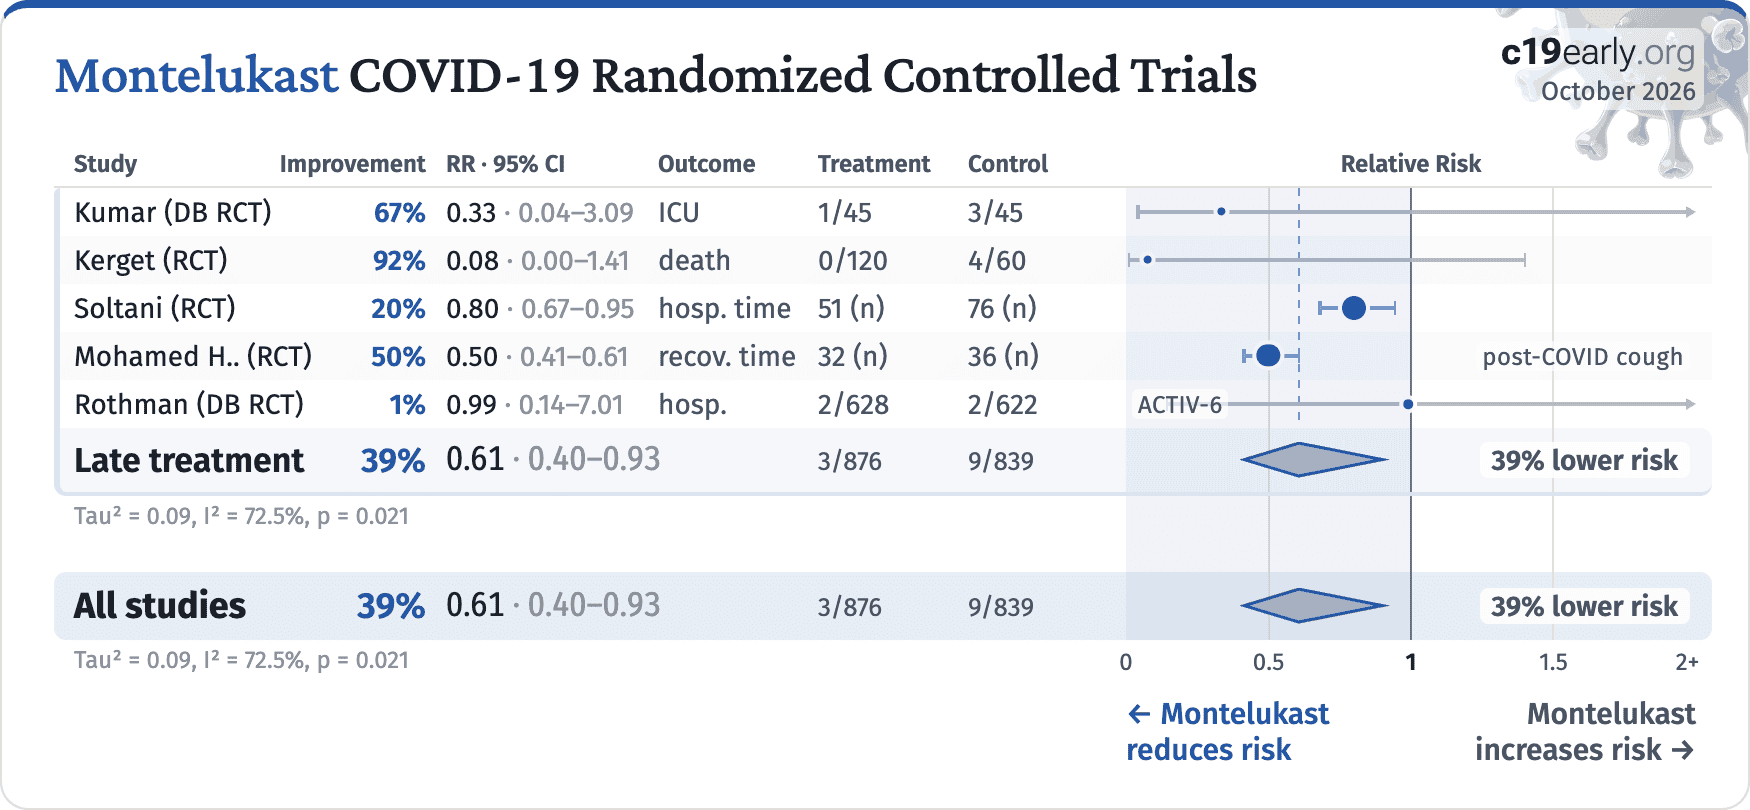
Montelukast COVID-19 Randomized Controlled Trials
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Kumar (DB RCT)67%0.33 · 0.04–3.09ICU1/453/45
Kerget (RCT)92%0.08 · 0.00–1.41death0/1204/60
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Mohamed H.. (RCT)50%0.50 · 0.41–0.61recov. time32 (n)36 (n)post-COVID cough
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Late treatment39%0.61 · 0.40–0.933/8769/83939% lower risk
Tau² = 0.09, I² = 72.5%, p = 0.021
All studies39%0.61 · 0.40–0.933/8769/83939% lower risk
Tau² = 0.09, I² = 72.5%, p = 0.02100.511.52+
Fig. 13. Random-effects meta-analysis for all Randomized Controlled Trials.
This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
Montelukast COVID-19 RCT mortality results
November 2026
StudyImprovementRR · 95% CITreatmentControlRelative Risk
Late treatment92%0.08 · 0.00–1.410/1204/6092% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.083
All studies92%0.08 · 0.00–1.410/1204/6092% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.08300.511.52+
Fig. 14. Random-effects meta-analysis for RCT mortality results.
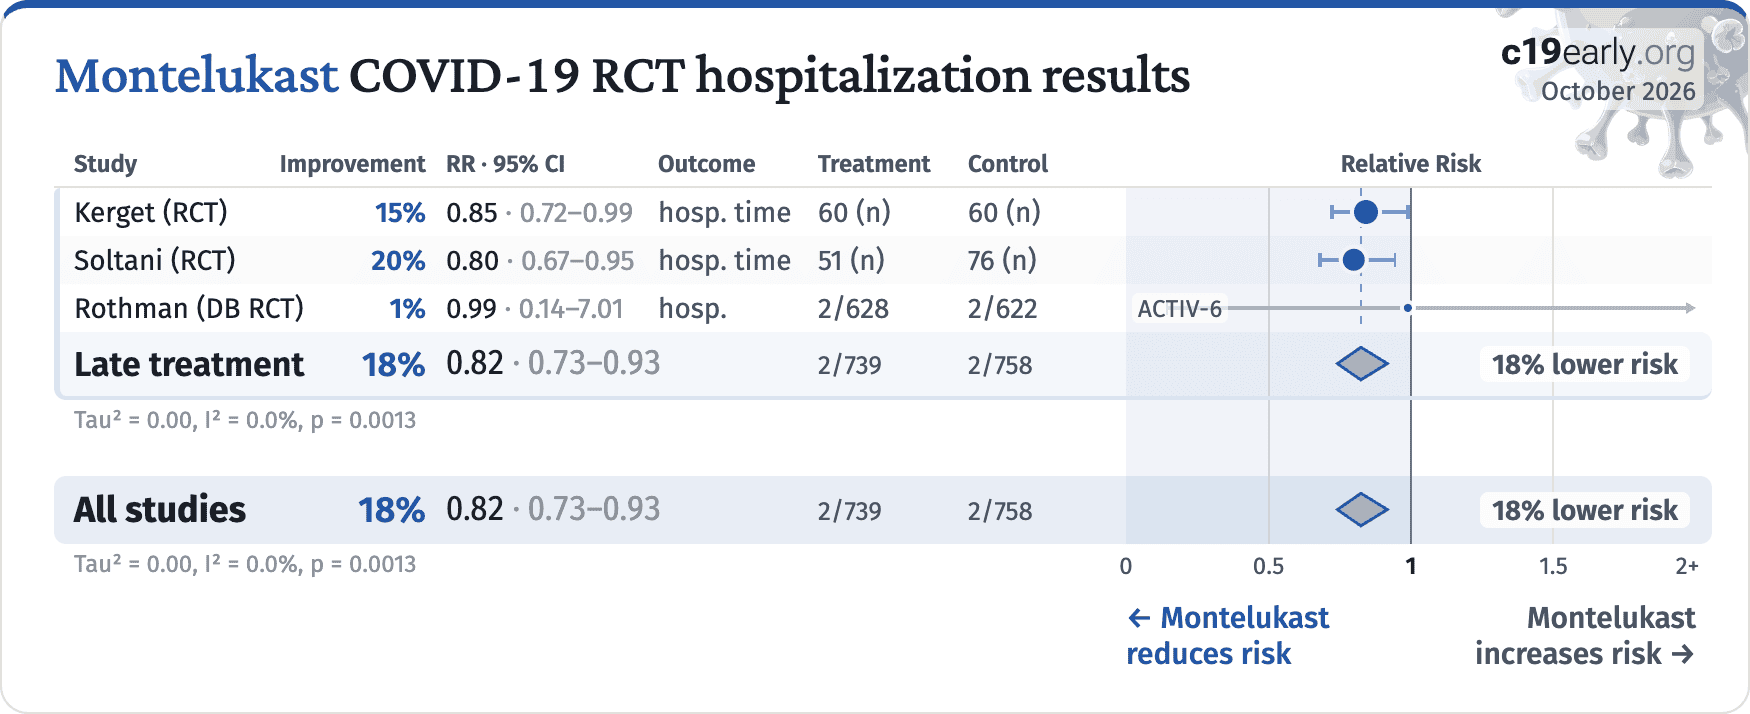
Montelukast COVID-19 RCT hospitalization results
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Kerget (RCT)15%0.85 · 0.72–0.99hosp. time60 (n)60 (n)
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Late treatment18%0.82 · 0.73–0.932/7392/75818% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0013
All studies18%0.82 · 0.73–0.932/7392/75818% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.001300.511.52+
Fig. 15. Random-effects meta-analysis for RCT hospitalization results.
To avoid bias in the selection of studies, we analyze all
non-retracted studies. Here we show the results after excluding
studies with major issues likely to alter results, non-standard studies, and
studies where very minimal detail is currently available. Our bias evaluation
is based on analysis of each study and identifying when there is a significant
chance that limitations will substantially change the outcome of the study. We
believe this can be more valuable than checklist-based approaches such as
Cochrane GRADE, which can be easily influenced by potential bias, may ignore
or underemphasize serious issues not captured in the checklists, and may
overemphasize issues unlikely to alter outcomes in specific cases (for example
certain specifics of randomization with a very large effect size and
well-matched baseline characteristics).
The studies excluded are as below.
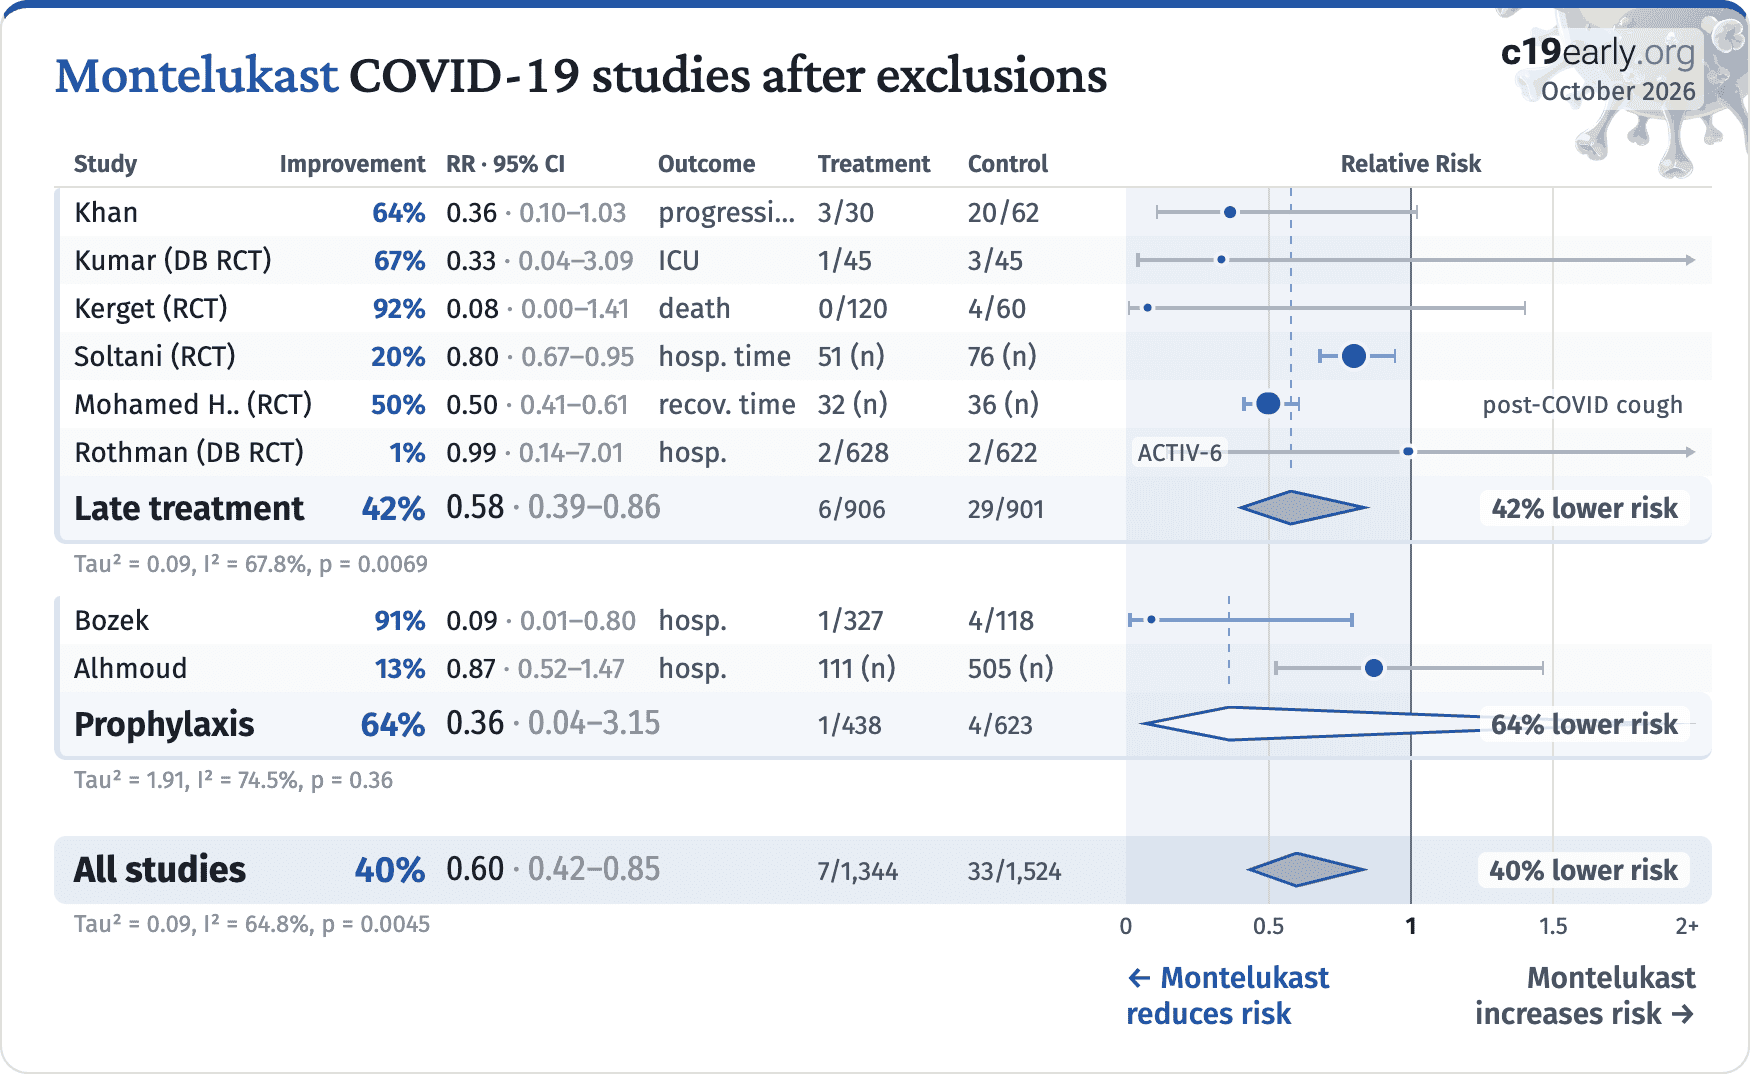
Fig. 17 shows a forest plot for random-effects
meta-analysis of all studies after exclusions.
Zengin, unadjusted results with minimal group details.
Montelukast COVID-19 studies after exclusions
November 2026
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Khan64%0.36 · 0.10–1.03progression3/3020/62
Kumar (DB RCT)67%0.33 · 0.04–3.09ICU1/453/45
Kerget (RCT)92%0.08 · 0.00–1.41death0/1204/60
Soltani (RCT)20%0.80 · 0.67–0.95hosp. time51 (n)76 (n)
Mohamed H.. (RCT)50%0.50 · 0.41–0.61recov. time32 (n)36 (n)post-COVID cough
Rothman (DB RCT)1%0.99 · 0.14–7.01hosp.2/6282/622ACTIV-6
Late treatment42%0.58 · 0.39–0.866/90629/90142% lower risk
Tau² = 0.09, I² = 67.8%, p = 0.0069
Prophylaxis64%0.36 · 0.04–3.151/4384/62364% lower risk
Tau² = 1.91, I² = 74.5%, p = 0.36
All studies40%0.60 · 0.42–0.857/1,34433/1,52440% lower risk
Tau² = 0.09, I² = 64.8%, p = 0.004500.511.52+
Fig. 17. Random-effects meta-analysis for all studies after exclusions.
This plot shows pooled effects,
see the specific outcome analyses for individual outcomes.
Analysis validating pooled outcomes for
COVID-19 can be found below.
Effect extraction is pre-specified, using the most serious outcome reported.
For details see the appendix.
Low-cost treatments were subject to bias and censorship during the pandemic.
Scientific bias is seen in the design, analysis, presentation, and selective
reporting of studies, which often favored negative results. A similar bias is seen in the media
coverage for low-cost treatments.
While broadly seen, bias was particularly notable for ivermectin and hydroxychloroquine, e.g., Scott Alexander noted that "if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."47.
We analyze media coverage for the 227 treatments we
cover using Altmetric66 and PlumX
Metrics67. Altmetric covers ~14,000
news outlets68 and PlumX covers
~55,000 news sources69.
The two services are complementary with coverage of different news sources and different
methods for identifying articles not containing a DOI. We consider studies to have
received significant media coverage if they were covered by at least 100 articles in
either Altmetric of PlumX69,70. The most widespread study was covered
by 1,047 outlets. Studies covered by major
syndicated sources shows hundreds of news articles, while studies covered by few outlets
typically appear in niche medical news sources or press releases.
Fig. 18 and 19 analyze coverage for all low-cost treatments and all high-profit treatments, showing significant bias.
For low-cost treatments media coverage favored negative results 5.4× more than positive results, whereas for high-profit treatments coverage favored positive results 3.8× more than negative results.
The media bias may result in widespread incorrect perceptions on the relative efficacy of high-profit and low-cost treatments. The impact is significant—increased cost limits the use of high-profit
treatments and treatment equity. High-profit treatments were also more difficult to access, especially for earlier treatment which improves efficacy and minimizes community transmission.
Media bias for low-cost COVID‑19 treatments
November 2026
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
2020
2021
2022
2023
2020
2021
2022
2023
0.8%
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
2020
2021
2022
2023
2020
2021
2022
2023
4%
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
5.4×
Negative bias for low-cost treatments
negative studies were 5.4 times more likely to be coveredFig. 18. Mainstream media coverage was biased against positive results for low-cost treatments. When restricting to RCTs, the bias was even larger, with negative RCTs 6.9× more likely to be covered.
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
2020
2021
2022
2023
2020
2021
2022
2023
11%
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
2020
2021
2022
2023
2020
2021
2022
2023
3%
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
3.8×
Positive bias for high-profit treatments
positive studies were 3.8 times more likely to be coveredFig. 19. For high-profit treatments, mainstream media coverage was biased towards positive results. When restricting to RCTs, the bias was even larger, with positive RCTs 12.0× more likely to be covered.
A combination of factors may have led to the very low media coverage of low-cost treatments:
•
Politicization
led to a media environment where coverage was often framed to support a political
narrative rather than to provide objective scientific information. As Scott Alexander
said: "if you say anything in favor of ivermectin you will be cast out
of civilization and thrown into the circle of social hell reserved for Klan members and
1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!'
at you and compare you to Josef Mengele."
There was strong social pressure to
discredit low-cost treatments.•
Censorship
of
information conflicting with selected authorities. For example, individuals and
organizations presenting conflicting science were often shadowbanned or completely banned
on Twitter and YouTube if the science they were reporting conflicted with the opinions of
specific authorities selected by those companies, including when the authorities had
not even reviewed the scientific results in question.•
FDA requires "no
adequate, approved, and available alternatives"
in order to grant an EUA for
novel high-profit interventions, creating an incentive for authorities to ignore or
downplay existing low-cost treatments.•
Regulatory
capture
biases authorities towards high-profit interventions.•
Authorities ignored
most evidence for low-cost treatments
, for example the NIH references only 2% of
studies in delayed, rarely-updated, biased commentaries with no quantitive analysis.•
Media coverage of
science is often not very accurate
, e.g., misunderstanding confounding issues. For
example the media widely considered the RECOVERY HCQ RCT to be conclusive on efficacy, but
very late treatment of late-stage patients (mostly on oxygen already) with an excessive
toxic dose (shown dangerous in a dose comparison RCT) provides no information on the
recommended early/prophylactic treatment. With difficulting in understanding basic
confounders like treatment delay and dose, the media may favor deferring to authorities.
Many studies for low-cost treatments require greater expertise to analyze.
•
Substantial funding
from pharmaceutical advertising
biases editorial decisions towards high-profit
interventions.•
PR power
-
companies/teams with strong PR presence are favored in the media, which correlates with
high-profit and high conflict of interest studies.•
The media was very
negative in general
, inflating risk, and elevating fear and anxiety. A negative bias may
improve ratings and revenue, increasing motivation to continue watching coverage.
26 low-cost treatments were approved in one
or more countries, yet many countries approved no low-cost treatments.
The countries that did adopt low-cost treatments analyzed the evidence early and made
timely approvals. With few exceptions, authorities did not change their initial views,
regardless of how much evidence accumulated showing either efficacy or harm. Why?
The harms of smoking here hidden for 25 yearsJ. Authorities did not analyze the data in real-time, failing to act when
harm was known.
Widespread acknowledgement of harm came only after attempts by two new surgeon generals,
along with pressure from health advocates and a new president, and a review of 7,000 studies.
Similarly for COVID-19, most authorities and experts did not proactively
analyze data in real-time. This guarantees delayed recognition of efficacy or harm, by
which time moral, legal, career, and reputational liabilities strongly disincentivize any
admission of error. Claims of no efficacy (for effective treatments) or safety (for
harmful treatments) were often made prior to strong data being available. Correction
would require admitting to errors that increased mortality, which is unlikely with the
same generation of officials.
Analysis of potential treatments was rarely done, and when done these were
typically minimal efforts.
For example, NIH reviews were highly delayed, cover only a tiny fraction of treatments,
reference only 2% of studies for the treatments covered, and include no
quantitative analysis.
They appear as rarely updated side projects from
external panels implicitly tasked with justifying prior failures.
As with smoking, the thousands of studies could (and should)
have been analyzed and acted on in real-time.
A key structural improvement, applicable to all current and future
diseases, is for authorities to implement real-time proactive analysis of clinical
evidence. This does not remove all bias, but does make it possible to act on evidence,
whereas delayed action may be unlikely due to moral, legal, career, and reputational
liabilities.
c19early.org
Delayed public health acknowledgments
Official acknowledgment of efficacy or harm is often delayed—legal, career, and status risks disincentivize admission of error.
| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
Heterogeneity in COVID-19 studies arises from many factors including:
The time between infection or the onset of symptoms and
treatment may critically affect how well a treatment works. For example an
antiviral may be very effective when used early but may not be effective in
late stage disease, and may even be harmful. Oseltamivir, for example, is
generally only considered effective for influenza when used within 0-36 or
0-48 hours71,72. Baloxavir marboxil studies for influenza
also show that treatment delay is critical — Ikematsu et al. report
an 86% reduction in cases for post-exposure prophylaxis, Hayden et al.
show a 33 hour reduction in the time to alleviation of symptoms for treatment
within 24 hours and a reduction of 13 hours for treatment within 24-48 hours,
and Kumar et al. report only 2.5 hours improvement for inpatient
treatment.
| Treatment delay | Result |
| Post-exposure prophylaxis | 86% fewer cases73 |
| <24 hours | -33 hours symptoms74 |
| 24-48 hours | -13 hours symptoms74 |
| Inpatients | -2.5 hours to improvement75 |
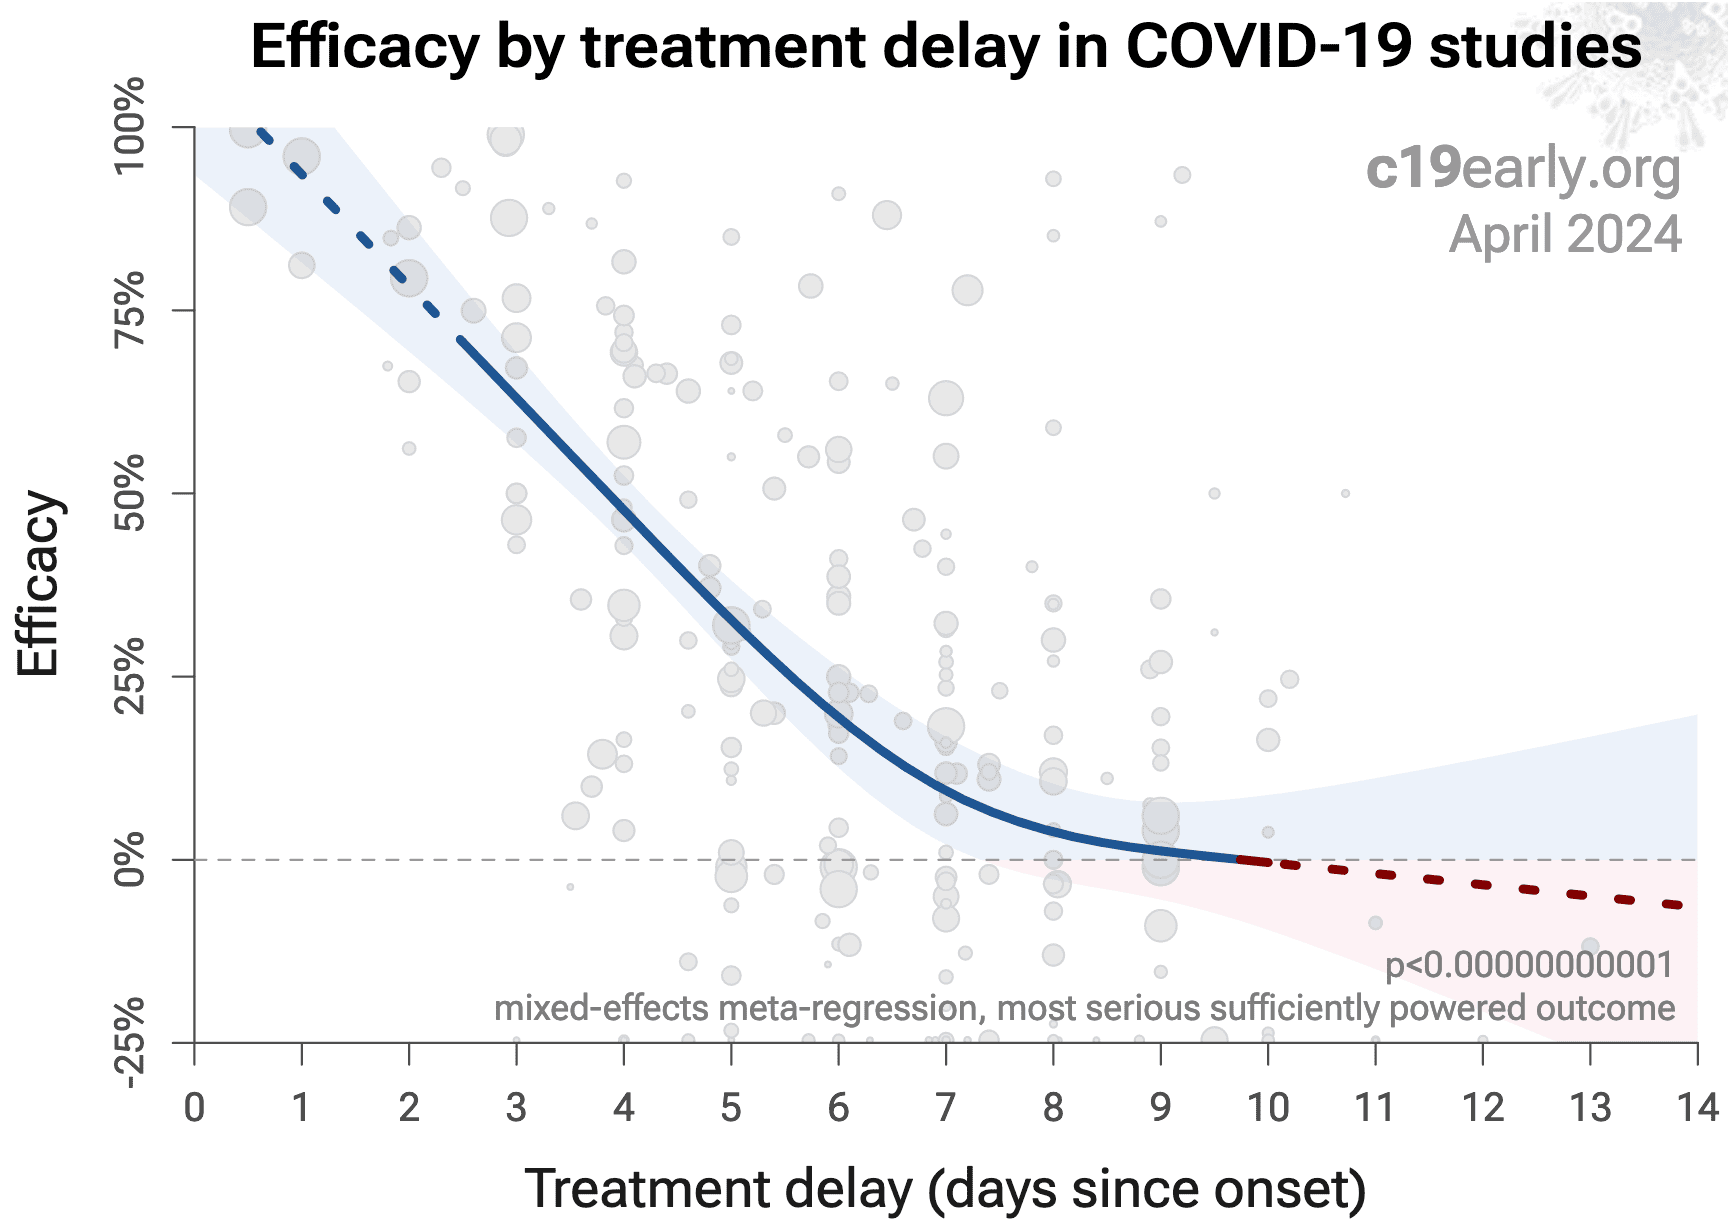
Fig. 20 shows a mixed-effects meta-regression for
efficacy as a function of treatment delay in COVID-19 studies from 227 treatments, showing that efficacy
declines rapidly with treatment delay. Early treatment is critical for COVID-19.
Fig. 20. Early treatment is more effective. Meta-regression showing efficacy as a function of treatment delay in COVID-19 studies from 227 treatments.
Details of the patient population including age and comorbidities may
critically affect how well a treatment works. For example, many COVID-19
studies with relatively young low-comorbidity patients show all patients
recovering quickly with or without treatment. In such cases, there is little
room for an effective treatment to improve results, for example as in
López-Medina et al.
Efficacy may depend critically on the distribution of
SARS-CoV-2 variants encountered by patients. Risk varies significantly across
variants77, for example the Gamma variant shows significantly
different characteristics78-81. Different
mechanisms of action may be more or less effective depending on variants, for
example the degree to which TMPRSS2 contributes to viral entry can differ
across variants82,83.
Effectiveness may depend strongly on the dosage and treatment regimen.
The quality of medications may vary significantly between
manufacturers and production batches, which may significantly affect efficacy
and safety. Williams et al. analyze ivermectin from 11 different sources,
showing highly variable antiparasitic efficacy across different manufacturers.
Xu et al. analyze a treatment from two different manufacturers, showing 9
different impurities, with significantly different concentrations for each
manufacturer.
Across all
studies there is a strong association between different outcomes, for example
improved recovery is strongly associated with lower mortality. However,
efficacy may differ depending on the effect measured, for example a treatment
may be more effective against secondary complications and have minimal effect
on viral clearance.
The
distribution of studies will alter the outcome of a meta-analysis. Consider a
simplified example where everything is equal except for the treatment delay,
and effectiveness decreases to zero or below with increasing delay. If there
are many studies using very late treatment, the outcome may be negative, even
though early treatment is very effective.
All meta-analyses combine heterogeneous studies, varying in population,
variants, and potentially all factors above, and therefore may obscure
efficacy by including studies where treatment is less effective. Generally, we
expect the estimated effect size from meta-analysis to be less than that for
the optimal case.
Looking at all studies is valuable for providing an overview of all research,
important to avoid cherry-picking, and informative when a positive result is
found despite combining less-optimal situations. However, the resulting
estimate does not apply to specific cases such as
early treatment in high-risk populations.
While we present results for all studies, we also present treatment time and
individual outcome analyses, which may be more informative for specific use
cases.
This section validates the use of pooled effects for COVID-19, which enables
earlier detection of efficacy, however pooled effects are no longer required
for montelukast as of July 2022. Efficacy is now known based on specific outcomes for all studies and when restricted to RCTs. Efficacy based on specific outcomes was delayed by 8.2 months compared to using pooled outcomes. Efficacy based on specific outcomes in RCTs was delayed by 20.1 months compared to using pooled outcomes in RCTs.
For COVID-19, delay in clinical results translates into
additional death and morbidity, as well as additional economic and societal
damage. Combining the results of studies reporting different outcomes is
required.
There may be no mortality in a trial with low-risk patients,
however a reduction in severity or improved viral clearance may translate
into lower mortality in a high-risk population.
Different studies may report lower severity, improved recovery, and lower mortality,
and the significance may be very high when combining the results.
"The studies reported different outcomes" is not a good reason for
disregarding results.
Pooling the results of studies reporting different outcomes allows us to use
more of the available information. Logically we should, and do, use additional
information when evaluating treatments—for example dose-response and
treatment delay-response relationships provide additional evidence of efficacy
that is considered when reviewing the evidence for a treatment.
We present both specific outcome and pooled analyses.
In order to combine the results of studies reporting different outcomes we use
the most serious outcome reported in each study, based on the thesis that
improvement in the most serious outcome provides comparable measures of
efficacy for a treatment. A critical advantage of this approach is
simplicity and transparency.
There are many other ways to combine evidence for different outcomes, along
with additional evidence such as dose-response relationships, however these
increase complexity.
Trials with high-risk patients may be restricted due to ethics for treatments
that are known or expected to be effective, and they increase difficulty for
recruiting. Using less severe outcomes as a proxy for more serious outcomes
allows faster and safer collection of evidence.
For many COVID-19 treatments, a reduction in mortality logically
follows from a reduction in hospitalization, which follows from a reduction in
symptomatic cases, which follows from a reduction in PCR positivity. We can
directly test this for COVID-19.
Analysis of the the association between different outcomes across studies from
all 227
treatments we cover confirms the validity of pooled outcome analysis for COVID-19.
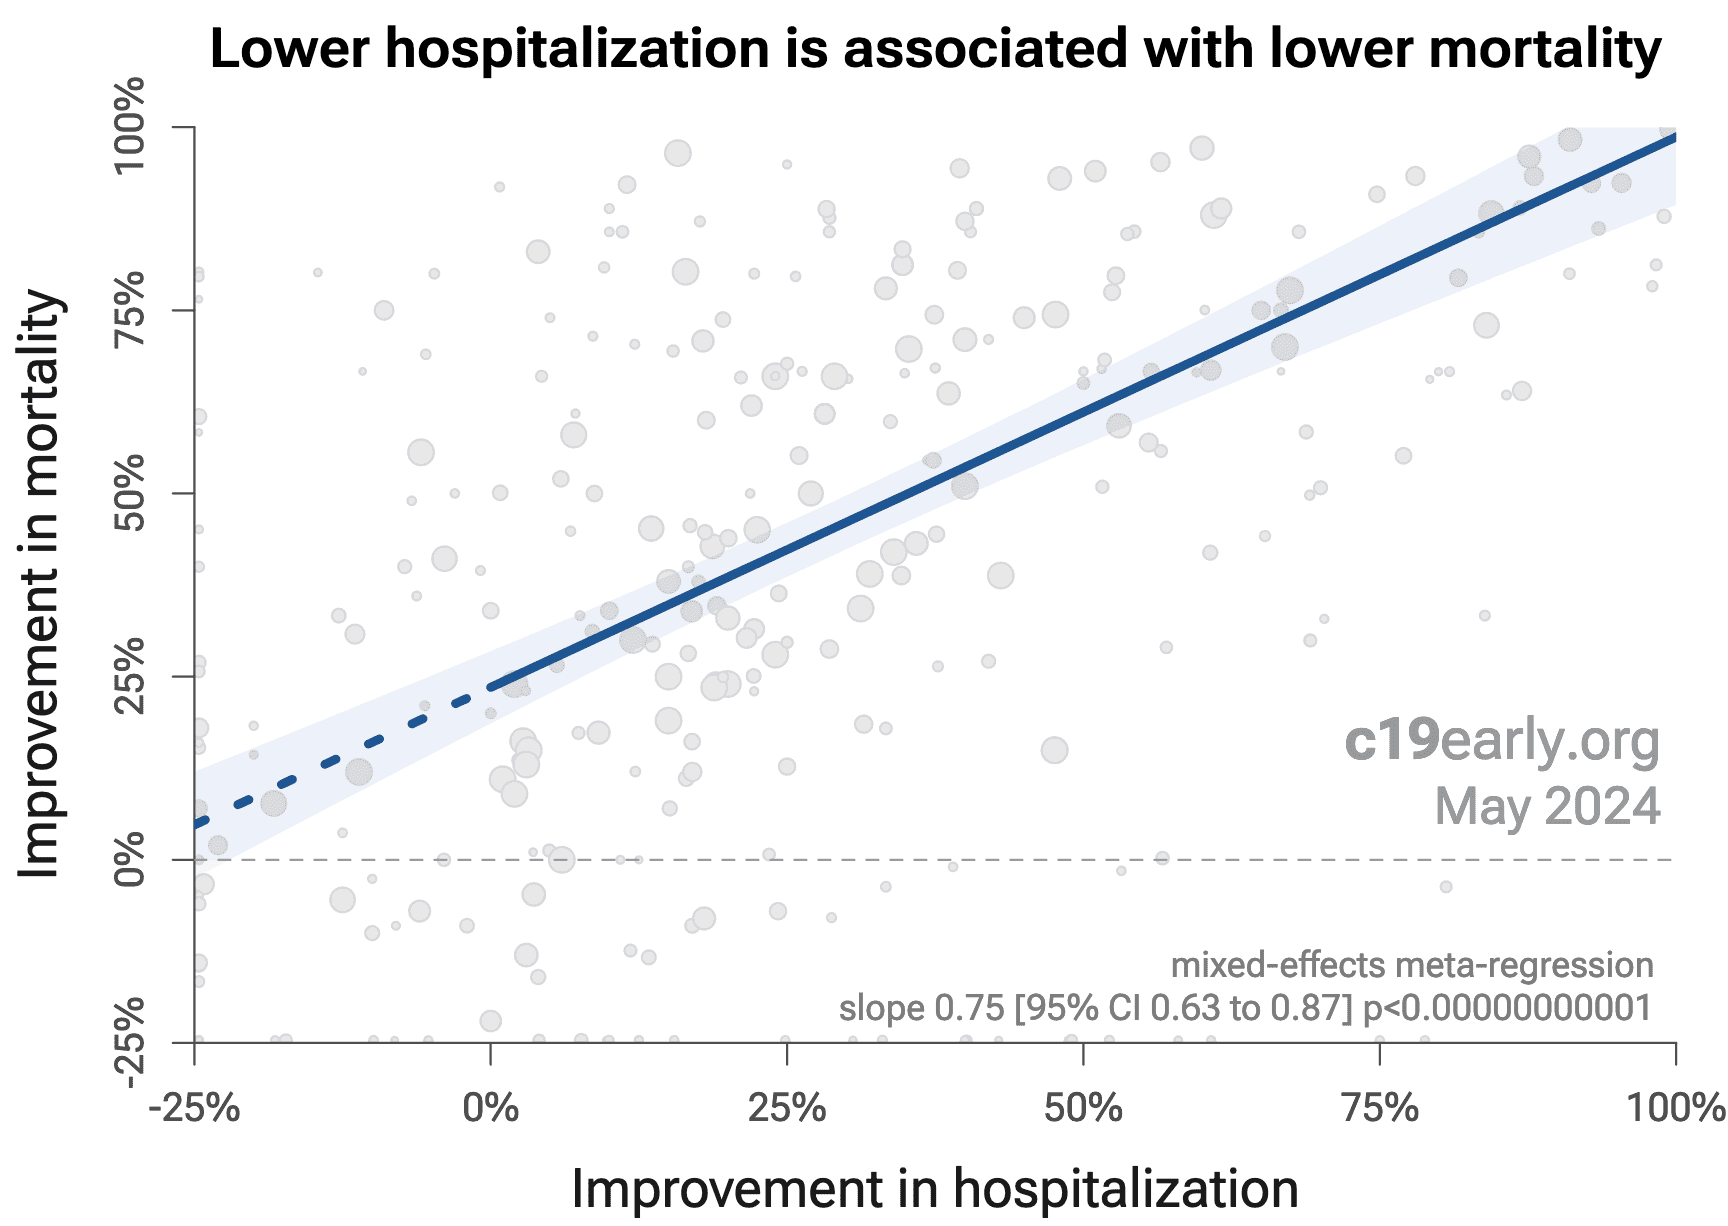
Fig. 21 shows that lower hospitalization is very strongly associated
with lower mortality (p < 0.0000000001).
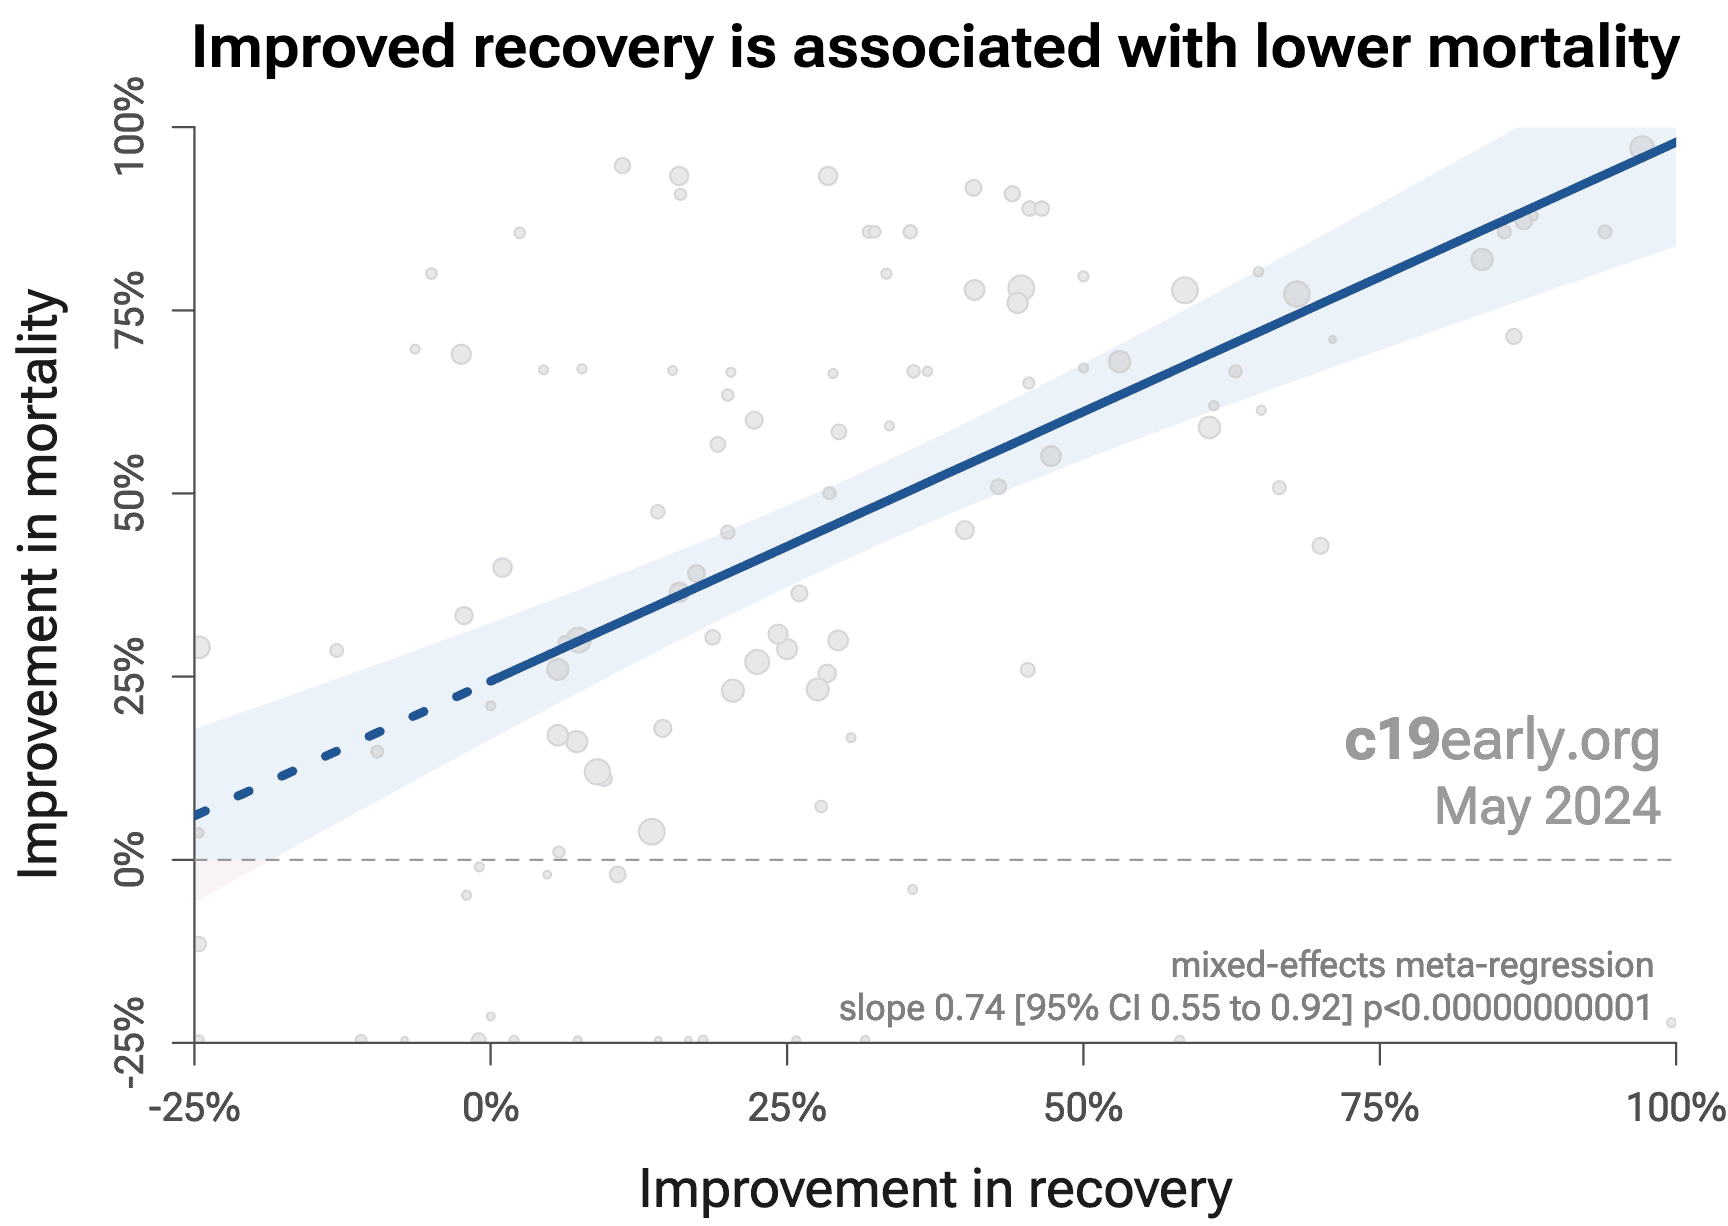
Similarly, Fig. 22 shows that improved recovery is very strongly associated
with lower mortality (p < 0.0000000001).
Considering the extremes, Singh et al. show an association between viral clearance and
hospitalization or death, with p = 0.003 after excluding one large
outlier from a mutagenic treatment, and based on 44 RCTs including 52,384
patients.
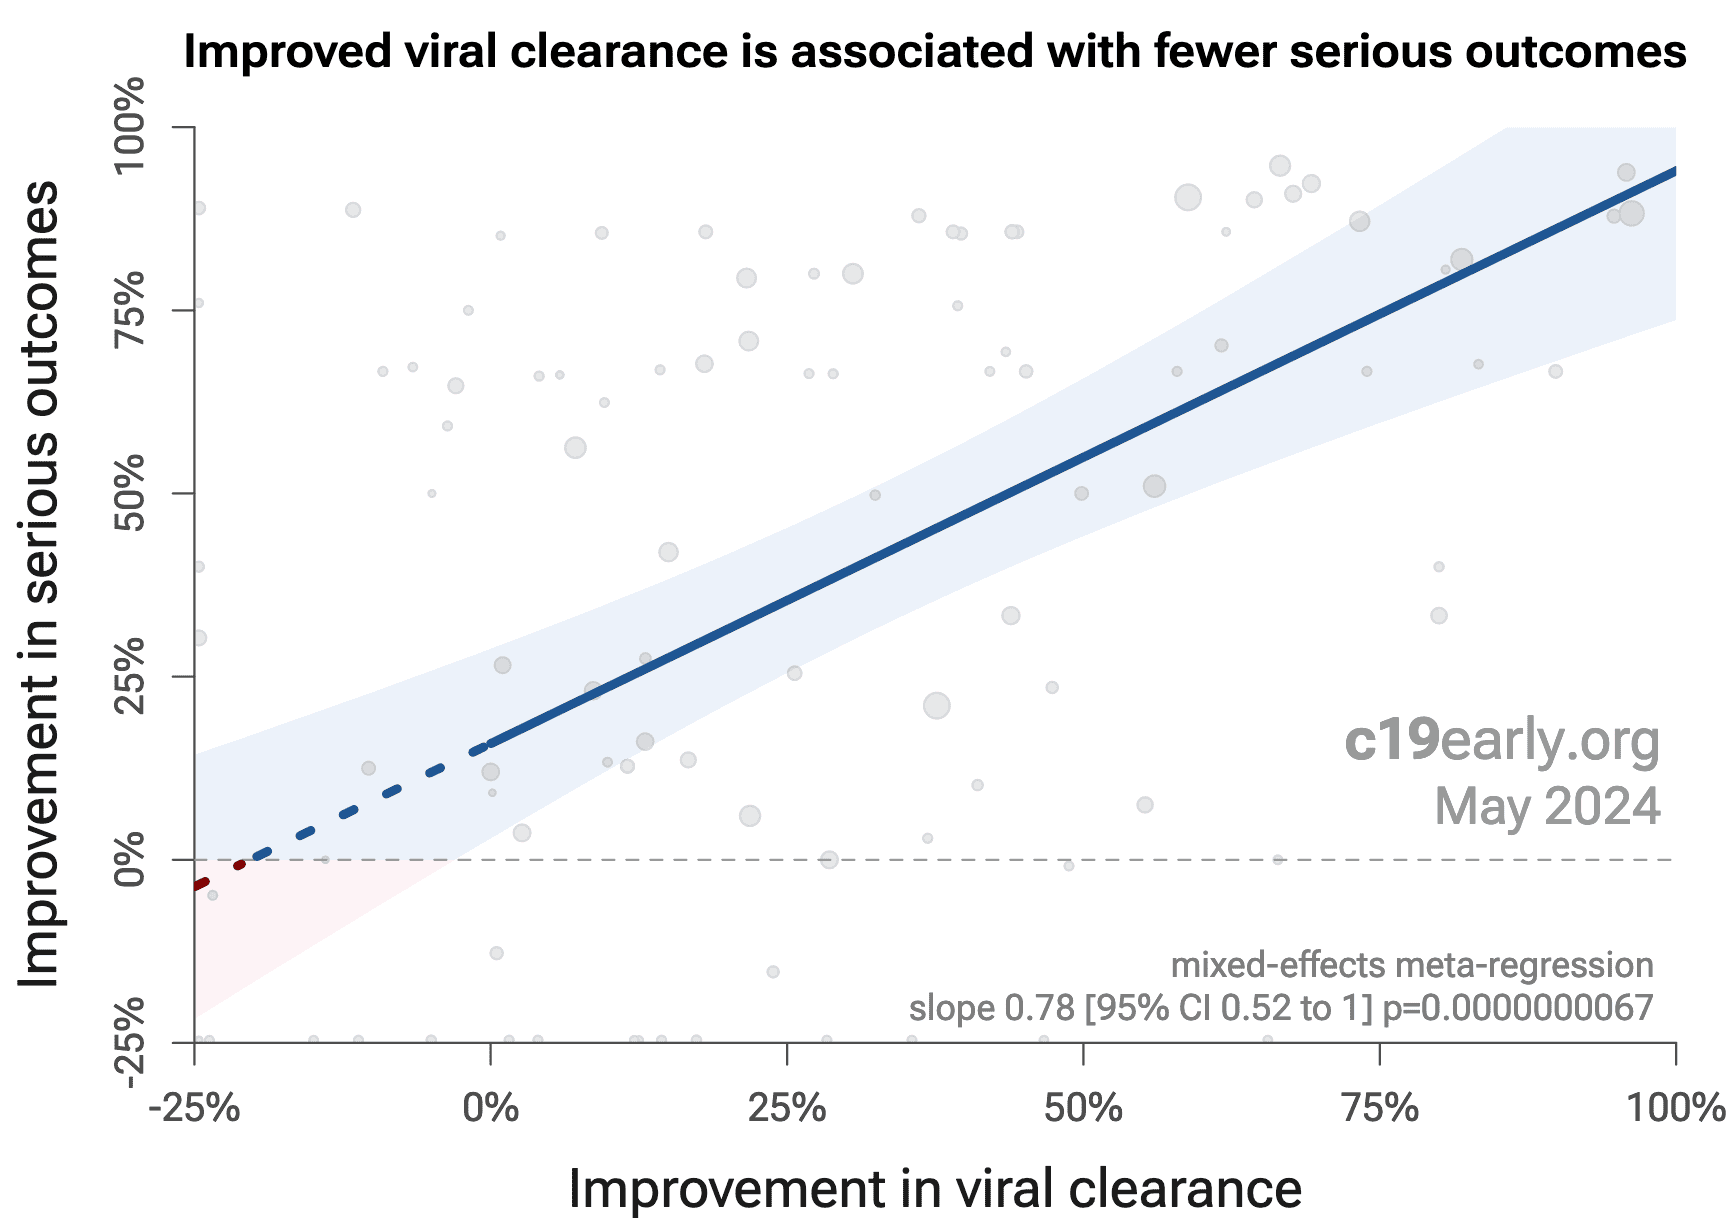
Fig. 23 shows that improved viral clearance is strongly associated
with fewer serious outcomes. The association is very similar to
Singh et al., with higher confidence due to the larger number of
studies. As with Singh et al., the confidence increases
when excluding the outlier treatment, from p = 0.0000000074 to p = 0.00000000015.
Fig. 21. Lower hospitalization is associated with lower mortality, supporting pooled outcome analysis.
Fig. 22. Improved recovery is associated with lower mortality, supporting pooled outcome analysis.
Fig. 21. Improved viral clearance is associated with fewer serious outcomes, supporting pooled outcome analysis.
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. 85% of these have been confirmed with one or more specific outcomes, with a mean delay of 4.6 months. When restricting to RCTs only, 53% of treatments showing statistically significant efficacy/harm with pooled effects have been confirmed with one or more specific outcomes, with a mean delay of 7.5 months.
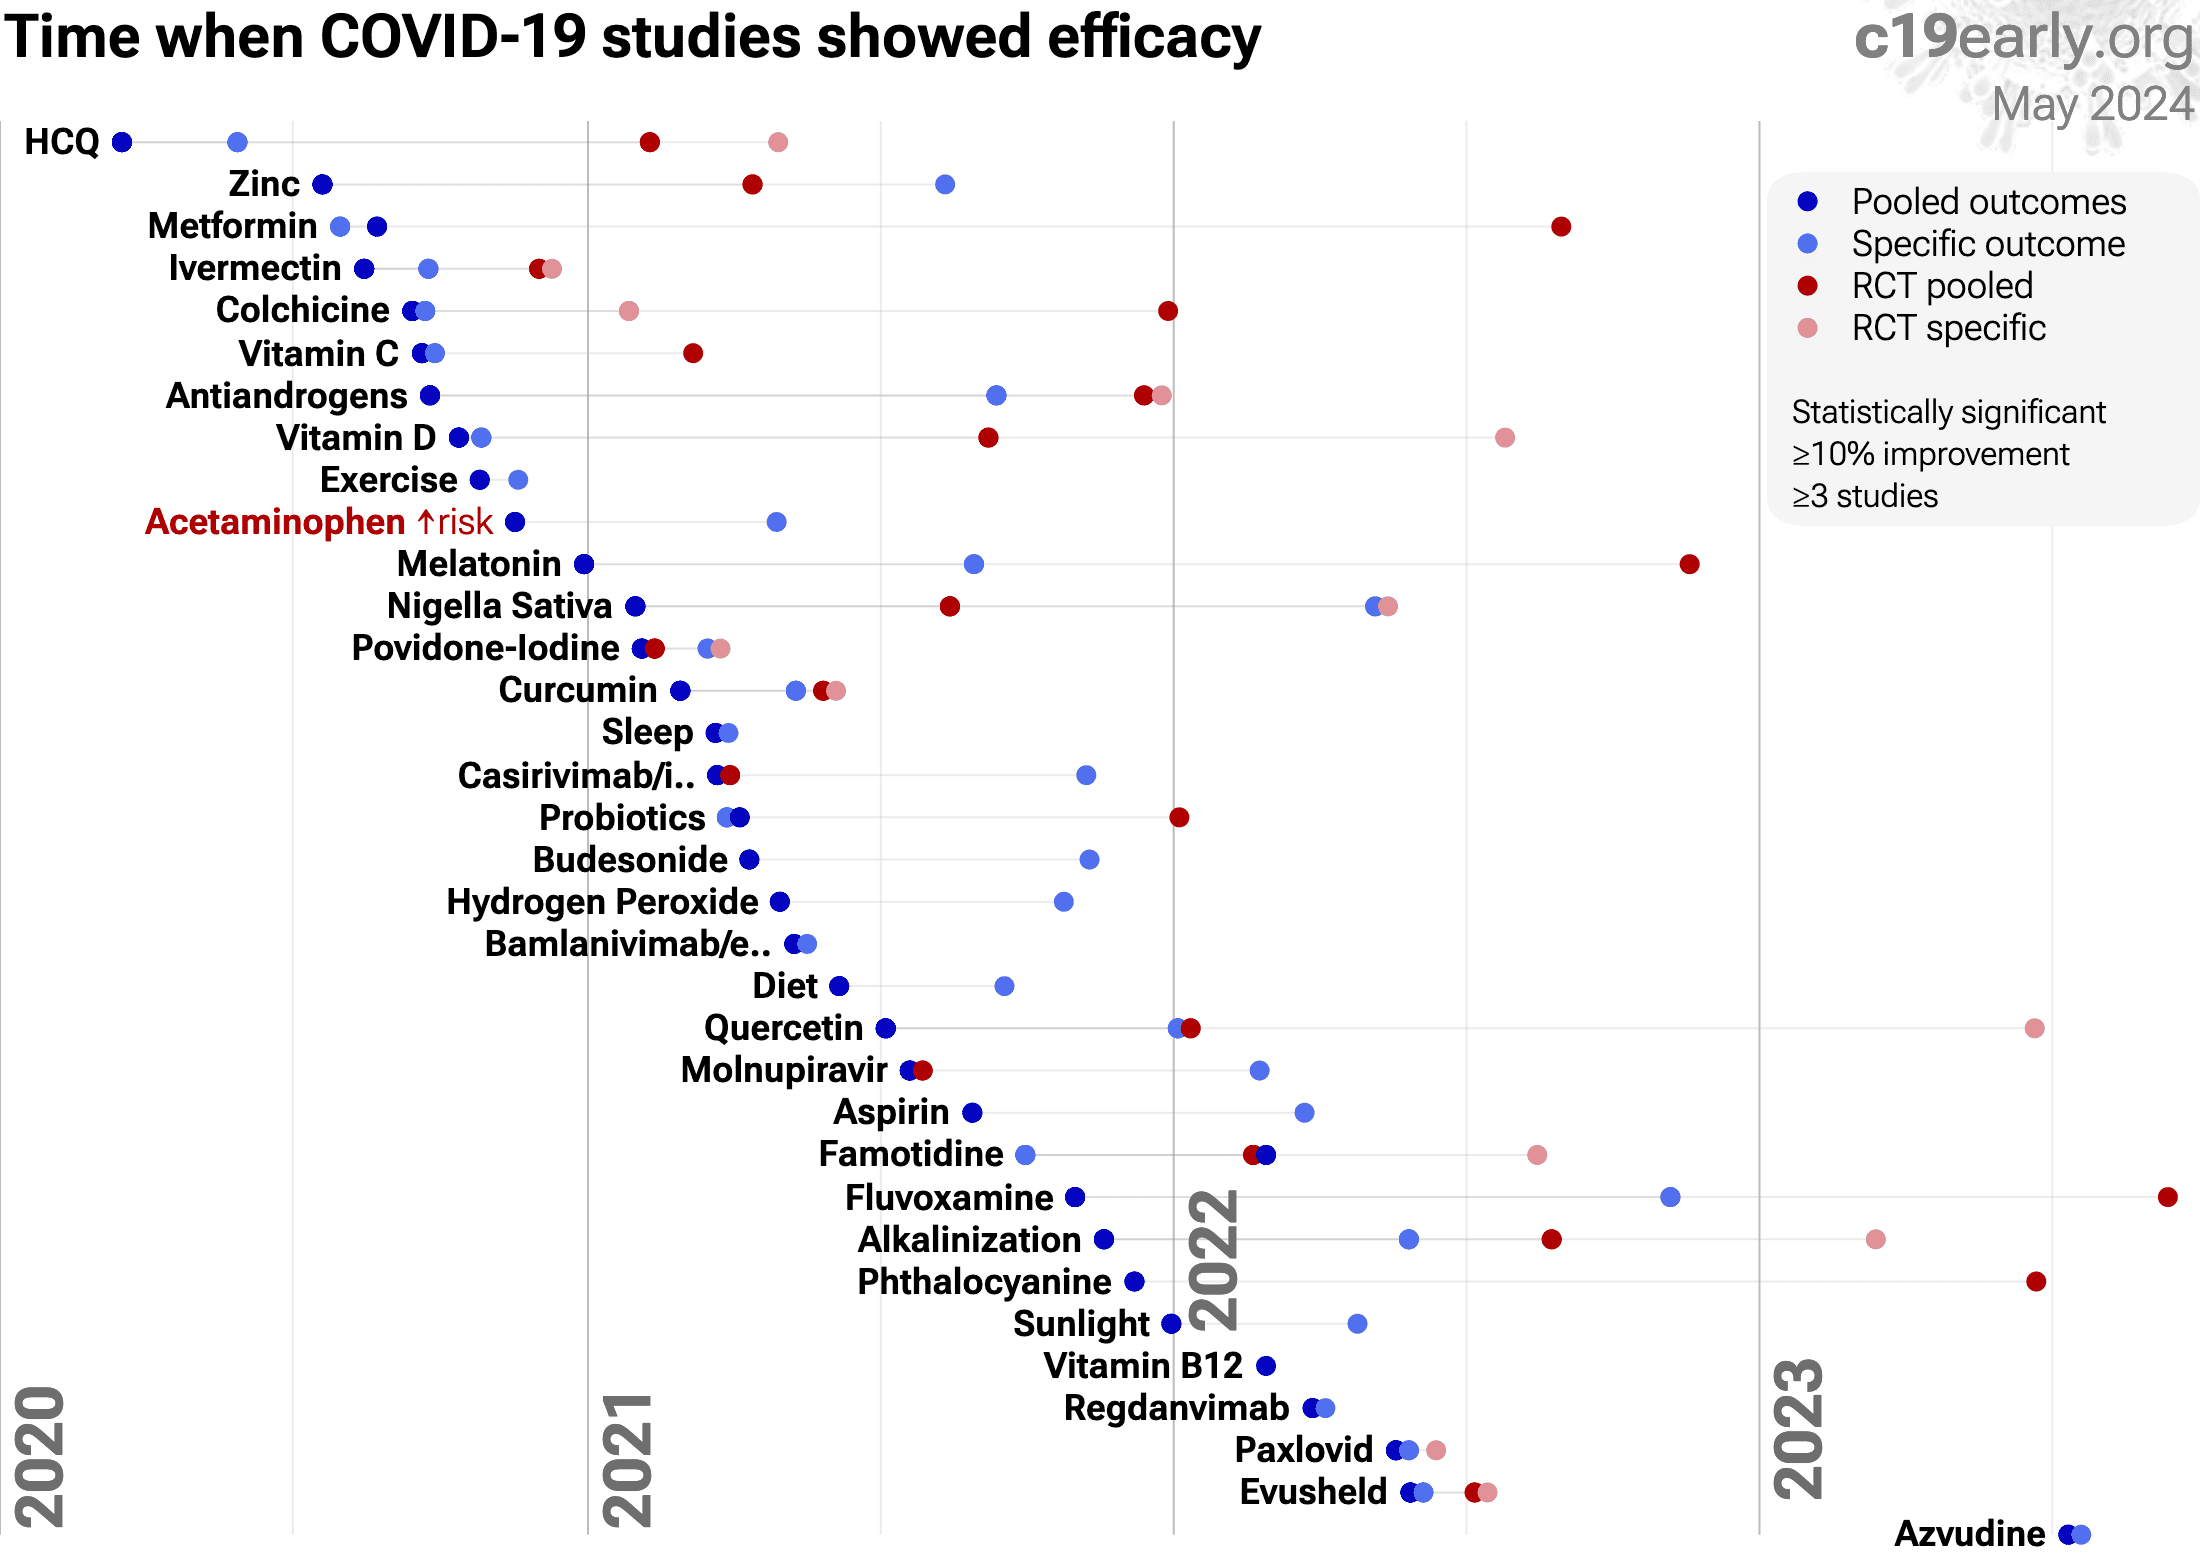
Fig. 24 shows when treatments were found effective during the
pandemic. Pooled outcomes often resulted in earlier detection of efficacy.
Fig. 24. The time when studies showed that
treatments were effective, defined as statistically significant improvement of
≥10% from ≥3 studies.
Pooled results typically show efficacy earlier than specific
outcome results. Results from all studies often shows efficacy much earlier
than when restricting to RCTs.
Results reflect conditions as used in trials to date, these depend on the
population treated, treatment delay, and treatment regimen.
Pooled analysis could hide efficacy, for example a treatment that is
beneficial for late stage patients but has no effect on viral clearance may
show no efficacy if most studies only examine viral clearance. In practice, it
is rare for a non-antiviral treatment to report viral clearance and to not
report clinical outcomes; and in practice other sources of heterogeneity such
as differences in treatment delay are more likely to hide efficacy.
Analysis validates the use of pooled effects and shows significantly faster
detection of efficacy on average.
However, as with all meta-analyses, it is important to review the different
studies included. We also present individual outcome analyses, which may be
more informative for specific use cases.
Montelukast has a boxed warning for neuropsychiatric side effects3.
Publishing is often biased
towards positive results, however evidence suggests that there may be a negative bias for
inexpensive treatments for COVID-19. Both negative and positive results are
very important for COVID-19, media in many countries prioritizes negative
results for inexpensive treatments (inverting the typical incentive for
scientists that value media recognition), and there are many reports of
difficulty publishing positive results112-115.
For montelukast, there is currently not
enough data to evaluate publication bias with high confidence.
One method to evaluate bias is to compare prospective vs.
retrospective studies. Prospective studies are more likely to be published
regardless of the result, while retrospective studies are more likely to
exhibit bias. For example, researchers may perform preliminary analysis with
minimal effort and the results may influence their decision to continue.
Retrospective studies also provide more opportunities for the specifics of
data extraction and adjustments to influence results.
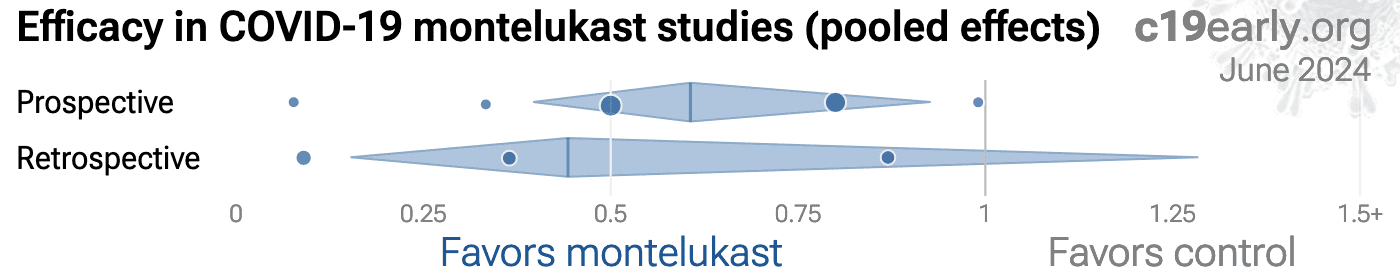
Fig. 25 shows a scatter plot of
results for prospective and retrospective studies.
The median effect size for
retrospective studies is 39% improvement,
compared to 50% for prospective
studies, suggesting a potential bias towards publishing results showing lower efficacy.
Fig. 25. Prospective vs. retrospective studies.
The diamonds show the results of random-effects meta-analysis.
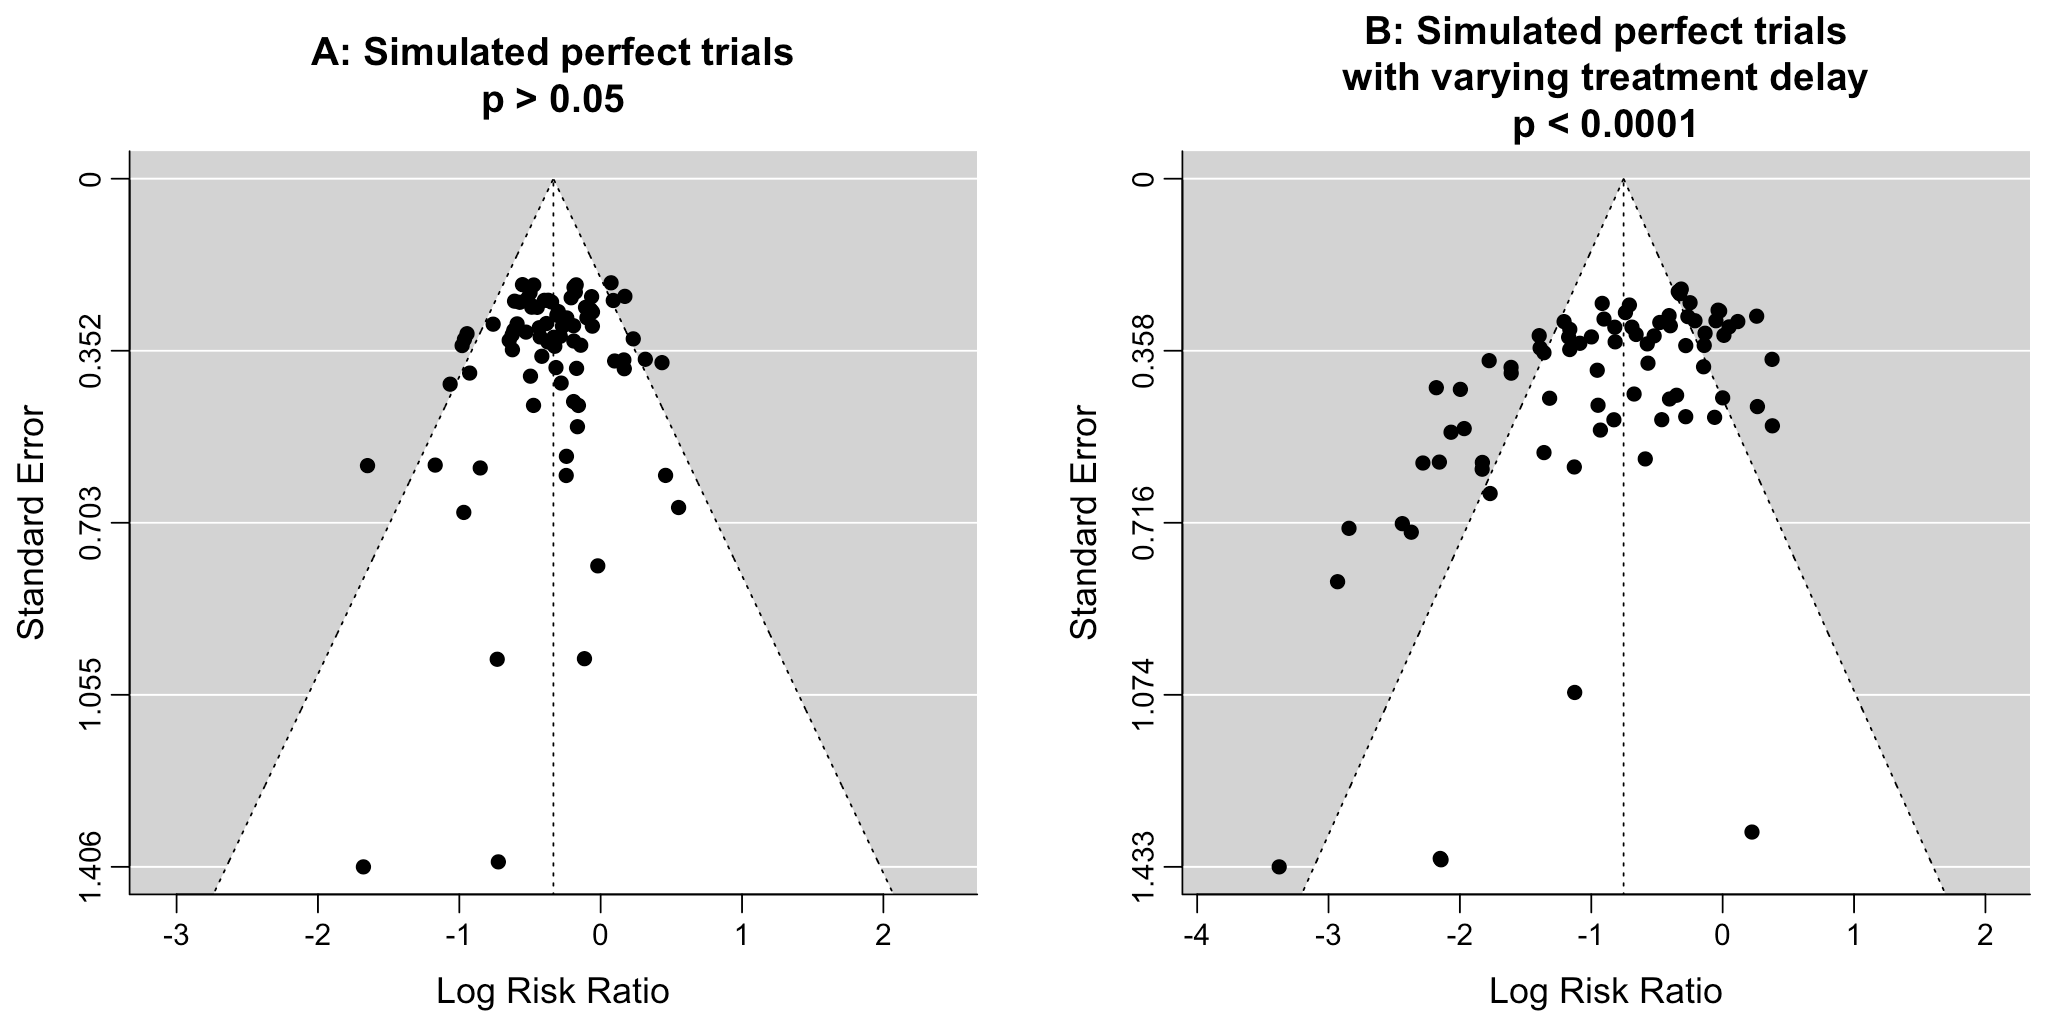
Funnel
plots have traditionally been used for analyzing publication bias. This is
invalid for COVID-19 acute treatment trials — the underlying assumptions
are invalid, which we can demonstrate with a simple example. Consider a set of
hypothetical perfect trials with no bias. Fig. 26 plot A
shows a funnel plot for a simulation of 80 perfect trials, with random group
sizes, and each patient's outcome randomly sampled (10% control event
probability, and a 30% effect size for treatment). Analysis shows no asymmetry
(p > 0.05). In plot B, we add a single typical variation in COVID-19 treatment
trials — treatment delay. Consider that efficacy varies from 90% for
treatment within 24 hours, reducing to 10% when treatment is delayed 3 days.
In plot B, each trial's treatment delay is randomly selected. Analysis now
shows highly significant asymmetry, p < 0.0001, with six variants of
Egger's test all showing p < 0.05116-123.
Note that these tests fail even though treatment delay is uniformly
distributed. In reality treatment delay is more complex — each trial has
a different distribution of delays across patients, and the distribution
across trials may be biased (e.g., late treatment trials may be more common).
Similarly, many other variations in trials may produce asymmetry, including
dose, administration, duration of treatment, differences in SOC,
comorbidities, age, variants, and bias in design, implementation, analysis,
and reporting.
Fig. 26. Example funnel plot analysis for simulated perfect trials.
Pharmaceutical drug
trials often have conflicts of interest whereby sponsors or trial staff have a
financial interest in the outcome being positive. Montelukast for COVID-19
lacks this because it is off-patent, has multiple manufacturers, and is very low cost.
In contrast, most COVID-19 montelukast trials have been run by
physicians on the front lines with the primary goal of finding the best
methods to save human lives and minimize the collateral damage caused by
COVID-19. While pharmaceutical companies are careful to run trials under
optimal conditions (for example, restricting patients to those most likely to
benefit, only including patients that can be treated soon after onset when
necessary, and ensuring accurate dosing), not all montelukast trials
represent the optimal conditions for efficacy.
Summary statistics from
meta-analysis necessarily lose information. As with all meta-analyses, studies
are heterogeneous, with differences
in treatment delay, treatment regimen, patient demographics, variants,
conflicts of interest, standard of care, and other factors. We provide analyses for specific
outcomes and by treatment delay, and we aim to identify key characteristics in
the forest plots and summaries. Results should be viewed in the context of
study characteristics.
Some analyses classify treatment based on early or late
administration, as done here, while others distinguish between mild, moderate,
and severe cases. Viral load does not indicate degree of symptoms — for
example patients may have a high viral load while being asymptomatic. With
regard to treatments that have antiviral properties, timing of treatment is
critical — late administration may be less helpful regardless of
severity.
Details of treatment delay per patient is often not available.
For example, a study may treat 90% of patients relatively early, but the
events driving the outcome may come from 10% of patients treated very late.
Our 5 day cutoff for early treatment may be too conservative, 5 days may be too late in many cases.
Comparison across treatments is confounded by differences in
the studies performed, for example dose, variants, and conflicts of interest.
Trials with conflicts of interest may use designs better suited to the
preferred outcome.
In some cases, the most serious outcome has very few events,
resulting in lower confidence results being used in pooled analysis, however
the method is simpler and more transparent. This is less critical as the
number of studies increases. Restriction to outcomes with sufficient power may
be beneficial in pooled analysis and improve accuracy when there are few
studies, however we maintain our pre-specified method to avoid any
retrospective changes.
Studies show that combinations of treatments can be highly
synergistic and may result in many times greater efficacy than individual
treatments alone86-110.
Therefore standard of care may be critical and benefits may diminish or
disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on
submissions. Accuracy benefits from widespread review and submission of
updates and corrections from reviewers. Less popular treatments may receive
fewer reviews.
No treatment or intervention is 100% available and
effective for all current and future variants. Efficacy may vary significantly
with different variants and within different populations. All treatments have
potential side effects. Propensity to experience side effects may be predicted
in advance by qualified physicians. We do not provide medical advice. Before
taking any medication, consult a qualified physician who can compare all
options, provide personalized advice, and provide details of risks and
benefits based on individual medical history and situations.
1 of 9 studies
combine treatments. The results of
montelukast
alone may differ.
None of the RCTs use combined treatment.
Currently all studies are peer-reviewed.
SARS-CoV-2 infection and replication involves a complex
interplay of 500+ host and viral proteins and other
factors34-41, providing many therapeutic
targets.
Over 12,000 compounds have been predicted to reduce COVID-19
risk42, either by directly
minimizing infection or replication, by supporting immune system function, or
by minimizing secondary complications.
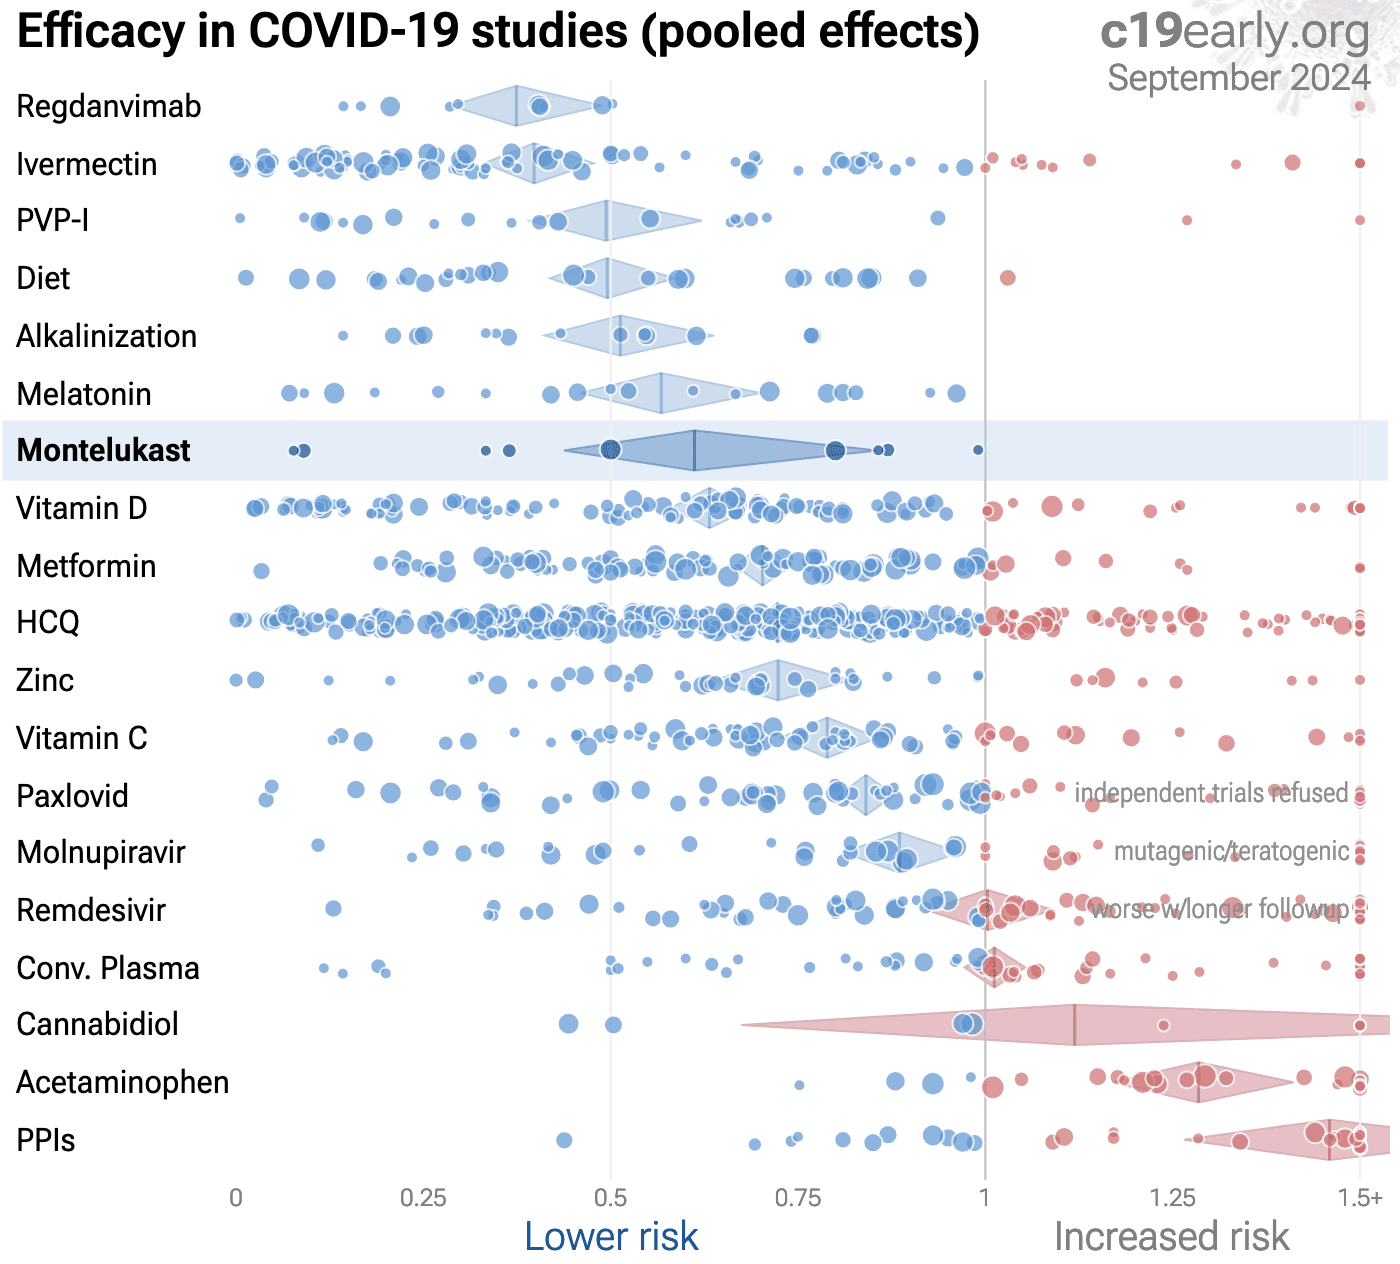
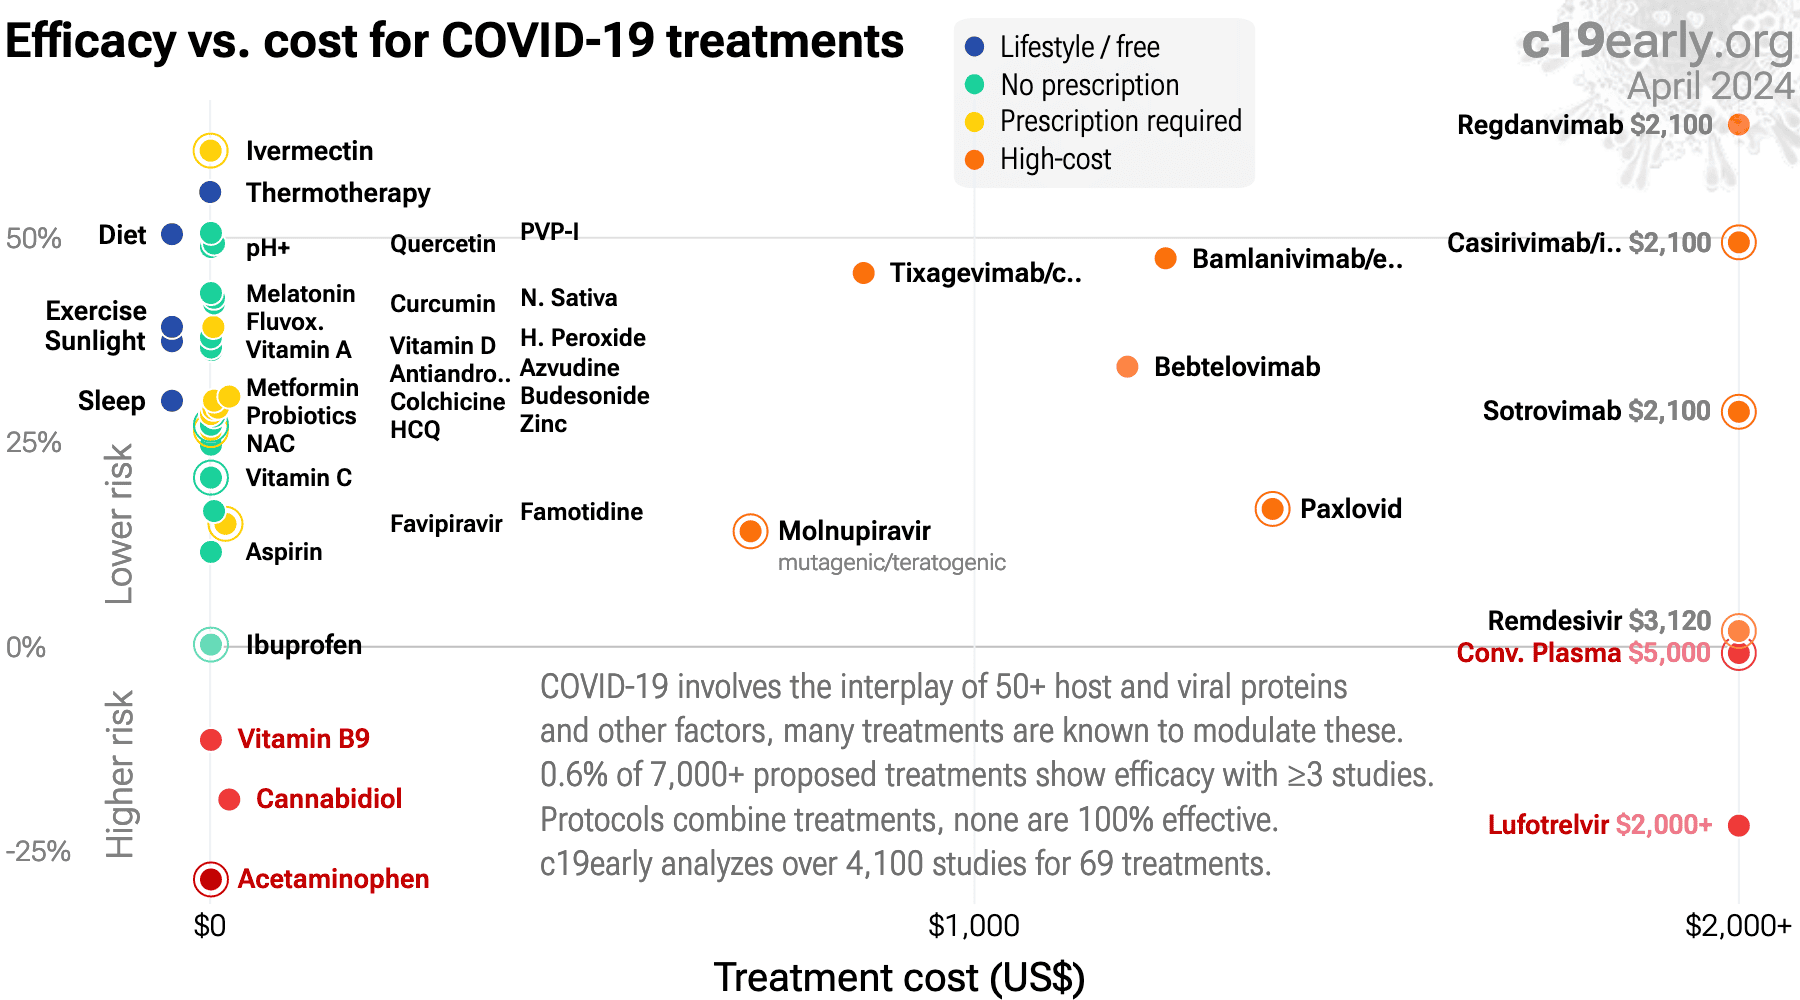
Fig. 27 shows an overview of the results for montelukast
in the context of multiple COVID-19 treatments, and Fig. 28 shows a plot
of efficacy vs. cost for COVID-19 treatments.
Fig. 28. Efficacy vs. cost for COVID-19 treatments.
Studies to date show that montelukast is
an effective treatment for COVID-19.
Significantly lower risk is seen for hospitalization and cases. 4 studies from 4 independent teams in 4 countries show significant
benefit.
Meta-analysis using the most serious outcome reported shows
39% [14‑56%] lower risk. Results are similar for Randomized Controlled Trials and higher quality studies.
Montelukast has a boxed warning for neuropsychiatric side effects3.
Currently there is limited data, with only 37 control events for the most serious outcome in trials to date.
Contact.
Contact us on X at @CovidAnalysis.
Funding.
We have received no funding or
compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest.
We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.AI.
We use AI models (Gemini, Grok, Claude, and
ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest
improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.Updates.
Our COVID-19 meta-analyses involve the extraction of over 229,000
datapoints from thousands of papers for 227 treatments. We thank the
thousands of scientists, physicians, and other contributors that have provided updates,
suggestions, feedback, and corrections. These are all welcome and can be submitted
at https://c19early.org/mkmeta.html.
Dedication.
This work is dedicated to top
evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce
mortality and morbidity during the pandemic. In alphabetical order:
Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty,
Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr.
Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch,
Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work
distributed in accordance with the Creative Commons CC0 1.0 Universal license, which
dedicates the work to the public domain by waiving all rights worldwide under copyright law.
You can distribute, remix, adapt, and build upon this work in any medium or format,
including for commercial purposes, without asking permission. Referenced material and
third-party images retain any original copyrights or restrictions.
See: https://creativecommons.org/publicdomain/zero/1.0/.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
No significant difference in hospitalization
Retrospective 616 COVID-19 patients with asthma in Qatar showing no significant difference in hospitalization risk with montelukast use.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Lower hospitalization and fewer cases
p = 0.019 (hospitalization) and p = 0.0037 (fewer cases)
Retrospective 445 elderly patients with severe asthma showing reduced risk of COVID-19 infection with montelukast treatment.
Estimated 284 patient montelukast late treatment RCT with results not reported over 3 years after estimated completion.
Estimated 380 patient montelukast early treatment RCT with results not reported over 4 years after estimated completion.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Lower mortality and progression
p = 0.012 (mortality) and p = 0.0071 (progression)
RCT 180 hospitalized COVID-19 patients in Turkey showing faster reduction in inflammatory markers, improved pulmonary function, and lower rates of macrophage activation syndrome, respiratory failure and mortality with montelukast treatment (10mg or 20mg daily) in addition to standard care. The higher dose of 20mg daily showed greater improvement in pulmonary function compared to 10mg daily. There was no mortality in the montelukast groups compared to 6.7% mortality with standard care alone.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Lower progression and shorter hospitalization
Not statistically significant · p = 0.085 (progression) and p = 0.33 (hospitalization)
Retrospective 92 hospitalized patients showing lower clinical deterioration with montelukast treatment, without statistical significance in multivariable analysis. The treatment group was older.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
primary
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Trial underpowered for serious outcomes
RCT 90 mild to moderate COVID-19 patients showing no significant differences with montelukast treatment.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Improved recovery with montelukast
p < 0.000001
RCT 68 post-COVID-19 outpatients showing improvement in cough severity measures with montelukast treatment. The montelukast group had a greater reduction in number of cough paroxysms per day, cough severity visual analog scale, cough severity index, and improved cough quality of life scores compared to the control group. The montelukast group also had a shorter duration of cough.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Higher progression with montelukast
Not statistically significant · p = 0.29
RCT 1,250 outpatients with mild to moderate COVID-19 showing no significant difference in time to sustained recovery with montelukast treatment. There were no deaths and only 2 hospitalizations in each group.
Notably, results were better with patients that had mild COVID-19 at baseline compared to moderate/severe cases, and overall efficacy is reduced by poor results with extremely late treatment 9 days after onset, and with patients that had no symptoms at baseline.
Authors note the treatment drug was voluntarily recalled and replaced from another source but do not report why the drug was recalled. Authors describe previous research testing 10mg and 20mg doses, noting that only 20mg showed improved pulmonary function testing, however authors do not indicate why they chose to test the lower dose for COVID-19.
It is unclear why authors only report all-cause hospitalization and urgent care and do not report COVID-19 specific outcomes. Given the low rate of urgent care visits and hospitalization, and the expected baseline frequency of these events independent of COVID-19, most or all of these events may be unrelated to COVID-19.
Authors note that previous research showed improvements specifically for cough, and authors collected cough data, however no results for cough are reported.
ACTIV trial authors have reported a number of issues that may affect the reliability of the results in ACTIV trials including participant fraud158, biased participant demographics159, resource issues that may have led to protocol deviations159, differences in trial design including inconsistent inclusion/exclusion criteria159, participant self-selection bias158,159, underrepresentation of older patients due to web-based recruitment159, changes in treatment and public health policies during trials159, treatment delay determination from shipping logs and delivery that may not be directly to the patient158, variable placebo responses (e.g., oral vs. inhaled)160, logistical challenges maintaining blinding160, errors from complex data collection systems160, unplanned design changes including endpoint changes160, and inconsistent SoC across trial sites and time periods160.
Notably, results were better with patients that had mild COVID-19 at baseline compared to moderate/severe cases, and overall efficacy is reduced by poor results with extremely late treatment 9 days after onset, and with patients that had no symptoms at baseline.
Authors note the treatment drug was voluntarily recalled and replaced from another source but do not report why the drug was recalled. Authors describe previous research testing 10mg and 20mg doses, noting that only 20mg showed improved pulmonary function testing, however authors do not indicate why they chose to test the lower dose for COVID-19.
It is unclear why authors only report all-cause hospitalization and urgent care and do not report COVID-19 specific outcomes. Given the low rate of urgent care visits and hospitalization, and the expected baseline frequency of these events independent of COVID-19, most or all of these events may be unrelated to COVID-19.
Authors note that previous research showed improvements specifically for cough, and authors collected cough data, however no results for cough are reported.
ACTIV trial authors have reported a number of issues that may affect the reliability of the results in ACTIV trials including participant fraud158, biased participant demographics159, resource issues that may have led to protocol deviations159, differences in trial design including inconsistent inclusion/exclusion criteria159, participant self-selection bias158,159, underrepresentation of older patients due to web-based recruitment159, changes in treatment and public health policies during trials159, treatment delay determination from shipping logs and delivery that may not be directly to the patient158, variable placebo responses (e.g., oral vs. inhaled)160, logistical challenges maintaining blinding160, errors from complex data collection systems160, unplanned design changes including endpoint changes160, and inconsistent SoC across trial sites and time periods160.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Shorter hospitalization and improved recovery
p = 0.011 (hospitalization) and p = 0.00056 (recovery)
RCT 180 hospitalized COVID-19 patients showing improved cough symptoms and shorter hospitalization with montelukast/gabapentin compared to gabapentin. For gabapentin vs. dextromethorphan there was no significant difference in hospitalization and reduced improvement in cough symptoms.
Montelukast for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Montelukast
reduces riskMontelukast
increases risk →
reduces riskMontelukast
increases risk →
Higher ICU admission with montelukast
Not statistically significant · p = 0.46
Retrospective 75 hospitalized COVID-19 patients over 60 in Turkey showing no significant differences with montelukast treatment.
We perform ongoing searches of PubMed, medRxiv, Europe PMC, ClinicalTrials.gov, The Cochrane
Library, Google Scholar, Research Square, ScienceDirect, Oxford University Press, the
reference lists of other studies and meta-analyses, and submissions to the site c19early.org, which regularly receives notification of studies upon
publication.
Search terms are montelukast and COVID-19 or SARS-CoV-2. Automated searches are performed twice daily, with all matches reviewed for inclusion.
All studies regarding the use of montelukast for COVID-19 that report a comparison with a
control group are included in the main analysis.
Sensitivity analysis is performed, excluding studies with major issues, epidemiological
studies, and studies with minimal available information.
Studies with major unexplained data issues, for example major outcome data that is
impossible to be correct with no response from the authors, are excluded.

Fig. 29.
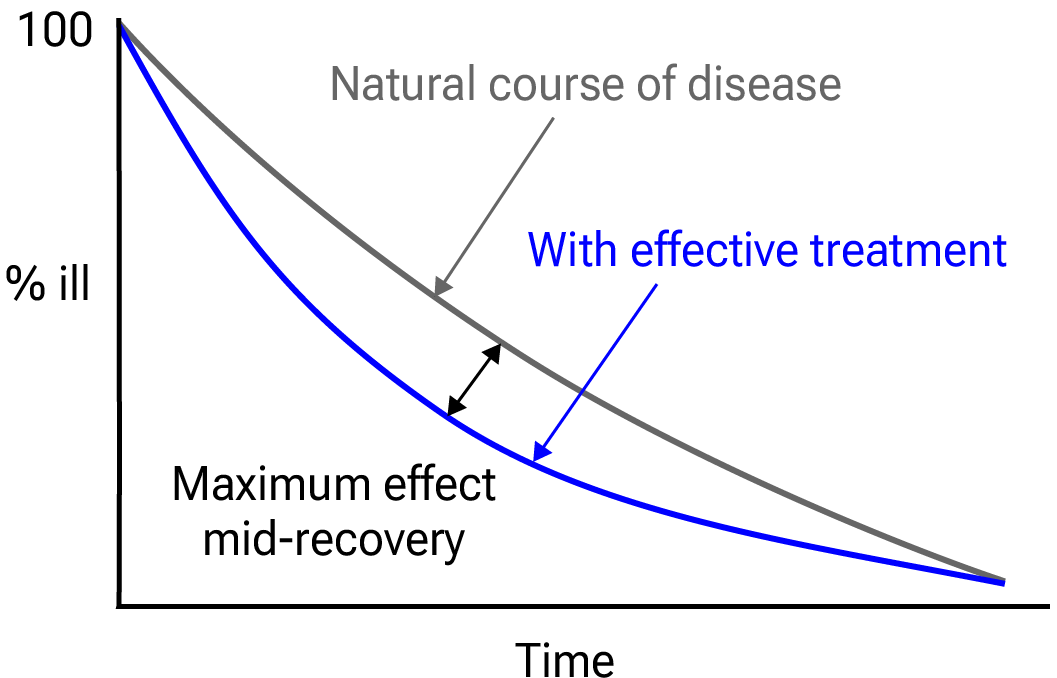
Mid-recovery results can more accurately reflect efficacy when almost all patients
recover. Mateja et al. confirm that intermediate viral load results more accurately
reflect hospitalization/death.
We extracted effect sizes and associated data from all studies. If studies report multiple
kinds of effects then the most serious outcome is used in pooled analysis, while
other outcomes are included in the outcome-specific analyses. For example, if effects for
mortality and cases are reported then they are both used in specific outcome analyses,
while mortality is used for pooled analysis.
If symptomatic results are reported at multiple times, we use the latest time, for example
if mortality results are provided at 14 days and 28 days, the results at 28 days have
preference. Mortality alone is preferred over combined outcomes.
Outcomes with zero events in both arms are not used, the next most serious outcome with
one or more events is used. For example, in low-risk populations with no mortality, a
reduction in mortality with treatment is not possible, however a reduction in
hospitalization, for example, is still valuable.
Clinical outcomes are considered more important than viral outcomes.
When basically all patients recover in both treatment and control groups, preference for
viral clearance and recovery is given to results mid-recovery where available. After most
or all patients have recovered there is little or no room for an effective treatment to do
better, however faster recovery is valuable.
An IPD meta-analysis confirms that intermediate viral load reduction is more closely
associated with hospitalization/death than later viral load reduction161.
If only individual symptom data is available, the most serious symptom has
priority, for example difficulty breathing or low SpO2 is more
important than cough.
Forest plots are computed using PythonMeta162 with the DerSimonian and
Laird random-effects model (the fixed effect assumption is not plausible in this case) and
inverse variance weighting.
Results are presented with 95% confidence intervals. Heterogeneity among studies was
assessed using the I2 statistic.
When results provide an odds ratio, we compute the relative risk when possible, or convert
to a relative risk according to Zhang et al.
Reported confidence intervals and p-values are used when available, and adjusted
values are used when provided. If multiple types of adjustments are reported propensity
score matching and multivariable regression has preference over propensity score matching
or weighting, which has preference over multivariable regression. Adjusted results have
preference over unadjusted results for a more serious outcome when the adjustments
significantly alter results.
When needed, conversion between reported p-values and confidence intervals followed
Altman, Altman (B), and Fisher's exact test was used to calculate
p-values for event data. If continuity correction for zero values is required, we
use the reciprocal of the opposite arm with the sum of the correction factors equal to
1166.
Results are expressed with RR < 1.0 favoring treatment, and using the risk of a negative
outcome when applicable (for example, the risk of death rather than the risk of survival).
If studies only report relative continuous values such as relative times, the ratio of the
time for the treatment group versus the time for the control group is used. Calculations
are done in Python (3.15.2) with
scipy (1.18.1), pythonmeta (1.26), numpy (2.5.4), statsmodels (0.15.0), and plotly (6.9.0).
Mixed-effects meta-regression results are computed with R (4.4.0) using the metafor
(4.6-0) and rms (6.8-0) packages, and using the most serious sufficiently powered outcome.
For all statistical tests, a p-value less than 0.05 was considered statistically
significant.
Grobid 0.8.2 is used to parse PDF documents.
When evaluating potential effect modification across groups, we use an
interaction test as described by Altman (C) et al. We compared the log-transformed
relative risks using a z-test, deriving the standard error of the difference from
the 95% confidence intervals. A two-sided interaction p-value of < 0.05 was
considered a statistically significant difference in treatment effect between the
groups.
Cochrane RoB 2/ROBINS-I are often used to evaluate studies, and have the advantage of
providing standardized rules that can be applied with minimal understanding of the domain
and study. However, the rules do not account for many real-world issues, often
overemphasize or underemphasize others, and studies show low inter-rater
reliability174.
Certain domains are more applicable for these tools, however the time-sensitive nature of
a pandemic, with significant mortality for every day of delay in evidence assessment, and
the characteristics of COVID-19 make them inappropriate for this domain.
This can be demonstrated with examples where expert RoB 2/ROBINS-I ratings do not match
reality for COVID-19. Popp et al. use RoB 2 to classify Reis et al. as low
risk of bias, however this is the opposite of reality—the trial not only has very
high risk of bias, but has very high actual known bias, refusing to release data despite
pledging to, reporting multiple impossible numbers, having blinding and randomization
failure, and many other issues176.
Axfors et al. use RoB 2 to classify Horby et al. as low risk of bias, however
this is the opposite of reality—the very late treatment and excessive dosage used
produces results with no relevance to recommended usage.
HCQ shows poor results with
late treatment and excessive dosage, and the combination shows harmK.
Hempenius et al. use ROBINS-I to classify 33 studies for HCQ. The two rated as having
the lowest risk of bias172,173 are far from the most informative. Both
involve very late treatment, providing no information on recommended usage, and ROBINS-I
does a very poor job of accounting for the impact of confounding factorsL.
Our quality evaluation focuses on known issues and bias, and the potential
impact on outcomes, rather than just the risk of bias.
The estimated potential impact of each confounding factor, and the direction of the impact
is considered. For example, consider a study that shows significantly lower risk, the
value of the study varies significantly if confounding points to an underestimate or an
overestimate of efficacy. In one case, the real effect may be null, while the other case
provides stronger evidence of efficacy (which may be greater than the study shows).
Analysis focusing on the risk of bias, while simpler, may penalize studies for theoretical
or technical issues that have no or minimal impact on outcomes. Analysis also depends on
the outcome, for example certain issues are less relevant for objective outcomes such as
mortality.
Inaccurate penalization, and inaccurate high-quality evaluation in the face of known major
issues affecting outcomes, increases in significance during a pandemic when immediate
recognition of new evidence is critical, and when considering all global studies, as
required during a pandemic. Investigators in other countries may have different customs
for design, analysis, and reporting, and different English language skills, however they
may not be less diligent or have greater bias.
Investigators in lower-pharmaceutical-profit countries may have lower bias towards
profitable interventions.
We have classified studies as
early treatment if most patients are not already at a severe stage at the time of
treatment (for example based on oxygen status or lung involvement), and treatment started
within 5 days of the onset of symptoms. If studies contain a mix of early treatment and
late treatment patients, we consider the treatment time of patients contributing most to
the events (for example, consider a study where most patients are treated early but late
treatment patients are included, and all mortality events were observed with late
treatment patients).
We note that a shorter time may be preferable. Antivirals are typically only considered
effective when used within a shorter timeframe, for example 0-36 or 0-48 hours for
oseltamivir, with longer delays not being effective71,72.
This is a living analysis and is updated regularly.
We received no funding, this research is done in our spare time.
We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/mkmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
| Durdagi, 6/1/2022, Randomized Controlled Trial, Turkey, trial NCT04718285 (history). | Estimated 380 patient RCT with results unknown and over 4 years late. |
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
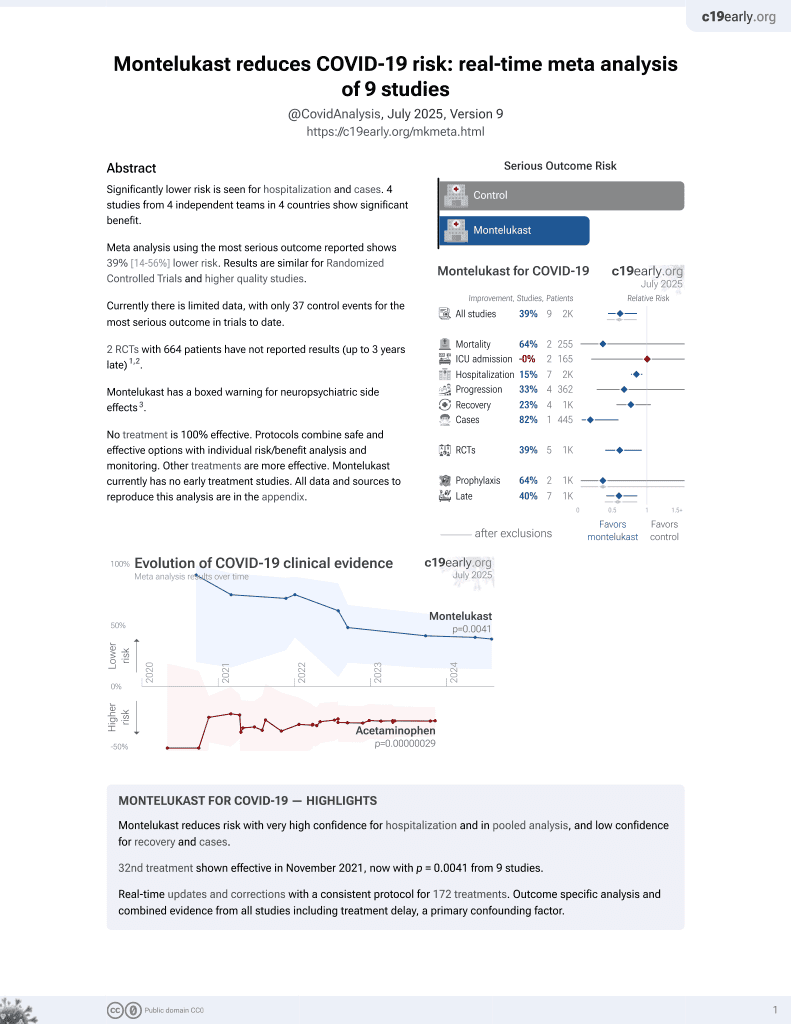
| Cordero, 8/31/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, trial NCT04695704 (history) (E-SPERANZA). | Estimated 284 patient RCT with results unknown and over 3 years late. |
| Kerget, 1/4/2022, Randomized Controlled Trial, Turkey, peer-reviewed, mean age 54.6, 4 authors, study period May 2021 - July 2021, trial NCT05094596 (history). | risk of death, 92.3% lower, RR 0.08, p = 0.01, treatment 0 of 120 (0.0%), control 4 of 60 (6.7%), NNT 15, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| risk of death, 88.9% lower, RR 0.11, p = 0.12, treatment 0 of 60 (0.0%), control 4 of 60 (6.7%), NNT 15, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 20mg. | |
| risk of death, 88.9% lower, RR 0.11, p = 0.12, treatment 0 of 60 (0.0%), control 4 of 60 (6.7%), NNT 15, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 10mg. | |
| MAS or respiratory failure, 81.2% lower, RR 0.19, p = 0.007, treatment 3 of 120 (2.5%), control 8 of 60 (13.3%), NNT 9.2. | |
| MAS or respiratory failure, 87.5% lower, RR 0.12, p = 0.03, treatment 1 of 60 (1.7%), control 8 of 60 (13.3%), NNT 8.6, 20mg. | |
| MAS or respiratory failure, 75.0% lower, RR 0.25, p = 0.09, treatment 2 of 60 (3.3%), control 8 of 60 (13.3%), NNT 10.0, 10mg. | |
| hospitalization time, 15.5% lower, relative time 0.85, p = 0.04, treatment mean 9.3 (±3.6) n=60, control mean 11.0 (±5.3) n=60, 20mg. | |
| hospitalization time, 14.5% lower, relative time 0.85, p = 0.03, treatment mean 9.4 (±2.1) n=60, control mean 11.0 (±5.3) n=60, 10mg. | |
| Khan, 3/4/2021, retrospective, USA, peer-reviewed, 16 authors. | risk of progression, 63.5% lower, RR 0.36, p = 0.09, treatment 3 of 30 (10.0%), control 20 of 62 (32.3%), NNT 4.5, adjusted per study, odds ratio converted to relative risk, multivariable. |
| hospitalization time, 12.5% lower, relative time 0.88, p = 0.33, treatment median 7.0 IQR 6.5 n=30, control median 8.0 IQR 6.0 n=62. | |
| Kumar (B), 11/22/2021, Double Blind Randomized Controlled Trial, placebo-controlled, India, peer-reviewed, mean age 45.0, 10 authors, study period 1 September, 2020 - 31 December, 2020, average treatment delay 5.8 days. | risk of ICU admission, 66.7% lower, RR 0.33, p = 0.62, treatment 1 of 45 (2.2%), control 3 of 45 (6.7%), NNT 23. |
| risk of progression, 25.0% higher, RR 1.25, p = 0.79, treatment 10 of 45 (22.2%), control 8 of 45 (17.8%), primary outcome. | |
| risk of no hospital discharge, no change, RR 1.00, p = 1.00, treatment 21 of 45 (46.7%), control 21 of 45 (46.7%). | |
| Lima-Morales, 2/10/2021, prospective, Mexico, peer-reviewed, 10 authors, average treatment delay 7.2 days, this trial uses multiple treatments in the treatment arm (combined with azithromycin, montelukast, and aspirin) - results of individual treatments may vary, excluded: combined treatments may contribute more to the effect seen. | risk of death, 77.7% lower, RR 0.22, p < 0.001, treatment 15 of 481 (3.1%), control 52 of 287 (18.1%), NNT 6.7, adjusted per study, odds ratio converted to relative risk, multivariate. |
| risk of mechanical ventilation, 51.9% lower, RR 0.48, p = 0.15, treatment 8 of 434 (1.8%), control 11 of 287 (3.8%), NNT 50. | |
| risk of hospitalization, 67.4% lower, RR 0.33, p < 0.001, treatment 44 of 481 (9.1%), control 89 of 287 (31.0%), NNT 4.6, adjusted per study, odds ratio converted to relative risk, multivariate. | |
| risk of no recovery, 58.6% lower, RR 0.41, p < 0.001, treatment 75 of 481 (15.6%), control 118 of 287 (41.1%), NNT 3.9, adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, recovery at day 14 after symptoms, multivariate. | |
| Mohamed Hussein, 9/15/2022, Randomized Controlled Trial, Egypt, peer-reviewed, mean age 43.0, 7 authors, post-COVID cough. | improvement, 50.0% lower, relative time 0.50, p < 0.001, treatment mean 5.0 (±1.4) n=32, control mean 10.0 (±1.5) n=36. |
| paroxysms/day, 70.0% lower, relative time 0.30, p < 0.001, treatment mean 3.0 (±1.2) n=32, control mean 10.0 (±4.1) n=36. | |
| VAS, 81.8% lower, relative time 0.18, p < 0.001, treatment mean 12.0 (±6.0) n=32, control mean 66.0 (±12.0) n=36. | |
| severity index, 80.0% lower, relative time 0.20, p < 0.001, treatment mean 4.0 (±1.1) n=32, control mean 20.0 (±5.0) n=36. | |
| QOL, 81.6% lower, relative time 0.18, p < 0.001, treatment mean 18.0 (±2.5) n=32, control mean 98.0 (±2.0) n=36. | |
| Rothman, 5/18/2024, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, median age 53.0, 32 authors, study period 27 January, 2023 - 23 June, 2023, average treatment delay 5.0 days, trial NCT04885530 (history) (ACTIV-6). | risk of hospitalization, 1.0% lower, RR 0.99, p = 1.00, treatment 2 of 628 (0.3%), control 2 of 622 (0.3%), NNT 32551. |
| hosp./ER, 1.0% lower, RR 0.99, p = 1.00, treatment 18 of 628 (2.9%), control 18 of 622 (2.9%), NNT 3617. | |
| risk of progression, 48.0% higher, OR 1.48, p = 0.29, clinical progression, day 28, RR approximated with OR. | |
| risk of progression, 29.0% lower, OR 0.71, p = 0.82, clinical progression, day 14, RR approximated with OR. | |
| risk of progression, 31.0% higher, OR 1.31, p = 0.27, clinical progression, day 7, RR approximated with OR. | |
| risk of no recovery, 2.0% lower, HR 0.98, p = 0.72, treatment 628, control 622, inverted to make HR<1 favor treatment, all patients. | |
| risk of no recovery, 16.0% lower, HR 0.84, p = 0.12, treatment 186, control 183, inverted to make HR<1 favor treatment, patients with mild symptoms on day 1. | |
| risk of no recovery, 2.9% lower, HR 0.97, p = 0.72, treatment 341, control 337, inverted to make HR<1 favor treatment, patients with moderate symptoms on day 1. | |
| risk of no recovery, 37.0% higher, HR 1.37, p = 0.56, treatment 10, control 13, inverted to make HR<1 favor treatment, patients with severe symptoms on day 1. | |
| risk of no recovery, 614.3% higher, HR 7.14, p < 0.001, treatment 186, control 183, inverted to make HR<1 favor treatment, patients with no symptoms on day 1. | |
| recovery time, 2.0% lower, relative time 0.98, p = 0.07, treatment 11.77 [11.58-11.97] n=628, control 12.01 [11.83-12.17] n=622. | |
| Soltani, 7/31/2022, Randomized Controlled Trial, Iran, peer-reviewed, mean age 56.8, 6 authors, study period April 2020 - May 2020. | hospitalization time, 20.0% lower, relative time 0.80, p = 0.01, treatment median 8.0 IQR 3.0 n=51, control median 10.0 IQR 7.0 n=76. |
| risk of no recovery, 25.0% lower, RR 0.75, p < 0.001, treatment mean 1.96 (±0.69) n=51, control mean 1.47 (±0.81) n=76, relative BCSS improvement, GPT/MTL vs. GPT. | |
| risk of no recovery, 20.6% lower, RR 0.79, p = 0.07, treatment mean 1.8 (±1.11) n=51, control mean 1.43 (±1.13) n=76, relative VAS improvement, GPT/MTL vs. GPT. | |
| Zengin, 8/5/2024, retrospective, Turkey, peer-reviewed, 9 authors, study period September 2021 - December 2022, excluded in exclusion analyses: unadjusted results with minimal group details. | risk of death, 14.3% lower, RR 0.86, p = 1.00, treatment 3 of 35 (8.6%), control 4 of 40 (10.0%), NNT 70. |
| risk of ICU admission, 90.5% higher, RR 1.90, p = 0.46, treatment 5 of 35 (14.3%), control 3 of 40 (7.5%). | |
| hospitalization time, 3.4% lower, relative time 0.97, p = 0.81, treatment mean 10.51 (±5.44) n=35, control mean 10.88 (±7.24) n=40. |
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
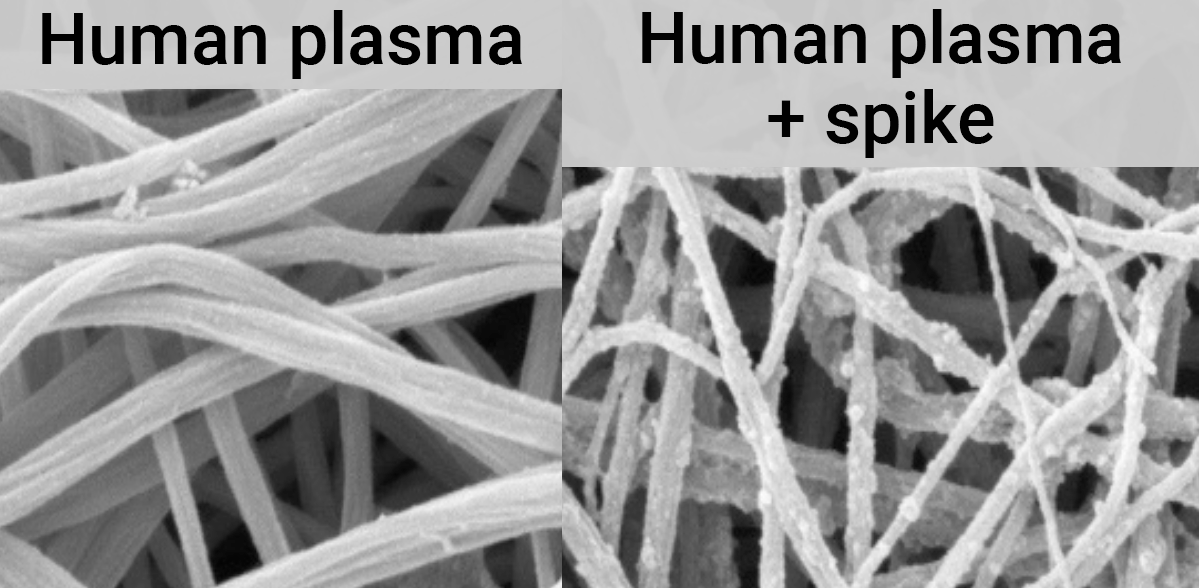
| Alhmoud, 9/23/2023, retrospective, Qatar, peer-reviewed, median age 44.0, 10 authors, study period 10 March, 2020 - 10 August, 2020. | risk of hospitalization, 13.0% lower, OR 0.87, p = 0.61, treatment 111, control 505, adjusted per study, multivariable, RR approximated with OR. |
| Bozek, 9/17/2020, retrospective, Germany, peer-reviewed, 2 authors, study period March 2020 - April 2020. | risk of hospitalization, 91.0% lower, RR 0.09, p = 0.02, treatment 1 of 327 (0.3%), control 4 of 118 (3.4%), NNT 32. |
| risk of case, 82.0% lower, RR 0.18, p = 0.004, treatment 4 of 327 (1.2%), control 8 of 118 (6.8%), NNT 18. |
Viral infection and replication involves attachment, entry, uncoating and release, genome replication and transcription, translation and protein processing, assembly and budding, and release. Each step can be disrupted by therapeutics.
The trimeric spike (S) protein is a glycoprotein that mediates viral entry by binding to the host ACE2 receptor, is critical for SARS-CoV-2's ability to infect host cells, and is a target of neutralizing antibodies. Inhibition of the spike protein prevents viral attachment, halting infection at the earliest stage.
The receptor binding domain is a specific region of the spike protein that binds ACE2 and is a major target of neutralizing antibodies. Focusing on the precise binding site allows highly specific disruption of viral attachment with reduced potential for off-target effects.
The main protease or Mpro, also known as 3CLpro or nsp5, is a cysteine protease that cleaves viral polyproteins into functional units needed for replication. Inhibiting Mpro disrupts the SARS-CoV-2 lifecycle within the host cell, preventing the creation of new copies.
RNA-dependent RNA polymerase (RdRp), also called nsp12, is the core enzyme of the viral replicase-transcriptase complex that copies the positive-sense viral RNA genome into negative-sense templates for progeny RNA synthesis. Inhibiting RdRp blocks viral genome replication and transcription.
The papain-like protease (PLpro) has multiple functions including cleaving viral polyproteins and suppressing the host immune response by deubiquitination and deISGylation of host proteins. Inhibiting PLpro may block viral replication and help restore normal immune responses.
The nucleocapsid (N) protein binds and encapsulates the viral genome by coating the viral RNA. N enables formation and release of infectious virions and plays additional roles in viral replication and pathogenesis. N is also an immunodominant antigen used in diagnostic assays.
The helicase, or nsp13, protein unwinds the double-stranded viral RNA, a crucial step in replication and transcription. Inhibition may prevent viral genome replication and the creation of new virus components.
Monoclonal antibodies were
previously included. Other treatments such as dexamethasone, tocilizumab, and baricitinib
were recommended for late stage hospitalized patients.
Smoking was
known to cause lung cancer since at least 1939, but this was not widely recognized in the
US until 1964, 25 years later. Surgeon general Leroy Burney tried publicizing the danger
starting in 1957, with limited success. Surgeon general Luther Terry, appointed in 1961,
prompted by President Kennedy in 1962 amid pressure from health advocates, finally got
recognition in 1964. The 1964 report reviewed 7,000+ studies, but these could (and should)
have been reviewed and acted upon in real-time as they were published.
Historians attribute the 25 year delay to an industry campaign to manufacture doubt and
controversy, through tactics like funding biased and fraudulent research from
"independent" organizations, attacking scientists, and political lobbying.
The success of the industry campaign is only possible because officials did not analyze
the research in detail. Fraudulent industry research supported prior failures, but would
have been called out as fraudulent by officials that analyzed and understood the research
in real-time.
When administered late in infection, HCQ may enhance viral egress by further increasing
lysosomal pH beyond the effect of ORF3a's water channel activity, thereby promoting
lysosomal exocytosis, inactivating degradative enzymes, and facilitating the release of
SARS-CoV-2 particles into the extracellular environment168,169.
Research also suggests potential cardioprotective effects at lower doses, but
cardiotoxicity with excessive dosage170. Bobrowski et al. also
indicate negative effects if HCQ and remdesivir are combined.
Peters (B) et al. is subject to confounding by calendar-time (SOC evolved rapidly early in
the pandemic, the linear covariate does not reflect non-linear SOC changes and hospital
specific effects), hospital type (non-treatment hospitals were tertiary university
centers), confounding by indication (4/7 hospitals initiated treatment on deterioration),
immortal-time bias for as-treated (exposure assigned after baseline), significant
differences for other experimental treatments, potential overadjustment from collider bias
(steroid use and indication bias), limited baseline severity information, differences in
hospice referral propensity across hospitals, unadjusted difference in time from onset to
admission, difference in PCR positivity, and other factors.
Mahévas et al. is subject to confounding by hospital (treatment highly dependent on
the hospital, different SOC/ICU transfer practices, not included in PS), immortal time
(only partly addressed in sensitivity analysis), co-treatment differences, calendar-time
(SOC evolved rapidly early in the pandemic), binary coding for age (age ≥65 despite steep
age-risk gradient), residual imbalance (variables dropped from PS), a composite outcome
dependent on hospital triage/capacity, and other factors.
Cordero et al., Double-blind Randomized Clinical Trial, Placebo-controlled to Assess the Efficacy of Montelukast in Mild-moderate Respiratory Symptoms in Patients With Long-COVID-19: E-SPERANZA COVID-19 PROJECT, NCT04695704, clinicaltrials.gov/study/NCT04695704.
Durdagi et al., A National, Multi-Center, Open-Label, Three-Arm, Phase II Study to Investigate the Effect of Montelukast Between Emergency Room Visits and Hospitalizations in COVID-19 Pneumonia in Comparison With Standard Treatment, NCT04718285, clinicaltrials.gov/study/NCT04718285.
fda.gov, www.fda.gov/drugs/drug-safety-and-availability/fda-requires-boxed-warning-about-serious-mental-health-side-effects-asthma-and-allergy-drug.
Ryu et al., Fibrin drives thromboinflammation and neuropathology in COVID-19, Nature, doi:10.1038/s41586-024-07873-4.
Rong et al., Persistence of spike protein at the skull-meninges-brain axis may contribute to the neurological sequelae of COVID-19, Cell Host & Microbe, doi:10.1016/j.chom.2024.11.007.
Yang et al., SARS-CoV-2 infection causes dopaminergic neuron senescence, Cell Stem Cell, doi:10.1016/j.stem.2023.12.012.
Scardua-Silva et al., Microstructural brain abnormalities, fatigue, and cognitive dysfunction after mild COVID-19, Scientific Reports, doi:10.1038/s41598-024-52005-7.
Hampshire et al., Cognition and Memory after Covid-19 in a Large Community Sample, New England Journal of Medicine, doi:10.1056/NEJMoa2311330.
Duloquin et al., Is COVID-19 Infection a Multiorganic Disease? Focus on Extrapulmonary Involvement of SARS-CoV-2, Journal of Clinical Medicine, doi:10.3390/jcm13051397.
Sodagar et al., Pathological Features and Neuroinflammatory Mechanisms of SARS-CoV-2 in the Brain and Potential Therapeutic Approaches, Biomolecules, doi:10.3390/biom12070971.
Sagar et al., COVID-19-associated cerebral microbleeds in the general population, Brain Communications, doi:10.1093/braincomms/fcae127.
Verma et al., Persistent Neurological Deficits in Mouse PASC Reveal Antiviral Drug Limitations, bioRxiv, doi:10.1101/2024.06.02.596989.
Panagea et al., Neurocognitive Impairment in Long COVID: A Systematic Review, Archives of Clinical Neuropsychology, doi:10.1093/arclin/acae042.
Ariza et al., COVID-19: Unveiling the Neuropsychiatric Maze—From Acute to Long-Term Manifestations, Biomedicines, doi:10.3390/biomedicines12061147.
Vashisht et al., Neurological Complications of COVID-19: Unraveling the Pathophysiological Underpinnings and Therapeutic Implications, Viruses, doi:10.3390/v16081183.
Ahmad et al., Neurological Complications and Outcomes in Critically Ill Patients With COVID-19: Results From International Neurological Study Group From the COVID-19 Critical Care Consortium, The Neurohospitalist, doi:10.1177/19418744241292487.
Wang et al., SARS-CoV-2 membrane protein induces neurodegeneration via affecting Golgi-mitochondria interaction, Translational Neurodegeneration, doi:10.1186/s40035-024-00458-1.
Freitas et al., Central nervous system and systemic inflammatory networks associated with acute neurological outcomes in COVID-19, Scientific Reports, doi:10.1038/s41598-025-08632-9.
Lu et al., Risk of neuropsychiatric and related conditions associated with SARS-CoV-2 infection: a difference-in-differences analysis, Nature Communications, doi:10.1038/s41467-025-61961-1.
Jachman-Kapułka et al., Cross-Section of Neurological Manifestations Among SARS-CoV-2 Omicron Subvariants—Single-Center Study, Brain Sciences, doi:10.3390/brainsci14111161.
Beckman et al., SARS-CoV-2 infects neurons and induces neuroinflammation in a non-human primate model of COVID-19, Cell Reports, doi:10.1016/j.celrep.2022.111573.
Eberhardt et al., SARS-CoV-2 infection triggers pro-atherogenic inflammatory responses in human coronary vessels, Nature Cardiovascular Research, doi:10.1038/s44161-023-00336-5.
Van Tin et al., Spike Protein of SARS-CoV-2 Activates Cardiac Fibrogenesis through NLRP3 Inflammasomes and NF-κB Signaling, Cells, doi:10.3390/cells13161331.
Borka Balas et al., COVID-19 and Cardiac Implications—Still a Mystery in Clinical Practice, Reviews in Cardiovascular Medicine, doi:10.31083/j.rcm2405125.
AlTaweel et al., An In-Depth Insight into Clinical, Cellular and Molecular Factors in COVID19-Associated Cardiovascular Ailments for Identifying Novel Disease Biomarkers, Drug Targets and Clinical Management Strategies, Archives of Microbiology & Immunology, doi:10.26502/ami.936500177.
Saha et al., COVID-19 beyond the lungs: Unraveling its vascular impact and cardiovascular complications—mechanisms and therapeutic implications, Science Progress, doi:10.1177/00368504251322069.
Yin et al., COVID-19: a vascular nightmare unfolding, Frontiers in Immunology, doi:10.3389/fimmu.2025.1593885.
Bruno et al., Accelerated vascular ageing after COVID-19 infection: the CARTESIAN study, European Heart Journal, doi:10.1093/eurheartj/ehaf430.
Abiri et al., The silent legacy of COVID-19: exploring genomic instability in long-term COVID-19 survivors, BMC Infectious Diseases, doi:10.1186/s12879-025-11419-y.
Gioia et al., SARS-CoV-2 infection induces DNA damage, through CHK1 degradation and impaired 53BP1 recruitment, and cellular senescence, Nature Cell Biology, doi:10.1038/s41556-023-01096-x.
Doğan et al., Clinical Investigation of Leukocyte DNA Damage in COVID-19 Patients, Current Issues in Molecular Biology, doi:10.3390/cimb45020062.
Rueda-Torres et al., Longitudinal Assessment of DNA Damage in PBMCs From Hospitalized COVID‐19 Patients via Alkaline Comet Assay, Environmental and Molecular Mutagenesis, doi:10.1002/em.70055.
Trender et al., Changes in memory and cognition during the SARS-CoV-2 human challenge study, eClinicalMedicine, doi:10.1016/j.eclinm.2024.102842.
Dugied et al., Multimodal SARS-CoV-2 interactome sketches the virus-host spatial organization, Communications Biology, doi:10.1038/s42003-025-07933-z.
Malone et al., Structures and functions of coronavirus replication–transcription complexes and their relevance for SARS-CoV-2 drug design, Nature Reviews Molecular Cell Biology, doi:10.1038/s41580-021-00432-z.
Murigneux et al., Proteomic analysis of SARS-CoV-2 particles unveils a key role of G3BP proteins in viral assembly, Nature Communications, doi:10.1038/s41467-024-44958-0.
Lv et al., Host proviral and antiviral factors for SARS-CoV-2, Virus Genes, doi:10.1007/s11262-021-01869-2.
Lui et al., Nsp1 facilitates SARS-CoV-2 replication through calcineurin-NFAT signaling, Virology, doi:10.1128/mbio.00392-24.
Niarakis et al., Drug-target identification in COVID-19 disease mechanisms using computational systems biology approaches, Frontiers in Immunology, doi:10.3389/fimmu.2023.1282859.
Katiyar et al., SARS-CoV-2 Assembly: Gaining Infectivity and Beyond, Viruses, doi:10.3390/v16111648.
Wu et al., Decoding the genome of SARS-CoV-2: a pathway to drug development through translation inhibition, RNA Biology, doi:10.1080/15476286.2024.2433830.
Haque et al., Exploring potential therapeutic candidates against COVID-19: a molecular docking study, Discover Molecules, doi:10.1007/s44345-024-00005-5.
Mulgaonkar et al., Montelukast and Telmisartan as Inhibitors of SARS-CoV-2 Omicron Variant, Pharmaceutics, doi:10.3390/pharmaceutics15071891.
Hamdan et al., In silico Evaluation of H1-Antihistamine as Potential Inhibitors of SARS-CoV-2 RNA-dependent RNA Polymerase: Repurposing Study of COVID-19 Therapy, Turkish Journal of Pharmaceutical Sciences, doi:10.4274/tjps.galenos.2024.49768.
Camera et al., Montelukast Inhibits Platelet Activation Induced by Plasma From COVID-19 Patients, Frontiers in Pharmacology, doi:10.3389/fphar.2022.784214.
web.archive.org, web.archive.org/web/20211117052139/https://astralcodexten.substack.com/p/ivermectin-much-more-than-you-wanted.
Hayward et al., Ivermectin for COVID-19 in adults in the community (PRINCIPLE): an open, randomised, controlled, adaptive platform trial of short- and longer-term outcomes, Journal of Infection, doi:10.1016/j.jinf.2024.106130.
Jadad et al., Randomized Controlled Trials: Questions, Answers, and Musings, Second Edition, doi:10.1002/9780470691922.
Gøtzsche, P., Bias in double-blind trials, Doctoral Thesis, University of Copenhagen, www.scientificfreedom.dk/2023/05/16/bias-in-double-blind-trials-doctoral-thesis/.
Als-Nielsen et al., Association of Funding and Conclusions in Randomized Drug Trials, JAMA, doi:10.1001/jama.290.7.921.
Bekelman et al., Scope and Impact of Financial Conflicts of Interest in Biomedical Research, JAMA, doi:10.1001/jama.289.4.454.
Lundh et al., Industry sponsorship and research outcome, Cochrane Database of Systematic Reviews, doi:10.1002/14651858.MR000033.pub3.
Concato et al., Randomized, Controlled Trials, Observational Studies, and the Hierarchy of Research Designs, New England Journal of Medicine, doi:10.1056/NEJM200006223422507.
Anglemyer et al., Healthcare outcomes assessed with observational study designs compared with those assessed in randomized trials, Cochrane Database of Systematic Reviews, doi:10.1002/14651858.MR000034.pub2.
Lee et al., Analysis of Overall Level of Evidence Behind Infectious Diseases Society of America Practice Guidelines, Arch Intern Med., 2011, 171:1, 18-22, doi:10.1001/archinternmed.2010.482.
Deaton et al., Understanding and misunderstanding randomized controlled trials, Social Science & Medicine, 210, doi:10.1016/j.socscimed.2017.12.005.
Nichol et al., Challenging issues in randomised controlled trials, Injury, 2010, doi: 10.1016/j.injury.2010.03.033, www.injuryjournal.com/article/S0020-1383(10)00233-0/fulltext.
Zengin et al., The Effect of Montelukast Treatment on Elderly Patients Diagnosed with COVID-19, Genel Tıp Dergisi, doi:10.54005/geneltip.1352153.
Meschede et al., Cross-metric compatability and inconsistencies of altmetrics, Scientometrics, doi:10.1007/s11192-018-2674-1.
Ortega, J., Reliability and accuracy of altmetric providers: a comparison among Altmetric.com, PlumX and Crossref Event Data, Scientometrics, doi:10.1007/s11192-018-2838-z.
Treanor et al., Efficacy and Safety of the Oral Neuraminidase Inhibitor Oseltamivir in Treating Acute Influenza: A Randomized Controlled Trial, JAMA, 2000, 283:8, 1016-1024, doi:10.1001/jama.283.8.1016.
McLean et al., Impact of Late Oseltamivir Treatment on Influenza Symptoms in the Outpatient Setting: Results of a Randomized Trial, Open Forum Infect. Dis. September 2015, 2:3, doi:10.1093/ofid/ofv100.
Ikematsu et al., Baloxavir Marboxil for Prophylaxis against Influenza in Household Contacts, New England Journal of Medicine, doi:10.1056/NEJMoa1915341.
Hayden et al., Baloxavir Marboxil for Uncomplicated Influenza in Adults and Adolescents, New England Journal of Medicine, doi:10.1056/NEJMoa1716197.
Kumar et al., Combining baloxavir marboxil with standard-of-care neuraminidase inhibitor in patients hospitalised with severe influenza (FLAGSTONE): a randomised, parallel-group, double-blind, placebo-controlled, superiority trial, The Lancet Infectious Diseases, doi:10.1016/S1473-3099(21)00469-2.
López-Medina et al., Effect of Ivermectin on Time to Resolution of Symptoms Among Adults With Mild COVID-19: A Randomized Clinical Trial, JAMA, doi:10.1001/jama.2021.3071.
Korves et al., SARS-CoV-2 Genetic Variants and Patient Factors Associated with Hospitalization Risk, medRxiv, doi:10.1101/2024.03.08.24303818.
Faria et al., Genomics and epidemiology of the P.1 SARS-CoV-2 lineage in Manaus, Brazil, Science, doi:10.1126/science.abh2644.
Nonaka et al., SARS-CoV-2 variant of concern P.1 (Gamma) infection in young and middle-aged patients admitted to the intensive care units of a single hospital in Salvador, Northeast Brazil, February 2021, International Journal of Infectious Diseases, doi:10.1016/j.ijid.2021.08.003.
Karita et al., Trajectory of viral load in a prospective population-based cohort with incident SARS-CoV-2 G614 infection, medRxiv, doi:10.1101/2021.08.27.21262754.
Zavascki et al., Advanced ventilatory support and mortality in hospitalized patients with COVID-19 caused by Gamma (P.1) variant of concern compared to other lineages: cohort study at a reference center in Brazil, Research Square, doi:10.21203/rs.3.rs-910467/v1.
Willett et al., The hyper-transmissible SARS-CoV-2 Omicron variant exhibits significant antigenic change, vaccine escape and a switch in cell entry mechanism, medRxiv, doi:10.1101/2022.01.03.21268111.
Peacock et al., The SARS-CoV-2 variant, Omicron, shows rapid replication in human primary nasal epithelial cultures and efficiently uses the endosomal route of entry, bioRxiv, doi:10.1101/2021.12.31.474653.
Williams, T., Not All Ivermectin Is Created Equal: Comparing The Quality of 11 Different Ivermectin Sources, Do Your Own Research, doyourownresearch.substack.com/p/not-all-ivermectin-is-created-equal.
Xu et al., A study of impurities in the repurposed COVID-19 drug hydroxychloroquine sulfate by UHPLC-Q/TOF-MS and LC-SPE-NMR, Rapid Communications in Mass Spectrometry, doi:10.1002/rcm.9358.
Jitobaom et al., Favipiravir and Ivermectin Showed in Vitro Synergistic Antiviral Activity against SARS-CoV-2, Research Square, doi:10.21203/rs.3.rs-941811/v1.
Jitobaom (B) et al., Synergistic anti-SARS-CoV-2 activity of repurposed anti-parasitic drug combinations, BMC Pharmacology and Toxicology, doi:10.1186/s40360-022-00580-8.
Jeffreys et al., Remdesivir-ivermectin combination displays synergistic interaction with improved in vitro activity against SARS-CoV-2, International Journal of Antimicrobial Agents, doi:10.1016/j.ijantimicag.2022.106542.
Ostrov et al., Highly Specific Sigma Receptor Ligands Exhibit Anti-Viral Properties in SARS-CoV-2 Infected Cells, Pathogens, doi:10.3390/pathogens10111514.
Alsaidi et al., Griffithsin and Carrageenan Combination Results in Antiviral Synergy against SARS-CoV-1 and 2 in a Pseudoviral Model, Marine Drugs, doi:10.3390/md19080418.
Andreani et al., In vitro testing of combined hydroxychloroquine and azithromycin on SARS-CoV-2 shows synergistic effect, Microbial Pathogenesis, doi:10.1016/j.micpath.2020.104228.
De Forni et al., Synergistic drug combinations designed to fully suppress SARS-CoV-2 in the lung of COVID-19 patients, PLoS ONE, doi:10.1371/journal.pone.0276751.
Wan et al., Synergistic inhibition effects of andrographolide and baicalin on coronavirus mechanisms by downregulation of ACE2 protein level, Scientific Reports, doi:10.1038/s41598-024-54722-5.
Said et al., The effect of Nigella sativa and vitamin D3 supplementation on the clinical outcome in COVID-19 patients: A randomized controlled clinical trial, Frontiers in Pharmacology, doi:10.3389/fphar.2022.1011522.
Fiaschi et al., In Vitro Combinatorial Activity of Direct Acting Antivirals and Monoclonal Antibodies against the Ancestral B.1 and BQ.1.1 SARS-CoV-2 Viral Variants, Viruses, doi:10.3390/v16020168.
Xing et al., Published anti-SARS-CoV-2 in vitro hits share common mechanisms of action that synergize with antivirals, Briefings in Bioinformatics, doi:10.1093/bib/bbab249.
Chen et al., Synergistic Inhibition of SARS-CoV-2 Replication Using Disulfiram/Ebselen and Remdesivir, ACS Pharmacology & Translational Science, doi:10.1021/acsptsci.1c00022.
Hempel et al., Synergistic inhibition of SARS-CoV-2 cell entry by otamixaban and covalent protease inhibitors: pre-clinical assessment of pharmacological and molecular properties, Chemical Science, doi:10.1039/D1SC01494C.
Schultz et al., Pyrimidine inhibitors synergize with nucleoside analogues to block SARS-CoV-2, Nature, doi:10.1038/s41586-022-04482-x.
Ohashi et al., Potential anti-COVID-19 agents, cepharanthine and nelfinavir, and their usage for combination treatment, iScience, doi:10.1016/j.isci.2021.102367.
Al Krad et al., The protease inhibitor Nirmatrelvir synergizes with inhibitors of GRP78 to suppress SARS-CoV-2 replication, bioRxiv, doi:10.1101/2025.03.09.642200.
Abd Elsalam et al., Anti-COVID-19 activity and simple HPLC method for concurrent detection of repurposed drugs in novel binary mixtures, AMB Express, doi:10.1186/s13568-026-02030-8.
Rana et al., Ivermectin and Doxycycline combination as a promising anti-viral drug candidate: an in-silico and DFT study, In Silico Pharmacology, doi:10.1007/s40203-026-00576-w.
Setz et al., Synergistic Virus Neutralizing Activities of European Black Elderberry Fruit Extract and Iota-Carrageenan Against SARS-CoV-2, Influenza A Virus and Respiratory Syncytial Virus, Nutrients, doi:10.3390/nu18081205.
Ali et al., Preclinical Screening Platform Identifies Azatadine‐Dimaleate as a Potent Repurposed Therapeutic Against SARS‐CoV‐2 Infection, Journal of Medical Virology, doi:10.1002/jmv.70713.
Lew et al., Combination of Remdesivir and Ivermectin Exerts Highly Potent and Synergistic Antiviral Activity Against Murine Coronavirus and SARS-CoV-2 Infections, Cells, doi:10.3390/cells15131146.
Khatun et al., An All-Oral Antiviral Combination Strategy against COVID-19 Enabled by the Synergistic Mechanism of Action of Auranofin and Remdesivir, Elsevier BV, doi:10.2139/ssrn.6942990.
How et al., The Combination of Nirmatrelvir and Ivermectin Exerts Strongly Synergistic Antiviral and Anti-Inflammatory Effects Against Murine Coronavirus Infection of Macrophages, International Journal of Molecular Sciences, doi:10.3390/ijms27167316.
Tan et al., Combination Treatment With Remdesivir and Ivermectin Exerts Highly Synergistic and Potent Antiviral Activity Against Murine Coronavirus Infection, Frontiers in Cellular and Infection Microbiology, doi:10.3389/fcimb.2021.700502.
Thairu et al., A Comparison of Ivermectin and Non Ivermectin Based Regimen for COVID-19 in Abuja: Effects on Virus Clearance, Days-to-discharge and Mortality, Journal of Pharmaceutical Research International, doi:10.9734/jpri/2022/v34i44A36328.
Singh et al., The relationship between viral clearance rates and disease progression in early symptomatic COVID-19: a systematic review and meta-regression analysis, Journal of Antimicrobial Chemotherapy, doi:10.1093/jac/dkae045.
Boulware, D., Comments regarding paper rejection, twitter.com/boulware_dr/status/1311331372884205570.
Rothstein, H., Publication Bias in Meta-Analysis: Prevention, Assessment and Adjustments, www.wiley.com/en-ae/Publication+Bias+in+Meta+Analysis:+Prevention,+Assessment+and+Adjustments-p-9780470870143.
Stanley et al., Meta-regression approximations to reduce publication selection bias, Research Synthesis Methods, doi:10.1002/jrsm.1095.
Rücker et al., Arcsine test for publication bias in meta-analyses with binary outcomes, Statistics in Medicine, doi:10.1002/sim.2971.
Peters, J., Comparison of Two Methods to Detect Publication Bias in Meta-analysis, JAMA, doi:10.1001/jama.295.6.676.
Moreno et al., Assessment of regression-based methods to adjust for publication bias through a comprehensive simulation study, BMC Medical Research Methodology, doi:10.1186/1471-2288-9-2.
Macaskill et al., A comparison of methods to detect publication bias in meta-analysis, Statistics in Medicine, doi:10.1002/sim.698.
Egger et al., Bias in meta-analysis detected by a simple, graphical test, BMJ, doi:10.1136/bmj.315.7109.629.
Harbord et al., A modified test for small-study effects in meta-analyses of controlled trials with binary endpoints, Statistics in Medicine, doi:10.1002/sim.2380.
McCarthy, M., Montelukast as a potential treatment for COVID-19, Expert Opinion on Pharmacotherapy, doi:10.1080/14656566.2023.2192866.
Barré et al., Montelukast Drug May Improve COVID-19 Prognosis: A Review of Evidence, Frontiers in Pharmacology, doi:10.3389/fphar.2020.01344.
Rothman et al., Time to Sustained Recovery Among Outpatients With COVID-19 Receiving Montelukast vs Placebo, JAMA Network Open, doi:10.1001/jamanetworkopen.2024.39332.
Mohamed Hussein et al., Value of montelukast as a potential treatment of post-COVID-19 persistent cough: a non-randomized controlled pilot study, The Egyptian Journal of Bronchology, doi:10.1186/s43168-022-00154-6.
Soltani et al., The effectiveness of gabapentin and gabapentin/montelukast combination compared with dextromethorphan in the improvement of COVID‐19‐ related cough: A randomized, controlled clinical trial, The Clinical Respiratory Journal, doi:10.1111/crj.13529.
Kerget et al., Effect of montelukast therapy on clinical course, pulmonary function, and mortality in patients with COVID‐19, Journal of Medical Virology, doi:10.1002/jmv.27552.
Kumar (B) et al., Efficacy of montelukast in the management of COVID-19: double blind randomized placebo controlled trial, International Journal of Basic & Clinical Pharmacology, doi:10.18203/2319-2003.ijbcp20214502.
Khan et al., Montelukast in hospitalized patients diagnosed with COVID-19, Journal of Asthma, doi:10.1080/02770903.2021.1881967.
Lima-Morales et al., Effectiveness of a multidrug therapy consisting of ivermectin, azithromycin, montelukast and acetylsalicylic acid to prevent hospitalization and death among ambulatory COVID-19 cases in Tlaxcala, Mexico, International Journal of Infectious Diseases, doi:10.1016/j.ijid.2021.02.014.
Alhmoud et al., Characteristics and outcomes of adult patients with asthma presenting with COVID-19: A comparative cohort study, Qatar Medical Journal, doi:10.5339/qmj.2023.15.
Bozek et al., Montelukast’s ability to fight COVID-19 infection, Journal of Asthma, doi:10.1080/02770903.2020.1786112.
Luedemann et al., Montelukast is a dual-purpose inhibitor of SARS-CoV-2 infection and virus-induced IL-6 expression identified by structure-based drug repurposing, Computational and Structural Biotechnology Journal, doi:10.1016/j.csbj.2022.01.024.
Salehi-Pourmehr et al., Effect of Montelukast on Treatment of Coronavirus Pneumonia (COVID-19): A Systematic Review, Biomedical Research Bulletin, doi:10.34172/biomedrb.2023.06.
Porta et al., Targeting SARS-CoV-2 Non-Structural Proteins: A Blueprint for Next-Generation Small-Molecule Coronavirus Antivirals, Pharmaceutics, doi:10.3390/pharmaceutics18060693.
Akinbolade et al., Repurposed Medicines for Viruses With Epidemic or Pandemic Potential: A Horizon Scan, Pharmacology Research & Perspectives, doi:10.1002/prp2.70271.
Yang (B) et al., Lipid metabolism, viral infection, and antiviral immunity: a new host-pathogen interface, Frontiers in Cellular and Infection Microbiology, doi:10.3389/fcimb.2026.1765502.
Castro et al., Stalling the Enemy: Targeting Nsp13 for Next-Generation SARS-CoV-2 Antivirals, International Journal of Molecular Sciences, doi:10.3390/ijms27062587.
Ricke, D., Mast cells and histamine receptor-targeted adjunctive treatments for COVID-19: A literature review, Innovative Medicines & Omics, doi:10.36922/IMO025440058.
Akinbolade (B) et al., Repurposed antiviral medicines for potential pandemic viruses: A horizon scan, medRxiv, doi:10.1101/2025.09.09.25335403.
Kumar (C) et al., Advancements in the development of antivirals against SARS-Coronavirus, Frontiers in Cellular and Infection Microbiology, doi:10.3389/fcimb.2025.1520811.
Abdollahpour et al., An in silico Drug Repurposing Study to Inhibit the Spike Protein of SARS-CoV2, Momona Ethiopian Journal of Science, doi:10.4314/mejs.v16i2.11.
Ridha Al Fiqri et al., Basic Structure of the Pharmacophore Virtual Screening Protein 7kg7 for Candidate Therapeutic Options COVID-19, Indonesian Journal of Medical Chemistry and Bioinformatics, doi:10.7454/ijmcb.v2i2.1004.
Loucera et al., Drug repurposing for COVID-19 using machine learning and mechanistic models of signal transduction circuits related to SARS-CoV-2 infection, Signal Transduction and Targeted Therapy, doi:10.1038/s41392-020-00417-y.
Masoudi-Sobhanzadeh et al., Structure-based drug repurposing against COVID-19 and emerging infectious diseases: methods, resources and discoveries, Briefings in Bioinformatics, doi:10.1093/bib/bbab113.
Malar et al., Network analysis-guided drug repurposing strategies targeting LPAR receptor in the interplay of COVID, Alzheimer’s, and diabetes, Scientific Reports, doi:10.1038/s41598-024-55013-9.
Maffucci et al., In Silico Drug Repurposing for SARS-CoV-2 Main Proteinase and Spike Proteins, Journal of Proteome Research, doi:10.1021/acs.jproteome.0c00383.
Wu (B) et al., Analysis of therapeutic targets for SARS-CoV-2 and discovery of potential drugs by computational methods, Acta Pharmaceutica Sinica B, doi:10.1016/j.apsb.2020.02.008.
Gysi et al., Network Medicine Framework for Identifying Drug Repurposing Opportunities for COVID-19, arXiv, doi:10.48550/arXiv.2004.07229.
Mittal et al., Identification of potential molecules against COVID-19 main protease through structure-guided virtual screening approach, Journal of Biomolecular Structure and Dynamics, doi:10.1080/07391102.2020.1768151.
Tam et al., Targeting SARS-CoV-2 Non-Structural Proteins, International Journal of Molecular Sciences, doi:10.3390/ijms241613002.
Chen (B) et al., Metabolic alterations upon SARS-CoV-2 infection and potential therapeutic targets against coronavirus infection, Signal Transduction and Targeted Therapy, doi:10.1038/s41392-023-01510-8.
Mehyar, N., Coronaviruses SARS-CoV, MERS-CoV, and SARS-CoV-2 helicase inhibitors: A systematic review of in vitro studies, Journal of Virus Eradication, doi:10.1016/j.jve.2023.100327.
Oliver et al., Different drug approaches to COVID-19 treatment worldwide: an update of new drugs and drugs repositioning to fight against the novel coronavirus, Therapeutic Advances in Vaccines and Immunotherapy, doi:10.1177/25151355221144845.
Lindsell et al., ACTIV-6: Operationalizing a decentralized, outpatient randomized platform trial to evaluate efficacy of repurposed medicines for COVID-19, Journal of Clinical and Translational Science, doi:10.1017/cts.2023.644.
Wohl et al., Engaging communities in therapeutics clinical research during pandemics: Experiences and lessons from the ACTIV COVID-19 therapeutics research initiative, Journal of Clinical and Translational Science, doi:10.1017/cts.2024.561.
Lindsell (B) et al., The statistical design and analysis of pandemic platform trials: Implications for the future, Journal of Clinical and Translational Science, doi:10.1017/cts.2024.514.
Mateja et al., The choice of viral load endpoint in early phase trials of COVID-19 treatments aiming to reduce 28-day hospitalization and/or death, The Journal of Infectious Diseases, doi:10.1093/infdis/jiaf282.
Zhang et al., What's the relative risk? A method of correcting the odds ratio in cohort studies of common outcomes, JAMA, 80:19, 1690, doi:10.1001/jama.280.19.1690.
Altman (B) et al., How to obtain the confidence interval from a P value, BMJ, doi:10.1136/bmj.d2090.
Sweeting et al., What to add to nothing? Use and avoidance of continuity corrections in meta-analysis of sparse data, Statistics in Medicine, doi:10.1002/sim.1761.
Altman (C) et al., Interaction revisited: the difference between two estimates, BMJ, doi:10.1136/bmj.326.7382.219.
Michelucci et al., SARS-CoV-2 ORF3a accessory protein is a water-permeable channel that induces lysosome swelling, Communications Biology, doi:10.1038/s42003-024-07442-5.
Ghosh et al., β-Coronaviruses Use Lysosomes for Egress Instead of the Biosynthetic Secretory Pathway, Cell, doi:10.1016/j.cell.2020.10.039.
Kamga Kapchoup et al., In vitro effect of hydroxychloroquine on pluripotent stem cells and their cardiomyocytes derivatives, Frontiers in Pharmacology, doi:10.3389/fphar.2023.1128382.
Bobrowski et al., Synergistic and Antagonistic Drug Combinations against SARS-CoV-2, Molecular Therapy, doi:10.1016/j.ymthe.2020.12.016.
Peters (B) et al., Outcomes of Persons With COVID-19 in Hospitals With and Without Standard Treatment With (Hydroxy)chloroquine, Clinical Microbiology and Infection, doi:10.1016/j.cmi.2020.10.004.
Mahévas et al., Clinical efficacy of hydroxychloroquine in patients with covid-19 pneumonia who require oxygen: observational comparative study using routine care data, BMJ 2020, doi:10.1136/bmj.m1844.
Minozzi et al., The revised Cochrane risk of bias tool for randomized trials (RoB 2) showed low interrater reliability and challenges in its application, Journal of Clinical Epidemiology, doi:10.1016/j.jclinepi.2020.06.015.
Popp et al., Ivermectin for preventing and treating COVID-19, Cochrane Database of Systematic Reviews, doi:10.1002/14651858.CD015017.pub3.
Reis et al., Effect of Early Treatment with Ivermectin among Patients with Covid-19, New England Journal of Medicine, doi:10.1056/NEJMoa2115869.
Axfors et al., Mortality outcomes with hydroxychloroquine and chloroquine in COVID-19 from an international collaborative meta-analysis of randomized trials, Nature, doi:10.1038/s41467-021-22446-z.