Media coverage of nitric oxide for COVID‑19
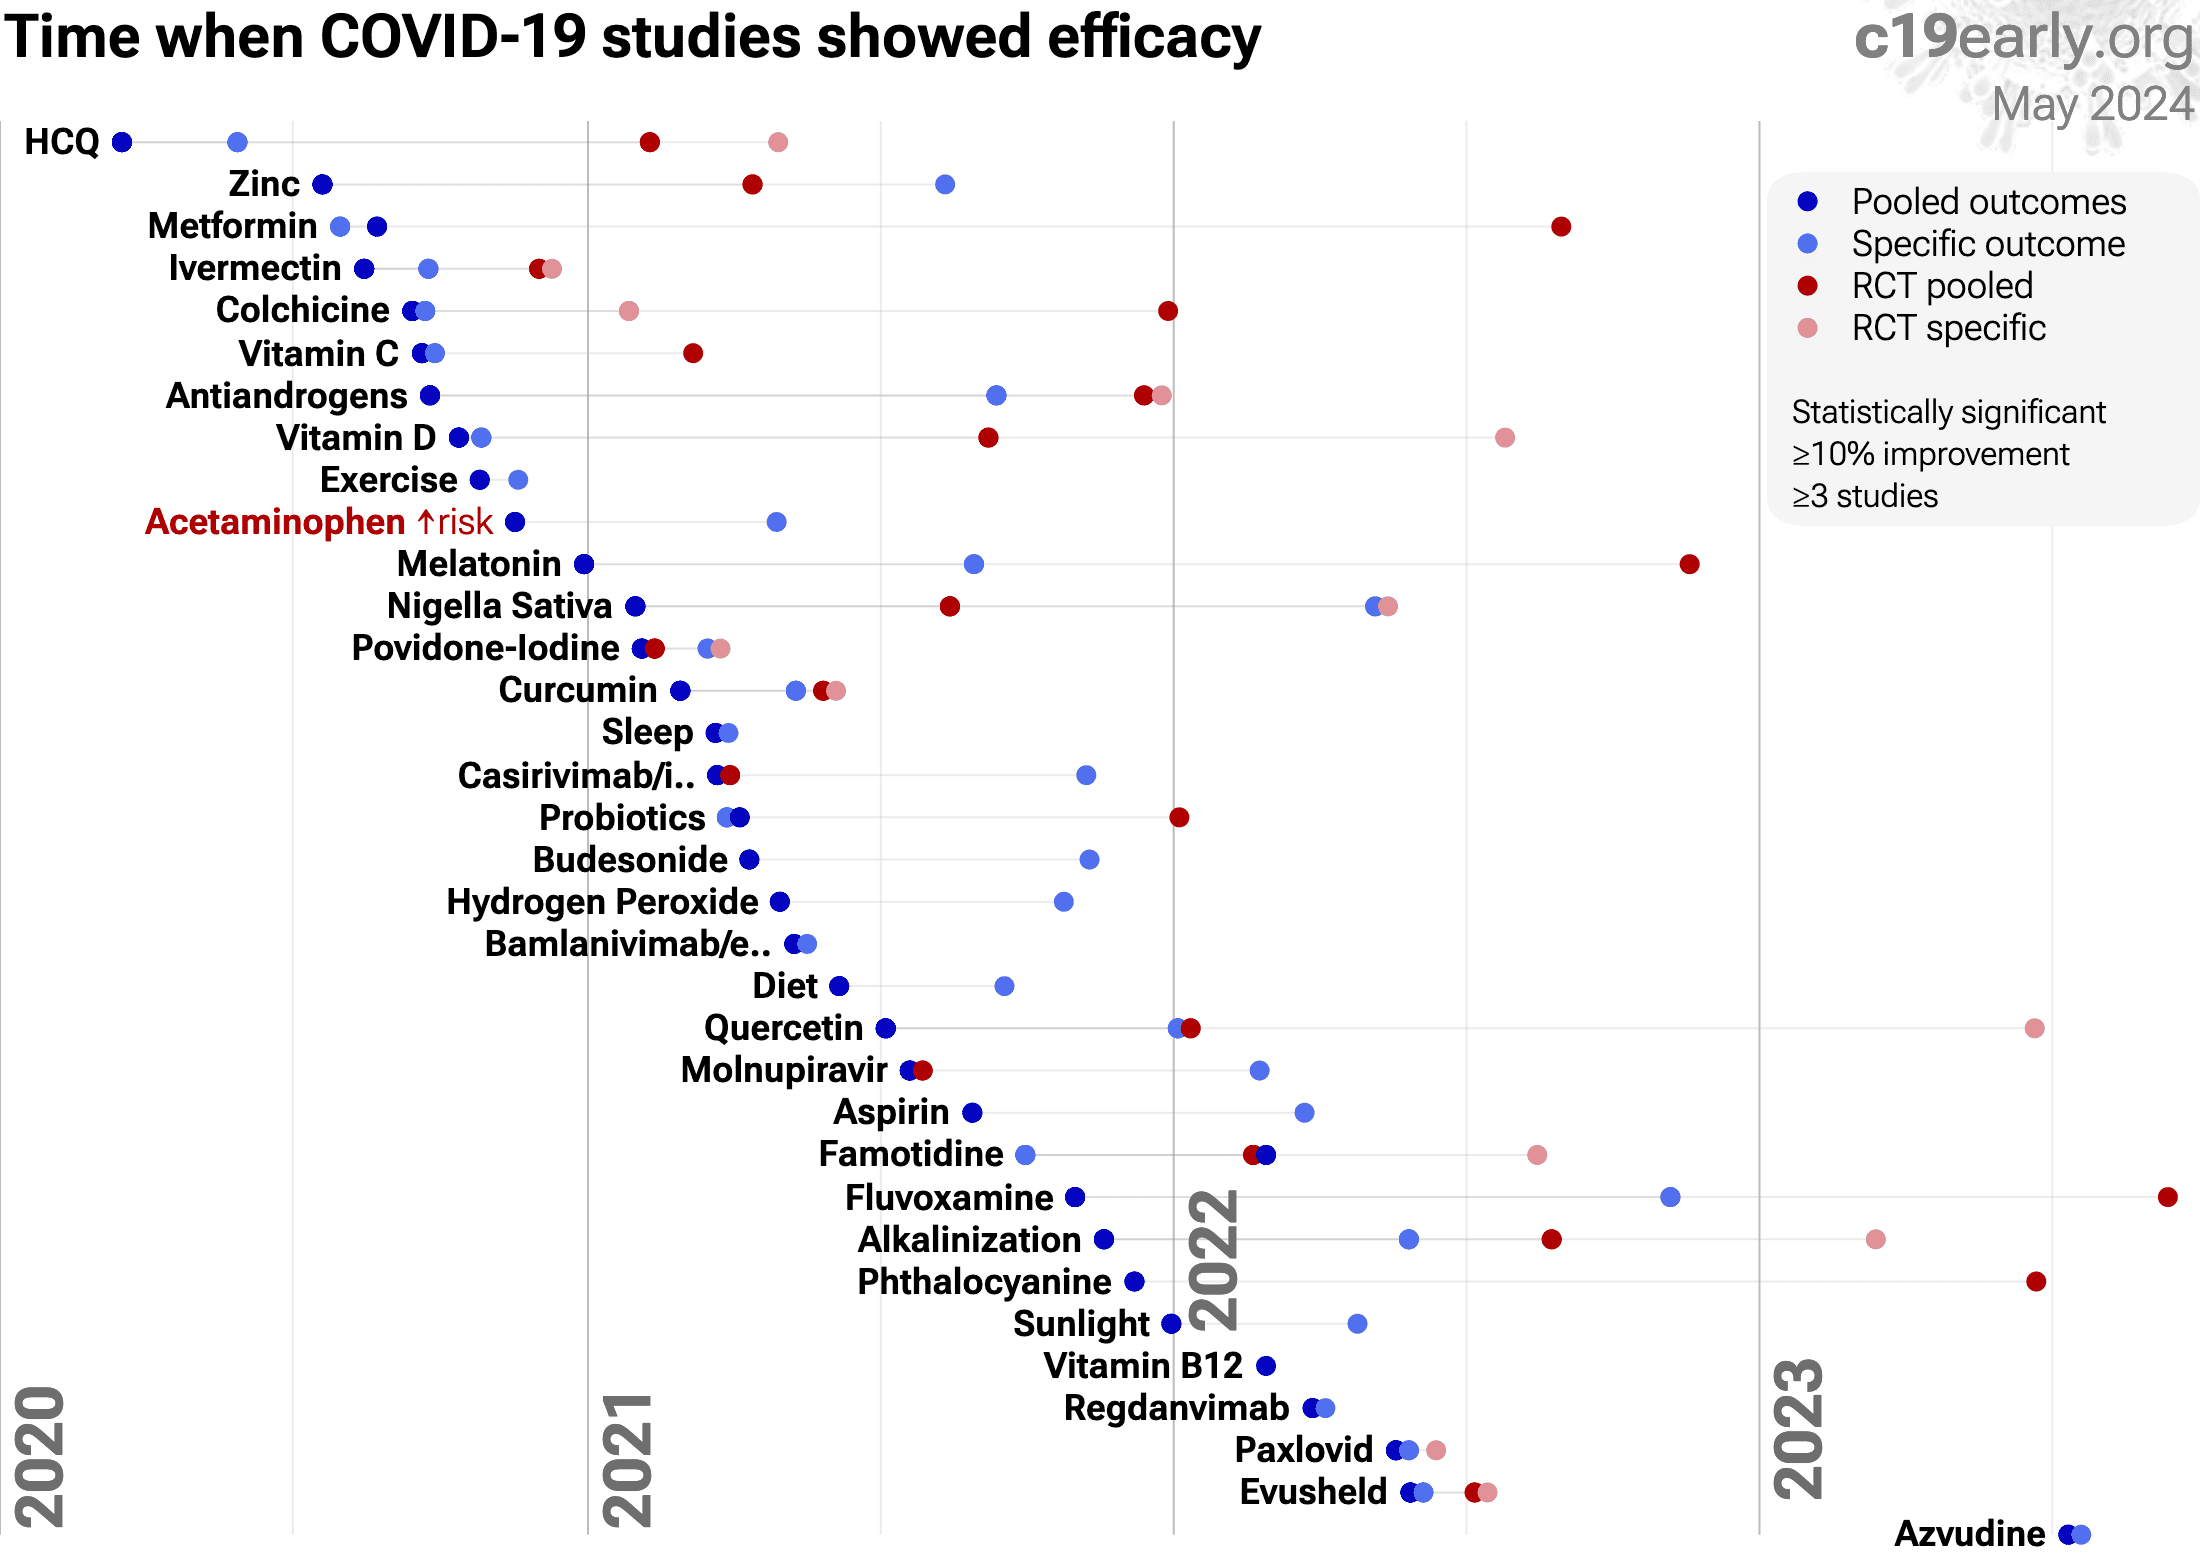
Media covered none of the 6 studies showing significantly lower risk
No positive nitric oxide studies were covered
Nitric Oxide for COVID-19
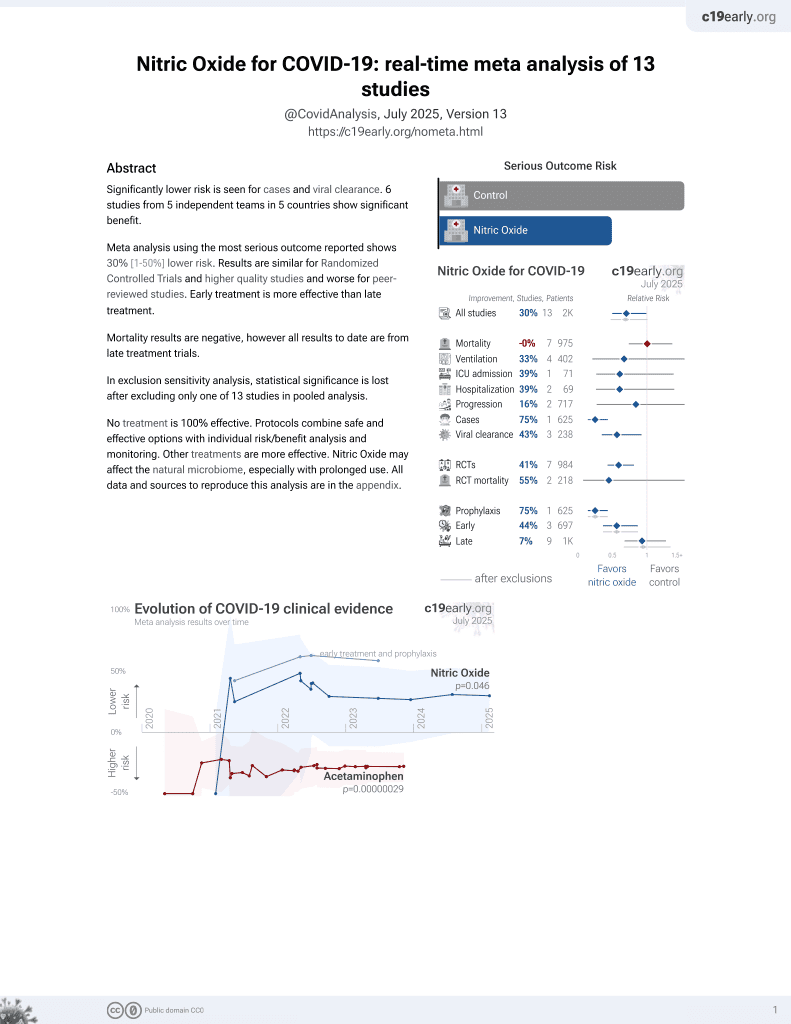
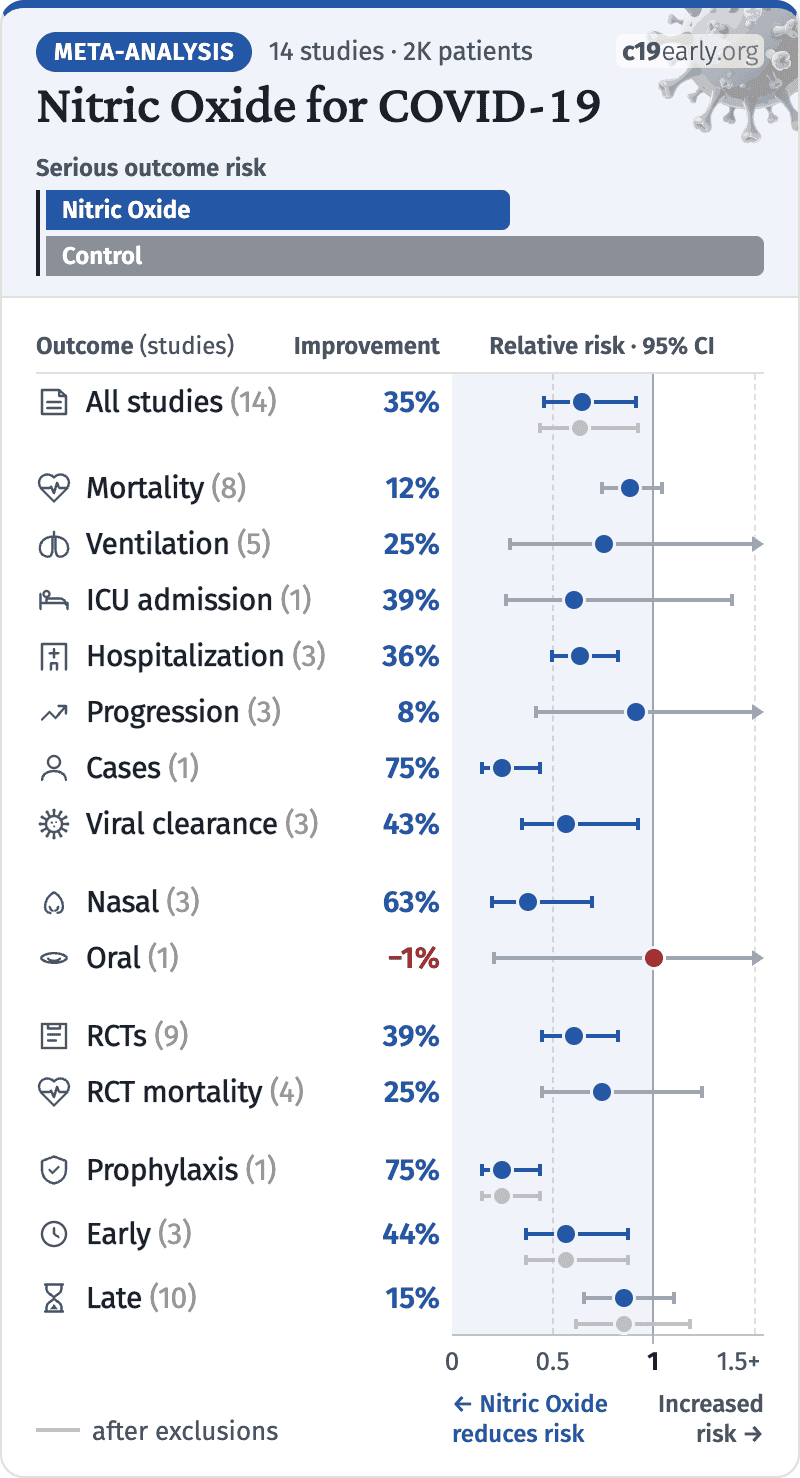
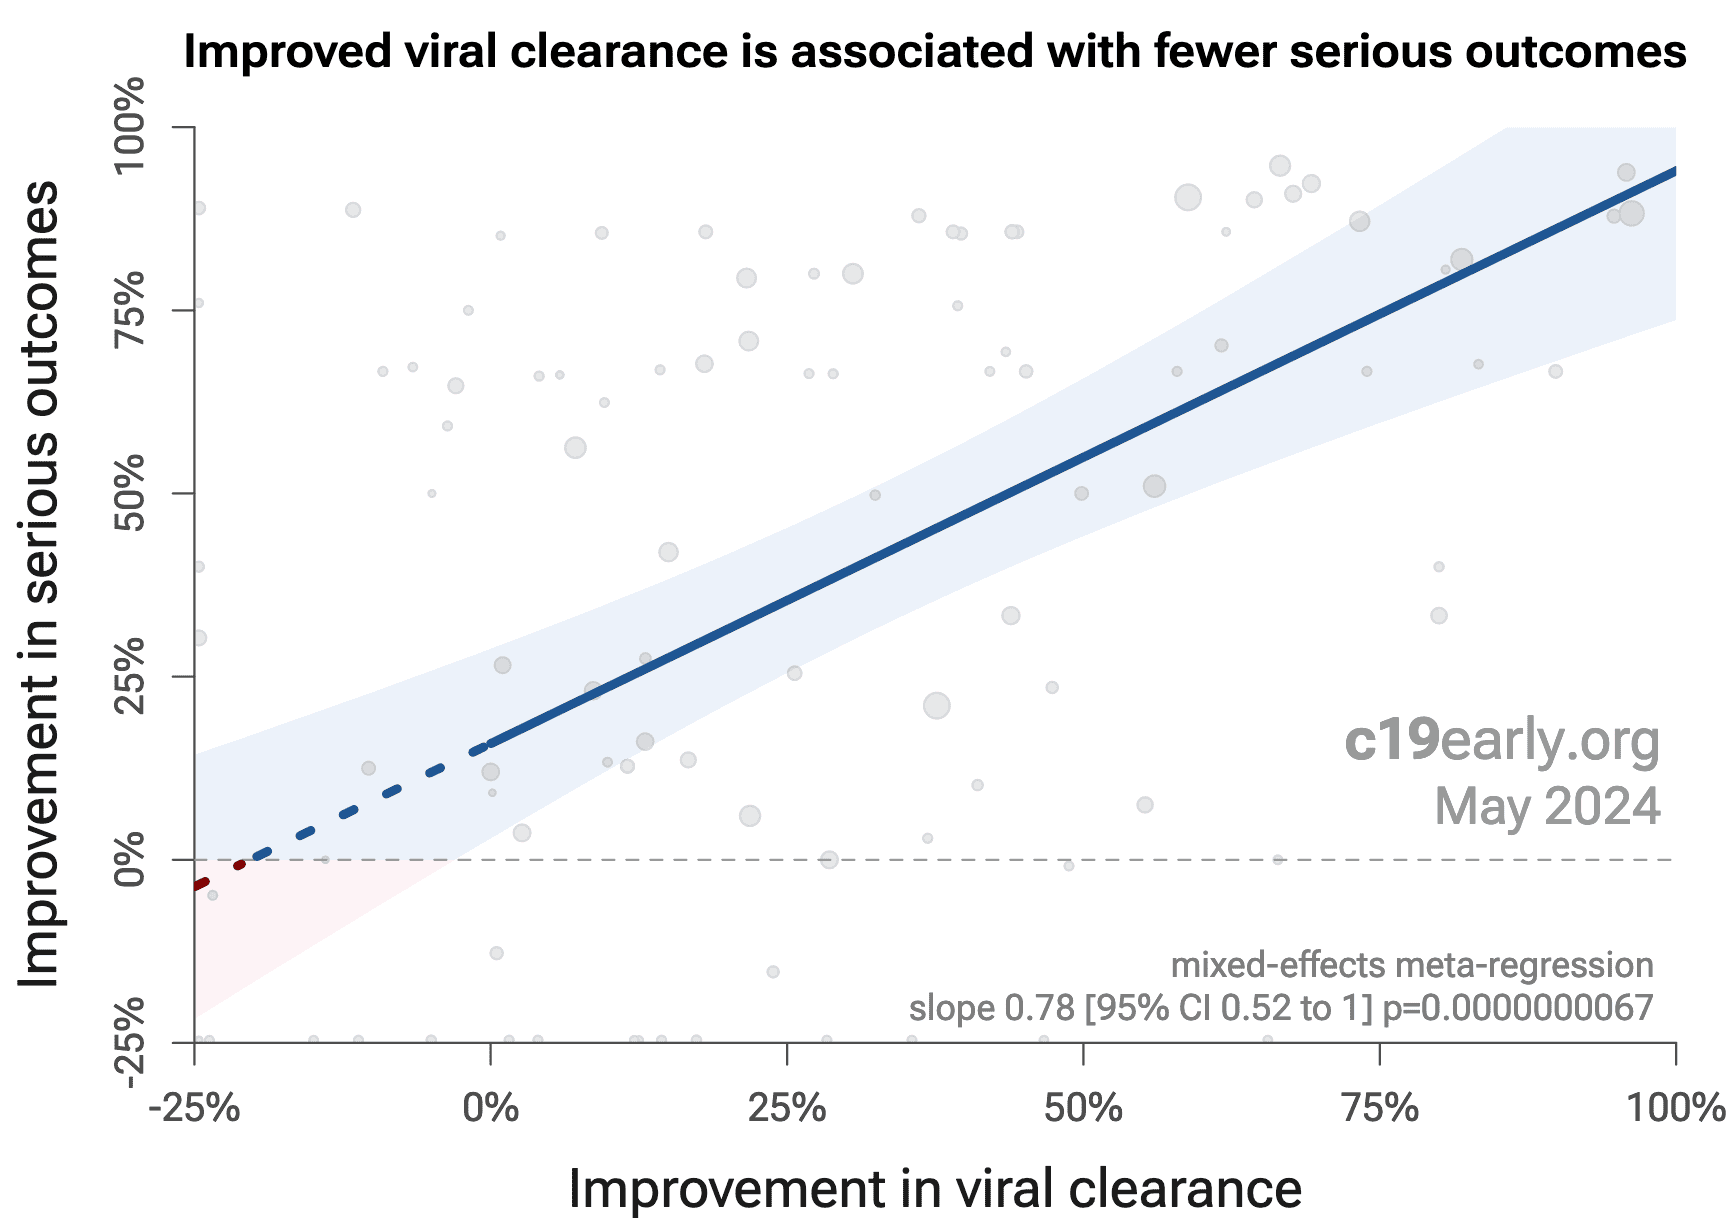
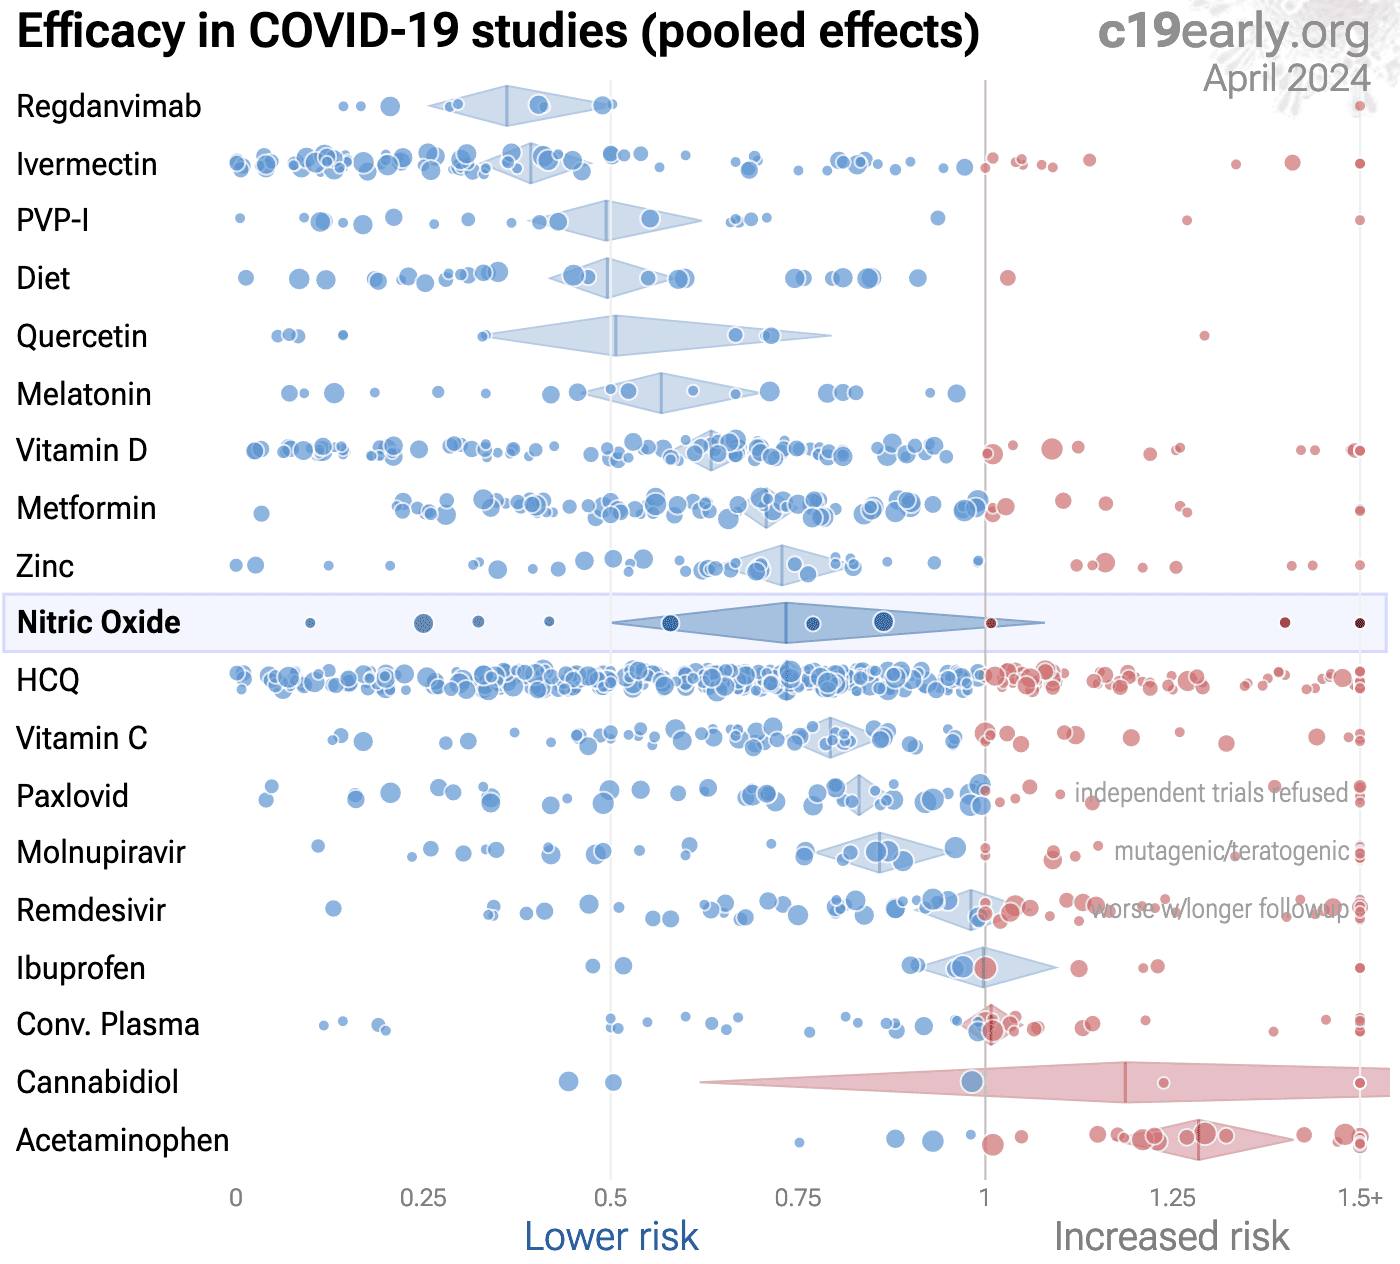
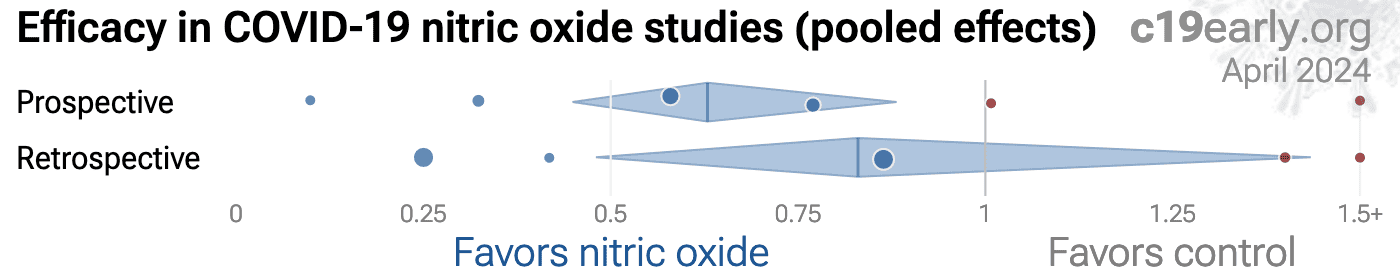
Highlights- Nitric Oxide reduces risk with very high confidence for hospitalization, high confidence for viral clearance and in pooled analysis, low confidence for cases, and very low confidence for mortality and ICU admission.
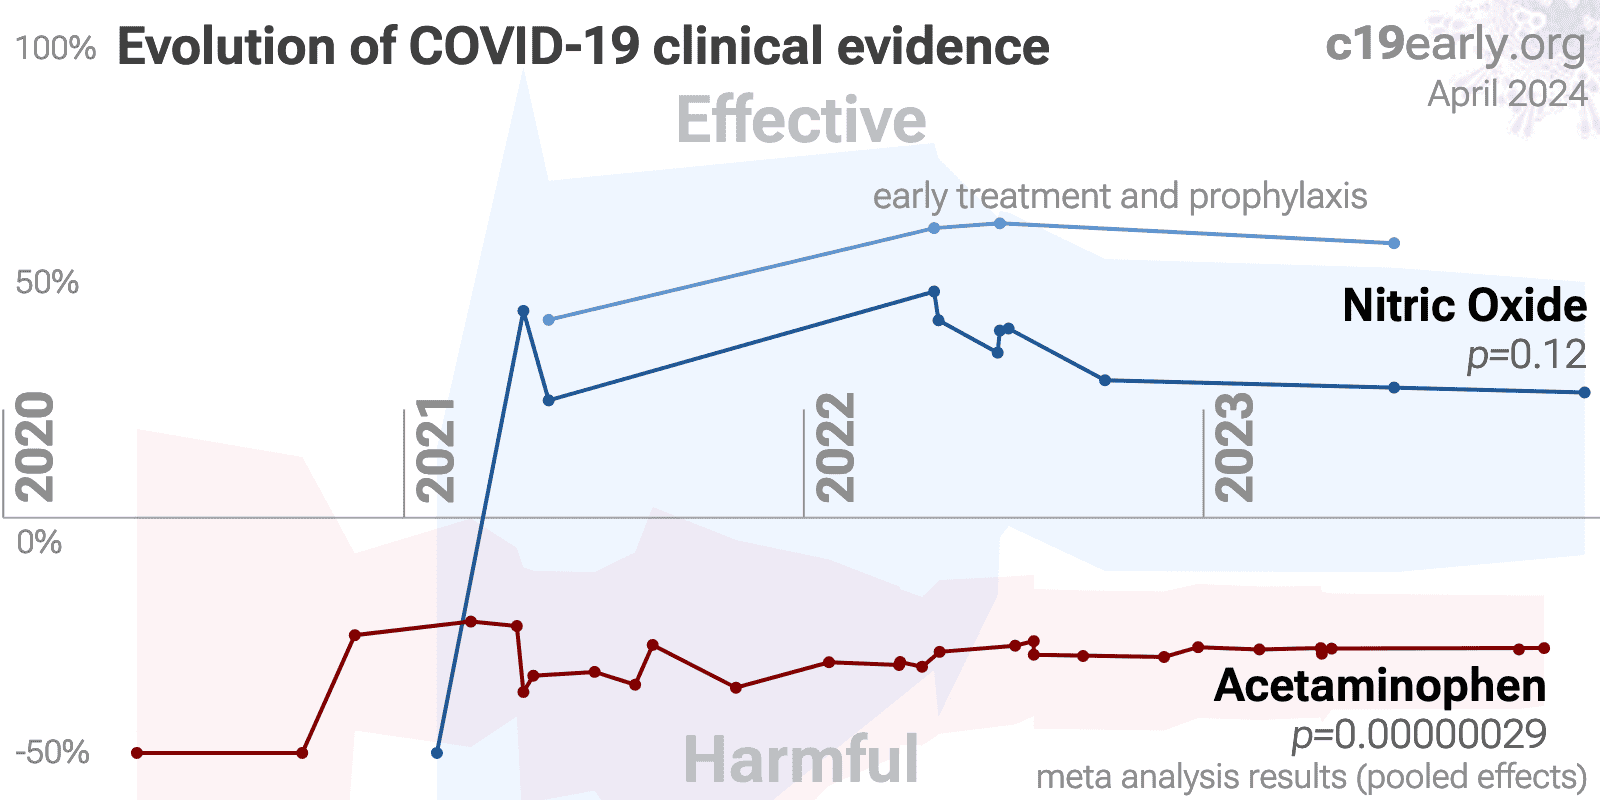
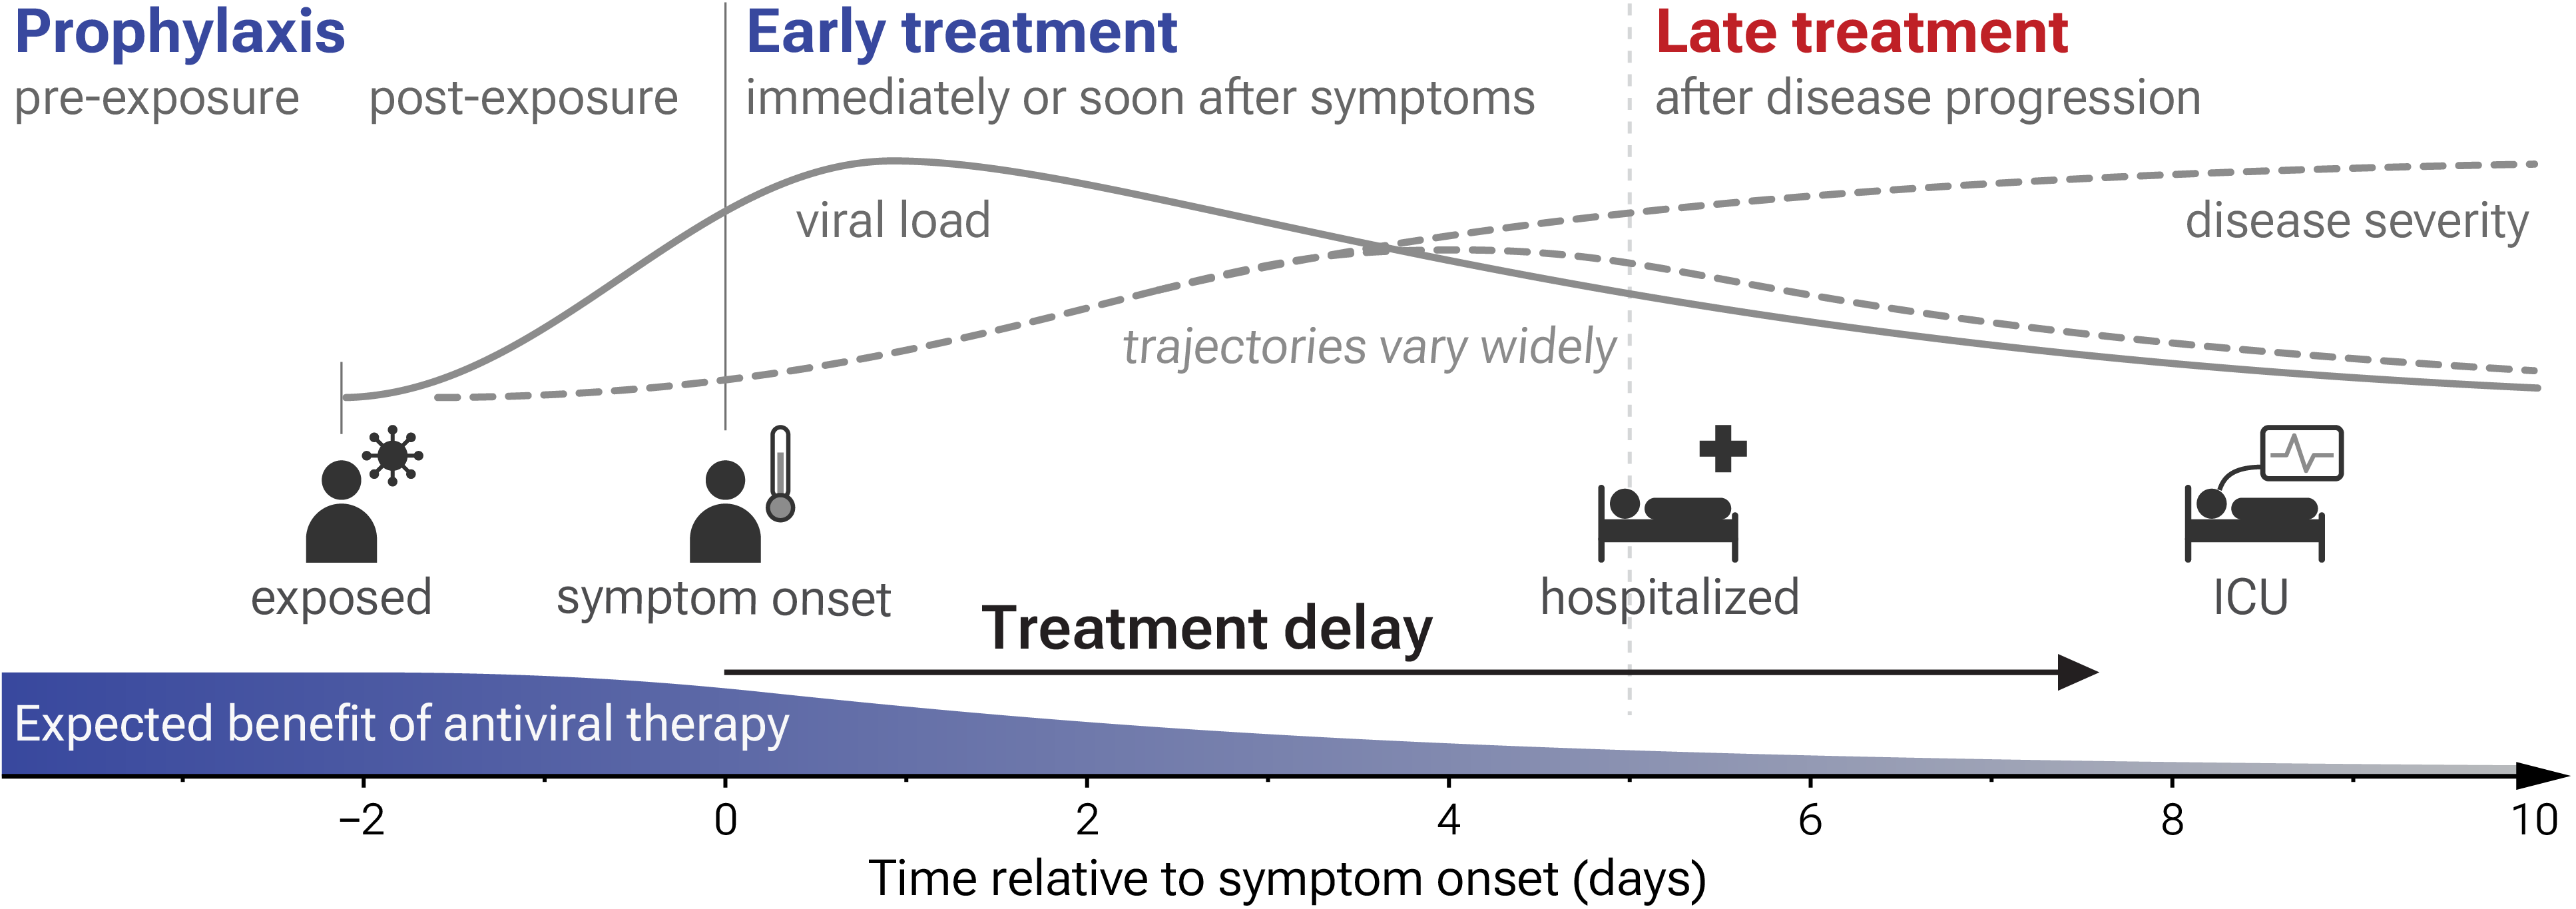
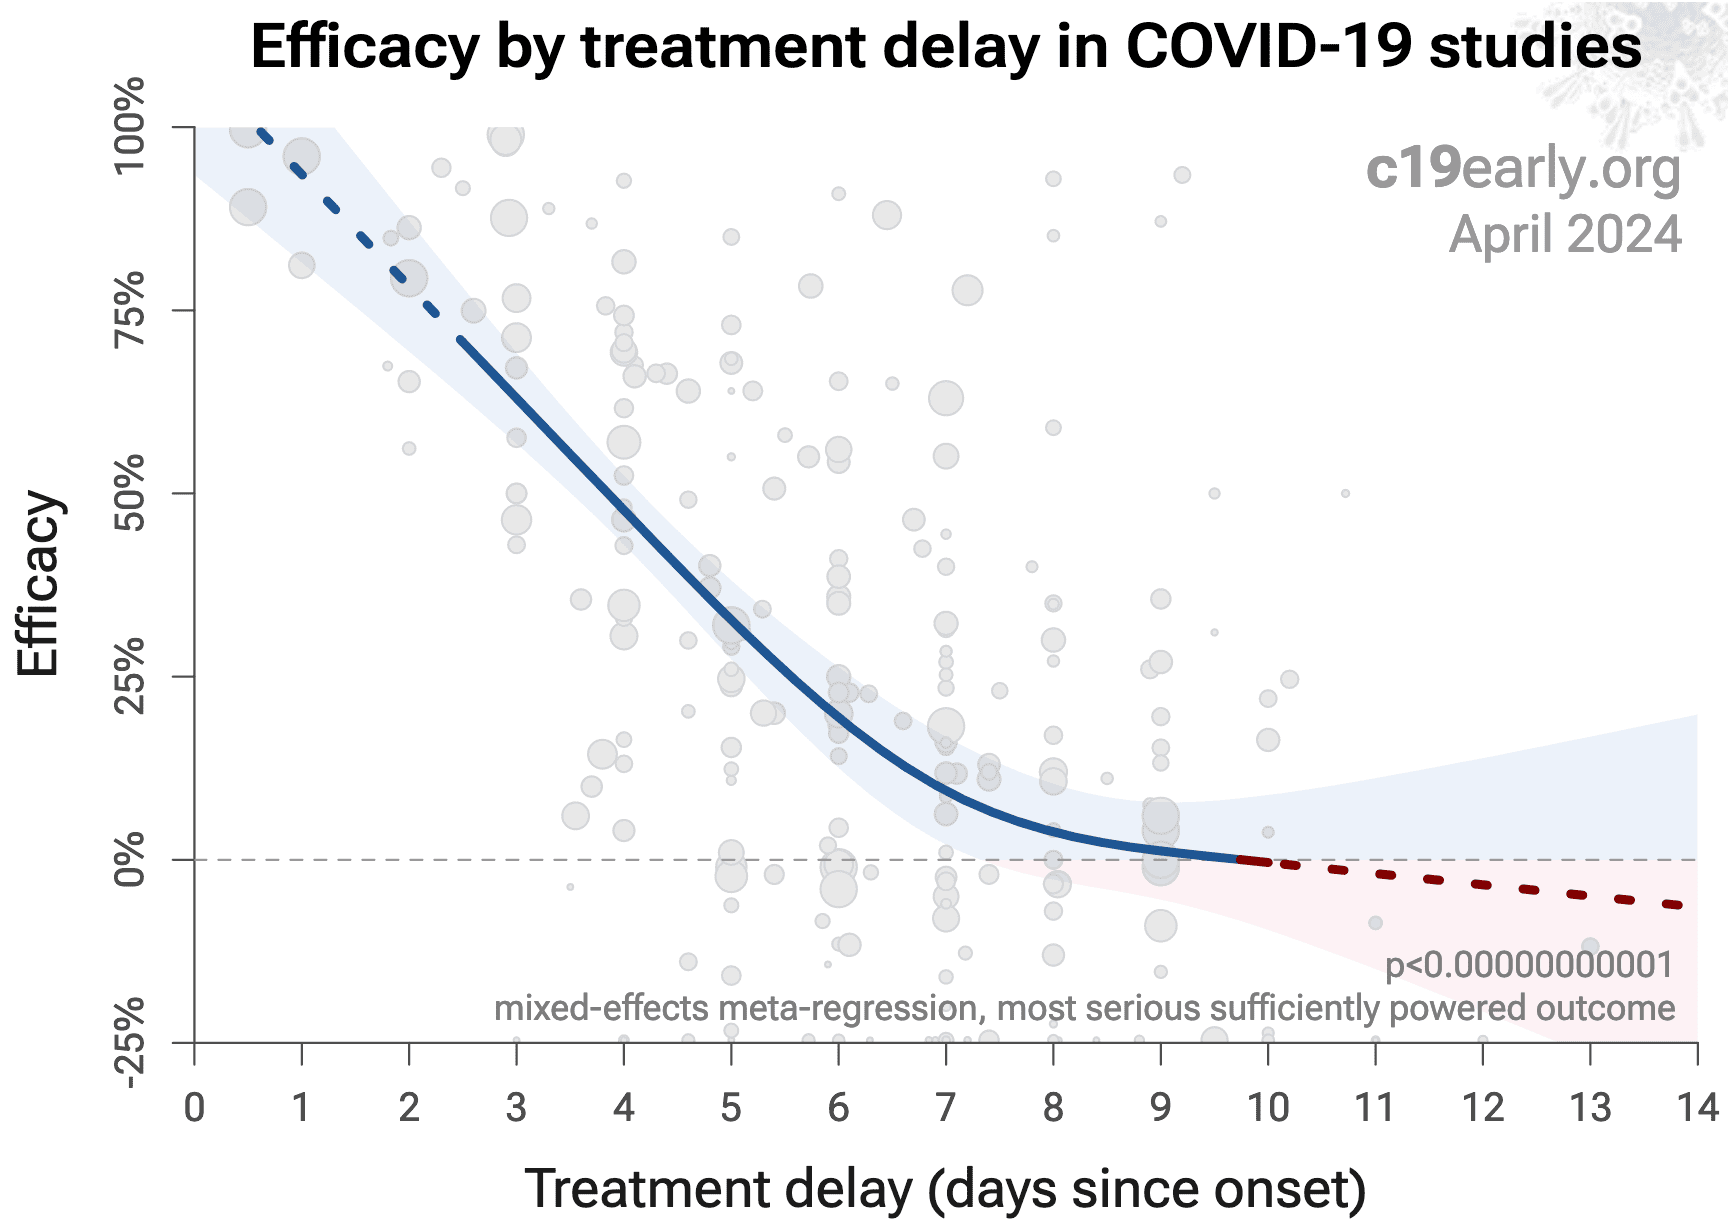
- Emergent results for the efficacy gradient across stages (p < 0.0000001) that match the biological mechanisms confirm efficacy.
- 43rd treatment shown effective in June 2022, now with p = 0.013 from 14 studies, recognized in 10 countries.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
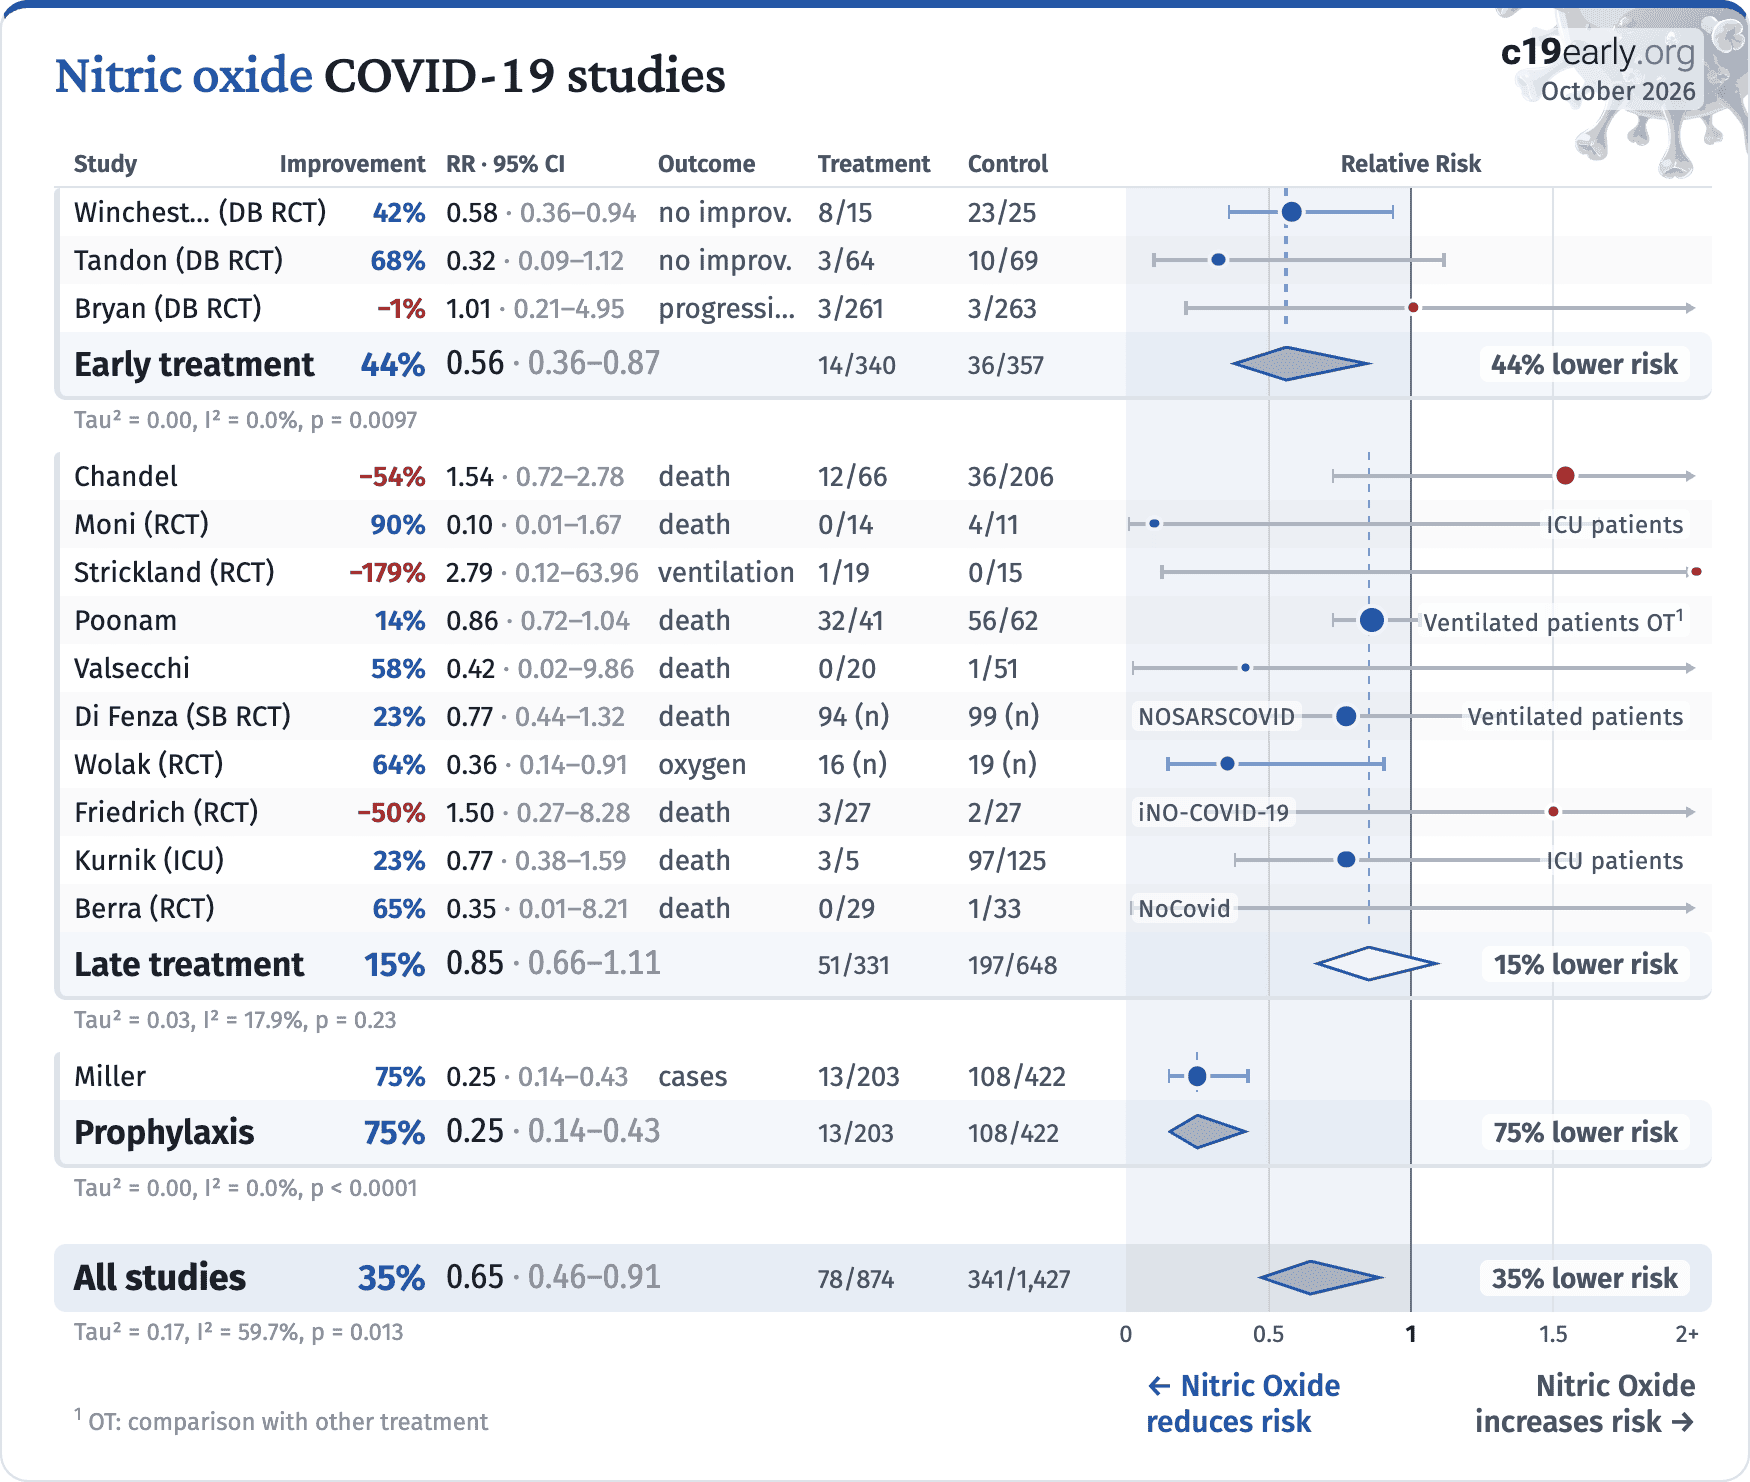
Nitric oxide COVID-19 studies
Nitric Oxide for COVID-19: meta-analysis results
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Nitric oxide COVID-19 studies
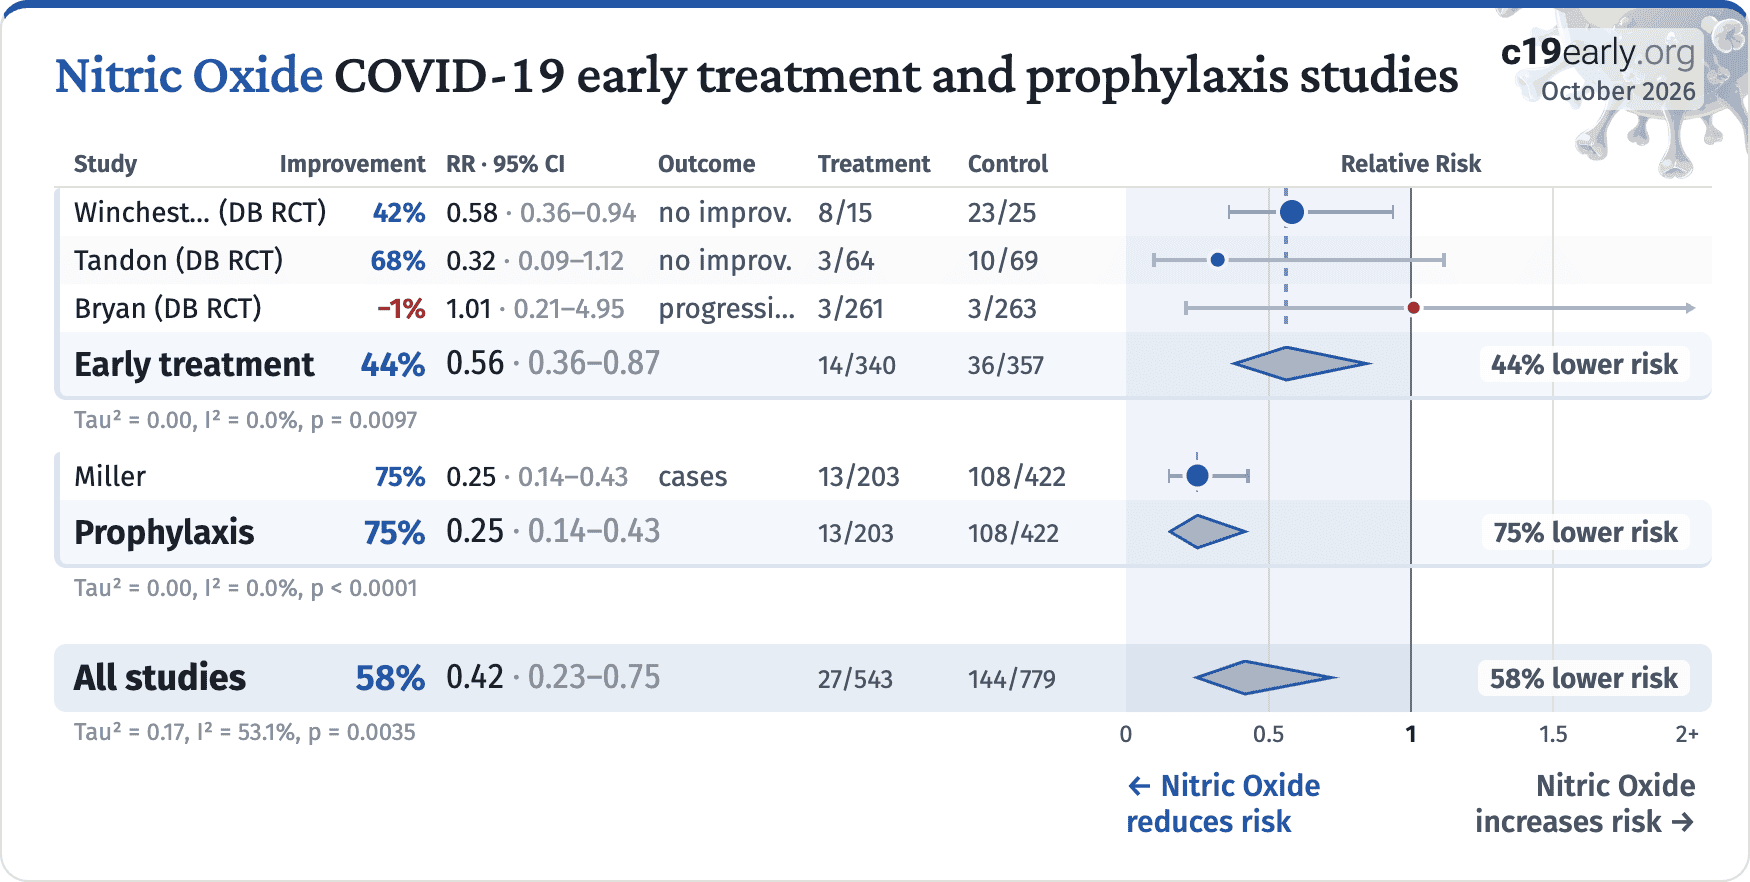
Nitric Oxide COVID-19 early treatment and prophylaxis studies
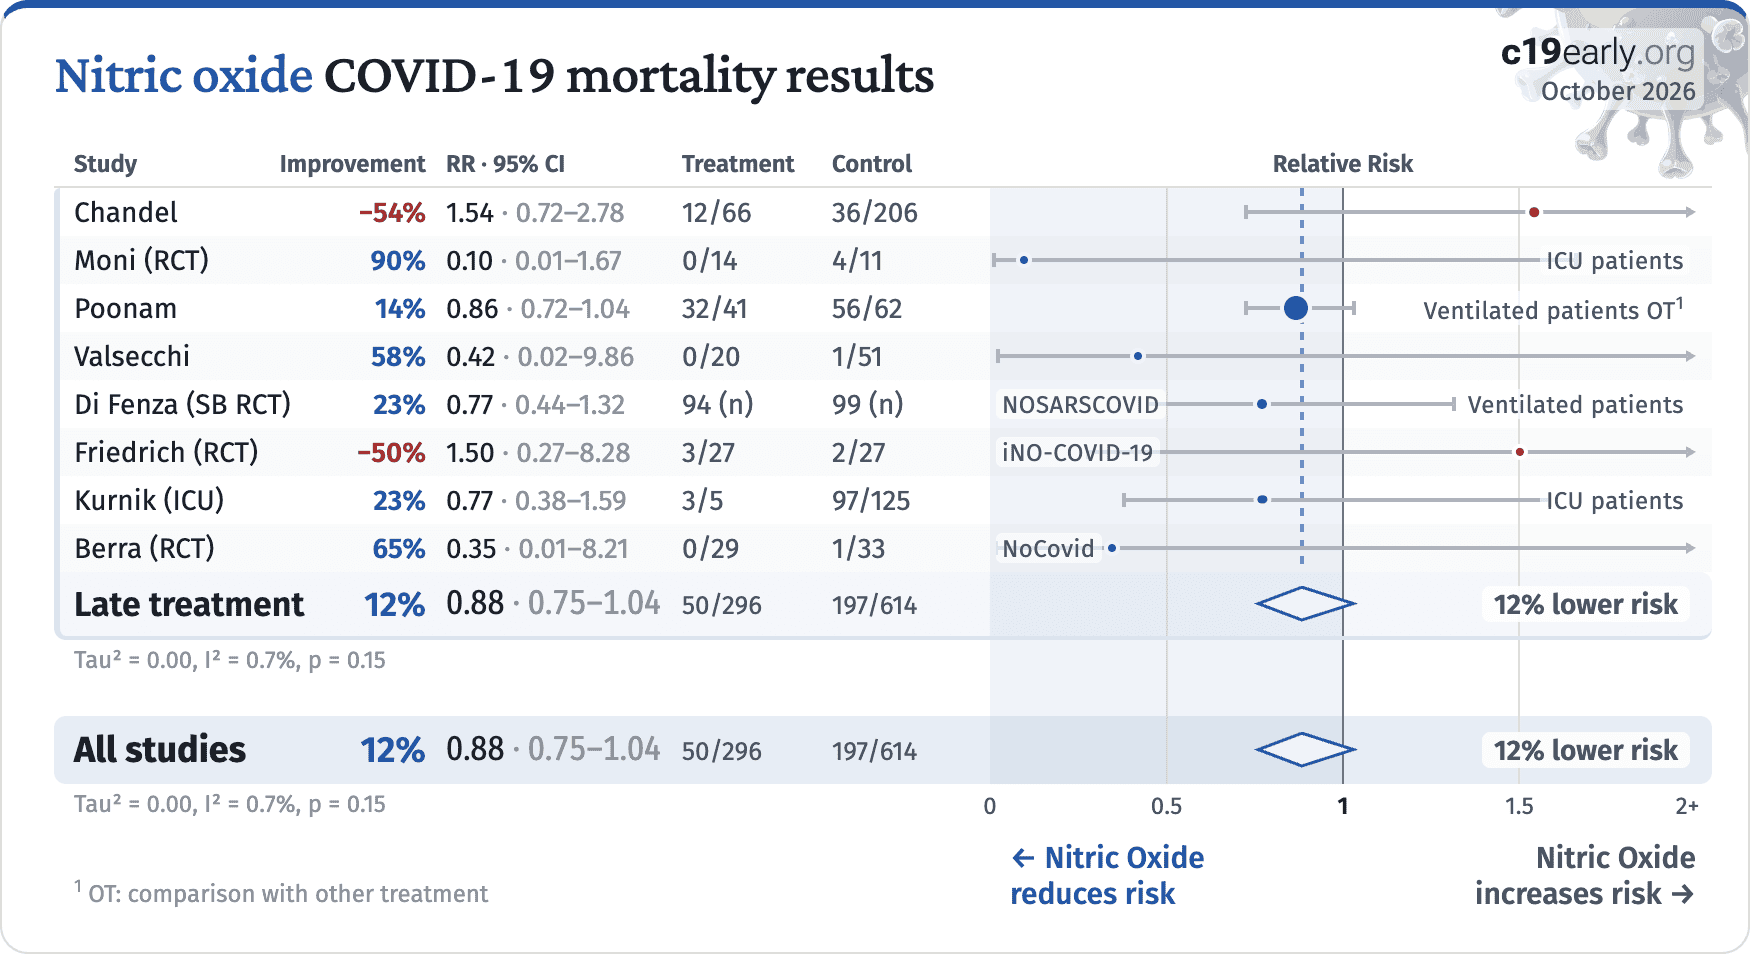
Nitric oxide COVID-19 mortality results
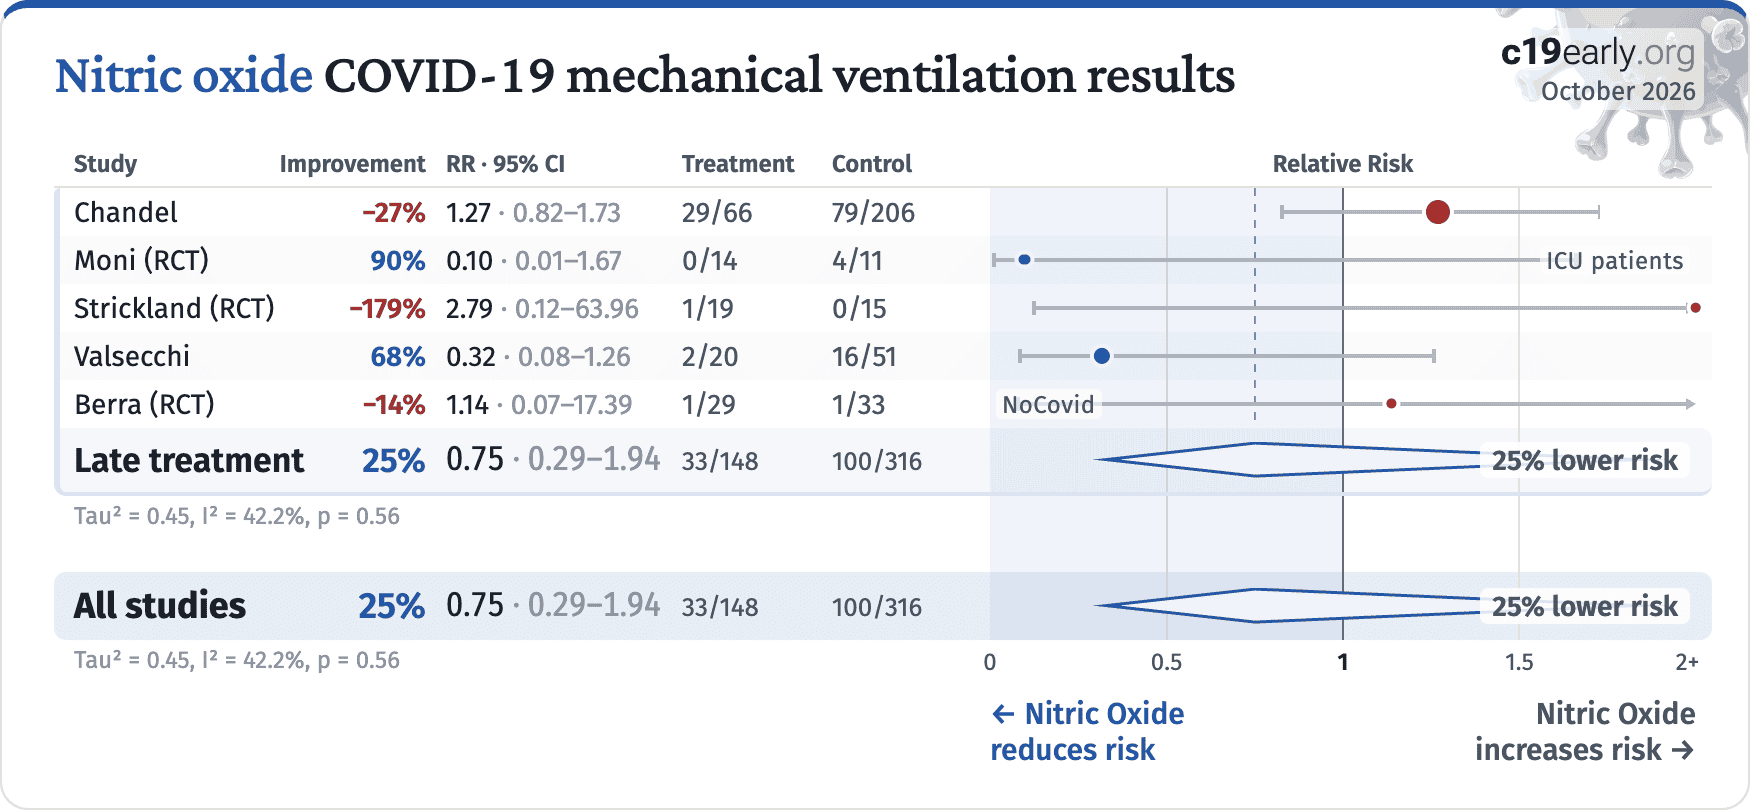
Nitric oxide COVID-19 mechanical ventilation results
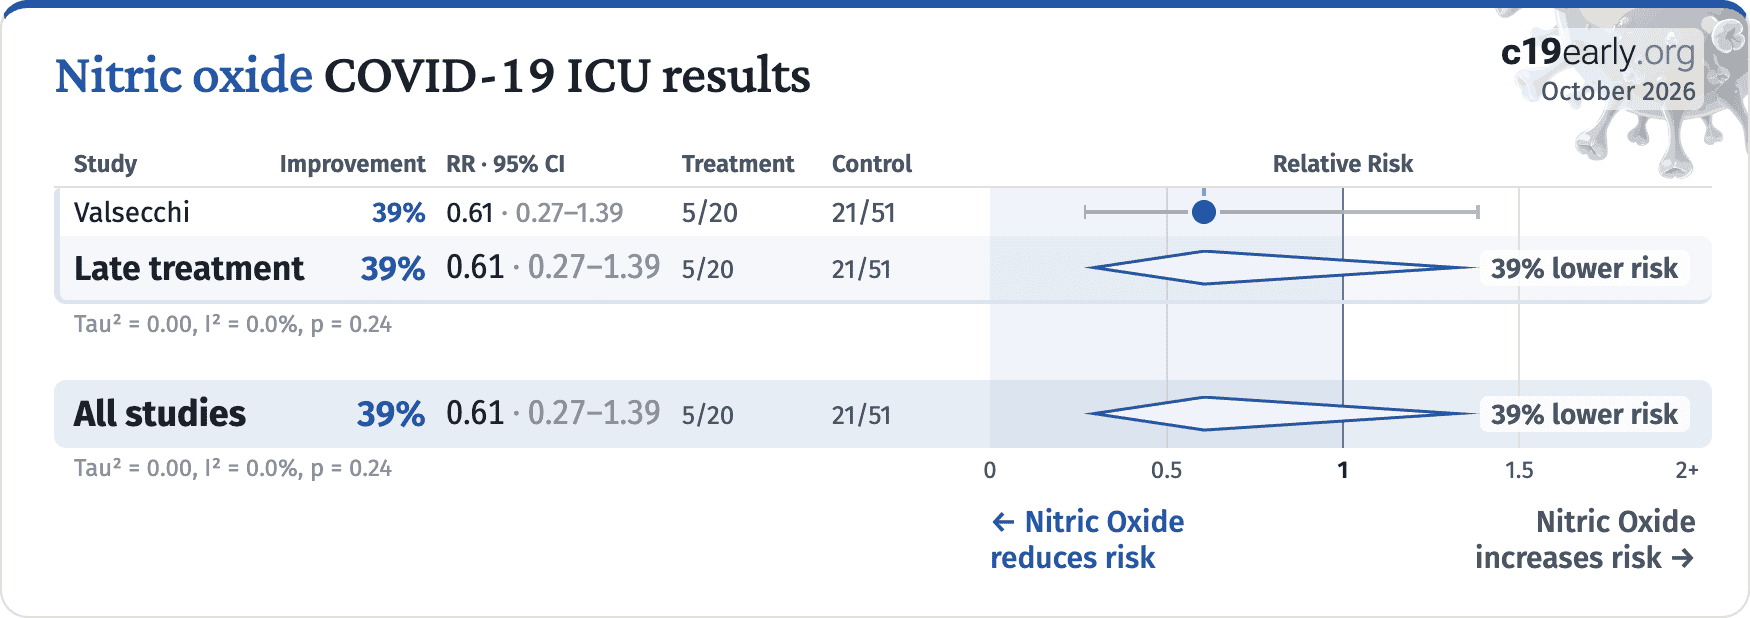
Nitric oxide COVID-19 ICU results
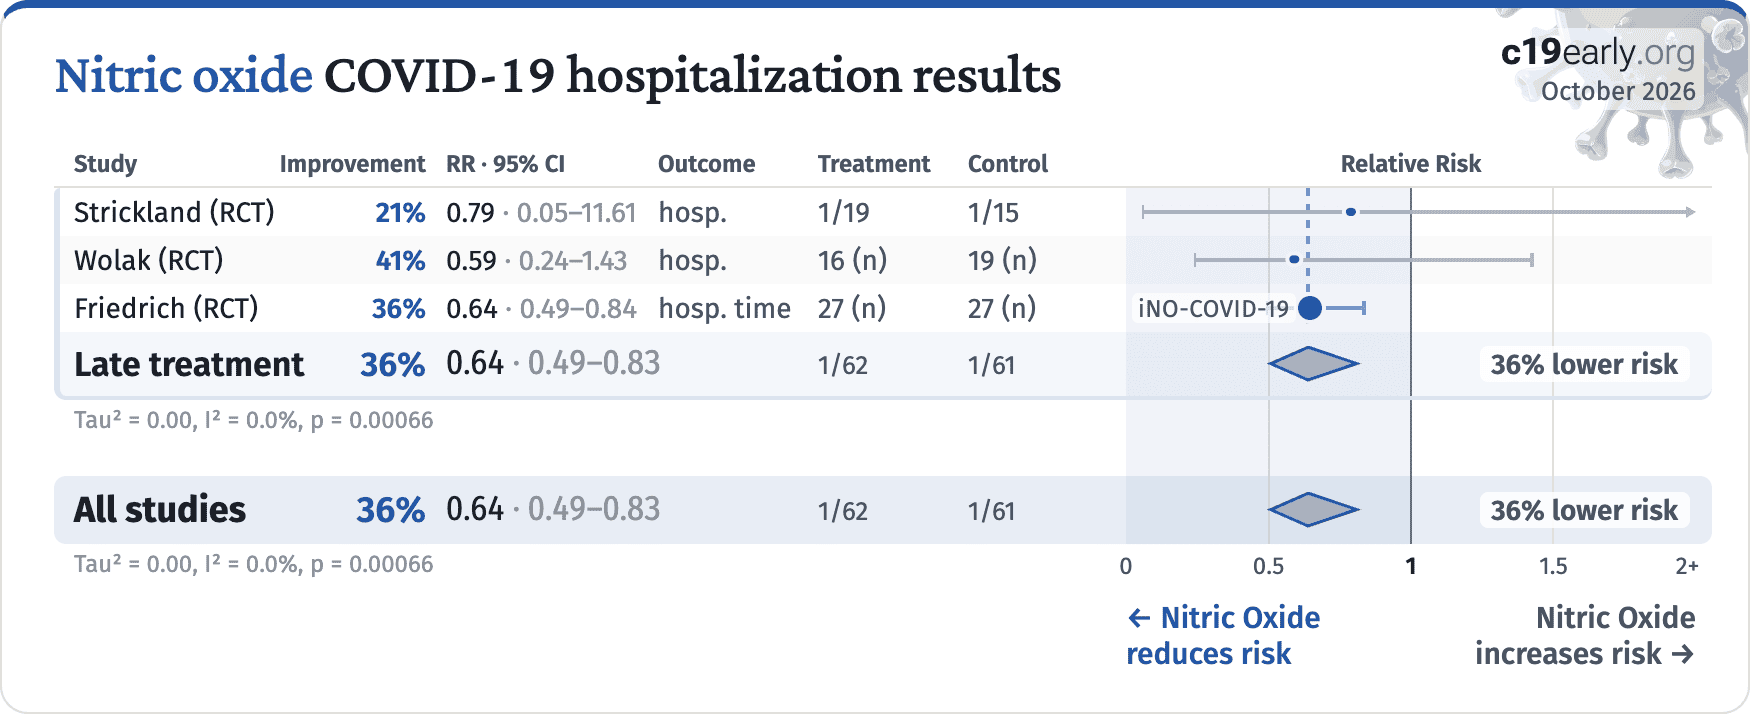
Nitric oxide COVID-19 hospitalization results
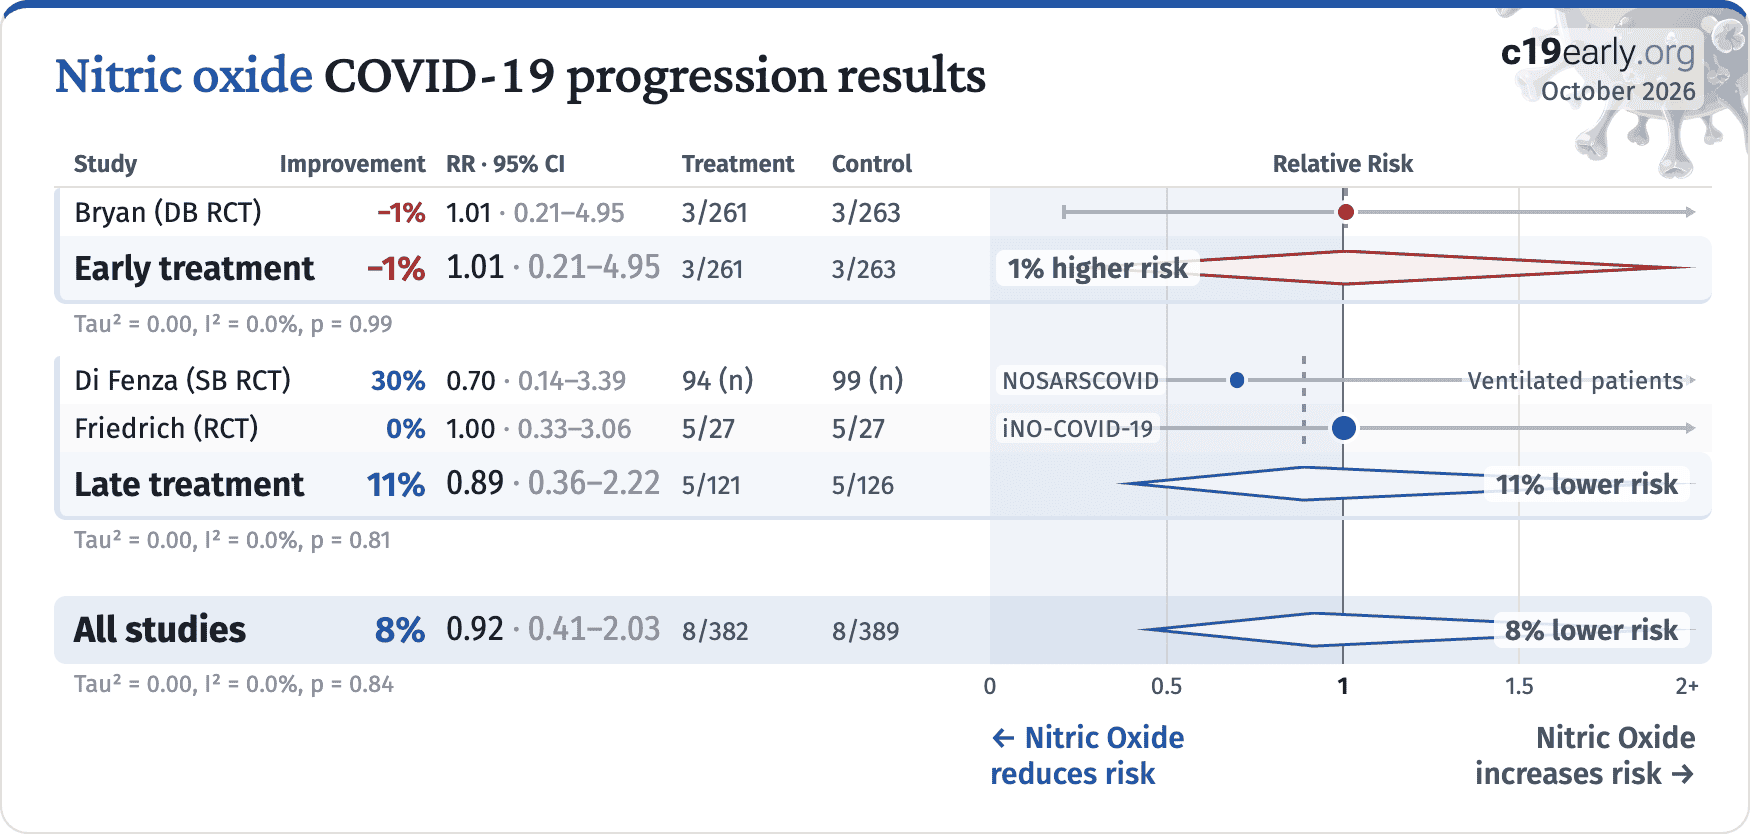
Nitric oxide COVID-19 progression results
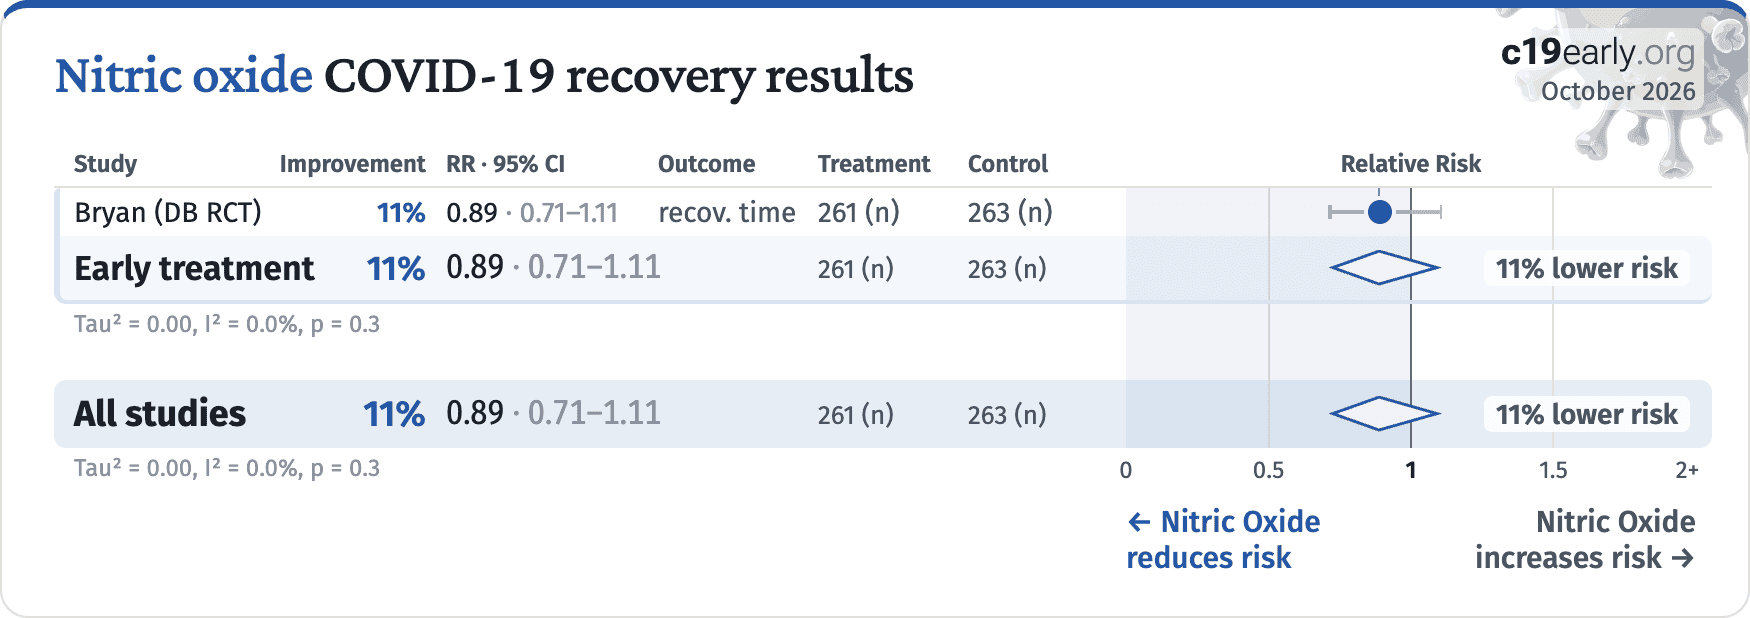
Nitric oxide COVID-19 recovery results
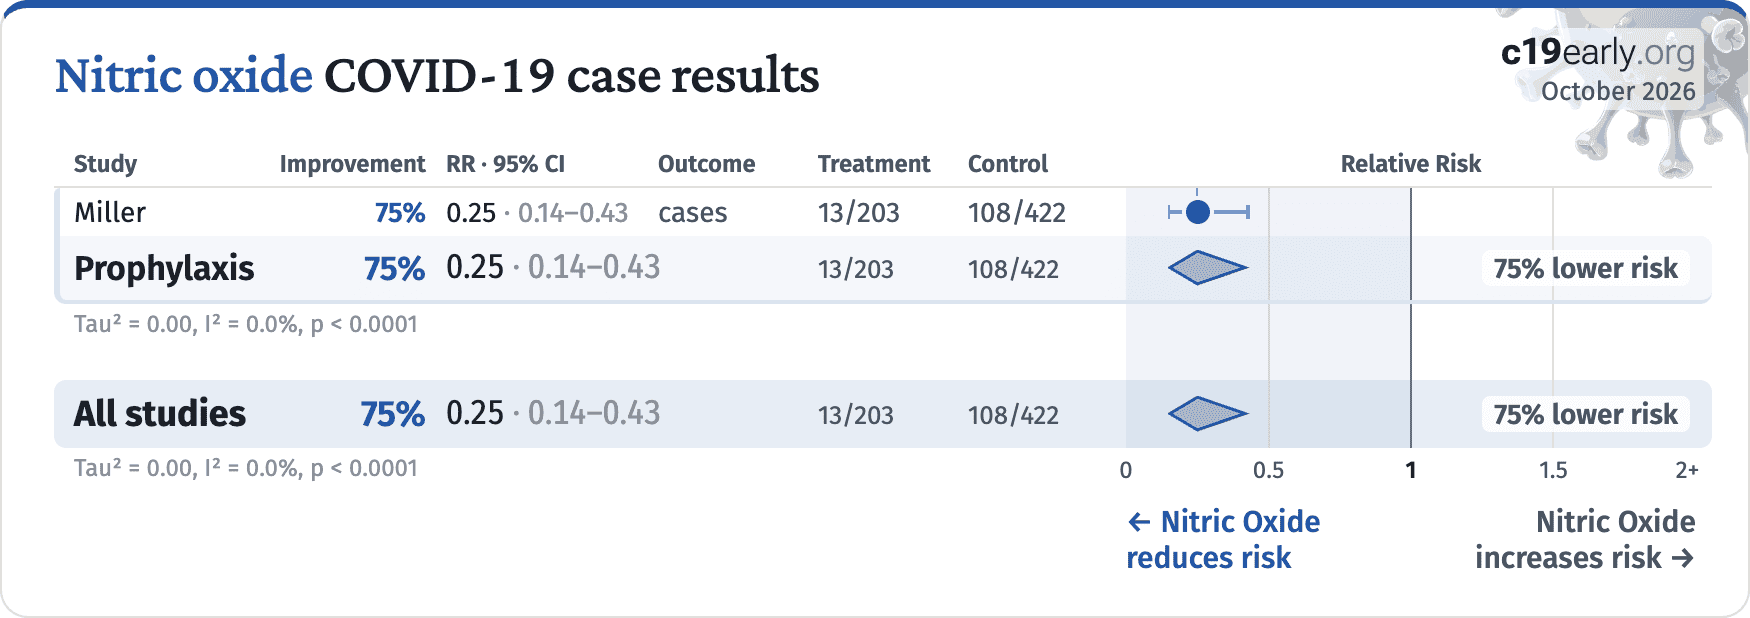
Nitric oxide COVID-19 case results
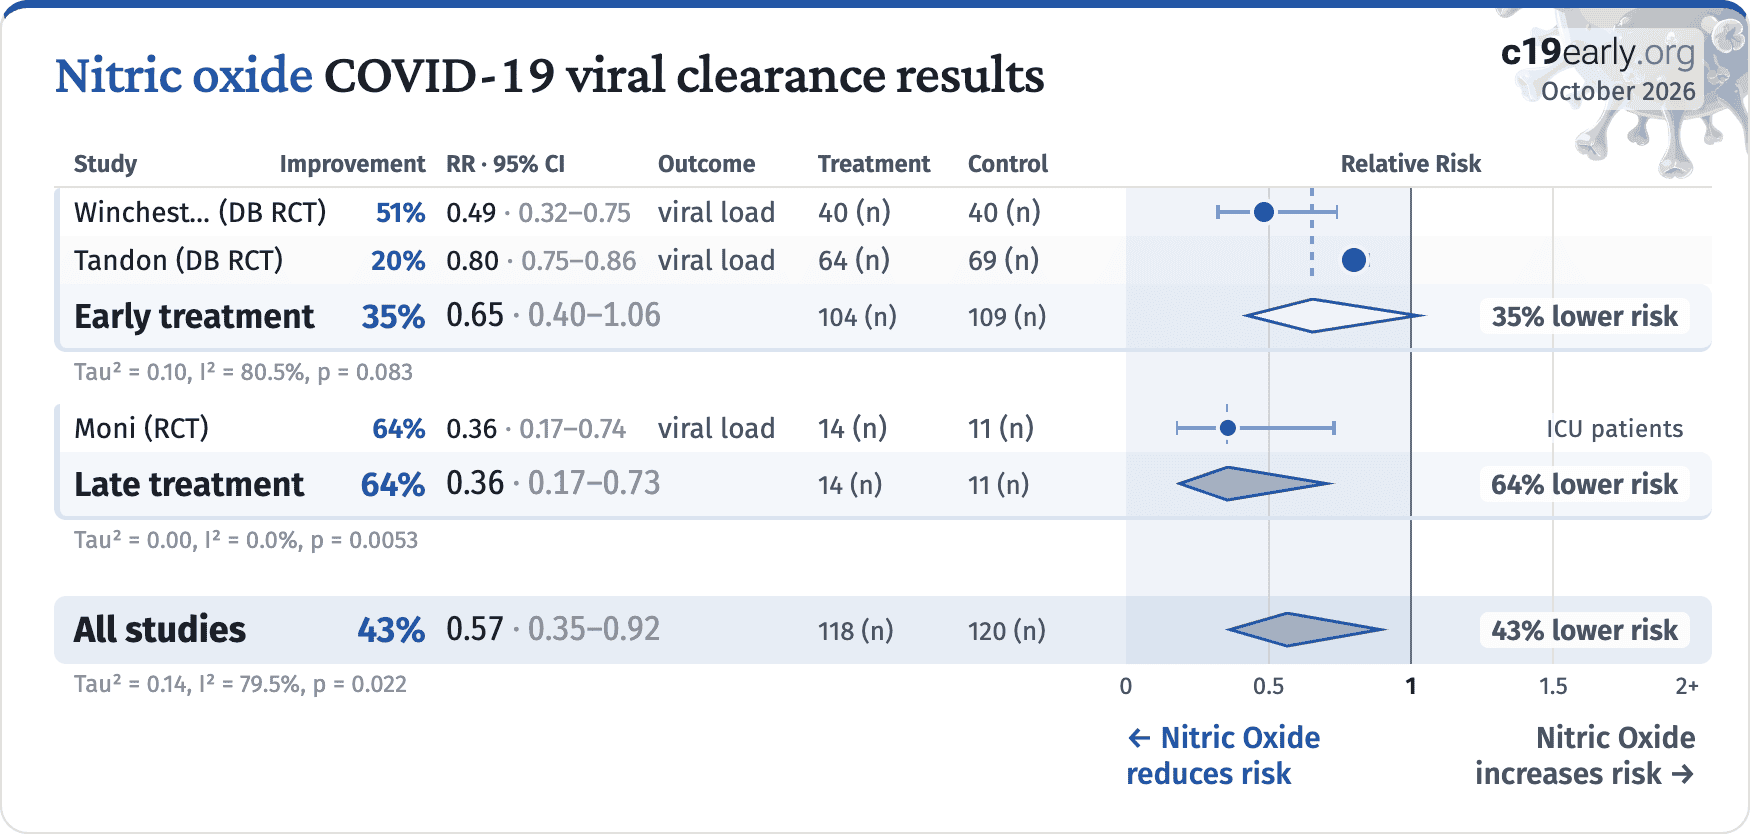
Nitric oxide COVID-19 viral clearance results
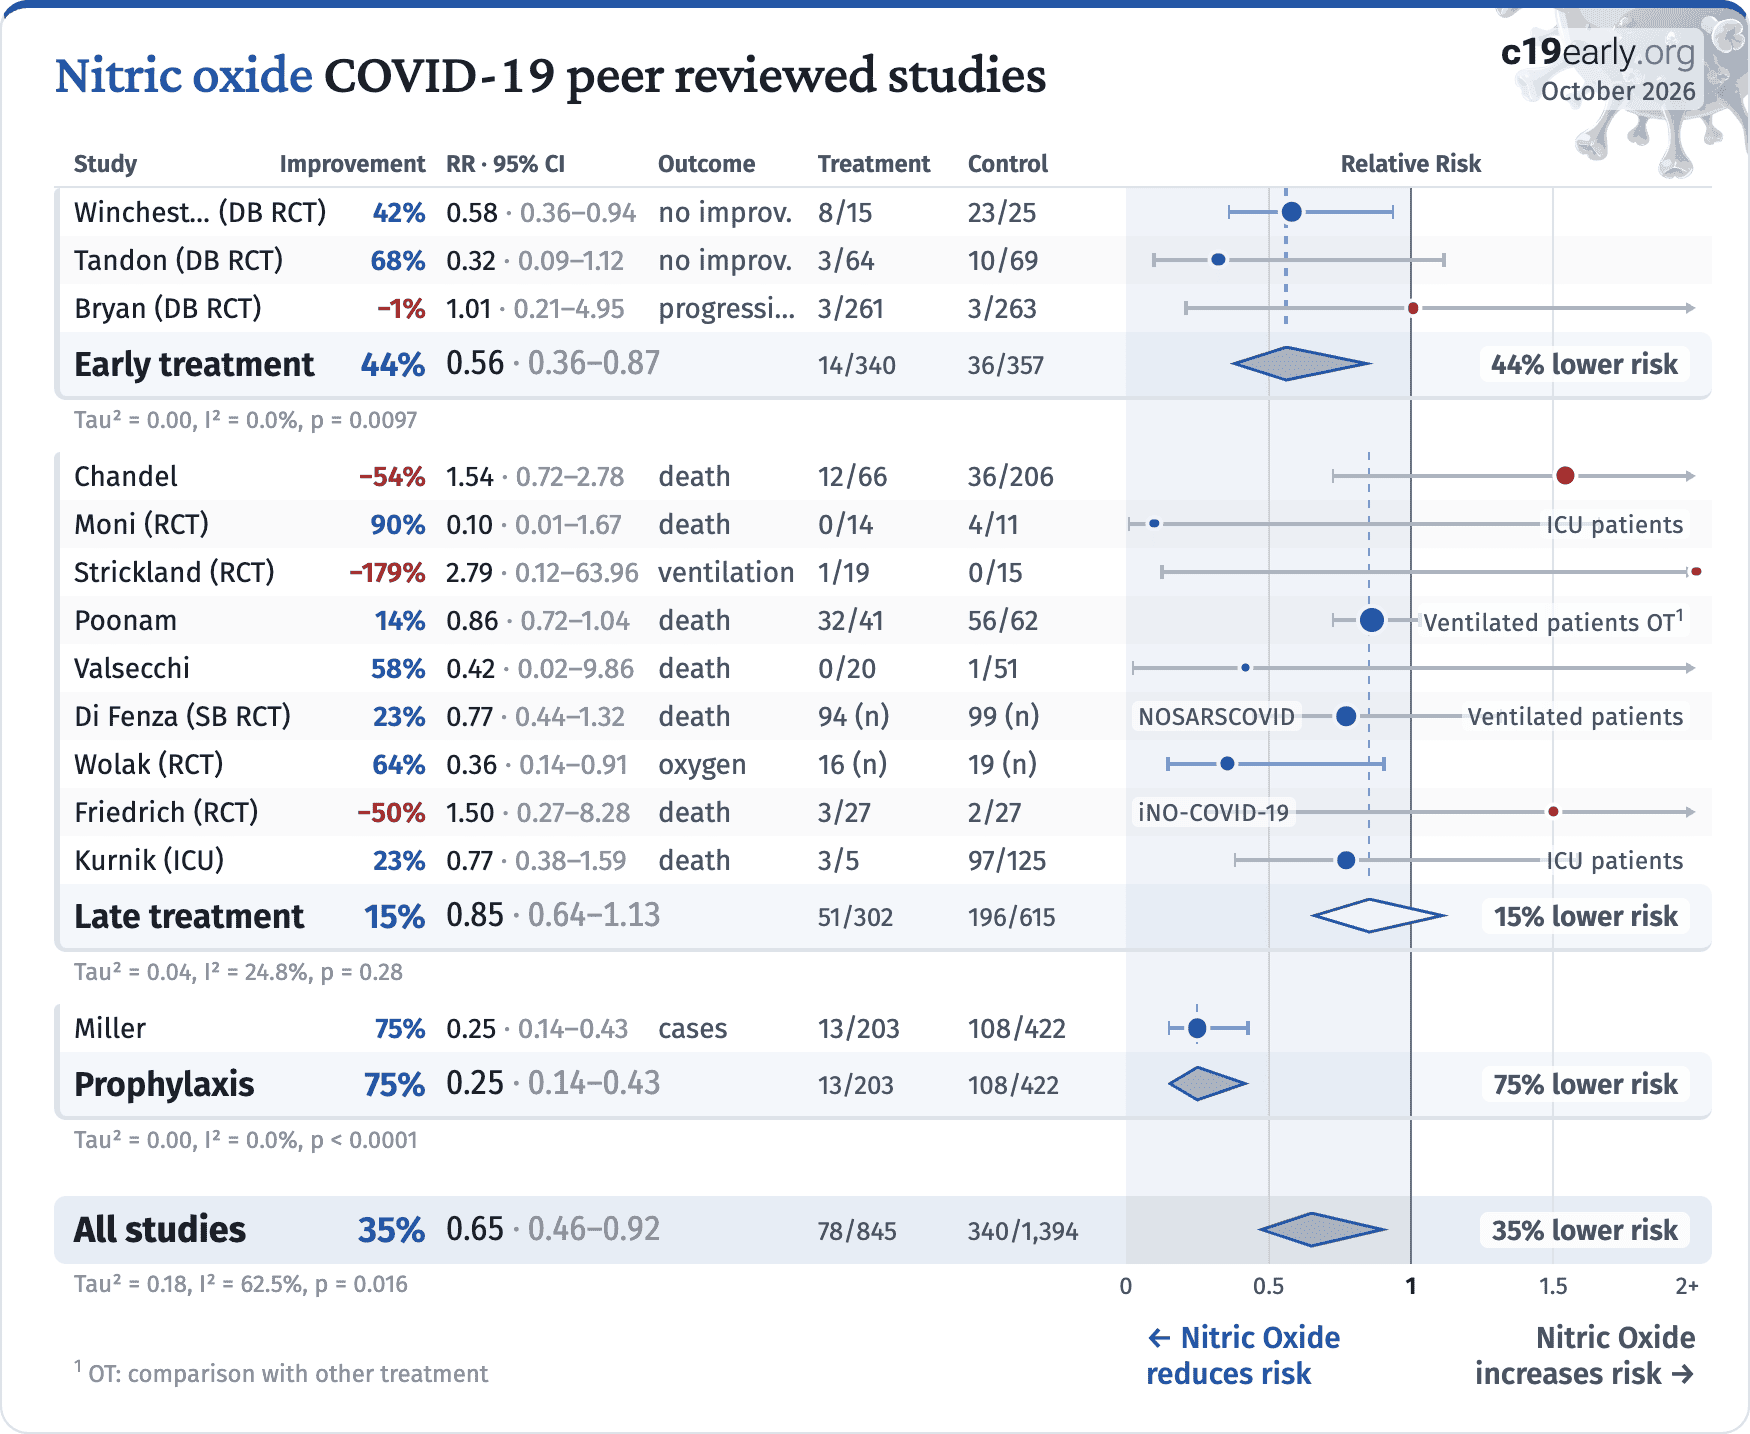
Nitric oxide COVID-19 peer reviewed studies
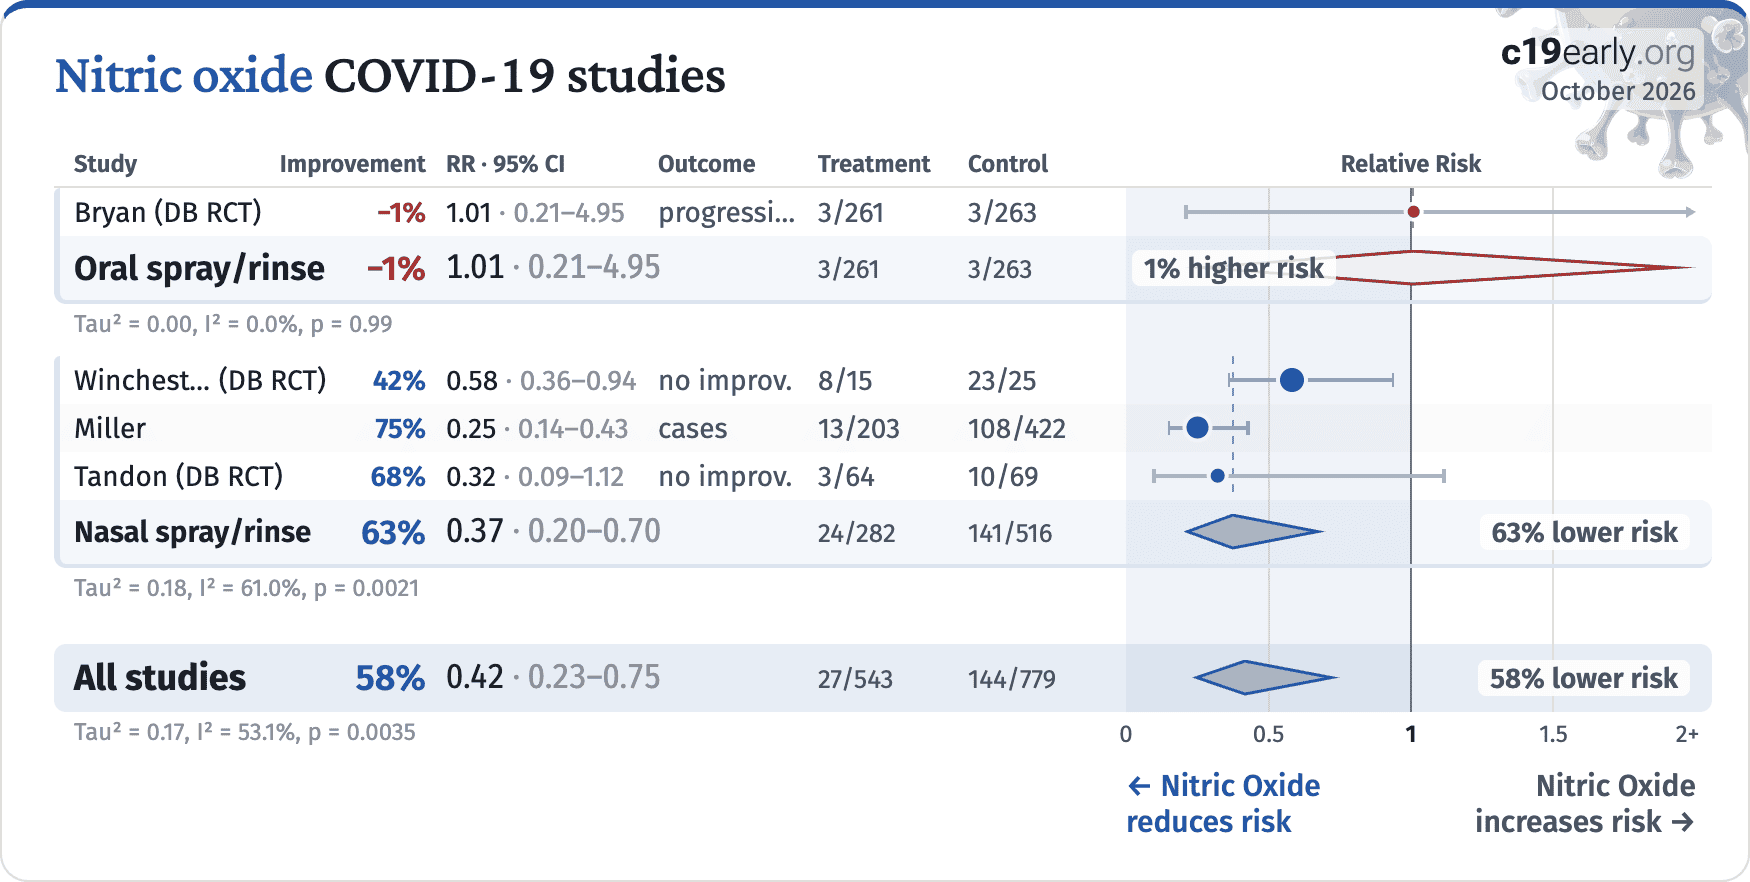
Nitric oxide COVID-19 studies
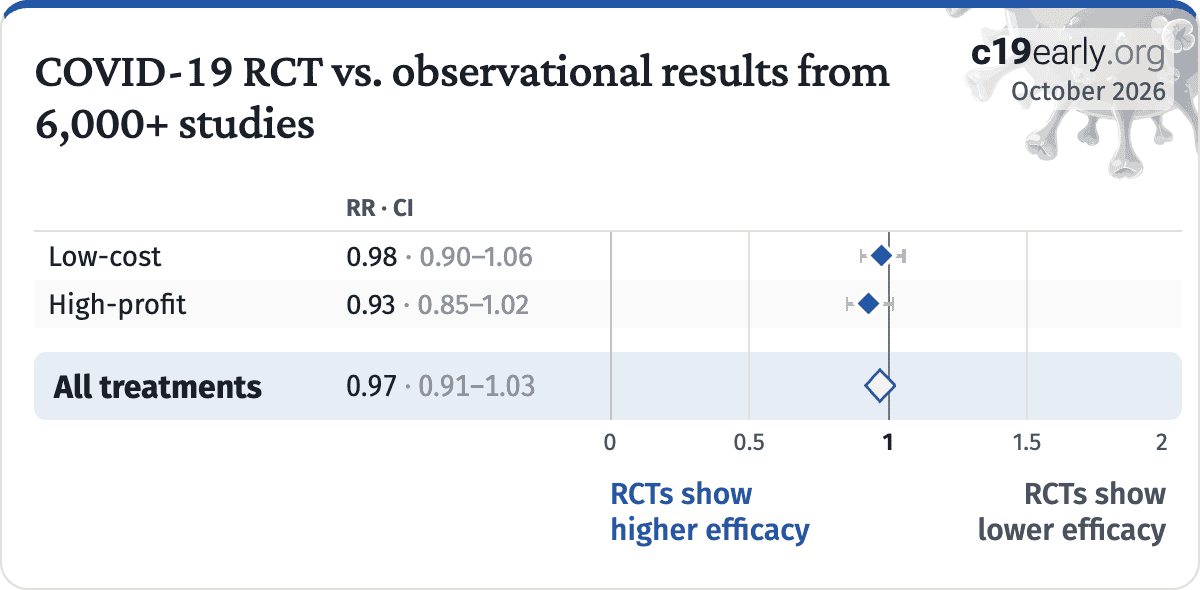
COVID-19 RCT vs. observational results from 6,000+ studies
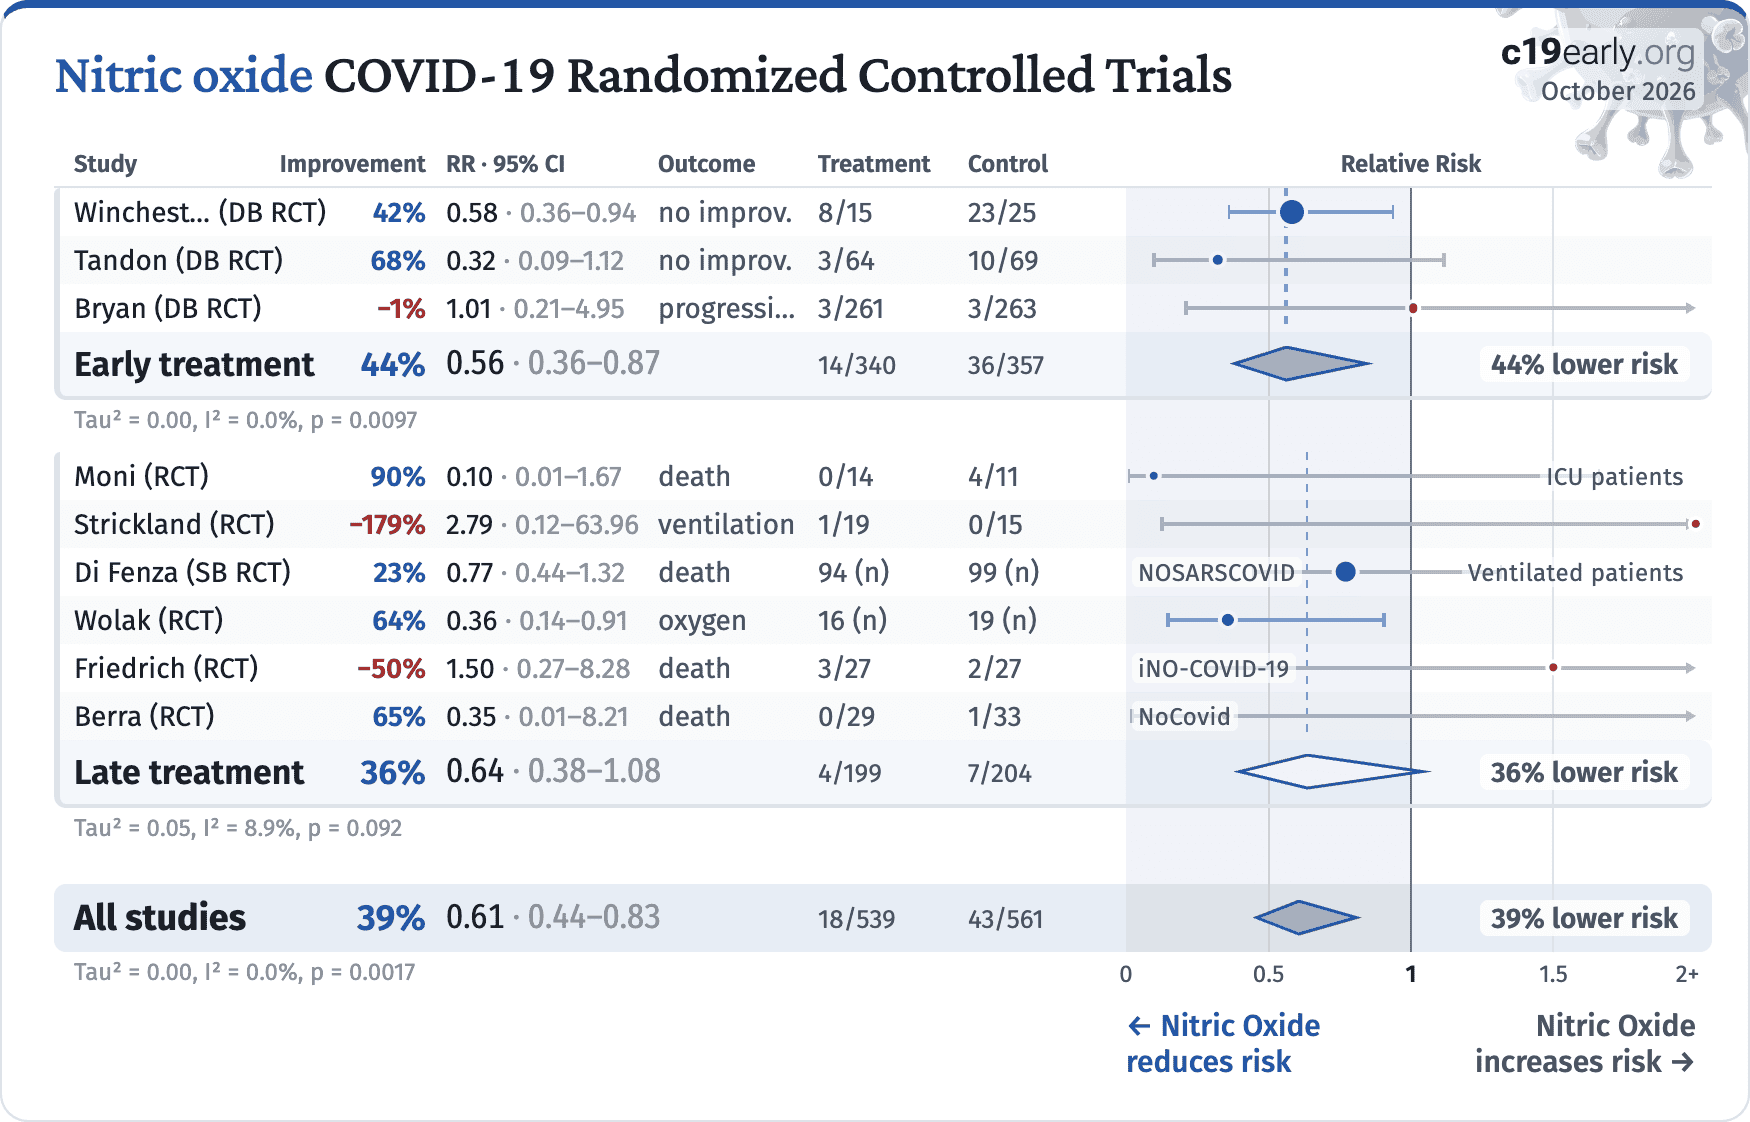
Nitric oxide COVID-19 Randomized Controlled Trials
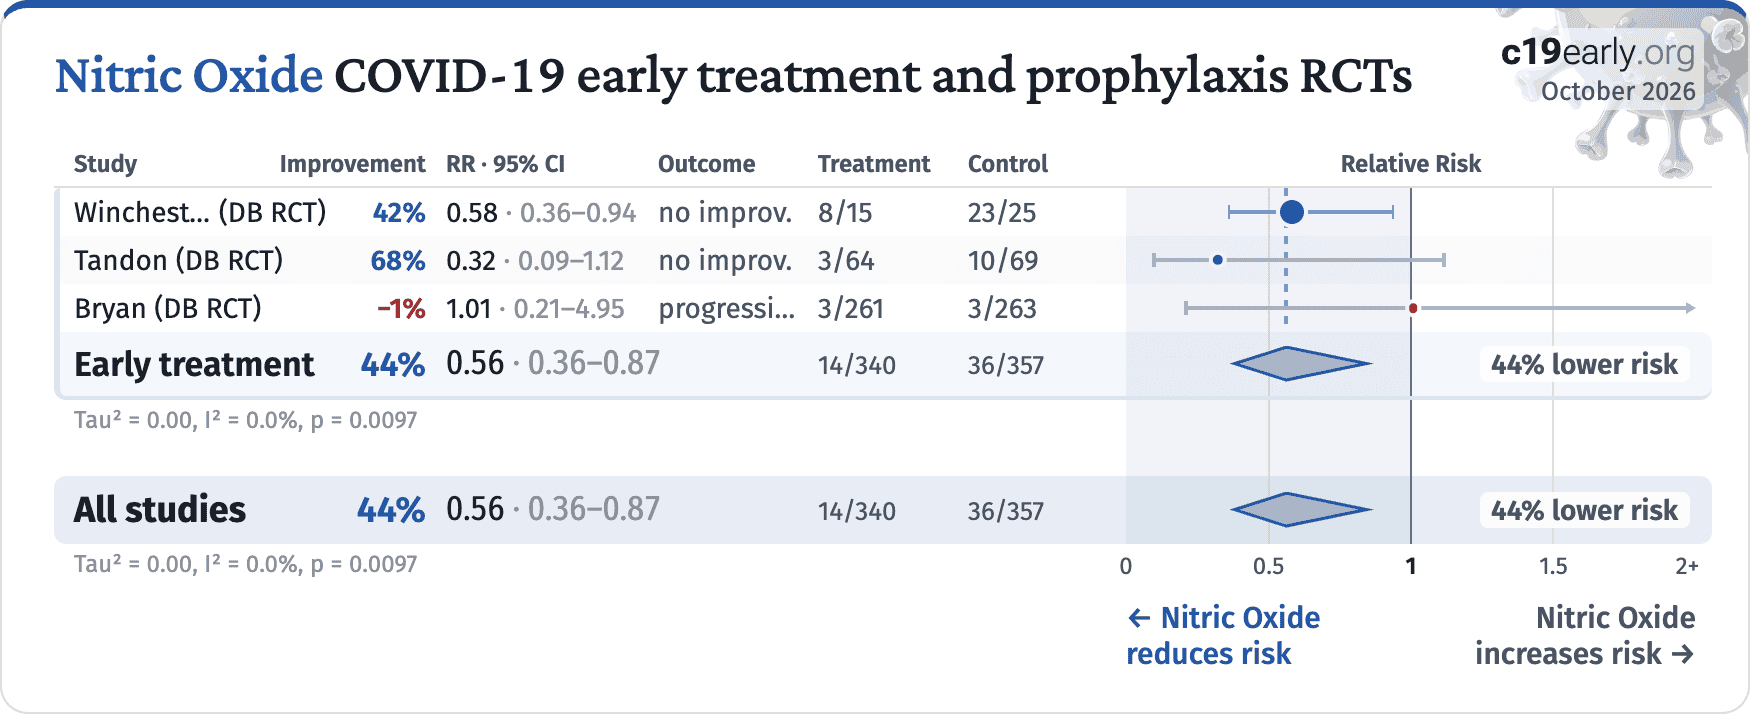
Nitric Oxide COVID-19 early treatment and prophylaxis RCTs
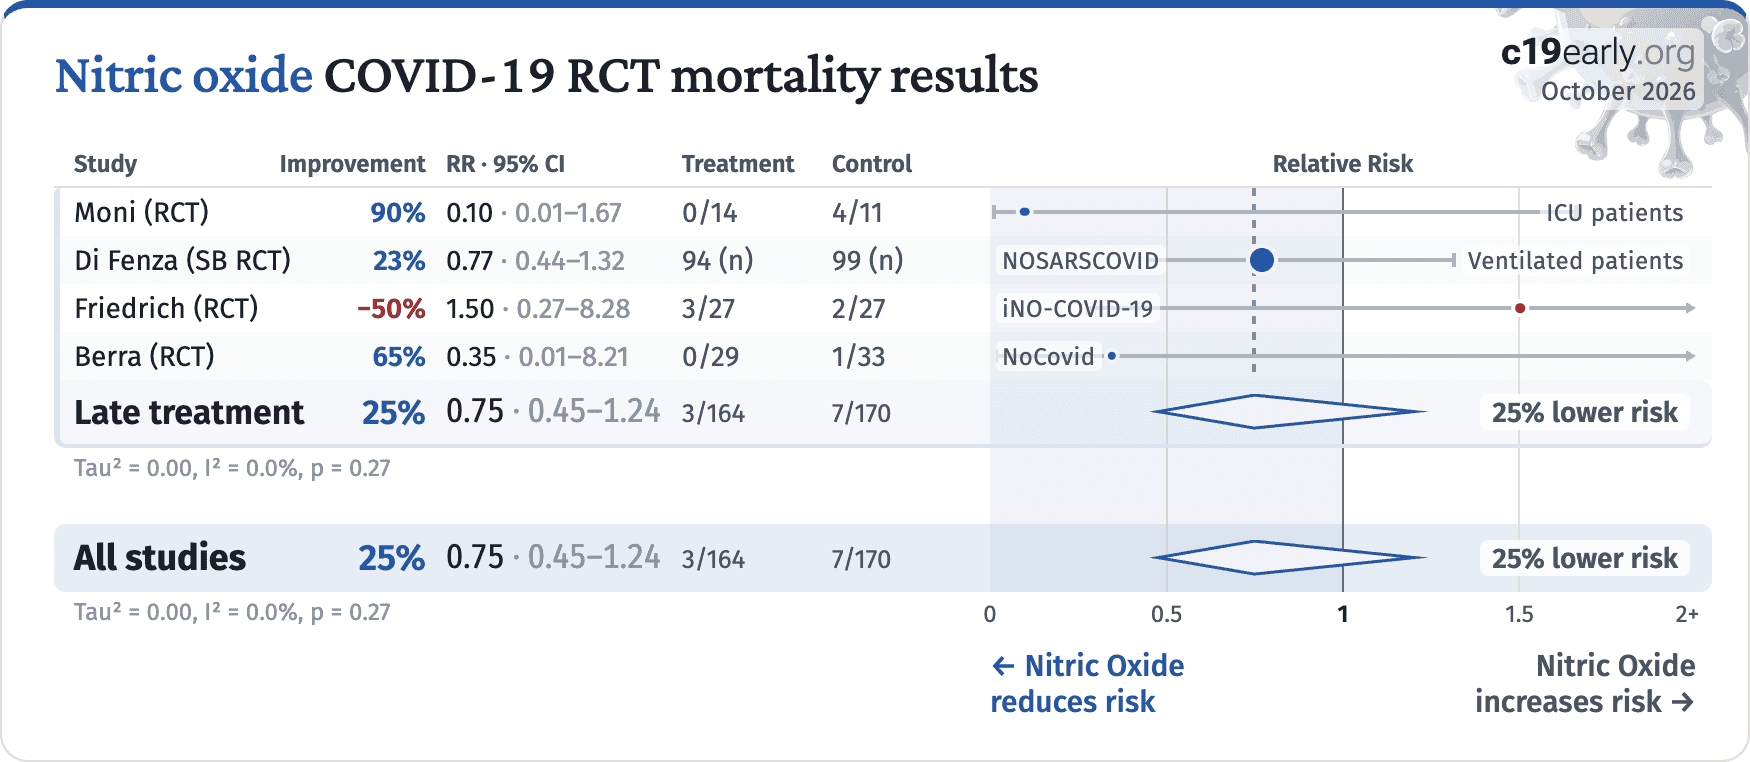
Nitric oxide COVID-19 RCT mortality results
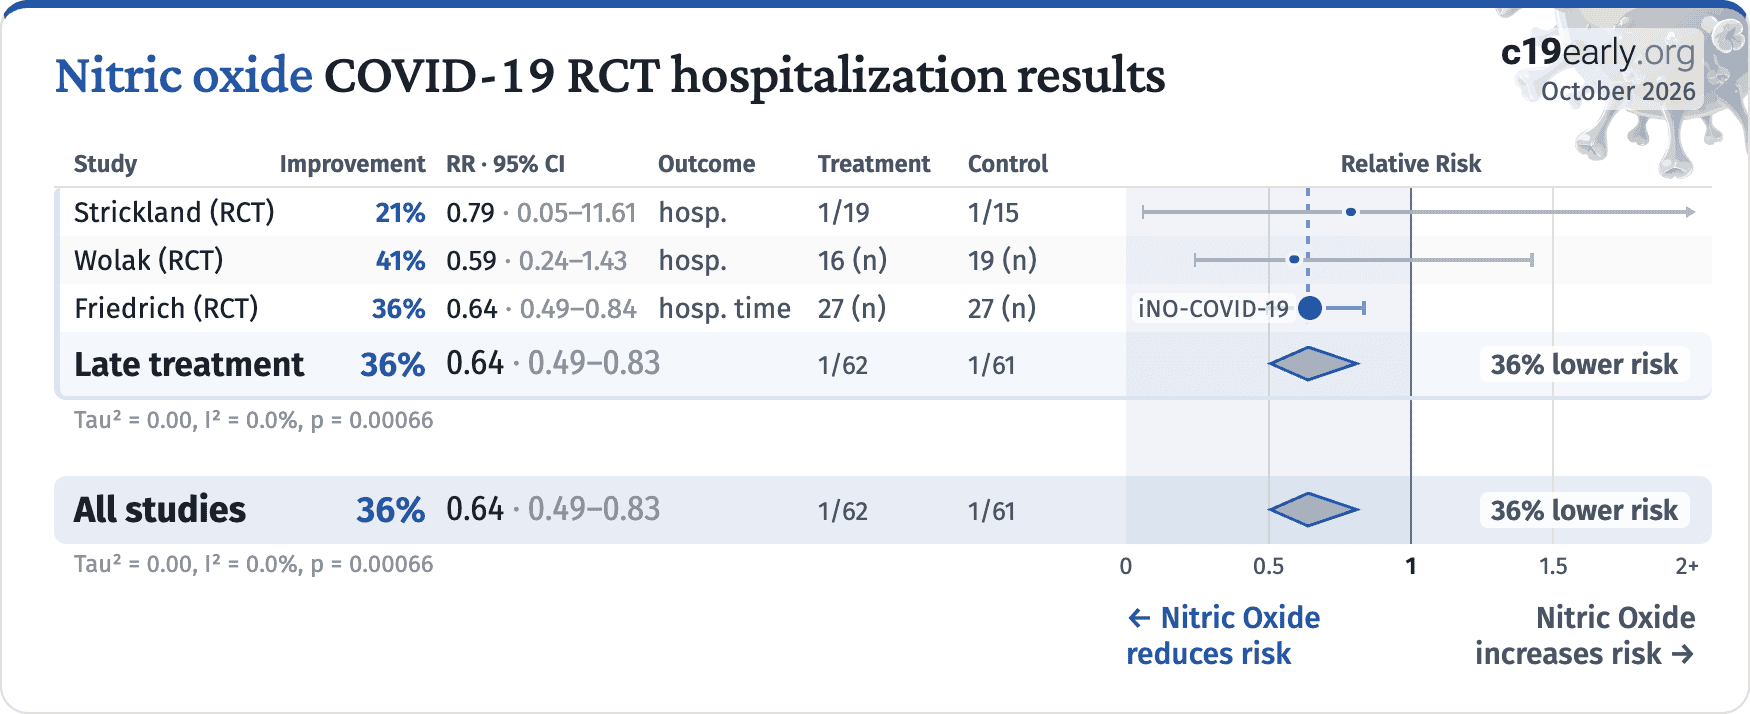
Nitric oxide COVID-19 RCT hospitalization results
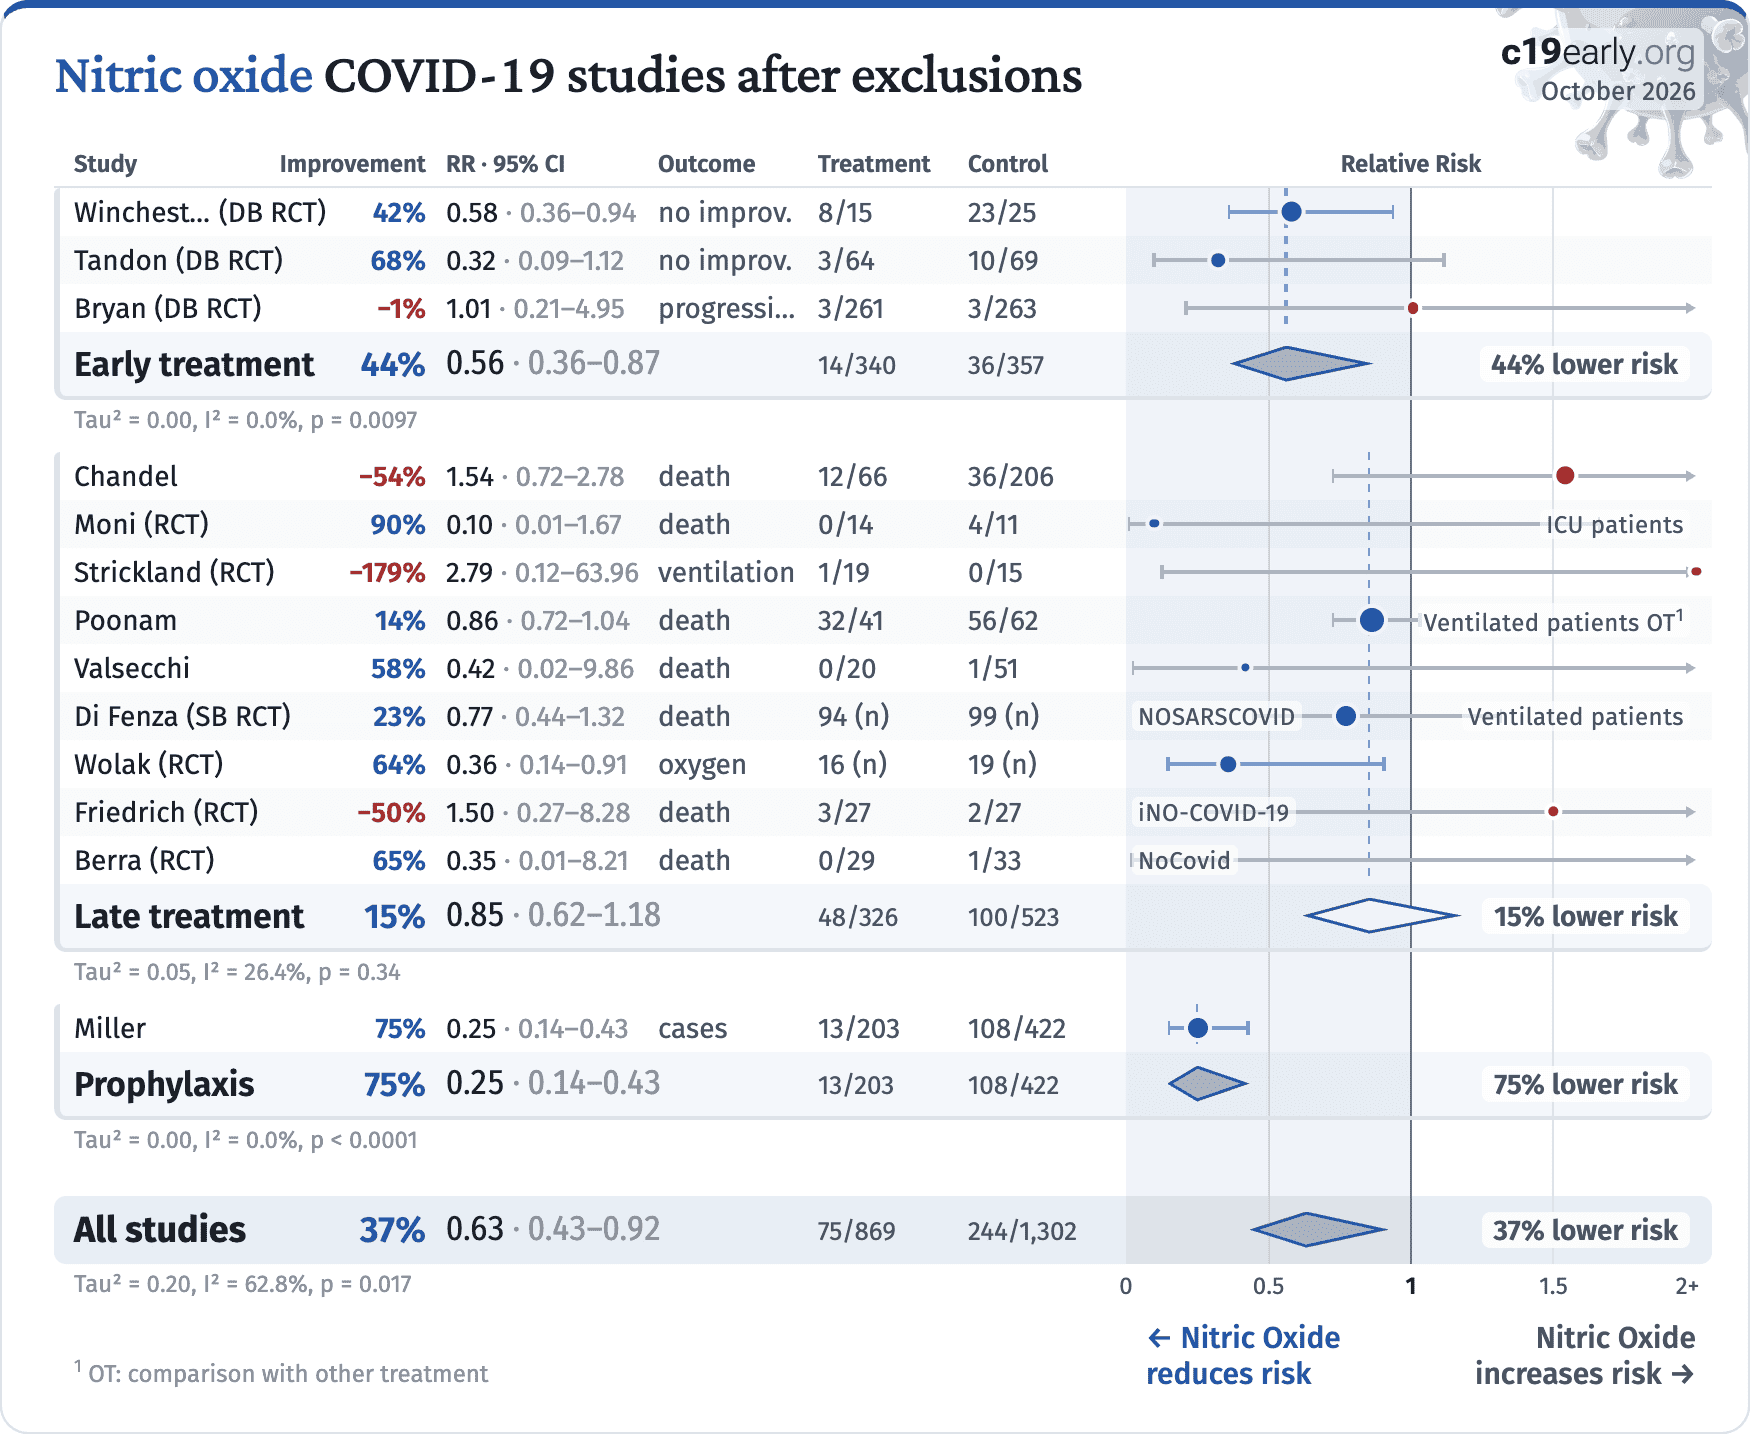
Nitric oxide COVID-19 studies after exclusions
Media coverage of nitric oxide for COVID‑19
Media covered none of the 6 studies showing significantly lower risk
No positive nitric oxide studies were covered
Media bias for low-cost COVID‑19 treatments
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
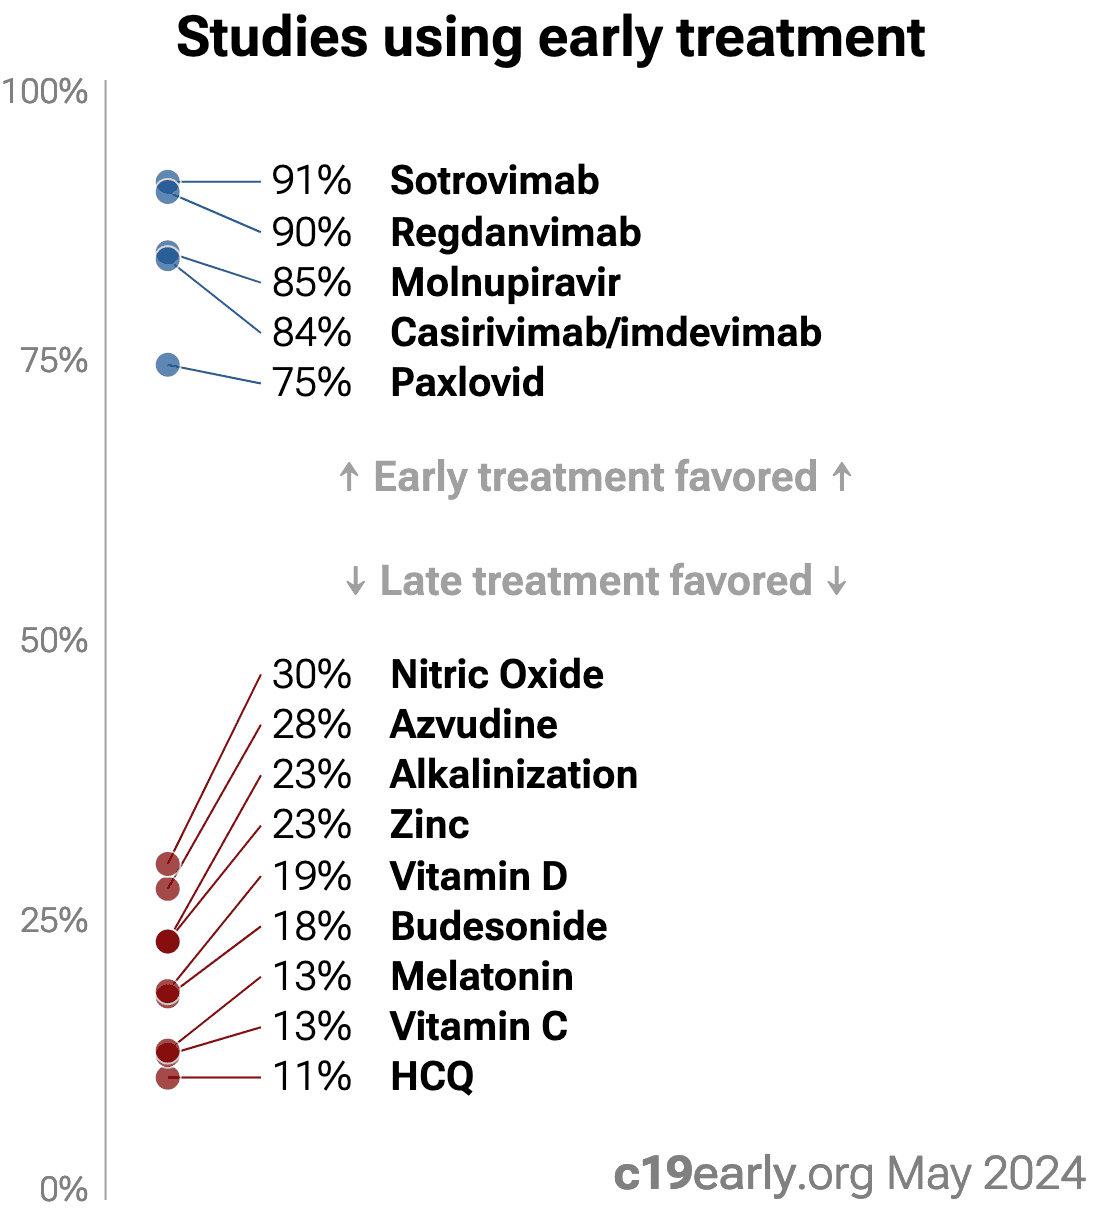
Early treatment is more effective: baloxavir marboxil
| Administration | Improvement | Studies |
|---|---|---|
| Nasal & oral | 88% [72‑95%] | 10 |
| Nasal spray/rinse | 59% [50‑66%] | 21 |
| Oral spray/rinse | 38% [25‑49%] | 11 |
| Virucidal action | Chemically inactivating or destroying the structure of viral particles |
| Blocking attachment | Binding to the virus or host cells to prevent viral attachment to host cells |
| Physical barrier | Forming a physical layer over the nasal mucosa preventing viral access to host cells |
| Physical removal | Mechanical washout/flushing of viral particles and mucus (e.g., large volume irrigation) |
| Mucociliary clearance | Stimulating the natural beating of nasal cilia to accelerate the clearing of trapped pathogens |
| Treatment | Mechanisms | Notes |
|---|---|---|
| Azelastine122 |
Antiviral: inhibits interaction between spike protein and ACE2 Antiviral: potential inhibition of viral protease (Mpro) Other: H1-receptor antagonist (antihistamine) Other: mast cell stabilizer |
Antihistamine. Designed to affect human receptors. Risks include dysgeusia, drowsiness, and nasal burning. |
| Cetylpyridinium Chloride123 |
Virucidal: disrupts viral lipid envelope Antiseptic: quaternary ammonium compound |
Chemical virucide. Common in mouthwashes. Can cause temporary staining of teeth or tongue irritation if used frequently. |
| Chlorhexidine124 |
Virucidal: disrupts viral lipid membranes Antiseptic: cationic polybiguanide |
Chemical virucide. May cause tooth staining and altered taste. |
| Chlorpheniramine125 |
Antiviral: binds to viral spike protein to block entry Antiviral: high affinity for viral transport proteins Other: H1-receptor antagonist (1st generation antihistamine) Other: anticholinergic activity |
Antihistamine. Stronger systemic risks than azelastine. Known to cause significant sedation/drowsiness and cognitive impairment. |
| Hydrogen Peroxide126 |
Virucidal: oxidizing agent that destroys viral parts Other: tissue debridement |
Chemical virucide. Can be toxic to healthy tissue if concentration is too high (>1%). Long-term safety on nasal mucosa is debated. |
| Hypochlorous Acid127 |
Virucidal: oxidizes viral proteins, causing aggregation and loss of function. Impairs spike-ACE2 binding Antiseptic: broad-spectrum antimicrobial activity via oxidative damage to microbial proteins and membranes |
Chemical virucide. Activity depends on concentration, pH, and contact time. Saliva may reduce activity. |
| Inhaled Heparin128 |
Antiviral: acts as a decoy receptor (mimics heparan sulfate) Antiviral: anti-inflammatory effects on lung tissue Other: Anticoagulant |
Anticoagulant. Use requires caution regarding bleeding risks. |
| Iota-carrageenan129 |
Barrier: forms a viscous physical layer on mucosa Trap: electrostatistically traps virus particles (mimics cell surface) |
Physical barrier. High safety profile for daily use. |
| NaCl130 |
Cleaning: physically washes away viral particles Support: moisturizes mucosa to support natural immune barrier |
Physical wash. High degree of safety, reduces viral load via physical removal. |
| Nitric Oxide |
Virucidal: physically damages viral structure via nitrosylation Other: vasodilator (relaxes blood vessels) in systemic use |
Virucide/drug hybrid. In nasal spray form, it acts primarily as a topical disinfectant. Rapidly cleared, so systemic vasodilation risks are low but present. |
| Phthalocyanine131 |
Virucidal: generates reactive oxygen species (ROS) when exposed to light to kill virus Other: photosensitizer |
Chemical virucide. A synthetic compound often used in photodynamic therapy. Works by creating an oxidative environment hostile to the virus. |
| Povidone-Iodine132 |
Virucidal: oxidizes viral proteins and destabilizes membrane structures Antiseptic: broad-spectrum bacterial/fungal killer |
Chemical virucide. Highly effective but risk of thyroid absorption with chronic use. Can be irritating to mucous membranes. |
| Sodium Bicarbonate133 |
Environment: raises pH to inhibit viral fusion Cleaning: improves mucociliary clearance (washing) |
Physical/chemical environment. Changes the environment rather than attacking the virus directly. High degree of safety. |
| Treatment | Microbiome disruption potential | Notes |
|---|---|---|
| Iota-carrageenan129 | Low | Primarily antiviral, however extended use may mildly affect the microbiome |
| Nitric Oxide | Low to moderate | More selective towards pathogens, however excessive concentrations or prolonged use may disrupt the balance of bacteria |
| Alkalinization136 | Moderate | Increases pH, negatively impacting beneficial microbes that thrive in a slightly acidic environment |
| Cetylpyridinium Chloride123 | Moderate | Quaternary ammonium broad-spectrum antiseptic that can disrupt beneficial and harmful bacteria |
| Hypochlorous Acid127 | Moderate | Broad-spectrum oxidizing antiseptic that may affect beneficial and harmful bacteria |
| Phthalocyanine131 | Moderate to high | Photodynamic compound with antimicrobial activity, likely to affect the microbiome |
| Chlorhexidine124 | High | Potent antiseptic with broad activity, significantly disrupts the microbiome |
| Hydrogen Peroxide126 | High | Strong oxidizer, harming both beneficial and harmful microbes |
| Povidone-Iodine132 | High | Potent broad-spectrum antiseptic harmful to beneficial microbes |
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
Enrollment number inconsistencies: the abstract reports 27+27 randomized with 1 excluded; the results text says 28 were allocated to iNO; the flowchart shows 54 randomized as 27+27.
Percentage calculation errors: vaccination rates (70.8% and 66.7%) correspond to a denominator of 24, not the reported 27 per group, suggesting unreported missing data.
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →
reduces riskNitric Oxide
increases risk →

| Bryan, 6/24/2023, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 3 authors, study period 1 November, 2020 - 30 November, 2022, trial NCT04601077 (history). | risk of progression, 0.8% higher, RR 1.01, p = 1.00, treatment 3 of 261 (1.1%), control 3 of 263 (1.1%), combined hospitalization, ICU admission, intubation, dialysis, and death. |
| recovery time, 11.2% lower, relative time 0.89, p = 0.30, treatment 261, control 263. | |
| Tandon, 6/29/2022, Double Blind Randomized Controlled Trial, placebo-controlled, India, peer-reviewed, 10 authors, study period 10 August, 2021 - 25 January, 2022, trial CTRI/2021/08. | risk of no improvement, 67.7% lower, RR 0.32, p = 0.08, treatment 3 of 64 (4.7%), control 10 of 69 (14.5%), NNT 10, mITT high risk, day 18. |
| risk of no improvement, 66.8% lower, RR 0.33, p = 0.04, treatment 4 of 64 (6.2%), control 13 of 69 (18.8%), NNT 7.9, mITT high risk, day 16. | |
| risk of no improvement, 41.9% lower, RR 0.58, p = 0.06, treatment 14 of 64 (21.9%), control 26 of 69 (37.7%), NNT 6.3, mITT high risk, day 8. | |
| risk of no improvement, 22.3% lower, RR 0.78, p = 0.63, treatment 8 of 105 (7.6%), control 10 of 102 (9.8%), NNT 46, day 18, modified intention-to-treat. | |
| risk of no improvement, 17.8% lower, RR 0.82, p = 0.67, treatment 11 of 105 (10.5%), control 13 of 102 (12.7%), NNT 44, day 16, modified intention-to-treat. | |
| risk of no improvement, 8.9% lower, RR 0.91, p = 0.76, treatment 30 of 105 (28.6%), control 32 of 102 (31.4%), NNT 36, day 8, modified intention-to-treat. | |
| viral load, 19.8% lower, relative load 0.80, p < 0.001, treatment mean 2.62 (±0.14) n=64, control mean 2.1 (±0.14) n=69, mITT high risk, day 8. | |
| viral load, 13.5% lower, relative load 0.86, p < 0.001, treatment mean 2.51 (±0.11) n=105, control mean 2.17 (±0.12) n=102, day 8, modified intention-to-treat. | |
| time to viral-, 26.1% lower, relative time 0.74, p = 0.09, treatment 64, control 69, inverted to make RR<1 favor treatment, mITT high risk, Kaplan-Meier. | |
| time to viral-, 6.5% lower, relative time 0.94, p = 0.66, treatment 105, control 102, inverted to make RR<1 favor treatment, Kaplan-Meier, modified intention-to-treat. | |
| Winchester, 5/13/2021, Double Blind Randomized Controlled Trial, placebo-controlled, United Kingdom, peer-reviewed, 4 authors, study period 15 December, 2020 - 31 March, 2021. | risk of no improvement, 42.0% lower, RR 0.58, p = 0.008, treatment 8 of 15 (53.3%), control 23 of 25 (92.0%), NNT 2.6. |
| viral load, 51.3% lower, relative load 0.49, p = 0.001, treatment 40, control 40, AUC relative mean change. |
| Berra, 3/23/2026, Randomized Controlled Trial, USA, preprint, 1 author, trial NCT04305457 (history) (NoCovid). | risk of death, 65.3% lower, RR 0.35, p = 1.00, treatment 0 of 29 (0.0%), control 1 of 33 (3.0%), NNT 33, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| risk of mechanical ventilation, 13.8% higher, RR 1.14, p = 1.00, treatment 1 of 29 (3.4%), control 1 of 33 (3.0%). | |
| Chandel, 1/31/2021, retrospective, USA, peer-reviewed, 14 authors, study period 1 March, 2020 - 9 June, 2020. | risk of death, 54.1% higher, RR 1.54, p = 0.25, treatment 12 of 66 (18.2%), control 36 of 206 (17.5%), adjusted per study, odds ratio converted to relative risk, multivariable. |
| risk of mechanical ventilation, 27.2% higher, RR 1.27, p = 0.26, treatment 29 of 66 (43.9%), control 79 of 206 (38.3%), adjusted per study, odds ratio converted to relative risk, multivariable. | |
| Di Fenza, 12/15/2023, Single Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 54 authors, study period 22 March, 2020 - 21 May, 2021, trial NCT04306393 (history) (NOSARSCOVID). | risk of death, 23.0% lower, RR 0.77, p = 0.36, treatment 94, control 99, including additional covariates with SMD > 0.20, day 90, Table E1. |
| risk of death, 26.0% lower, RR 0.74, p = 0.36, treatment 94, control 99, including additional covariates with SMD > 0.20, day 28, Table E1. | |
| risk of death, 13.0% lower, RR 0.87, p = 0.60, treatment 94, control 99, day 90. | |
| risk of death, 15.0% lower, RR 0.85, p = 0.56, treatment 94, control 99, day 28. | |
| VV-ECMO, 30.0% lower, RR 0.70, p = 0.67, treatment 94, control 99. | |
| neurological symptoms, 83.0% lower, RR 0.17, p = 0.01, treatment 94, control 99, day 90. | |
| Friedrich, 2/6/2025, Randomized Controlled Trial, Brazil, peer-reviewed, median age 55.0, 20 authors, study period November 2020 - March 2022, trial RBR-8nfx26 (iNO-COVID-19). | risk of death, 50.0% higher, RR 1.50, p = 1.00, treatment 3 of 27 (11.1%), control 2 of 27 (7.4%). |
| risk of oxygen therapy, 50.0% lower, RR 0.50, p = 0.09, treatment 7 of 27 (25.9%), control 14 of 27 (51.9%), NNT 3.9, day 7. | |
| risk of oxygen therapy, 35.0% lower, RR 0.65, p = 0.09, treatment 13 of 27 (48.1%), control 20 of 27 (74.1%), NNT 3.9, day 5. | |
| risk of oxygen therapy, 30.8% lower, RR 0.69, p = 0.01, treatment 18 of 27 (66.7%), control 26 of 27 (96.3%), NNT 3.4, day 3. | |
| risk of progression, no change, RR 1.00, p = 1.00, treatment 5 of 27 (18.5%), control 5 of 27 (18.5%). | |
| hospitalization time, 35.7% lower, relative time 0.64, p = 0.001, treatment median 4.5 IQR 3.3 n=27, control median 7.0 IQR 4.0 n=27. | |
| Kurnik, 2/11/2025, retrospective, Slovenia, peer-reviewed, mean age 76.8, 3 authors, study period October 2020 - April 2021, excluded in exclusion analyses: unadjusted results with no group details. | risk of death, 22.7% lower, RR 0.77, p = 0.33, treatment 3 of 5 (60.0%), control 97 of 125 (77.6%), NNT 5.7, day 1000. |
| Moni, 4/20/2021, Randomized Controlled Trial, India, peer-reviewed, 16 authors, study period September 2020 - December 2020, average treatment delay 6.78 days, trial ISRCTN16806663. | risk of death, 90.1% lower, RR 0.10, p = 0.03, treatment 0 of 14 (0.0%), control 4 of 11 (36.4%), NNT 2.8, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28. |
| risk of mechanical ventilation, 90.1% lower, RR 0.10, p = 0.03, treatment 0 of 14 (0.0%), control 4 of 11 (36.4%), NNT 2.8, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 28. | |
| risk of <2 point WOS improvement, 42.5% better, RR 0.58, p = 0.47, treatment 3 of 14 (21.4%), control 7 of 11 (63.6%), NNT 2.4, adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, day 14. | |
| time to viral load reduction, 64.4% lower, RR 0.36, p = 0.005, treatment 14, control 11, adjusted per study, inverted to make RR<1 favor treatment, N gene. | |
| time to viral load reduction, 63.4% lower, RR 0.37, p = 0.005, treatment 14, control 11, adjusted per study, inverted to make RR<1 favor treatment, Orf1ab gene. | |
| Poonam, 6/27/2022, retrospective, USA, peer-reviewed, 5 authors, study period 1 March, 2020 - 30 June, 2020, this trial compares with another treatment - results may be better when compared to placebo. | risk of death, 13.6% lower, RR 0.86, p = 0.10, treatment 32 of 41 (78.0%), control 56 of 62 (90.3%), NNT 8.1. |
| Strickland, 5/4/2022, Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 8 authors. | risk of mechanical ventilation, 178.9% higher, RR 2.79, p = 1.00, treatment 1 of 19 (5.3%), control 0 of 15 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm). |
| risk of hospitalization, 21.1% lower, RR 0.79, p = 1.00, treatment 1 of 19 (5.3%), control 1 of 15 (6.7%), NNT 71. | |
| return to ER, 38.2% higher, RR 1.38, p = 0.72, treatment 7 of 19 (36.8%), control 4 of 15 (26.7%). | |
| Valsecchi, 7/7/2022, retrospective, Israel, peer-reviewed, 20 authors, study period March 2020 - December 2021. | risk of death, 58.2% lower, RR 0.42, p = 1.00, treatment 0 of 20 (0.0%), control 1 of 51 (2.0%), NNT 51, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| risk of mechanical ventilation, 68.1% lower, RR 0.32, p = 0.08, treatment 2 of 20 (10.0%), control 16 of 51 (31.4%), NNT 4.7. | |
| risk of ICU admission, 39.3% lower, RR 0.61, p = 0.28, treatment 5 of 20 (25.0%), control 21 of 51 (41.2%), NNT 6.2. | |
| Wolak, 7/26/2024, Randomized Controlled Trial, Israel, peer-reviewed, 7 authors. | oxygen support time, 64.3% lower, HR 0.36, p = 0.03, treatment 16, control 19, inverted to make HR<1 favor treatment, Cox proportional hazards. |
| time to SpO2≥93, 81.5% lower, HR 0.19, p = 0.049, treatment 16, control 19, inverted to make HR<1 favor treatment, Cox proportional hazards. | |
| hospitalization time, 41.2% lower, HR 0.59, p = 0.24, treatment 16, control 19, inverted to make HR<1 favor treatment, Cox proportional hazards. |
| Miller, 4/30/2022, retrospective, Thailand, peer-reviewed, 2 authors. | risk of case, 75.0% lower, RR 0.25, p < 0.001, treatment 13 of 203 (6.4%), control 108 of 422 (25.6%), NNT 5.2. |