Nafamostat for COVID-19
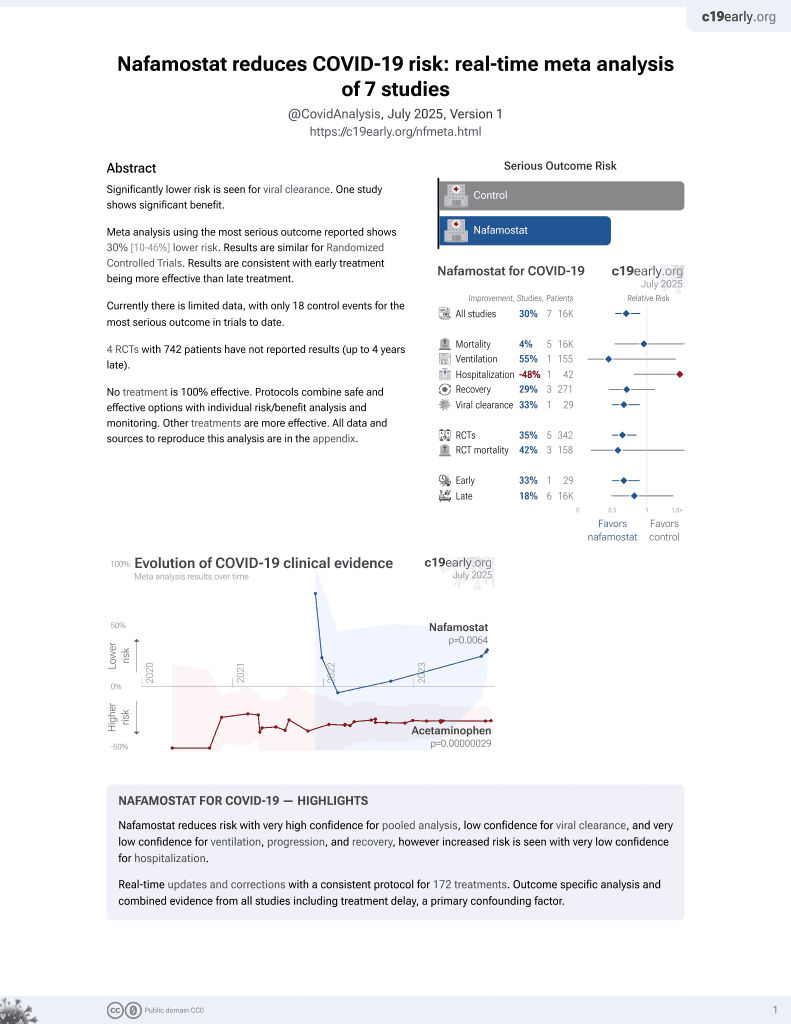
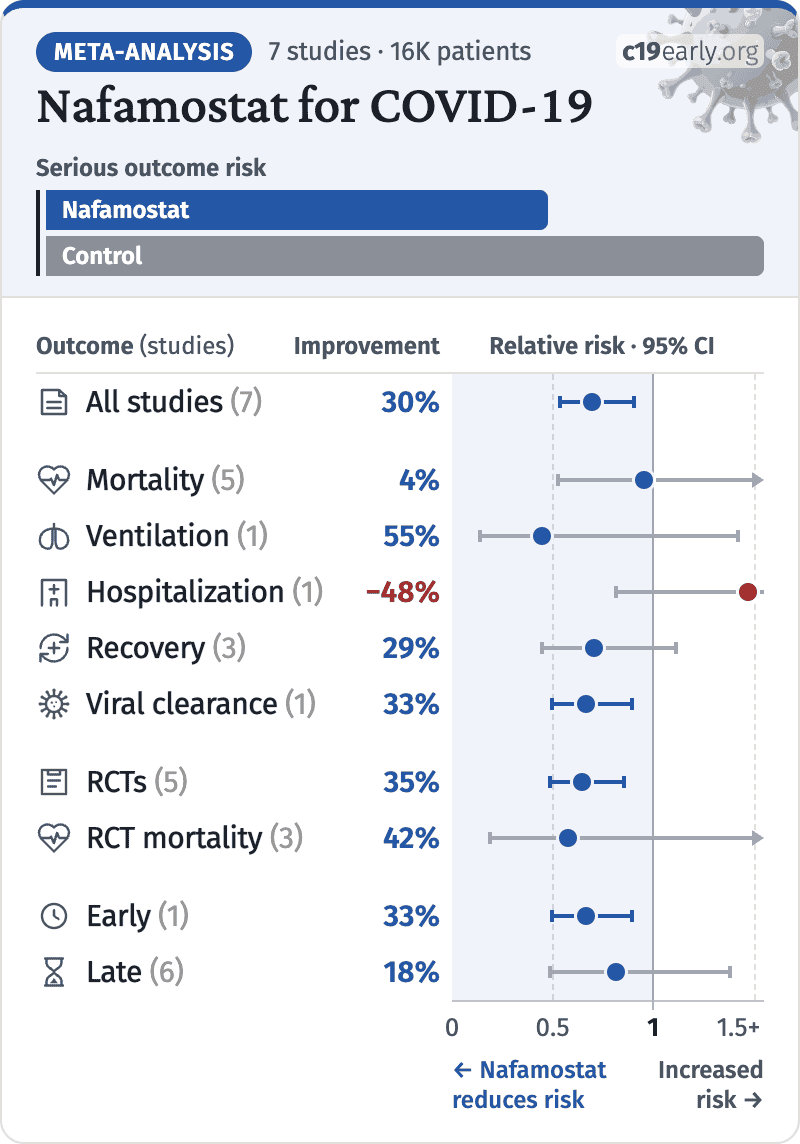
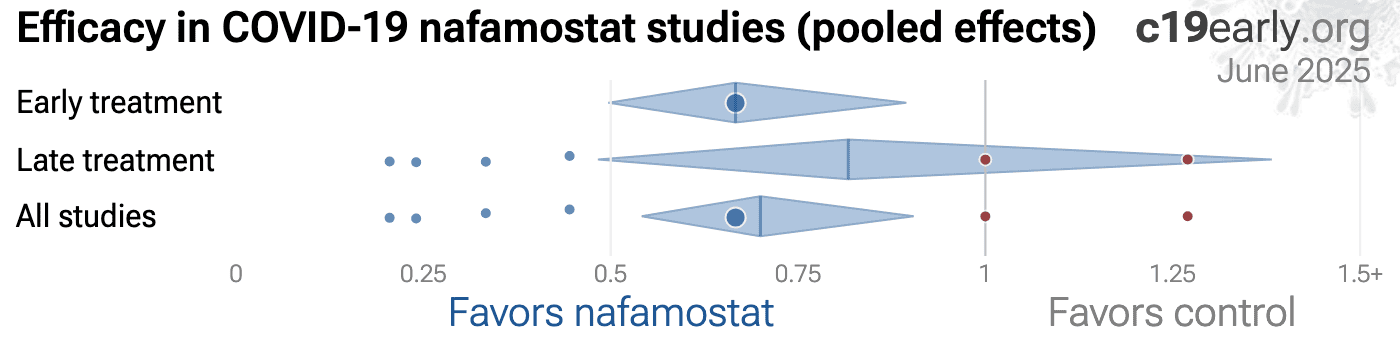
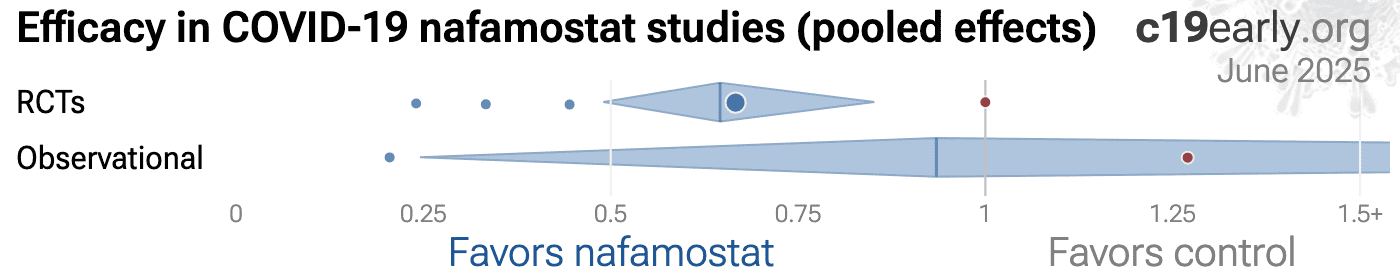
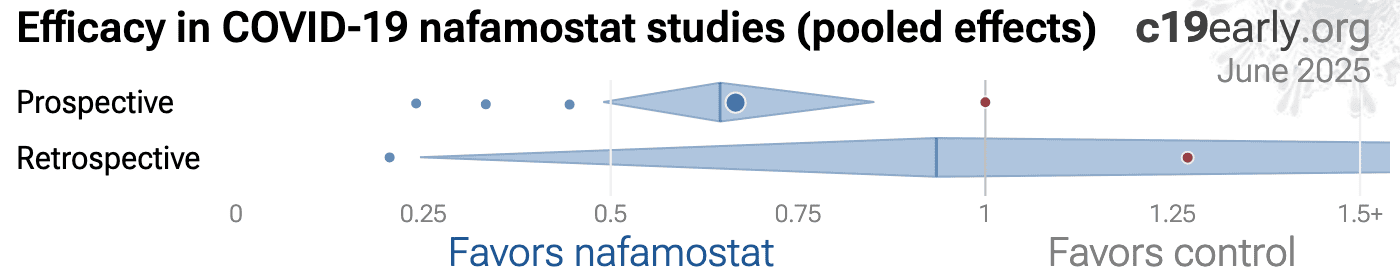
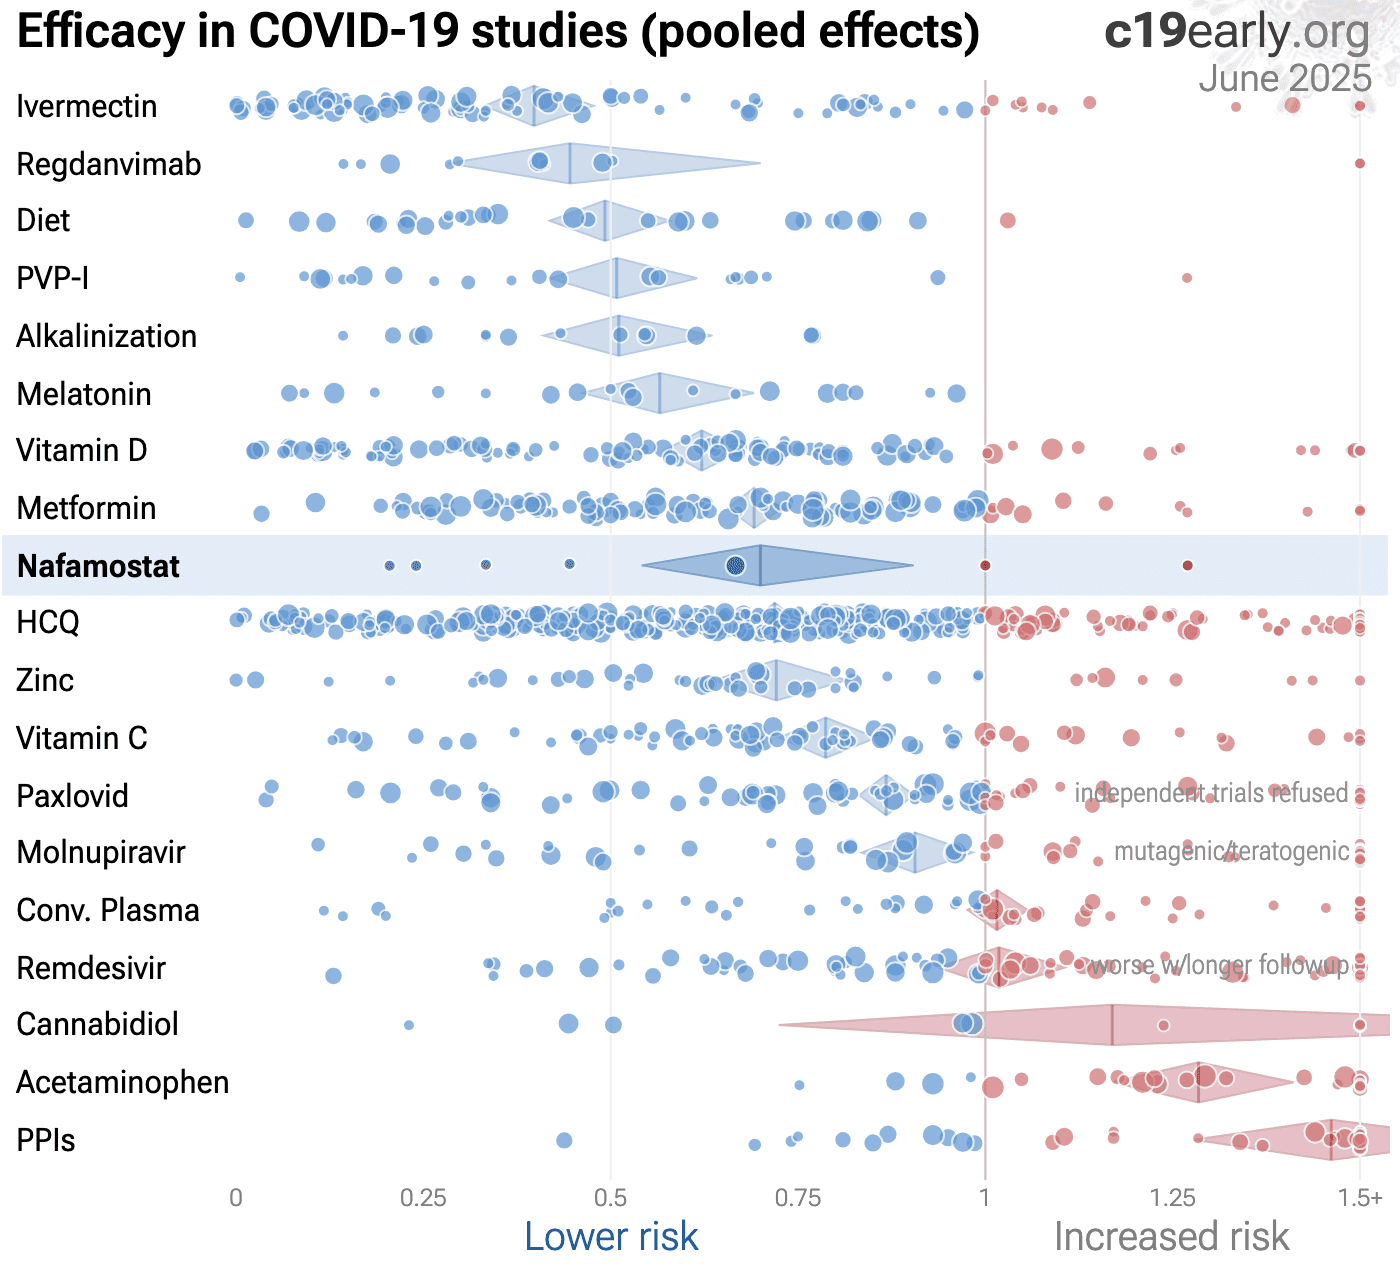
Highlights- Nafamostat reduces risk with very high confidence for pooled analysis, low confidence for viral clearance, and very low confidence for ventilation, progression, and recovery.
- However increased risk is seen with very low confidence for hospitalization.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
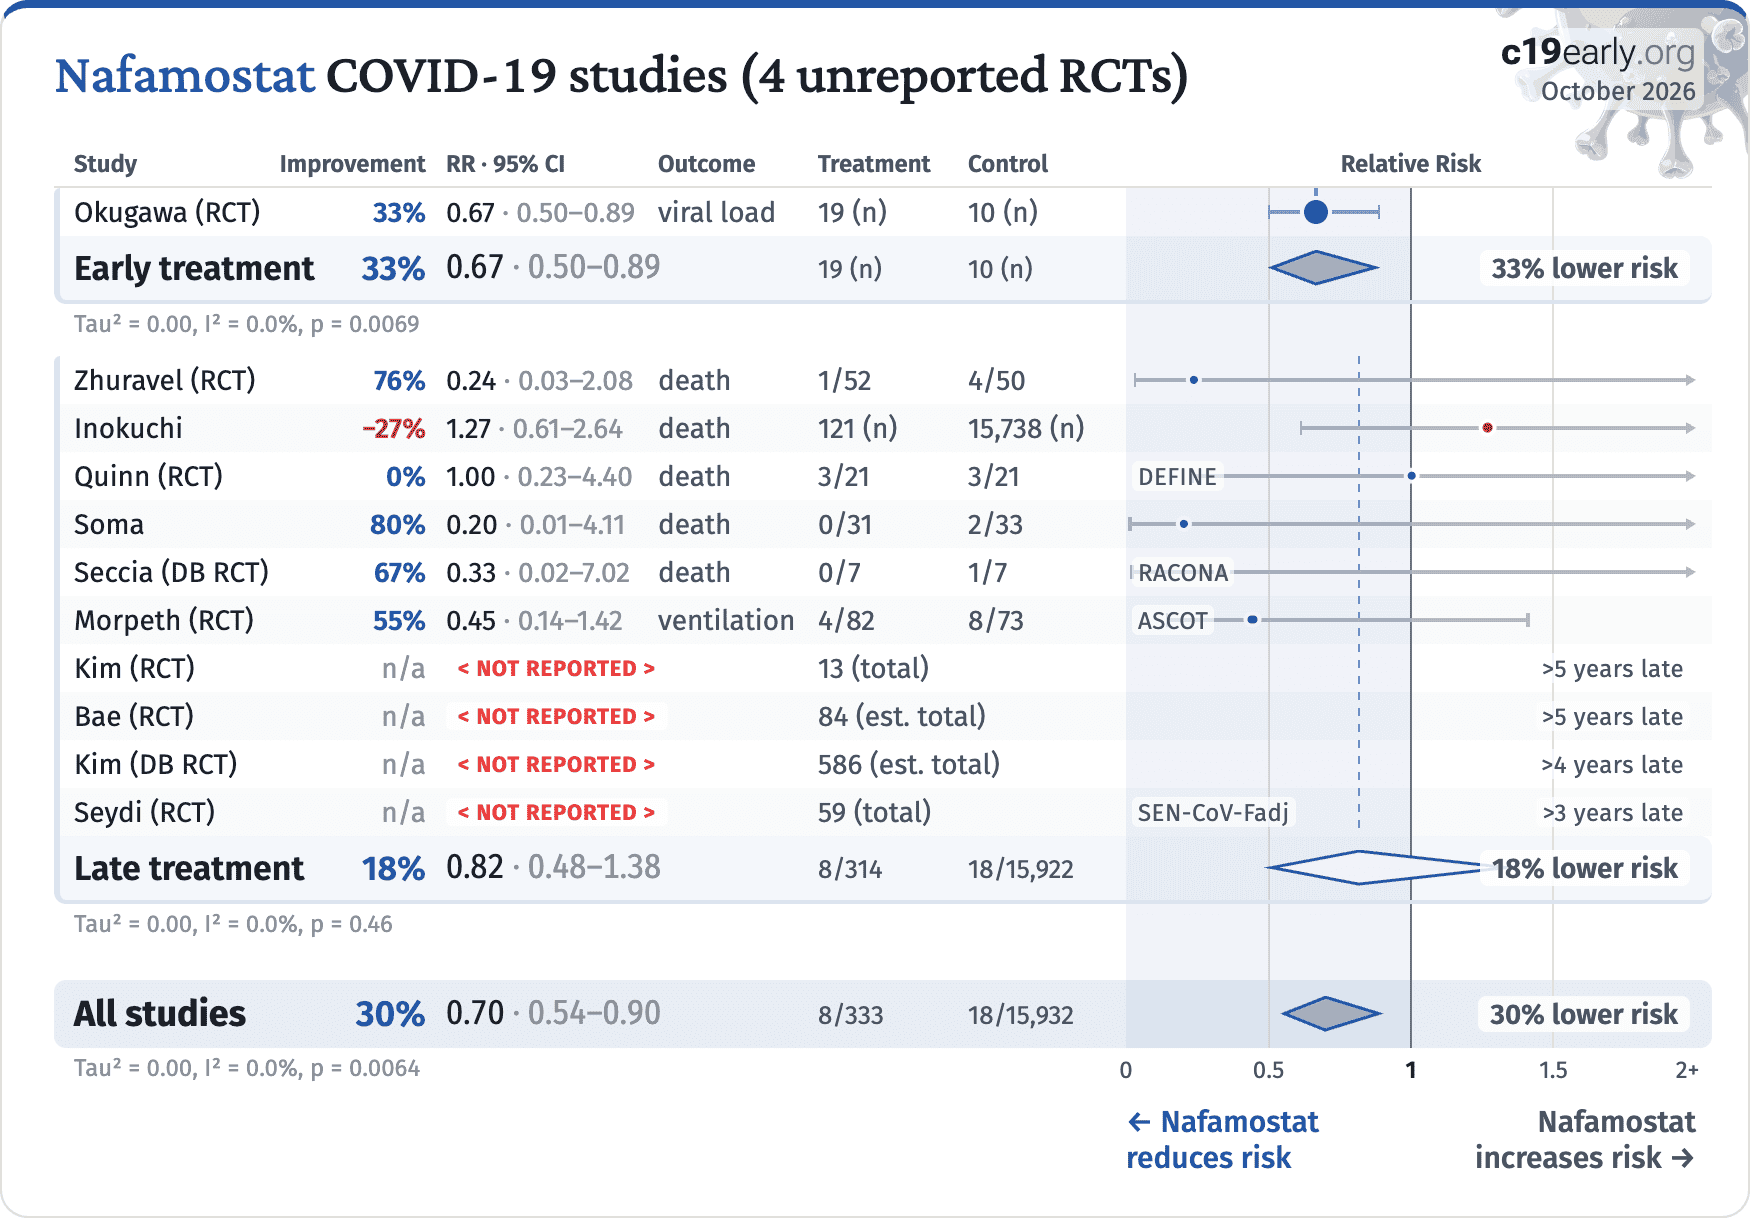
Nafamostat COVID-19 studies (4 unreported RCTs)
Nafamostat for COVID-19: meta-analysis results
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Nafamostat COVID-19 studies (4 unreported RCTs)
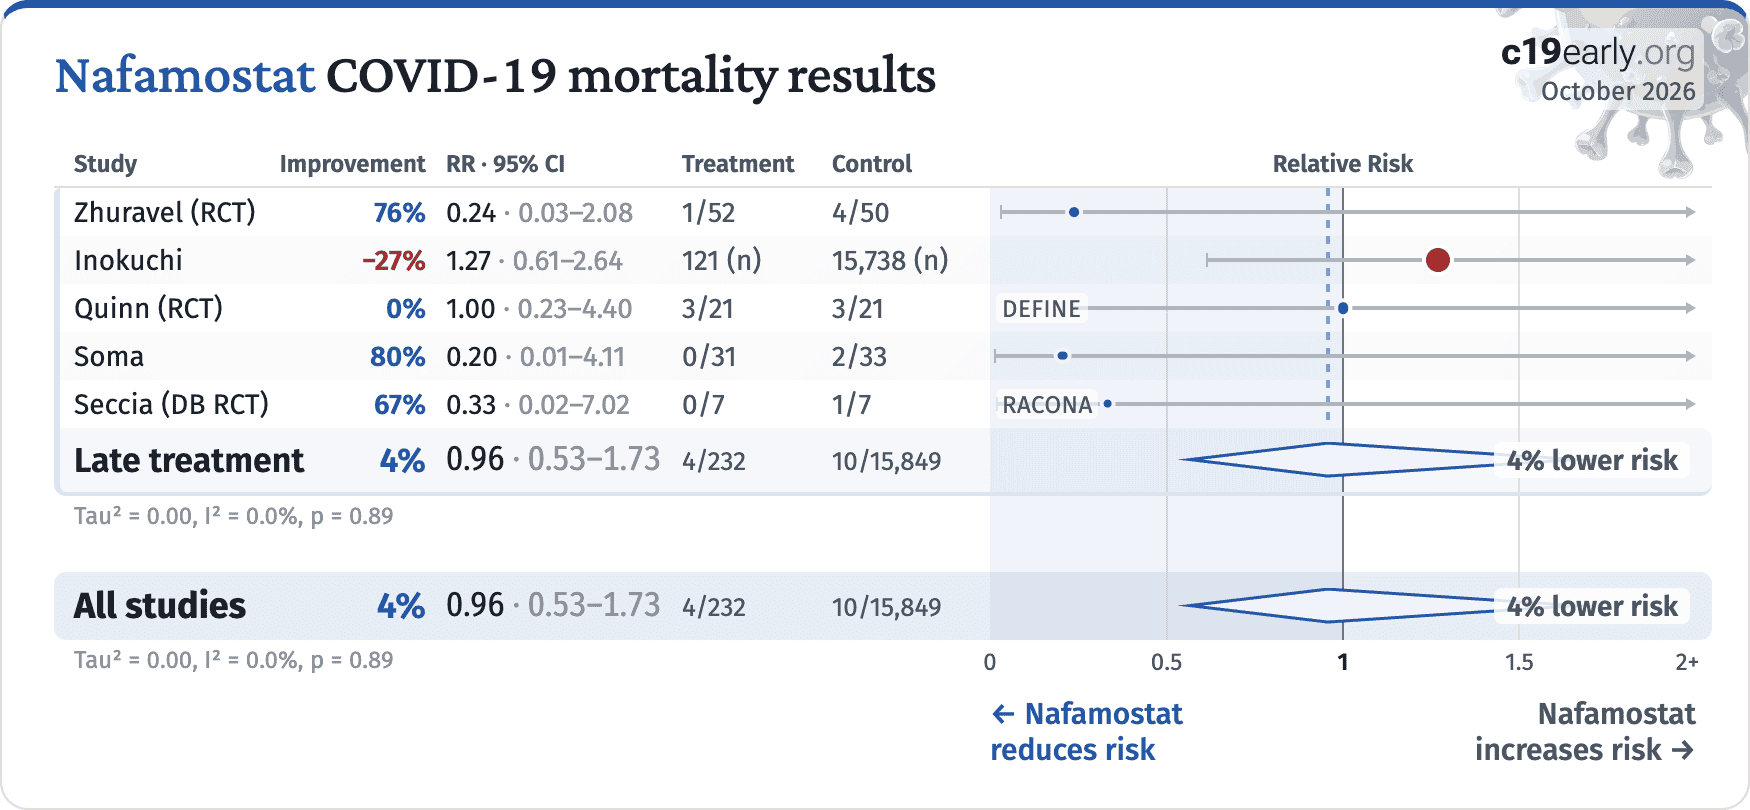
Nafamostat COVID-19 mortality results
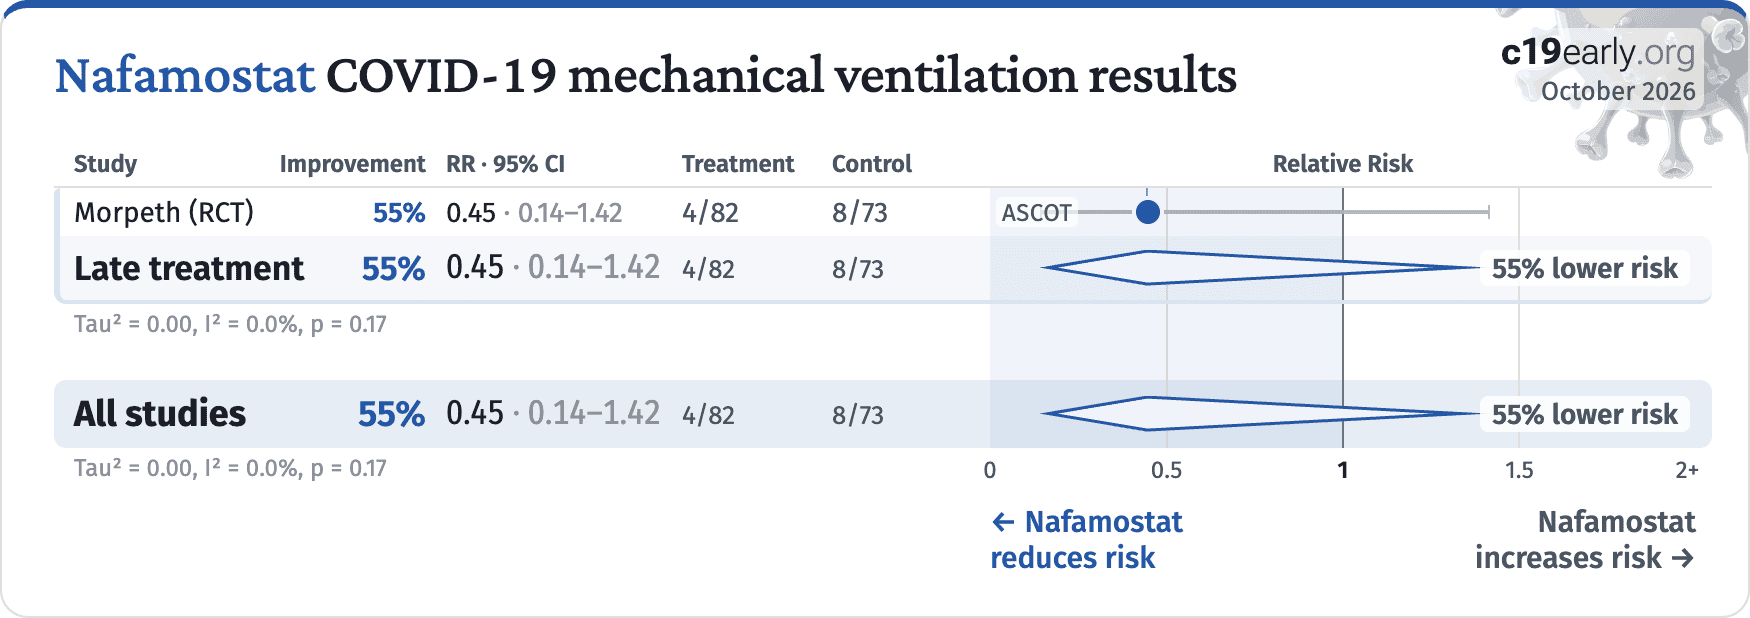
Nafamostat COVID-19 mechanical ventilation results
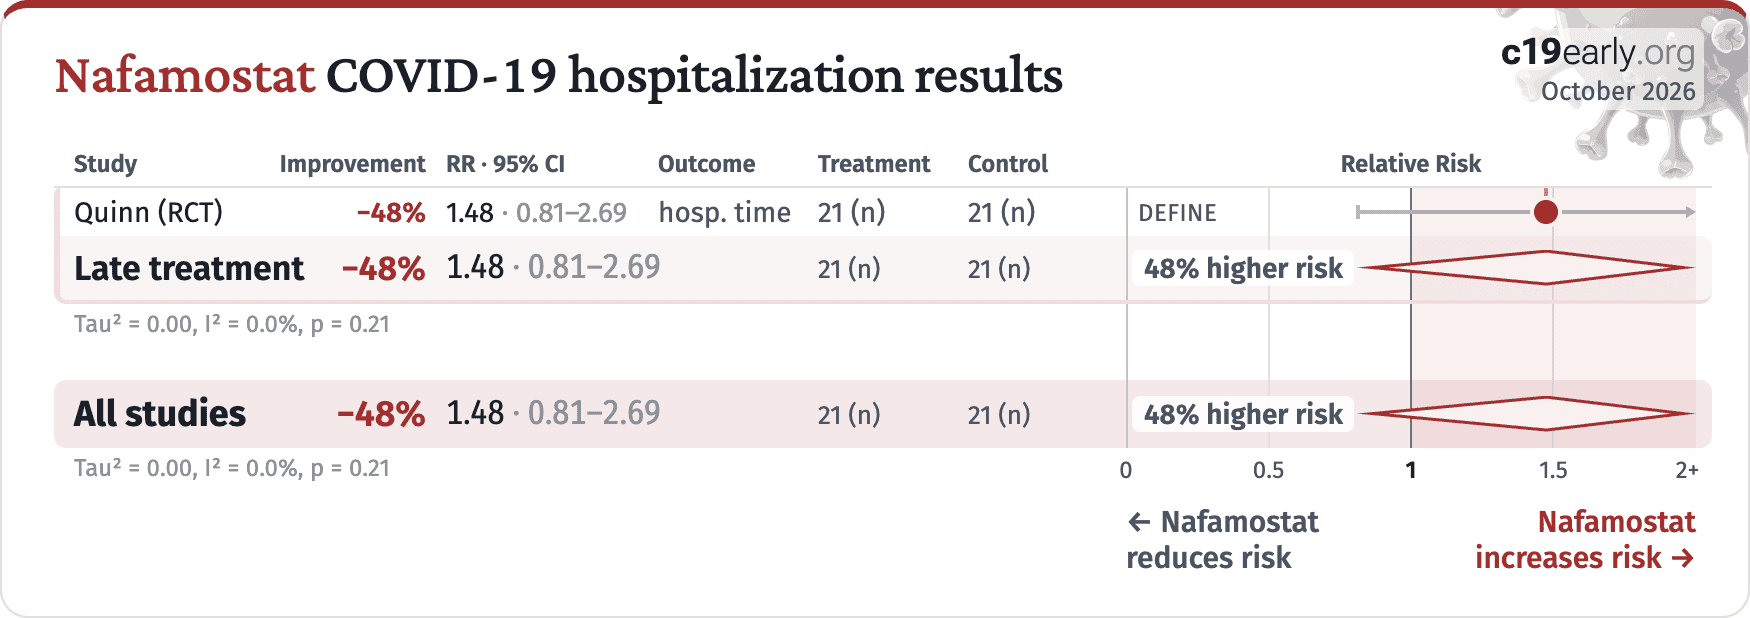
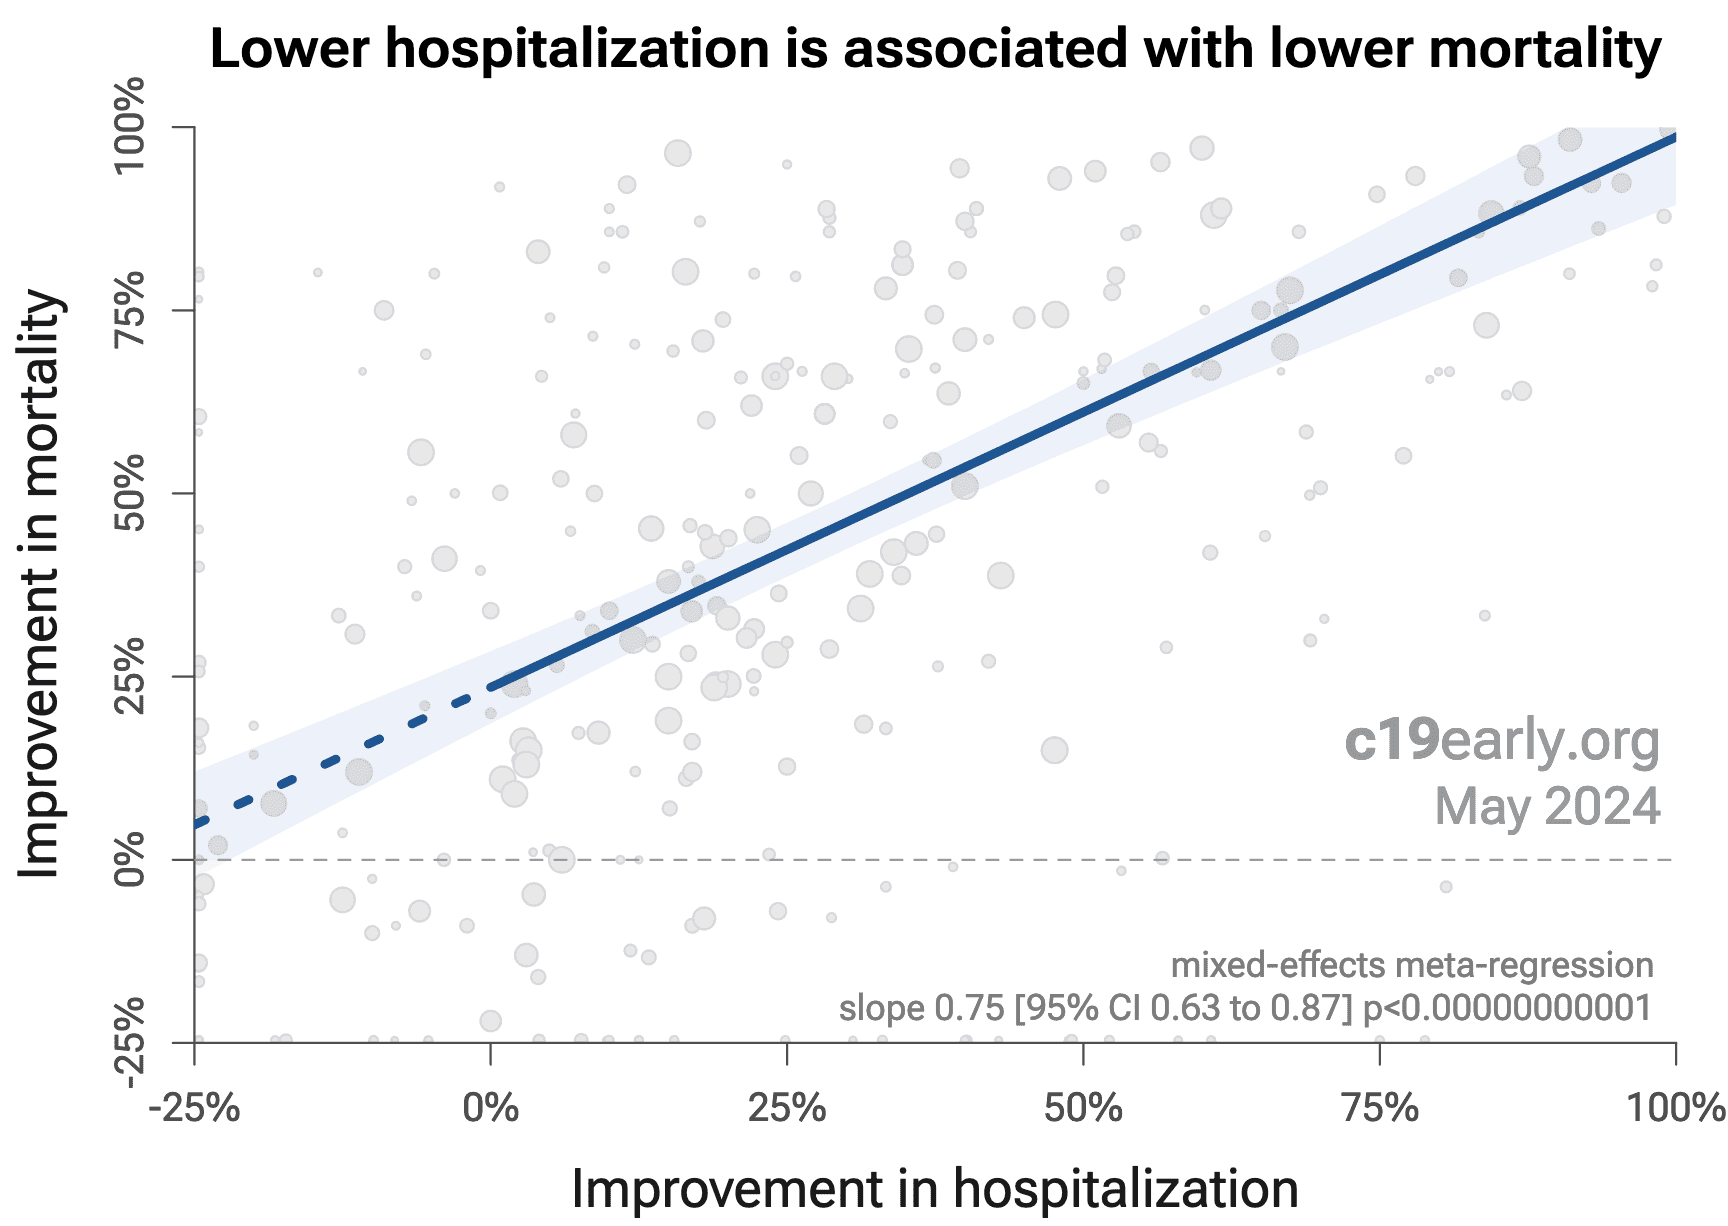
Nafamostat COVID-19 hospitalization results
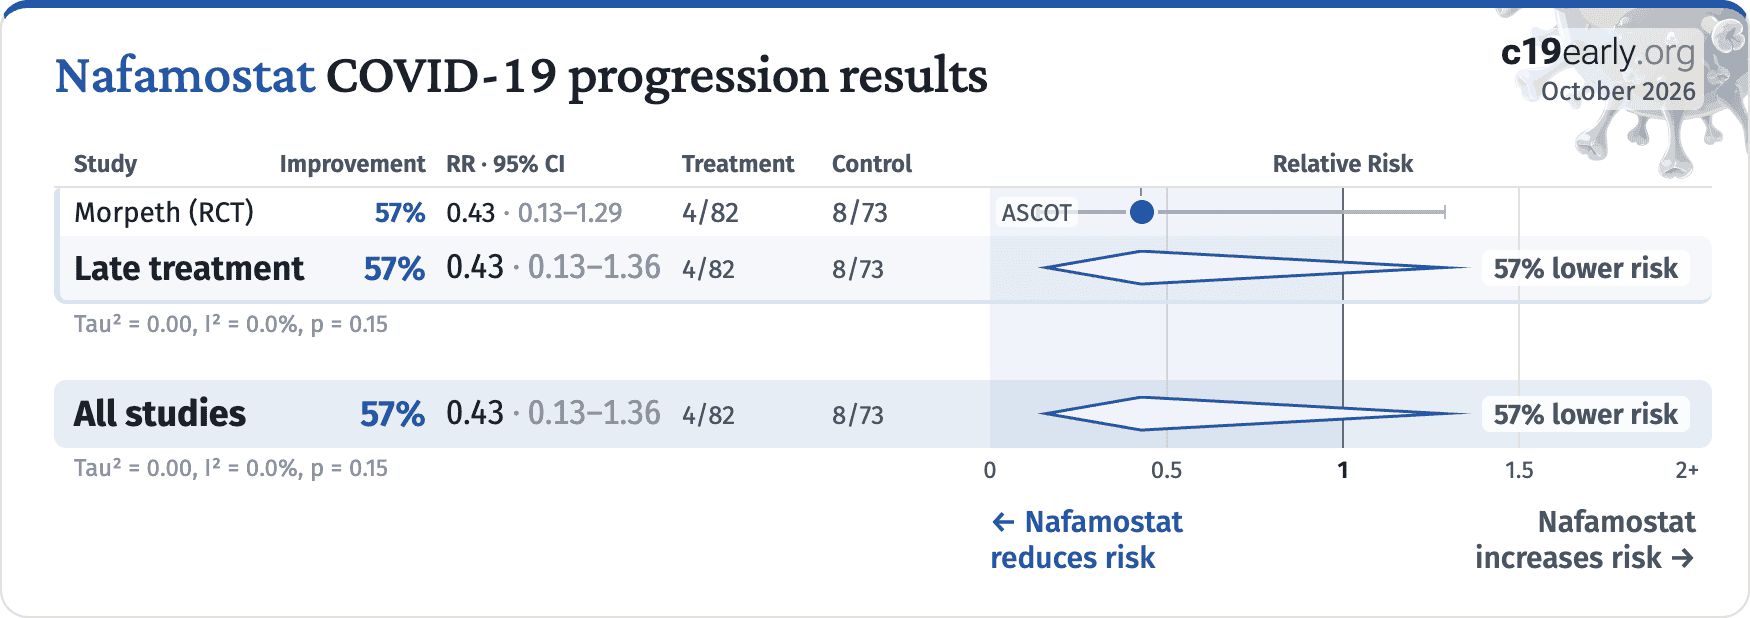
Nafamostat COVID-19 progression results
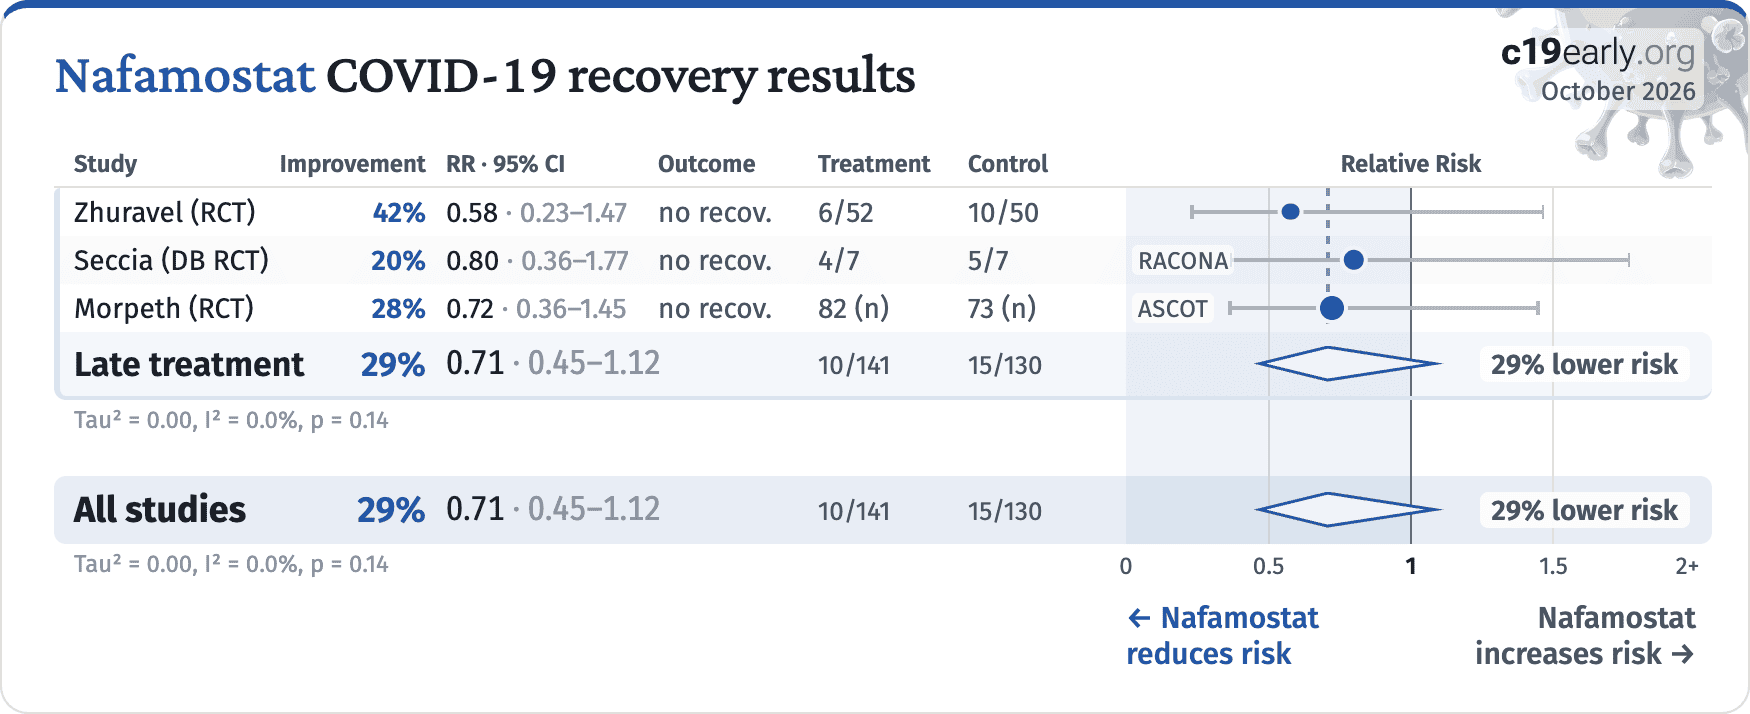
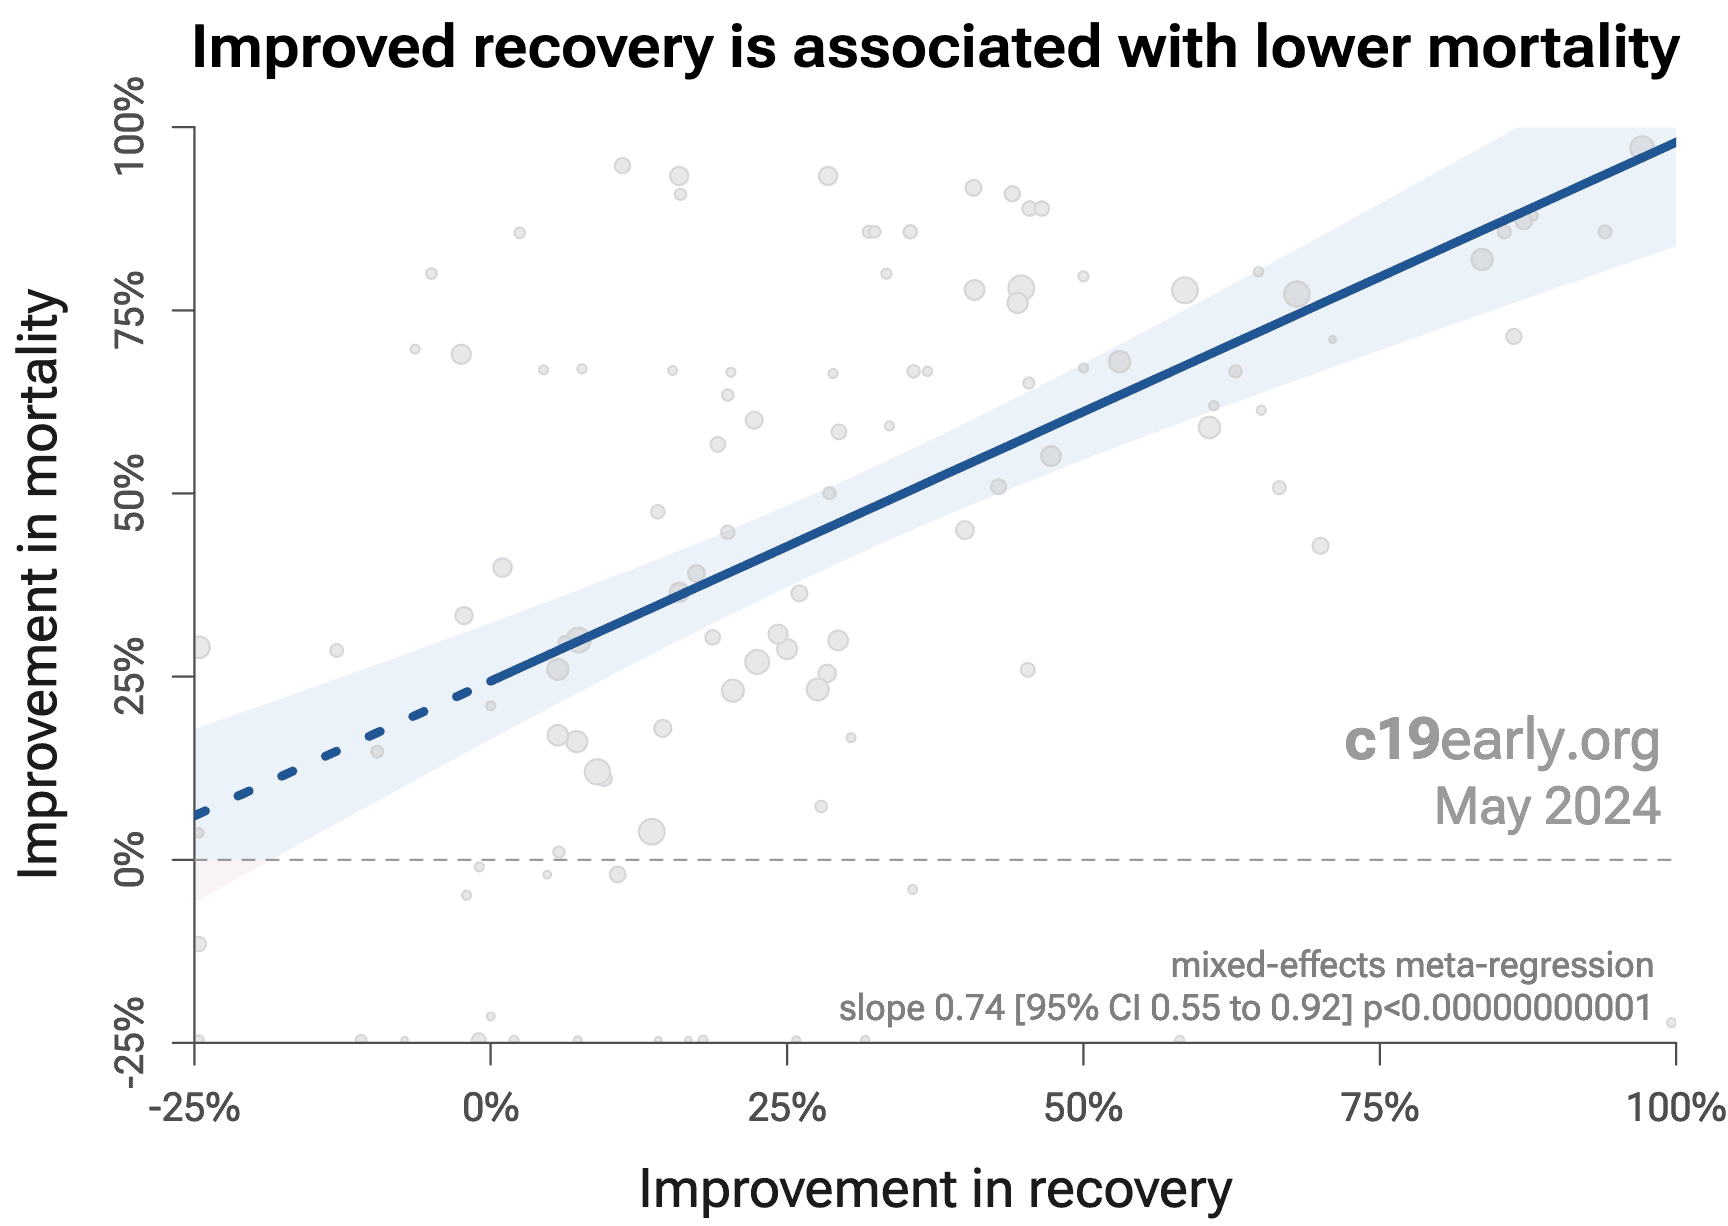
Nafamostat COVID-19 recovery results
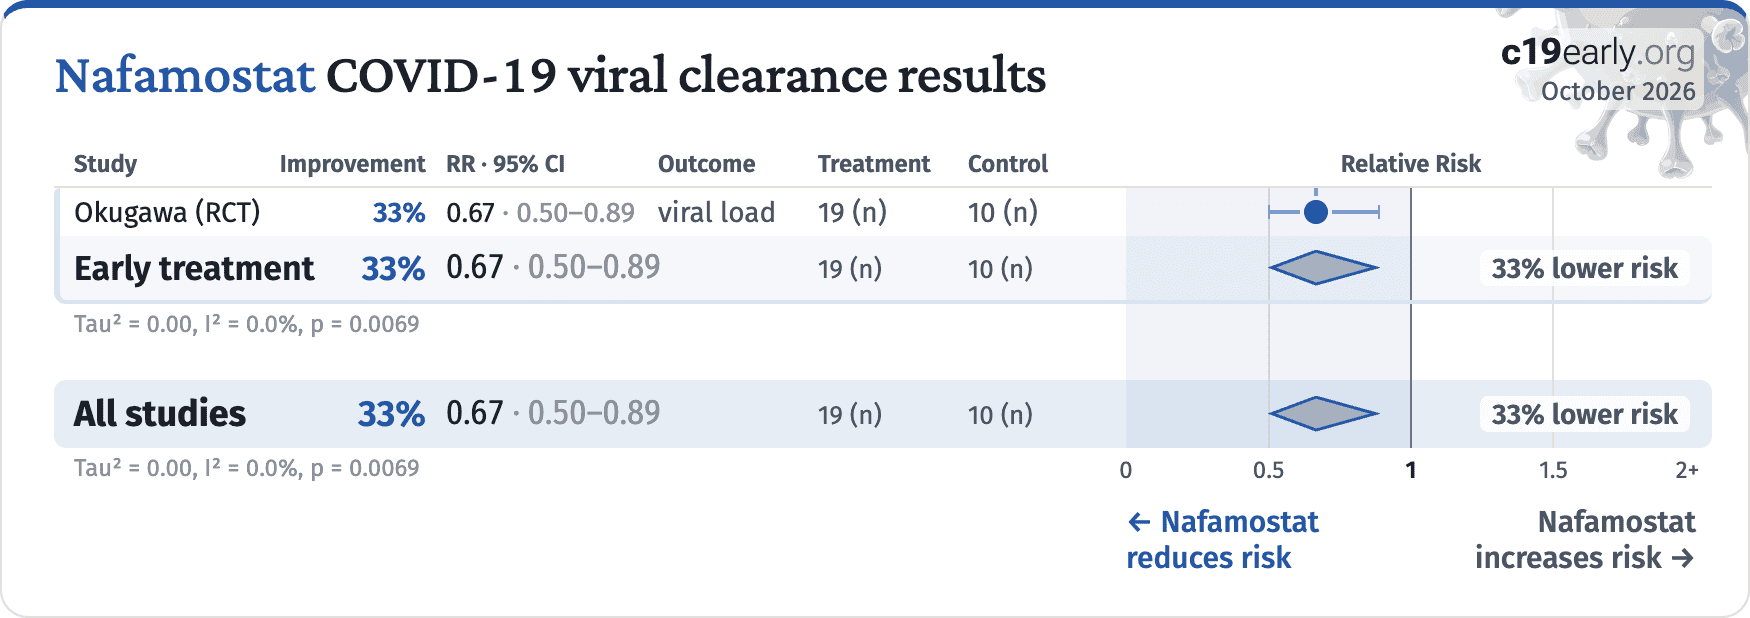
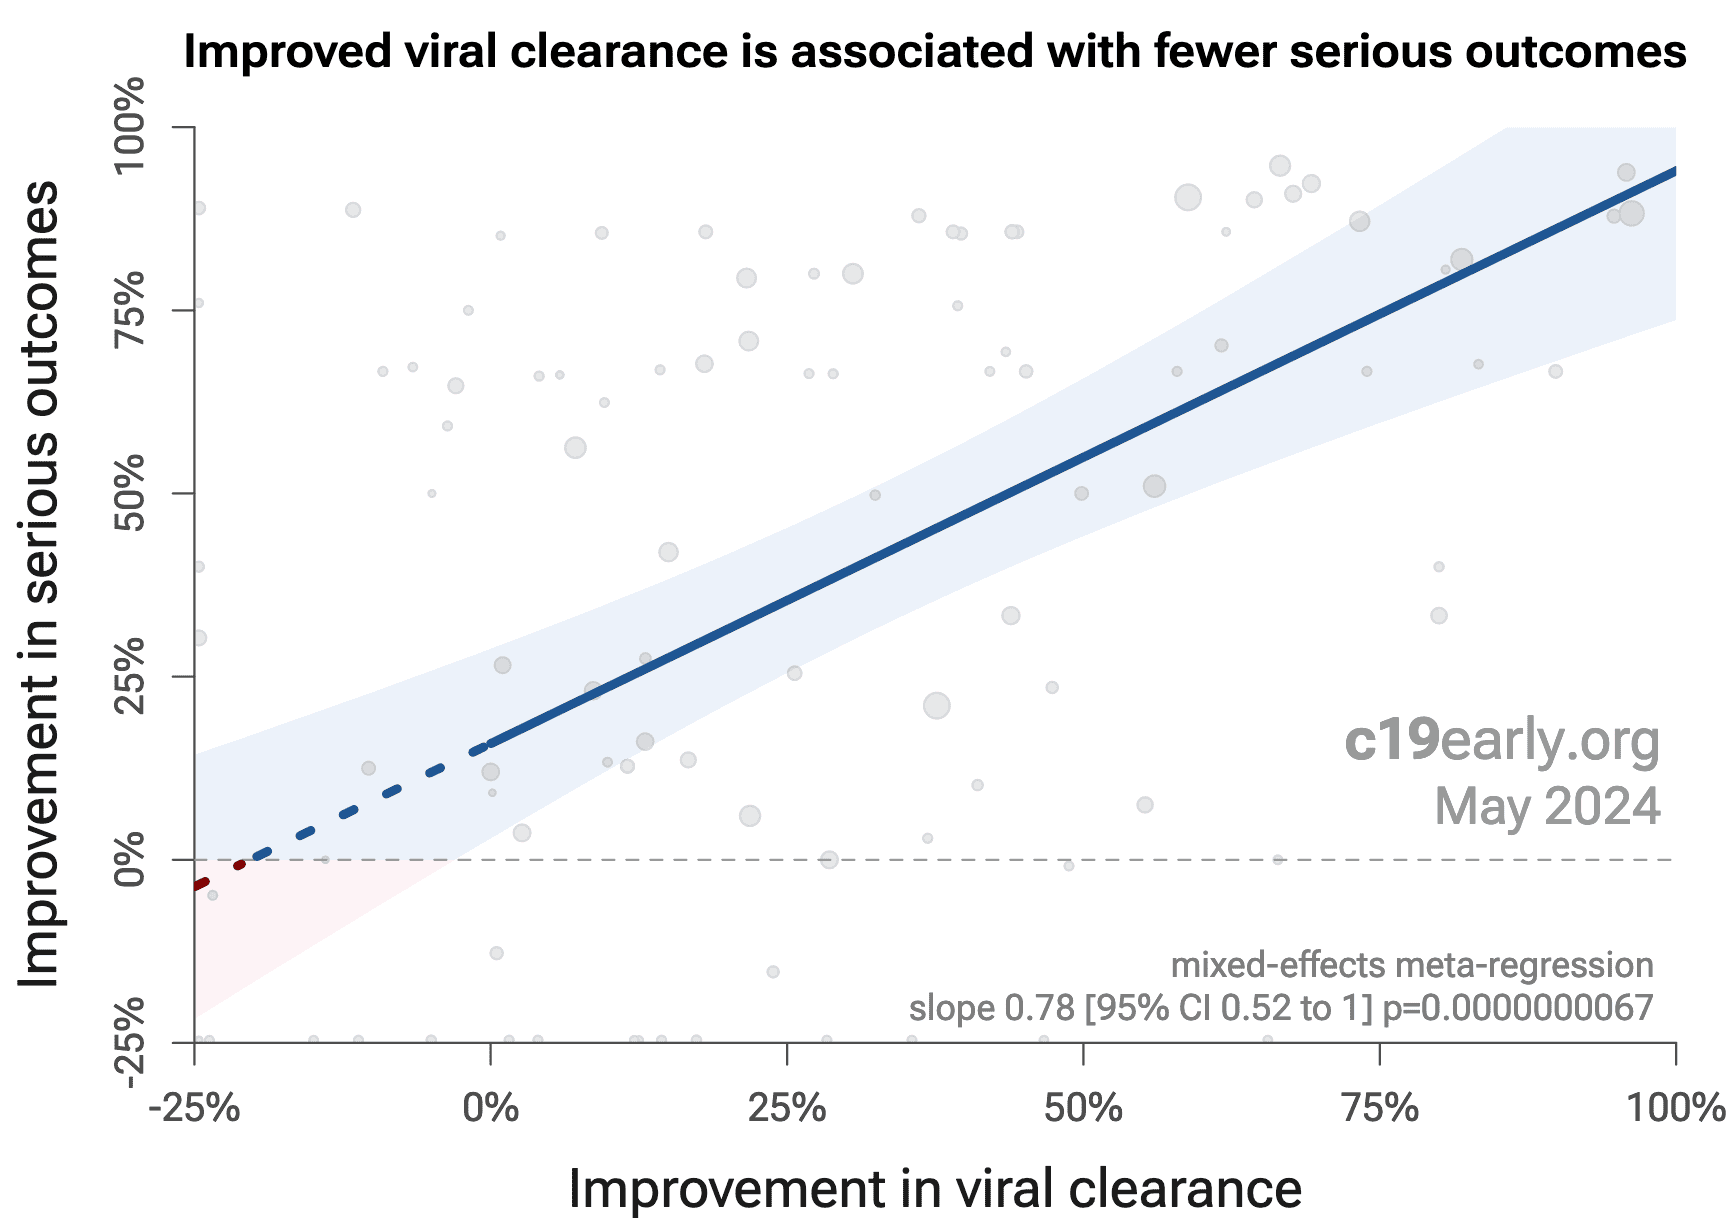
Nafamostat COVID-19 viral clearance results
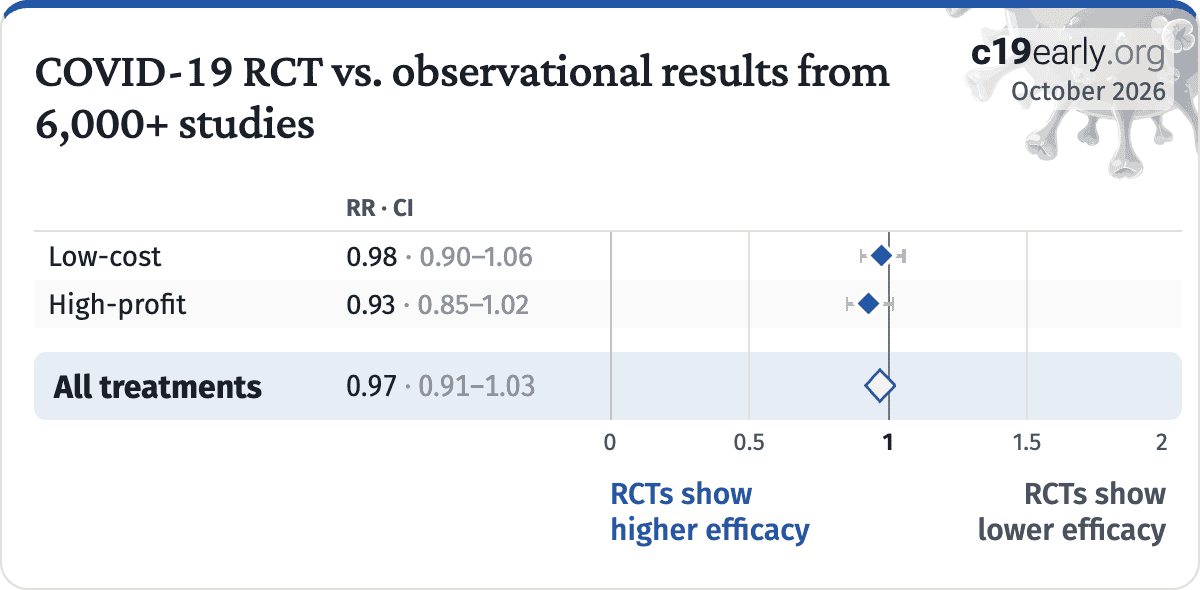
COVID-19 RCT vs. observational results from 6,000+ studies
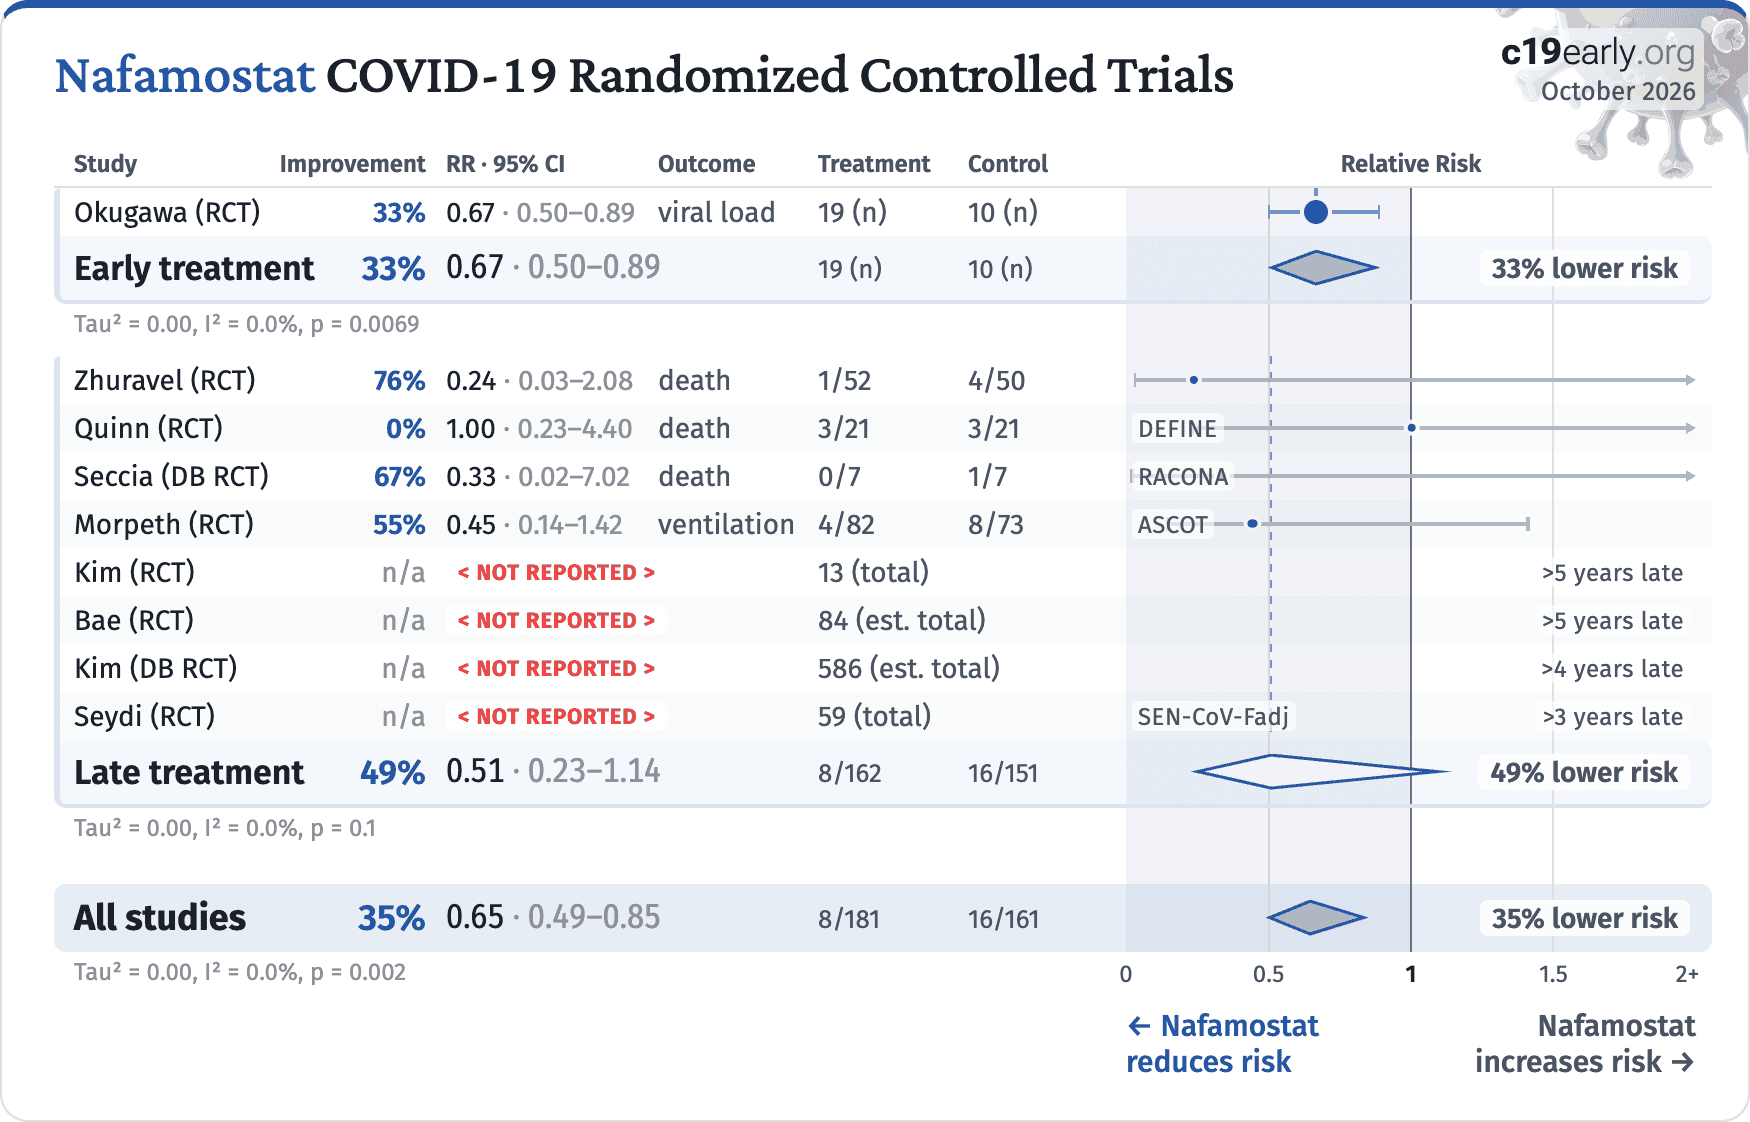
Nafamostat COVID-19 Randomized Controlled Trials
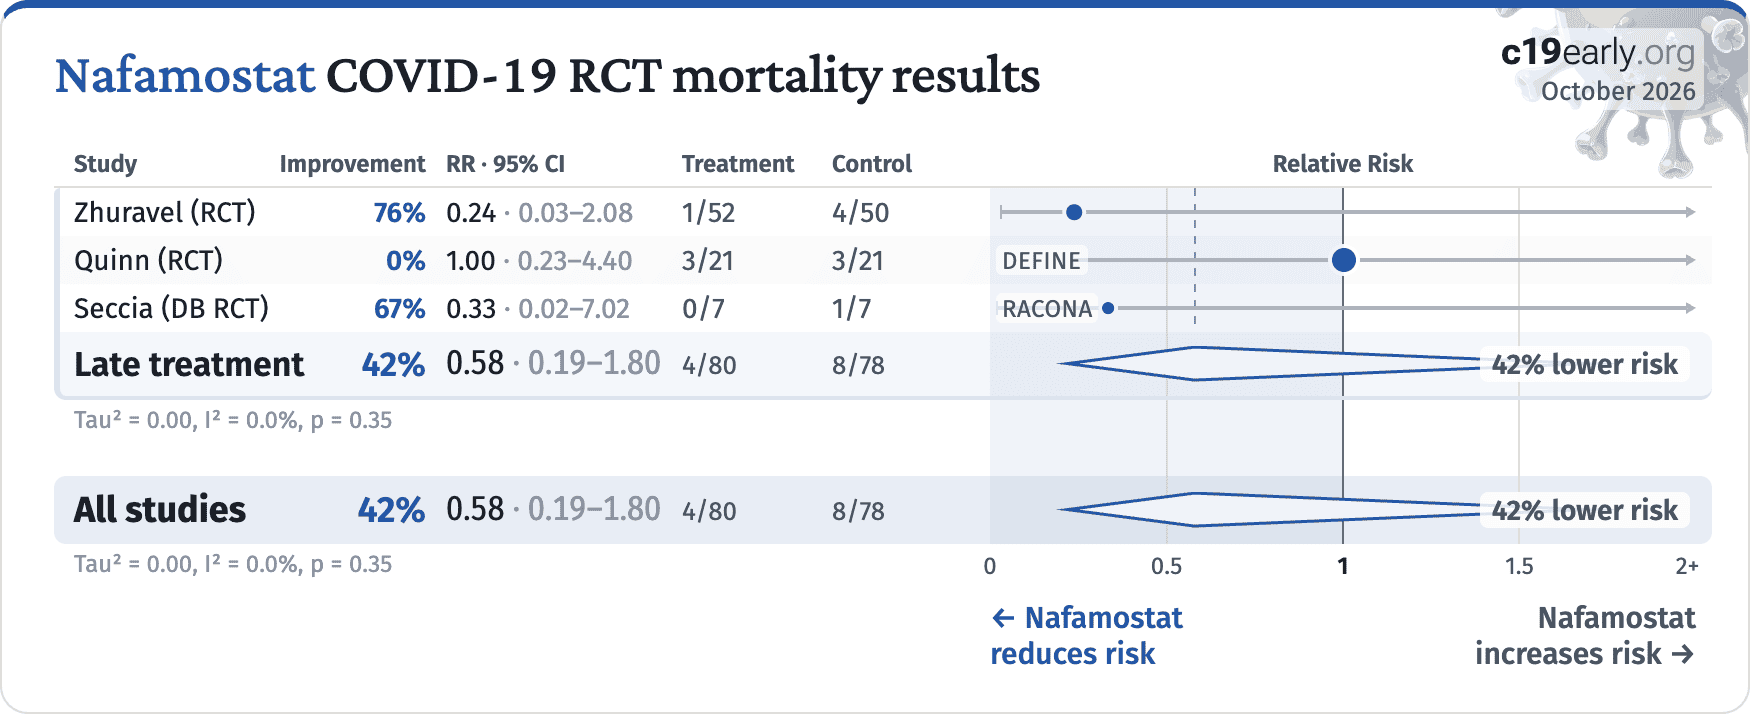
Nafamostat COVID-19 RCT mortality results
Media bias for low-cost COVID‑19 treatments
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
National treatment protocols
Protocols varied widely
Most widely used early treatments selected by the most populous countries. Official protocols varied widely. Treatments only expected to be helpful for late-stage patients are excluded. low-cost, high-profit, and increased risk.
Full matrix and analysis →| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
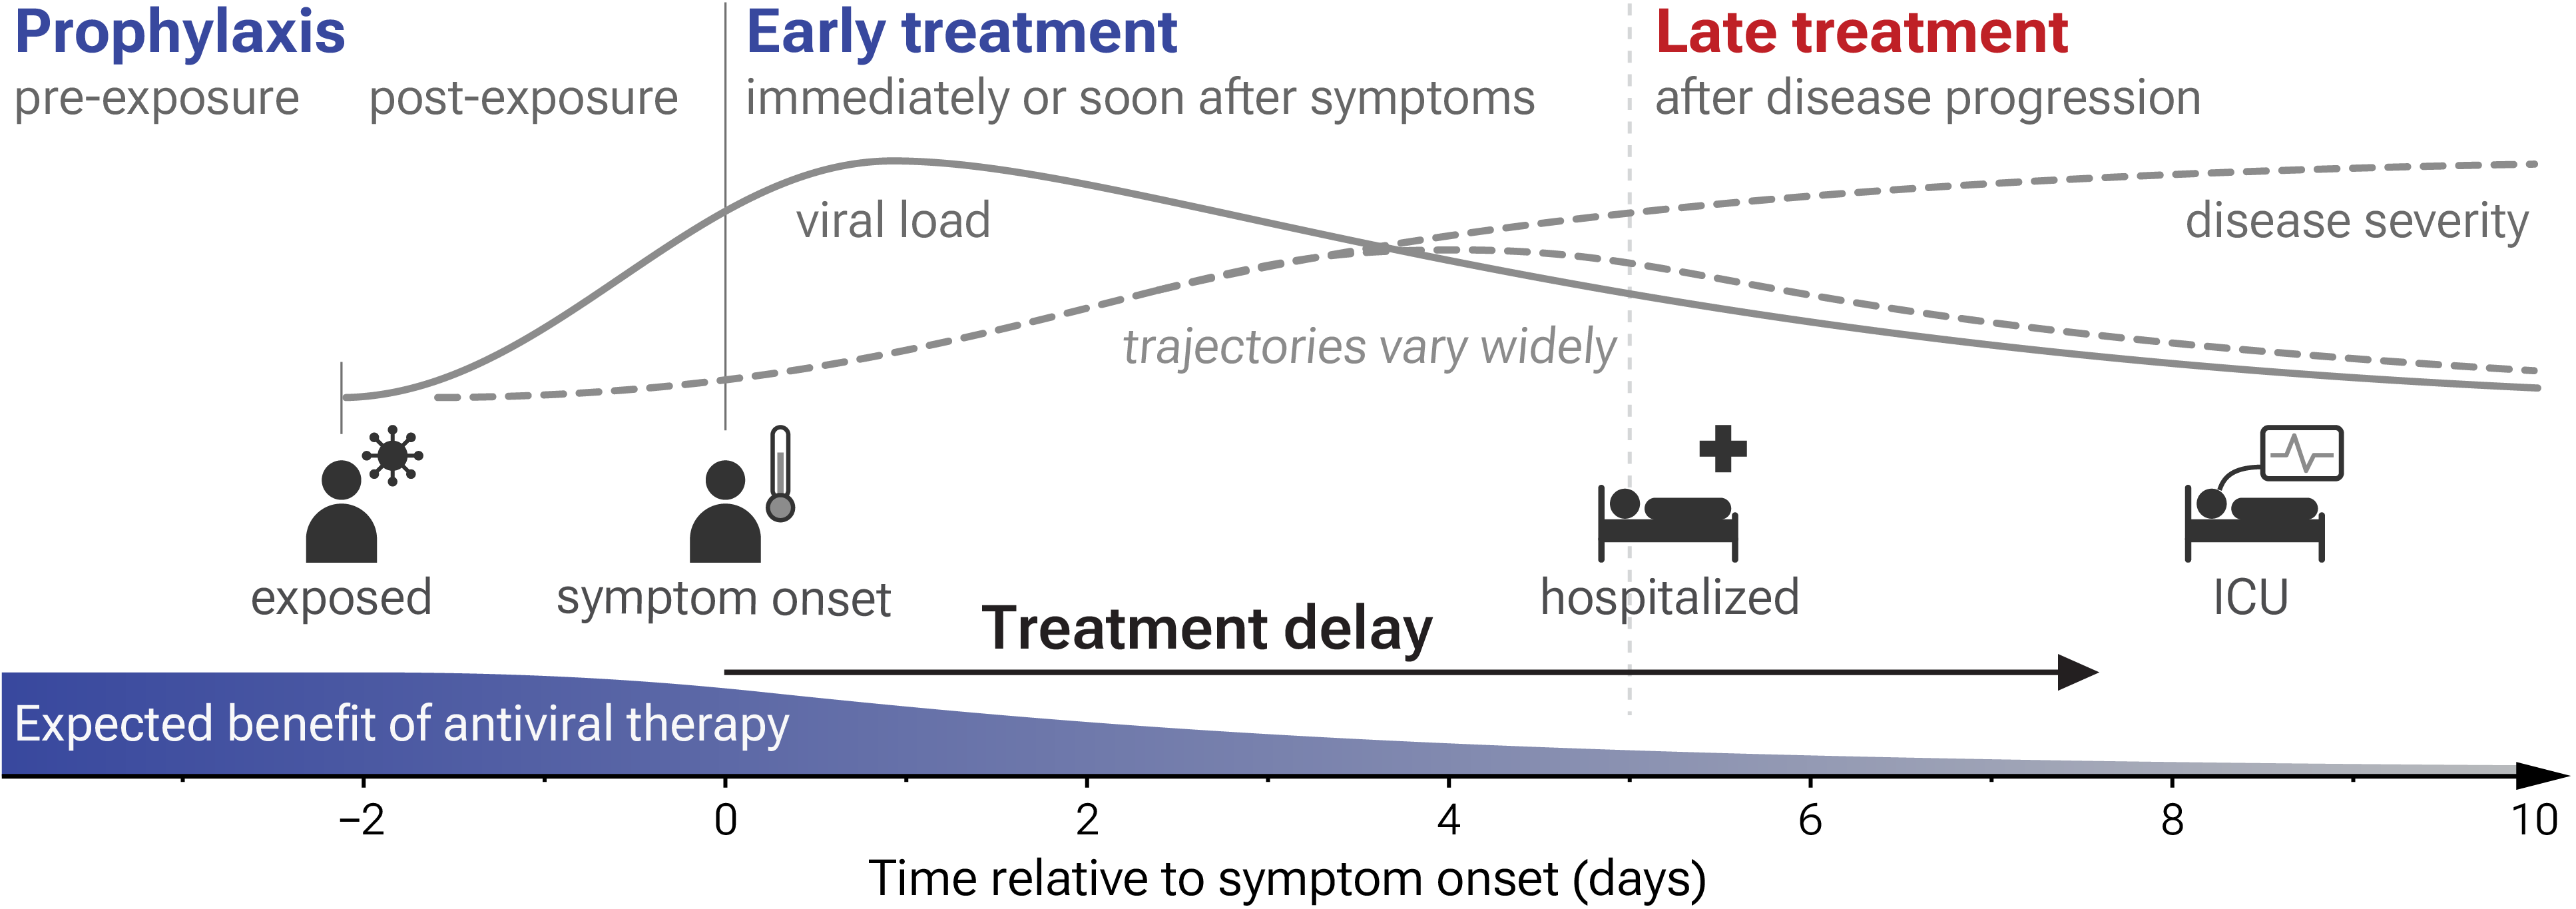
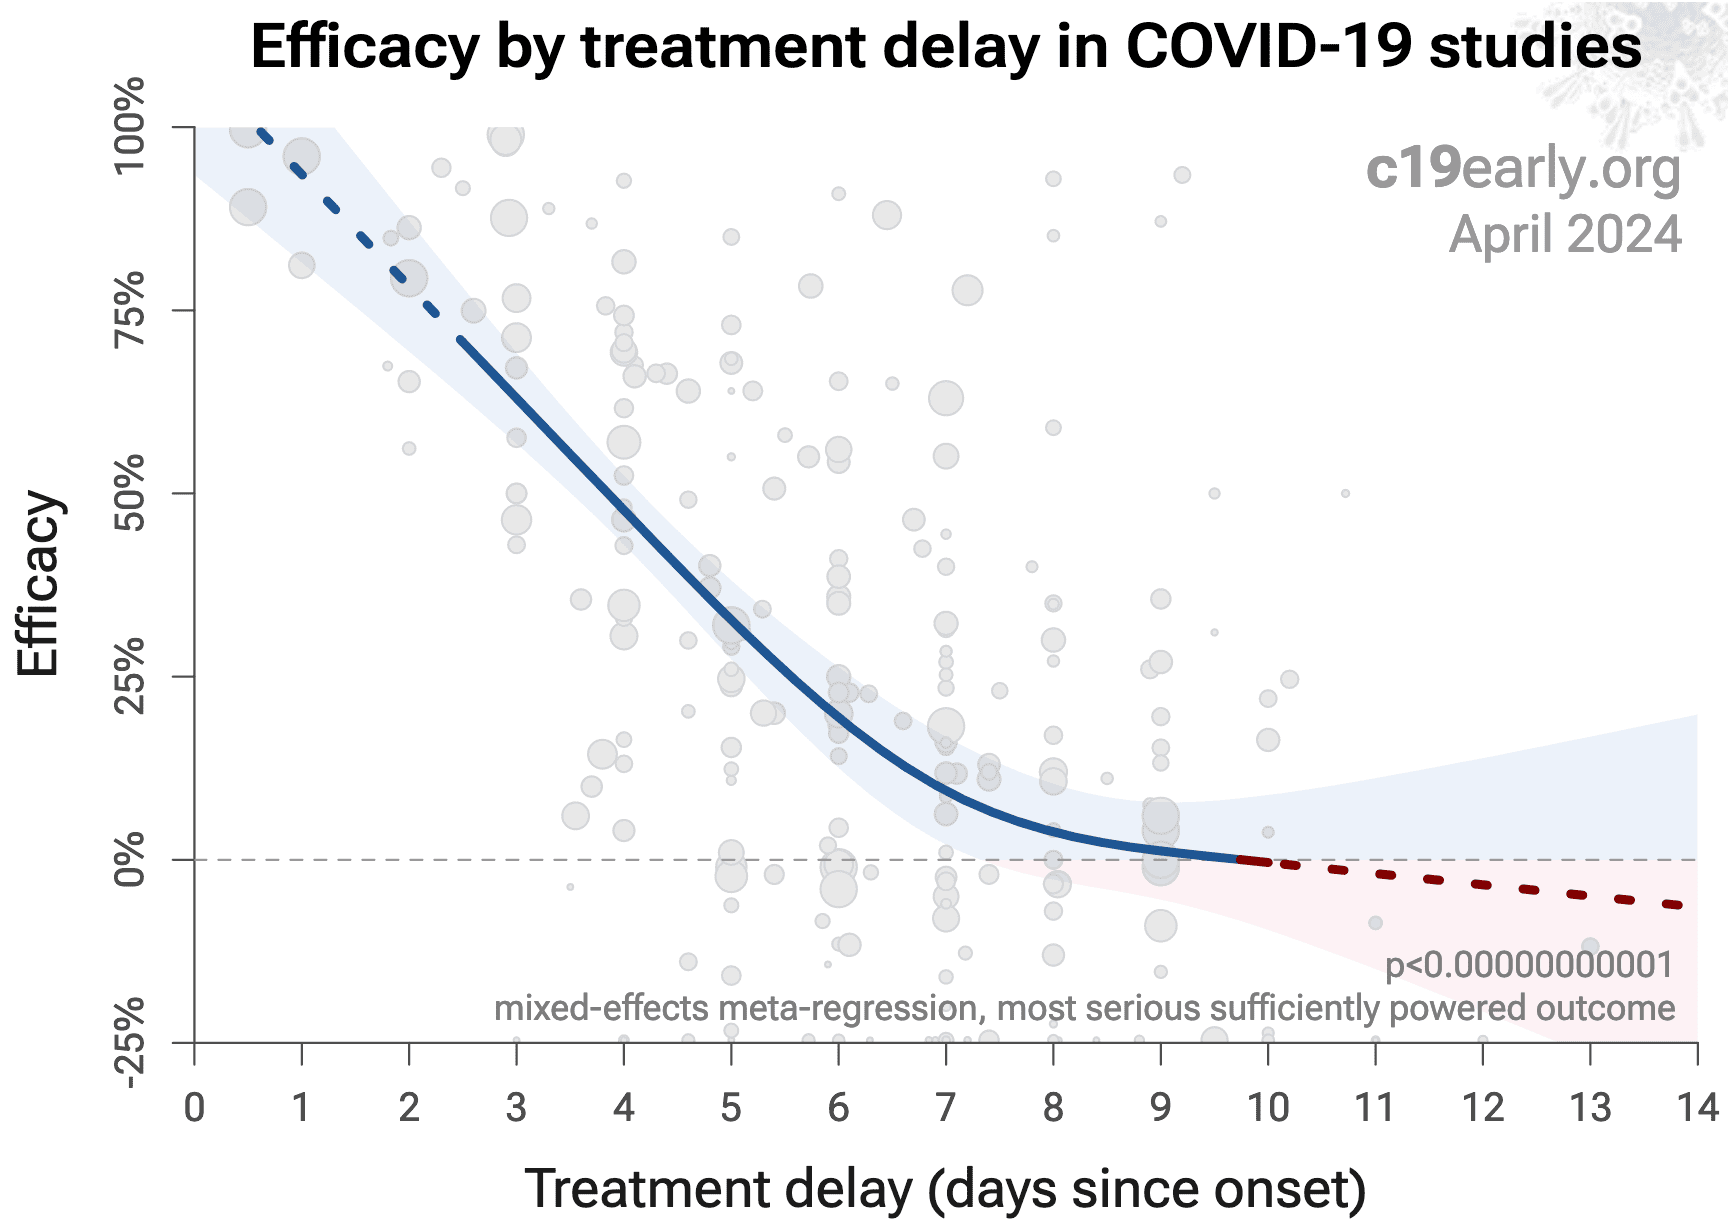
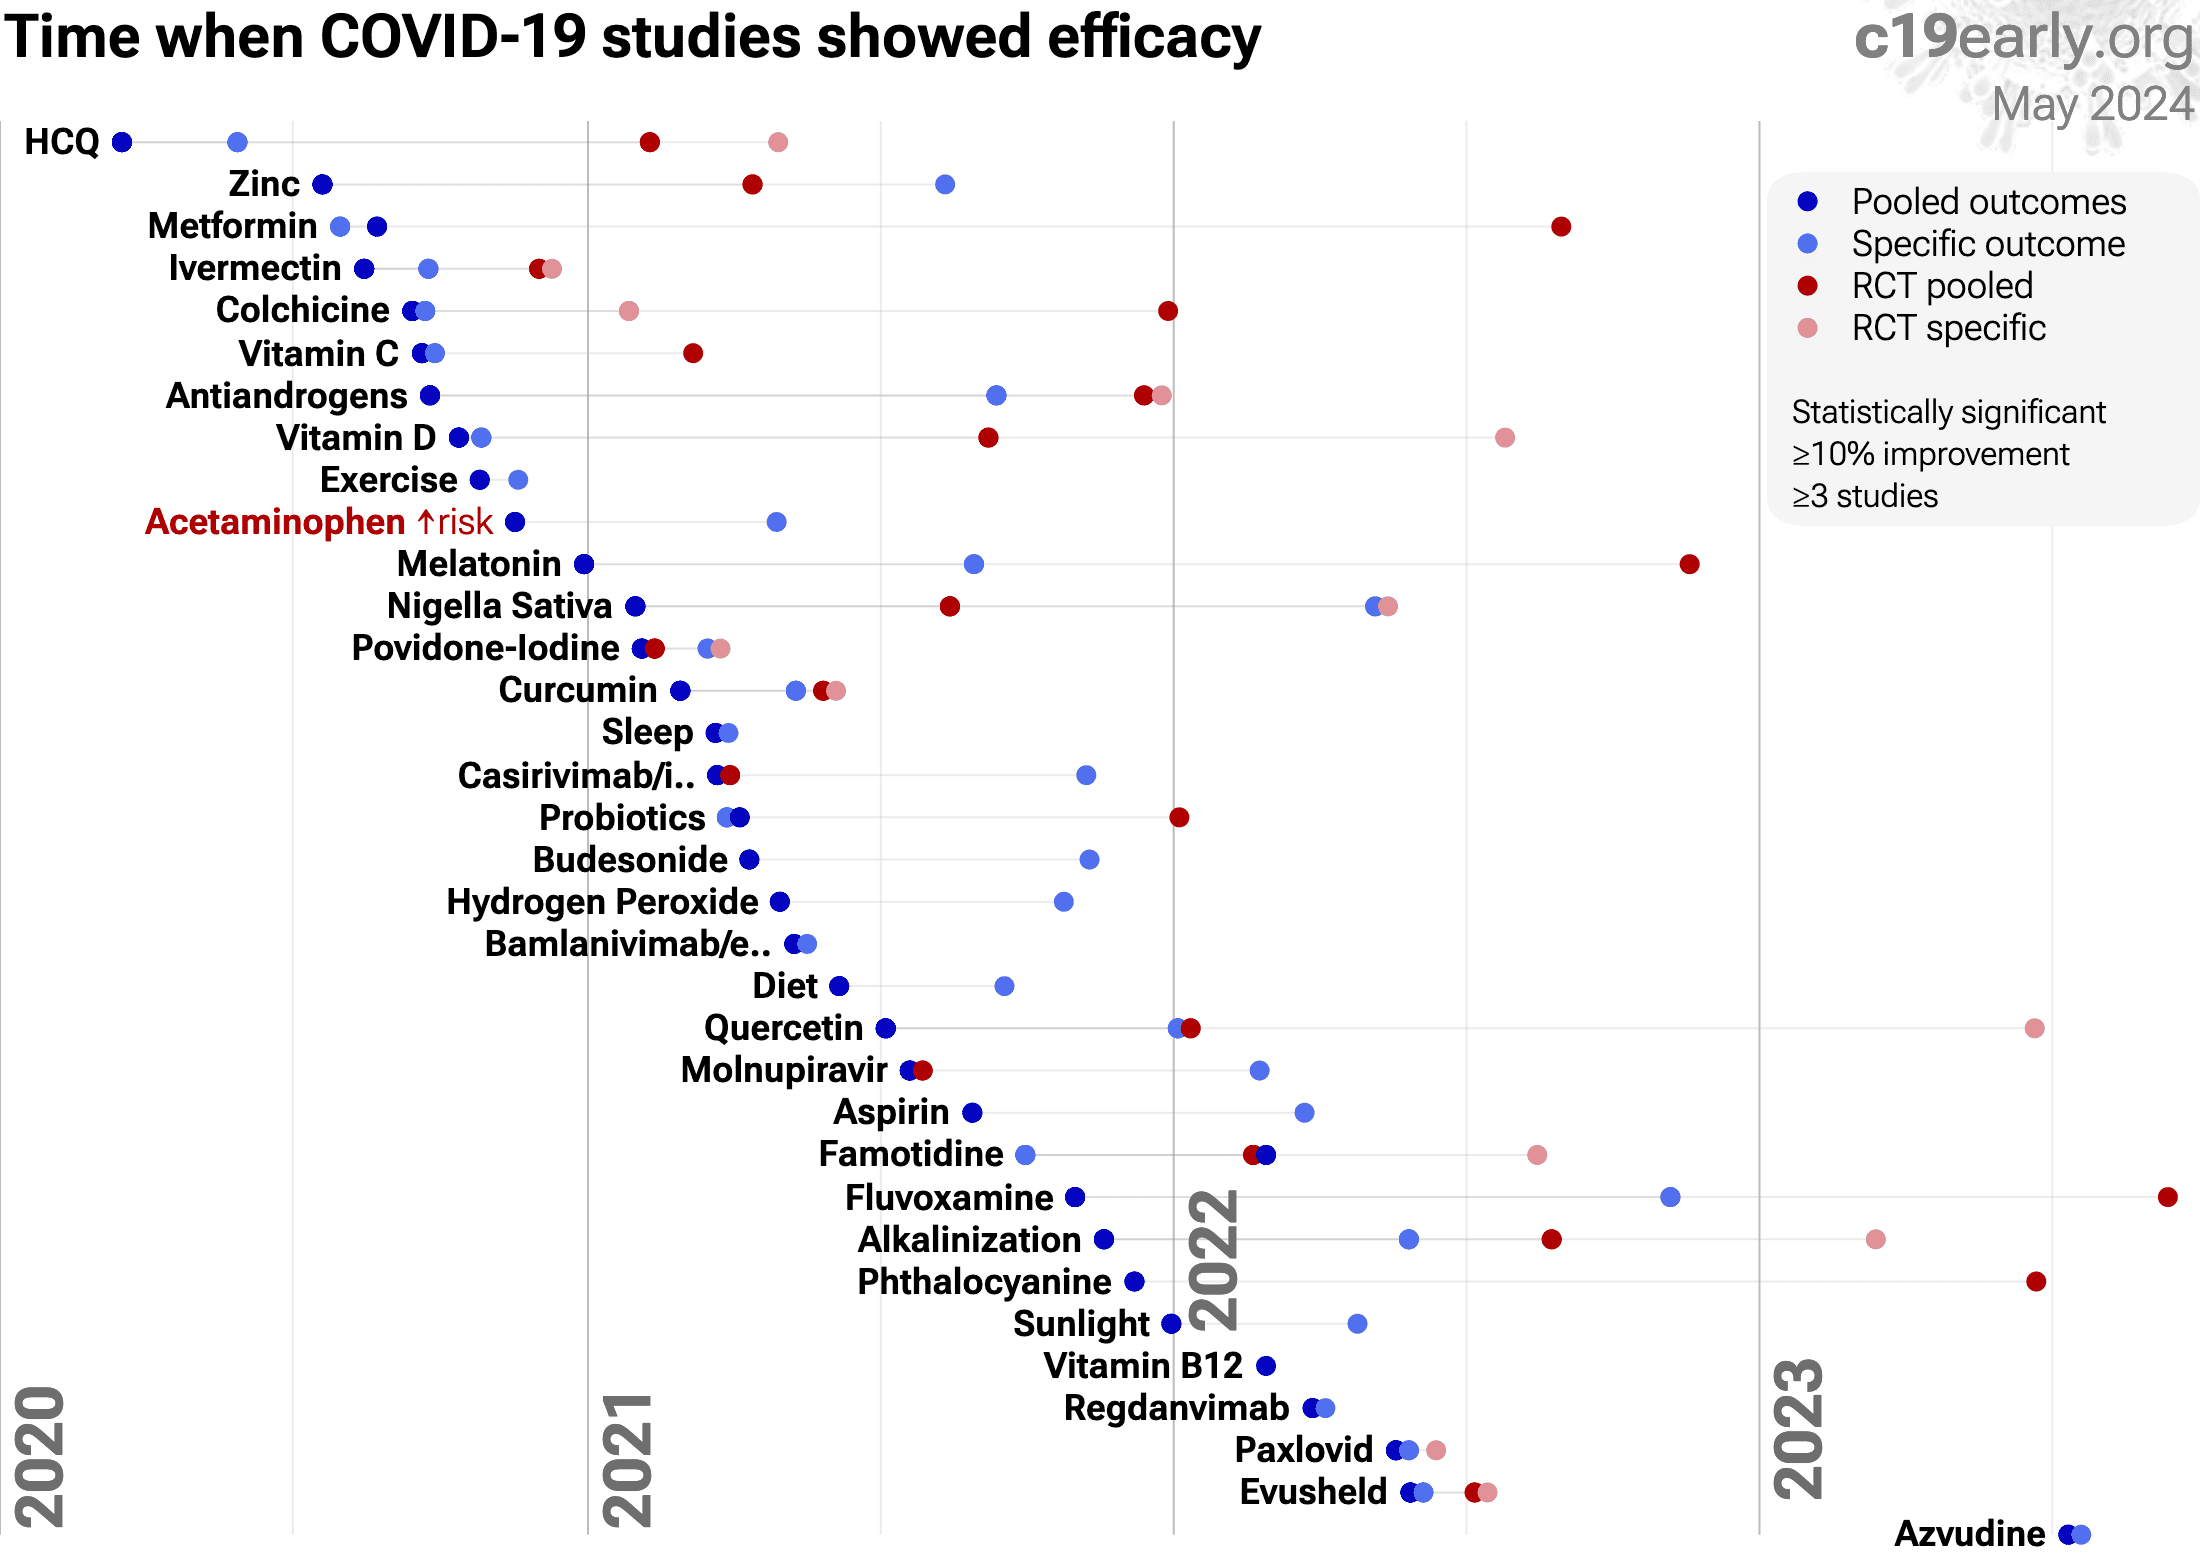
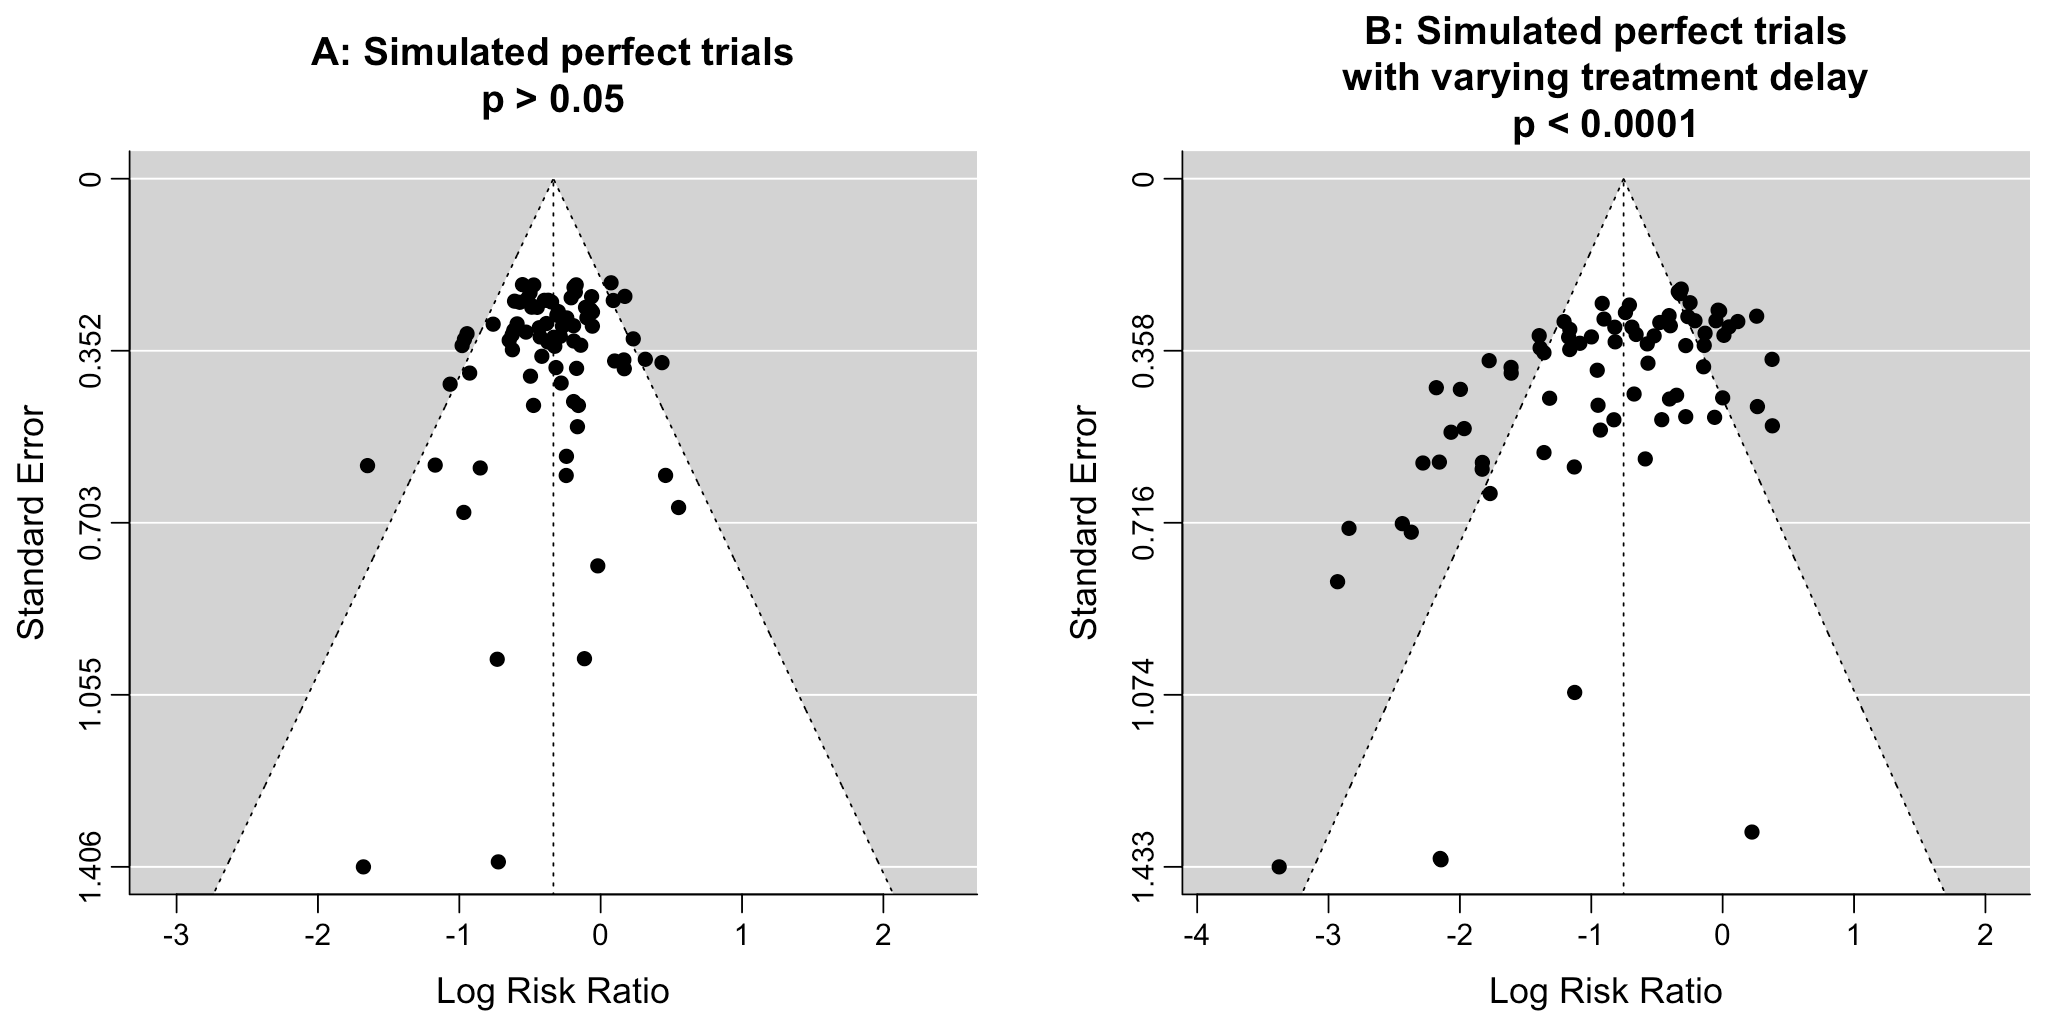
Early treatment is more effective: baloxavir marboxil
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →
reduces riskNafamostat
increases risk →

| Okugawa, 9/30/2023, Randomized Controlled Trial, Japan, peer-reviewed, mean age 39.3, 22 authors, study period July 2021 - July 2022, average treatment delay 2.5 days. | viral load, 33.3% lower, relative load 0.67, p = 0.007, treatment mean 3.0 (±0.91) n=19, control mean 2.0 (±0.8) n=10, relative reduction in viral load, day 6. |
| viral load, 60.0% lower, relative load 0.40, p = 0.01, treatment mean 1.5 (±0.91) n=19, control mean 0.6 (±0.79) n=10, relative reduction in viral load, mid-recovery, day 3. |
| Bae, 4/30/2021, Randomized Controlled Trial, South Korea, trial NCT04418128 (history). | Estimated 84 patient RCT with results unknown and over 5 years late. |
| Inokuchi, 12/26/2021, retrospective, Japan, peer-reviewed, 11 authors, study period 1 January, 2020 - 31 December, 2020. | risk of death, 27.0% higher, OR 1.27, p = 0.52, treatment 121, control 15,738, RR approximated with OR. | Kim, 8/1/2022, Double Blind Randomized Controlled Trial, placebo-controlled, South Korea, trial NCT04871646 (history). | Estimated 586 patient RCT with results unknown and over 4 years late. | Kim (B), 4/5/2021, Randomized Controlled Trial, South Korea, trial NCT04628143 (history). | 13 patient RCT with results unknown and over 5 years late. |
| Morpeth, 10/24/2023, Randomized Controlled Trial, multiple countries, peer-reviewed, 64 authors, study period 17 May, 2021 - 12 August, 2022, trial NCT04483960 (history) (ASCOT). | risk of mechanical ventilation, 55.5% lower, RR 0.45, p = 0.23, treatment 4 of 82 (4.9%), control 8 of 73 (11.0%), NNT 16, day 28. |
| risk of progression, 57.2% lower, RR 0.43, p = 0.14, treatment 4 of 82 (4.9%), control 8 of 73 (11.0%), NNT 16, adjusted per study, odds ratio converted to relative risk, death, ventilation, or vasopressor support, day 28. | |
| risk of no recovery, 28.0% lower, OR 0.72, p = 0.36, treatment 82, control 73, WHO scale, day 28, RR approximated with OR. | |
| Quinn, 2/28/2022, Randomized Controlled Trial, United Kingdom, peer-reviewed, mean age 63.6, 49 authors, study period September 2020 - February 2021, average treatment delay 8.5 days, trial NCT04473053 (history) (DEFINE). | risk of death, no change, RR 1.00, p = 1.00, treatment 3 of 21 (14.3%), control 3 of 21 (14.3%). |
| hospitalization time, 47.5% higher, relative time 1.48, p = 0.21, treatment mean 9.0 (±8.4) n=21, control mean 6.1 (±6.0) n=21. | |
| Seccia, 10/19/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Italy, peer-reviewed, 15 authors, study period June 2021 - August 2022, trial NCT04352400 (history) (RACONA). | risk of death, 66.7% lower, RR 0.33, p = 1.00, treatment 0 of 7 (0.0%), control 1 of 7 (14.3%), NNT 7.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| risk of no recovery, 20.0% lower, RR 0.80, p = 1.00, treatment 4 of 7 (57.1%), control 5 of 7 (71.4%), NNT 7.0, no improvement in WHO score of 2+ points. | Seydi, 2/8/2023, Randomized Controlled Trial, Senegal, trial NCT04390594 (history) (SEN-CoV-Fadj). | 59 patient RCT with results unknown and over 3 years late. |
| Soma, 9/30/2022, retrospective, Japan, peer-reviewed, 9 authors, study period 29 March, 2020 - 21 January, 2021. | risk of death, 79.5% lower, RR 0.20, p = 0.49, treatment 0 of 31 (0.0%), control 2 of 33 (6.1%), NNT 16, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| risk of severe case, 6.5% higher, RR 1.06, p = 1.00, treatment 10 of 31 (32.3%), control 10 of 33 (30.3%). | |
| Zhuravel, 11/30/2021, Randomized Controlled Trial, placebo-controlled, Russia, peer-reviewed, mean age 58.6, 7 authors, study period 25 September, 2020 - 14 November, 2020, average treatment delay 10.0 days, trial NCT04623021 (history). | risk of death, 76.0% lower, RR 0.24, p = 0.20, treatment 1 of 52 (1.9%), control 4 of 50 (8.0%), NNT 16. |
| risk of no improvement, 42.3% lower, RR 0.58, p = 0.28, treatment 6 of 52 (11.5%), control 10 of 50 (20.0%), NNT 12. | |
| risk of no recovery, 42.3% lower, RR 0.58, p = 0.28, treatment 6 of 52 (11.5%), control 10 of 50 (20.0%), NNT 12. | |
| risk of no recovery, 40.9% lower, RR 0.59, p = 0.09, treatment mean 1.3 (±2.3) n=52, control mean 2.2 (±3.0) n=50, relative NEWS score at day 11, day 11. |