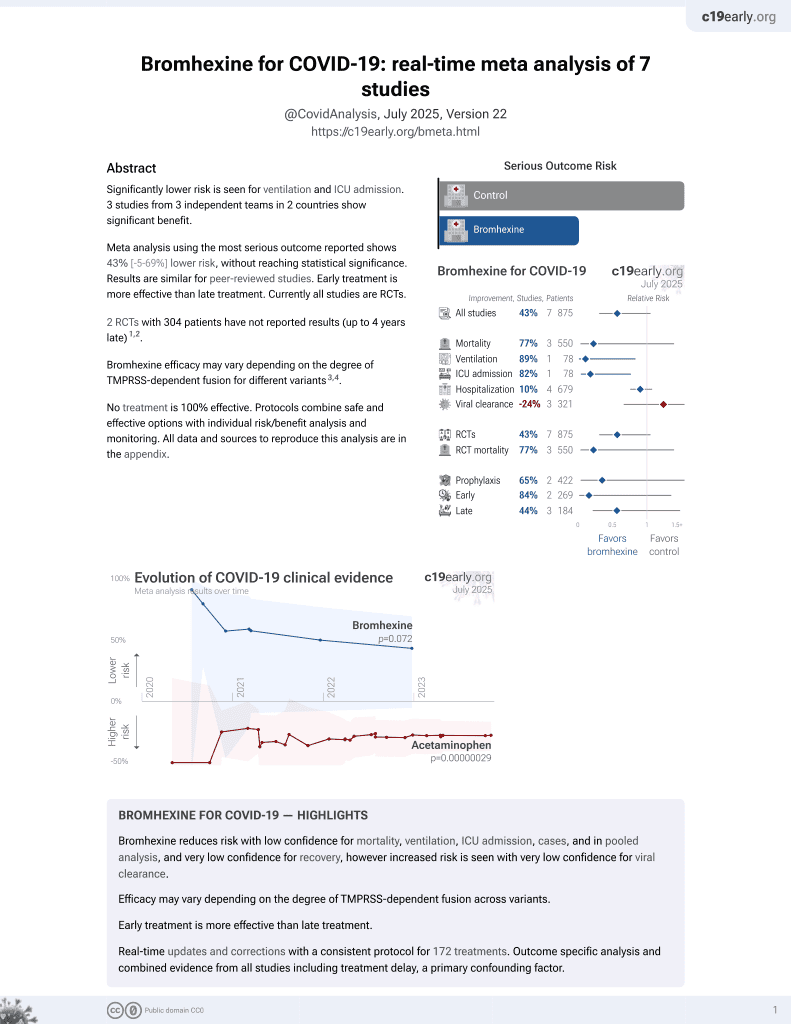
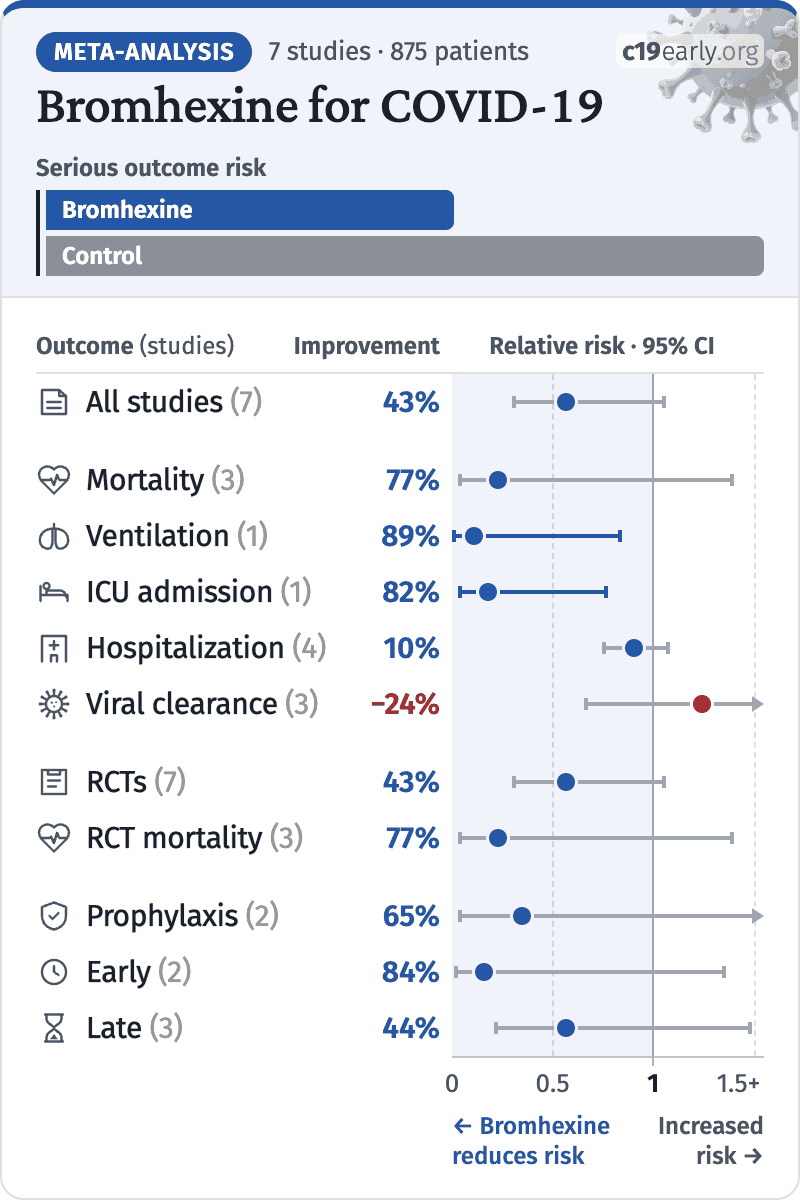
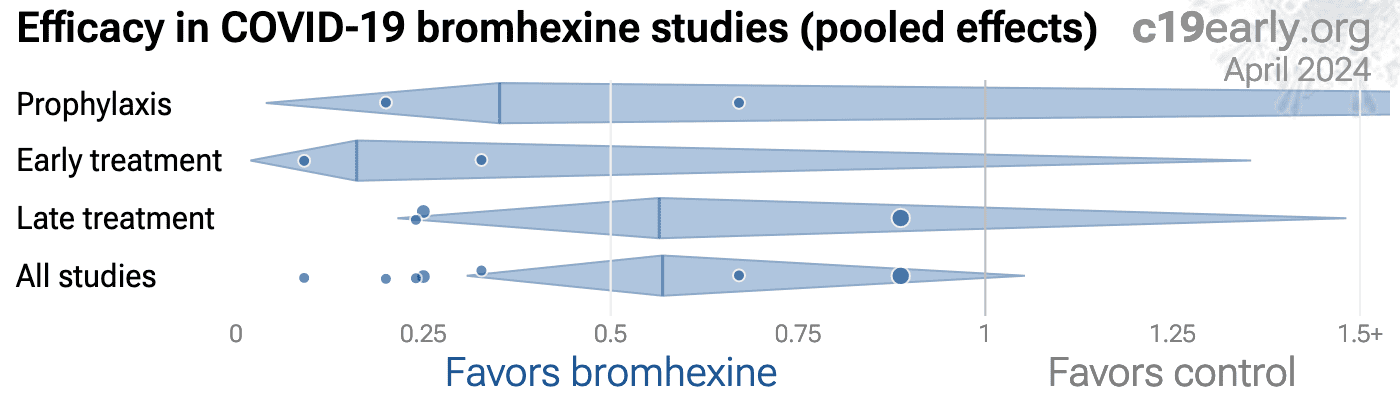
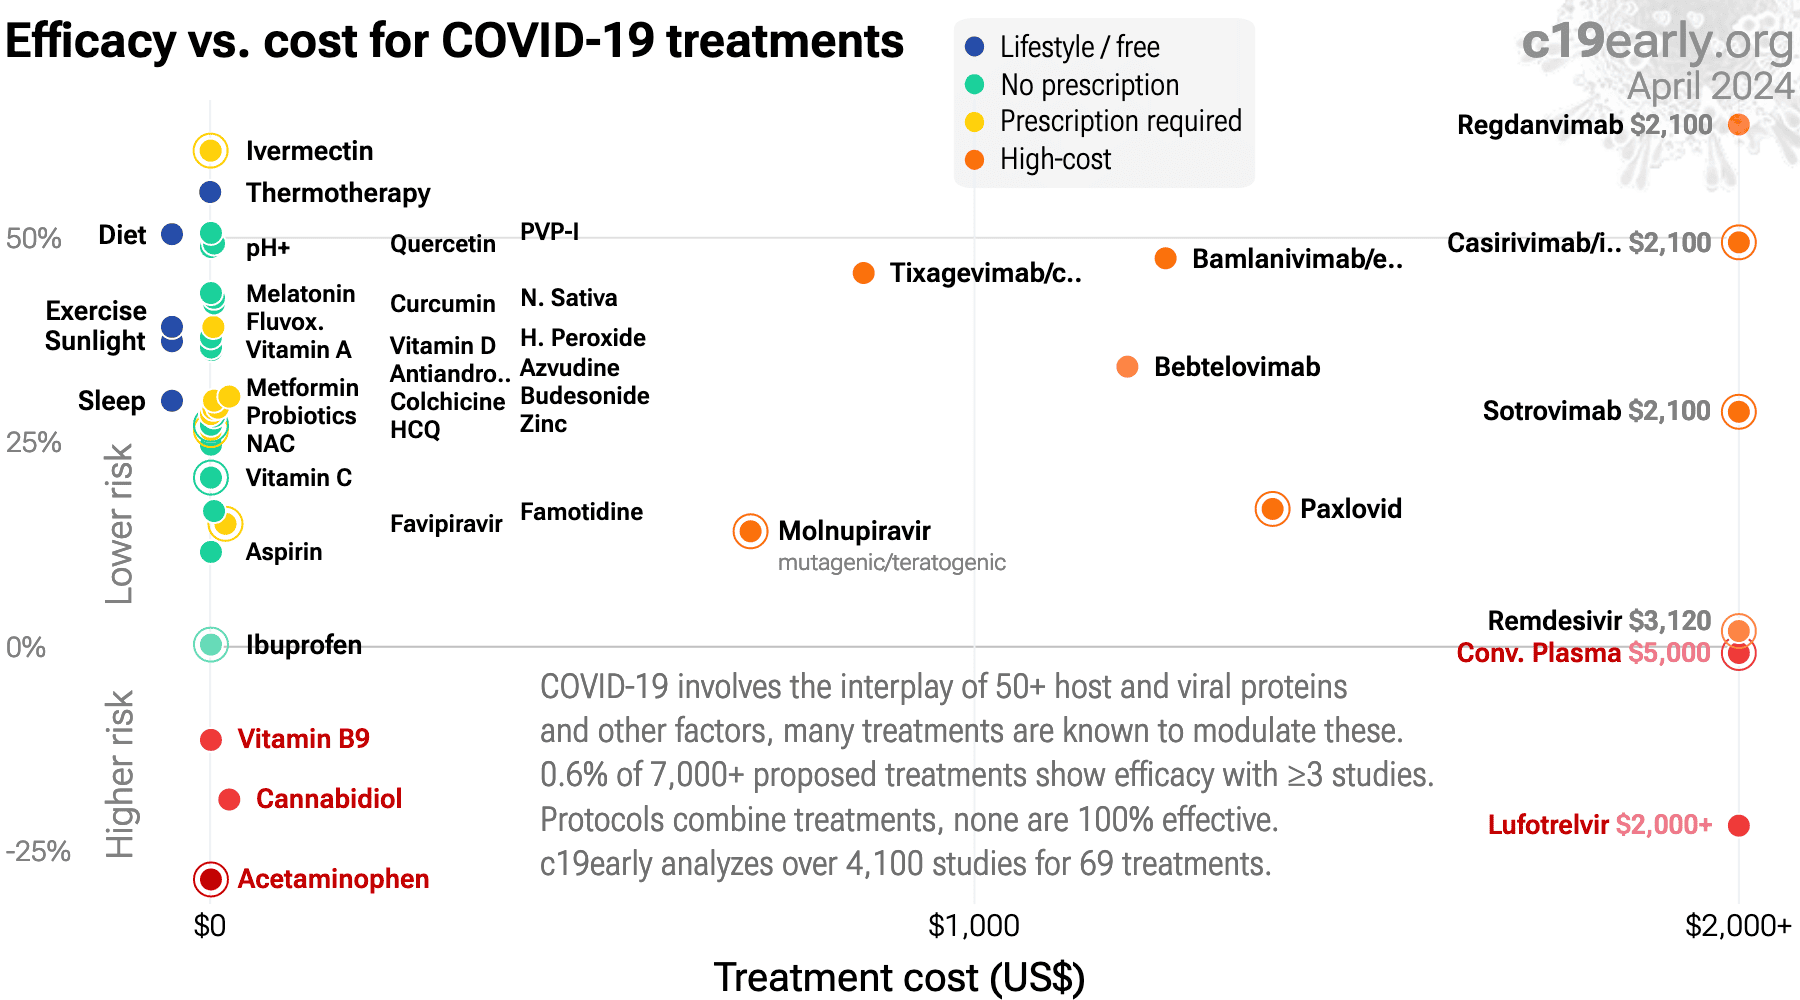
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/bmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
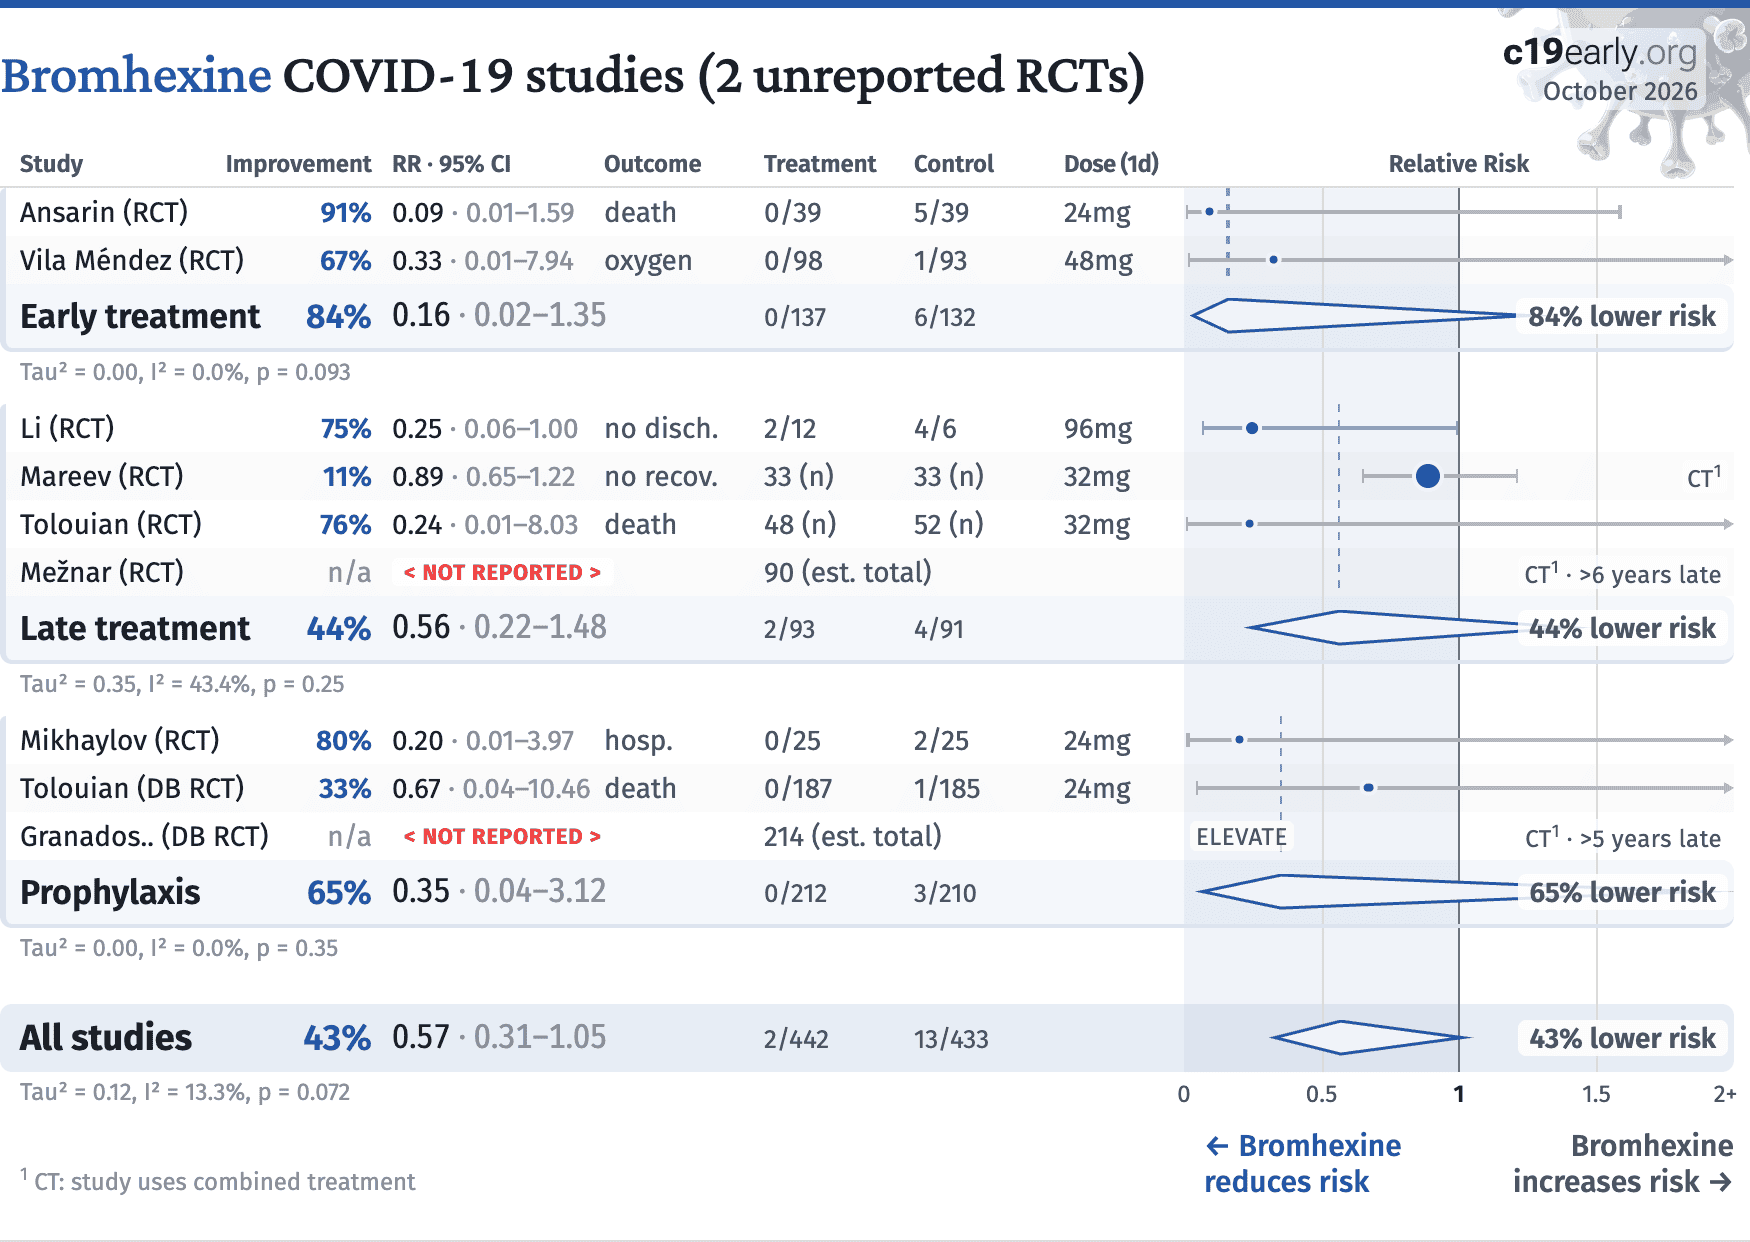
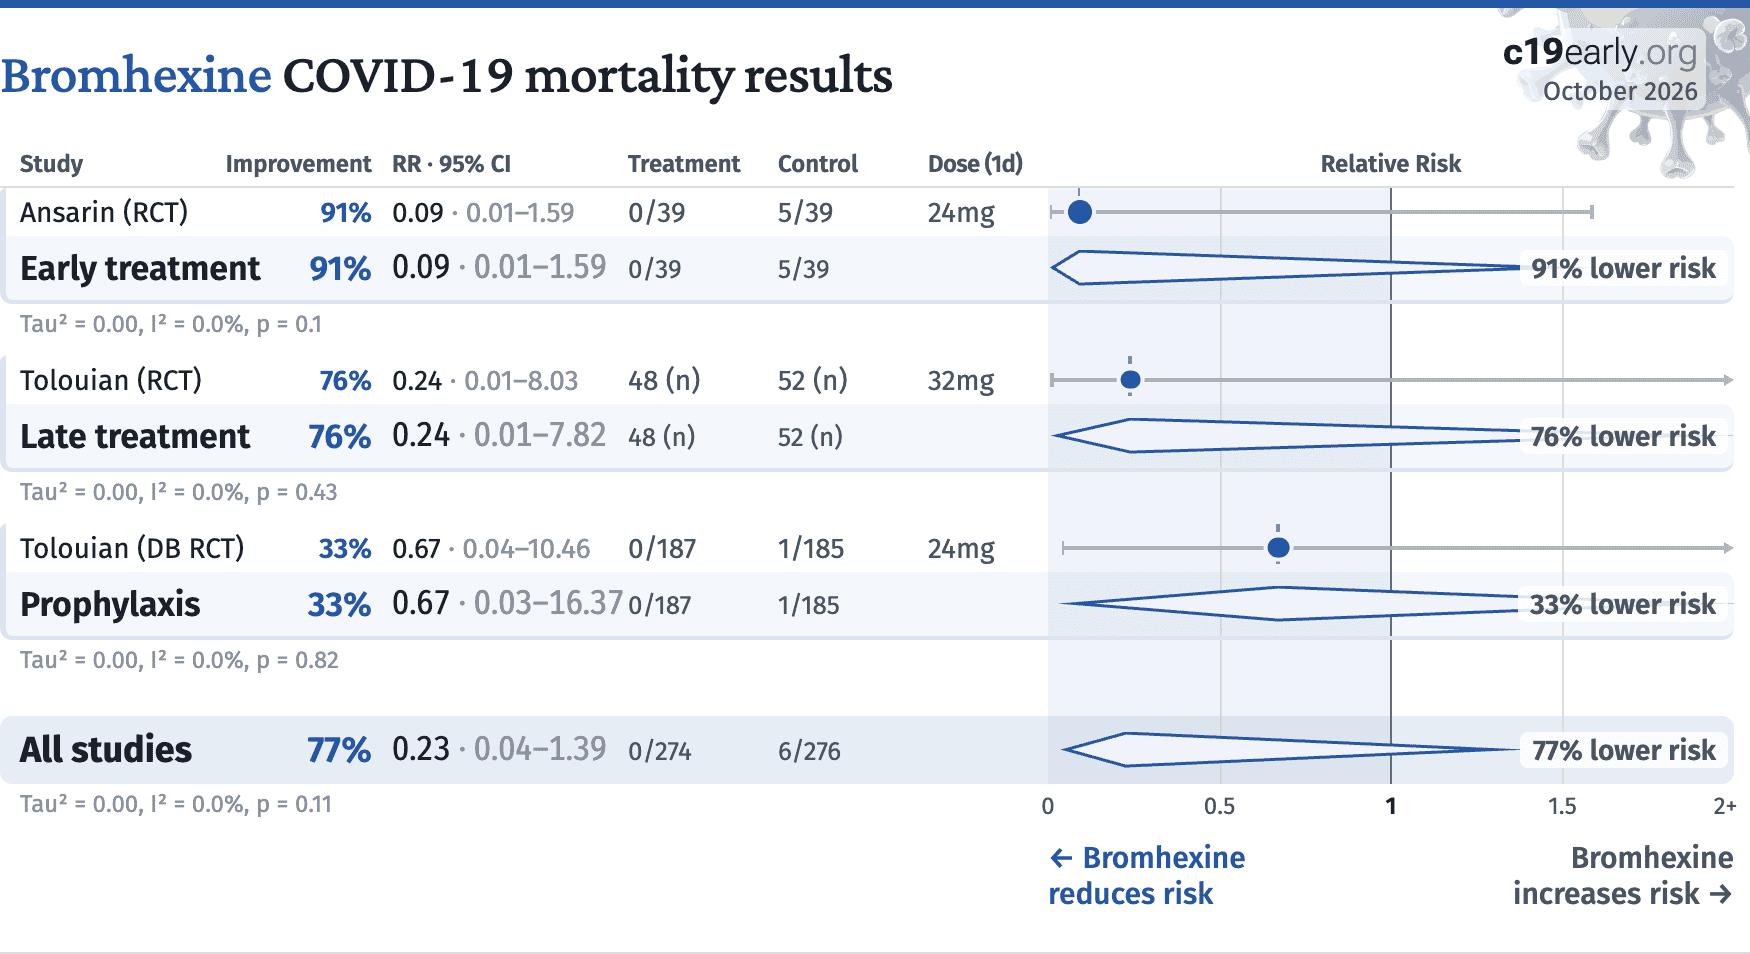
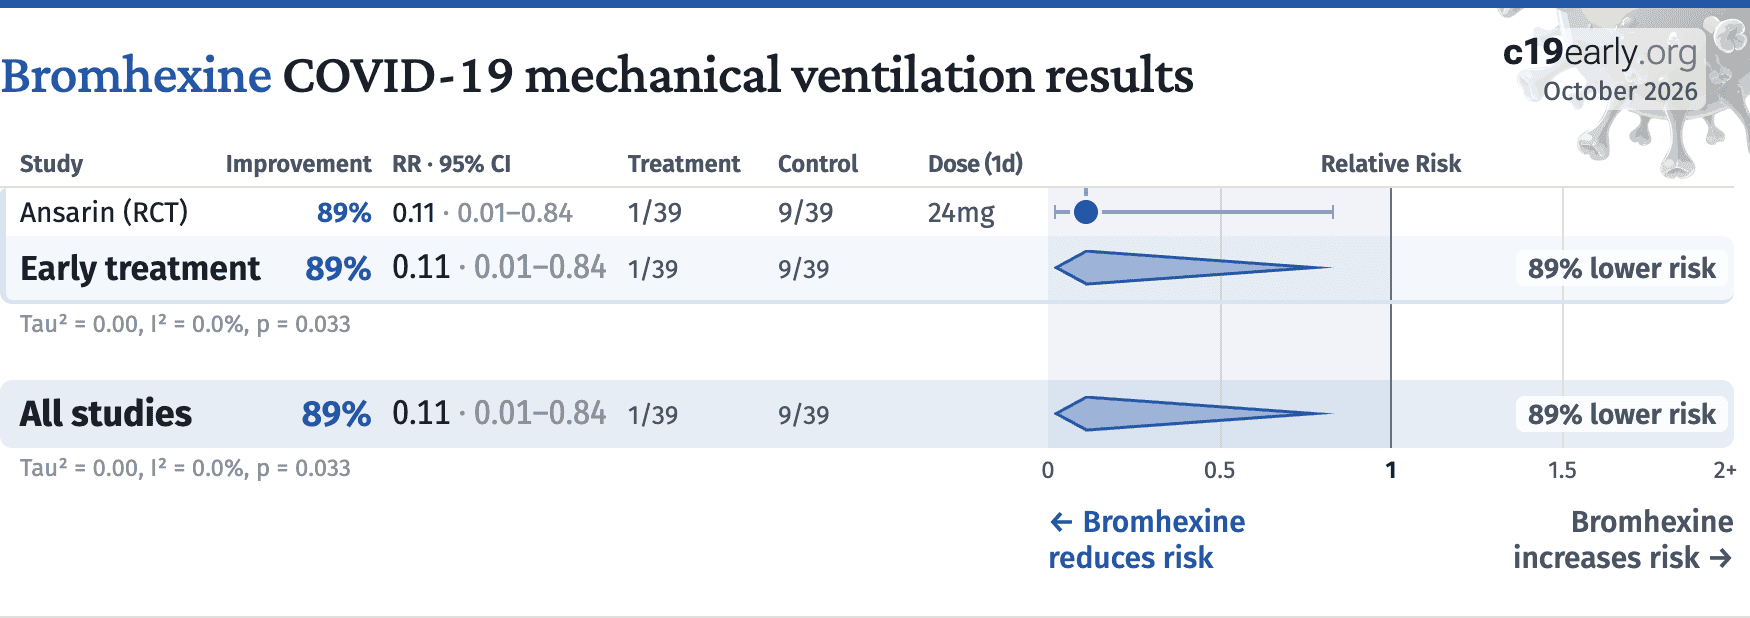
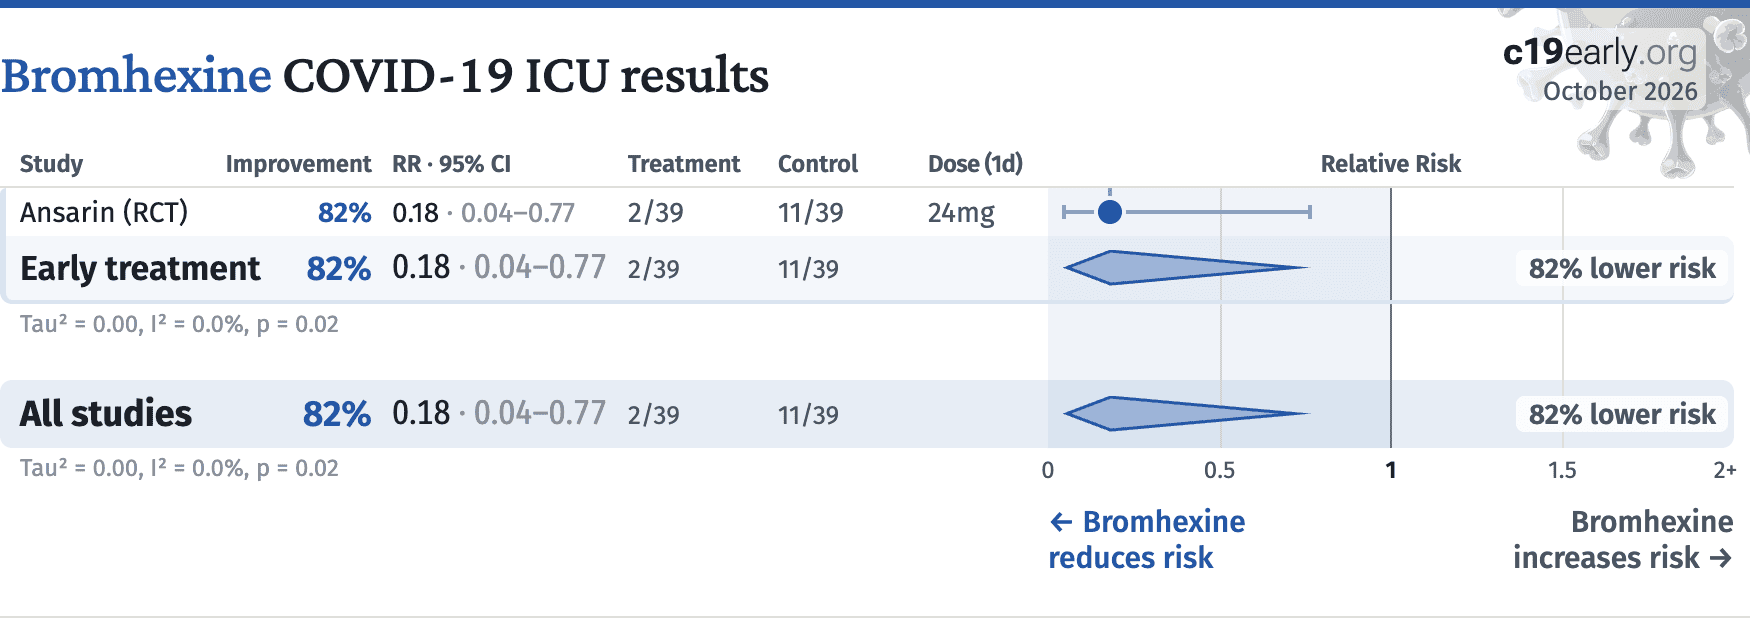
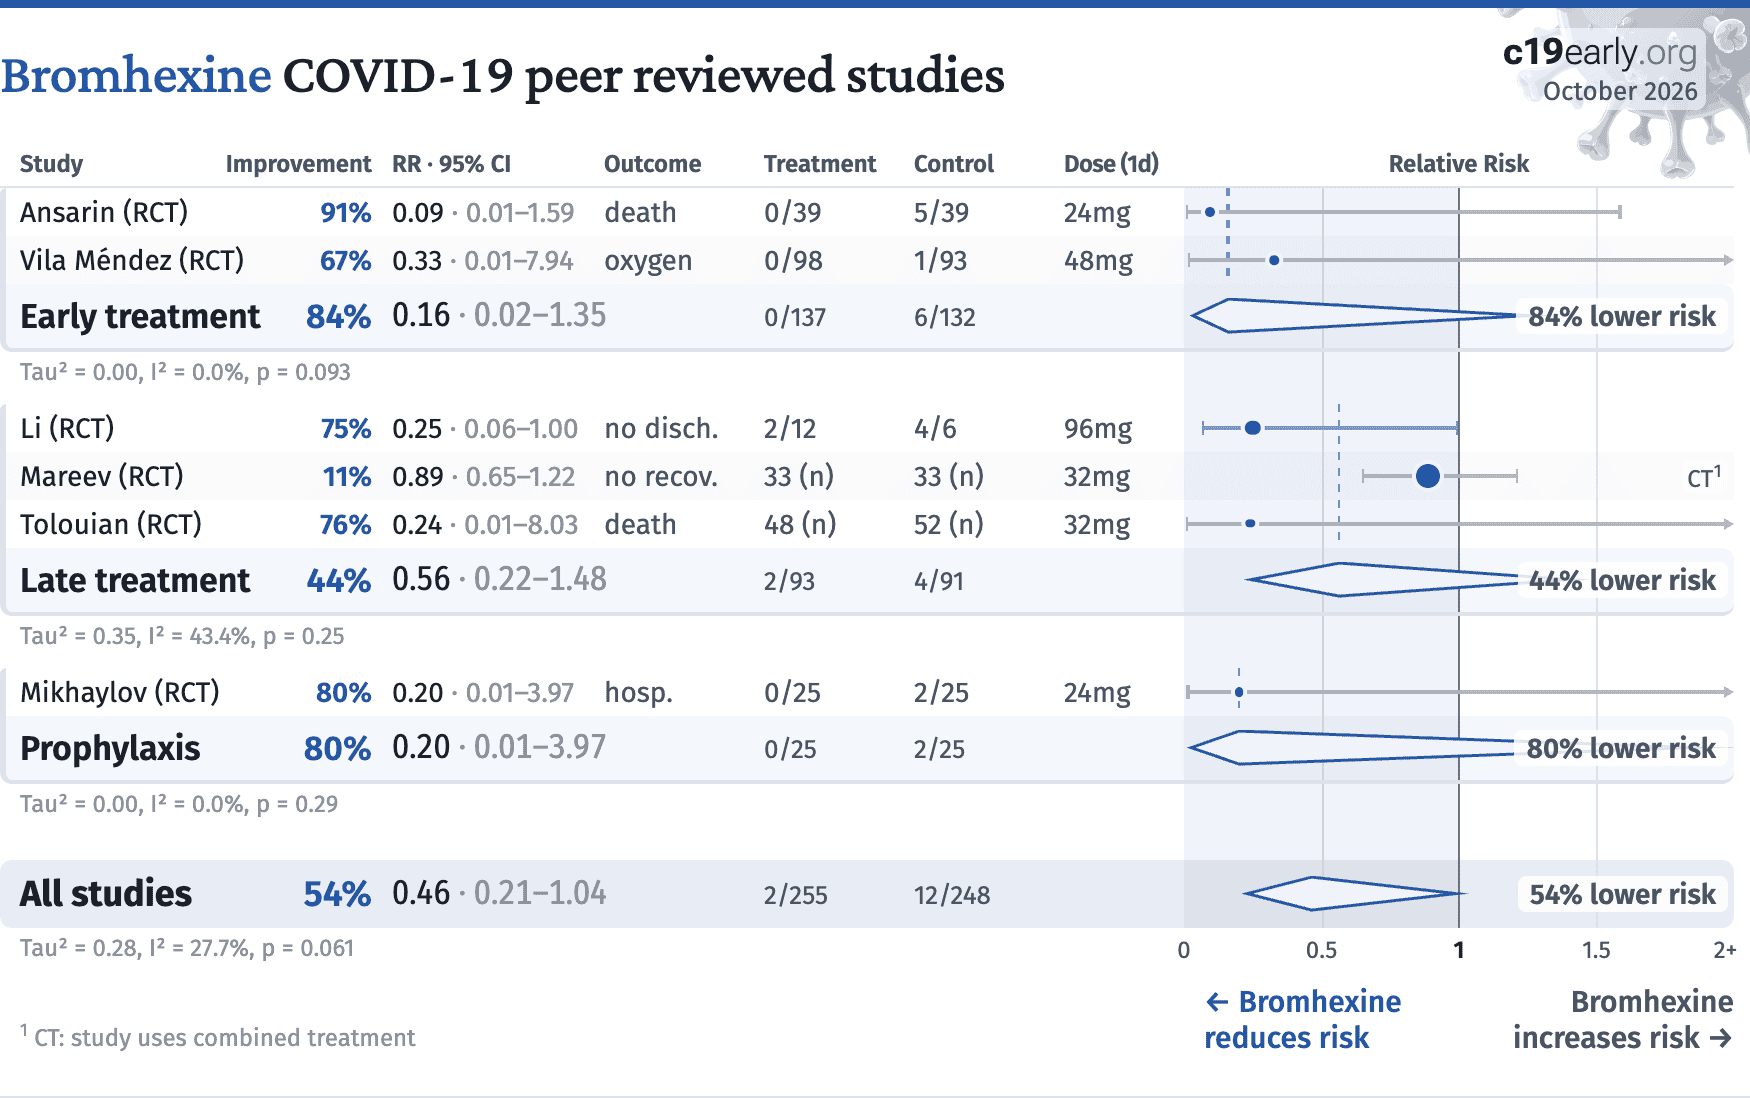
Ansarin, 7/19/2020, Randomized Controlled Trial, Iran, peer-reviewed, 11 authors, study period 18 April, 2020 - 19 May, 2020.
|
risk of death, 90.9% lower, RR 0.09, p = 0.05, treatment 0 of 39 (0.0%), control 5 of 39 (12.8%), NNT 7.8, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of mechanical ventilation, 88.9% lower, RR 0.11, p = 0.01, treatment 1 of 39 (2.6%), control 9 of 39 (23.1%), NNT 4.9.
|
|
risk of ICU admission, 81.8% lower, RR 0.18, p = 0.01, treatment 2 of 39 (5.1%), control 11 of 39 (28.2%), NNT 4.3.
|
|
Vila Méndez, 12/24/2022, Randomized Controlled Trial, Spain, peer-reviewed, 38 authors, study period 24 February, 2022 - 28 July, 2022, trial EudraCT2021-001227-41.
|
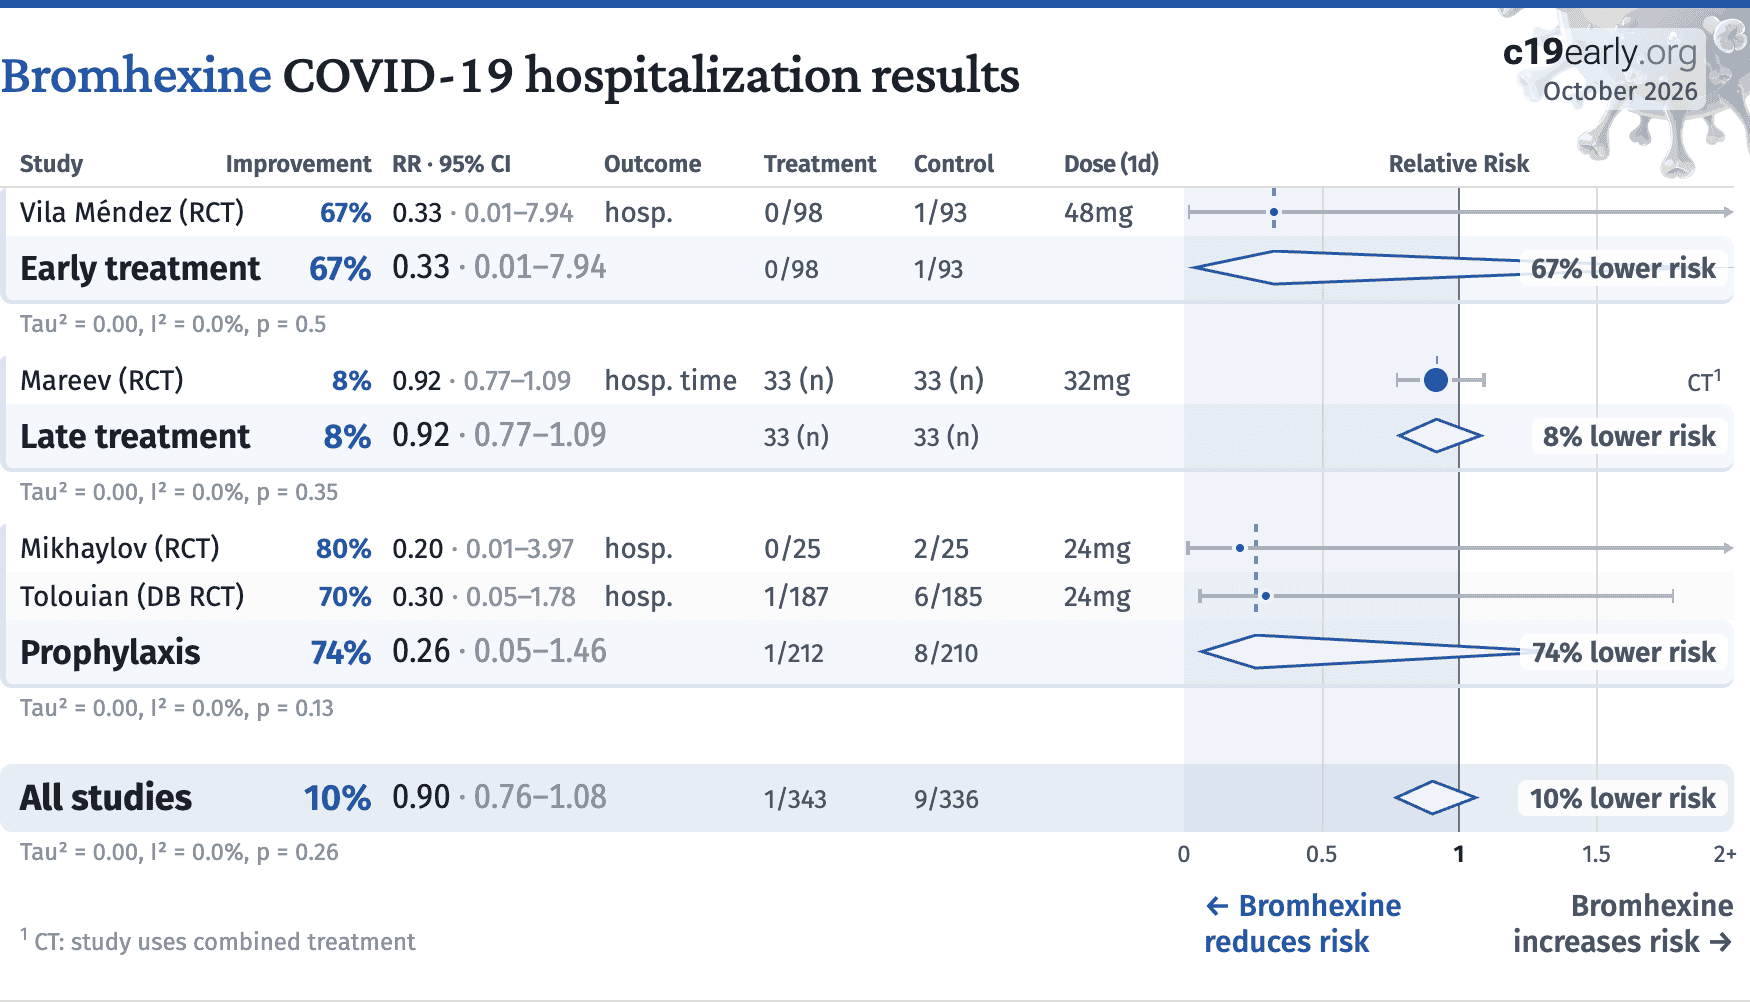
risk of oxygen therapy, 67.3% lower, RR 0.33, p = 0.49, treatment 0 of 98 (0.0%), control 1 of 93 (1.1%), NNT 93, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 67.3% lower, RR 0.33, p = 0.49, treatment 0 of 98 (0.0%), control 1 of 93 (1.1%), NNT 93, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
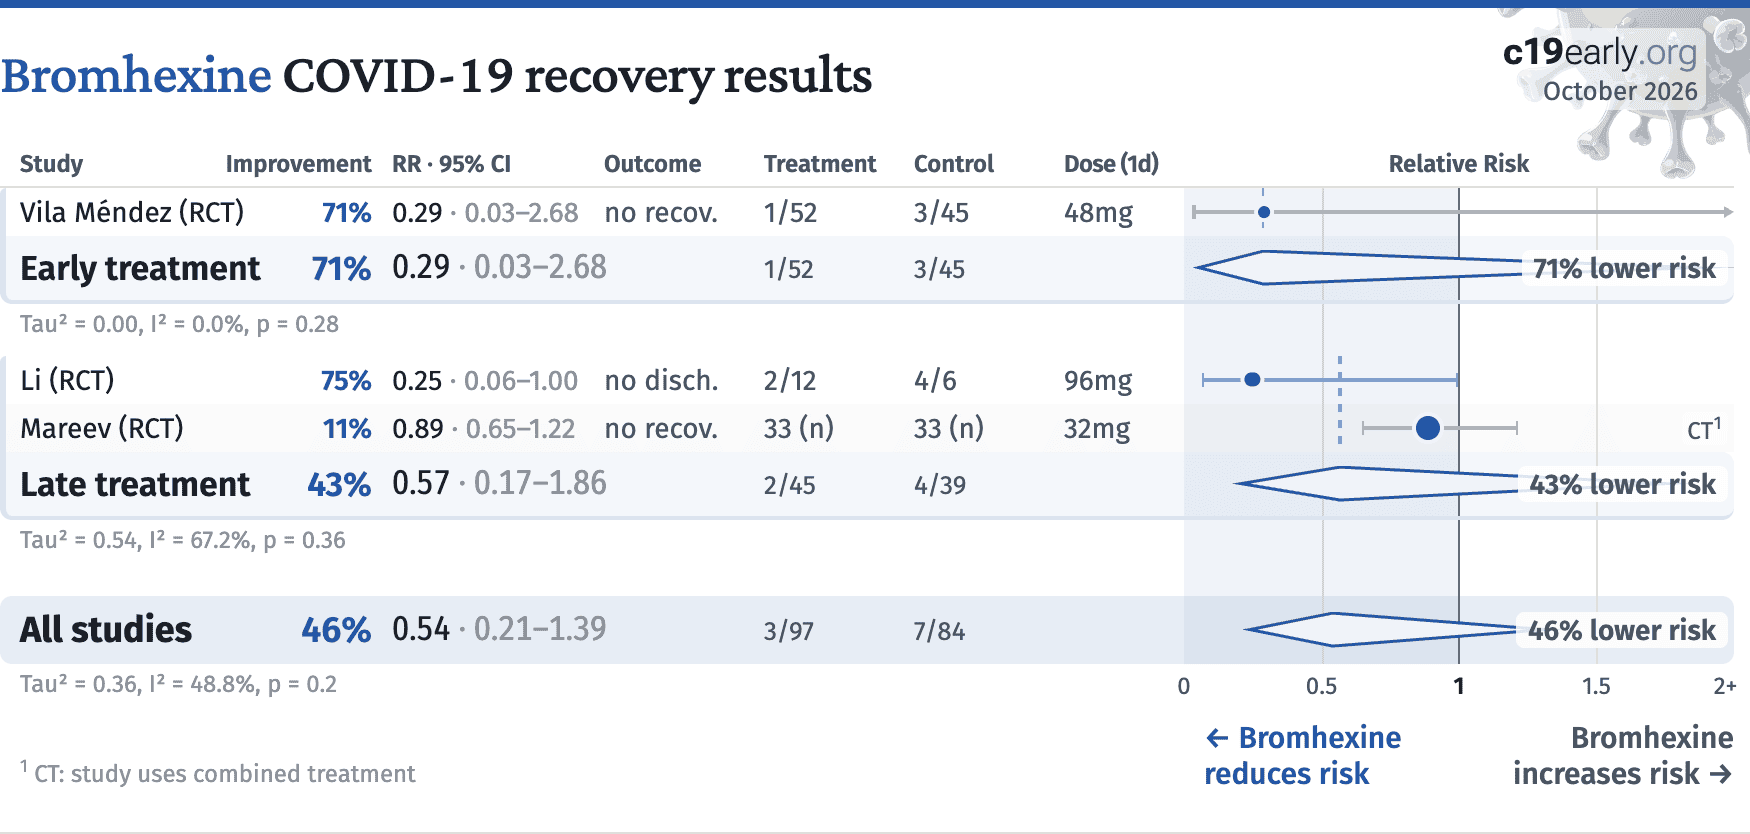
risk of no recovery, 71.2% lower, RR 0.29, p = 0.33, treatment 1 of 52 (1.9%), control 3 of 45 (6.7%), NNT 21, dyspnea.
|
|
risk of no recovery, 186.5% higher, RR 2.87, p = 1.00, treatment 1 of 52 (1.9%), control 0 of 45 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), fever.
|
|
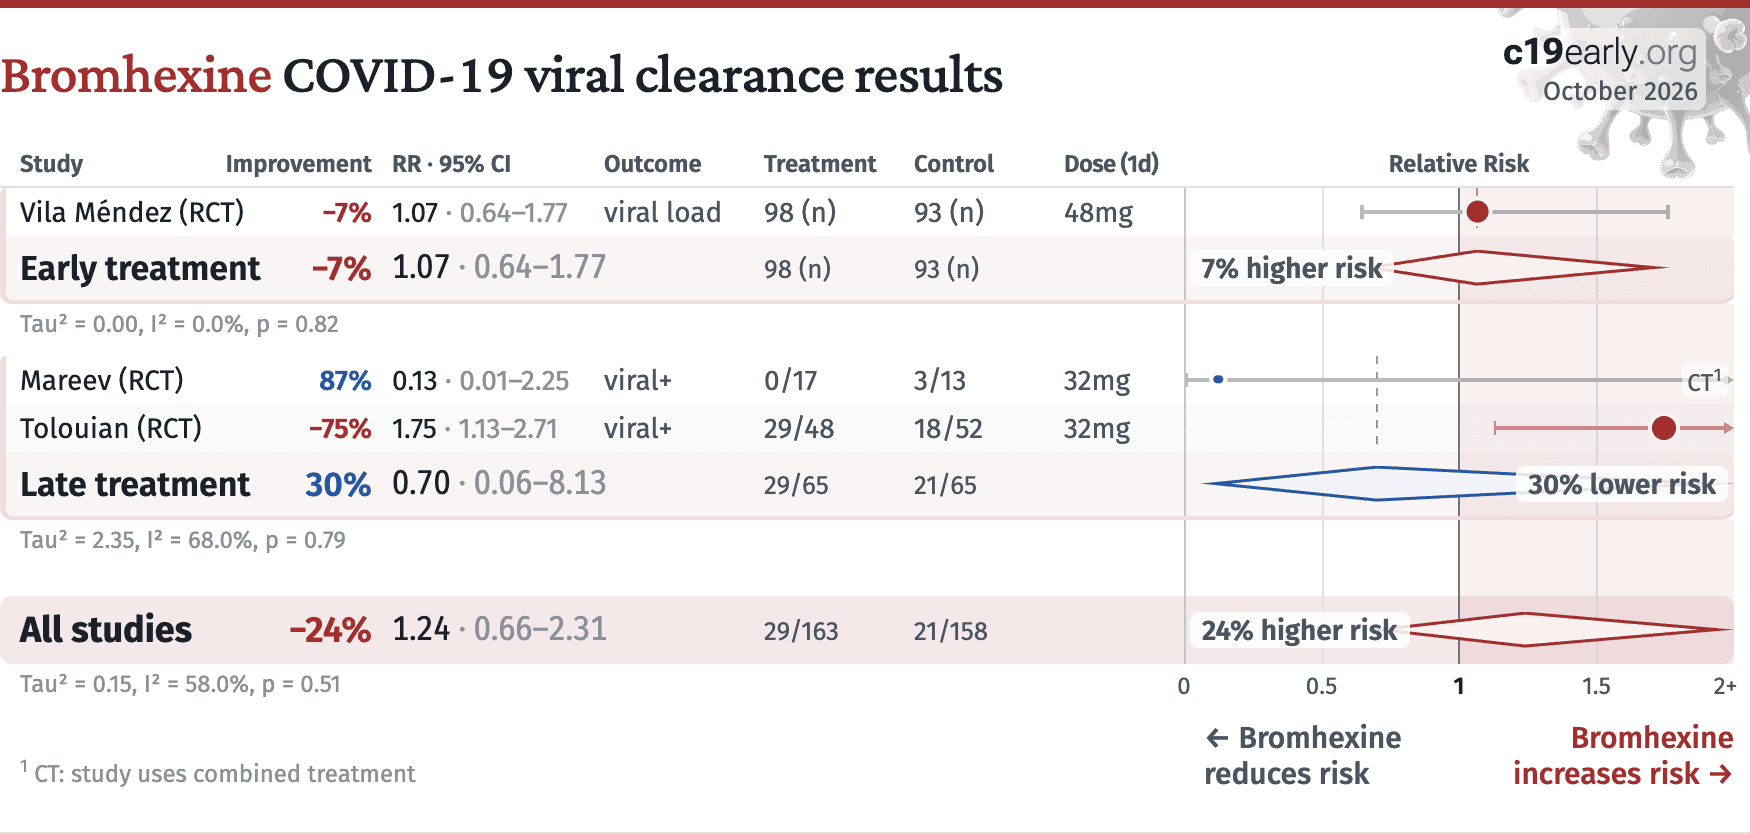
viral load, 6.6% higher, relative load 1.07, p = 0.82, treatment mean 13.54 (±26.02) n=98, control mean 14.43 (±26.94) n=93, relative change in ORF1ab Ct value, day 4, primary outcome.
|
|
viral load, 17.4% lower, relative load 0.83, p = 0.60, treatment mean 6.36 (±17.05) n=98, control mean 7.7 (±18.47) n=93, relative change in N Ct value, day 4, primary outcome.
|
|
viral load, 41.5% higher, relative load 1.41, p = 0.32, treatment mean 9.74 (±29.54) n=98, control mean 13.78 (±26.81) n=93, relative change in S Ct value, day 4, primary outcome.
|
|
risk of no viral clearance, 13.4% lower, RR 0.87, p = 0.31, treatment 52 of 98 (53.1%), control 57 of 93 (61.3%), NNT 12, day 14.
|
|
risk of no viral clearance, 13.6% higher, RR 1.14, p = 0.21, treatment 73 of 98 (74.5%), control 61 of 93 (65.6%), day 7.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Li, 9/3/2020, Randomized Controlled Trial, China, peer-reviewed, 10 authors, study period 16 February, 2020 - 10 May, 2020, trial NCT04273763 (history).
|
risk of no hospital discharge, 75.0% lower, RR 0.25, p = 0.11, treatment 2 of 12 (16.7%), control 4 of 6 (66.7%), NNT 2.0.
|
|
risk of oxygen therapy, 50.0% lower, RR 0.50, p = 0.57, treatment 2 of 12 (16.7%), control 2 of 6 (33.3%), NNT 6.0.
|
|
Mareev, 12/3/2020, Randomized Controlled Trial, Russia, peer-reviewed, 20 authors, this trial uses multiple treatments in the treatment arm (combined with spironolactone) - results of individual treatments may vary, trial NCT04424134 (history).
|
relative SHOKS-COVID score, 11.3% better, RR 0.89, p = 0.47, treatment mean 2.12 (±1.39) n=33, control mean 2.39 (±1.59) n=33.
|
|
risk of PCR+ on day 10 or hospitalization >10 days, 38.8% lower, RR 0.61, p = 0.02, treatment 14 of 24 (58.3%), control 20 of 21 (95.2%), NNT 2.7, odds ratio converted to relative risk.
|
|
hospitalization time, 8.2% lower, relative time 0.92, p = 0.35, treatment 33, control 33.
|
|
risk of no viral clearance, 87.4% lower, RR 0.13, p = 0.08, treatment 0 of 17 (0.0%), control 3 of 13 (23.1%), NNT 4.3, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 10.
|
Mežnar, 7/31/2020, Randomized Controlled Trial, this trial uses multiple treatments in the treatment arm (combined with HCQ) - results of individual treatments may vary, trial NCT04355026 (history).
|
Estimated 90 patient RCT with results unknown and over 6 years late.
|
|
Tolouian, 3/15/2021, Randomized Controlled Trial, Iran, peer-reviewed, 7 authors.
|
risk of death, 76.0% lower, OR 0.24, p = 0.43, treatment 48, control 52, adjusted per study, Table 3, RR approximated with OR.
|
|
risk of no improvement, 75.9% better, OR 0.24, p = 0.43, treatment 48, control 52, adjusted per study, inverted to make OR<1 favor treatment, Table 2, RR approximated with OR.
|
|
risk of no viral clearance, 74.5% higher, RR 1.75, p = 0.02, treatment 29 of 48 (60.4%), control 18 of 52 (34.6%), mid-recovery day 7.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
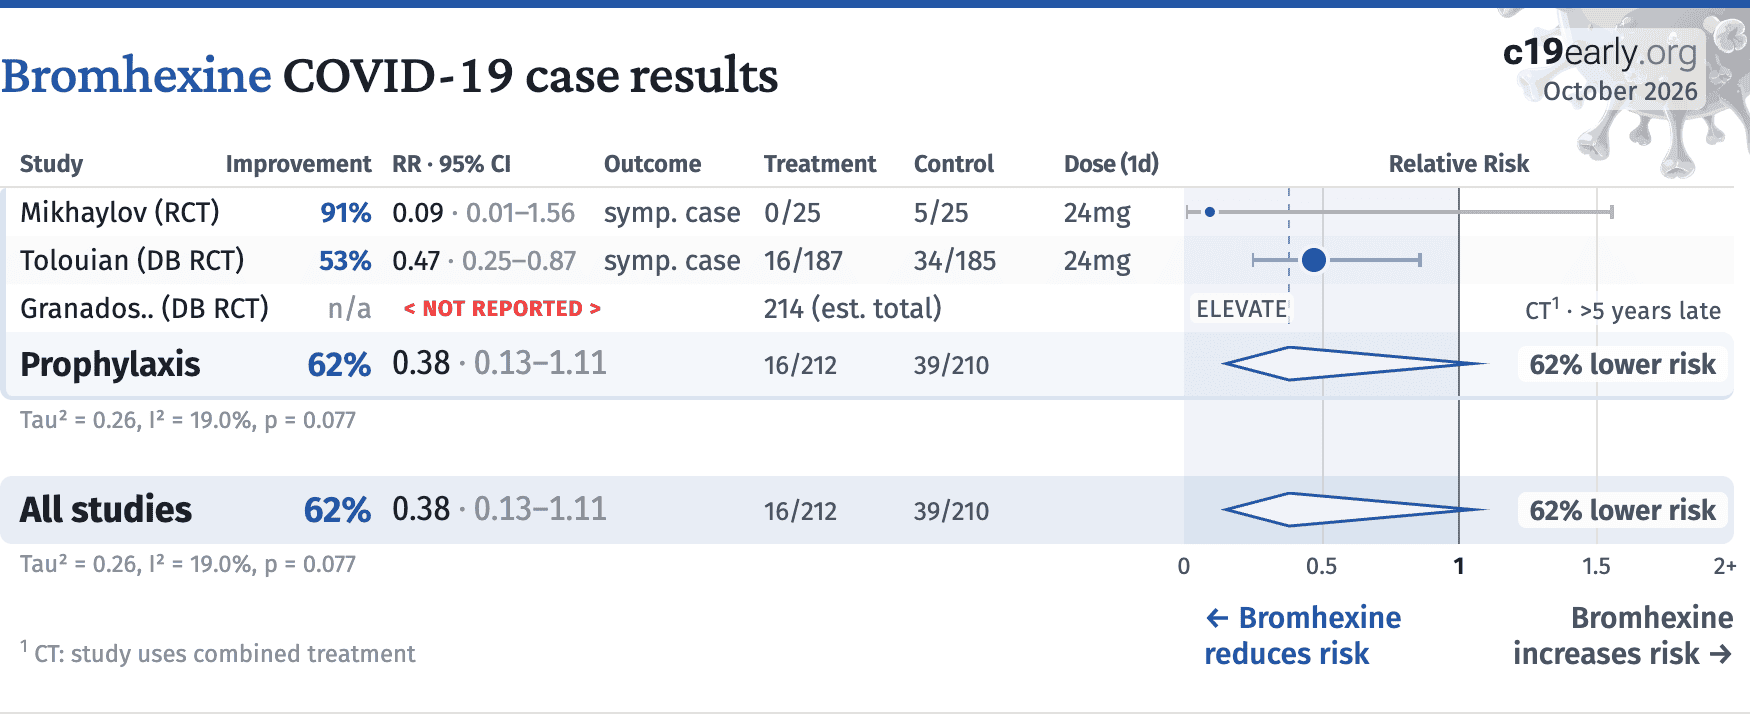
Granados-Montiel, 6/30/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Mexico, peer-reviewed, this trial uses multiple treatments in the treatment arm (combined with HCQ) - results of individual treatments may vary, trial NCT04340349 (history) (ELEVATE).
|
Estimated 214 patient RCT with results unknown and over 5 years late.
|
|
Mikhaylov, 3/8/2021, Randomized Controlled Trial, Russia, peer-reviewed, 8 authors, study period 13 May, 2020 - 25 July, 2020, trial NCT04405999 (history).
|
risk of hospitalization, 80.0% lower, RR 0.20, p = 0.49, treatment 0 of 25 (0.0%), control 2 of 25 (8.0%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of symptomatic case, 90.9% lower, RR 0.09, p = 0.05, treatment 0 of 25 (0.0%), control 5 of 25 (20.0%), NNT 5.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of case, 71.4% lower, RR 0.29, p = 0.14, treatment 2 of 25 (8.0%), control 7 of 25 (28.0%), NNT 5.0, primary outcome.
|
|
Tolouian (B), 12/20/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, preprint, 16 authors, study period 21 December, 2020 - 25 July, 2021.
|
risk of death, 32.9% lower, RR 0.67, p = 0.76, treatment 0 of 187 (0.0%), control 1 of 185 (0.5%), odds ratio converted to relative risk, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 70.3% lower, RR 0.30, p = 0.14, treatment 1 of 187 (0.5%), control 6 of 185 (3.2%), adjusted per study, odds ratio converted to relative risk.
|
|
risk of symptomatic case, 53.0% lower, RR 0.47, p = 0.007, treatment 16 of 187 (8.6%), control 34 of 185 (18.4%), NNT 10, odds ratio converted to relative risk.
|
|
risk of case, 50.2% lower, RR 0.50, p = 0.03, treatment 13 of 187 (7.0%), control 26 of 185 (14.1%), NNT 14, odds ratio converted to relative risk.
|