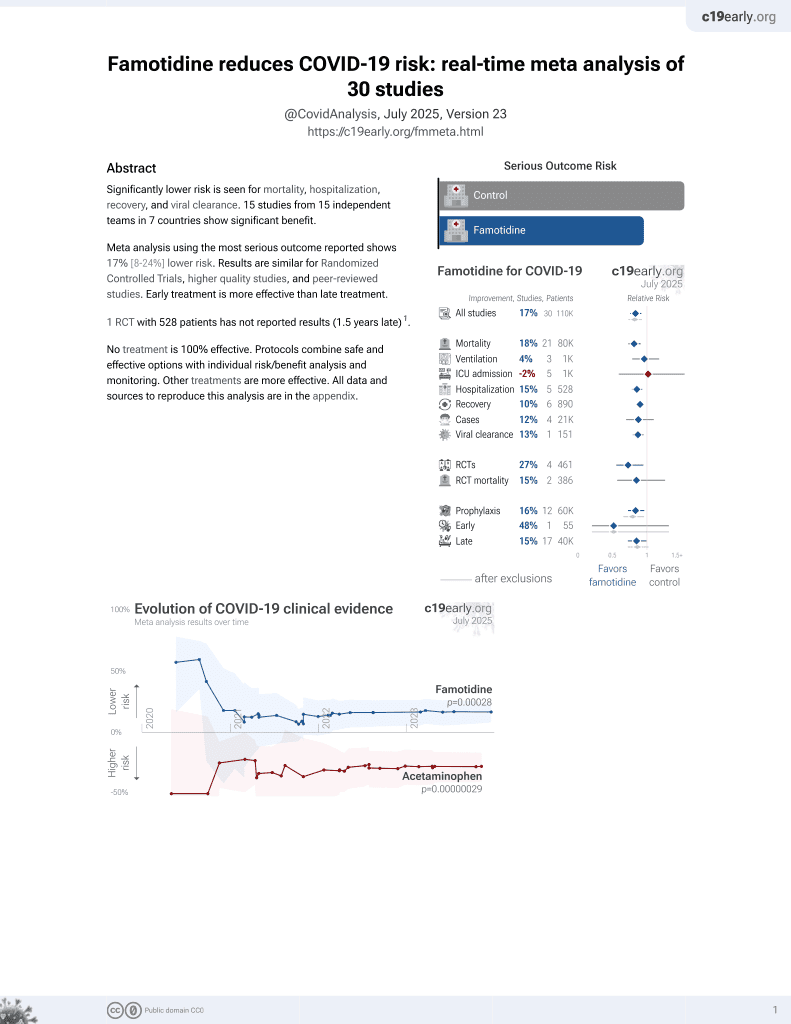
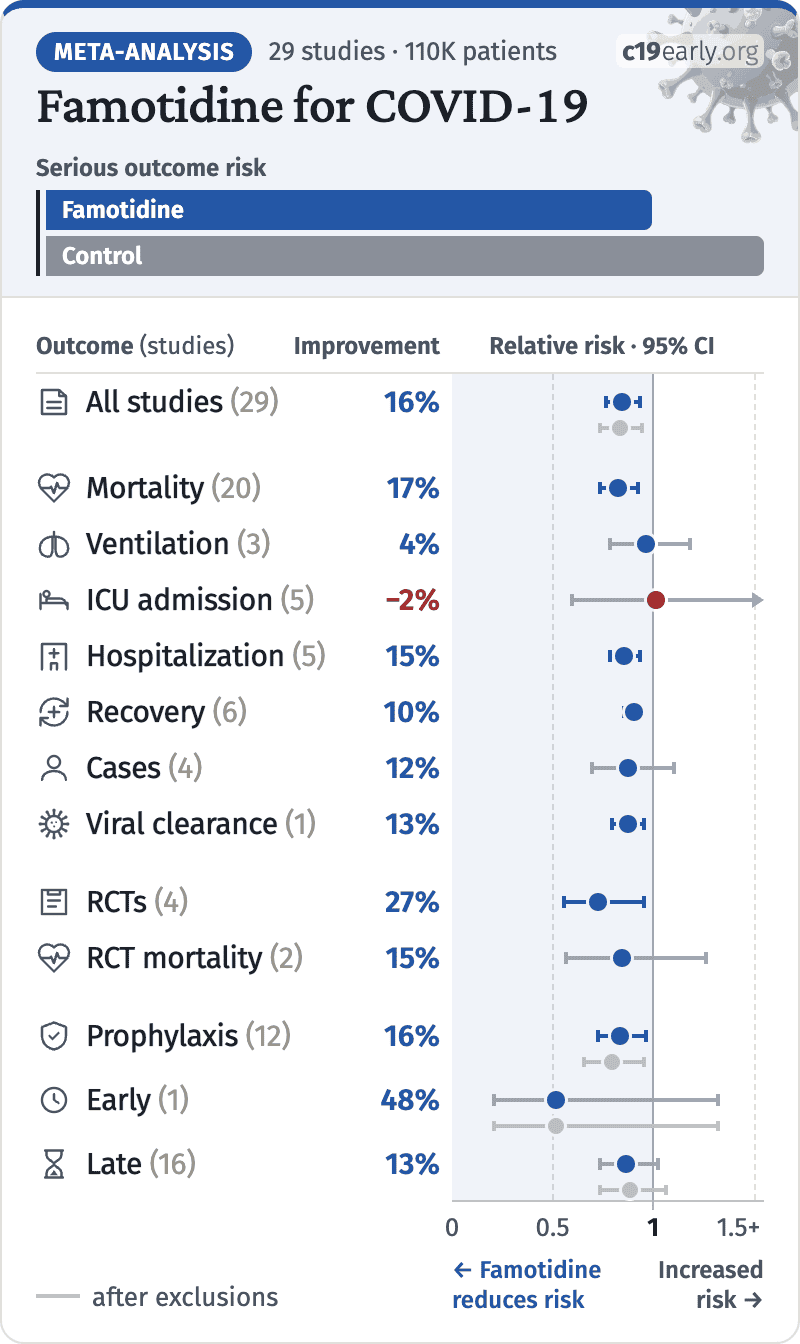
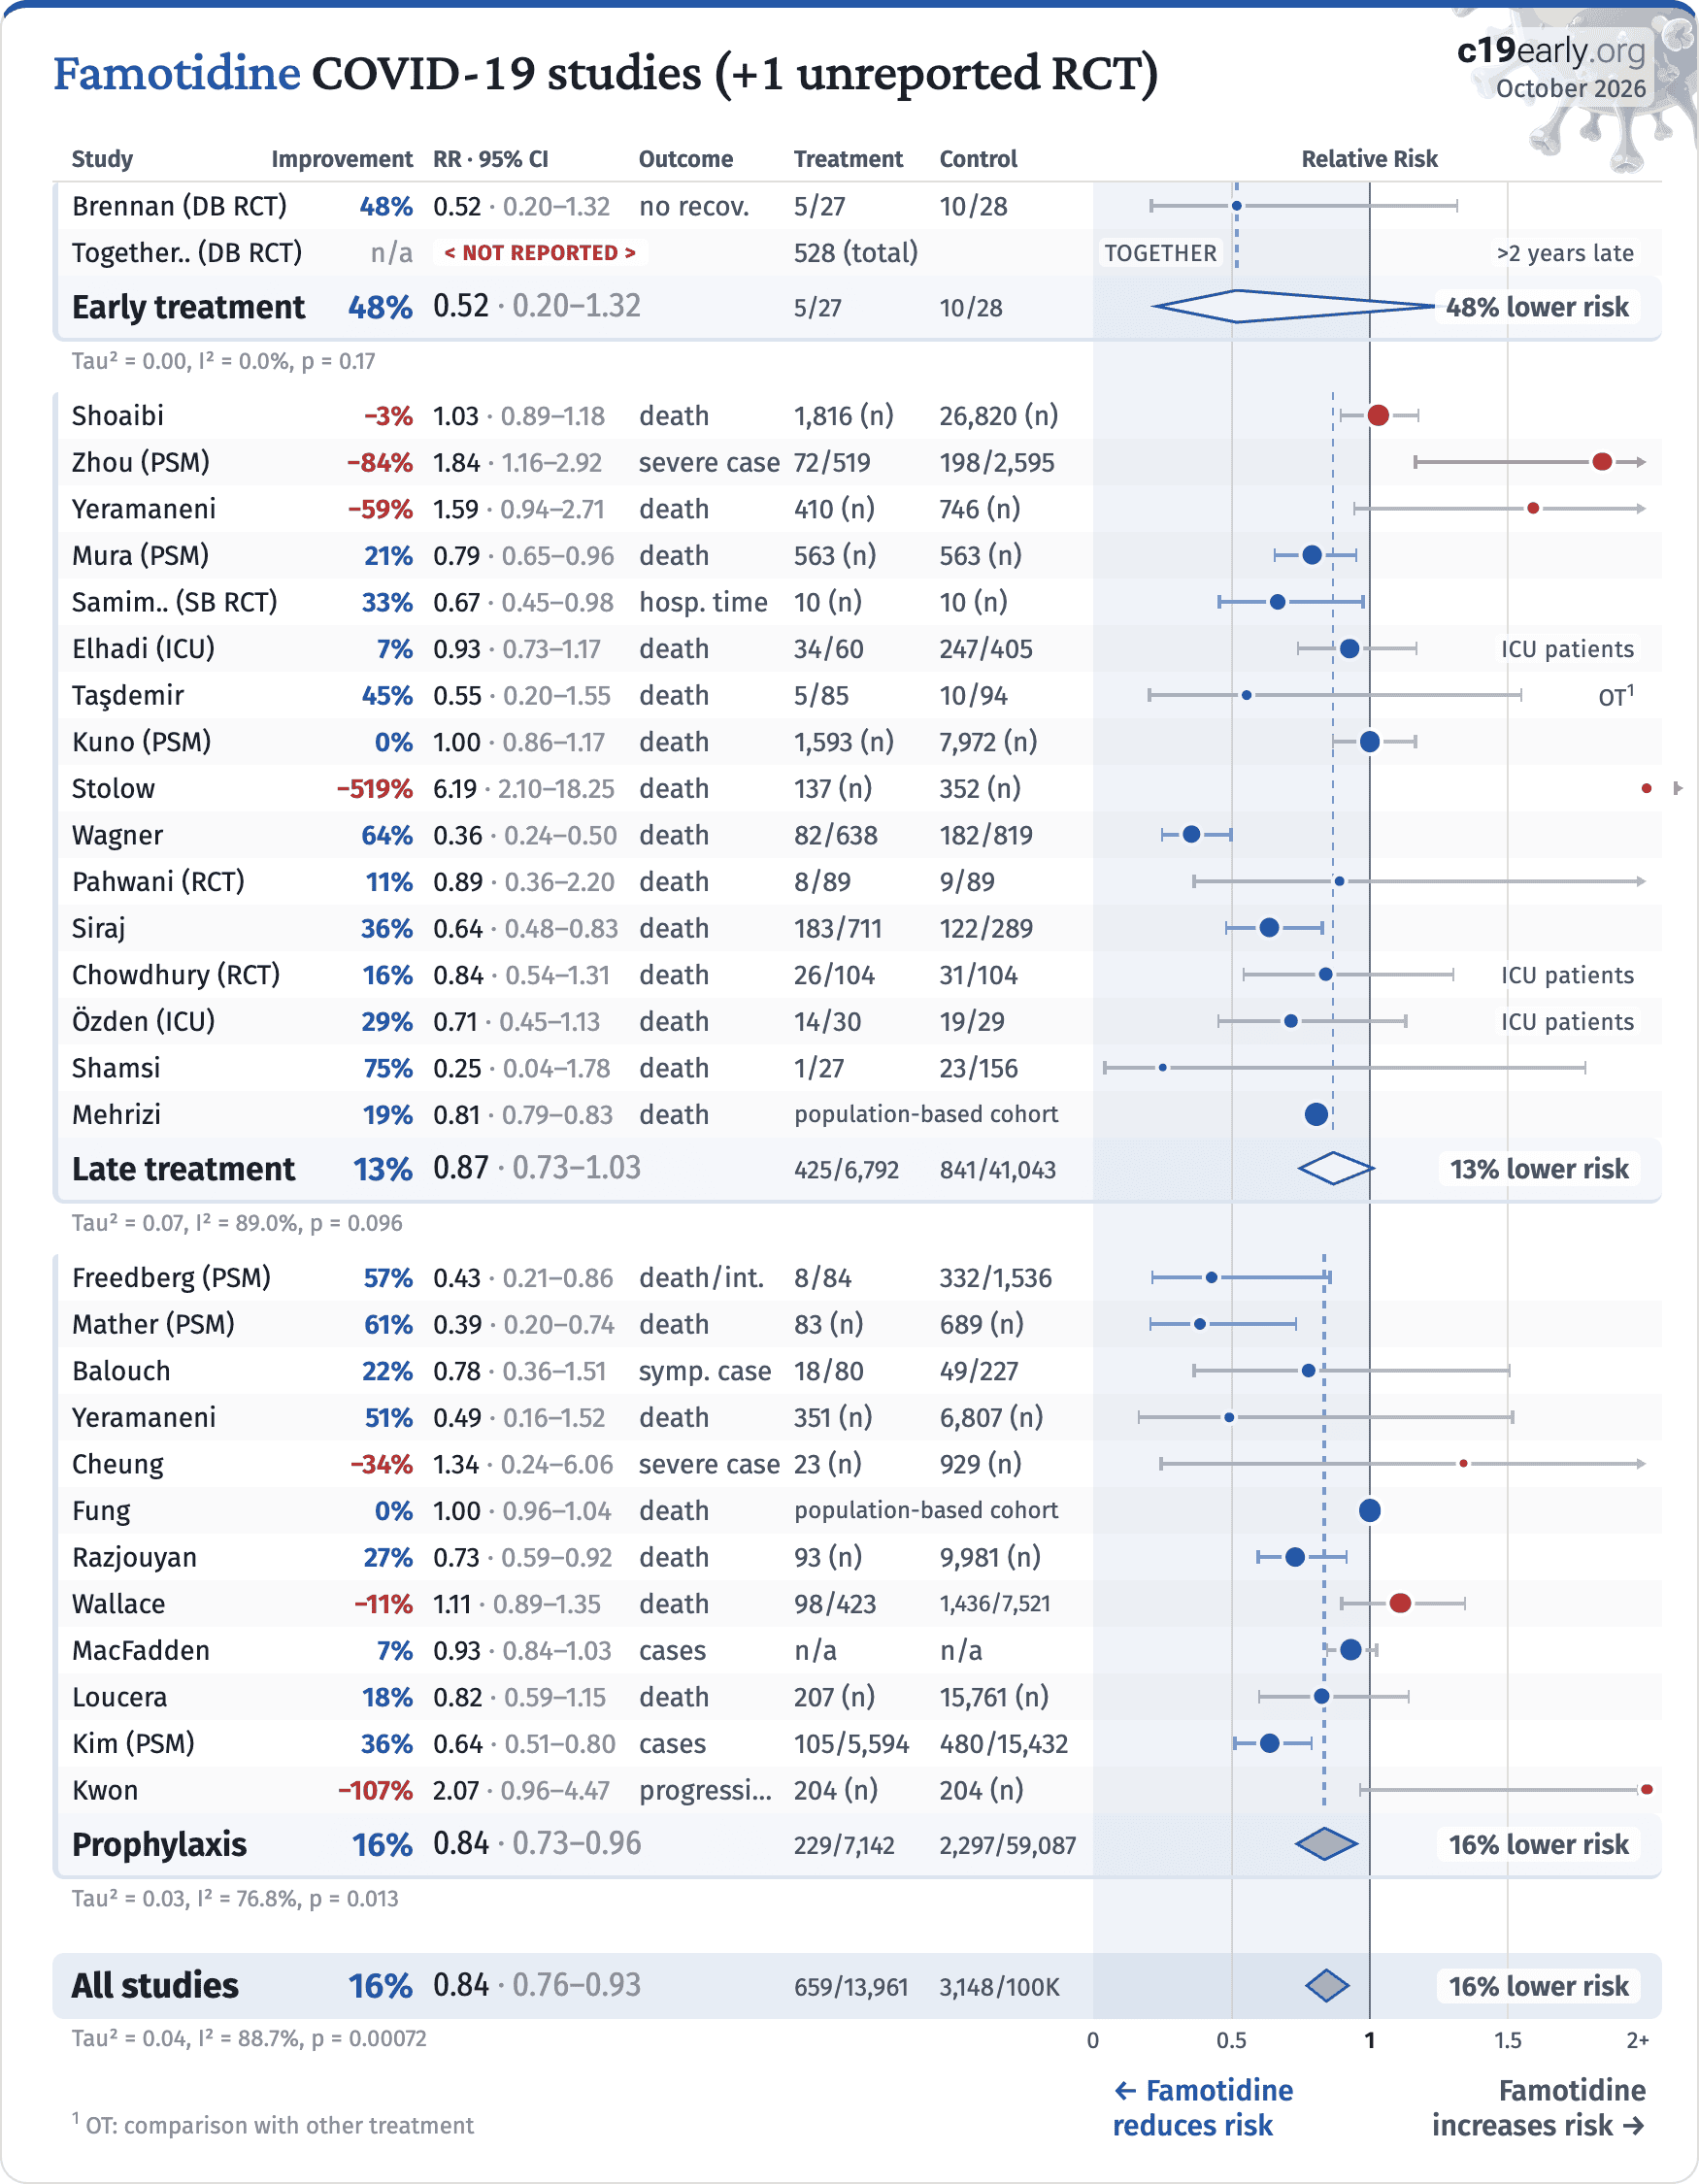
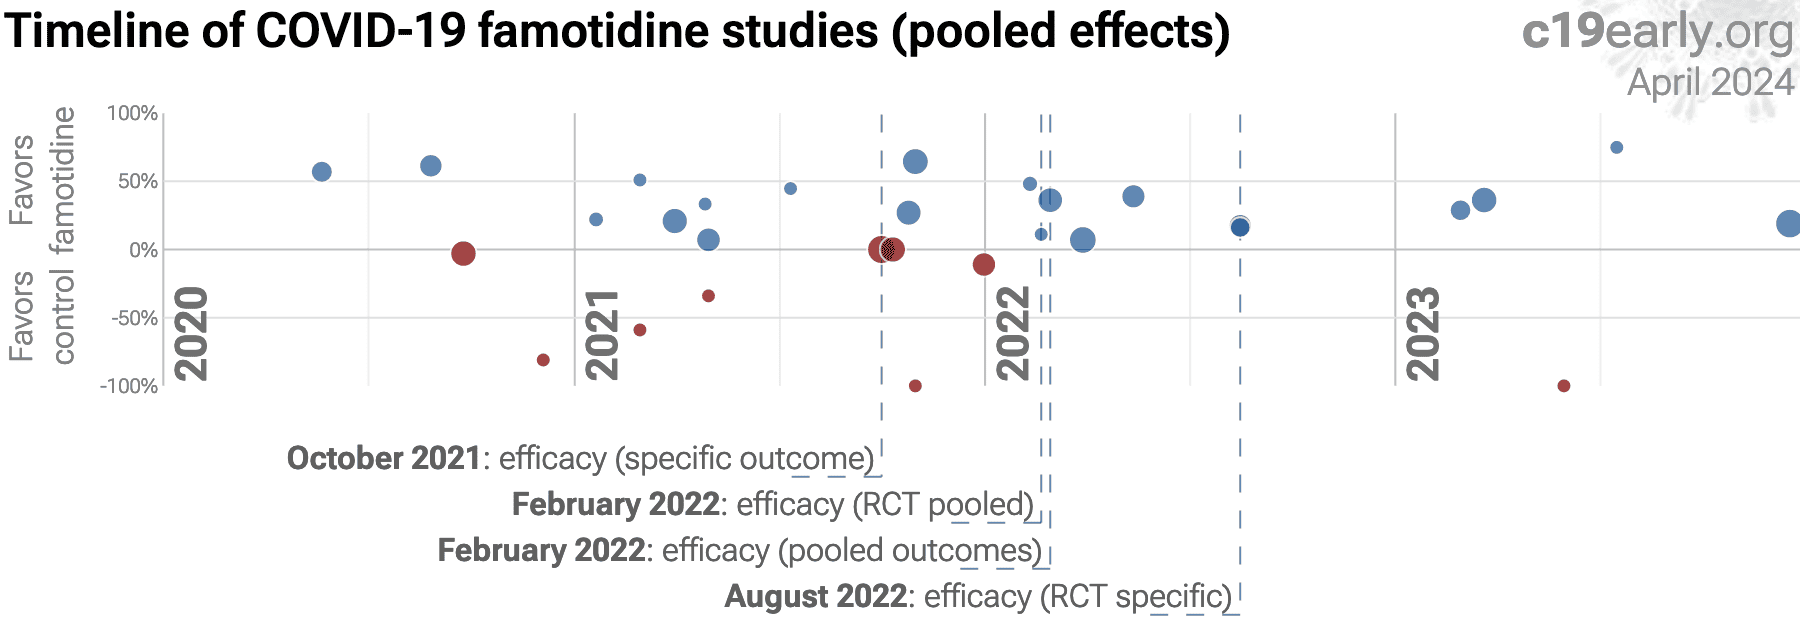
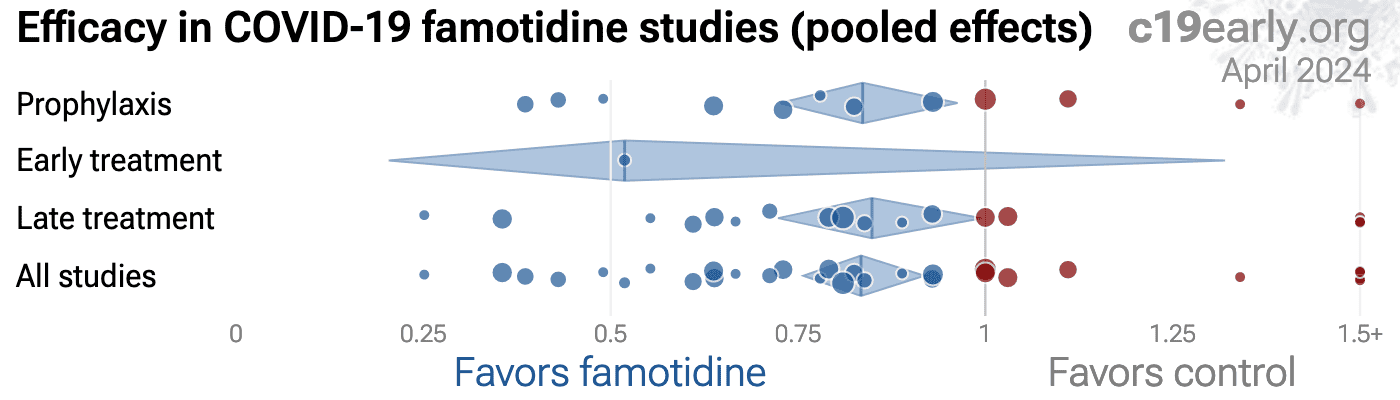
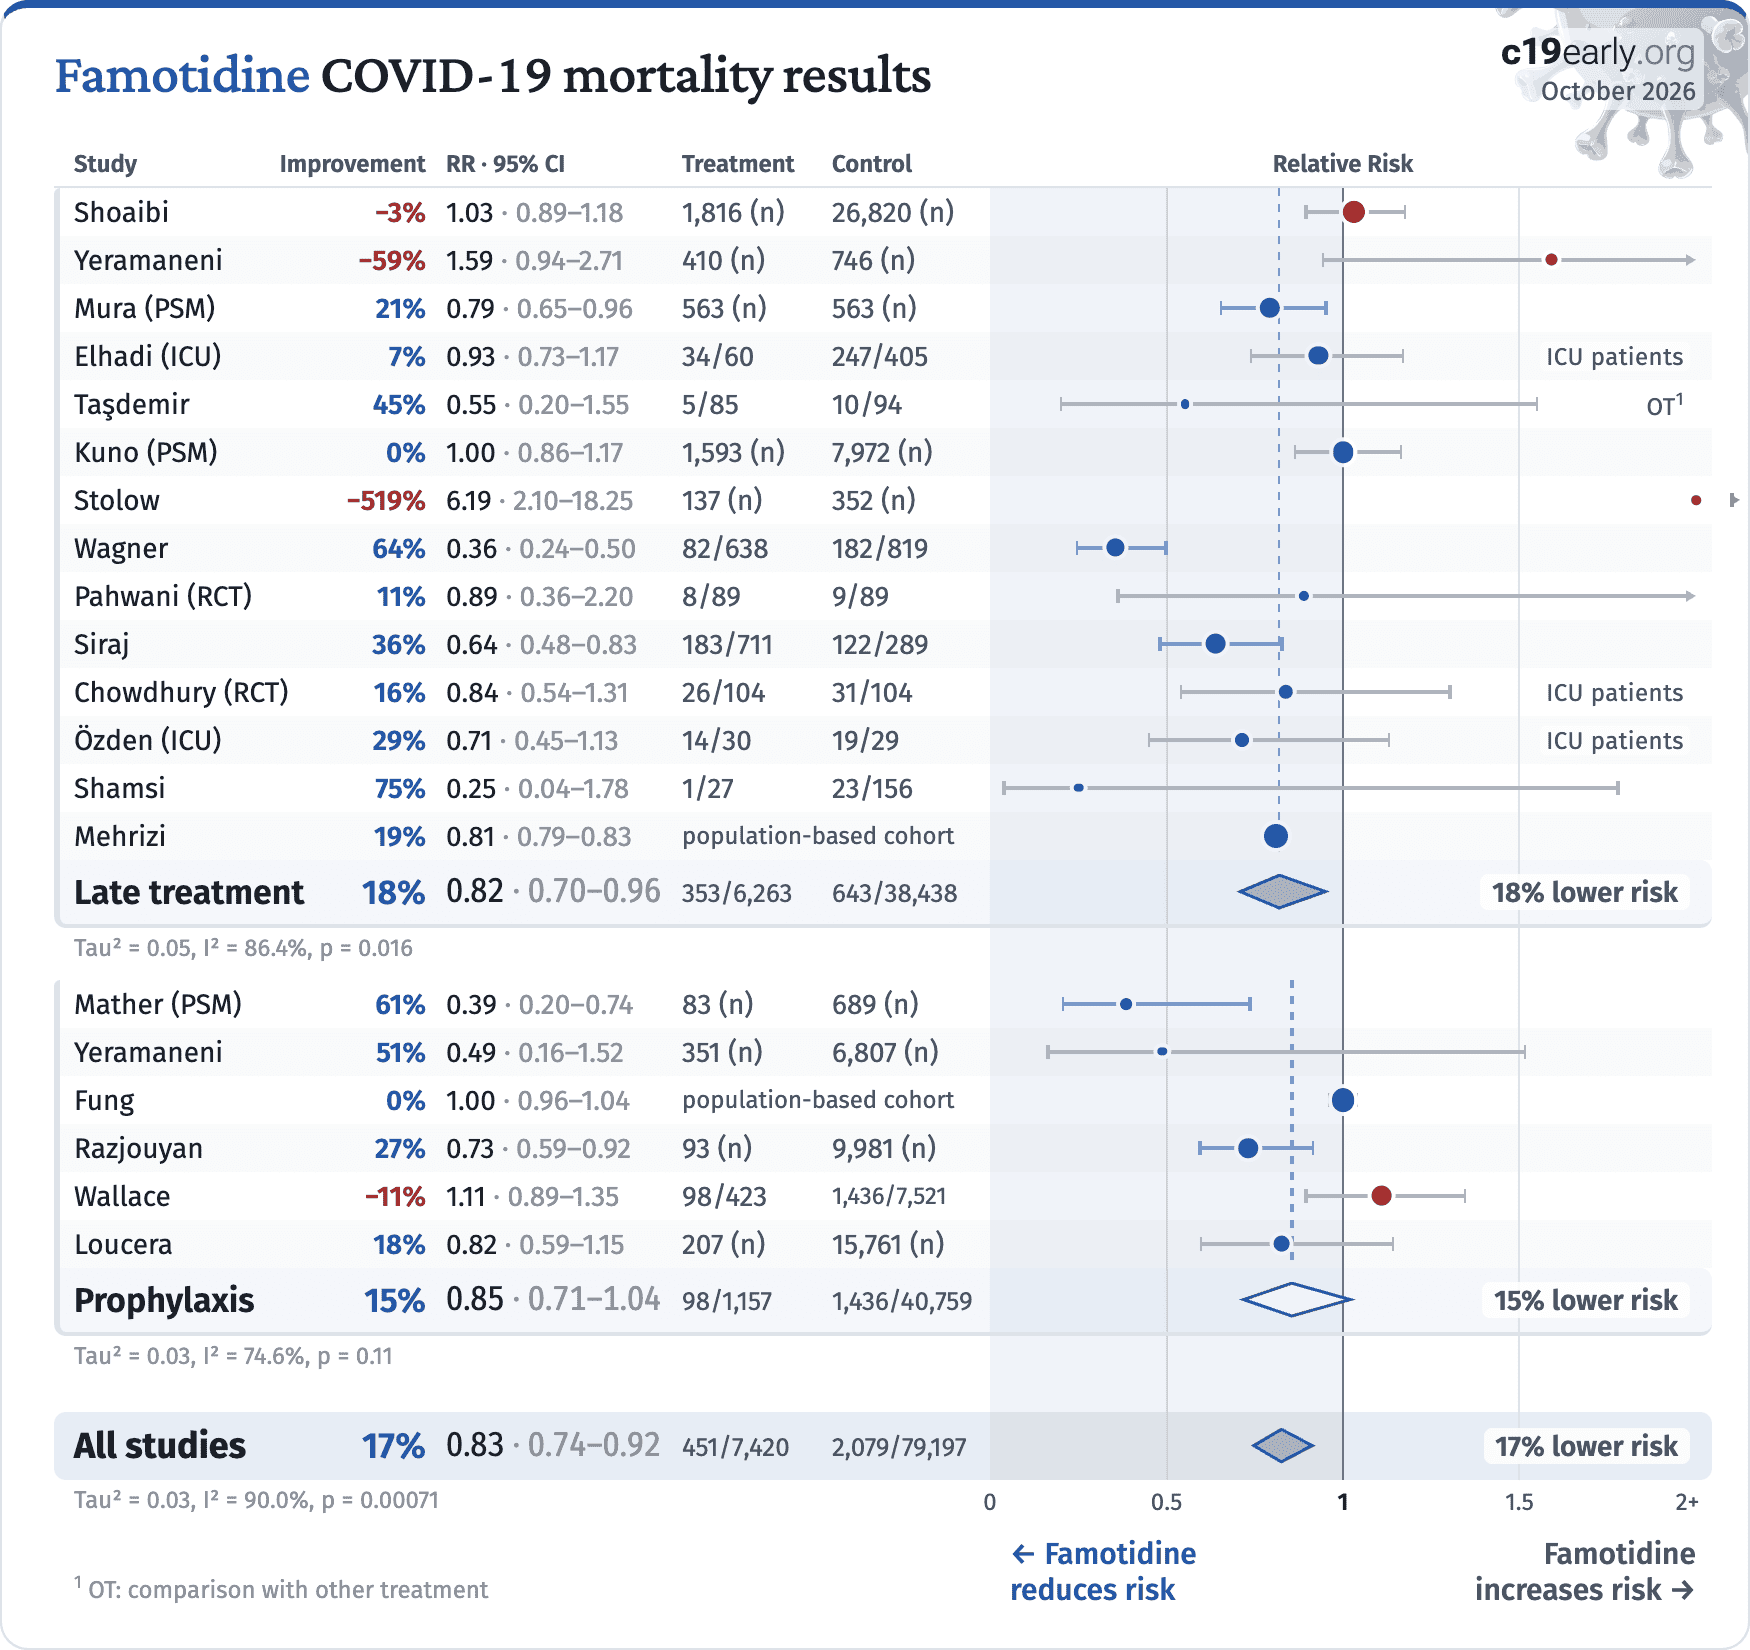
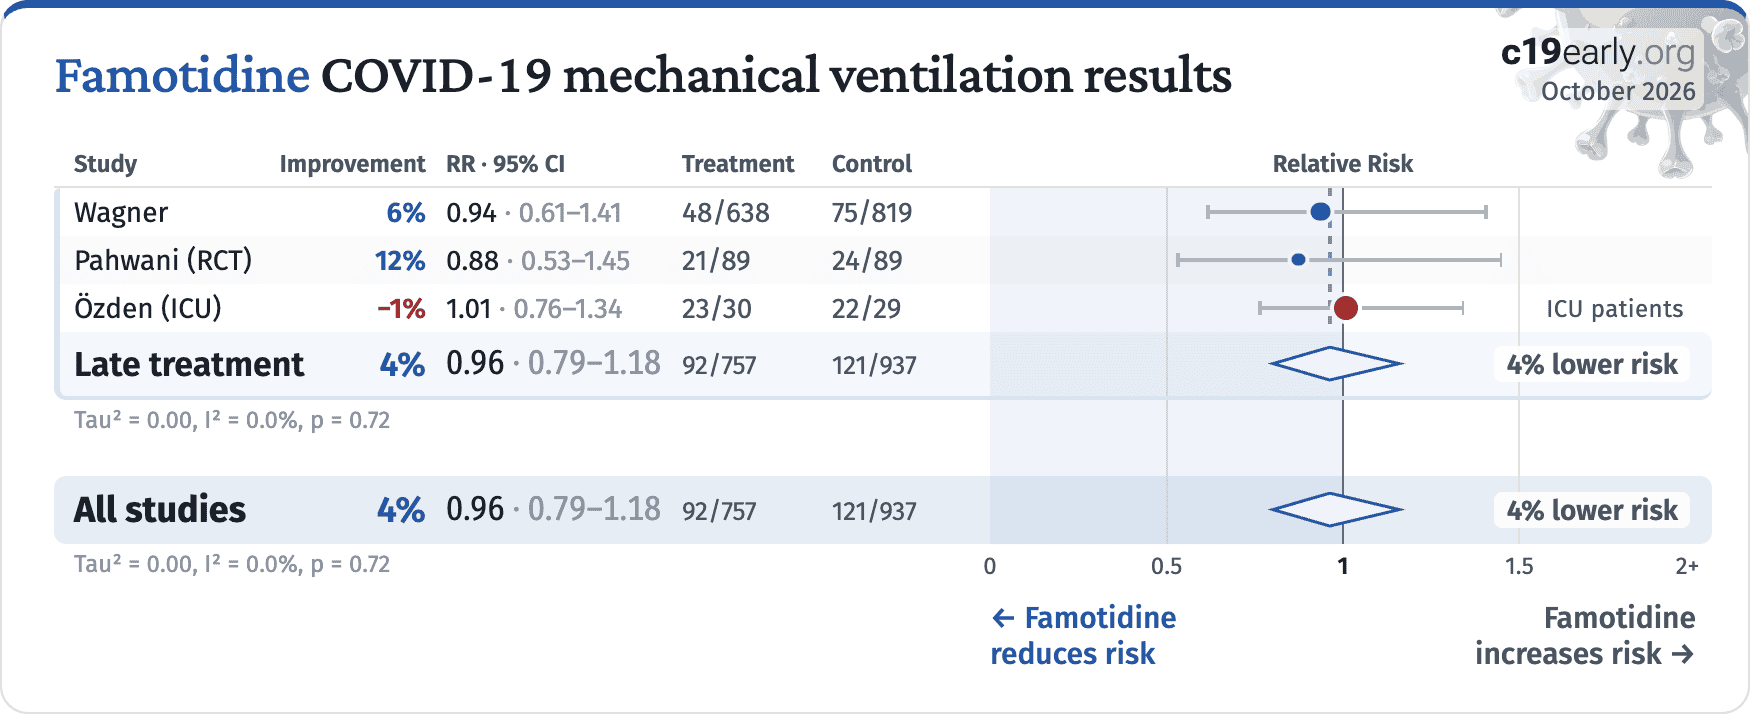
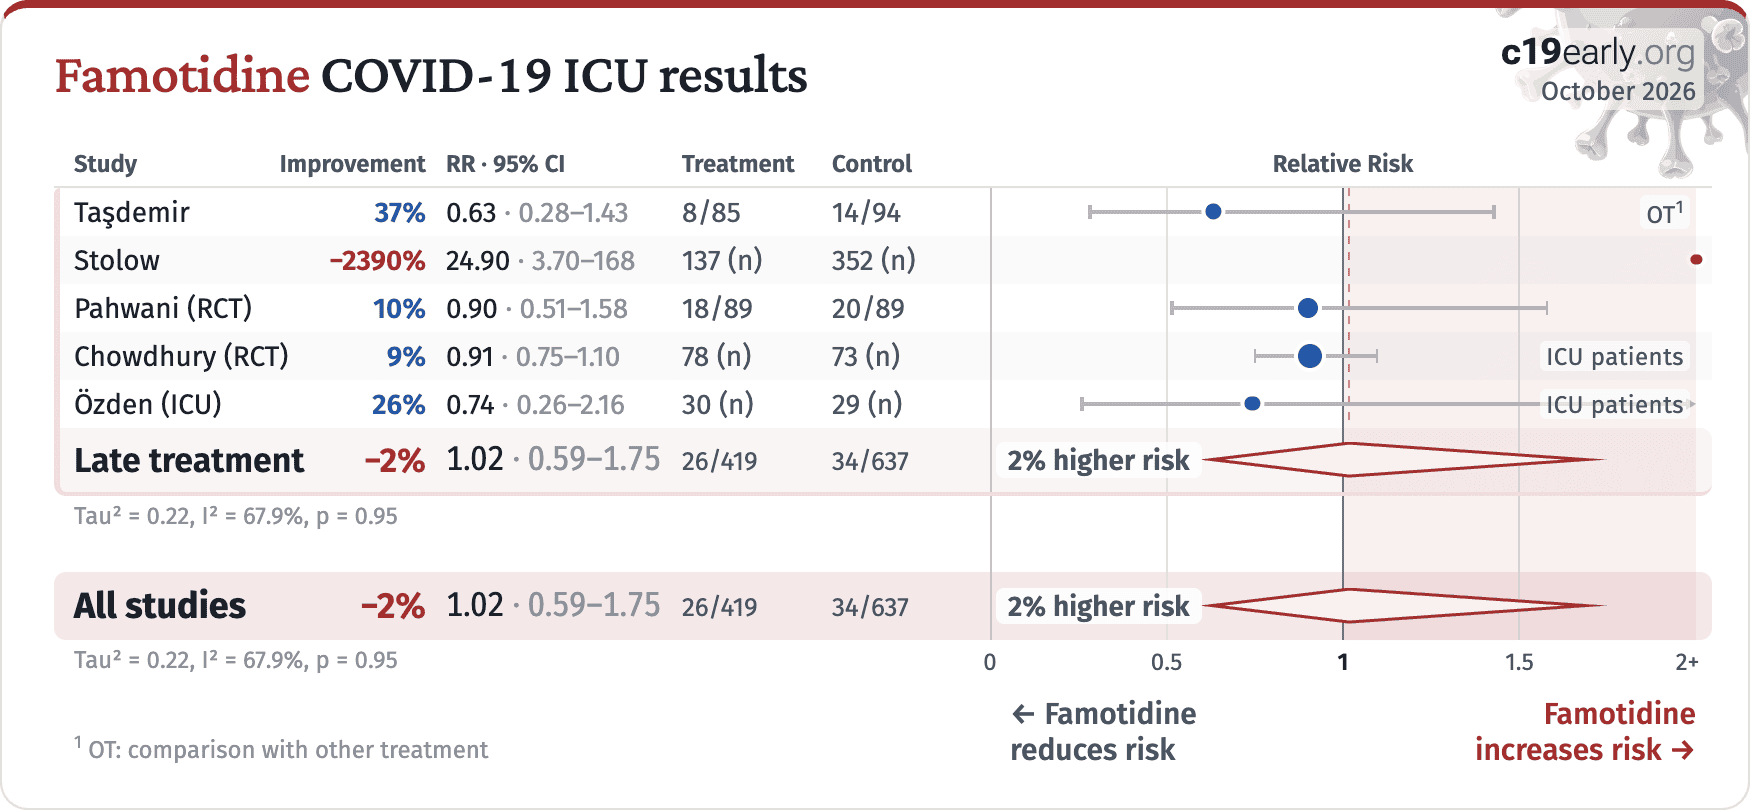
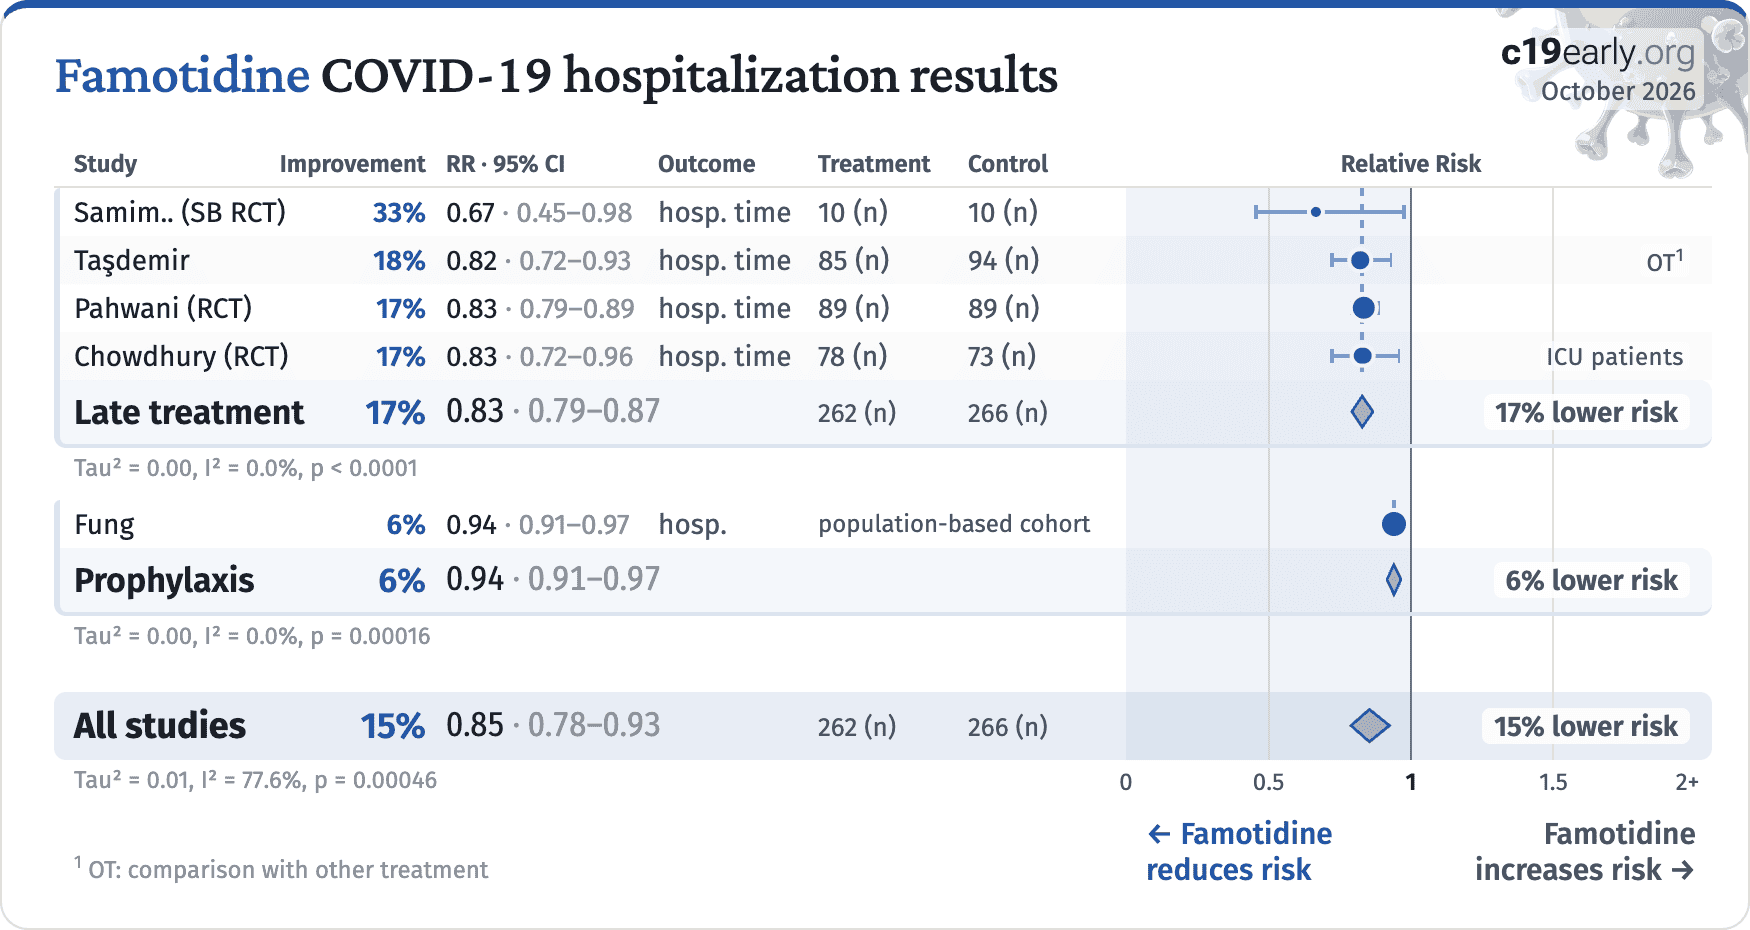
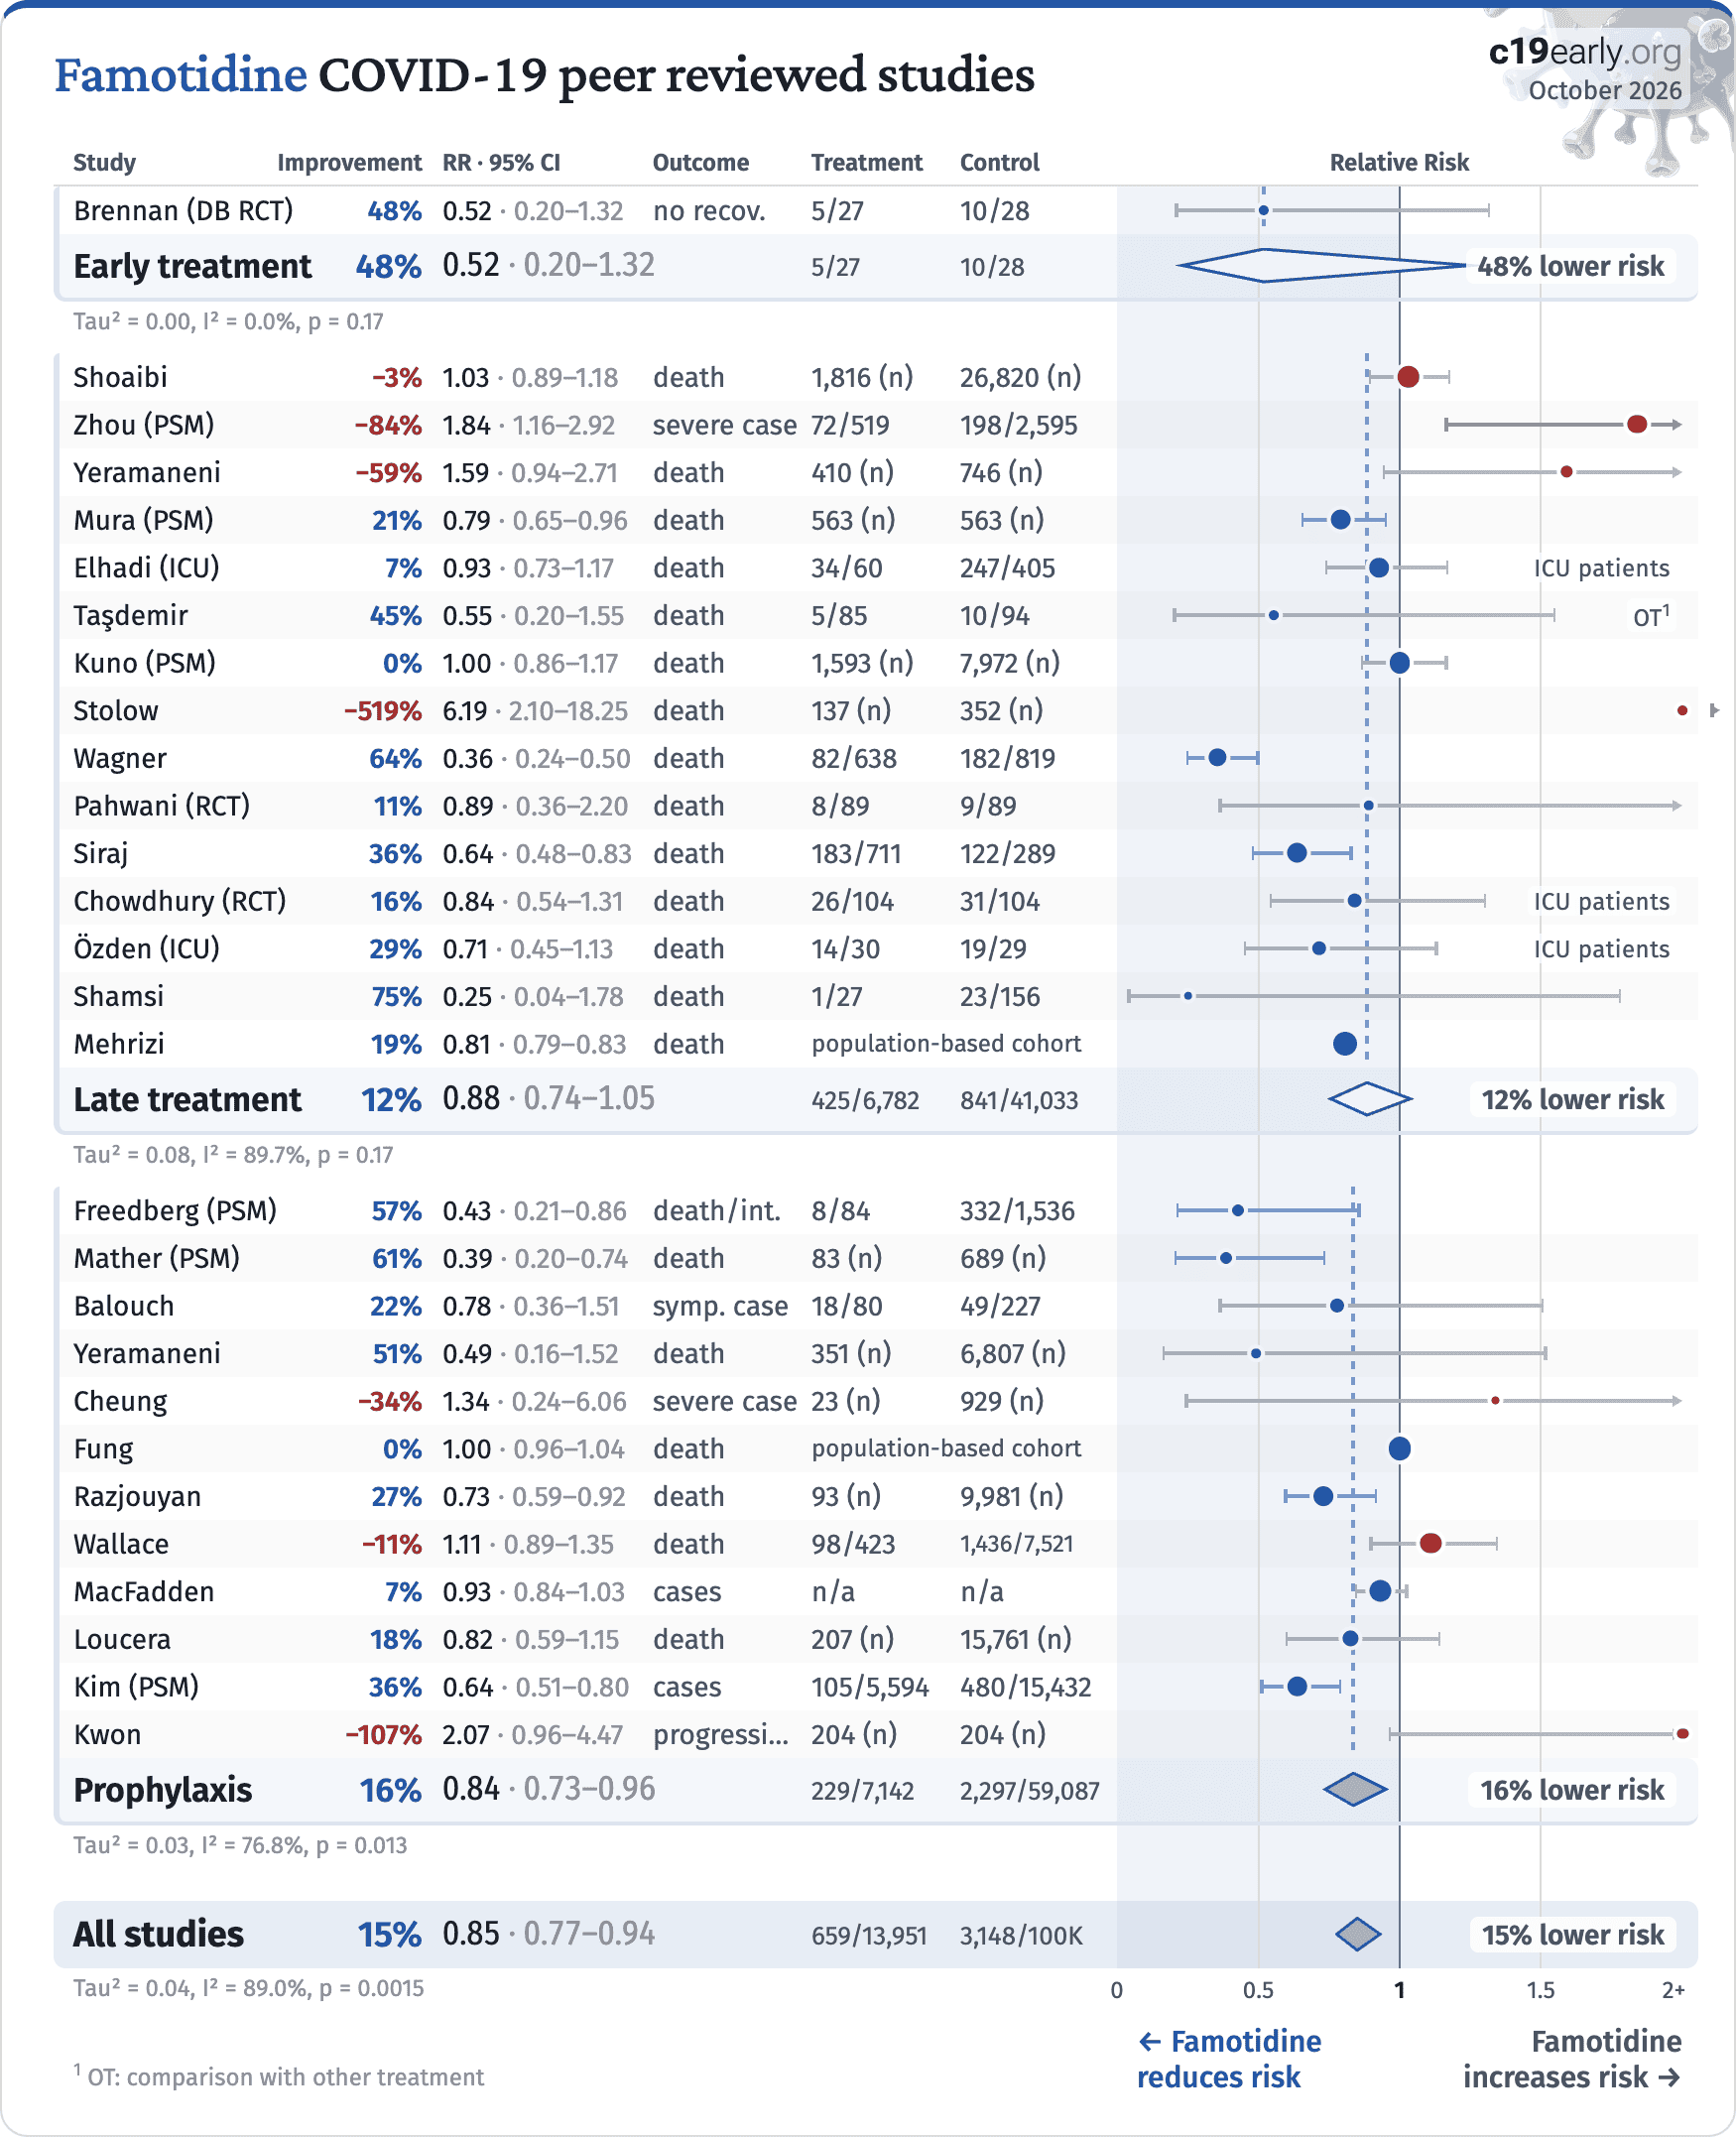
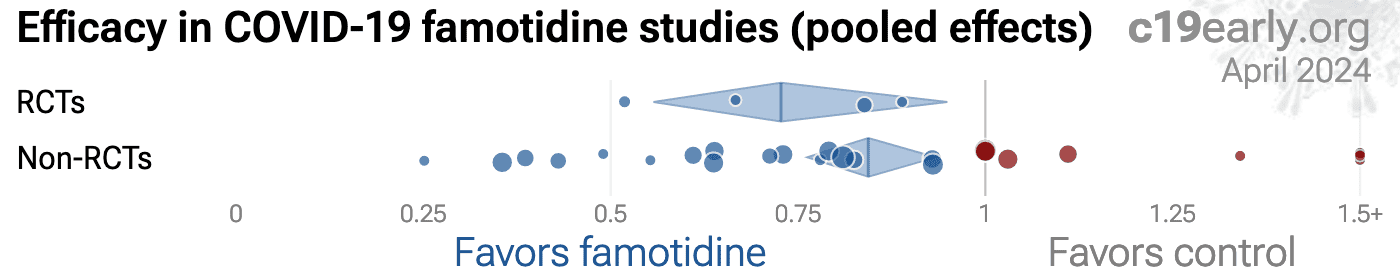
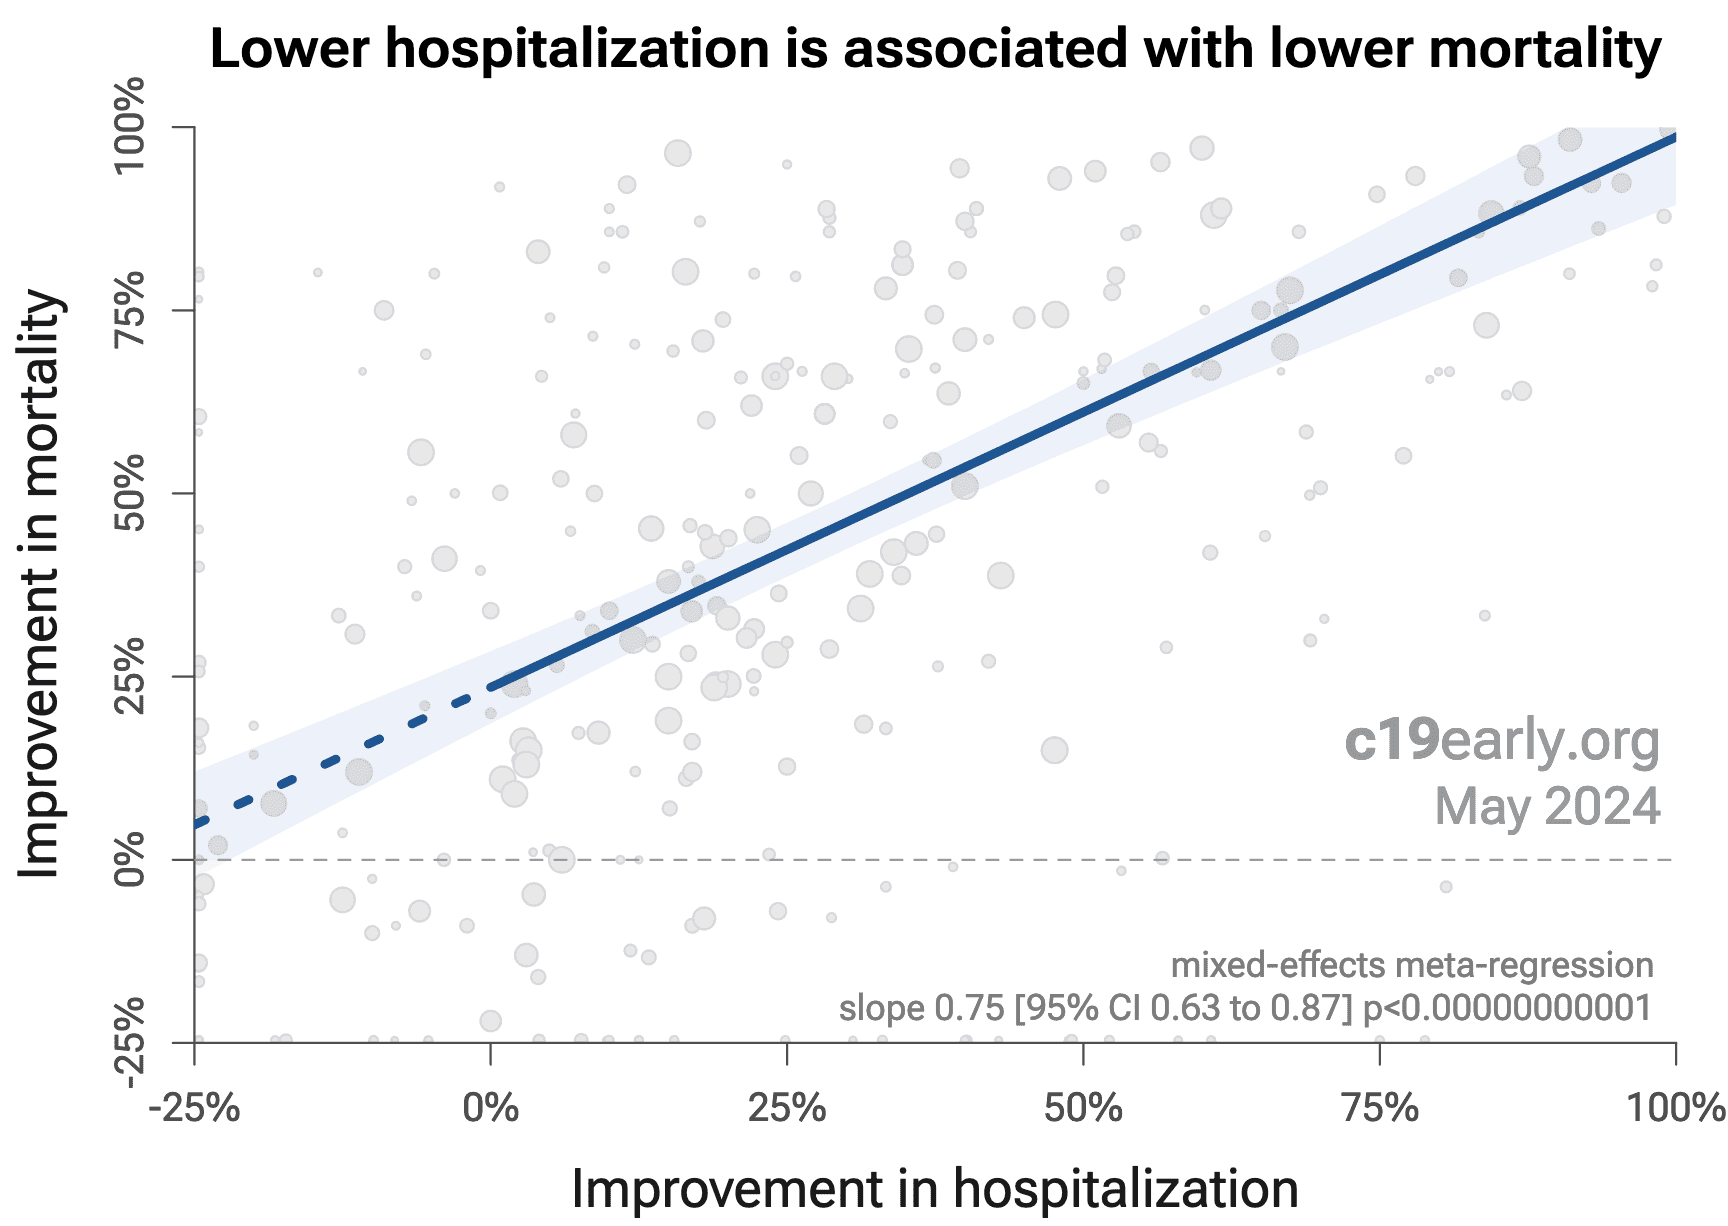
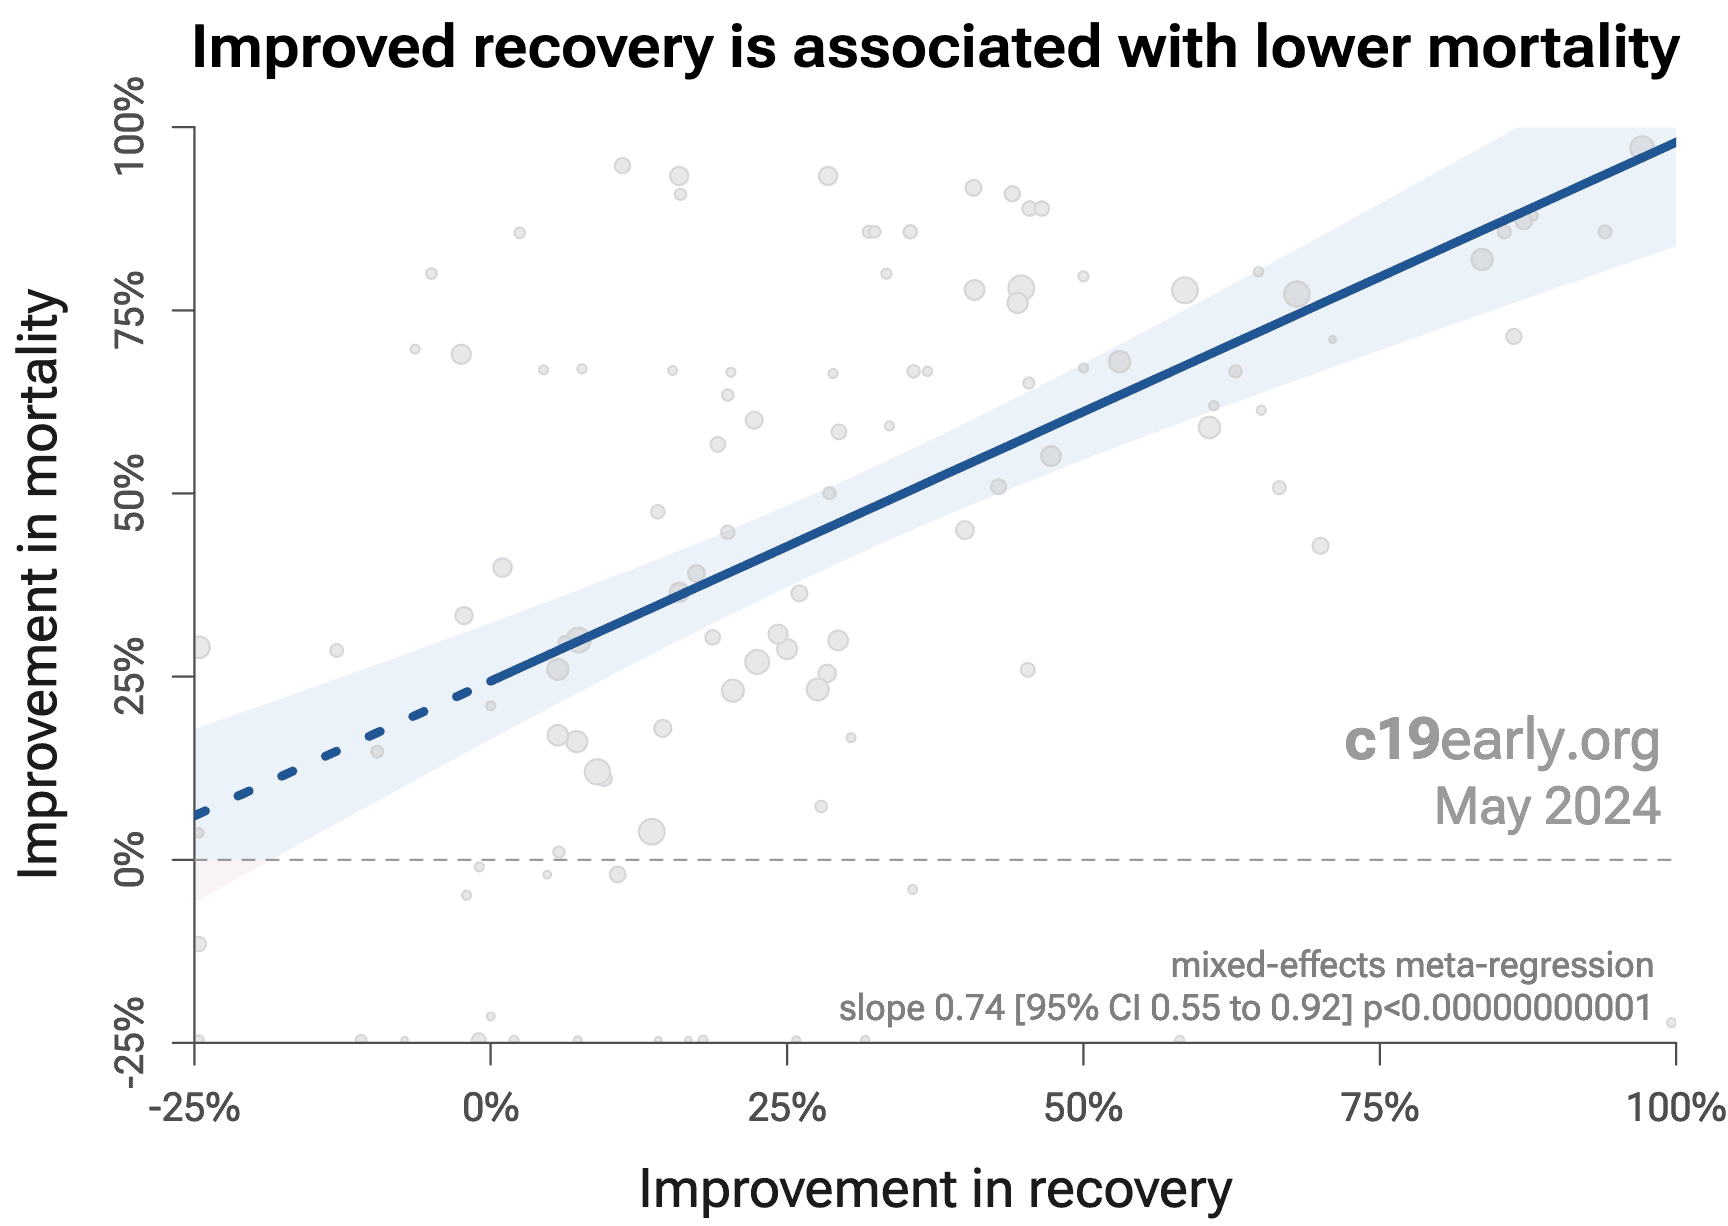
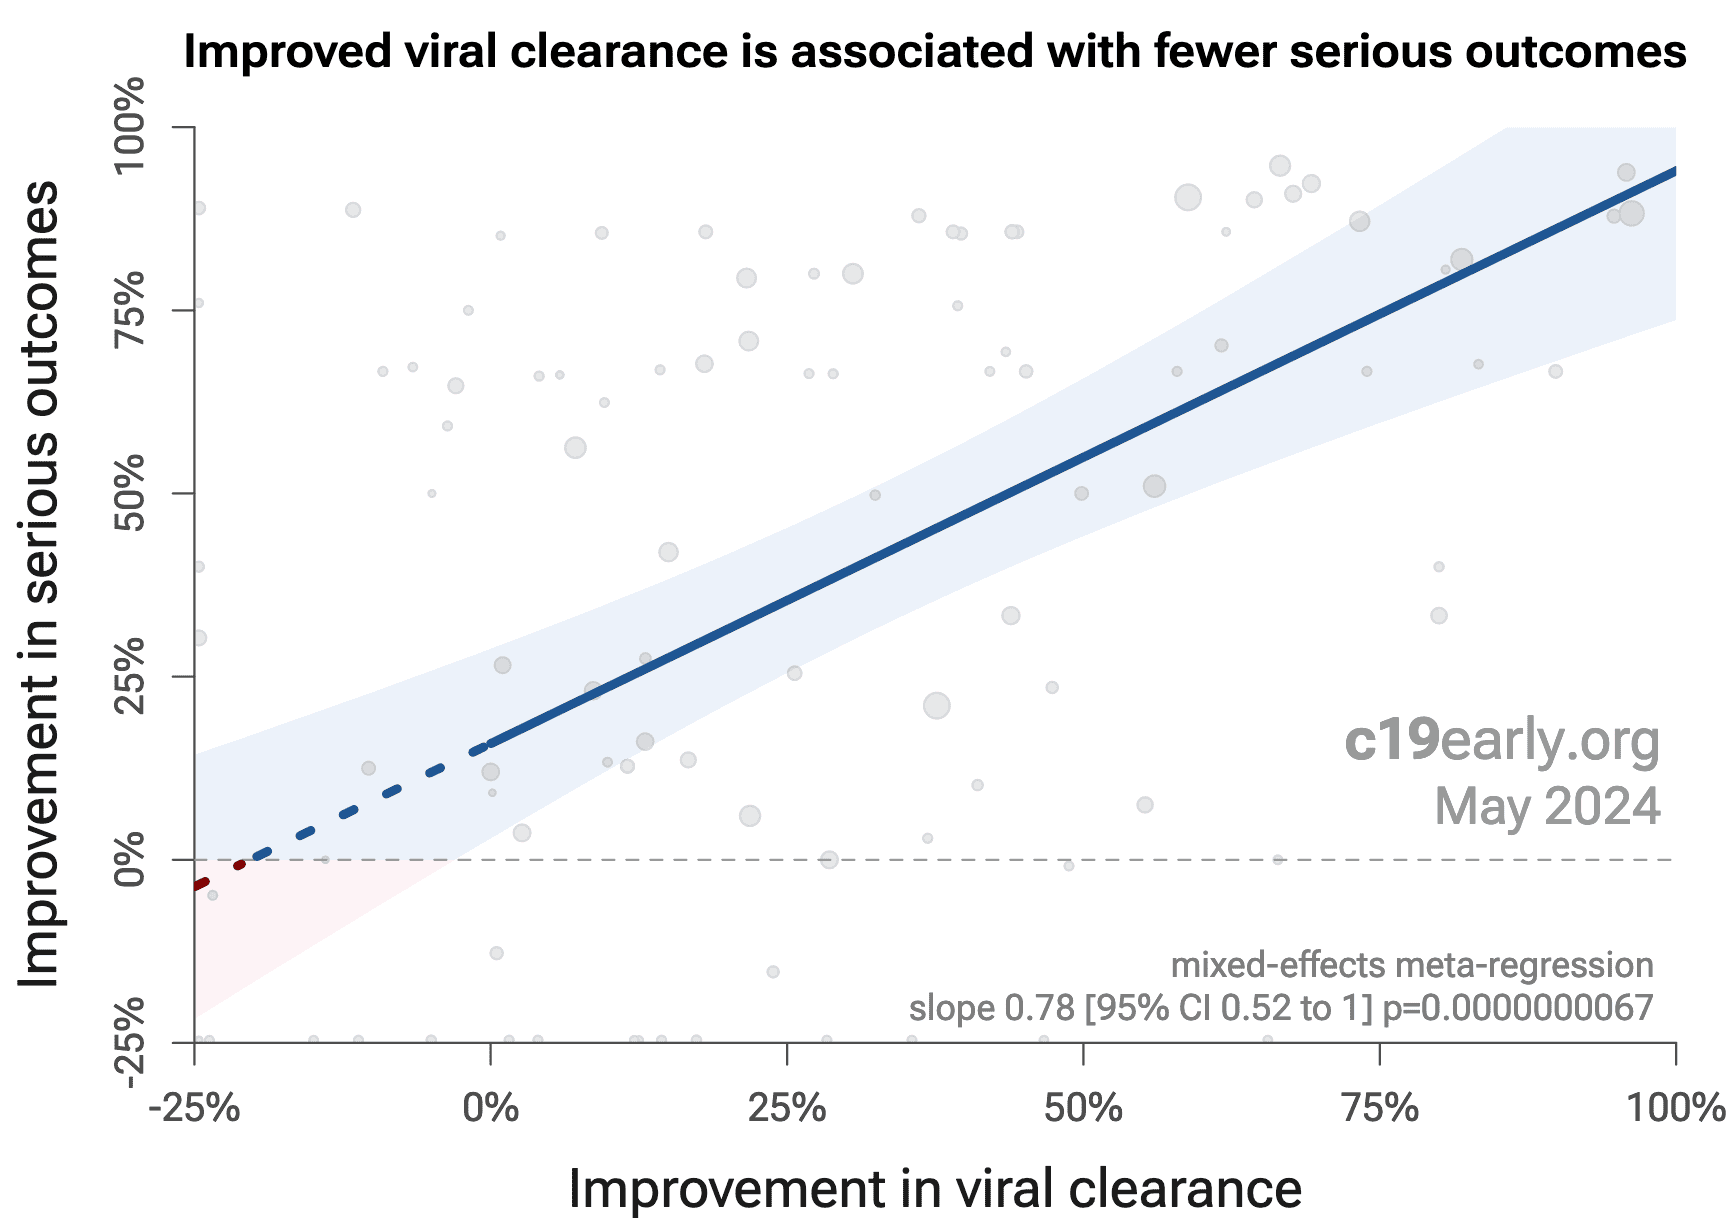
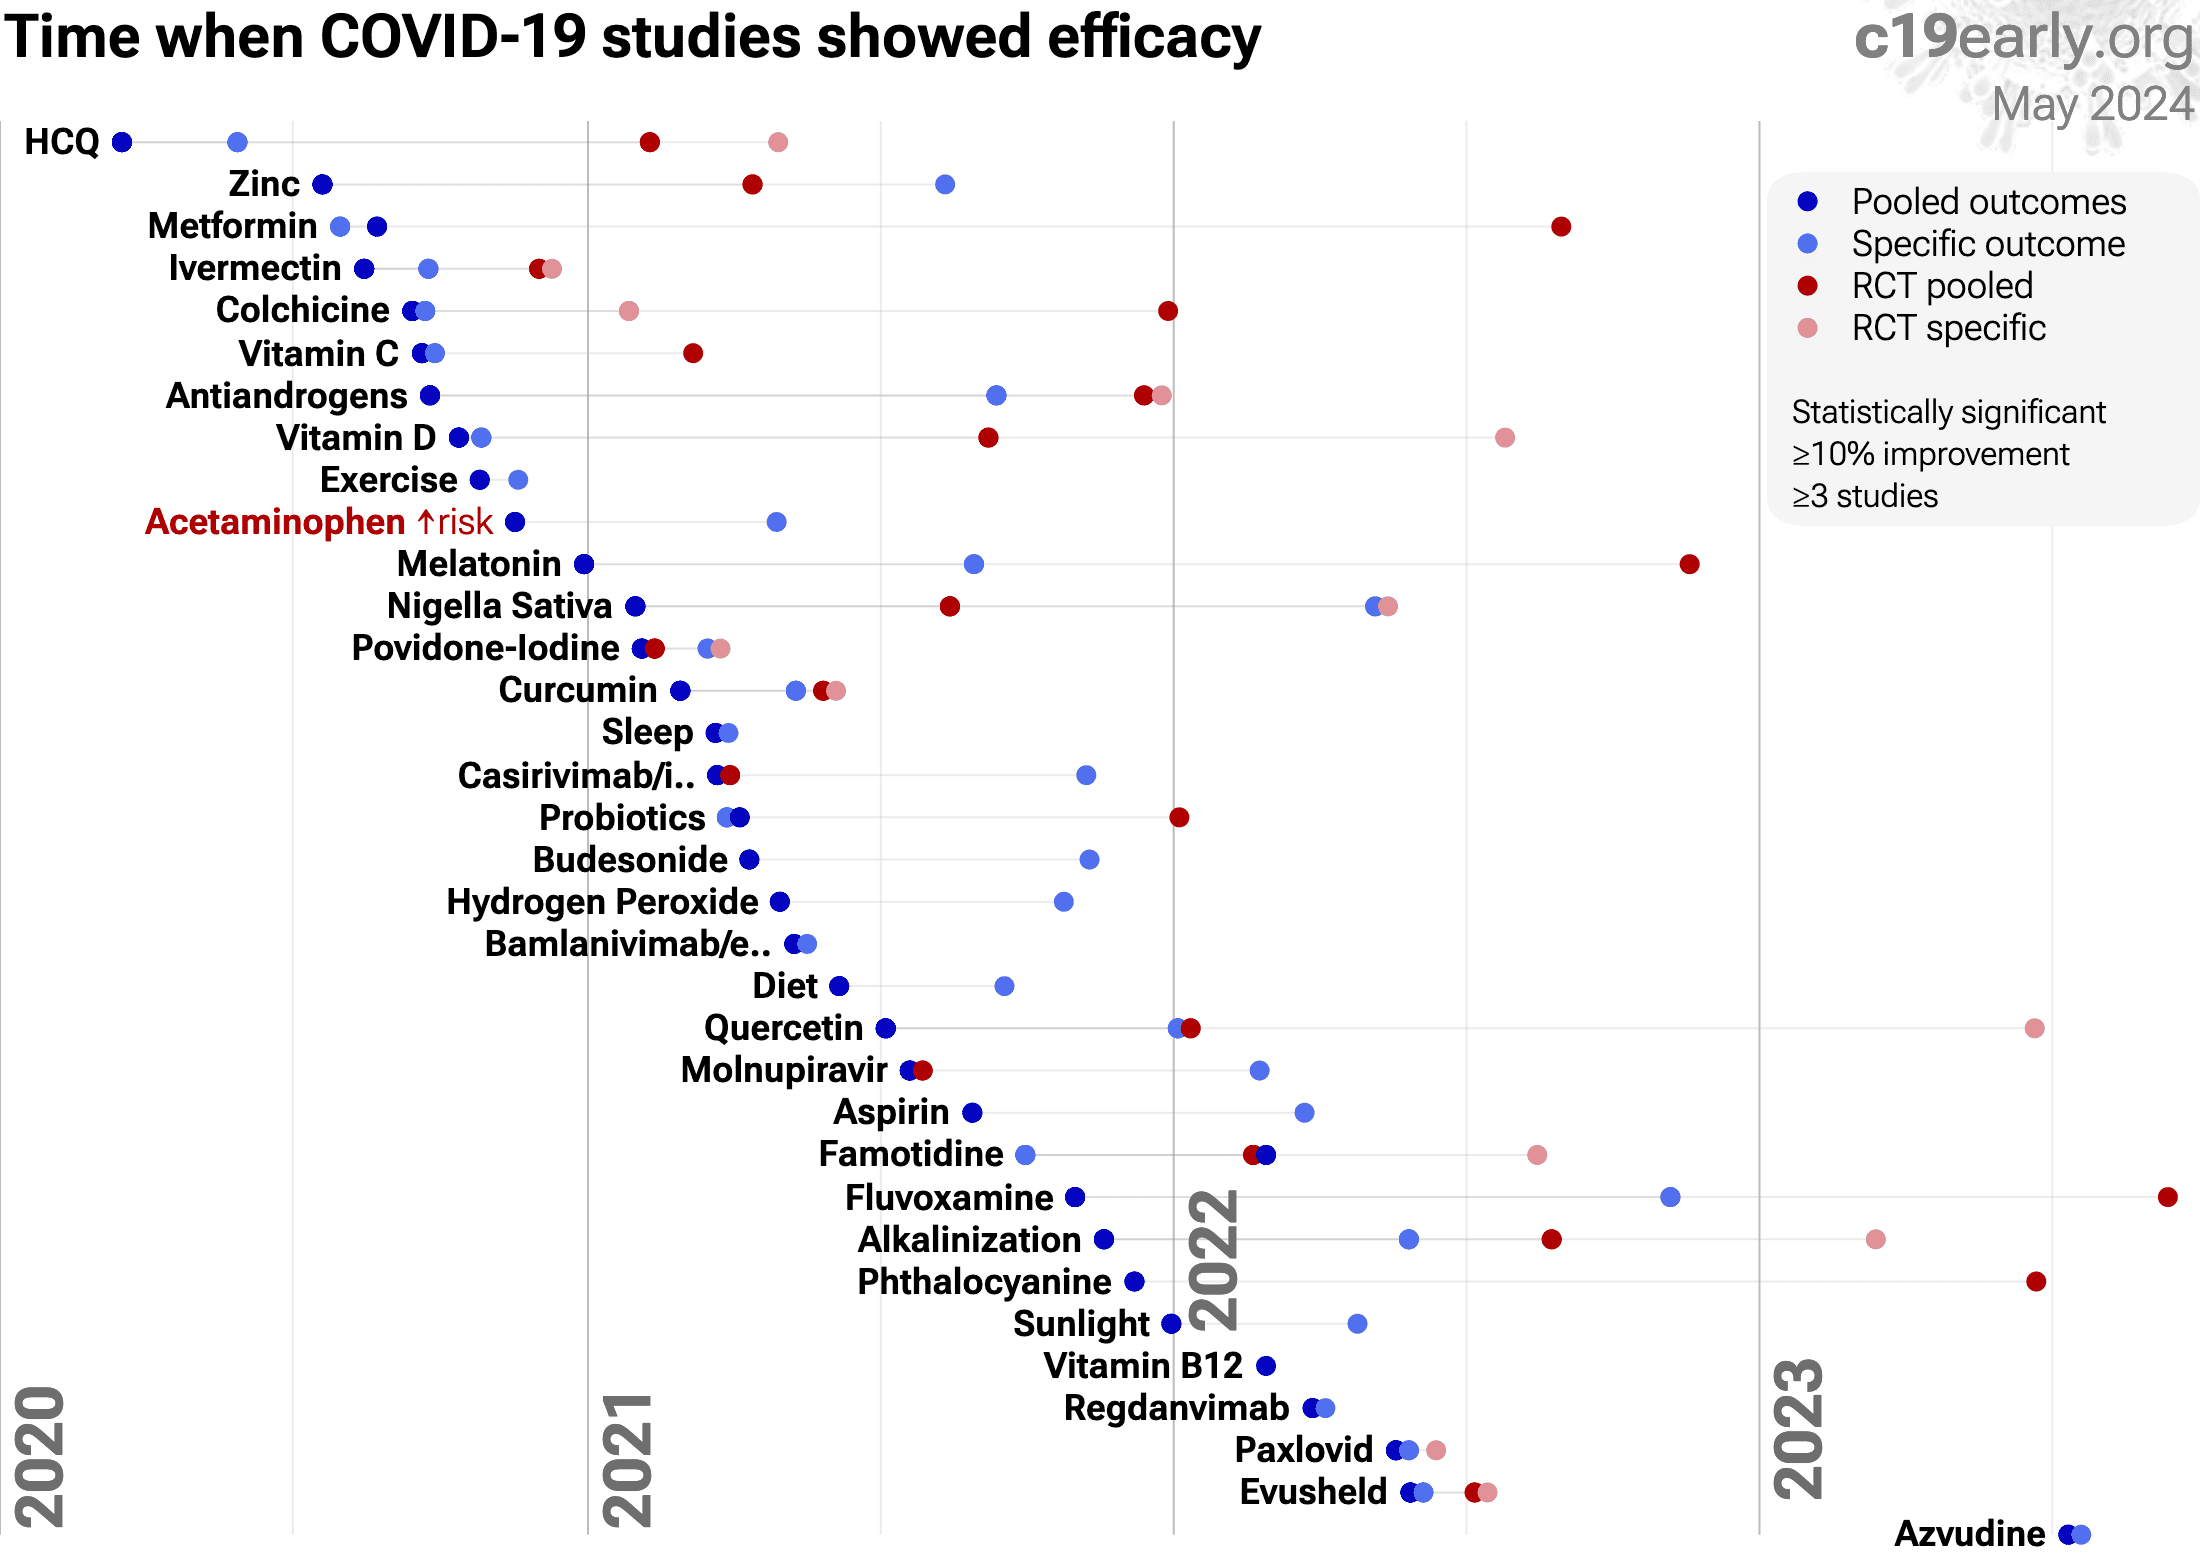
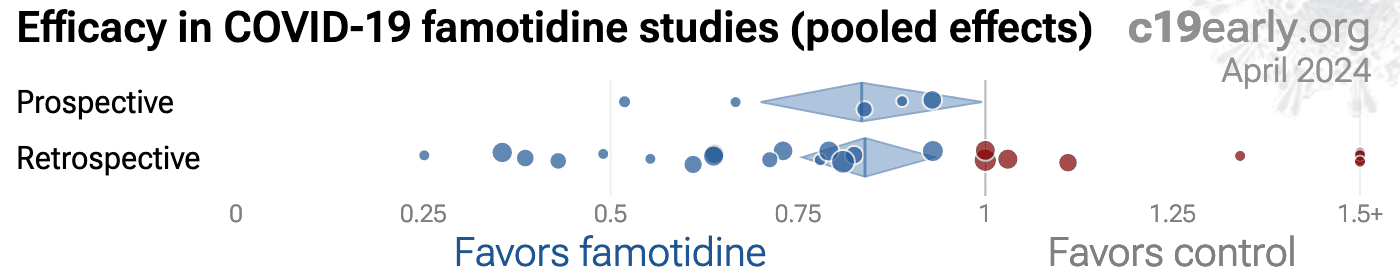
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/fmmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
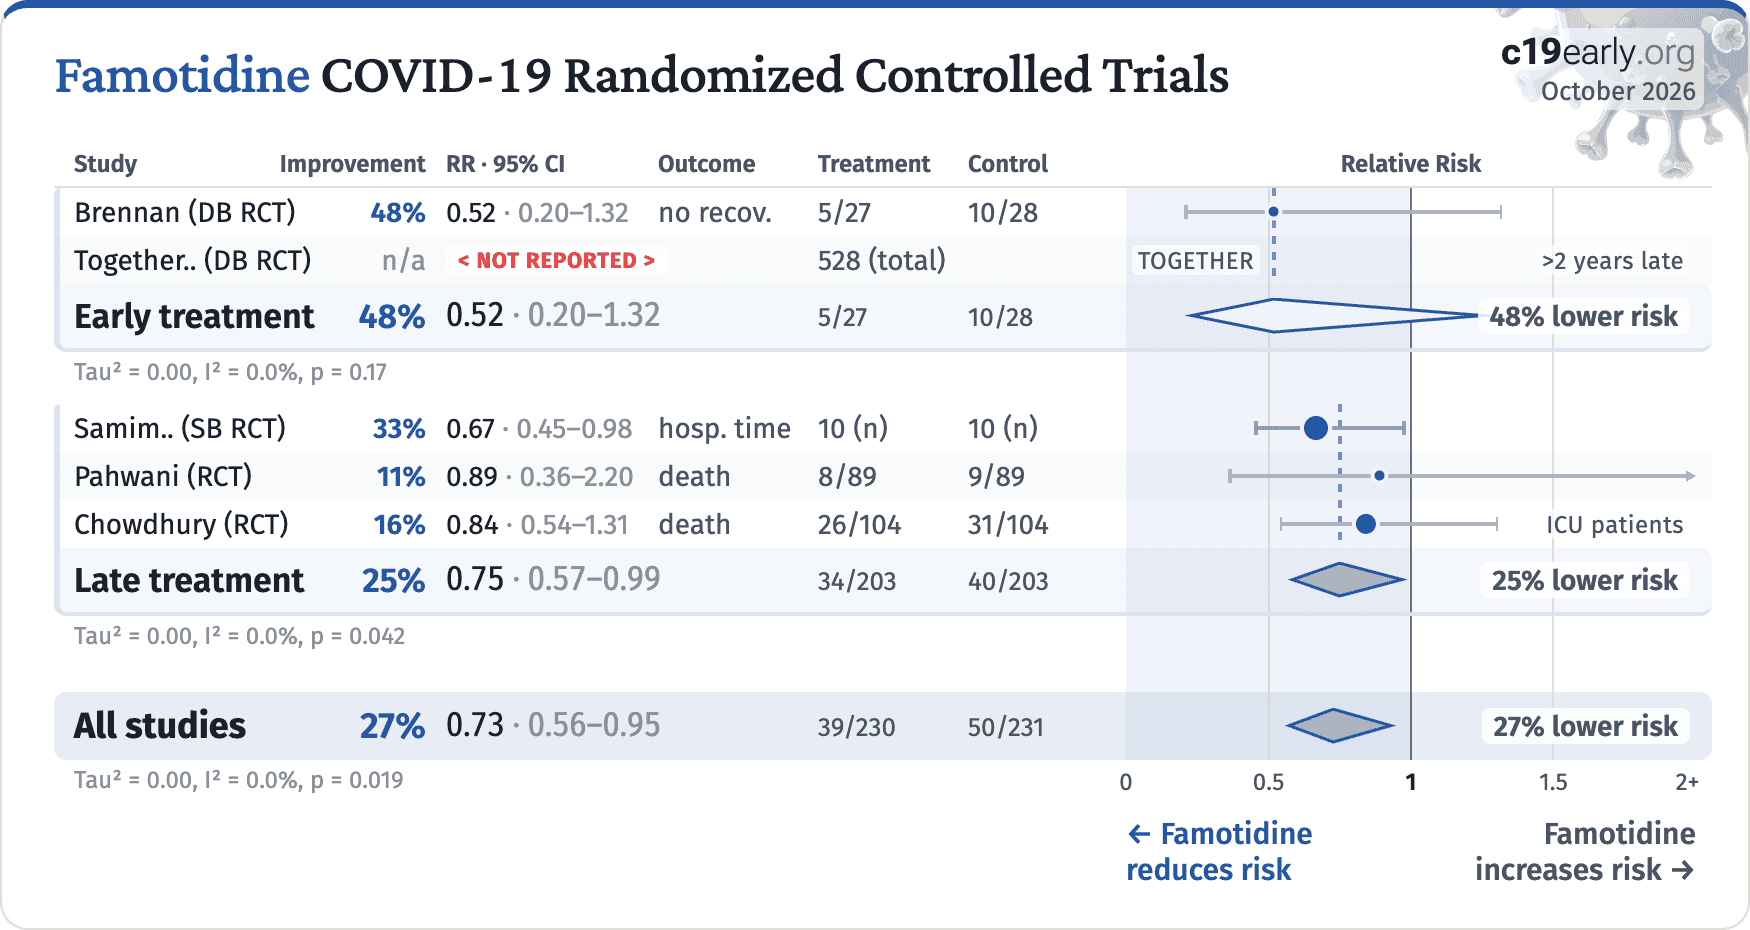
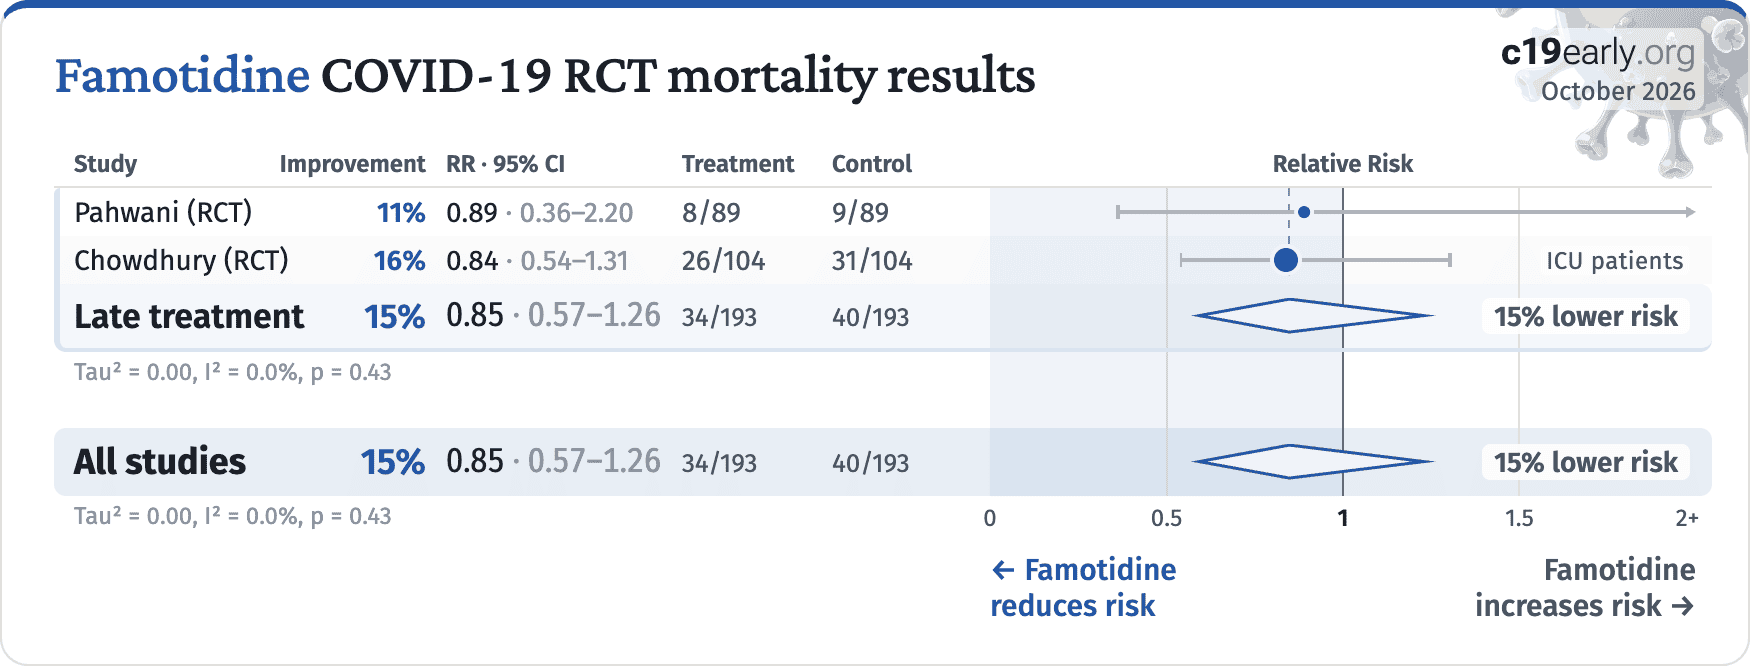
Chowdhury, 8/16/2022, Randomized Controlled Trial, Bangladesh, peer-reviewed, mean age 57.1, 11 authors, study period 1 August, 2020 - 15 April, 2021, trial NCT04504240 (history).
|
risk of death, 16.1% lower, RR 0.84, p = 0.53, treatment 26 of 104 (25.0%), control 31 of 104 (29.8%), NNT 21.
|
|
ICU time, 9.3% lower, relative time 0.91, p = 0.33, treatment 78, control 73.
|
|
time to improvement, 32.9% lower, relative time 0.67, p < 0.001, treatment mean 9.53 (±5.0) n=78, control mean 14.21 (±5.6) n=73, time to clinical improvement.
|
|
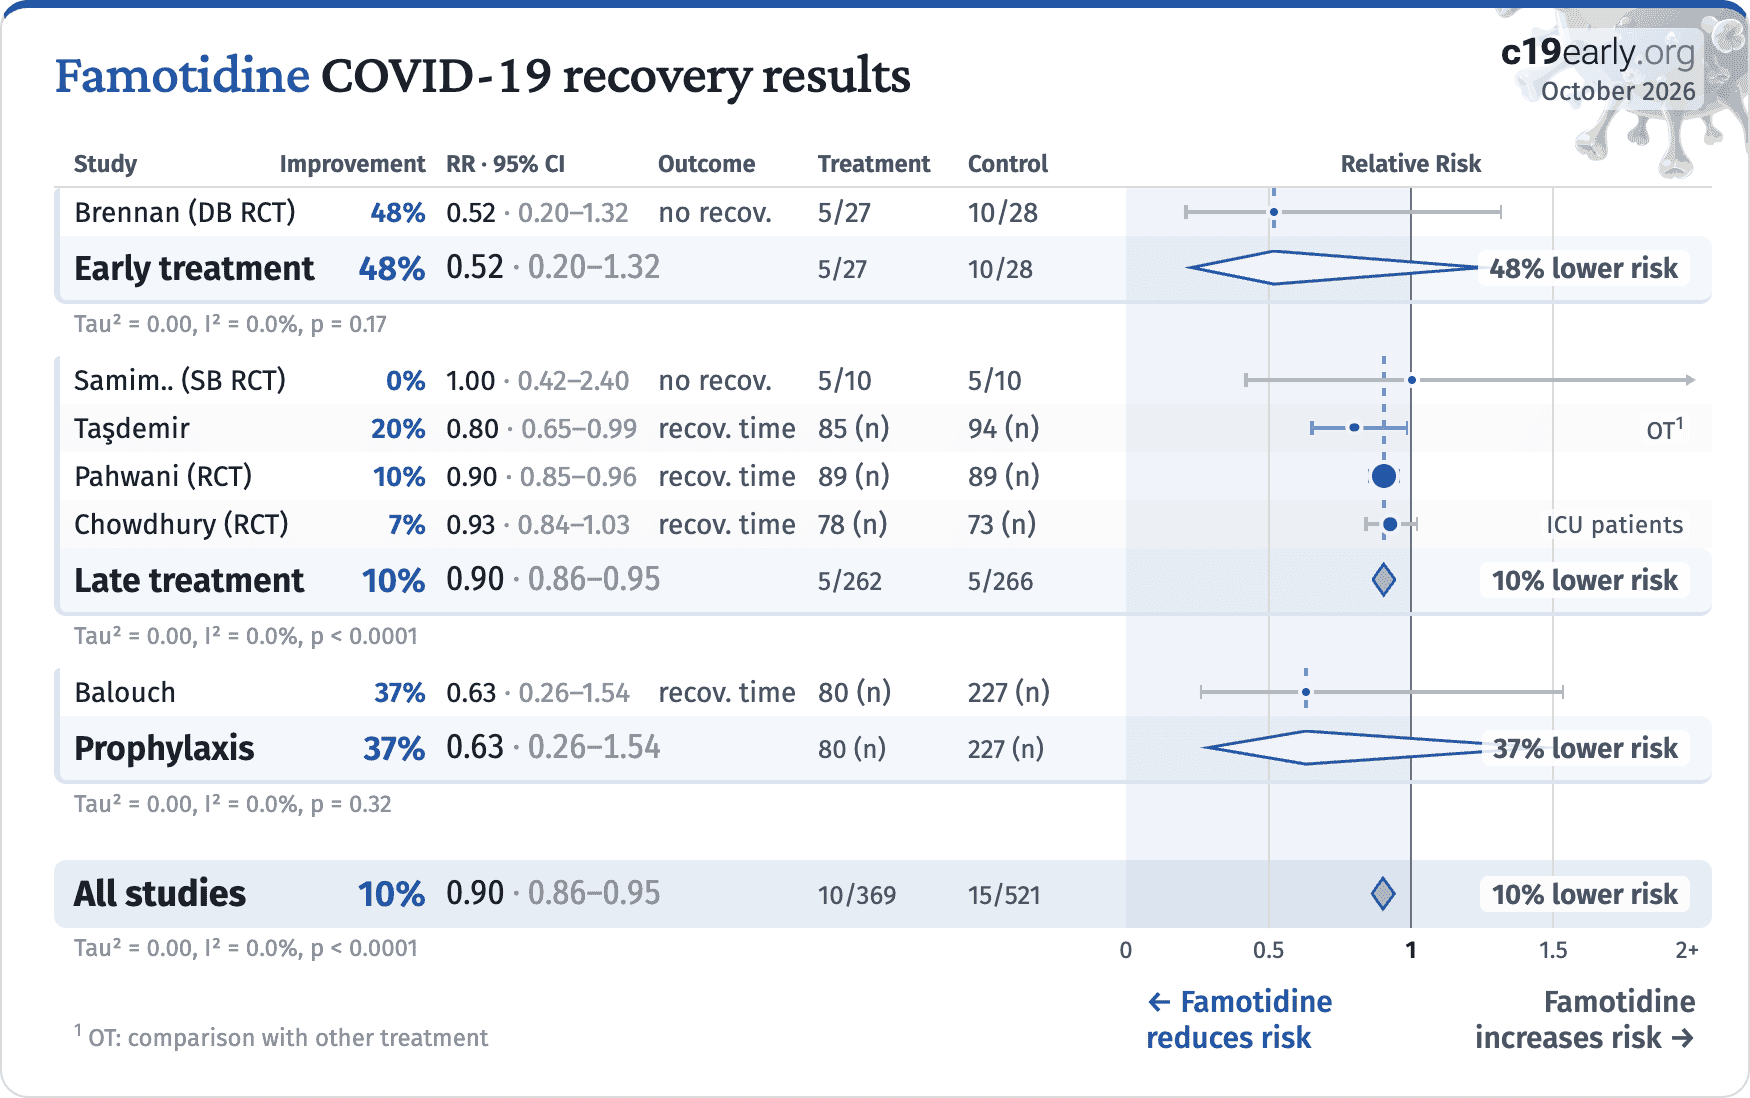
recovery time, 7.3% lower, relative time 0.93, p = 0.14, treatment mean 17.9 (±5.4) n=78, control mean 19.3 (±6.3) n=73, time to symptomatic recovery.
|
|
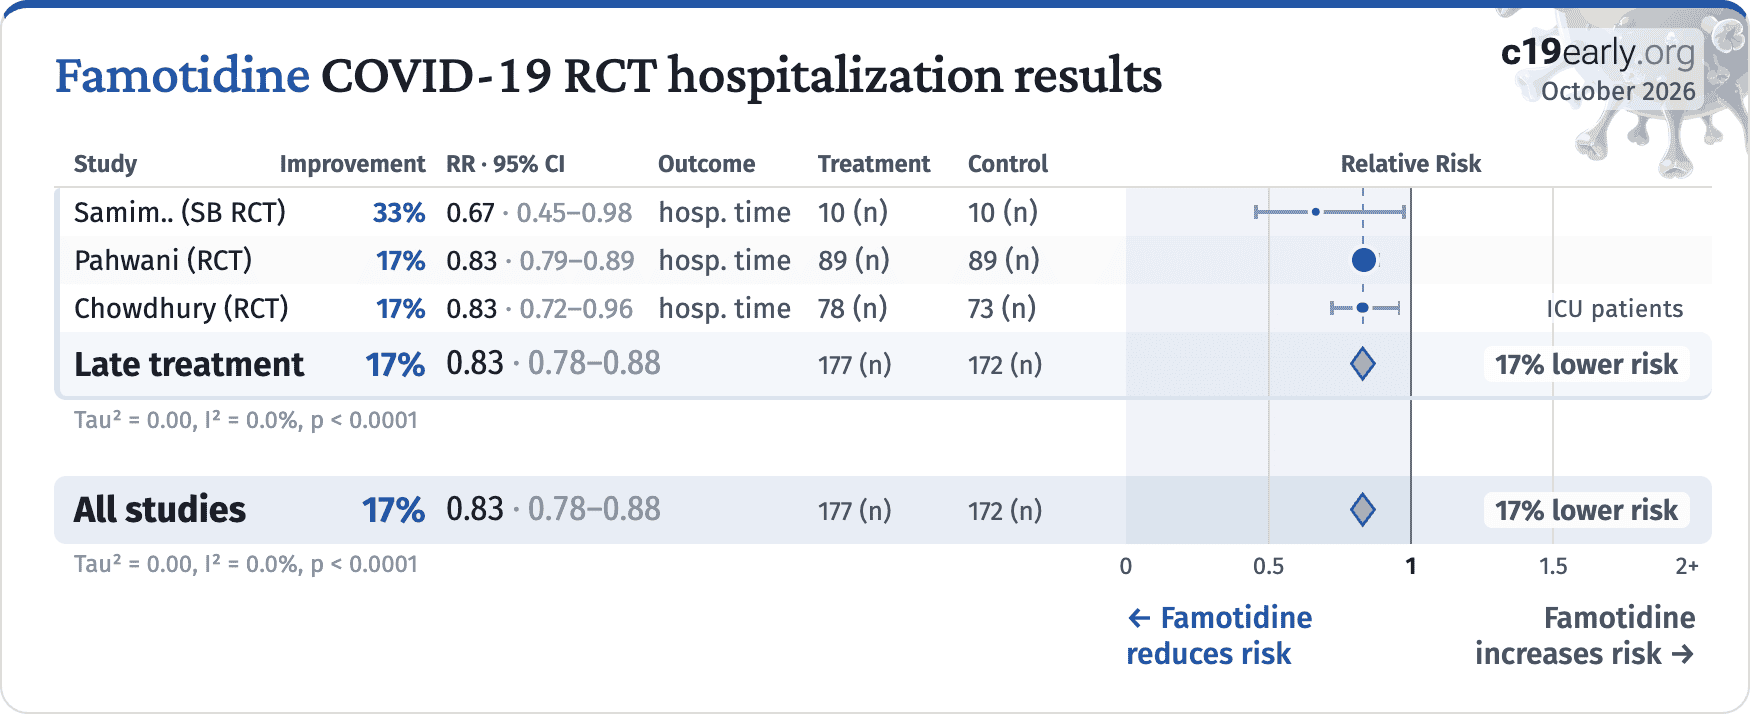
hospitalization time, 17.0% lower, relative time 0.83, p = 0.01, treatment 78, control 73.
|
|
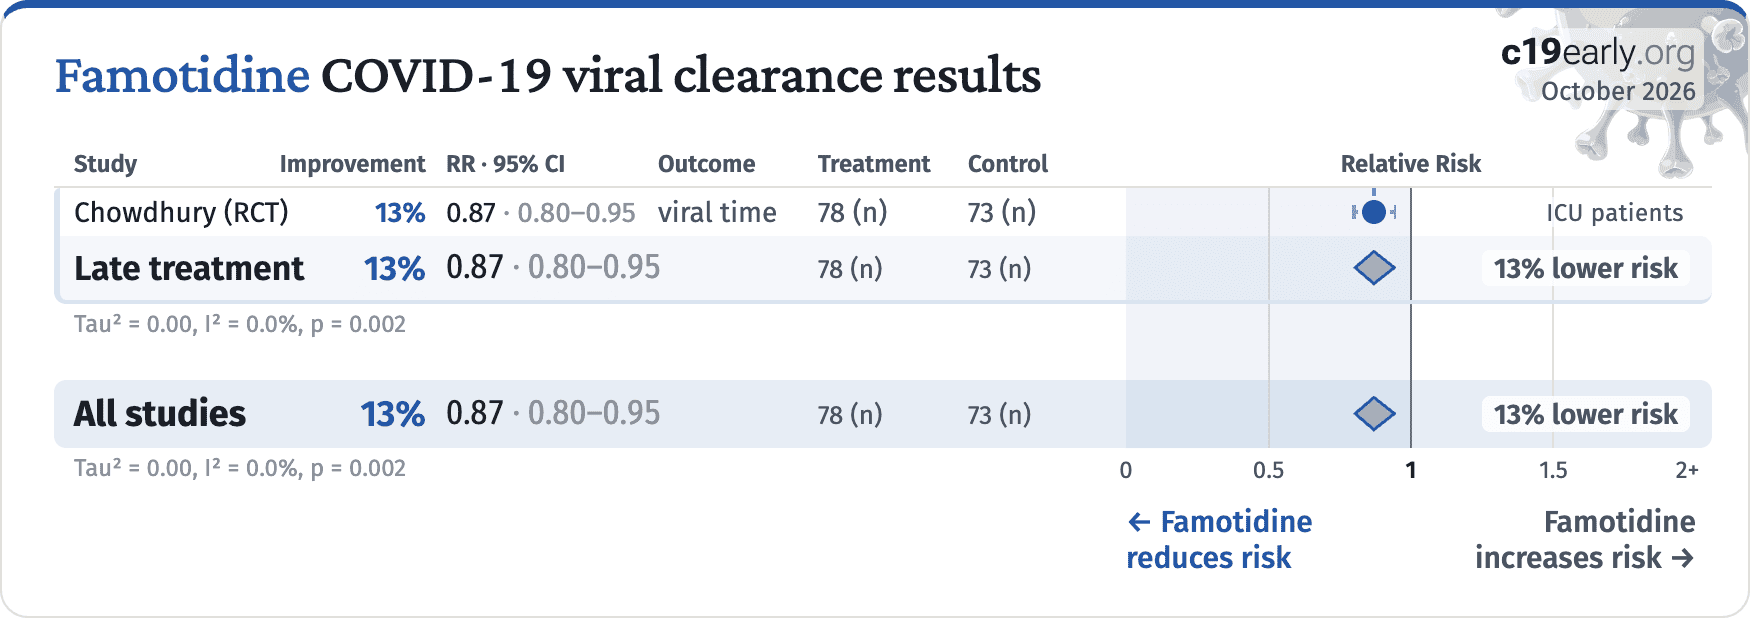
time to viral-, 13.0% lower, relative time 0.87, p = 0.002, treatment 78, control 73.
|
|
Elhadi, 4/30/2021, prospective, Libya, peer-reviewed, 21 authors, study period 29 May, 2020 - 30 December, 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 7.1% lower, RR 0.93, p = 0.57, treatment 34 of 60 (56.7%), control 247 of 405 (61.0%), NNT 23.
|
|
Kuno, 10/11/2021, retrospective, propensity score matching, USA, peer-reviewed, 4 authors, study period 1 March, 2020 - 30 March, 2021.
|
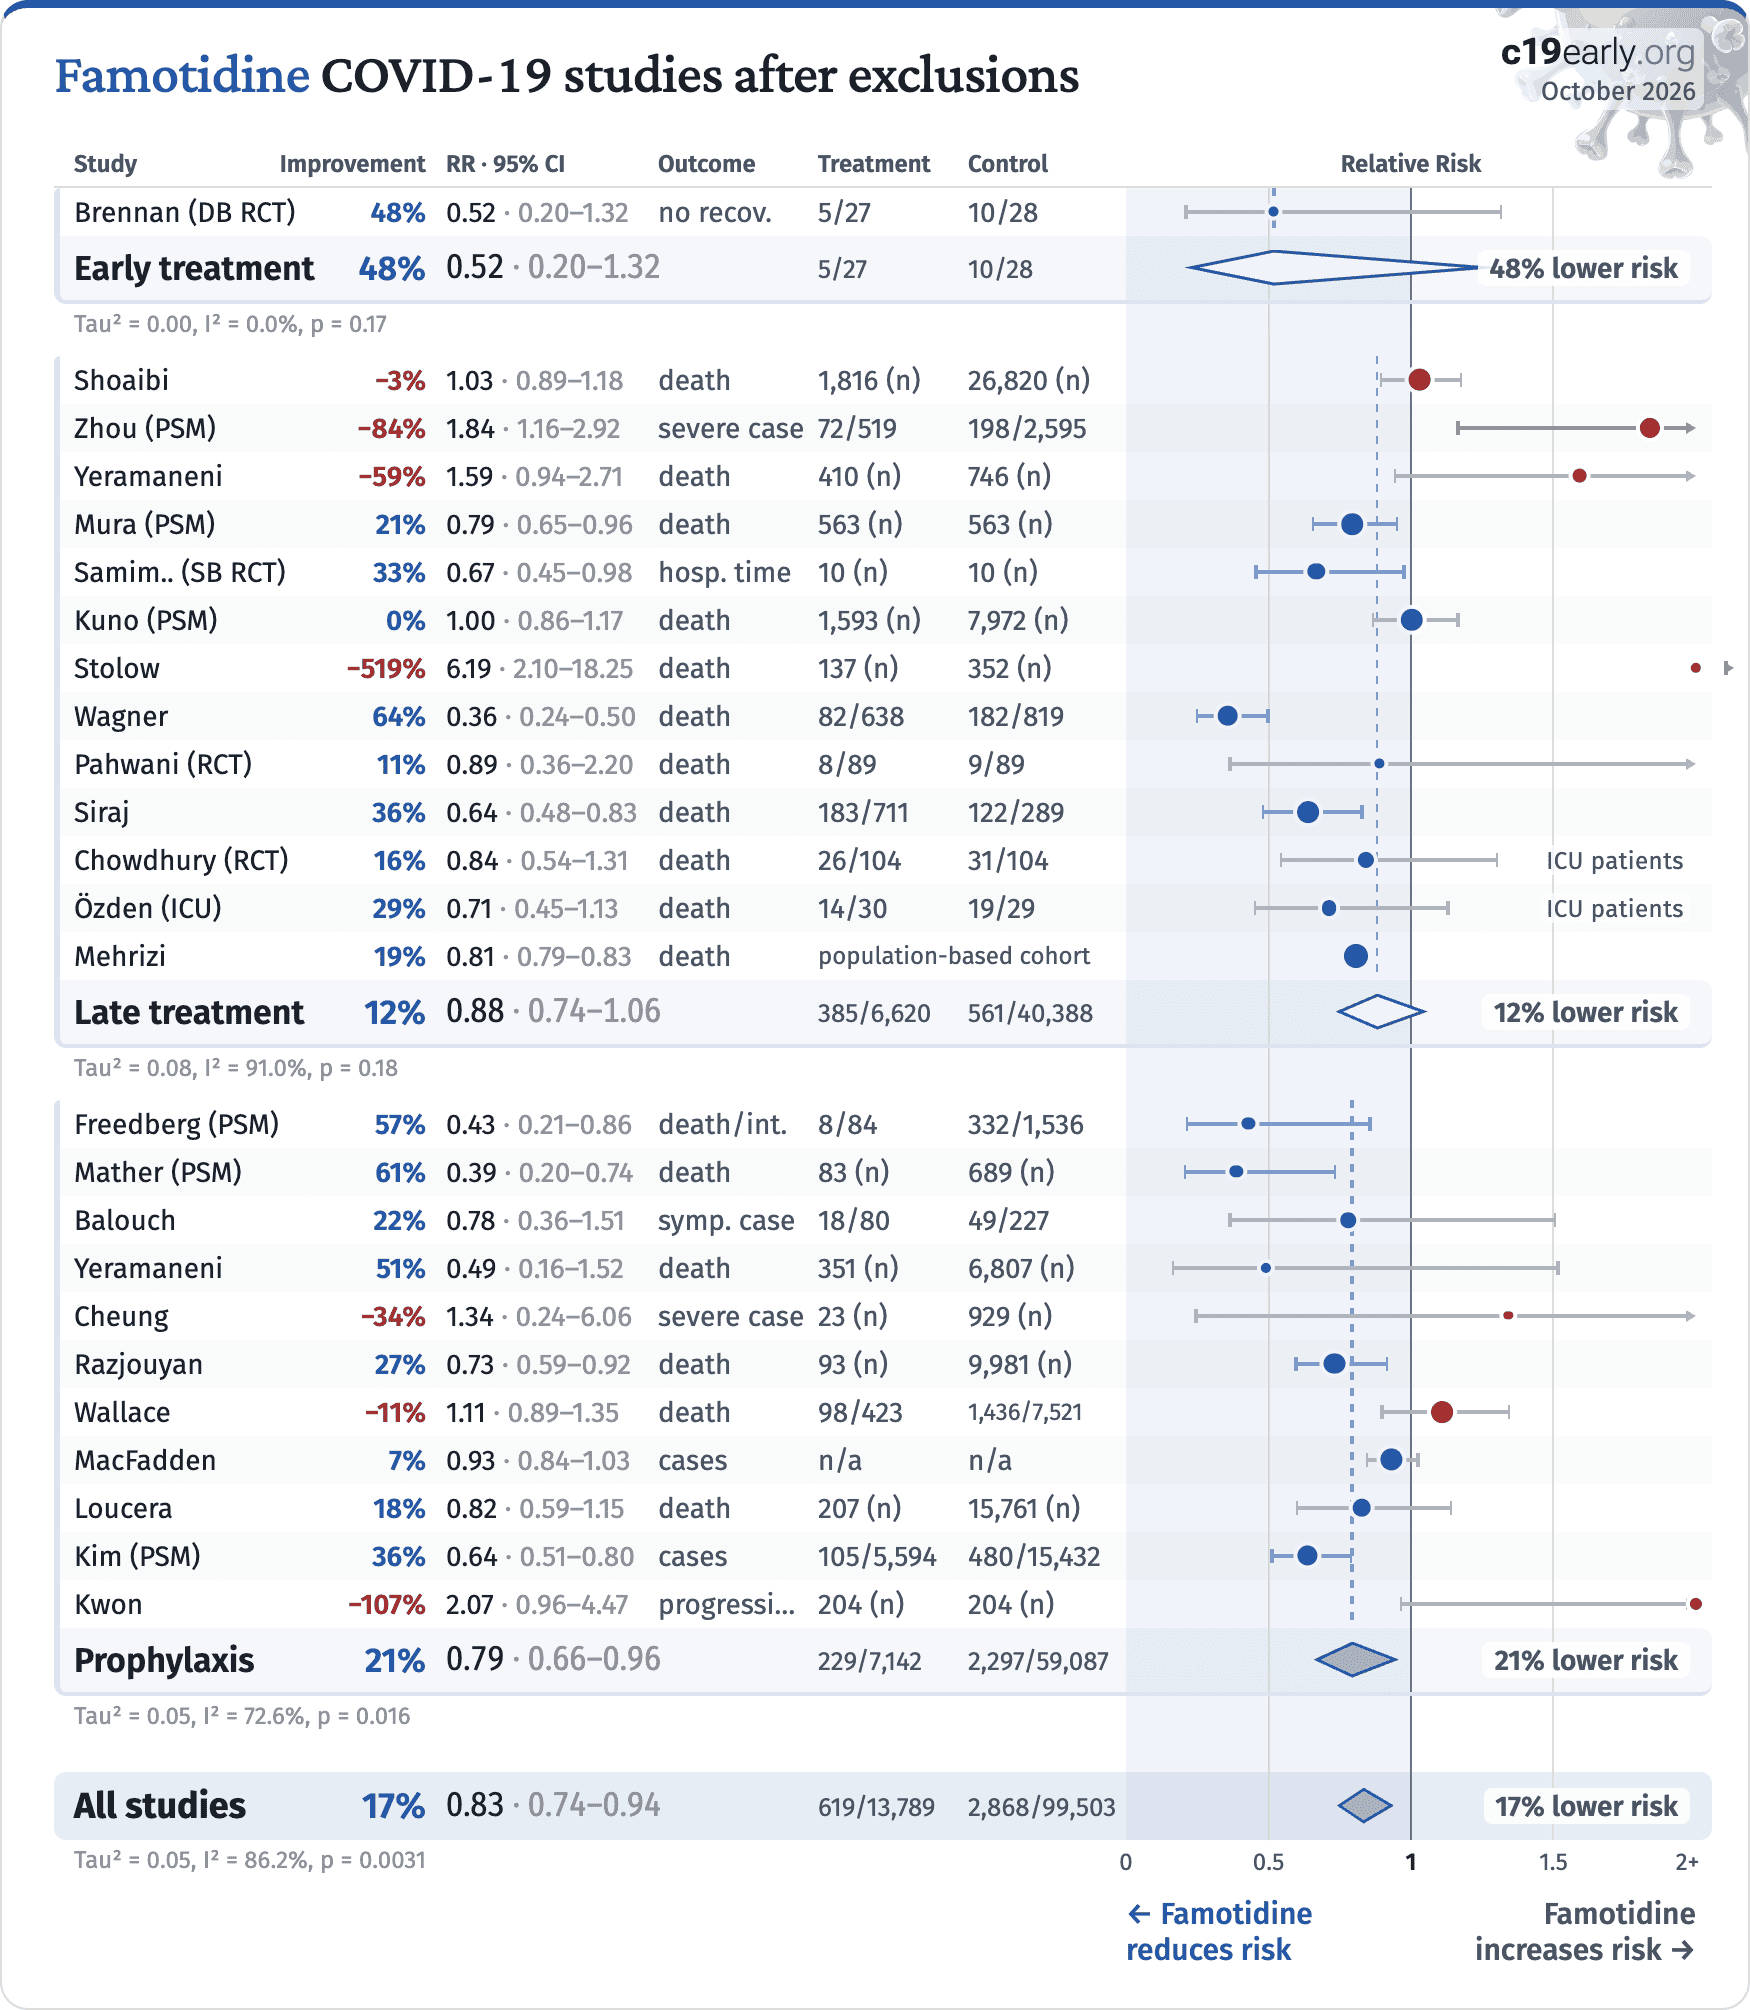
risk of death, no change, OR 1.00, p = 0.97, treatment 1,593, control 7,972, RR approximated with OR.
|
|
Mehrizi, 12/18/2023, retrospective, Iran, peer-reviewed, 10 authors, study period 1 February, 2020 - 20 March, 2022.
|
risk of death, 19.0% lower, OR 0.81, p < 0.001, RR approximated with OR.
|
|
Mura, 3/31/2021, retrospective, database analysis, multiple countries, peer-reviewed, 6 authors.
|
risk of death, 20.9% lower, RR 0.79, p = 0.02, treatment 563, control 563, odds ratio converted to relative risk, famotidine only, control prevalence approximated with treatment prevalence, propensity score matching.
|
|
risk of death, 37.3% lower, RR 0.63, p = 0.001, treatment 305, control 305, odds ratio converted to relative risk, famotidine and aspirin, control prevalence approximated with treatment prevalence, propensity score matching.
|
|
Pahwani, 2/20/2022, Randomized Controlled Trial, Pakistan, peer-reviewed, mean age 52.0, 8 authors, study period December 2020 - September 2021.
|
risk of death, 11.1% lower, RR 0.89, p = 1.00, treatment 8 of 89 (9.0%), control 9 of 89 (10.1%), NNT 89.
|
|
risk of mechanical ventilation, 12.5% lower, RR 0.88, p = 0.73, treatment 21 of 89 (23.6%), control 24 of 89 (27.0%), NNT 30.
|
|
risk of ICU admission, 10.0% lower, RR 0.90, p = 0.86, treatment 18 of 89 (20.2%), control 20 of 89 (22.5%), NNT 44.
|
|
hospitalization time, 16.5% lower, relative time 0.83, p < 0.001, treatment mean 8.6 (±1.6) n=89, control mean 10.3 (±2.2) n=89.
|
|
recovery time, 9.6% lower, relative time 0.90, p = 0.001, treatment mean 8.5 (±1.7) n=89, control mean 9.4 (±1.9) n=89.
|
|
Samimagham, 4/27/2021, Single Blind Randomized Controlled Trial, placebo-controlled, Iran, preprint, 6 authors.
|
hospitalization time, 33.3% lower, relative time 0.67, p = 0.04, treatment 10, control 10.
|
|
risk of no recovery, no change, RR 1.00, p = 1.00, treatment 5 of 10 (50.0%), control 5 of 10 (50.0%), >50% CT lung involvment.
|
|
risk of no recovery, 50.0% lower, RR 0.50, p = 0.37, treatment 3 of 10 (30.0%), control 6 of 10 (60.0%), NNT 3.3, no improvement in cough.
|
|
Shamsi, 7/17/2023, retrospective, Iran, peer-reviewed, 4 authors, study period 1 March, 2020 - 1 August, 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 74.9% lower, RR 0.25, p = 0.21, treatment 1 of 27 (3.7%), control 23 of 156 (14.7%), NNT 9.1.
|
|
Shoaibi, 9/24/2020, retrospective, database analysis, USA, peer-reviewed, 5 authors.
|
risk of death, 3.0% higher, RR 1.03, p = 0.67, treatment 1,816, control 26,820.
|
|
risk of death/ICU, 3.0% higher, RR 1.03, p = 0.62, treatment 1,816, control 26,820.
|
|
Siraj, 2/28/2022, retrospective, India, peer-reviewed, median age 56.0, 13 authors, study period March 2020 - December 2020.
|
risk of death, 36.2% lower, RR 0.64, p = 0.002, treatment 183 of 711 (25.7%), control 122 of 289 (42.2%), NNT 6.1, adjusted per study, inverted to make RR<1 favor treatment, odds ratio converted to relative risk, multivariable.
|
|
Stolow, 10/31/2021, retrospective, USA, peer-reviewed, 9 authors.
|
risk of death, 518.9% higher, OR 6.19, p < 0.001, treatment 137, control 352, RR approximated with OR.
|
|
risk of ICU admission, 2389.6% higher, OR 24.90, p < 0.001, treatment 137, control 352, RR approximated with OR.
|
|
Taşdemir, 7/12/2021, retrospective, Turkey, peer-reviewed, 7 authors, this trial compares with another treatment - results may be better when compared to placebo, excluded in exclusion analyses:
excessive unadjusted differences between groups.
|
risk of death, 44.7% lower, RR 0.55, p = 0.29, treatment 5 of 85 (5.9%), control 10 of 94 (10.6%), NNT 21.
|
|
risk of ICU admission, 36.8% lower, RR 0.63, p = 0.36, treatment 8 of 85 (9.4%), control 14 of 94 (14.9%), NNT 18.
|
|
hospitalization time, 18.1% lower, relative time 0.82, p = 0.003, treatment 85, control 94.
|
|
recovery time, 20.0% lower, relative time 0.80, p = 0.04, treatment 85, control 94, duration of fever.
|
|
Wagner, 10/31/2021, retrospective, USA, peer-reviewed, 5 authors, study period 1 March, 2020 - 1 March, 2021.
|
risk of death, 64.5% lower, RR 0.36, p < 0.001, treatment 82 of 638 (12.9%), control 182 of 819 (22.2%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
risk of mechanical ventilation, 6.4% lower, RR 0.94, p = 0.77, treatment 48 of 638 (7.5%), control 75 of 819 (9.2%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Yeramaneni, 2/28/2021, retrospective, USA, peer-reviewed, 6 authors, study period 11 February, 2020 - 8 May, 2020.
|
risk of death, 59.0% higher, OR 1.59, p = 0.09, treatment 410, control 746, adjusted per study, hospital use only, multivariable, RR approximated with OR, late treatment result.
|
|
Zhou, 12/4/2020, retrospective, propensity score matching, China, peer-reviewed, 7 authors, study period 1 January, 2020 - 22 August, 2020.
|
risk of severe case, 84.0% higher, HR 1.84, p < 0.001, treatment 72 of 519 (13.9%), control 198 of 2,595 (7.6%), adjusted per study, death/intubation/ICU, propensity score matching, multivariable, Cox proportional hazards.
|
|
Özden, 2/28/2023, retrospective, Turkey, peer-reviewed, mean age 65.3, 2 authors, study period September 2020 - February 2021, trial NCT05122208 (history).
|
risk of death, 28.8% lower, RR 0.71, p = 0.19, treatment 14 of 30 (46.7%), control 19 of 29 (65.5%), NNT 5.3.
|
|
risk of mechanical ventilation, 1.1% higher, RR 1.01, p = 1.00, treatment 23 of 30 (76.7%), control 22 of 29 (75.9%).
|
|
ventilation time, 33.3% higher, relative time 1.33, p = 0.28, treatment 30, control 29.
|
|
ICU time, 25.5% lower, relative time 0.74, p = 0.60, treatment 30, control 29.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Balouch, 1/20/2021, retrospective, USA, peer-reviewed, 5 authors.
|
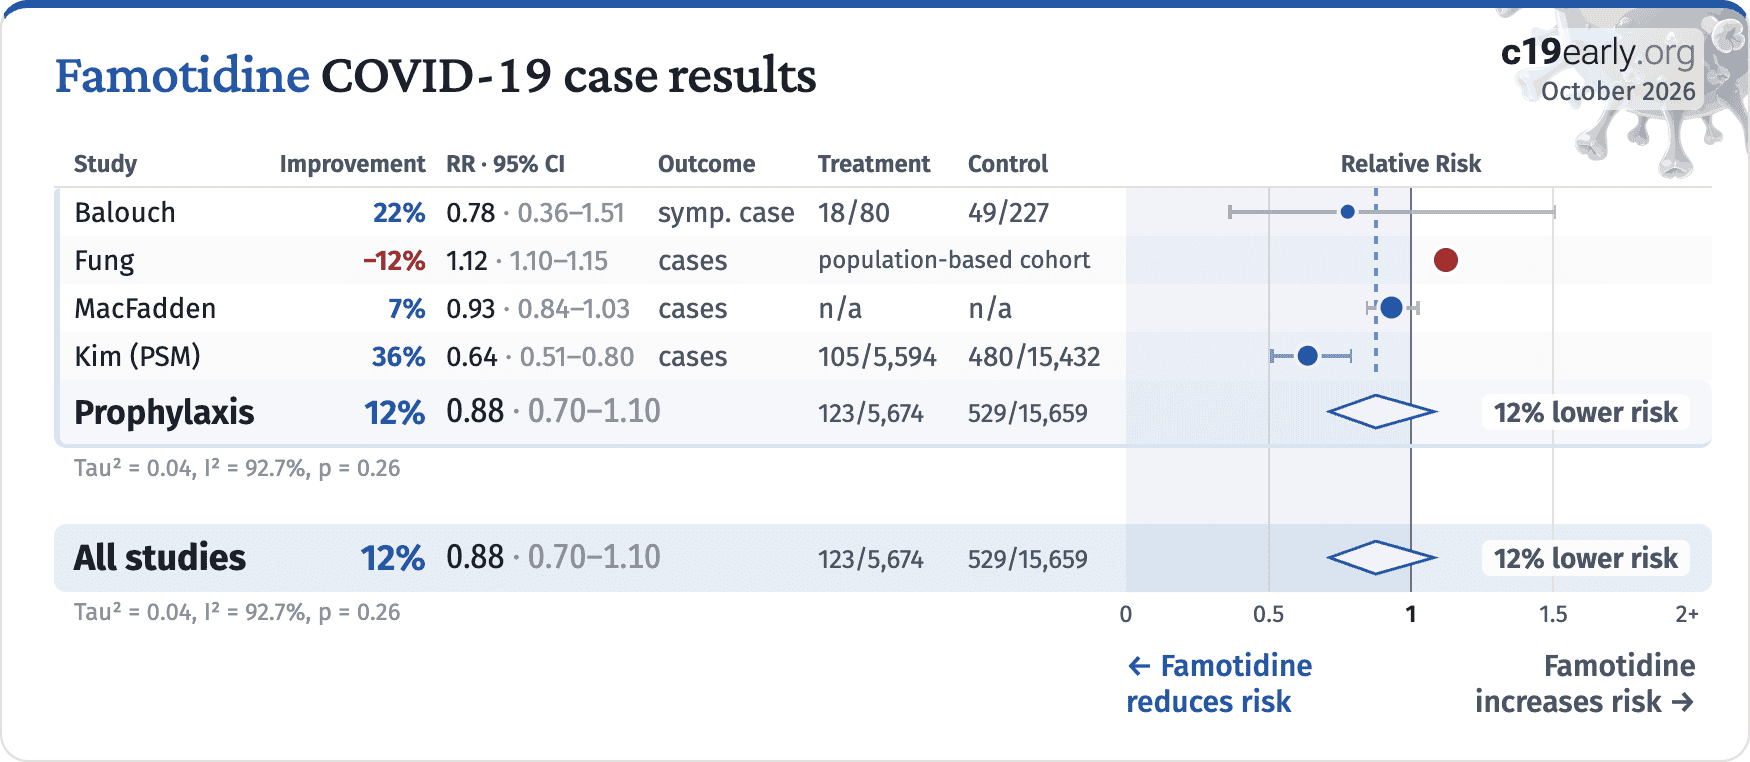
risk of symptomatic case, 22.0% lower, RR 0.78, p = 0.49, treatment 18 of 80 (22.5%), control 49 of 227 (21.6%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
recovery time, 36.9% lower, relative time 0.63, p = 0.32, treatment 80, control 227.
|
|
Cheung, 4/30/2021, retrospective, China, peer-reviewed, 3 authors.
|
risk of severe case, 34.0% higher, OR 1.34, p = 0.72, treatment 23, control 929, adjusted per study, multivariable, RR approximated with OR.
|
|
Freedberg, 5/21/2020, retrospective, propensity score matching, USA, peer-reviewed, 15 authors.
|
risk of death/intubation, 57.0% lower, HR 0.43, p = 0.02, treatment 8 of 84 (9.5%), control 332 of 1,536 (21.6%), NNT 8.3, adjusted per study, propensity score matching, multivariable, Cox proportional hazards.
|
|
Fung, 10/1/2021, retrospective, population-based cohort, USA, peer-reviewed, 6 authors, excluded in exclusion analyses:
not fully adjusting for the different baseline risk of systemic autoimmune patients.
|
risk of death, no change, HR 1.00, p = 1.00, vs. never used.
|
|
risk of hospitalization, 6.0% lower, HR 0.94, p < 0.001, vs. never used.
|
|
risk of case, 12.0% higher, HR 1.12, p < 0.001, vs. never used.
|
|
Kim, 3/21/2023, retrospective, South Korea, peer-reviewed, 8 authors, study period 1 January, 2020 - 4 June, 2020.
|
risk of case, 36.3% lower, RR 0.64, p < 0.001, treatment 105 of 5,594 (1.9%), control 480 of 15,432 (3.1%), NNT 81, adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable, model 3.
|
|
Kwon, 5/31/2023, retrospective, South Korea, peer-reviewed, 8 authors, study period 1 July, 2020 - 31 December, 2020.
|
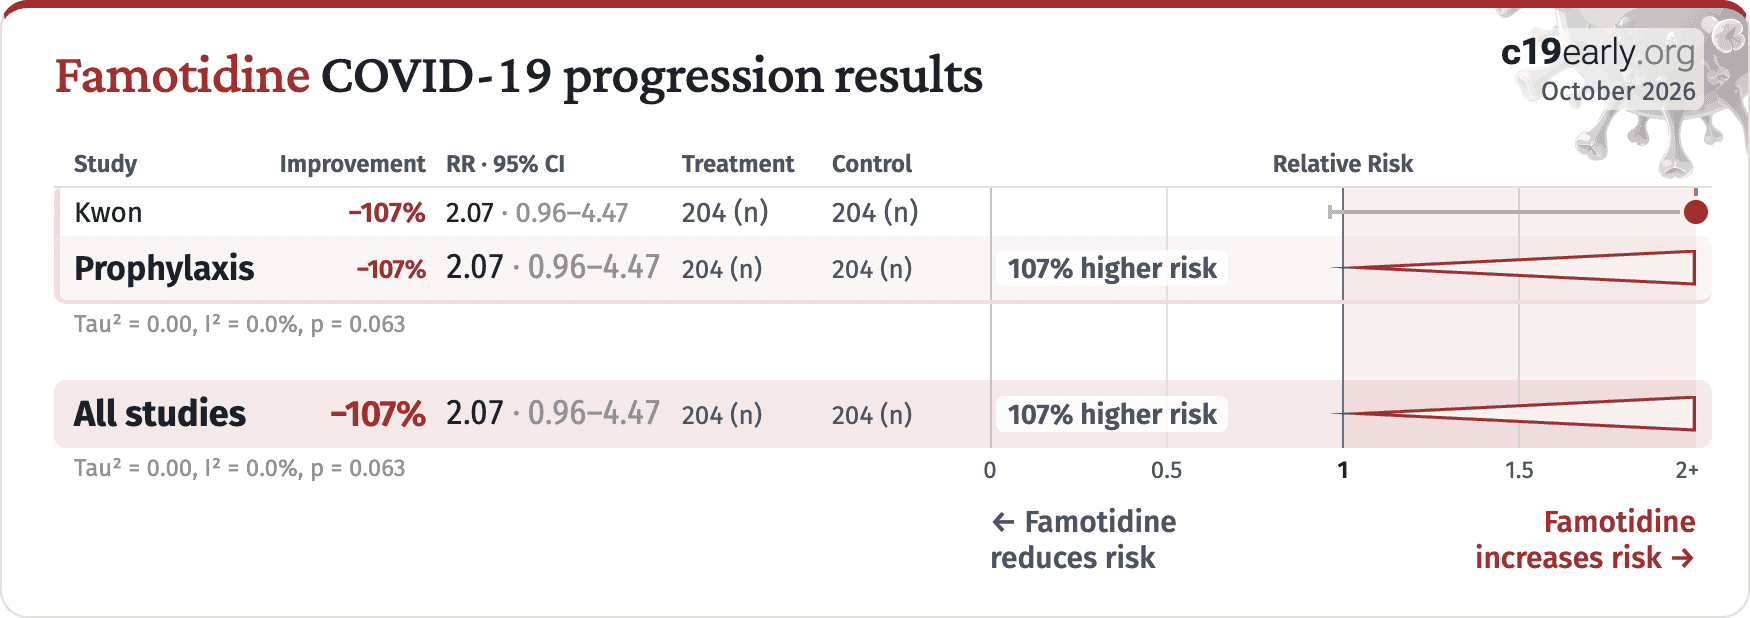
risk of progression, 107.0% higher, OR 2.07, p = 0.06, treatment 204, control 204, adjusted per study, ICU, mechanical ventilation, or death, famotidine vs. other H2-blocker use, multivariable, RR approximated with OR.
|
|
risk of progression, 256.0% higher, OR 3.56, p = 0.04, treatment 204, control 204, adjusted per study, high oxygen, ICU, mechanical ventilation, or death, famotidine vs. other H2-blocker use, multivariable, RR approximated with OR.
|
|
risk of oxygen therapy, 109.0% higher, OR 2.09, p = 0.07, treatment 204, control 204, adjusted per study, famotidine vs. other H2-blocker use, multivariable, RR approximated with OR.
|
|
Loucera, 8/16/2022, retrospective, Spain, peer-reviewed, 8 authors, study period January 2020 - November 2020.
|
risk of death, 17.5% lower, HR 0.82, p = 0.25, treatment 207, control 15,761, Cox proportional hazards, day 30.
|
|
MacFadden, 3/29/2022, retrospective, Canada, peer-reviewed, 9 authors, study period 15 January, 2020 - 31 December, 2020.
|
risk of case, 7.0% lower, OR 0.93, p = 0.16, RR approximated with OR.
|
|
Mather, 8/26/2020, retrospective, USA, peer-reviewed, 3 authors.
|
risk of death, 61.4% lower, HR 0.39, p = 0.004, treatment 83, control 689, propensity score matching, Cox proportional hazards.
|
|
risk of death/intubation, 50.5% lower, HR 0.49, p = 0.003, treatment 83, control 689, propensity score matching, Cox proportional hazards.
|
|
Razjouyan, 10/25/2021, retrospective, USA, peer-reviewed, 7 authors.
|
risk of death, 27.0% lower, OR 0.73, p = 0.006, treatment 93, control 9,981, adjusted per study, RR approximated with OR.
|
|
Wallace, 12/31/2021, retrospective, database analysis, USA, peer-reviewed, 6 authors.
|
risk of death, 11.0% higher, RR 1.11, p = 0.33, treatment 98 of 423 (23.2%), control 1,436 of 7,521 (19.1%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Yeramaneni, 2/28/2021, retrospective, USA, peer-reviewed, 6 authors, study period 11 February, 2020 - 8 May, 2020.
|
risk of death, 51.0% lower, OR 0.49, p = 0.22, treatment 351, control 6,807, adjusted per study, with home use, multivariable, day 30, RR approximated with OR.
|