Azelastine for COVID-19
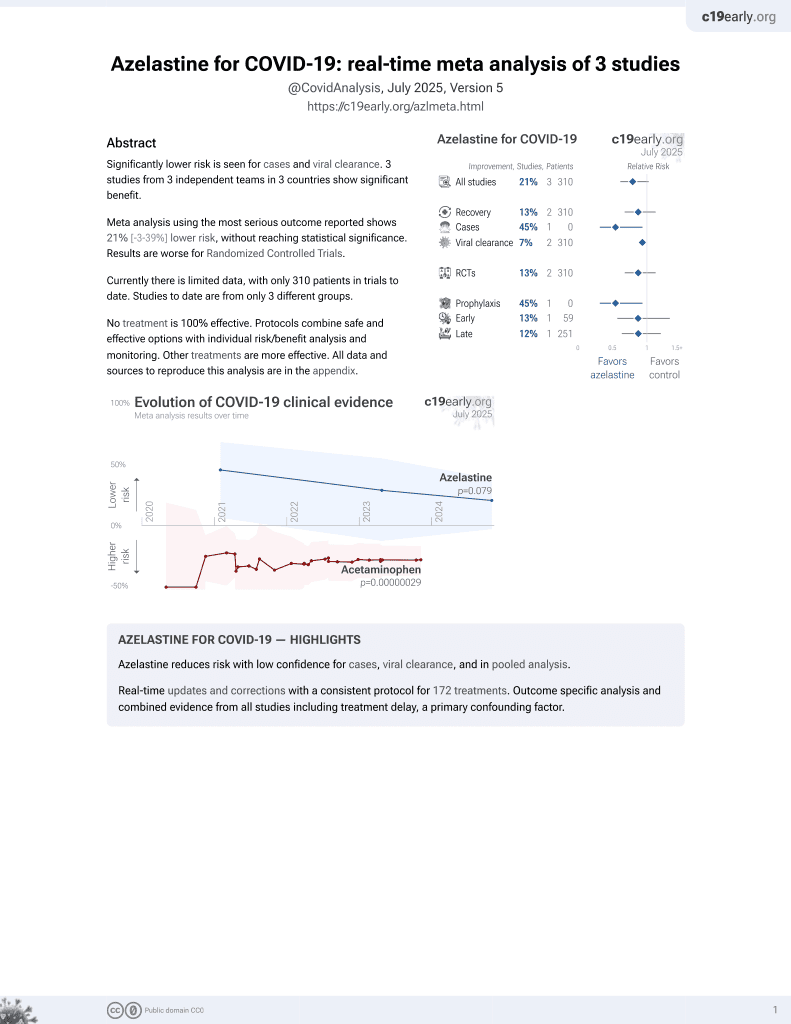
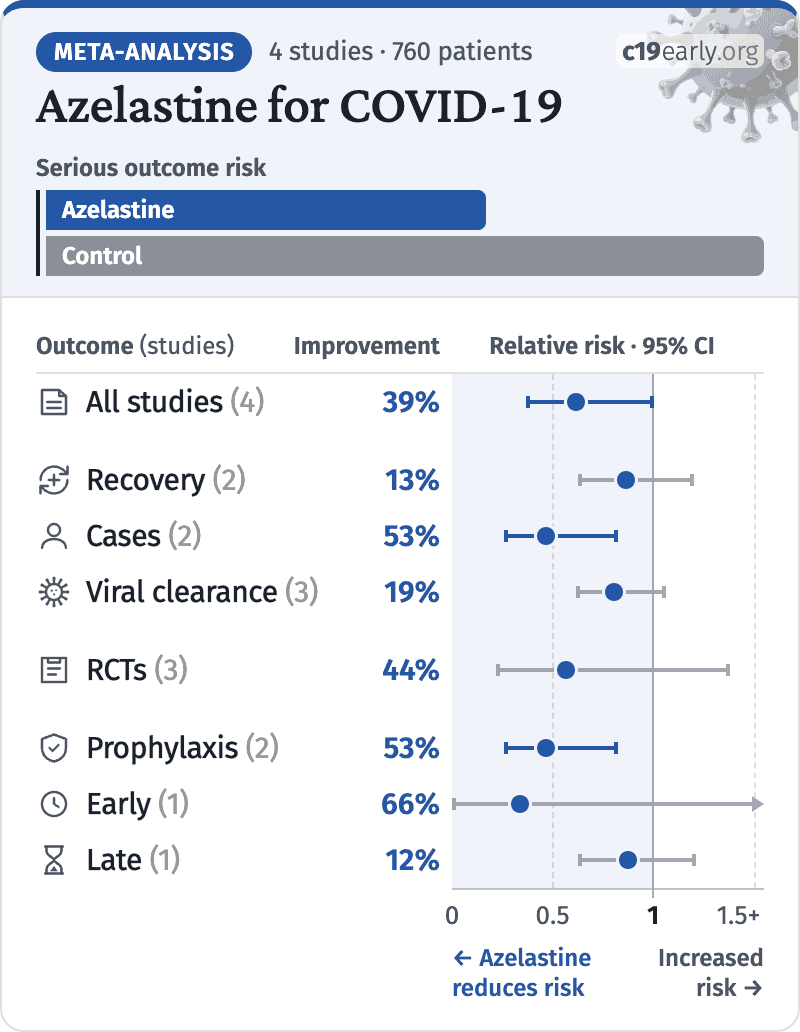
Highlights- Azelastine reduces risk with high confidence for pooled analysis and low confidence for cases and viral clearance.
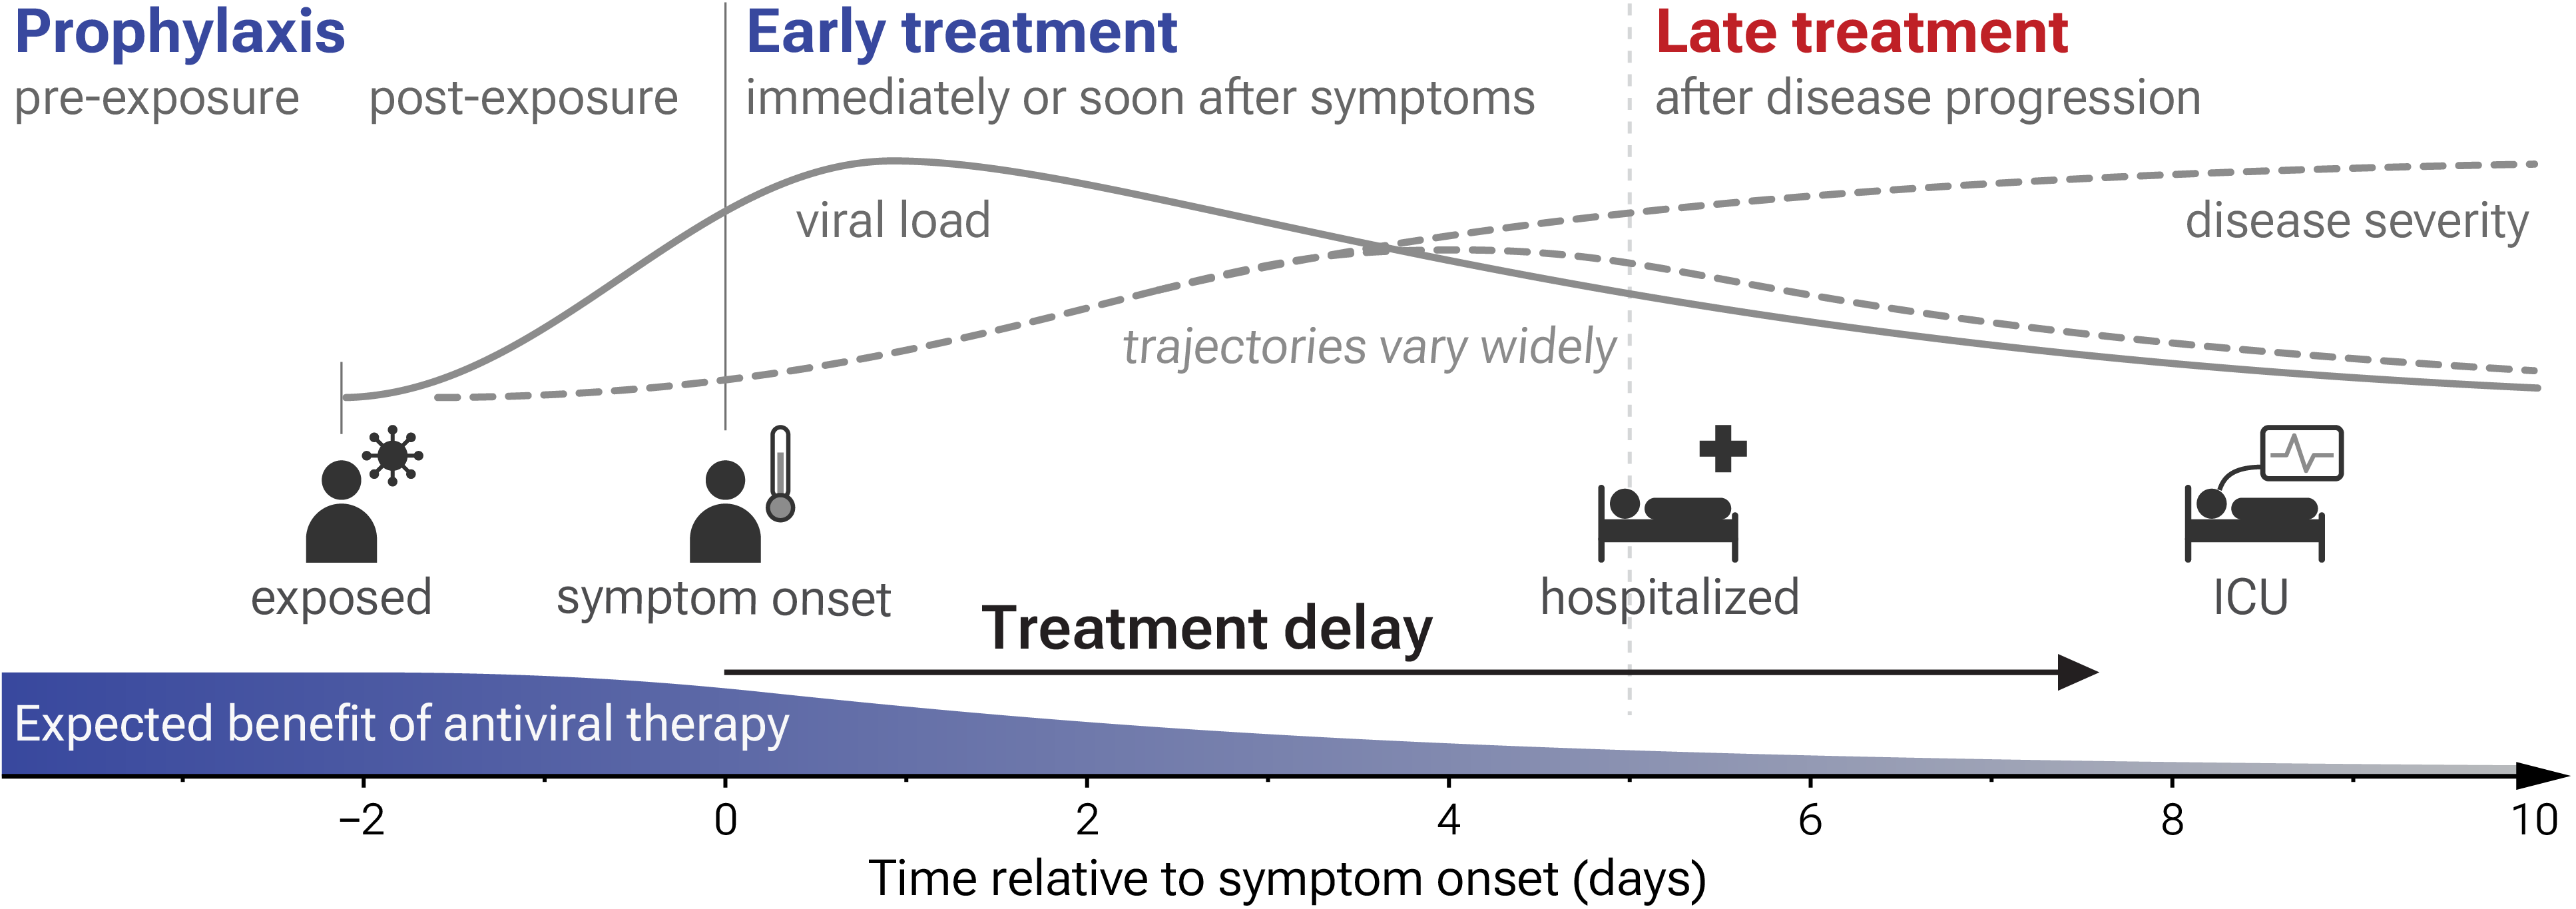
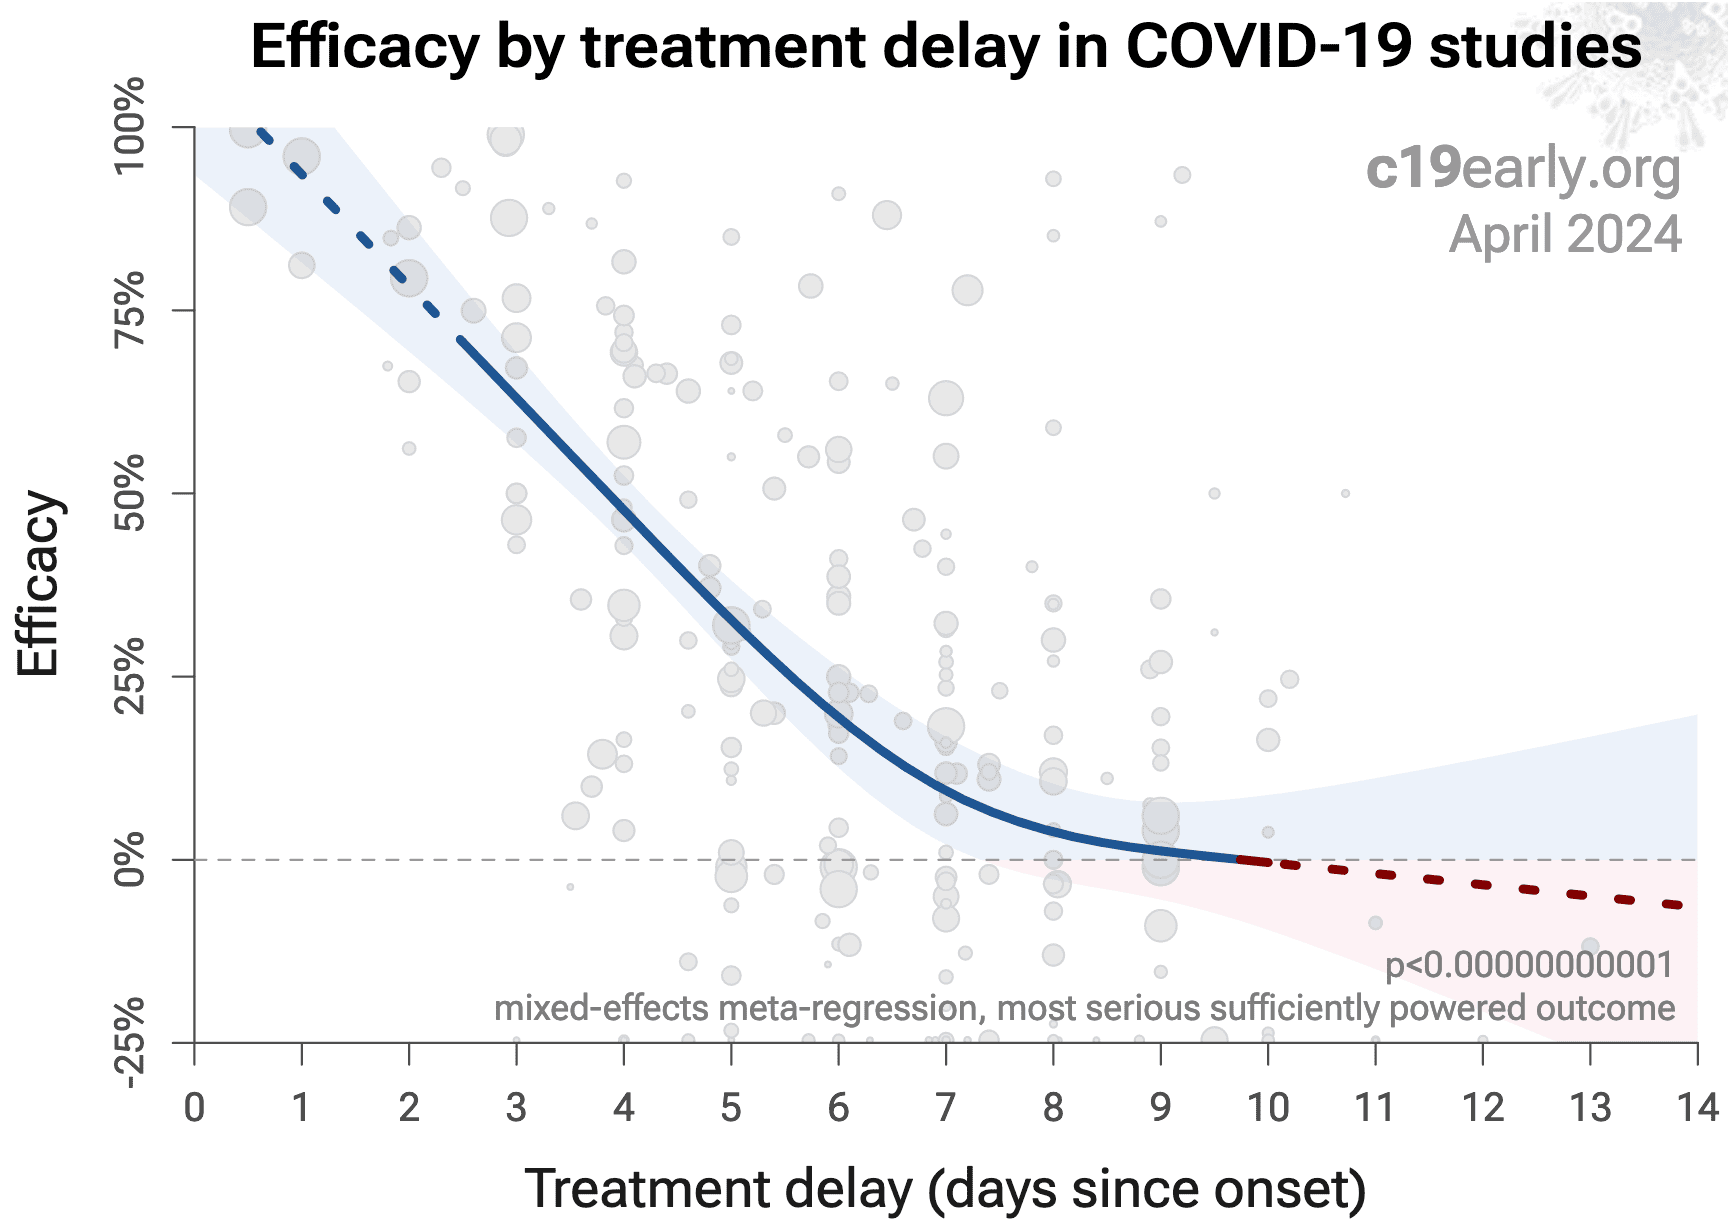
- Early treatment and prophylaxis are more effective than late treatment.
- 57th treatment shown effective in September 2025, now with p = 0.048 from 4 studies.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
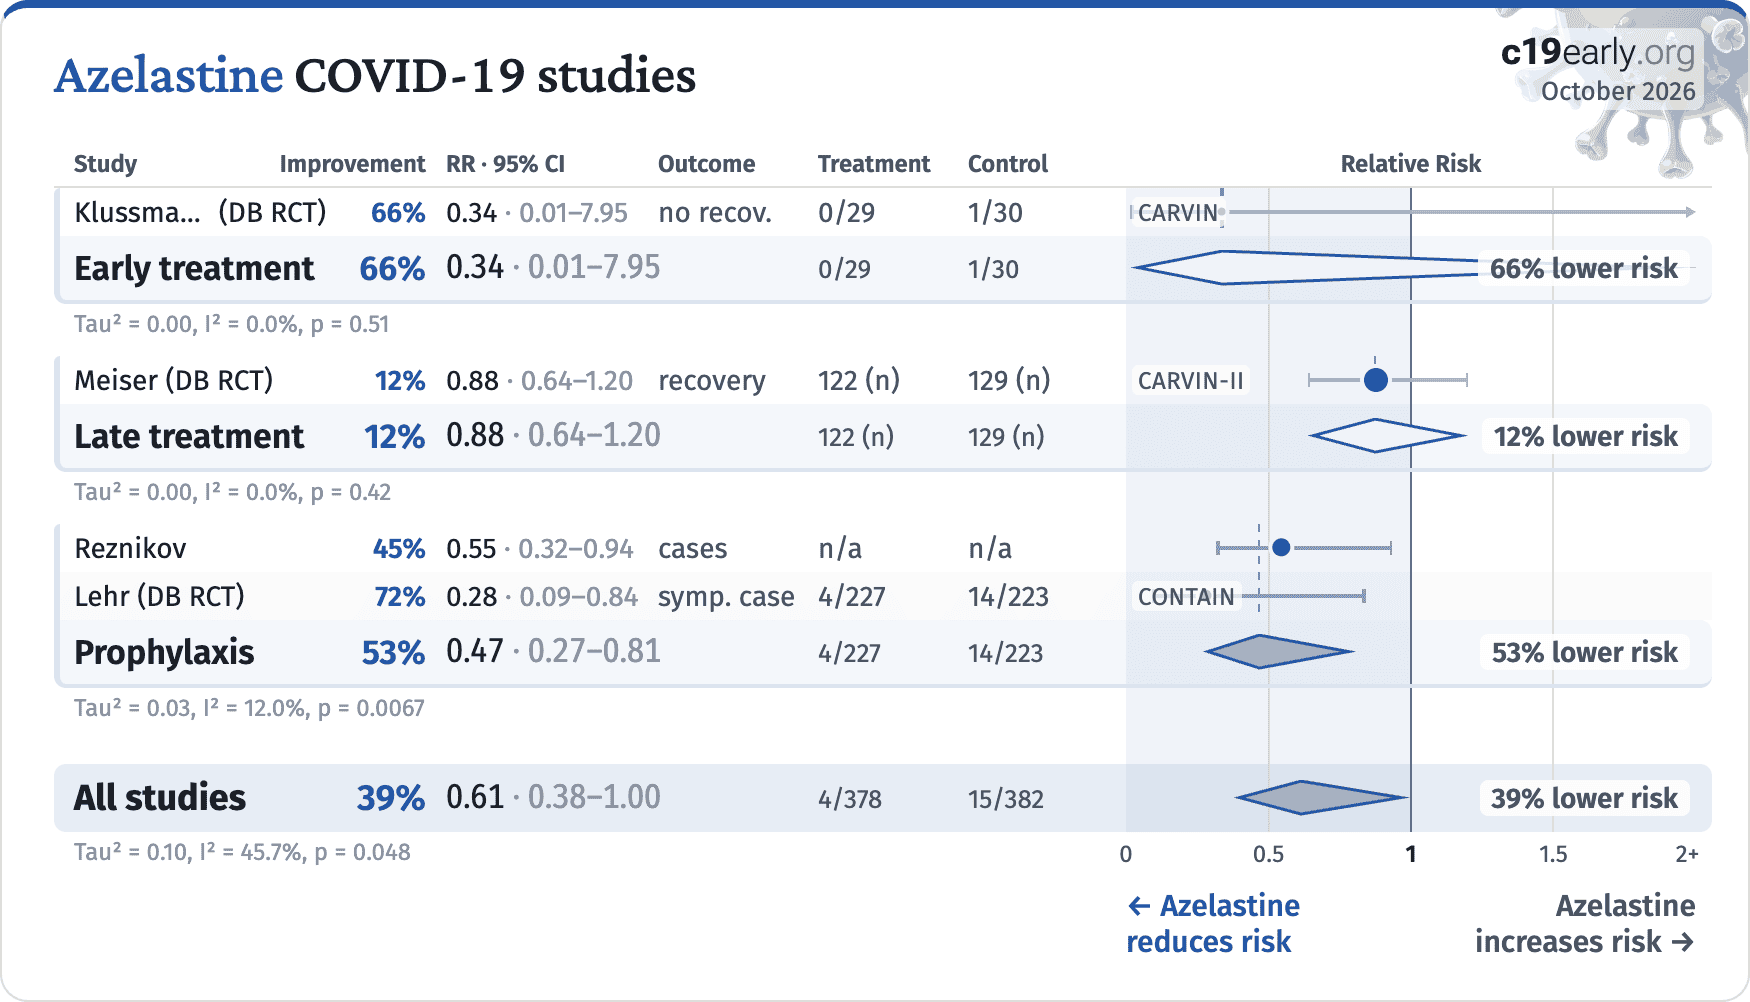
Azelastine COVID-19 studies
Azelastine for COVID-19: meta-analysis results
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Azelastine COVID-19 studies
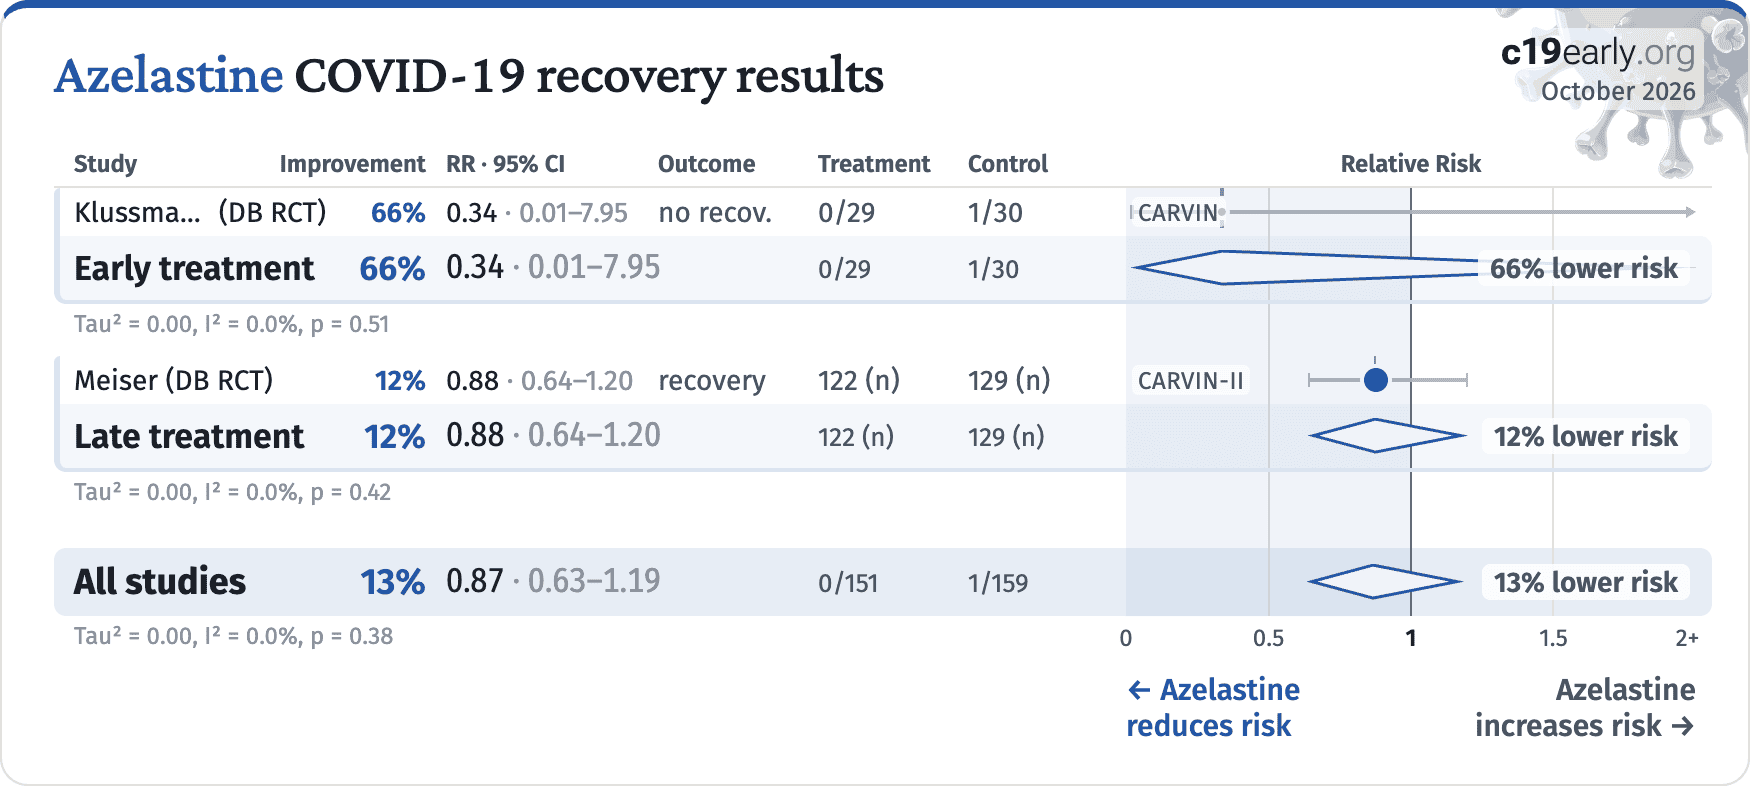
Azelastine COVID-19 recovery results
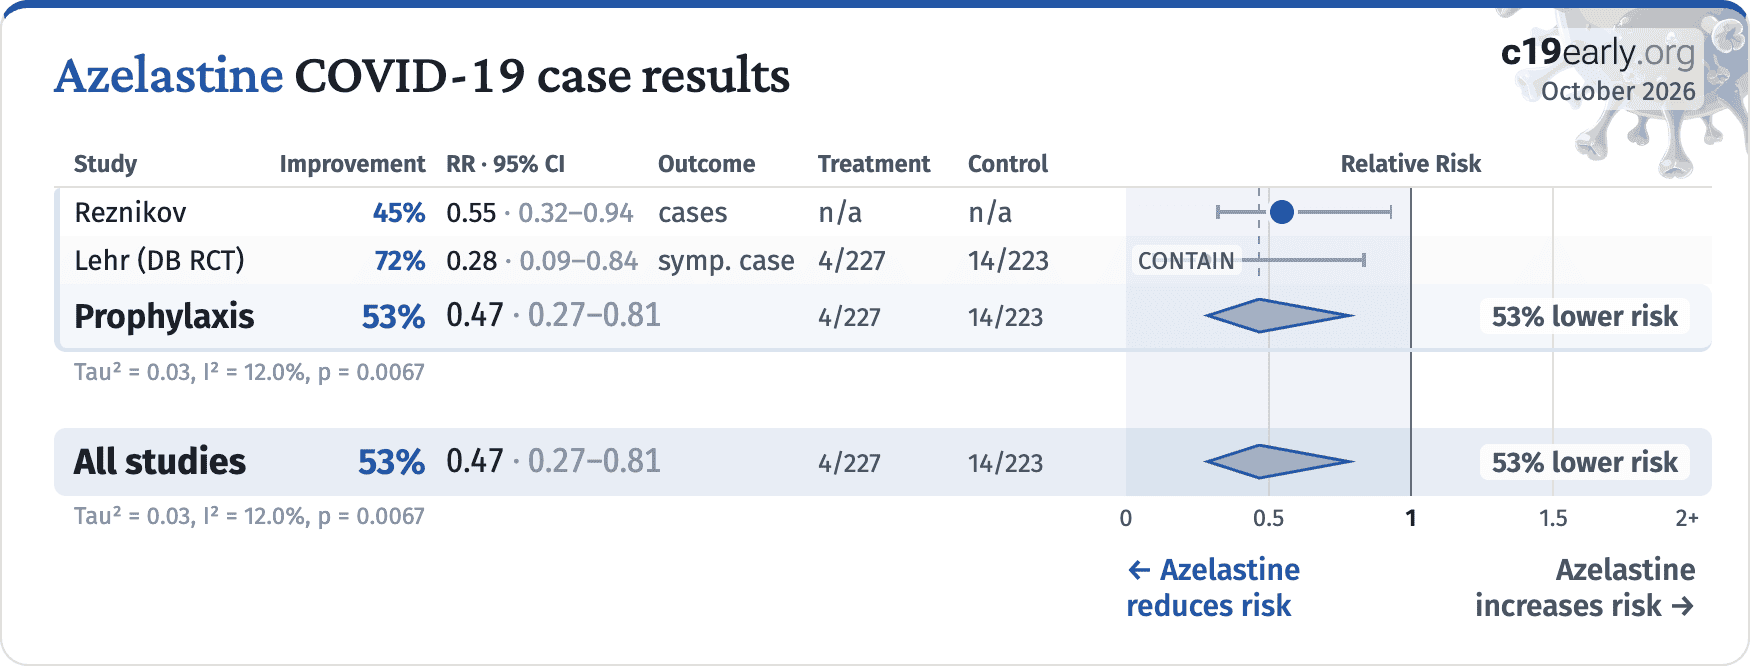
Azelastine COVID-19 case results
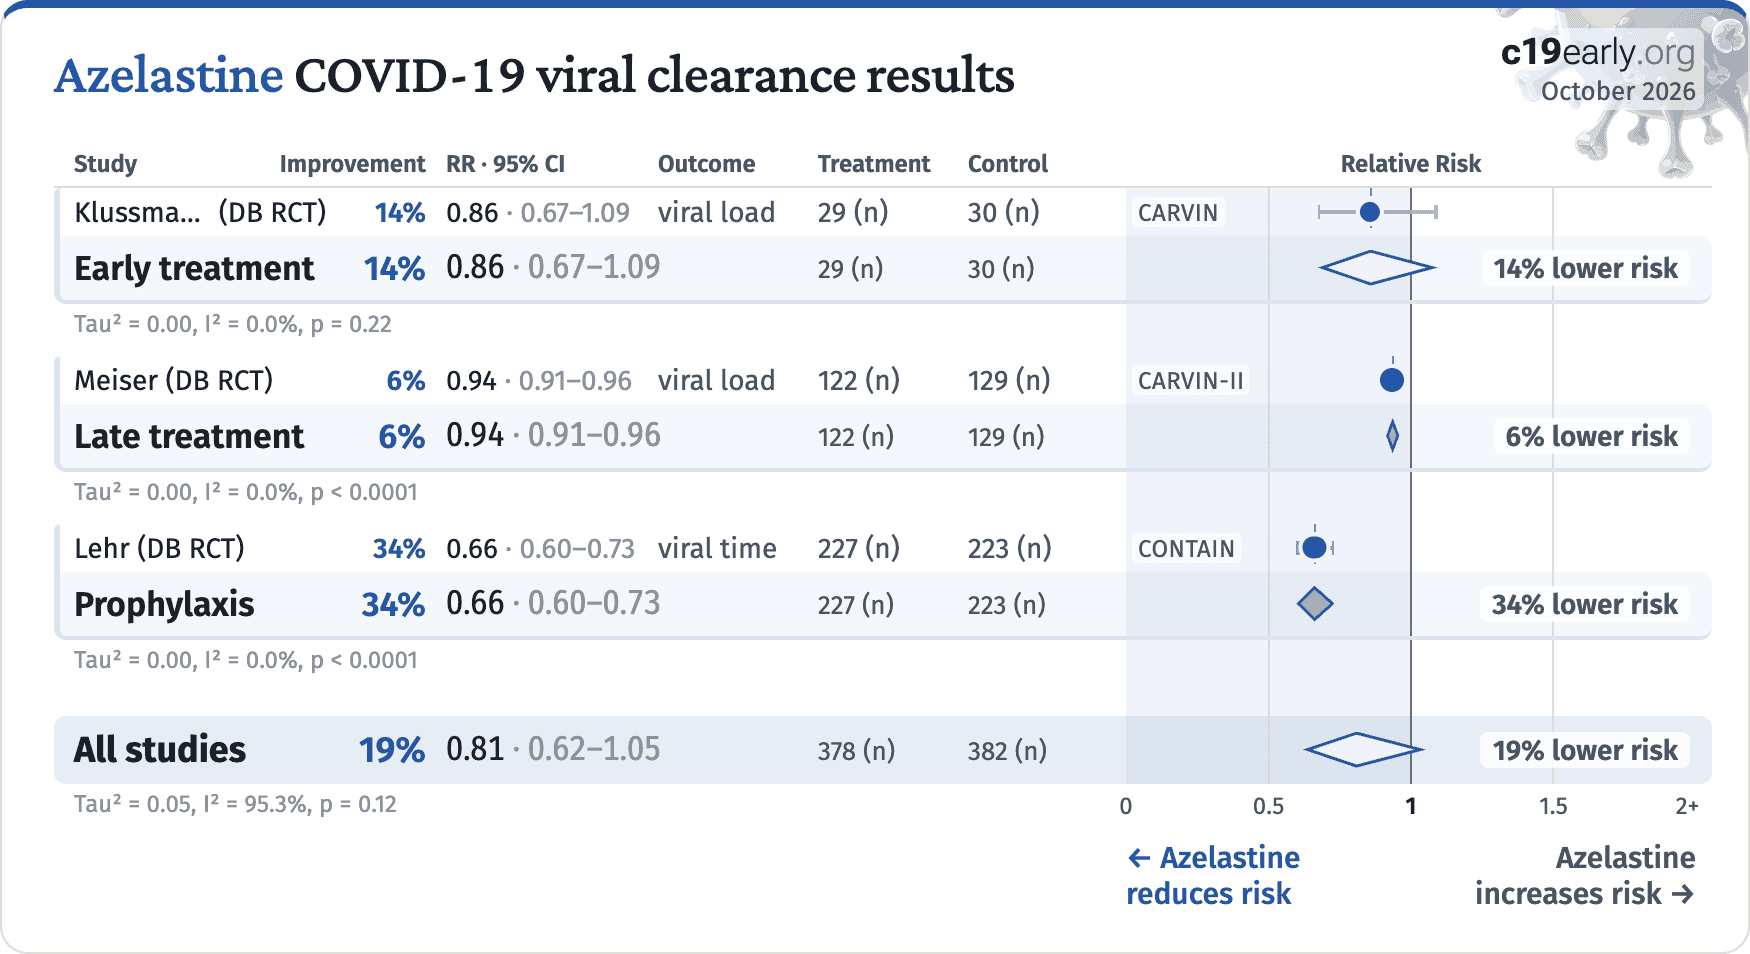
Azelastine COVID-19 viral clearance results
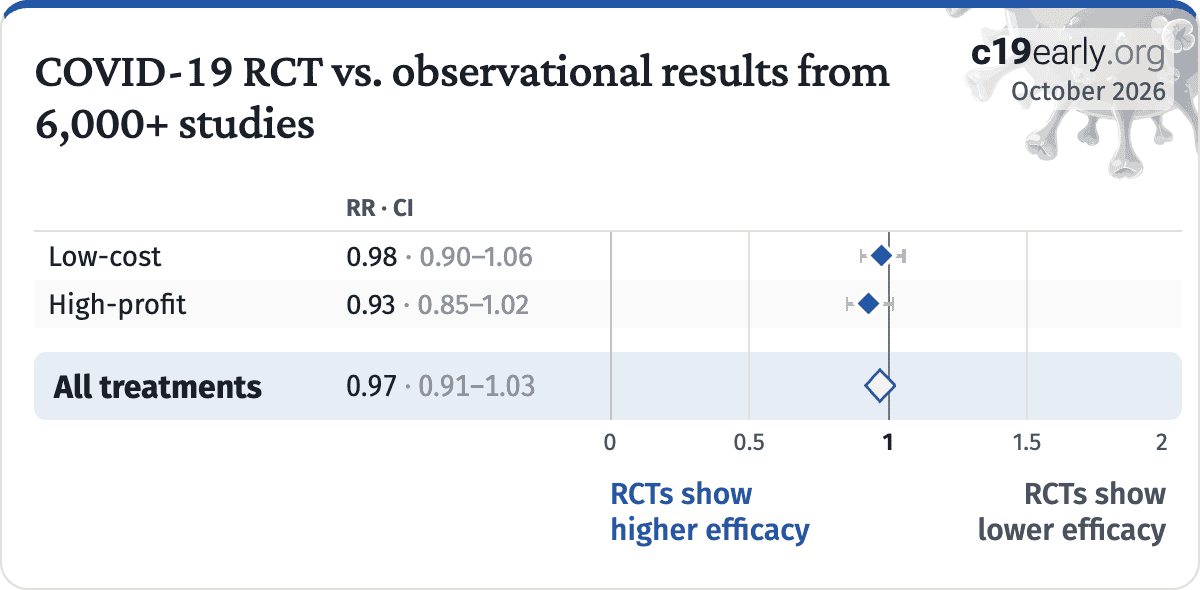
COVID-19 RCT vs. observational results from 6,000+ studies
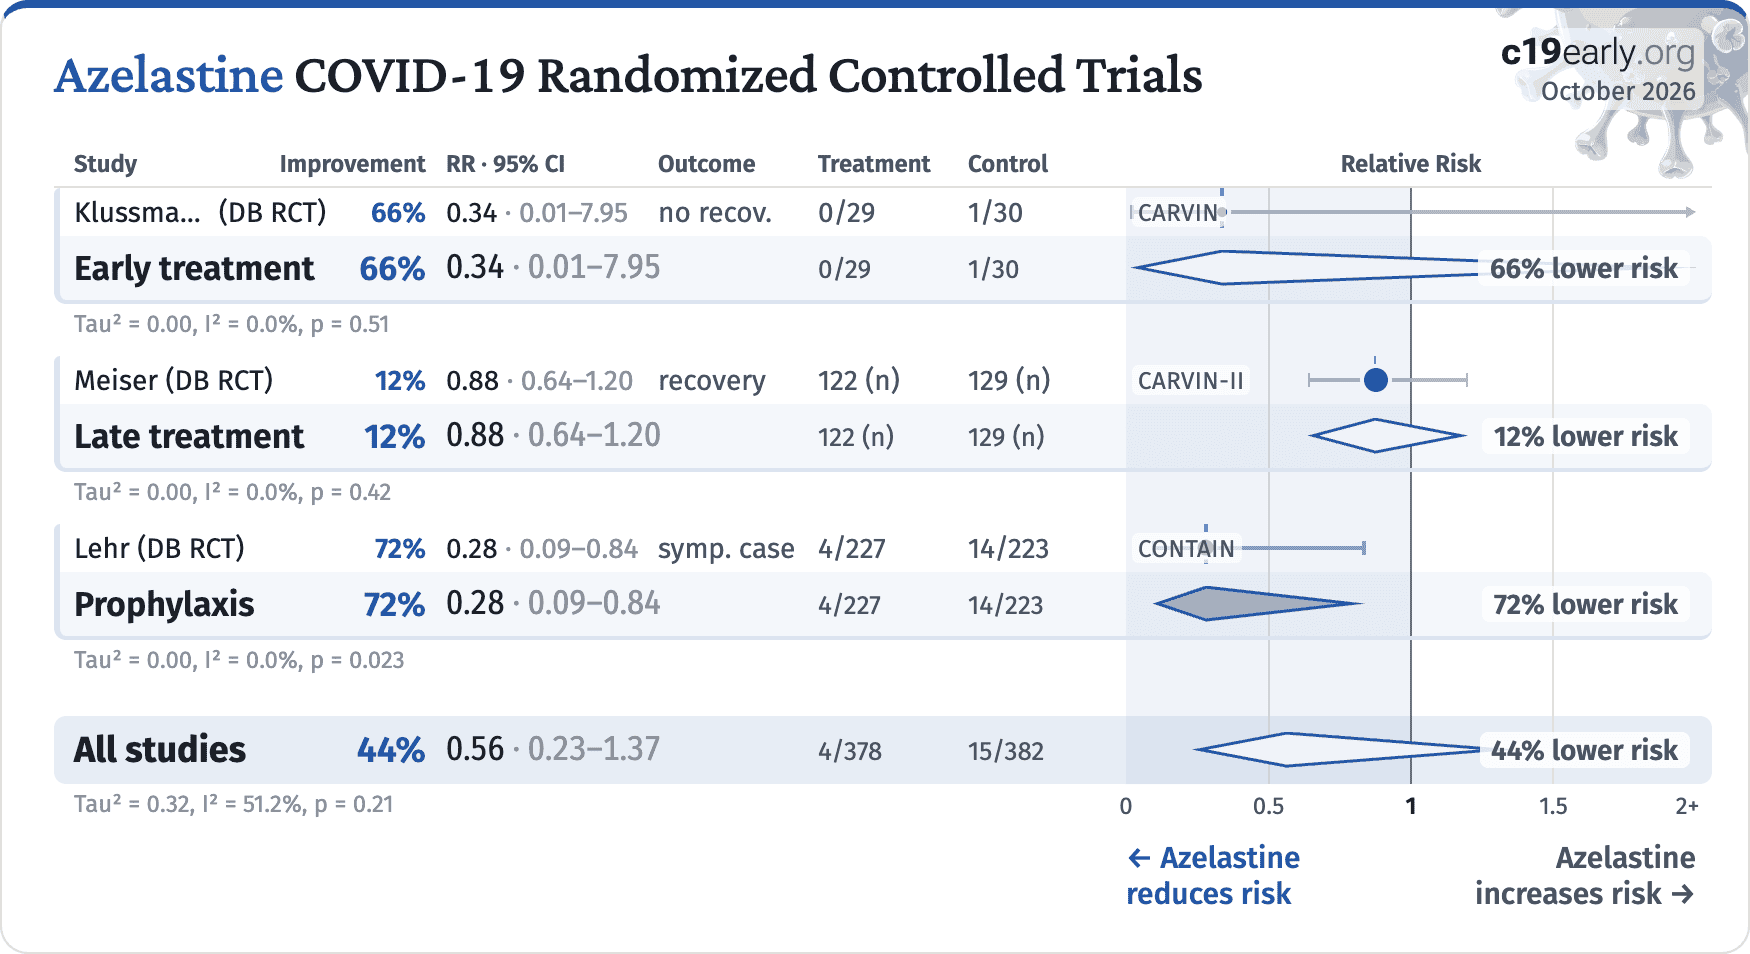
Azelastine COVID-19 Randomized Controlled Trials
Media bias for low-cost COVID‑19 treatments
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
National treatment protocols
Protocols varied widely
Most widely used early treatments selected by the most populous countries. Official protocols varied widely. Treatments only expected to be helpful for late-stage patients are excluded. low-cost, high-profit, and increased risk.
Full matrix and analysis →| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
Early treatment is more effective: baloxavir marboxil
| Administration | Improvement | Studies |
|---|---|---|
| Nasal & oral | 88% [72‑95%] | 10 |
| Nasal spray/rinse | 59% [50‑66%] | 21 |
| Oral spray/rinse | 38% [25‑49%] | 11 |
| Virucidal action | Chemically inactivating or destroying the structure of viral particles |
| Blocking attachment | Binding to the virus or host cells to prevent viral attachment to host cells |
| Physical barrier | Forming a physical layer over the nasal mucosa preventing viral access to host cells |
| Physical removal | Mechanical washout/flushing of viral particles and mucus (e.g., large volume irrigation) |
| Mucociliary clearance | Stimulating the natural beating of nasal cilia to accelerate the clearing of trapped pathogens |
| Treatment | Mechanisms | Notes |
|---|---|---|
| Azelastine |
Antiviral: inhibits interaction between spike protein and ACE2 Antiviral: potential inhibition of viral protease (Mpro) Other: H1-receptor antagonist (antihistamine) Other: mast cell stabilizer |
Antihistamine. Designed to affect human receptors. Risks include dysgeusia, drowsiness, and nasal burning. |
| Cetylpyridinium Chloride116 |
Virucidal: disrupts viral lipid envelope Antiseptic: quaternary ammonium compound |
Chemical virucide. Common in mouthwashes. Can cause temporary staining of teeth or tongue irritation if used frequently. |
| Chlorhexidine117 |
Virucidal: disrupts viral lipid membranes Antiseptic: cationic polybiguanide |
Chemical virucide. May cause tooth staining and altered taste. |
| Chlorpheniramine118 |
Antiviral: binds to viral spike protein to block entry Antiviral: high affinity for viral transport proteins Other: H1-receptor antagonist (1st generation antihistamine) Other: anticholinergic activity |
Antihistamine. Stronger systemic risks than azelastine. Known to cause significant sedation/drowsiness and cognitive impairment. |
| Hydrogen Peroxide119 |
Virucidal: oxidizing agent that destroys viral parts Other: tissue debridement |
Chemical virucide. Can be toxic to healthy tissue if concentration is too high (>1%). Long-term safety on nasal mucosa is debated. |
| Hypochlorous Acid120 |
Virucidal: oxidizes viral proteins, causing aggregation and loss of function. Impairs spike-ACE2 binding Antiseptic: broad-spectrum antimicrobial activity via oxidative damage to microbial proteins and membranes |
Chemical virucide. Activity depends on concentration, pH, and contact time. Saliva may reduce activity. |
| Inhaled Heparin121 |
Antiviral: acts as a decoy receptor (mimics heparan sulfate) Antiviral: anti-inflammatory effects on lung tissue Other: Anticoagulant |
Anticoagulant. Use requires caution regarding bleeding risks. |
| Iota-carrageenan122 |
Barrier: forms a viscous physical layer on mucosa Trap: electrostatistically traps virus particles (mimics cell surface) |
Physical barrier. High safety profile for daily use. |
| NaCl123 |
Cleaning: physically washes away viral particles Support: moisturizes mucosa to support natural immune barrier |
Physical wash. High degree of safety, reduces viral load via physical removal. |
| Nitric Oxide124 |
Virucidal: physically damages viral structure via nitrosylation Other: vasodilator (relaxes blood vessels) in systemic use |
Virucide/drug hybrid. In nasal spray form, it acts primarily as a topical disinfectant. Rapidly cleared, so systemic vasodilation risks are low but present. |
| Phthalocyanine125 |
Virucidal: generates reactive oxygen species (ROS) when exposed to light to kill virus Other: photosensitizer |
Chemical virucide. A synthetic compound often used in photodynamic therapy. Works by creating an oxidative environment hostile to the virus. |
| Povidone-Iodine126 |
Virucidal: oxidizes viral proteins and destabilizes membrane structures Antiseptic: broad-spectrum bacterial/fungal killer |
Chemical virucide. Highly effective but risk of thyroid absorption with chronic use. Can be irritating to mucous membranes. |
| Sodium Bicarbonate127 |
Environment: raises pH to inhibit viral fusion Cleaning: improves mucociliary clearance (washing) |
Physical/chemical environment. Changes the environment rather than attacking the virus directly. High degree of safety. |
| Treatment | Microbiome disruption potential | Notes |
|---|---|---|
| Iota-carrageenan122 | Low | Primarily antiviral, however extended use may mildly affect the microbiome |
| Nitric Oxide124 | Low to moderate | More selective towards pathogens, however excessive concentrations or prolonged use may disrupt the balance of bacteria |
| Alkalinization130 | Moderate | Increases pH, negatively impacting beneficial microbes that thrive in a slightly acidic environment |
| Cetylpyridinium Chloride116 | Moderate | Quaternary ammonium broad-spectrum antiseptic that can disrupt beneficial and harmful bacteria |
| Hypochlorous Acid120 | Moderate | Broad-spectrum oxidizing antiseptic that may affect beneficial and harmful bacteria |
| Phthalocyanine125 | Moderate to high | Photodynamic compound with antimicrobial activity, likely to affect the microbiome |
| Chlorhexidine117 | High | Potent antiseptic with broad activity, significantly disrupts the microbiome |
| Hydrogen Peroxide119 | High | Strong oxidizer, harming both beneficial and harmful microbes |
| Povidone-Iodine126 | High | Potent broad-spectrum antiseptic harmful to beneficial microbes |
reduces riskAzelastine
increases risk →
reduces riskAzelastine
increases risk →
reduces riskAzelastine
increases risk →
Authors report that treatment was associated with significant improvement in fever, weakness, and hypoxia compared to placebo, however detailed results are not provided for these and other symptoms.
Treatment delay from symptom onset is not specified, however the baseline viral load, lack of progression, and recovery profile are consistent with relatively late treatment among low-risk patients.
Time to recovery results are not clear, with an inconsistent HR and 95% CI reported 0.32 [0.83-2.32].
reduces riskAzelastine
increases risk →
In vitro study showing these drugs exhibit direct antiviral activity against SARS-CoV-2. Molecular docking suggests hydroxyzine and azelastine may exert antiviral effects by binding ACE2 and the sigma-1 receptor.

| Klussmann, 4/26/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Germany, peer-reviewed, 27 authors, CARVIN trial. | risk of no recovery, 66.3% lower, RR 0.34, p = 1.00, treatment 0 of 29 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 0.1%. |
| risk of no recovery, 67.0% lower, RR 0.33, p = 0.49, treatment 0 of 31 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 0.02%. | |
| symptoms, 12.7% lower, RR 0.87, p = 0.54, treatment mean 12.74 (±10.74) n=29, control mean 11.12 (±9.45) n=30, relative change in symptom score, 0.1%. | |
| symptoms, 32.7% higher, RR 1.33, p = 0.26, treatment mean 8.38 (±9.42) n=31, control mean 11.12 (±9.45) n=30, relative change in symptom score, 0.02%. | |
| viral load, 14.2% lower, relative load 0.86, p = 0.22, treatment mean 4.45 (±2.25) n=29, control mean 3.82 (±1.61) n=30, 0.1%. | |
| viral load, 7.3% lower, relative load 0.93, p = 0.52, treatment mean 4.12 (±2.01) n=31, control mean 3.82 (±1.61) n=30, 0.02%. | |
| risk of no viral clearance, 21.7% lower, RR 0.78, p = 0.04, treatment mean 24.14 (±13.12) n=29, control mean 18.89 (±4.7) n=30, relative AUC, 0.1%. | |
| risk of no viral clearance, 6.2% lower, RR 0.94, p = 0.54, treatment mean 24.14 (±12.56) n=31, control mean 22.64 (±4.7) n=30, relative AUC, 0.02%. |
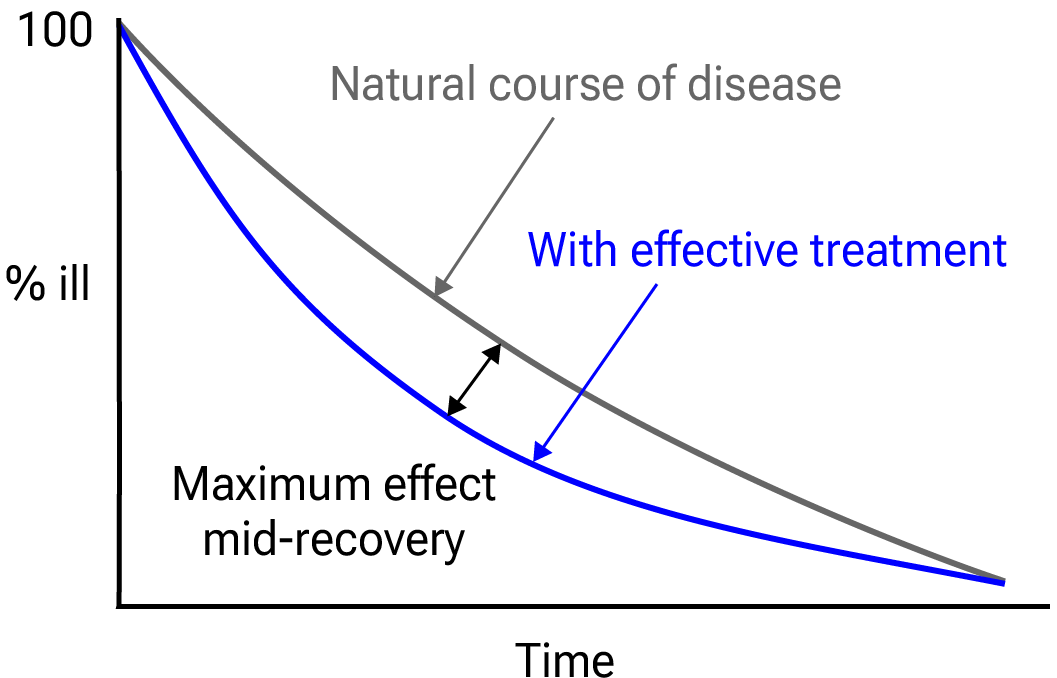
| Meiser, 10/31/2024, Double Blind Randomized Controlled Trial, placebo-controlled, India, peer-reviewed, 8 authors, study period 27 September, 2022 - 16 May, 2023, trial CTRI/2022/09 (CARVIN-II). | risk of no recovery, 12.5% lower, RR 0.87, p = 0.42, treatment mean 0.8 (±0.99) n=122, control mean 0.7 (±0.96) n=129, WHO scale improvement, mid-recovery, day 3. |
| viral load, 6.4% lower, relative load 0.94, p < 0.001, treatment mean 2.8 (±0.27) n=122, control mean 2.62 (±0.26) n=129, relative viral load reduction, mid-recovery, day 3. | |
| viral load, 2.2% lower, relative load 0.98, p = 0.001, treatment mean 5.05 (±0.29) n=122, control mean 4.94 (±0.25) n=129, relative viral load reduction, mid-recovery, day 6. | |
| viral load, 1.3% lower, relative load 0.99, p = 0.003, treatment mean 5.93 (±0.22) n=122, control mean 5.85 (±0.2) n=129, relative viral load reduction, mid-recovery, day 11. | |
| risk of no viral clearance, 3.2% lower, RR 0.97, p < 0.001, treatment mean 1014.96 (±35.25) n=122, control mean 982.98 (±31.68) n=129, relative AUC. |
| Lehr, 9/2/2025, Double Blind Randomized Controlled Trial, placebo-controlled, Germany, peer-reviewed, 25 authors, study period March 2023 - July 2024, trial 2022-003756-13 (CONTAIN). | risk of symptomatic case, 71.9% lower, RR 0.28, p = 0.02, treatment 4 of 227 (1.8%), control 14 of 223 (6.3%), NNT 22. |
| risk of case, 69.0% lower, HR 0.31, p = 0.03, treatment 5 of 227 (2.2%), control 15 of 223 (6.7%), NNT 22, Cox proportional hazards, Kaplan-Meier. | |
| time to viral-, 33.9% lower, relative time 0.66, p < 0.001, treatment mean 3.4 (±1.34) n=227, control mean 5.14 (±2.98) n=223. | |
| Reznikov, 1/31/2021, retrospective, USA, peer-reviewed, 9 authors. | risk of case, 45.5% lower, RR 0.55, p = 0.03, adjusted per study, age groups combined. |
| risk of case, 58.8% lower, OR 0.41, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 61+, multivariable, RR approximated with OR. | |
| risk of case, 28.6% lower, OR 0.71, p = 0.17, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 31-60, multivariable, RR approximated with OR. |