Vitamin A for COVID-19: real-time meta-analysis of 21 studies (14 treatment studies and 7 sufficiency studies)

Abstract
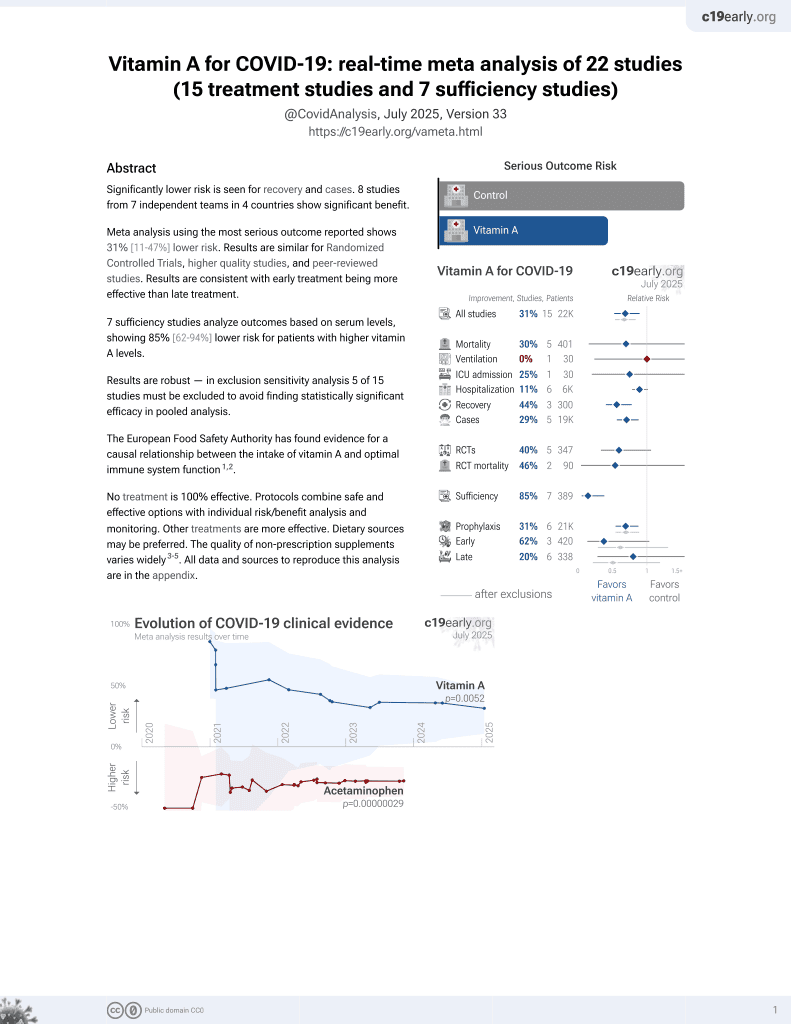
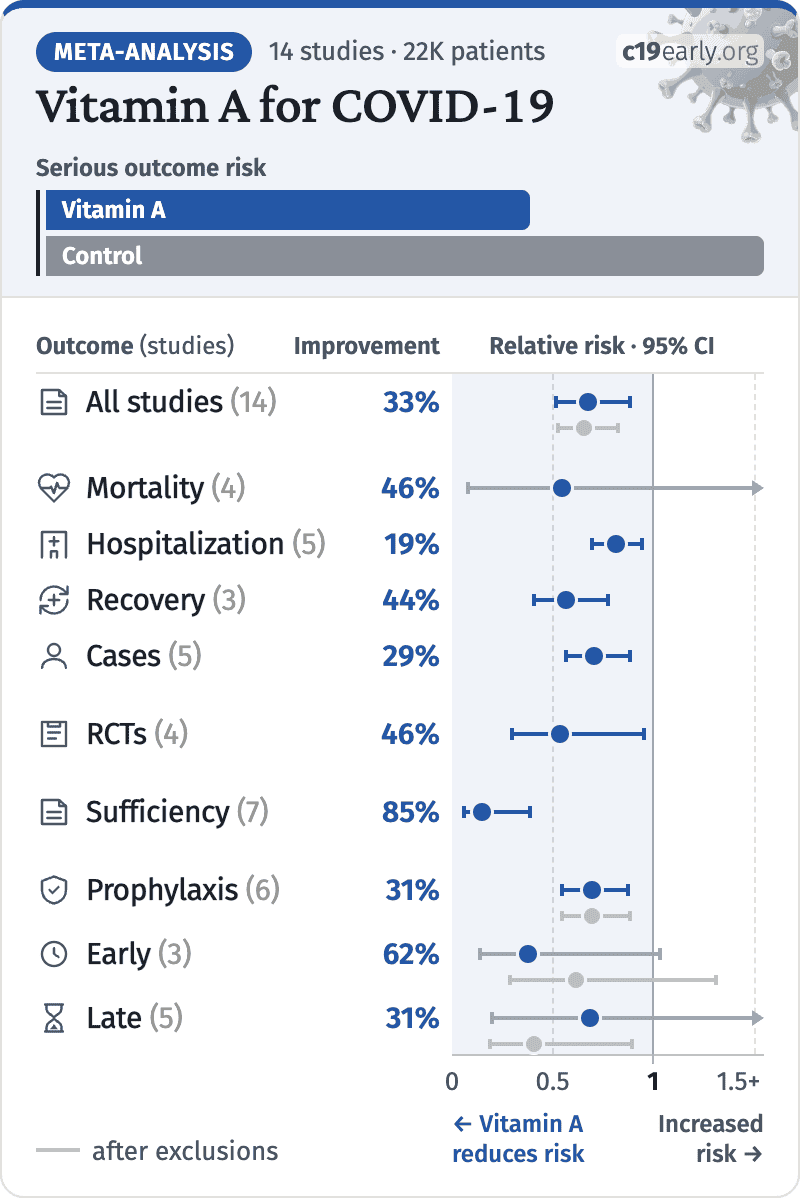
Significantly lower risk is seen for hospitalization, recovery, and cases. 8 studies from 7 independent teams in 4 countries show significant benefit.
Meta-analysis using the most serious outcome reported shows 33% [12‑49%] lower risk. Results are similar for higher quality and peer-reviewed studies and better for Randomized Controlled Trials. Results are consistent with early treatment being more effective than late treatment.
7 sufficiency studies analyze outcomes based on serum levels, showing 85% [62‑94%] lower risk for patients with higher vitamin A levels.
Results are robust—in worst case exclusion sensitivity analysis 5 of 14 studies must be excluded before statistical significance is lost.
The European Food Safety Authority has found evidence for a causal relationship between the intake of vitamin A and optimal immune system function1,2.
No treatment is 100% effective. Protocols combine safe and effective options with individual risk/benefit analysis and monitoring. Other treatments are more effective. Dietary sources may be preferred. The quality of non-prescription supplements varies widely3-5. Administration with a high-fat meal increases the bioavailability of vitamin A, and may aid distribution to target tissues. All data and sources to reproduce this analysis are in the appendix.
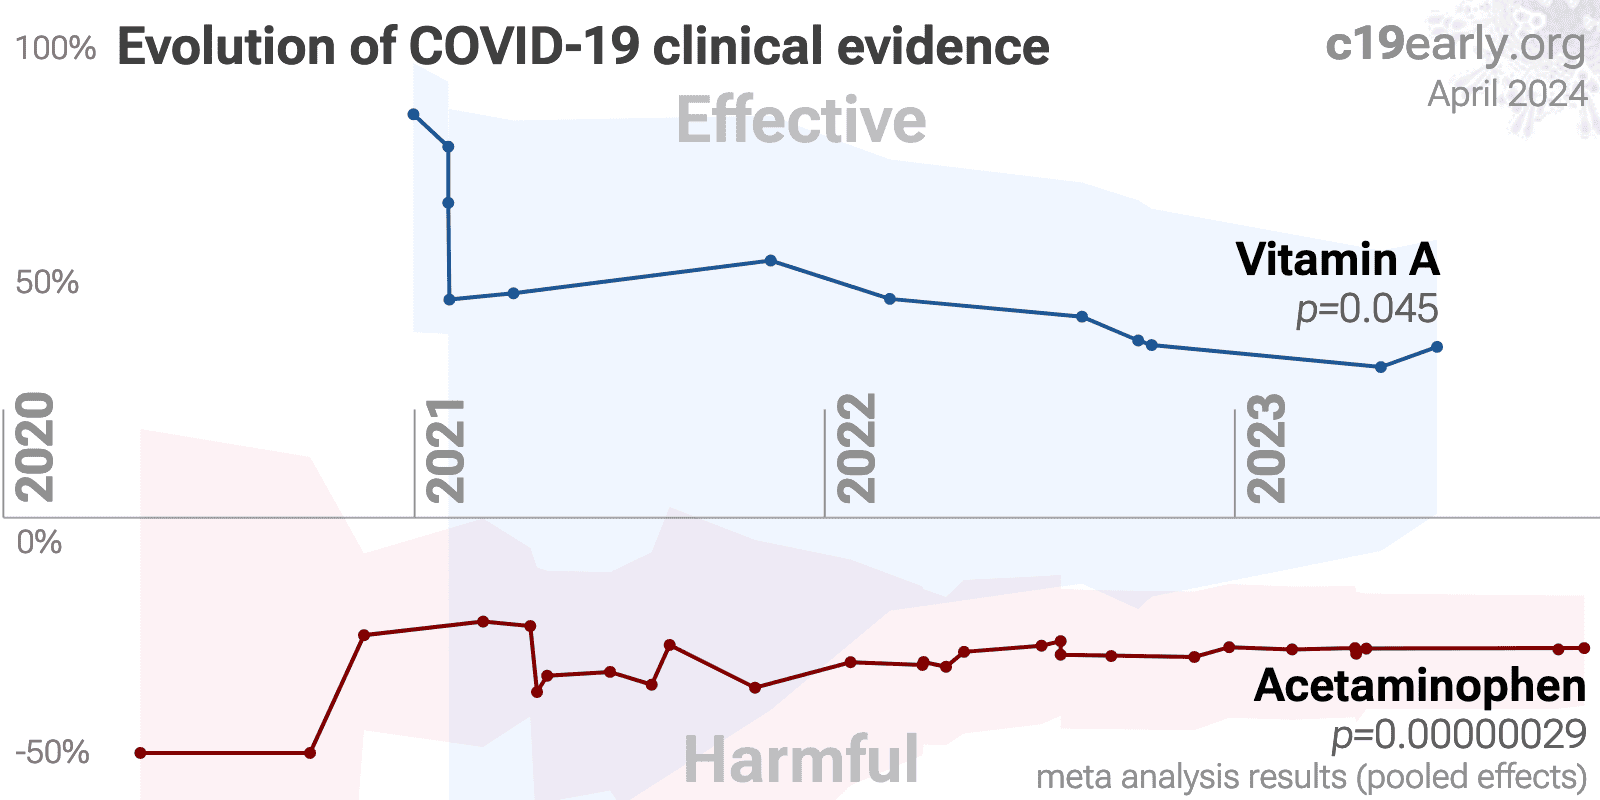
Evolution of COVID-19 clinical evidence Meta-analysis results over time Vitamin A p=0.004 Acetaminophen p=0.00000021 2020 2021 2022 2023 2024 2025 2026 Lowerrisk Higherrisk c19early.org October 2026 50% 0% -50%

Vitamin A for COVID-19

Highlights
A
October 2026

Vitamin A COVID-19 studies

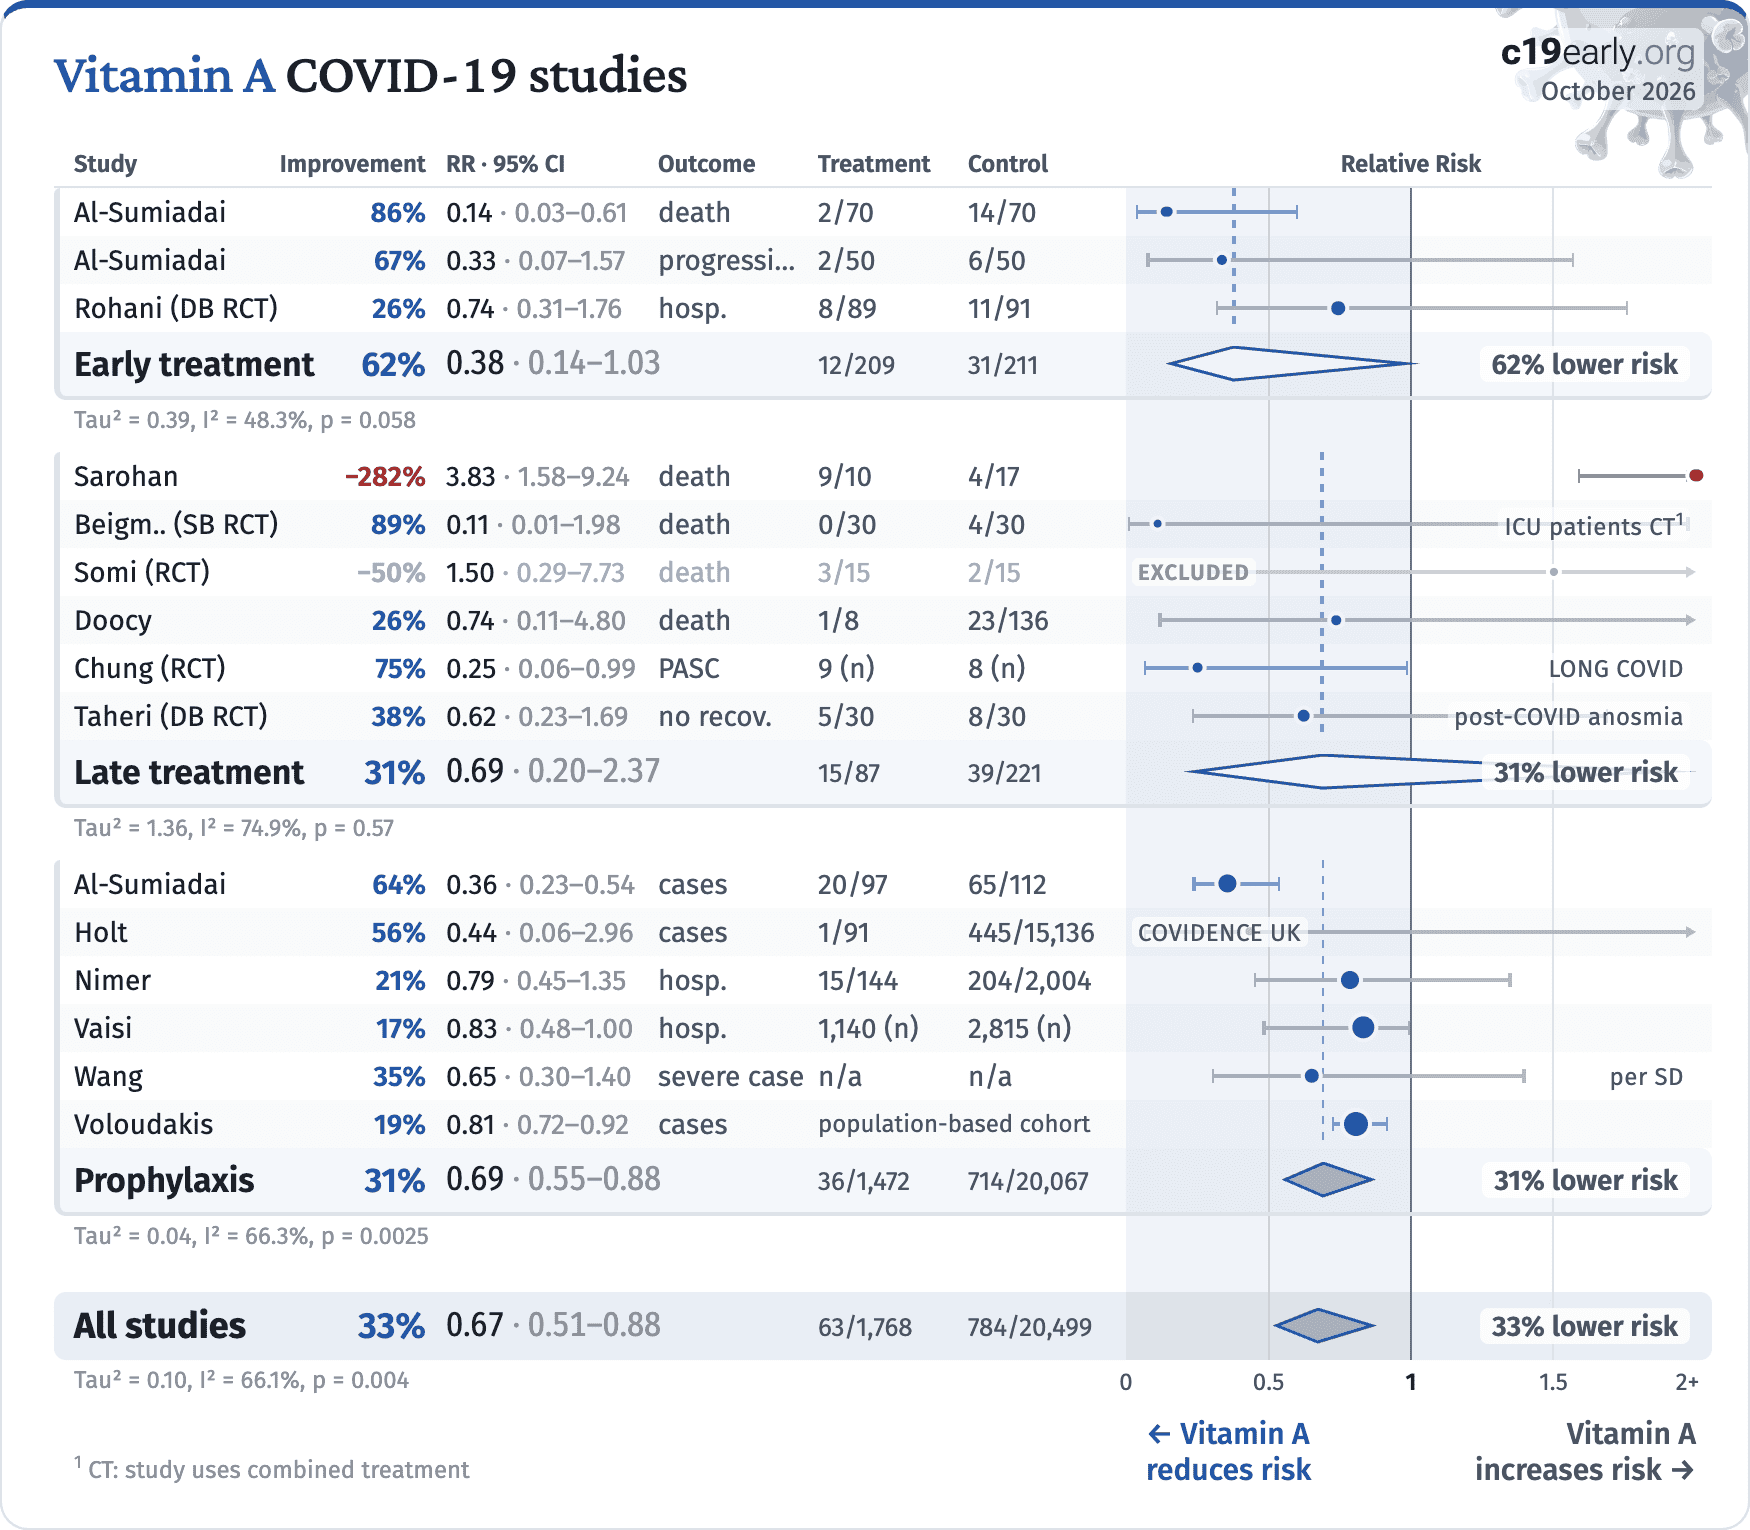
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment62%0.38 · 0.14–1.0312/20931/21162% lower risk
Tau² = 0.39, I² = 48.3%, p = 0.058
Late treatment31%0.69 · 0.20–2.3715/8739/22131% lower risk
Tau² = 1.36, I² = 74.9%, p = 0.57
Prophylaxis31%0.69 · 0.55–0.8836/1,472714/20,06731% lower risk
Tau² = 0.04, I² = 66.3%, p = 0.0025
All studies33%0.67 · 0.51–0.8863/1,768784/20,49933% lower risk
Tau² = 0.10, I² = 66.1%, p = 0.00400.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
B
Loading..
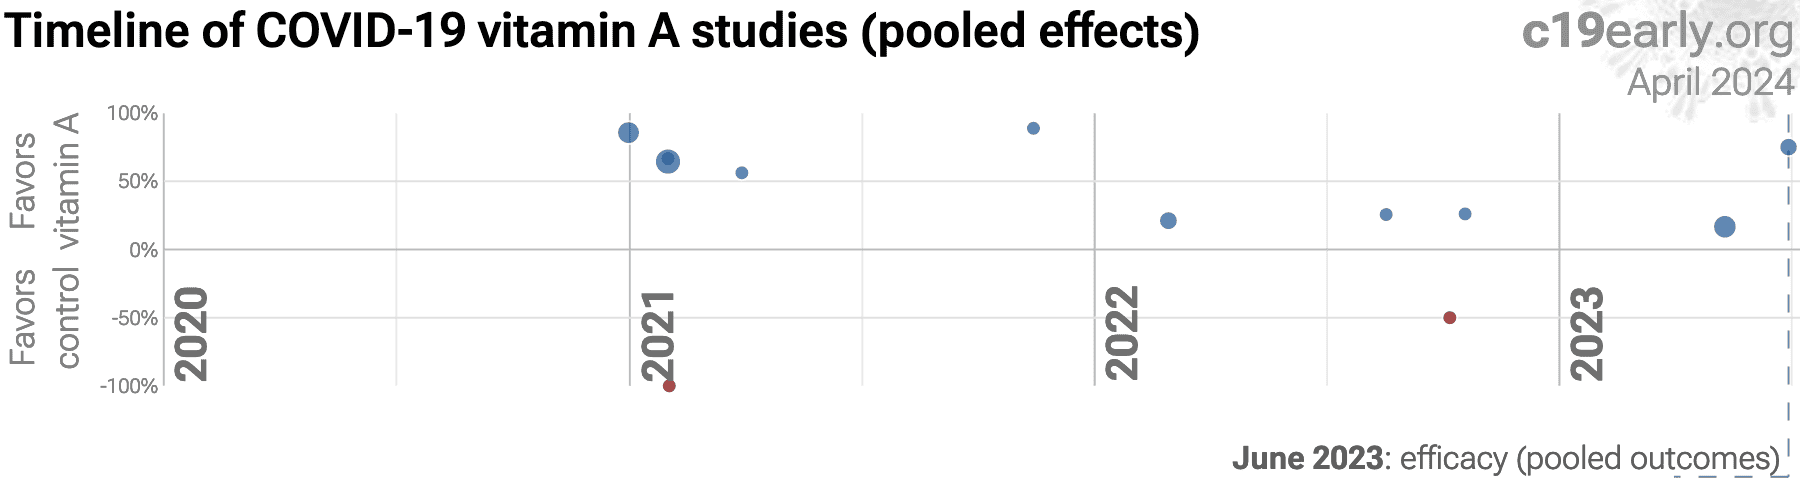
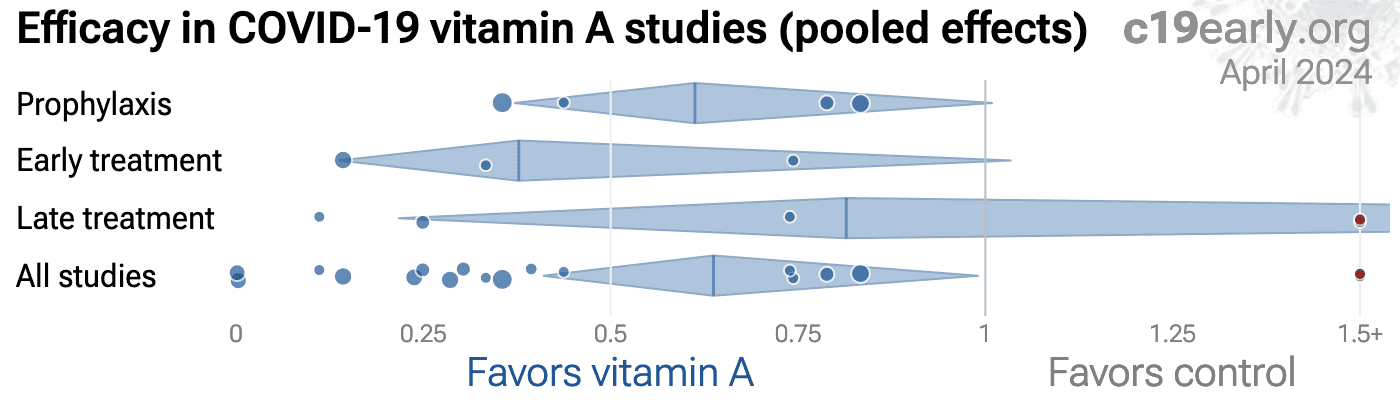
Fig. 1. A. Random-effects meta-analysis. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix. B. Timeline of results in vitamin A studies. The marked dates indicate the time when efficacy was known with a statistically significant improvement of ≥10% from ≥3 studies for pooled outcomes, one or more specific outcome, and pooled outcomes in RCTs. Efficacy based on RCTs only was delayed by 12.8 months, compared to using all studies.
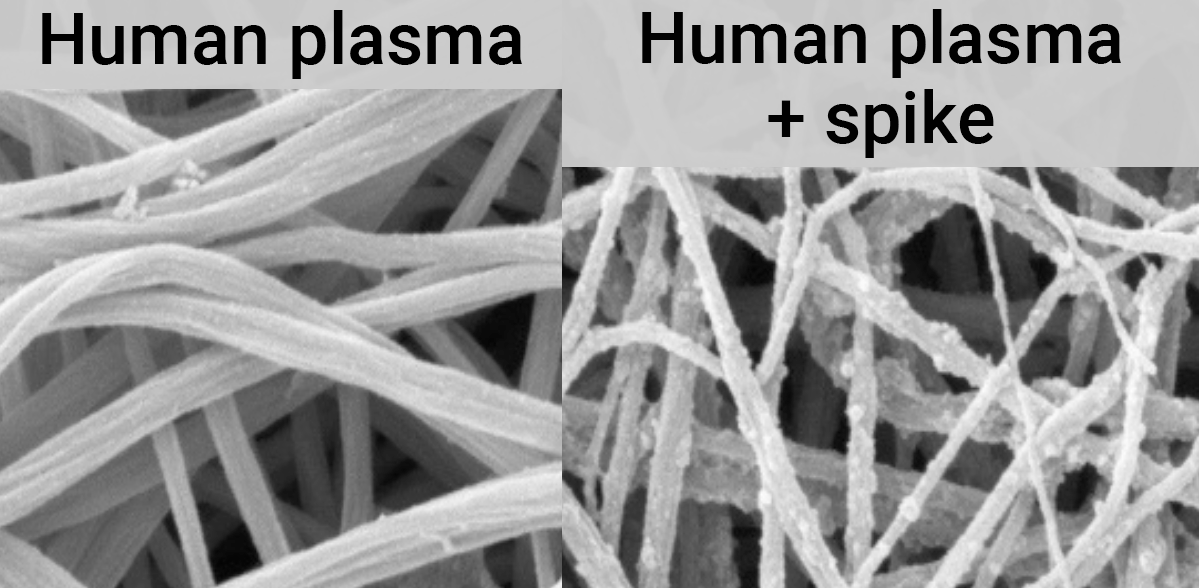
Fig. 2. SARS-CoV-2 spike protein fibrin binding leads to thromboinflammation and neuropathology, from6.
SARS-CoV-2 infection primarily begins in the upper respiratory tract and may progress to the lower respiratory tract, other tissues, and the nervous and cardiovascular systems, which may lead to cytokine storm, pneumonia, ARDS, neurological injury7-23 and cognitive deficits10,15, cardiovascular complications24-30, DNA damage31-34, organ failure, and death. Even mild untreated infections may result in persistent cognitive deficits35—the spike protein binds to fibrin leading to fibrinolysis-resistant blood clots, thromboinflammation, and neuropathology. Minimizing replication as early as possible is recommended.
SARS-CoV-2 infection and replication involves the complex interplay of 500+ host and viral proteins and other factorsA,36-43, providing many therapeutic targets for which many existing compounds have known activity. Scientists have predicted that over 12,000 compounds may reduce COVID-19 risk44, either by directly minimizing infection or replication, by supporting immune system function, or by minimizing secondary complications.
Vitamin A has been identified by the European Food Safety Authority (EFSA) as having sufficient evidence for a causal relationship between intake and optimal immune system function1,2,45. Vitamin A has potent antiviral activity against SARS-CoV-2 in both human cell lines and human organoids of the lower respiratory tract (active metabolite all-trans retinoic acid, ATRA)46, is predicted to bind critical host and viral proteins for SARS-CoV-2 and may compensate for gene expression changes related to SARS-CoV-247-49, may be beneficial for COVID-19 via antiviral, anti-inflammatory, and immunomodulatory effects according to network pharmacology analysis50, reduces barrier compromise caused by TNF-α in Calu-3 cells51, inhibits mouse coronavirus replication52, may stimulate innate immunity by activating interferon responses in an IRF3-dependent manner (ATRA)52, may reduce excessive inflammation induced by SARS-CoV-249, shows SARS-CoV-2 antiviral activity In Vitro49,53,54, is effective against multiple SARS-CoV-2 variants in Calu-3 cells54, and inhibits the entry and replication of SARS-CoV-2 via binding to ACE2 / 3CLpro / RdRp / helicase / 3'-to-5' exonuclease49.
We analyze all significant controlled studies of vitamin A for COVID-19. Search methods, inclusion criteria, effect extraction criteria (more serious outcomes have priority), all individual study data, PRISMA answers, and statistical methods are detailed in Appendix 1. We present random-effects meta-analysis results for all studies, studies within each treatment stage, individual outcomes, peer-reviewed studies, Randomized Controlled Trials (RCTs), and higher quality studies.
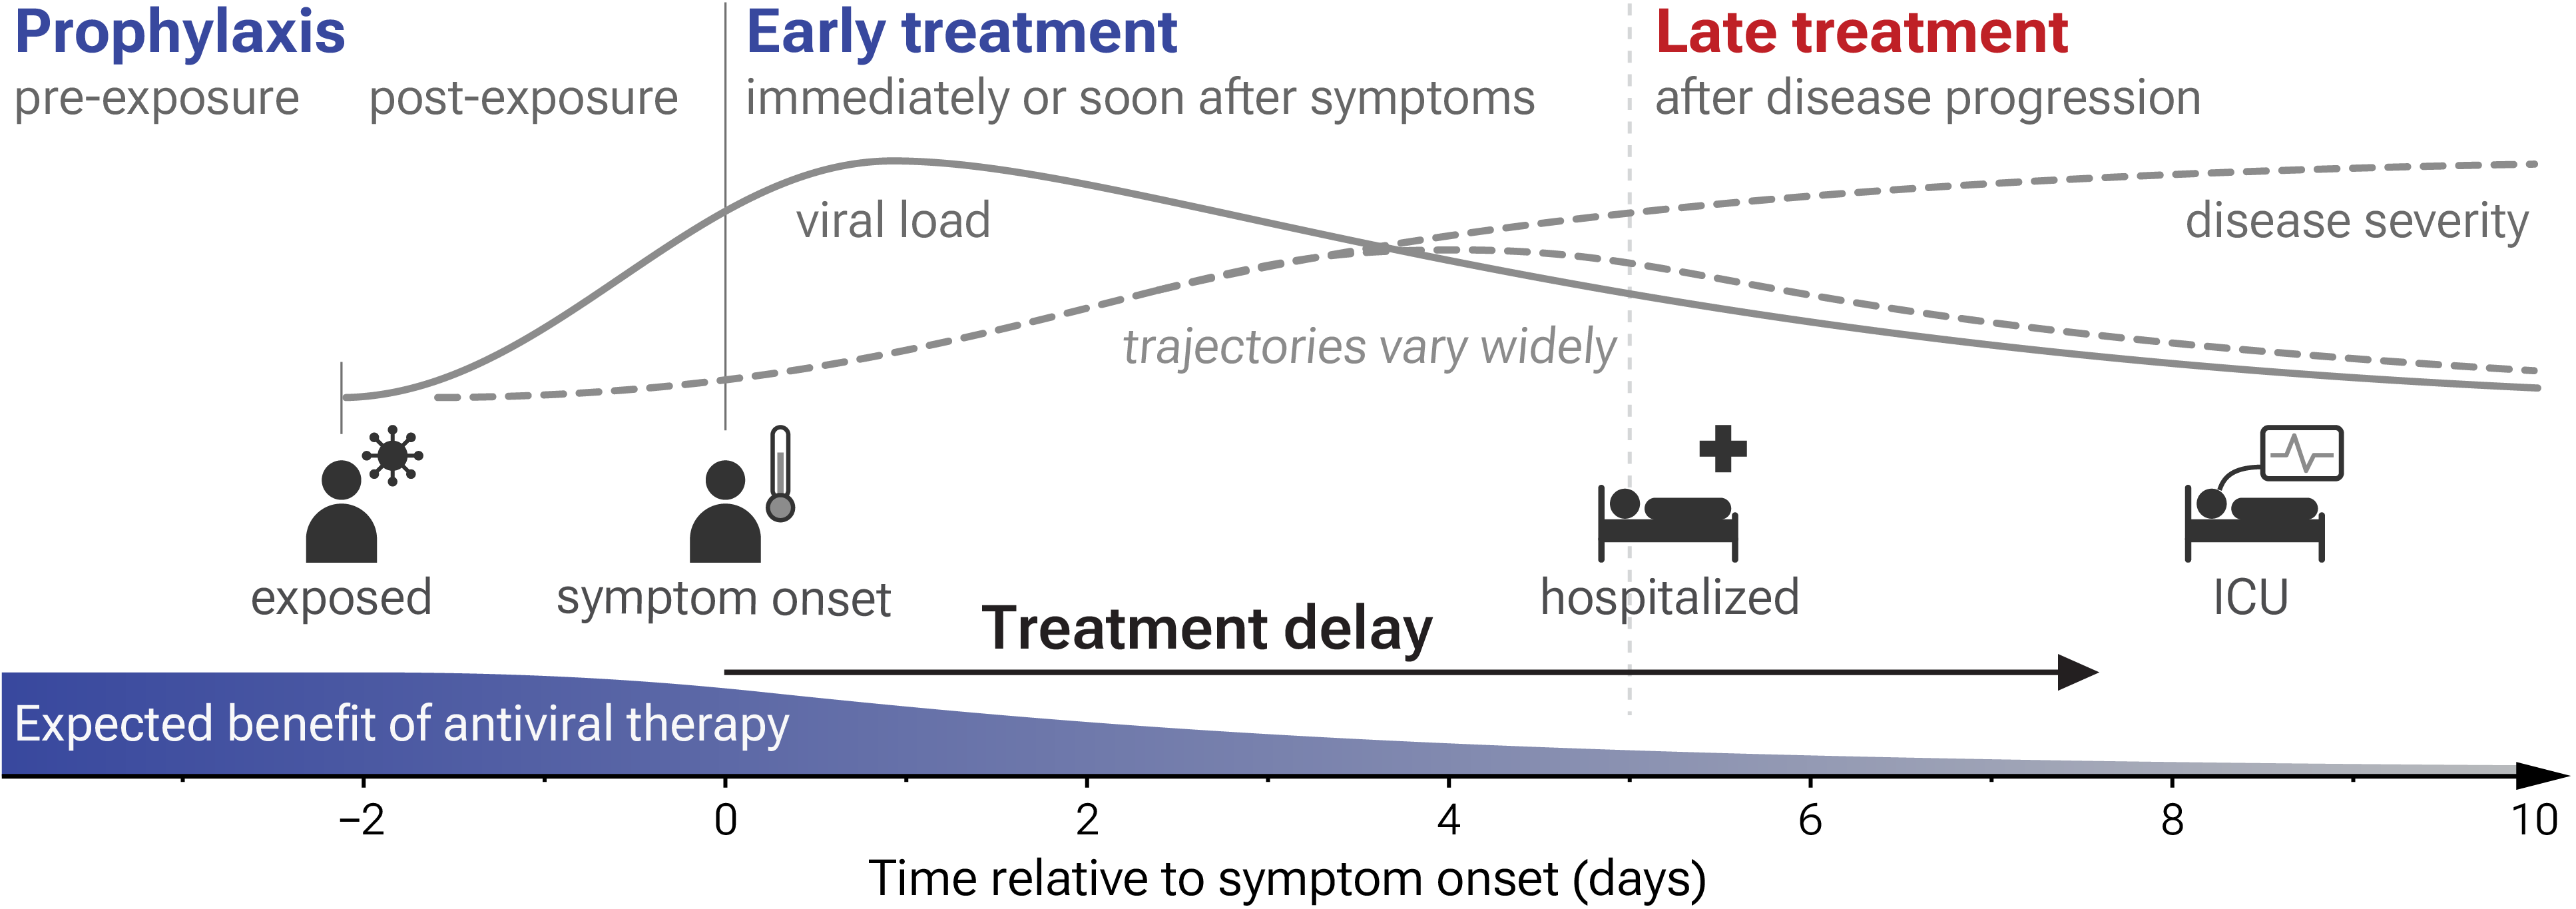
Fig. 3 shows stages of possible treatment for COVID-19. Prophylaxis refers to regularly taking medication before becoming sick, in order to prevent or minimize infection. Early treatment refers to treatment immediately or soon after symptoms appear, while late treatment refers to more delayed treatment.
Prophylaxis pre-exposure post-exposure Early treatment Late treatment Treatment delay viral load disease severity exposed symptom onset hospitalized ICU Expected benefit of antiviral therapy −2 0 2 4 6 8 10 Time relative to symptom onset (days) trajectories vary widely immediately or soon after symptoms after disease progression
Fig. 3. Treatment stages.
Vitamin A has potent antiviral activity against SARS-CoV-2 in both human cell lines and human organoids of the lower respiratory tract (active metabolite all-trans retinoic acid, ATRA)46, is predicted to bind critical host and viral proteins for SARS-CoV-2 and may compensate for gene expression changes related to SARS-CoV-247-49, may be beneficial for COVID-19 via antiviral, anti-inflammatory, and immunomodulatory effects according to network pharmacology analysis50, reduces barrier compromise caused by TNF-α in Calu-3 cells51, inhibits mouse coronavirus replication52, may stimulate innate immunity by activating interferon responses in an IRF3-dependent manner (ATRA)52, may reduce excessive inflammation induced by SARS-CoV-249, shows SARS-CoV-2 antiviral activity In Vitro49,53,54, is effective against multiple SARS-CoV-2 variants in Calu-3 cells54, and inhibits the entry and replication of SARS-CoV-2 via binding to ACE2 / 3CLpro / RdRp / helicase / 3'-to-5' exonuclease49.
5 in silico studies support the efficacy of vitamin A47-50,62.
5 in vitro studies support the efficacy of vitamin A46,49,51,53,54.
An in vivo animal study supports the efficacy of vitamin A52.
Preclinical research is an important part of the development of treatments, however results may be very different in clinical trials. Preclinical results are not used in this paper.
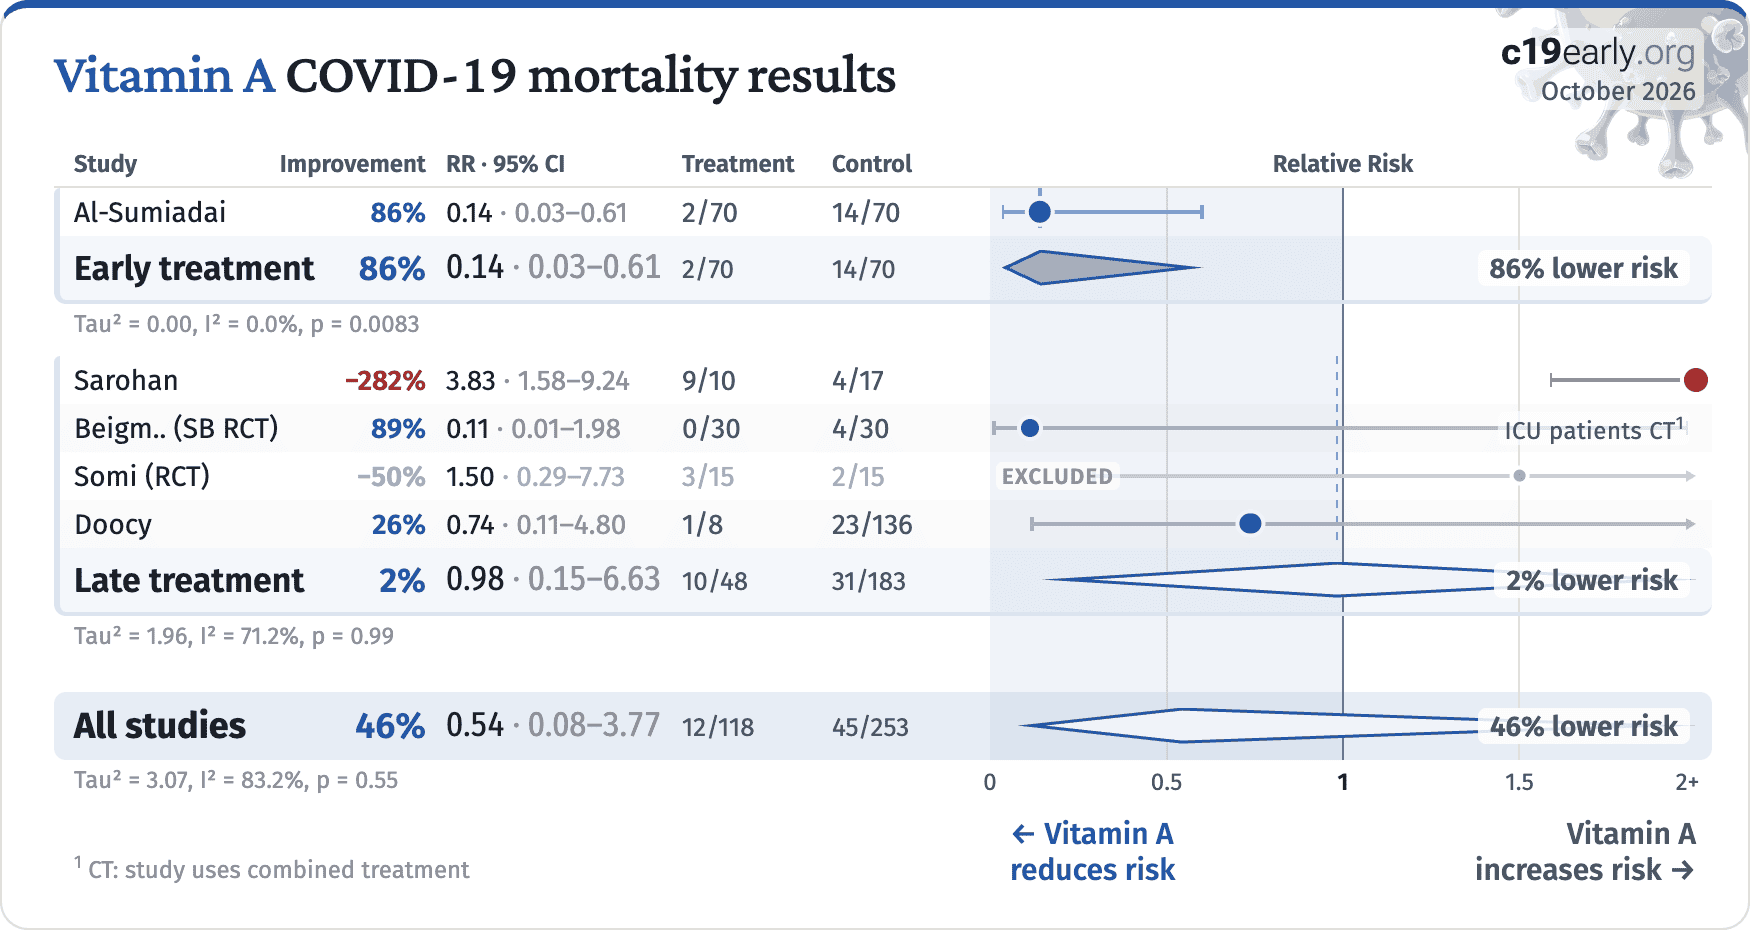
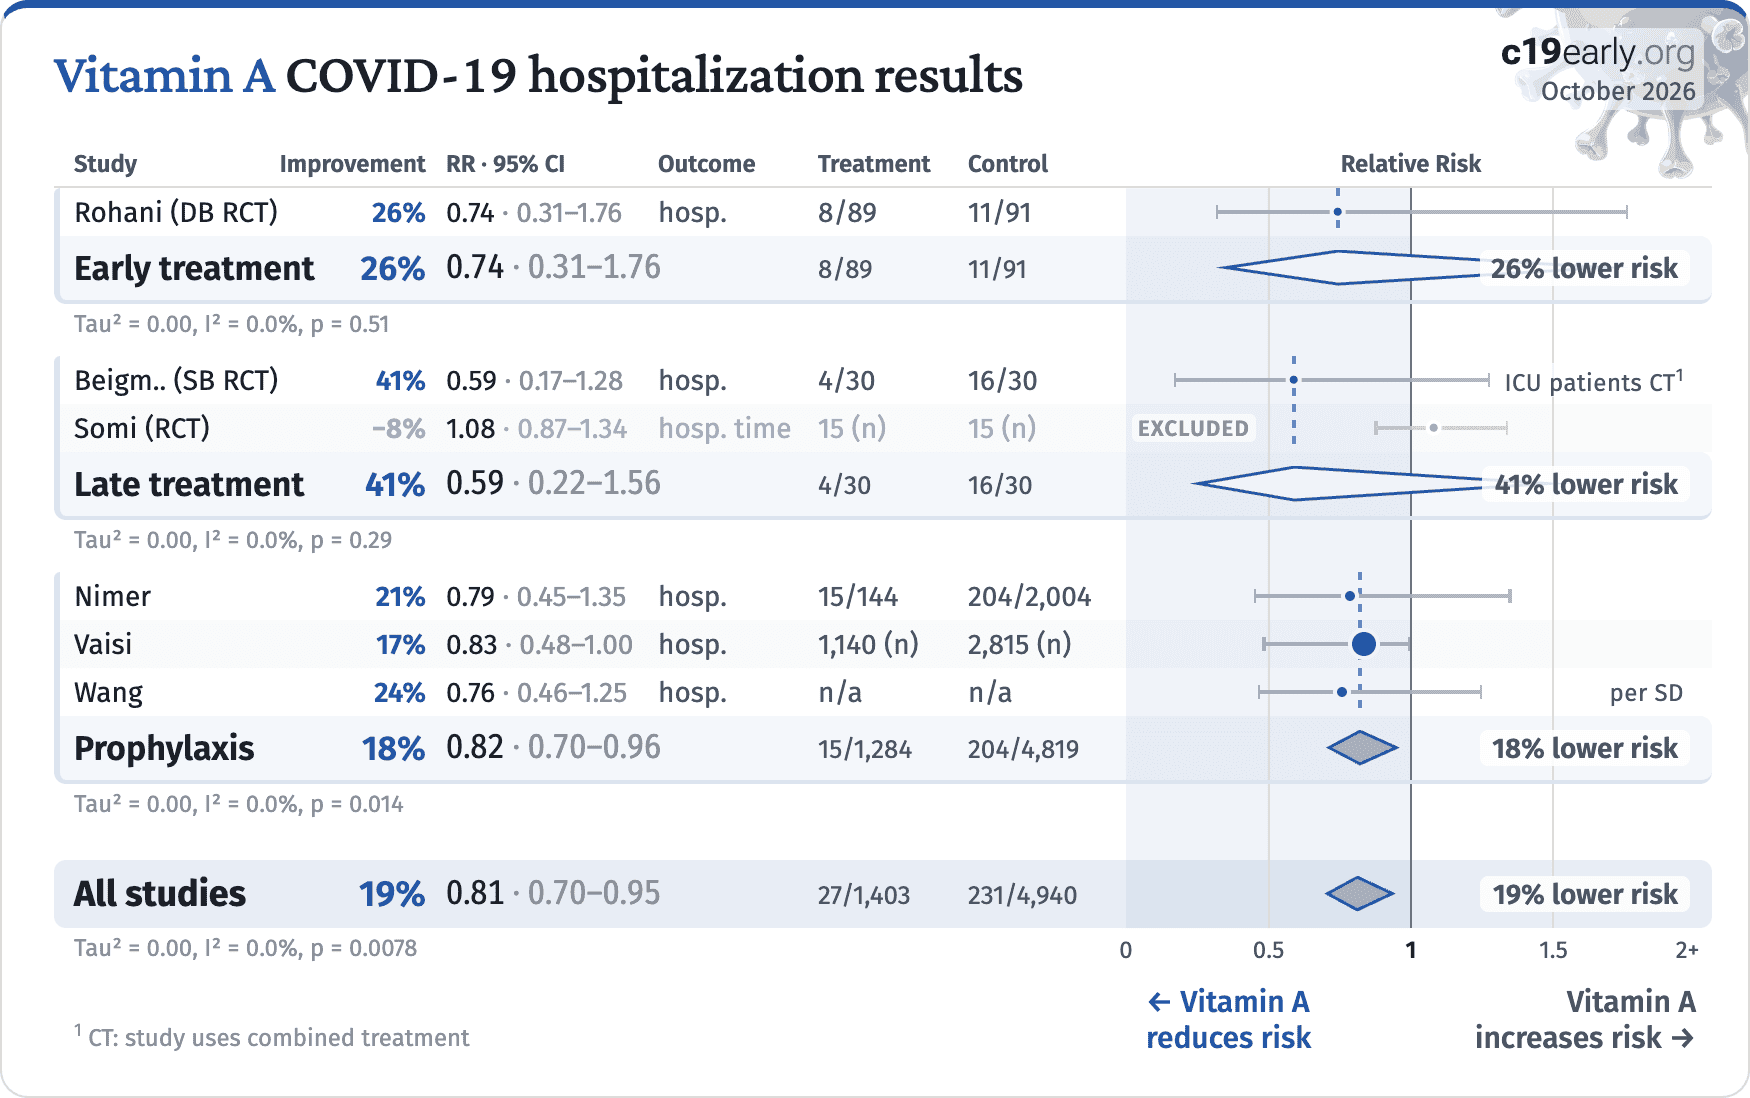
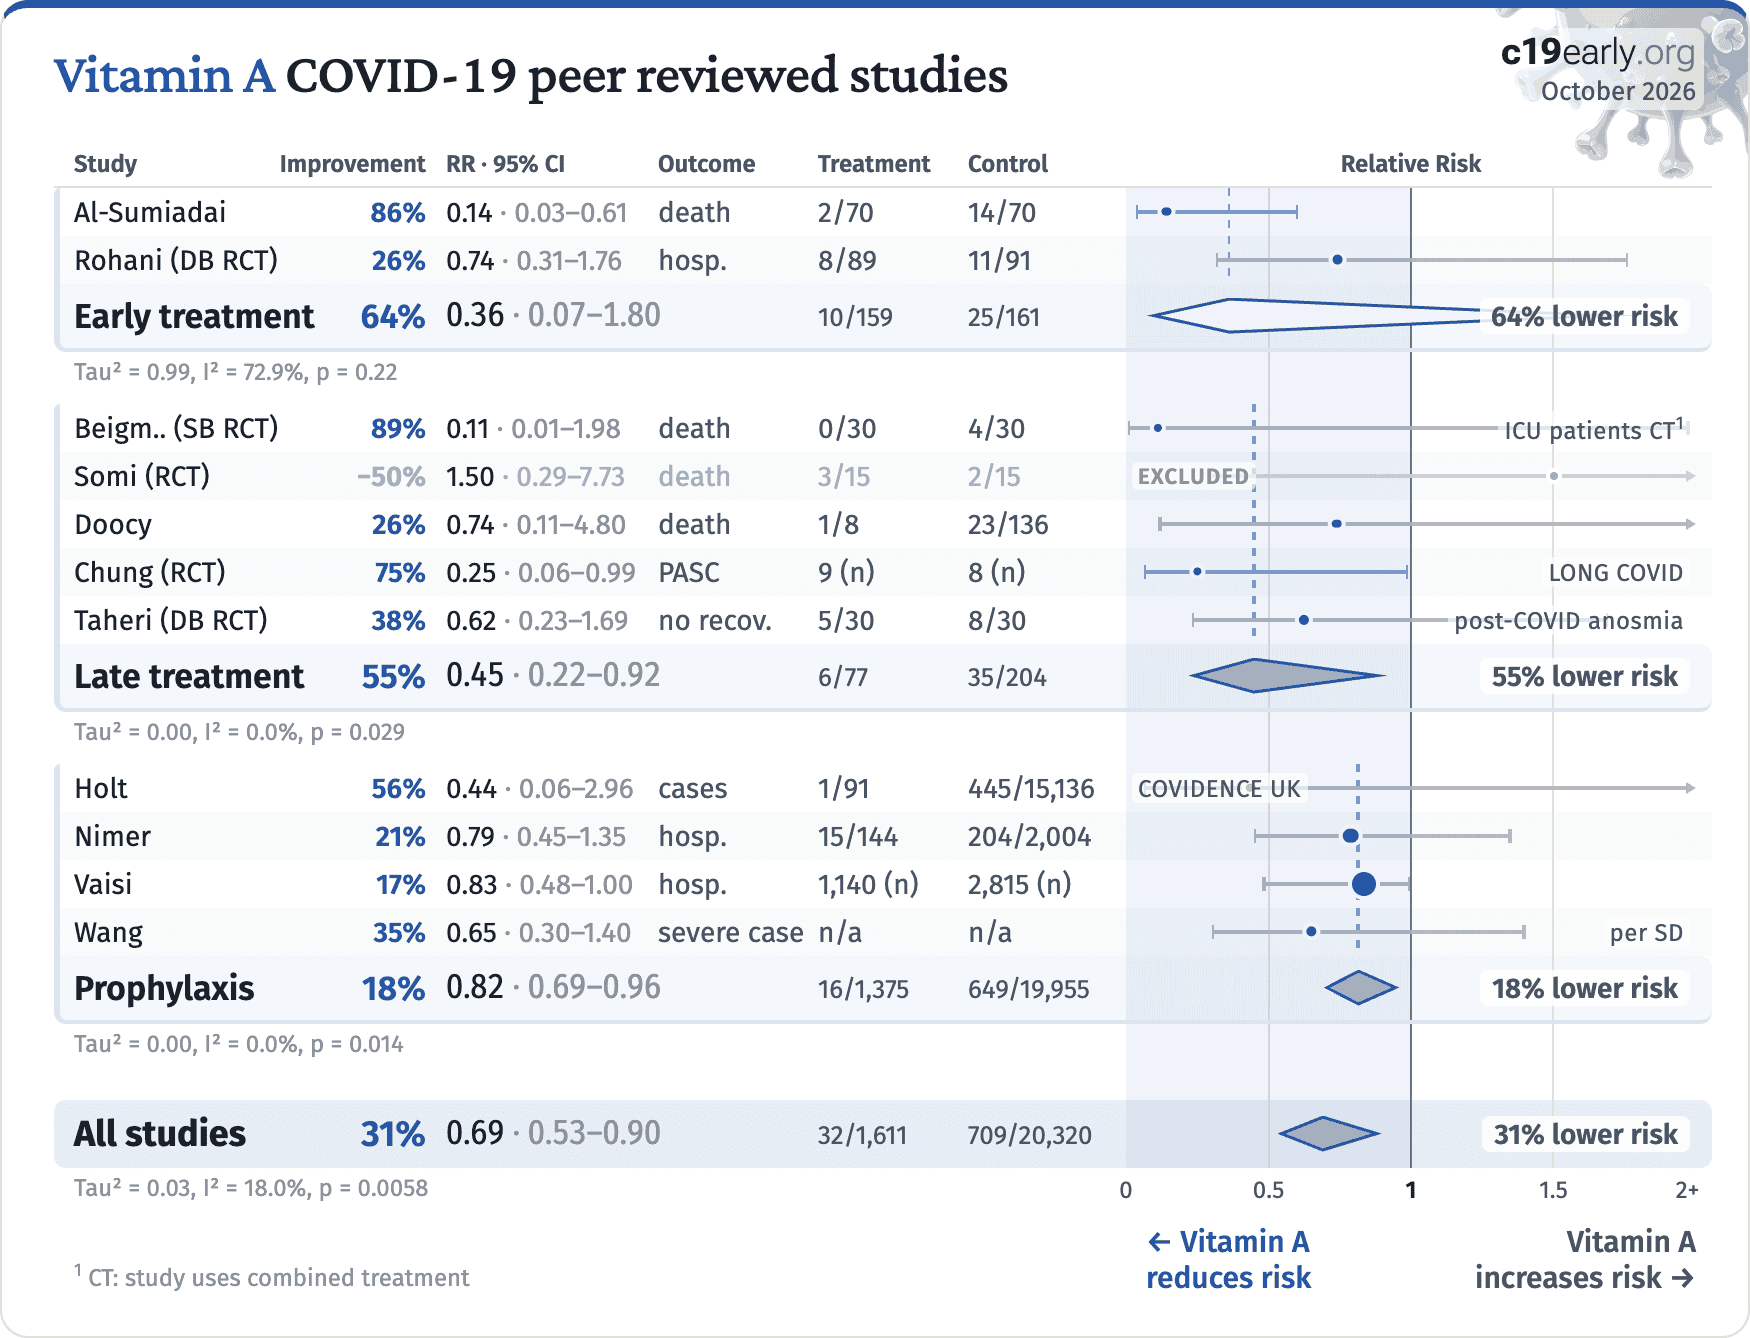
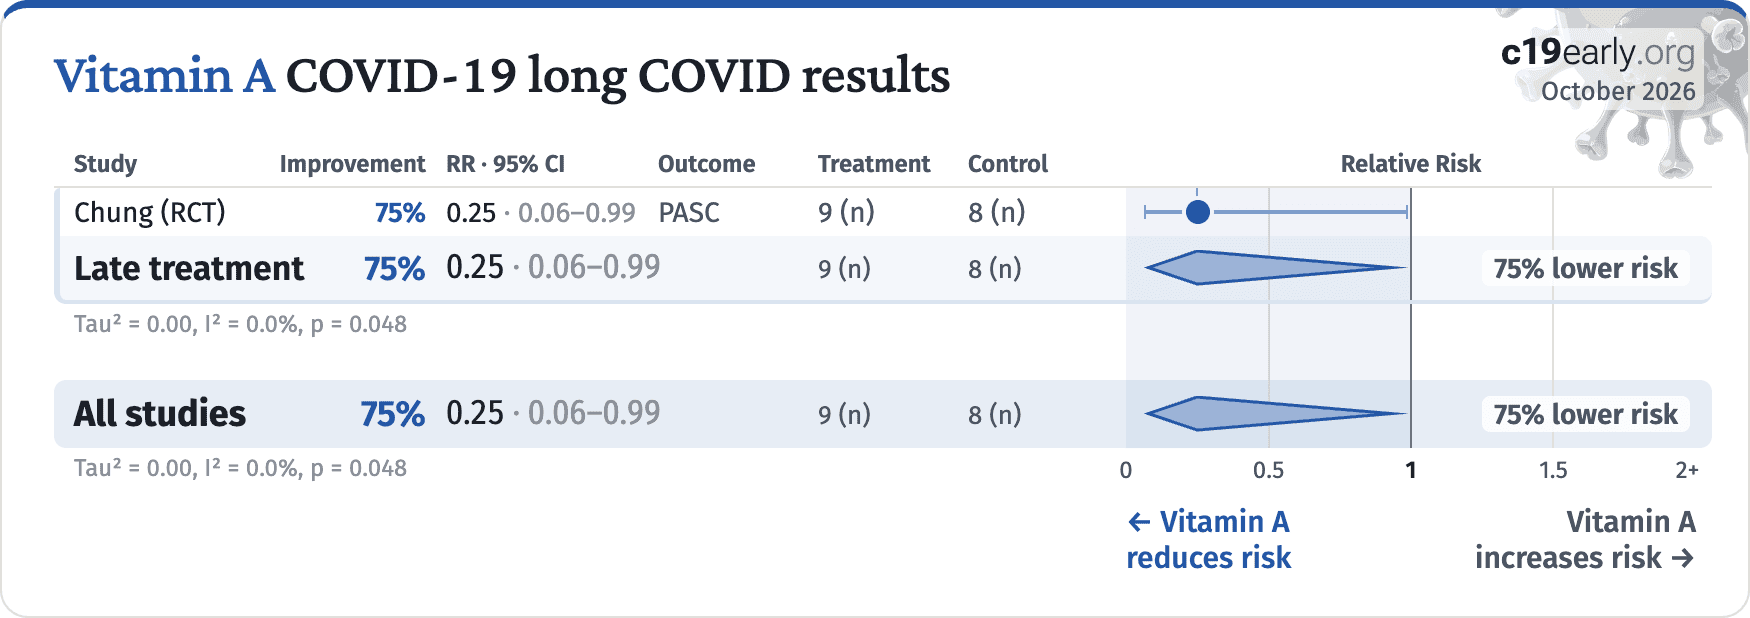
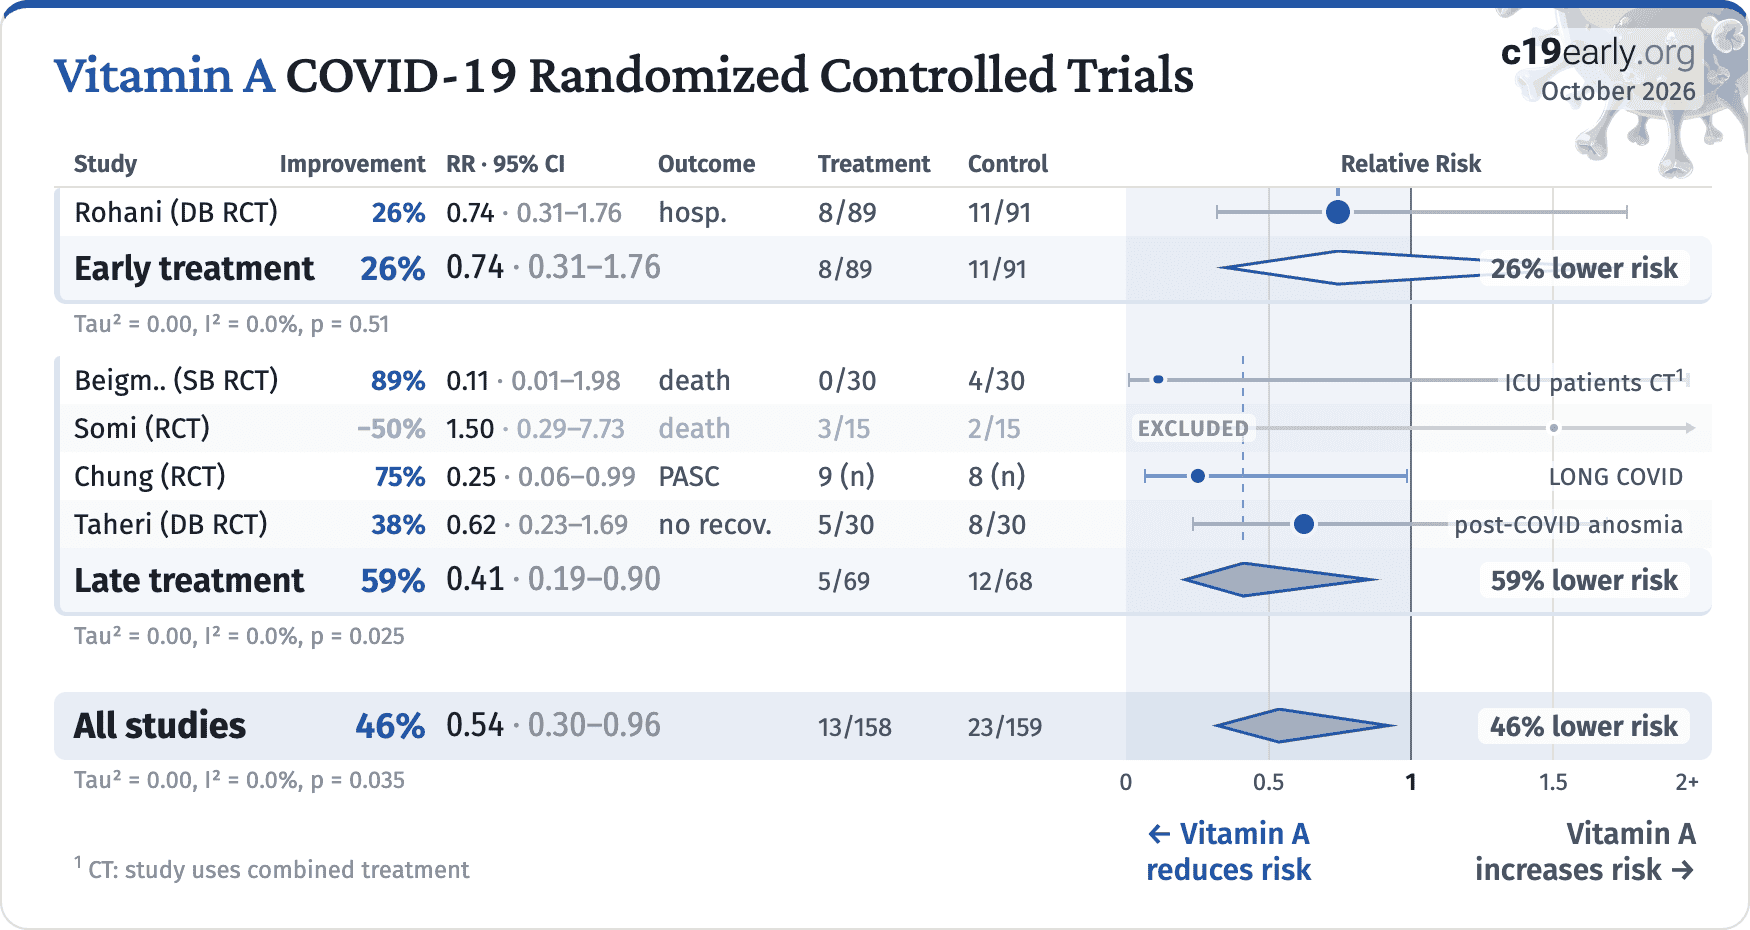
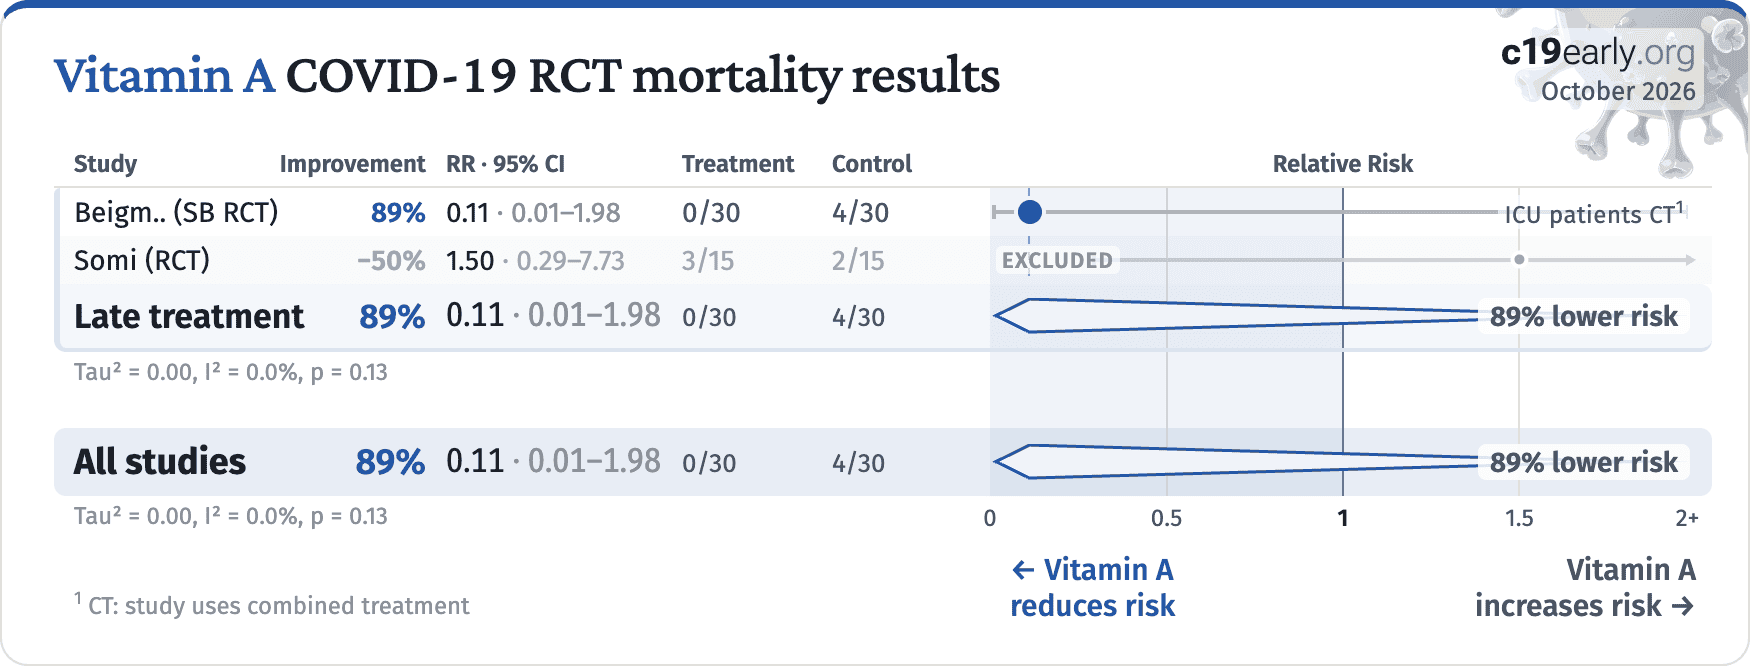
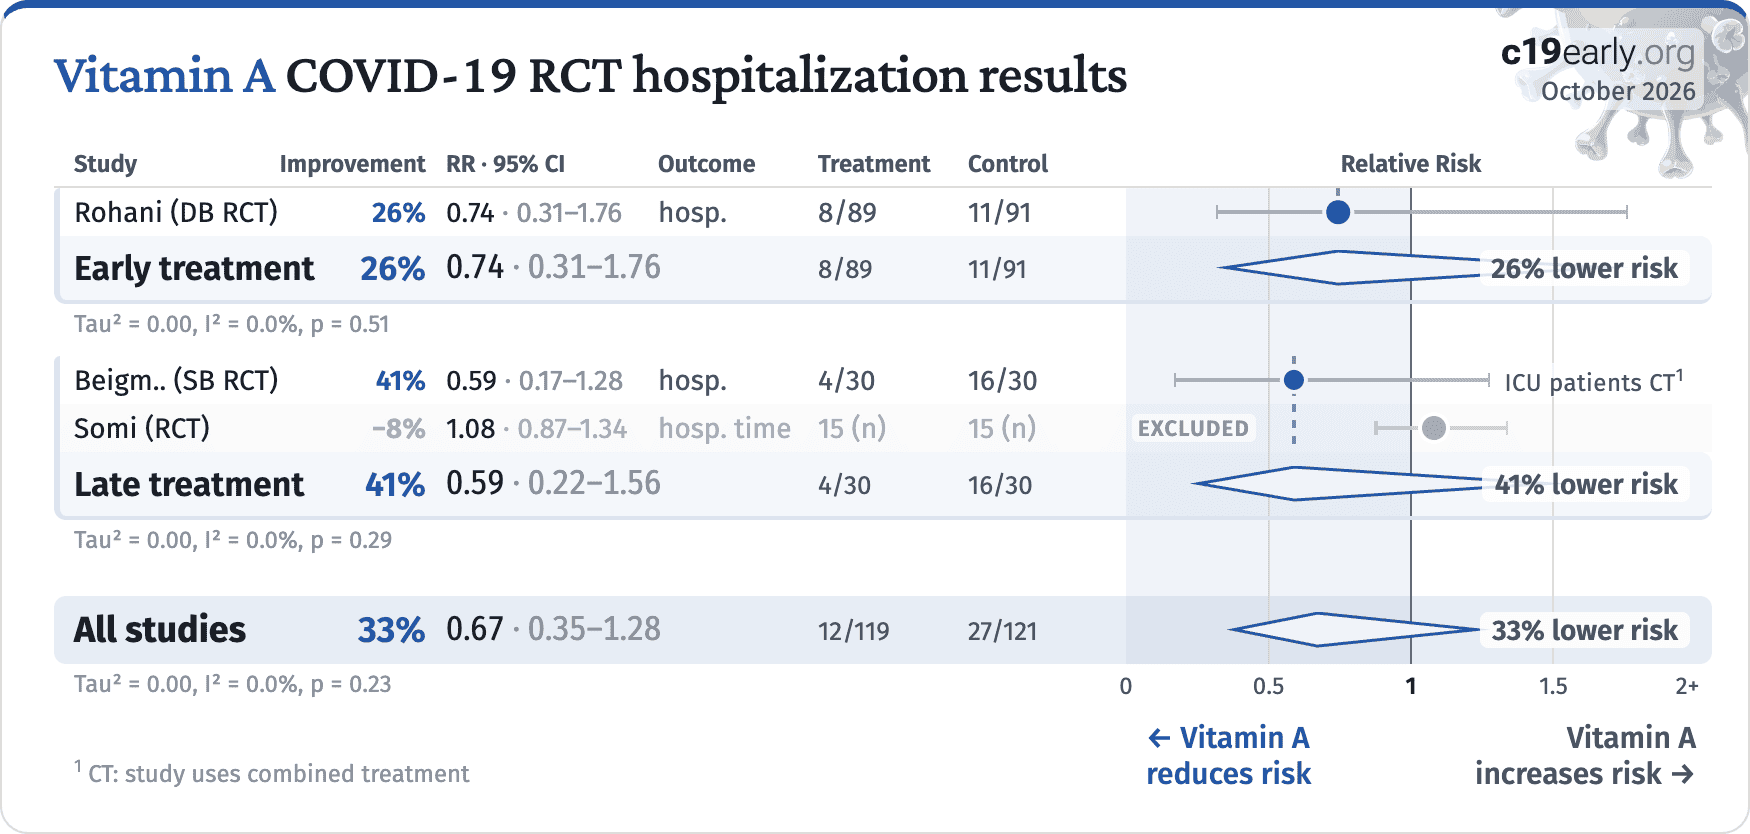
Table 1 summarizes the results for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, after exclusions, and for specific outcomes. Table 2 shows results by treatment stage. Fig. 4 plots individual results by treatment stage. Fig. 5, 6, 7, 8, 9, 10, 11, 12, and 13 show forest plots for random-effects meta-analysis of all studies with pooled effects, mortality results, hospitalization, progression, recovery, cases, sufficiency studies, peer reviewed studies, and long COVID.
Table 1. Random-effects meta-analysis for all stages combined, for Randomized Controlled Trials, for peer-reviewed studies, after exclusions, and for specific outcomes. Results show the relative risk with treatment and the 95% confidence interval. * p<0.05  ** p<0.01  *** p<0.001.
Relative Risk Studies Patients
All studies0.67 [0.51‑0.88]**1420K
After exclusions0.66 [0.53‑0.83]***106,729
Peer-reviewedPeer-reviewed0.69 [0.53‑0.90]**1020K
RCTsRCTs0.54 [0.30‑0.96]*4317
Mortality0.54 [0.08‑3.77]4371
HospitalizationHosp.0.81 [0.70‑0.95]**56,343
Recovery0.56 [0.41‑0.78]***3300
Cases0.71 [0.56‑0.88]**510K
RCT hospitalizationRCT hosp.0.67 [0.35‑1.28]2240
Table 2. Random-effects meta-analysis results by treatment stage. Results show the relative risk with treatment and the 95% confidence interval.treatment and the 95% confidence interval. * p<0.05  ** p<0.01  *** p<0.001.
Early treatment Late treatment Prophylaxis
All studies0.38 [0.14‑1.03]0.38
[0.14‑1.03]
0.69 [0.20‑2.37]0.69
[0.20‑2.37]
0.69 [0.55‑0.88]**0.69**
[0.55‑0.88]
After exclusions0.62 [0.29‑1.31]0.62
[0.29‑1.31]
0.41 [0.19‑0.90]*0.41*
[0.19‑0.90]
0.69 [0.54‑0.89]**0.69**
[0.54‑0.89]
Peer-reviewedPeer-reviewed0.36 [0.07‑1.80]0.36
[0.07‑1.80]
0.45 [0.22‑0.92]*0.45*
[0.22‑0.92]
0.82 [0.69‑0.96]*0.82*
[0.69‑0.96]
RCTsRCTs0.74 [0.31‑1.76]0.74
[0.31‑1.76]
0.41 [0.19‑0.90]*0.41*
[0.19‑0.90]
Mortality0.14 [0.03‑0.61]**0.14**
[0.03‑0.61]
0.98 [0.15‑6.63]0.98
[0.15‑6.63]
HospitalizationHosp.0.74 [0.31‑1.76]0.74
[0.31‑1.76]
0.59 [0.17‑1.28]0.59
[0.17‑1.28]
0.82 [0.70‑0.96]*0.82*
[0.70‑0.96]
Recovery0.68 [0.20‑2.33]0.68
[0.20‑2.33]
0.55 [0.40‑0.78]***0.55***
[0.40‑0.78]
Cases0.71 [0.56‑0.88]**0.71**
[0.56‑0.88]
RCT hospitalizationRCT hosp.0.74 [0.31‑1.76]0.74
[0.31‑1.76]
0.59 [0.17‑1.28]0.59
[0.17‑1.28]
Loading..
Fig. 4. Scatter plot showing the most serious outcome in all studies, and for studies within each stage. Diamonds shows the results of random-effects meta-analysis.
October 2026

Vitamin A COVID-19 studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment62%0.38 · 0.14–1.0312/20931/21162% lower risk
Tau² = 0.39, I² = 48.3%, p = 0.058
Late treatment31%0.69 · 0.20–2.3715/8739/22131% lower risk
Tau² = 1.36, I² = 74.9%, p = 0.57
Prophylaxis31%0.69 · 0.55–0.8836/1,472714/20,06731% lower risk
Tau² = 0.04, I² = 66.3%, p = 0.0025
All studies33%0.67 · 0.51–0.8863/1,768784/20,49933% lower risk
Tau² = 0.10, I² = 66.1%, p = 0.00400.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 5. Random-effects meta-analysis for all studies. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
October 2026

Vitamin A COVID-19 mortality results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Early treatment86%0.14 · 0.03–0.612/7014/7086% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0083
Late treatment2%0.98 · 0.15–6.6310/4831/1832% lower risk
Tau² = 1.96, I² = 71.2%, p = 0.99
All studies46%0.54 · 0.08–3.7712/11845/25346% lower risk
Tau² = 3.07, I² = 83.2%, p = 0.5500.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 6. Random-effects meta-analysis for mortality results.
October 2026

Vitamin A COVID-19 hospitalization results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment26%0.74 · 0.31–1.768/8911/9126% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.51
Late treatment41%0.59 · 0.22–1.564/3016/3041% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.29
Prophylaxis18%0.82 · 0.70–0.9615/1,284204/4,81918% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
All studies19%0.81 · 0.70–0.9527/1,403231/4,94019% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.007800.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 7. Random-effects meta-analysis for hospitalization.
October 2026

Vitamin A COVID-19 progression results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
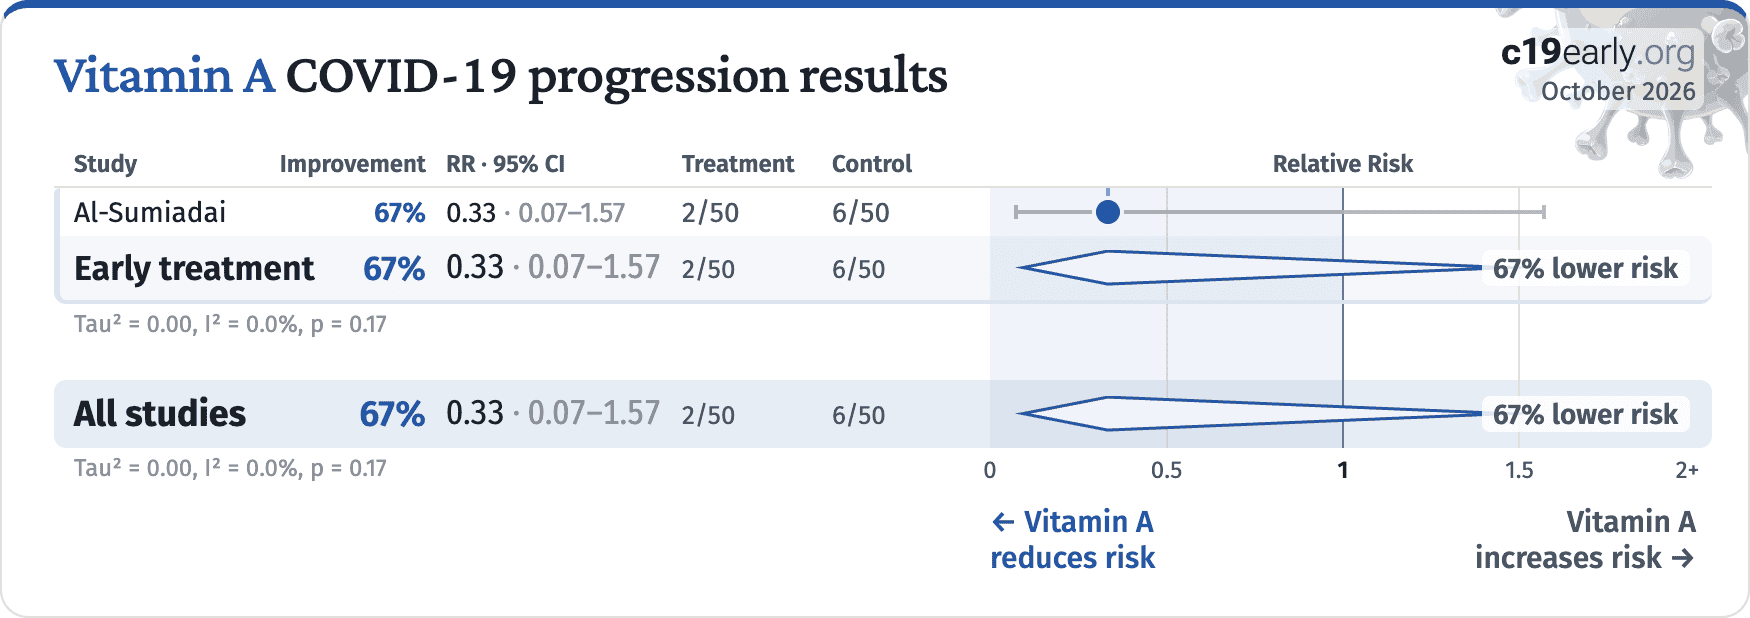
Early treatment67%0.33 · 0.07–1.572/506/5067% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.17
All studies67%0.33 · 0.07–1.572/506/5067% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.1700.511.52+
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 8. Random-effects meta-analysis for progression.
October 2026

Vitamin A COVID-19 recovery results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
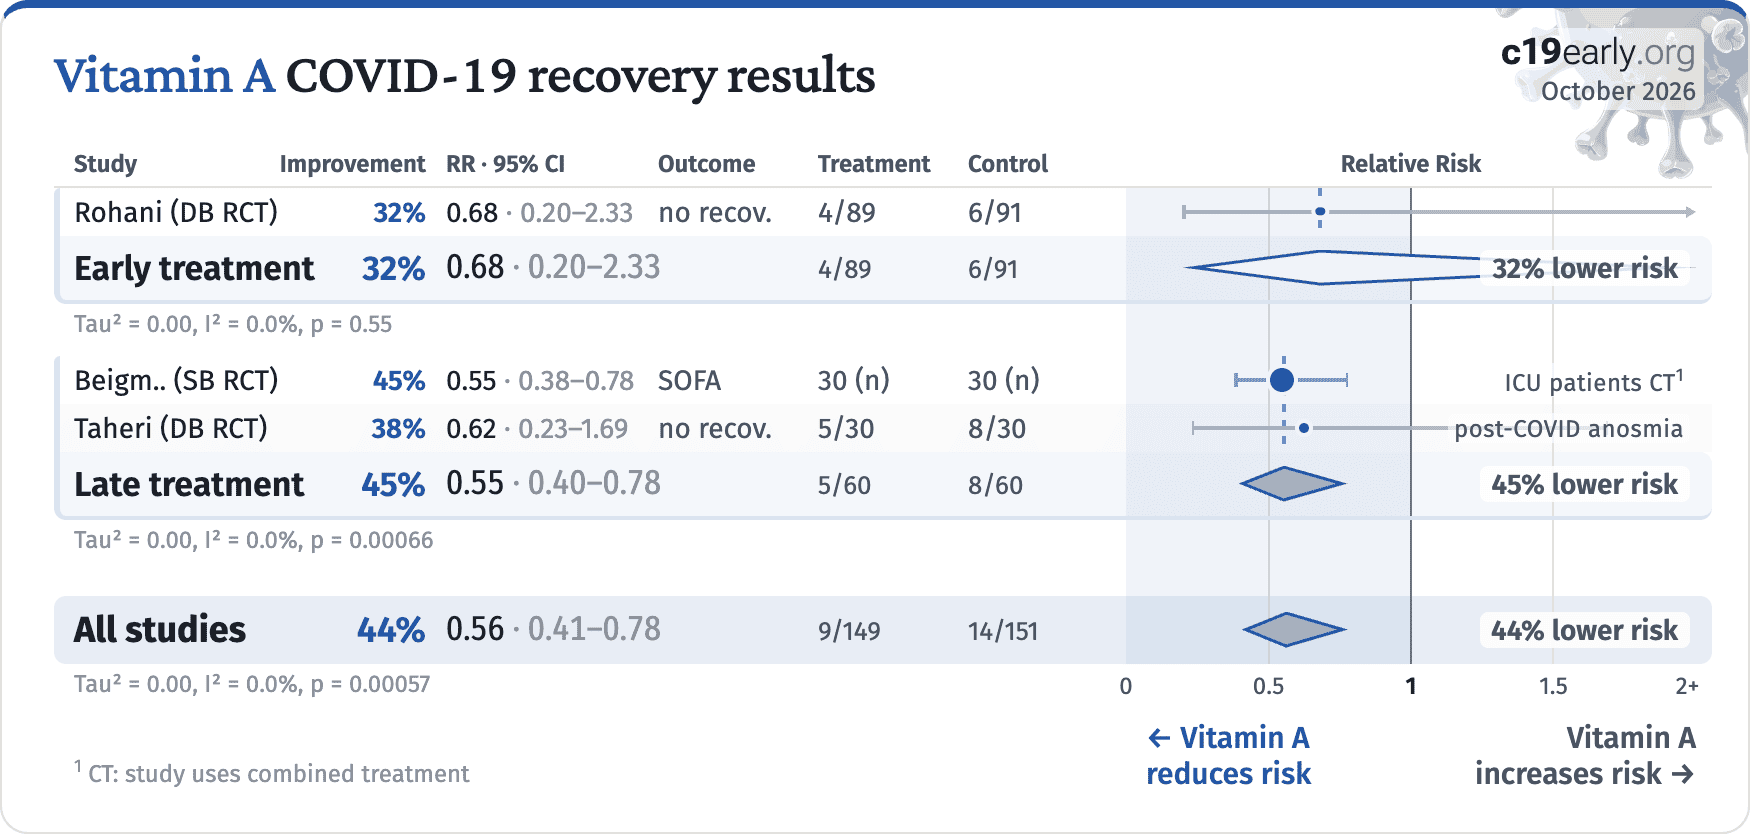
Early treatment32%0.68 · 0.20–2.334/896/9132% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.55
Late treatment45%0.55 · 0.40–0.785/608/6045% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.00066
All studies44%0.56 · 0.41–0.789/14914/15144% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.0005700.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 9. Random-effects meta-analysis for recovery.
October 2026

Vitamin A COVID-19 case results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
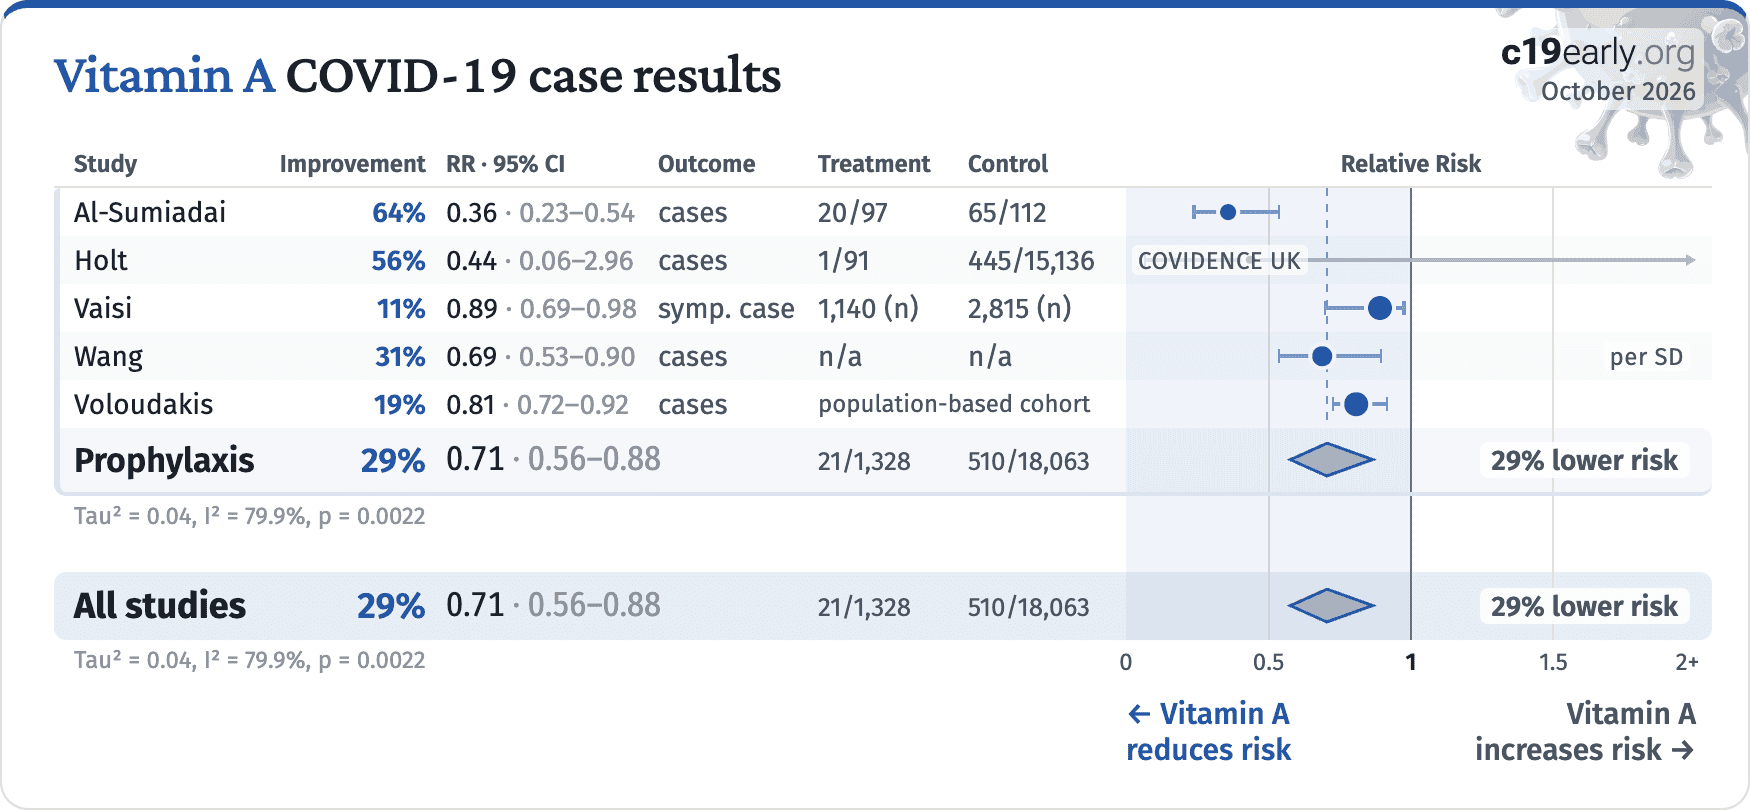
Prophylaxis29%0.71 · 0.56–0.8821/1,328510/18,06329% lower risk
Tau² = 0.04, I² = 79.9%, p = 0.0022
All studies29%0.71 · 0.56–0.8821/1,328510/18,06329% lower risk
Tau² = 0.04, I² = 79.9%, p = 0.002200.511.52+
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 10. Random-effects meta-analysis for cases.
October 2026

Vitamin A COVID-19 sufficiency studies

StudyImprovementRR · 95% CIOutcomeHigh LevelsLow LevelsRelative Risk
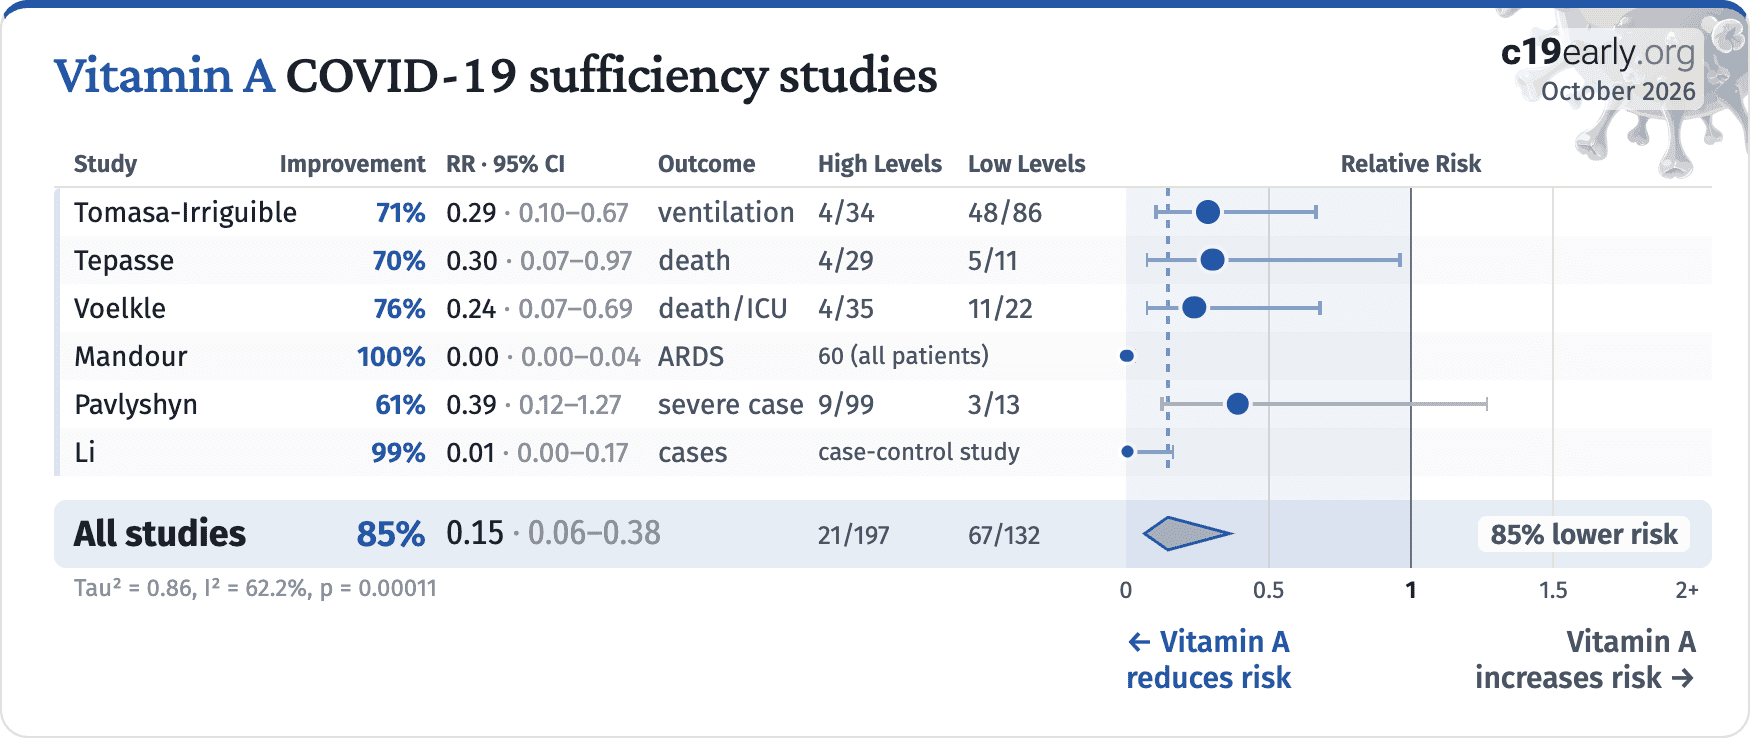
All studies85%0.15 · 0.06–0.3821/19767/13285% lower risk
Tau² = 0.86, I² = 62.2%, p = 0.0001100.511.52+
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 11. Random-effects meta-analysis for sufficiency studies. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
October 2026

Vitamin A COVID-19 peer reviewed studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment64%0.36 · 0.07–1.8010/15925/16164% lower risk
Tau² = 0.99, I² = 72.9%, p = 0.22
Late treatment55%0.45 · 0.22–0.926/7735/20455% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.029
Prophylaxis18%0.82 · 0.69–0.9616/1,375649/19,95518% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
All studies31%0.69 · 0.53–0.9032/1,611709/20,32031% lower risk
Tau² = 0.03, I² = 18.0%, p = 0.005800.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 12. Random-effects meta-analysis for peer reviewed studies. Zeraatkar et al. analyze 356 COVID-19 trials, finding no significant evidence that preprint results are inconsistent with peer-reviewed studies. They also show extremely long peer-review delays, with a median of 6 months to journal publication. A six month delay was equivalent to around 1.5 million deaths during the first two years of the pandemic. Authors recommend using preprint evidence, with appropriate checks for potential falsified data, which provides higher certainty much earlier. Davidson et al. also showed no important difference between meta-analysis results of preprints and peer-reviewed publications for COVID-19, based on 37 meta-analyses including 114 trials. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
October 2026

Vitamin A COVID-19 long COVID results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Late treatment75%0.25 · 0.06–0.999 (n)8 (n)75% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.048
All studies75%0.25 · 0.06–0.999 (n)8 (n)75% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.04800.511.52+
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 13. Random-effects meta-analysis for long COVID. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
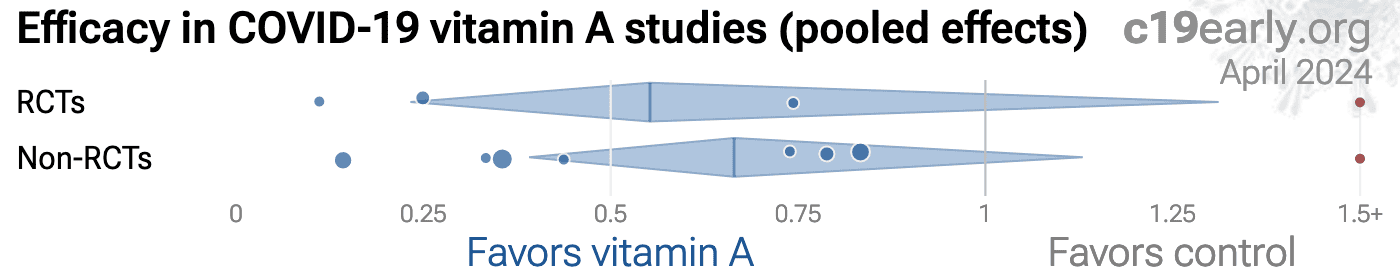
Fig. 14 shows a comparison of results for RCTs and observational studies. Random-effects meta-analysis of RCTs shows 46% improvement, compared to 29% for other studies. Fig. 15, 16, and 17 show forest plots for random-effects meta-analysis of all Randomized Controlled Trials, RCT mortality results, and RCT hospitalization results. RCT results are included in Table 1 and Table 2.
Loading..
Fig. 14. Results for RCTs and observational studies.
RCTs help to make study groups more similar and can provide a higher level of evidence, however they are subject to many biases65, and analysis of double-blind RCTs has identified extreme levels of bias66. For COVID-19, the overhead may delay treatment, dramatically compromising efficacy; they may encourage monotherapy for simplicity at the cost of efficacy which may rely on combined or synergistic effects; the participants that sign up may not reflect real world usage or the population that benefits most in terms of age, comorbidities, severity of illness, or other factors; standard of care may be compromised and unable to evolve quickly based on emerging research for new diseases; errors may be made in randomization and medication delivery; and investigators may have hidden agendas or vested interests influencing design, operation, analysis, reporting, and the potential for fraud. All of these biases have been observed with COVID-19 RCTs. There is no guarantee that a specific RCT provides a higher level of evidence.
RCTs are expensive and many RCTs are funded by pharmaceutical companies or other organizations with conflicts of interest, for example governments that previously denied treatment with the study drug. For COVID-19, this creates an incentive to show efficacy for patented commercial products, and an incentive to show a lack of efficacy for inexpensive treatments. The bias is expected to be significant, for example Als-Nielsen et al. analyzed 370 RCTs from Cochrane reviews, showing that trials funded by for-profit organizations were 5 times more likely to recommend the experimental drug compared with those funded by nonprofit organizations. Bekelman et al. and Lundh et al. show that industry-sponsored studies are more likely to be favorable. For COVID-19, some major philanthropic organizations are largely funded by investments with extreme conflicts of interest for and against specific COVID-19 interventions.
High quality RCTs for novel acute diseases are more challenging, with increased ethical issues due to the urgency of treatment, increased risk due to enrollment delays, and more difficult design with a rapidly evolving evidence base. For COVID-19, the most common site of initial infection is the upper respiratory tract. Immediate treatment is likely to be most successful and may prevent or slow progression to other parts of the body. For a non-prophylaxis RCT, it makes sense to provide treatment in advance and instruct patients to use it immediately on symptoms, just as some governments have done by providing medication kits in advance. Unfortunately, no RCTs have been done in this way. Every treatment RCT to date involves delayed treatment. Among the 227 treatments we have analyzed, 67% of RCTs involve very late treatment 5+ days after onset. No non-prophylaxis COVID-19 RCTs match the potential real-world use of early treatments. They may more accurately represent results for treatments that require visiting a medical facility, e.g., those requiring intravenous administration.
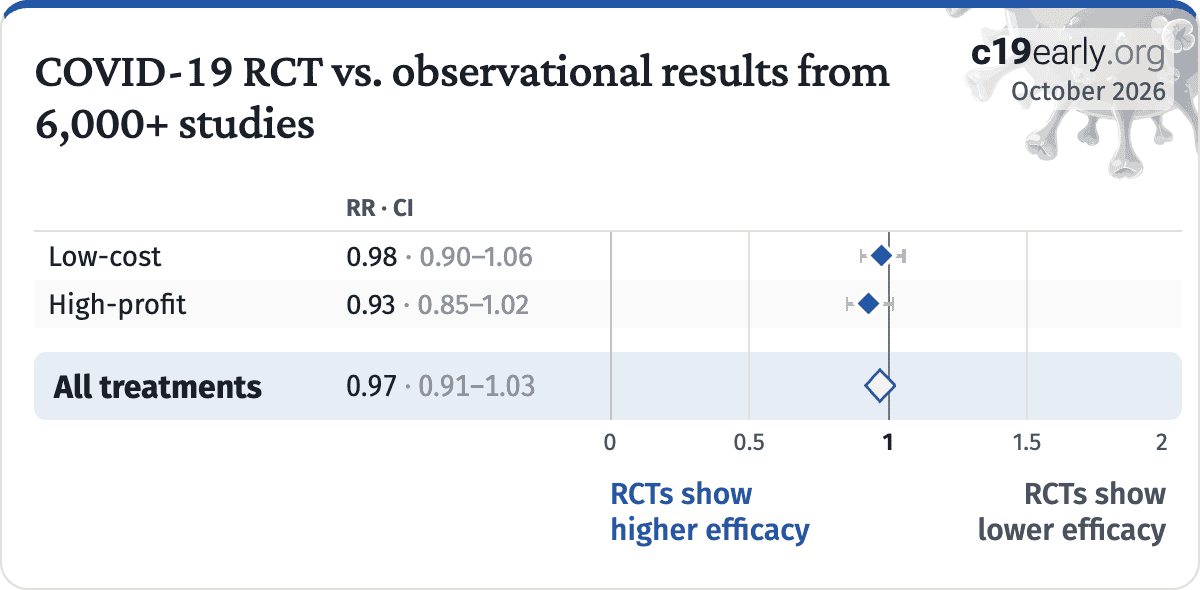
Fig. 18. For COVID-19, observational study results do not systematically differ from RCTs, RR 0.97 [0.91‑1.03] across 227 treatments70.
Evidence shows that observational studies can also provide reliable results. Concato et al. found that well-designed observational studies do not systematically overestimate the magnitude of the effects of treatment compared to RCTs. Anglemyer et al. analyzed reviews comparing RCTs to observational studies and found little evidence for significant differences in effect estimates.
We performed a similar analysis across the 227 treatments we cover, showing no significant difference in the results of RCTs compared to observational studies, RR 0.97 [0.91‑1.03]59. Similar results are found for all low-cost treatments, RR 0.98 [0.90‑1.06]. High-cost treatments show a non-significant trend towards RCTs showing greater efficacy, RR 0.93 [0.85‑1.02]. Details can be found in the supplementary data.
Lee et al. showed that only 14% of the guidelines of the Infectious Diseases Society of America were based on RCTs. Evaluation of studies relies on an understanding of the study and potential biases. Limitations in an RCT can outweigh the benefits, for example excessive dosages, excessive treatment delays, or remote survey bias may have a greater effect on results. Ethical issues may also prevent running RCTs for known effective treatments. For more on issues with RCTs see74,75.
Concato et al. report a paradoxical finding—RCT results had higher variability, and only RCTs were found to sometimes report significant results the opposite of the overall result. The same trend is seen for the most popular (most politicized) COVID-19 treatments—considering all statistically significant results reported in studies, RCTs are slightly more likely to report a result in the opposite direction. In other words, for these COVID-19 treatments and for the topics covered by Concato et al., assuming causality from a single study is more likely to result in an incorrect conclusion for RCTs.
Increased risk of inconsistent results for RCTs suggests higher prevalence of bias, which may arise due to many issues including design bias, conflicts of interest, treatment differences by physicians aware of allocation, attrition bias, ascertainment bias, randomization failures, errors, or fraud.
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. Of these, 54% have been confirmed in RCTs, with a mean delay of 7.8 months (62% with 8.7 months delay for low-cost treatments). The remaining treatments either have no RCTs, or the point estimate is consistent.
Neither observational studies nor RCTs prove causation—any study can be flawed or fraudulent. We need much more, for example a combination of results from many independent teams, detailed understanding of each study, knowledge of conflicts/team reliability, dose-response relationships, delay-response relationships, logical results across outcomes, or details consistent with preclinical expectations.
All studies must be evaluated individually. RCTs for a given medication and disease may be more reliable, however they may also be less reliable. For off-patent medications, very high conflict of interest trials may be more likely to be RCTs, and more likely to be large trials that dominate meta-analyses.
October 2026

Vitamin A COVID-19 Randomized Controlled Trials

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment26%0.74 · 0.31–1.768/8911/9126% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.51
Late treatment59%0.41 · 0.19–0.905/6912/6859% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.025
All studies46%0.54 · 0.30–0.9613/15823/15946% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.03500.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 15. Random-effects meta-analysis for all Randomized Controlled Trials. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
October 2026

Vitamin A COVID-19 RCT mortality results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Late treatment89%0.11 · 0.01–1.980/304/3089% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.13
All studies89%0.11 · 0.01–1.980/304/3089% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.1300.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 16. Random-effects meta-analysis for RCT mortality results.
October 2026

Vitamin A COVID-19 RCT hospitalization results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment26%0.74 · 0.31–1.768/8911/9126% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.51
Late treatment41%0.59 · 0.22–1.564/3016/3041% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.29
All studies33%0.67 · 0.35–1.2812/11927/12133% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.2300.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 17. Random-effects meta-analysis for RCT hospitalization results.
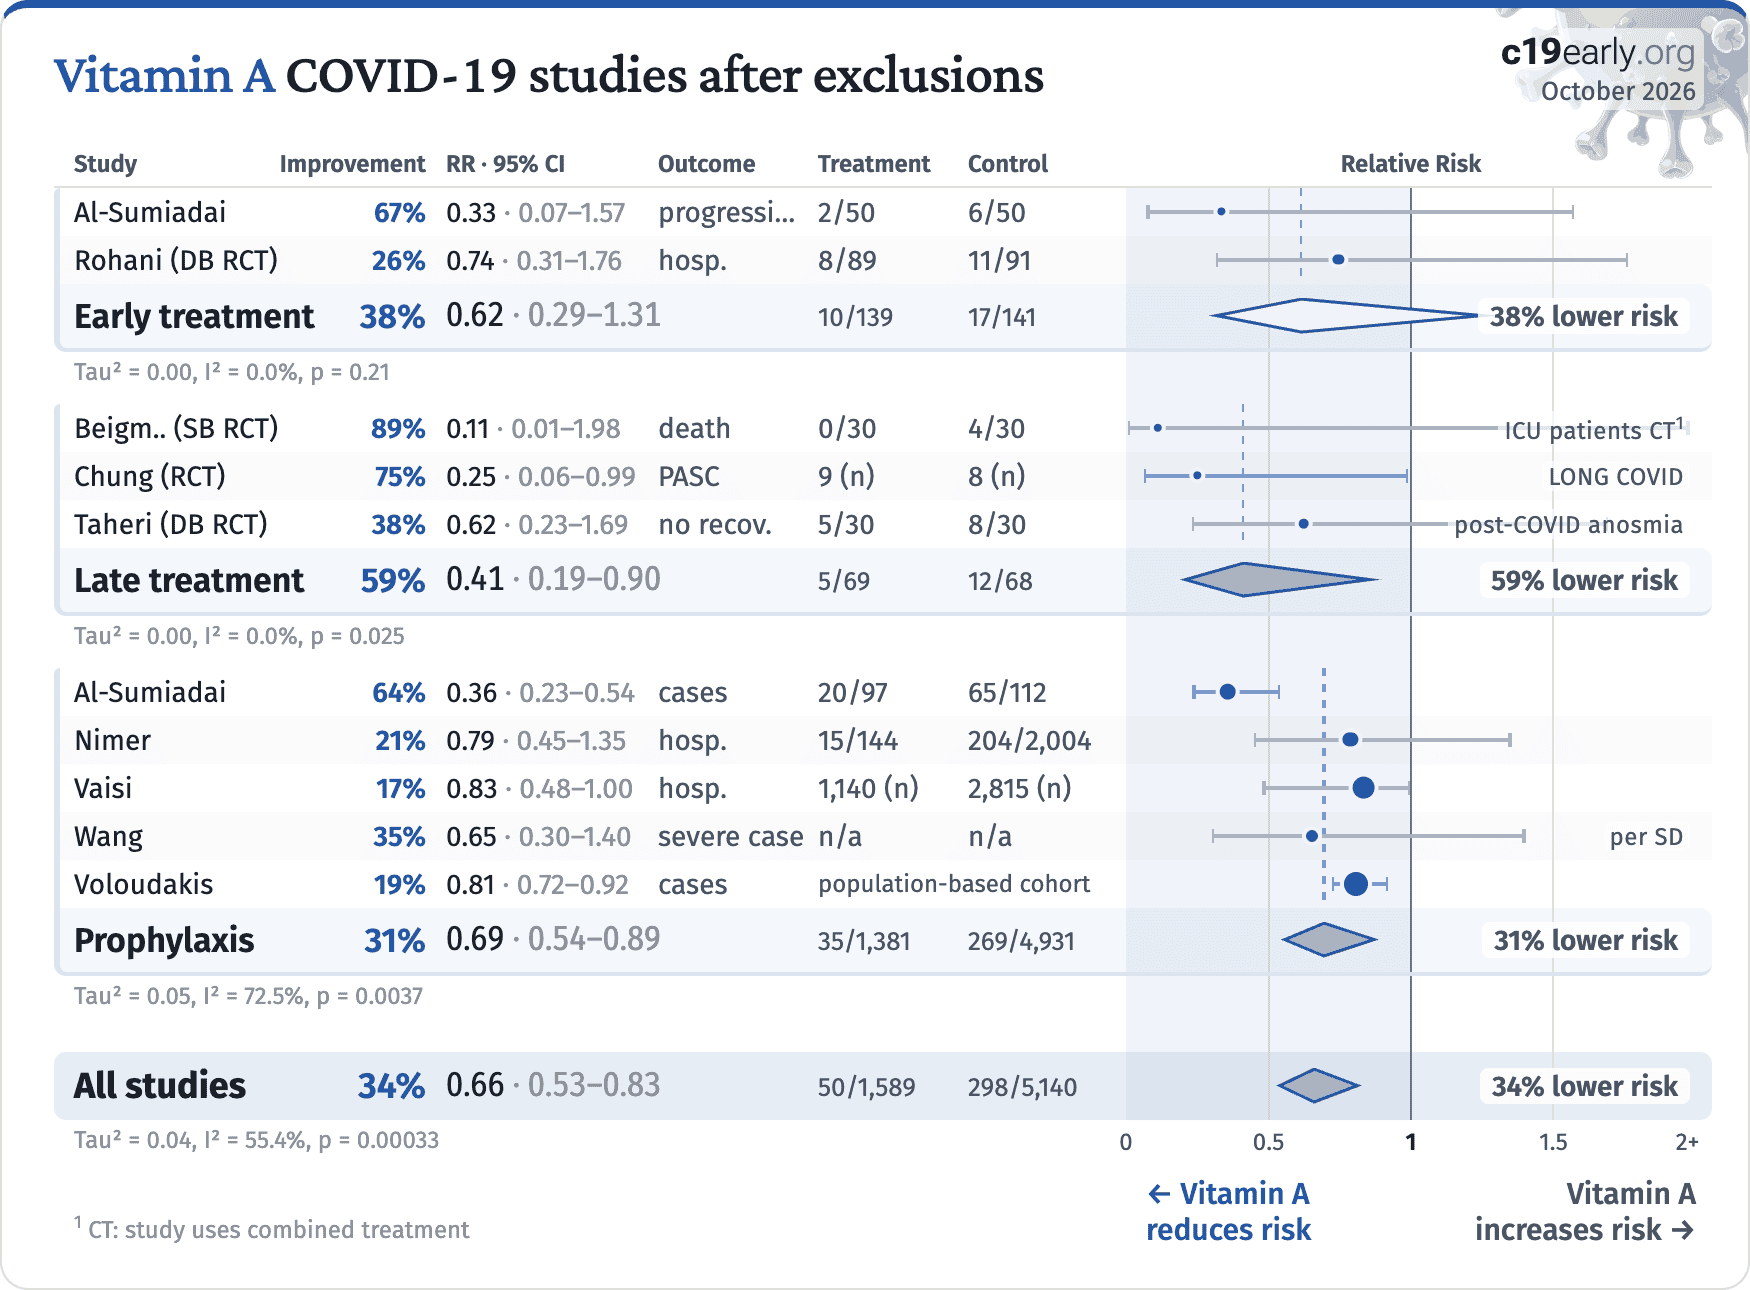
To avoid bias in the selection of studies, we analyze all non-retracted studies. Here we show the results after excluding studies with major issues likely to alter results, non-standard studies, and studies where very minimal detail is currently available. Our bias evaluation is based on analysis of each study and identifying when there is a significant chance that limitations will substantially change the outcome of the study. We believe this can be more valuable than checklist-based approaches such as Cochrane GRADE, which can be easily influenced by potential bias, may ignore or underemphasize serious issues not captured in the checklists, and may overemphasize issues unlikely to alter outcomes in specific cases (for example certain specifics of randomization with a very large effect size and well-matched baseline characteristics).
The studies excluded are as below. Fig. 19 shows a forest plot for random-effects meta-analysis of all studies after exclusions.
Al-Sumiadai, minimal details of groups provided.
Doocy, unadjusted results with no group details.
Holt, significant unadjusted confounding possible.
Sarohan, unadjusted results with no group details, comments suggest significant group differences and confounding.
October 2026

Vitamin A COVID-19 studies after exclusions

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Early treatment38%0.62 · 0.29–1.3110/13917/14138% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.21
Late treatment59%0.41 · 0.19–0.905/6912/6859% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.025
Prophylaxis31%0.69 · 0.54–0.8935/1,381269/4,93131% lower risk
Tau² = 0.05, I² = 72.5%, p = 0.0037
All studies34%0.66 · 0.53–0.8350/1,589298/5,14034% lower risk
Tau² = 0.04, I² = 55.4%, p = 0.0003300.511.52+
1 CT: study uses combined treatment
Rotate screen for more detailsIncrease width for more details
← Vitamin A
reduces risk
Vitamin A
increases risk →
Fig. 19. Random-effects meta-analysis for all studies after exclusions. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
Low-cost treatments were subject to bias and censorship during the pandemic. Scientific bias is seen in the design, analysis, presentation, and selective reporting of studies, which often favored negative results. A similar bias is seen in the media coverage for low-cost treatments. While broadly seen, bias was particularly notable for ivermectin and hydroxychloroquine, e.g., Scott Alexander noted that "if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."55.
We analyze media coverage for the 227 treatments we cover using Altmetric80 and PlumX Metrics81. Altmetric covers ~14,000 news outlets82 and PlumX covers ~55,000 news sources83. The two services are complementary with coverage of different news sources and different methods for identifying articles not containing a DOI. We consider studies to have received significant media coverage if they were covered by at least 100 articles in either Altmetric of PlumX83,84. The most widespread study was covered by 1,047 outlets. Studies covered by major syndicated sources shows hundreds of news articles, while studies covered by few outlets typically appear in niche medical news sources or press releases. Fig. 20 and 21 show bias towards negative results for low-cost treatments, in contrast to the opposite bias for high-profit treatments.
The media bias may result in widespread incorrect perceptions on the relative efficacy of high-profit and low-cost treatments. The impact is significant—increased cost limits the use of high-profit treatments and treatment equity. High-profit treatments were also more difficult to access, especially for earlier treatment which improves efficacy and minimizes community transmission.
October 2026

Media coverage of low-cost COVID‑19 treatments

Media covered only 0.8% of studies showing significantly lower COVID-19 risk

Only 5 positive studies were covered

0.8%

34 negative studies were covered

4%
5.4×
Negative bias for low-cost treatments
negative studies were 5.4 times more likely to be covered
Fig. 20. Mainstream media coverage was biased against positive results for low-cost treatments. When restricting to RCTs, the bias was even larger, with negative RCTs 6.9× more likely to be covered.
October 2026

Media coverage of high-profit COVID‑19 treatments

Media was 3.8× more likely to cover positive studies

19 positive studies were covered

11%

Only 6 negative studies were covered

3%
3.8×
Positive bias for high-profit treatments
positive studies were 3.8 times more likely to be covered
Fig. 21. For high-profit treatments, mainstream media coverage was biased towards positive results. When restricting to RCTs, the bias was even larger, with positive RCTs 12.0× more likely to be covered.
A combination of factors may have led to the very low media coverage of low-cost treatments:
•
Politicization
led to a media environment where coverage was often framed to support a political narrative rather than to provide objective scientific information. As Scott Alexander said:
"if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."
There was strong social pressure to discredit low-cost treatments.
•
Censorship
of information conflicting with selected authorities. For example, individuals and organizations presenting conflicting science were often shadowbanned or completely banned on Twitter and YouTube if the science they were reporting conflicted with the opinions of specific authorities selected by those companies, including when the authorities had not even reviewed the scientific results in question.
•
FDA requires "no adequate, approved, and available alternatives"
in order to grant an EUA for novel high-profit interventions, creating an incentive for authorities to ignore or downplay existing low-cost treatments.
•
Regulatory capture
biases authorities towards high-profit interventions.
•
Authorities ignored most evidence for low-cost treatments
, for example the NIH references only 2% of studies in delayed, rarely-updated, biased commentaries with no quantitive analysis.
•
Media coverage of science is often not very accurate
, e.g., misunderstanding confounding issues. For example the media widely considered the RECOVERY HCQ RCT to be conclusive on efficacy, but very late treatment of late-stage patients (mostly on oxygen already) with an excessive toxic dose (shown dangerous in a dose comparison RCT) provides no information on the recommended early/prophylactic treatment. With difficulting in understanding basic confounders like treatment delay and dose, the media may favor deferring to authorities. Many studies for low-cost treatments require greater expertise to analyze.
•
Substantial funding from pharmaceutical advertising
biases editorial decisions towards high-profit interventions.
•
PR power
- companies/teams with strong PR presence are favored in the media, which correlates with high-profit and high conflict of interest studies.
•
The media was very negative in general
, inflating risk, and elevating fear and anxiety. A negative bias may improve ratings and revenue, increasing motivation to continue watching coverage.
26 low-cost treatments were approved in one or more countries, yet many countries approved no low-cost treatments. The countries that did adopt low-cost treatments analyzed the evidence early and made timely approvals. With few exceptions, authorities did not change their initial views, regardless of how much evidence accumulated showing either efficacy or harm. Why?
The harms of smoking here hidden for 25 yearsC. Authorities did not analyze the data in real-time, failing to act when harm was known. Widespread acknowledgement of harm came only after attempts by two new surgeon generals, along with pressure from health advocates and a new president, and a review of 7,000 studies.
Similarly for COVID-19, most authorities and experts did not proactively analyze data in real-time. This guarantees delayed recognition of efficacy or harm, by which time moral, legal, career, and reputational liabilities strongly disincentivize any admission of error. Claims of no efficacy (for effective treatments) or safety (for harmful treatments) were often made prior to strong data being available. Correction would require admitting to errors that increased mortality, which is unlikely with the same generation of officials.
Analysis of potential treatments was rarely done, and when done these were typically minimal efforts. For example, NIH reviews were highly delayed, cover only a tiny fraction of treatments, reference only 2% of studies for the treatments covered, and include no quantitative analysis. They appear as rarely updated side projects from external panels implicitly tasked with justifying prior failures. As with smoking, the thousands of studies could (and should) have been analyzed and acted on in real-time.
A key structural improvement, applicable to all current and future diseases, is for authorities to implement real-time proactive analysis of clinical evidence. This does not remove all bias, but does make it possible to act on evidence, whereas delayed action may be unlikely due to moral, legal, career, and reputational liabilities.
c19early.org
Delayed public health acknowledgments
Official acknowledgment of efficacy or harm is often delayed—legal, career, and status risks disincentivize admission of error.
Evidence Official Acknowledgment Approx. Delay
Citrus Fruit (vitamin C) for Scurvy (effectiveness) 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. 48 years
Handwashing (lower mortality) 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). ~20+ years
Helicobacter pylori (bacteria causes ulcers) 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. ~12 years
Asbestos (causes asbestosis & cancer) 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. ~47 years
Leaded Gasoline (neurotoxicity) ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. ~49 years
Harms of Smoking (causes lung cancer) 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. 25 years
Heterogeneity in COVID-19 studies arises from many factors including:
The time between infection or the onset of symptoms and treatment may critically affect how well a treatment works. For example an antiviral may be very effective when used early but may not be effective in late stage disease, and may even be harmful. Oseltamivir, for example, is generally only considered effective for influenza when used within 0-36 or 0-48 hours85,86. Baloxavir marboxil studies for influenza also show that treatment delay is critical — Ikematsu et al. report an 86% reduction in cases for post-exposure prophylaxis, Hayden et al. show a 33 hour reduction in the time to alleviation of symptoms for treatment within 24 hours and a reduction of 13 hours for treatment within 24-48 hours, and Kumar et al. report only 2.5 hours improvement for inpatient treatment.
Table 3. Studies of baloxavir marboxil for influenza show that early treatment is more effective.
Treatment delayResult
Post-exposure prophylaxis86% fewer cases87
<24 hours-33 hours symptoms88
24-48 hours-13 hours symptoms88
Inpatients-2.5 hours to improvement89
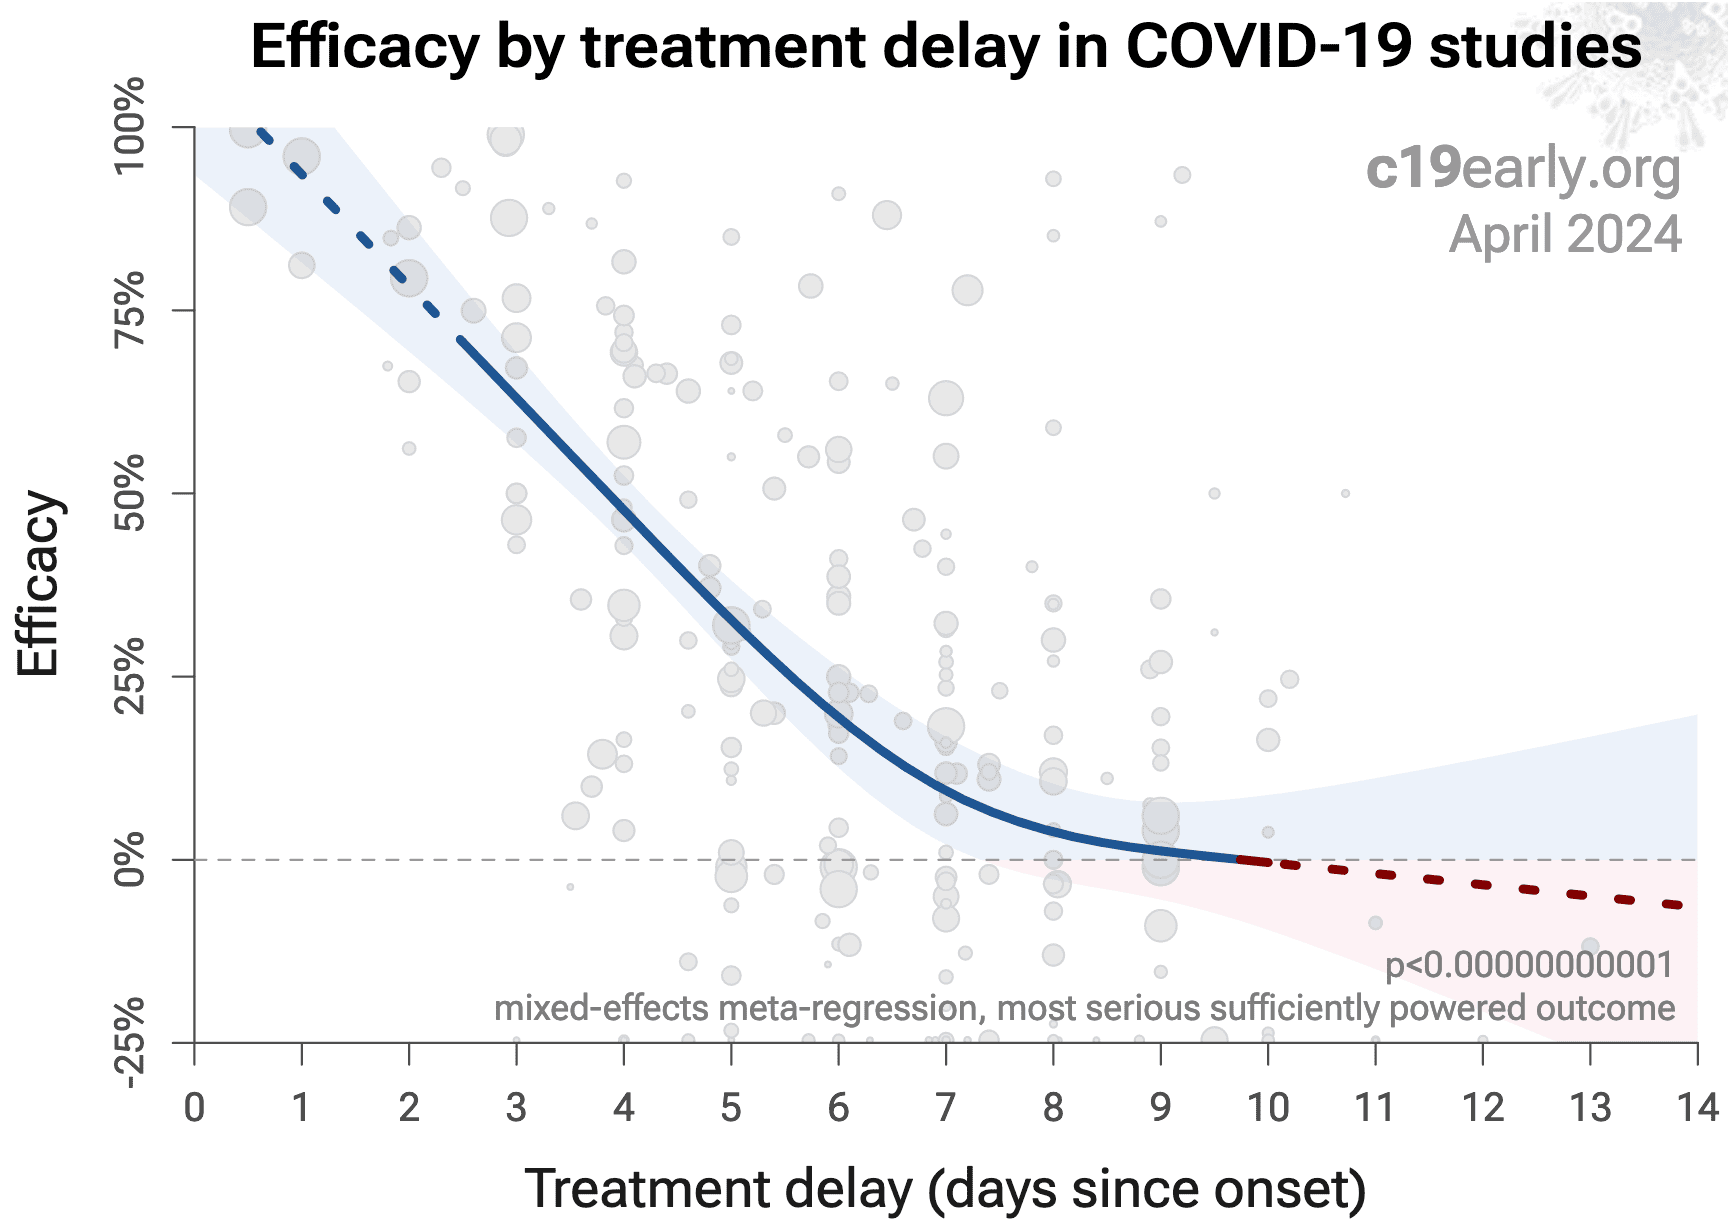
Fig. 22 shows a mixed-effects meta-regression for efficacy as a function of treatment delay in COVID-19 studies from 227 treatments, showing that efficacy declines rapidly with treatment delay. Early treatment is critical for COVID-19.
Loading..
Fig. 22. Early treatment is more effective. Meta-regression showing efficacy as a function of treatment delay in COVID-19 studies from 227 treatments.
Details of the patient population including age and comorbidities may critically affect how well a treatment works. For example, many COVID-19 studies with relatively young low-comorbidity patients show all patients recovering quickly with or without treatment. In such cases, there is little room for an effective treatment to improve results, for example as in López-Medina et al.
Efficacy may depend critically on the distribution of SARS-CoV-2 variants encountered by patients. Risk varies significantly across variants91, for example the Gamma variant shows significantly different characteristics92-95. Different mechanisms of action may be more or less effective depending on variants, for example the degree to which TMPRSS2 contributes to viral entry can differ across variants96,97.
Effectiveness may depend strongly on the dosage and treatment regimen.
The quality of medications may vary significantly between manufacturers and production batches, which may significantly affect efficacy and safety. Williams et al. analyze ivermectin from 11 different sources, showing highly variable antiparasitic efficacy across different manufacturers. Xu et al. analyze a treatment from two different manufacturers, showing 9 different impurities, with significantly different concentrations for each manufacturer. Non-prescription supplements may show very wide variations in quality3,4.
The use of other treatments may significantly affect outcomes, including supplements, other medications, or other interventions such as prone positioning. Treatments may be synergistic100-124, therefore efficacy may depend strongly on combined treatments.
Across all studies there is a strong association between different outcomes, for example improved recovery is strongly associated with lower mortality. However, efficacy may differ depending on the effect measured, for example a treatment may be more effective against secondary complications and have minimal effect on viral clearance.
The distribution of studies will alter the outcome of a meta-analysis. Consider a simplified example where everything is equal except for the treatment delay, and effectiveness decreases to zero or below with increasing delay. If there are many studies using very late treatment, the outcome may be negative, even though early treatment is very effective. All meta-analyses combine heterogeneous studies, varying in population, variants, and potentially all factors above, and therefore may obscure efficacy by including studies where treatment is less effective. Generally, we expect the estimated effect size from meta-analysis to be less than that for the optimal case. Looking at all studies is valuable for providing an overview of all research, important to avoid cherry-picking, and informative when a positive result is found despite combining less-optimal situations. However, the resulting estimate does not apply to specific cases such as early treatment in high-risk populations. While we present results for all studies, we also present treatment time and individual outcome analyses, which may be more informative for specific use cases.
This section validates the use of pooled effects for COVID-19, which enables earlier detection of efficacy, however pooled effects are no longer required for vitamin A as of May 2023. Efficacy is now known based on specific outcomes.
For COVID-19, delay in clinical results translates into additional death and morbidity, as well as additional economic and societal damage. Combining the results of studies reporting different outcomes is required. There may be no mortality in a trial with low-risk patients, however a reduction in severity or improved viral clearance may translate into lower mortality in a high-risk population. Different studies may report lower severity, improved recovery, and lower mortality, and the significance may be very high when combining the results. "The studies reported different outcomes" is not a good reason for disregarding results. Pooling the results of studies reporting different outcomes allows us to use more of the available information. Logically we should, and do, use additional information when evaluating treatments—for example dose-response and treatment delay-response relationships provide additional evidence of efficacy that is considered when reviewing the evidence for a treatment.
We present both specific outcome and pooled analyses. In order to combine the results of studies reporting different outcomes we use the most serious outcome reported in each study, based on the thesis that improvement in the most serious outcome provides comparable measures of efficacy for a treatment. A critical advantage of this approach is simplicity and transparency. There are many other ways to combine evidence for different outcomes, along with additional evidence such as dose-response relationships, however these increase complexity.
Trials with high-risk patients may be restricted due to ethics for treatments that are known or expected to be effective, and they increase difficulty for recruiting. Using less severe outcomes as a proxy for more serious outcomes allows faster and safer collection of evidence.
For many COVID-19 treatments, a reduction in mortality logically follows from a reduction in hospitalization, which follows from a reduction in symptomatic cases, which follows from a reduction in PCR positivity. We can directly test this for COVID-19.
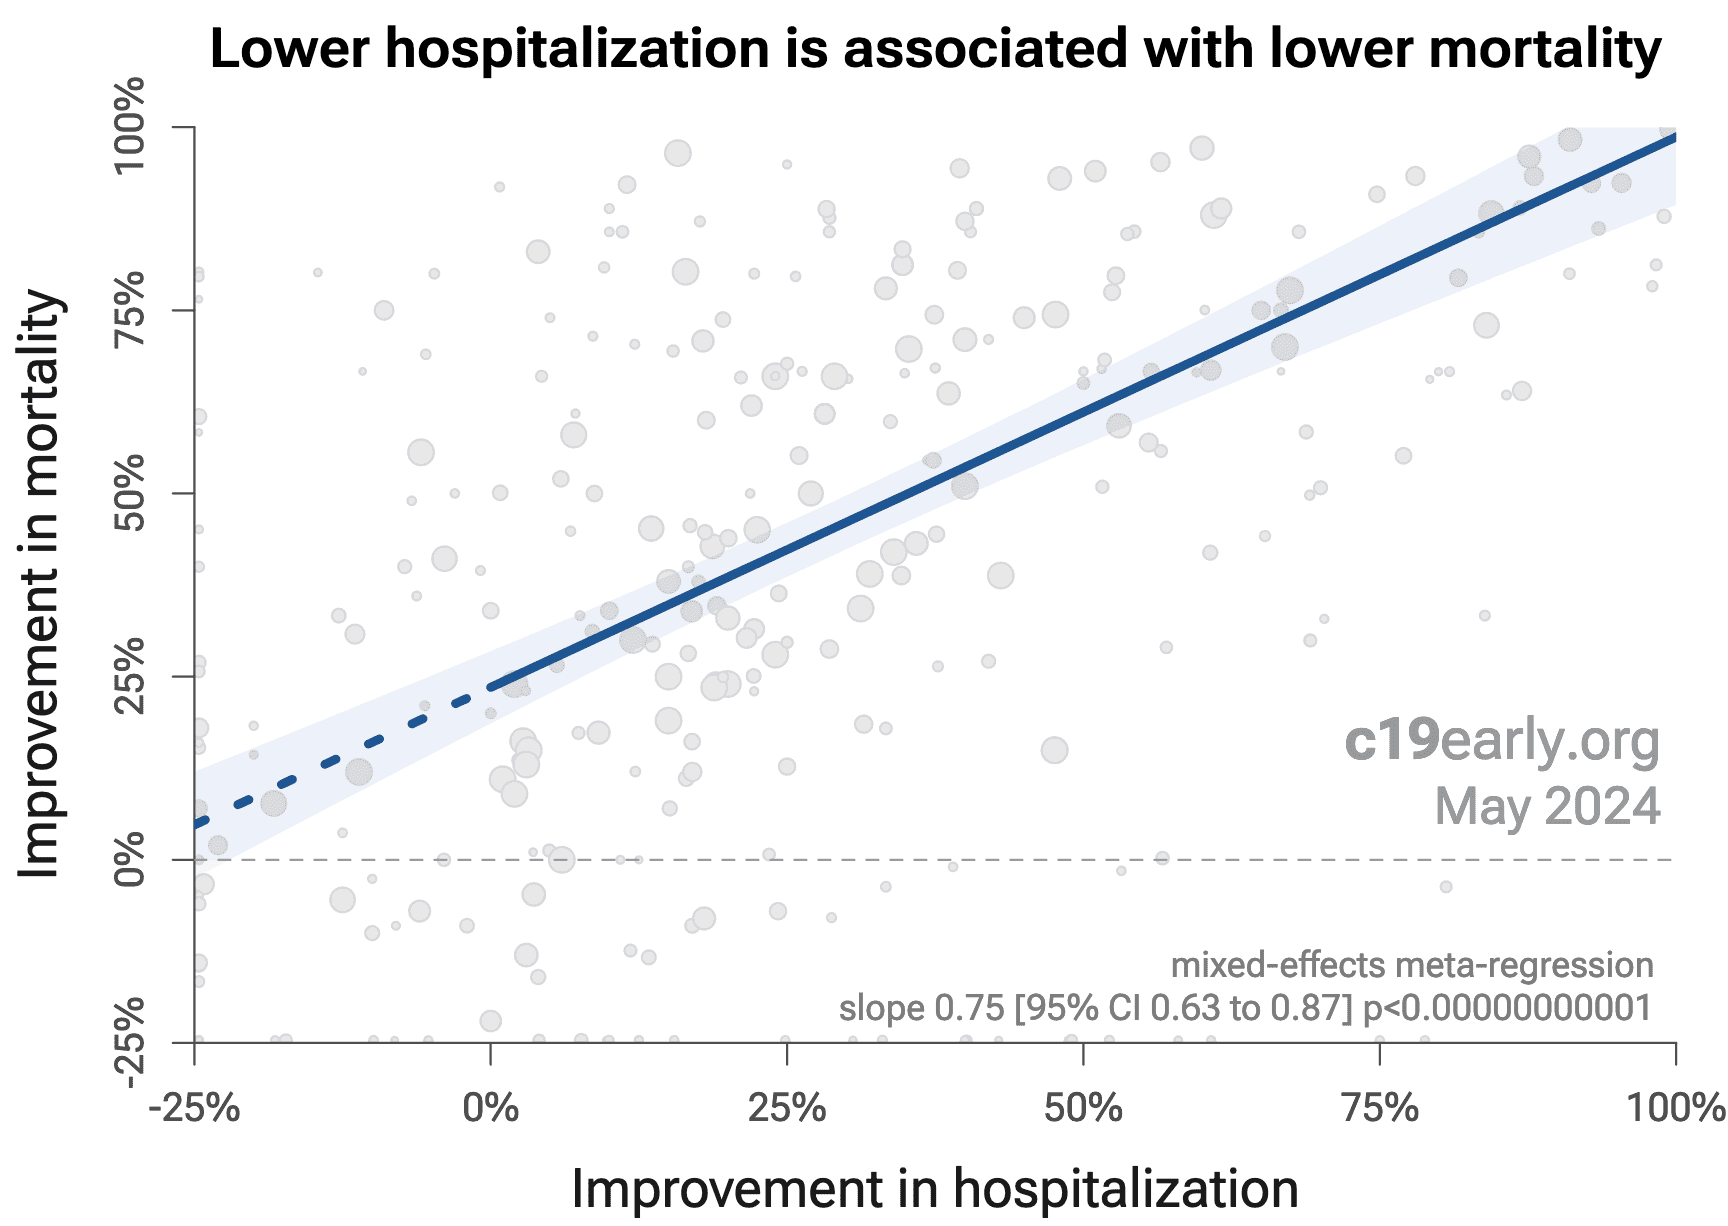
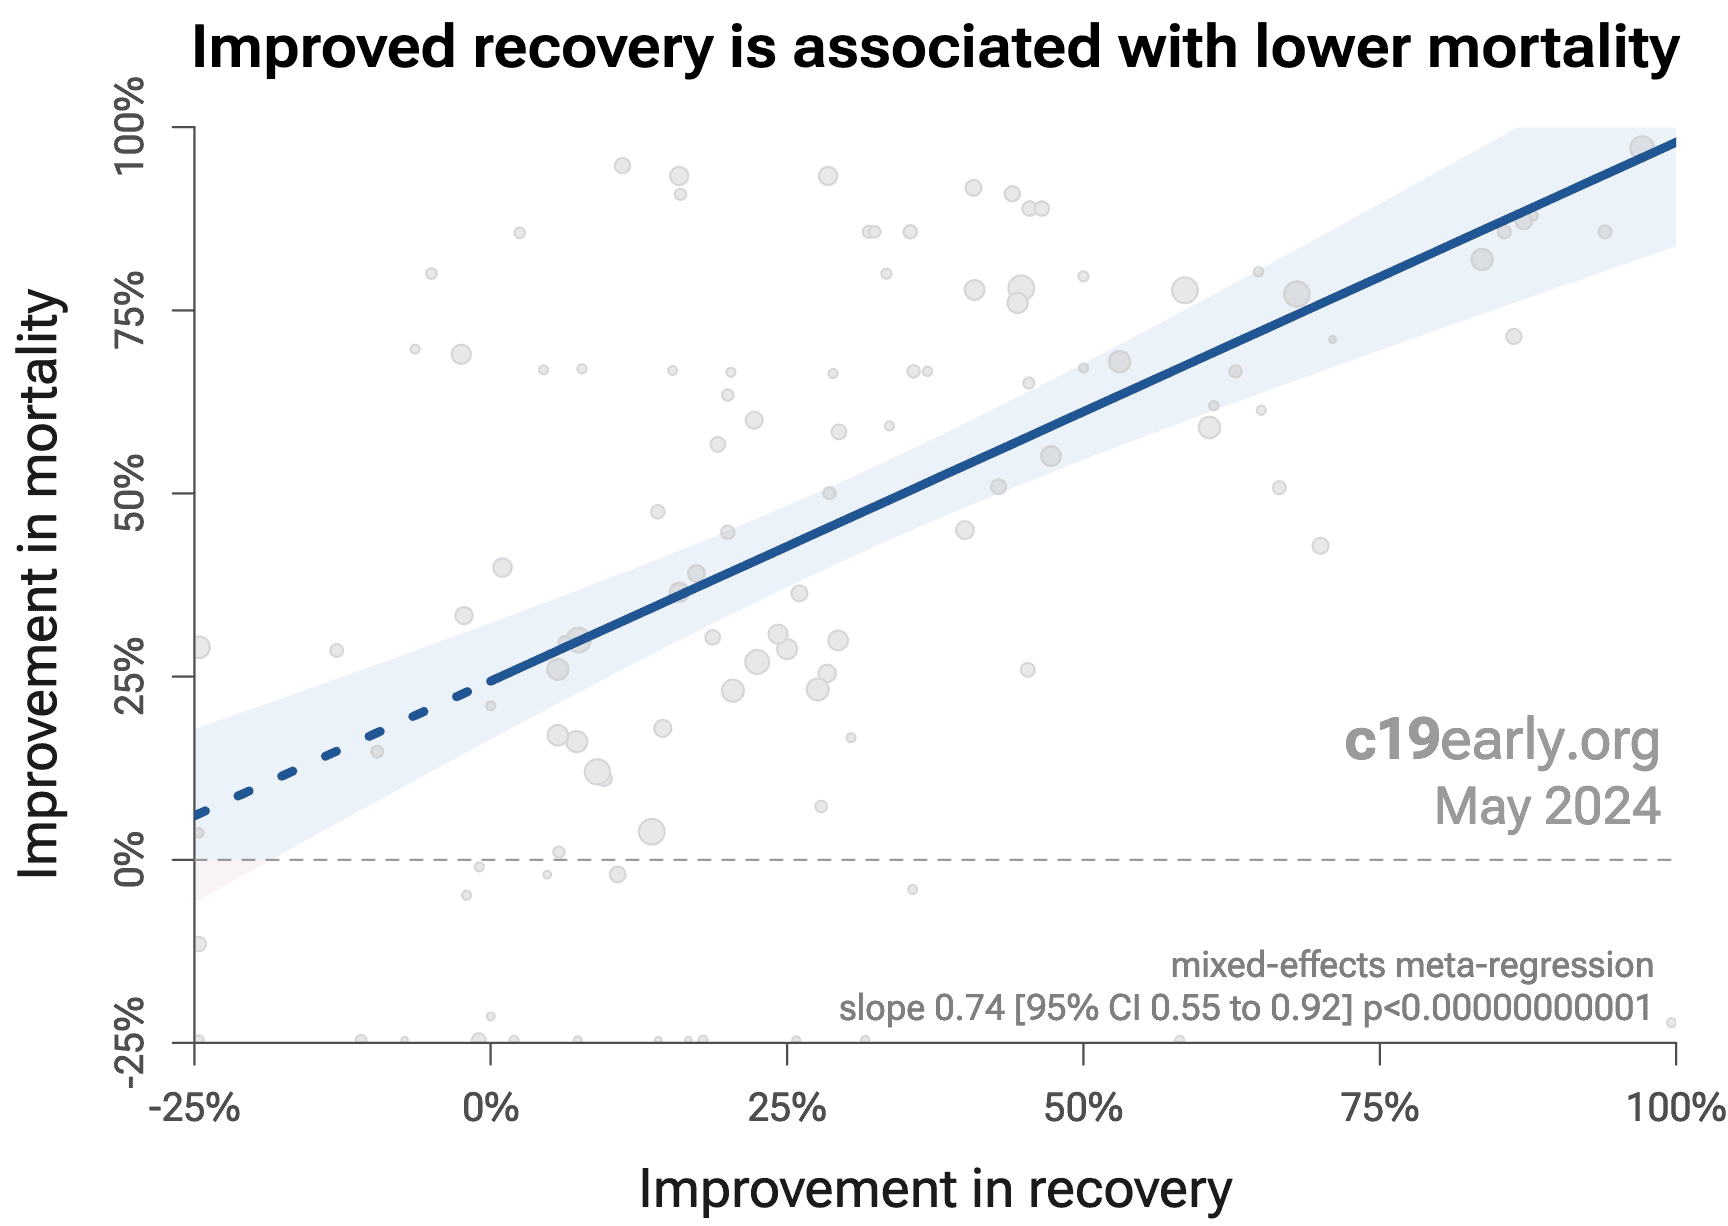
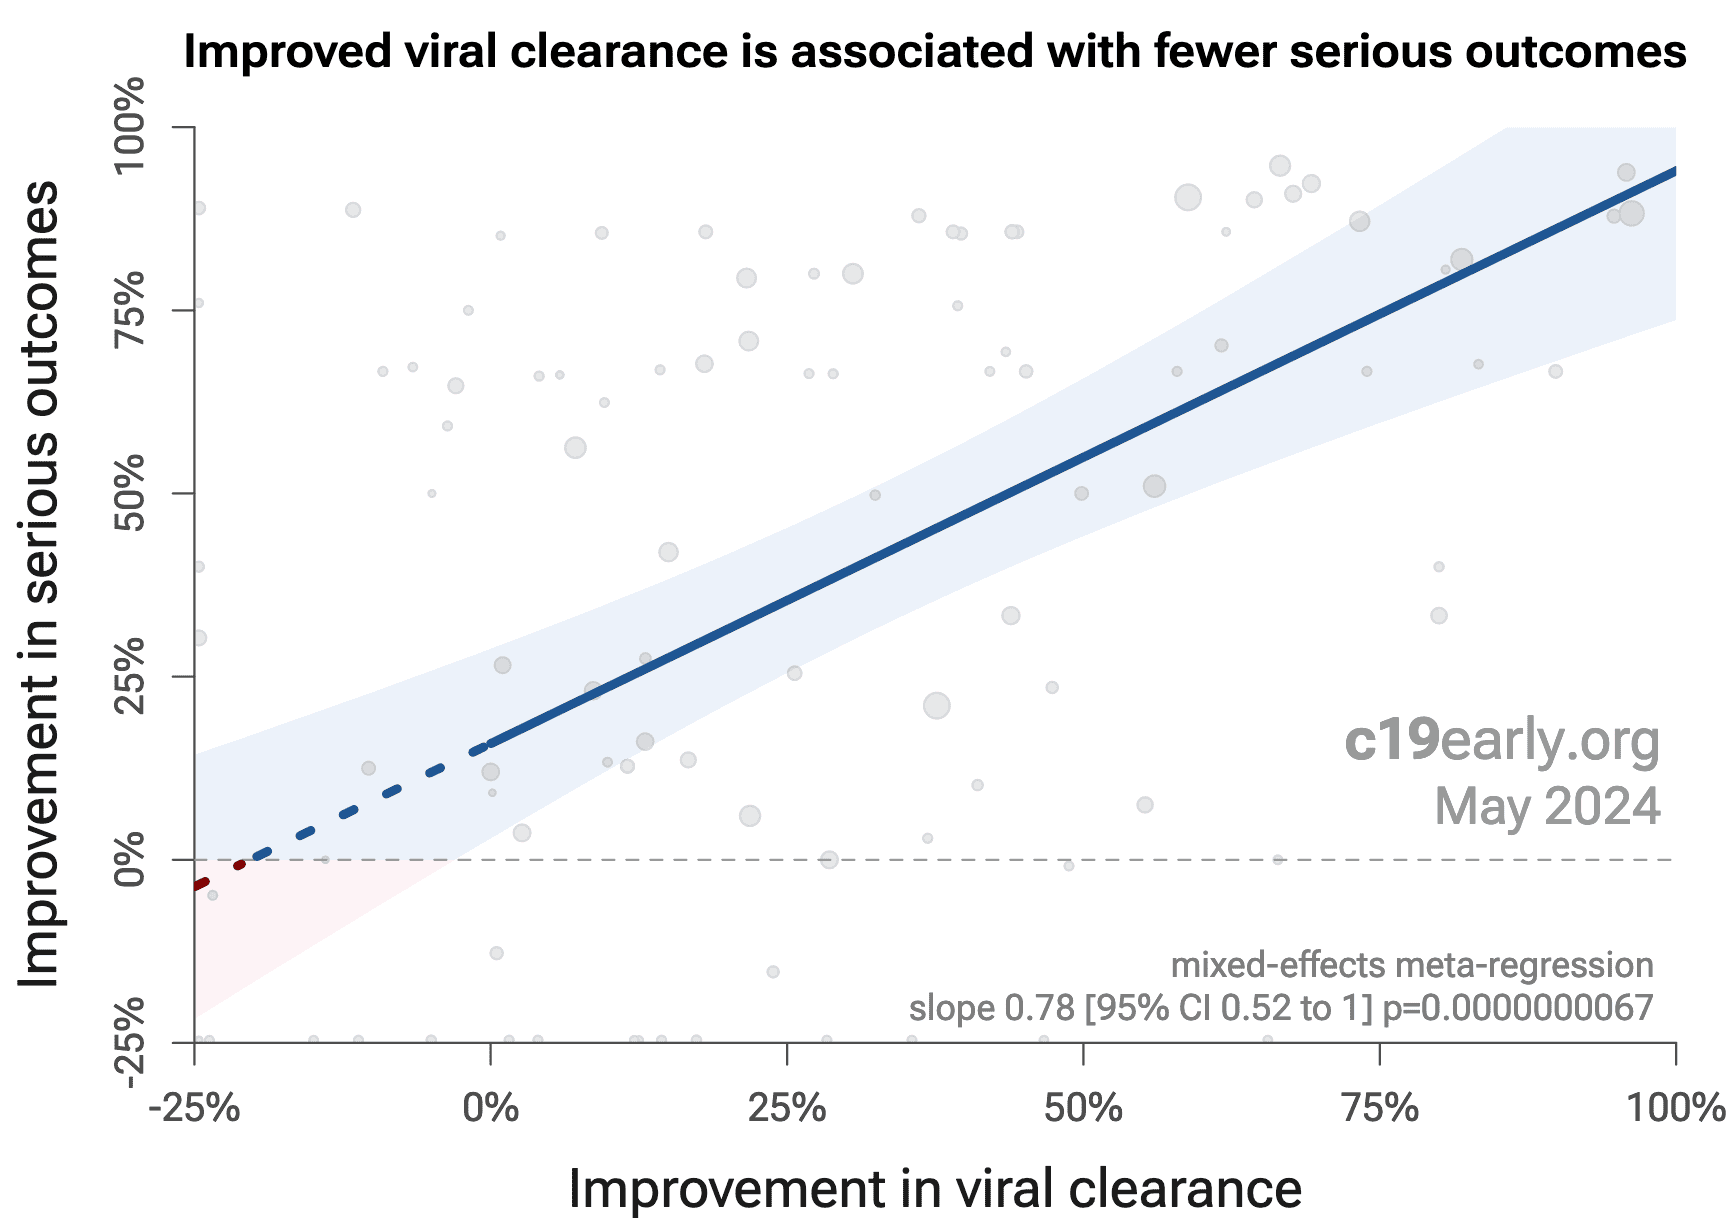
Analysis of the the association between different outcomes across studies from all 227 treatments we cover confirms the validity of pooled outcome analysis for COVID-19. Fig. 23 shows that lower hospitalization is very strongly associated with lower mortality (p < 0.0000000001). Similarly, Fig. 24 shows that improved recovery is very strongly associated with lower mortality (p < 0.0000000001). Considering the extremes, Singh et al. show an association between viral clearance and hospitalization or death, with p = 0.003 after excluding one large outlier from a mutagenic treatment, and based on 44 RCTs including 52,384 patients. Fig. 25 shows that improved viral clearance is strongly associated with fewer serious outcomes. The association is very similar to Singh et al., with higher confidence due to the larger number of studies. As with Singh et al., the confidence increases when excluding the outlier treatment, from p = 0.0000000074 to p = 0.00000000015.
Loading..
Fig. 23. Lower hospitalization is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 24. Improved recovery is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 23. Improved viral clearance is associated with fewer serious outcomes, supporting pooled outcome analysis.
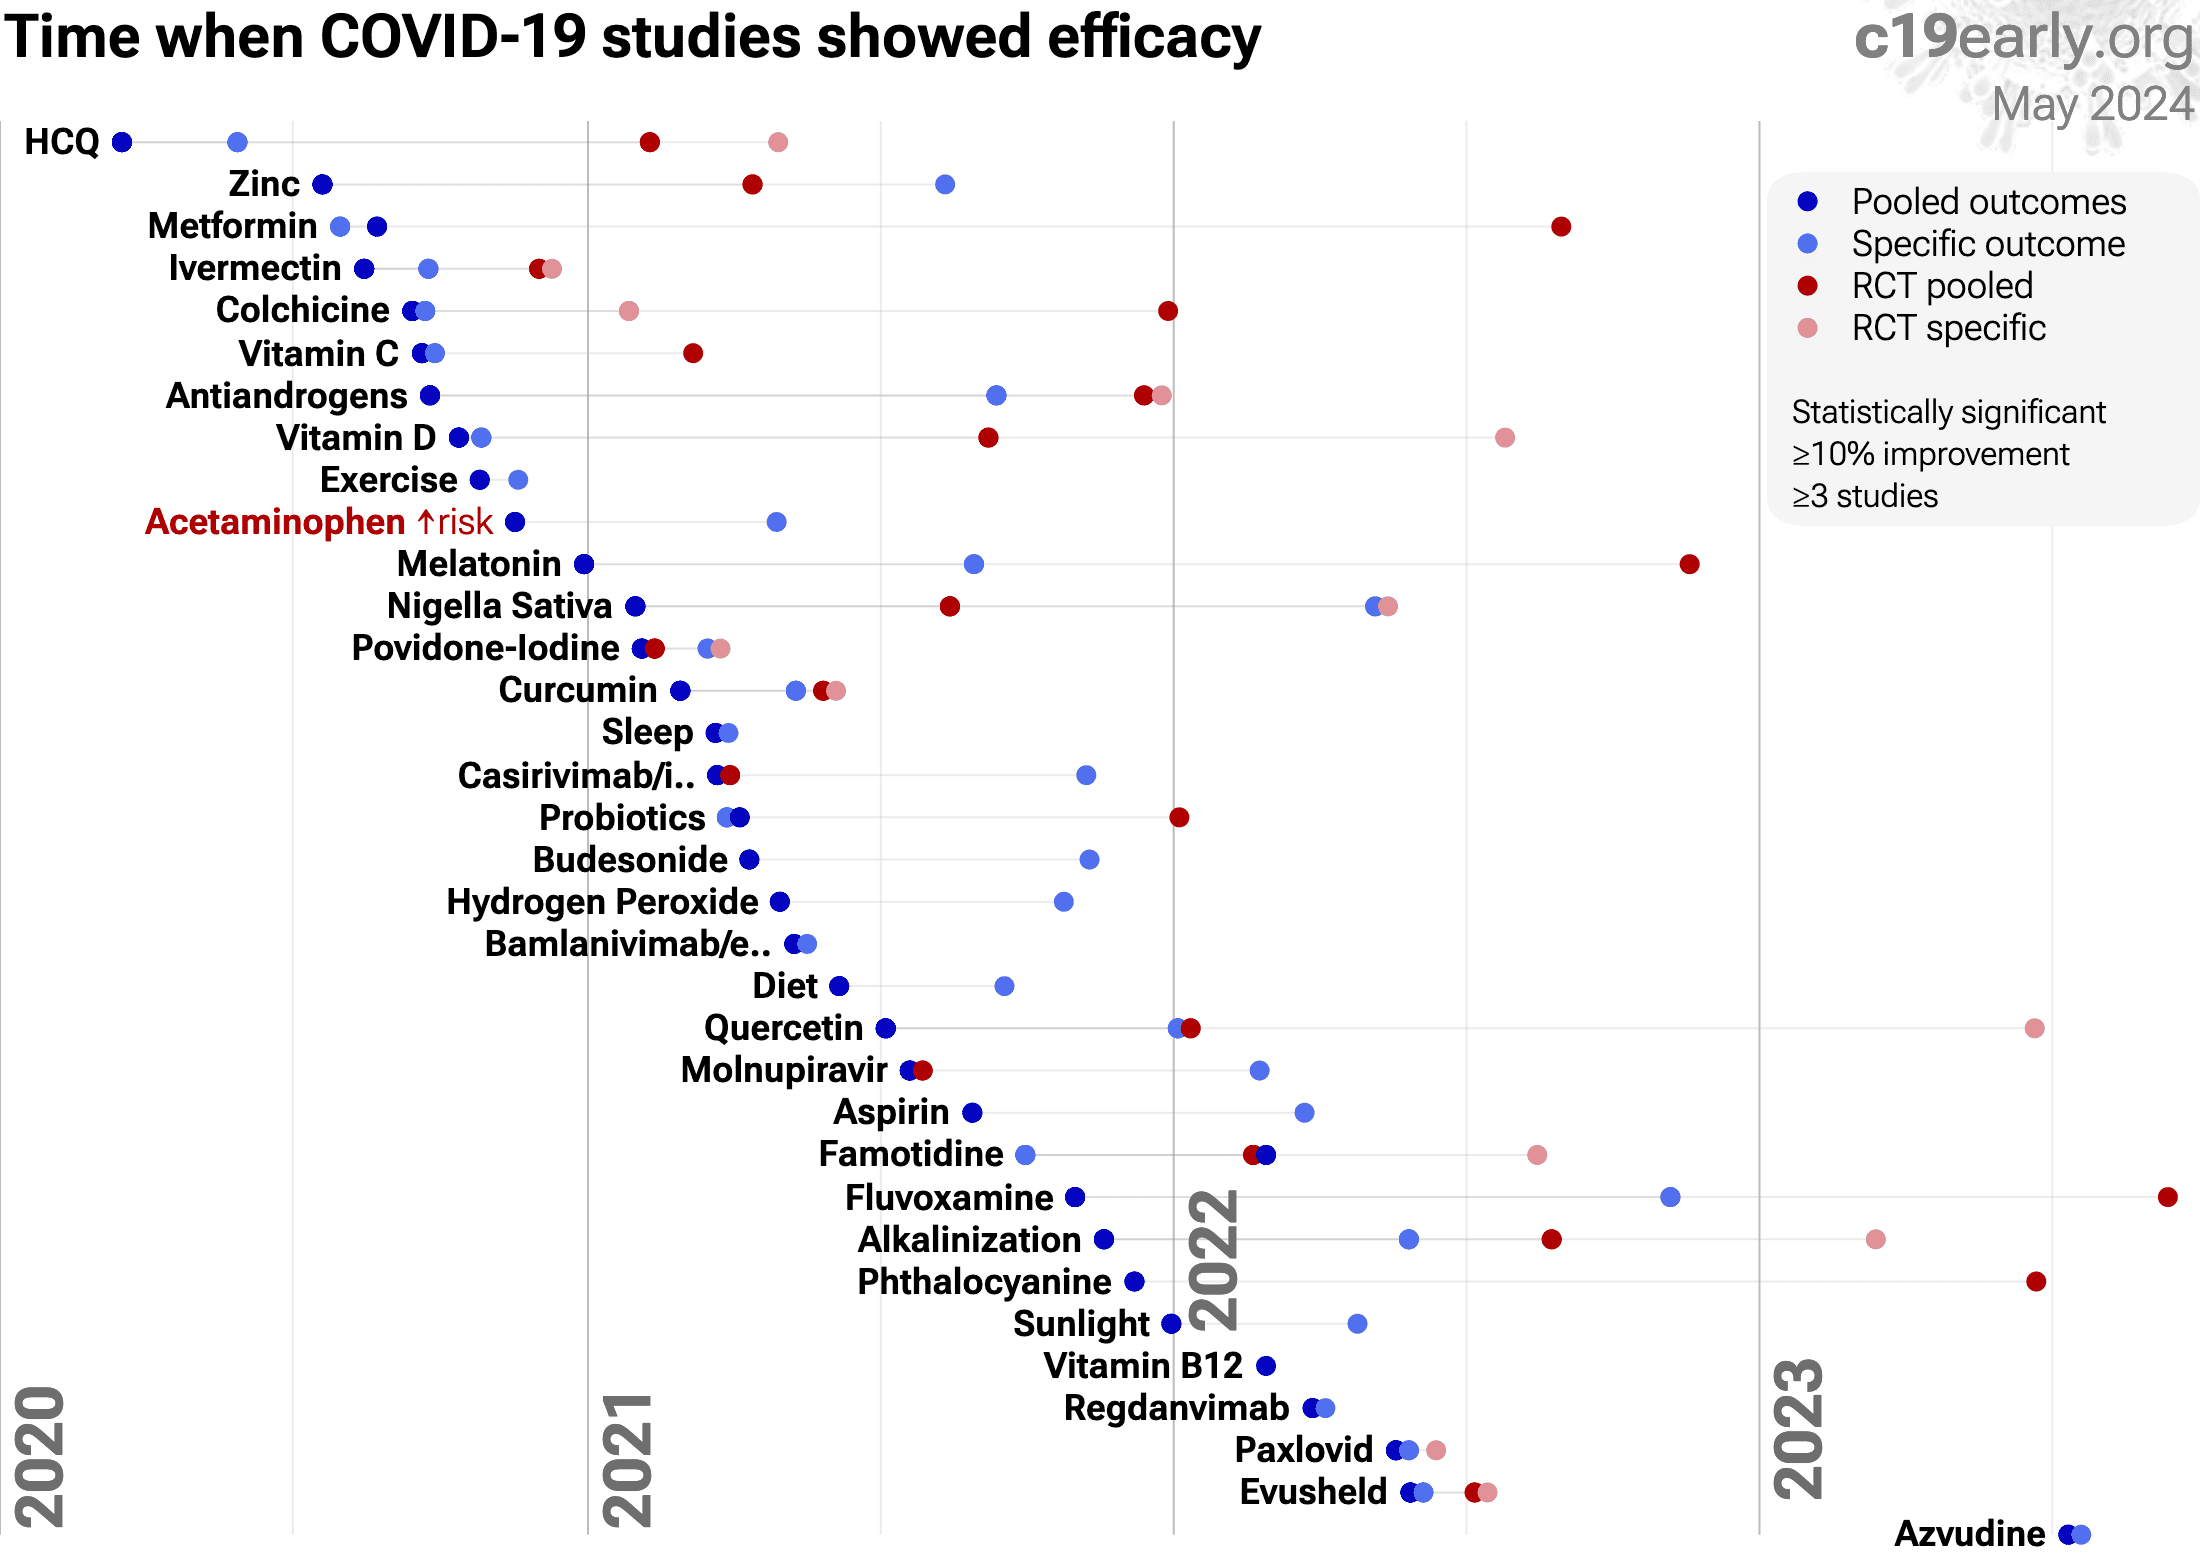
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. 85% of these have been confirmed with one or more specific outcomes, with a mean delay of 4.6 months. When restricting to RCTs only, 53% of treatments showing statistically significant efficacy/harm with pooled effects have been confirmed with one or more specific outcomes, with a mean delay of 7.5 months. Fig. 26 shows when treatments were found effective during the pandemic. Pooled outcomes often resulted in earlier detection of efficacy.
Loading..
Loading..
Fig. 26. The time when studies showed that treatments were effective, defined as statistically significant improvement of ≥10% from ≥3 studies. Pooled results typically show efficacy earlier than specific outcome results. Results from all studies often shows efficacy much earlier than when restricting to RCTs. Results reflect conditions as used in trials to date, these depend on the population treated, treatment delay, and treatment regimen.
Pooled analysis could hide efficacy, for example a treatment that is beneficial for late stage patients but has no effect on viral clearance may show no efficacy if most studies only examine viral clearance. In practice, it is rare for a non-antiviral treatment to report viral clearance and to not report clinical outcomes; and in practice other sources of heterogeneity such as differences in treatment delay are more likely to hide efficacy.
Analysis validates the use of pooled effects and shows significantly faster detection of efficacy on average. However, as with all meta-analyses, it is important to review the different studies included. We also present individual outcome analyses, which may be more informative for specific use cases.
There are many complementary mechanisms of action for COVID-19 treatments, with over 500 therapeutic targets60. Studies show complementary and synergistic effects with polytherapy100-124. For example, Jitobaom et al.101 shows >10x reduction in IC50 with ivermectin and niclosamide, an RCT by Said et al.108 showed the combination of nigella sativa and vitamin D was more effective than either alone, and an RCT by Wannigama et al.126 showed improved results with fluvoxamine combined with additional treatments, compared to fluvoxamine alone.
SARS-CoV-2 can rapidly acquire mutations altering infectivity, disease severity, and drug resistance even without selective pressure127-134. Antigenic drift can undermine more variant-specific treatments like monoclonal antibodies and more specific antivirals. Treatment with targeted antivirals may select for escape mutations135. The efficacy of treatments varies depending on cell type136 due to differences in viral receptor expression, drug distribution and metabolism, and cell-specific mechanisms. Efficacy may also vary based on genetic variants137-147.
Variable efficacy across variants, cell types, tissues, and host genetics, along with the complementary and synergistic actions of different treatments, all point to greater efficacy with polytherapy. In many studies, the standard of care given to all patients includes other treatments—efficacy seen in these trials may rely in part on synergistic effects. Less variant specific treatments and polytherapy targeting multiple viral and host proteins may be more effective. Meta-analysis of all early treatment trials shows 71% [60‑79%] lower risk for studies using combined treatments, compared to 27% [24‑30%] for single treatments.
Polytherapy vs. monotherapy for all treatments
Monotherapy Polytherapy
Early treatment
27% [24–30%]
71% [60–79%]
Late treatment
18% [16–20%]
49% [41–55%]
Prophylaxis
28% [25–30%]
90% [48–98%]
Studies where combined treatments may significantly contribute to efficacy are excluded from this meta-analysis148. While not reaching statistical significance, vitamin A studies using polytherapy also show greater efficacy than monotherapy studies. This comparison includes combined treatment studies excluded from the rest of this paper148.
Polytherapy vs. monotherapy for vitamin A
Monotherapy Polytherapy
Late treatment
13% [-214–76%]
73% [56–84%]
c19early.org
Combined treatment is more effective
SARS-CoV-2 involves the complex interplay of 500+ host and viral proteins and factors, providing many therapeutic targets. Many compounds have antiviral activity for SARS-CoV-2, with many different mechanisms including blocking attachment, entry, and replication. Combinations of treatments, with careful attention to potential side effects, allows improved efficacy via complementary and synergistic mechanisms.
Tissue and cell coverage Different compounds have different tissue penetration profiles and efficacy across cell types
Variant coverage Compounds with different viral resistance profiles
Intra/extracellular Disabling and removing intracellular and extracellular viral particles
Resistance Minimizing persistence and emergence of resistant variants
Genetics Robustness against individual variations in efficacy based on genetics
Lower doses Potentially lower doses of individual agents, reducing toxicity
Viral and host-directed Antivirals targeting viral and host proteins
Immune system function Supporting or enhancing natural immune system function
Disease phases Addressing multiple disease phases (viral replication, inflammation, secondary complications)
Publishing is often biased towards positive results, however evidence suggests that there may be a negative bias for inexpensive treatments for COVID-19. Both negative and positive results are very important for COVID-19, media in many countries prioritizes negative results for inexpensive treatments (inverting the typical incentive for scientists that value media recognition), and there are many reports of difficulty publishing positive results149-152. For vitamin A, there is currently not enough data to evaluate publication bias with high confidence.
One method to evaluate bias is to compare prospective vs. retrospective studies. Prospective studies are more likely to be published regardless of the result, while retrospective studies are more likely to exhibit bias. For example, researchers may perform preliminary analysis with minimal effort and the results may influence their decision to continue. Retrospective studies also provide more opportunities for the specifics of data extraction and adjustments to influence results.
Fig. 27 shows a scatter plot of results for prospective and retrospective treatment studies. 67% of retrospective studies report a statistically significant positive effect for one or more outcomes, compared to 50% of prospective studies, consistent with a bias toward publishing positive results. The median effect size for retrospective studies is 20% improvement, compared to 60% for prospective studies, suggesting a potential bias towards publishing results showing lower efficacy.
Loading..
Fig. 27. Prospective vs. retrospective studies. The diamonds show the results of random-effects meta-analysis.
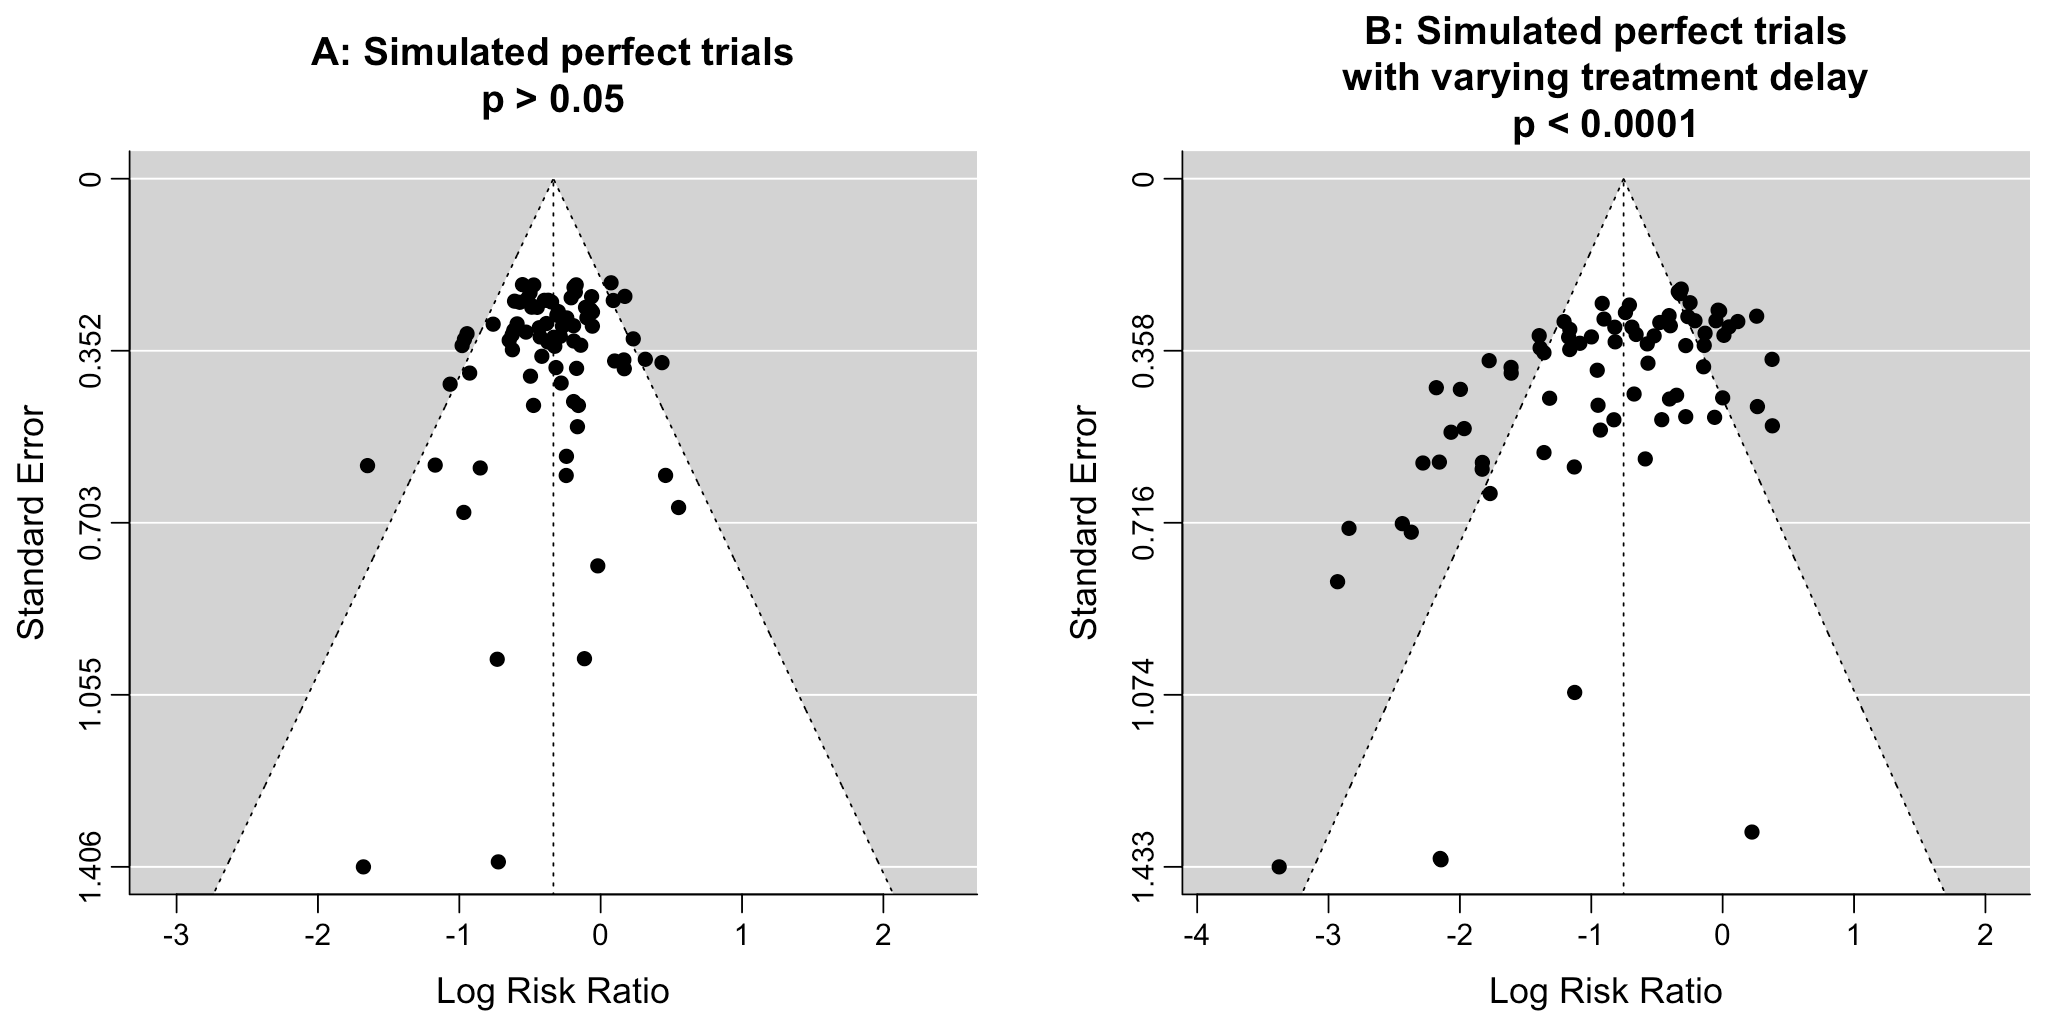
Funnel plots have traditionally been used for analyzing publication bias. This is invalid for COVID-19 acute treatment trials — the underlying assumptions are invalid, which we can demonstrate with a simple example. Consider a set of hypothetical perfect trials with no bias. Fig. 28 plot A shows a funnel plot for a simulation of 80 perfect trials, with random group sizes, and each patient's outcome randomly sampled (10% control event probability, and a 30% effect size for treatment). Analysis shows no asymmetry (p > 0.05). In plot B, we add a single typical variation in COVID-19 treatment trials — treatment delay. Consider that efficacy varies from 90% for treatment within 24 hours, reducing to 10% when treatment is delayed 3 days. In plot B, each trial's treatment delay is randomly selected. Analysis now shows highly significant asymmetry, p < 0.0001, with six variants of Egger's test all showing p < 0.05153-160. Note that these tests fail even though treatment delay is uniformly distributed. In reality treatment delay is more complex — each trial has a different distribution of delays across patients, and the distribution across trials may be biased (e.g., late treatment trials may be more common). Similarly, many other variations in trials may produce asymmetry, including dose, administration, duration of treatment, differences in SOC, comorbidities, age, variants, and bias in design, implementation, analysis, and reporting.
Log Risk Ratio Standard Error 1.406 1.055 0.703 0.352 0 -3 -2 -1 0 1 2 A: Simulated perfect trials p > 0.05 Log Risk Ratio Standard Error 1.433 1.074 0.716 0.358 0 -4 -3 -2 -1 0 1 2 B: Simulated perfect trials with varying treatment delay p < 0.0001
Fig. 28. Example funnel plot analysis for simulated perfect trials.
Pharmaceutical drug trials often have conflicts of interest whereby sponsors or trial staff have a financial interest in the outcome being positive. Vitamin A for COVID-19 lacks this because it is an inexpensive and widely available supplement. In contrast, most COVID-19 vitamin A trials have been run by physicians on the front lines with the primary goal of finding the best methods to save human lives and minimize the collateral damage caused by COVID-19. While pharmaceutical companies are careful to run trials under optimal conditions (for example, restricting patients to those most likely to benefit, only including patients that can be treated soon after onset when necessary, and ensuring accurate dosing), not all vitamin A trials represent the optimal conditions for efficacy.
Summary statistics from meta-analysis necessarily lose information. As with all meta-analyses, studies are heterogeneous, with differences in treatment delay, treatment regimen, patient demographics, variants, conflicts of interest, standard of care, and other factors. We provide analyses for specific outcomes and by treatment delay, and we aim to identify key characteristics in the forest plots and summaries. Results should be viewed in the context of study characteristics.
Some analyses classify treatment based on early or late administration, as done here, while others distinguish between mild, moderate, and severe cases. Viral load does not indicate degree of symptoms — for example patients may have a high viral load while being asymptomatic. With regard to treatments that have antiviral properties, timing of treatment is critical — late administration may be less helpful regardless of severity.
Details of treatment delay per patient is often not available. For example, a study may treat 90% of patients relatively early, but the events driving the outcome may come from 10% of patients treated very late. Our 5 day cutoff for early treatment may be too conservative, 5 days may be too late in many cases.
Comparison across treatments is confounded by differences in the studies performed, for example dose, variants, and conflicts of interest. Trials with conflicts of interest may use designs better suited to the preferred outcome.
In some cases, the most serious outcome has very few events, resulting in lower confidence results being used in pooled analysis, however the method is simpler and more transparent. This is less critical as the number of studies increases. Restriction to outcomes with sufficient power may be beneficial in pooled analysis and improve accuracy when there are few studies, however we maintain our pre-specified method to avoid any retrospective changes.
Studies show that combinations of treatments can be highly synergistic and may result in many times greater efficacy than individual treatments alone100-124. Therefore standard of care may be critical and benefits may diminish or disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on submissions. Accuracy benefits from widespread review and submission of updates and corrections from reviewers. Less popular treatments may receive fewer reviews.
No treatment or intervention is 100% available and effective for all current and future variants. Efficacy may vary significantly with different variants and within different populations. All treatments have potential side effects. Propensity to experience side effects may be predicted in advance by qualified physicians. We do not provide medical advice. Before taking any medication, consult a qualified physician who can compare all options, provide personalized advice, and provide details of risks and benefits based on individual medical history and situations.
1 of 14 studies combine treatments. The results of vitamin A alone may differ. 1 of 4 RCTs use combined treatment.
Many reviews cover vitamin A for COVID-19, presenting additional background on mechanisms and related results, including161-167.
Additional preclinical or review papers suggesting potential benefits of vitamin A for COVID-19 include178-183. We have not reviewed these studies in detail.
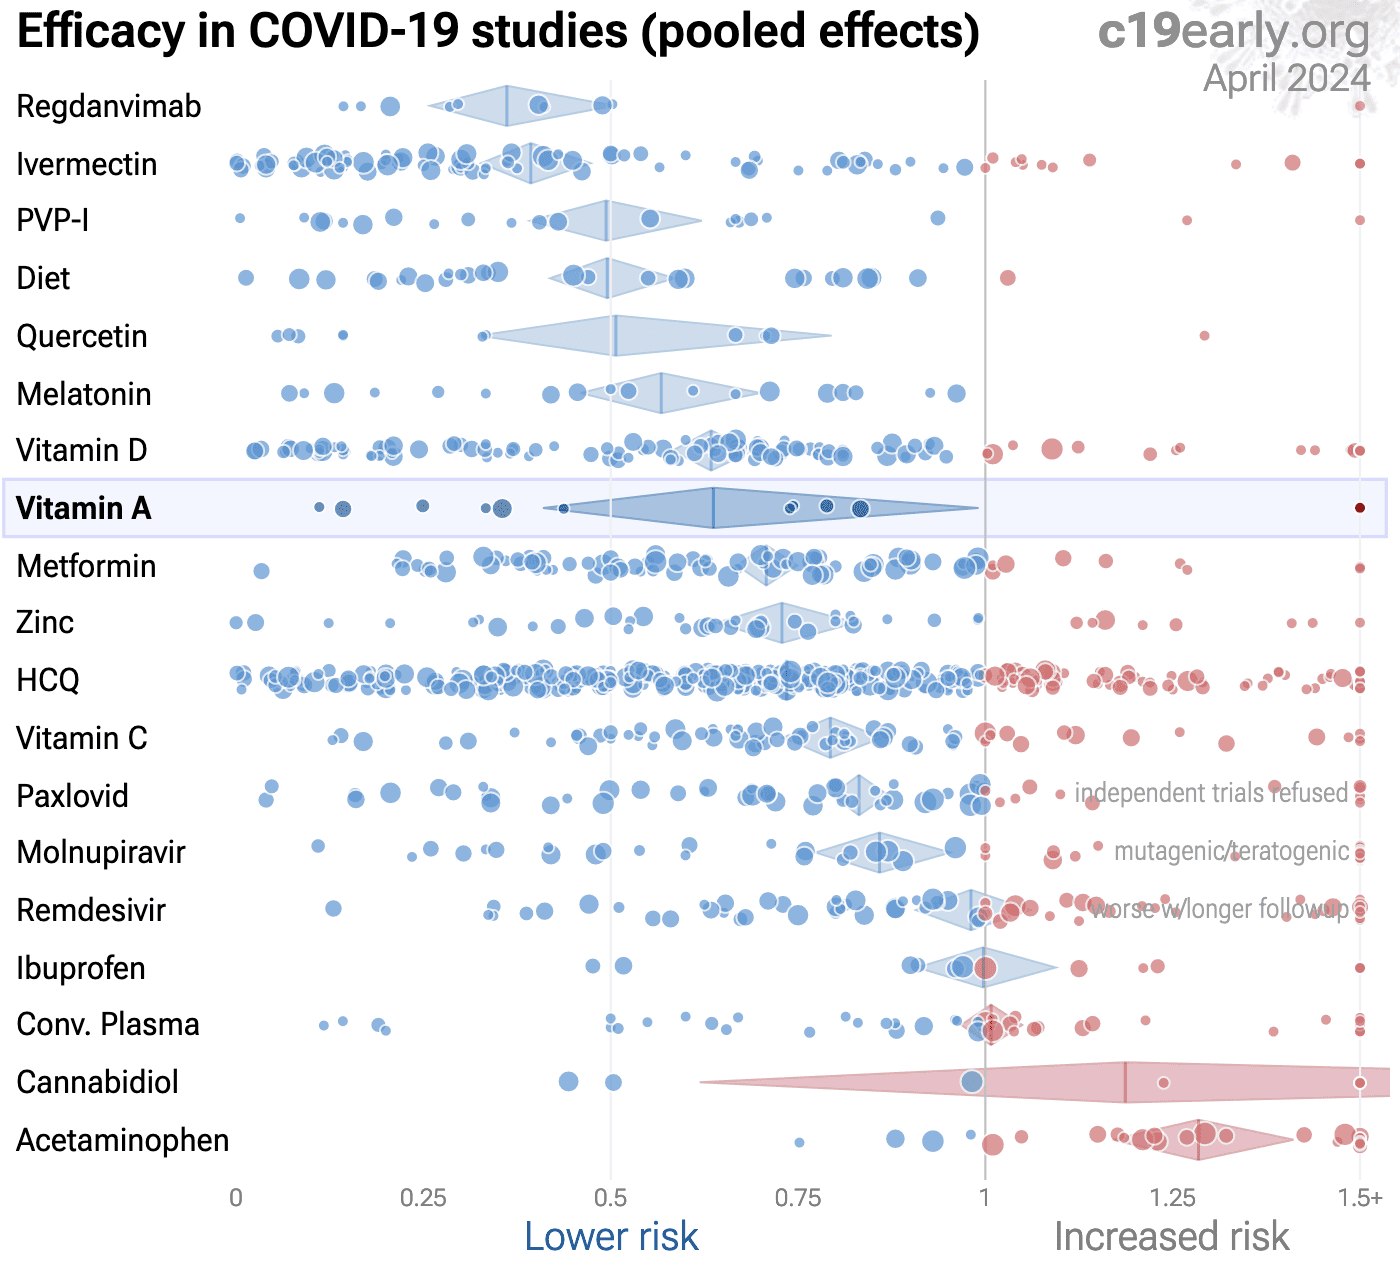
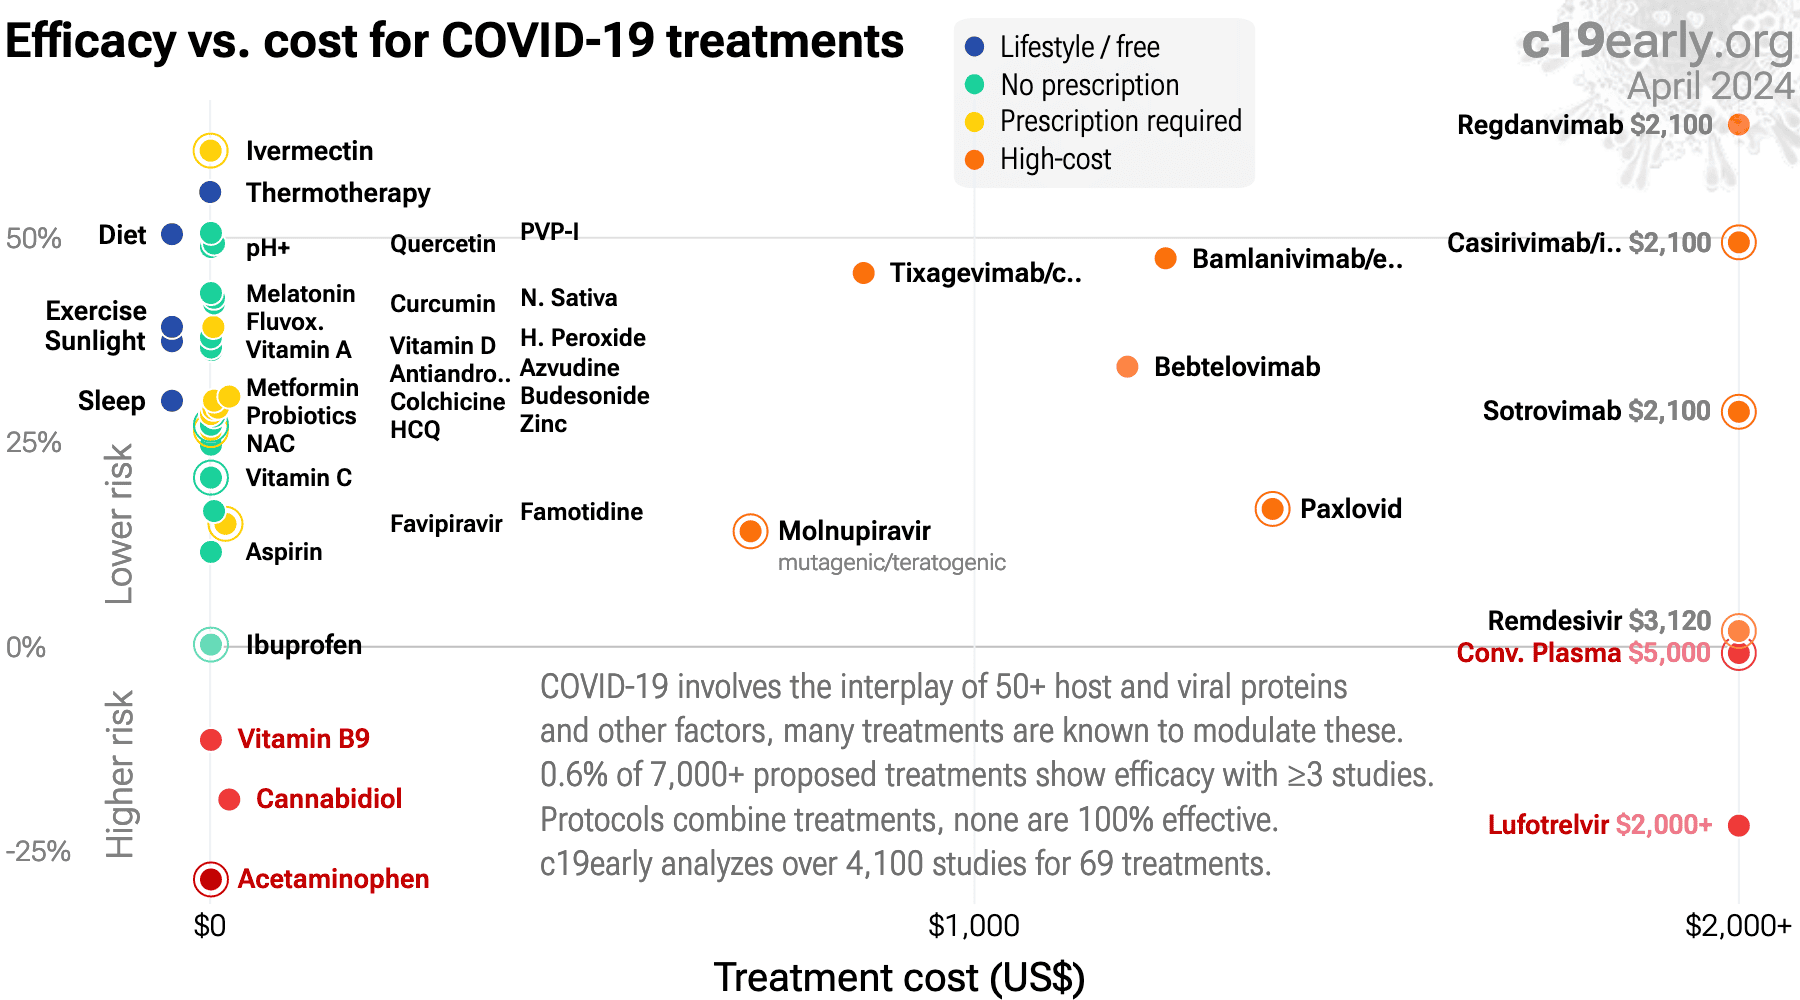
SARS-CoV-2 infection and replication involves a complex interplay of 500+ host and viral proteins and other factors36-43, providing many therapeutic targets. Over 12,000 compounds have been predicted to reduce COVID-19 risk44, either by directly minimizing infection or replication, by supporting immune system function, or by minimizing secondary complications. Fig. 29 shows an overview of the results for vitamin A in the context of multiple COVID-19 treatments, and Fig. 30 shows a plot of efficacy vs. cost for COVID-19 treatments.
Loading..
Fig. 29. Scatter plot showing results within the context of multiple COVID-19 treatments. Diamonds shows the results of random-effects meta-analysis. 0.5% of 12,000+ proposed treatments show efficacy184.
Loading..
Loading..
Fig. 30. Efficacy vs. cost for COVID-19 treatments.
Studies to date show that vitamin A is an effective treatment for COVID-19. Significantly lower risk is seen for hospitalization, recovery, and cases. 8 studies from 7 independent teams in 4 countries show significant benefit. Meta-analysis using the most serious outcome reported shows 33% [12‑49%] lower risk. Results are similar for higher quality and peer-reviewed studies and better for Randomized Controlled Trials. Results are consistent with early treatment being more effective than late treatment. 7 sufficiency studies analyze outcomes based on serum levels, showing 85% [62‑94%] lower risk for patients with higher vitamin A levels.
Results are robust—in worst case exclusion sensitivity analysis 5 of 14 studies must be excluded before statistical significance is lost.
The European Food Safety Authority has found evidence for a causal relationship between the intake of vitamin A and optimal immune system function1,2.
 
Contact.
Contact us on X at @CovidAnalysis.
Funding.
We have received no funding or compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
AI.
We use AI models (Gemini, Grok, Claude, and ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.
Updates.
Our COVID-19 meta-analyses involve the extraction of over 229,000 datapoints from thousands of papers for 227 treatments. We thank the thousands of scientists, physicians, and other contributors that have provided updates, suggestions, feedback, and corrections. These are all welcome and can be submitted at https://c19early.org/vameta.html.
Dedication.
This work is dedicated to top evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce mortality and morbidity during the pandemic. In alphabetical order: Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty, Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr. Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch, Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work distributed in accordance with the Creative Commons CC0 1.0 Universal license, which dedicates the work to the public domain by waiving all rights worldwide under copyright law. You can distribute, remix, adapt, and build upon this work in any medium or format, including for commercial purposes, without asking permission. Referenced material and third-party images retain any original copyrights or restrictions. See: https://creativecommons.org/publicdomain/zero/1.0/.
Treatment and prophylaxis studies of vitamin A in Iraq.

The prophylaxis study contained 209 contacts of COVID-19 patients, 97 treated with vitamin A, showing significantly lower cases with treatment, and shorter duration of symptoms.

The treatment study is listed separately169. Submit Corrections or Updates.
Treatment and prophylaxis studies of vitamin A in Iraq.

The treatment study contained 100 patients, 50 treated with 200,000IU vitamin A for two days, showing lower progression to severe disease, and shorter duration of symptoms.

The prophylaxis study is listed separately169. Submit Corrections or Updates.
Retrospective 70 severe condition patients treated with vitamin A (200,000IU for two days), salbutamol, and budesonide, and 70 patients not treated with vitamin A, showing significantly lower mortality with the addition of vitamin A. Submit Corrections or Updates.
ICU patientsRCT · 60 patients · Iran · Apr – Jul 2020
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Improved recovery with treatment
p = 0.001
Small RCT 60 ICU patients in Iran, 30 treated with vitamins A, B, C, D, and E, showing significant improvement in SOFA score and several inflammatory markers at day 7 with treatment.

5,000 IU vitamin A daily, 600,000 IU vitamin D once, 300 IU of vitamin E twice a day, 500 mg vitamin C four times a day, and one ampule daily of B vitamins [thiamine nitrate 3.1 mg, sodium riboflavin phosphate 4.9 mg (corresponding to vitamin B2 3.6 mg), nicotinamide 40 mg, pyridoxine hydrochloride 4.9 mg (corresponding to vitamin B6 4.0 mg), sodium pantothenate 16.5 mg (corresponding to pantothenic acid 15 mg), sodium ascorbate 113 mg (corresponding to vitamin C 100 mg), biotin 60 μg, folic acid 400 μg, and cyanocobalamin 5 μg]. Submit Corrections or Updates.
Long COVIDRCT · NCT04900415 · 24 patients · China · Aug 2020 – Jun 2021
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower long COVID with vitamin A
p = 0.048
RCT 24 patients with olfactory dysfunction post-COVID-19 in Hong Kong, showing significantly improved recovery with the addition of vitamin A to aerosolised diffuser olfactory training. 25,000IU vitamin A for 14 days. Submit Corrections or Updates.
Prospective study of 144 hospitalized COVID-19 patients in the DRC and South Sudan, showing no significant difference with vitamin A treatment in unadjusted results with only 8 patients receiving vitamin A. Submit Corrections or Updates.
Prospective survey-based study with 15,227 people in the UK, showing lower risk of COVID-19 cases with vitamin A, vitamin D, zinc, selenium, probiotics, and inhaled corticosteroids; and higher risk with metformin and vitamin C. Statistical significance was not reached for any of these. Except for vitamin D, the results for treatments we follow were only adjusted for age, sex, duration of participation, and test frequency. Submit Corrections or Updates.
Prospective study of 32 elderly COVID-19 patients and 30 healthy controls in China showing significantly lower vitamin A and D levels in COVID-19 patients. In multivariable analysis, vitamin A deficiency was associated with significantly higher risk. Submit Corrections or Updates.
Case control study with 30 ICU COVID-19 patients, 30 hospitalized non-ICU patients, and 30 matched healthy controls, showing vitamin A levels associated with COVID-19 and severity, with ICU patient levels < hospitalized patients < healthy controls. Authors also show significantly lower risk of ARDS with vitamin A levels above 0.65µg/ml. Submit Corrections or Updates.
ProphylaxisRetrospective · 2,148 patients · Jordan · Mar – Jul 2021
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Vitamin A
reduces risk
Vitamin A
increases risk →
Lower hospitalization and severe cases
Not statistically significant · p = 0.4 (hospitalization) and p = 0.36 (severe cases)
Retrospective 2,148 COVID-19 recovered patients in Jordan, showing no significant differences in the risk of severity and hospitalization with vitamin A prophylaxis. Submit Corrections or Updates.
SufficiencyRetrospective · 135 patients · Ukraine
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Vitamin A
reduces risk
Vitamin A
increases risk →
Lower severe cases and fewer cases
Not statistically significant · p = 0.14 (severe cases) and p = 0.2 (fewer cases)
Retrospective 112 pediatric COVID-19 patients and 23 healthy controls showing lower levels of vitamins A and D associated with more severe disease. Patients with moderate and severe COVID-19 had significantly lower vitamin A, vitamin D, and retinol-binding protein 4 (RBP4) levels compared to those with mild disease and healthy controls. Lower vitamin A and D levels were associated with higher levels of inflammatory markers such as CRP, leukocytes, and ESR. Submit Corrections or Updates.
Early treatmentRCT · IRCT46974 · 180 patients · Iran · May – Sep 2020
Vitamin A for COVID-19
RCT 91 vitamin A and 91 control patients in Iran, showing improved recovery with treatment. All patients received HCQ. 25,000IU/day oral vitamin A for 10 days. Submit Corrections or Updates.
Prospective pilot study of 20 critically ill COVID-19 ICU patients showing high deficiency rates of 50-100% for vitamins A, B6, and D; zinc; and selenium at admission. Deficiencies of vitamins B6 and D, and low iron status, persisted after 3 weeks. Plasma levels of vitamins A and E, zinc, and selenium increased over time as inflammation resolved, suggesting redistribution may explain some observed deficiencies. All patients received daily micronutrient administration. Additional intravenous and oral micronutrient administration for 10 patients did not significantly impact micronutrient levels or deficiency rates, however authors note that the administered doses may be too low. The form of vitamin D is not specified but may have been cholecalciferol which is expected to have a very long onset of action compared to more appropriate forms such as calcifediol or calcitriol. Submit Corrections or Updates.
Retrospective 27 severe COVID-19 patients and 23 non-COVID-19 patients, showing significantly lower vitamin A levels in COVID-19 patients (0.37mg/L vs. 0.52 mg/L, p<0.001). 10 of 27 COVID-19 patients received vitamin A, with higher mortality. Group details are not provided but authors note that 8 of 10 had comorbidities. Submit Corrections or Updates.
Late treatmentDouble-blind RCT · 60 patients · Iran · Mar 2020 – Mar 2021
Vitamin A for COVID-19
Improved recovery with vitamin A
Not statistically significant · p = 0.53
RCT 90 outpatients with post-COVID-19 anosmia showing significant improvements in smell alterations with olfactory training after 3 and 12 months. Adding oral vitamin A to olfactory training resulted in higher rates of improvement, but the difference was not statistically significant. Submit Corrections or Updates.
Prospective analysis of 40 hospitalized patients and 47 age-matched convalescent patients, showing significantly lower vitamin A levels in critical patients, and significantly lower vitamin A levels in hospitalized patients vs. controls. Low vitamin A levels were significantly associated with ARDS and mortality in hospitalized patients. Submit Corrections or Updates.
SufficiencyRetrospective · 120 patients · Spain · Mar – May 2020
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Vitamin A
reduces risk
Vitamin A
increases risk →
Lower ventilation and ICU admission
p = 0.001 (ventilation) and p = 0.004 (ICU admission)
Retrospective 120 hospitalized patients in Spain showing vitamin A deficiency associated with higher ICU admission. Submit Corrections or Updates.
ProphylaxisRetrospective · 3,955 patients · Iran
Vitamin A for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Vitamin A
reduces risk
Vitamin A
increases risk →
Lower hospitalization and fewer symptomatic cases
p = 0.043 (hospitalization) and p = 0.033 (fewer symptomatic cases)
Analysis of nutrient intake and COVID-19 outcomes for 3,996 people in Iran, showing lower risk of COVID-19 hospitalization with sufficient vitamin A, vitamin C, and selenium intake, with statistical significance for vitamin A and selenium. Submit Corrections or Updates.
Prospective study of 57 consecutive hospitalized COVID-19 patients in Switzerland, showing higher risk of mortality/ICU admission with vitamin A, vitamin D, and zinc deficiency, with statistical significance only for vitamin A and zinc. Adjustments only considered age. Submit Corrections or Updates.
Computational drug repurposing study integrating genetically regulated gene expression (GReX) and pharmaceutical databases to identify 7 FDA-approved compounds that may reverse COVID-19-related gene expression.

Analysis of 755,346 people in the Veterans Health Administration cohort showed that retinol and azathioprine were associated with reduced incidence of COVID-19.

In vitro analysis showed nelfinavir and saquinavir inhibited SARS-CoV-2 replication by ~95% and ~65% respectively. Submit Corrections or Updates.
Mendelian randomization study suggesting a causal association between retinol and related proteins (RBP4, RDH16, CRABP1) and COVID-19. The study found that genetically-predicted higher retinol levels were associated with lower COVID-19 susceptibility. There was a lower risk of hospitalization and severity without statistical significance. Authors conclude that the results support a potential protective effect of vitamin A treatment for COVID-19. Given the lack of clear evidence for pleiotropy, and the lower precision of the MR-Egger estimates, the IVW estimates are likely more reliable in this case when the IVW and MR-Egger estimates differ. Submit Corrections or Updates.
We perform ongoing searches of PubMed, medRxiv, Europe PMC, ClinicalTrials.gov, The Cochrane Library, Google Scholar, Research Square, ScienceDirect, Oxford University Press, the reference lists of other studies and meta-analyses, and submissions to the site c19early.org, which regularly receives notification of studies upon publication. Search terms are vitamin A and COVID-19 or SARS-CoV-2. Automated searches are performed twice daily, with all matches reviewed for inclusion. All studies regarding the use of vitamin A for COVID-19 that report a comparison with a control group are included in the main analysis. Sensitivity analysis is performed, excluding studies with major issues, epidemiological studies, and studies with minimal available information. Studies with major unexplained data issues, for example major outcome data that is impossible to be correct with no response from the authors, are excluded.
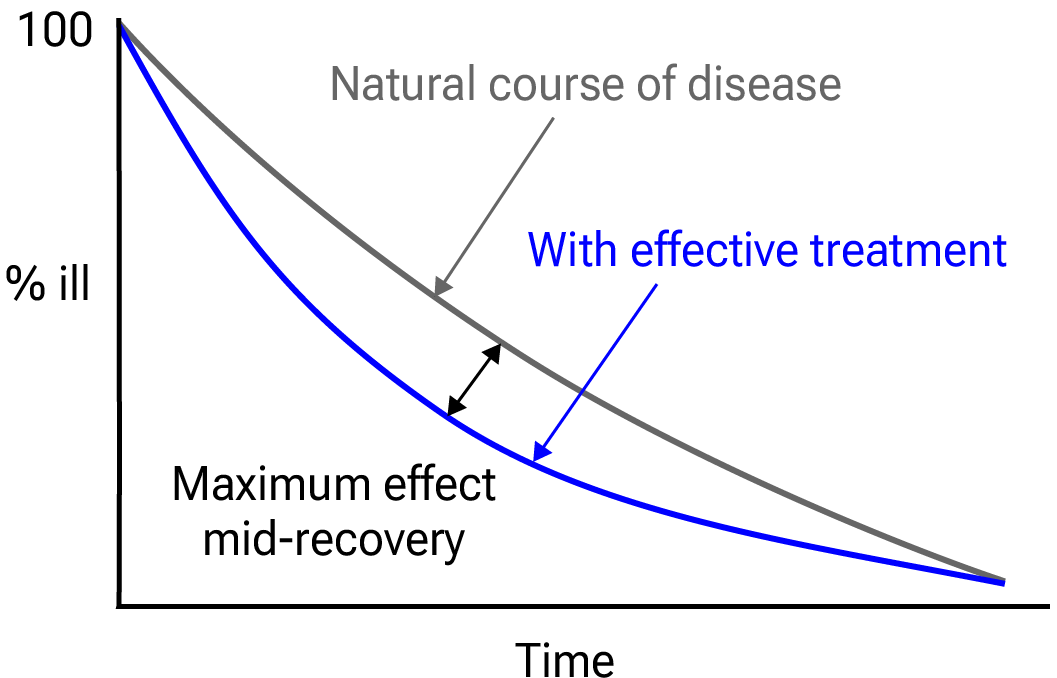
Fig. 31. Mid-recovery results can more accurately reflect efficacy when almost all patients recover. Mateja et al. confirm that intermediate viral load results more accurately reflect hospitalization/death.
We extracted effect sizes and associated data from all studies. If studies report multiple kinds of effects then the most serious outcome is used in pooled analysis, while other outcomes are included in the outcome-specific analyses. For example, if effects for mortality and cases are reported then they are both used in specific outcome analyses, while mortality is used for pooled analysis. If symptomatic results are reported at multiple times, we use the latest time, for example if mortality results are provided at 14 days and 28 days, the results at 28 days have preference. Mortality alone is preferred over combined outcomes. Outcomes with zero events in both arms are not used, the next most serious outcome with one or more events is used. For example, in low-risk populations with no mortality, a reduction in mortality with treatment is not possible, however a reduction in hospitalization, for example, is still valuable. Clinical outcomes are considered more important than viral outcomes. When basically all patients recover in both treatment and control groups, preference for viral clearance and recovery is given to results mid-recovery where available. After most or all patients have recovered there is little or no room for an effective treatment to do better, however faster recovery is valuable. An IPD meta-analysis confirms that intermediate viral load reduction is more closely associated with hospitalization/death than later viral load reduction185. If only individual symptom data is available, the most serious symptom has priority, for example difficulty breathing or low SpO2 is more important than cough.
Forest plots are computed using PythonMeta186 with the DerSimonian and Laird random-effects model (the fixed effect assumption is not plausible in this case) and inverse variance weighting. Results are presented with 95% confidence intervals. Heterogeneity among studies was assessed using the I2 statistic. When results provide an odds ratio, we compute the relative risk when possible, or convert to a relative risk according to Zhang et al. Reported confidence intervals and p-values are used when available, and adjusted values are used when provided. If multiple types of adjustments are reported propensity score matching and multivariable regression has preference over propensity score matching or weighting, which has preference over multivariable regression. Adjusted results have preference over unadjusted results for a more serious outcome when the adjustments significantly alter results. When needed, conversion between reported p-values and confidence intervals followed Altman, Altman (B), and Fisher's exact test was used to calculate p-values for event data. If continuity correction for zero values is required, we use the reciprocal of the opposite arm with the sum of the correction factors equal to 1190. Results are expressed with RR < 1.0 favoring treatment, and using the risk of a negative outcome when applicable (for example, the risk of death rather than the risk of survival). If studies only report relative continuous values such as relative times, the ratio of the time for the treatment group versus the time for the control group is used. Calculations are done in Python (3.15.0) with scipy (1.18.1), pythonmeta (1.26), numpy (2.5.4), statsmodels (0.15.0), and plotly (6.9.0). Mixed-effects meta-regression results are computed with R (4.4.0) using the metafor (4.6-0) and rms (6.8-0) packages, and using the most serious sufficiently powered outcome. For all statistical tests, a p-value less than 0.05 was considered statistically significant. Grobid 0.8.2 is used to parse PDF documents.
When evaluating potential effect modification across groups, we use an interaction test as described by Altman (C) et al. We compared the log-transformed relative risks using a z-test, deriving the standard error of the difference from the 95% confidence intervals. A two-sided interaction p-value of < 0.05 was considered a statistically significant difference in treatment effect between the groups.
Cochrane RoB 2/ROBINS-I are often used to evaluate studies, and have the advantage of providing standardized rules that can be applied with minimal understanding of the domain and study. However, the rules do not account for many real-world issues, often overemphasize or underemphasize others, and studies show low inter-rater reliability198. Certain domains are more applicable for these tools, however the time-sensitive nature of a pandemic, with significant mortality for every day of delay in evidence assessment, and the characteristics of COVID-19 make them inappropriate for this domain. This can be demonstrated with examples where expert RoB 2/ROBINS-I ratings do not match reality for COVID-19. Popp et al. use RoB 2 to classify Reis et al. as low risk of bias, however this is the opposite of reality—the trial not only has very high risk of bias, but has very high actual known bias, refusing to release data despite pledging to, reporting multiple impossible numbers, having blinding and randomization failure, and many other issues200. Axfors et al. use RoB 2 to classify Horby et al. as low risk of bias, however this is the opposite of reality—the very late treatment and excessive dosage used produces results with no relevance to recommended usage. HCQ shows poor results with late treatment and excessive dosage, and the combination shows harmD. Hempenius et al. use ROBINS-I to classify 33 studies for HCQ. The two rated as having the lowest risk of bias196,197 are far from the most informative. Both involve very late treatment, providing no information on recommended usage, and ROBINS-I does a very poor job of accounting for the impact of confounding factorsE.
Our quality evaluation focuses on known issues and bias, and the potential impact on outcomes, rather than just the risk of bias. The estimated potential impact of each confounding factor, and the direction of the impact is considered. For example, consider a study that shows significantly lower risk, the value of the study varies significantly if confounding points to an underestimate or an overestimate of efficacy. In one case, the real effect may be null, while the other case provides stronger evidence of efficacy (which may be greater than the study shows). Analysis focusing on the risk of bias, while simpler, may penalize studies for theoretical or technical issues that have no or minimal impact on outcomes. Analysis also depends on the outcome, for example certain issues are less relevant for objective outcomes such as mortality. Inaccurate penalization, and inaccurate high-quality evaluation in the face of known major issues affecting outcomes, increases in significance during a pandemic when immediate recognition of new evidence is critical, and when considering all global studies, as required during a pandemic. Investigators in other countries may have different customs for design, analysis, and reporting, and different English language skills, however they may not be less diligent or have greater bias. Investigators in lower-pharmaceutical-profit countries may have lower bias towards profitable interventions.
We have classified studies as early treatment if most patients are not already at a severe stage at the time of treatment (for example based on oxygen status or lung involvement), and treatment started within 5 days of the onset of symptoms. If studies contain a mix of early treatment and late treatment patients, we consider the treatment time of patients contributing most to the events (for example, consider a study where most patients are treated early but late treatment patients are included, and all mortality events were observed with late treatment patients). We note that a shorter time may be preferable. Antivirals are typically only considered effective when used within a shorter timeframe, for example 0-36 or 0-48 hours for oseltamivir, with longer delays not being effective85,86.
This is a living analysis and is updated regularly. Submit updates or corrections with the form below. We received no funding, this research is done in our spare time. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
A summary of study results is below. Please submit updates and corrections at the bottom of this page.
A summary of study results is below. Please submit updates and corrections at https://c19early.org/vameta.html.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
Al-Sumiadai (B), 1/31/2021, prospective, Iraq, preprint, 3 authors. risk of progression, 66.7% lower, RR 0.33, p = 0.27, treatment 2 of 50 (4.0%), control 6 of 50 (12.0%), NNT 13, progression to severe disease.
Al-Sumiadai, 12/31/2020, retrospective, Iraq, peer-reviewed, 3 authors, excluded in exclusion analyses: minimal details of groups provided. risk of death, 85.7% lower, RR 0.14, p = 0.002, treatment 2 of 70 (2.9%), control 14 of 70 (20.0%), NNT 5.8.
Rohani, 8/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, mean age 39.4, 6 authors, study period 1 May, 2020 - 1 September, 2020, trial IRCT46974. risk of hospitalization, 25.6% lower, RR 0.74, p = 0.63, treatment 8 of 89 (9.0%), control 11 of 91 (12.1%), NNT 32.
risk of no recovery, 31.8% lower, RR 0.68, p = 0.53, treatment 4 of 89 (4.5%), control 6 of 91 (6.6%), NNT 48, dyspnea.
risk of no recovery, 79.6% lower, RR 0.20, p = 0.03, treatment 2 of 89 (2.2%), control 10 of 91 (11.0%), NNT 11, fever.
risk of no recovery, 87.2% lower, RR 0.13, p = 0.01, treatment 1 of 89 (1.1%), control 8 of 91 (8.8%), NNT 13, body ache.
risk of no recovery, 48.9% lower, RR 0.51, p = 0.32, treatment 3 of 89 (3.4%), control 6 of 91 (6.6%), NNT 31, headache.
risk of no recovery, 62.8% lower, RR 0.37, p = 0.05, treatment 4 of 89 (4.5%), control 11 of 91 (12.1%), NNT 13, weakness and fatigue.
risk of no recovery, 20.5% lower, RR 0.80, p = 0.63, treatment 7 of 89 (7.9%), control 9 of 91 (9.9%), NNT 49, chest pain.
risk of no recovery, 40.4% lower, RR 0.60, p = 0.24, treatment 7 of 89 (7.9%), control 12 of 91 (13.2%), NNT 19, cough.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
Beigmohammadi, 11/14/2021, Single Blind Randomized Controlled Trial, Iran, peer-reviewed, 6 authors, study period April 2020 - July 2020, this trial uses multiple treatments in the treatment arm (combined with vitamins B, C, D, E) - results of individual treatments may vary, trial IRCT20200319046819N1. risk of death, 88.9% lower, RR 0.11, p = 0.11, treatment 0 of 30 (0.0%), control 4 of 30 (13.3%), NNT 7.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of hospitalization >7 days, 41.0% lower, RR 0.59, p = 0.25, treatment 4 of 30 (13.3%), control 16 of 30 (53.3%), NNT 2.5, adjusted per study, odds ratio converted to relative risk.
relative SOFA score @day 7, 45.5% better, RR 0.55, p < 0.001, treatment 30, control 30.
Chung, 6/30/2023, Randomized Controlled Trial, China, peer-reviewed, 14 authors, study period 14 August, 2020 - 11 June, 2021, trial NCT04900415 (history). relative BTT improvement, 75.1% better, RR 0.25, p = 0.048, treatment mean 3.01 (±2.52) n=9, control mean 0.75 (±1.67) n=8, vitamin A + OT vs. OT.
anosmia, 68.0% lower, RR 0.32, p = 0.47, treatment 0 of 9 (0.0%), control 1 of 8 (12.5%), NNT 8.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), vitamin A + OT vs. OT.
severe microsmia, 70.4% lower, RR 0.30, p = 0.29, treatment 1 of 9 (11.1%), control 3 of 8 (37.5%), NNT 3.8, vitamin A + OT vs. OT.
moderate microsmia, 74.6% lower, RR 0.25, p = 0.02, treatment 2 of 9 (22.2%), control 7 of 8 (87.5%), NNT 1.5, vitamin A + OT vs. OT.
Doocy, 10/19/2022, prospective, multiple countries, peer-reviewed, 6 authors, study period December 2020 - June 2021, average treatment delay 7.8 days, trial NCT04568499 (history), excluded in exclusion analyses: unadjusted results with no group details. risk of death, 26.1% lower, RR 0.74, p = 1.00, treatment 1 of 8 (12.5%), control 23 of 136 (16.9%), NNT 23, unadjusted.
Sarohan, 2/1/2021, retrospective, Turkey, preprint, 4 authors, excluded in exclusion analyses: unadjusted results with no group details, comments suggest significant group differences and confounding. risk of death, 282.5% higher, RR 3.83, p = 0.001, treatment 9 of 10 (90.0%), control 4 of 17 (23.5%).
Somi, 10/7/2022, Randomized Controlled Trial, Iran, peer-reviewed, mean age 60.2, 7 authors, study period April 2020 - July 2020, trial IRCT20170117032004N3, excluded: multiple data issues - pending author response. risk of death, 50.0% higher, RR 1.50, p = 1.00, treatment 3 of 15 (20.0%), control 2 of 15 (13.3%).
risk of mechanical ventilation, no change, RR 1.00, p = 1.00, treatment 3 of 15 (20.0%), control 3 of 15 (20.0%).
risk of ICU admission, 25.0% lower, RR 0.75, p = 1.00, treatment 3 of 15 (20.0%), control 4 of 15 (26.7%), NNT 15.
time to clinical response, 76.0% higher, HR 1.76, p = 0.21, treatment 15, control 15, Kaplan-Meier.
hospitalization time, 8.1% higher, relative time 1.08, p = 0.49, treatment mean 7.33 (±2.31) n=15, control mean 6.78 (±1.84) n=15.
Taheri, 6/3/2024, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, 6 authors, study period March 2020 - March 2021, post-COVID anosmia. risk of no recovery, 37.5% lower, RR 0.62, p = 0.53, treatment 5 of 30 (16.7%), control 8 of 30 (26.7%), NNT 10.0, 12 months.
risk of no recovery, 42.9% lower, RR 0.57, p = 0.51, treatment 4 of 30 (13.3%), control 7 of 30 (23.3%), NNT 10.0, 3 months.
risk of anosmia, 66.7% lower, RR 0.33, p = 1.00, treatment 0 of 30 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 12 months.
risk of anosmia, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 30 (0.0%), control 3 of 30 (10.0%), NNT 10.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 3 months.
risk of anosmia/severe hyposmia, 88.9% lower, RR 0.11, p = 0.11, treatment 0 of 30 (0.0%), control 4 of 30 (13.3%), NNT 7.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 12 months.
risk of anosmia/severe hyposmia, 88.9% lower, RR 0.11, p = 0.11, treatment 0 of 30 (0.0%), control 4 of 30 (13.3%), NNT 7.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 3 months.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
Al-Sumiadai (C), 1/31/2021, prospective, Iraq, preprint, 3 authors. risk of case, 64.5% lower, RR 0.36, p < 0.001, treatment 20 of 97 (20.6%), control 65 of 112 (58.0%), NNT 2.7.
Holt, 3/30/2021, prospective, United Kingdom, peer-reviewed, 34 authors, study period 1 May, 2020 - 5 February, 2021, trial NCT04330599 (history) (COVIDENCE UK), excluded in exclusion analyses: significant unadjusted confounding possible. risk of case, 56.3% lower, RR 0.44, p = 0.41, treatment 1 of 91 (1.1%), control 445 of 15,136 (2.9%), NNT 54, adjusted per study, odds ratio converted to relative risk, minimally adjusted, group sizes approximated.
Nimer, 2/28/2022, retrospective, Jordan, peer-reviewed, survey, 4 authors, study period March 2021 - July 2021. risk of hospitalization, 21.2% lower, RR 0.79, p = 0.40, treatment 15 of 144 (10.4%), control 204 of 2,004 (10.2%), adjusted per study, odds ratio converted to relative risk, multivariable.
risk of severe case, 20.8% lower, RR 0.79, p = 0.36, treatment 17 of 144 (11.8%), control 243 of 2,004 (12.1%), adjusted per study, odds ratio converted to relative risk, multivariable.
Vaisi, 5/11/2023, retrospective, Iran, peer-reviewed, 5 authors. risk of hospitalization, 16.7% lower, HR 0.83, p = 0.04, treatment 1,140, control 2,815, adjusted per study, inverted to make HR<1 favor treatment, sufficient vs. insufficient intake, multivariable, Cox proportional hazards.
risk of symptomatic case, 10.6% lower, HR 0.89, p = 0.03, treatment 1,140, control 2,815, adjusted per study, inverted to make HR<1 favor treatment, sufficient vs. insufficient intake, multivariable, Cox proportional hazards.
Voloudakis, 1/14/2025, retrospective, USA, preprint, 21 authors. risk of case, 19.0% lower, OR 0.81, p < 0.001, adjusted per study, multivariable, RR approximated with OR.
Wang (B), 4/26/2024, retrospective, multiple countries, peer-reviewed, 6 authors, Mendelian - per SD. risk of severe case, 35.0% lower, OR 0.65, p = 0.28, IVW, RR approximated with OR, per SD.
risk of hospitalization, 24.0% lower, OR 0.76, p = 0.29, IVW, RR approximated with OR, per SD.
risk of case, 31.0% lower, OR 0.69, p = 0.006, IVW, RR approximated with OR, per SD.
Viral infection and replication involves attachment, entry, uncoating and release, genome replication and transcription, translation and protein processing, assembly and budding, and release. Each step can be disrupted by therapeutics.
Monoclonal antibodies were previously included. Other treatments such as dexamethasone, tocilizumab, and baricitinib were recommended for late stage hospitalized patients.
Smoking was known to cause lung cancer since at least 1939, but this was not widely recognized in the US until 1964, 25 years later. Surgeon general Leroy Burney tried publicizing the danger starting in 1957, with limited success. Surgeon general Luther Terry, appointed in 1961, prompted by President Kennedy in 1962 amid pressure from health advocates, finally got recognition in 1964. The 1964 report reviewed 7,000+ studies, but these could (and should) have been reviewed and acted upon in real-time as they were published. Historians attribute the 25 year delay to an industry campaign to manufacture doubt and controversy, through tactics like funding biased and fraudulent research from "independent" organizations, attacking scientists, and political lobbying. The success of the industry campaign is only possible because officials did not analyze the research in detail. Fraudulent industry research supported prior failures, but would have been called out as fraudulent by officials that analyzed and understood the research in real-time.
When administered late in infection, HCQ may enhance viral egress by further increasing lysosomal pH beyond the effect of ORF3a's water channel activity, thereby promoting lysosomal exocytosis, inactivating degradative enzymes, and facilitating the release of SARS-CoV-2 particles into the extracellular environment192,193. Research also suggests potential cardioprotective effects at lower doses, but cardiotoxicity with excessive dosage194. Bobrowski et al. also indicate negative effects if HCQ and remdesivir are combined.
Peters (B) et al. is subject to confounding by calendar-time (SOC evolved rapidly early in the pandemic, the linear covariate does not reflect non-linear SOC changes and hospital specific effects), hospital type (non-treatment hospitals were tertiary university centers), confounding by indication (4/7 hospitals initiated treatment on deterioration), immortal-time bias for as-treated (exposure assigned after baseline), significant differences for other experimental treatments, potential overadjustment from collider bias (steroid use and indication bias), limited baseline severity information, differences in hospice referral propensity across hospitals, unadjusted difference in time from onset to admission, difference in PCR positivity, and other factors. Mahévas et al. is subject to confounding by hospital (treatment highly dependent on the hospital, different SOC/ICU transfer practices, not included in PS), immortal time (only partly addressed in sensitivity analysis), co-treatment differences, calendar-time (SOC evolved rapidly early in the pandemic), binary coding for age (age ≥65 despite steep age-risk gradient), residual imbalance (variables dropped from PS), a composite outcome dependent on hospital triage/capacity, and other factors.