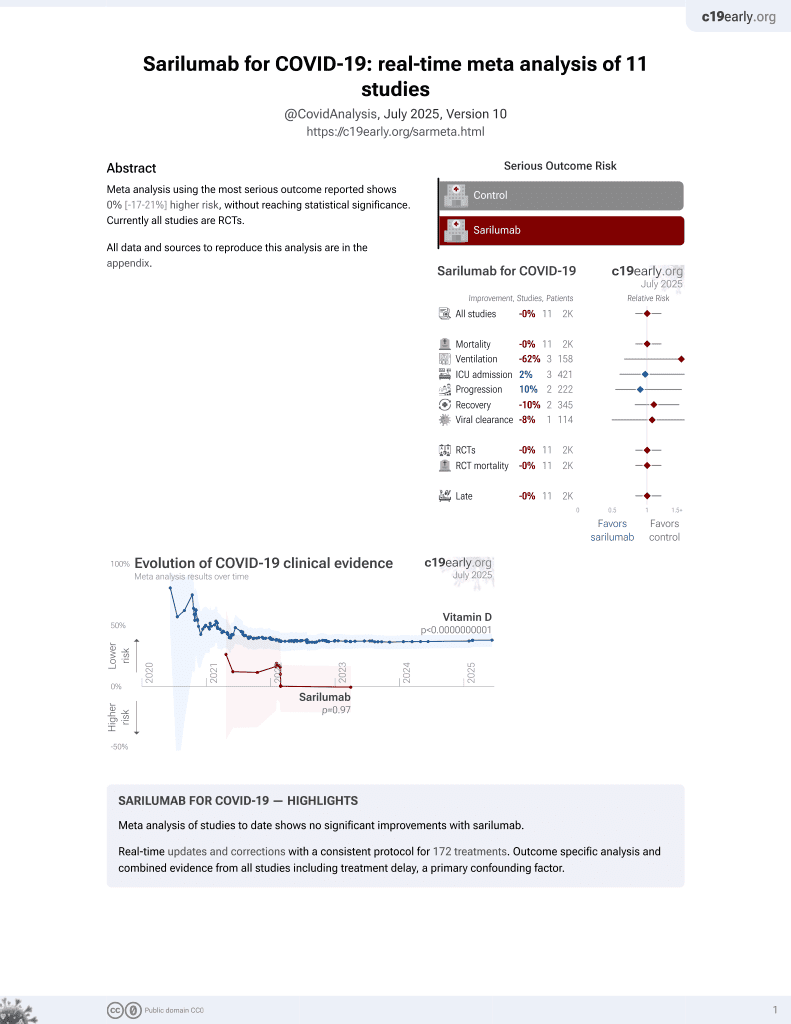
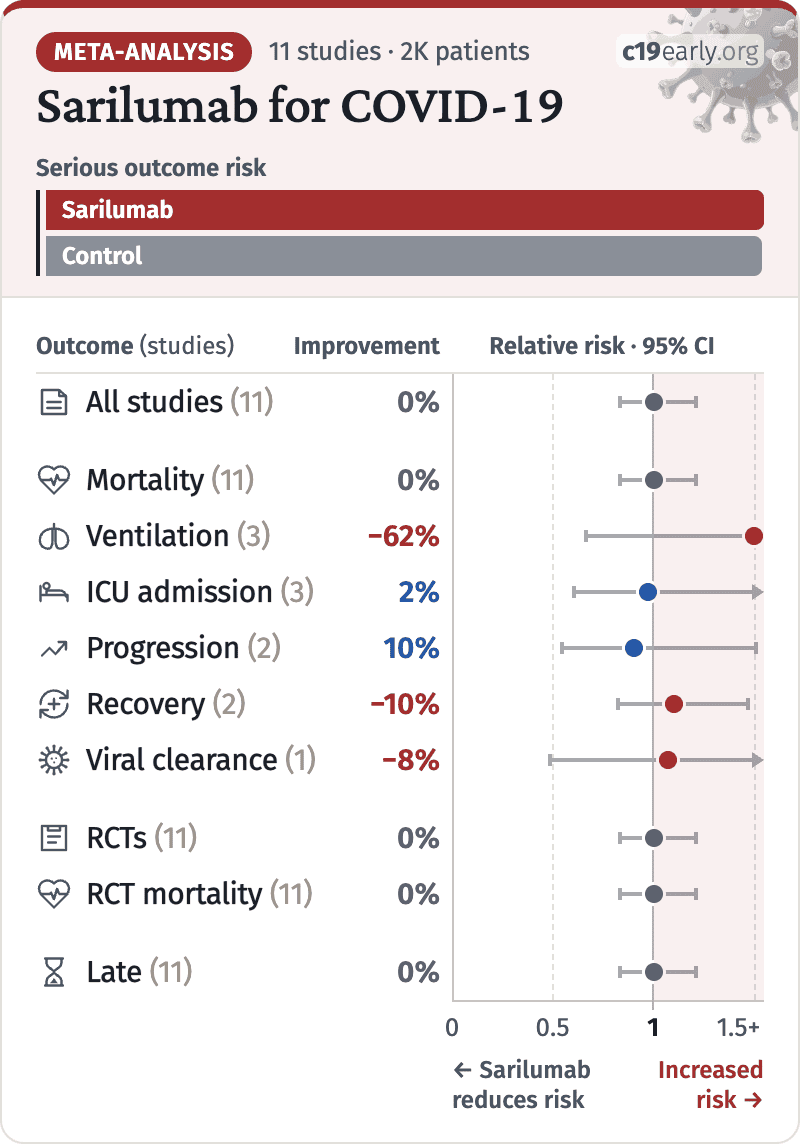
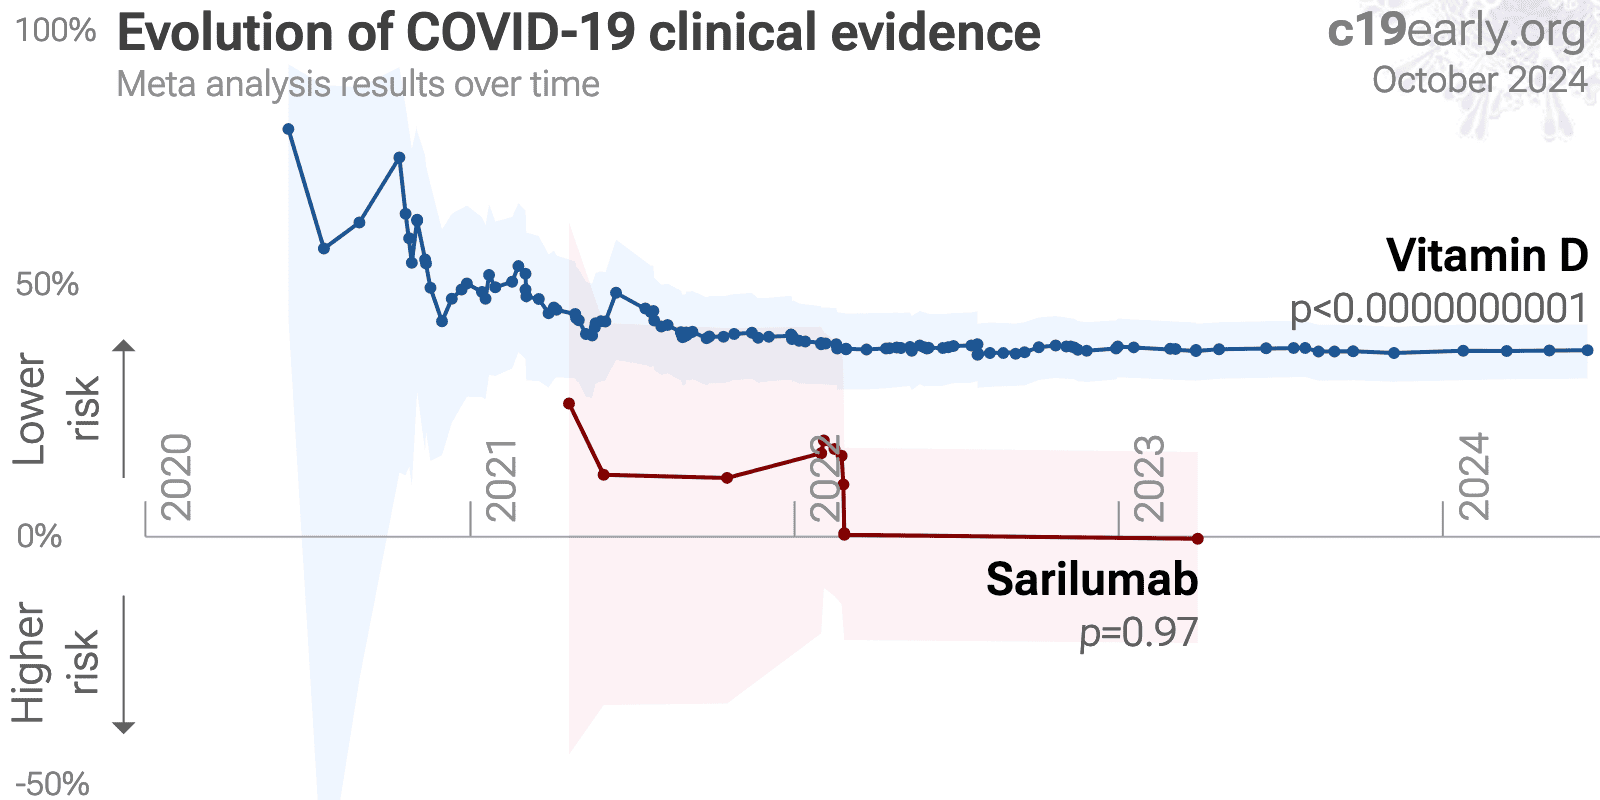
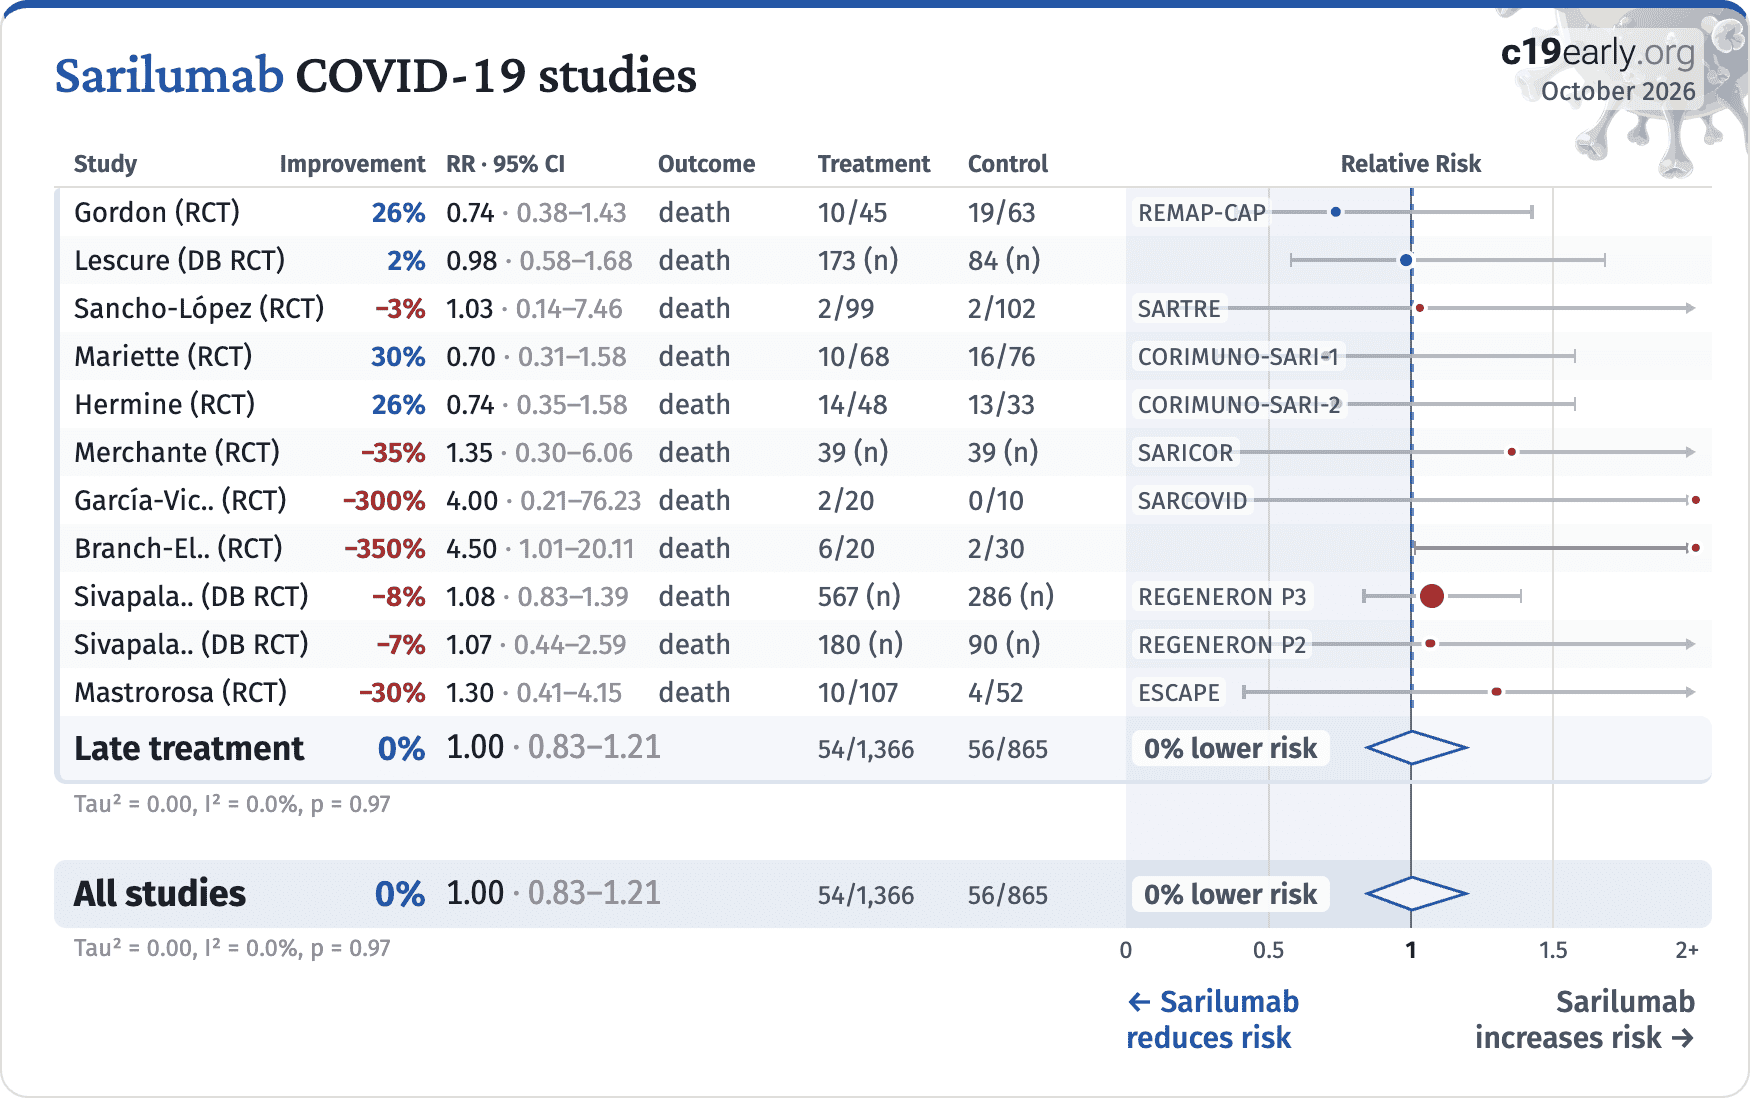
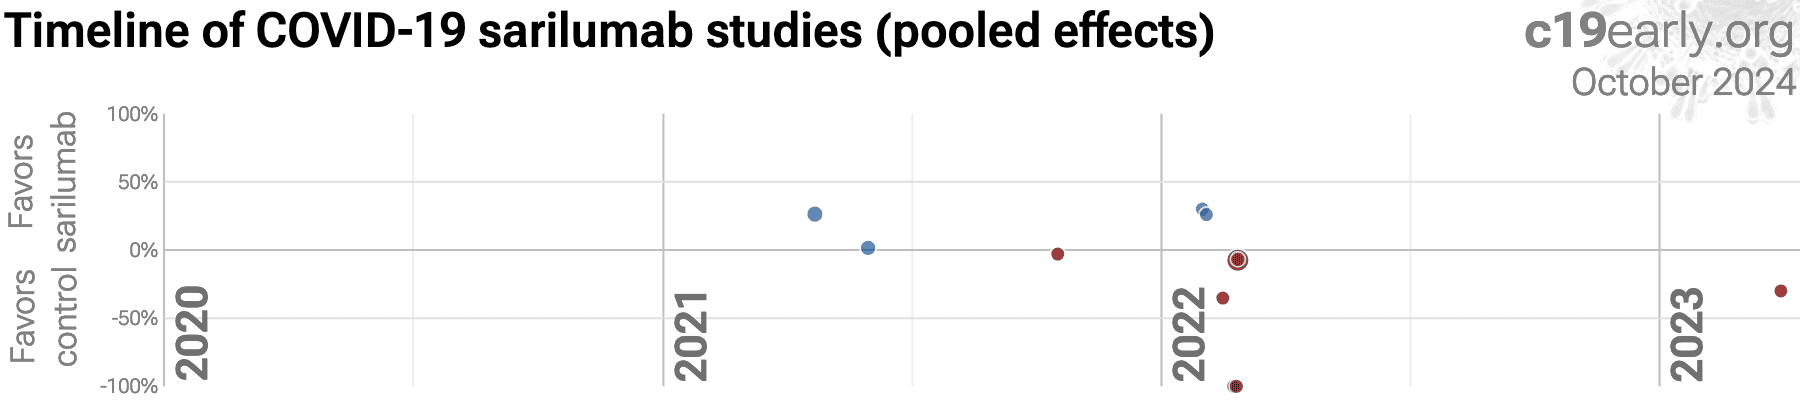
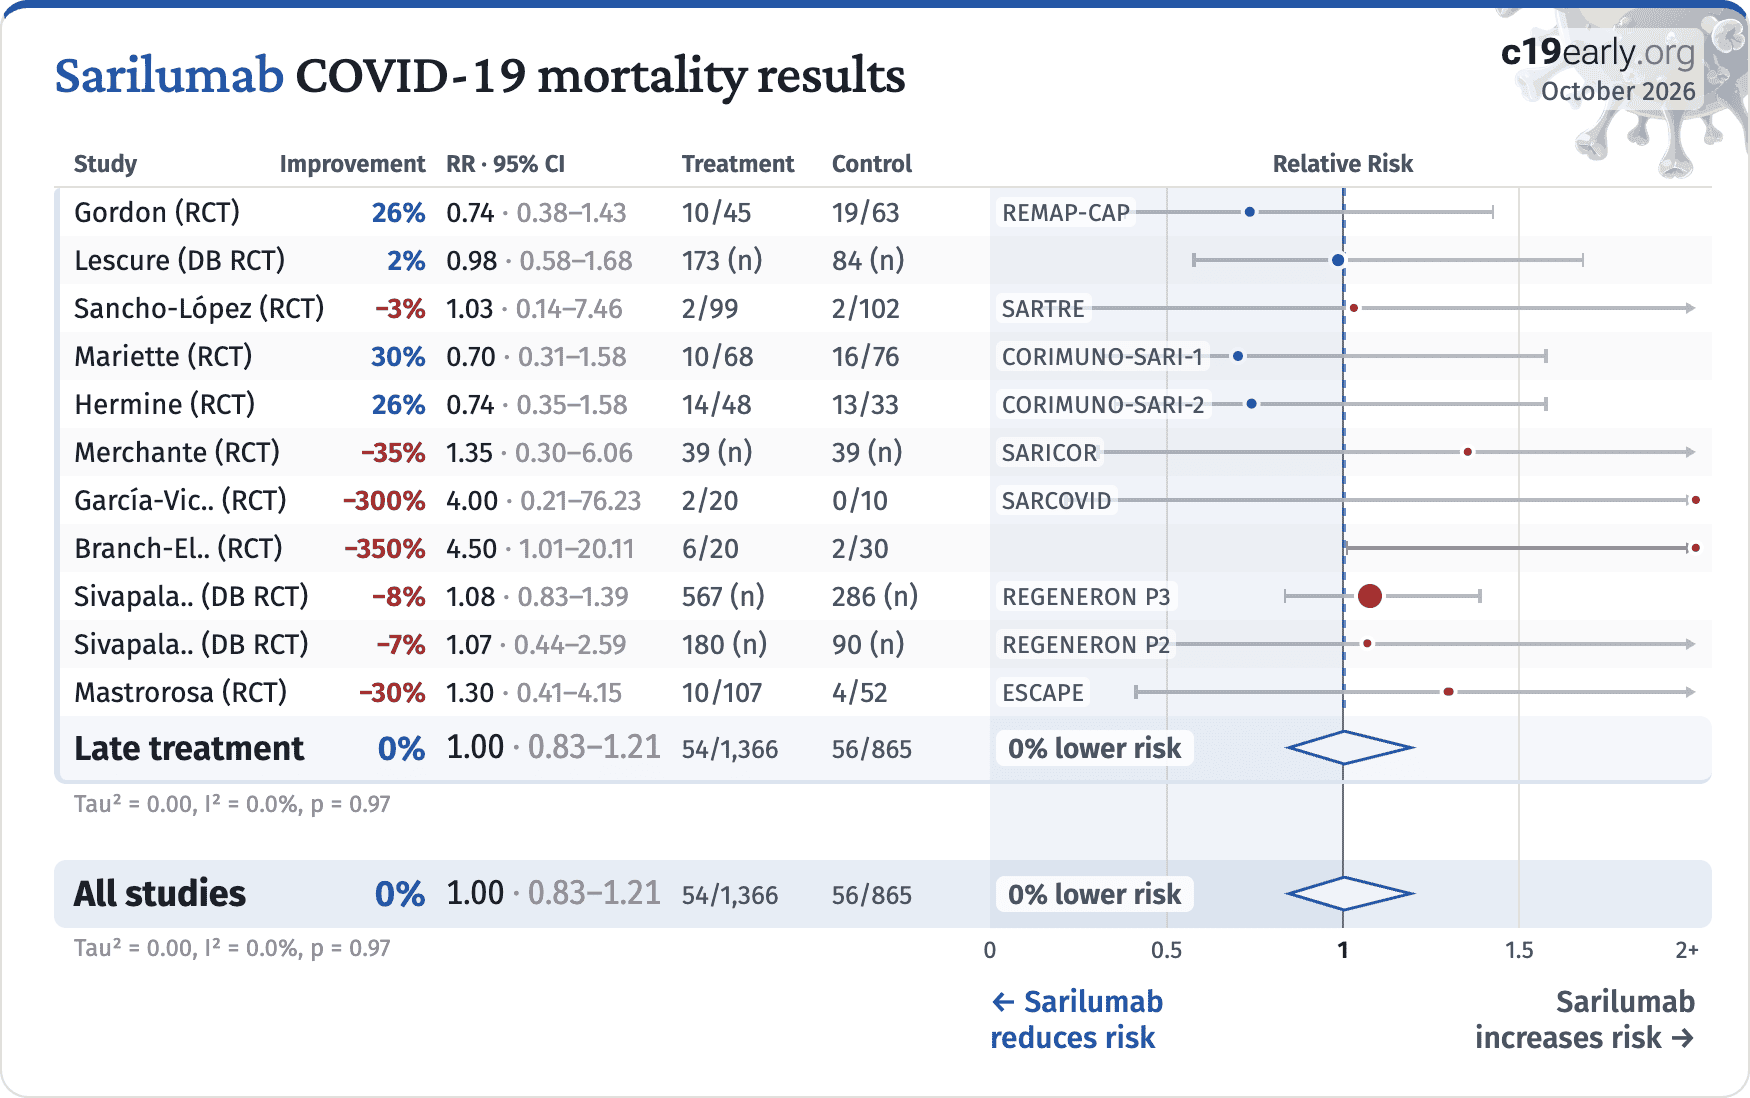
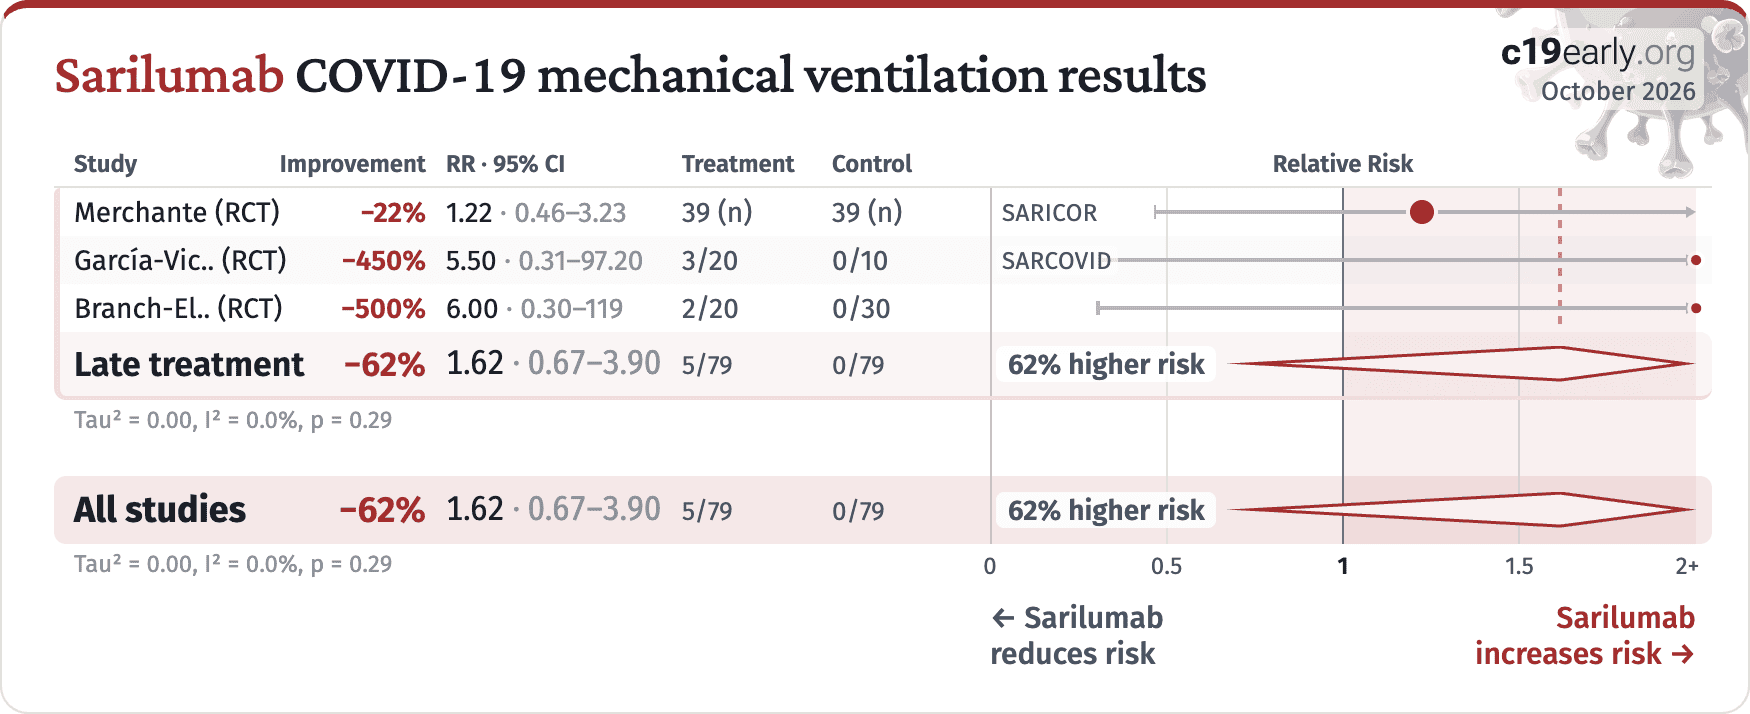
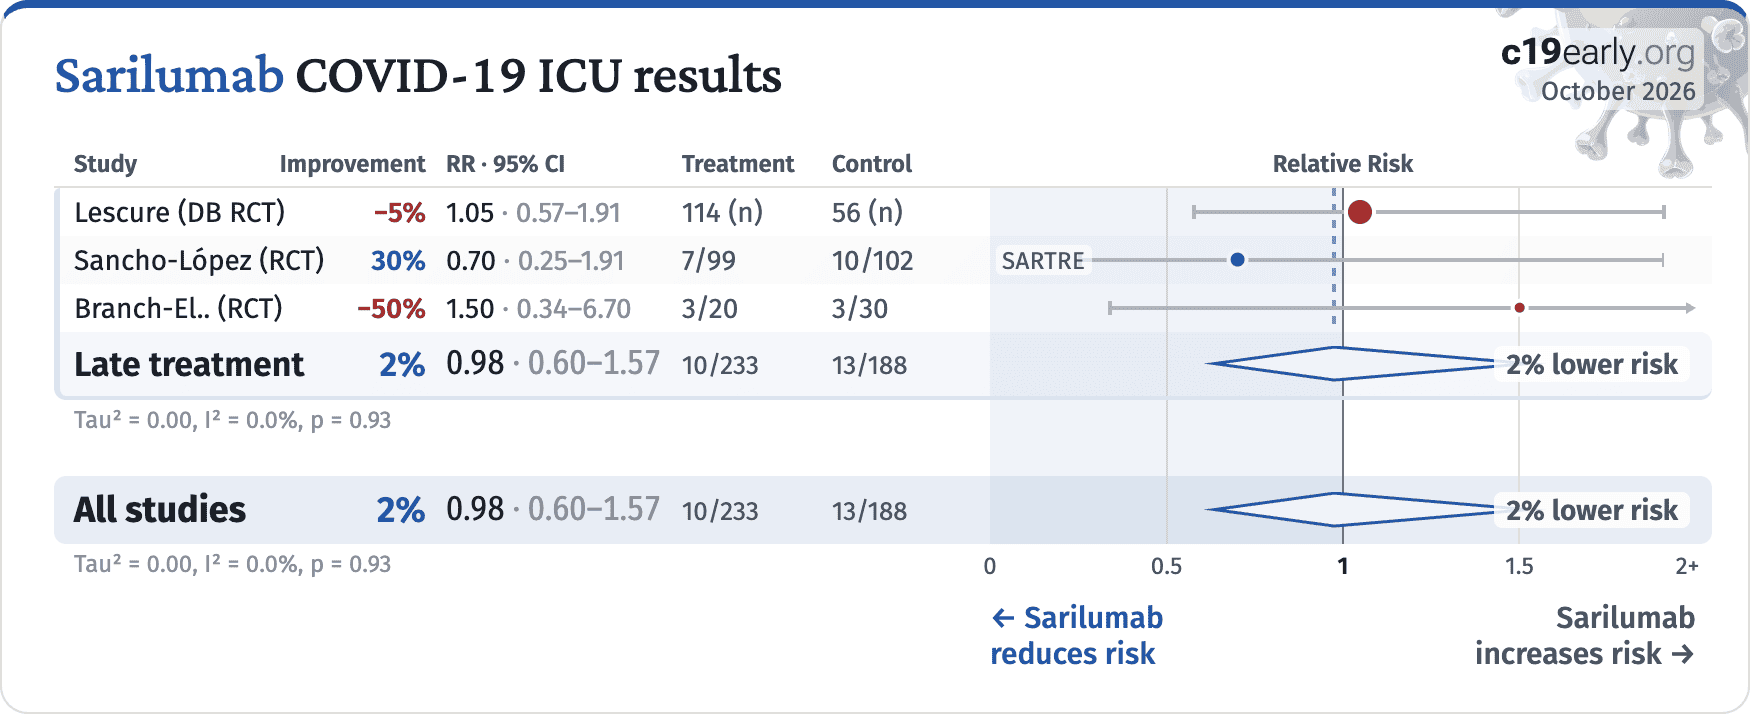
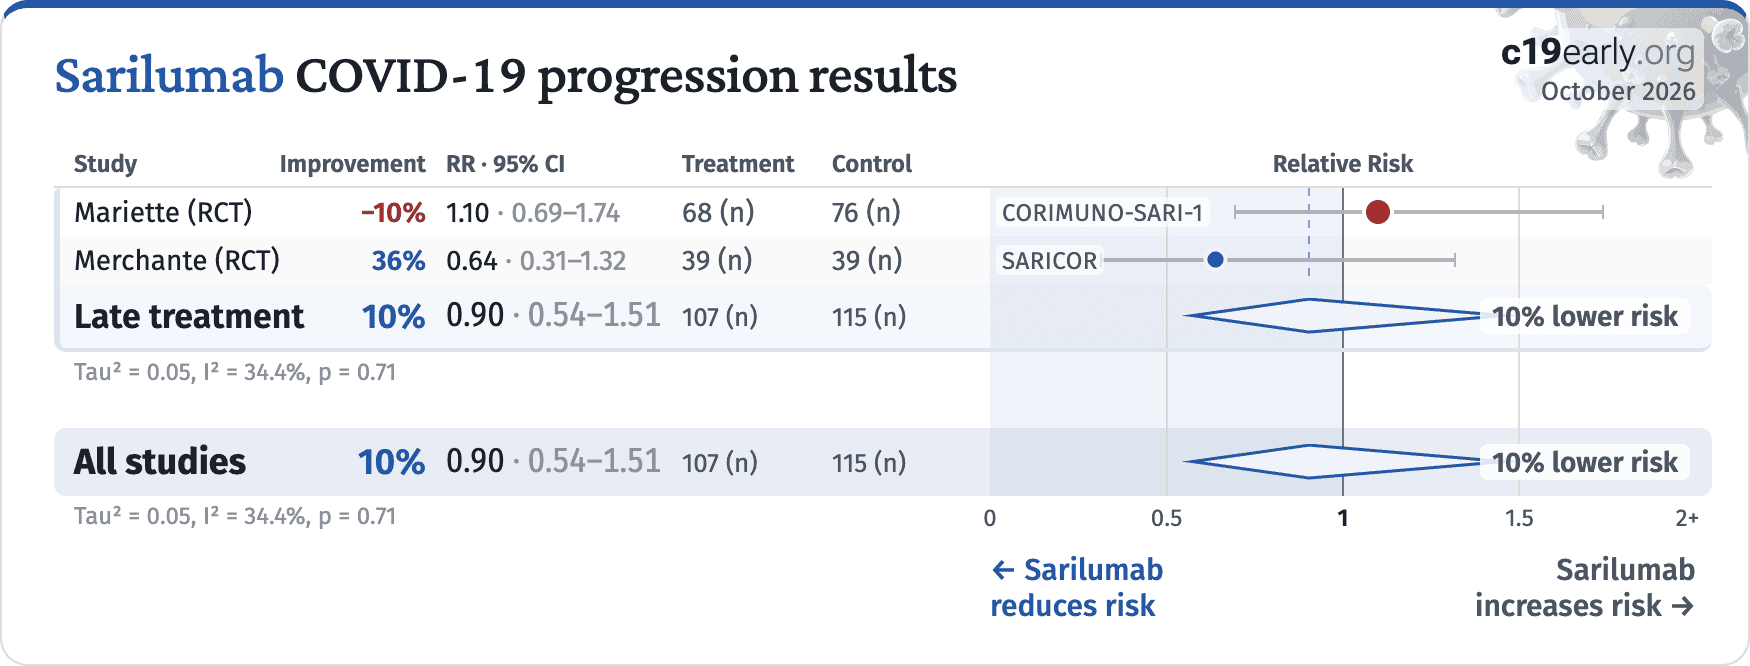
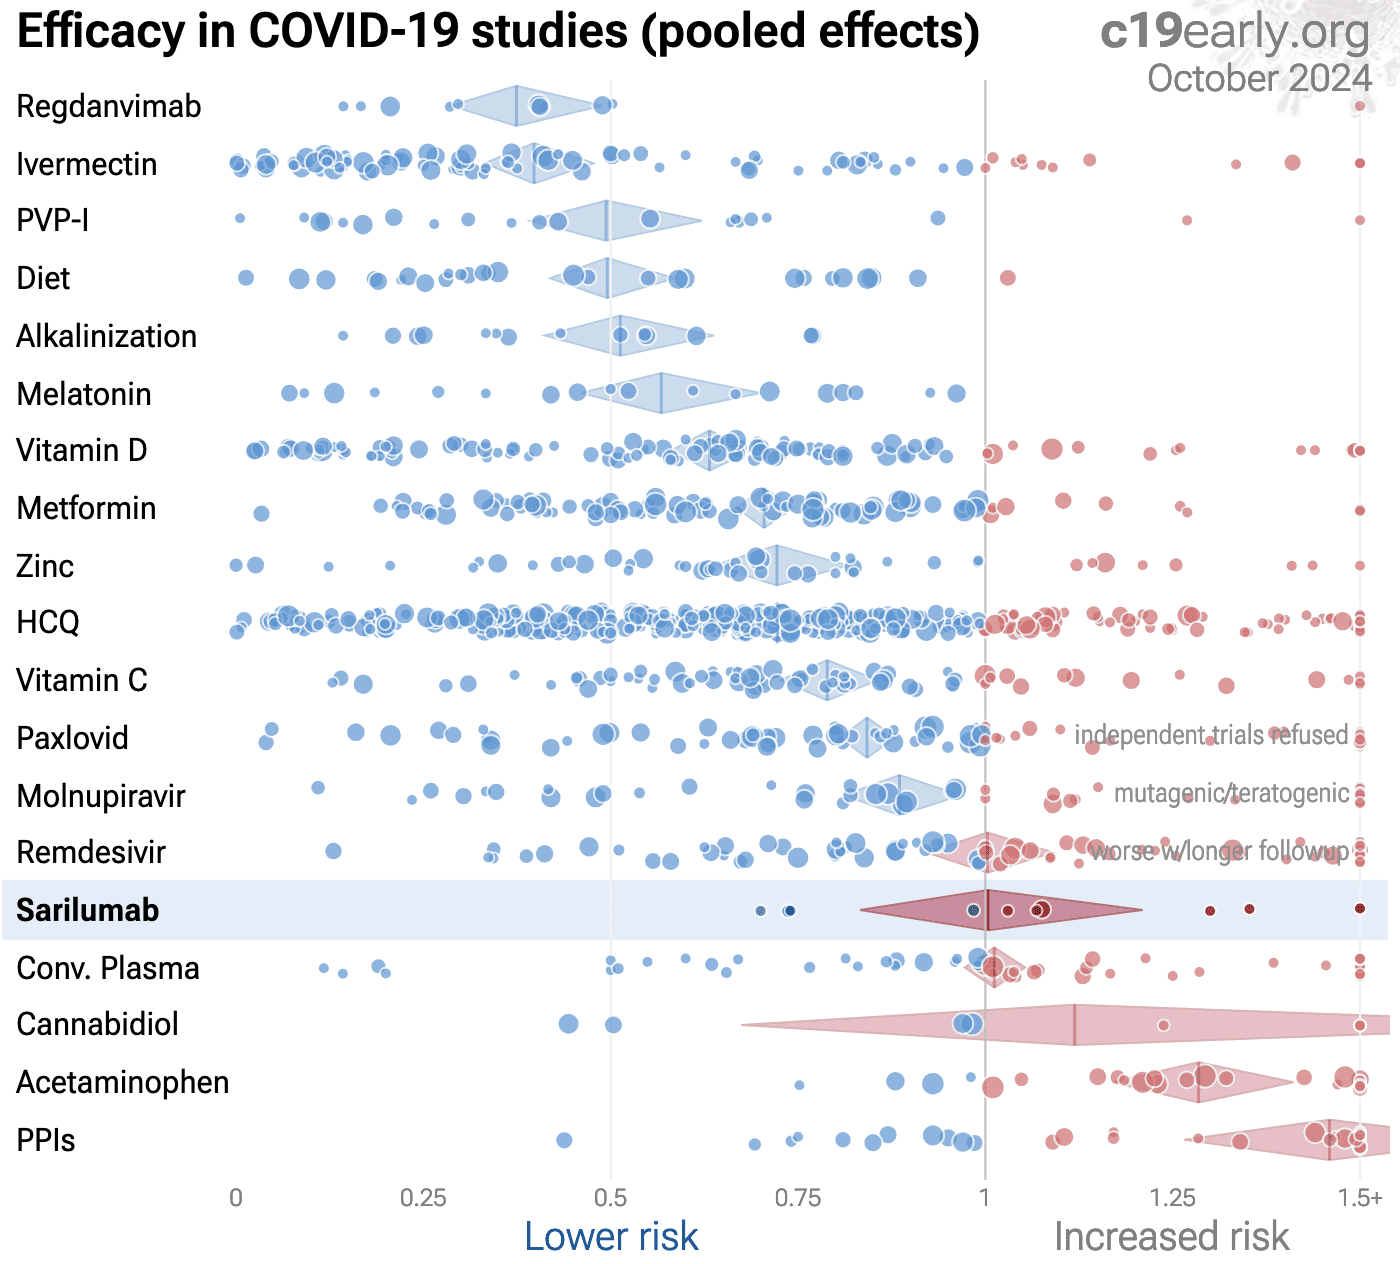
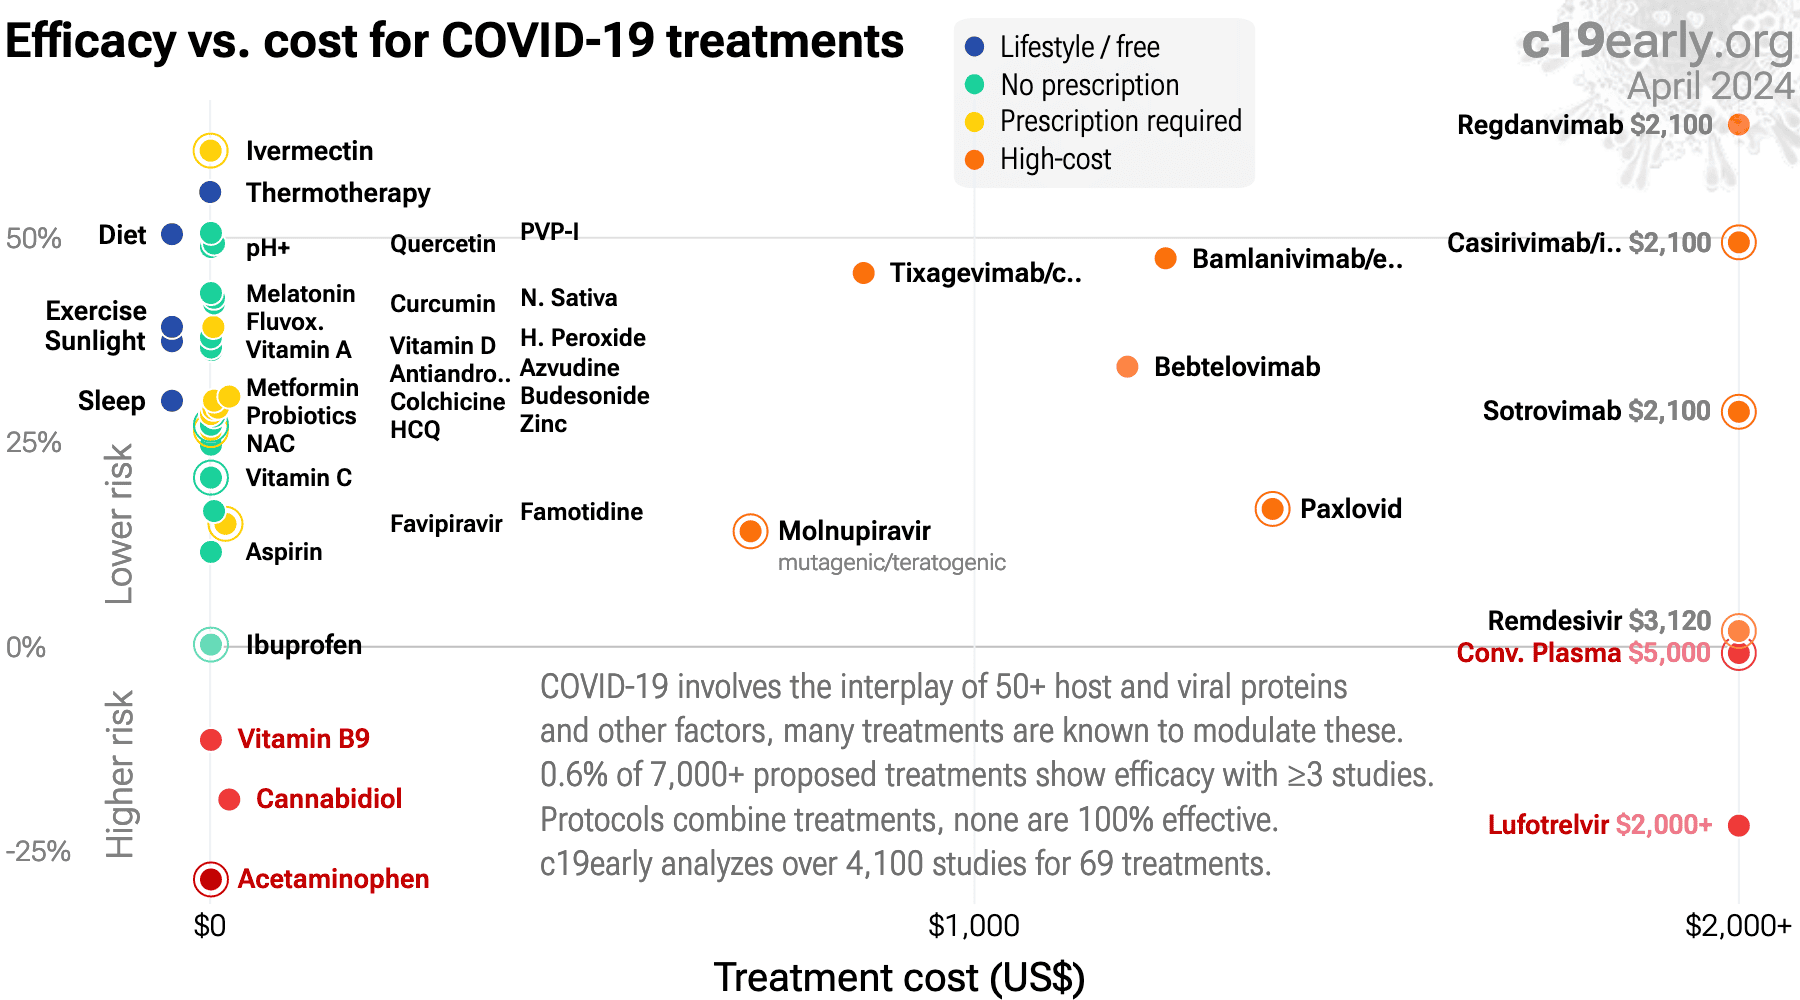
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/sarmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Branch-Elliman, 2/25/2022, Randomized Controlled Trial, USA, peer-reviewed, mean age 72.3, 21 authors, study period 10 April, 2020 - 3 February, 2021, trial NCT04359901 (history).
|
risk of death, 350.0% higher, RR 4.50, p = 0.047, treatment 6 of 20 (30.0%), control 2 of 30 (6.7%), day 30.
|
|
risk of death/intubation, 650.0% higher, RR 7.50, p = 0.03, treatment 5 of 20 (25.0%), control 1 of 30 (3.3%), day 14, primary outcome.
|
|
risk of mechanical ventilation, 500.0% higher, RR 6.00, p = 0.16, treatment 2 of 20 (10.0%), control 0 of 30 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 14.
|
|
risk of ICU admission, 50.0% higher, RR 1.50, p = 0.67, treatment 3 of 20 (15.0%), control 3 of 30 (10.0%), day 30.
|
|
García-Vicuña, 2/23/2022, Randomized Controlled Trial, Spain, peer-reviewed, median age 61.5, 13 authors, study period 13 April, 2020 - 30 October, 2020, trial NCT04357808 (history) (SARCOVID).
|
risk of death, 300.0% higher, RR 4.00, p = 0.54, treatment 2 of 20 (10.0%), control 0 of 10 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of mechanical ventilation, 450.0% higher, RR 5.50, p = 0.53, treatment 3 of 20 (15.0%), control 0 of 10 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
relative median improvement in clinical status, 33.3% worse, RR 1.33, p = 0.36, treatment 20, control 10, day 14.
|
|
relative median improvement in clinical status, 50.0% worse, RR 1.50, p = 0.32, treatment 20, control 10, day 7.
|
|
Gordon, 4/22/2021, Randomized Controlled Trial, multiple countries, peer-reviewed, 62 authors, trial NCT02735707 (history) (REMAP-CAP).
|
risk of death, 26.3% lower, RR 0.74, p = 0.39, treatment 10 of 45 (22.2%), control 19 of 63 (30.2%), NNT 13, concurrent control patients.
|
|
risk of death, 50.2% lower, HR 0.50, p = 0.048, treatment 45, control 397, inverted to make HR<1 favor treatment, including non-concurrent control patients.
|
|
Hermine, 2/3/2022, Randomized Controlled Trial, France, peer-reviewed, 6 authors, study period 31 March, 2020 - 20 April, 2020, trial NCT04324073 (history) (CORIMUNO-SARI-2).
|
risk of death, 26.0% lower, HR 0.74, p = 0.44, treatment 14 of 48 (29.2%), control 13 of 33 (39.4%), NNT 9.8.
|
|
Lescure, 5/31/2021, Double Blind Randomized Controlled Trial, placebo-controlled, multiple countries, peer-reviewed, median age 59.0, 8 authors, study period 28 March, 2020 - 3 July, 2020, trial NCT04327388 (history).
|
risk of death, 1.6% lower, RR 0.98, p = 0.96, treatment 173, control 84, all patients.
|
|
risk of death, 2.9% lower, RR 0.97, p = 1.00, treatment 18 of 173 (10.4%), control 9 of 84 (10.7%), NNT 323, 400mg, day 60, Table S6.
|
|
risk of death, 0.2% lower, RR 1.00, p = 1.00, treatment 17 of 159 (10.7%), control 9 of 84 (10.7%), NNT 4452, 200mg, day 60, Table S6.
|
|
risk of ICU admission, 4.7% higher, RR 1.05, p = 0.89, treatment 114, control 56, all patients.
|
|
risk of ICU admission, 19.3% higher, RR 1.19, p = 0.82, treatment 17 of 114 (14.9%), control 7 of 56 (12.5%), 400mg, day 60, Table S6.
|
|
risk of ICU admission, 10.2% lower, RR 0.90, p = 0.80, treatment 11 of 98 (11.2%), control 7 of 56 (12.5%), NNT 78, 200mg, day 60, Table S6.
|
|
risk of no improvement, 7.9% lower, HR 0.92, p = 0.47, treatment 173, control 84, all patients.
|
|
risk of no improvement, 12.3% lower, HR 0.88, p = 0.40, treatment 173, control 84, inverted to make HR<1 favor treatment, 400mg, day 29, Table 2.
|
|
risk of no improvement, 2.9% lower, HR 0.97, p = 0.86, treatment 159, control 84, inverted to make HR<1 favor treatment, 200mg, day 29, Table 2.
|
|
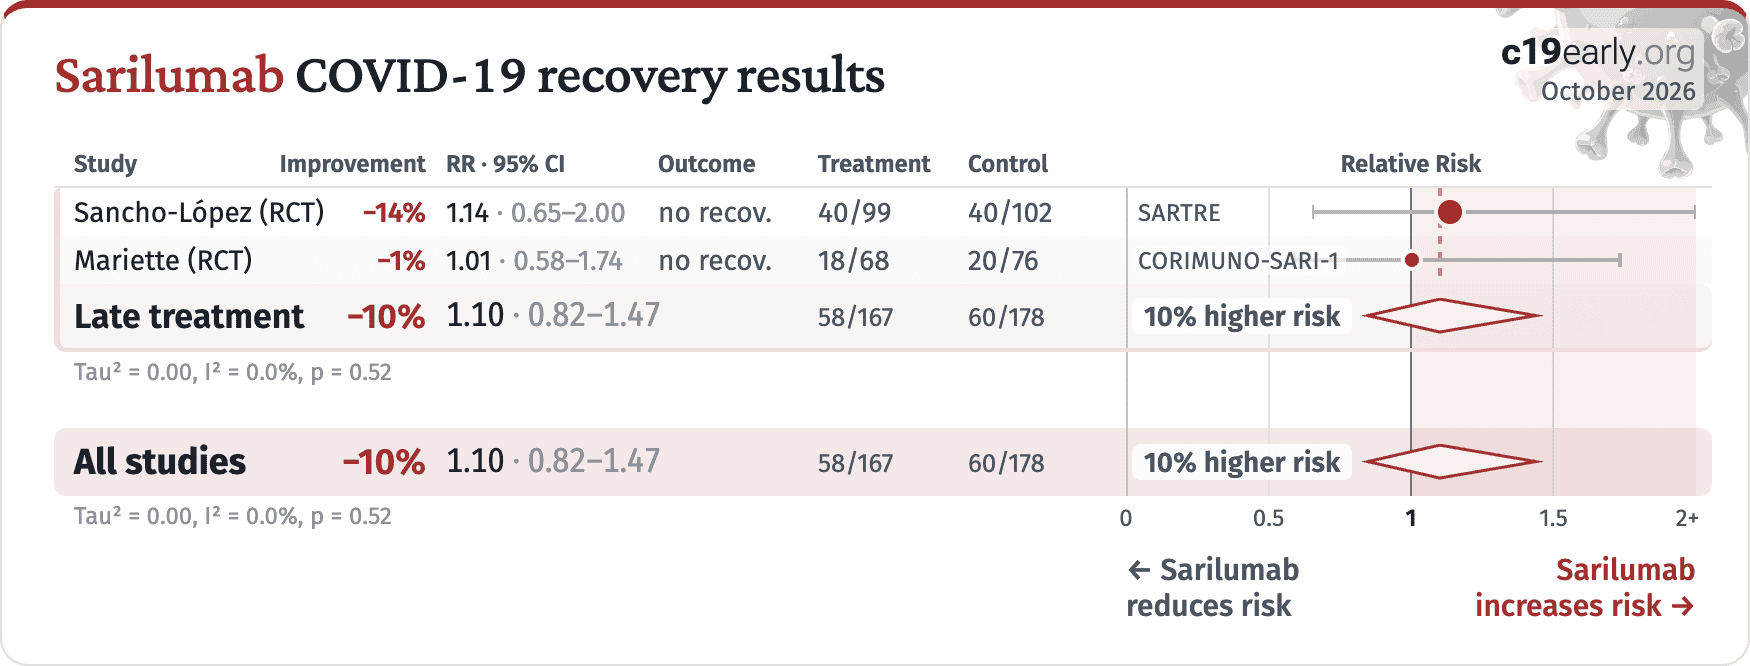
Mariette, 1/31/2022, Randomized Controlled Trial, France, peer-reviewed, 6 authors, study period 27 March, 2020 - 6 April, 2020, trial NCT04324073 (history) (CORIMUNO-SARI-1).
|
risk of death, 30.0% lower, HR 0.70, p = 0.40, treatment 10 of 68 (14.7%), control 16 of 76 (21.1%), NNT 16, adjusted per study, day 90.
|
|
risk of death, 35.0% lower, HR 0.65, p = 0.35, treatment 8 of 68 (11.8%), control 14 of 76 (18.4%), NNT 15, adjusted per study, day 28.
|
|
risk of death, 32.0% lower, HR 0.68, p = 0.50, treatment 6 of 68 (8.8%), control 8 of 76 (10.5%), adjusted per study, day 14.
|
|
WHO CPS>5, 0.6% higher, RR 1.01, p = 1.00, treatment 18 of 68 (26.5%), control 20 of 76 (26.3%), day 4, primary outcome.
|
|
non-invasive ventilation, mechanical ventilation, or death, 10.0% higher, HR 1.10, p = 0.70, treatment 68, control 76, day 14, primary outcome.
|
|
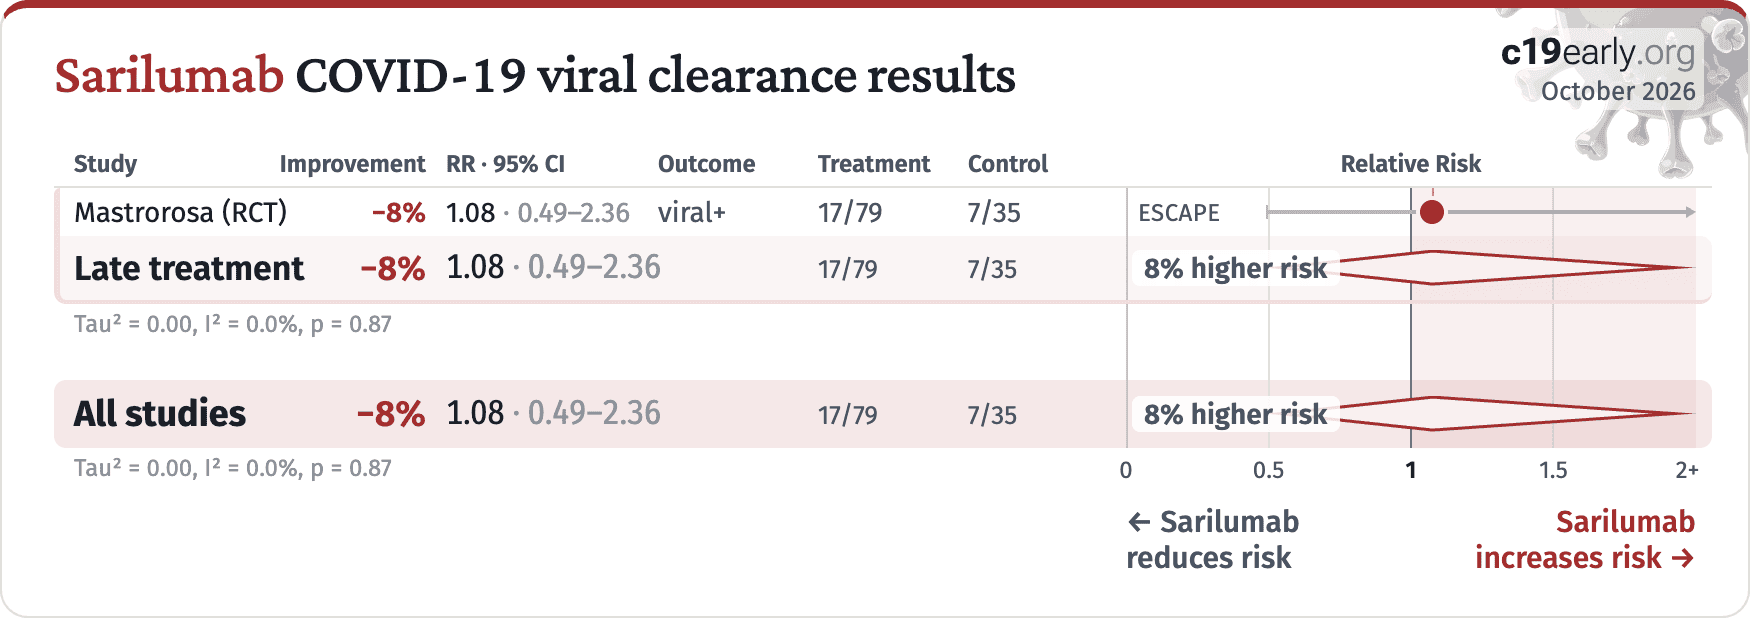
Mastrorosa, 3/31/2023, Randomized Controlled Trial, Italy, peer-reviewed, median age 61.0, 94 authors, study period 11 May, 2020 - 5 May, 2021, ESCAPE trial.
|
risk of death, 30.0% higher, HR 1.30, p = 0.67, treatment 10 of 107 (9.3%), control 4 of 52 (7.7%), Kaplan-Meier, day 30.
|
|
risk of no improvement, 6.5% lower, HR 0.93, p = 0.69, treatment 121, control 55, inverted to make HR<1 favor treatment, Kaplan-Meier, day 30.
|
|
risk of no viral clearance, 7.6% higher, RR 1.08, p = 1.00, treatment 17 of 79 (21.5%), control 7 of 35 (20.0%), day 30.
|
|
Merchante, 2/15/2022, Randomized Controlled Trial, Spain, peer-reviewed, median age 59.0, 20 authors, study period 13 July, 2020 - 5 March, 2021, trial NCT04357860 (history) (SARICOR).
|
risk of death, 35.2% higher, HR 1.35, p = 0.71, treatment 39, control 39, all patients.
|
|
risk of death, 99.0% lower, HR 0.01, p = 0.21, treatment 0 of 39 (0.0%), control 3 of 39 (7.7%), relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 400mg, Cox proportional hazards, day 28.
|
|
risk of death, 41.0% higher, HR 1.41, p = 0.67, treatment 4 of 37 (10.8%), control 3 of 39 (7.7%), 200mg, Cox proportional hazards, day 28.
|
|
risk of mechanical ventilation, 22.2% higher, HR 1.22, p = 0.70, treatment 39, control 39, all patients.
|
|
risk of mechanical ventilation, 22.0% lower, HR 0.78, p = 0.76, treatment 3 of 39 (7.7%), control 4 of 39 (10.3%), NNT 39, 400mg, Cox proportional hazards, day 28.
|
|
risk of mechanical ventilation, 68.0% higher, HR 1.68, p = 0.43, treatment 6 of 37 (16.2%), control 4 of 39 (10.3%), 200mg, Cox proportional hazards, day 28.
|
|
HFNO, NIMV or IMV, 36.0% lower, HR 0.64, p = 0.23, treatment 39, control 39, all patients, primary outcome.
|
|
HFNO, NIMV or IMV, 59.0% lower, HR 0.41, p = 0.10, treatment 5 of 39 (12.8%), control 11 of 39 (28.2%), NNT 6.5, 400mg, Cox proportional hazards, day 28, primary outcome.
|
|
HFNO, NIMV or IMV, 13.0% lower, HR 0.87, p = 0.76, treatment 10 of 37 (27.0%), control 11 of 39 (28.2%), NNT 85, 200mg, Cox proportional hazards, day 28, primary outcome.
|
|
Sancho-López, 10/17/2021, Randomized Controlled Trial, Spain, peer-reviewed, median age 60.0, 22 authors, study period 4 August, 2020 - 23 March, 2021, SARTRE trial.
|
risk of death, 3.0% higher, RR 1.03, p = 0.98, treatment 2 of 99 (2.0%), control 2 of 102 (2.0%), adjusted per study, day 28.
|
|
risk of ICU admission, 30.0% lower, RR 0.70, p = 0.50, treatment 7 of 99 (7.1%), control 10 of 102 (9.8%), NNT 37, adjusted per study, day 28.
|
|
Brescia ≥ 2, 14.0% higher, RR 1.14, p = 0.66, treatment 40 of 99 (40.4%), control 40 of 102 (39.2%), adjusted per study, day 28.
|
|
Brescia ≥ 3 at any moment, 3.0% higher, RR 1.03, p = 0.94, treatment 40 of 99 (40.4%), control 40 of 102 (39.2%), adjusted per study, day 28.
|
|
Brescia ≥ 3 at any moment, 3.0% higher, RR 1.03, p = 0.94, treatment 40 of 99 (40.4%), control 40 of 102 (39.2%), adjusted per study, day 14, primary outcome.
|
|
Sivapalasingam, 2/26/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, median age 61.0, 40 authors, study period 18 March, 2020 - 2 July, 2020, trial NCT04315298 (history) (REGENERON P2).
|
risk of death, 6.8% higher, HR 1.07, p = 0.89, treatment 180, control 90, adjusted per study, all 400mg patients.
|
|
risk of death, 1341.2% higher, HR 14.41, p = 0.03, treatment 9 of 51 (17.6%), control 0 of 25 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), 400mg, severe patients, phase 2, day 60.
|
|
risk of death, 30.0% lower, HR 0.70, p = 0.28, treatment 23 of 88 (26.1%), control 15 of 44 (34.1%), NNT 13, adjusted per study, 400mg, critical patients, phase 2, day 60.
|
|
risk of death, 2.0% higher, HR 1.02, p = 0.97, treatment 17 of 41 (41.5%), control 9 of 21 (42.9%), NNT 72, adjusted per study, 400mg, MSOD patients, phase 2, day 60.
|
|
risk of death, 22.4% higher, HR 1.22, p = 0.41, treatment 187, control 90, adjusted per study, all 200mg patients.
|
|
risk of death, 300.0% higher, HR 4.00, p = 0.55, treatment 2 of 50 (4.0%), control 0 of 25 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), 200mg, severe patients, phase 2, day 60.
|
|
risk of death, 21.0% higher, HR 1.21, p = 0.55, treatment 38 of 94 (40.4%), control 15 of 44 (34.1%), adjusted per study, 200mg, critical patients, phase 2, day 60.
|
|
risk of death, 15.0% higher, HR 1.15, p = 0.74, treatment 20 of 43 (46.5%), control 9 of 21 (42.9%), adjusted per study, 200mg, MSOD patients, phase 2, day 60.
|
|
risk of no improvement, 4.4% higher, RR 1.04, p = 0.91, treatment 180, control 90, all 400mg patients.
|
|
risk of no improvement, 292.2% higher, RR 3.92, p = 0.04, treatment 16 of 51 (31.4%), control 2 of 25 (8.0%), 400mg, severe patients, phase 2, day 22.
|
|
risk of no improvement, 39.7% lower, RR 0.60, p = 0.006, treatment 35 of 88 (39.8%), control 29 of 44 (65.9%), NNT 3.8, 400mg, critical patients, phase 2, day 22.
|
|
risk of no improvement, 7.1% higher, RR 1.07, p = 0.79, treatment 23 of 41 (56.1%), control 11 of 21 (52.4%), 400mg, MSOD patients, phase 2, day 22.
|
|
risk of no improvement, 12.2% lower, RR 0.88, p = 0.30, treatment 187, control 90, all 200mg patients.
|
|
risk of no improvement, no change, RR 1.00, p = 1.00, treatment 4 of 50 (8.0%), control 2 of 25 (8.0%), 200mg, severe patients, phase 2, day 22.
|
|
risk of no improvement, 20.9% lower, RR 0.79, p = 0.14, treatment 49 of 94 (52.1%), control 29 of 44 (65.9%), NNT 7.3, 200mg, critical patients, phase 2, day 22.
|
|
risk of no improvement, 15.4% higher, RR 1.15, p = 0.60, treatment 26 of 43 (60.5%), control 11 of 21 (52.4%), 200mg, MSOD patients, phase 2, day 22.
|
|
Sivapalasingam (B), 2/26/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, median age 61.0, 40 authors, study period 18 March, 2020 - 2 July, 2020, trial NCT04315298 (history) (REGENERON P3).
|
risk of death, 7.5% higher, HR 1.08, p = 0.59, treatment 567, control 286, adjusted per study, all 400mg patients.
|
|
risk of death, 17.0% higher, HR 1.17, p = 0.71, treatment 21 of 137 (15.3%), control 9 of 70 (12.9%), adjusted per study, 400mg, severe patients, phase 3, day 60.
|
|
risk of death, no change, HR 1.00, p = 1.00, treatment 114 of 338 (33.7%), control 59 of 170 (34.7%), NNT 102, adjusted per study, 400mg, critical patients, phase 3, day 60.
|
|
risk of death, 32.0% higher, HR 1.32, p = 0.35, treatment 40 of 92 (43.5%), control 16 of 46 (34.8%), adjusted per study, 400mg, MSOD patients, phase 3, day 60.
|
|
risk of death, 11.6% lower, HR 0.88, p = 0.45, treatment 477, control 286, adjusted per study, all 200mg patients.
|
|
risk of death, 36.0% lower, HR 0.64, p = 0.31, treatment 12 of 140 (8.6%), control 9 of 70 (12.9%), NNT 23, adjusted per study, 200mg, severe patients, phase 3, day 60.
|
|
risk of death, 19.0% lower, HR 0.81, p = 0.24, treatment 70 of 242 (28.9%), control 59 of 170 (34.7%), NNT 17, adjusted per study, 200mg, critical patients, phase 3, day 60.
|
|
risk of death, 27.0% higher, HR 1.27, p = 0.43, treatment 40 of 95 (42.1%), control 16 of 46 (34.8%), adjusted per study, 200mg, MSOD patients, phase 3, day 60.
|
|
risk of no improvement, 5.9% higher, RR 1.06, p = 0.47, treatment 567, control 286, all 400mg patients.
|
|
risk of no improvement, 23.5% higher, RR 1.23, p = 0.58, treatment 29 of 137 (21.2%), control 12 of 70 (17.1%), 400mg, severe patients, phase 3, day 22.
|
|
risk of no improvement, 5.8% higher, RR 1.06, p = 0.64, treatment 164 of 338 (48.5%), control 78 of 170 (45.9%), 400mg, critical patients, phase 3, day 22.
|
|
risk of no improvement, 3.3% higher, RR 1.03, p = 0.85, treatment 62 of 92 (67.4%), control 30 of 46 (65.2%), 400mg, MSOD patients, phase 3, day 22.
|
|
risk of no improvement, 11.4% lower, RR 0.89, p = 0.13, treatment 477, control 286, all 200mg patients.
|
|
risk of no improvement, no change, RR 1.00, p = 1.00, treatment 24 of 140 (17.1%), control 12 of 70 (17.1%), 200mg, severe patients, phase 3, day 22.
|
|
risk of no improvement, 16.2% lower, RR 0.84, p = 0.11, treatment 105 of 242 (43.4%), control 88 of 170 (51.8%), NNT 12, 200mg, critical patients, phase 3, day 22.
|
|
risk of no improvement, 4.8% lower, RR 0.95, p = 0.85, treatment 59 of 95 (62.1%), control 30 of 46 (65.2%), NNT 32, 200mg, MSOD patients, phase 3, day 22.
|