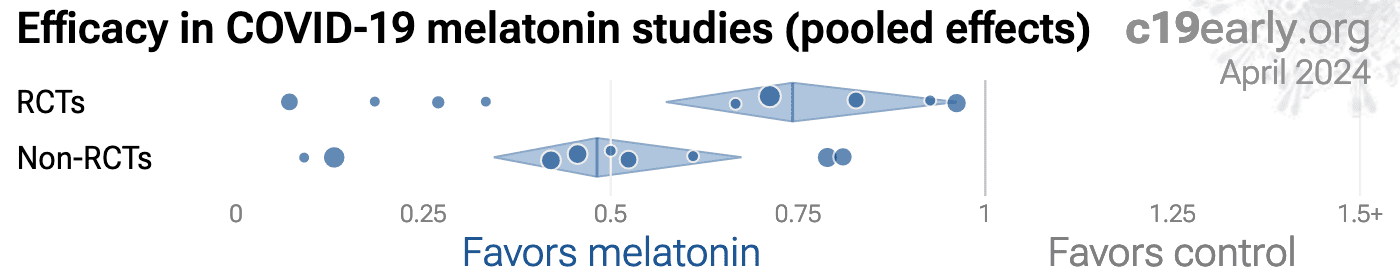
Media coverage of melatonin for COVID‑19
Media covered none of the 11 studies showing significantly lower risk
No positive melatonin studies were covered
Melatonin for COVID-19
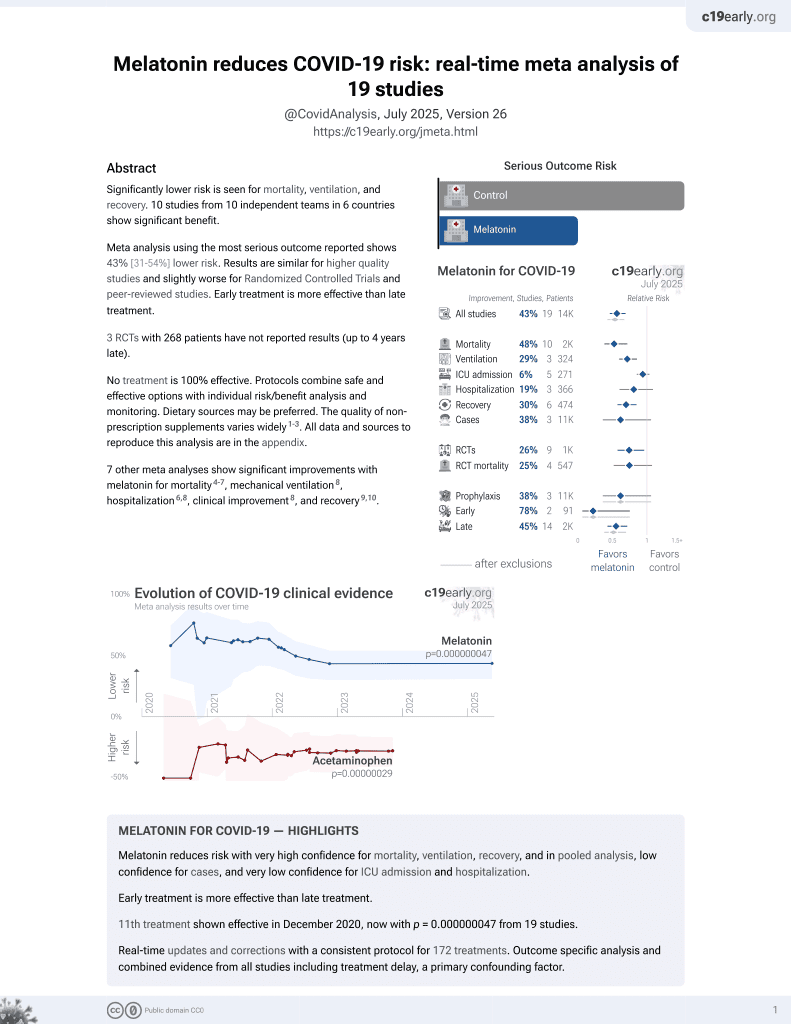
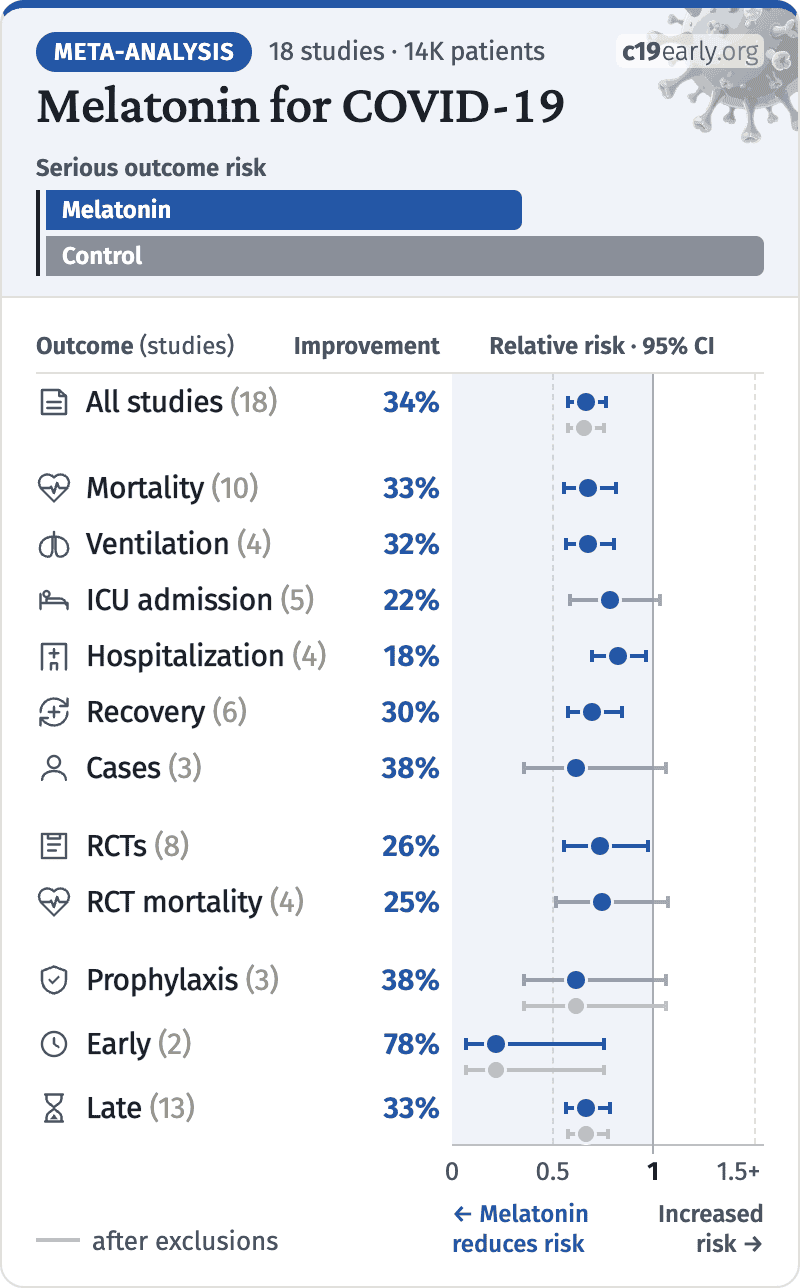
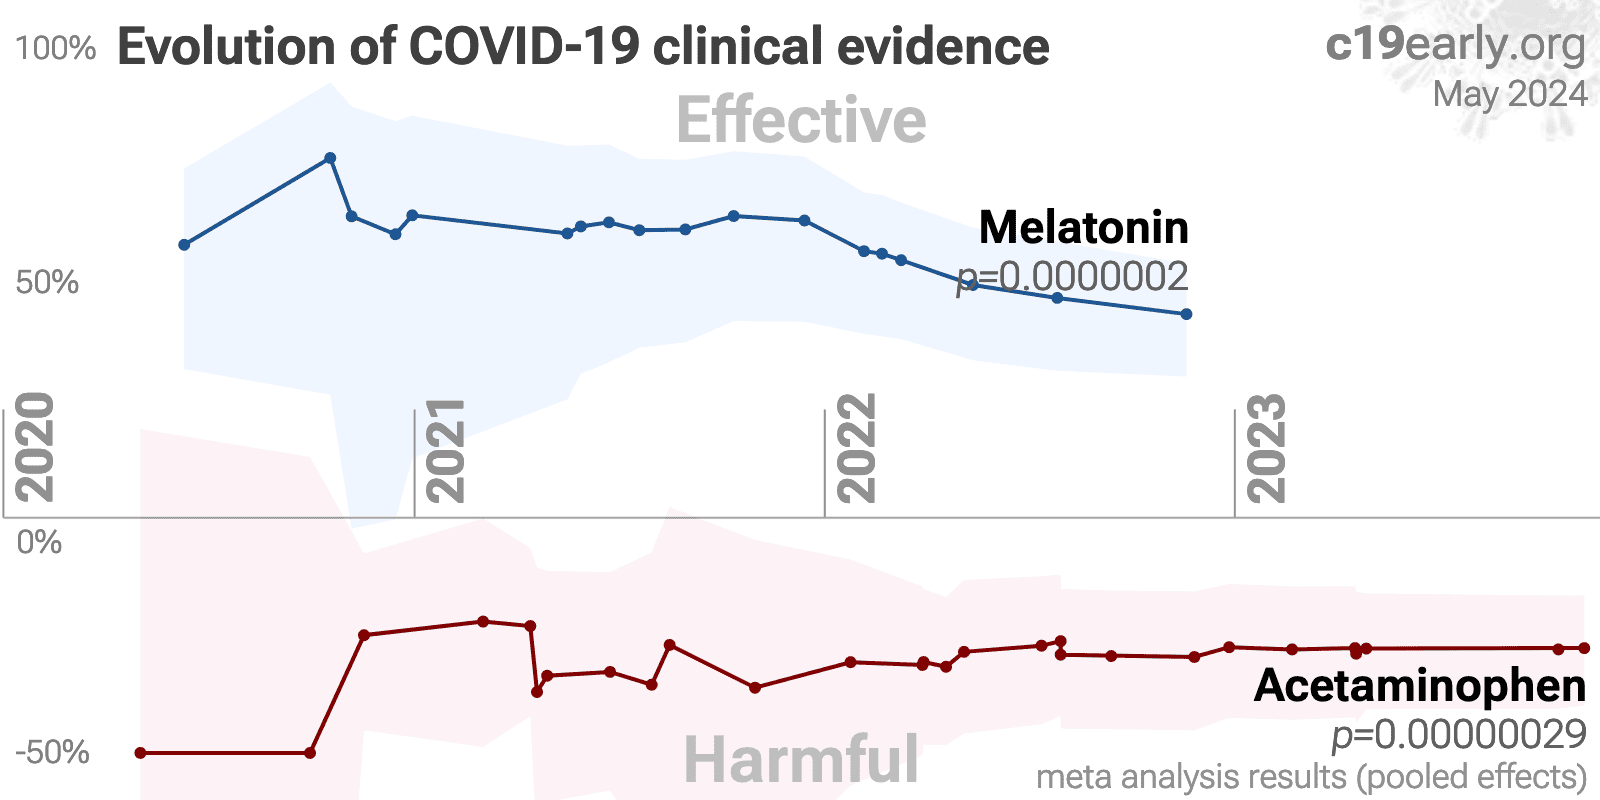
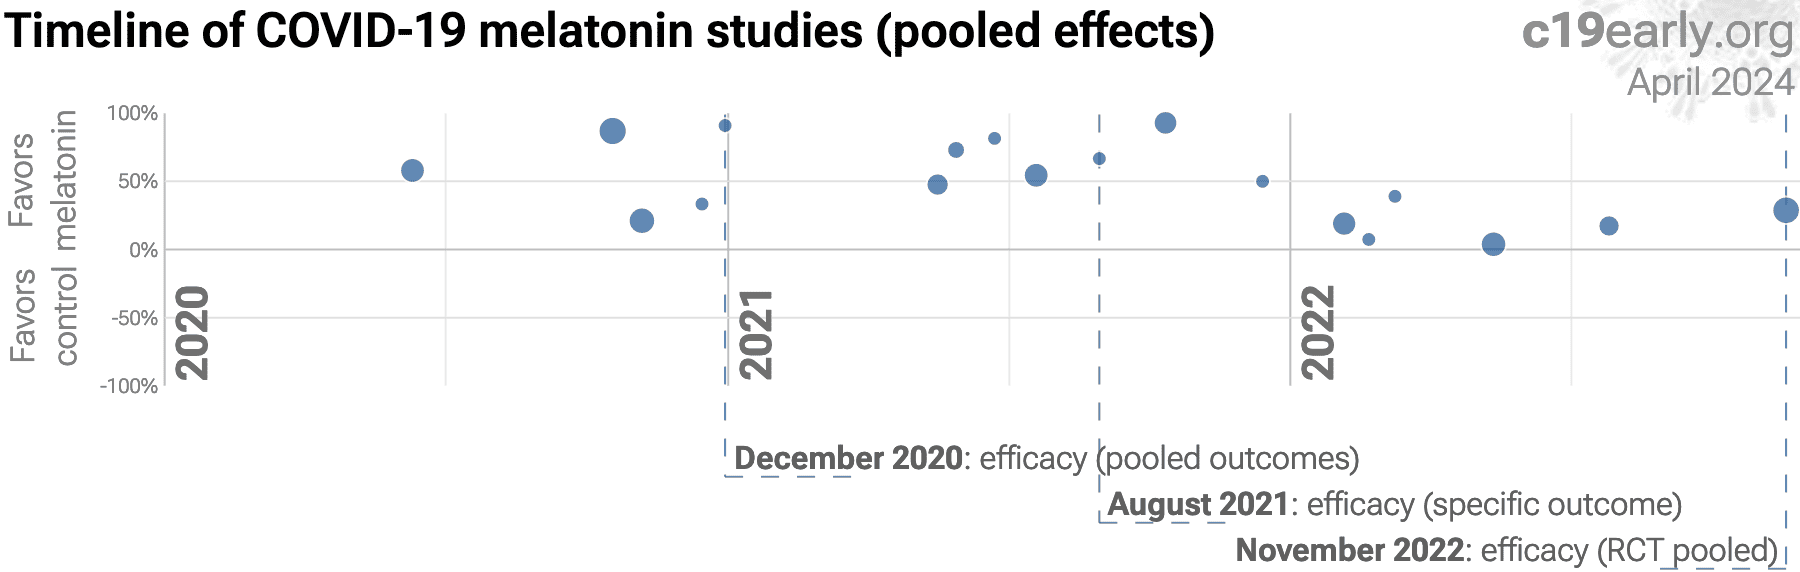
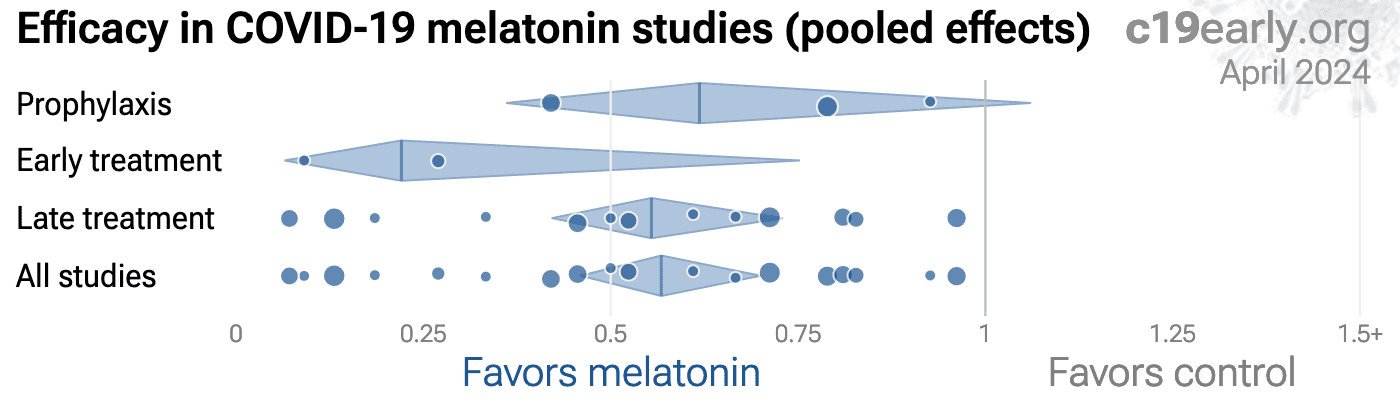
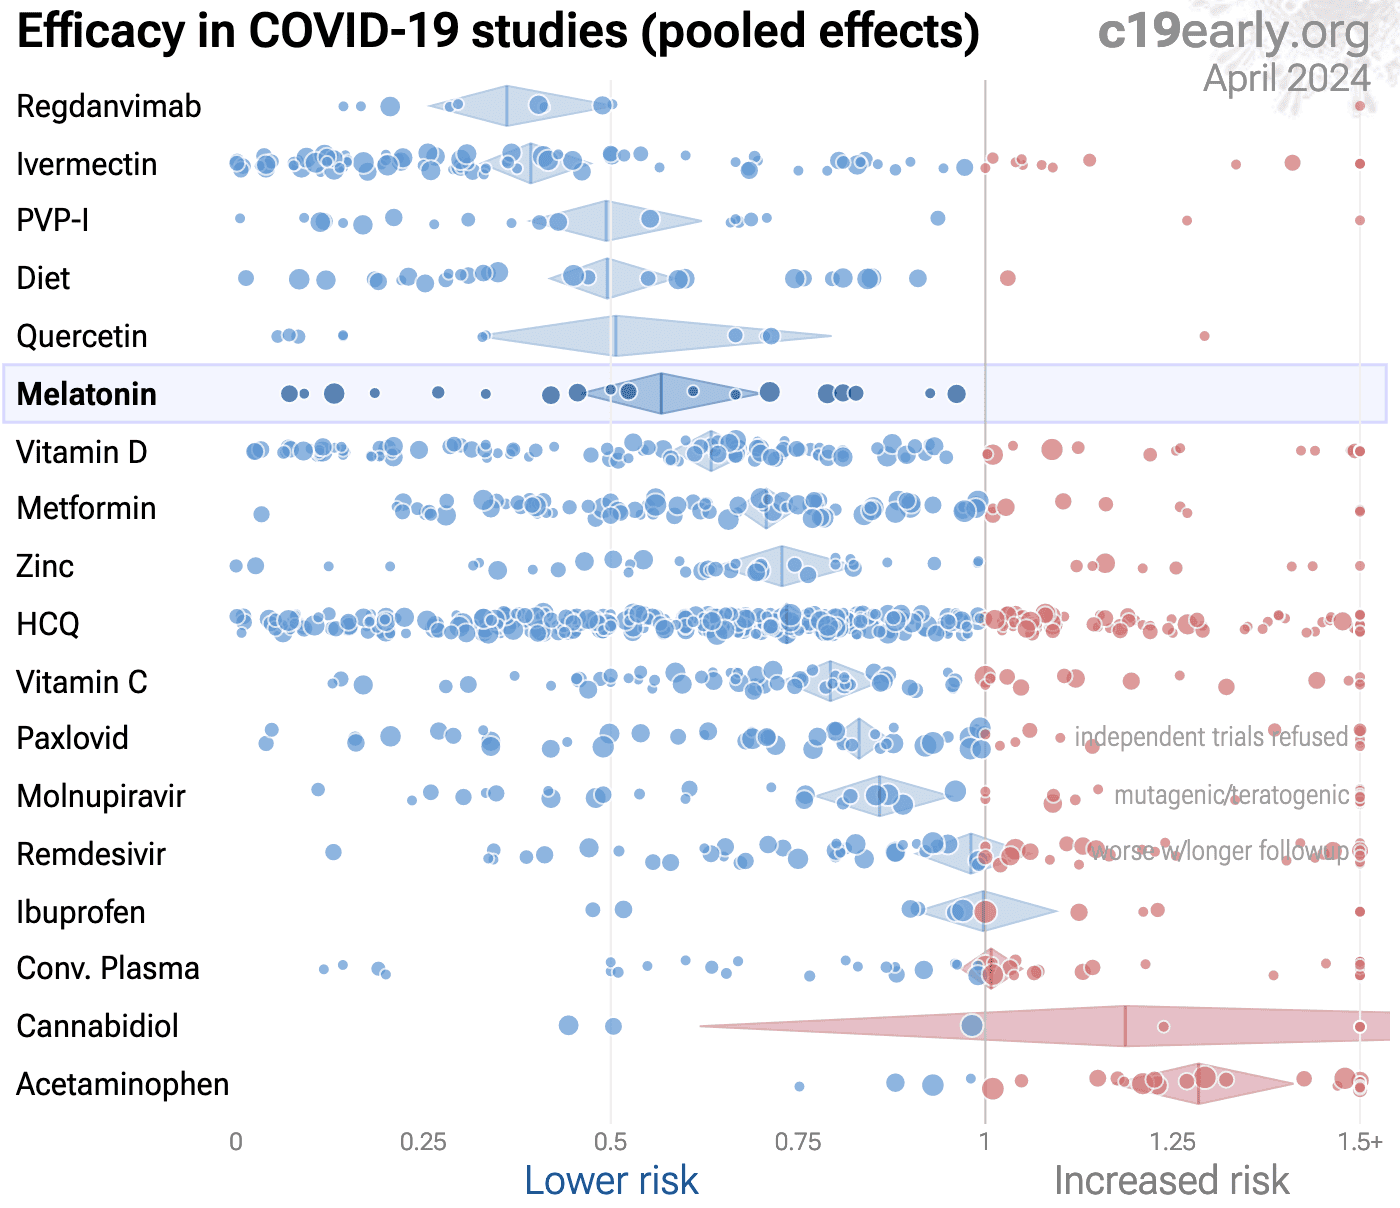
Highlights- Melatonin reduces risk with very high confidence for mortality, ventilation, recovery, and in pooled analysis, high confidence for hospitalization, and low confidence for ICU admission and cases.
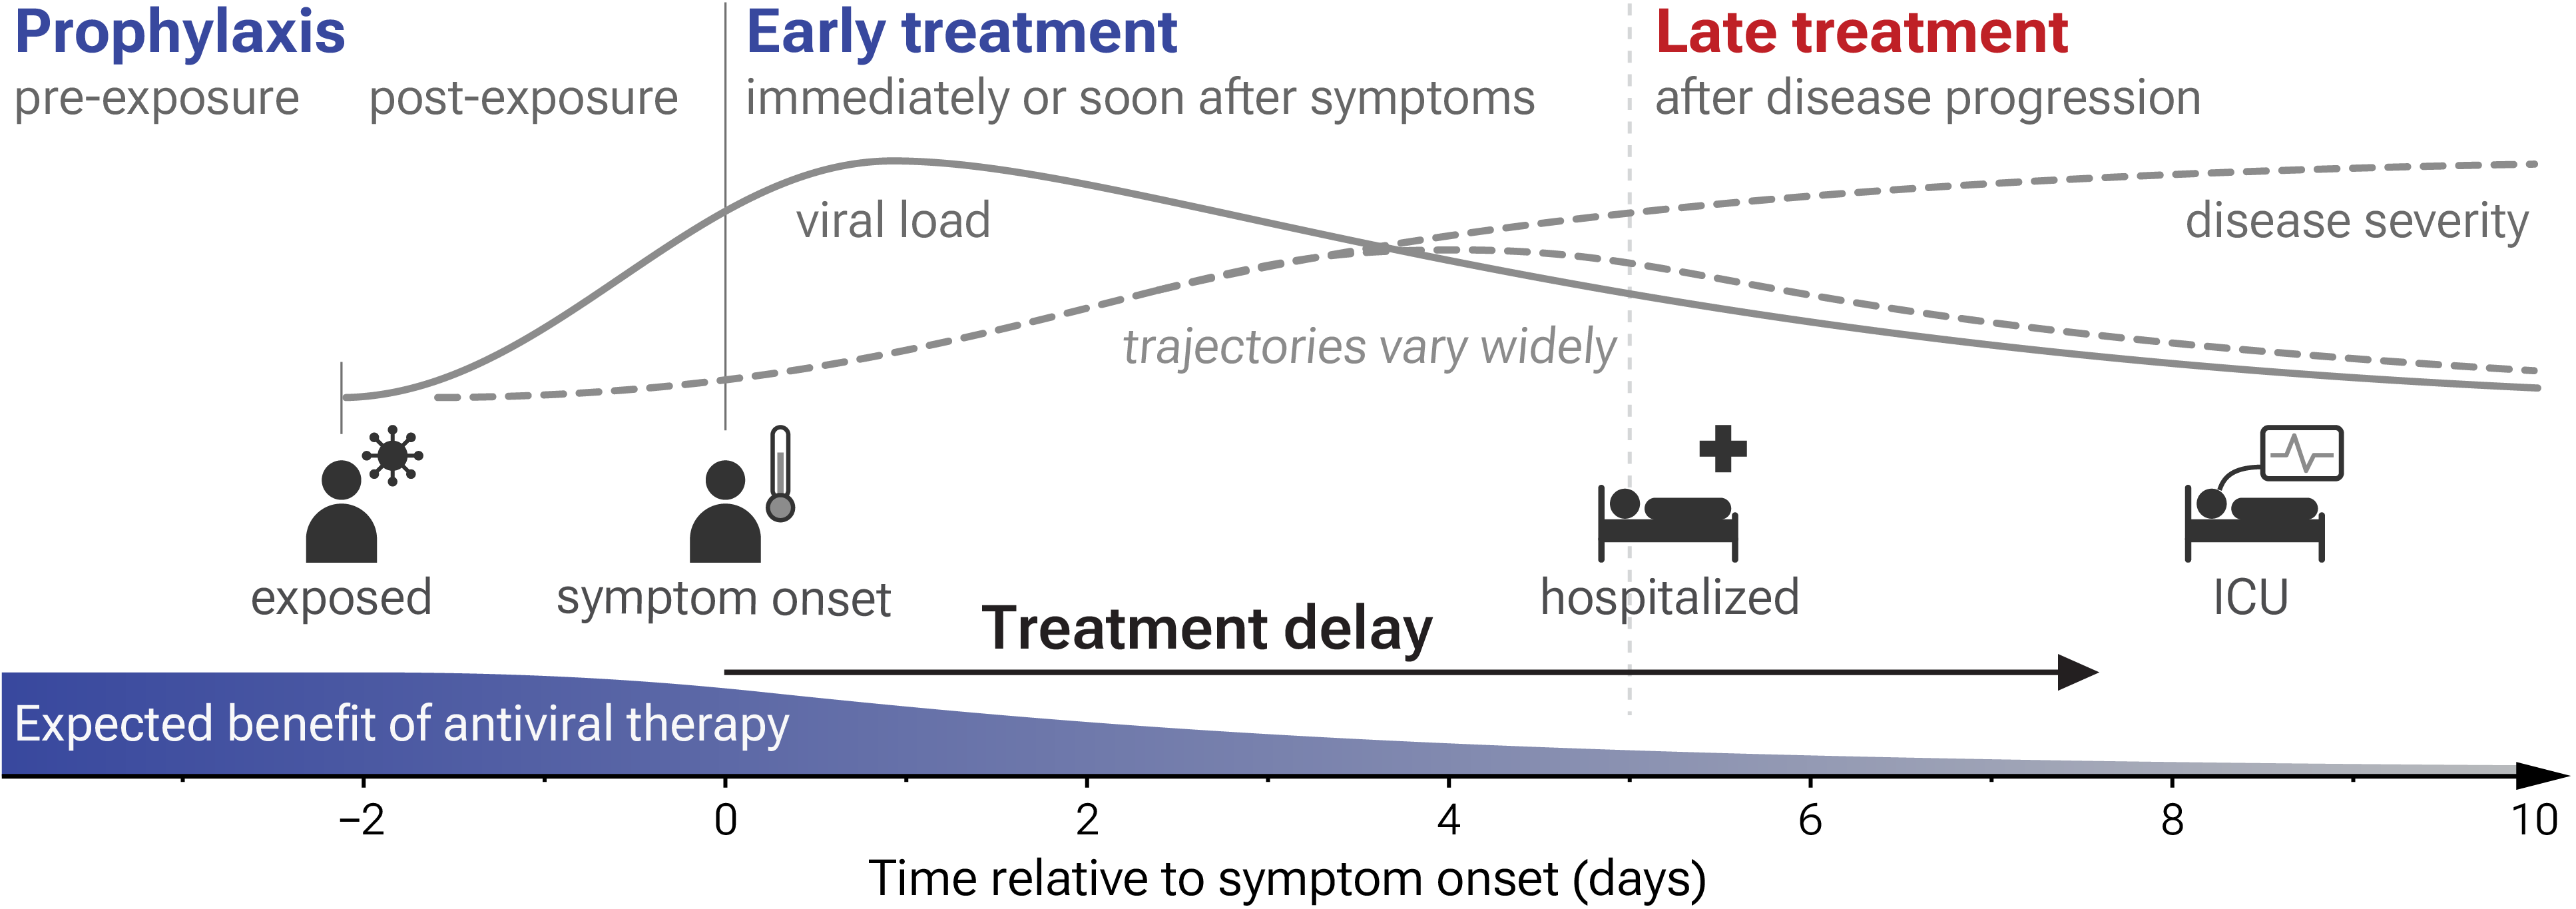
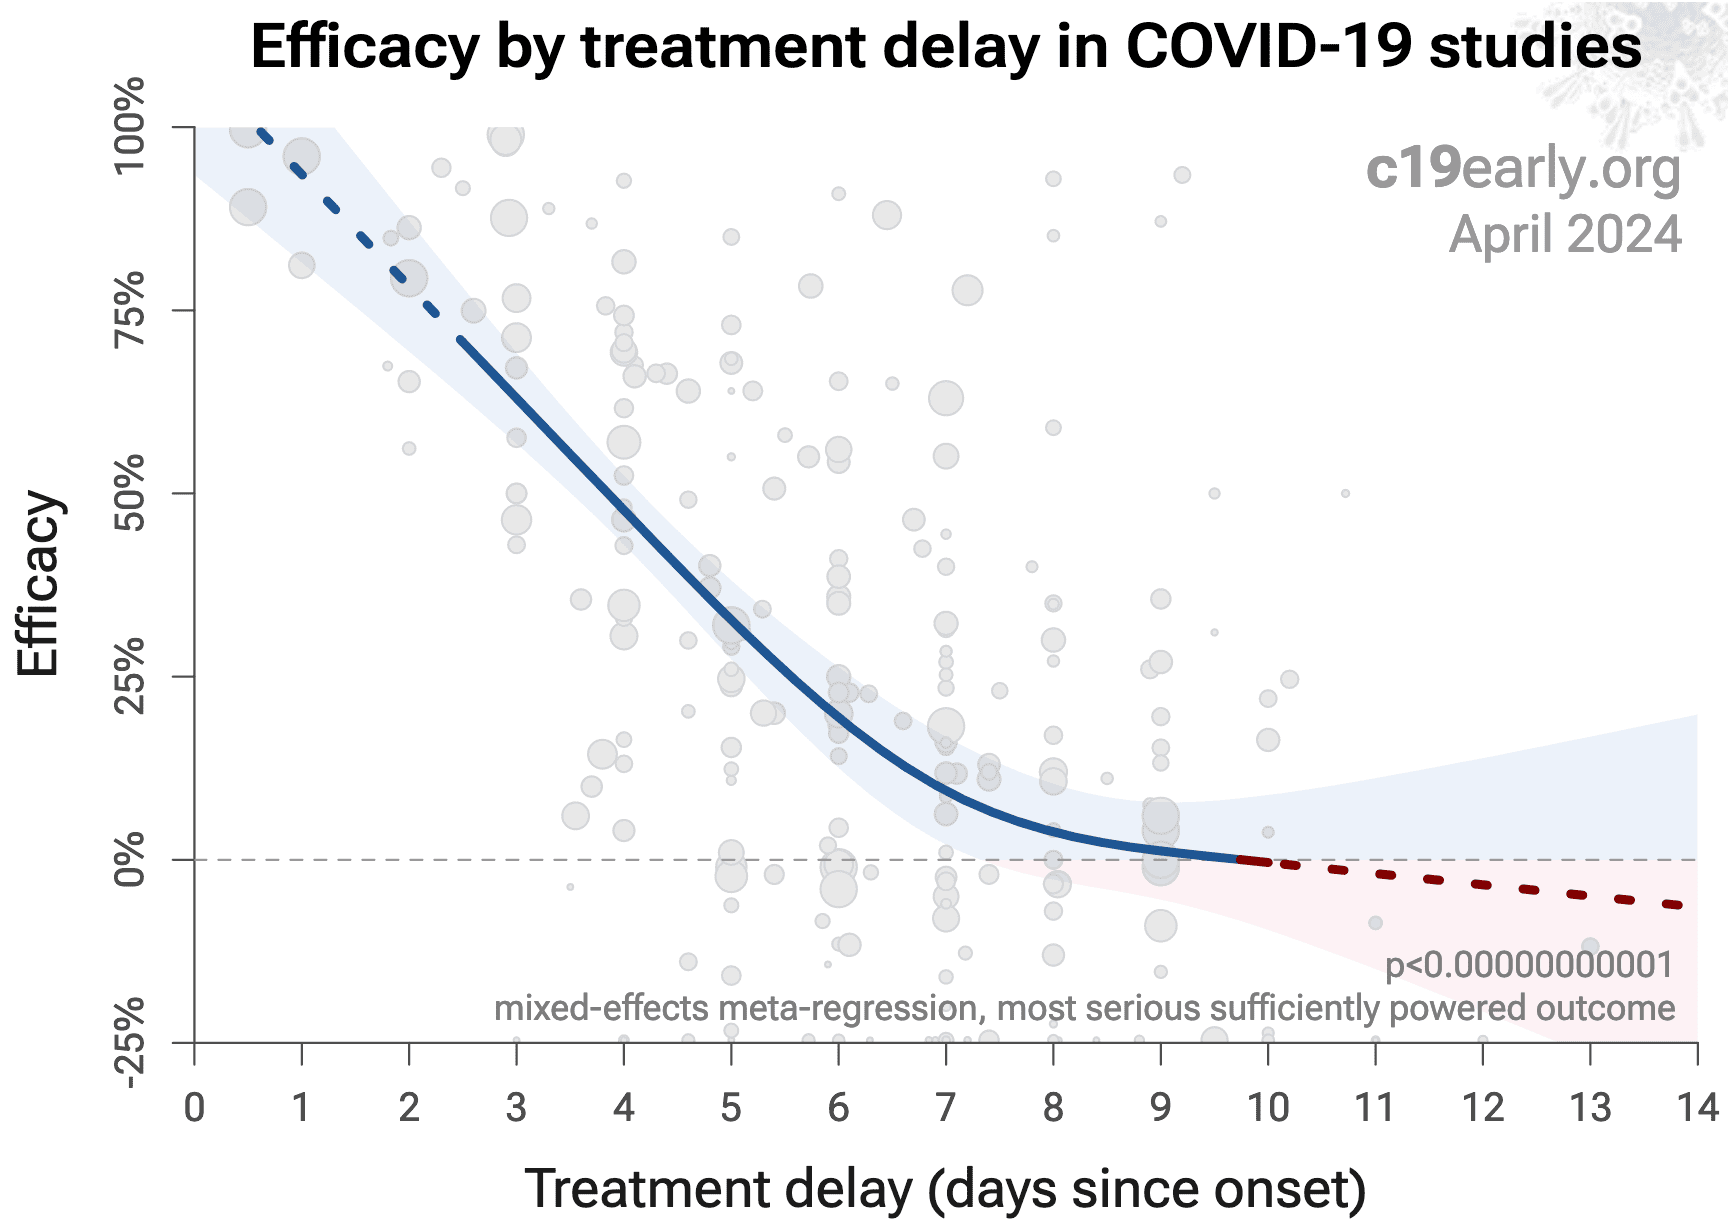
- Early treatment is more effective than late treatment.
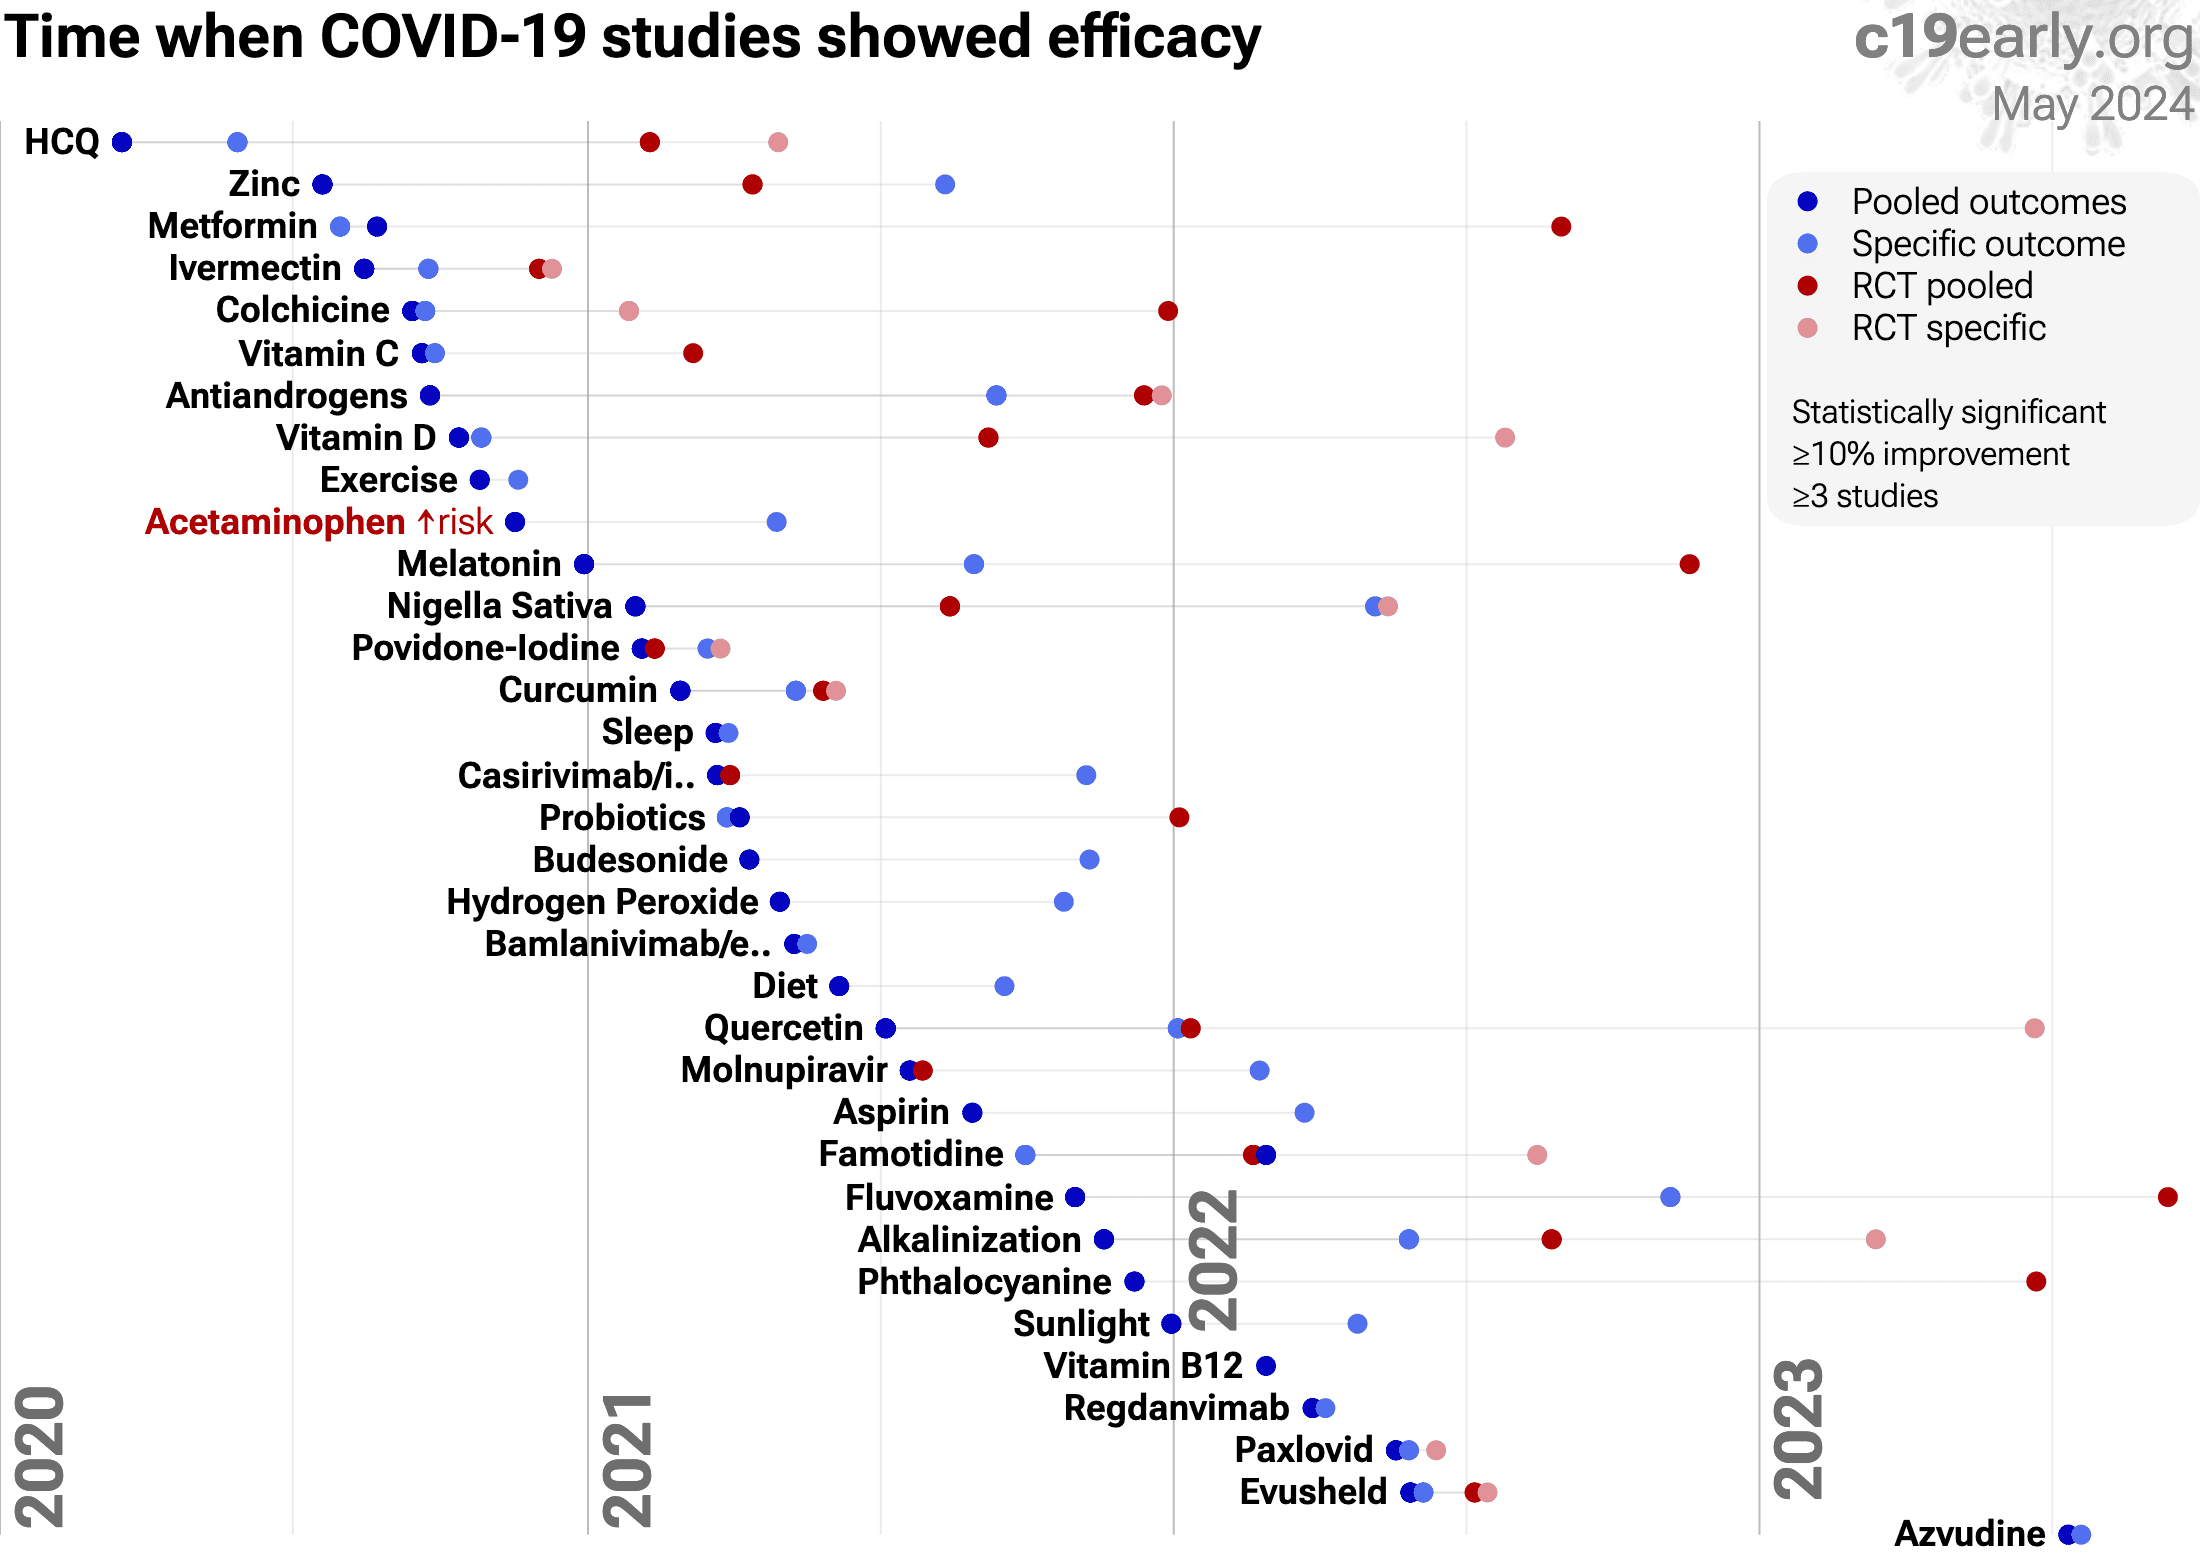
- 25th treatment shown effective in May 2021, now with p = 0.000000015 from 18 studies.
- Real-time updates and corrections with a consistent protocol for 227 treatments. Outcome specific analysis and combined evidence from all studies including treatment delay, a primary confounding factor.
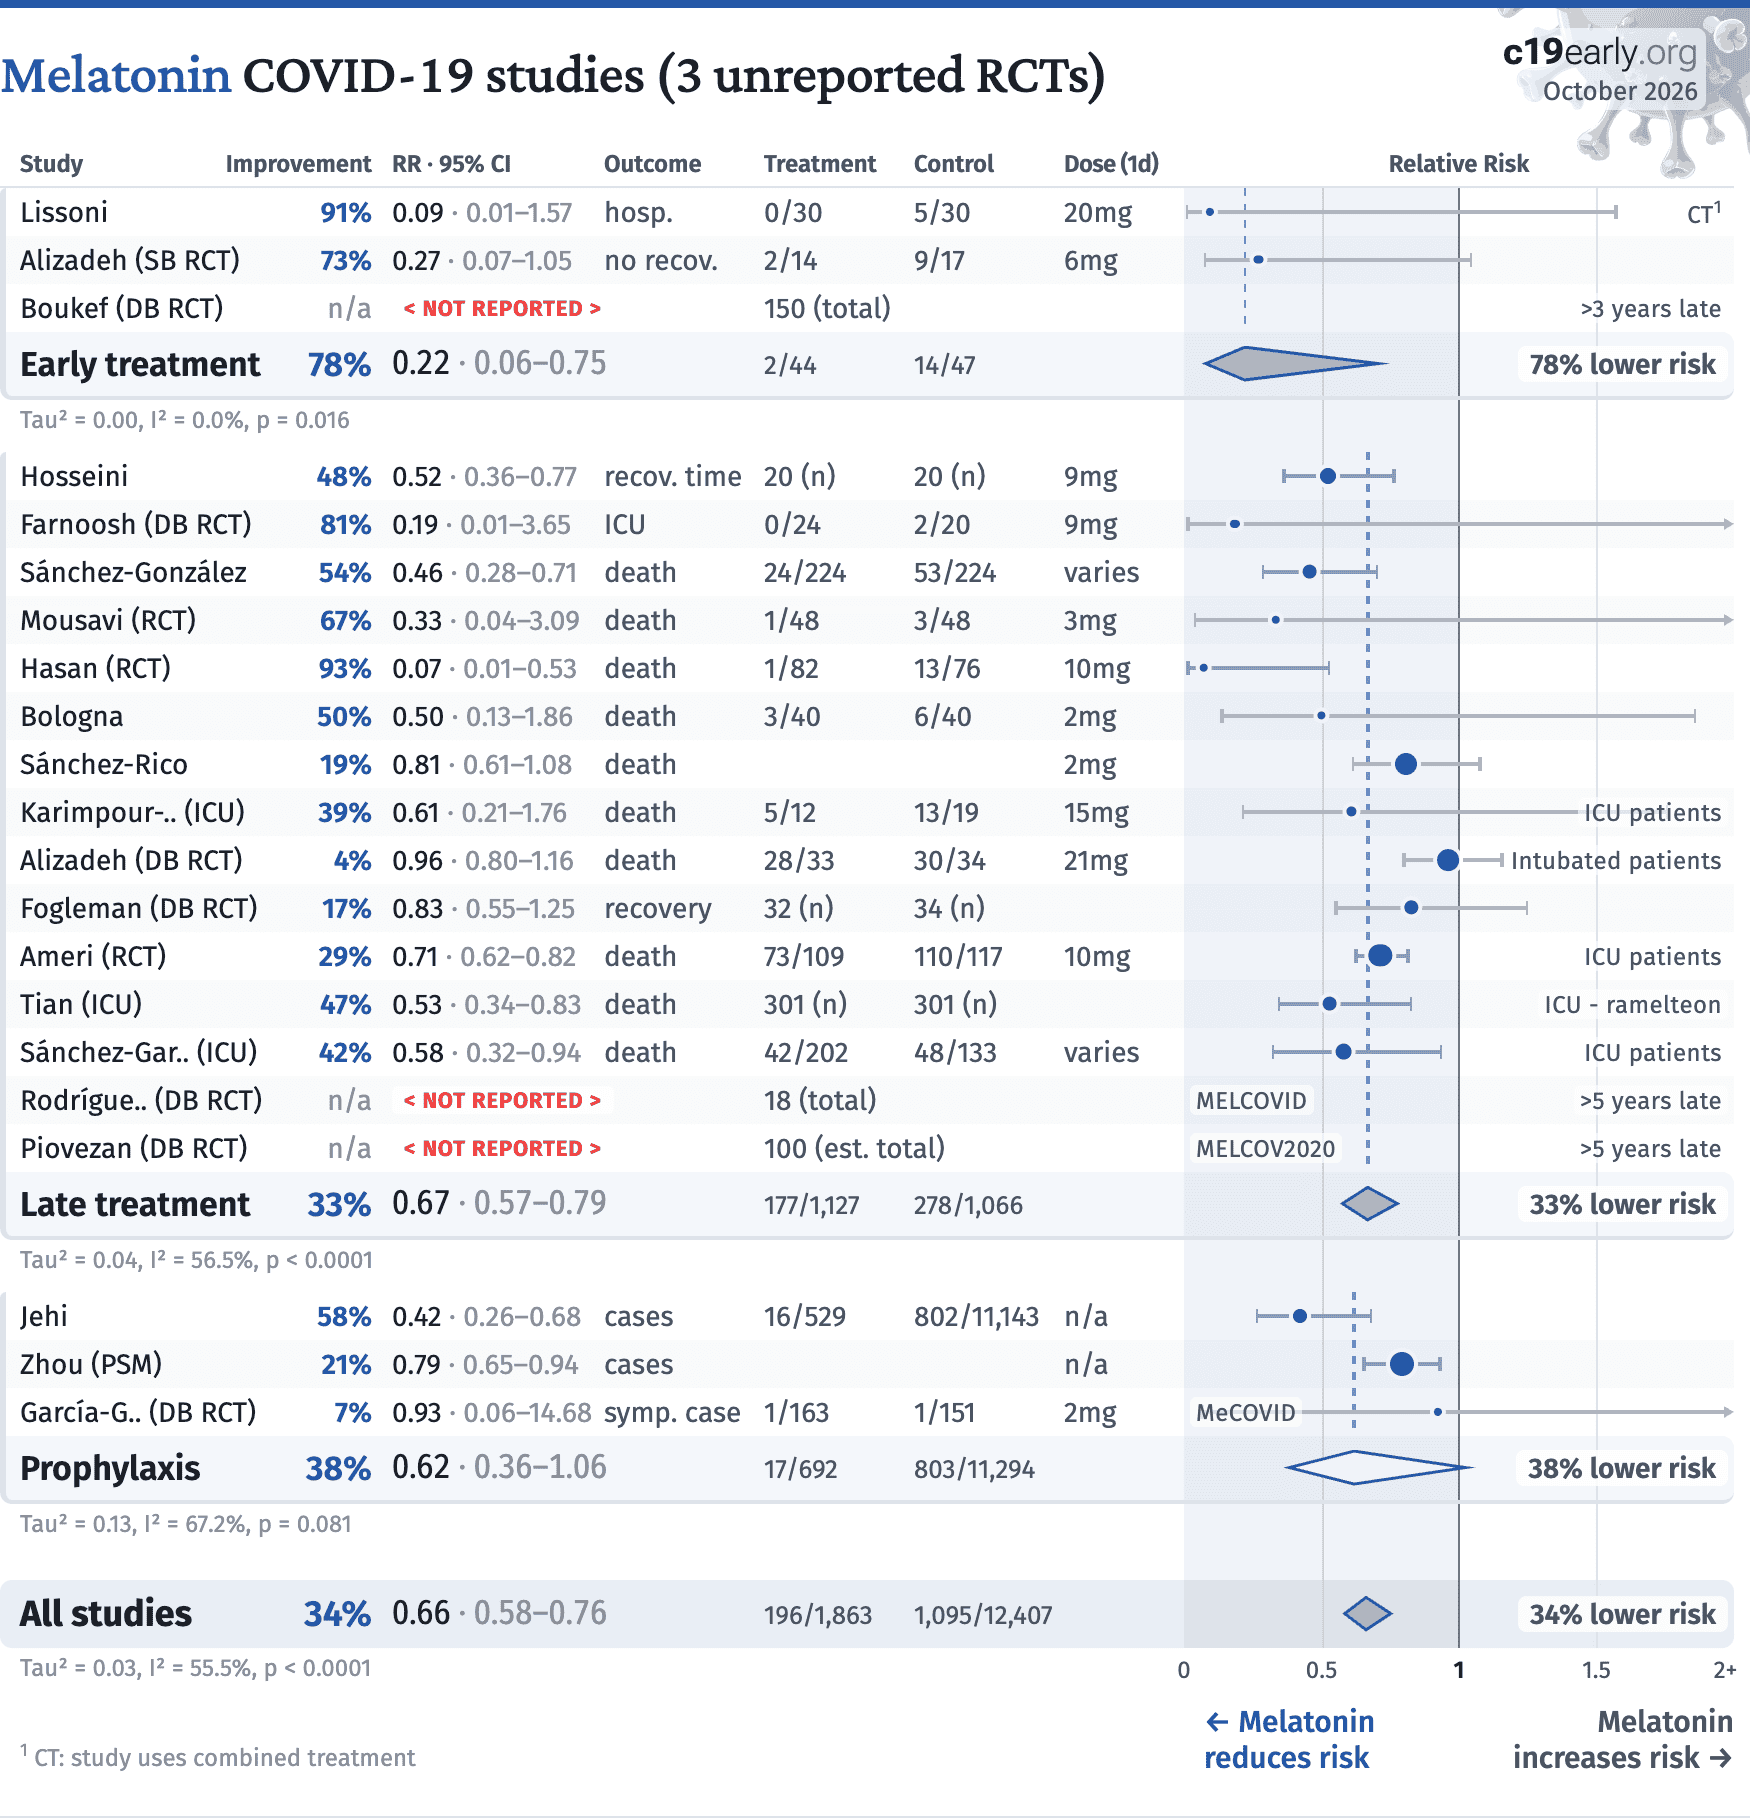
Melatonin COVID-19 studies (3 unreported RCTs)
Melatonin: potential mechanisms of action for COVID-19
Melatonin for COVID-19: meta-analysis results
Random-effects meta-analysis. Relative risk with 95% CI. * p < 0.05, ** p < 0.01, *** p < 0.001.
Melatonin COVID-19 studies (3 unreported RCTs)
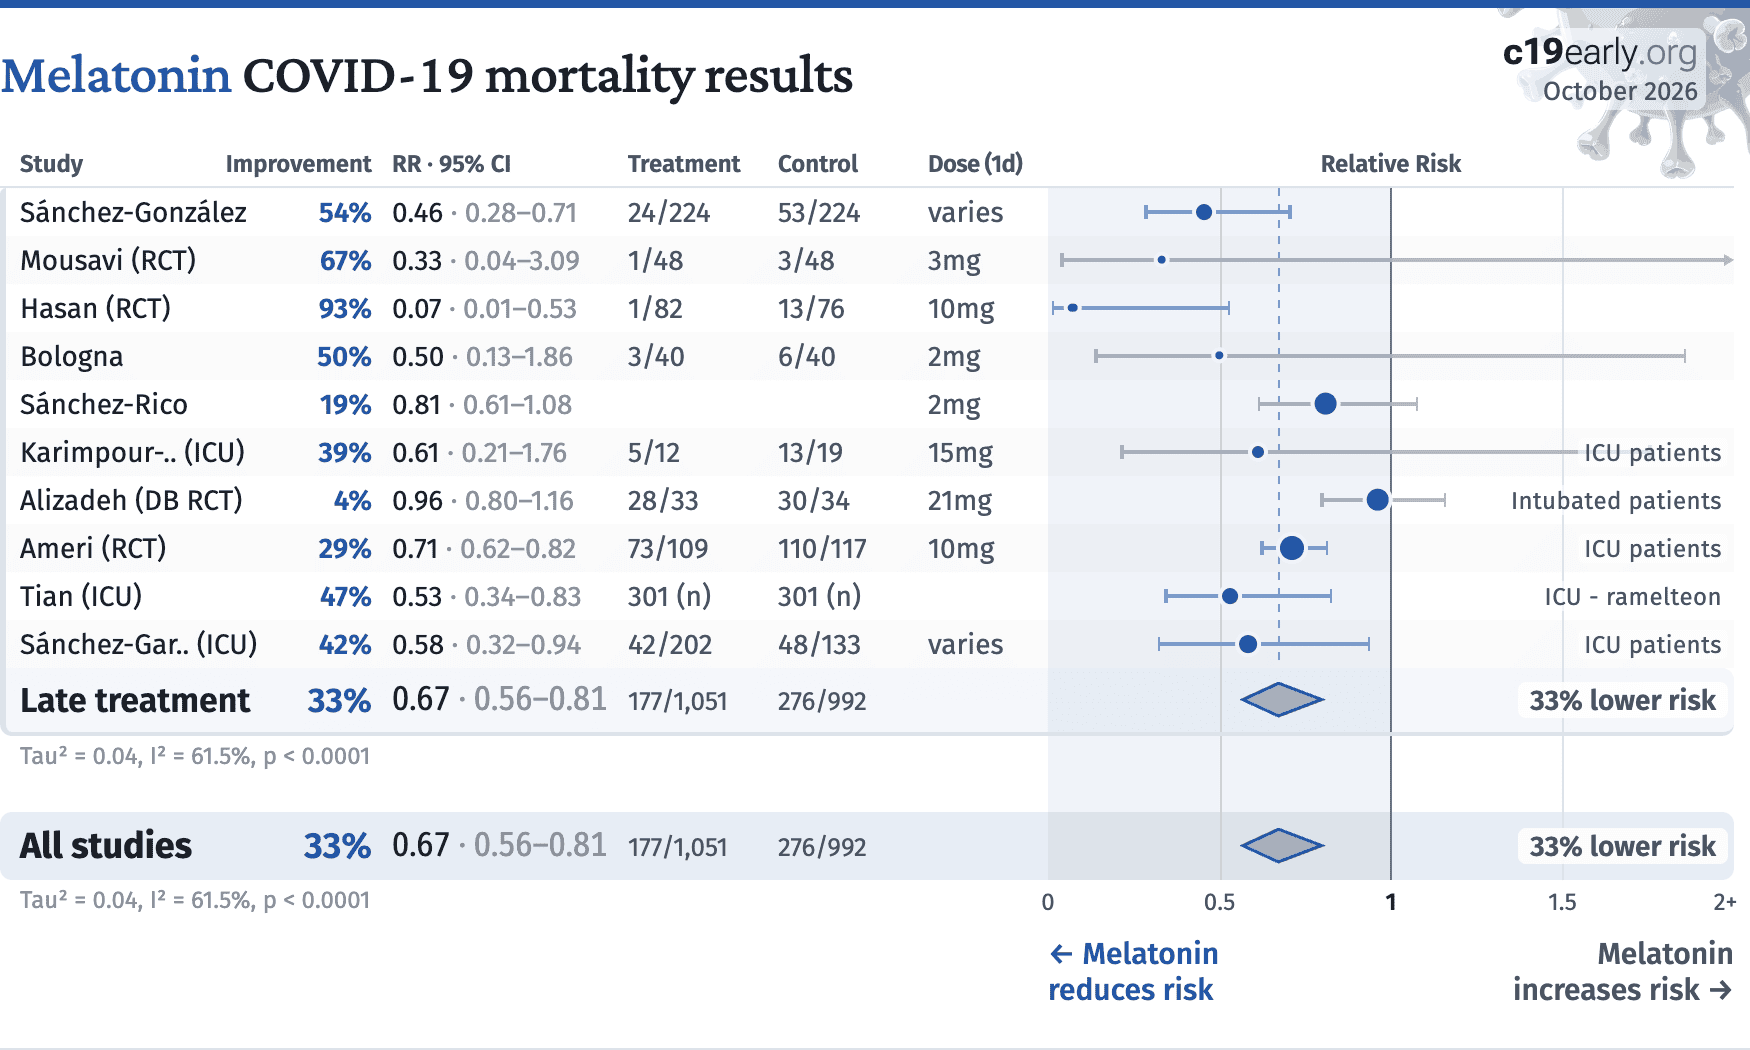
Melatonin COVID-19 mortality results
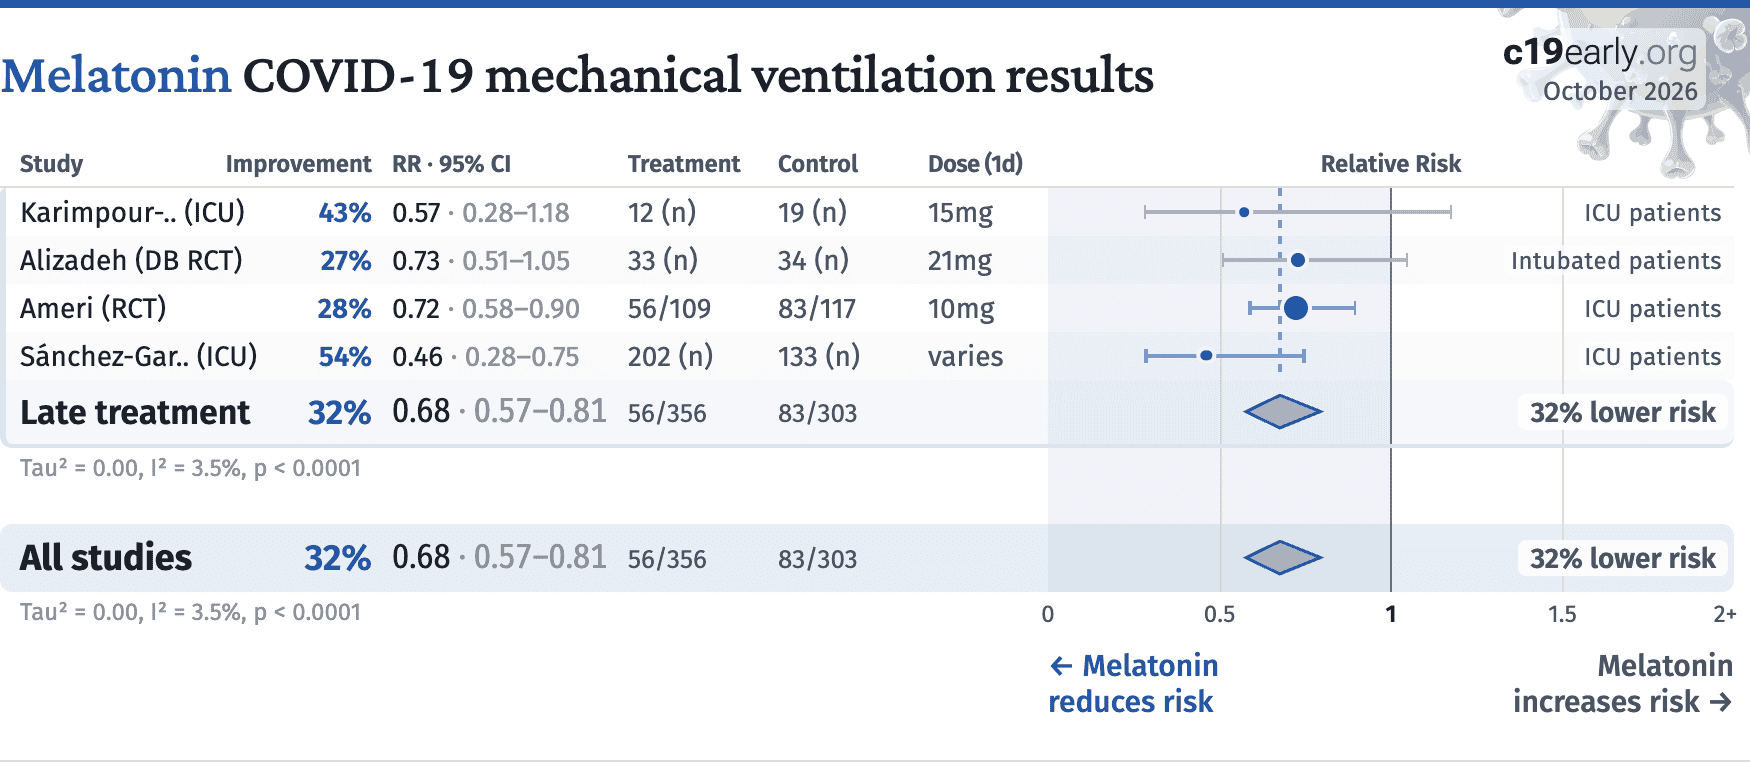
Melatonin COVID-19 mechanical ventilation results
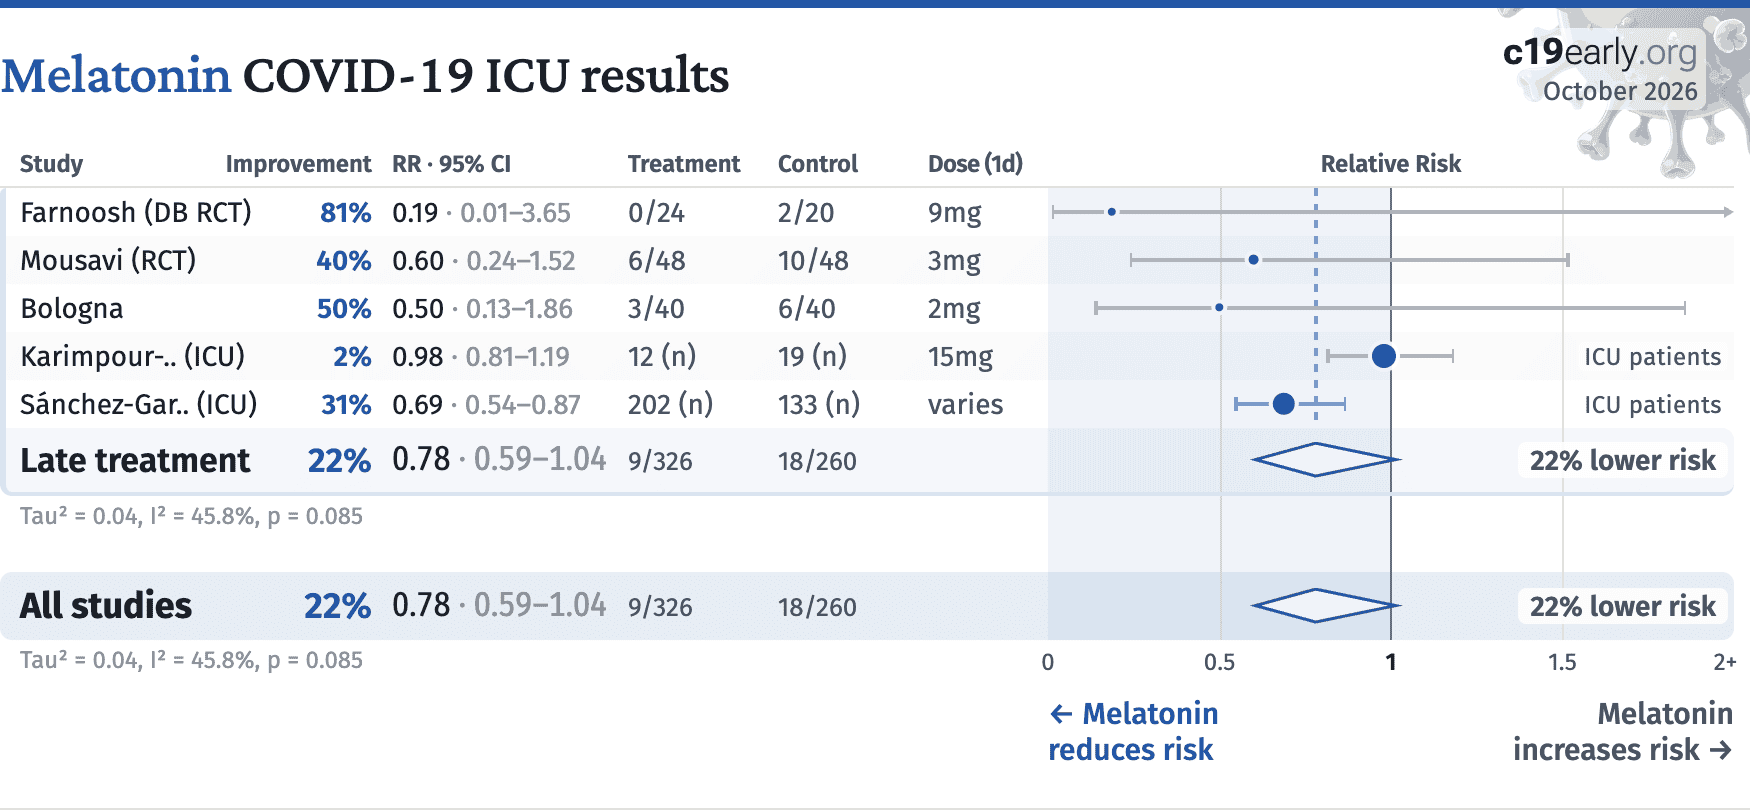
Melatonin COVID-19 ICU results
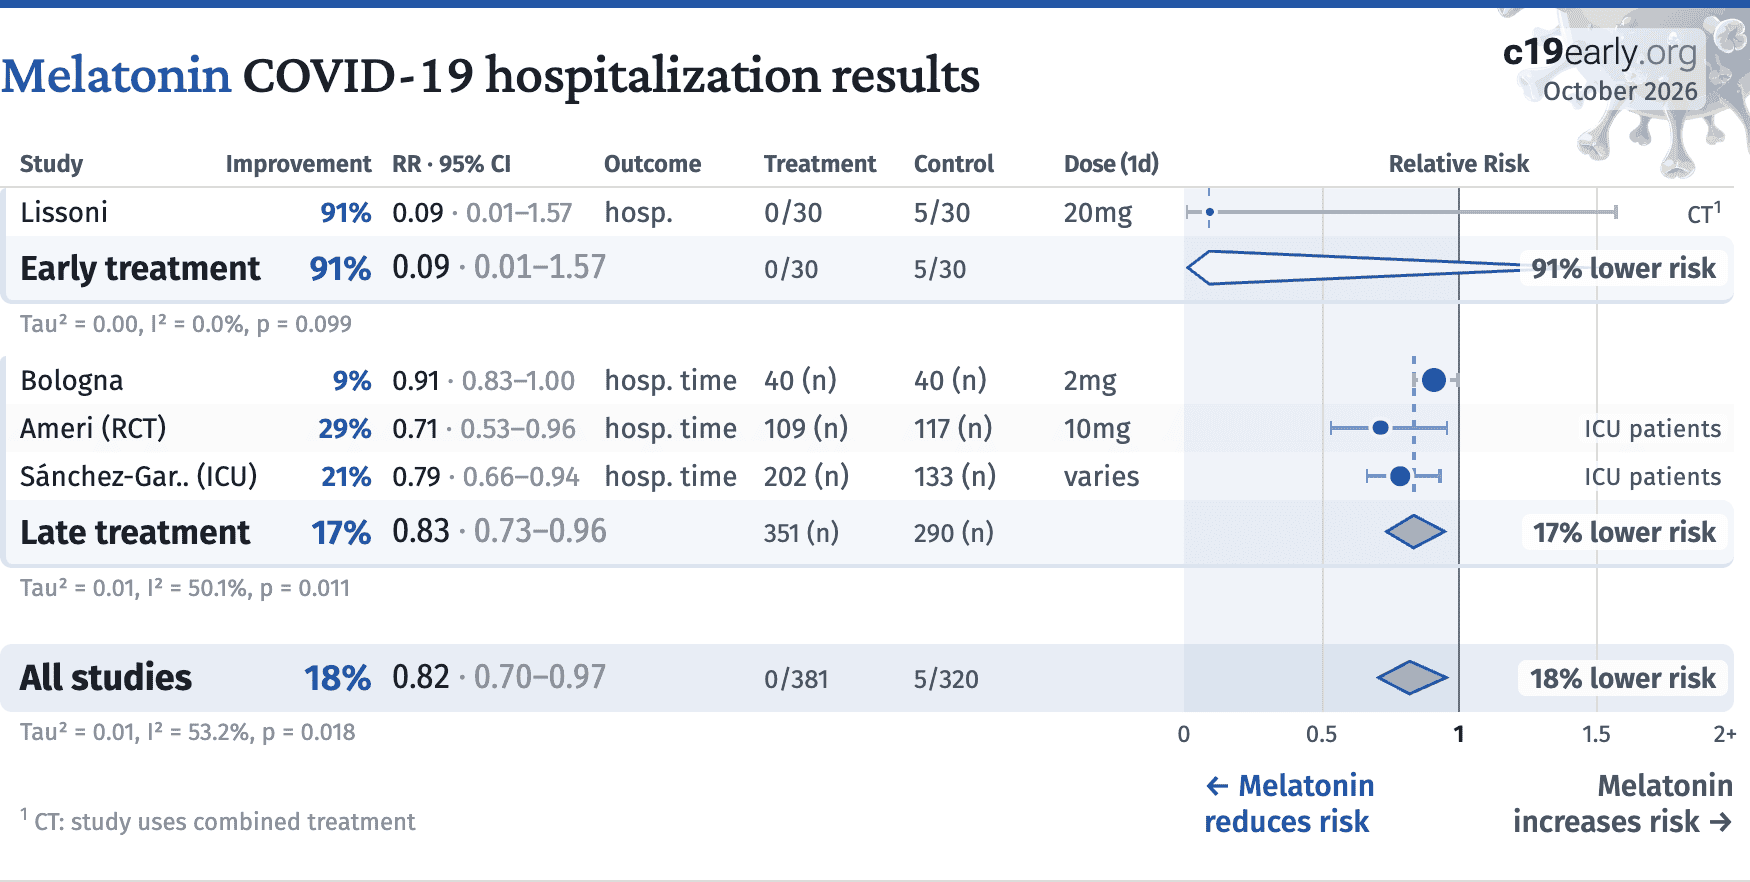
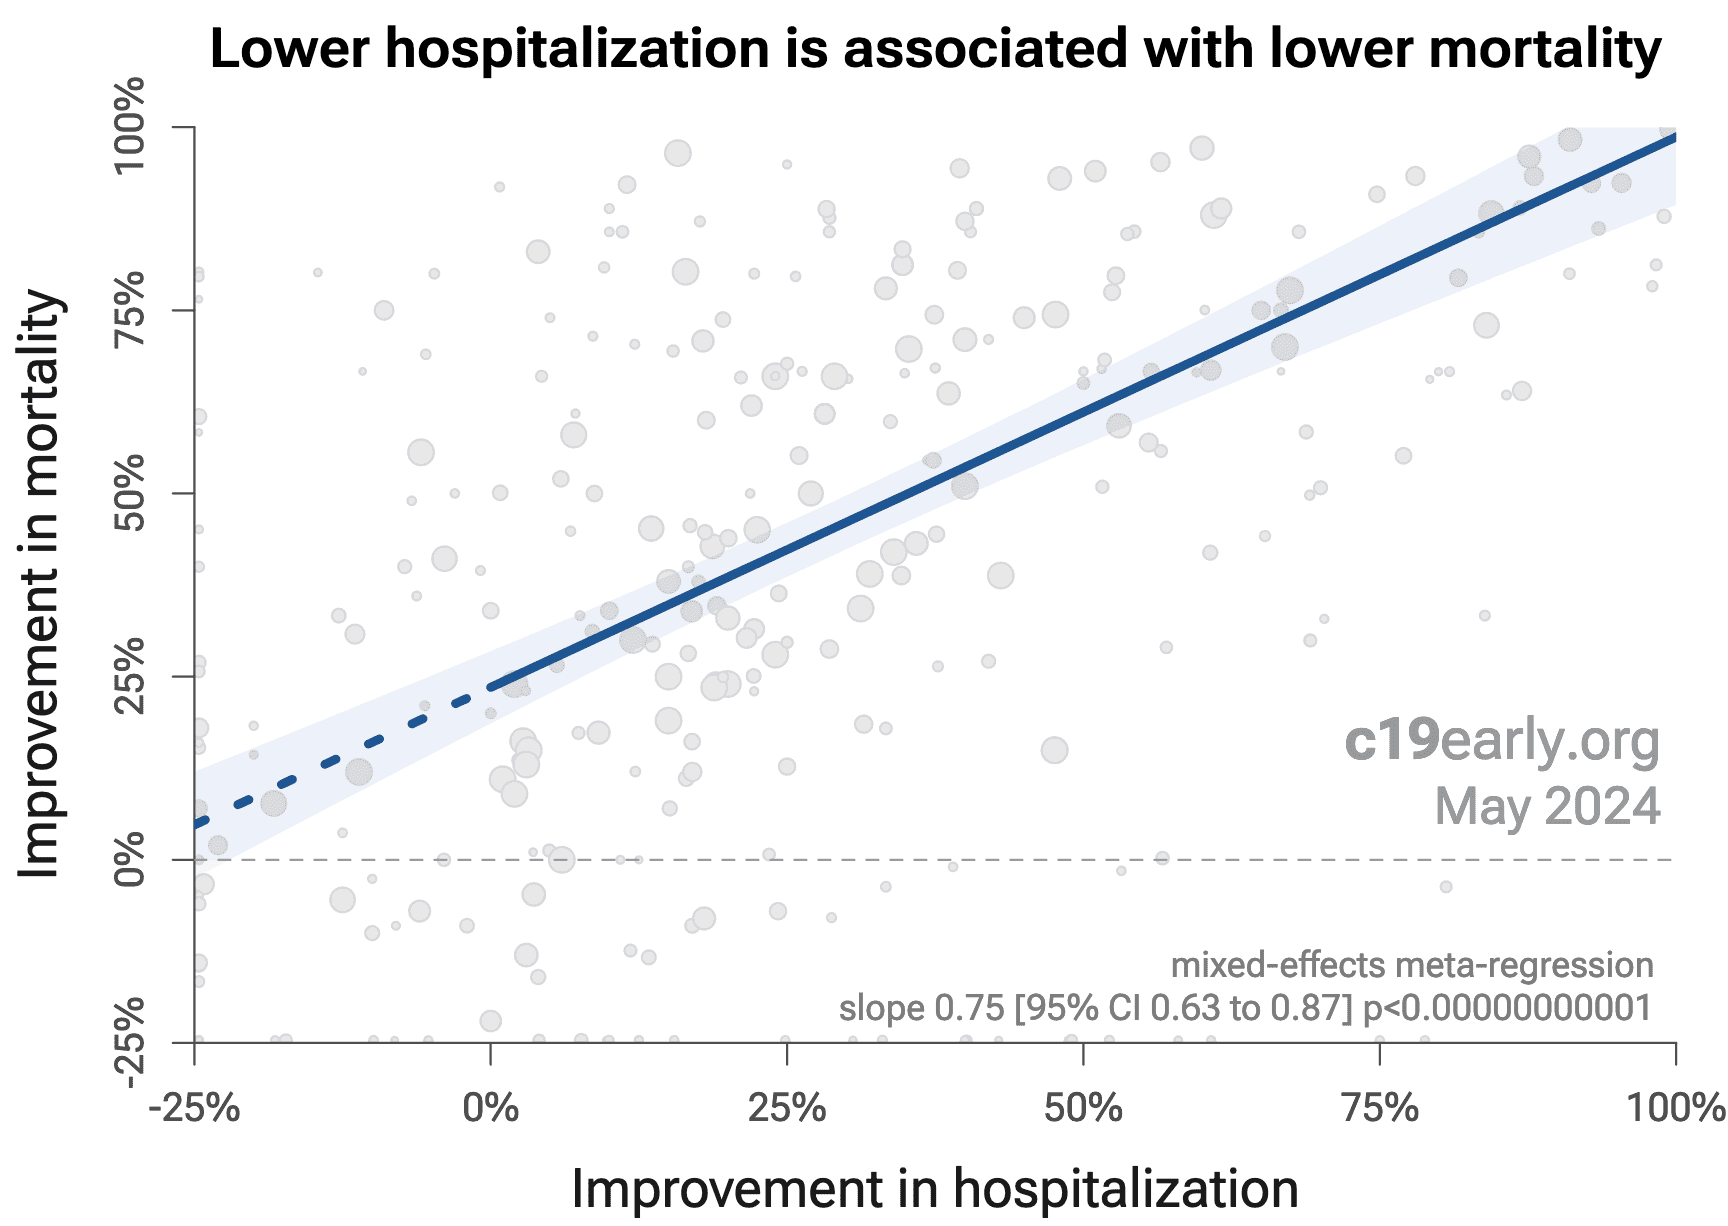
Melatonin COVID-19 hospitalization results
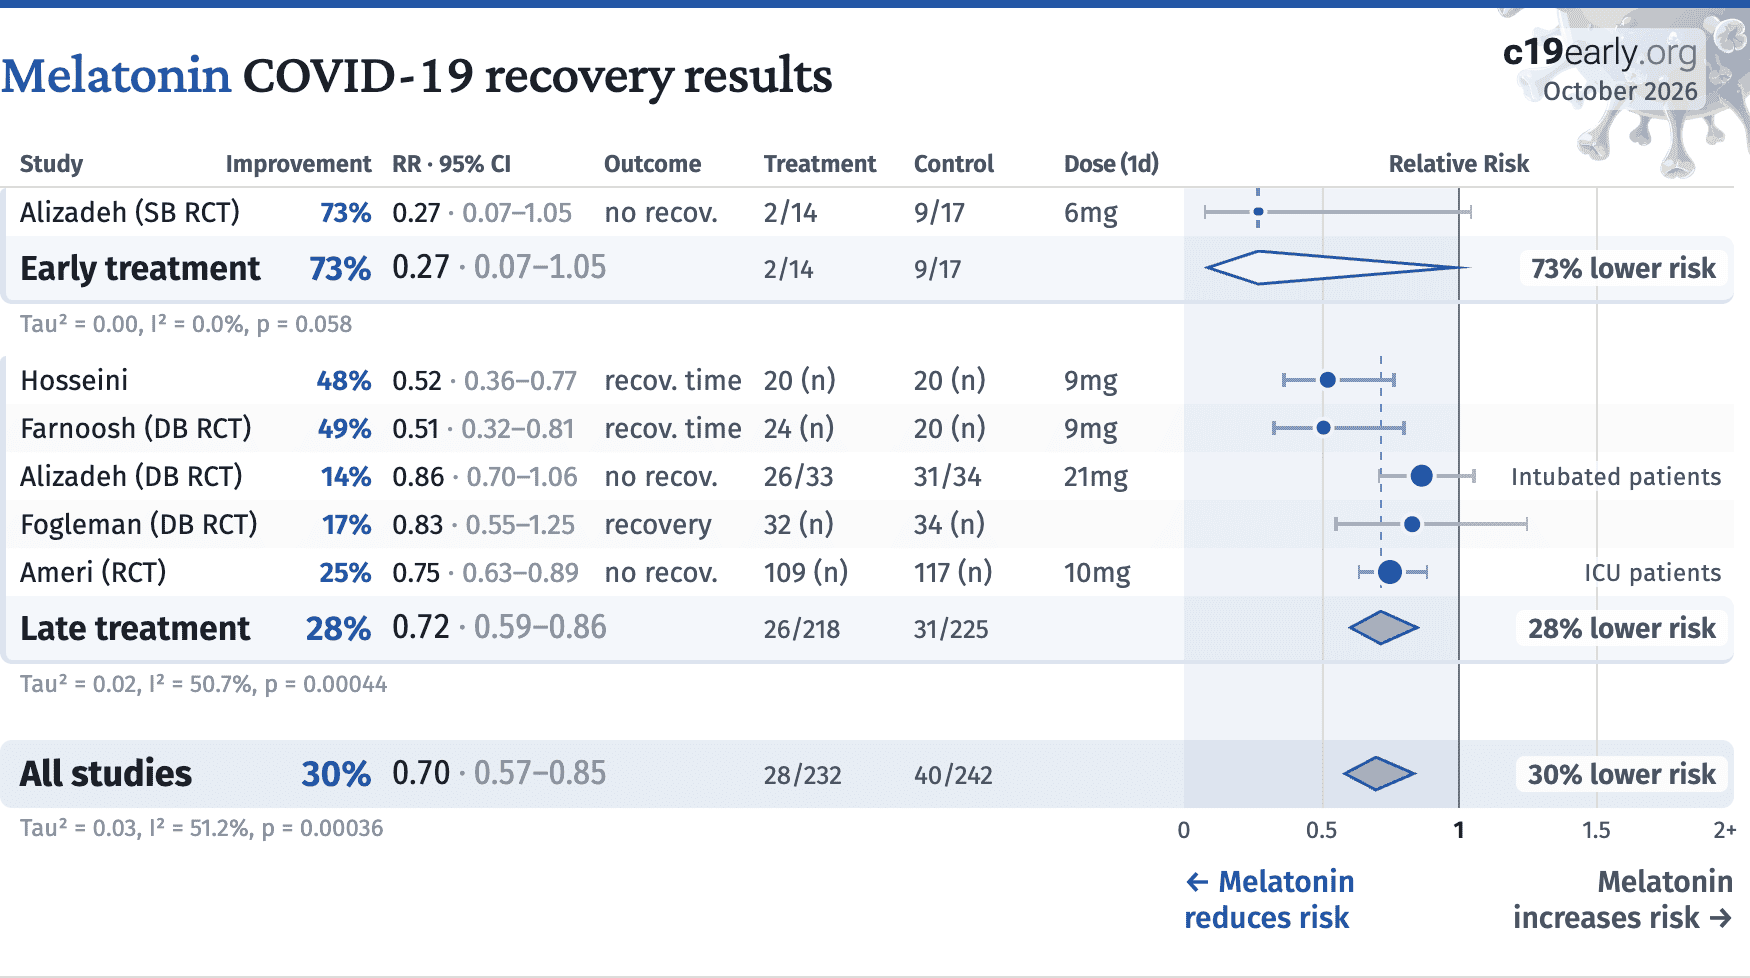
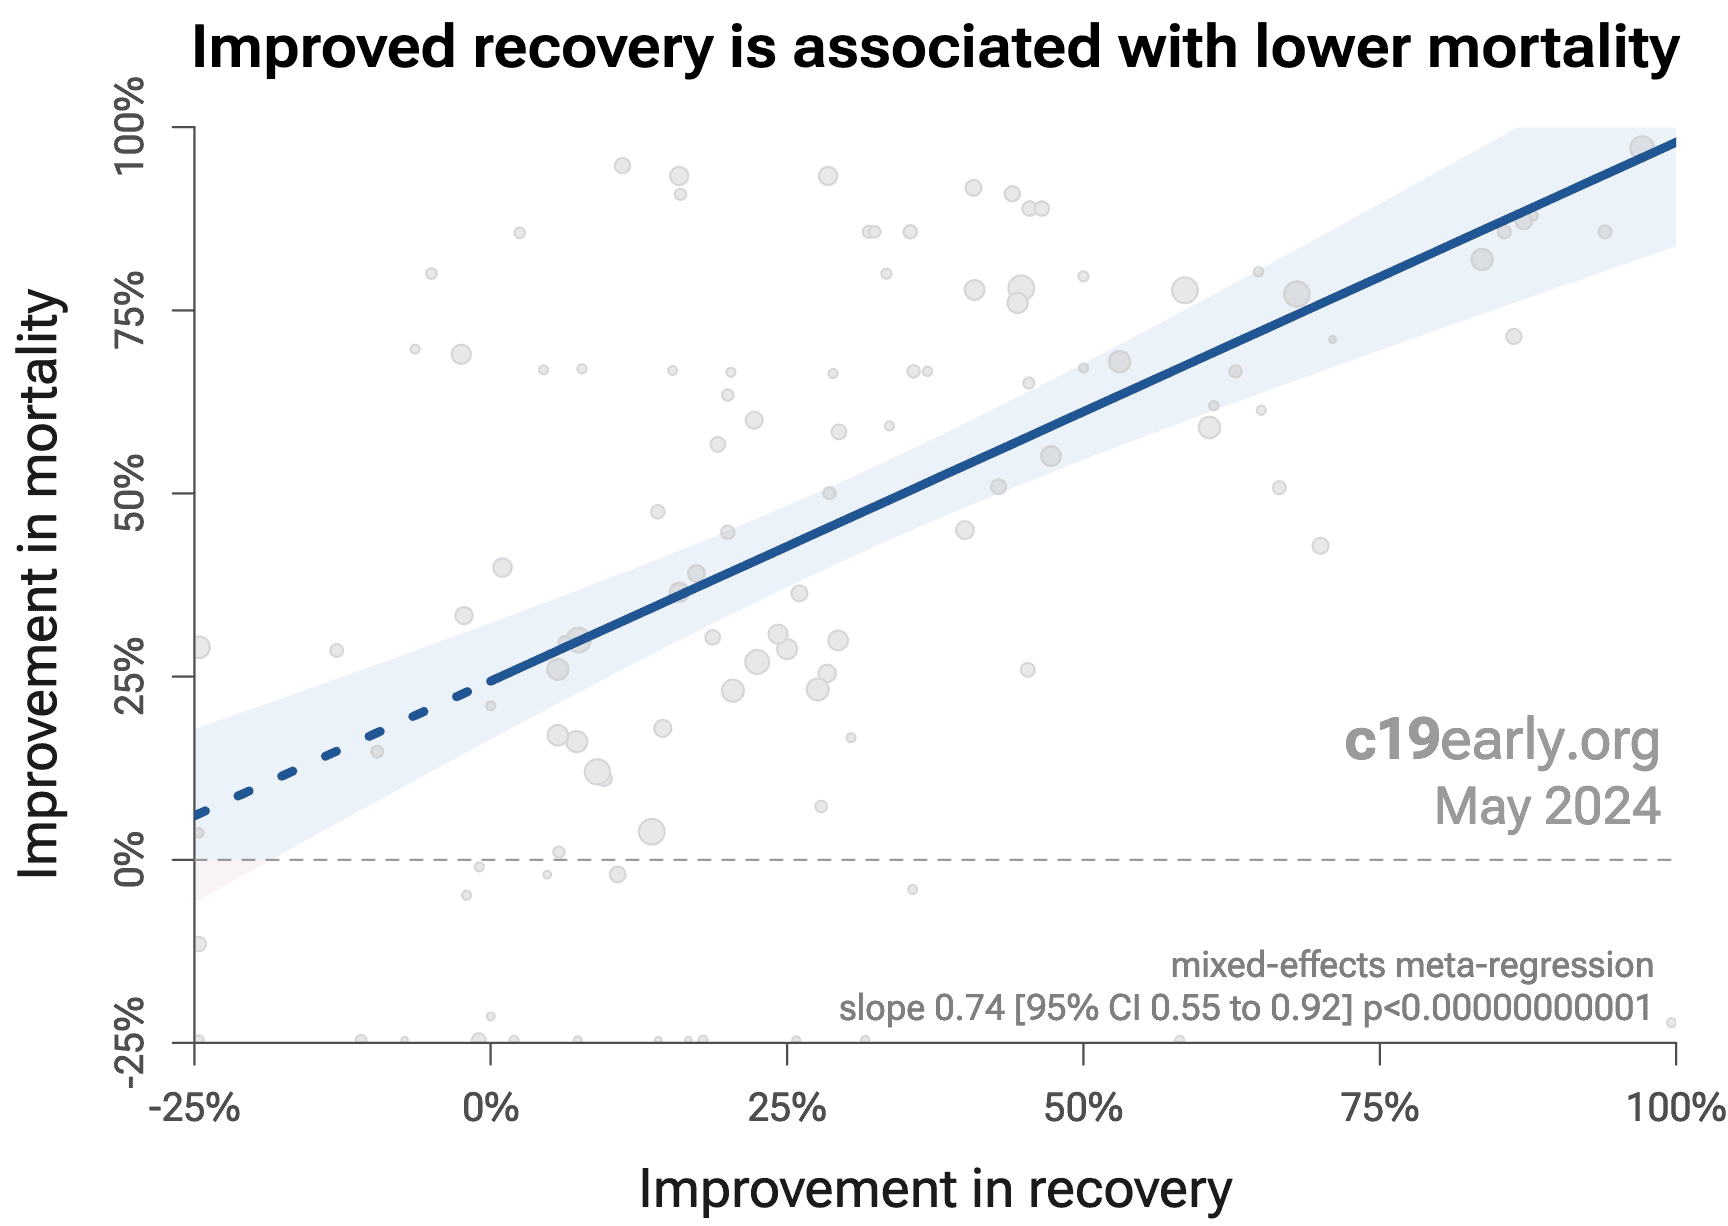
Melatonin COVID-19 recovery results
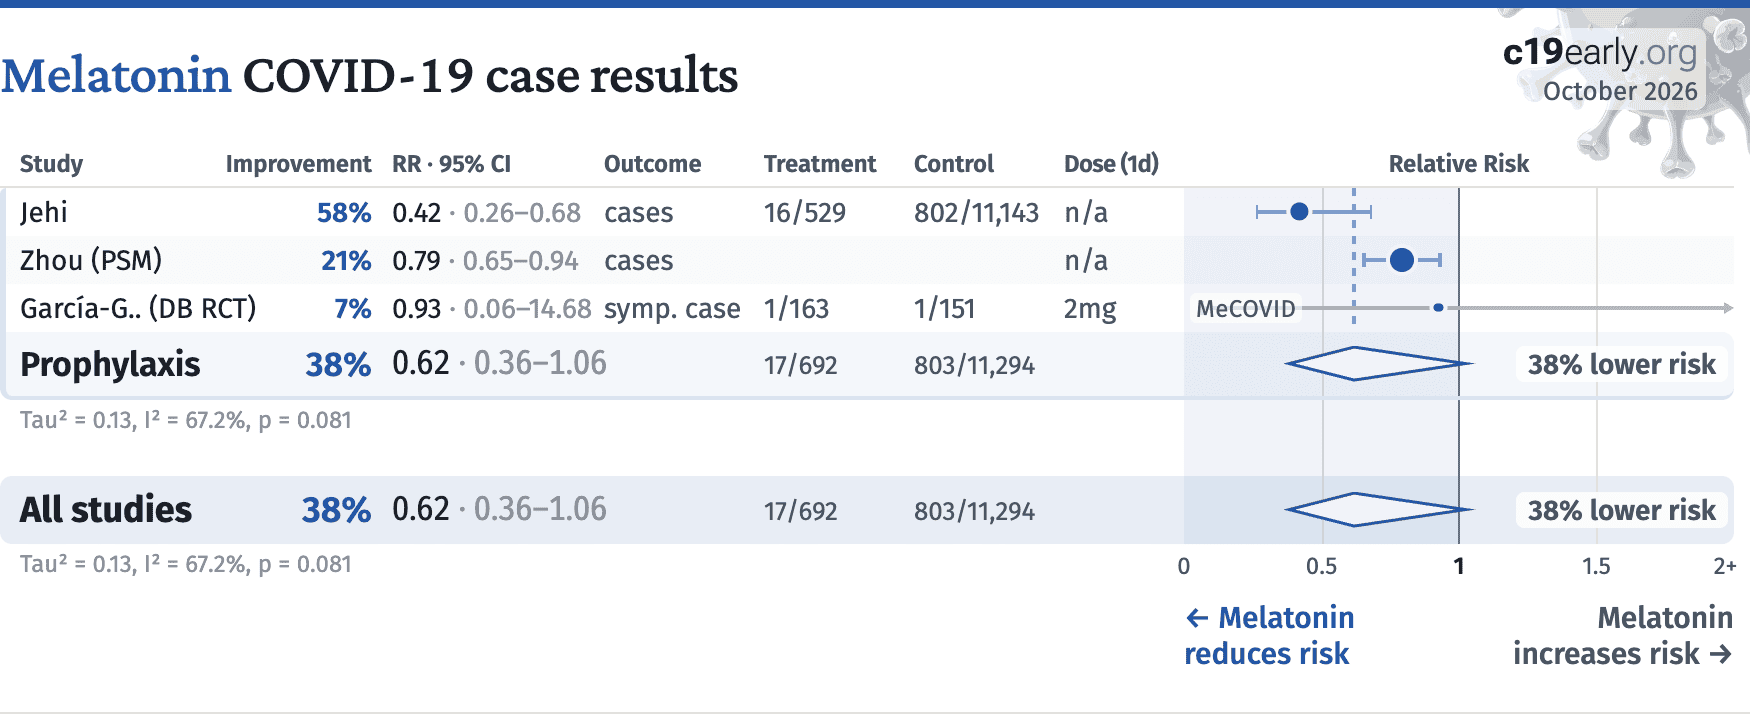
Melatonin COVID-19 case results
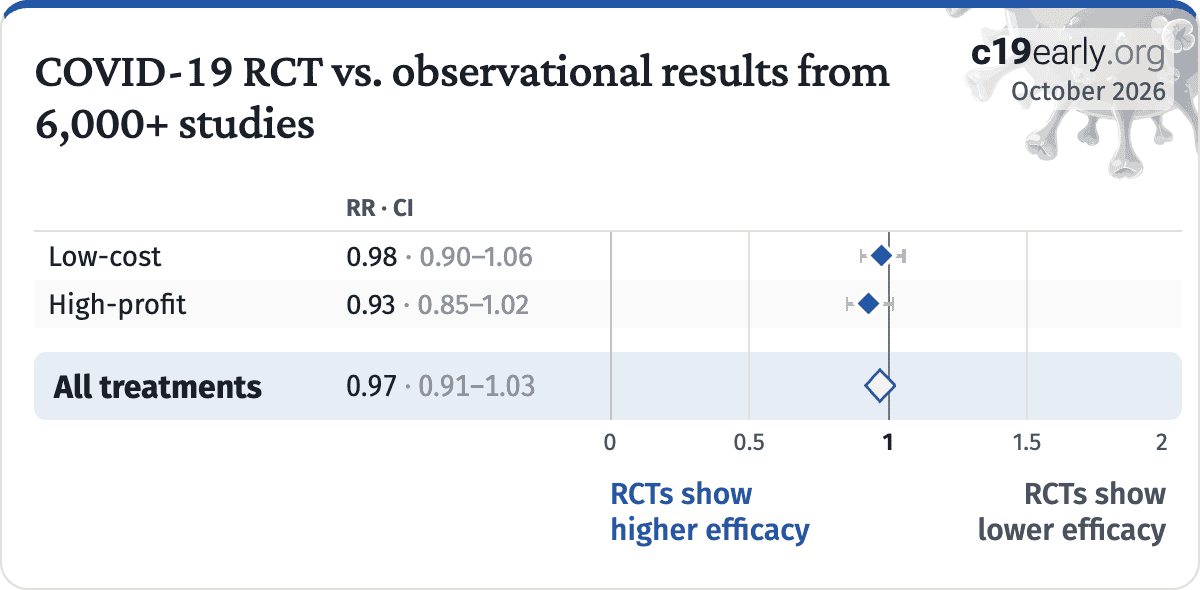
COVID-19 RCT vs. observational results from 6,000+ studies
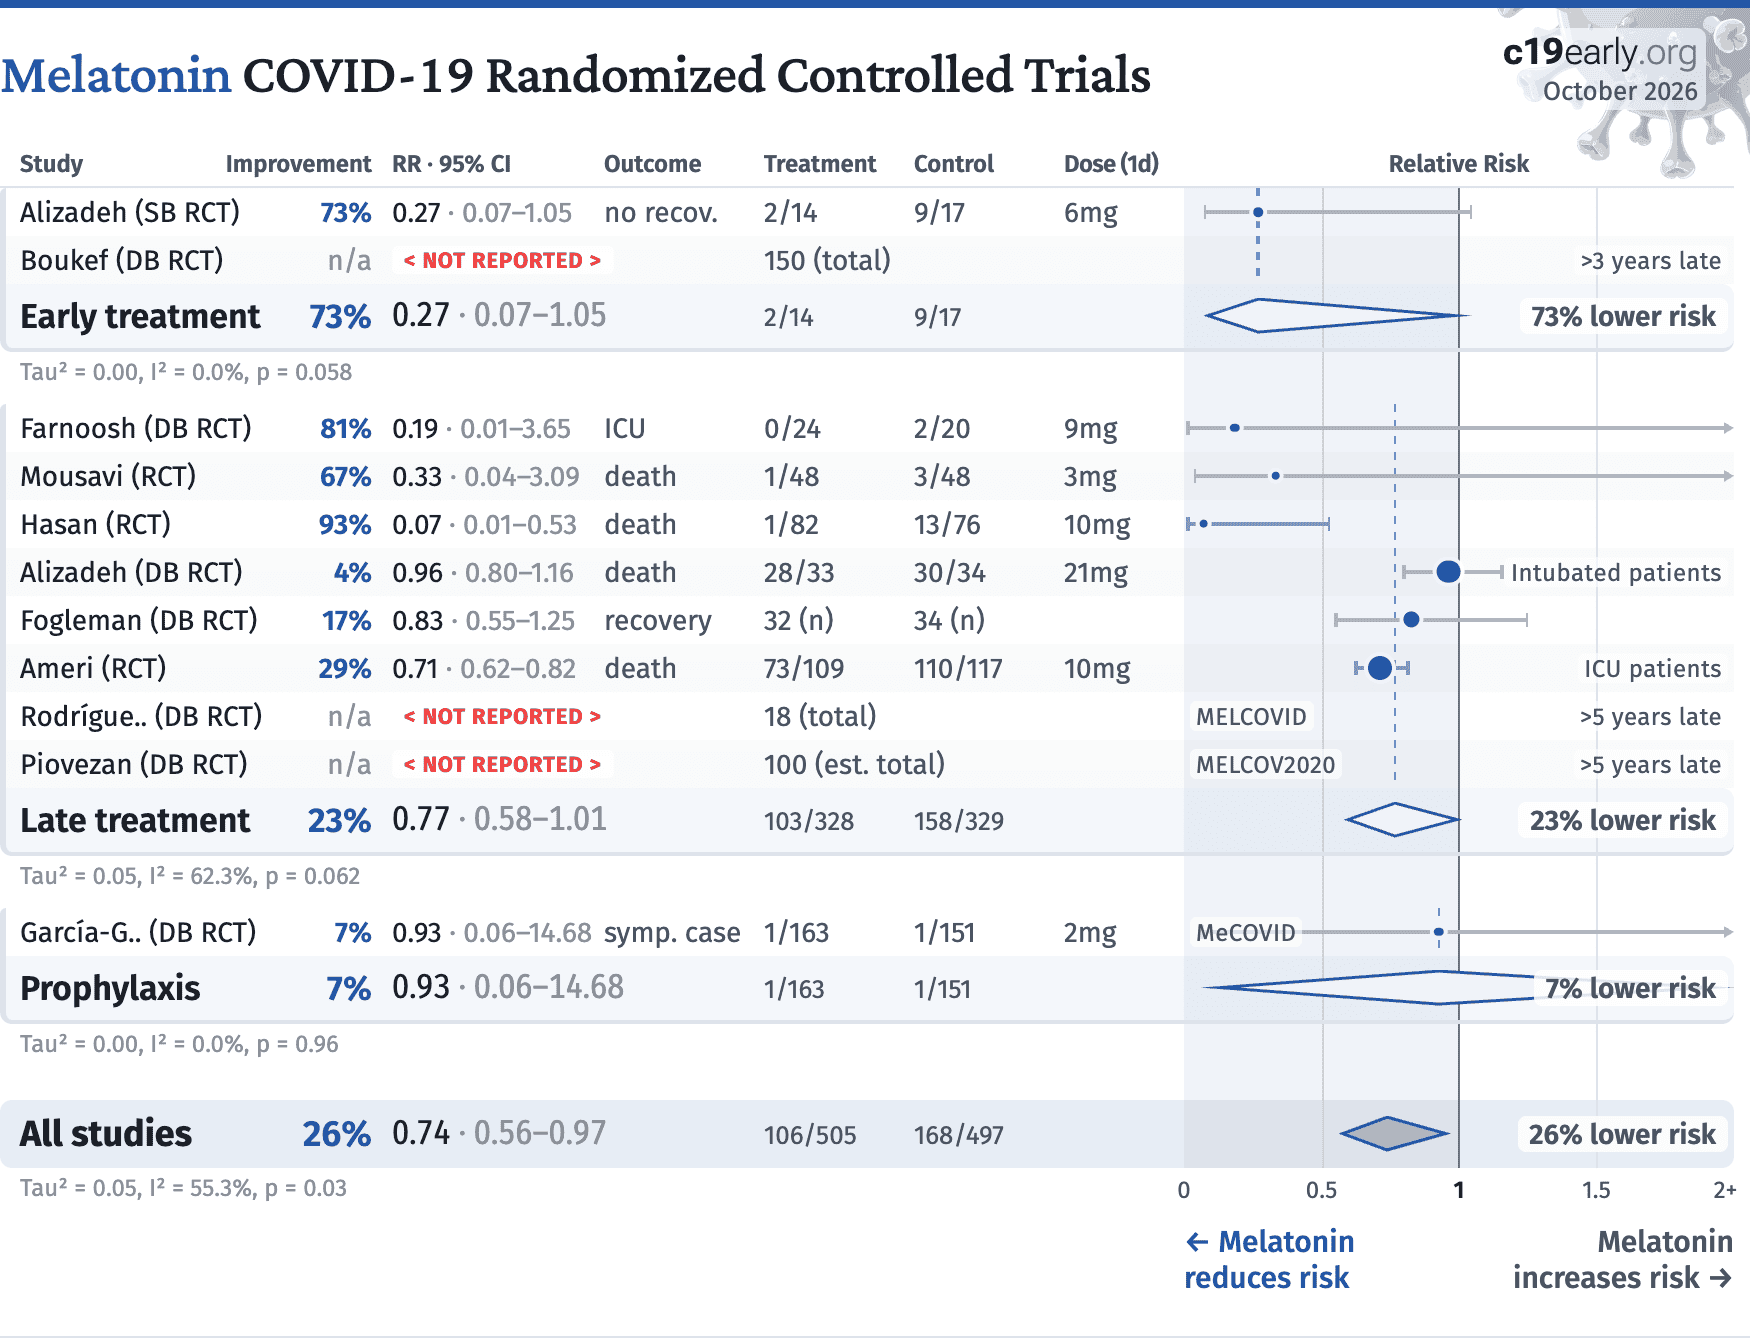
Melatonin COVID-19 Randomized Controlled Trials
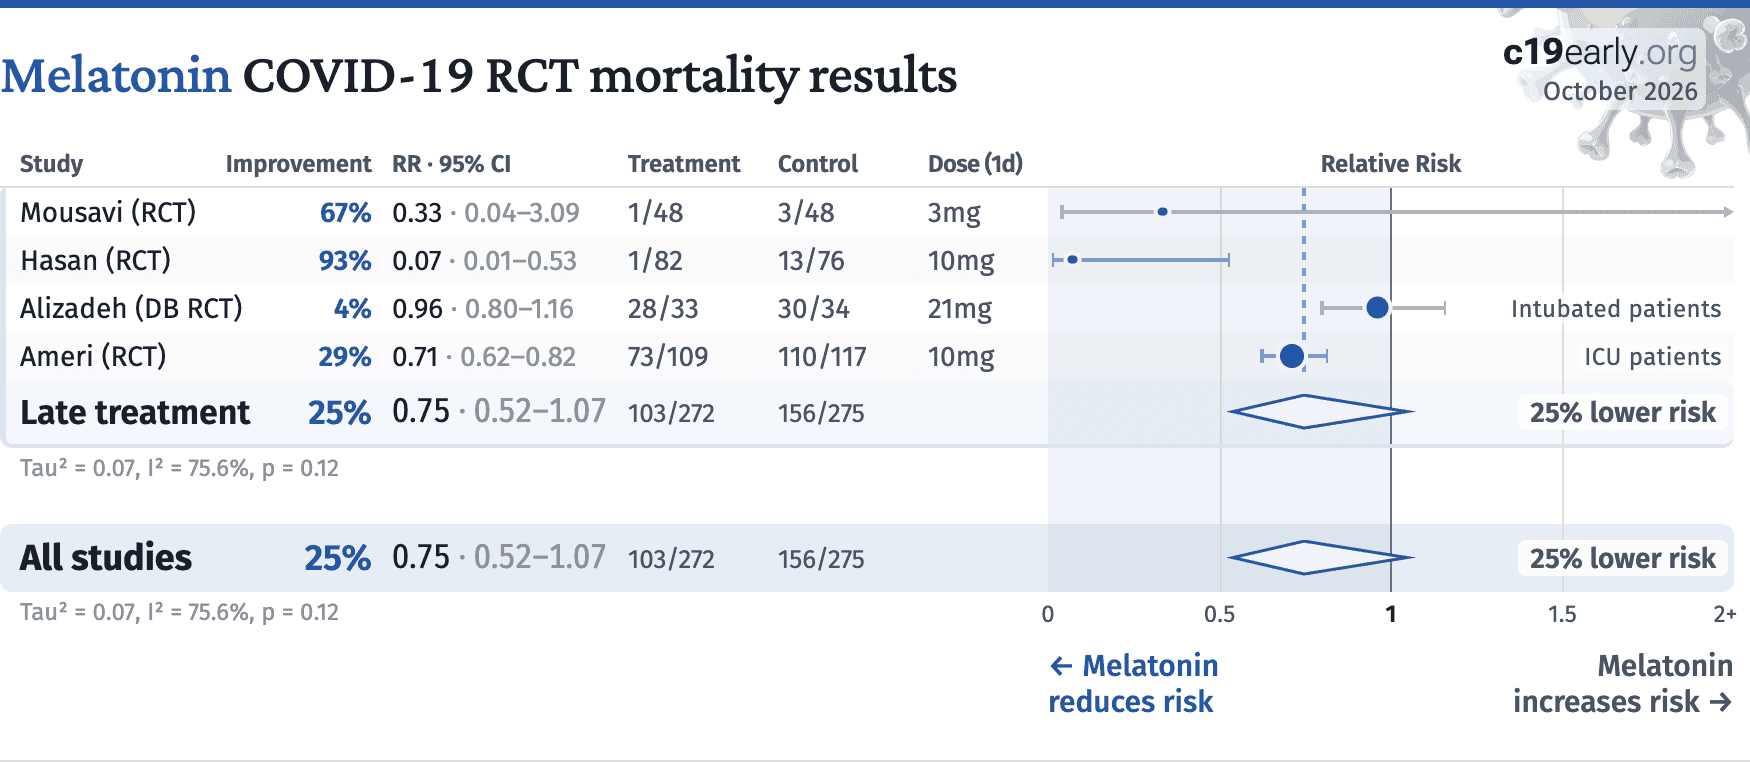
Melatonin COVID-19 RCT mortality results
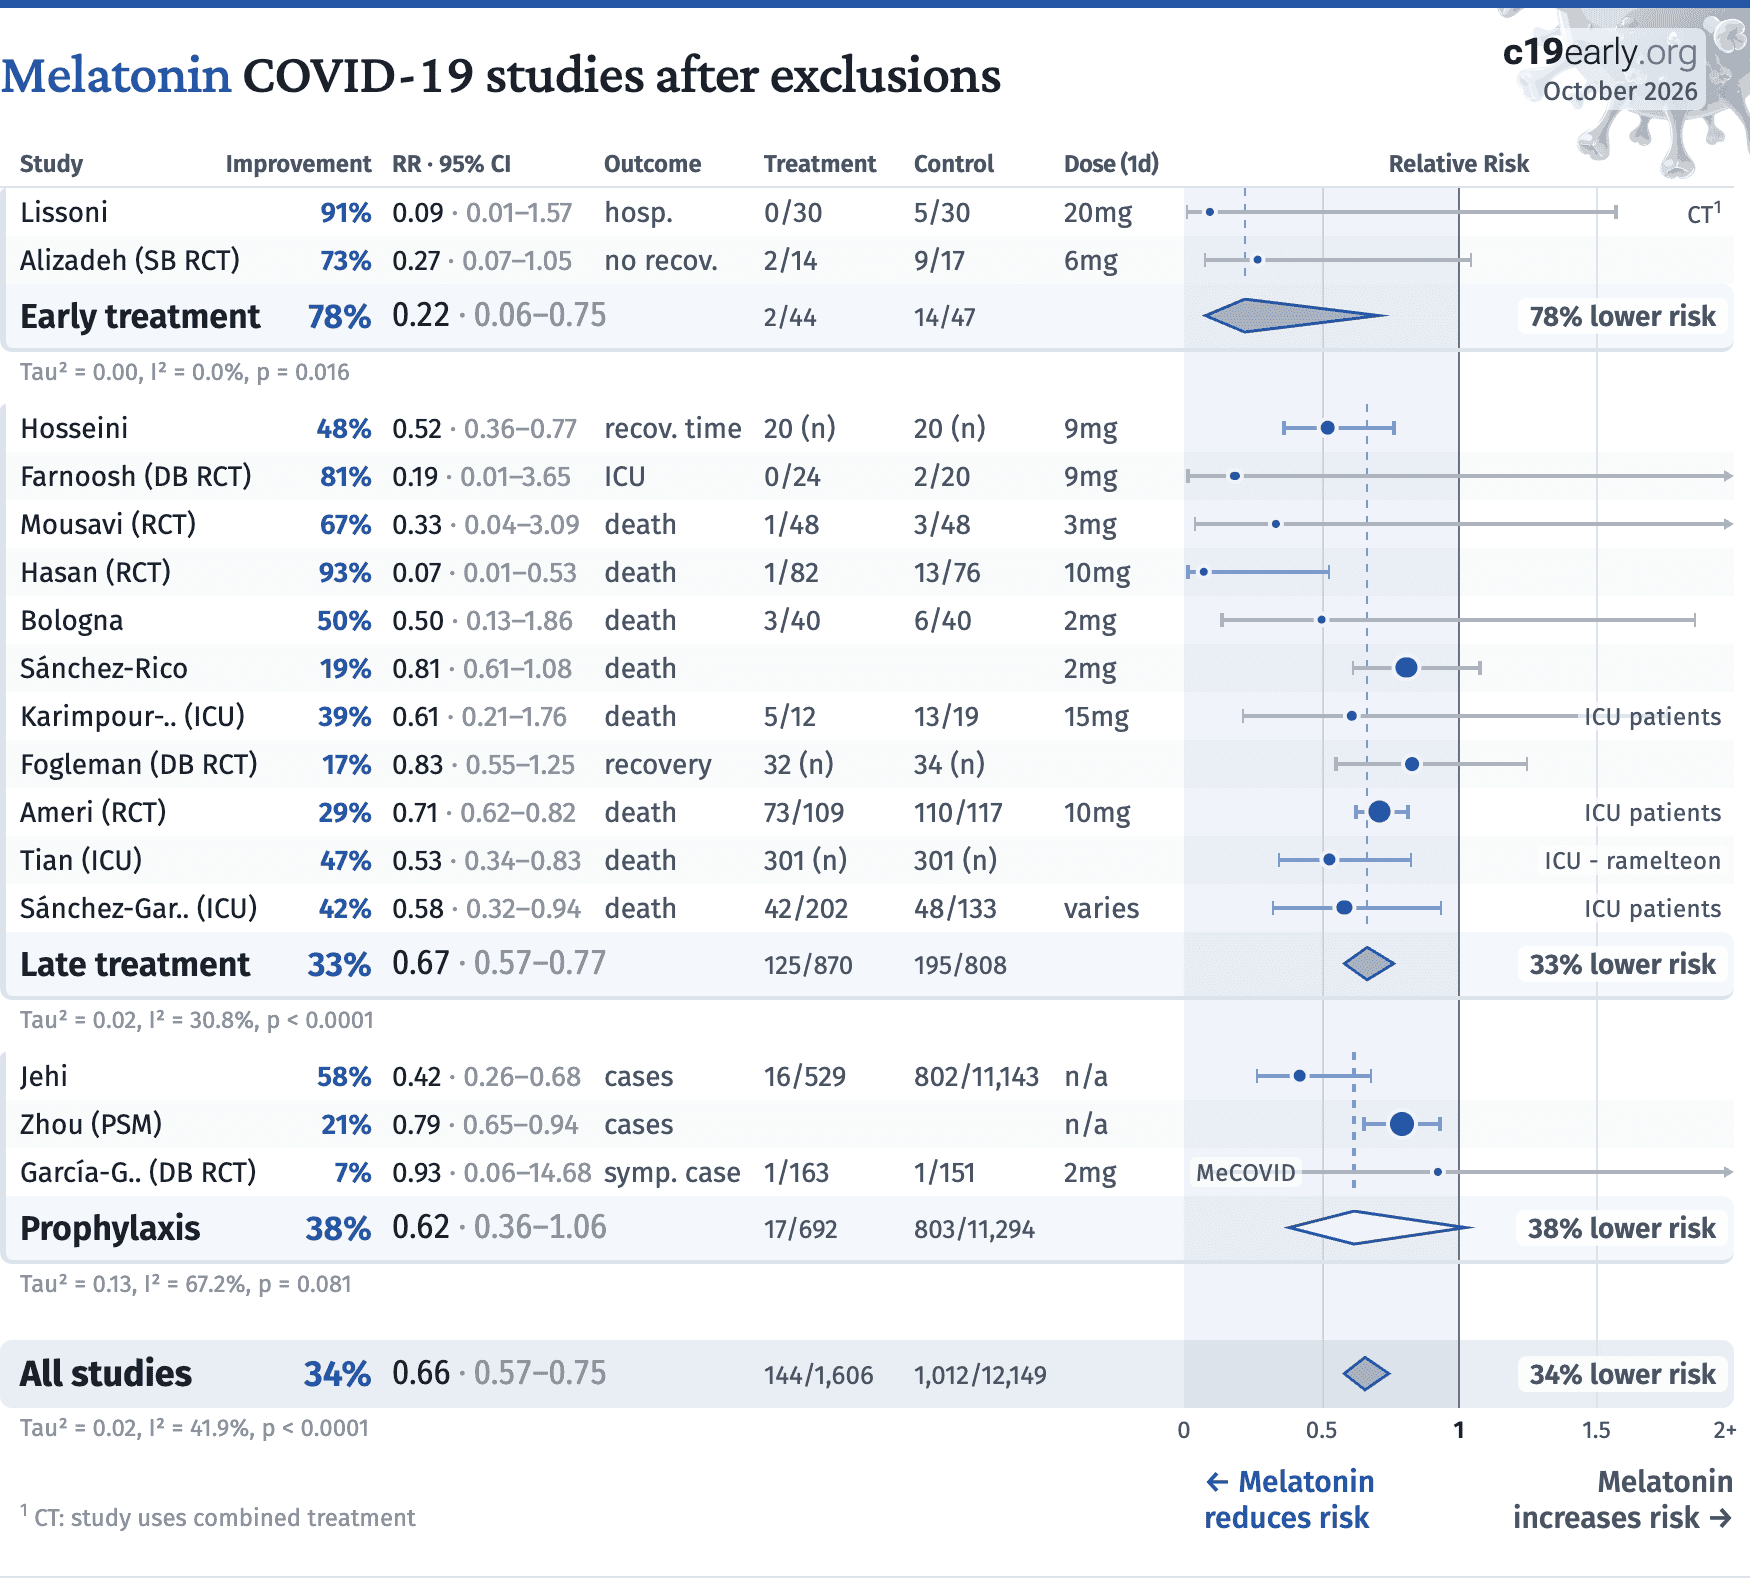
Melatonin COVID-19 studies after exclusions
Media coverage of melatonin for COVID‑19
Media covered none of the 11 studies showing significantly lower risk
No positive melatonin studies were covered
Media bias for low-cost COVID‑19 treatments
Media covered only 0.8% of studies showing significantly lower COVID-19 risk
Only 5 positive studies were covered
one each: budesonide, cannabidiol, fluvoxamine, HCQ, vitamin D
34 negative studies were covered
HCQ 12, ivermectin 6, lopinavir/ritonavir 4, azithromycin 3, vitamin D 3, fluvoxamine 2, one each: ibuprofen, metformin, vitamin C, zinc
Media was 3.8× more likely to cover positive studies
19 positive studies were covered
paxlovid 5, remdesivir 3, casirivimab/imdevimab 2, convalescent plasma 2, molnupiravir 2, one each: antiandrogens, peginterferon lambda, sargramostim, tixagevimab/cilgavimab, tocilizumab
Only 6 negative studies were covered
remdesivir 3, one each: bamlanivimab/etesevimab, bebtelovimab, sotrovimab
| Evidence | Official Acknowledgment | Approx. Delay | |
|---|---|---|---|
| Citrus Fruit (vitamin C) for Scurvy (effectiveness) | 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. | 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. | 48 years |
| Handwashing (lower mortality) | 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. | ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). | ~20+ years |
| Helicobacter pylori (bacteria causes ulcers) | 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. | 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. | ~12 years |
| Asbestos (causes asbestosis & cancer) | 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. | 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. | ~47 years |
| Leaded Gasoline (neurotoxicity) | ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. | 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. | ~49 years |
| Harms of Smoking (causes lung cancer) | 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. | 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. | 25 years |
Early treatment is more effective: baloxavir marboxil
| Tissue and cell coverage | Different compounds have different tissue penetration profiles and efficacy across cell types |
| Variant coverage | Compounds with different viral resistance profiles |
| Intra/extracellular | Disabling and removing intracellular and extracellular viral particles |
| Resistance | Minimizing persistence and emergence of resistant variants |
| Genetics | Robustness against individual variations in efficacy based on genetics |
| Lower doses | Potentially lower doses of individual agents, reducing toxicity |
| Viral and host-directed | Antivirals targeting viral and host proteins |
| Immune system function | Supporting or enhancing natural immune system function |
| Disease phases | Addressing multiple disease phases (viral replication, inflammation, secondary complications) |
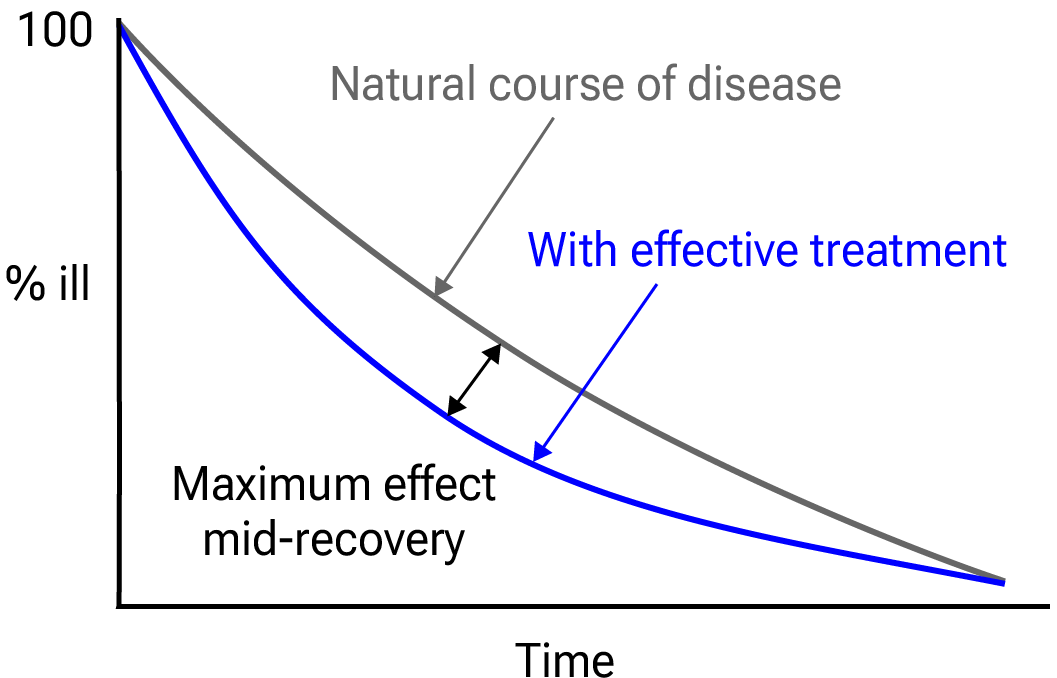
0.1% mortality with early treatment vs. 6.2% with late treatment (49× lower)
Early-treatment physicians treated patients on presentation, while late-treatment physicians followed official guidance with treatment only on hospitalization. Groups are not randomized. Results are subject to selection and ascertainment bias and accurate analysis requires details of the patient populations and followup, however the results are consistent across many teams, and consistent with the extensive controlled clinical evidence showing a significant reduction in risk with many early treatments, and complementary/synergistic benefits with combined treatment.
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →
reduces riskMelatonin
increases risk →

| Alizadeh (B), 5/29/2021, Single Blind Randomized Controlled Trial, Iran, peer-reviewed, 6 authors, study period 30 June, 2020 - 5 August, 2020. | risk of no recovery, 73.0% lower, RR 0.27, p = 0.06, treatment 2 of 14 (14.3%), control 9 of 17 (52.9%), NNT 2.6, day 14. | Boukef, 2/28/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Tunisia, trial NCT05670444 (history). | 150 patient RCT with results unknown and over 3 years late. |
| Lissoni, 12/30/2020, prospective, Italy, peer-reviewed, 14 authors, this trial uses multiple treatments in the treatment arm (combined with cannabidiol and angiotensin 1-7) - results of individual treatments may vary. | risk of hospitalization, 90.9% lower, RR 0.09, p = 0.05, treatment 0 of 30 (0.0%), control 5 of 30 (16.7%), NNT 6.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| Alizadeh, 5/13/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, 11 authors, study period June 2020 - September 2020, excluded in exclusion analyses: extremely late treatment, over 75% control mortality. | risk of death, 3.8% lower, RR 0.96, p = 0.73, treatment 28 of 33 (84.8%), control 30 of 34 (88.2%), NNT 30. |
| risk of no extubation, 13.6% lower, RR 0.86, p = 0.19, treatment 26 of 33 (78.8%), control 31 of 34 (91.2%), NNT 8.1. | |
| ventilation time, 27.0% lower, relative time 0.73, p = 0.09, treatment 33, control 34. | |
| Ameri, 11/19/2022, Randomized Controlled Trial, Iran, peer-reviewed, 9 authors, study period 1 March, 2021 - 30 November, 2021. | risk of death, 28.8% lower, RR 0.71, p < 0.001, treatment 73 of 109 (67.0%), control 110 of 117 (94.0%), NNT 3.7, primary outcome. |
| risk of mechanical ventilation, 27.6% lower, RR 0.72, p = 0.003, treatment 56 of 109 (51.4%), control 83 of 117 (70.9%), NNT 5.1, primary outcome. | |
| clinical status, 25.0% lower, RR 0.75, p = 0.001, treatment 109, control 117, day 14. | |
| recovery time, 25.0% lower, relative time 0.75, p = 0.04, treatment 109, control 117. | |
| hospitalization time, 28.6% lower, relative time 0.71, p = 0.03, treatment 109, control 117. | |
| Bologna, 12/14/2021, retrospective, Italy, peer-reviewed, 3 authors. | risk of death, 50.0% lower, RR 0.50, p = 0.48, treatment 3 of 40 (7.5%), control 6 of 40 (15.0%), NNT 13. |
| risk of ICU admission, 50.0% lower, RR 0.50, p = 0.48, treatment 3 of 40 (7.5%), control 6 of 40 (15.0%), NNT 13. | |
| hospitalization time, 8.7% lower, relative time 0.91, p = 0.05, treatment mean 31.3 (±6.8) n=40, control mean 34.3 (±6.9) n=40. | |
| relative sub-intensive hospitalization time, 38.8% better, relative time 0.61, p < 0.001, treatment mean 12.3 (±3.0) n=40, control mean 20.1 (±6.1) n=40. | |
| relative NIV time, 58.4% better, relative time 0.42, p < 0.001, treatment mean 5.2 (±3.0) n=40, control mean 12.5 (±4.2) n=40. | |
| relative high flow oxygen time, 7.8% better, relative time 0.92, p = 0.35, treatment mean 7.1 (±2.5) n=40, control mean 7.7 (±3.2) n=40. | |
| relative sleep time, 18.2% better, RR 0.82, p < 0.001, treatment mean 5.5 (±0.8) n=40, control mean 4.5 (±1.2) n=40. | |
| delirium, 33.3% lower, RR 0.67, p < 0.001, treatment mean 2.2 (±1.1) n=40, control mean 3.3 (±1.3) n=40. | |
| Farnoosh, 6/23/2021, Double Blind Randomized Controlled Trial, Iran, peer-reviewed, 12 authors, study period 25 April, 2020 - 5 June, 2020, average treatment delay 7.0 days. | risk of ICU admission, 81.5% lower, RR 0.19, p = 0.20, treatment 0 of 24 (0.0%), control 2 of 20 (10.0%), NNT 10.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm). |
| recovery time, 49.0% lower, relative time 0.51, p = 0.004, treatment 24, control 20. | |
| risk of no hospital discharge, 44.4% lower, RR 0.56, p = 0.65, treatment 2 of 24 (8.3%), control 3 of 20 (15.0%), NNT 15. | |
| time to discharge, 42.9% lower, relative time 0.57, p = 0.02, treatment 24, control 20. | Fernandez-Tresguerres, 3/31/2022, Spain, trial NCT05596617 (history). | 335 patient study with results unknown and over 4 years late. |
| Fogleman, 7/27/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, mean age 52.0, 7 authors, study period 5 October, 2020 - 21 June, 2021, average treatment delay 6.0 days, trial NCT04530539 (history). | relative recovery, 17.3% better, RR 0.83, p = 0.38, treatment mean 20.33 (±16.4) n=32, control mean 16.82 (±15.7) n=34, mid-recovery, relative symptom improvement, day 9. |
| Hasan, 10/12/2021, Randomized Controlled Trial, Iraq, peer-reviewed, 3 authors, study period 1 December, 2020 - 1 June, 2021. | risk of death, 92.9% lower, RR 0.07, p < 0.001, treatment 1 of 82 (1.2%), control 13 of 76 (17.1%), NNT 6.3. |
| Hosseini, 5/17/2021, prospective, Iran, peer-reviewed, 9 authors. | recovery time, 47.6% lower, relative time 0.52, p = 0.001, treatment 20, control 20. |
| Karimpour-razkenari, 3/10/2022, retrospective, Iran, peer-reviewed, 6 authors, study period 13 March, 2020 - 30 May, 2020. | risk of death, 39.0% lower, HR 0.61, p = 0.37, treatment 5 of 12 (41.7%), control 13 of 19 (68.4%), NNT 3.7, Kaplan-Meier. |
| ventilation time, 42.9% lower, relative time 0.57, p = 0.13, treatment 12, control 19. | |
| ICU time, 1.9% lower, relative time 0.98, p = 0.85, treatment 12, control 19. | |
| Mousavi, 8/30/2021, Randomized Controlled Trial, Iran, peer-reviewed, 7 authors, study period 14 April, 2020 - 15 June, 2020. | risk of death, 66.7% lower, RR 0.33, p = 0.62, treatment 1 of 48 (2.1%), control 3 of 48 (6.2%), NNT 24, day 10. |
| risk of ICU admission, 40.0% lower, RR 0.60, p = 0.41, treatment 6 of 48 (12.5%), control 10 of 48 (20.8%), NNT 12, day 10. | Piovezan, 3/1/2021, Double Blind Randomized Controlled Trial, placebo-controlled, Brazil, trial NCT04470297 (history) (MELCOV2020). | Estimated 100 patient RCT with results unknown and over 5 years late. | Rodríguez-Rubio, 8/5/2020, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, trial NCT04568863 (history) (MELCOVID). | 18 patient RCT with results unknown and over 5 years late. |
| Sánchez-García, 7/21/2025, prospective, Spain, peer-reviewed, 23 authors, study period 30 March, 2020 - 27 April, 2021. | risk of death, 41.9% lower, RR 0.58, p = 0.002, treatment 42 of 202 (20.8%), control 48 of 133 (36.1%), NNT 6.5, adjusted per study, odds ratio converted to relative risk, day 90. |
| risk of mechanical ventilation, 54.0% lower, OR 0.46, p = 0.002, treatment 202, control 133, adjusted per study, day 90, RR approximated with OR. | |
| ICU time, 31.2% lower, relative time 0.69, p = 0.002, treatment 11.0 [5.0-24.0] n=202, control 16.0 [7.5-33.5] n=133. | |
| hospitalization time, 21.4% lower, relative time 0.79, p = 0.007, treatment 22.0 [15.0-36.25] n=202, control 28.0 [19.5-41.0] n=133. | |
| Sánchez-González, 7/20/2021, retrospective, Spain, peer-reviewed, 4 authors, excluded in exclusion analyses: immortal-time bias may significantly affect results. | risk of death, 54.4% lower, RR 0.46, p < 0.001, treatment 24 of 224 (10.7%), control 53 of 224 (23.7%), NNT 7.7, odds ratio converted to relative risk, PSM. |
| Sánchez-Rico, 2/5/2022, retrospective, France, peer-reviewed, 6 authors, study period 24 January, 2020 - 31 October, 2021. | risk of death, 19.0% lower, RR 0.81, p = 0.15, treatment 82 of 272 (30.1%), control 6,487 of 58,290 (11.1%), adjusted per study, model b. |
| Tian, 5/19/2025, retrospective, China, peer-reviewed, 3 authors. | risk of death, 47.0% lower, HR 0.53, p = 0.005, treatment 301, control 301, adjusted per study, propensity score matching, multivariable, ramelteon. |
| García-García, 2/21/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Spain, peer-reviewed, 25 authors, study period April 2020 - December 2020, trial NCT04353128 (history) (MeCOVID). | risk of symptomatic case, 7.4% lower, RR 0.93, p = 1.00, treatment 1 of 163 (0.6%), control 1 of 151 (0.7%), NNT 2051, primary outcome. |
| risk of case, 108.4% higher, RR 2.08, p = 0.26, treatment 9 of 163 (5.5%), control 4 of 151 (2.6%), post-hoc primary outcome. | |
| Jehi, 6/10/2020, retrospective, USA, peer-reviewed, 8 authors. | risk of case, 58.0% lower, RR 0.42, p < 0.001, treatment 16 of 529 (3.0%), control 802 of 11,143 (7.2%), NNT 24, development cohort. |
| risk of case, 99.7% lower, RR 0.003, p = 0.09, treatment 0 of 18 (0.0%), control 290 of 2,005 (14.5%), NNT 6.9, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), Florida validation cohort. | |
| Zhou (B), 11/6/2020, retrospective, propensity score matching, USA, peer-reviewed, 18 authors. | risk of case, 21.1% lower, RR 0.79, p = 0.01, treatment 222 of 1,055 (21.0%), control 8,052 of 25,724 (31.3%), NNT 9.7, odds ratio converted to relative risk, PSM. |