October 2026
Melatonin COVID-19 outcomes
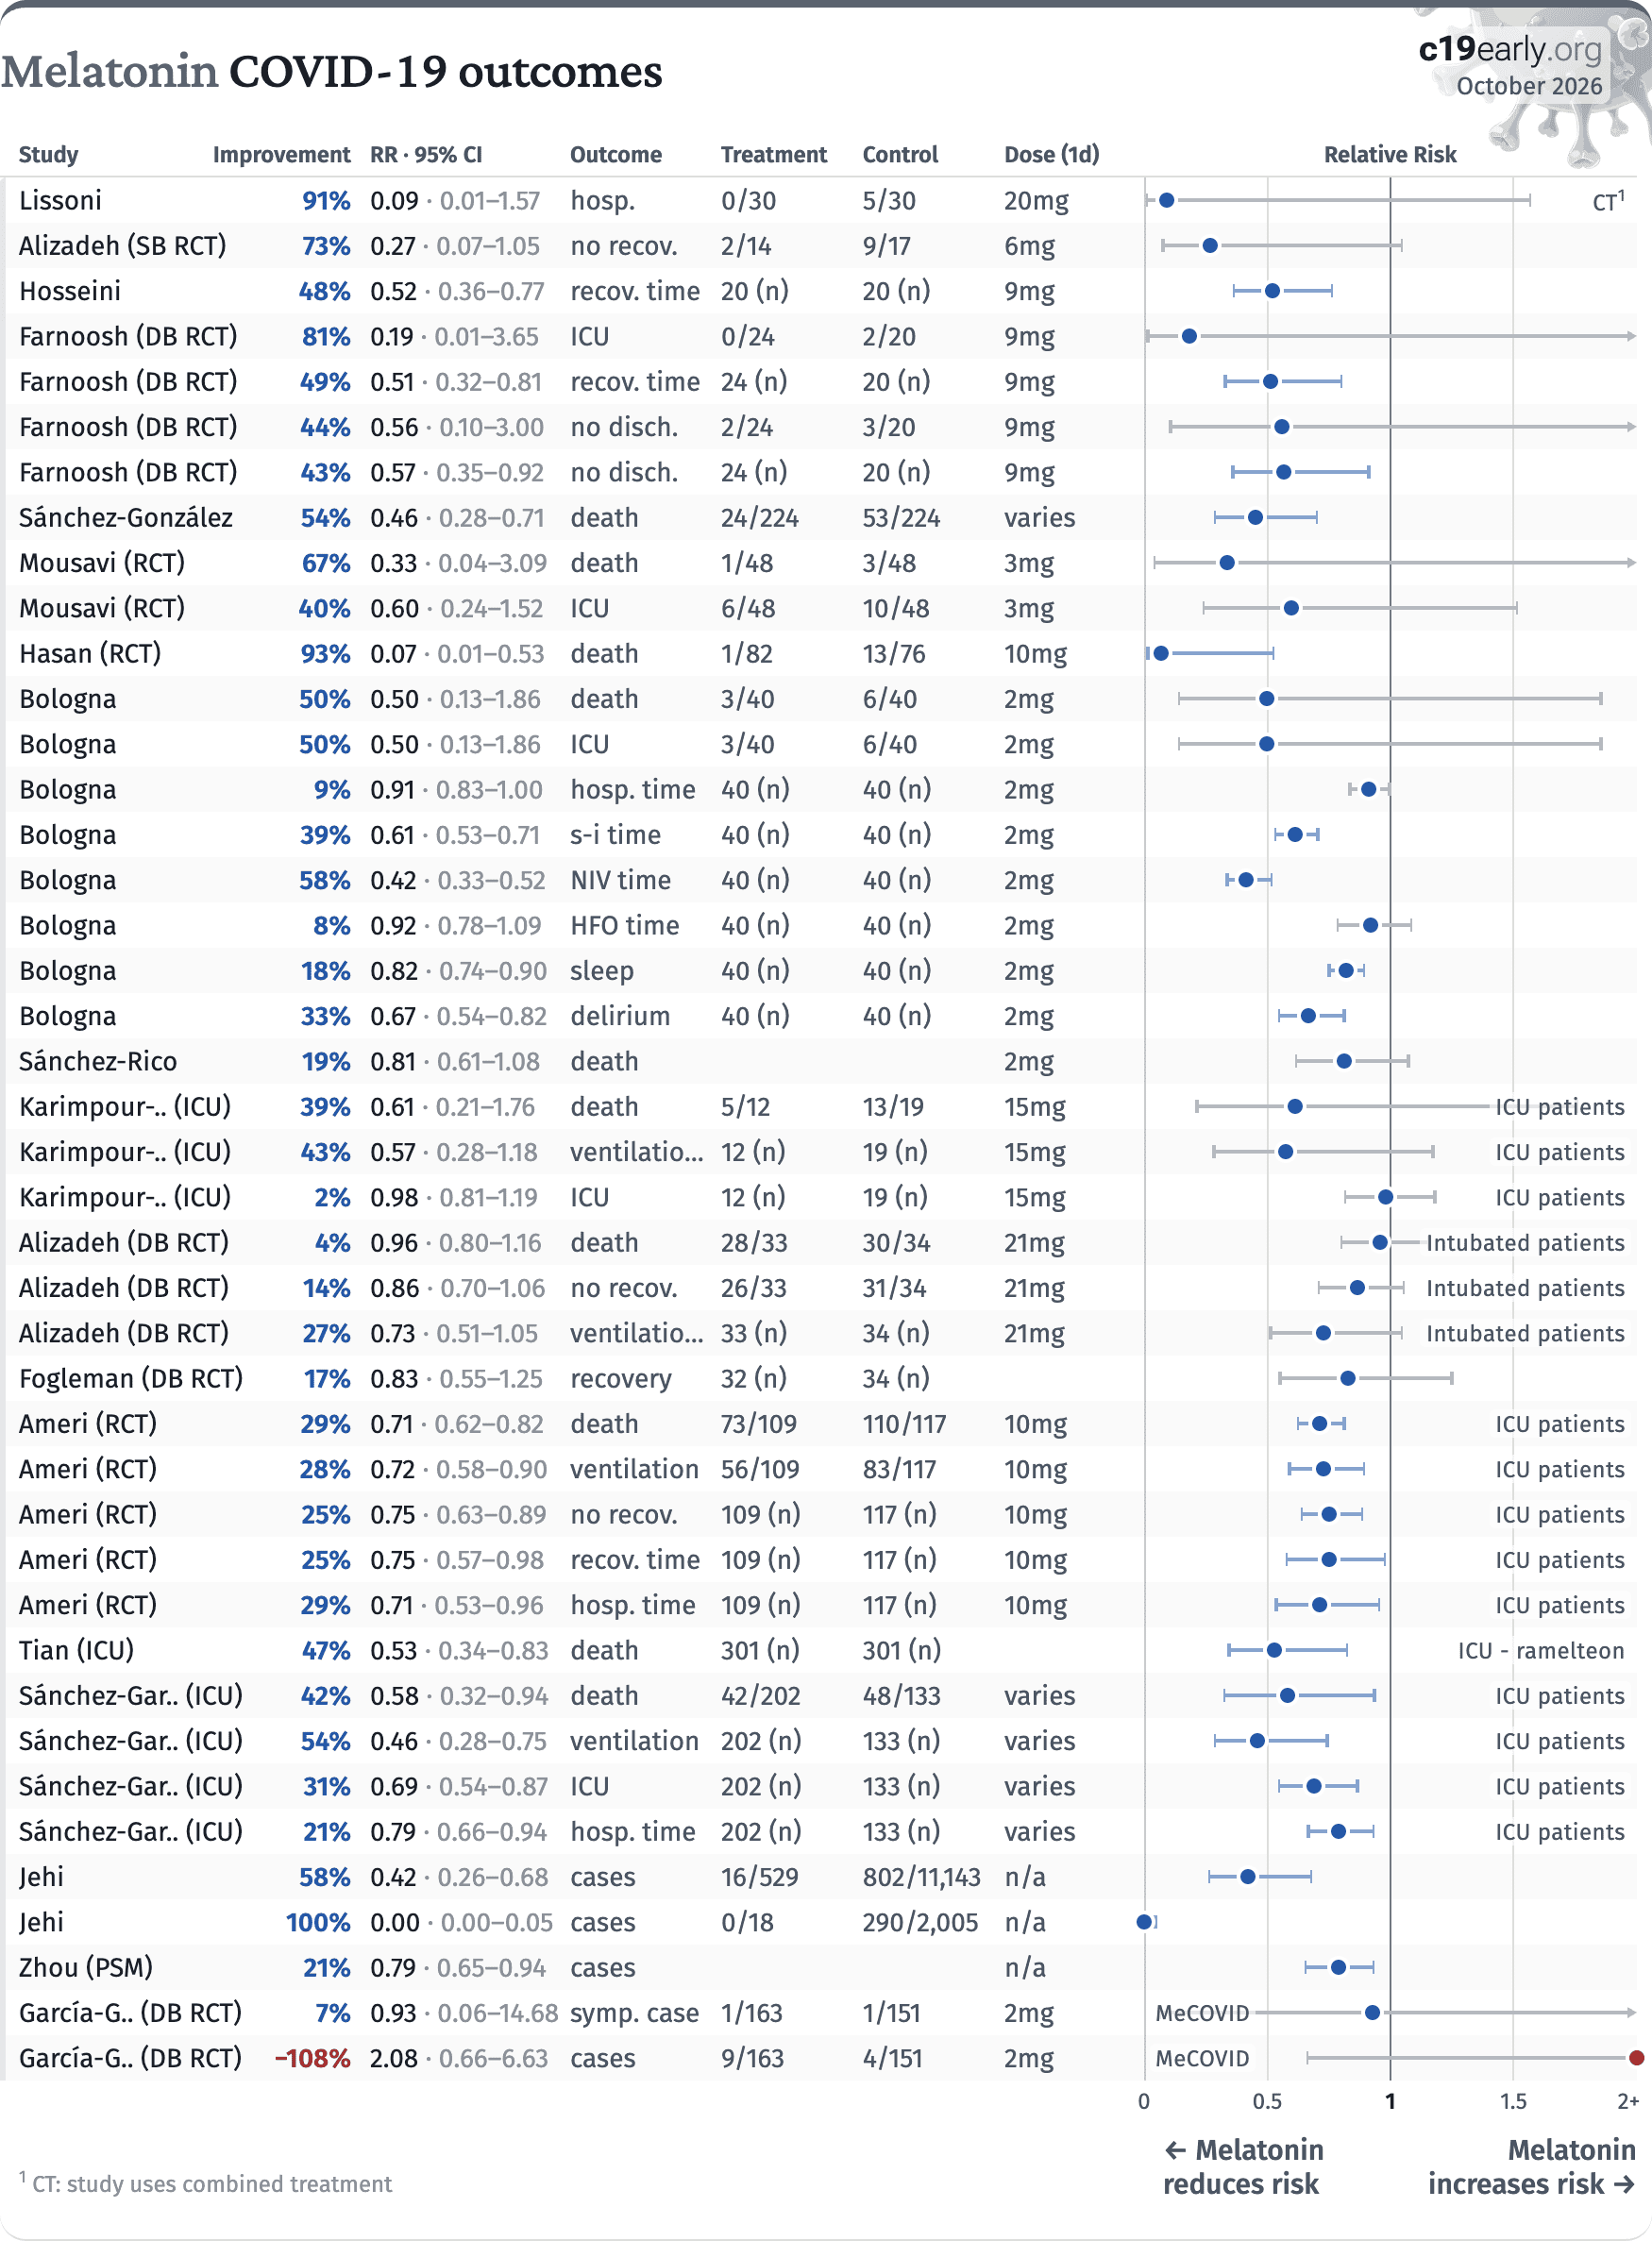
StudyImprovementRR · 95% CIOutcomeTreatmentControlDose (1d)Relative Risk
Lissoni91%0.09 · 0.01–1.57hosp.0/305/3020mgCT1
Alizadeh (SB RCT)73%0.27 · 0.07–1.05no recov.2/149/176mg
Hosseini48%0.52 · 0.36–0.77recov. time20 (n)20 (n)9mg
Farnoosh (DB RCT)81%0.19 · 0.01–3.65ICU0/242/209mg
Farnoosh (DB RCT)49%0.51 · 0.32–0.81recov. time24 (n)20 (n)9mg
Farnoosh (DB RCT)44%0.56 · 0.10–3.00no disch.2/243/209mg
Farnoosh (DB RCT)43%0.57 · 0.35–0.92no disch.24 (n)20 (n)9mg
Sánchez-González54%0.46 · 0.28–0.71death24/22453/224varies
Mousavi (RCT)67%0.33 · 0.04–3.09death1/483/483mg
Mousavi (RCT)40%0.60 · 0.24–1.52ICU6/4810/483mg
Hasan (RCT)93%0.07 · 0.01–0.53death1/8213/7610mg
Bologna50%0.50 · 0.13–1.86death3/406/402mg
Bologna50%0.50 · 0.13–1.86ICU3/406/402mg
Bologna9%0.91 · 0.83–1.00hosp. time40 (n)40 (n)2mg
Bologna39%0.61 · 0.53–0.71s-i time40 (n)40 (n)2mg
Bologna58%0.42 · 0.33–0.52NIV time40 (n)40 (n)2mg
Bologna8%0.92 · 0.78–1.09HFO time40 (n)40 (n)2mg
Bologna18%0.82 · 0.74–0.90sleep40 (n)40 (n)2mg
Bologna33%0.67 · 0.54–0.82delirium40 (n)40 (n)2mg
Sánchez-Rico19%0.81 · 0.61–1.08death2mg
Karimpour-.. (ICU)39%0.61 · 0.21–1.76death5/1213/1915mgICU patients
Karimpour-.. (ICU)43%0.57 · 0.28–1.18ventilation time12 (n)19 (n)15mgICU patients
Karimpour-.. (ICU)2%0.98 · 0.81–1.19ICU12 (n)19 (n)15mgICU patients
Alizadeh (DB RCT)4%0.96 · 0.80–1.16death28/3330/3421mgIntubated patients
Alizadeh (DB RCT)14%0.86 · 0.70–1.06no recov.26/3331/3421mgIntubated patients
Alizadeh (DB RCT)27%0.73 · 0.51–1.05ventilation time33 (n)34 (n)21mgIntubated patients
Fogleman (DB RCT)17%0.83 · 0.55–1.25recovery32 (n)34 (n)
Ameri (RCT)29%0.71 · 0.62–0.82death73/109110/11710mgICU patients
Ameri (RCT)28%0.72 · 0.58–0.90ventilation56/10983/11710mgICU patients
Ameri (RCT)25%0.75 · 0.63–0.89no recov.109 (n)117 (n)10mgICU patients
Ameri (RCT)25%0.75 · 0.57–0.98recov. time109 (n)117 (n)10mgICU patients
Ameri (RCT)29%0.71 · 0.53–0.96hosp. time109 (n)117 (n)10mgICU patients
Tian (ICU)47%0.53 · 0.34–0.83death301 (n)301 (n)ICU - ramelteon
Sánchez-Gar.. (ICU)42%0.58 · 0.32–0.94death42/20248/133variesICU patients
Sánchez-Gar.. (ICU)54%0.46 · 0.28–0.75ventilation202 (n)133 (n)variesICU patients
Sánchez-Gar.. (ICU)31%0.69 · 0.54–0.87ICU202 (n)133 (n)variesICU patients
Sánchez-Gar.. (ICU)21%0.79 · 0.66–0.94hosp. time202 (n)133 (n)variesICU patients
Jehi58%0.42 · 0.26–0.68cases16/529802/11,143n/a
Jehi100%0.00 · 0.00–0.05cases0/18290/2,005n/a
Zhou (PSM)21%0.79 · 0.65–0.94casesn/a
García-G.. (DB RCT)7%0.93 · 0.06–14.68symp. case1/1631/1512mgMeCOVID
García-G.. (DB RCT)−108%2.08 · 0.66–6.63cases9/1634/1512mgMeCOVID
00.511.52+