Exercise reduces COVID-19 risk: real-time meta-analysis of 68 studies

October 2026

Media coverage of exercise for COVID‑19

Media covered only 8% of studies showing significantly lower COVID-19 risk

Only 4 positive exercise studies were covered

8%
Abstract
Significantly lower risk is seen for mortality, ventilation, ICU admission, hospitalization, progression, recovery, and cases. 52 studies from 52 independent teams in 24 countries show significant benefit.
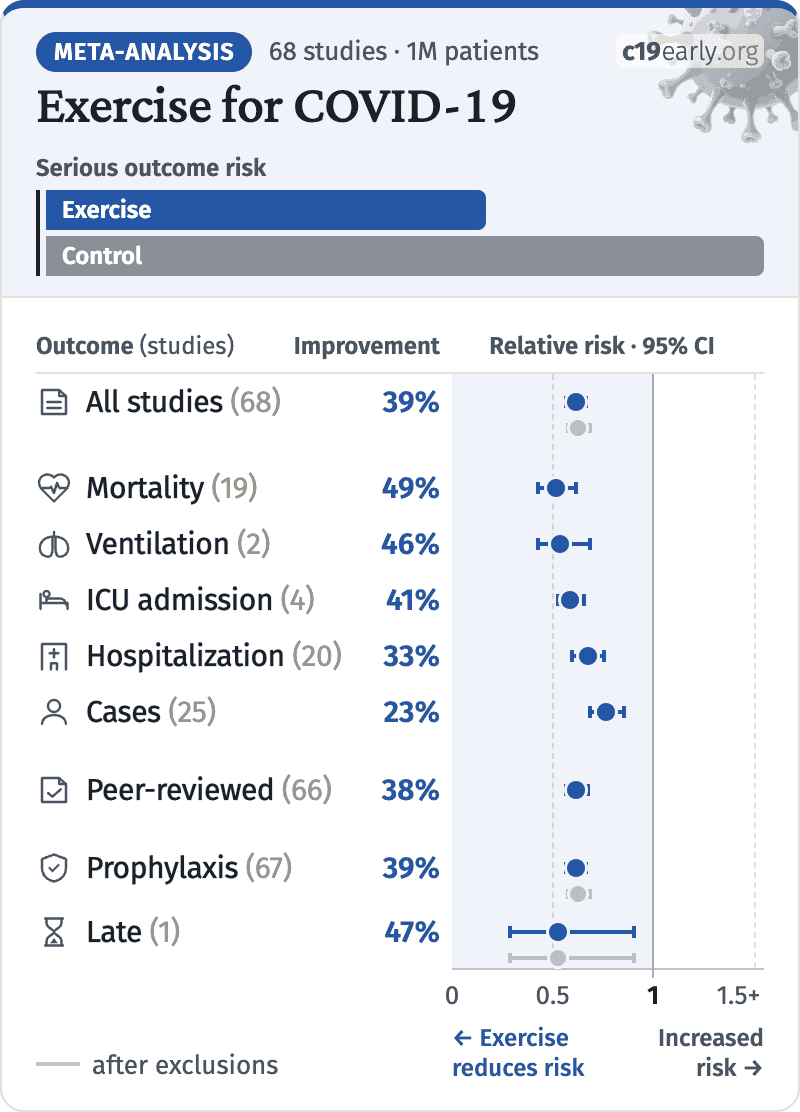
Meta-analysis using the most serious outcome reported shows 39% [33‑44%] lower risk. Results are similar for higher quality and peer-reviewed studies.
Results are very robust—in worst case exclusion sensitivity analysis 56 of 68 studies must be excluded before statistical significance is lost. Emergent results for the efficacy gradient across outcomes (p = 0.00059) that match the biological mechanisms confirm efficacy.
Results are consistent with the overall risk of all cause mortality based on cardiorespiratory fitness — Laukkanen show RR 0.55 [0.50-0.61] for the top vs. bottom tertiles.
Most studies analyze activity levels before infection, comparing regular/moderate exercise and lower/no exercise. Risk may increase with more extreme activity levels. Exercise may also be beneficial after infection. One study shows lower COVID-19 mortality with exercise during hospitalization2. Exercise during infection may increase the risk of transmission to others3, precautions should be taken to avoid transmission if potentially infected.
No treatment is 100% effective. Protocols combine safe and effective options with individual risk/benefit analysis and monitoring. All data and sources to reproduce this analysis are in the appendix.
6 other meta-analyses show significant improvements with exercise for mortality4-8, ICU admission4, hospitalization4,5,8,9, severity5-7, and cases5.
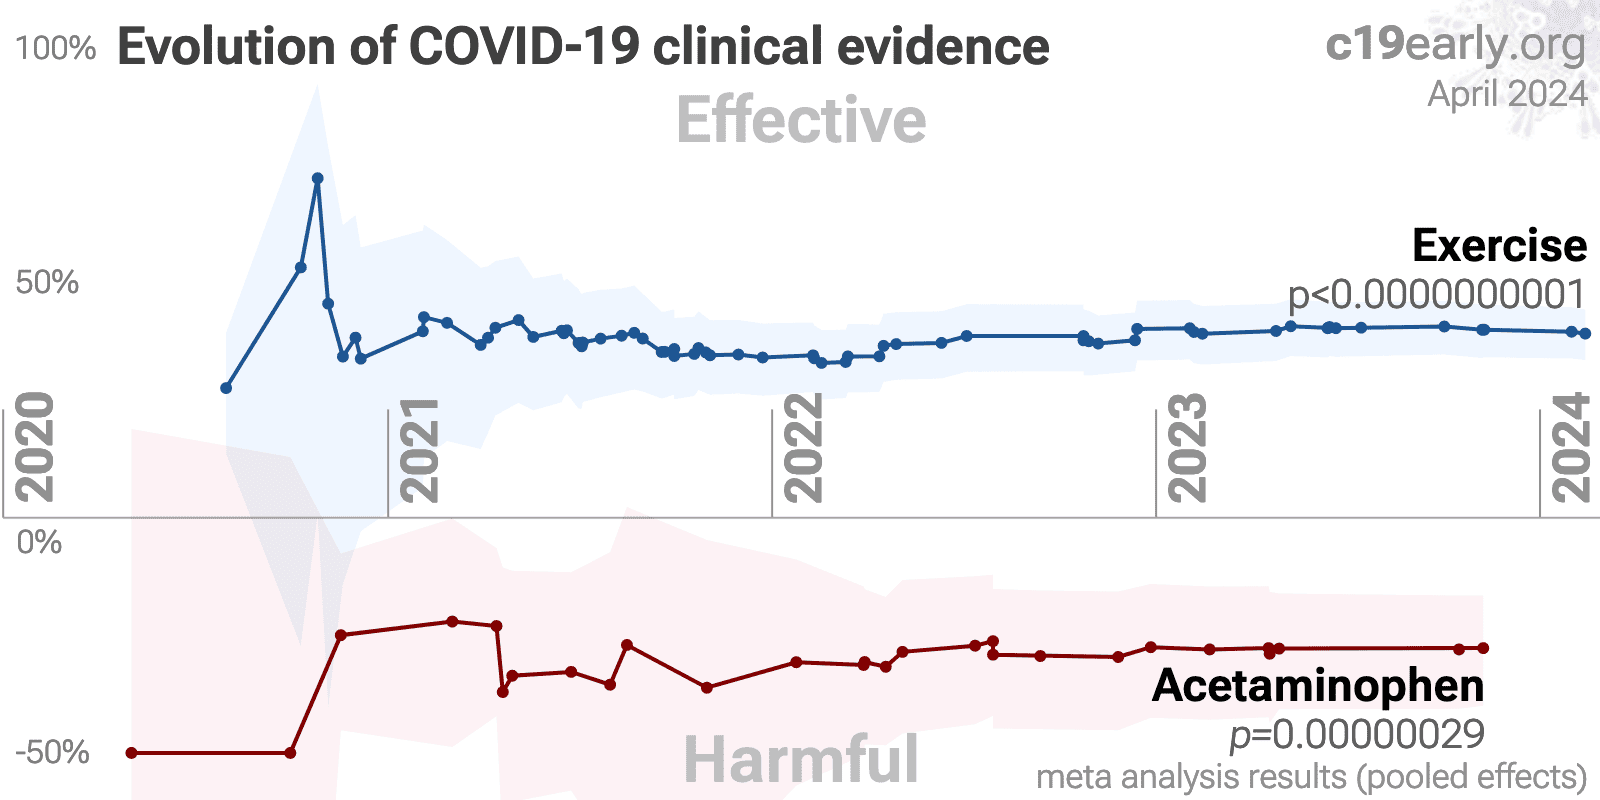
Evolution of COVID-19 clinical evidence Meta-analysis results over time Exercise p<0.0000000001 Acetaminophen p=0.00000021 2020 2021 2022 2023 2024 2025 2026 Lowerrisk Higherrisk c19early.org October 2026 50% 0% -50%

Exercise for COVID-19

Highlights
A
October 2026

Exercise COVID-19 studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Late treatment47%0.53 · 0.31–0.8816/20162/23847% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
Hamer28%0.72 · 0.61–0.87hosp.n/an/a Brawner74%0.26 · 0.11–0.58hosp.n/an/a Tret'yakov98%0.02 · 0.00–0.27severe case0/2753/266 Gao−105%2.05 · 1.39–3.02casescase-control study Ho35%0.65 · 0.48–0.89hosp.213/123,58859/14,887 Halabchi89%0.11 · 0.01–1.46death0/24979/4,445 Zhang26%0.74 · 0.48–1.14deathn/an/a Li81%0.19 · 0.05–0.74severe casen/an/aper SD increase Tavakol69%0.31 · 0.10–1.02severe case3/6419/124 Yates45%0.55 · 0.38–0.79death72/163,91262/30,119 Holt17%0.83 · 0.63–1.09cases15,227 (all patients)COVIDENCE UK Cho53%0.47 · 0.26–0.87deathcase-control study Sallis59%0.41 · 0.22–0.76death11/3,118170/6,984 Christensen63%0.37 · 0.16–0.85death543 (n)529 (n) Lobelo20%0.80 · 0.66–0.97hosp.2,121 (n)1,648 (n) Hegazy46%0.54 · 0.30–1.00m/s case24/827/13 Latorre-Román76%0.24 · 0.05–1.04hosp.n/an/a Marcus42%0.58 · 0.48–0.71symp. case240/10,627134/3,708 Yuan91%0.09 · 0.01–1.65death0/616/103 Brandenburg−6%1.06 · 0.23–4.79hosp.102 (n)39 (n) Bielik30%0.70 · 0.40–1.21mod. case775 (n)365 (n) af Geijerstam50%0.50 · 0.31–0.81death318,902 (n)336,271 (n) Lee74%0.26 · 0.07–0.99death2/11,07232/41,293 Maltagliati52%0.48 · 0.25–0.87hosp.n/an/a Baynouna AlKetbi98%0.01 · 0.00–0.44deathn/an/a Ahmadi30%0.70 · 0.54–0.89death160/232,613112/95,221 Nguyen20%0.80 · 0.72–0.88symp. case904/2,836483/1,111 Lin47%0.53 · 0.12–2.33casesn/an/a de Souza73%0.27 · 0.07–1.06ventilation3/6116/327 Mohsin19%0.81 · 0.66–0.99severe case86/258224/544 Ekblom-Bak48%0.52 · 0.30–0.92severe casen/an/a Lengelé74%0.26 · 0.07–0.80cases23/2294/12 Saadeh9%0.91 · 0.56–1.43symp. case362 (n)225 (n) Hamrouni29%0.71 · 0.55–0.92death138/106,006109/47,827 Huang47%0.53 · 0.23–1.22severe case7/7416/90 Hamdan16%0.84 · 0.49–1.39hosp.22/12837/172 Steenkamp42%0.58 · 0.50–0.68death29,469 (n)13,366 (n) Gilley−42%1.42 · 0.60–3.35cases172/1,9175/79 Almansour6%0.94 · 0.40–1.47cases35/7138/71 Beydoun43%0.57 · 0.32–1.01cases1,710 (n)448 (n) Salgado-Aranda83%0.17 · 0.05–0.56death4/22341/297 Paul38%0.62 · 0.30–1.20PASC1,811 (all patients)LONG COVID Kontopoulou66%0.34 · 0.24–0.47recov. time42 (n)24 (n) Malisoux63%0.37 · 0.14–0.98progression115 (n)108 (n) Antunes80%0.20 · 0.03–1.41ICU1/149/25 Tsuzuki56%0.44 · 0.36–0.52severe case3,340 (n)1,528 (n) Reis41%0.59 · 0.26–1.26hosp.9/24129/305 Pływaczewska-J..11%0.89 · 0.72–1.11m/s case490 (n)1,357 (n) Pitanga33%0.67 · 0.45–1.01cases1,469 (n)1,552 (n) Green42%0.58 · 0.53–0.63cases1,267/11,14416,198/101,931 Kapusta71%0.29 · 0.20–0.43severe case181 (n)387 (n) Young74%0.26 · 0.20–0.33death11,279 (n)29,099 (n) Wang11%0.89 · 0.75–1.06PASC274/691283/594LONG COVID Park26%0.74 · 0.53–1.04deathn/an/a Sanchez54%0.46 · 0.38–0.55symp. casen/an/a Cardoso73%0.27 · 0.17–0.45severe casecase-control study Feter26%0.74 · 0.58–0.95PASC52 (n)95 (n)LONG COVID Sutkowska62%0.38 · 0.08–1.72death71 (n)60 (n) Frish53%0.47 · 0.23–0.95cases212 (n)1,202 (n) Schmidt31%0.69 · 0.50–0.94cases956 (n)2,705 (n)CoCo-Fakt Šebić89%0.11 · 0.01–1.90oxygen0/534/47 Hegazy54%0.46 · 0.27–0.77m/s case15/5015/23 Akbar7%0.93 · 0.79–1.10cases3,333 (n)3,333 (n) Pavlidou42%0.58 · 0.51–0.68cases902 (n)4,295 (n) Rocha20%0.80 · 0.63–0.99PASC388 (n)2,096 (n)LONG COVID Wang30%0.70 · 0.61–0.80death57,930 (n)10,966 (n) Muñoz-Vergara27%0.73 · 0.60–0.90hosp.332/42,159203/12,405
Prophylaxis39%0.61 · 0.56–0.674,017/1146K18,437/774K39% lower risk
Tau² = 0.07, I² = 80.6%, p < 0.0001
All studies39%0.61 · 0.56–0.674,033/1147K18,499/774K39% lower risk
Tau² = 0.07, I² = 80.3%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
B
Loading..
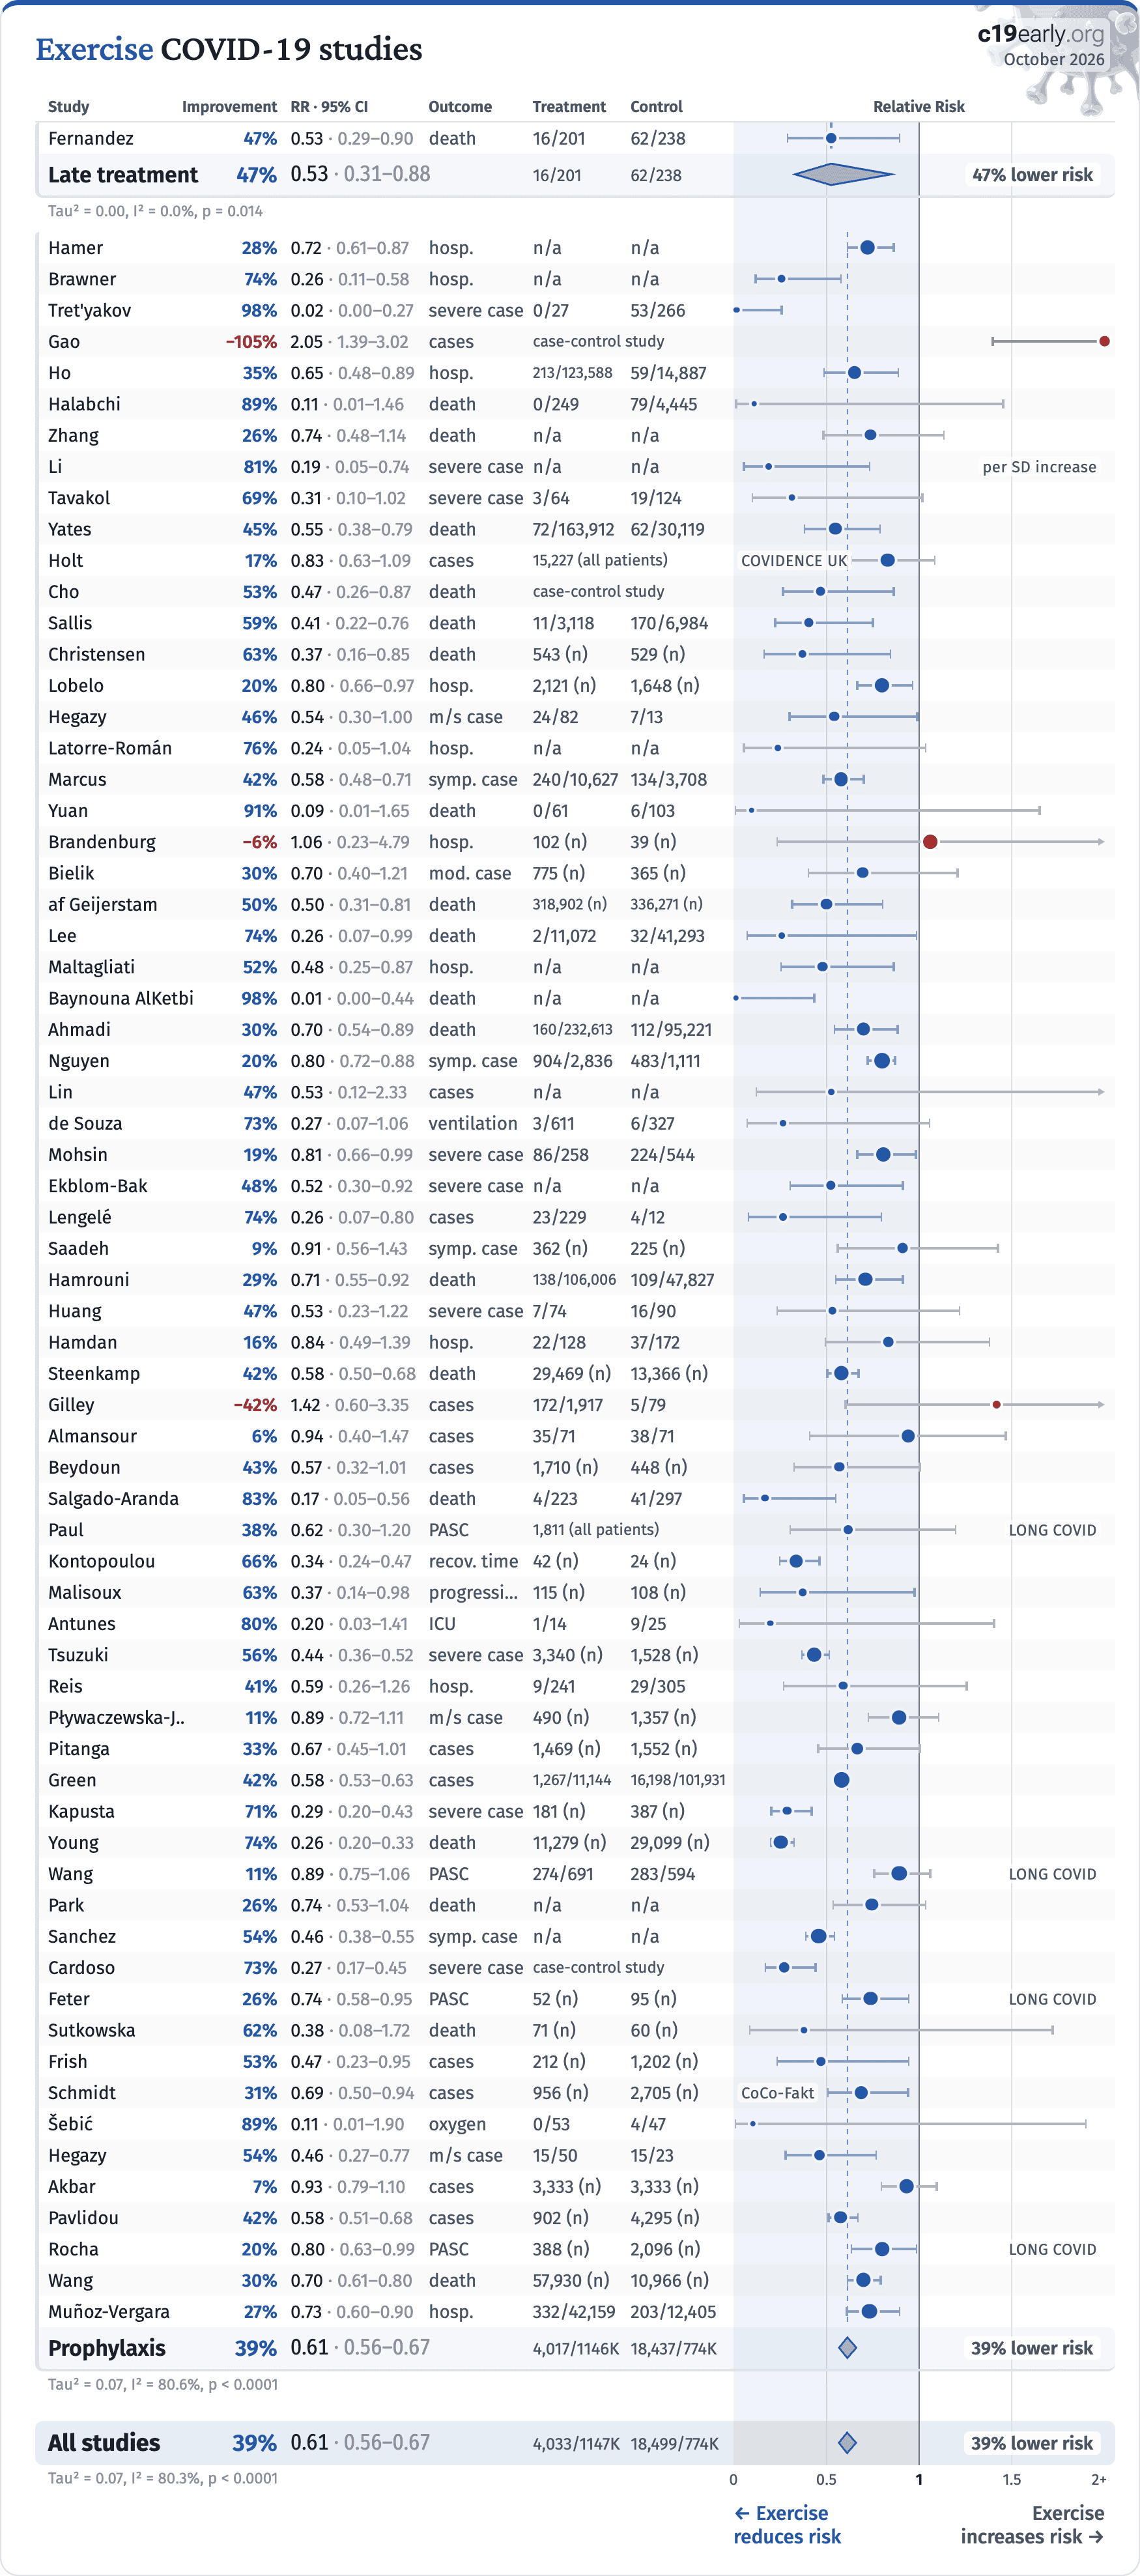
Fig. 1. A. Random-effects meta-analysis. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix. B. Timeline of results in exercise studies. The marked dates indicate the time when efficacy was known with a statistically significant improvement of ≥10% from ≥3 studies for pooled outcomes and one or more specific outcome. Efficacy based on specific outcomes was delayed by 0.8 months, compared to using pooled outcomes.
Exercise can improve immune system function, reduce chronic inflammation, improve cardiovascular health, improve comorbidities, enhance lung function, reduce stress, and increase nitric oxide. Prolonged high-intensity workouts may temporarily suppress the immune system.
Insufficient physical activity is a risk factor for many diseases, is common around the world, has increasing prevalence over time, and has over two times greater prevalence in high-income countries10. For upper respiratory tract infections, research shows lower risk for moderate activity vs. a sedentary lifestyle, however risk may increase with more extreme activity levels11.
Efficacy with exercise has been shown for pneumonia12.
We analyze all significant studies reporting COVID-19 outcomes as a function of physical activity levels. Search methods, inclusion criteria, effect extraction criteria (more serious outcomes have priority), all individual study data, PRISMA answers, and statistical methods are detailed in Appendix 1. We present random-effects meta-analysis results for all studies, studies within each treatment stage, individual outcomes, peer-reviewed studies, and higher quality studies.
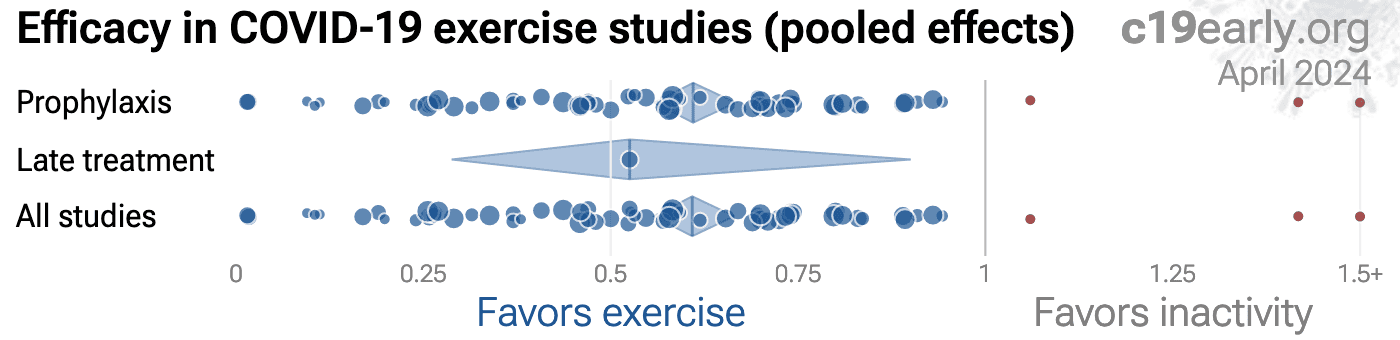
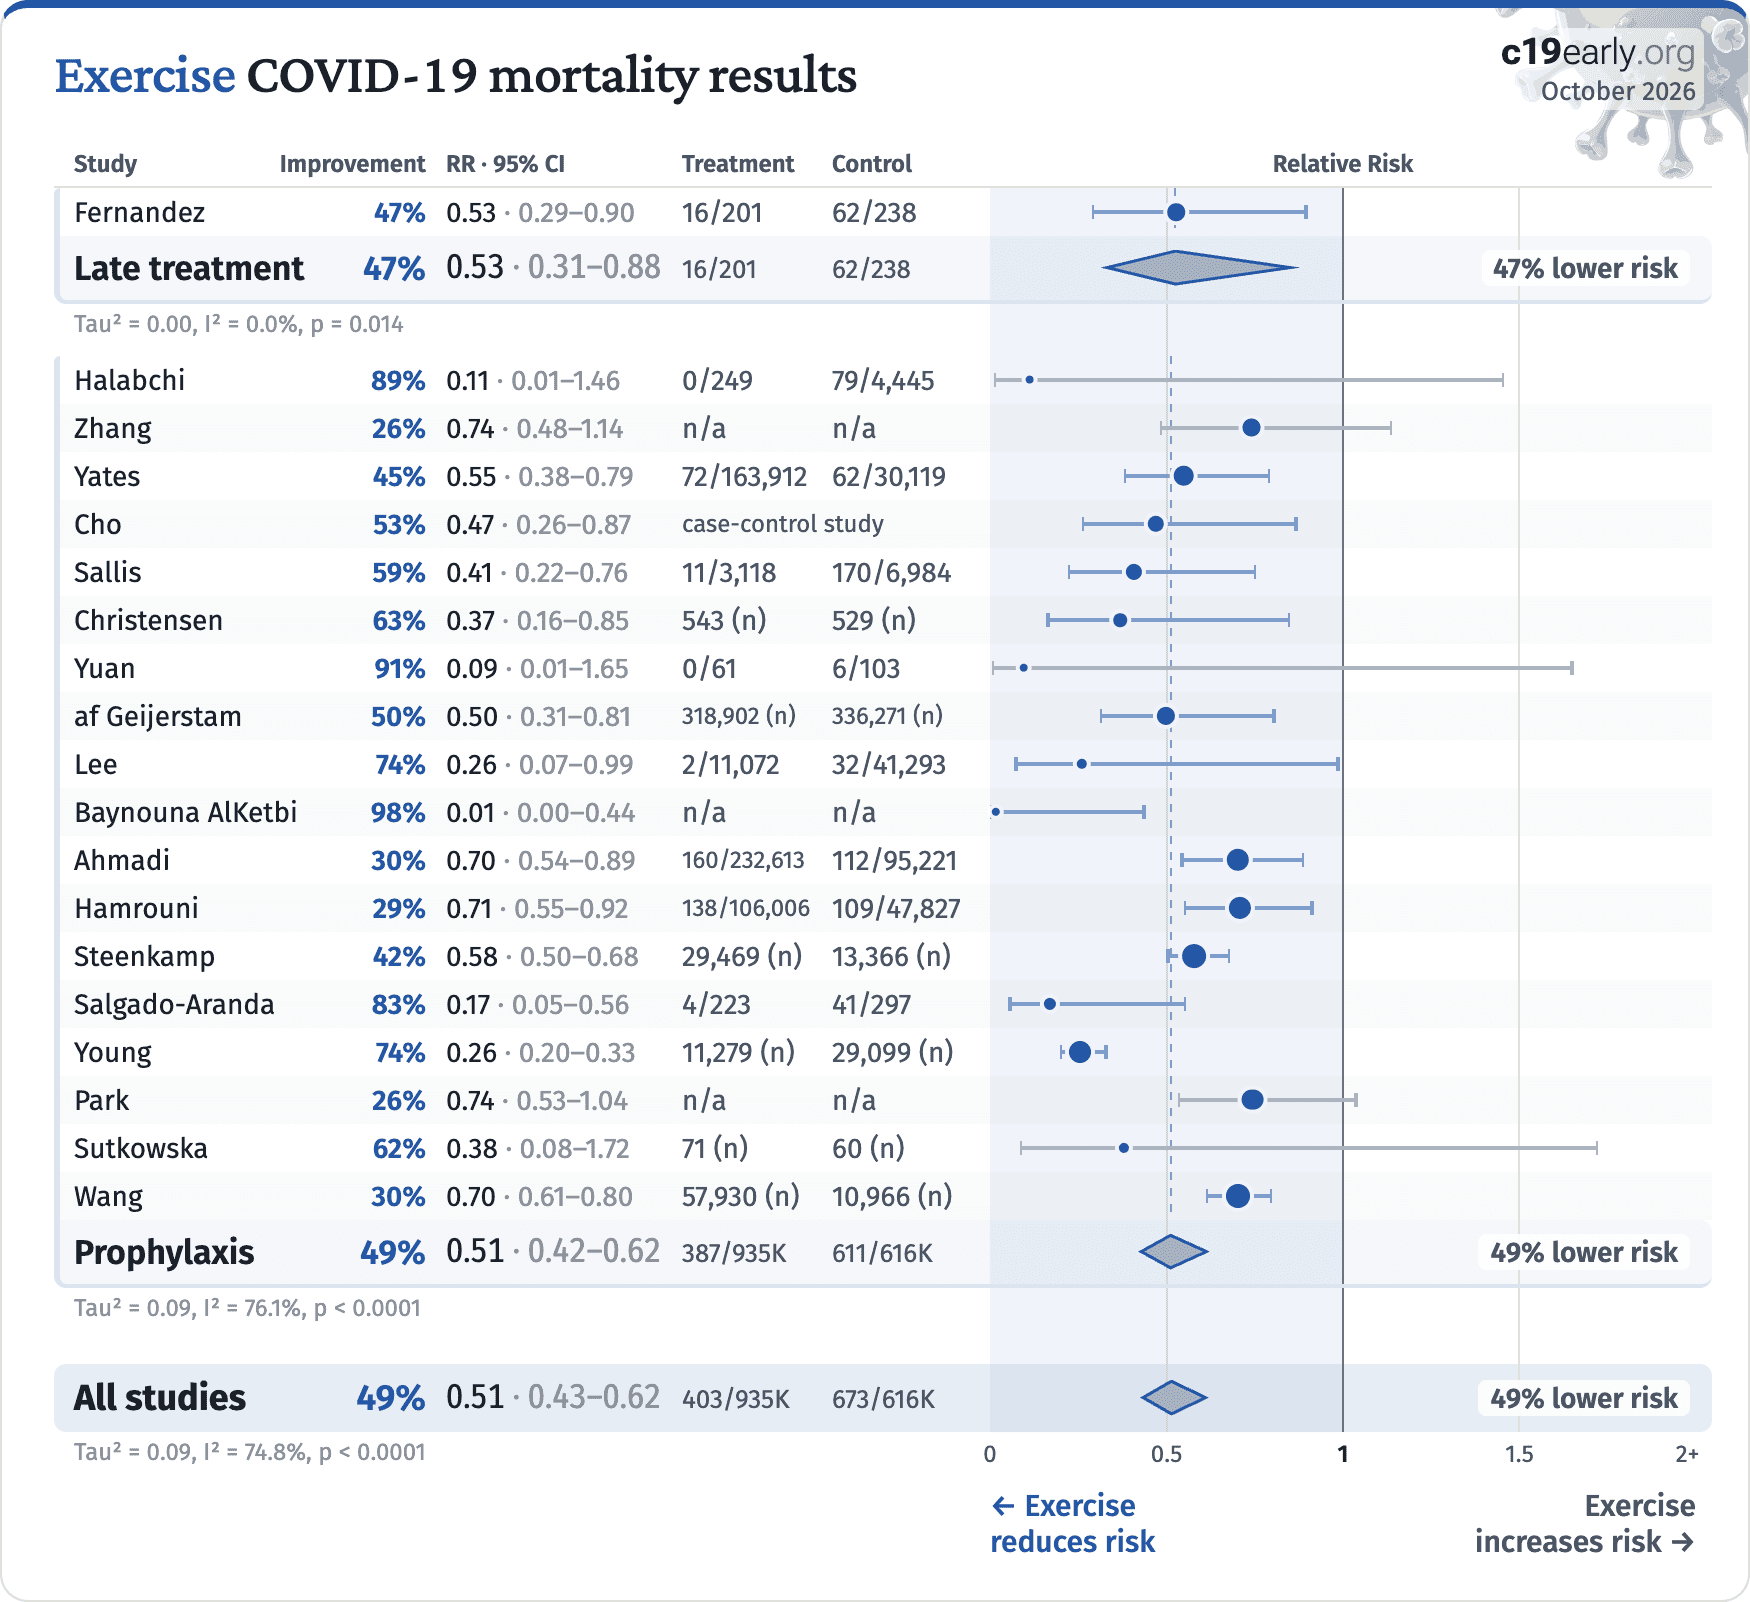
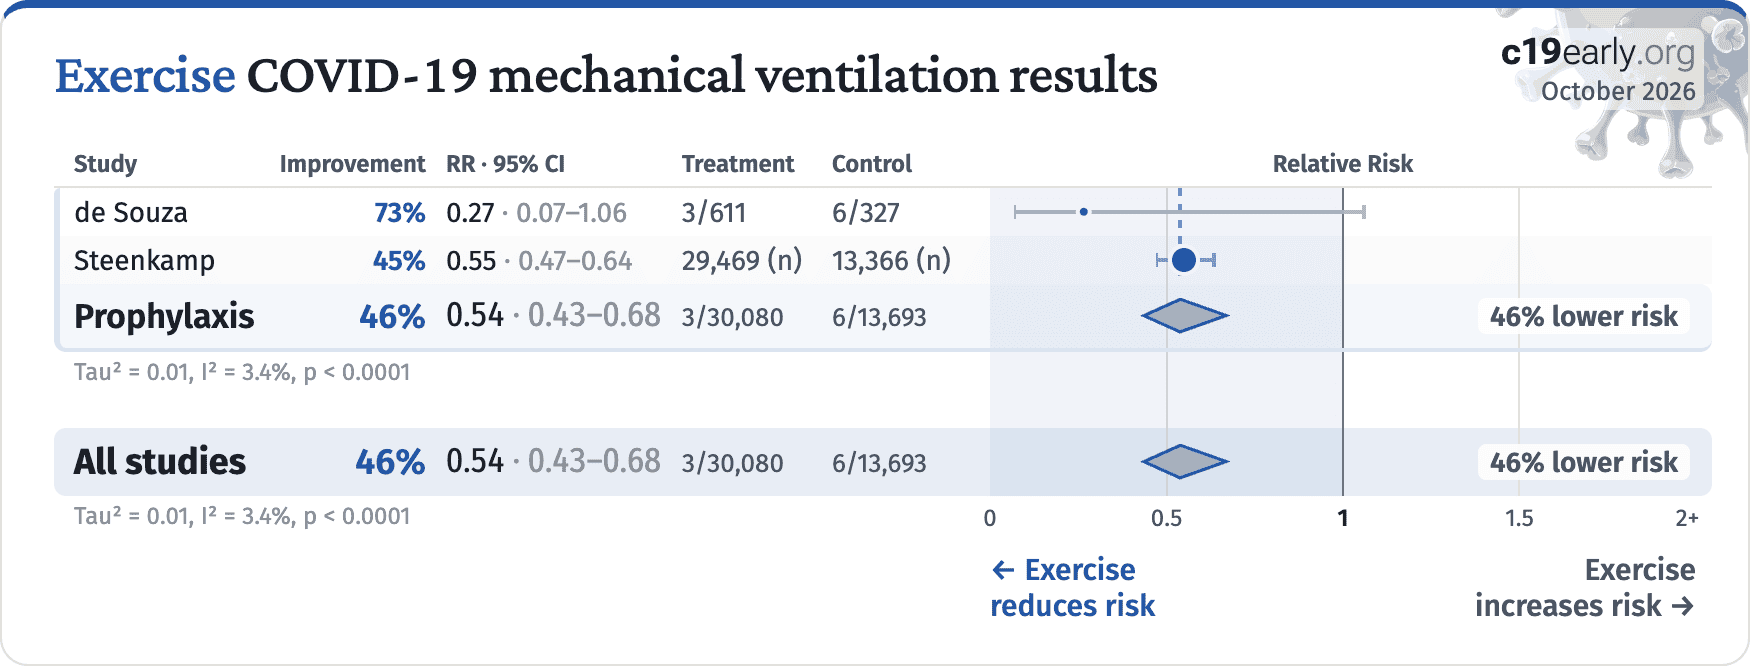
Table 1 summarizes the results for all studies, for peer-reviewed studies, after exclusions, and for specific outcomes. Fig. 2 plots individual results by treatment stage. Fig. 3, 4, 5, 6, 7, 8, 9, 10, 11, and 12 show forest plots for random-effects meta-analysis of all studies with pooled effects, mortality results, ventilation, ICU admission, hospitalization, progression, recovery, cases, peer reviewed studies, and long COVID.
Table 1. Random-effects meta-analysis for all studies, for peer-reviewed studies, after exclusions, and for specific outcomes. Results show the relative risk with increased activity levels and the 95% confidence interval. * p<0.05  **** p<0.0001.
Relative Risk Studies Patients
All studies0.61 [0.56‑0.67]****681M
After exclusions0.62 [0.57‑0.68]****631M
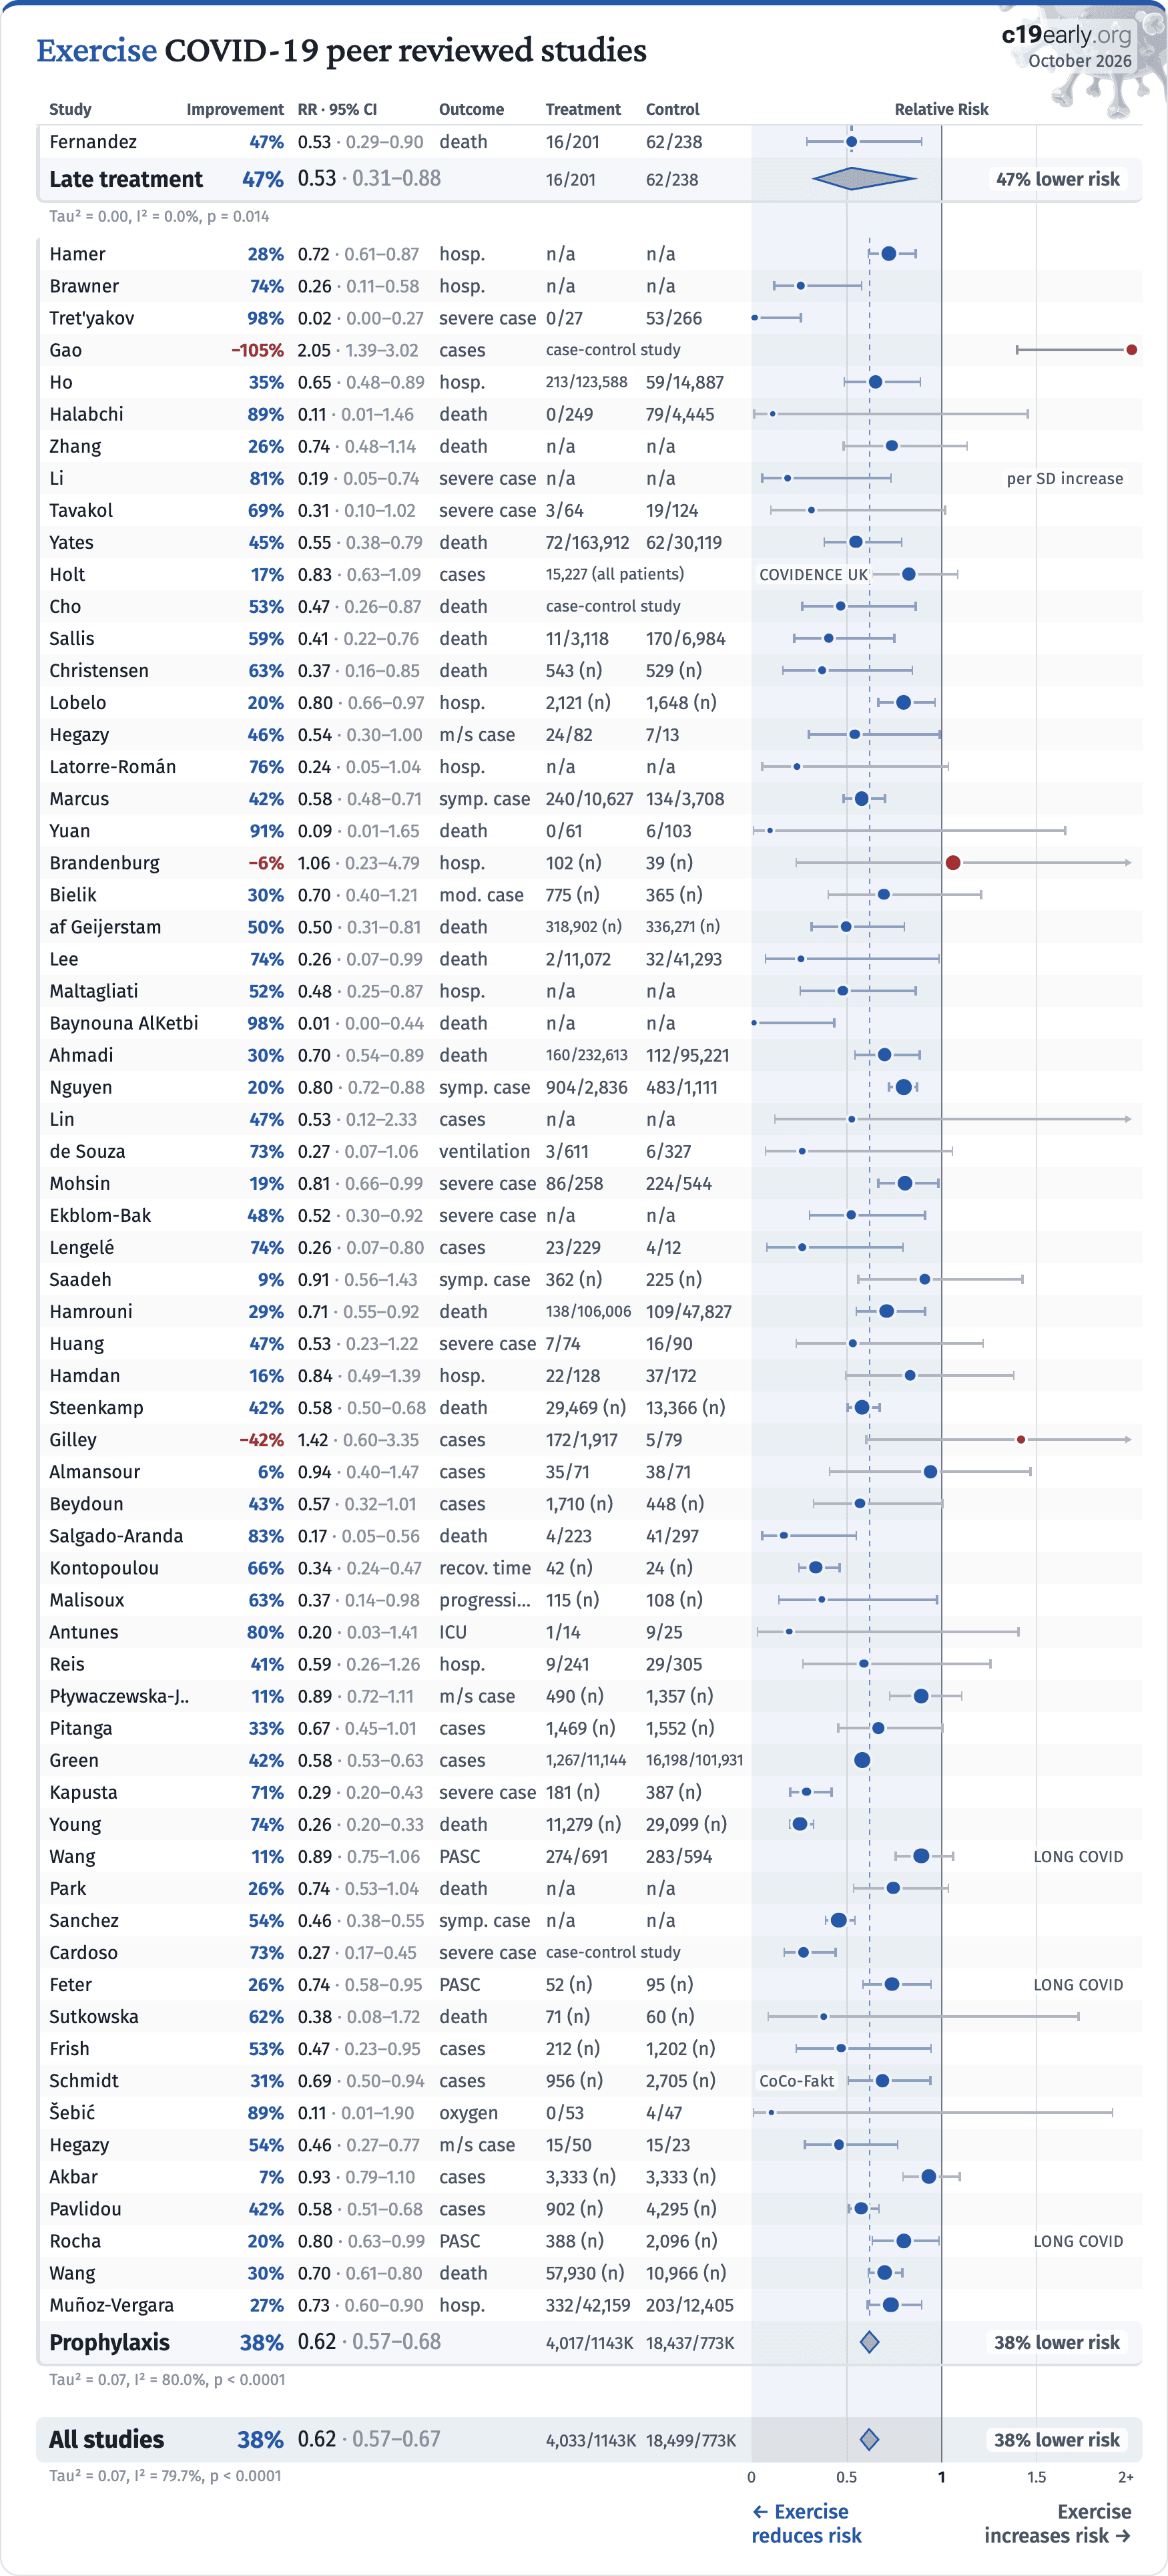
Peer-reviewedPeer-reviewed0.62 [0.57‑0.67]****661M
Mortality0.51 [0.43‑0.62]****191M
VentilationVent.0.54 [0.43‑0.68]****240K
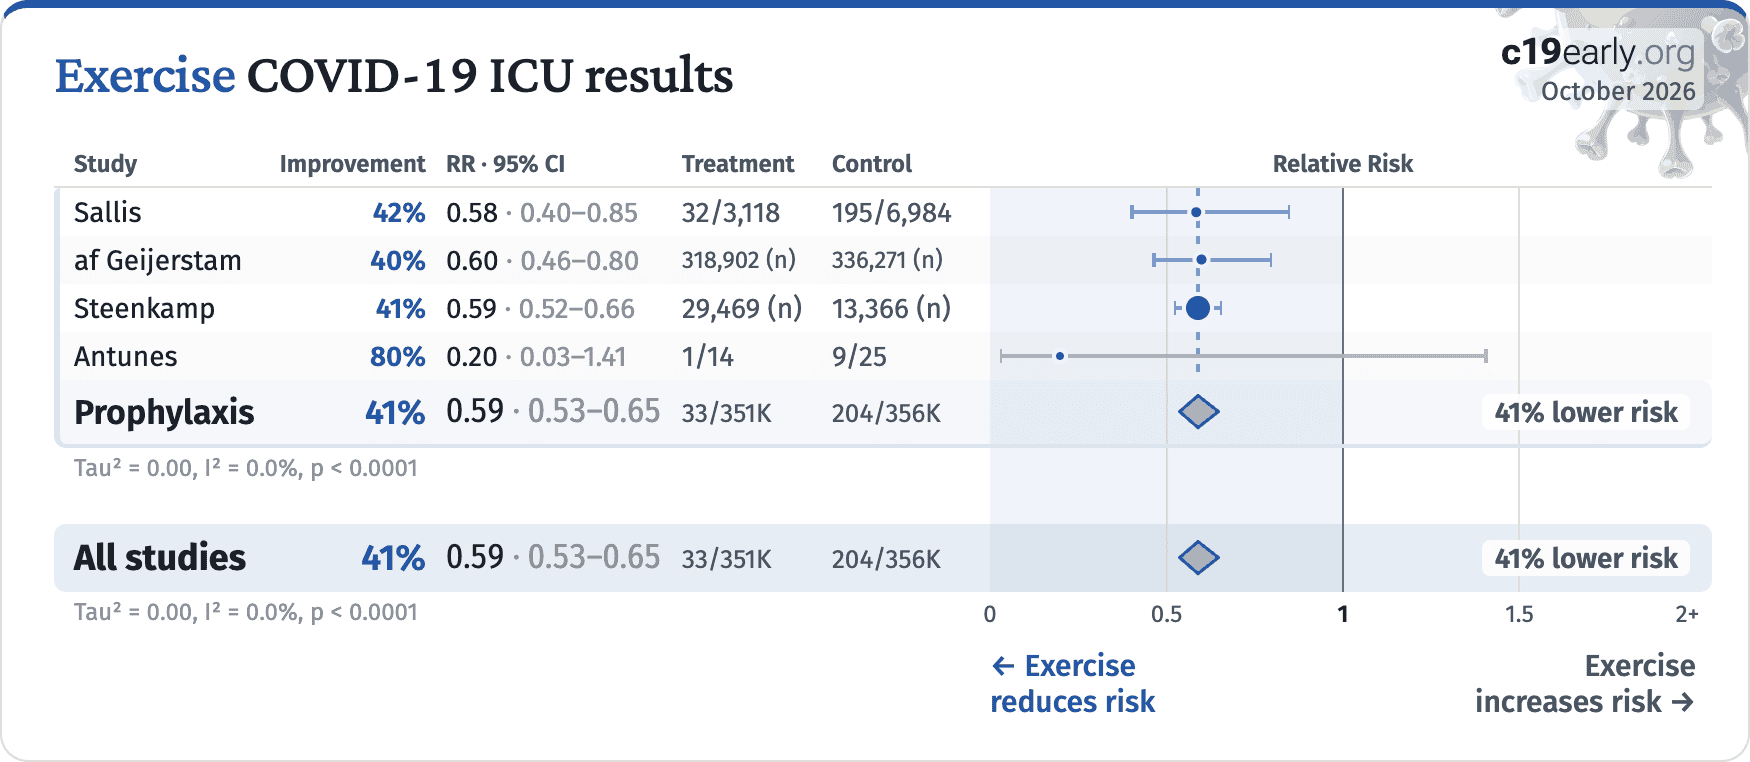
ICU admissionICU0.59 [0.53‑0.65]****4700K
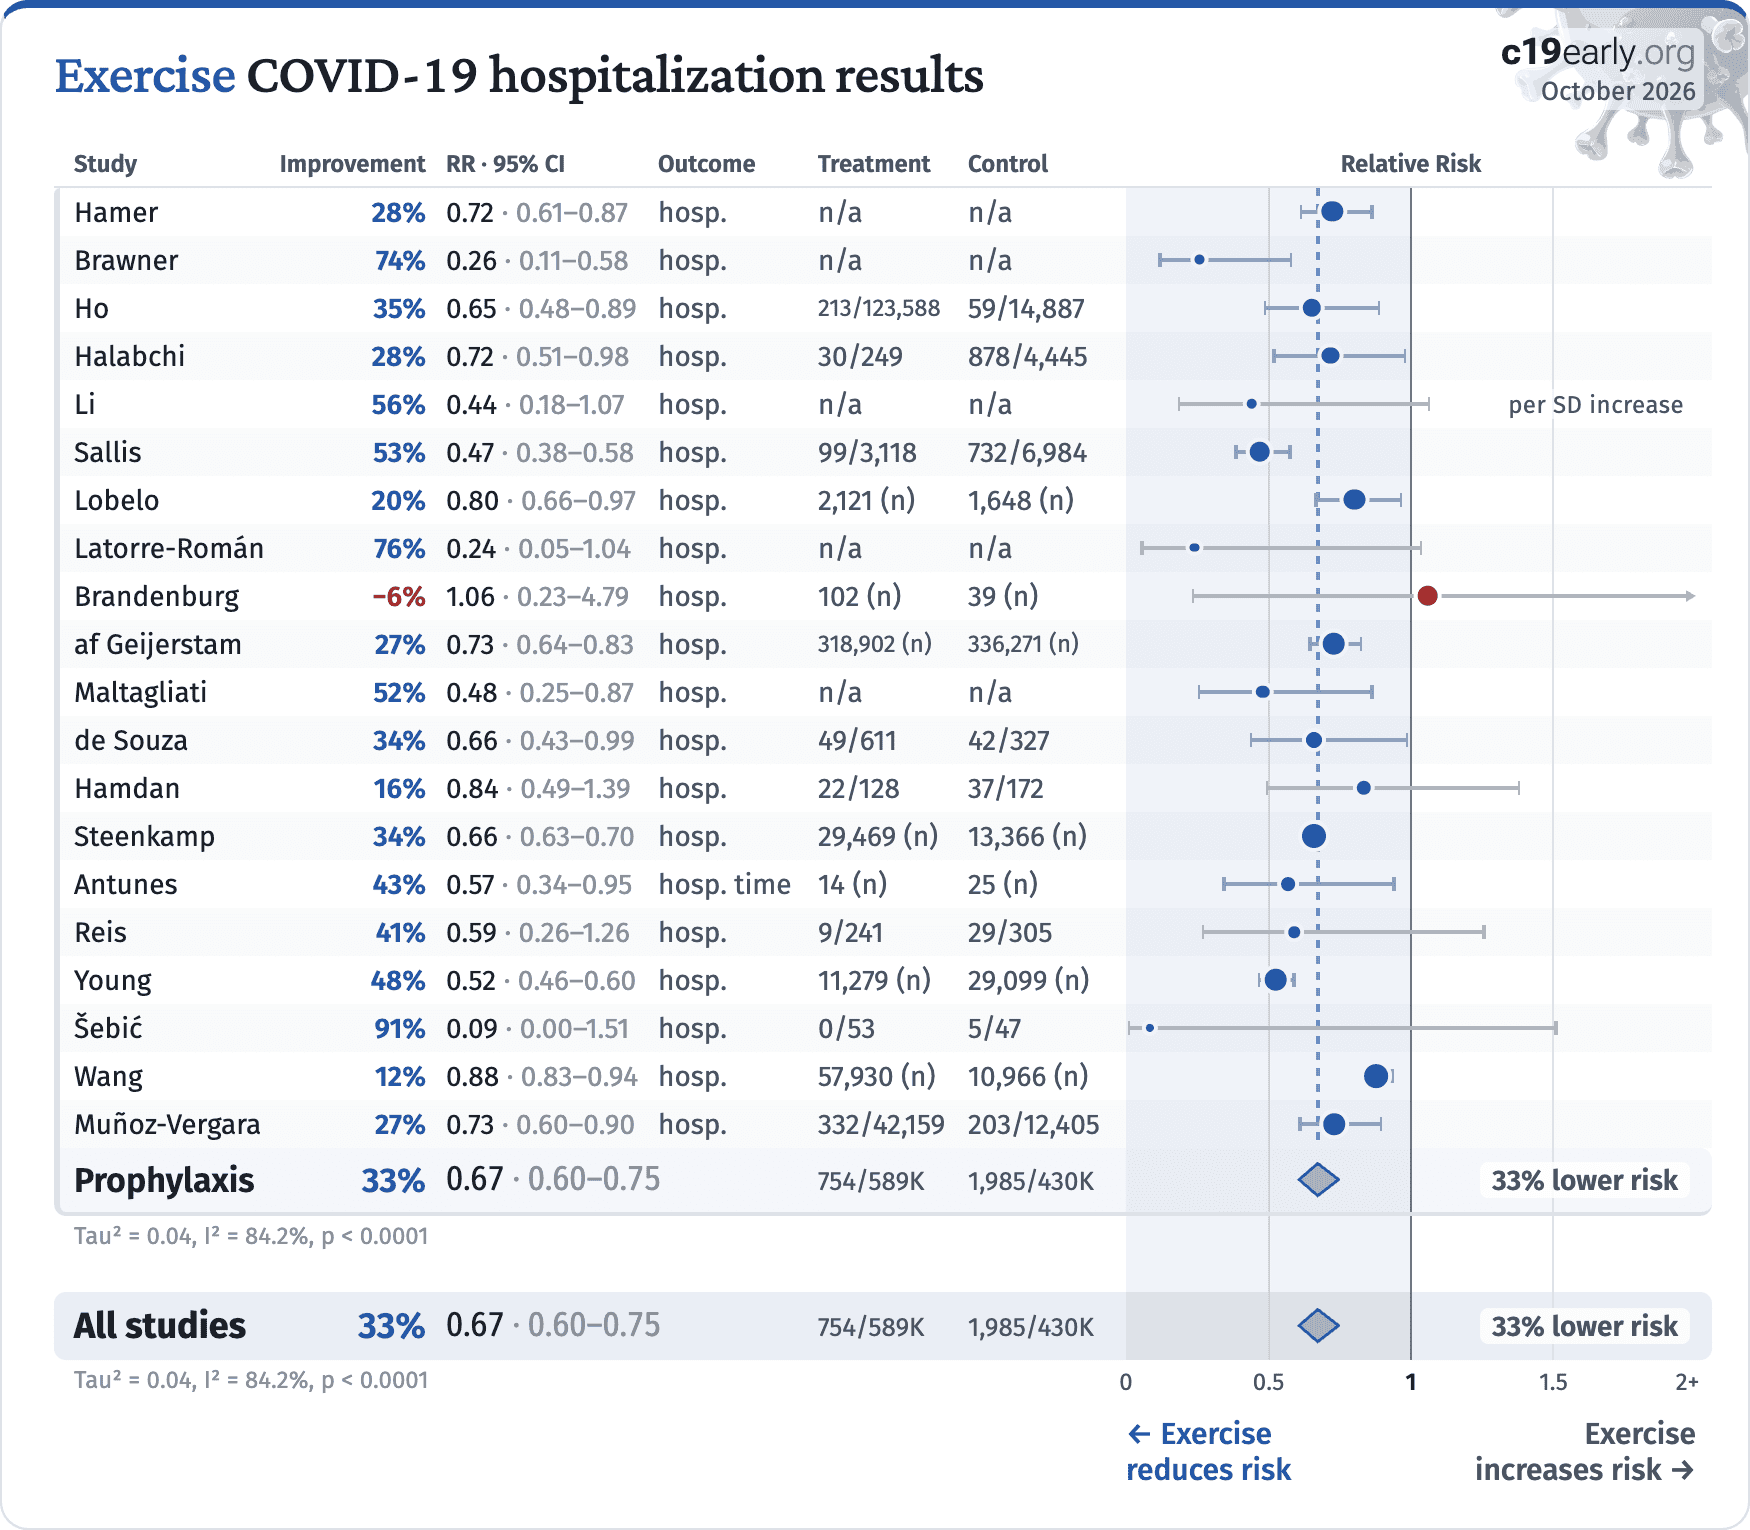
HospitalizationHosp.0.67 [0.60‑0.75]****201M
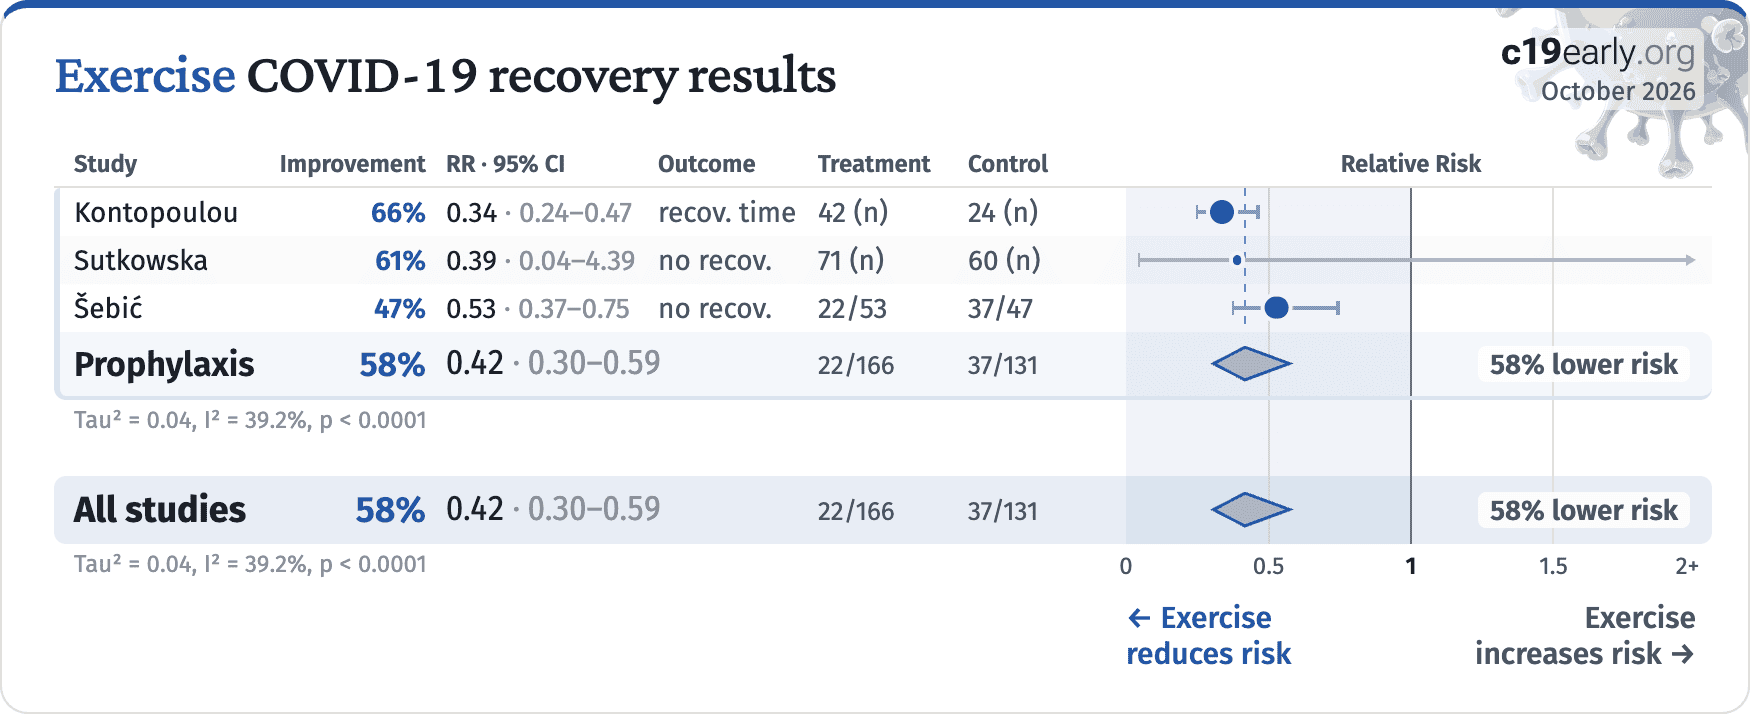
Recovery0.42 [0.30‑0.59]****3297
Cases0.77 [0.69‑0.86]****25280K
Loading..
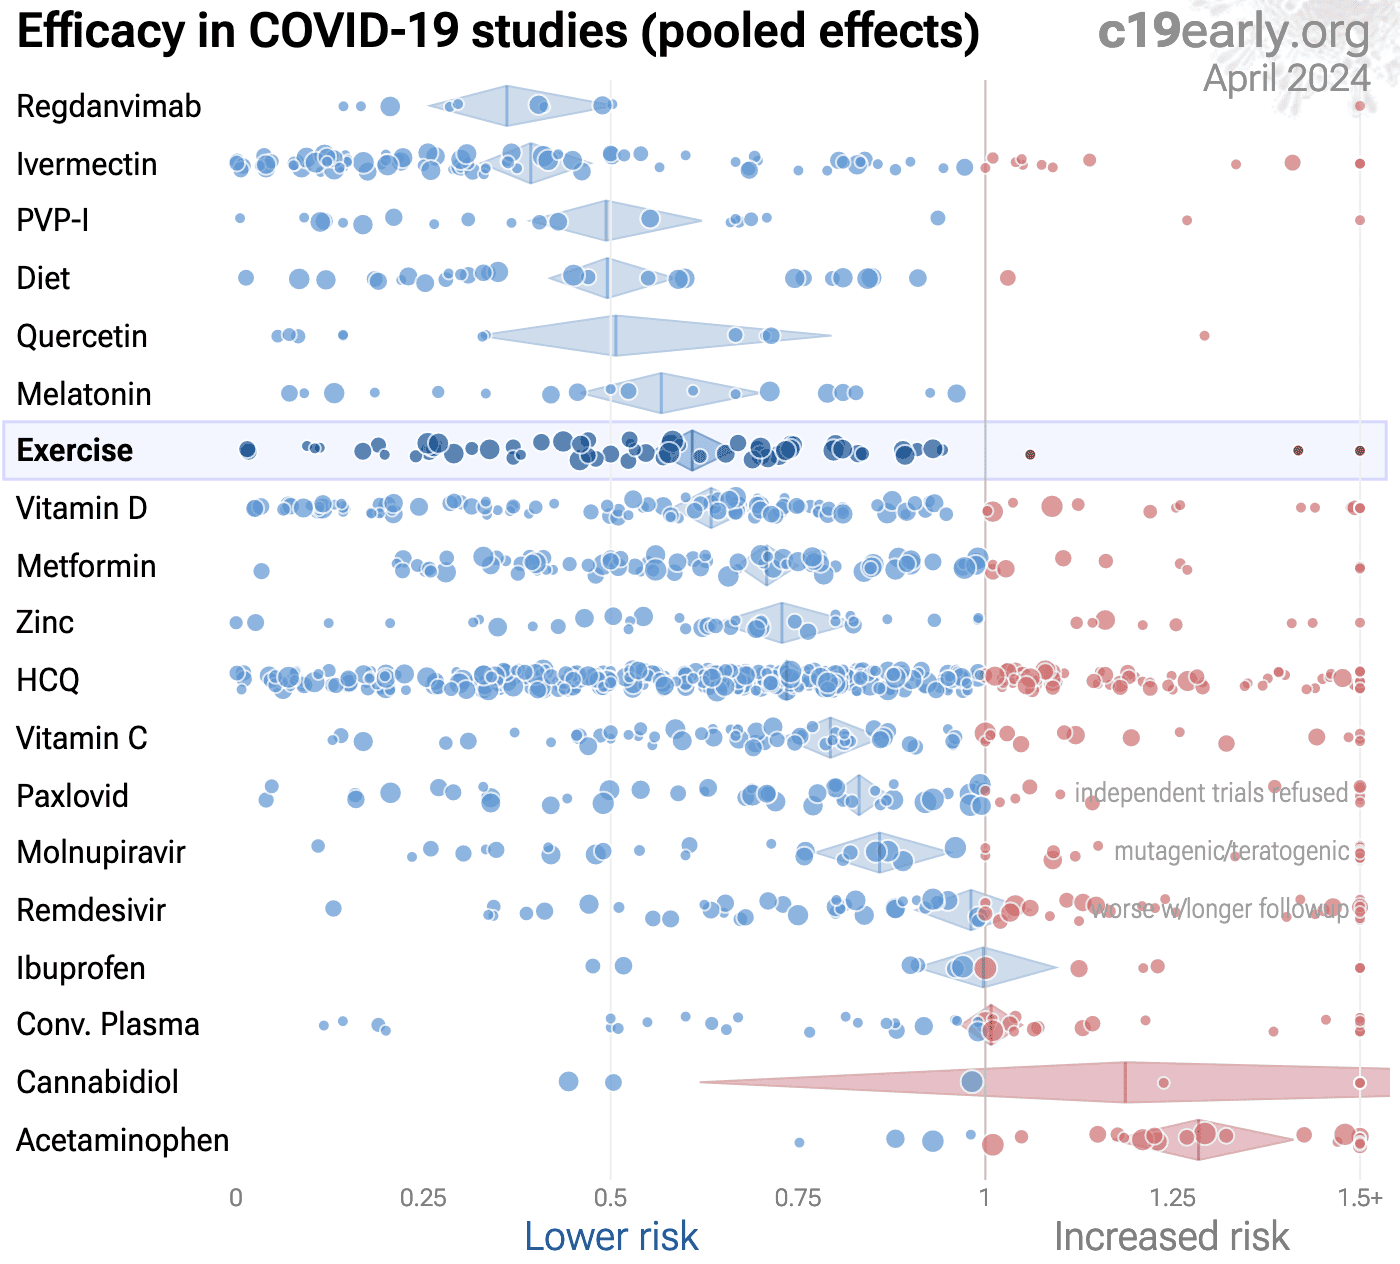
Fig. 2. Scatter plot showing the most serious outcome in all studies, and for studies within each stage. Diamonds shows the results of random-effects meta-analysis.
October 2026

Exercise COVID-19 studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Late treatment47%0.53 · 0.31–0.8816/20162/23847% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
Hamer28%0.72 · 0.61–0.87hosp.n/an/a Brawner74%0.26 · 0.11–0.58hosp.n/an/a Tret'yakov98%0.02 · 0.00–0.27severe case0/2753/266 Gao−105%2.05 · 1.39–3.02casescase-control study Ho35%0.65 · 0.48–0.89hosp.213/123,58859/14,887 Halabchi89%0.11 · 0.01–1.46death0/24979/4,445 Zhang26%0.74 · 0.48–1.14deathn/an/a Li81%0.19 · 0.05–0.74severe casen/an/aper SD increase Tavakol69%0.31 · 0.10–1.02severe case3/6419/124 Yates45%0.55 · 0.38–0.79death72/163,91262/30,119 Holt17%0.83 · 0.63–1.09cases15,227 (all patients)COVIDENCE UK Cho53%0.47 · 0.26–0.87deathcase-control study Sallis59%0.41 · 0.22–0.76death11/3,118170/6,984 Christensen63%0.37 · 0.16–0.85death543 (n)529 (n) Lobelo20%0.80 · 0.66–0.97hosp.2,121 (n)1,648 (n) Hegazy46%0.54 · 0.30–1.00m/s case24/827/13 Latorre-Román76%0.24 · 0.05–1.04hosp.n/an/a Marcus42%0.58 · 0.48–0.71symp. case240/10,627134/3,708 Yuan91%0.09 · 0.01–1.65death0/616/103 Brandenburg−6%1.06 · 0.23–4.79hosp.102 (n)39 (n) Bielik30%0.70 · 0.40–1.21mod. case775 (n)365 (n) af Geijerstam50%0.50 · 0.31–0.81death318,902 (n)336,271 (n) Lee74%0.26 · 0.07–0.99death2/11,07232/41,293 Maltagliati52%0.48 · 0.25–0.87hosp.n/an/a Baynouna AlKetbi98%0.01 · 0.00–0.44deathn/an/a Ahmadi30%0.70 · 0.54–0.89death160/232,613112/95,221 Nguyen20%0.80 · 0.72–0.88symp. case904/2,836483/1,111 Lin47%0.53 · 0.12–2.33casesn/an/a de Souza73%0.27 · 0.07–1.06ventilation3/6116/327 Mohsin19%0.81 · 0.66–0.99severe case86/258224/544 Ekblom-Bak48%0.52 · 0.30–0.92severe casen/an/a Lengelé74%0.26 · 0.07–0.80cases23/2294/12 Saadeh9%0.91 · 0.56–1.43symp. case362 (n)225 (n) Hamrouni29%0.71 · 0.55–0.92death138/106,006109/47,827 Huang47%0.53 · 0.23–1.22severe case7/7416/90 Hamdan16%0.84 · 0.49–1.39hosp.22/12837/172 Steenkamp42%0.58 · 0.50–0.68death29,469 (n)13,366 (n) Gilley−42%1.42 · 0.60–3.35cases172/1,9175/79 Almansour6%0.94 · 0.40–1.47cases35/7138/71 Beydoun43%0.57 · 0.32–1.01cases1,710 (n)448 (n) Salgado-Aranda83%0.17 · 0.05–0.56death4/22341/297 Paul38%0.62 · 0.30–1.20PASC1,811 (all patients)LONG COVID Kontopoulou66%0.34 · 0.24–0.47recov. time42 (n)24 (n) Malisoux63%0.37 · 0.14–0.98progression115 (n)108 (n) Antunes80%0.20 · 0.03–1.41ICU1/149/25 Tsuzuki56%0.44 · 0.36–0.52severe case3,340 (n)1,528 (n) Reis41%0.59 · 0.26–1.26hosp.9/24129/305 Pływaczewska-J..11%0.89 · 0.72–1.11m/s case490 (n)1,357 (n) Pitanga33%0.67 · 0.45–1.01cases1,469 (n)1,552 (n) Green42%0.58 · 0.53–0.63cases1,267/11,14416,198/101,931 Kapusta71%0.29 · 0.20–0.43severe case181 (n)387 (n) Young74%0.26 · 0.20–0.33death11,279 (n)29,099 (n) Wang11%0.89 · 0.75–1.06PASC274/691283/594LONG COVID Park26%0.74 · 0.53–1.04deathn/an/a Sanchez54%0.46 · 0.38–0.55symp. casen/an/a Cardoso73%0.27 · 0.17–0.45severe casecase-control study Feter26%0.74 · 0.58–0.95PASC52 (n)95 (n)LONG COVID Sutkowska62%0.38 · 0.08–1.72death71 (n)60 (n) Frish53%0.47 · 0.23–0.95cases212 (n)1,202 (n) Schmidt31%0.69 · 0.50–0.94cases956 (n)2,705 (n)CoCo-Fakt Šebić89%0.11 · 0.01–1.90oxygen0/534/47 Hegazy54%0.46 · 0.27–0.77m/s case15/5015/23 Akbar7%0.93 · 0.79–1.10cases3,333 (n)3,333 (n) Pavlidou42%0.58 · 0.51–0.68cases902 (n)4,295 (n) Rocha20%0.80 · 0.63–0.99PASC388 (n)2,096 (n)LONG COVID Wang30%0.70 · 0.61–0.80death57,930 (n)10,966 (n) Muñoz-Vergara27%0.73 · 0.60–0.90hosp.332/42,159203/12,405
Prophylaxis39%0.61 · 0.56–0.674,017/1146K18,437/774K39% lower risk
Tau² = 0.07, I² = 80.6%, p < 0.0001
All studies39%0.61 · 0.56–0.674,033/1147K18,499/774K39% lower risk
Tau² = 0.07, I² = 80.3%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 3. Random-effects meta-analysis for all studies. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
Fig. 4. Random-effects meta-analysis for mortality results.
October 2026

Exercise COVID-19 mechanical ventilation results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Prophylaxis46%0.54 · 0.43–0.683/30,0806/13,69346% lower risk
Tau² = 0.01, I² = 3.4%, p < 0.0001
All studies46%0.54 · 0.43–0.683/30,0806/13,69346% lower risk
Tau² = 0.01, I² = 3.4%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 5. Random-effects meta-analysis for ventilation.
October 2026

Exercise COVID-19 ICU results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Prophylaxis41%0.59 · 0.53–0.6533/351K204/356K41% lower risk
Tau² = 0.00, I² = 0.0%, p < 0.0001
All studies41%0.59 · 0.53–0.6533/351K204/356K41% lower risk
Tau² = 0.00, I² = 0.0%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 6. Random-effects meta-analysis for ICU admission.
Fig. 7. Random-effects meta-analysis for hospitalization.
October 2026

Exercise COVID-19 progression results

StudyImprovementRR · 95% CITreatmentControlRelative Risk
Prophylaxis75%0.25 · 0.11–0.554/16822/15575% lower risk
Tau² = 0.09, I² = 27.2%, p = 0.00076
All studies75%0.25 · 0.11–0.554/16822/15575% lower risk
Tau² = 0.09, I² = 27.2%, p = 0.0007600.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
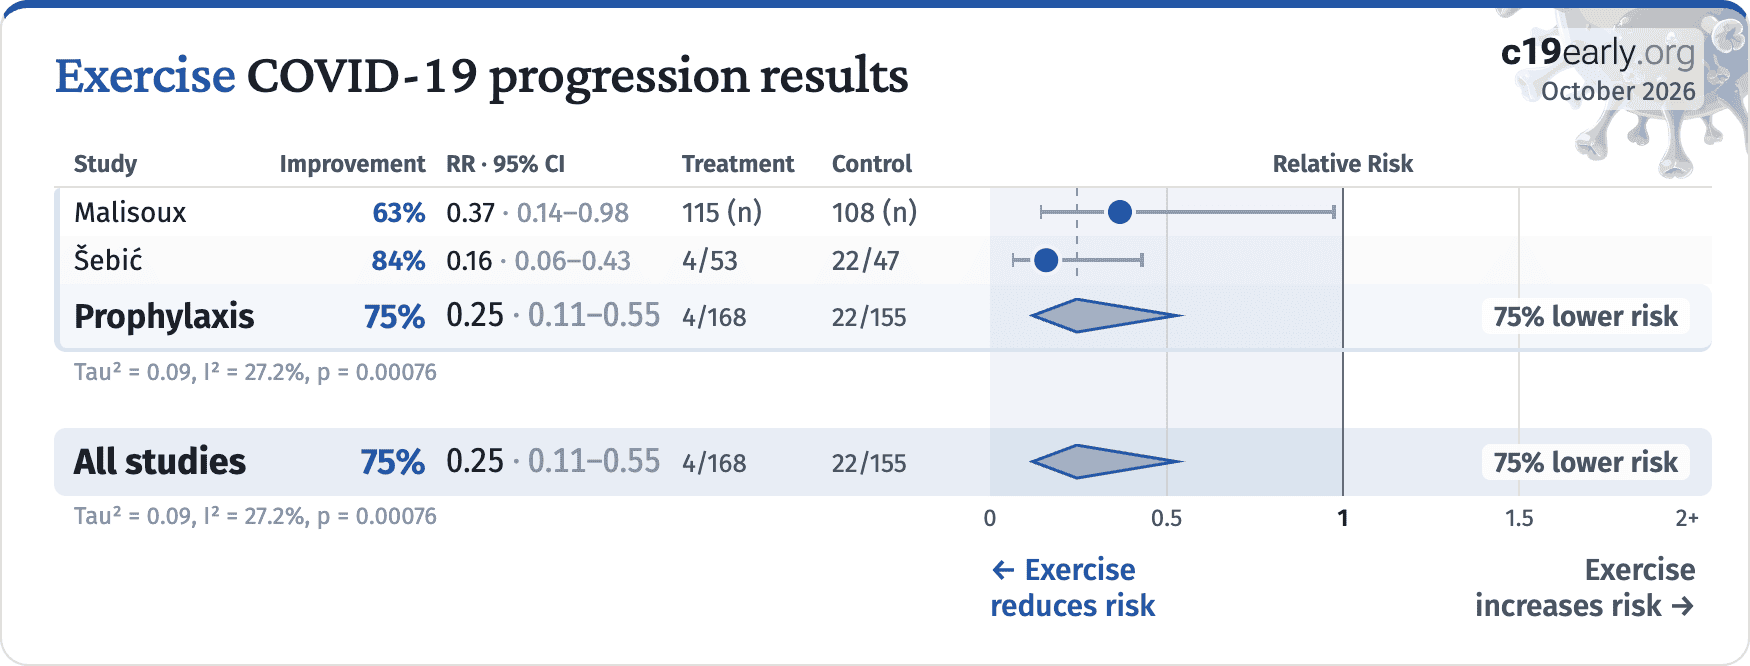
Fig. 8. Random-effects meta-analysis for progression.
October 2026

Exercise COVID-19 recovery results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Prophylaxis58%0.42 · 0.30–0.5922/16637/13158% lower risk
Tau² = 0.04, I² = 39.2%, p < 0.0001
All studies58%0.42 · 0.30–0.5922/16637/13158% lower risk
Tau² = 0.04, I² = 39.2%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 9. Random-effects meta-analysis for recovery.
October 2026

Exercise COVID-19 case results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
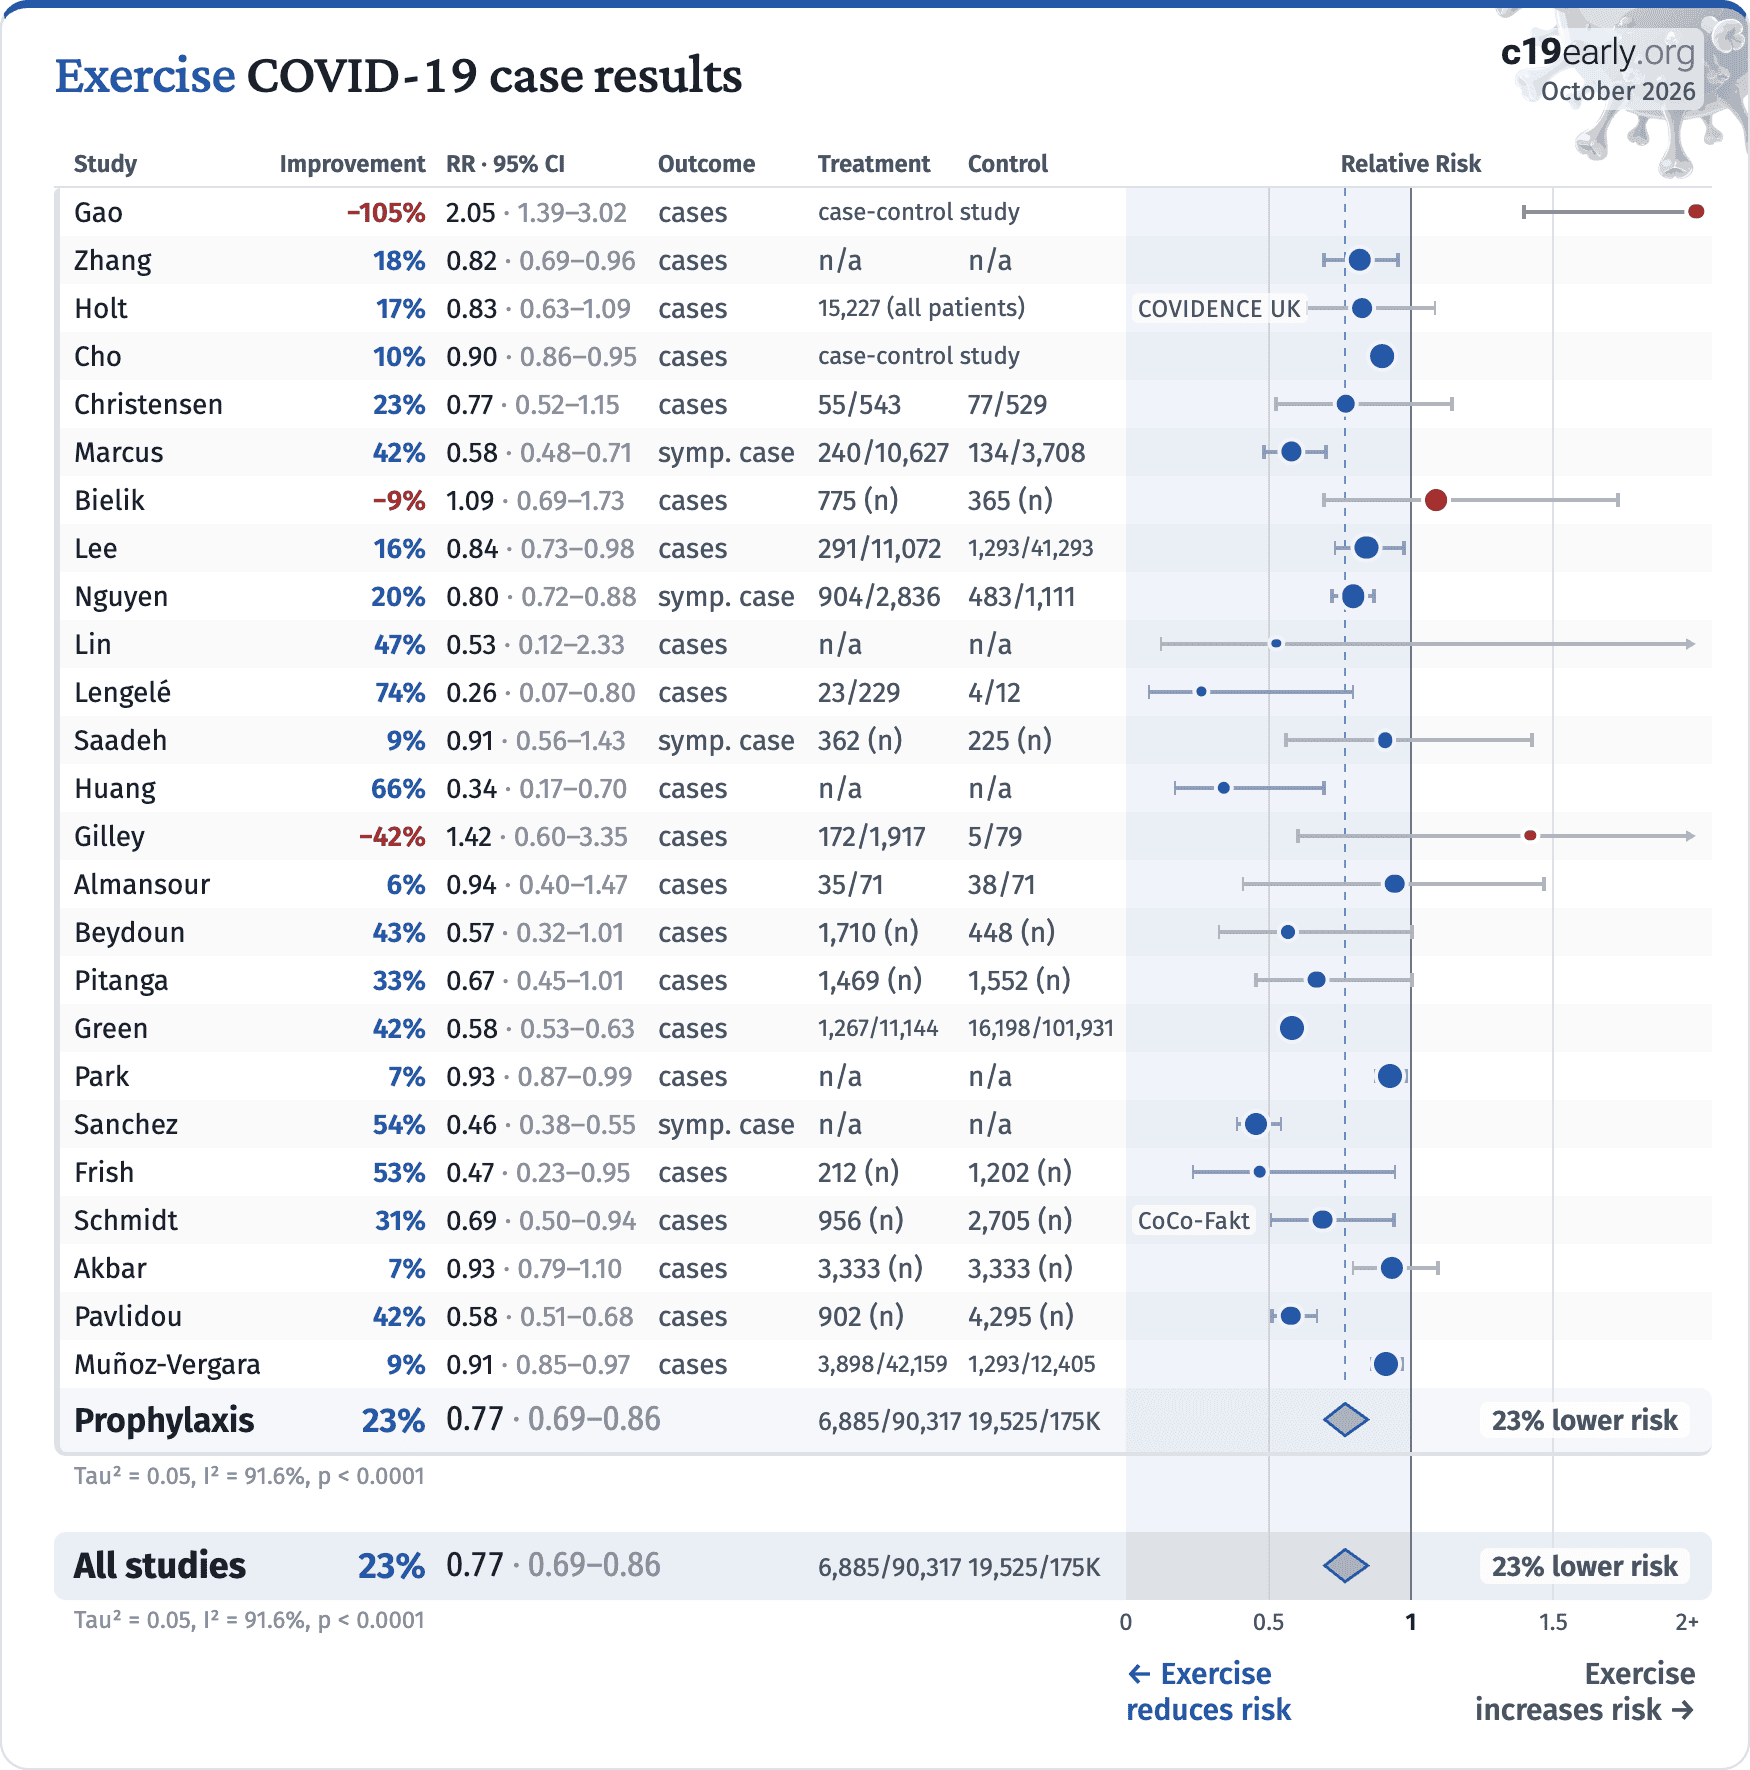
Prophylaxis23%0.77 · 0.69–0.866,885/90,31719,525/175K23% lower risk
Tau² = 0.05, I² = 91.6%, p < 0.0001
All studies23%0.77 · 0.69–0.866,885/90,31719,525/175K23% lower risk
Tau² = 0.05, I² = 91.6%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 10. Random-effects meta-analysis for cases.
October 2026

Exercise COVID-19 peer reviewed studies

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Late treatment47%0.53 · 0.31–0.8816/20162/23847% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
Hamer28%0.72 · 0.61–0.87hosp.n/an/a Brawner74%0.26 · 0.11–0.58hosp.n/an/a Tret'yakov98%0.02 · 0.00–0.27severe case0/2753/266 Gao−105%2.05 · 1.39–3.02casescase-control study Ho35%0.65 · 0.48–0.89hosp.213/123,58859/14,887 Halabchi89%0.11 · 0.01–1.46death0/24979/4,445 Zhang26%0.74 · 0.48–1.14deathn/an/a Li81%0.19 · 0.05–0.74severe casen/an/aper SD increase Tavakol69%0.31 · 0.10–1.02severe case3/6419/124 Yates45%0.55 · 0.38–0.79death72/163,91262/30,119 Holt17%0.83 · 0.63–1.09cases15,227 (all patients)COVIDENCE UK Cho53%0.47 · 0.26–0.87deathcase-control study Sallis59%0.41 · 0.22–0.76death11/3,118170/6,984 Christensen63%0.37 · 0.16–0.85death543 (n)529 (n) Lobelo20%0.80 · 0.66–0.97hosp.2,121 (n)1,648 (n) Hegazy46%0.54 · 0.30–1.00m/s case24/827/13 Latorre-Román76%0.24 · 0.05–1.04hosp.n/an/a Marcus42%0.58 · 0.48–0.71symp. case240/10,627134/3,708 Yuan91%0.09 · 0.01–1.65death0/616/103 Brandenburg−6%1.06 · 0.23–4.79hosp.102 (n)39 (n) Bielik30%0.70 · 0.40–1.21mod. case775 (n)365 (n) af Geijerstam50%0.50 · 0.31–0.81death318,902 (n)336,271 (n) Lee74%0.26 · 0.07–0.99death2/11,07232/41,293 Maltagliati52%0.48 · 0.25–0.87hosp.n/an/a Baynouna AlKetbi98%0.01 · 0.00–0.44deathn/an/a Ahmadi30%0.70 · 0.54–0.89death160/232,613112/95,221 Nguyen20%0.80 · 0.72–0.88symp. case904/2,836483/1,111 Lin47%0.53 · 0.12–2.33casesn/an/a de Souza73%0.27 · 0.07–1.06ventilation3/6116/327 Mohsin19%0.81 · 0.66–0.99severe case86/258224/544 Ekblom-Bak48%0.52 · 0.30–0.92severe casen/an/a Lengelé74%0.26 · 0.07–0.80cases23/2294/12 Saadeh9%0.91 · 0.56–1.43symp. case362 (n)225 (n) Hamrouni29%0.71 · 0.55–0.92death138/106,006109/47,827 Huang47%0.53 · 0.23–1.22severe case7/7416/90 Hamdan16%0.84 · 0.49–1.39hosp.22/12837/172 Steenkamp42%0.58 · 0.50–0.68death29,469 (n)13,366 (n) Gilley−42%1.42 · 0.60–3.35cases172/1,9175/79 Almansour6%0.94 · 0.40–1.47cases35/7138/71 Beydoun43%0.57 · 0.32–1.01cases1,710 (n)448 (n) Salgado-Aranda83%0.17 · 0.05–0.56death4/22341/297 Kontopoulou66%0.34 · 0.24–0.47recov. time42 (n)24 (n) Malisoux63%0.37 · 0.14–0.98progression115 (n)108 (n) Antunes80%0.20 · 0.03–1.41ICU1/149/25 Reis41%0.59 · 0.26–1.26hosp.9/24129/305 Pływaczewska-J..11%0.89 · 0.72–1.11m/s case490 (n)1,357 (n) Pitanga33%0.67 · 0.45–1.01cases1,469 (n)1,552 (n) Green42%0.58 · 0.53–0.63cases1,267/11,14416,198/101,931 Kapusta71%0.29 · 0.20–0.43severe case181 (n)387 (n) Young74%0.26 · 0.20–0.33death11,279 (n)29,099 (n) Wang11%0.89 · 0.75–1.06PASC274/691283/594LONG COVID Park26%0.74 · 0.53–1.04deathn/an/a Sanchez54%0.46 · 0.38–0.55symp. casen/an/a Cardoso73%0.27 · 0.17–0.45severe casecase-control study Feter26%0.74 · 0.58–0.95PASC52 (n)95 (n)LONG COVID Sutkowska62%0.38 · 0.08–1.72death71 (n)60 (n) Frish53%0.47 · 0.23–0.95cases212 (n)1,202 (n) Schmidt31%0.69 · 0.50–0.94cases956 (n)2,705 (n)CoCo-Fakt Šebić89%0.11 · 0.01–1.90oxygen0/534/47 Hegazy54%0.46 · 0.27–0.77m/s case15/5015/23 Akbar7%0.93 · 0.79–1.10cases3,333 (n)3,333 (n) Pavlidou42%0.58 · 0.51–0.68cases902 (n)4,295 (n) Rocha20%0.80 · 0.63–0.99PASC388 (n)2,096 (n)LONG COVID Wang30%0.70 · 0.61–0.80death57,930 (n)10,966 (n) Muñoz-Vergara27%0.73 · 0.60–0.90hosp.332/42,159203/12,405
Prophylaxis38%0.62 · 0.57–0.684,017/1143K18,437/773K38% lower risk
Tau² = 0.07, I² = 80.0%, p < 0.0001
All studies38%0.62 · 0.57–0.674,033/1143K18,499/773K38% lower risk
Tau² = 0.07, I² = 79.7%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 11. Random-effects meta-analysis for peer reviewed studies. Zeraatkar et al. analyze 356 COVID-19 trials, finding no significant evidence that preprint results are inconsistent with peer-reviewed studies. They also show extremely long peer-review delays, with a median of 6 months to journal publication. A six month delay was equivalent to around 1.5 million deaths during the first two years of the pandemic. Authors recommend using preprint evidence, with appropriate checks for potential falsified data, which provides higher certainty much earlier. Davidson et al. also showed no important difference between meta-analysis results of preprints and peer-reviewed publications for COVID-19, based on 37 meta-analyses including 114 trials. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
October 2026

Exercise COVID-19 long COVID results

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
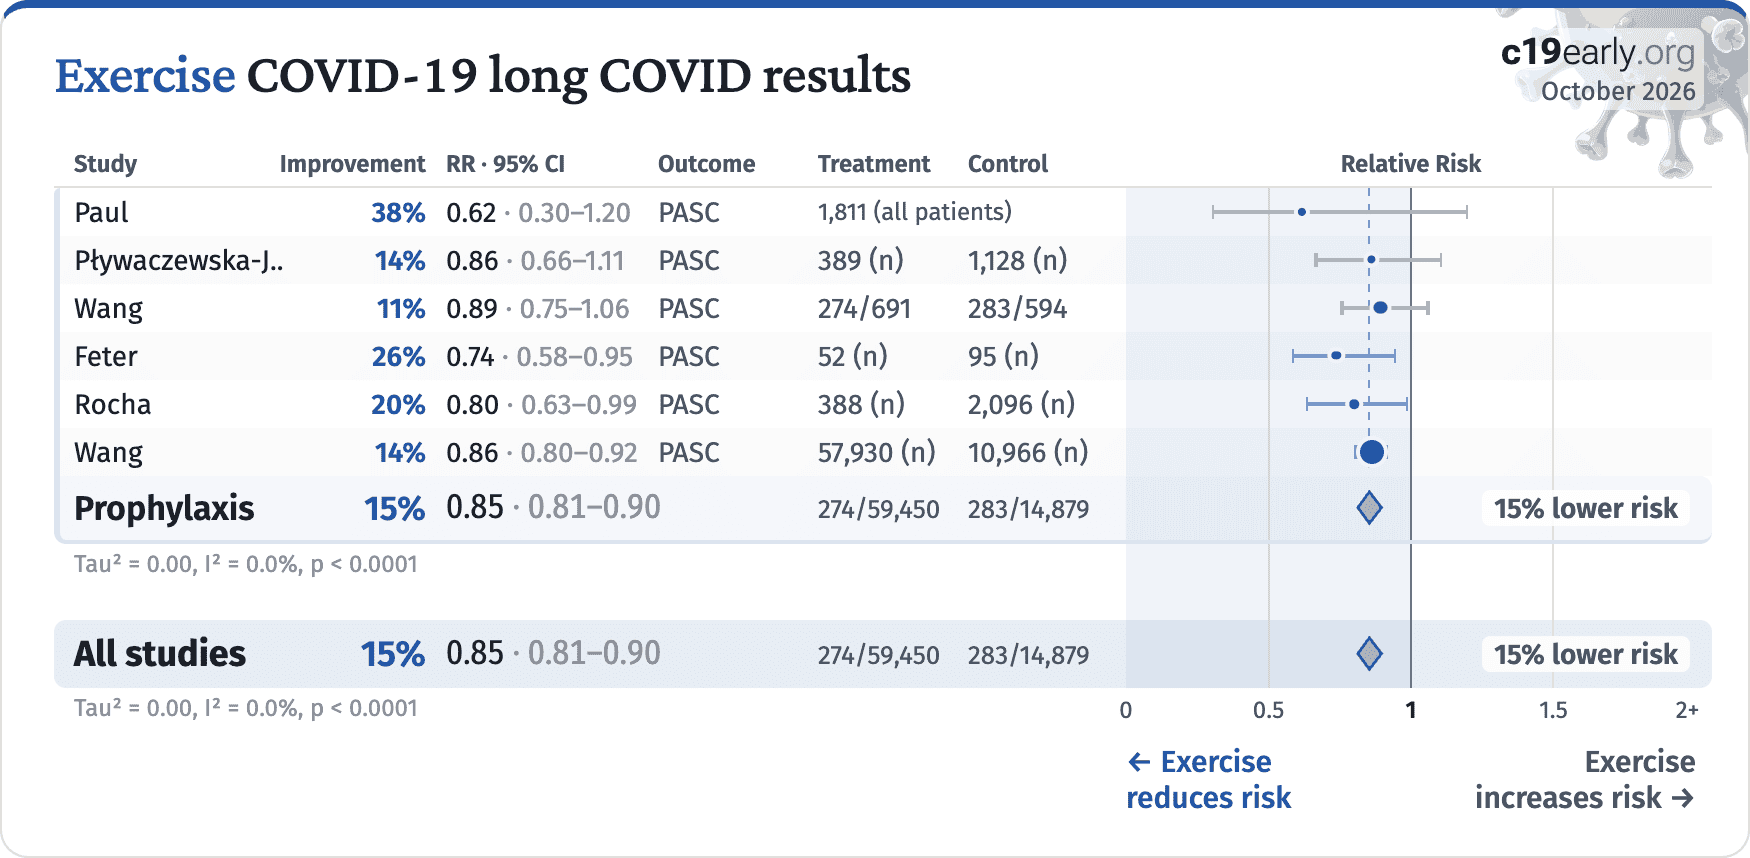
Prophylaxis15%0.85 · 0.81–0.90274/59,450283/14,87915% lower risk
Tau² = 0.00, I² = 0.0%, p < 0.0001
All studies15%0.85 · 0.81–0.90274/59,450283/14,87915% lower risk
Tau² = 0.00, I² = 0.0%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 12. Random-effects meta-analysis for long COVID. Effect extraction is pre-specified, using the most serious outcome reported, see the appendix for details. Analysis validating pooled outcomes for COVID-19 can be found below.
To avoid bias in the selection of studies, we analyze all non-retracted studies. Here we show the results after excluding studies with major issues likely to alter results, non-standard studies, and studies where very minimal detail is currently available. Our bias evaluation is based on analysis of each study and identifying when there is a significant chance that limitations will substantially change the outcome of the study. We believe this can be more valuable than checklist-based approaches such as Cochrane GRADE, which can be easily influenced by potential bias, may ignore or underemphasize serious issues not captured in the checklists, and may overemphasize issues unlikely to alter outcomes in specific cases (for example certain specifics of randomization with a very large effect size and well-matched baseline characteristics).
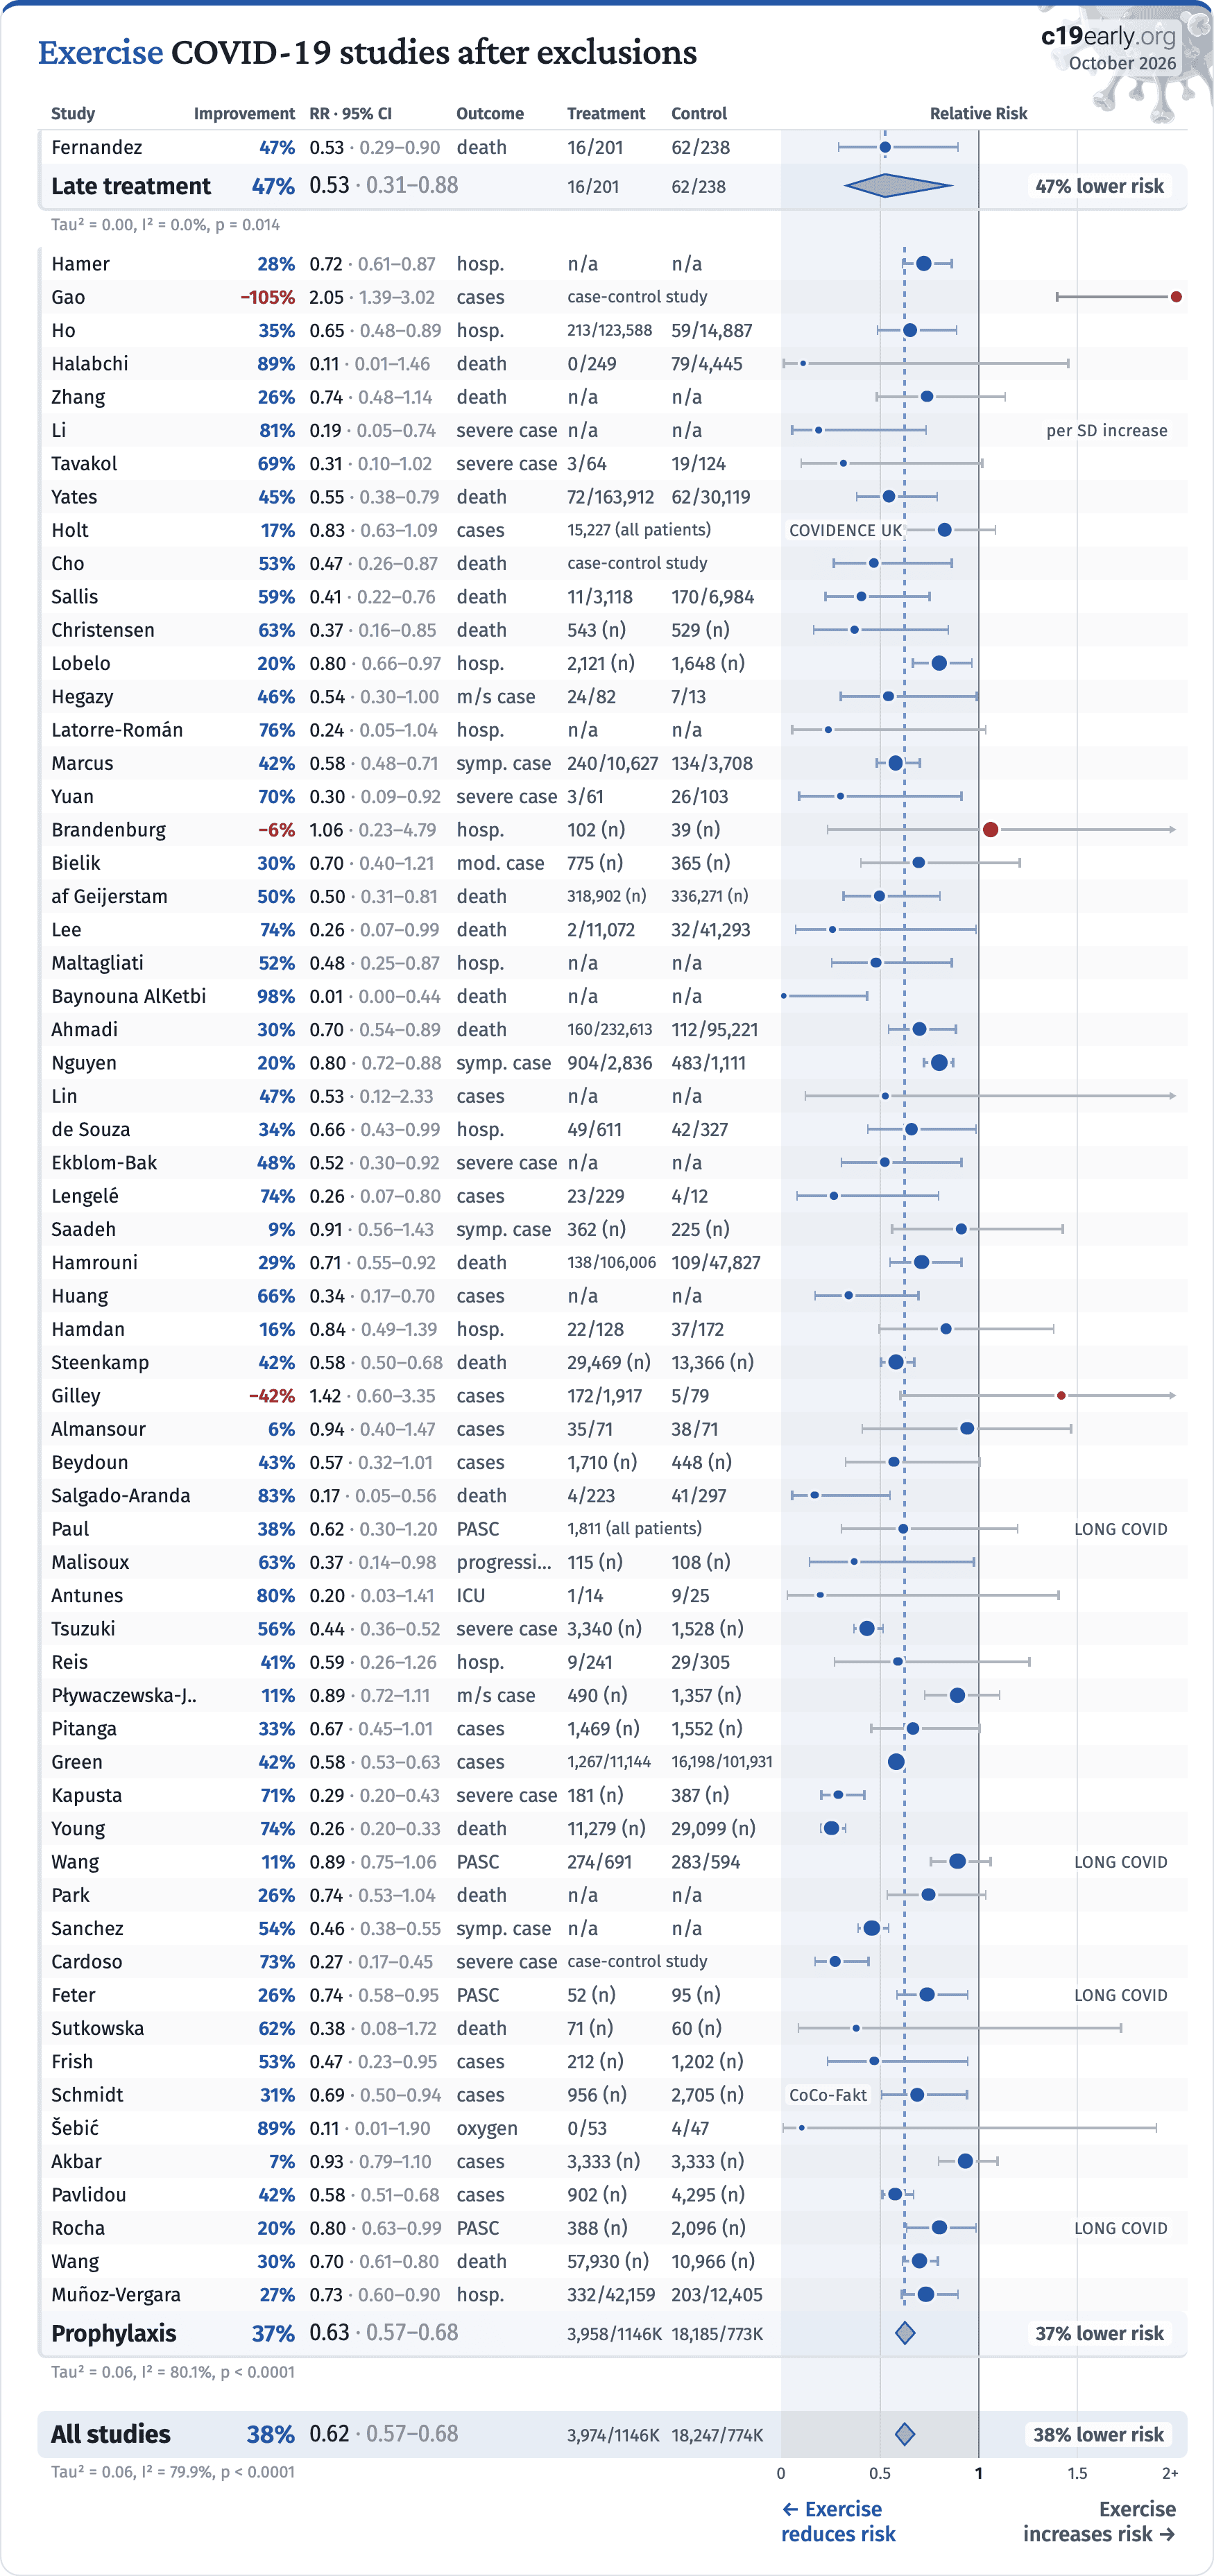
The studies excluded are as below. Fig. 13 shows a forest plot for random-effects meta-analysis of all studies after exclusions.
Brawner, unadjusted results with no group details.
de Souza, unadjusted results with no group details. Excluded results: mechanical ventilation.
Hegazy, unadjusted results with no group details.
Huang, unadjusted results with no group details. Excluded results: severe case.
Kontopoulou, unadjusted results with no group details.
Mohsin, unadjusted results with no group details.
Tret'yakov, unadjusted results with no group details.
Yuan, excessive unadjusted differences between groups. Excluded results: death.
October 2026

Exercise COVID-19 studies after exclusions

StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Late treatment47%0.53 · 0.31–0.8816/20162/23847% lower risk
Tau² = 0.00, I² = 0.0%, p = 0.014
Hamer28%0.72 · 0.61–0.87hosp.n/an/a Gao−105%2.05 · 1.39–3.02casescase-control study Ho35%0.65 · 0.48–0.89hosp.213/123,58859/14,887 Halabchi89%0.11 · 0.01–1.46death0/24979/4,445 Zhang26%0.74 · 0.48–1.14deathn/an/a Li81%0.19 · 0.05–0.74severe casen/an/aper SD increase Tavakol69%0.31 · 0.10–1.02severe case3/6419/124 Yates45%0.55 · 0.38–0.79death72/163,91262/30,119 Holt17%0.83 · 0.63–1.09cases15,227 (all patients)COVIDENCE UK Cho53%0.47 · 0.26–0.87deathcase-control study Sallis59%0.41 · 0.22–0.76death11/3,118170/6,984 Christensen63%0.37 · 0.16–0.85death543 (n)529 (n) Lobelo20%0.80 · 0.66–0.97hosp.2,121 (n)1,648 (n) Hegazy46%0.54 · 0.30–1.00m/s case24/827/13 Latorre-Román76%0.24 · 0.05–1.04hosp.n/an/a Marcus42%0.58 · 0.48–0.71symp. case240/10,627134/3,708 Yuan70%0.30 · 0.09–0.92severe case3/6126/103 Brandenburg−6%1.06 · 0.23–4.79hosp.102 (n)39 (n) Bielik30%0.70 · 0.40–1.21mod. case775 (n)365 (n) af Geijerstam50%0.50 · 0.31–0.81death318,902 (n)336,271 (n) Lee74%0.26 · 0.07–0.99death2/11,07232/41,293 Maltagliati52%0.48 · 0.25–0.87hosp.n/an/a Baynouna AlKetbi98%0.01 · 0.00–0.44deathn/an/a Ahmadi30%0.70 · 0.54–0.89death160/232,613112/95,221 Nguyen20%0.80 · 0.72–0.88symp. case904/2,836483/1,111 Lin47%0.53 · 0.12–2.33casesn/an/a de Souza34%0.66 · 0.43–0.99hosp.49/61142/327 Ekblom-Bak48%0.52 · 0.30–0.92severe casen/an/a Lengelé74%0.26 · 0.07–0.80cases23/2294/12 Saadeh9%0.91 · 0.56–1.43symp. case362 (n)225 (n) Hamrouni29%0.71 · 0.55–0.92death138/106,006109/47,827 Huang66%0.34 · 0.17–0.70casesn/an/a Hamdan16%0.84 · 0.49–1.39hosp.22/12837/172 Steenkamp42%0.58 · 0.50–0.68death29,469 (n)13,366 (n) Gilley−42%1.42 · 0.60–3.35cases172/1,9175/79 Almansour6%0.94 · 0.40–1.47cases35/7138/71 Beydoun43%0.57 · 0.32–1.01cases1,710 (n)448 (n) Salgado-Aranda83%0.17 · 0.05–0.56death4/22341/297 Paul38%0.62 · 0.30–1.20PASC1,811 (all patients)LONG COVID Malisoux63%0.37 · 0.14–0.98progression115 (n)108 (n) Antunes80%0.20 · 0.03–1.41ICU1/149/25 Tsuzuki56%0.44 · 0.36–0.52severe case3,340 (n)1,528 (n) Reis41%0.59 · 0.26–1.26hosp.9/24129/305 Pływaczewska-J..11%0.89 · 0.72–1.11m/s case490 (n)1,357 (n) Pitanga33%0.67 · 0.45–1.01cases1,469 (n)1,552 (n) Green42%0.58 · 0.53–0.63cases1,267/11,14416,198/101,931 Kapusta71%0.29 · 0.20–0.43severe case181 (n)387 (n) Young74%0.26 · 0.20–0.33death11,279 (n)29,099 (n) Wang11%0.89 · 0.75–1.06PASC274/691283/594LONG COVID Park26%0.74 · 0.53–1.04deathn/an/a Sanchez54%0.46 · 0.38–0.55symp. casen/an/a Cardoso73%0.27 · 0.17–0.45severe casecase-control study Feter26%0.74 · 0.58–0.95PASC52 (n)95 (n)LONG COVID Sutkowska62%0.38 · 0.08–1.72death71 (n)60 (n) Frish53%0.47 · 0.23–0.95cases212 (n)1,202 (n) Schmidt31%0.69 · 0.50–0.94cases956 (n)2,705 (n)CoCo-Fakt Šebić89%0.11 · 0.01–1.90oxygen0/534/47 Akbar7%0.93 · 0.79–1.10cases3,333 (n)3,333 (n) Pavlidou42%0.58 · 0.51–0.68cases902 (n)4,295 (n) Rocha20%0.80 · 0.63–0.99PASC388 (n)2,096 (n)LONG COVID Wang30%0.70 · 0.61–0.80death57,930 (n)10,966 (n) Muñoz-Vergara27%0.73 · 0.60–0.90hosp.332/42,159203/12,405
Prophylaxis37%0.63 · 0.57–0.683,958/1146K18,185/773K37% lower risk
Tau² = 0.06, I² = 80.1%, p < 0.0001
All studies38%0.62 · 0.57–0.683,974/1146K18,247/774K38% lower risk
Tau² = 0.06, I² = 79.9%, p < 0.000100.511.52+
Rotate screen for more detailsIncrease width for more details
← Exercise
reduces risk
Exercise
increases risk →
Fig. 13. Random-effects meta-analysis for all studies after exclusions. This plot shows pooled effects, see the specific outcome analyses for individual outcomes. Analysis validating pooled outcomes for COVID-19 can be found below. Effect extraction is pre-specified, using the most serious outcome reported. For details see the appendix.
Exercise is not expected to have a direct antiviral effect; rather, any benefits are hypothesized to stem from improving immune system function (host-directed efficacy). For such immunomodulatory treatments, we may expect a gradient of efficacy across outcomes, with minimal impact on preventing initial infection (PCR+ cases), but increasing efficacy as the disease progresses to more severe stages.
For exercise, random-effects meta-regression shows a significant association with increasing efficacy for more severe outcomes. For every one-step increase in severity (cases → hospitalization → critical outcomes: ICU, ventilation, and mortality), meta-regression shows that the Risk Ratio decreases by a factor of 1.22 (slope β = -0.20 [-0.32 to -0.09]; p = 0.00059). In other words, the protective effect becomes stronger as the outcome becomes more critical.
The trend across outcomes is consistent with a host-directed immunomodulatory mechanism rather than a direct antiviral effect. This reinforces the reliability of the overall finding that exercise reduces risk for COVID-19. If the observed efficacy was due to a systematic bias increasing the efficacy of outcomes, it would not be expected to create a trend across outcomes that matches the biological mechanism. Moreover, systematic biases are more likely to effect subjective outcomes than the objective mortality outcome. The fact that exercise shows the strongest effect on the most objective outcome (mortality) argues against such bias explaining the results.
With 68 studies for exercise, we can analyze trends across studies. A significant interaction that matches the biological mechanisms provides further confirmation of efficacy. Analysis of the efficacy gradient across outcomes shows a significant interaction, with p = 0.00059.
This reinforces the reliability of the overall finding that exercise reduces risk for COVID-19. If the observed efficacy was due to a systematic bias increasing efficacy in results, we would not expect analysis across studies to find this significant interaction that matches the biological mechanisms.
Low-cost treatments were subject to bias and censorship during the pandemic. Scientific bias is seen in the design, analysis, presentation, and selective reporting of studies, which often favored negative results. A similar bias is seen in the media coverage for low-cost treatments. While broadly seen, bias was particularly notable for ivermectin and hydroxychloroquine, e.g., Scott Alexander noted that "if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."13.
We analyze media coverage for the 227 treatments we cover using Altmetric31 and PlumX Metrics32. Altmetric covers ~14,000 news outlets33 and PlumX covers ~55,000 news sources34. The two services are complementary with coverage of different news sources and different methods for identifying articles not containing a DOI. We consider studies to have received significant media coverage if they were covered by at least 100 articles in either Altmetric of PlumX34,35. The most widespread study was covered by 1,047 outlets. Studies covered by major syndicated sources shows hundreds of news articles, while studies covered by few outlets typically appear in niche medical news sources or press releases. Fig. 14 and 15 show bias towards negative results for low-cost treatments, in contrast to the opposite bias for high-profit treatments.
Fig. 16 shows that the mainstream media covered only a small fraction of the positive studies for exercise.
The media bias may result in widespread incorrect perceptions on the relative efficacy of high-profit and low-cost treatments. The impact is significant—increased cost limits the use of high-profit treatments and treatment equity. High-profit treatments were also more difficult to access, especially for earlier treatment which improves efficacy and minimizes community transmission.
October 2026

Media coverage of low-cost COVID‑19 treatments

Media covered only 0.8% of studies showing significantly lower COVID-19 risk

Only 5 positive studies were covered

0.8%

34 negative studies were covered

4%
5.4×
Negative bias for low-cost treatments
negative studies were 5.4 times more likely to be covered
Fig. 14. Mainstream media coverage was biased against positive results for low-cost treatments. When restricting to RCTs, the bias was even larger, with negative RCTs 6.9× more likely to be covered.
October 2026

Media coverage of high-profit COVID‑19 treatments

Media was 3.8× more likely to cover positive studies

19 positive studies were covered

11%

Only 6 negative studies were covered

3%
3.8×
Positive bias for high-profit treatments
positive studies were 3.8 times more likely to be covered
Fig. 15. For high-profit treatments, mainstream media coverage was biased towards positive results. When restricting to RCTs, the bias was even larger, with positive RCTs 12.0× more likely to be covered.
October 2026

Media coverage of exercise for COVID‑19

Media covered only 8% of studies showing significantly lower COVID-19 risk

Only 4 positive exercise studies were covered

8%
Fig. 16. Mainstream media covered only a small fraction of the positive studies for exercise.
A combination of factors may have led to the very low media coverage of low-cost treatments:
•
Politicization
led to a media environment where coverage was often framed to support a political narrative rather than to provide objective scientific information. As Scott Alexander said:
"if you say anything in favor of ivermectin you will be cast out of civilization and thrown into the circle of social hell reserved for Klan members and 1/6 insurrectionists. All the health officials in the world will shout 'horse dewormer!' at you and compare you to Josef Mengele."
There was strong social pressure to discredit low-cost treatments.
•
Censorship
of information conflicting with selected authorities. For example, individuals and organizations presenting conflicting science were often shadowbanned or completely banned on Twitter and YouTube if the science they were reporting conflicted with the opinions of specific authorities selected by those companies, including when the authorities had not even reviewed the scientific results in question.
•
FDA requires "no adequate, approved, and available alternatives"
in order to grant an EUA for novel high-profit interventions, creating an incentive for authorities to ignore or downplay existing low-cost treatments.
•
Regulatory capture
biases authorities towards high-profit interventions.
•
Authorities ignored most evidence for low-cost treatments
, for example the NIH references only 2% of studies in delayed, rarely-updated, biased commentaries with no quantitive analysis.
•
Media coverage of science is often not very accurate
, e.g., misunderstanding confounding issues. For example the media widely considered the RECOVERY HCQ RCT to be conclusive on efficacy, but very late treatment of late-stage patients (mostly on oxygen already) with an excessive toxic dose (shown dangerous in a dose comparison RCT) provides no information on the recommended early/prophylactic treatment. With difficulting in understanding basic confounders like treatment delay and dose, the media may favor deferring to authorities. Many studies for low-cost treatments require greater expertise to analyze.
•
Substantial funding from pharmaceutical advertising
biases editorial decisions towards high-profit interventions.
•
PR power
- companies/teams with strong PR presence are favored in the media, which correlates with high-profit and high conflict of interest studies.
•
The media was very negative in general
, inflating risk, and elevating fear and anxiety. A negative bias may improve ratings and revenue, increasing motivation to continue watching coverage.
26 low-cost treatments were approved in one or more countries, yet many countries approved no low-cost treatments. The countries that did adopt low-cost treatments analyzed the evidence early and made timely approvals. With few exceptions, authorities did not change their initial views, regardless of how much evidence accumulated showing either efficacy or harm. Why?
The harms of smoking here hidden for 25 yearsB. Authorities did not analyze the data in real-time, failing to act when harm was known. Widespread acknowledgement of harm came only after attempts by two new surgeon generals, along with pressure from health advocates and a new president, and a review of 7,000 studies.
Similarly for COVID-19, most authorities and experts did not proactively analyze data in real-time. This guarantees delayed recognition of efficacy or harm, by which time moral, legal, career, and reputational liabilities strongly disincentivize any admission of error. Claims of no efficacy (for effective treatments) or safety (for harmful treatments) were often made prior to strong data being available. Correction would require admitting to errors that increased mortality, which is unlikely with the same generation of officials.
Analysis of potential treatments was rarely done, and when done these were typically minimal efforts. For example, NIH reviews were highly delayed, cover only a tiny fraction of treatments, reference only 2% of studies for the treatments covered, and include no quantitative analysis. They appear as rarely updated side projects from external panels implicitly tasked with justifying prior failures. As with smoking, the thousands of studies could (and should) have been analyzed and acted on in real-time.
A key structural improvement, applicable to all current and future diseases, is for authorities to implement real-time proactive analysis of clinical evidence. This does not remove all bias, but does make it possible to act on evidence, whereas delayed action may be unlikely due to moral, legal, career, and reputational liabilities.
c19early.org
Delayed public health acknowledgments
Official acknowledgment of efficacy or harm is often delayed—legal, career, and status risks disincentivize admission of error.
Evidence Official Acknowledgment Approx. Delay
Citrus Fruit (vitamin C) for Scurvy (effectiveness) 1747: James Lind conducted one of the first-ever controlled clinical trials, proving that oranges and lemons cured scurvy in sailors. 1795: The British Royal Navy finally made a daily ration of lemon juice a standard issue for all its sailors, effectively eliminating the disease. 48 years
Handwashing (lower mortality) 1847: Dr. Ignaz Semmelweis provided conclusive proof that having doctors wash their hands with a chlorine solution before delivering babies reduced maternal mortality rates from over 18% to around 1%. ~1870s: Semmelweis's findings were rejected and he was ridiculed. His work was only validated decades later (after his death). ~20+ years
Helicobacter pylori (bacteria causes ulcers) 1982-1984: Marshall and Warren discovered that Helicobacter pylori bacteria causes ulcers, confirmed via direct exposure. Officials maintained that ulcers were caused by stress and spicy food. 1994: The US NIH released a consensus statement officially recommending antibiotics as the standard treatment for peptic ulcers, overturning decades of acid-suppression therapy. ~12 years
Asbestos (causes asbestosis & cancer) 1924: The British Medical Journal published the first case study of a death from "asbestosis." By 1918, U.S. insurance companies had stopped selling life insurance to asbestos workers. 1971 (US): The Occupational Safety and Health Administration (OSHA) was formed and began regulating asbestos as a carcinogen, setting the first federal workplace safety standards for it. ~47 years
Leaded Gasoline (neurotoxicity) ~1924: Dangers of low-level lead exposure were known. Experts like Alice Hamilton warned the U.S. Surgeon General that adding lead to gasoline would cause widespread public poisoning. 1973 (US): The Environmental Protection Agency (EPA) ordered the first phasedown of lead in gasoline, following the Clean Air Act of 1970. A full ban for on-road vehicles took effect in 1996. ~49 years
Harms of Smoking (causes lung cancer) 1939: Franz Müller (Germany) published the first case-control epidemiological study strongly linking tobacco smoking to lung cancer. This was followed by major U.S. & U.K. studies in the 1950s. 1964 (US): The U.S. Surgeon General's report, "Smoking and Health," was released. It was the first U.S. government report to definitively link smoking to lung cancer and heart disease. 25 years
This section validates the use of pooled effects for COVID-19, which enables earlier detection of efficacy, however pooled effects are no longer required for exercise as of November 2020. Efficacy is now known based on specific outcomes. Efficacy based on specific outcomes was delayed by 0.8 months compared to using pooled outcomes.
For COVID-19, delay in clinical results translates into additional death and morbidity, as well as additional economic and societal damage. Combining the results of studies reporting different outcomes is required. There may be no mortality in a trial with low-risk patients, however a reduction in severity or improved viral clearance may translate into lower mortality in a high-risk population. Different studies may report lower severity, improved recovery, and lower mortality, and the significance may be very high when combining the results. "The studies reported different outcomes" is not a good reason for disregarding results. Pooling the results of studies reporting different outcomes allows us to use more of the available information. Logically we should, and do, use additional information when evaluating treatments—for example dose-response and treatment delay-response relationships provide additional evidence of efficacy that is considered when reviewing the evidence for a treatment.
We present both specific outcome and pooled analyses. In order to combine the results of studies reporting different outcomes we use the most serious outcome reported in each study, based on the thesis that improvement in the most serious outcome provides comparable measures of efficacy for a treatment. A critical advantage of this approach is simplicity and transparency. There are many other ways to combine evidence for different outcomes, along with additional evidence such as dose-response relationships, however these increase complexity.
Trials with high-risk patients may be restricted due to ethics for treatments that are known or expected to be effective, and they increase difficulty for recruiting. Using less severe outcomes as a proxy for more serious outcomes allows faster and safer collection of evidence.
For many COVID-19 treatments, a reduction in mortality logically follows from a reduction in hospitalization, which follows from a reduction in symptomatic cases, which follows from a reduction in PCR positivity. We can directly test this for COVID-19.
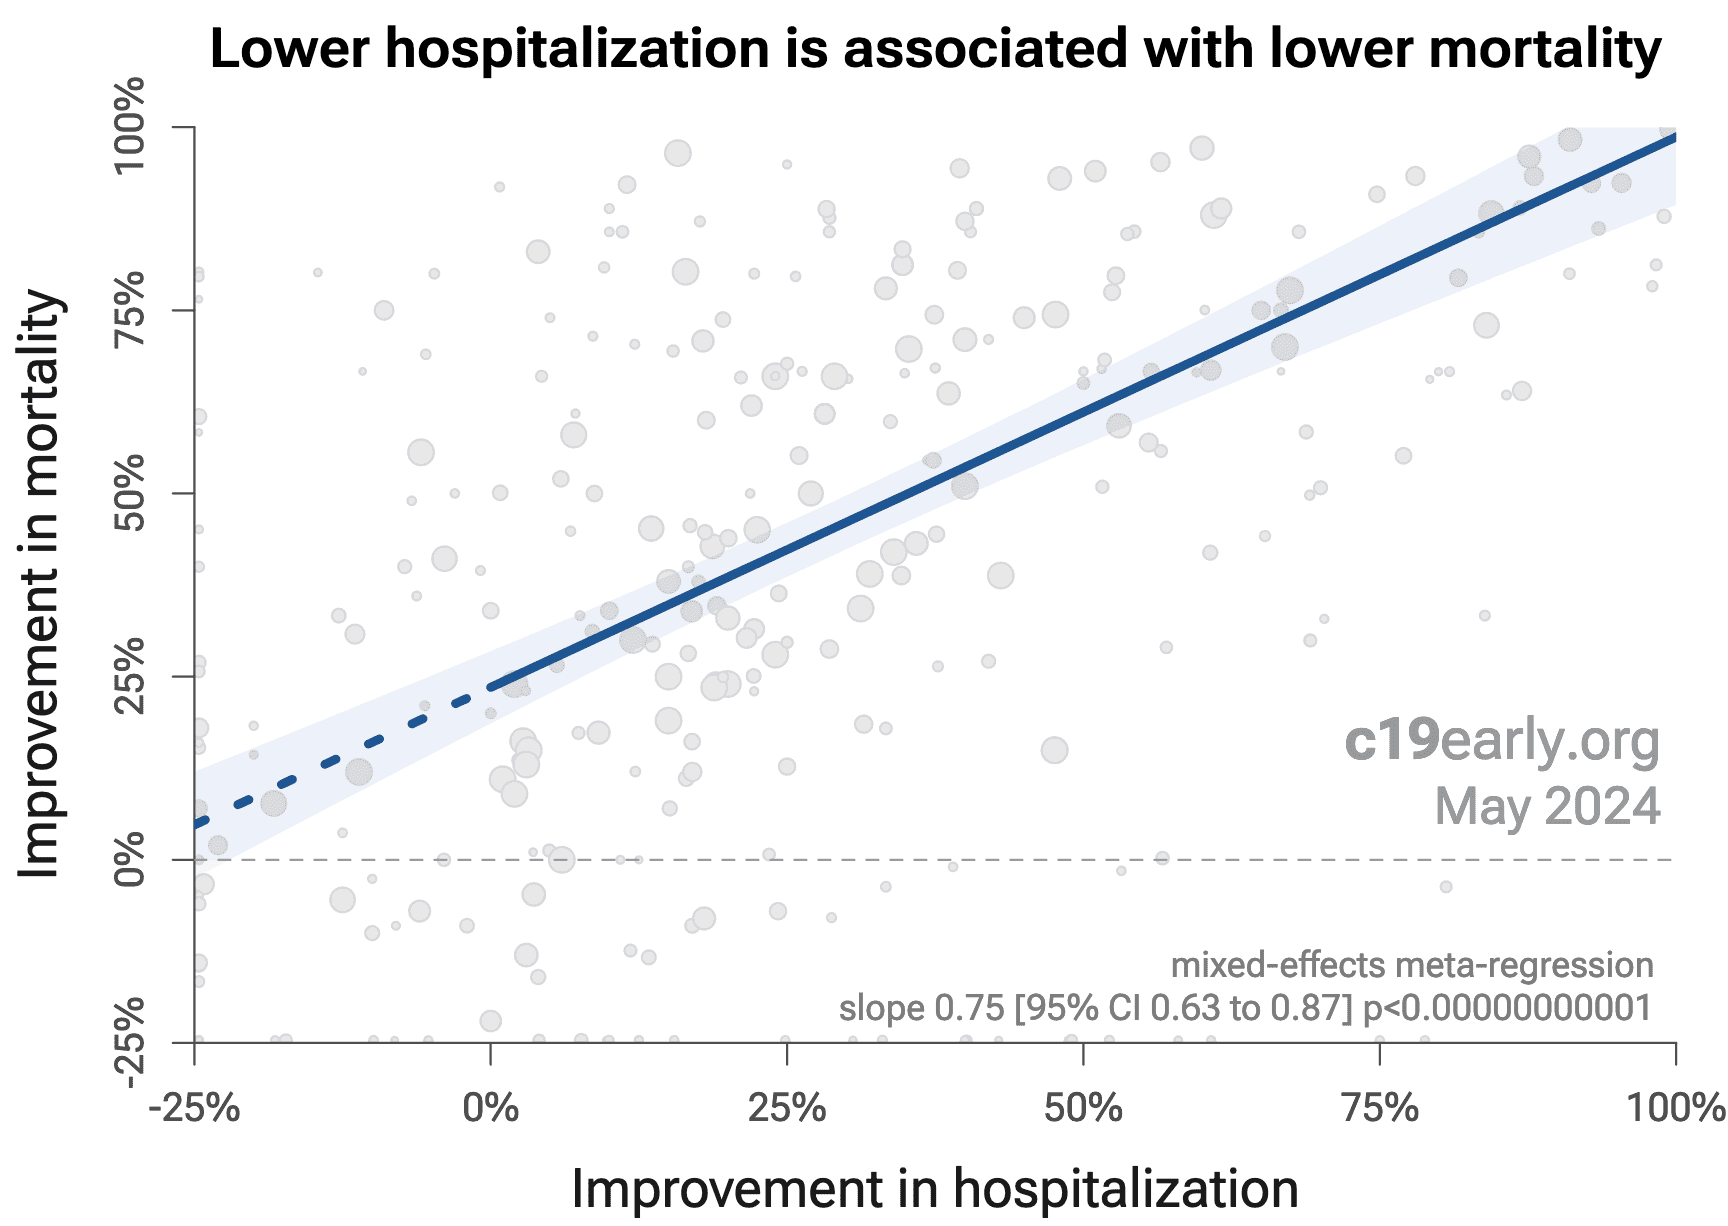
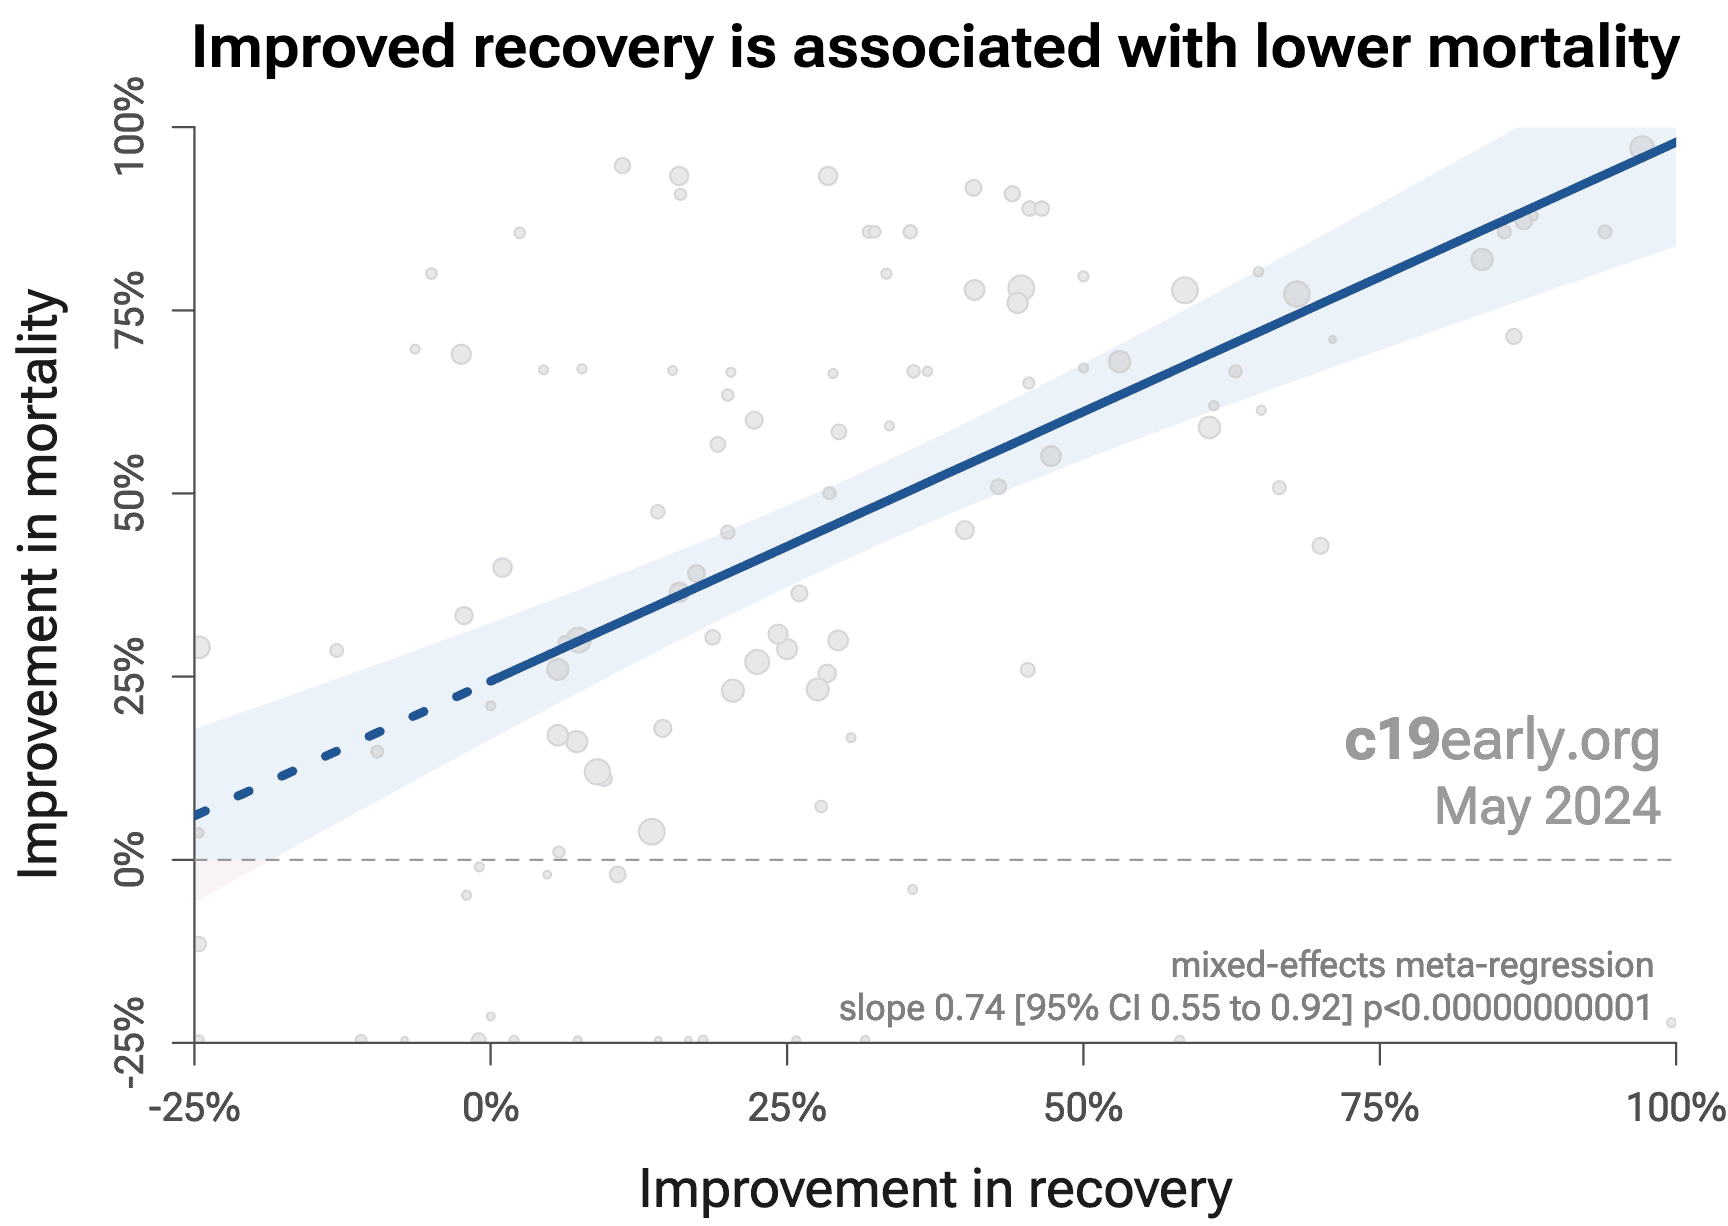
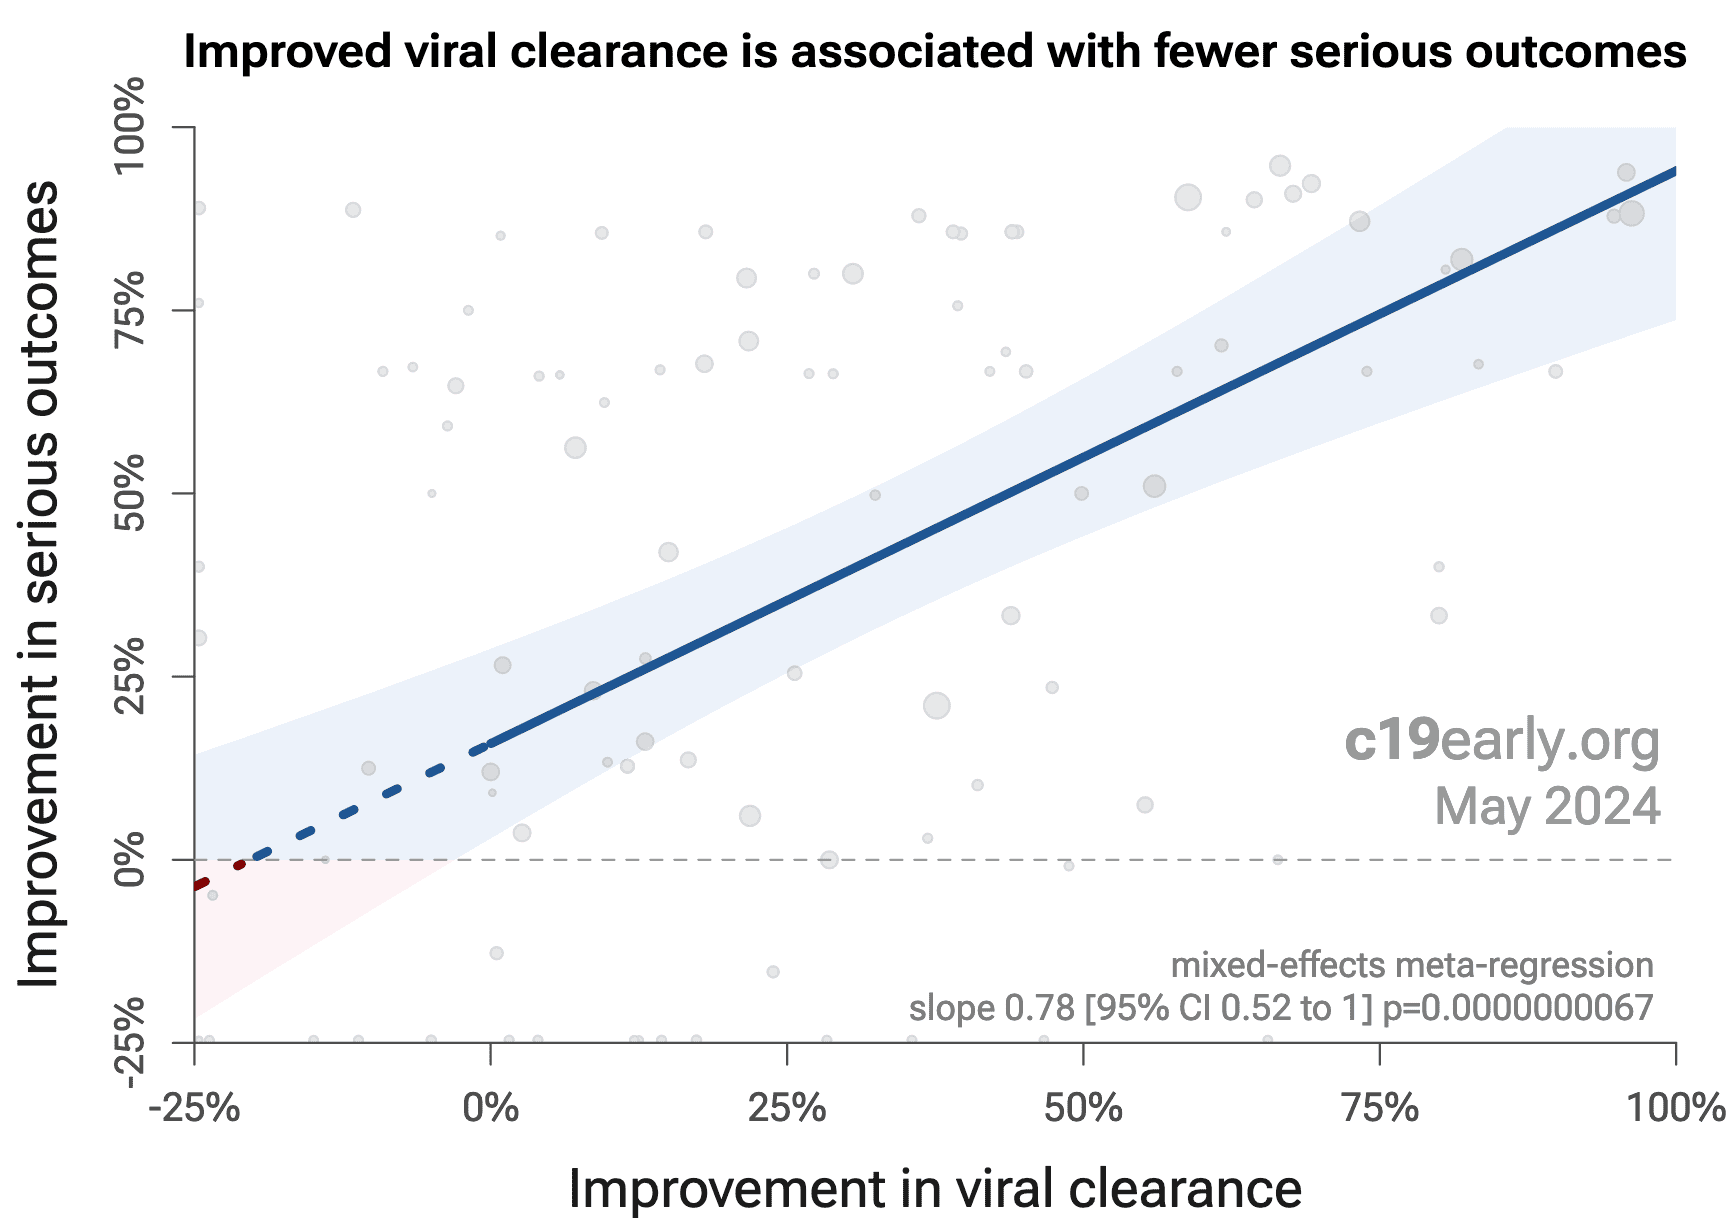
Analysis of the the association between different outcomes across studies from all 227 treatments we cover confirms the validity of pooled outcome analysis for COVID-19. Fig. 17 shows that lower hospitalization is very strongly associated with lower mortality (p < 0.0000000001). Similarly, Fig. 18 shows that improved recovery is very strongly associated with lower mortality (p < 0.0000000001). Considering the extremes, Singh et al. show an association between viral clearance and hospitalization or death, with p = 0.003 after excluding one large outlier from a mutagenic treatment, and based on 44 RCTs including 52,384 patients. Fig. 19 shows that improved viral clearance is strongly associated with fewer serious outcomes. The association is very similar to Singh et al., with higher confidence due to the larger number of studies. As with Singh et al., the confidence increases when excluding the outlier treatment, from p = 0.0000000074 to p = 0.00000000015.
Loading..
Fig. 17. Lower hospitalization is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 18. Improved recovery is associated with lower mortality, supporting pooled outcome analysis.
Loading..
Fig. 17. Improved viral clearance is associated with fewer serious outcomes, supporting pooled outcome analysis.
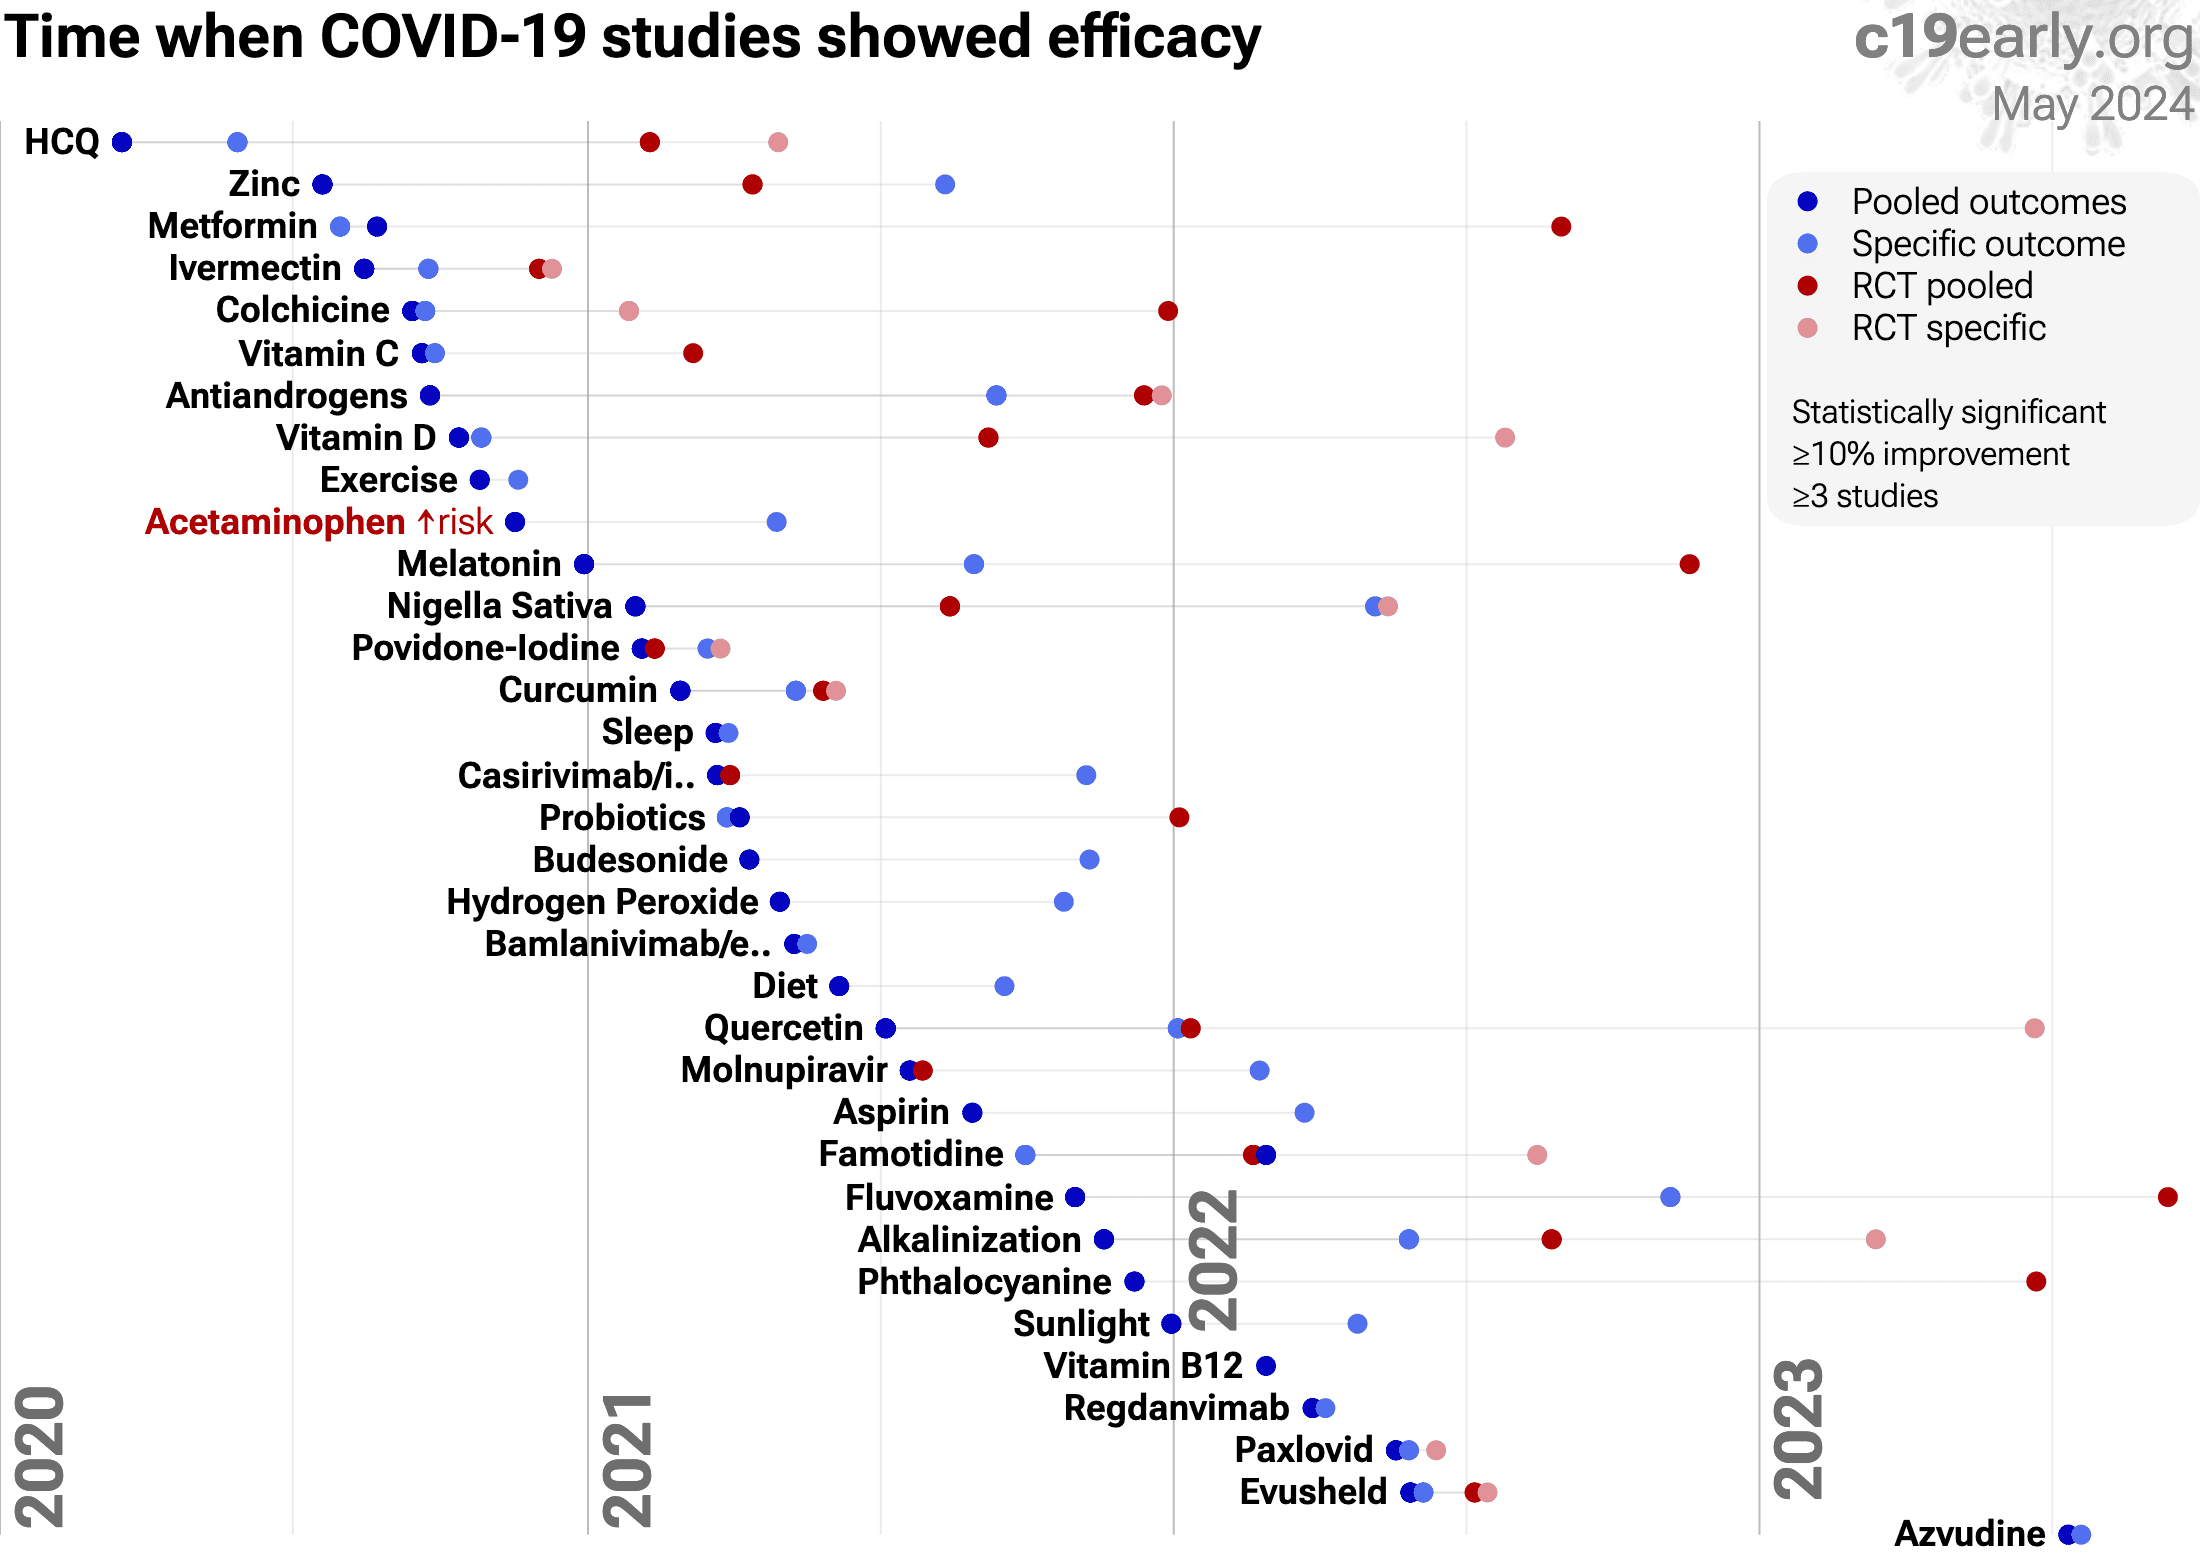
Currently, 59 of the treatments we analyze show statistically significant efficacy or harm, defined as ≥10% decreased risk or >0% increased risk from ≥3 studies. 85% of these have been confirmed with one or more specific outcomes, with a mean delay of 4.6 months. When restricting to RCTs only, 53% of treatments showing statistically significant efficacy/harm with pooled effects have been confirmed with one or more specific outcomes, with a mean delay of 7.5 months. Fig. 20 shows when treatments were found effective during the pandemic. Pooled outcomes often resulted in earlier detection of efficacy.
Loading..
Loading..
Fig. 20. The time when studies showed that treatments were effective, defined as statistically significant improvement of ≥10% from ≥3 studies. Pooled results typically show efficacy earlier than specific outcome results. Results from all studies often shows efficacy much earlier than when restricting to RCTs. Results reflect conditions as used in trials to date, these depend on the population treated, treatment delay, and treatment regimen.
Pooled analysis could hide efficacy, for example a treatment that is beneficial for late stage patients but has no effect on viral clearance may show no efficacy if most studies only examine viral clearance. In practice, it is rare for a non-antiviral treatment to report viral clearance and to not report clinical outcomes; and in practice other sources of heterogeneity such as differences in treatment delay are more likely to hide efficacy.
Analysis validates the use of pooled effects and shows significantly faster detection of efficacy on average. However, as with all meta-analyses, it is important to review the different studies included. We also present individual outcome analyses, which may be more informative for specific use cases.
Efficacy with exercise has also been shown for pneumonia12.
Most studies analyze activity levels before infection, comparing regular/moderate exercise and lower/no exercise. Risk may increase with more extreme activity levels. Exercise may also be beneficial after infection. One study shows lower COVID-19 mortality with exercise during hospitalization2. When appropriate and within limits, exercise may be beneficial even for later stage patients, for example a non-COVID-19 RCT with critical patients under mechanical ventilation (APACHE II 22) shows lower mortality with exercise37.
Exercise during infection may increase the risk of transmission to others3, precautions should be taken to avoid transmission if potentially infected.
6 other meta-analyses show significant improvements with exercise for mortality4-8, ICU admission4, hospitalization4,5,8,9, severity5-7, and cases5.
Multiple reviews cover exercise for COVID-19, presenting additional background on mechanisms and related results, including3,38-40.
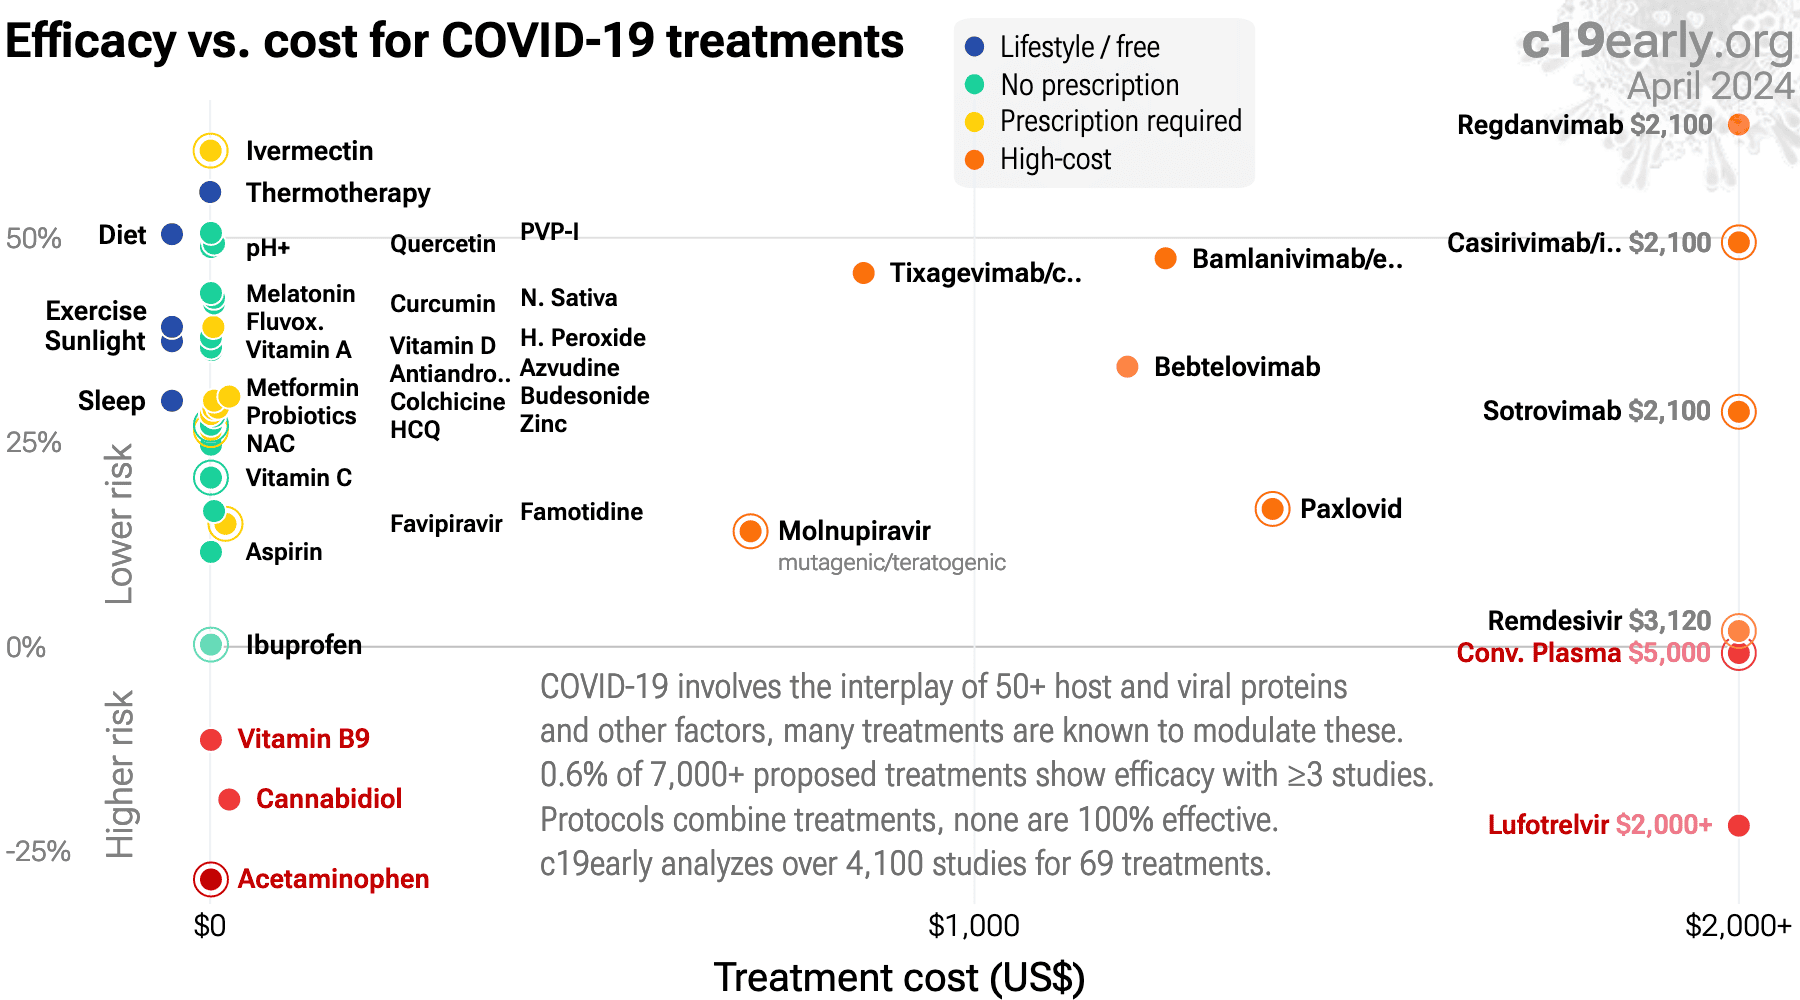
SARS-CoV-2 infection and replication involves a complex interplay of 500+ host and viral proteins and other factors41-48, providing many therapeutic targets. Over 12,000 compounds have been predicted to reduce COVID-19 risk19, either by directly minimizing infection or replication, by supporting immune system function, or by minimizing secondary complications. Exercise can improve immune system function, reduce chronic inflammation, improve cardiovascular health, improve comorbidities, enhance lung function, reduce stress, and increase nitric oxide. Prolonged high-intensity workouts may temporarily suppress the immune system. Fig. 21 shows an overview of the results for exercise in the context of multiple COVID-19 treatments, and Fig. 22 shows a plot of efficacy vs. cost for COVID-19 treatments.
Loading..
Fig. 21. Scatter plot showing results within the context of multiple COVID-19 treatments. Diamonds shows the results of random-effects meta-analysis. 0.5% of 12,000+ proposed treatments show efficacy49.
Loading..
Loading..
Fig. 22. Efficacy vs. cost for COVID-19 treatments.
Exercise can improve immune system function, reduce chronic inflammation, improve cardiovascular health, improve comorbidities, enhance lung function, reduce stress, and increase nitric oxide. Prolonged high-intensity workouts may temporarily suppress the immune system.
More physically active people have reduced risk for COVID-19. Significantly lower risk is seen for mortality, ventilation, ICU admission, hospitalization, progression, recovery, and cases. 52 studies from 52 independent teams in 24 countries show significant benefit. Meta-analysis using the most serious outcome reported shows 39% [33‑44%] lower risk. Results are similar for higher quality and peer-reviewed studies. Results are consistent with the overall risk of all cause mortality based on cardiorespiratory fitness — Laukkanen show RR 0.55 [0.50-0.61] for the top vs. bottom tertiles.
Results are very robust—in worst case exclusion sensitivity analysis 56 of 68 studies must be excluded before statistical significance is lost. Emergent results for the efficacy gradient across outcomes (p = 0.00059) that match the biological mechanisms confirm efficacy.
Most studies analyze activity levels before infection, comparing regular/moderate exercise and lower/no exercise. Risk may increase with more extreme activity levels. Exercise may also be beneficial after infection. One study shows lower COVID-19 mortality with exercise during hospitalization2.
6 other meta-analyses show significant improvements with exercise for mortality4-8, ICU admission4, hospitalization4,5,8,9, severity5-7, and cases5.
Efficacy with exercise has also been shown for pneumonia12.
Exercise during infection may increase the risk of transmission to others3, precautions should be taken to avoid transmission if potentially infected.
 
Contact.
Contact us on X at @CovidAnalysis.
Funding.
We have received no funding or compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
AI.
We use AI models (Gemini, Grok, Claude, and ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.
Updates.
Our COVID-19 meta-analyses involve the extraction of over 229,000 datapoints from thousands of papers for 227 treatments. We thank the thousands of scientists, physicians, and other contributors that have provided updates, suggestions, feedback, and corrections. These are all welcome and can be submitted at https://c19early.org/exmeta.html.
Dedication.
This work is dedicated to top evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce mortality and morbidity during the pandemic. In alphabetical order: Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty, Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr. Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch, Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work distributed in accordance with the Creative Commons CC0 1.0 Universal license, which dedicates the work to the public domain by waiving all rights worldwide under copyright law. You can distribute, remix, adapt, and build upon this work in any medium or format, including for commercial purposes, without asking permission. Referenced material and third-party images retain any original copyrights or restrictions. See: https://creativecommons.org/publicdomain/zero/1.0/.
ProphylaxisProspective · 1,559,187 patients · Sweden · Mar – Sep 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and ICU admission
p = 0.0047 (mortality) and p = 0.00032 (ICU admission)
Prospective study of 1,559,187 men in Sweden with cardiorespiratory fitness levels measured on military conscription, showing high cardiorespiratory fitness associated with lower risk of COVID-19 hospitalization, ICU admission, and death. Submit Corrections or Updates.
Retrospective 468,569 adults in the UK, showing significantly lower COVID-19 mortality with physical activity. Submit Corrections or Updates.
Retrospective 10,000 adults in Qatar, showing lower risk of COVID-19 cases with increased leisure time physical activity, without statistical significance. Authors do not analyze COVID-19 severity. Submit Corrections or Updates.
Retrospective 142 patients in Saudi Arabia, showing no significant difference in cases with physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 39 patients · Brazil · Sep – Dec 2020
Exercise for COVID-19
Shorter hospitalization with higher activity levels
p = 0.03
Retrospective 39 hospitalized COVID-19 survivors >60 years old, showing shorter hospitalization for patients with active lifestyles before COVID-19 symptoms. Submit Corrections or Updates.
Retrospective 234 COVID-19 cases in the United Arab Emirates, showing lower risk of mortality with increased physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 2,158 patients · USA
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Fewer cases with higher activity levels
Not statistically significant · p = 0.055
Retrospective 2,830 people in the USA, showing lower risk of COVID-19 with a history of moderate/vigorous exercise. Submit Corrections or Updates.
ProphylaxisRetrospective · 1,140 patients · Slovakia · December 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Fewer moderate/severe cases with higher activity levels
Not statistically significant · p = 0.1
Retrospective 1,544 participants in Slovakia, showing a lower risk of more severe COVID-19 for physically active participants, without statistical significance. Submit Corrections or Updates.
ProphylaxisRetrospective · 211 patients · multinational
Exercise for COVID-19
Lower severe cases with higher activity levels
Not statistically significant · p = 0.3
Retrospective 263 COVID+ patients, showing lower hospitalization with higher self-reported cardiorespiratory fitness, but no significant differences for physical activity. Participants in the study were healthier and more fit than the general population. Submit Corrections or Updates.
Retrospective 246 COVID-19 patients in the USA, showing the risk of hospitalization inversely associated with maximal exercise capacity. Adjusted results are only provided for MET as a continuous variable. Submit Corrections or Updates.
Case control study with 307 severe COVID-19 ICU patients and 307 matched COVID-19 outpatients in Brazil, showing significantly higher risk of severe cases with low physical activity. Submit Corrections or Updates.
Retrospective 6,288 COVID+ patients and 125,772 matched controls in South Korea, showing significantly lower risk of COVID-19 infection and mortality with higher physical activity. Submit Corrections or Updates.
Prospective study of 2,690 adults in the UK Biobank showing lower cardiorespiritory fitness associated with COVID-19 mortality. Submit Corrections or Updates.
ProphylaxisRetrospective · 938 patients · Brazil · Jun – Aug 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
unadjusted
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Lower hospitalization with higher activity levels
p = 0.046
Retrospective survey of 938 COVID-19 recovered patients in Brazil, showing lower hospitalization with physical activity. NCT04396353. Submit Corrections or Updates.
Retrospective 857 severe COVID-19 cases and matched controls in Sweden, showing lower risk of severe COVID-19 with higher cardiorespiratory fitness. Submit Corrections or Updates.
Retrospective 439 severe COVID-19 hospitalized patients with hypertension, 201 receiving a supervised exercise program, showing significantly lower mortality with exercise. Exercise included of aerobic, breathing, and musculoskeletal exercises, 3 to 4 times per week. There were significantly more control patients on beta-adrenergic blockers and thiazide diuretics.

There are many possible mechanisms of action, including improved circulation, stress reduction, hormone regulation, improved sleep, increased antioxidant levels, and increased nitric oxide levels in the respiratory system. Over-exercising may be detrimental and lead to impaired immune function. Submit Corrections or Updates.
Analysis of 237 COVID-19 patients in Brazil, showing lower risk of long COVID with physical activity. Submit Corrections or Updates.
Retrospective 3,038 bariatric surgery patients in Israel, showing higher risk of SARS-CoV-2 infection with vitamin D deficiency, and lower risk with physical activity. Submit Corrections or Updates.
Case control study in China with 105 cases and 210 matched controls, showing COVID-19 cases associated with physical activity ≥5 times per week. Authors note that people may choose gyms for exercise in winter, leading to higher exposure risk. Submit Corrections or Updates.
Retrospective survey of 1,997 college students in the USA, showing no significant difference in COVID-19 cases with exercise in unadjusted results. Submit Corrections or Updates.
Retrospective 113,075 people in Israel, showing lower risk of COVID-19 cases with physical activity and a dose dependent response. Submit Corrections or Updates.
Retrospective 4,694 COVID-19 patients in Iran, showing lower risk of hospitalization and mortality with regular sports participation. Submit Corrections or Updates.
Retrospective 300 participants in Palestine, showing lower risk of hospitalization with physical activity, without statistical significance. Submit Corrections or Updates.
UK Biobank retrospective analysis of 387,109 people, showing lower risk of COVID-19 hospitalization with physical activity. Submit Corrections or Updates.
Prospective UK Biobank analysis, showing a history of low physical activity associated with COVID-19 mortality. Submit Corrections or Updates.
ProphylaxisRetrospective · 73 patients · Egypt · May 2021 – Feb 2022
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Fewer moderate/severe cases with higher activity levels
p = 0.0096
Retrospective 68 COVID-19 patients showing physical activity and healthier nutrition associated with lower COVID-19 severity. Submit Corrections or Updates.
Analysis of 200 mild and moderate COVID-19 outpatients showing an association between higher ESSAP scores (measuring exercise, sugar and prebiotic consumption, sleep, and antibiotic use) and milder COVID-19 disease. Authors find increased risk with daily yogurt containing probiotics. Probiotic intake based on yogurt only may be inaccurate. Authors hypothesize that commercial yogurt products may not contain sufficient beneficial bacteria or may be contaminated. Other research shows that probiotic food labels are often misleading—of 26 probiotic foods tested, only 5 contained Bifidobacterium in sufficient concentration for exhibiting a therapeutic effect50. For sleep, authors compare <8 hours and ≥8 hours, while sleep for less than or longer than a recommended range may indicate increased risk. Submit Corrections or Updates.
UK Biobank retrospective 235,928 participants using walking pace as a proxy for physical fitness, showing lower risk of COVID-19 hospitalization with an average vs. slow walking pace. Submit Corrections or Updates.
Prospective survey-based study with 15,227 people in the UK, showing reduced risk of COVID-19 cases with lower impact physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 164 patients · China · Feb – Mar 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
unadjusted
unadjusted
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Fewer cases with higher activity levels
p = 0.0035
Retrospective 164 COVID-19 patients and 188 controls in China, showing lower risk of cases with regular exercise. Submit Corrections or Updates.
Retrospective 568 convalescent COVID-19 patients in Poland, showing lower risk of severe cases with regular physical activity in the 3 months before COVID-19. Submit Corrections or Updates.
Retrospective 66 hospitalized COVID-19 patients in Greece, showing significantly improved recovery with a history of exercise in unadjusted results. Exercise after hospitalization was also associated with lower levels of dyspnea one month post hospitalization. Submit Corrections or Updates.
Retrospective 420 people in Spain, showing lower risk of COVID-19 hospitalization with a history of physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 52,365 patients · South Korea · Jan – Jul 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and severe cases
p = 0.046 (mortality) and p = 0.03 (severe cases)
Retrospective 212,768 adults in South Korea, showing lower risk of COVID-19 cases, severity, and mortality with physical activity. Notably, results for aerobic and muscle strengthening activities combined were much better than results for either one in isolation. Submit Corrections or Updates.
Analysis of 241 adults >65yo in Belgium, showing lower risk of COVID-19 with a history of physical activity. Submit Corrections or Updates.
Mendelian randomization study showing lower risk of severe COVID-19 with physical activity. Submit Corrections or Updates.
Prospective survey analysis of 28,575 people in 99 countries, showing a lower risk of COVID-19 with a exercise, without statistical significance. Submit Corrections or Updates.
Retrospective 5,712 COVID-19 patients in the USA, showing higher risk of COVID-19 hospitalization with a history of physical inactivity. Submit Corrections or Updates.
ProphylaxisRetrospective · 224 patients · Luxembourg · May 2020 – Jun 2021
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower progression with higher activity levels
p = 0.045
Retrospective 452 participants in Luxembourg, showing lower risk of moderate cases with higher physical activity. Submit Corrections or Updates.
Retrospective 3,139 adults >50 in Europe, with 66 COVID-19 hospitalizations, showing lower risk of hospitalization with higher physical activity and with higher muscle strength. Note that model 2 includes muscle strength which is correlated with physical activity51. Submit Corrections or Updates.
Prospective survey based study with 14,335 participants, showing lower risk of viral symptoms with regular exercise. Submit Corrections or Updates.
Retrospective 1,500 COVID+ patients in Bangladesh, showing lower risk of severe cases with regular exercise in unadjusted results. Submit Corrections or Updates.
ProphylaxisProspective · 61,557 patients · USA
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Lower hospitalization and fewer cases
p = 0.0024 (hospitalization) and p = 0.0043 (fewer cases)
Prospective study of 61,557 adults aged 45+ years showing reduced risk of COVID-19 diagnosis and hospitalization for those meeting physical activity guidelines of ≥7.5 MET-hours/week before the pandemic compared to inactive individuals. Submit Corrections or Updates.
Analysis of 3,947 participants in Vietnam, showing significantly lower risk of COVID-19-like symptoms with physical activity and with a healthy diet. The combination of being physically active and eating healthy reduced risk further compared to either alone. The analyzed period was Feb 14 to Mar 2, 2020, which may have been before testing was widely available. Submit Corrections or Updates.
ProphylaxisRetrospective · South Korea · Jan – Aug 2020
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Fewer cases with higher activity levels
p = 0.016
Retrospective 4,363 COVID-19 patients and 67,125 controls in South Korea, showing higher risk of mortality and cases with insufficient physical activity. Submit Corrections or Updates.
Retrospective 1,811 COVID-19 patients in the UK, showing lower risk of self-reported long COVID with 3+ hours of exercise per week in the month before infection, without statistical significance (p=0.16). Submit Corrections or Updates.
Retrospective 5,197 Greek adults over 65. After adjustment for confounders, COVID-19 infection was independently associated with poor sleep, low physical activity, low Mediterranean diet adherence, living in urban areas, smoking, obesity, depression, anxiety, stress, and poor health-related quality of life. Submit Corrections or Updates.
ProphylaxisRetrospective · 4,476 patients · Brazil
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Fewer cases with higher activity levels
Not statistically significant · p = 0.052
Retrospective 4,476 participants in Brazil, showing lower risk of COVID-19 cases with a history of physical activity, statistically significant only for those following specific practices to protect against COVID-19. Submit Corrections or Updates.
ProphylaxisRetrospective · 1,847 patients · Poland · May 2020 – Jan 2022
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Fewer moderate/severe cases and lower long COVID
Not statistically significant · p = 0.3 (Fewer moderate/severe cases) and p = 0.24 (long COVID)
Retrospective 1,847 COVID+ patients in Poland, showing no significant difference in moderate/severe cases with physical activity. Hospitalized patients were excluded. Submit Corrections or Updates.
Retrospective 546 COVID+ patients in the USA, showing lower risk of hospitalization with higher frequency of strength training, without statistical significance. Submit Corrections or Updates.
ProphylaxisRetrospective · 2,919 patients · Brazil · Dec 2020 – Mar 2021
Exercise for COVID-19
Lower long COVID with higher activity levels
p = 0.05
Retrospective 2,919 non-hospitalized COVID-19 patients in Brazil showing remaining physically active before and after COVID-19 infection reduces the probability of experiencing long COVID symptoms, particularly those affecting the musculoskeletal, neurological and respiratory systems. Submit Corrections or Updates.
Retrospective 904 patients in Sweden, showing higher risk of COVID-19-like symptoms with poor muscle strength. Risk was slightly higher for physical inactivity, without statistical significance. Submit Corrections or Updates.
Retrospective 520 COVID-19 patients in Spain, showing significantly lower mortality with a history of physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 10,102 patients · USA
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and ICU admission
p = 0.0047 (mortality) and p = 0.0056 (ICU admission)
Retrospective 48,440 COVID-19 patients in the USA, showing significantly lower mortality, ICU admission, and hospitalization with exercise. Submit Corrections or Updates.
Retrospective 29,875 university staff and students in Spain, 3,662 with data, showing lower risk of COVID-19 symptoms for people that exercise. Exercise more than 5 days/week was the most protective, and intense exercise was more effective than moderate exercise. Submit Corrections or Updates.
ProphylaxisRetrospective · 5,338 patients · Germany
Exercise for COVID-19
Fewer cases with higher activity levels
p = 0.02
Retrospective 5,338 individuals with confirmed contact with a COVID-19 patient, showing lower risk of COVID-19 with exercise. Submit Corrections or Updates.
ProphylaxisRetrospective · 42,835 patients · Mar 2020 – Jun 2021
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and ventilation
p < 0.0001 (mortality) and p < 0.0001 (ventilation)
Retrospective 65,361 COVID-19 patients in South Africa, showing significantly lower hospitalization, ICU admission, ventilation, and mortality with exercise. Submit Corrections or Updates.
ProphylaxisProspective · 131 patients · Poland · Jan – Feb 2022
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
00.511.52+
← Exercise
reduces risk
Exercise
increases risk →
Lower mortality and improved recovery
Not statistically significant · p = 0.21 (mortality) and p = 0.19 (recovery)
Prospective study of 131 hospitalized patients in Poland, showing lower mortality and improved recovery with a history of higher physical activity. Submit Corrections or Updates.
Retrospective 206 patients in Iran, showing COVID-19 disease severity associated with lower physical activity. Submit Corrections or Updates.
Retrospective 293 COVID+ patients in Russia, showing lower risk of severe COVID-19 for individuals who regularly practice aerobic training in unadjusted results. Submit Corrections or Updates.
Retrospective 4,868 elderly COVID-19 patients in Japan, showing higher risk of severe cases with poor physical activity status. Submit Corrections or Updates.
ProphylaxisProspective · 68,896 patients · UK
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower mortality and hospitalization
p < 0.0001 (mortality) and p < 0.0001 (hospitalization)
Prospective study of 68,896 UK Biobank participants with COVID-19 showing adherence to a healthy lifestyle prior to infection, characterized by 10 factors including adequate physical activity and sleep, not smoking, and a healthy BMI, was associated with a significantly lower risk of mortality, hospitalization, and post-COVID multisystem sequelae. Risk decreased monotonically for increasing numbers of healthy lifestyle factors from 5-10. Reduced risks were evident across cardiovascular, metabolic, neurologic, respiratory, and other disorders over 210 days following infection, during both acute and post-acute phases, regardless of age, sex, ethnicity, test setting, vaccination status, or SARS-CoV-2 variant. Submit Corrections or Updates.
ProphylaxisProspective · 1,285 patients · USA · Apr 2020 – Nov 2021
Exercise for COVID-19
Lower long COVID with higher activity levels
Not statistically significant · p = 0.2
Prospective analysis of 32,249 women, showing lower risk of PASC with a healthy lifestyle, in a dose-dependent manner. Participants with 5 or 6 healthy lifestyle factors had significantly lower COVID-19 hospitalization and PASC. BMI and sleep were independently associated with risk of PASC. Submit Corrections or Updates.
UK Biobank retrospective 412,596 people, showing severe COVID-19 and COVID-19 mortality inversely associated with self-reported walking pace. Submit Corrections or Updates.
ProphylaxisRetrospective · 94,731 patients · USA · Jan 2020 – May 2021
Exercise for COVID-19
Retrospective 194,191 COVID-19 patients in the USA, showing lower risk of hospitalization and mortality with physical activity, with a dose response relationship. Submit Corrections or Updates.
Retrospective 164 COVID-19 patients in China, showing physical inactivity associated with an increased risk of severe COVID-19. Submit Corrections or Updates.
UK Biobank retrospective showing significantly lower COVID-19 cases with objectively measured physical activity. Submit Corrections or Updates.
ProphylaxisRetrospective · 100 patients · Bosnia and Herzegovina
Exercise for COVID-19
Outcome
Improvement
Relative Risk · 95% CI
Lower need for oxygen therapy and lower hospitalization
p = 0.045 (need for oxygen) and p = 0.02 (hospitalization)
Retrospective 100 COVID-19 patients in Bosnia and Herzegovina, showing lower symptom severity and faster recovery with a history of regular physical activity. Submit Corrections or Updates.
We perform ongoing searches of PubMed, medRxiv, Europe PMC, ClinicalTrials.gov, The Cochrane Library, Google Scholar, Research Square, ScienceDirect, Oxford University Press, the reference lists of other studies and meta-analyses, and submissions to the site c19early.org, which regularly receives notification of studies upon publication. Search terms are (exercise OR "physical activity") AND COVID-19. Automated searches are performed twice daily, with all matches reviewed for inclusion. All studies regarding the use of exercise for COVID-19 that report a comparison with a control group are included in the main analysis. Sensitivity analysis is performed, excluding studies with major issues, epidemiological studies, and studies with minimal available information. Studies with major unexplained data issues, for example major outcome data that is impossible to be correct with no response from the authors, are excluded.
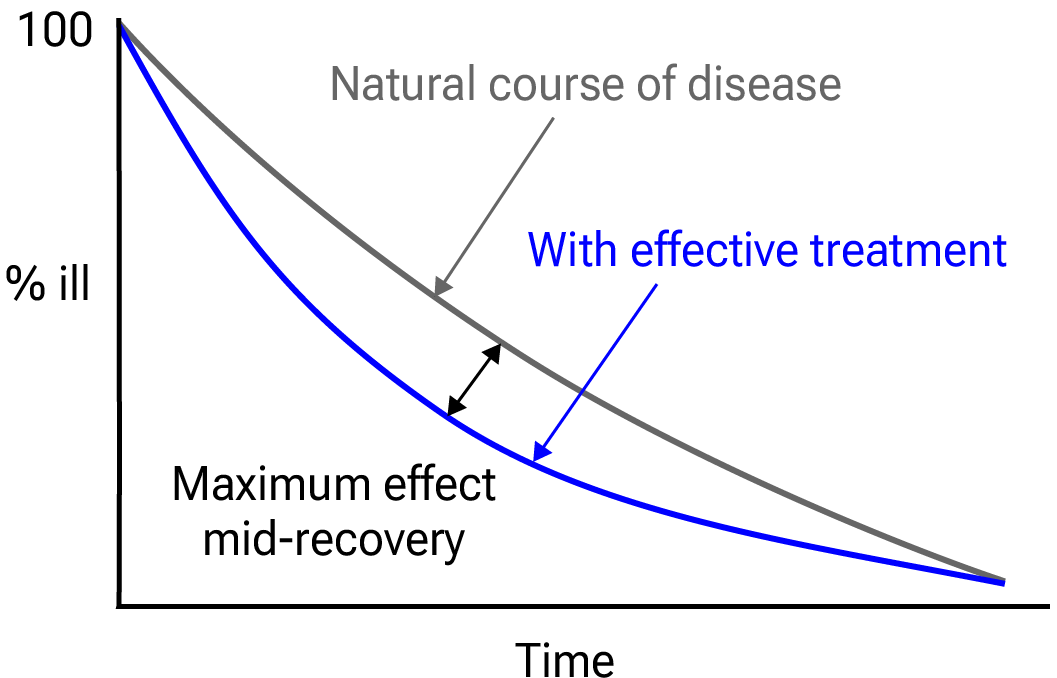
Fig. 23. Mid-recovery results can more accurately reflect efficacy when almost all patients recover. Mateja et al. confirm that intermediate viral load results more accurately reflect hospitalization/death.
We extracted effect sizes and associated data from all studies. If studies report multiple kinds of effects then the most serious outcome is used in pooled analysis, while other outcomes are included in the outcome-specific analyses. For example, if effects for mortality and cases are reported then they are both used in specific outcome analyses, while mortality is used for pooled analysis. If symptomatic results are reported at multiple times, we use the latest time, for example if mortality results are provided at 14 days and 28 days, the results at 28 days have preference. Mortality alone is preferred over combined outcomes. Outcomes with zero events in both arms are not used, the next most serious outcome with one or more events is used. For example, in low-risk populations with no mortality, a reduction in mortality with treatment is not possible, however a reduction in hospitalization, for example, is still valuable. Clinical outcomes are considered more important than viral outcomes. When basically all patients recover in both treatment and control groups, preference for viral clearance and recovery is given to results mid-recovery where available. After most or all patients have recovered there is little or no room for an effective treatment to do better, however faster recovery is valuable. An IPD meta-analysis confirms that intermediate viral load reduction is more closely associated with hospitalization/death than later viral load reduction52. If only individual symptom data is available, the most serious symptom has priority, for example difficulty breathing or low SpO2 is more important than cough.
Forest plots are computed using PythonMeta53 with the DerSimonian and Laird random-effects model (the fixed effect assumption is not plausible in this case) and inverse variance weighting. Results are presented with 95% confidence intervals. Heterogeneity among studies was assessed using the I2 statistic. When results provide an odds ratio, we compute the relative risk when possible, or convert to a relative risk according to Zhang (B) et al. Reported confidence intervals and p-values are used when available, and adjusted values are used when provided. If multiple types of adjustments are reported propensity score matching and multivariable regression has preference over propensity score matching or weighting, which has preference over multivariable regression. Adjusted results have preference over unadjusted results for a more serious outcome when the adjustments significantly alter results. When needed, conversion between reported p-values and confidence intervals followed Altman, Altman (B), and Fisher's exact test was used to calculate p-values for event data. If continuity correction for zero values is required, we use the reciprocal of the opposite arm with the sum of the correction factors equal to 157. Results are expressed with RR < 1.0 favoring treatment, and using the risk of a negative outcome when applicable (for example, the risk of death rather than the risk of survival). If studies only report relative continuous values such as relative times, the ratio of the time for the treatment group versus the time for the control group is used. Calculations are done in Python (3.14.8) with scipy (1.18.1), pythonmeta (1.26), numpy (2.5.4), statsmodels (0.15.0), and plotly (6.9.0). Mixed-effects meta-regression results are computed with R (4.4.0) using the metafor (4.6-0) and rms (6.8-0) packages, and using the most serious sufficiently powered outcome. For all statistical tests, a p-value less than 0.05 was considered statistically significant. Grobid 0.8.2 is used to parse PDF documents.
For treatments that may improve immune system function but are not expected to have a direct antiviral effect, we may expect a gradient of efficacy across outcomes, with minimal impact on preventing initial infection (PCR+ cases), but increasing efficacy against more severe outcomes. To evaluate this hypothesis we performed meta-regression with robust variance estimation. Clinical outcomes were categorized into an ordinal severity scale with cases at severity 1, hospitalization at severity 2, and critical outcomes at severity 3 (ICU admission, ventilation, and mortality). The dependent variable was the natural logarithm of the Risk Ratio (ln(RR)) for each outcome, and the independent variable was the ordinal severity score. We used the DerSimonian and Laird (DL) method-of-moments estimator to estimate residual heterogeneity (τ2) around the meta-regression line, with weights assigned using the inverse-variance method (wi = 1 / (vi + τ2)). To account for the non-independence of multiple outcomes reported within the same study (e.g., mortality and hospitalization data derived from the same patient population), we used cluster-robust standard errors clustered by study ID. The meta-regression slope (β) represents the change in ln(RR) per unit increase in severity. A negative slope indicates improving efficacy (lower Risk Ratio) for more severe outcomes.
When evaluating potential effect modification across groups, we use an interaction test as described by Altman (C) et al. We compared the log-transformed relative risks using a z-test, deriving the standard error of the difference from the 95% confidence intervals. A two-sided interaction p-value of < 0.05 was considered a statistically significant difference in treatment effect between the groups.
Cochrane RoB 2/ROBINS-I are often used to evaluate studies, and have the advantage of providing standardized rules that can be applied with minimal understanding of the domain and study. However, the rules do not account for many real-world issues, often overemphasize or underemphasize others, and studies show low inter-rater reliability65. Certain domains are more applicable for these tools, however the time-sensitive nature of a pandemic, with significant mortality for every day of delay in evidence assessment, and the characteristics of COVID-19 make them inappropriate for this domain. This can be demonstrated with examples where expert RoB 2/ROBINS-I ratings do not match reality for COVID-19. Popp et al. use RoB 2 to classify Reis et al. as low risk of bias, however this is the opposite of reality—the trial not only has very high risk of bias, but has very high actual known bias, refusing to release data despite pledging to, reporting multiple impossible numbers, having blinding and randomization failure, and many other issues67. Axfors et al. use RoB 2 to classify Horby et al. as low risk of bias, however this is the opposite of reality—the very late treatment and excessive dosage used produces results with no relevance to recommended usage. HCQ shows poor results with late treatment and excessive dosage, and the combination shows harmC. Hempenius et al. use ROBINS-I to classify 33 studies for HCQ. The two rated as having the lowest risk of bias63,64 are far from the most informative. Both involve very late treatment, providing no information on recommended usage, and ROBINS-I does a very poor job of accounting for the impact of confounding factorsD.
Our quality evaluation focuses on known issues and bias, and the potential impact on outcomes, rather than just the risk of bias. The estimated potential impact of each confounding factor, and the direction of the impact is considered. For example, consider a study that shows significantly lower risk, the value of the study varies significantly if confounding points to an underestimate or an overestimate of efficacy. In one case, the real effect may be null, while the other case provides stronger evidence of efficacy (which may be greater than the study shows). Analysis focusing on the risk of bias, while simpler, may penalize studies for theoretical or technical issues that have no or minimal impact on outcomes. Analysis also depends on the outcome, for example certain issues are less relevant for objective outcomes such as mortality. Inaccurate penalization, and inaccurate high-quality evaluation in the face of known major issues affecting outcomes, increases in significance during a pandemic when immediate recognition of new evidence is critical, and when considering all global studies, as required during a pandemic. Investigators in other countries may have different customs for design, analysis, and reporting, and different English language skills, however they may not be less diligent or have greater bias. Investigators in lower-pharmaceutical-profit countries may have lower bias towards profitable interventions.
We have classified studies as early treatment if most patients are not already at a severe stage at the time of treatment (for example based on oxygen status or lung involvement), and treatment started within 5 days of the onset of symptoms. If studies contain a mix of early treatment and late treatment patients, we consider the treatment time of patients contributing most to the events (for example, consider a study where most patients are treated early but late treatment patients are included, and all mortality events were observed with late treatment patients). We note that a shorter time may be preferable. Antivirals are typically only considered effective when used within a shorter timeframe, for example 0-36 or 0-48 hours for oseltamivir, with longer delays not being effective71,72.
This is a living analysis and is updated regularly. Submit updates or corrections with the form below. We received no funding, this research is done in our spare time. We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
A summary of study results is below. Please submit updates and corrections at the bottom of this page.
A summary of study results is below. Please submit updates and corrections at https://c19early.org/exmeta.html.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
Fernandez, 2/2/2023, retrospective, Chile, peer-reviewed, 10 authors. risk of death, 47.5% lower, RR 0.53, p = 0.02, high activity levels 16 of 201 (8.0%), low activity levels 62 of 238 (26.1%), NNT 5.5, adjusted per study, odds ratio converted to relative risk, multivariable.
Effect extraction follows pre-specified rules as detailed above and gives priority to more serious outcomes. For pooled analyses, the first (most serious) outcome is used, which may differ from the effect a paper focuses on. Other outcomes are used in outcome specific analyses.
af Geijerstam, 7/5/2021, prospective, Sweden, peer-reviewed, 9 authors, study period March 2020 - September 2020. risk of death, 50.0% lower, OR 0.50, p = 0.005, high vs. low fitness, model 7, RR approximated with OR.
risk of ICU admission, 40.0% lower, OR 0.60, p < 0.001, high vs. low fitness, model 7, RR approximated with OR.
risk of hospitalization, 27.0% lower, OR 0.73, p < 0.001, high vs. low fitness, model 7, RR approximated with OR.
Ahmadi, 8/31/2021, retrospective, United Kingdom, peer-reviewed, 5 authors. risk of death, 30.0% lower, RR 0.70, p = 0.005, adjusted per study, sufficient vs. inactive, model 2, multivariable.
Akbar, 11/7/2023, retrospective, Qatar, peer-reviewed, mean age 40.3, 9 authors, study period March 2020 - September 2020. risk of case, 7.0% lower, OR 0.93, p = 0.40, high activity levels 3,333, low activity levels 3,333, adjusted per study, T3 vs. T1, multivariable, model 2, RR approximated with OR.
Almansour, 2/17/2022, retrospective, Saudi Arabia, peer-reviewed, 12 authors, study period April 2020 - June 2020. risk of case, 5.7% lower, RR 0.94, p = 0.85, high activity levels 35 of 71 (49.3%), low activity levels 38 of 71 (53.5%), NNT 24, adjusted per study, odds ratio converted to relative risk, multivariable.
Antunes, 6/11/2022, retrospective, Brazil, peer-reviewed, survey, 5 authors, study period September 2020 - December 2020. risk of ICU admission, 80.2% lower, RR 0.20, p = 0.06, high activity levels 1 of 14 (7.1%), low activity levels 9 of 25 (36.0%), NNT 3.5.
risk of miscellaneous, 40.5% lower, RR 0.60, p = 0.48, high activity levels 3 of 14 (21.4%), low activity levels 9 of 25 (36.0%), NNT 6.9, CT abnormalities >50%.
risk of miscellaneous, 72.5% lower, RR 0.27, p = 0.04, high activity levels 2 of 14 (14.3%), low activity levels 13 of 25 (52.0%), NNT 2.7, CT abnormalities 25-50%.
hospitalization time, 43.4% lower, relative time 0.57, p = 0.03, high activity levels 14, low activity levels 25.
miscellaneous, 25.5% lower, relative time 0.74, p = 0.02, high activity levels 14, low activity levels 25.
Baynouna AlKetbi, 8/23/2021, retrospective, United Arab Emirates, peer-reviewed, 16 authors. risk of death, 98.5% lower, OR 0.01, p = 0.02, adjusted per study, multivariable, RR approximated with OR.
Beydoun, 3/12/2022, retrospective, USA, peer-reviewed, survey, 7 authors. risk of case, 43.0% lower, OR 0.57, p = 0.05, high activity levels 1,710, low activity levels 448, adjusted per study, multivariable, >1/week vs. none, model 2, RR approximated with OR.
risk of case, 62.0% lower, OR 0.38, p = 0.010, high activity levels 672, low activity levels 448, adjusted per study, multivariable, 1-4/mon vs. none, model 2, RR approximated with OR.
Bielik, 7/4/2021, retrospective, Slovakia, peer-reviewed, survey, 3 authors, study period 7 December, 2020 - 12 December, 2020. risk of moderate case, 30.4% lower, RR 0.70, p = 0.10, high activity levels 775, low activity levels 365, adjusted per study, physically active group.
risk of case, 9.1% higher, RR 1.09, p = 0.36, high activity levels 775, low activity levels 365, adjusted per study, physically active group.
Brandenburg, 7/1/2021, retrospective, multiple countries, peer-reviewed, survey, 4 authors. risk of hospitalization, 6.0% higher, OR 1.06, p = 0.60, high activity levels 102, low activity levels 39, adjusted per study, multivariable, PA, >1h vigorous vs. no/low, RR approximated with OR.
risk of hospitalization, 78.0% lower, OR 0.22, p = 0.05, high activity levels 177, low activity levels 34, adjusted per study, multivariable, CRF, 6.2-8.7 vs. >10, RR approximated with OR.
risk of hospitalization, 64.0% lower, OR 0.36, p = 0.04, high activity levels 97, low activity levels 34, adjusted per study, multivariable, CRF, 8.7-10 vs. >10, RR approximated with OR.
risk of severe case, 35.0% lower, OR 0.65, p = 0.30, high activity levels 102, low activity levels 39, adjusted per study, multivariable, PA, >1h vigorous vs. no/low, RR approximated with OR.
risk of severe case, 24.0% lower, OR 0.76, p = 0.60, high activity levels 52, low activity levels 34, adjusted per study, multivariable, CRF, 4.4-6.2 vs. >10, RR approximated with OR.
Brawner, 10/10/2020, retrospective, USA, peer-reviewed, 10 authors, study period 29 February, 2020 - 30 May, 2020, excluded in exclusion analyses: unadjusted results with no group details. risk of hospitalization, 74.2% lower, OR 0.26, p = 0.001, unadjusted, inverted to make OR<1 favor high activity levels, highest fitness quartile vs. lowest fitness quartile, RR approximated with OR.
Cardoso, 5/9/2023, retrospective, Brazil, peer-reviewed, 6 authors, study period April 2020 - February 2022. risk of severe case, 73.0% lower, OR 0.27, p < 0.001, high activity levels 307, low activity levels 307, adjusted per study, inverted to make OR<1 favor high activity levels, case control OR, moderate/high vs. low physical activity, multivariable.
Cho, 4/6/2021, retrospective, South Korea, peer-reviewed, 9 authors. risk of death, 53.0% lower, OR 0.47, p = 0.01, high activity levels 17 of 48 (35.4%) cases, 3,223 of 4,536 (71.1%) controls, case control OR, moderate to vigorous vs. inactive.
risk of case, 10.0% lower, OR 0.90, p < 0.001, high activity levels 3,223 of 4,536 (71.1%) cases, 68,609 of 92,587 (74.1%) controls, NNT 142, case control OR, moderate to vigorous vs. inactive.
Christensen, 5/5/2021, prospective, United Kingdom, peer-reviewed, 5 authors, study period 16 March, 2020 - 26 July, 2020. risk of death, 63.0% lower, RR 0.37, p = 0.02, high activity levels 543, low activity levels 529, adjusted per study, high fitness vs. low fitness, multivariable.
risk of case, 23.0% lower, RR 0.77, p = 0.20, high activity levels 55 of 543 (10.1%), low activity levels 77 of 529 (14.6%), NNT 23, adjusted per study, high fitness vs. low fitness, multivariable.
de Souza, 9/30/2021, retrospective, Brazil, peer-reviewed, 8 authors, study period June 2020 - August 2020, trial NCT04396353 (history). risk of mechanical ventilation, 73.2% lower, RR 0.27, p = 0.07, high activity levels 3 of 611 (0.5%), low activity levels 6 of 327 (1.8%), NNT 74, unadjusted, excluded in exclusion analyses: unadjusted results with no group details.
risk of hospitalization, 34.3% lower, RR 0.66, p = 0.046, high activity levels 49 of 611 (8.0%), low activity levels 42 of 327 (12.8%), NNT 21, adjusted per study, sufficient vs. insufficient, model 3, multivariable.
Ekblom-Bak, 10/19/2021, retrospective, Sweden, peer-reviewed, 13 authors. risk of severe case, 47.6% lower, OR 0.52, p = 0.02, inverted to make OR<1 favor high activity levels, case control OR, model 3, high vs. very low CRF.
Feter, 6/13/2023, retrospective, Brazil, peer-reviewed, survey, mean age 37.1, 17 authors. risk of long COVID, 26.0% lower, RR 0.74, p = 0.02, high activity levels 52, low activity levels 95, adjusted per study, before and during pandemic, multivariable.
risk of long COVID, 17.0% lower, RR 0.83, p = 0.04, high activity levels 67, low activity levels 170, adjusted per study, during pandemic, multivariable.
Frish, 6/15/2023, retrospective, Israel, peer-reviewed, 7 authors, study period 1 February, 2020 - 31 December, 2020. risk of case, 53.0% lower, OR 0.47, p = 0.04, high activity levels 212, low activity levels 1,202, adjusted per study, >3 times per week vs. none, multivariable, RR approximated with OR.
Gao, 11/5/2020, retrospective, China, peer-reviewed, survey, median age 55.0, 11 authors, study period 10 February, 2020 - 1 March, 2020. risk of case, 105.0% higher, HR 2.05, p < 0.001, high activity levels 59 of 105 (56.2%) cases, 69 of 210 (32.9%) controls, case control OR, Cox proportional hazards.
Gilley, 2/10/2022, retrospective, USA, peer-reviewed, survey, 21 authors, study period September 2020 - December 2020, trial NCT04766788 (history). risk of case, 41.8% higher, RR 1.42, p = 0.55, high activity levels 172 of 1,917 (9.0%), low activity levels 5 of 79 (6.3%), unadjusted.
Green, 11/7/2022, retrospective, Israel, peer-reviewed, 9 authors, study period 1 February, 2020 - 31 December, 2020. risk of case, 41.7% lower, RR 0.58, p < 0.001, high activity levels 1,267 of 11,144 (11.4%), low activity levels 16,198 of 101,931 (15.9%), adjusted per study, odds ratio converted to relative risk, >3 times per week vs. none, multivariable.
Halabchi (B), 12/1/2020, retrospective, Iran, peer-reviewed, 8 authors. risk of death, 88.8% lower, RR 0.11, p = 0.08, high activity levels 0 of 249 (0.0%), low activity levels 79 of 4,445 (1.8%), NNT 56, adjusted per study, odds ratio converted to relative risk, multivariable.
risk of hospitalization, 28.3% lower, RR 0.72, p = 0.04, high activity levels 30 of 249 (12.0%), low activity levels 878 of 4,445 (19.8%), adjusted per study, odds ratio converted to relative risk, multivariable.
Hamdan, 12/23/2021, retrospective, Palestine, peer-reviewed, survey, mean age 30.5, 7 authors. risk of hospitalization, 16.4% lower, RR 0.84, p = 0.53, high activity levels 22 of 128 (17.2%), low activity levels 37 of 172 (21.5%), NNT 23, adjusted per study, odds ratio converted to relative risk, multivariable.
Hamer, 7/31/2020, retrospective, United Kingdom, peer-reviewed, 4 authors. risk of hospitalization, 27.5% lower, RR 0.72, p < 0.001, adjusted per study, inverted to make RR<1 favor high activity levels, model 2, sufficient vs. no activity, multivariable.
risk of hospitalization, 33.8% lower, RR 0.66, p < 0.001, adjusted per study, inverted to make RR<1 favor high activity levels, model 1, sufficient vs. no activity, multivariable.
Hamrouni, 11/3/2021, prospective, United Kingdom, peer-reviewed, 5 authors. risk of death, 29.0% lower, RR 0.71, p = 0.009, high activity levels 138 of 106,006 (0.1%), low activity levels 109 of 47,827 (0.2%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, high vs. low physical activity, multivariable.
Hegazy, 10/2/2023, retrospective, Egypt, peer-reviewed, 7 authors, study period May 2021 - February 2022, trial NCT04447144 (history), excluded in exclusion analyses: unadjusted results with no group details. risk of moderate case, 54.0% lower, RR 0.46, p = 0.010, high activity levels 15 of 50 (30.0%), low activity levels 15 of 23 (65.2%), NNT 2.8, active vs. inactive.
risk of moderate case, 97.1% lower, RR 0.03, p = 0.02, high activity levels 0 of 7 (0.0%), low activity levels 30 of 61 (49.2%), NNT 2.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), moderate vs. low/inactive.
Hegazy (B), 6/7/2021, retrospective, Egypt, peer-reviewed, 10 authors, trial NCT04447144 (history). risk of moderate/severe case, 45.6% lower, RR 0.54, p = 0.11, high activity levels 24 of 82 (29.3%), low activity levels 7 of 13 (53.8%), NNT 4.1, >10min/day vs. none.
Ho, 11/19/2020, retrospective, United Kingdom, peer-reviewed, survey, 13 authors. risk of hospitalization, 34.6% lower, RR 0.65, p = 0.007, high activity levels 213 of 123,588 (0.2%), low activity levels 59 of 14,887 (0.4%), adjusted per study, inverted to make RR<1 favor high activity levels, model 2, average vs. slow walking pace, multivariable.
Holt, 3/30/2021, prospective, United Kingdom, peer-reviewed, 34 authors, study period 1 May, 2020 - 5 February, 2021, trial NCT04330599 (history) (COVIDENCE UK). risk of case, 17.0% lower, OR 0.83, p = 0.18, adjusted per study, fully adjusted, ≥2 hours lower impact physical activity vs. 0 hours, RR approximated with OR.
Huang, 11/30/2021, retrospective, China, peer-reviewed, survey, 5 authors, study period 10 February, 2020 - 28 March, 2020. risk of severe case, 46.8% lower, RR 0.53, p = 0.18, high activity levels 7 of 74 (9.5%), low activity levels 16 of 90 (17.8%), NNT 12, unadjusted, exercise habit, ≥1 time per week, excluded in exclusion analyses: unadjusted results with no group details.
risk of severe case, 8.0% lower, RR 0.92, p = 1.00, high activity levels 3 of 23 (13.0%), low activity levels 20 of 141 (14.2%), NNT 88, unadjusted, ≥30 minutes ≥3 times per week, excluded in exclusion analyses: unadjusted results with no group details.
risk of case, 65.9% lower, OR 0.34, p = 0.004, adjusted per study, inverted to make OR<1 favor high activity levels, case control OR, regular exercise, multivariable.
Kapusta, 12/12/2022, retrospective, Poland, peer-reviewed, survey, mean age 70.4, 7 authors, study period 1 March, 2020 - 30 August, 2020, trial NCT05018052 (history). risk of severe case, 70.9% lower, OR 0.29, p = 0.001, high activity levels 181, low activity levels 387, inverted to make OR<1 favor high activity levels, RR approximated with OR.
Kontopoulou, 4/17/2022, retrospective, Greece, peer-reviewed, survey, 4 authors, study period November 2020 - December 2020, excluded in exclusion analyses: unadjusted results with no group details. recovery time, 66.2% lower, relative time 0.34, p < 0.001, high activity levels mean 22.0 (±14.0) n=42, low activity levels mean 65.0 (±32.0) n=24.
relative dyspnea after hospitalization, 66.7% better, RR 0.33, p < 0.001, high activity levels mean 1.0 (±1.0) n=42, low activity levels mean 3.0 (±1.0) n=24, inverted to make RR<1 favor high activity levels.
Latorre-Román, 6/15/2021, retrospective, Spain, peer-reviewed, survey, 7 authors. risk of hospitalization, 76.0% lower, OR 0.24, p = 0.05, moderate physical activity, >150 min per week, RR approximated with OR.
risk of hospitalization, 87.0% lower, OR 0.13, p = 0.07, moderate physical activity, 30-150 min per week, RR approximated with OR.
Lee, 7/22/2021, retrospective, South Korea, peer-reviewed, 25 authors, study period 1 January, 2020 - 31 July, 2020. risk of death, 74.0% lower, RR 0.26, p = 0.046, high activity levels 2 of 11,072 (0.0%), low activity levels 32 of 41,293 (0.1%), NNT 1683, adjusted per study, odds ratio converted to relative risk, model 2,aerobic and muscle strengthening vs. insufficient aerobic and muscle strengthening, multivariable.
risk of severe case, 57.8% lower, RR 0.42, p = 0.03, high activity levels 39 of 11,072 (0.4%), low activity levels 273 of 41,293 (0.7%), adjusted per study, odds ratio converted to relative risk, model 2,aerobic and muscle strengthening vs. insufficient aerobic and muscle strengthening, multivariable.
risk of case, 15.6% lower, RR 0.84, p = 0.03, high activity levels 291 of 11,072 (2.6%), low activity levels 1,293 of 41,293 (3.1%), NNT 199, adjusted per study, odds ratio converted to relative risk, model 2,aerobic and muscle strengthening vs. insufficient aerobic and muscle strengthening, multivariable.
Lengelé, 10/23/2021, prospective, Belgium, peer-reviewed, median age 75.6, 8 authors, study period March 2020 - April 2021. risk of case, 73.6% lower, RR 0.26, p = 0.03, high activity levels 23 of 229 (10.0%), low activity levels 4 of 12 (33.3%), NNT 4.3, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk.
Li (B), 2/3/2021, retrospective, United Kingdom, peer-reviewed, 2 authors, per SD increase. risk of severe case, 81.0% lower, OR 0.19, p = 0.02, RR approximated with OR.
risk of hospitalization, 56.0% lower, OR 0.44, p = 0.07, RR approximated with OR.
Lin, 9/21/2021, prospective, multiple countries, peer-reviewed, survey, 19 authors, study period 26 March, 2020 - 8 October, 2020. risk of case, 47.4% lower, OR 0.53, p = 0.40, inverted to make OR<1 favor high activity levels, exercise ≥1/month vs. exercise <1/month, RR approximated with OR.
Lobelo, 5/19/2021, retrospective, Georgia, peer-reviewed, 7 authors, study period 3 March, 2020 - 29 October, 2020. risk of hospitalization, 20.0% lower, OR 0.80, p = 0.02, high activity levels 2,121, low activity levels 1,648, adjusted per study, inverted to make OR<1 favor high activity levels, active vs. inactive, multivariable, RR approximated with OR.
Malisoux, 4/29/2022, retrospective, Luxembourg, peer-reviewed, survey, median age 42.0, 6 authors, study period May 2020 - June 2021, trial NCT04380987 (history). risk of progression, 63.0% lower, OR 0.37, p = 0.045, high activity levels 115, low activity levels 108, moderate case, >82 vs. <30 MET-hour/week, RR approximated with OR.
risk of progression, 52.0% lower, OR 0.48, p = 0.14, high activity levels 116, low activity levels 108, moderate case, >52-82 vs. <30 MET-hour/week, RR approximated with OR.
risk of progression, 43.0% lower, OR 0.57, p = 0.28, high activity levels 113, low activity levels 108, moderate case, 30-52 vs. <30 MET-hour/week, RR approximated with OR.
Maltagliati, 8/11/2021, retrospective, multiple countries, peer-reviewed, survey, 8 authors. risk of hospitalization, 52.0% lower, OR 0.48, p = 0.02, adjusted per study, model 1, more than once a week vs. hardly ever or never, multivariable, RR approximated with OR.
Marcus, 6/17/2021, prospective, multiple countries, peer-reviewed, survey, 12 authors, study period 26 March, 2020 - 3 May, 2020. risk of symptomatic case, 42.1% lower, RR 0.58, p < 0.001, high activity levels 240 of 10,627 (2.3%), low activity levels 134 of 3,708 (3.6%), NNT 74, adjusted per study, odds ratio converted to relative risk, multivariable.
Mohsin, 9/30/2021, retrospective, Bangladesh, peer-reviewed, survey, 10 authors, study period November 2020 - April 2021, excluded in exclusion analyses: unadjusted results with no group details. risk of severe case, 19.0% lower, RR 0.81, p = 0.04, high activity levels 86 of 258 (33.3%), low activity levels 224 of 544 (41.2%), NNT 13, exercise >30 minutes.
risk of severe case, 0.9% higher, RR 1.01, p = 0.91, high activity levels 290 of 698 (41.5%), low activity levels 224 of 544 (41.2%), exercise <30 minutes.
Muñoz-Vergara, 2/13/2024, prospective, USA, peer-reviewed, 7 authors. risk of hospitalization, 26.7% lower, RR 0.73, p = 0.002, high activity levels 332 of 42,159 (0.8%), low activity levels 203 of 12,405 (1.6%), adjusted per study, odds ratio converted to relative risk, sufficiently active vs. inactive, multivariable, model 3.
risk of case, 9.1% lower, RR 0.91, p = 0.004, high activity levels 3,898 of 42,159 (9.2%), low activity levels 1,293 of 12,405 (10.4%), NNT 85, adjusted per study, odds ratio converted to relative risk, sufficiently active vs. inactive, multivariable, model 3.
Nguyen, 9/18/2021, retrospective, Vietnam, peer-reviewed, survey, 17 authors, study period 14 February, 2020 - 2 March, 2020. risk of symptomatic case, 20.3% lower, RR 0.80, p < 0.001, high activity levels 904 of 2,836 (31.9%), low activity levels 483 of 1,111 (43.5%), NNT 8.6, adjusted per study, odds ratio converted to relative risk, active vs. inactive, COVID-19-like symptoms, multivariable.
Park, 2/14/2023, retrospective, South Korea, peer-reviewed, survey, 4 authors, study period 1 January, 2020 - 14 August, 2020. risk of death, 25.6% lower, OR 0.74, p = 0.08, inverted to make OR<1 favor high activity levels, sufficient vs. insufficient PA, model 3, RR approximated with OR.
risk of death, 38.4% lower, OR 0.62, p = 0.02, inverted to make OR<1 favor high activity levels, sufficient vs. insufficient PA, model 2, RR approximated with OR.
risk of case, 7.2% lower, OR 0.93, p = 0.02, inverted to make OR<1 favor high activity levels, sufficient vs. insufficient PA, model 3, RR approximated with OR.
risk of case, 10.4% lower, OR 0.90, p < 0.001, inverted to make OR<1 favor high activity levels, sufficient vs. insufficient PA, model 2, RR approximated with OR.
Paul, 4/13/2022, retrospective, United Kingdom, preprint, survey, 2 authors. risk of long COVID, 38.1% lower, RR 0.62, p = 0.16, adjusted per study, odds ratio converted to relative risk, 3+ hours per week vs. none, multivariable, model 4, control prevalance approximated with overall prevalence.
risk of long COVID, 4.1% lower, RR 0.96, p = 0.89, adjusted per study, odds ratio converted to relative risk, ≤2 hours per week vs. none, multivariable, model 4, control prevalance approximated with overall prevalence.
Pavlidou, 11/9/2023, retrospective, Greece, peer-reviewed, 14 authors. risk of case, 42.2% lower, OR 0.58, p = 0.001, high activity levels 902, low activity levels 4,295, adjusted per study, inverted to make OR<1 favor high activity levels, high vs. low/moderate IPAQ, multivariable, RR approximated with OR.
Pitanga, 10/29/2022, retrospective, Brazil, peer-reviewed, survey, 11 authors. risk of case, 33.0% lower, OR 0.67, p = 0.05, high activity levels 1,469, low activity levels 1,552, combined results with and without protection practices, RR approximated with OR.
Pływaczewska-Jakubowska, 10/24/2022, retrospective, Poland, peer-reviewed, median age 51.0, 5 authors, study period May 2020 - January 2022. risk of moderate/severe case, 11.0% lower, OR 0.89, p = 0.30, high activity levels 490, low activity levels 1,357, adjusted per study, multivariable, model 3, RR approximated with OR.
risk of long COVID, 14.0% lower, OR 0.86, p = 0.24, high activity levels 389, low activity levels 1,128, adjusted per study, multivariable, model 3, RR approximated with OR.
Reis (B), 10/24/2022, retrospective, USA, peer-reviewed, survey, 6 authors, study period December 2020 - February 2021. risk of hospitalization, 40.7% lower, RR 0.59, p = 0.18, high activity levels 9 of 241 (3.7%), low activity levels 29 of 305 (9.5%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, strength training 2+/week vs. <2, multivariable.
Rocha, 12/14/2023, retrospective, Brazil, peer-reviewed, 6 authors, study period December 2020 - March 2021. risk of long COVID, 20.0% lower, OR 0.80, p = 0.05, high activity levels 388, low activity levels 2,096, RR approximated with OR.
risk of long COVID, 30.0% lower, OR 0.70, p = 0.046, high activity levels 388, low activity levels 2,096, musculoskeletal, RR approximated with OR.
risk of long COVID, 39.0% lower, OR 0.61, p = 0.007, high activity levels 388, low activity levels 2,096, neurological, RR approximated with OR.
risk of long COVID, 42.0% lower, OR 0.58, p = 0.03, high activity levels 388, low activity levels 2,096, respiratory, RR approximated with OR.
risk of long COVID, 5.0% lower, OR 0.95, p = 0.79, high activity levels 388, low activity levels 2,096, sensory, RR approximated with OR.
risk of long COVID, 73.0% lower, OR 0.27, p = 0.19, high activity levels 388, low activity levels 2,096, digestive, RR approximated with OR.
Saadeh, 10/30/2021, retrospective, Sweden, peer-reviewed, 6 authors, study period March 2020 - June 2020. risk of symptomatic case, 9.1% lower, OR 0.91, p = 0.71, high activity levels 362, low activity levels 225, adjusted per study, inverted to make OR<1 favor high activity levels, 2+ symptoms, Table 8, physically active vs. inactive, multivariable, RR approximated with OR.
risk of symptomatic case, 3.8% lower, OR 0.96, p = 0.85, high activity levels 362, low activity levels 225, adjusted per study, inverted to make OR<1 favor high activity levels, 1+ symptoms, Table 2, model 2, physically active vs. inactive, multivariable, RR approximated with OR.
Salgado-Aranda, 3/14/2022, retrospective, Spain, peer-reviewed, 15 authors, study period 15 February, 2020 - 15 April, 2020. risk of death, 83.1% lower, HR 0.17, p = 0.003, high activity levels 4 of 223 (1.8%), low activity levels 41 of 297 (13.8%), NNT 8.3, inverted to make HR<1 favor high activity levels, active vs. sedentary, Cox proportional hazards.
Sallis, 4/13/2021, retrospective, USA, peer-reviewed, 8 authors. risk of death, 59.2% lower, RR 0.41, p = 0.005, high activity levels 11 of 3,118 (0.4%), low activity levels 170 of 6,984 (2.4%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, consistently active vs. consistently inactive, multivariable.
risk of ICU admission, 41.5% lower, RR 0.58, p = 0.006, high activity levels 32 of 3,118 (1.0%), low activity levels 195 of 6,984 (2.8%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, consistently active vs. consistently inactive, multivariable.
risk of hospitalization, 53.0% lower, RR 0.47, p < 0.001, high activity levels 99 of 3,118 (3.2%), low activity levels 732 of 6,984 (10.5%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, consistently active vs. consistently inactive, multivariable.
Sanchez, 4/25/2023, retrospective, Spain, peer-reviewed, 3 authors, trial NCT04624048 (history). risk of symptomatic case, 54.1% lower, OR 0.46, p < 0.001, inverted to make OR<1 favor high activity levels, exercise vs. no exercise before COVID-19, RR approximated with OR.
Schmidt, 6/21/2023, retrospective, Germany, peer-reviewed, 8 authors, CoCo-Fakt trial. risk of case, 31.1% lower, OR 0.69, p = 0.02, high activity levels 956, low activity levels 2,705, adjusted per study, inverted to make OR<1 favor high activity levels, above guidelines vs. below guidelines, multivariable, RR approximated with OR.
risk of case, 34.5% lower, OR 0.66, p = 0.02, high activity levels 956, low activity levels 1,113, adjusted per study, inverted to make OR<1 favor high activity levels, above guidelines vs. meeting guidelines, multivariable, RR approximated with OR.
risk of case, 22.7% lower, OR 0.77, p = 0.02, high activity levels 3,658, low activity levels 1,680, adjusted per study, inverted to make OR<1 favor high activity levels, exercise vs. no exercise, multivariable, RR approximated with OR.
risk of case, 21.6% lower, OR 0.78, p = 0.03, high activity levels 3,371, low activity levels 1,716, adjusted per study, inverted to make OR<1 favor high activity levels, moderate-to-vigorous vs. low intensity, multivariable, RR approximated with OR.
Steenkamp, 2/9/2022, retrospective, South Africa, peer-reviewed, 10 authors, study period 19 March, 2020 - 30 June, 2021. risk of death, 42.0% lower, RR 0.58, p < 0.001, high activity levels 29,469, low activity levels 13,366, adjusted per study, high activity vs. low activity, poisson regression, multivariable.
risk of mechanical ventilation, 45.0% lower, RR 0.55, p < 0.001, high activity levels 29,469, low activity levels 13,366, adjusted per study, high activity vs. low activity, poisson regression, multivariable.
risk of ICU admission, 41.0% lower, RR 0.59, p < 0.001, high activity levels 29,469, low activity levels 13,366, adjusted per study, high activity vs. low activity, poisson regression, multivariable.
risk of hospitalization, 34.0% lower, RR 0.66, p < 0.001, high activity levels 29,469, low activity levels 13,366, adjusted per study, high activity vs. low activity, poisson regression, multivariable.
Sutkowska, 6/14/2023, prospective, Poland, peer-reviewed, 14 authors, study period 31 January, 2022 - 11 February, 2022, trial NCT05200767 (history). risk of death, 62.0% lower, HR 0.38, p = 0.21, high activity levels 71, low activity levels 60, inverted to make HR<1 favor high activity levels, IPAQ 1/2 vs. IPAQ 0, Cox proportional hazards.
risk of no recovery, 61.0% lower, HR 0.39, p = 0.19, high activity levels 71, low activity levels 60, IPAQ 1/2 vs. IPAQ 0, Cox proportional hazards.
Tavakol, 2/4/2021, retrospective, Iran, peer-reviewed, 9 authors, study period 20 March, 2020 - 24 April, 2020. risk of severe case, 68.5% lower, RR 0.31, p = 0.05, high activity levels 3 of 64 (4.7%), low activity levels 19 of 124 (15.3%), NNT 9.4, adjusted per study, odds ratio converted to relative risk, moderate to high activity versus low activity, multivariable.
Tret'yakov, 10/26/2020, retrospective, Russia, peer-reviewed, 8 authors, excluded in exclusion analyses: unadjusted results with no group details. risk of severe case, 98.3% lower, RR 0.02, p = 0.007, high activity levels 0 of 27 (0.0%), low activity levels 53 of 266 (19.9%), NNT 5.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
Tsuzuki, 7/5/2022, retrospective, Japan, preprint, 4 authors, study period 1 January, 2022 - 16 May, 2022. risk of severe case, 56.3% lower, OR 0.44, p < 0.001, high activity levels 3,340, low activity levels 1,528, adjusted per study, inverted to make OR<1 favor high activity levels, good vs. poor physical activity status, multivariable, RR approximated with OR.
Wang, 1/31/2024, prospective, United Kingdom, peer-reviewed, 10 authors. risk of death, 30.0% lower, HR 0.70, p < 0.001, high activity levels 57,930, low activity levels 10,966, adjusted per study, ≥150 min/wk moderate or ≥75 min/wk vigorous vs. < 75 min/wk vigorous, multivariable.
risk of hospitalization, 12.0% lower, HR 0.88, p < 0.001, high activity levels 57,930, low activity levels 10,966, adjusted per study, ≥150 min/wk moderate or ≥75 min/wk vigorous vs. < 75 min/wk vigorous, multivariable.
risk of long COVID, 14.0% lower, HR 0.86, p < 0.001, high activity levels 57,930, low activity levels 10,966, adjusted per study, ≥150 min/wk moderate or ≥75 min/wk vigorous vs. < 75 min/wk vigorous, multivariable.
Wang (B), 2/6/2023, prospective, USA, peer-reviewed, survey, mean age 64.7, 8 authors, study period April 2020 - November 2021. risk of long COVID, 10.7% lower, RR 0.89, p = 0.20, high activity levels 274 of 691 (39.7%), low activity levels 283 of 594 (47.6%), NNT 13, adjusted per study, inverted to make RR<1 favor high activity levels, ≥210 vs. 0-30, multivariable, model 2.
risk of long COVID, 49.0% lower, RR 0.51, p = 0.002, high activity levels 188, low activity levels 66, 5 or 6 healthy lifestyle factors vs. 0.
Yates, 2/26/2021, retrospective, United Kingdom, peer-reviewed, 7 authors. risk of death, 45.3% lower, RR 0.55, p = 0.001, high activity levels 72 of 163,912 (0.0%), low activity levels 62 of 30,119 (0.2%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, multivariable.
risk of severe case, 46.7% lower, RR 0.53, p < 0.001, high activity levels 291 of 163,912 (0.2%), low activity levels 180 of 30,119 (0.6%), adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, multivariable.
Young, 12/14/2022, retrospective, USA, peer-reviewed, 7 authors, study period 1 January, 2020 - 31 May, 2021. risk of death, 74.4% lower, OR 0.26, p < 0.001, high activity levels 11,279, low activity levels 29,099, inverted to make OR<1 favor high activity levels, always active vs. always inactive, RR approximated with OR.
risk of death, 65.3% lower, OR 0.35, p < 0.001, high activity levels 11,279, low activity levels 83,452, inverted to make OR<1 favor high activity levels, always active vs. mostly inactive, RR approximated with OR.
risk of death, 47.9% lower, OR 0.52, p < 0.001, high activity levels 11,279, low activity levels 42,490, inverted to make OR<1 favor high activity levels, always active vs. some activity, RR approximated with OR.
risk of death, 35.5% lower, OR 0.65, p = 0.002, high activity levels 11,279, low activity levels 27,871, inverted to make OR<1 favor high activity levels, always active vs. consistently active, RR approximated with OR.
risk of hospitalization, 47.6% lower, OR 0.52, p < 0.001, high activity levels 11,279, low activity levels 29,099, inverted to make OR<1 favor high activity levels, always active vs. always inactive, RR approximated with OR.
risk of hospitalization, 41.9% lower, OR 0.58, p < 0.001, high activity levels 11,279, low activity levels 83,452, inverted to make OR<1 favor high activity levels, always active vs. mostly inactive, RR approximated with OR.
risk of hospitalization, 30.1% lower, OR 0.70, p < 0.001, high activity levels 11,279, low activity levels 42,490, inverted to make OR<1 favor high activity levels, always active vs. some activity, RR approximated with OR.
risk of hospitalization, 20.0% lower, OR 0.80, p < 0.001, high activity levels 11,279, low activity levels 27,871, inverted to make OR<1 favor high activity levels, always active vs. consistently active, RR approximated with OR.
Yuan, 6/20/2021, retrospective, China, peer-reviewed, 9 authors, study period 15 February, 2020 - 14 March, 2020. risk of death, 90.5% lower, RR 0.09, p = 0.09, high activity levels 0 of 61 (0.0%), low activity levels 6 of 103 (5.8%), NNT 17, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), excluded in exclusion analyses: excessive unadjusted differences between groups.
risk of severe case, 70.0% lower, RR 0.30, p = 0.03, high activity levels 3 of 61 (4.9%), low activity levels 26 of 103 (25.2%), NNT 4.9, adjusted per study, inverted to make RR<1 favor high activity levels, odds ratio converted to relative risk, multivariable.
Zhang (C), 12/6/2020, retrospective, United Kingdom, peer-reviewed, 9 authors. risk of death, 26.0% lower, OR 0.74, p = 0.17, adjusted per study, AMPA, per SD increase, multivariable, RR approximated with OR.
risk of case, 18.0% lower, OR 0.82, p = 0.01, adjusted per study, AMPA, per SD increase, multivariable, RR approximated with OR.
Šebić, 7/15/2023, retrospective, Bosnia and Herzegovina, peer-reviewed, 5 authors. risk of oxygen therapy, 89.5% lower, RR 0.11, p = 0.045, high activity levels 0 of 53 (0.0%), low activity levels 4 of 47 (8.5%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of hospitalization, 91.4% lower, RR 0.09, p = 0.02, high activity levels 0 of 53 (0.0%), low activity levels 5 of 47 (10.6%), NNT 9.4, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
risk of progression, 83.9% lower, RR 0.16, p < 0.001, high activity levels 4 of 53 (7.5%), low activity levels 22 of 47 (46.8%), NNT 2.5, pneumonia.
no recovery, 47.3% lower, RR 0.53, p < 0.001, high activity levels 22 of 53 (41.5%), low activity levels 37 of 47 (78.7%), NNT 2.7, day 14.
Monoclonal antibodies were previously included. Other treatments such as dexamethasone, tocilizumab, and baricitinib were recommended for late stage hospitalized patients.
Smoking was known to cause lung cancer since at least 1939, but this was not widely recognized in the US until 1964, 25 years later. Surgeon general Leroy Burney tried publicizing the danger starting in 1957, with limited success. Surgeon general Luther Terry, appointed in 1961, prompted by President Kennedy in 1962 amid pressure from health advocates, finally got recognition in 1964. The 1964 report reviewed 7,000+ studies, but these could (and should) have been reviewed and acted upon in real-time as they were published. Historians attribute the 25 year delay to an industry campaign to manufacture doubt and controversy, through tactics like funding biased and fraudulent research from "independent" organizations, attacking scientists, and political lobbying. The success of the industry campaign is only possible because officials did not analyze the research in detail. Fraudulent industry research supported prior failures, but would have been called out as fraudulent by officials that analyzed and understood the research in real-time.
When administered late in infection, HCQ may enhance viral egress by further increasing lysosomal pH beyond the effect of ORF3a's water channel activity, thereby promoting lysosomal exocytosis, inactivating degradative enzymes, and facilitating the release of SARS-CoV-2 particles into the extracellular environment59,60. Research also suggests potential cardioprotective effects at lower doses, but cardiotoxicity with excessive dosage61. Bobrowski et al. also indicate negative effects if HCQ and remdesivir are combined.
Peters et al. is subject to confounding by calendar-time (SOC evolved rapidly early in the pandemic, the linear covariate does not reflect non-linear SOC changes and hospital specific effects), hospital type (non-treatment hospitals were tertiary university centers), confounding by indication (4/7 hospitals initiated treatment on deterioration), immortal-time bias for as-treated (exposure assigned after baseline), significant differences for other experimental treatments, potential overadjustment from collider bias (steroid use and indication bias), limited baseline severity information, differences in hospice referral propensity across hospitals, unadjusted difference in time from onset to admission, difference in PCR positivity, and other factors. Mahévas et al. is subject to confounding by hospital (treatment highly dependent on the hospital, different SOC/ICU transfer practices, not included in PS), immortal time (only partly addressed in sensitivity analysis), co-treatment differences, calendar-time (SOC evolved rapidly early in the pandemic), binary coding for age (age ≥65 despite steep age-risk gradient), residual imbalance (variables dropped from PS), a composite outcome dependent on hospital triage/capacity, and other factors.