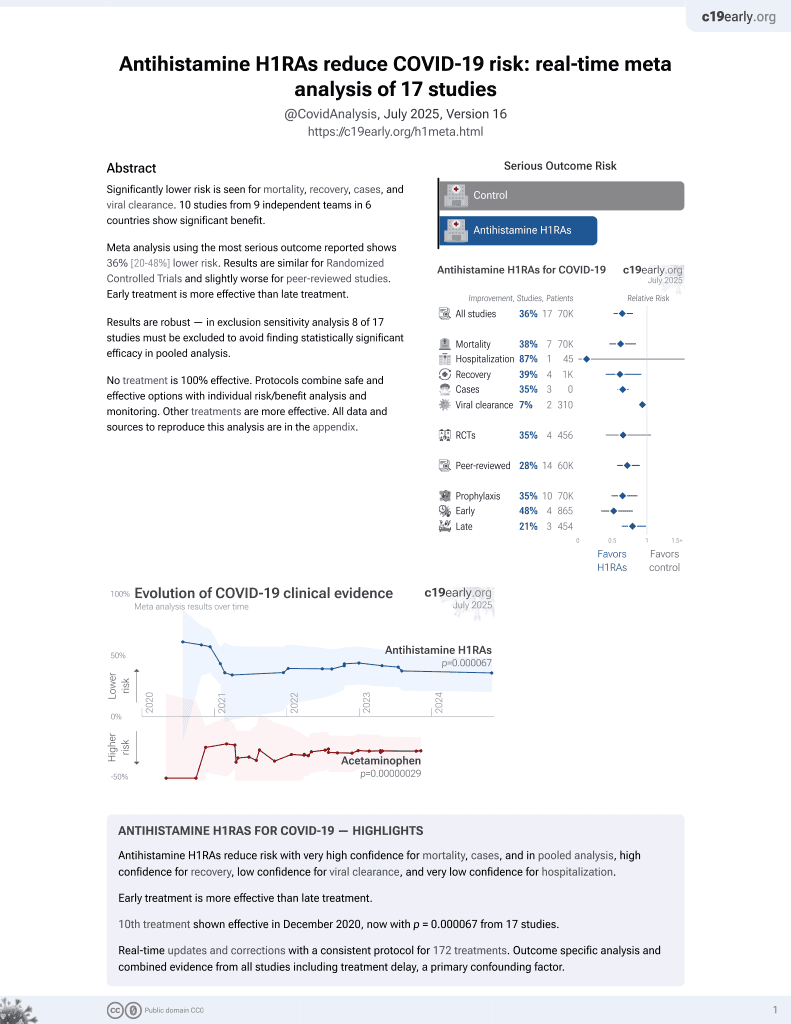
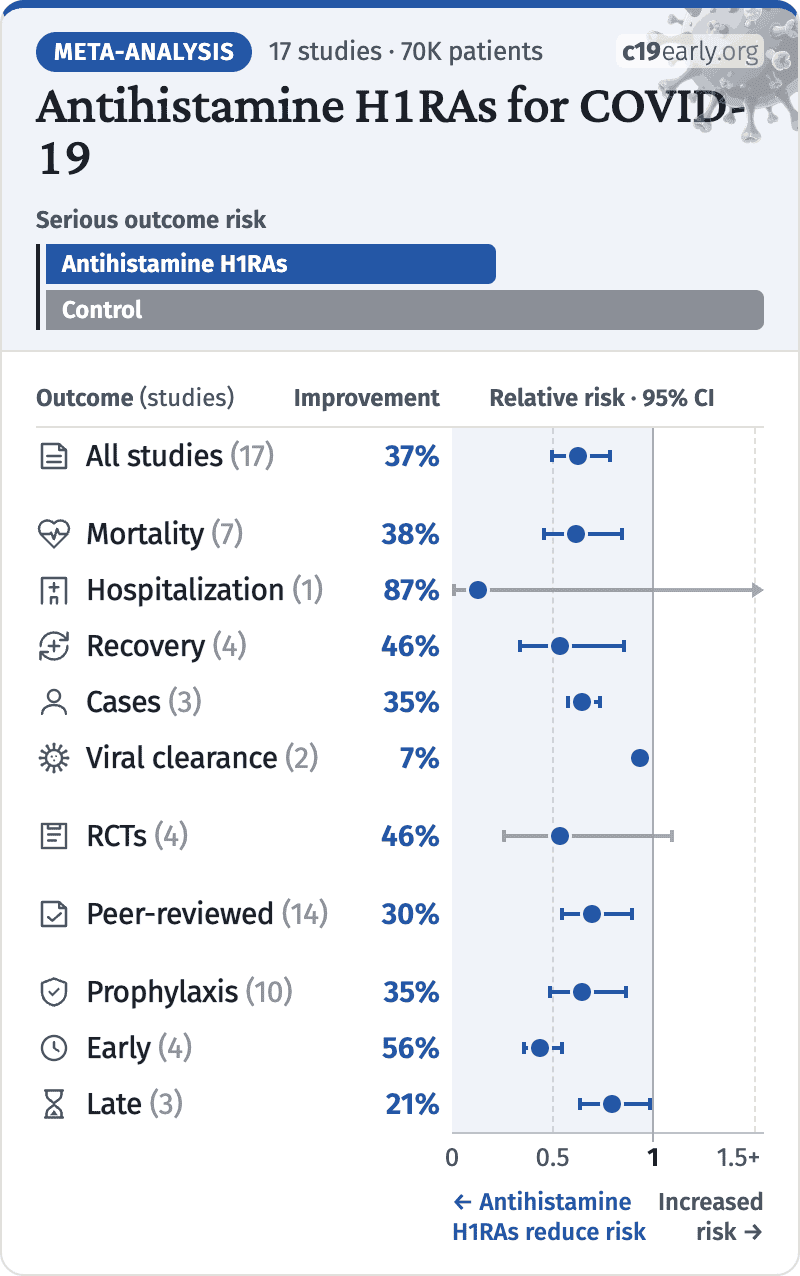
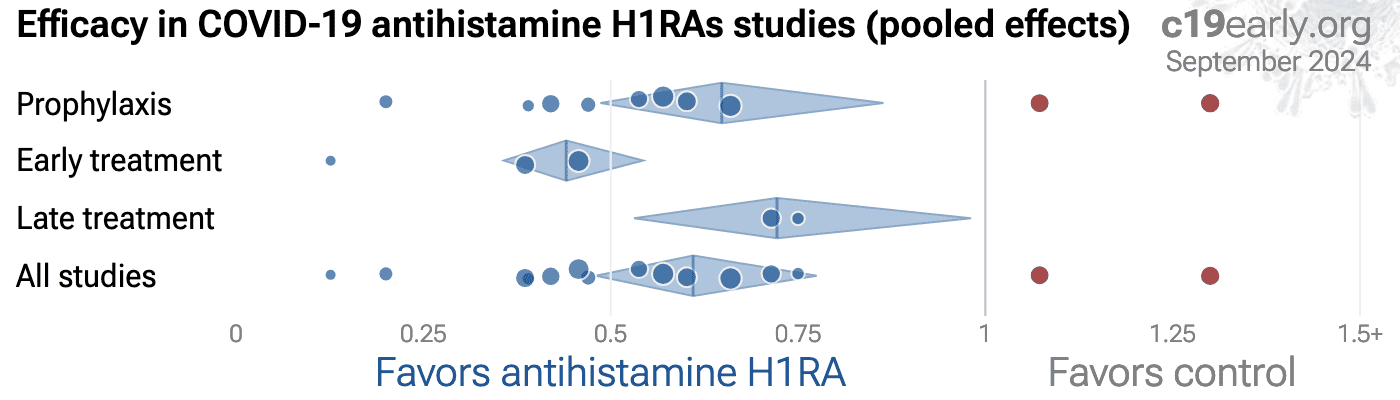
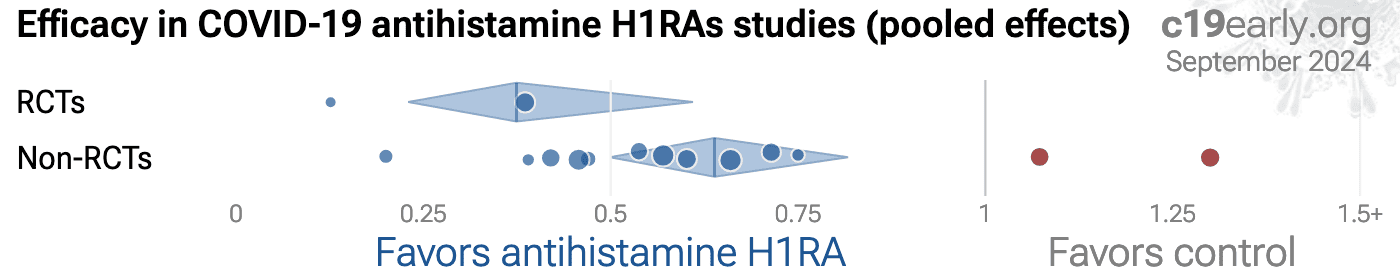
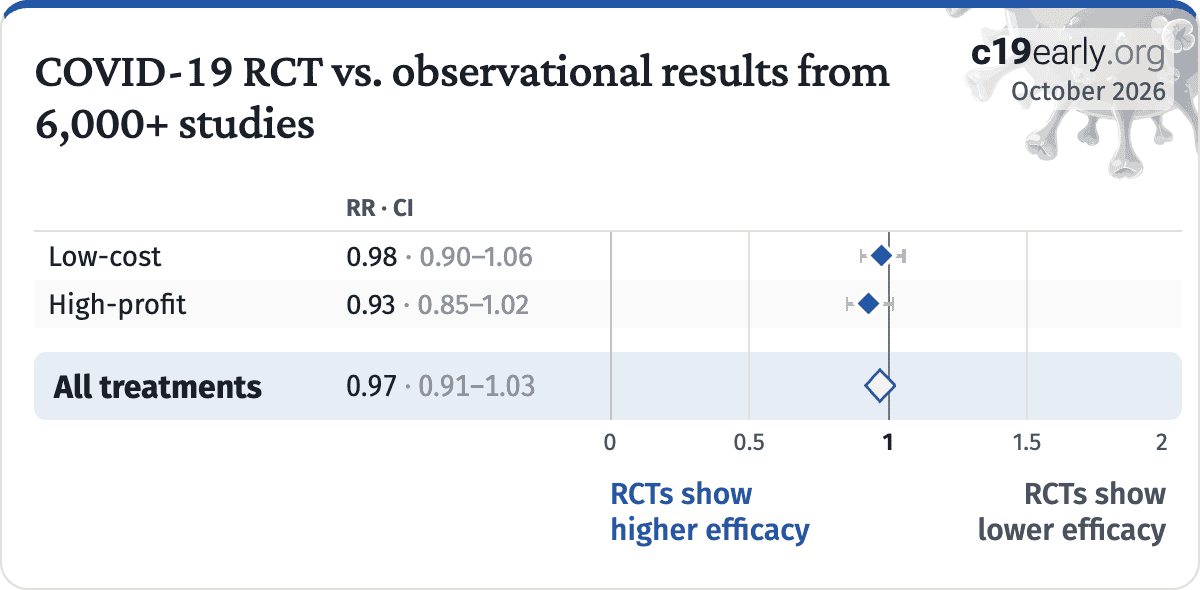
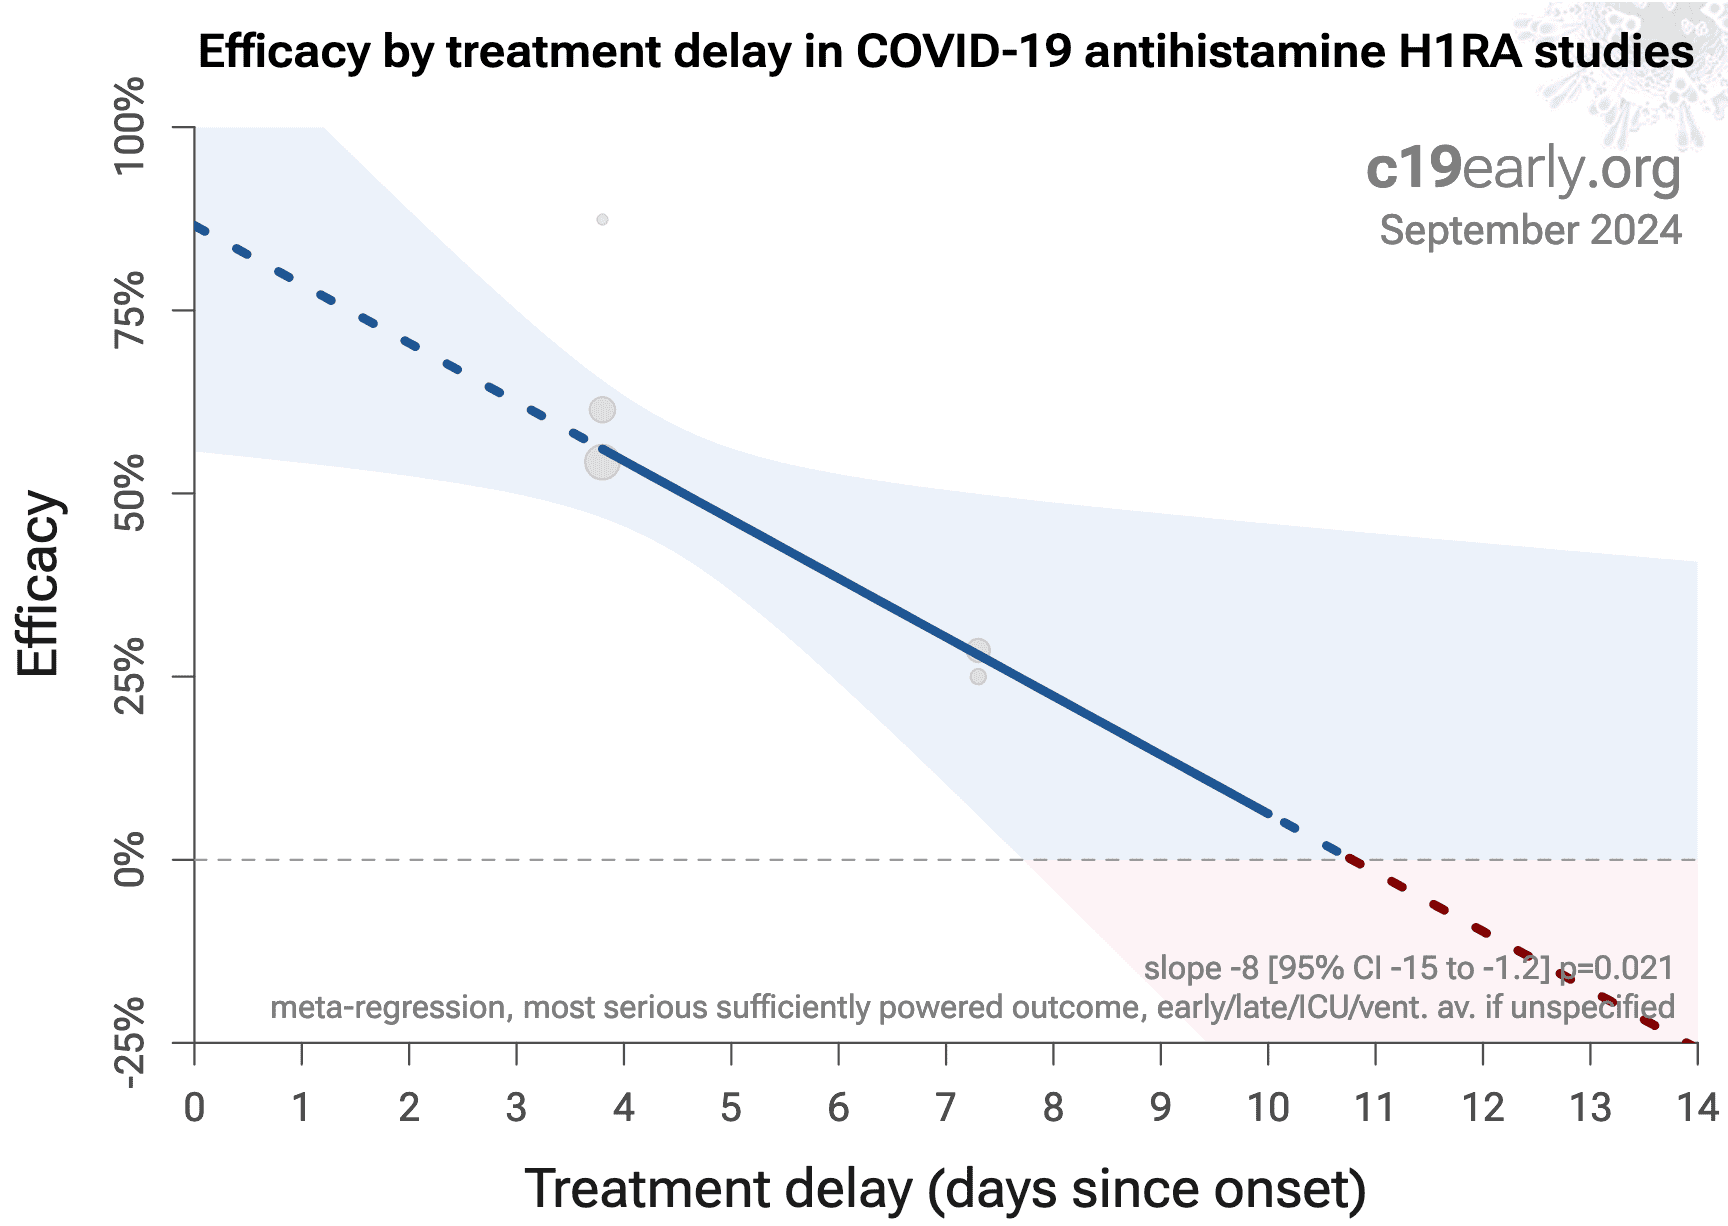
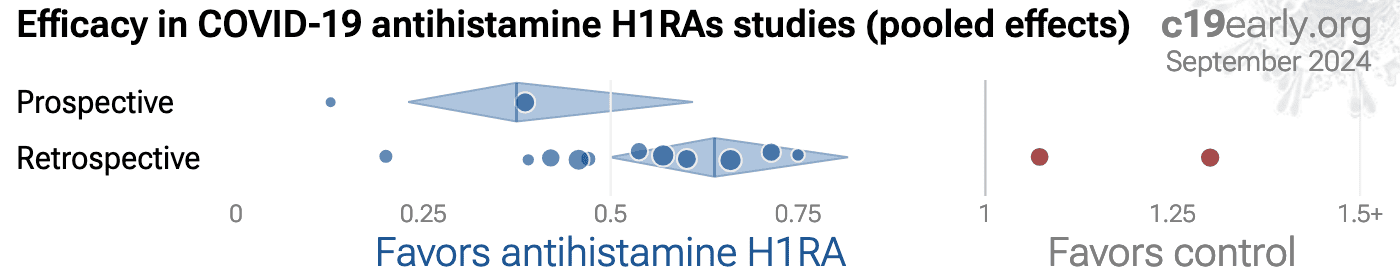
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/h1meta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
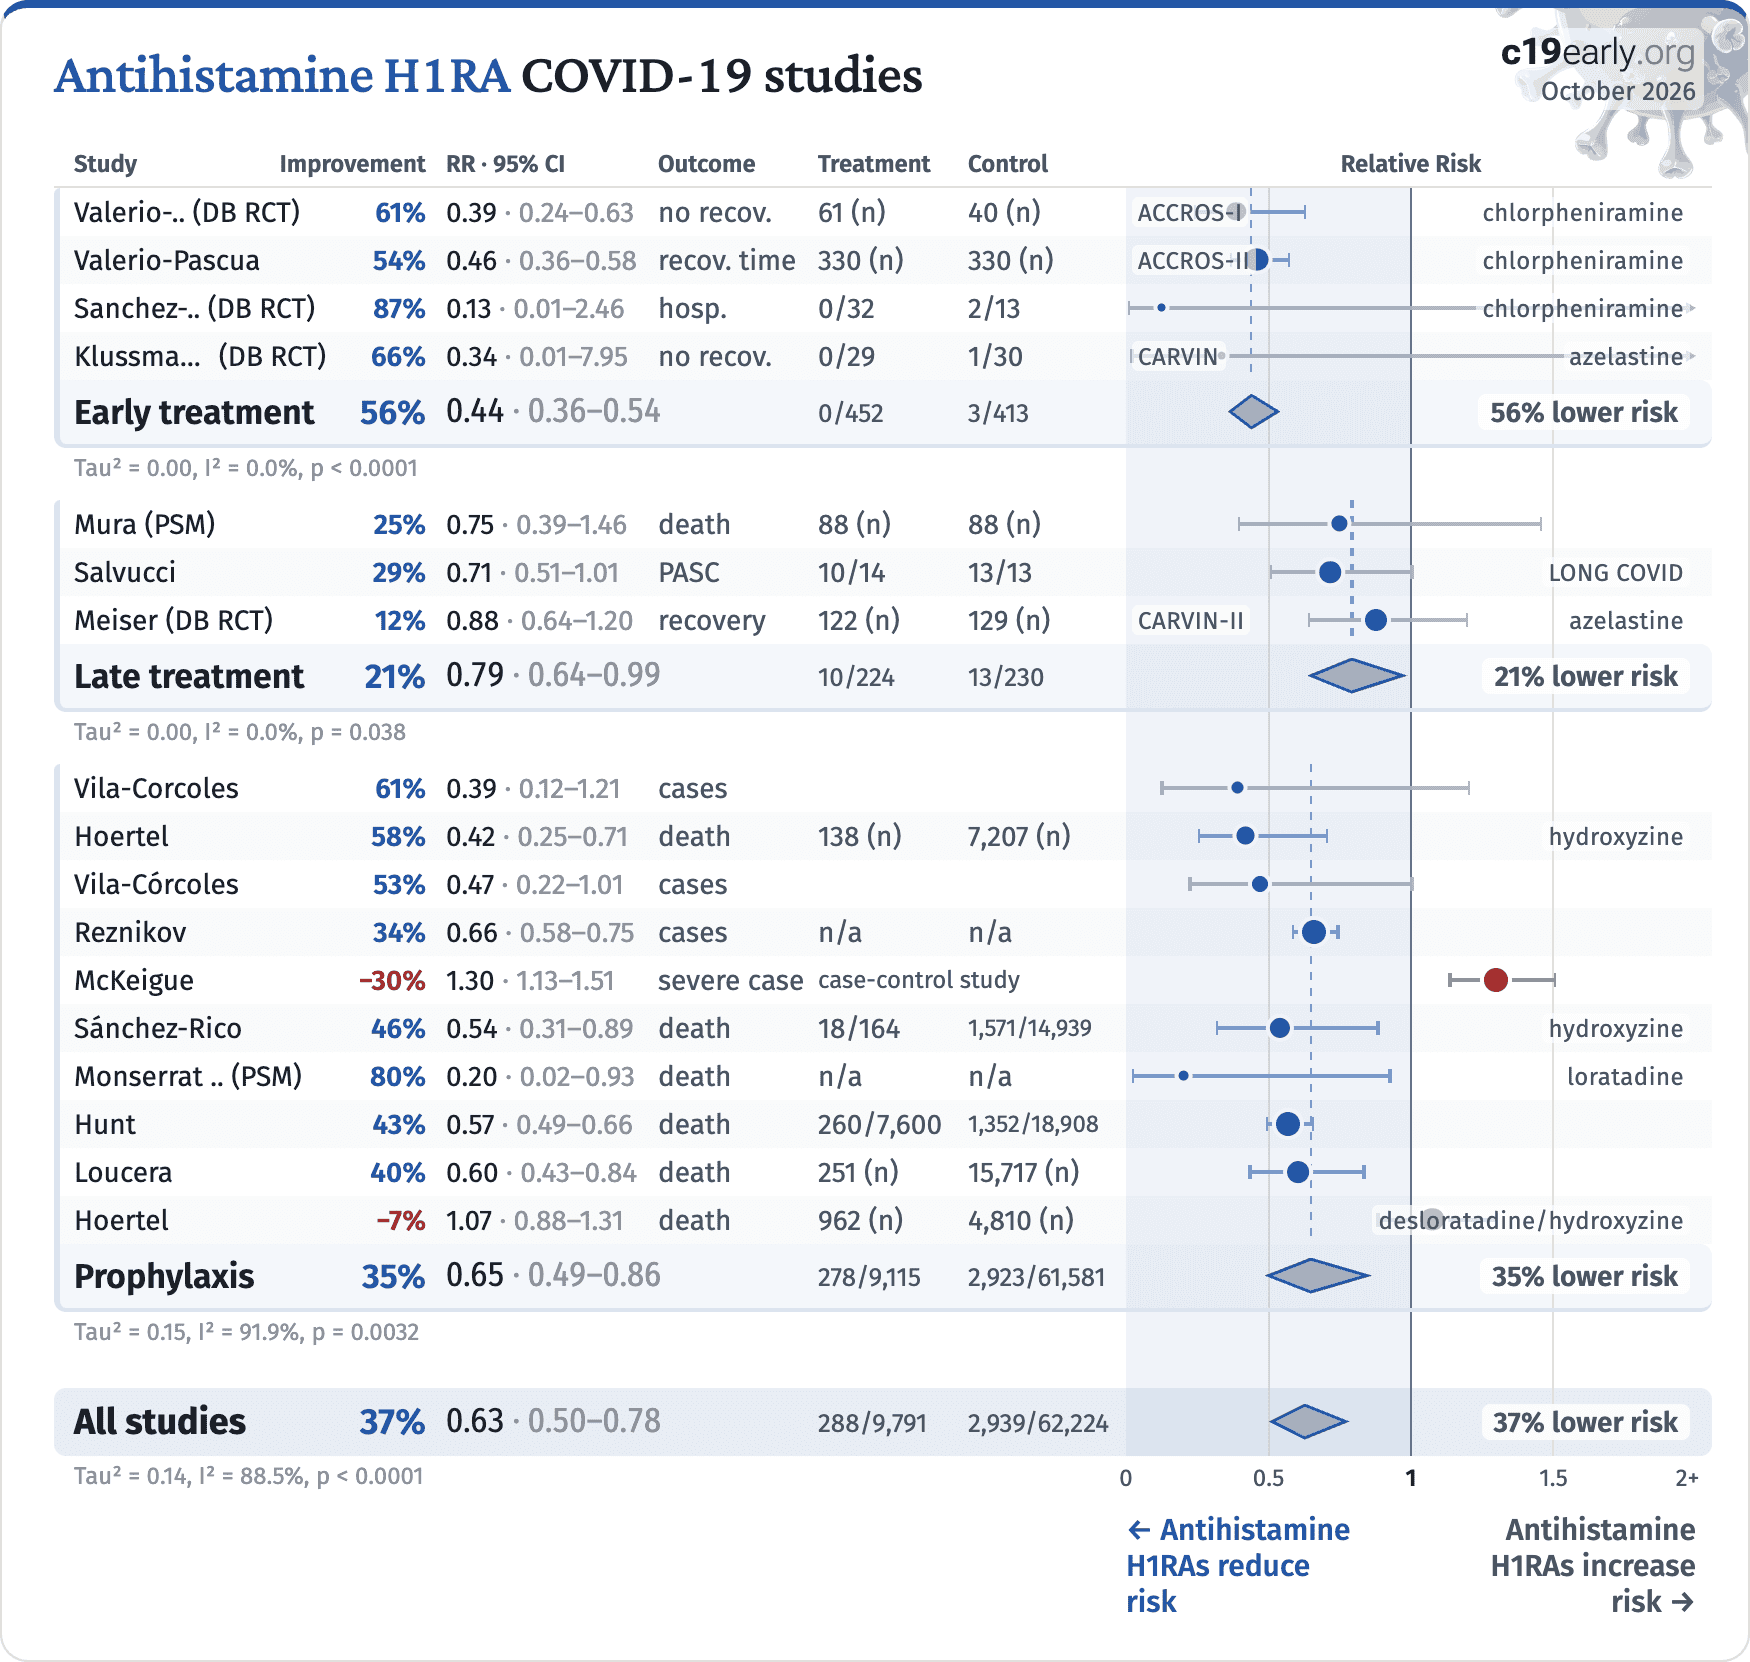
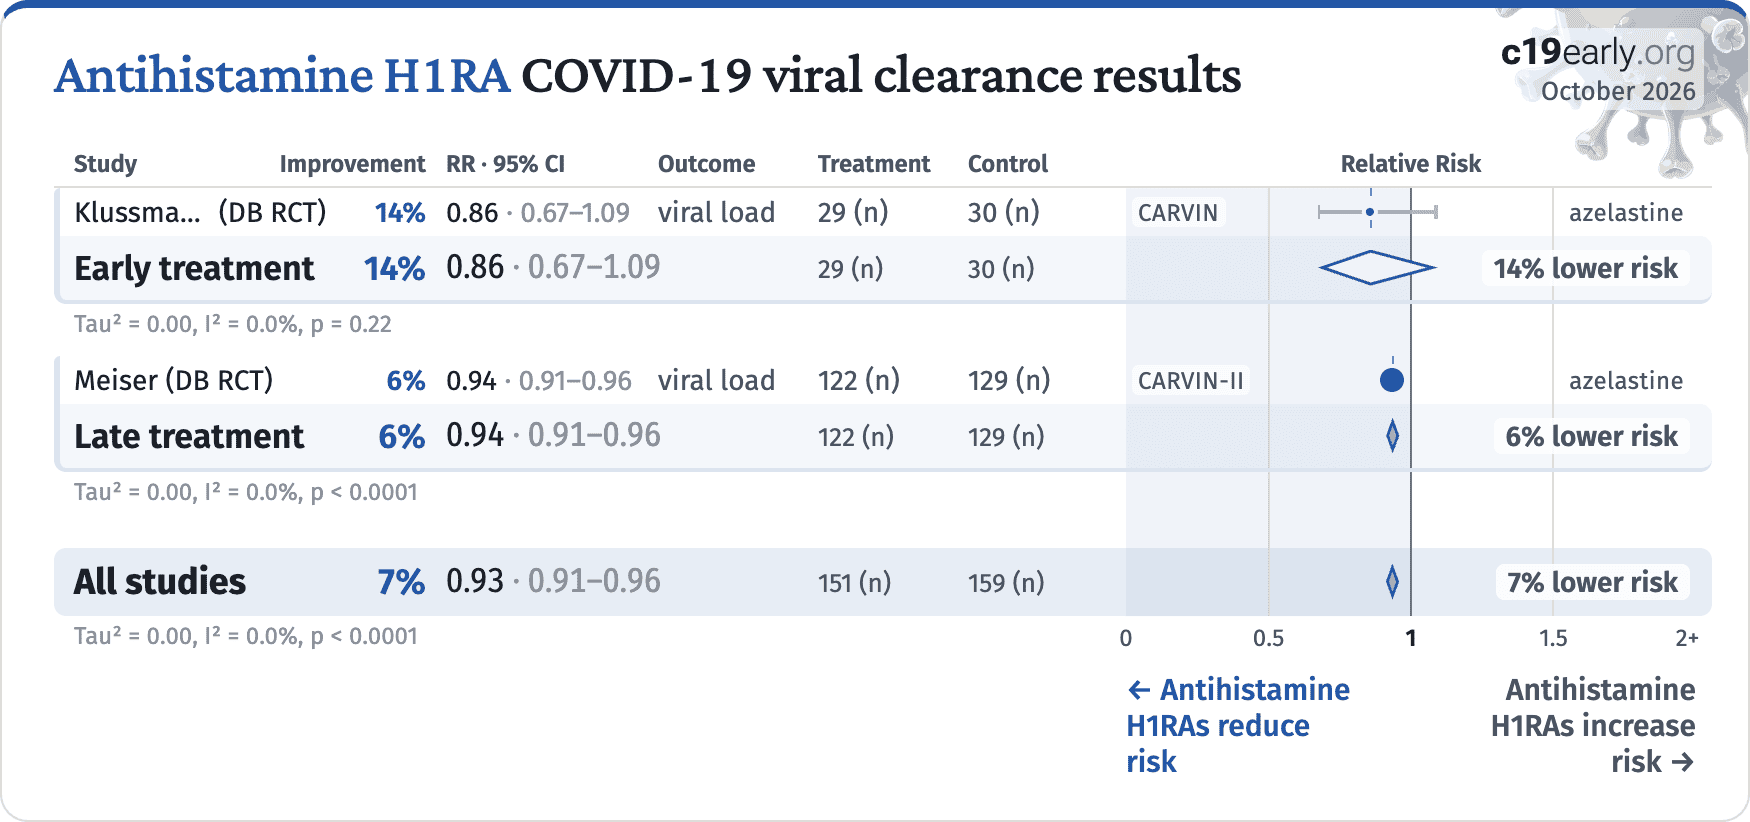
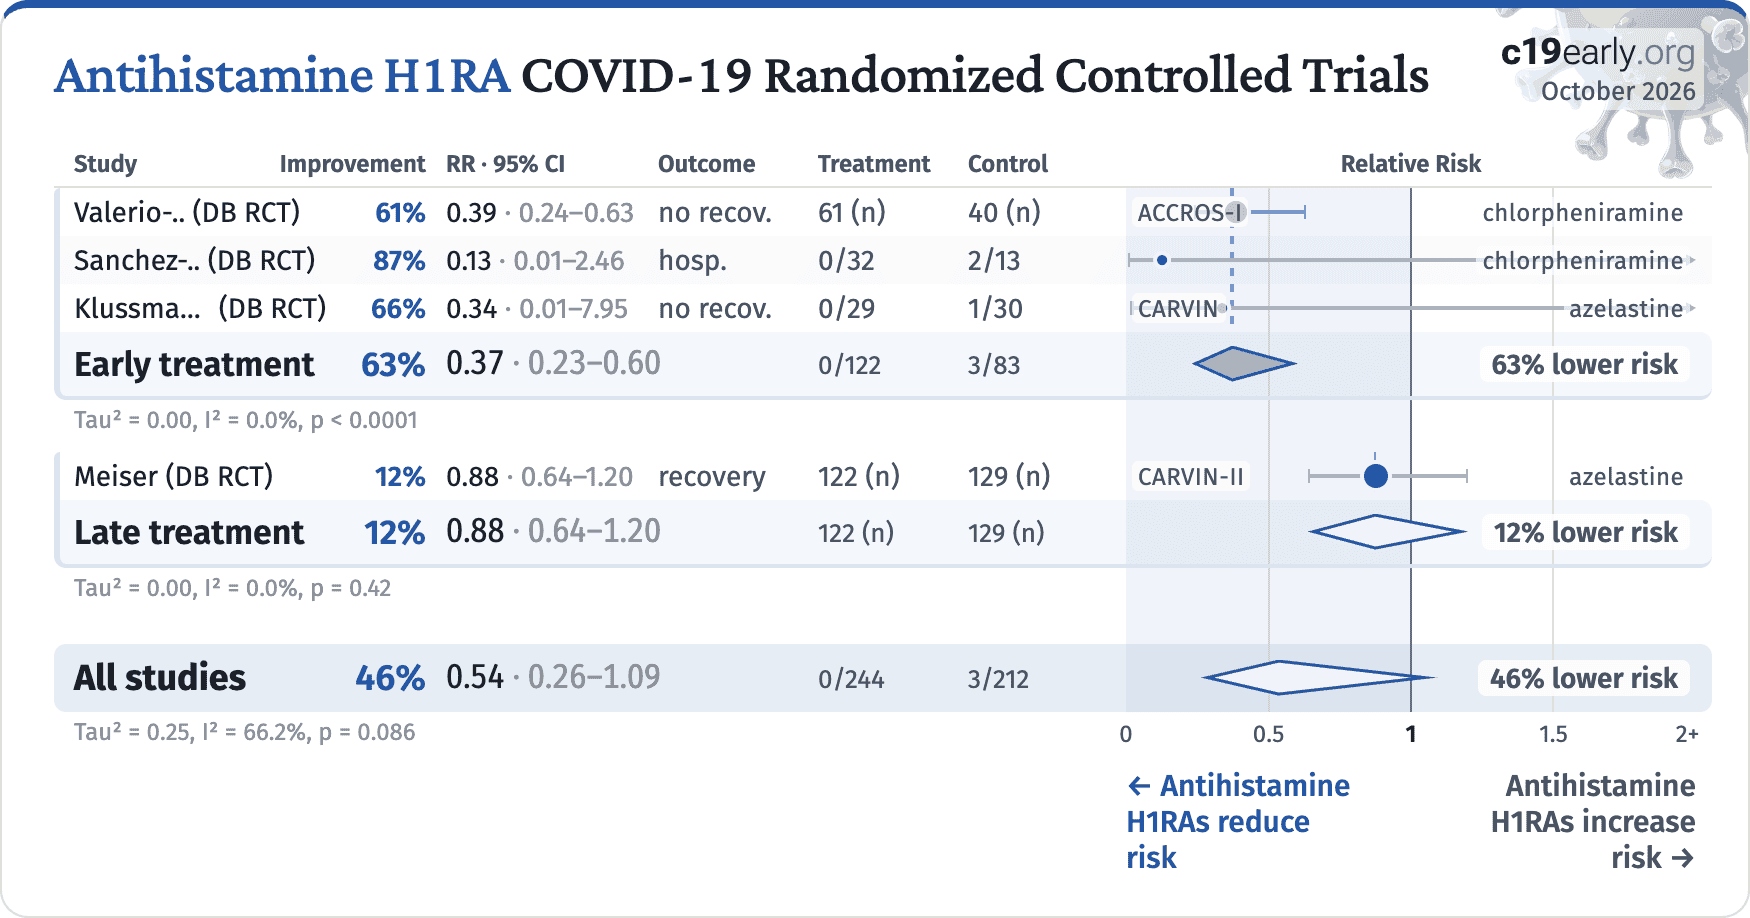
Klussmann, 4/26/2023, Double Blind Randomized Controlled Trial, placebo-controlled, Germany, peer-reviewed, 27 authors, CARVIN trial.
|
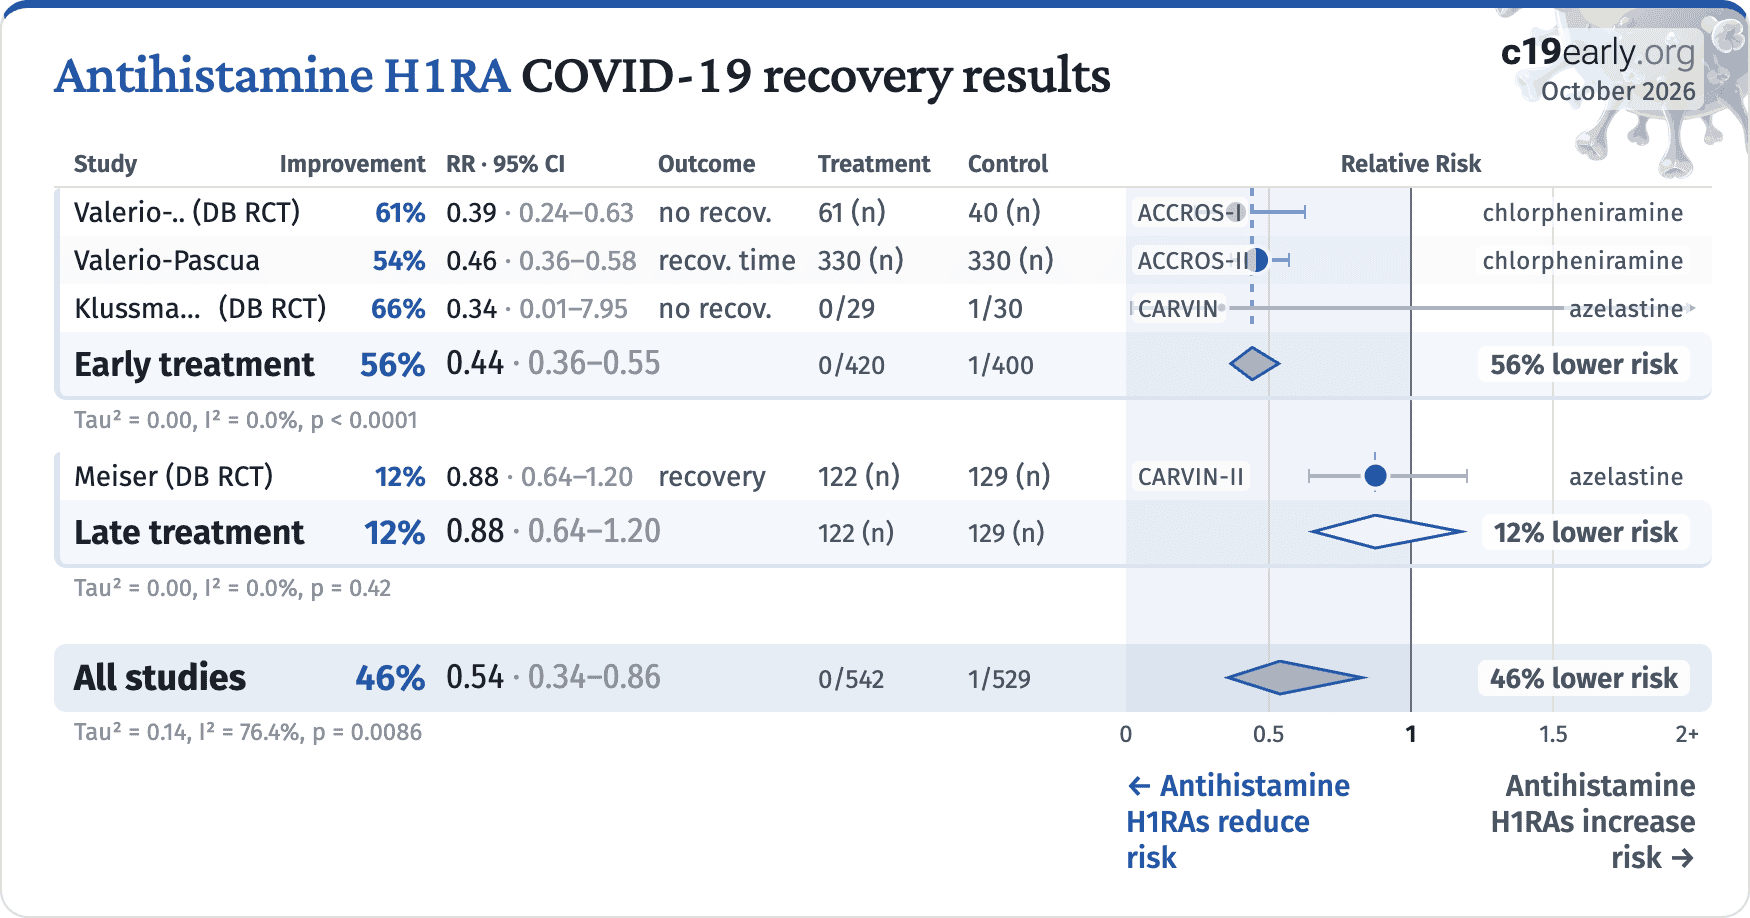
risk of no recovery, 66.3% lower, RR 0.34, p = 1.00, treatment 0 of 29 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 0.1%.
|
|
risk of no recovery, 67.0% lower, RR 0.33, p = 0.49, treatment 0 of 31 (0.0%), control 1 of 30 (3.3%), NNT 30, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), 0.02%.
|
|
symptoms, 12.7% lower, RR 0.87, p = 0.54, treatment mean 12.74 (±10.74) n=29, control mean 11.12 (±9.45) n=30, relative change in symptom score, 0.1%.
|
|
symptoms, 32.7% higher, RR 1.33, p = 0.26, treatment mean 8.38 (±9.42) n=31, control mean 11.12 (±9.45) n=30, relative change in symptom score, 0.02%.
|
|
viral load, 14.2% lower, relative load 0.86, p = 0.22, treatment mean 4.45 (±2.25) n=29, control mean 3.82 (±1.61) n=30, 0.1%.
|
|
viral load, 7.3% lower, relative load 0.93, p = 0.52, treatment mean 4.12 (±2.01) n=31, control mean 3.82 (±1.61) n=30, 0.02%.
|
|
risk of no viral clearance, 21.7% lower, RR 0.78, p = 0.04, treatment mean 24.14 (±13.12) n=29, control mean 18.89 (±4.7) n=30, relative AUC, 0.1%.
|
|
risk of no viral clearance, 6.2% lower, RR 0.94, p = 0.54, treatment mean 24.14 (±12.56) n=31, control mean 22.64 (±4.7) n=30, relative AUC, 0.02%.
|
|
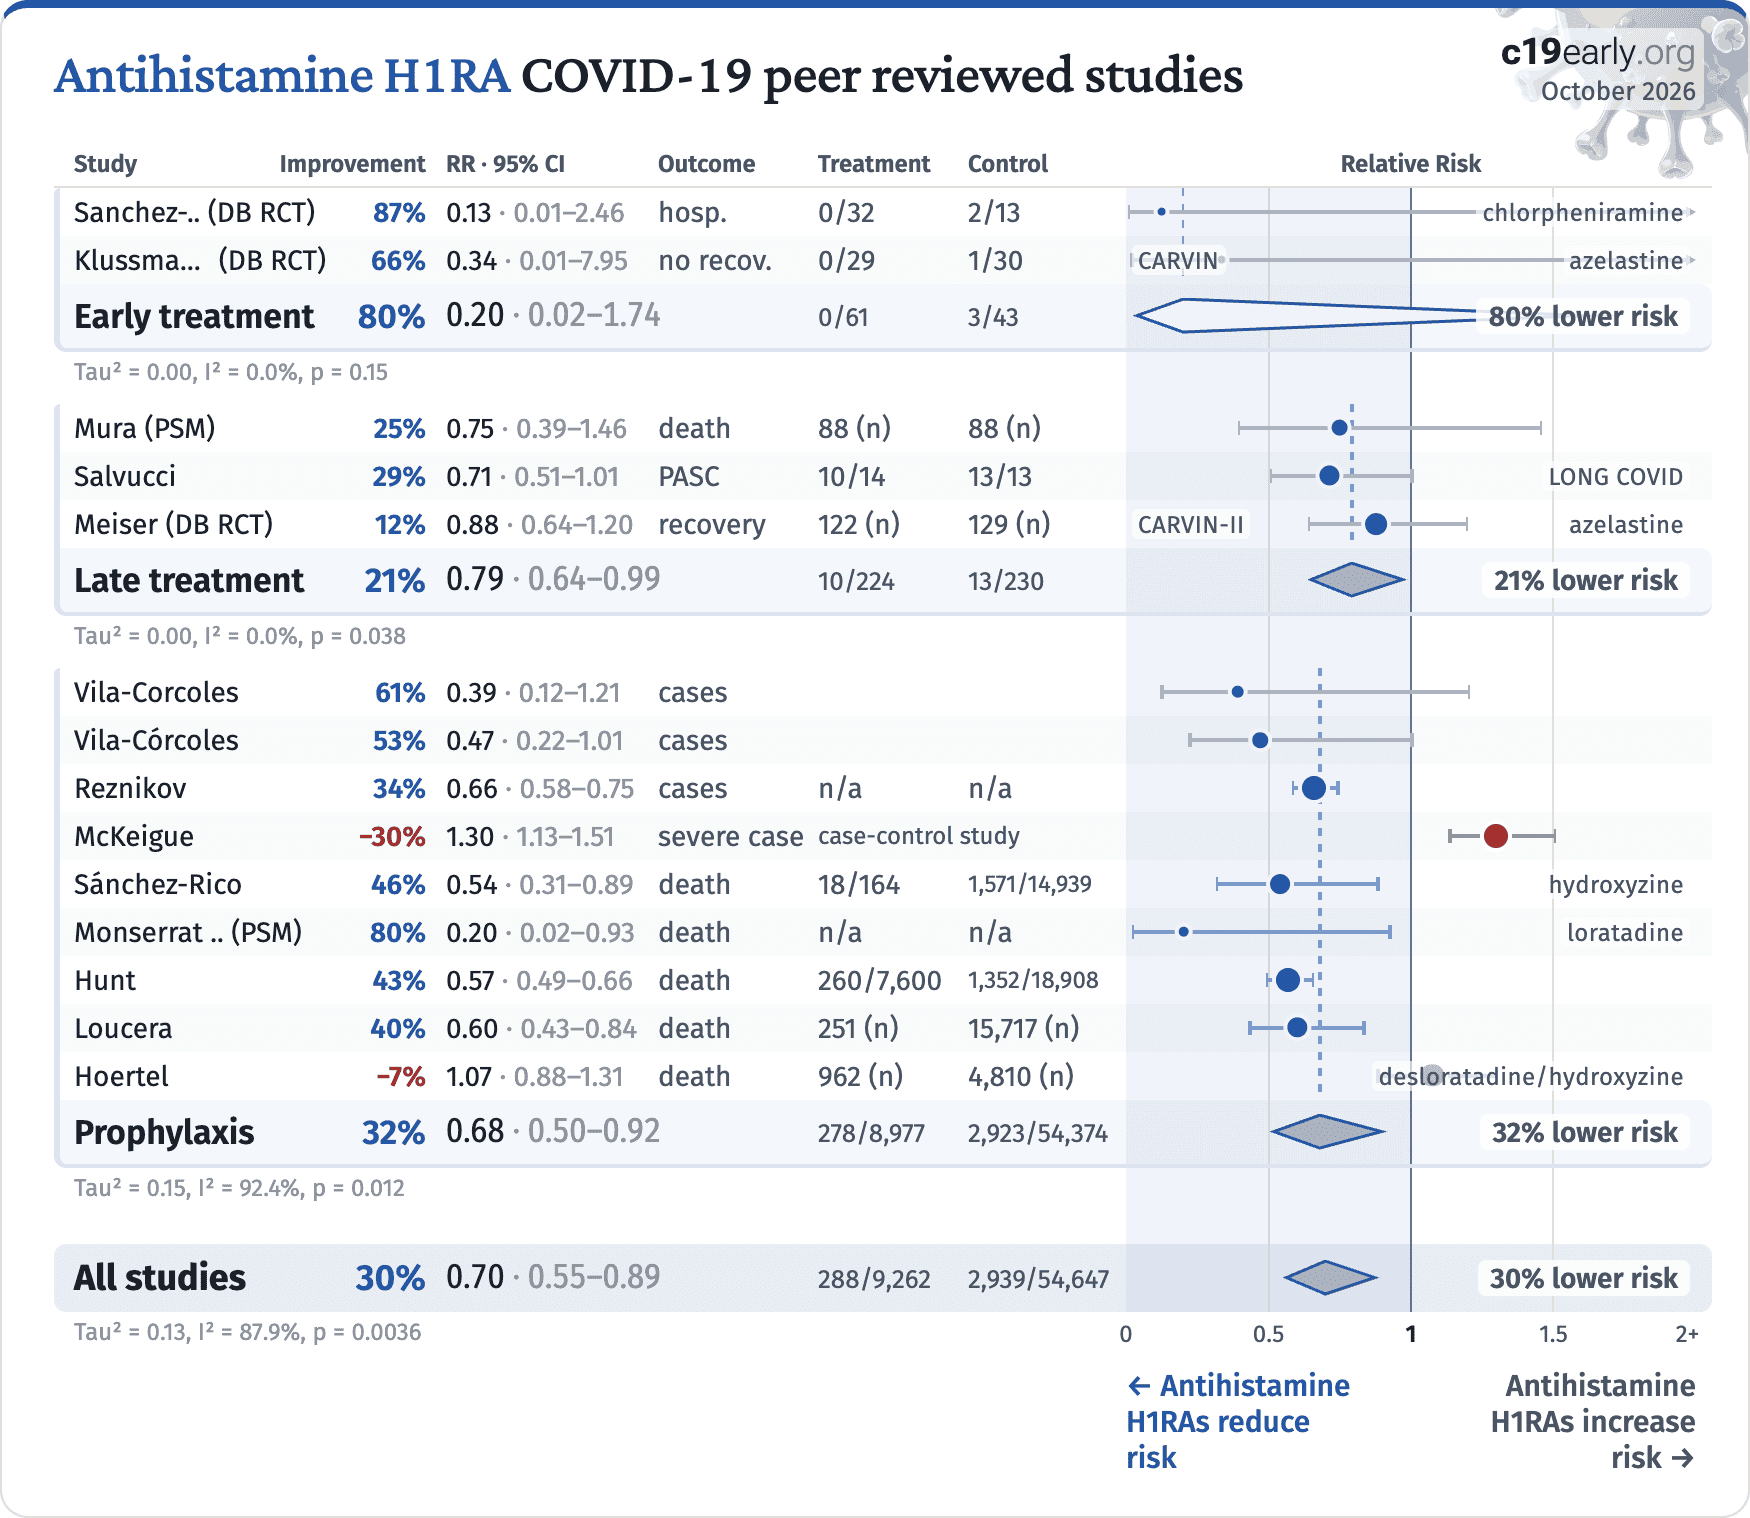
Sanchez-Gonzalez, 12/31/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, mean age 44.5, 5 authors.
|
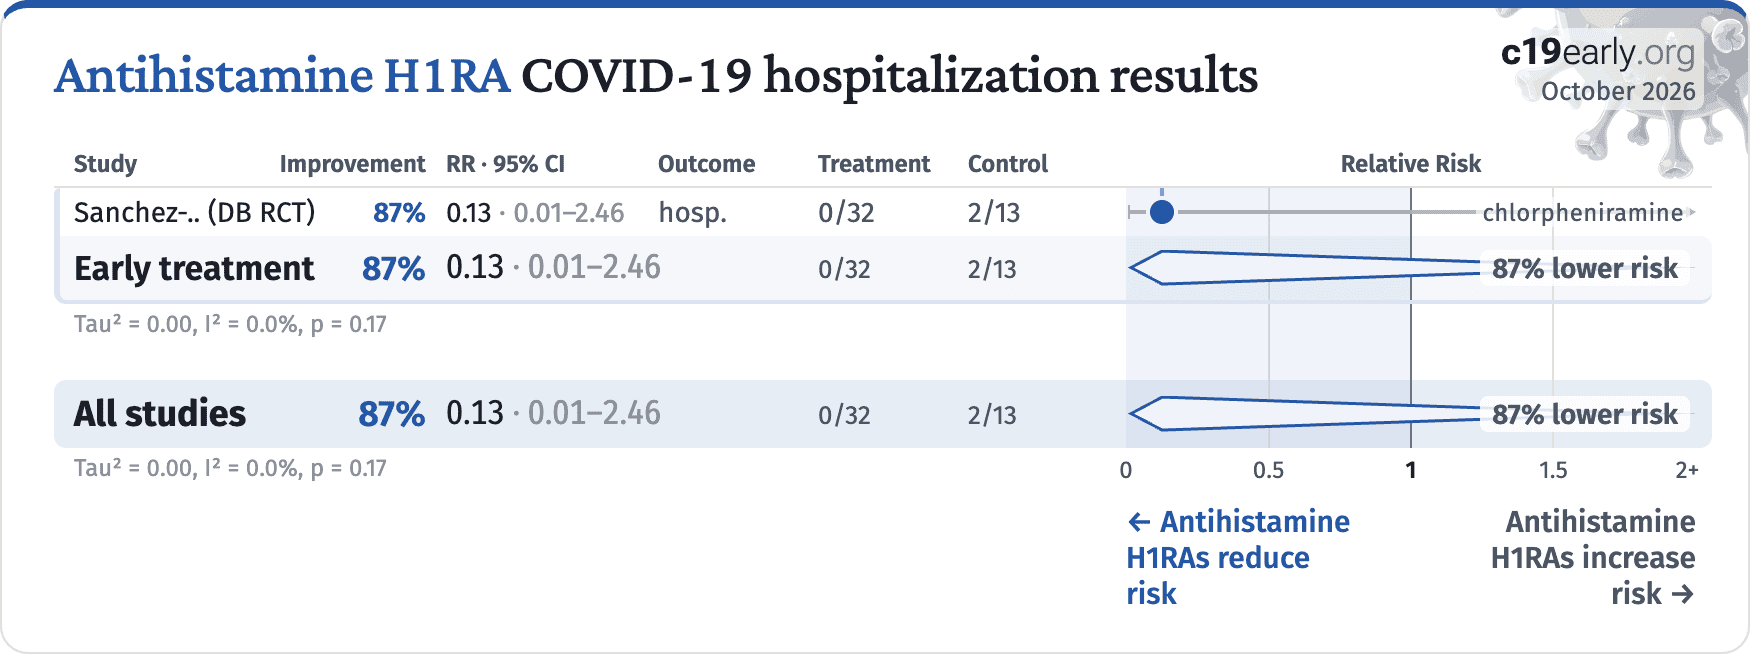
risk of hospitalization, 87.4% lower, RR 0.13, p = 0.08, treatment 0 of 32 (0.0%), control 2 of 13 (15.4%), NNT 6.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Valerio-Pascua (B), 10/18/2022, retrospective, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05520944 (history) (ACCROS-II).
|
recovery time, 54.3% lower, relative time 0.46, p < 0.001, treatment mean 4.97 (±3.32) n=330, control mean 10.88 (±6.64) n=330.
|
|
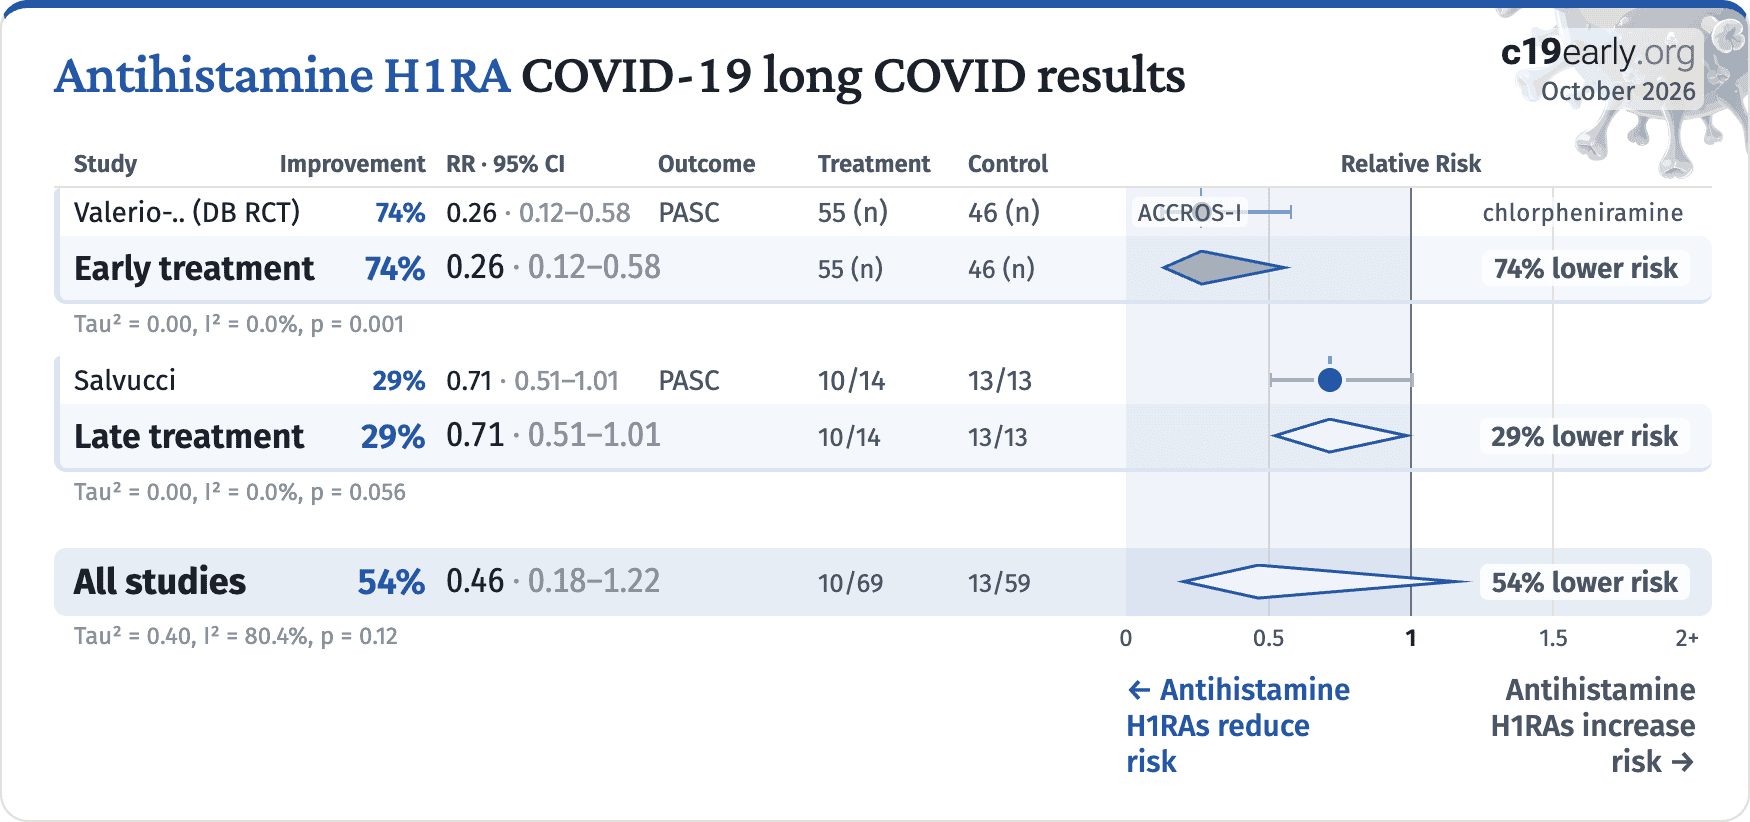
Valerio-Pascua, 10/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05449405 (history) (ACCROS-I).
|
risk of no recovery, 61.4% lower, RR 0.39, p < 0.001, treatment 61, control 40, all symptoms combined.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.15, treatment 3 of 61 (4.9%), control 6 of 40 (15.0%), NNT 9.9, day 7, anosmia.
|
|
risk of no recovery, 89.1% lower, RR 0.11, p = 0.01, treatment 1 of 61 (1.6%), control 6 of 40 (15.0%), NNT 7.5, day 7, ageusia.
|
|
risk of no recovery, 53.2% lower, RR 0.47, p = 0.05, treatment 10 of 61 (16.4%), control 14 of 40 (35.0%), NNT 5.4, day 7, cough.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.21, treatment 2 of 61 (3.3%), control 4 of 40 (10.0%), NNT 15, day 7, fatigue.
|
|
risk of no recovery, 59.0% lower, RR 0.41, p = 0.13, treatment 5 of 61 (8.2%), control 8 of 40 (20.0%), NNT 8.5, day 7, nasal congestion.
|
|
relative long COVID score, 73.5% better, RR 0.26, p < 0.001, treatment 55, control 46, relative average composite long COVID score.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Meiser, 10/31/2024, Double Blind Randomized Controlled Trial, placebo-controlled, India, peer-reviewed, 8 authors, study period 27 September, 2022 - 16 May, 2023, trial CTRI/2022/09 (CARVIN-II).
|
risk of no recovery, 12.5% lower, RR 0.87, p = 0.42, treatment mean 0.8 (±0.99) n=122, control mean 0.7 (±0.96) n=129, WHO scale improvement, mid-recovery, day 3.
|
|
viral load, 6.4% lower, relative load 0.94, p < 0.001, treatment mean 2.8 (±0.27) n=122, control mean 2.62 (±0.26) n=129, relative viral load reduction, mid-recovery, day 3.
|
|
viral load, 2.2% lower, relative load 0.98, p = 0.001, treatment mean 5.05 (±0.29) n=122, control mean 4.94 (±0.25) n=129, relative viral load reduction, mid-recovery, day 6.
|
|
viral load, 1.3% lower, relative load 0.99, p = 0.003, treatment mean 5.93 (±0.22) n=122, control mean 5.85 (±0.2) n=129, relative viral load reduction, mid-recovery, day 11.
|
|
risk of no viral clearance, 3.2% lower, RR 0.97, p < 0.001, treatment mean 1014.96 (±35.25) n=122, control mean 982.98 (±31.68) n=129, relative AUC.
|
|
Mura, 3/31/2021, retrospective, database analysis, multiple countries, peer-reviewed, 6 authors.
|
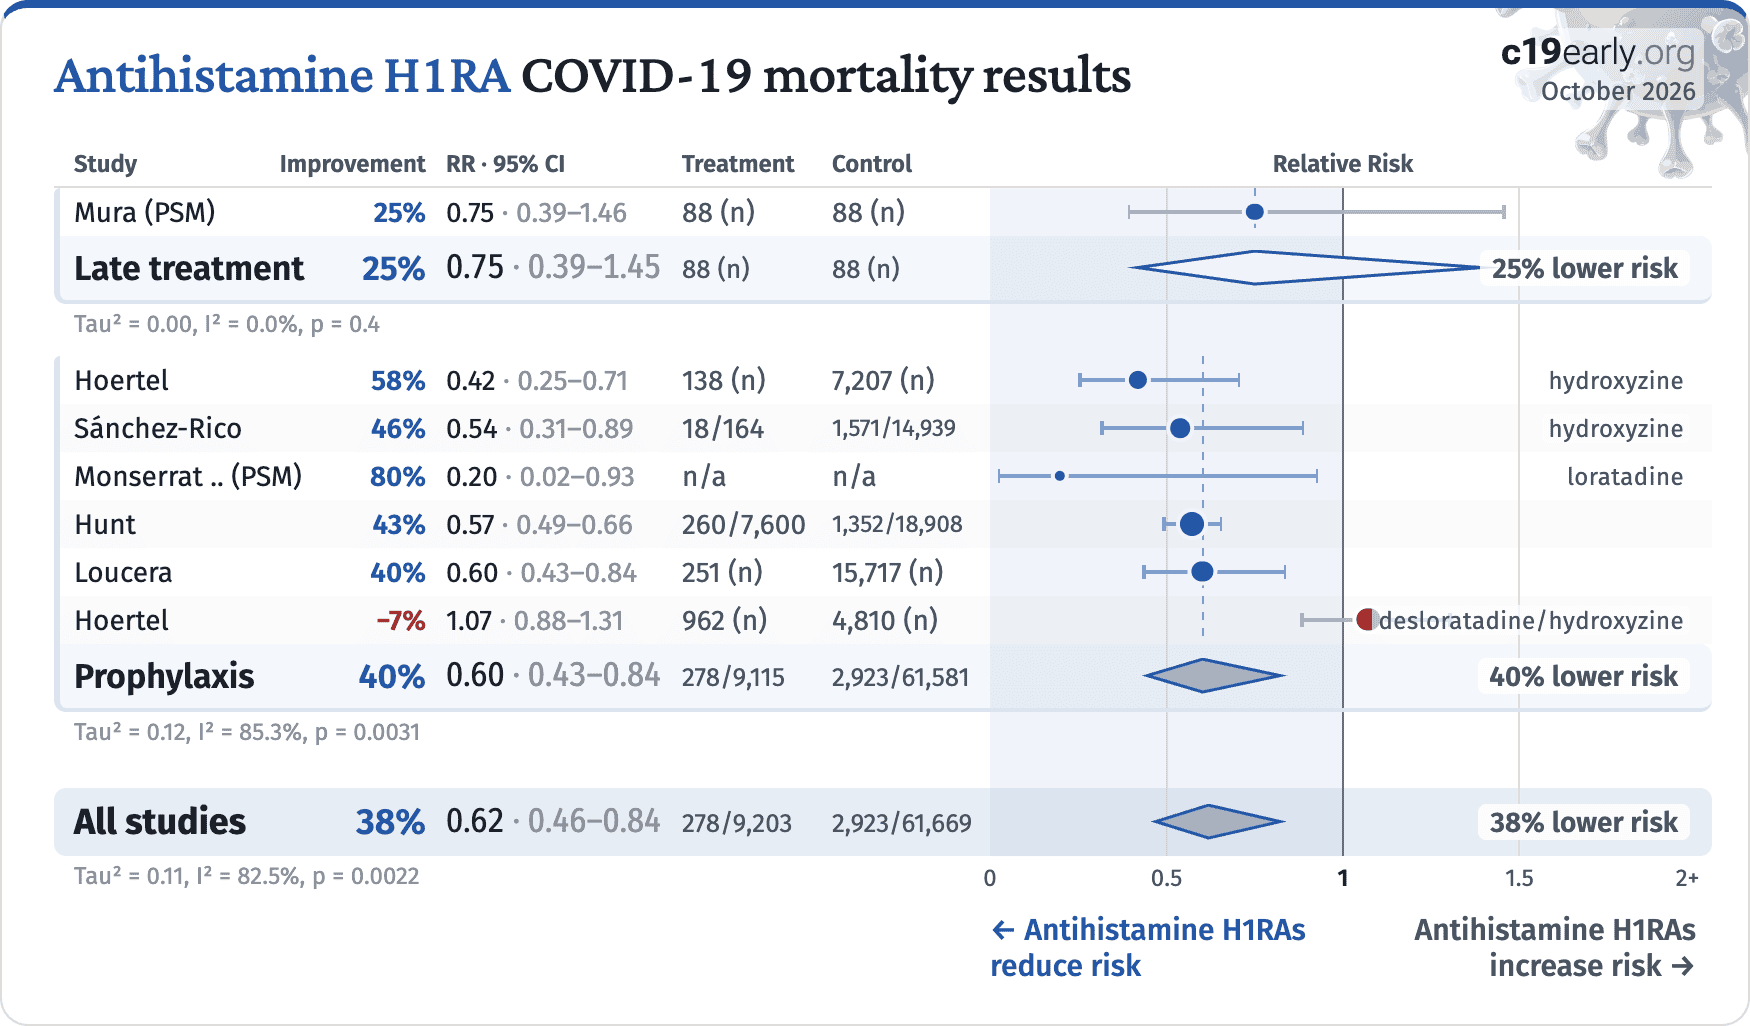
risk of death, 25.0% lower, OR 0.75, p = 0.40, treatment 88, control 88, H1+H2 vs. famotidine, propensity score matching, RR approximated with OR.
|
|
Salvucci, 7/17/2023, retrospective, Italy, peer-reviewed, 9 authors.
|
risk of long COVID, 28.6% lower, RR 0.71, p = 0.10, treatment 10 of 14 (71.4%), control 13 of 13 (100.0%), NNT 3.5.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Hoertel, 8/4/2023, retrospective, France, peer-reviewed, 14 authors, study period 2 May, 2020 - 31 August, 2022.
|
risk of death, 7.2% higher, HR 1.07, p = 0.50, treatment 962, control 4,810, adjusted per study, combined.
|
|
risk of death, 8.0% lower, HR 0.92, p = 0.81, treatment 11 of 94 (11.7%), control 62 of 470 (13.2%), NNT 67, adjusted per study, desloratadine, multivariable, Cox proportional hazards, day 28.
|
|
risk of death, 9.0% higher, HR 1.09, p = 0.40, treatment 104 of 962 (10.8%), control 591 of 4,810 (12.3%), adjusted per study, hydroxyzine, multivariable, Cox proportional hazards, day 28.
|
|
Hoertel (B), 10/27/2020, retrospective, France, preprint, 18 authors, study period 24 January, 2020 - 1 April, 2020.
|
risk of death, 58.0% lower, HR 0.42, p = 0.001, treatment 138, control 7,207, adjusted per study, propensity score weighting, multivariable.
|
|
Hunt, 6/29/2022, retrospective, USA, peer-reviewed, 8 authors, study period 1 March, 2020 - 10 September, 2020.
|
risk of death, 43.0% lower, RR 0.57, p < 0.001, treatment 260 of 7,600 (3.4%), control 1,352 of 18,908 (7.2%), NNT 27, adjusted per study, day 30.
|
|
Loucera, 8/16/2022, retrospective, Spain, peer-reviewed, 8 authors, study period January 2020 - November 2020.
|
risk of death, 39.8% lower, HR 0.60, p = 0.003, treatment 251, control 15,717, combined.
|
|
risk of death, 30.4% lower, HR 0.70, p = 0.05, treatment 251, control 15,717, loratadine, Cox proportional hazards, day 30.
|
|
risk of death, 50.6% lower, HR 0.49, p = 0.002, treatment 233, control 15,735, cetirizine, Cox proportional hazards, day 30.
|
|
McKeigue, 2/22/2021, retrospective, Scotland, peer-reviewed, 18 authors, trial EUPAS35558.
|
risk of severe case, 30.0% higher, OR 1.30, p < 0.001, treatment 263 of 2,357 (11.2%) cases,
2,556 of 33,803 (7.6%) controls, adjusted per study, case control OR.
|
|
Monserrat Villatoro, 1/8/2022, retrospective, propensity score matching, Spain, peer-reviewed, 18 authors.
|
risk of death, 80.0% lower, OR 0.20, p = 0.05, loratadine, RR approximated with OR.
|
|
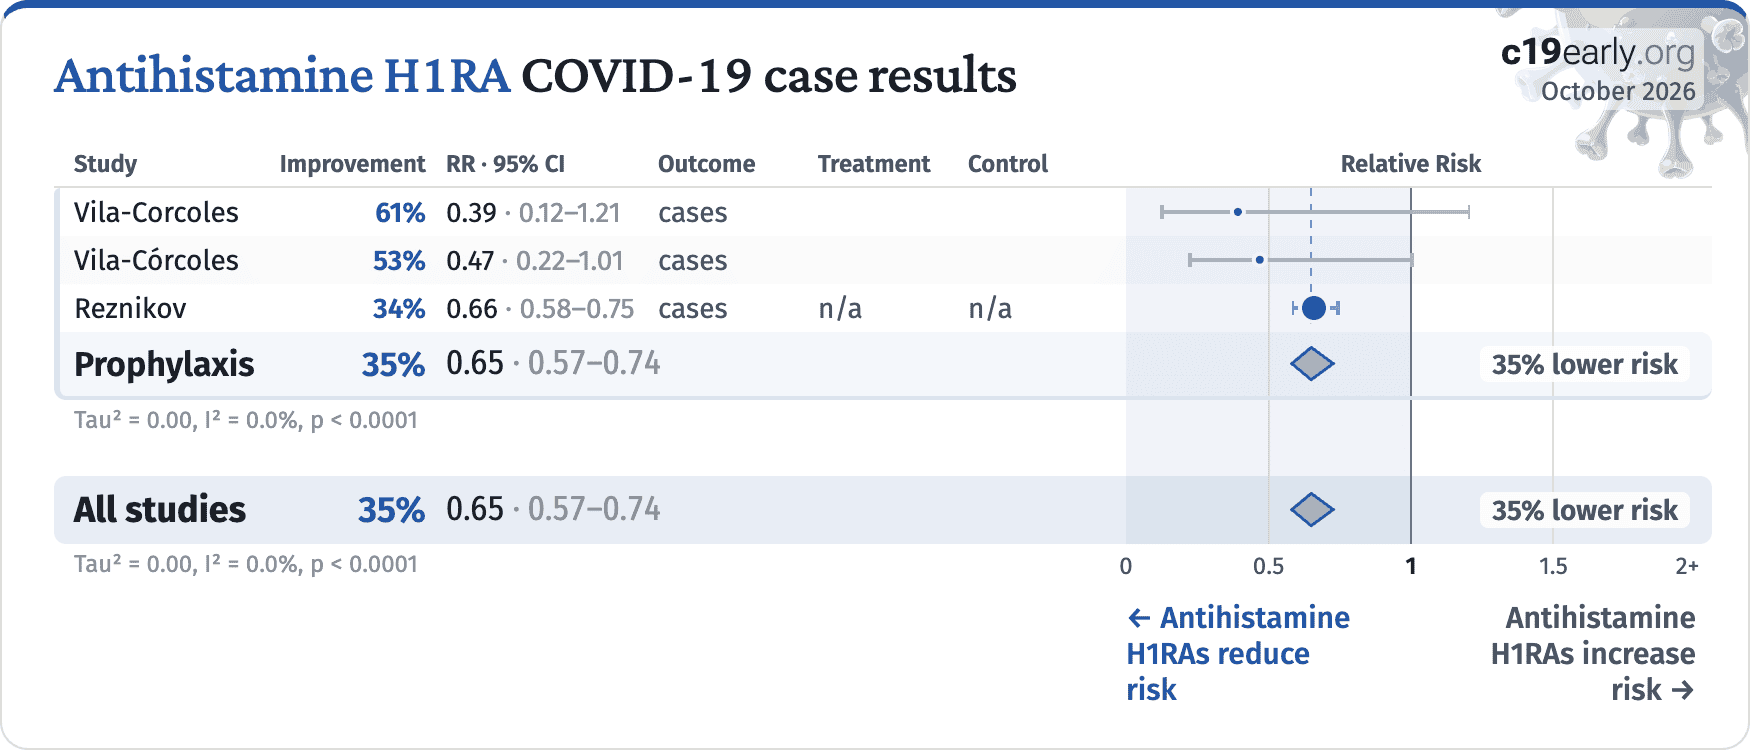
Reznikov, 1/31/2021, retrospective, USA, peer-reviewed, 9 authors.
|
risk of case, 34.0% lower, RR 0.66, p < 0.001, adjusted per study, all medications and age groups combined.
|
|
risk of case, 36.7% lower, OR 0.63, p = 0.01, adjusted per study, inverted to make OR<1 favor treatment, hydroxyzine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 16.7% lower, OR 0.83, p = 0.24, adjusted per study, inverted to make OR<1 favor treatment, hydroxyzine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 47.9% lower, OR 0.52, p = 0.27, adjusted per study, inverted to make OR<1 favor treatment, brompheniramine , 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 52.2% lower, OR 0.48, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, cetirizine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 42.9% lower, OR 0.57, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, cetirizine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 62.3% lower, OR 0.38, p = 0.13, adjusted per study, inverted to make OR<1 favor treatment, fexofenadine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 33.3% higher, OR 1.33, p = 0.58, adjusted per study, inverted to make OR<1 favor treatment, fexofenadine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 34.2% lower, OR 0.66, p = 0.008, adjusted per study, inverted to make OR<1 favor treatment, loratadine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 26.5% lower, OR 0.74, p = 0.04, adjusted per study, inverted to make OR<1 favor treatment, loratadine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 35.5% lower, OR 0.65, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, diphenhydramine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 13.8% lower, OR 0.86, p = 0.13, adjusted per study, inverted to make OR<1 favor treatment, diphenhydramine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 73.6% lower, OR 0.26, p = 0.05, adjusted per study, inverted to make OR<1 favor treatment, levocetirizine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 78.3% lower, OR 0.22, p = 0.0496, adjusted per study, inverted to make OR<1 favor treatment, levocetirizine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 36.3% lower, OR 0.64, p = 0.19, adjusted per study, inverted to make OR<1 favor treatment, chlorpheniramine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 8.3% lower, OR 0.92, p = 0.81, adjusted per study, inverted to make OR<1 favor treatment, chlorpheniramine, 31-60, multivariable, RR approximated with OR.
|
|
risk of case, 58.8% lower, OR 0.41, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 28.6% lower, OR 0.71, p = 0.17, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 31-60, multivariable, RR approximated with OR.
|
|
Sánchez-Rico, 12/15/2021, retrospective, France, peer-reviewed, 20 authors, study period 24 January, 2020 - 1 May, 2020.
|
risk of death, 46.2% lower, RR 0.54, p = 0.02, treatment 18 of 164 (11.0%), control 1,571 of 14,939 (10.5%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Vila-Corcoles, 7/25/2020, retrospective, Spain, peer-reviewed, mean age 70.9, 11 authors, study period 1 March, 2020 - 30 April, 2020.
|
risk of case, 61.0% lower, HR 0.39, p = 0.10, treatment 1,579, control 33,357, adjusted per study, multivariable, Cox proportional hazards.
|
|
Vila-Córcoles, 12/10/2020, retrospective, Spain, peer-reviewed, 10 authors, study period 1 March, 2020 - 23 May, 2020.
|
risk of case, 53.0% lower, HR 0.47, p = 0.05, treatment 3,264, control 75,819, adjusted per study, multivariable, Cox proportional hazards, RR approximated with OR.
|