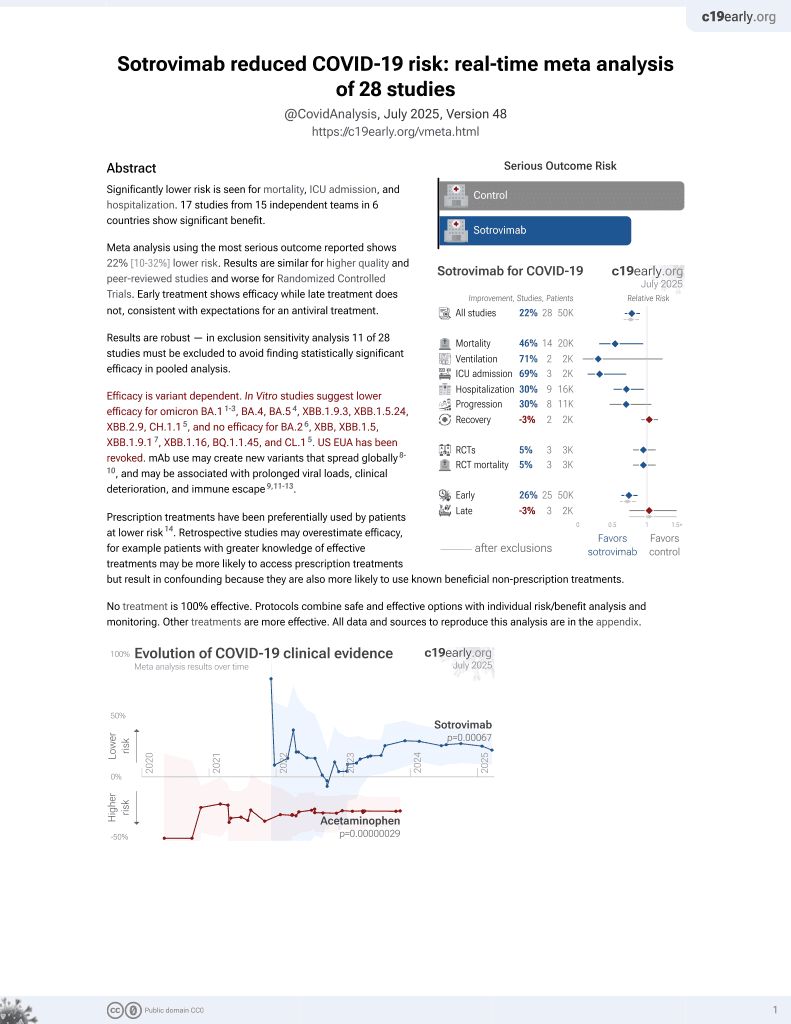
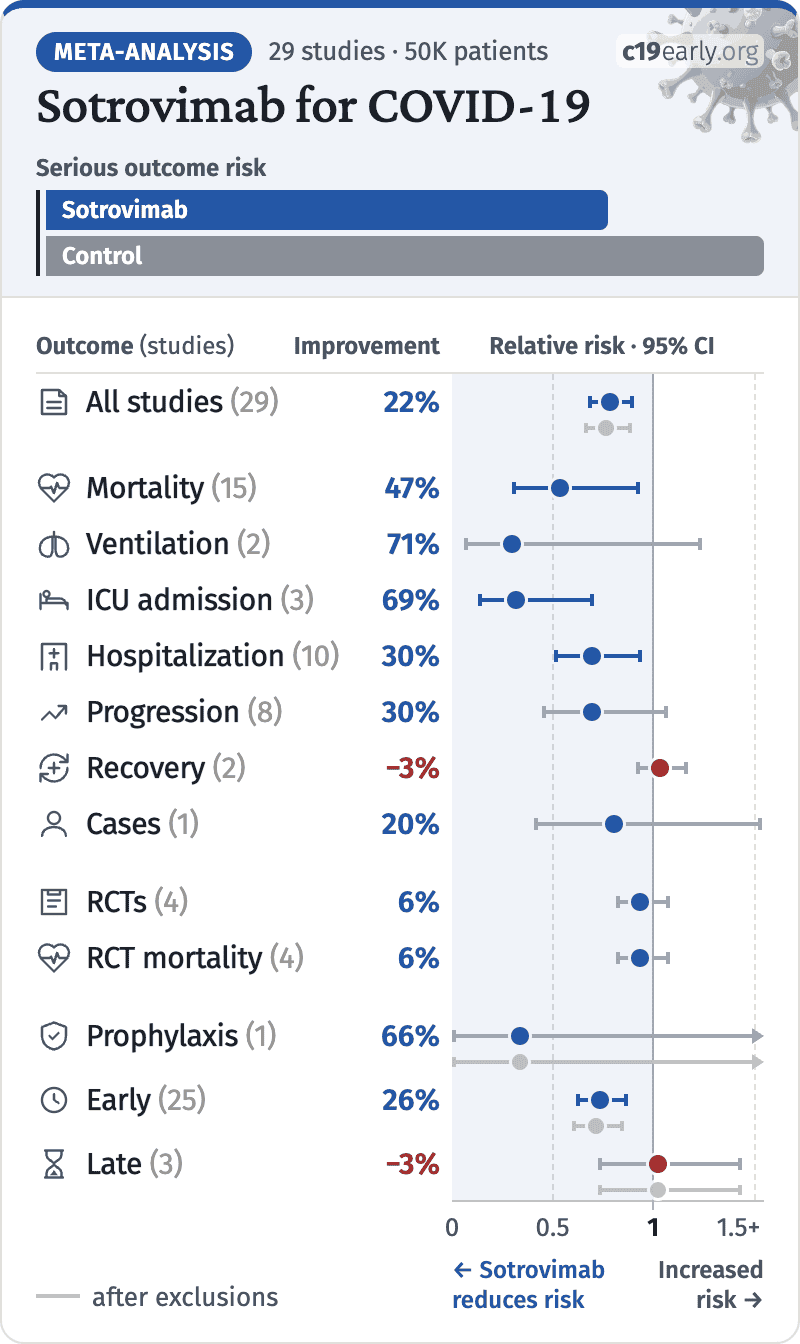
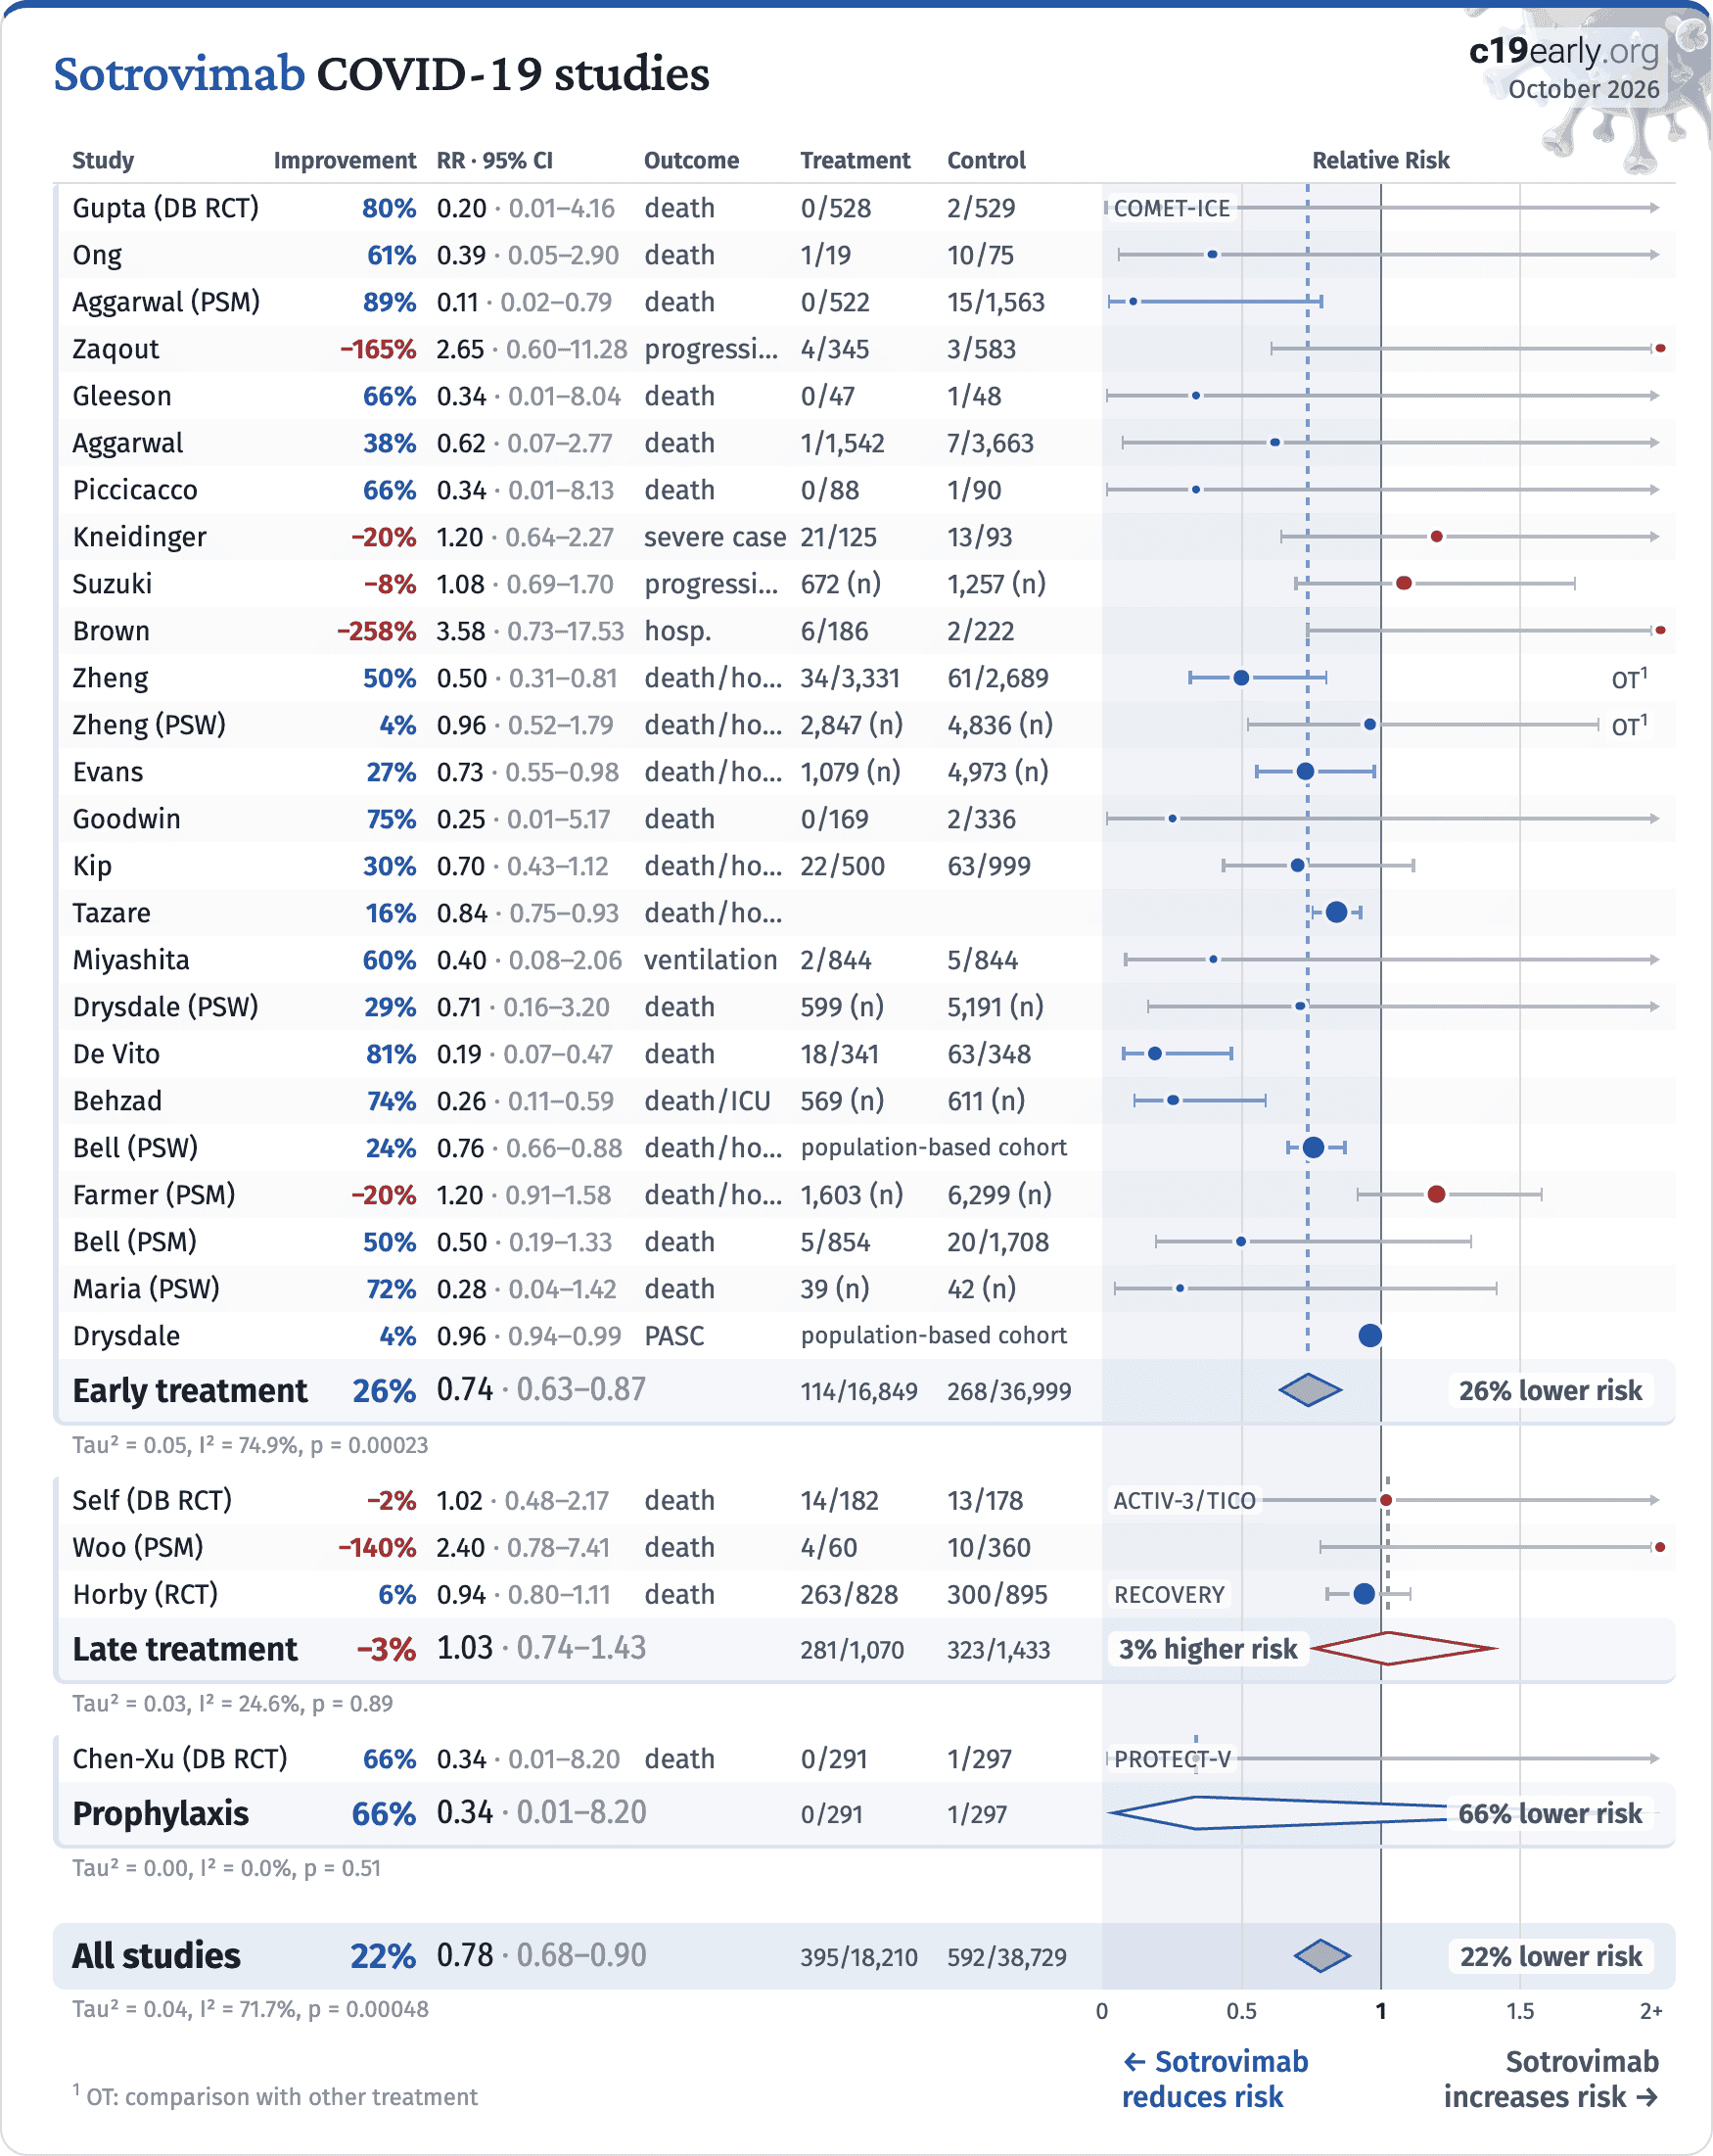
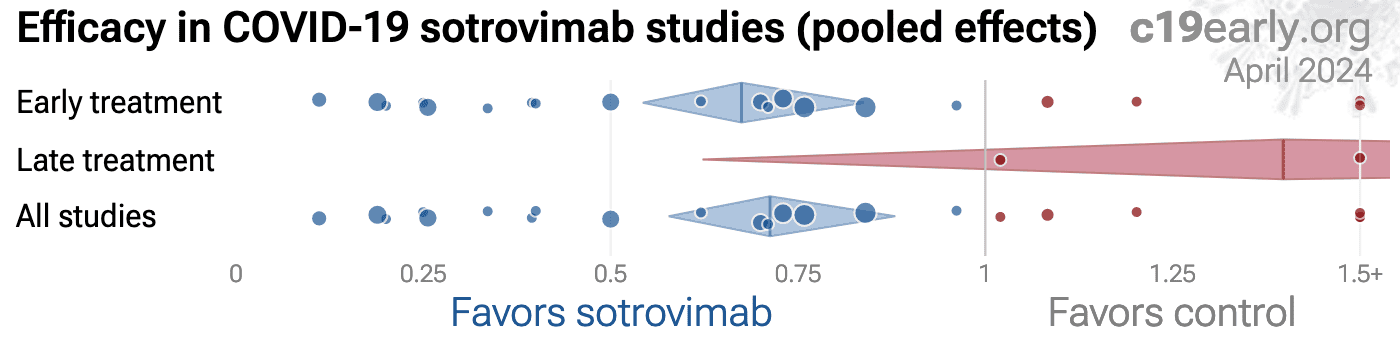
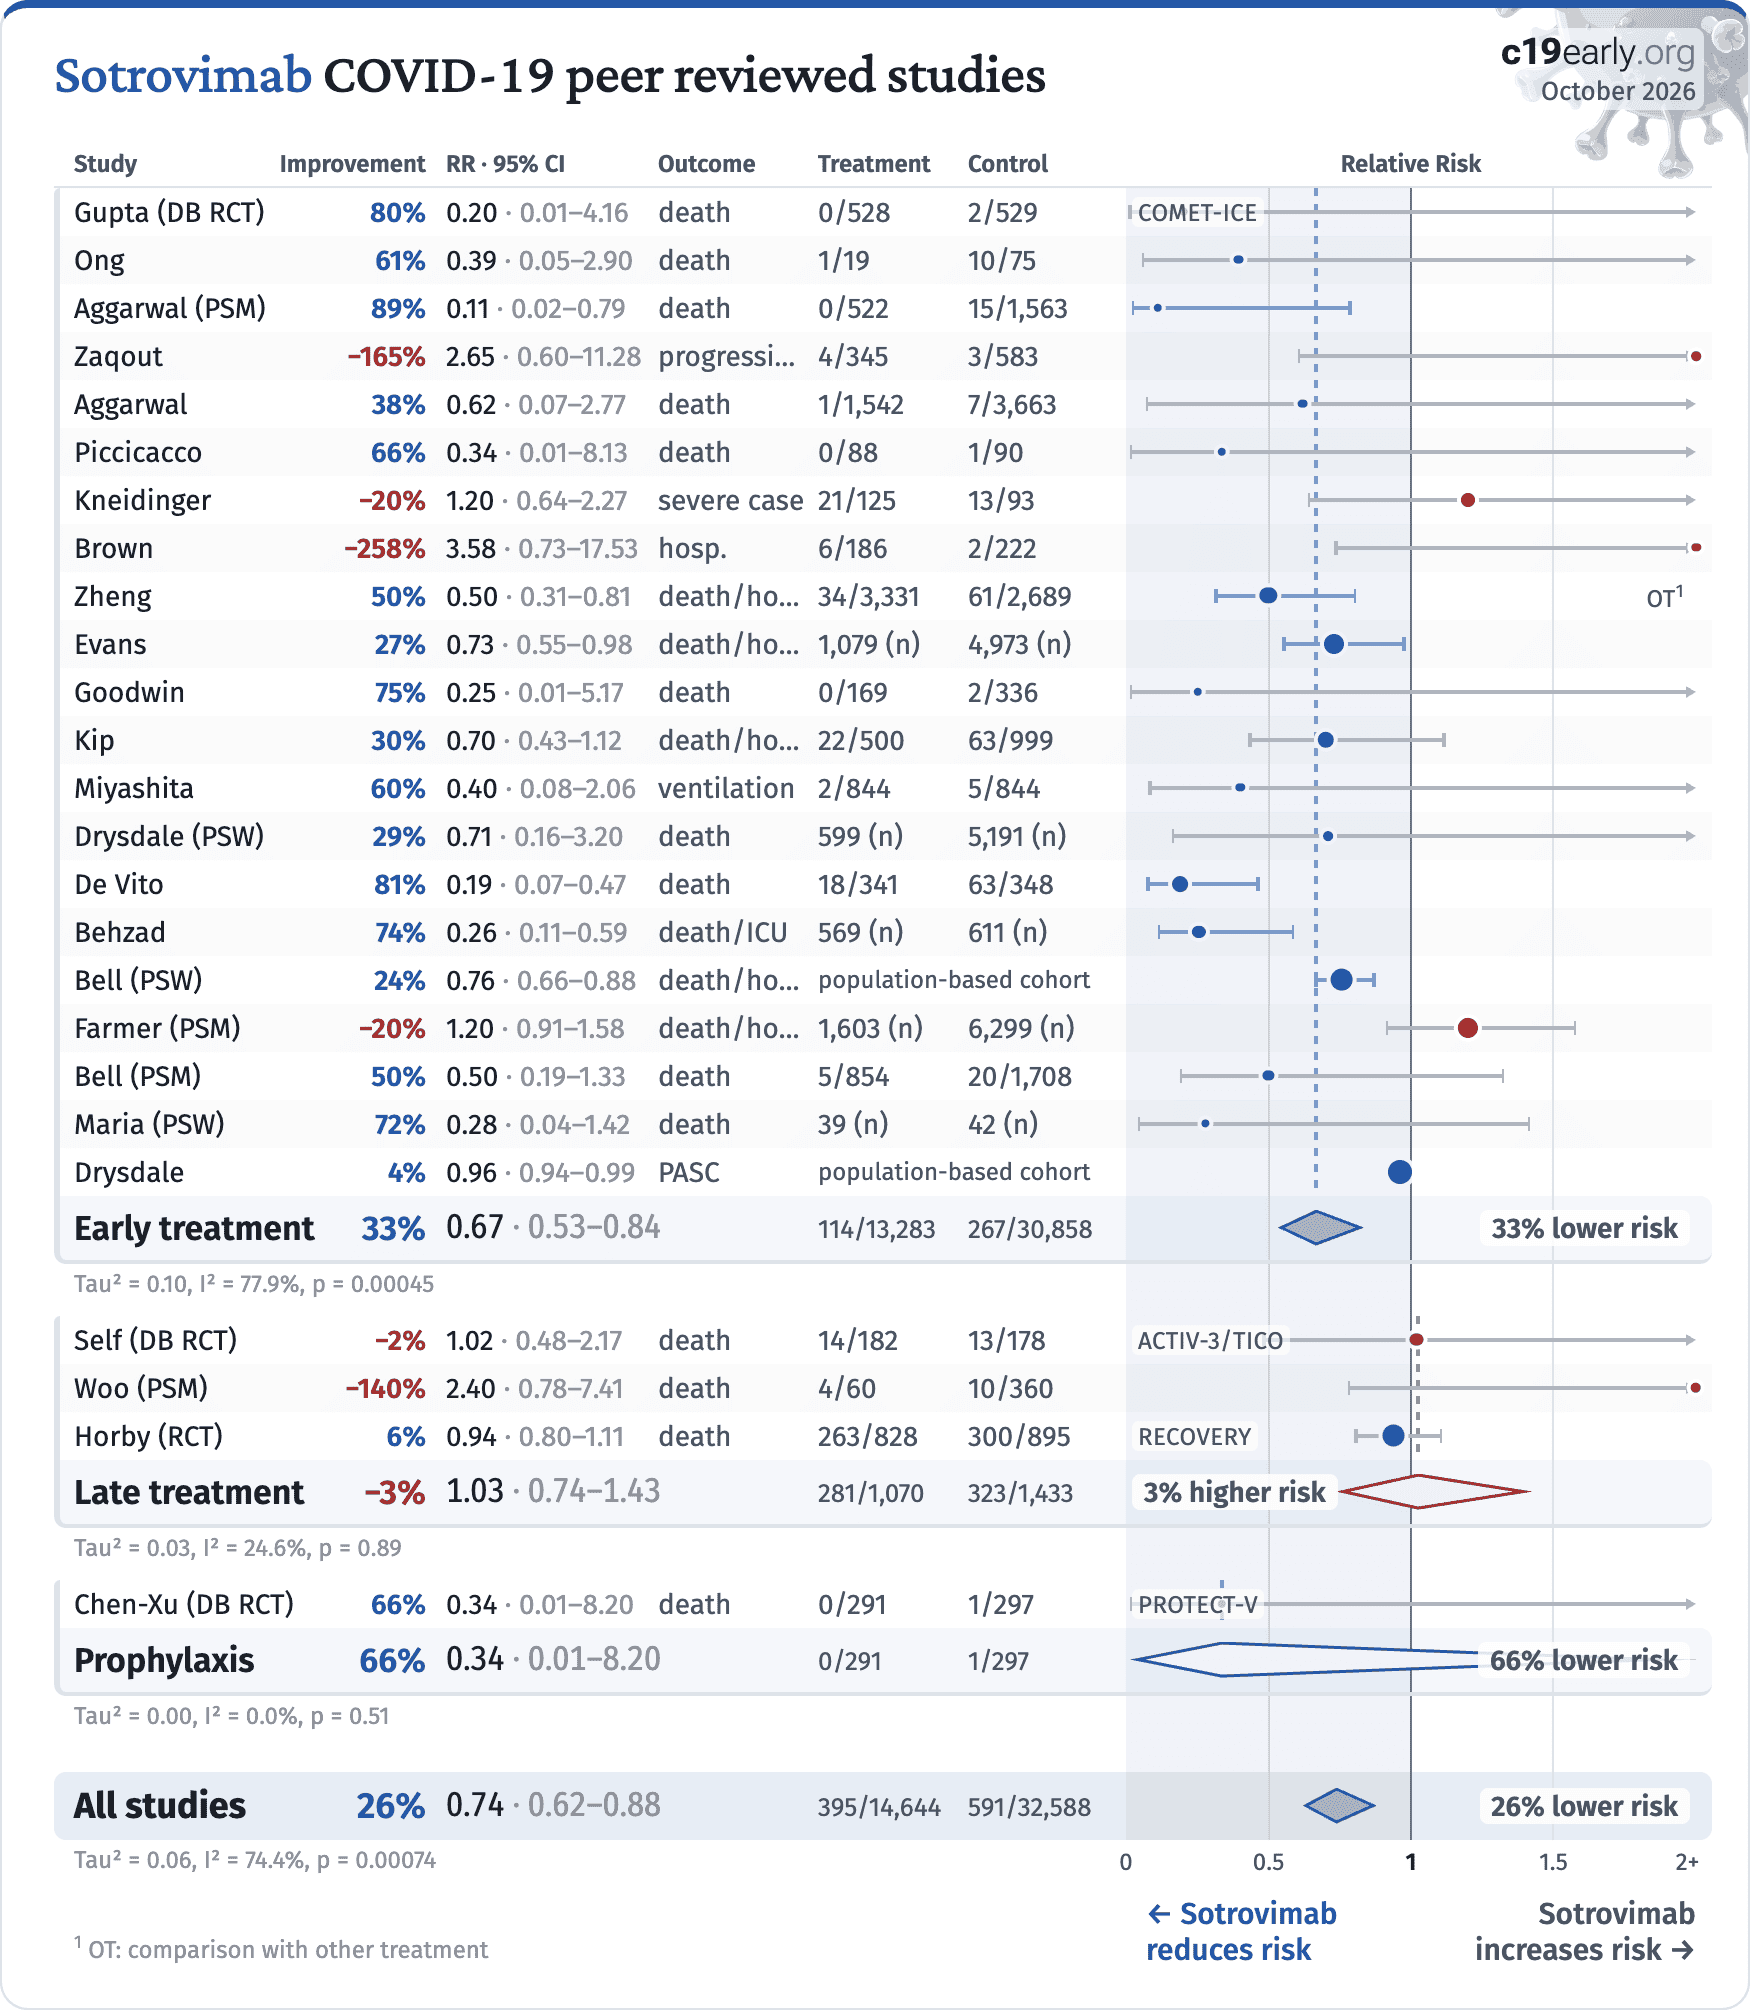
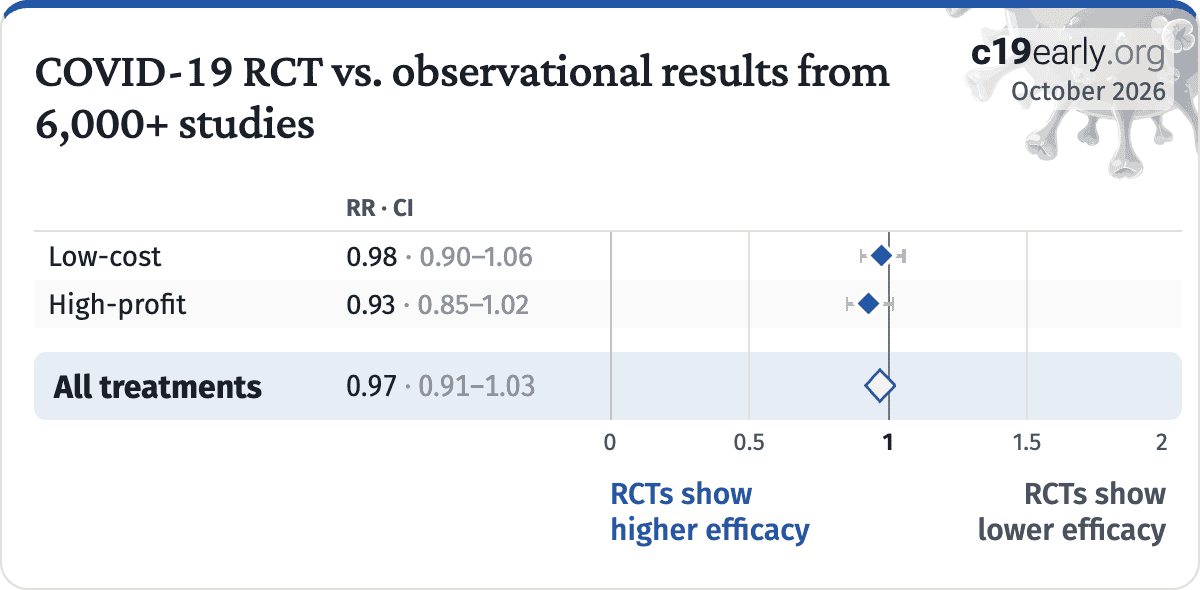
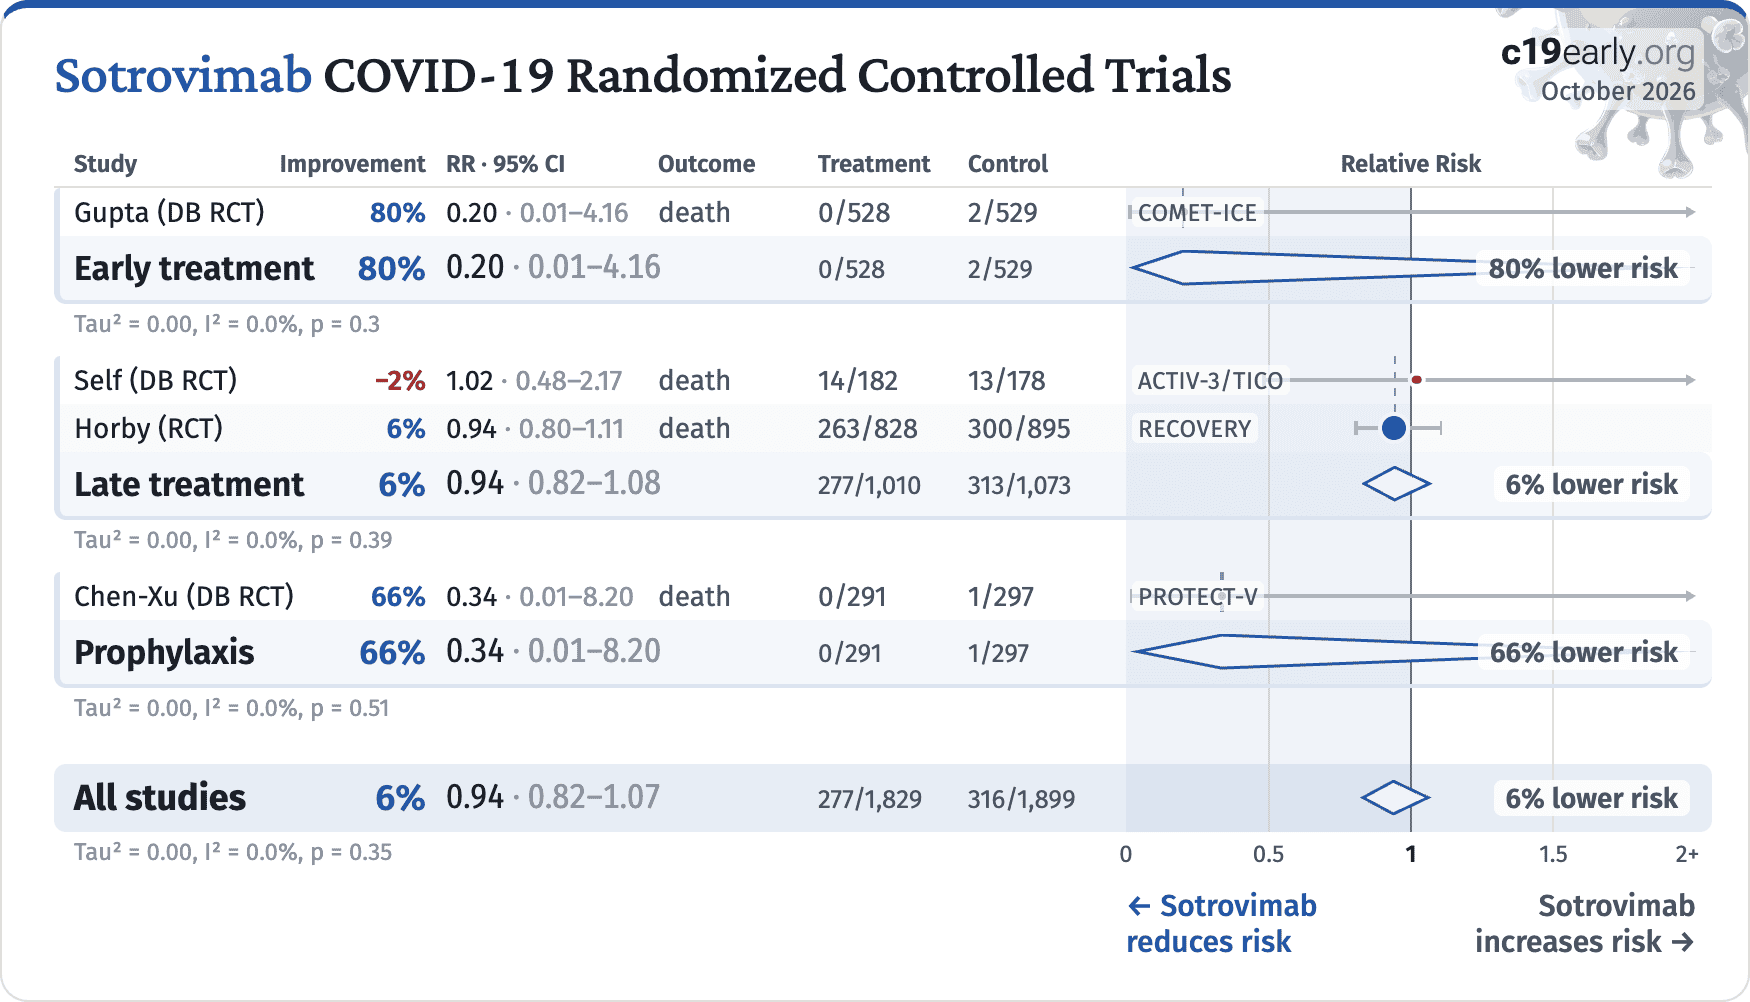
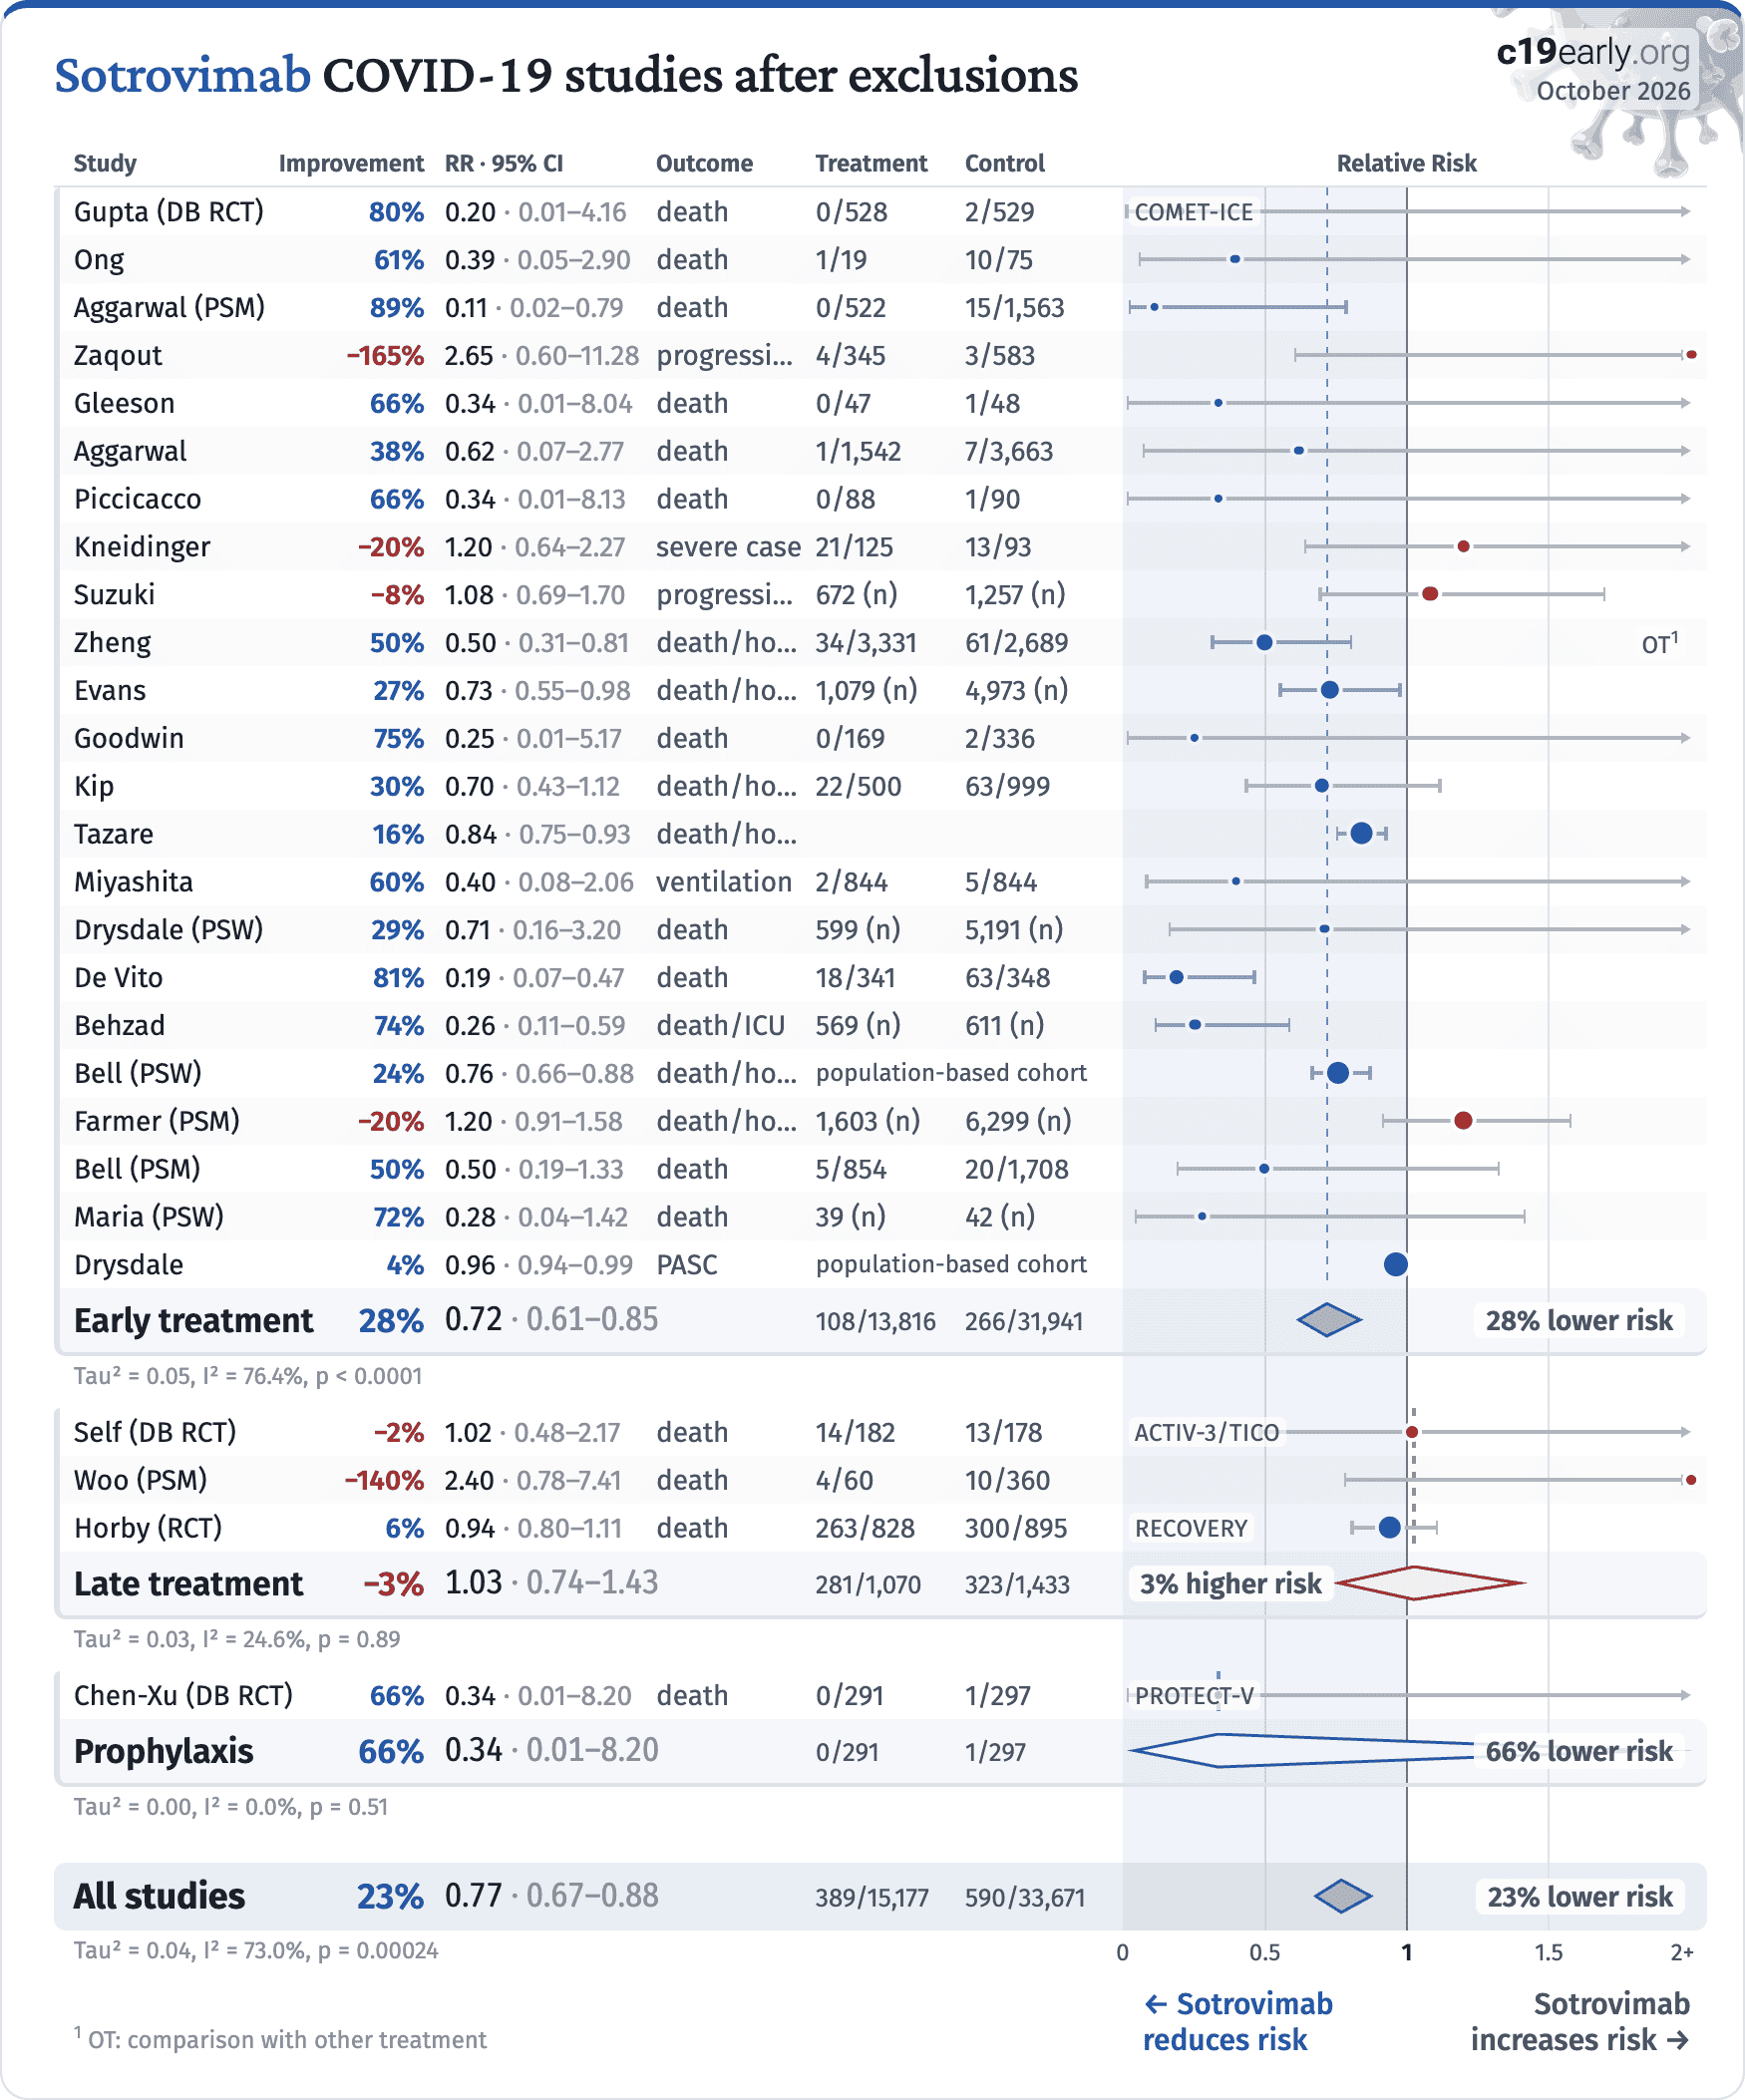
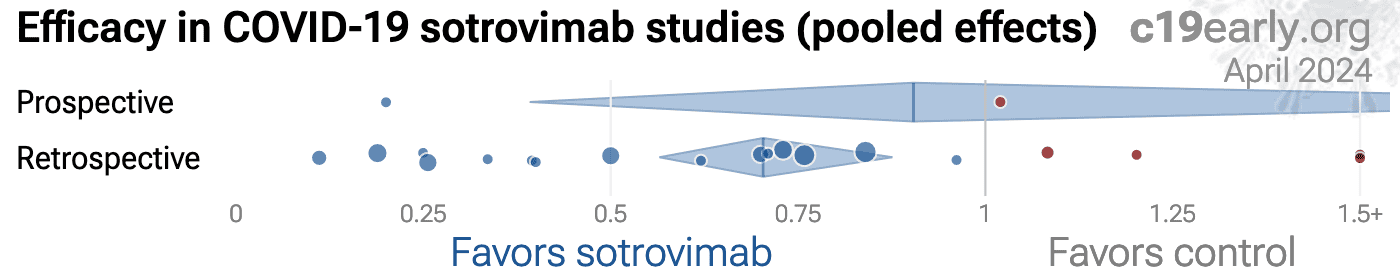
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/vmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Aggarwal, 6/18/2022, retrospective, USA, peer-reviewed, 10 authors, study period 26 December, 2021 - 10 March, 2022.
|
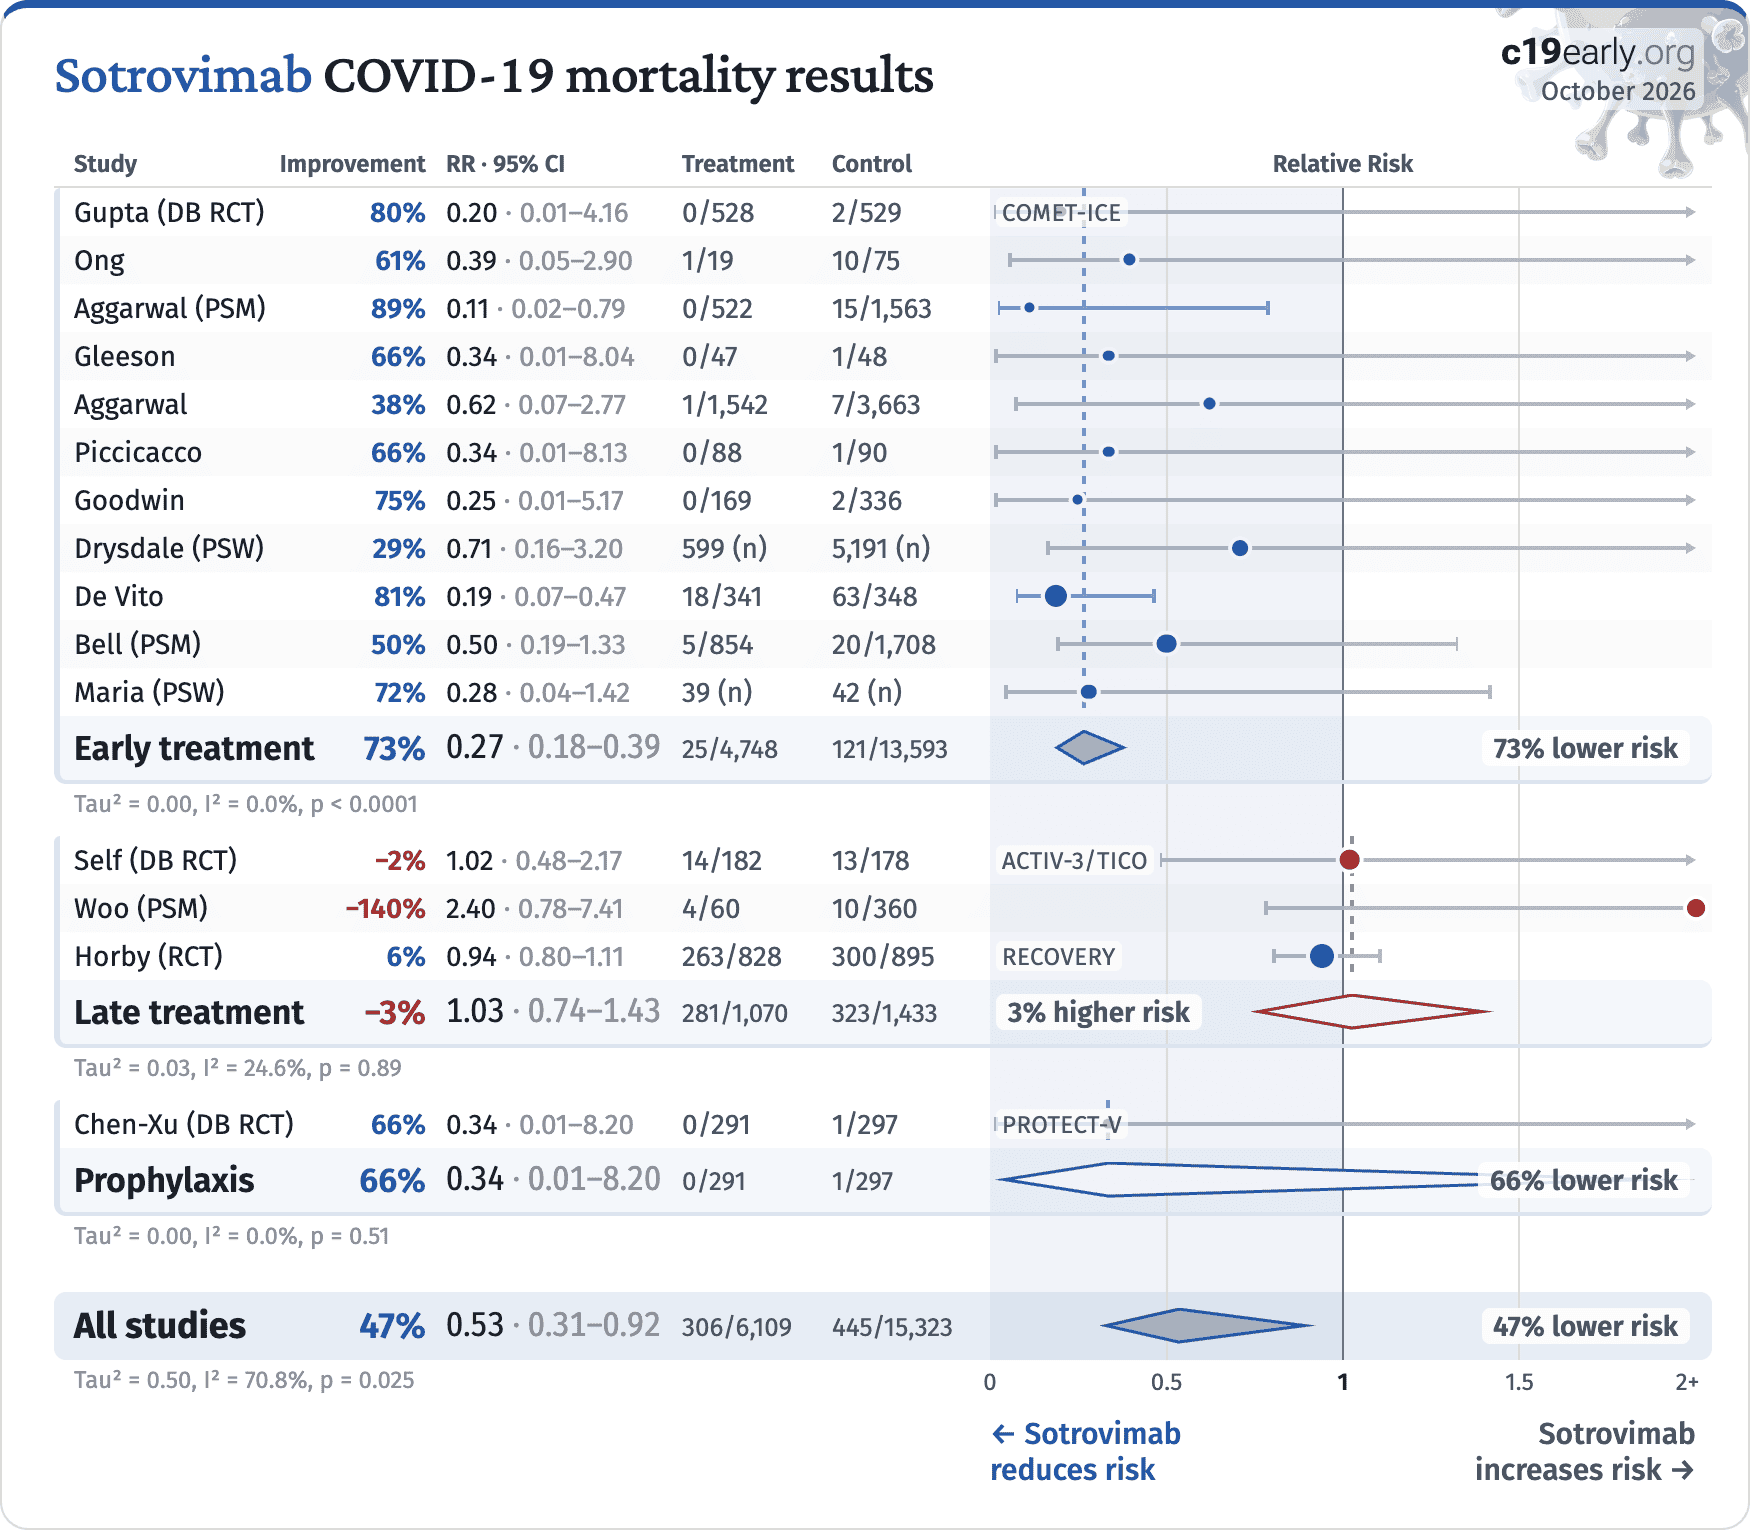
risk of death, 38.0% lower, RR 0.62, p = 0.62, treatment 1 of 1,542 (0.1%), control 7 of 3,663 (0.2%), odds ratio converted to relative risk.
|
|
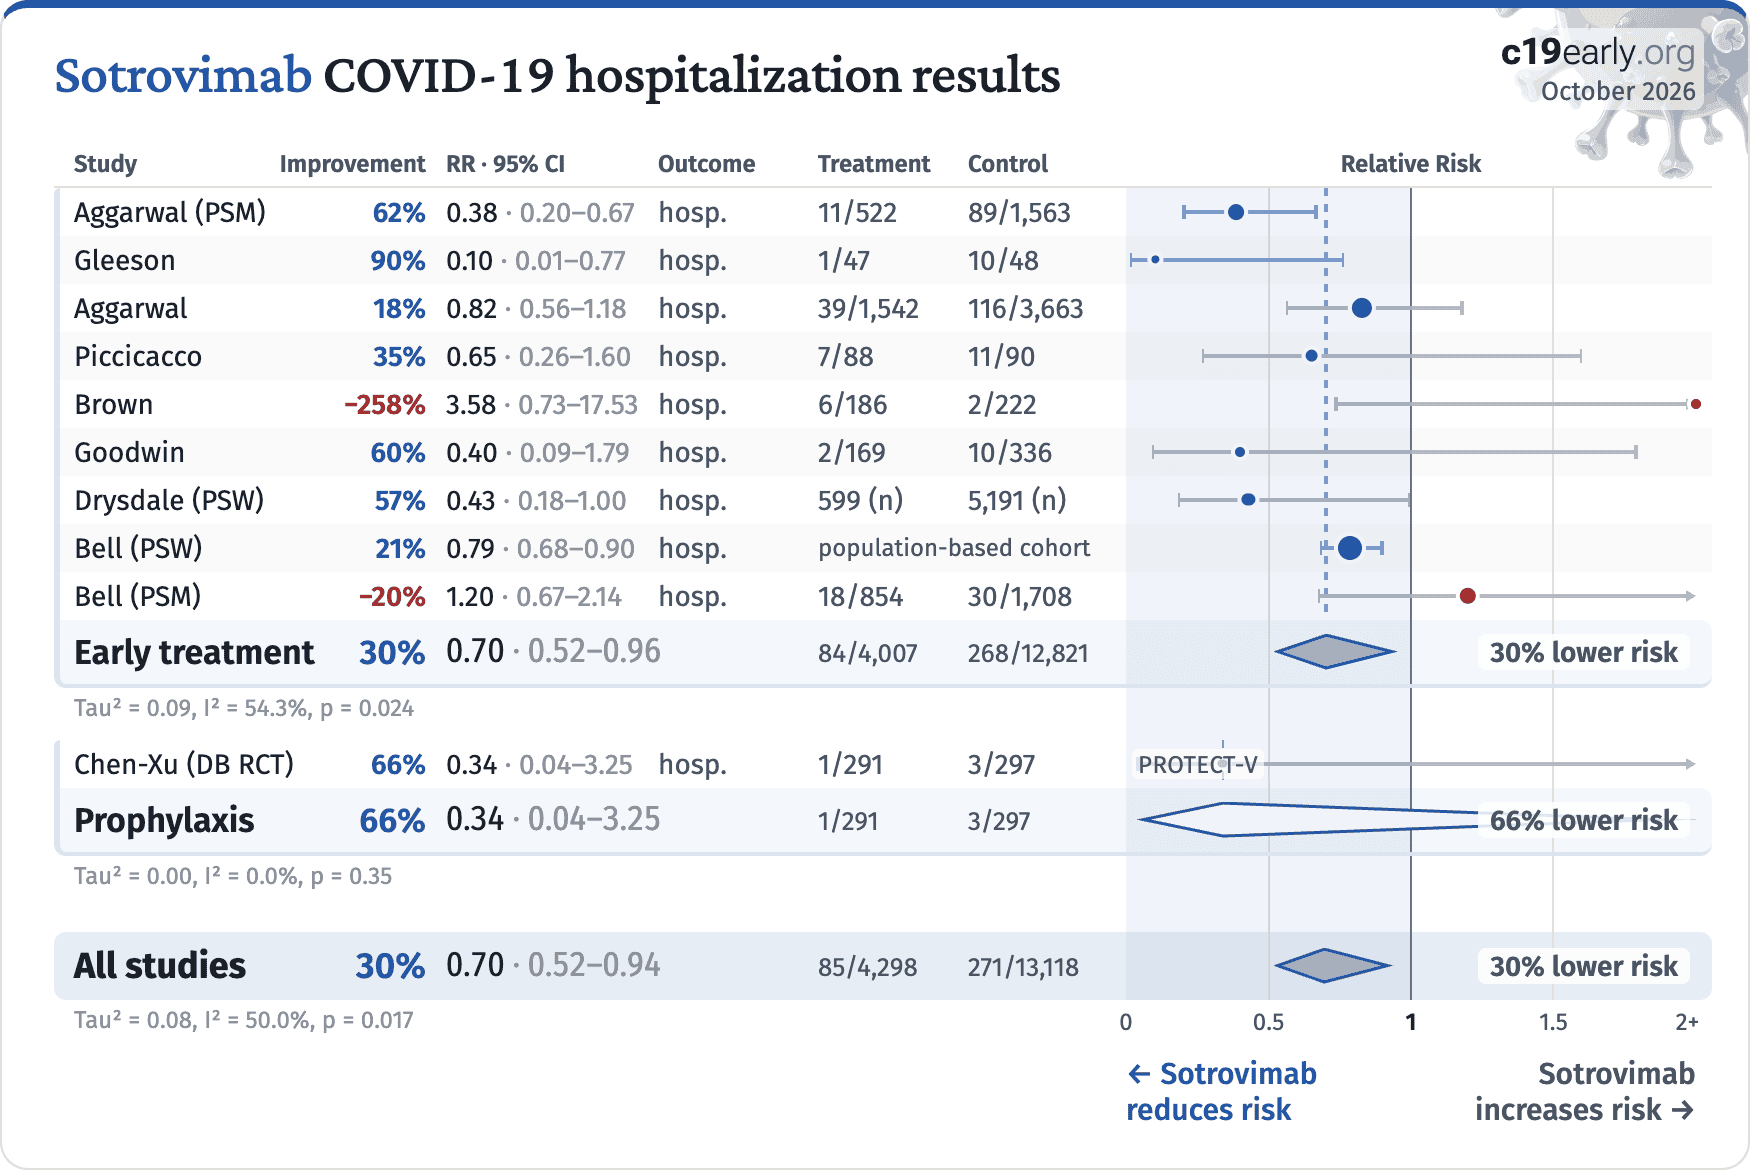
risk of hospitalization, 17.5% lower, RR 0.82, p = 0.32, treatment 39 of 1,542 (2.5%), control 116 of 3,663 (3.2%), NNT 157, odds ratio converted to relative risk, primary outcome.
|
|
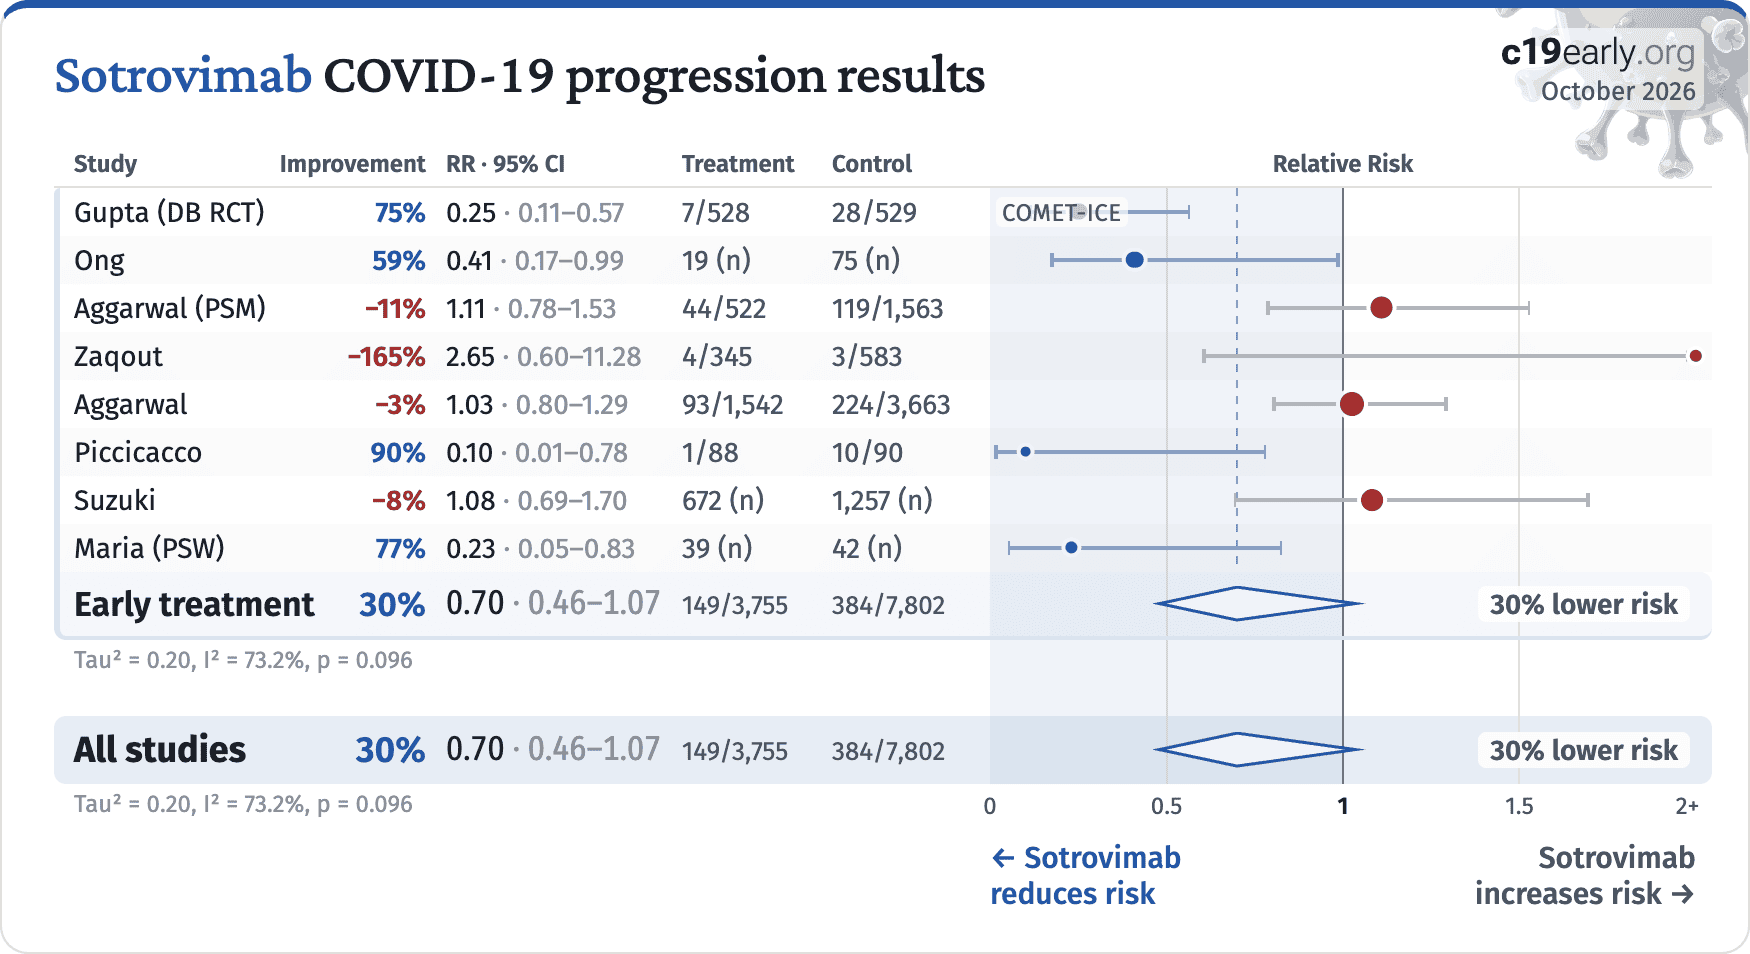
risk of progression, 2.8% higher, RR 1.03, p = 0.83, treatment 93 of 1,542 (6.0%), control 224 of 3,663 (6.1%), NNT 1189, odds ratio converted to relative risk, ED visit.
|
|
Aggarwal (B), 4/5/2022, retrospective, USA, peer-reviewed, 14 authors, study period 1 October, 2021 - 11 December, 2021.
|
risk of death, 88.9% lower, RR 0.11, p = 0.02, treatment 0 of 522 (0.0%), control 15 of 1,563 (1.0%), NNT 104, adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable, day 28.
|
|
risk of hospitalization, 61.6% lower, RR 0.38, p = 0.002, treatment 11 of 522 (2.1%), control 89 of 1,563 (5.7%), NNT 28, adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable, day 28, primary outcome.
|
|
ED visit, 11.0% higher, RR 1.11, p = 0.55, treatment 44 of 522 (8.4%), control 119 of 1,563 (7.6%), adjusted per study, odds ratio converted to relative risk, propensity score matching, multivariable, day 28.
|
|
Behzad, 12/4/2023, retrospective, Bahrain, peer-reviewed, 6 authors, study period 1 January, 2022 - 31 March, 2022.
|
risk of death/ICU, 74.4% lower, HR 0.26, p = 0.001, treatment 569, control 611.
|
|
Bell, 7/16/2024, retrospective, USA, peer-reviewed, 13 authors, study period 26 May, 2021 - 23 April, 2022.
|
risk of death, 50.0% lower, RR 0.50, p = 0.20, treatment 5 of 854 (0.6%), control 20 of 1,708 (1.2%), NNT 171, propensity score matching.
|
|
risk of death/hospitalization, 12.5% lower, RR 0.88, p = 0.70, treatment 21 of 854 (2.5%), control 48 of 1,708 (2.8%), NNT 285, propensity score matching.
|
|
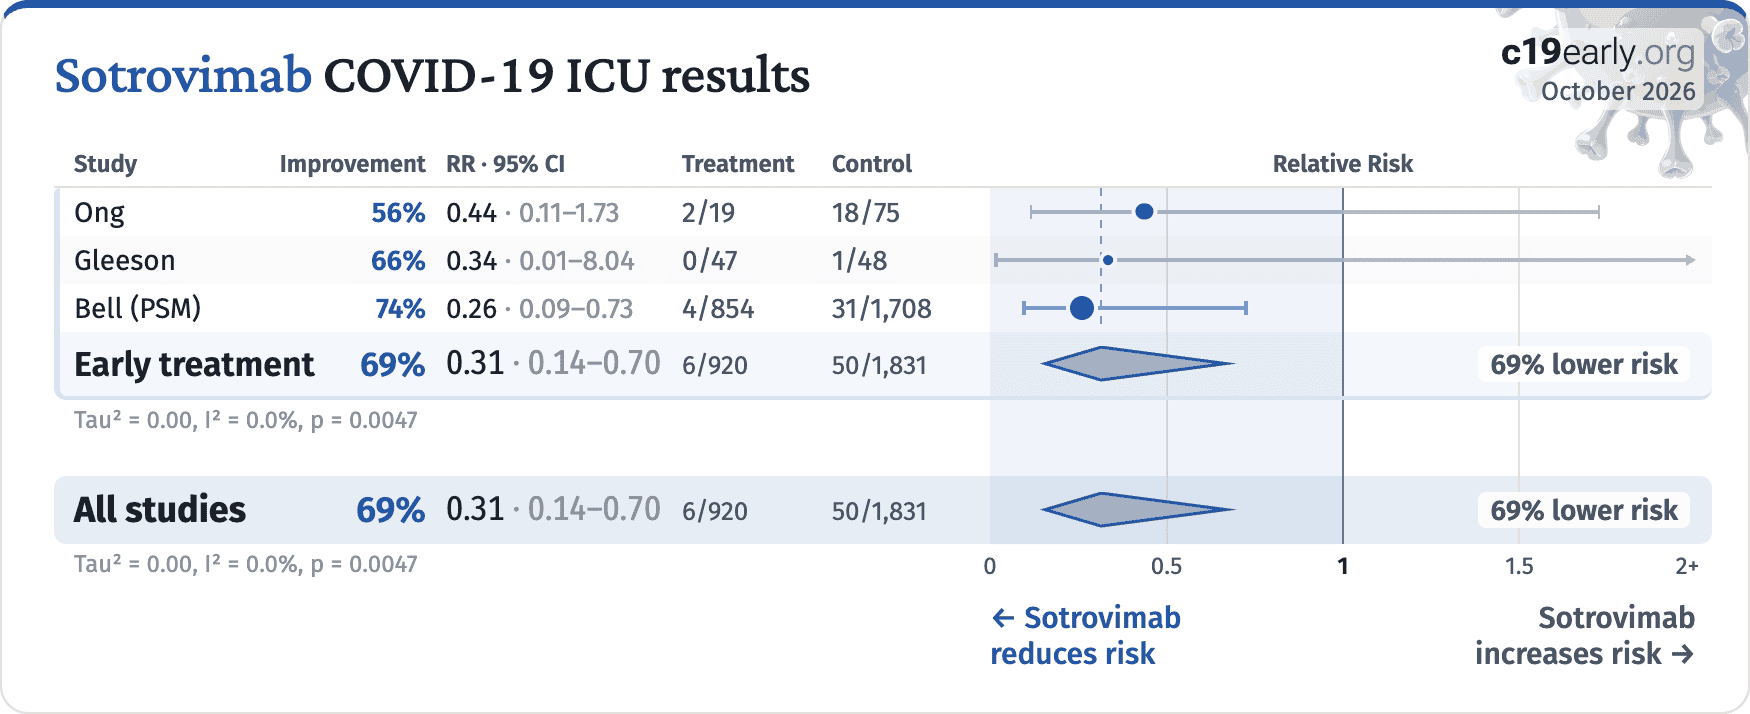
risk of ICU admission, 74.2% lower, RR 0.26, p = 0.006, treatment 4 of 854 (0.5%), control 31 of 1,708 (1.8%), NNT 74, propensity score matching.
|
|
risk of oxygen therapy, 59.5% lower, RR 0.41, p < 0.001, treatment 30 of 854 (3.5%), control 148 of 1,708 (8.7%), NNT 19, propensity score matching.
|
|
risk of hospitalization, 20.0% higher, RR 1.20, p = 0.54, treatment 18 of 854 (2.1%), control 30 of 1,708 (1.8%), propensity score matching.
|
|
Bell (B), 2/20/2024, retrospective, USA, peer-reviewed, 12 authors, study period 27 September, 2021 - 30 April, 2022.
|
risk of death/hospitalization, 24.2% lower, RR 0.76, p < 0.001, NNT 107, odds ratio converted to relative risk, propensity score weighting, day 29.
|
|
risk of hospitalization, 21.3% lower, RR 0.79, p = 0.001, NNT 121, odds ratio converted to relative risk, propensity score weighting, day 29.
|
|
Brown, 10/6/2022, retrospective, United Kingdom, peer-reviewed, 17 authors, excluded in exclusion analyses:
unadjusted results with no group details; significant unadjusted confounding possible.
|
risk of hospitalization, 258.1% higher, RR 3.58, p = 0.15, treatment 6 of 186 (3.2%), control 2 of 222 (0.9%).
|
|
De Vito, 8/17/2023, retrospective, Italy, peer-reviewed, 12 authors, study period 1 January, 2022 - 31 December, 2022, average treatment delay 1.0 days.
|
risk of death, 81.1% lower, RR 0.19, p < 0.001, treatment 18 of 341 (5.3%), control 63 of 348 (18.1%), NNT 7.8, odds ratio converted to relative risk.
|
|
risk of oxygen therapy, 91.8% lower, RR 0.08, p < 0.001, treatment 17 of 341 (5.0%), control 144 of 348 (41.4%), NNT 2.7, odds ratio converted to relative risk.
|
|
Drysdale, 3/22/2025, retrospective, USA, peer-reviewed, 12 authors, study period 26 May, 2021 - 5 April, 2022.
|
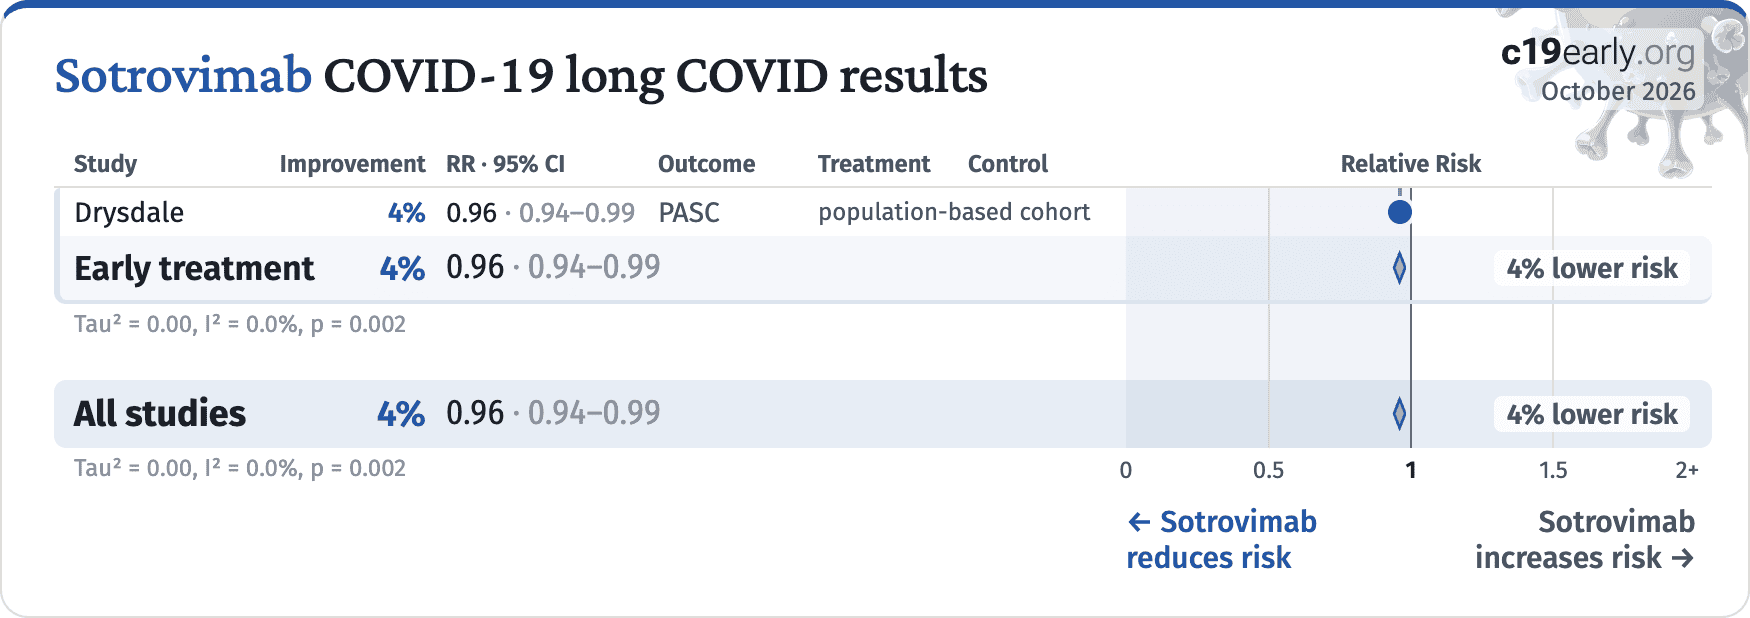
risk of long COVID, 4.0% lower, HR 0.96, p = 0.002, adjusted per study, multivariable, Cox proportional hazards, RR approximated with OR.
|
|
risk of long COVID, 8.0% lower, OR 0.92, p < 0.001, treatment 9,504, control 9,523, ATT, RR approximated with OR.
|
|
Drysdale (B), 7/27/2023, retrospective, United Kingdom, peer-reviewed, 14 authors, study period August 2020 - March 2021.
|
risk of death, 29.0% lower, HR 0.71, p = 0.65, treatment 599, control 5,191, propensity score weighting, Cox proportional hazards.
|
|
risk of death/hospitalization, 50.0% lower, HR 0.50, p = 0.07, treatment 599, control 5,191, propensity score weighting, Cox proportional hazards.
|
|
risk of hospitalization, 57.0% lower, HR 0.43, p = 0.05, treatment 599, control 5,191, propensity score weighting, Cox proportional hazards.
|
|
Evans, 1/25/2023, retrospective, United Kingdom, peer-reviewed, 11 authors, study period 16 December, 2021 - 22 April, 2022.
|
risk of death/hospitalization, 27.0% lower, HR 0.73, p = 0.03, treatment 1,079, control 4,973, Cox proportional hazards.
|
|
Farmer, 6/19/2024, retrospective, Canada, peer-reviewed, 14 authors, study period 15 December, 2021 - 30 April, 2022.
|
risk of death/hospitalization, 20.0% higher, OR 1.20, p = 0.20, treatment 1,603, control 6,299, adjusted per study, propensity score matching, multivariable, RR approximated with OR.
|
|
Gleeson, 5/3/2022, prospective, United Kingdom, preprint, 14 authors, study period 21 December, 2021 - 10 February, 2022.
|
risk of death, 66.4% lower, RR 0.34, p = 1.00, treatment 0 of 47 (0.0%), control 1 of 48 (2.1%), NNT 48, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), COVID-19.
|
|
risk of death, 79.8% lower, RR 0.20, p = 0.49, treatment 0 of 47 (0.0%), control 2 of 48 (4.2%), NNT 24, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), all cause.
|
|
risk of ICU admission, 66.4% lower, RR 0.34, p = 1.00, treatment 0 of 47 (0.0%), control 1 of 48 (2.1%), NNT 48, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 89.8% lower, RR 0.10, p = 0.008, treatment 1 of 47 (2.1%), control 10 of 48 (20.8%), NNT 5.3.
|
|
Goodwin, 3/15/2023, retrospective, United Kingdom, peer-reviewed, 3 authors, study period 22 December, 2021 - 20 February, 2022.
|
risk of death, 75.0% lower, RR 0.25, p = 0.55, treatment 0 of 169 (0.0%), control 2 of 336 (0.6%), NNT 168, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of hospitalization, 60.2% lower, RR 0.40, p = 0.35, treatment 2 of 169 (1.2%), control 10 of 336 (3.0%), NNT 56, COVID-19 related.
|
|
risk of hospitalization, 21.5% higher, RR 1.21, p = 0.69, treatment 11 of 169 (6.5%), control 18 of 336 (5.4%), all cause.
|
|
Gupta, 12/4/2021, Double Blind Randomized Controlled Trial, placebo-controlled, multiple countries, peer-reviewed, 68 authors, study period 27 August, 2020 - 2 September, 2021, average treatment delay 2.6 days, trial NCT04545060 (history) (COMET-ICE), conflicts of interest:
research funding from the drug patent holder, employee of the drug patent holder.
|
risk of death, 80.0% lower, RR 0.20, p = 0.50, treatment 0 of 528 (0.0%), control 2 of 529 (0.4%), NNT 264, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 29.
|
|
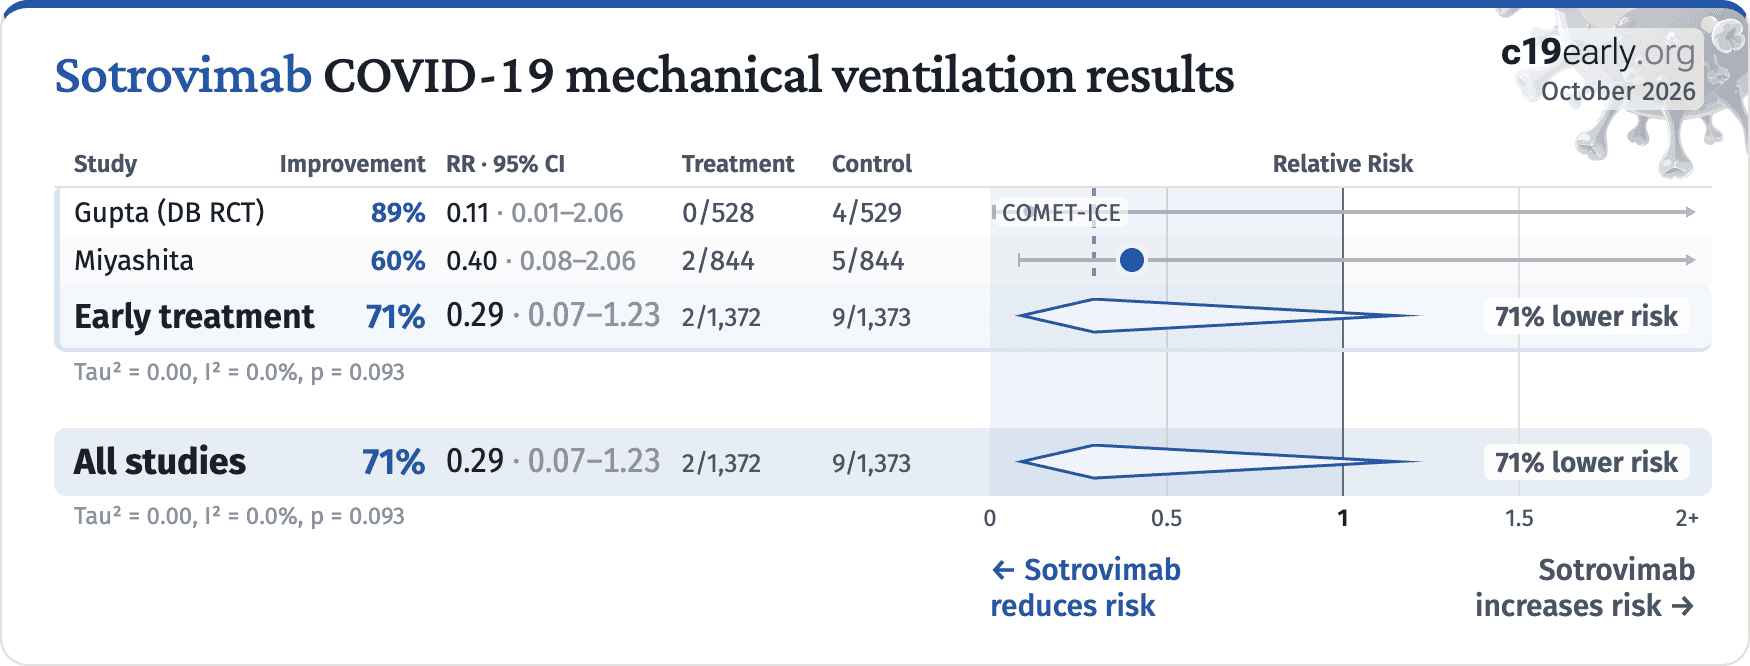
risk of mechanical ventilation, 88.9% lower, RR 0.11, p = 0.12, treatment 0 of 528 (0.0%), control 4 of 529 (0.8%), NNT 132, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 29.
|
|
risk of progression, 75.0% lower, RR 0.25, p < 0.001, treatment 7 of 528 (1.3%), control 28 of 529 (5.3%), NNT 25, day 29.
|
|
risk of hospitalization >24hrs or death, 79.0% lower, RR 0.21, p < 0.001, treatment 6 of 528 (1.1%), control 30 of 529 (5.7%), NNT 22, day 29, ITT, primary outcome.
|
|
Kip, 4/4/2023, retrospective, USA, peer-reviewed, 16 authors, study period 8 December, 2020 - 31 August, 2022.
|
risk of death/hospitalization, 30.0% lower, RR 0.70, p = 0.14, treatment 22 of 500 (4.4%), control 63 of 999 (6.3%), NNT 52, delta and omicron variants, day 28.
|
|
Kneidinger, 9/9/2022, retrospective, Germany, peer-reviewed, 11 authors, study period 1 January, 2022 - 20 March, 2022, lung transplant patients.
|
risk of severe case, 20.2% higher, RR 1.20, p = 0.79, treatment 21 of 125 (16.8%), control 13 of 93 (14.0%).
|
|
Maria, 10/4/2024, retrospective, Italy, peer-reviewed, 10 authors, study period 1 January, 2022 - 31 December, 2023, average treatment delay 2.0 days.
|
risk of death, 72.0% lower, OR 0.28, p = 0.15, treatment 39, control 42, propensity score weighting, RR approximated with OR.
|
|
risk of progression, 77.0% lower, OR 0.23, p = 0.03, treatment 39, control 42, propensity score weighting, RR approximated with OR.
|
|
Miyashita, 5/31/2023, retrospective, Japan, peer-reviewed, 7 authors, study period December 2021 - July 2022.
|
risk of mechanical ventilation, 60.0% lower, RR 0.40, p = 0.45, treatment 2 of 844 (0.2%), control 5 of 844 (0.6%), NNT 281, all.
|
|
risk of mechanical ventilation, 33.3% lower, RR 0.67, p = 1.00, treatment 2 of 642 (0.3%), control 3 of 642 (0.5%), NNT 642, BA.1.
|
|
risk of mechanical ventilation, 80.0% lower, RR 0.20, p = 0.50, treatment 0 of 202 (0.0%), control 2 of 202 (1.0%), NNT 101, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), BA.2.
|
|
risk of oxygen therapy, 55.3% lower, RR 0.45, p < 0.001, treatment 34 of 844 (4.0%), control 76 of 844 (9.0%), NNT 20, all.
|
|
risk of oxygen therapy, 53.6% lower, RR 0.46, p < 0.001, treatment 26 of 642 (4.0%), control 56 of 642 (8.7%), NNT 21, BA.1.
|
|
risk of oxygen therapy, 60.0% lower, RR 0.40, p = 0.03, treatment 8 of 202 (4.0%), control 20 of 202 (9.9%), NNT 17, BA.2.
|
|
Ong, 3/5/2022, retrospective, Singapore, peer-reviewed, 10 authors, average treatment delay 2.0 days.
|
risk of death, 60.5% lower, RR 0.39, p = 0.45, treatment 1 of 19 (5.3%), control 10 of 75 (13.3%), NNT 12.
|
|
risk of ICU admission, 56.1% lower, RR 0.44, p = 0.35, treatment 2 of 19 (10.5%), control 18 of 75 (24.0%), NNT 7.4.
|
|
risk of progression, 59.0% lower, HR 0.41, p = 0.047, treatment 19, control 75, Cox proportional hazards.
|
|
Piccicacco, 8/1/2022, retrospective, USA, peer-reviewed, 7 authors, study period 27 December, 2021 - 4 February, 2022, average treatment delay 4.4 days.
|
risk of death, 66.4% lower, RR 0.34, p = 1.00, treatment 0 of 88 (0.0%), control 1 of 90 (1.1%), NNT 90, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 29.
|
|
risk of hospitalization, 34.9% lower, RR 0.65, p = 0.46, treatment 7 of 88 (8.0%), control 11 of 90 (12.2%), NNT 23, day 29.
|
|
risk of hospitalization/ER, 66.3% lower, RR 0.34, p = 0.01, treatment 7 of 88 (8.0%), control 21 of 90 (23.3%), NNT 6.5, odds ratio converted to relative risk, day 29.
|
|
risk of progression, 89.8% lower, RR 0.10, p = 0.009, treatment 1 of 88 (1.1%), control 10 of 90 (11.1%), NNT 10, ER visit, day 29.
|
|
Suzuki, 10/5/2022, retrospective, Japan, preprint, 53 authors.
|
risk of progression, 8.3% higher, OR 1.08, p = 0.73, treatment 672, control 1,257, adjusted per study, multivariable, RR approximated with OR.
|
|
Tazare, 5/16/2023, retrospective, United Kingdom, preprint, 31 authors, study period 16 December, 2021 - 21 May, 2022.
|
risk of death/hospitalization, 16.0% lower, HR 0.84, p = 0.002, treatment 6,408, control 65,568.
|
|
Zaqout, 4/21/2022, retrospective, Qatar, peer-reviewed, median age 40.0, 17 authors, study period 20 October, 2021 - 28 February, 2022.
|
risk of progression, 164.7% higher, RR 2.65, p = 0.19, treatment 4 of 345 (1.2%), control 3 of 583 (0.5%), adjusted per study, odds ratio converted to relative risk, progression to severe/critical disease or mortality.
|
|
Zheng, 1/22/2023, retrospective, United Kingdom, preprint, mean age 54.3, 9 authors, study period 11 February, 2022 - 1 October, 2022, this trial compares with another treatment - results may be better when compared to placebo, excluded in exclusion analyses:
study compares against another treatment showing significant efficacy.
|
risk of death/hospitalization, 3.8% lower, HR 0.96, p = 0.91, treatment 2,847, control 4,836, inverted to make HR<1 favor treatment, COVID-19 related, propensity score weighting, Cox proportional hazards, day 60, model 4.
|
|
risk of death/hospitalization, 13.6% higher, HR 1.14, p = 0.70, treatment 19 of 2,847 (0.7%), control 33 of 4,836 (0.7%), inverted to make HR<1 favor treatment, COVID-19 related, propensity score weighting, Cox proportional hazards, day 28, model 4.
|
|
Zheng (B), 11/16/2022, retrospective, United Kingdom, peer-reviewed, mean age 52.0, 33 authors, study period 16 December, 2021 - 10 February, 2022, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death/hospitalization, 50.0% lower, HR 0.50, p = 0.005, treatment 34 of 3,331 (1.0%), control 61 of 2,689 (2.3%), NNT 80, adjusted per study, multivariable, Cox proportional hazards, day 60, model 4.
|
|
risk of death/hospitalization, 46.0% lower, HR 0.54, p = 0.01, treatment 32 of 3,331 (1.0%), control 55 of 2,689 (2.0%), NNT 92, adjusted per study, multivariable, Cox proportional hazards, day 28, model 4.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.