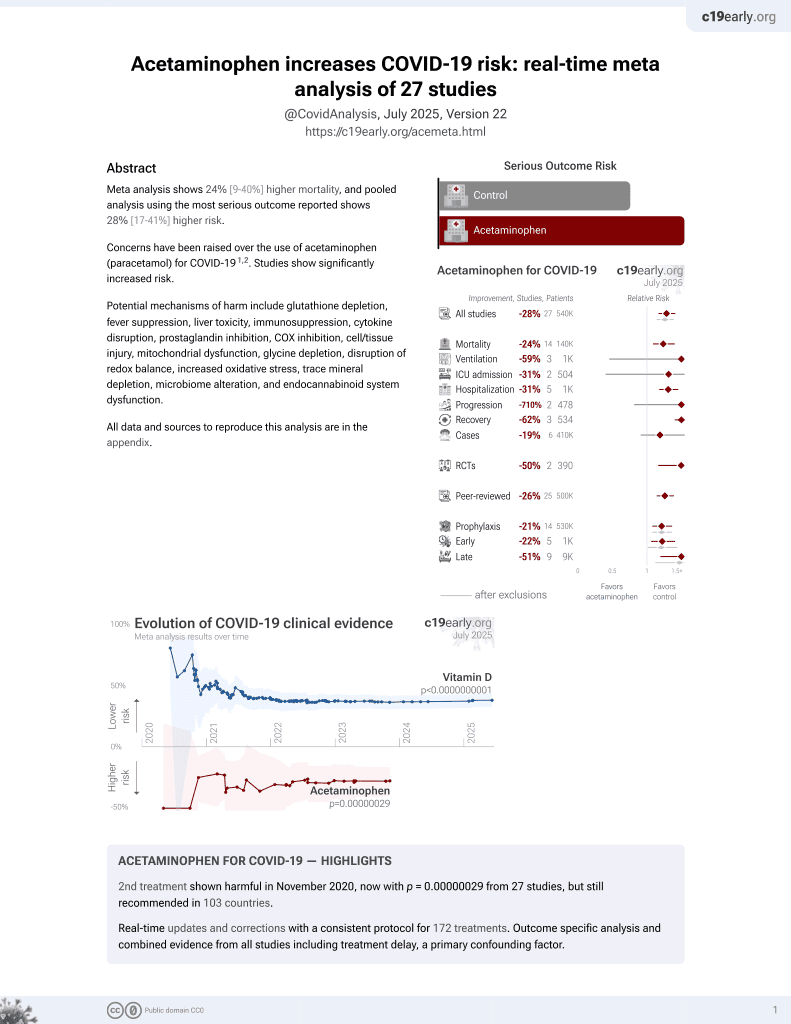
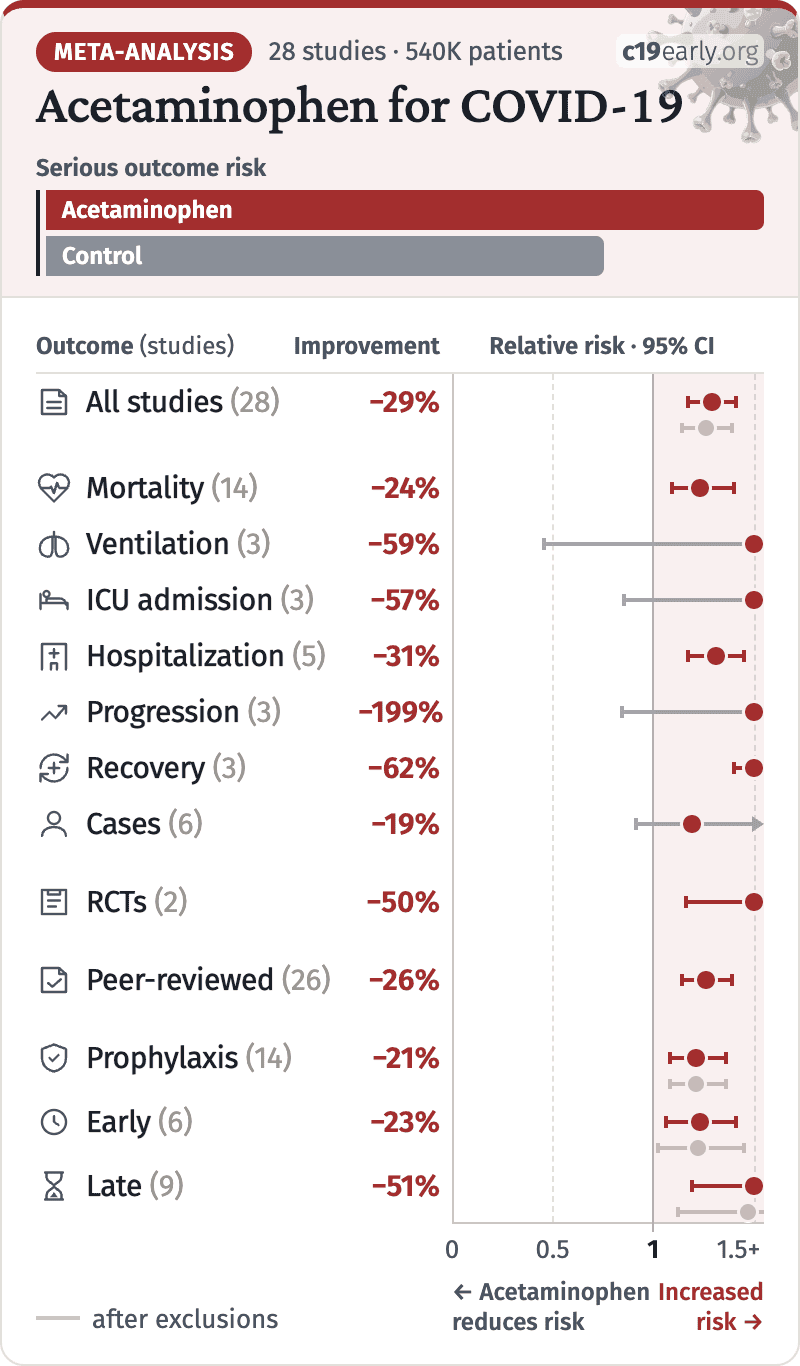
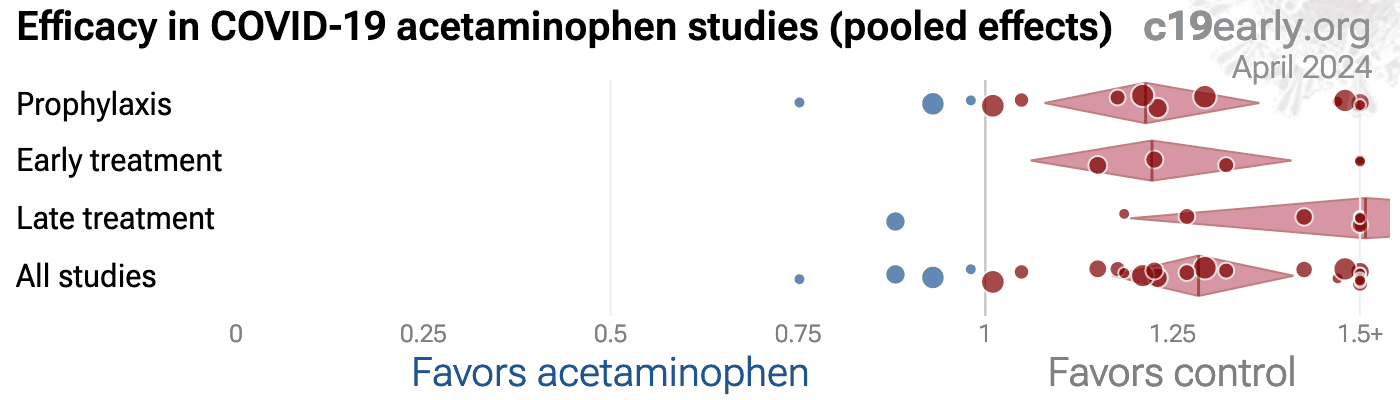
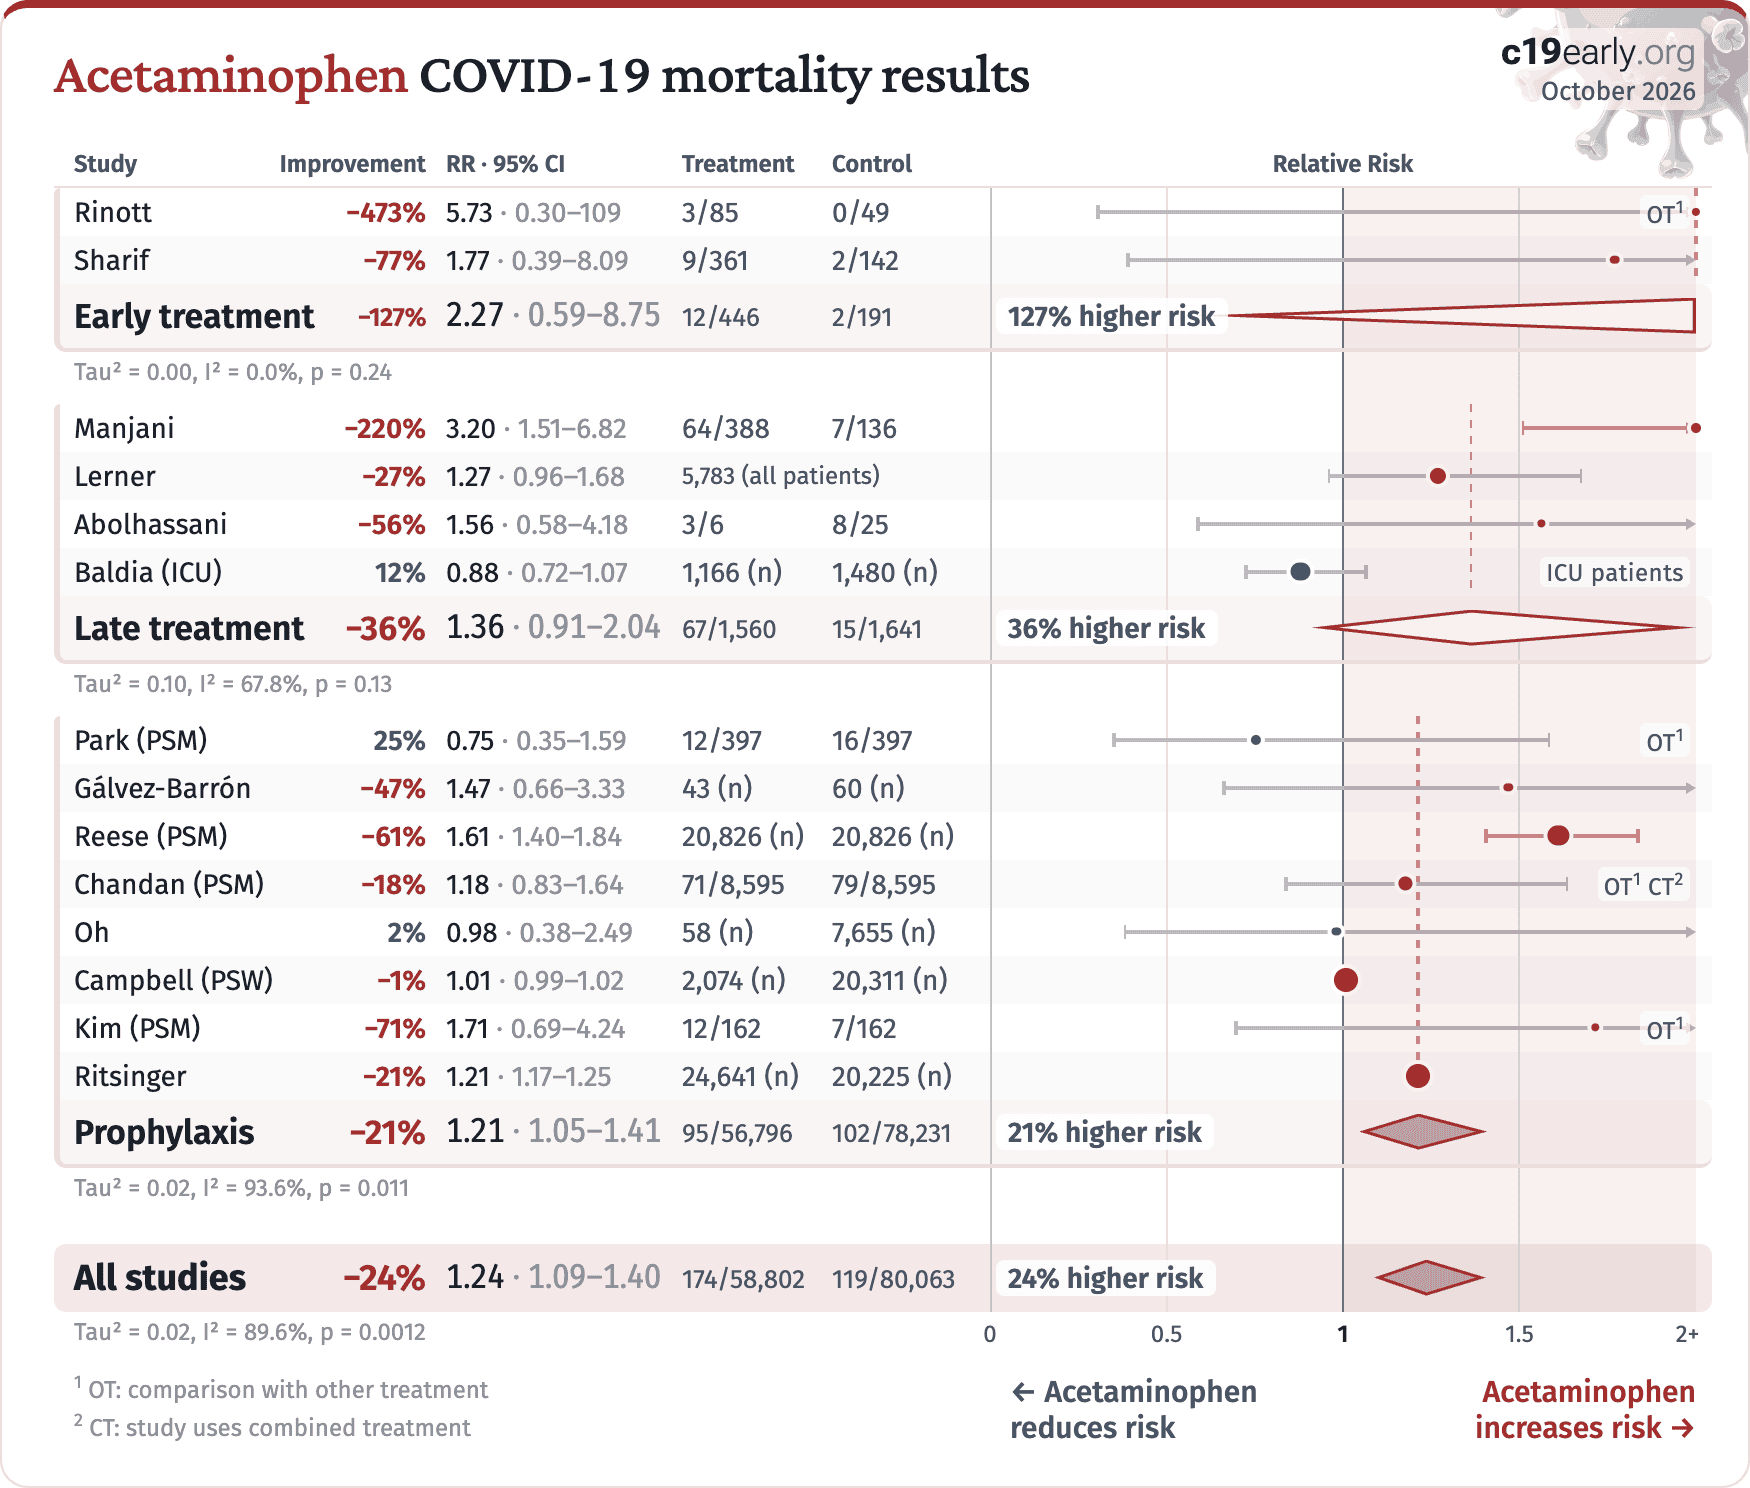
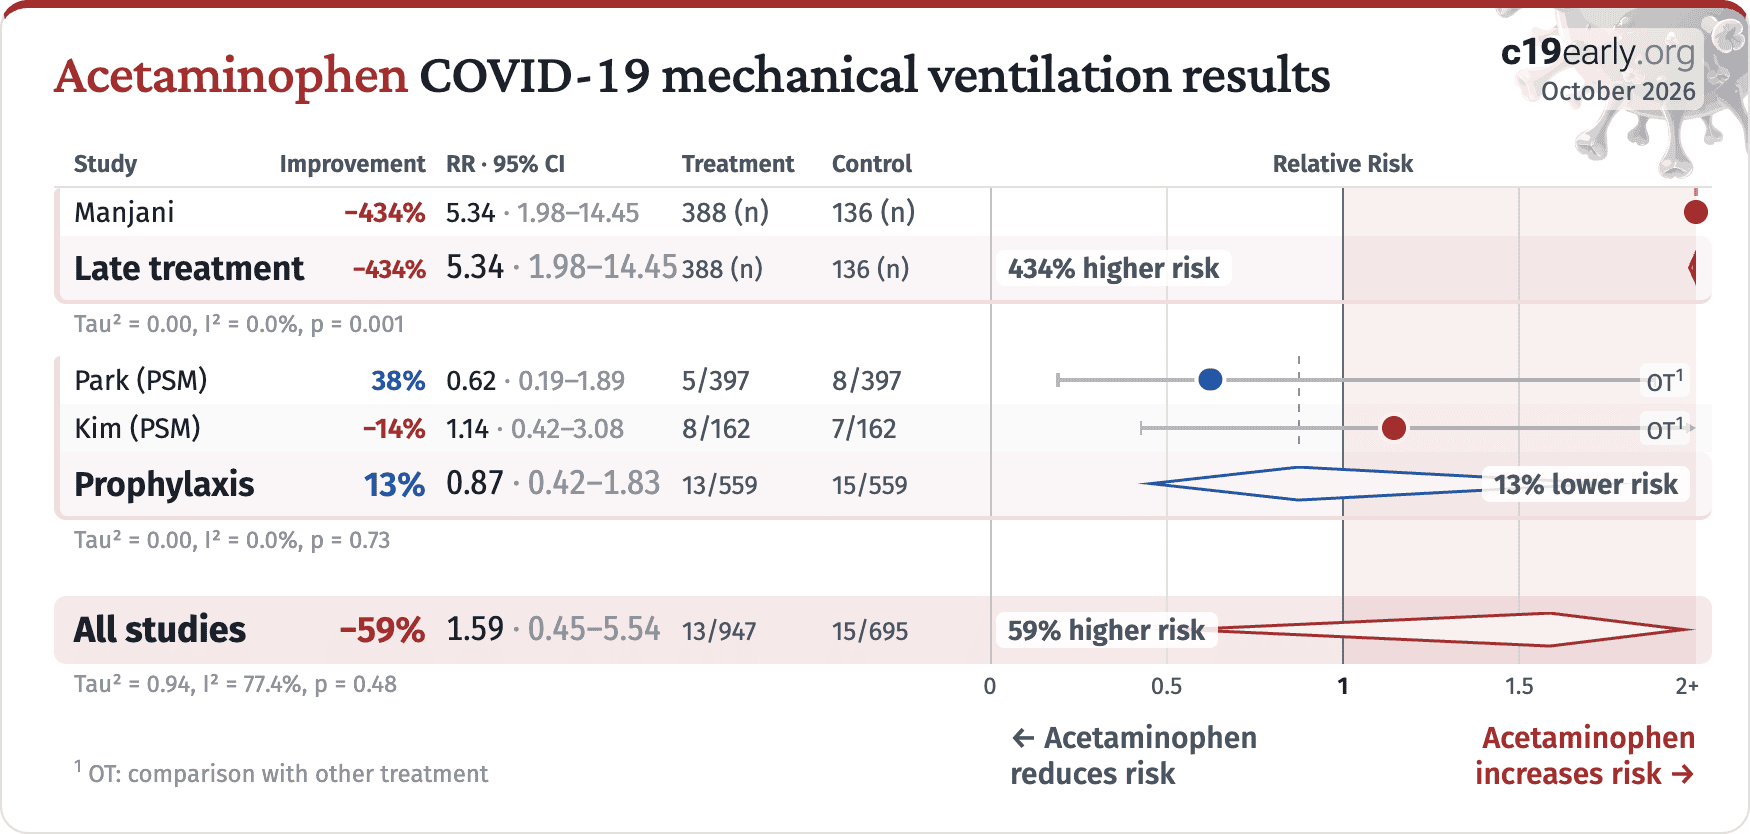
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/acemeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
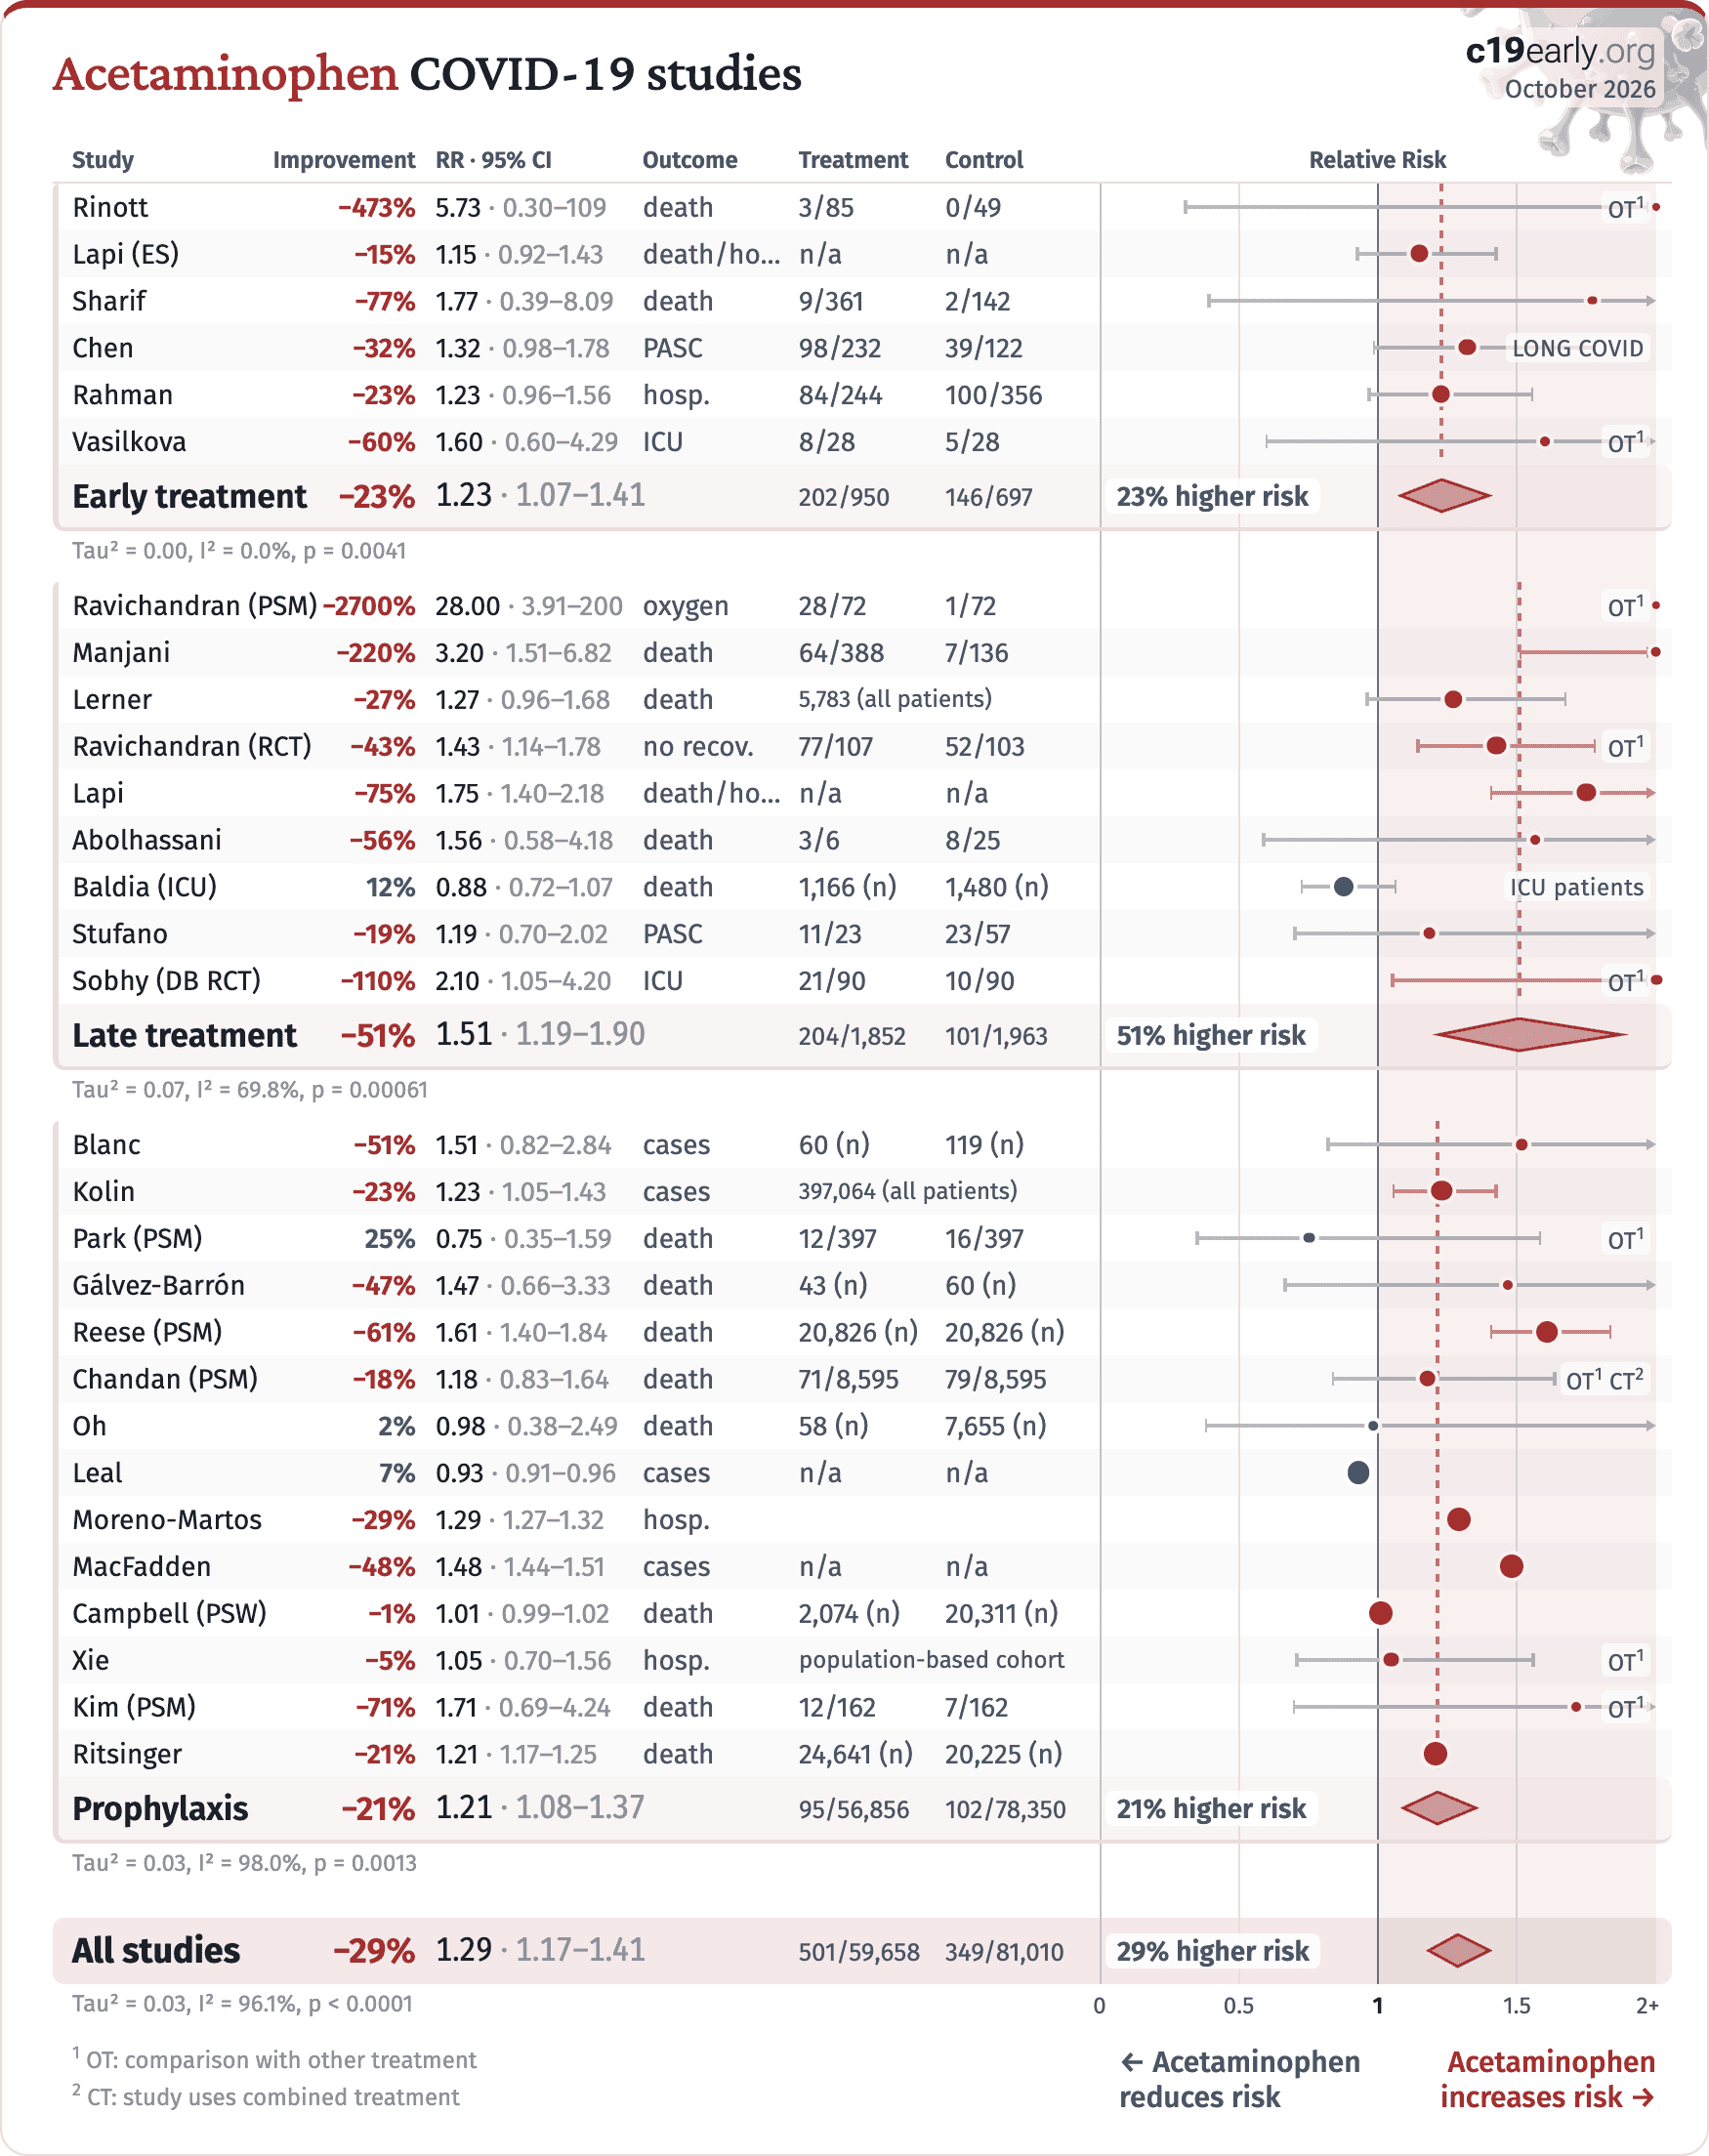
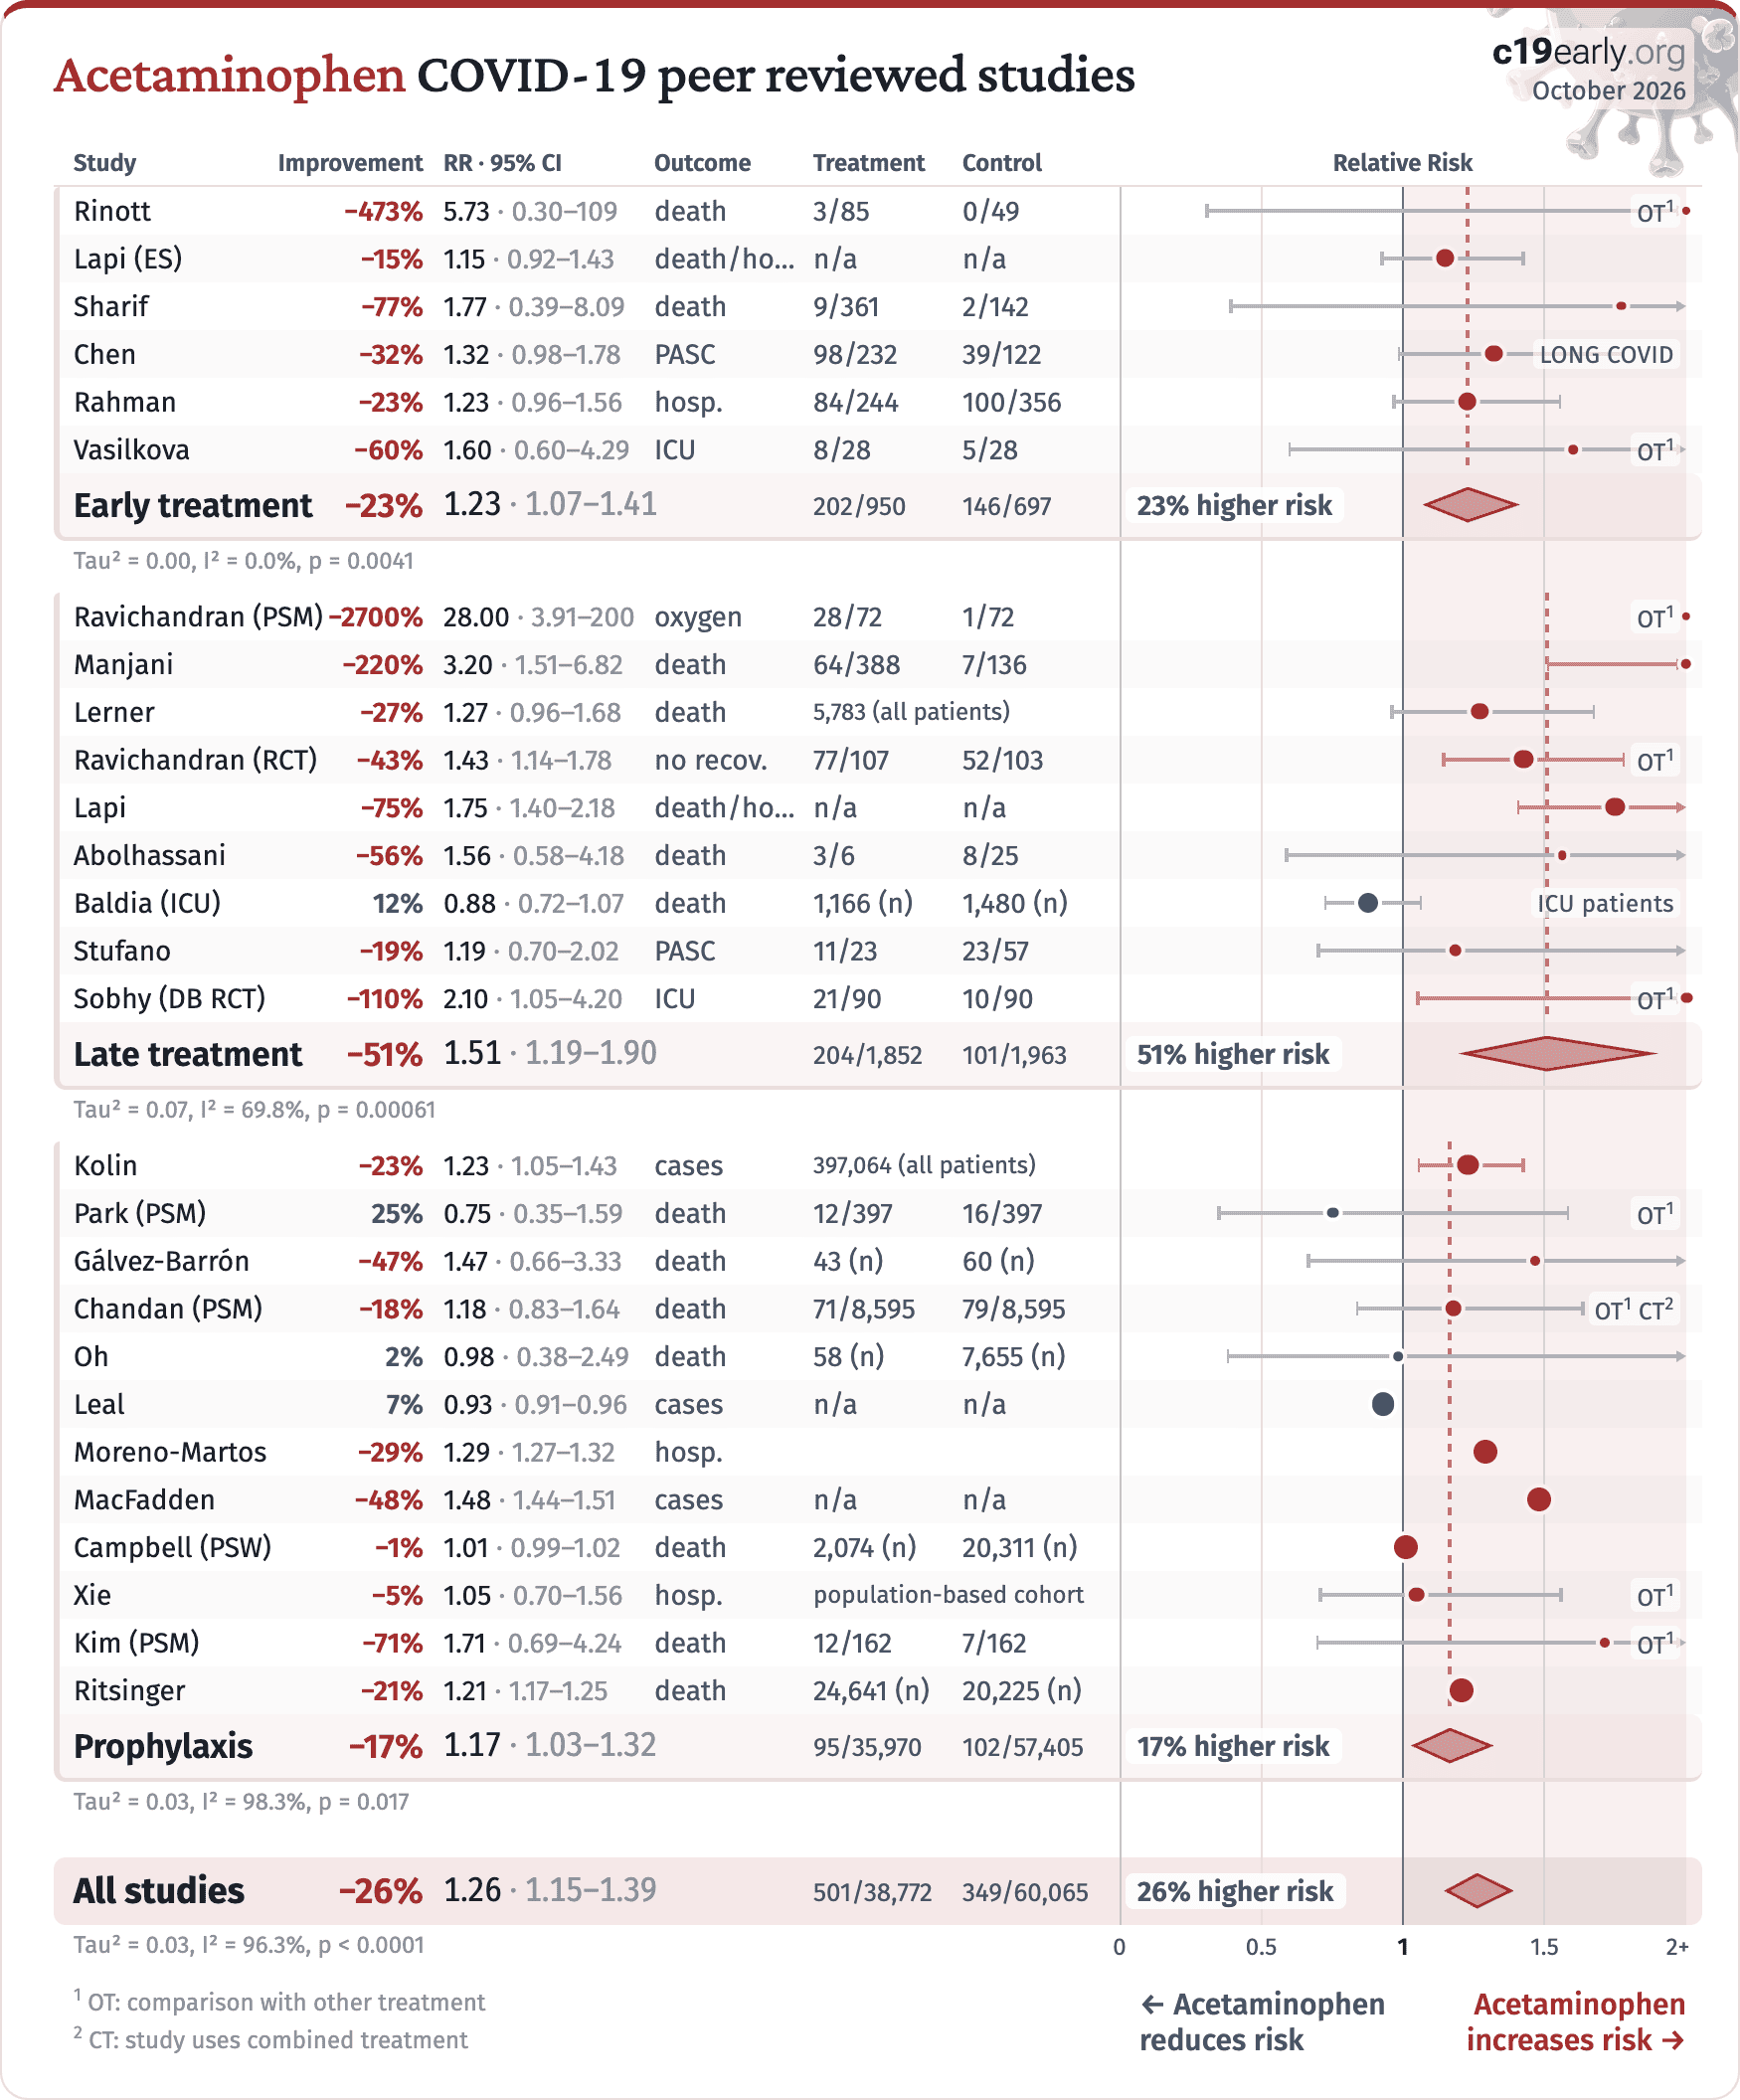
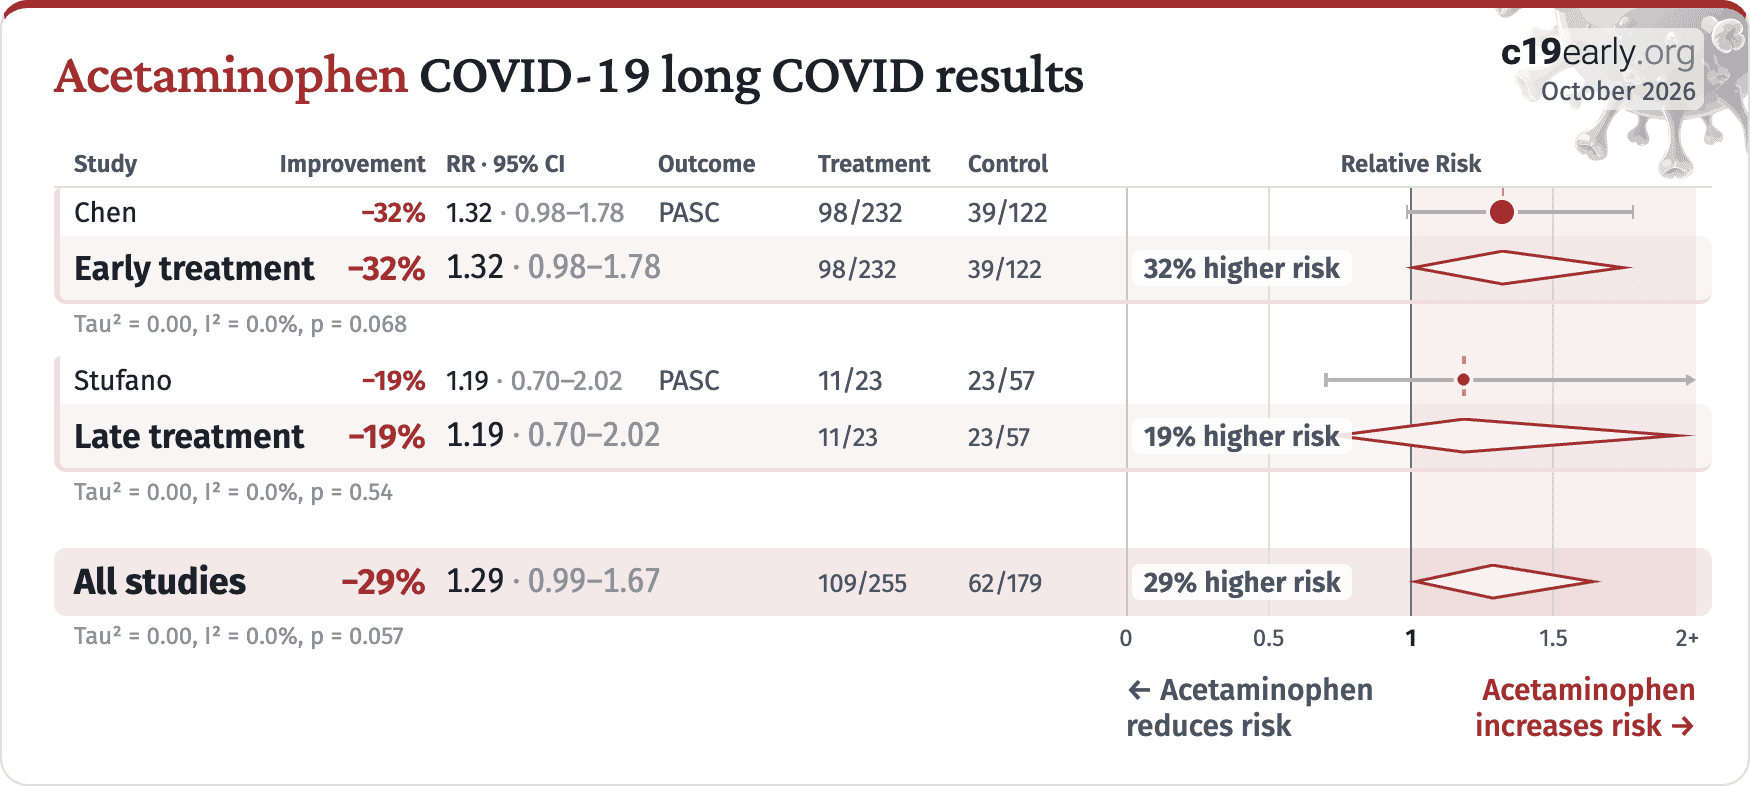
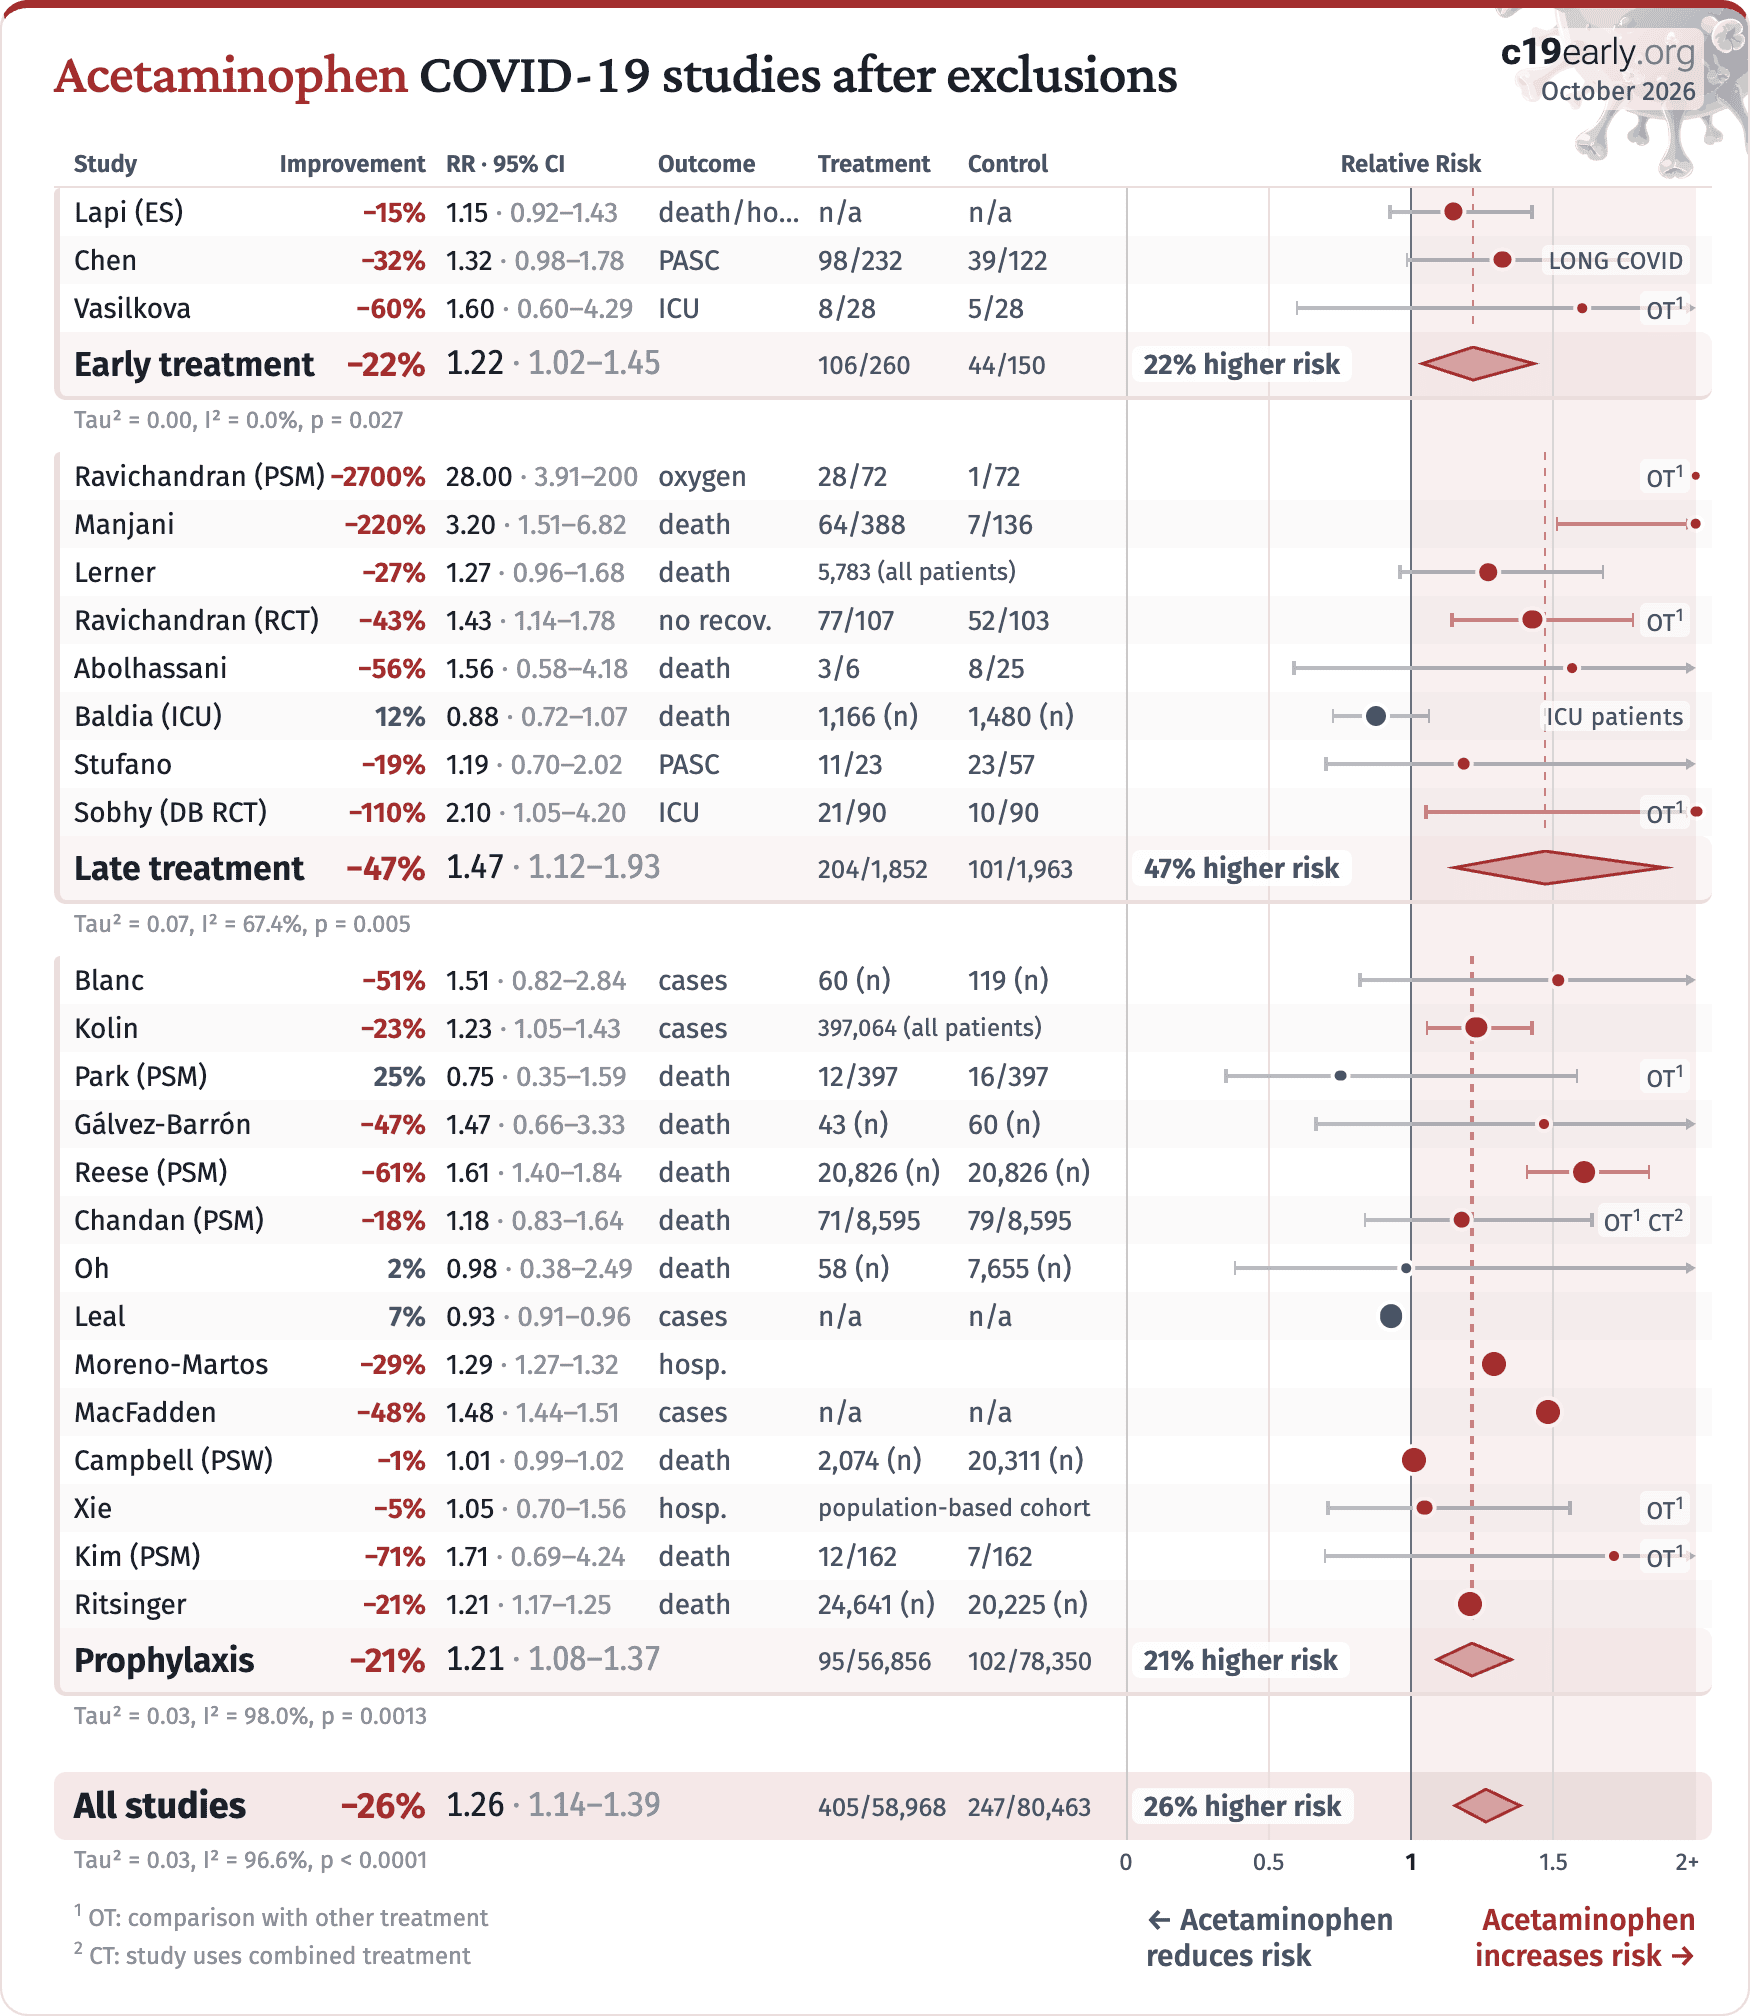
Chen (B), 10/16/2023, prospective, USA, peer-reviewed, 17 authors, study period May 2020 - June 2021.
|
risk of long COVID, 32.1% higher, RR 1.32, p = 0.07, treatment 98 of 232 (42.2%), control 39 of 122 (32.0%).
|
|
risk of long COVID, 0.9% higher, RR 1.01, p = 1.00, treatment 16 of 41 (39.0%), control 121 of 313 (38.7%), ibuprofen.
|
|
Lapi, 7/30/2022, retrospective, Italy, peer-reviewed, 8 authors, early treatment subset.
|
risk of death/hospitalization, 15.0% higher, OR 1.15, p = 0.22, adjusted per study, early use, RR approximated with OR.
|
|
risk of death/hospitalization, 29.0% higher, OR 1.29, p = 0.52, adjusted per study, mid-term use, RR approximated with OR.
|
|
Rahman, 11/8/2023, retrospective, Bangladesh, peer-reviewed, 5 authors, excluded in exclusion analyses:
unadjusted results with no group details; significant unadjusted confounding possible.
|
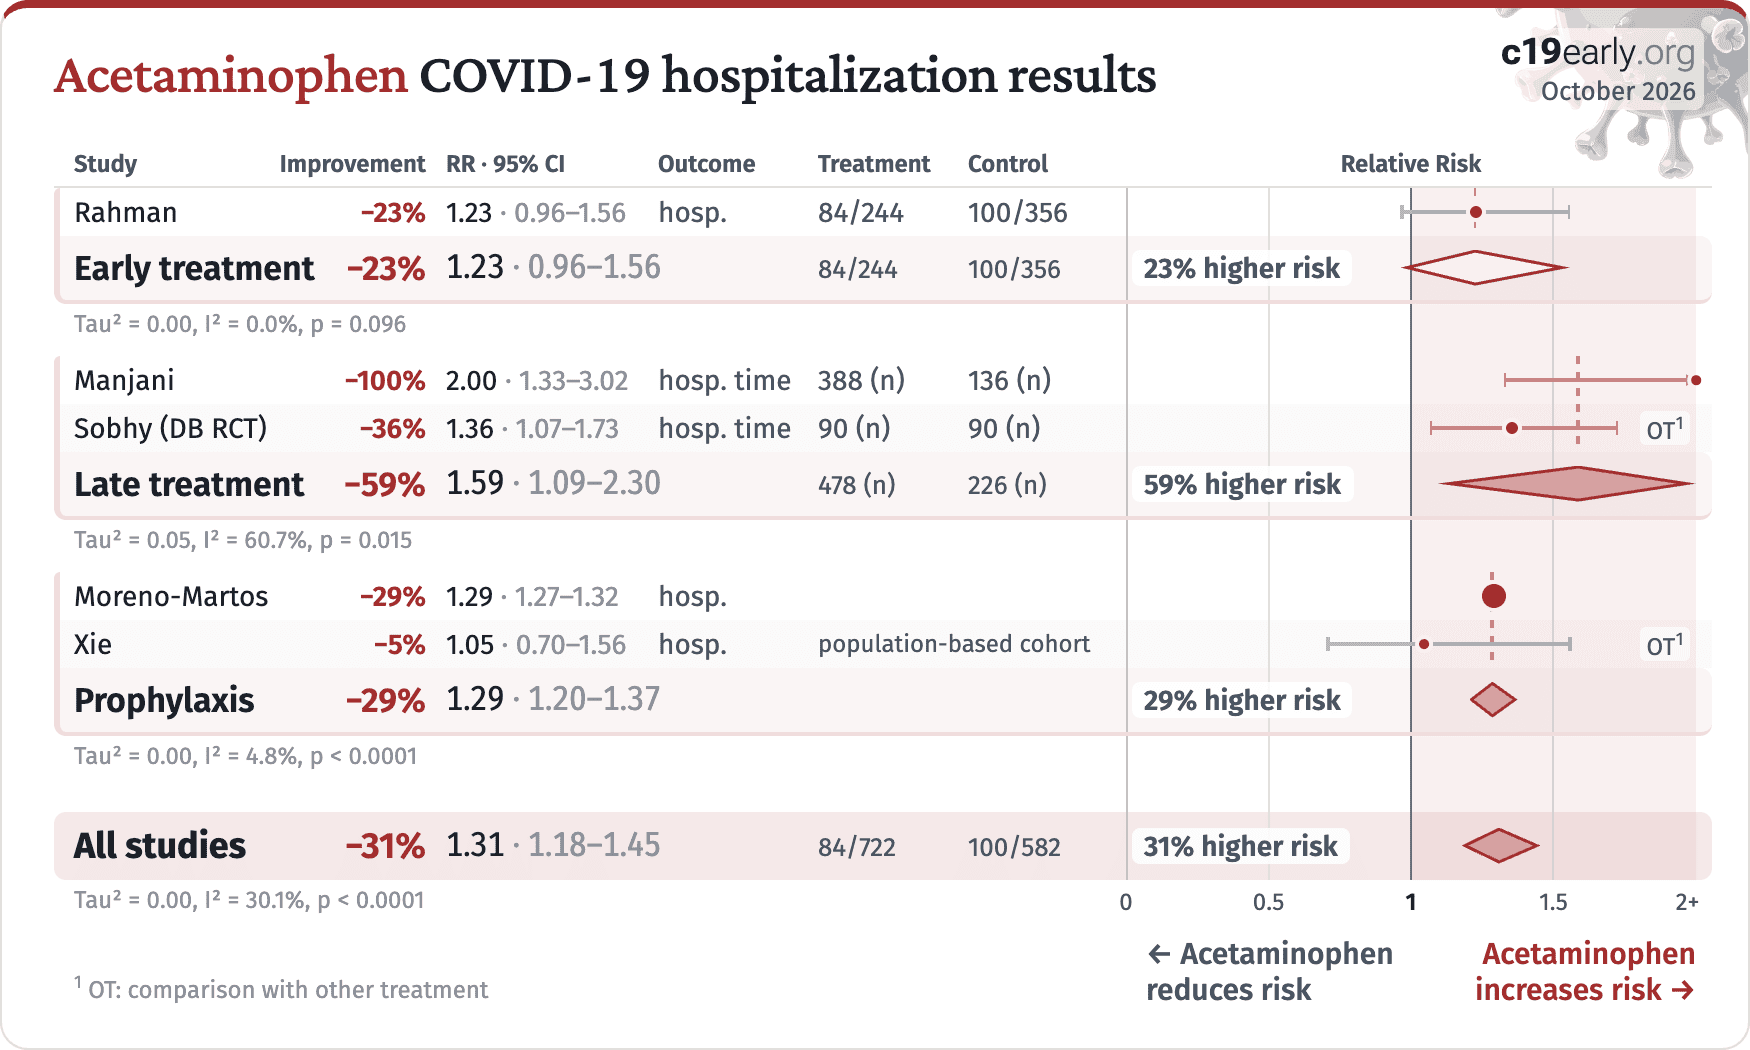
risk of hospitalization, 22.6% higher, RR 1.23, p = 0.11, treatment 84 of 244 (34.4%), control 100 of 356 (28.1%).
|
|
Rinott, 9/30/2020, retrospective, Israel, peer-reviewed, median age 45.0, 5 authors, study period 15 March, 2020 - 15 April, 2020, this trial compares with another treatment - results may be better when compared to placebo, excluded in exclusion analyses:
unadjusted differences between groups.
|
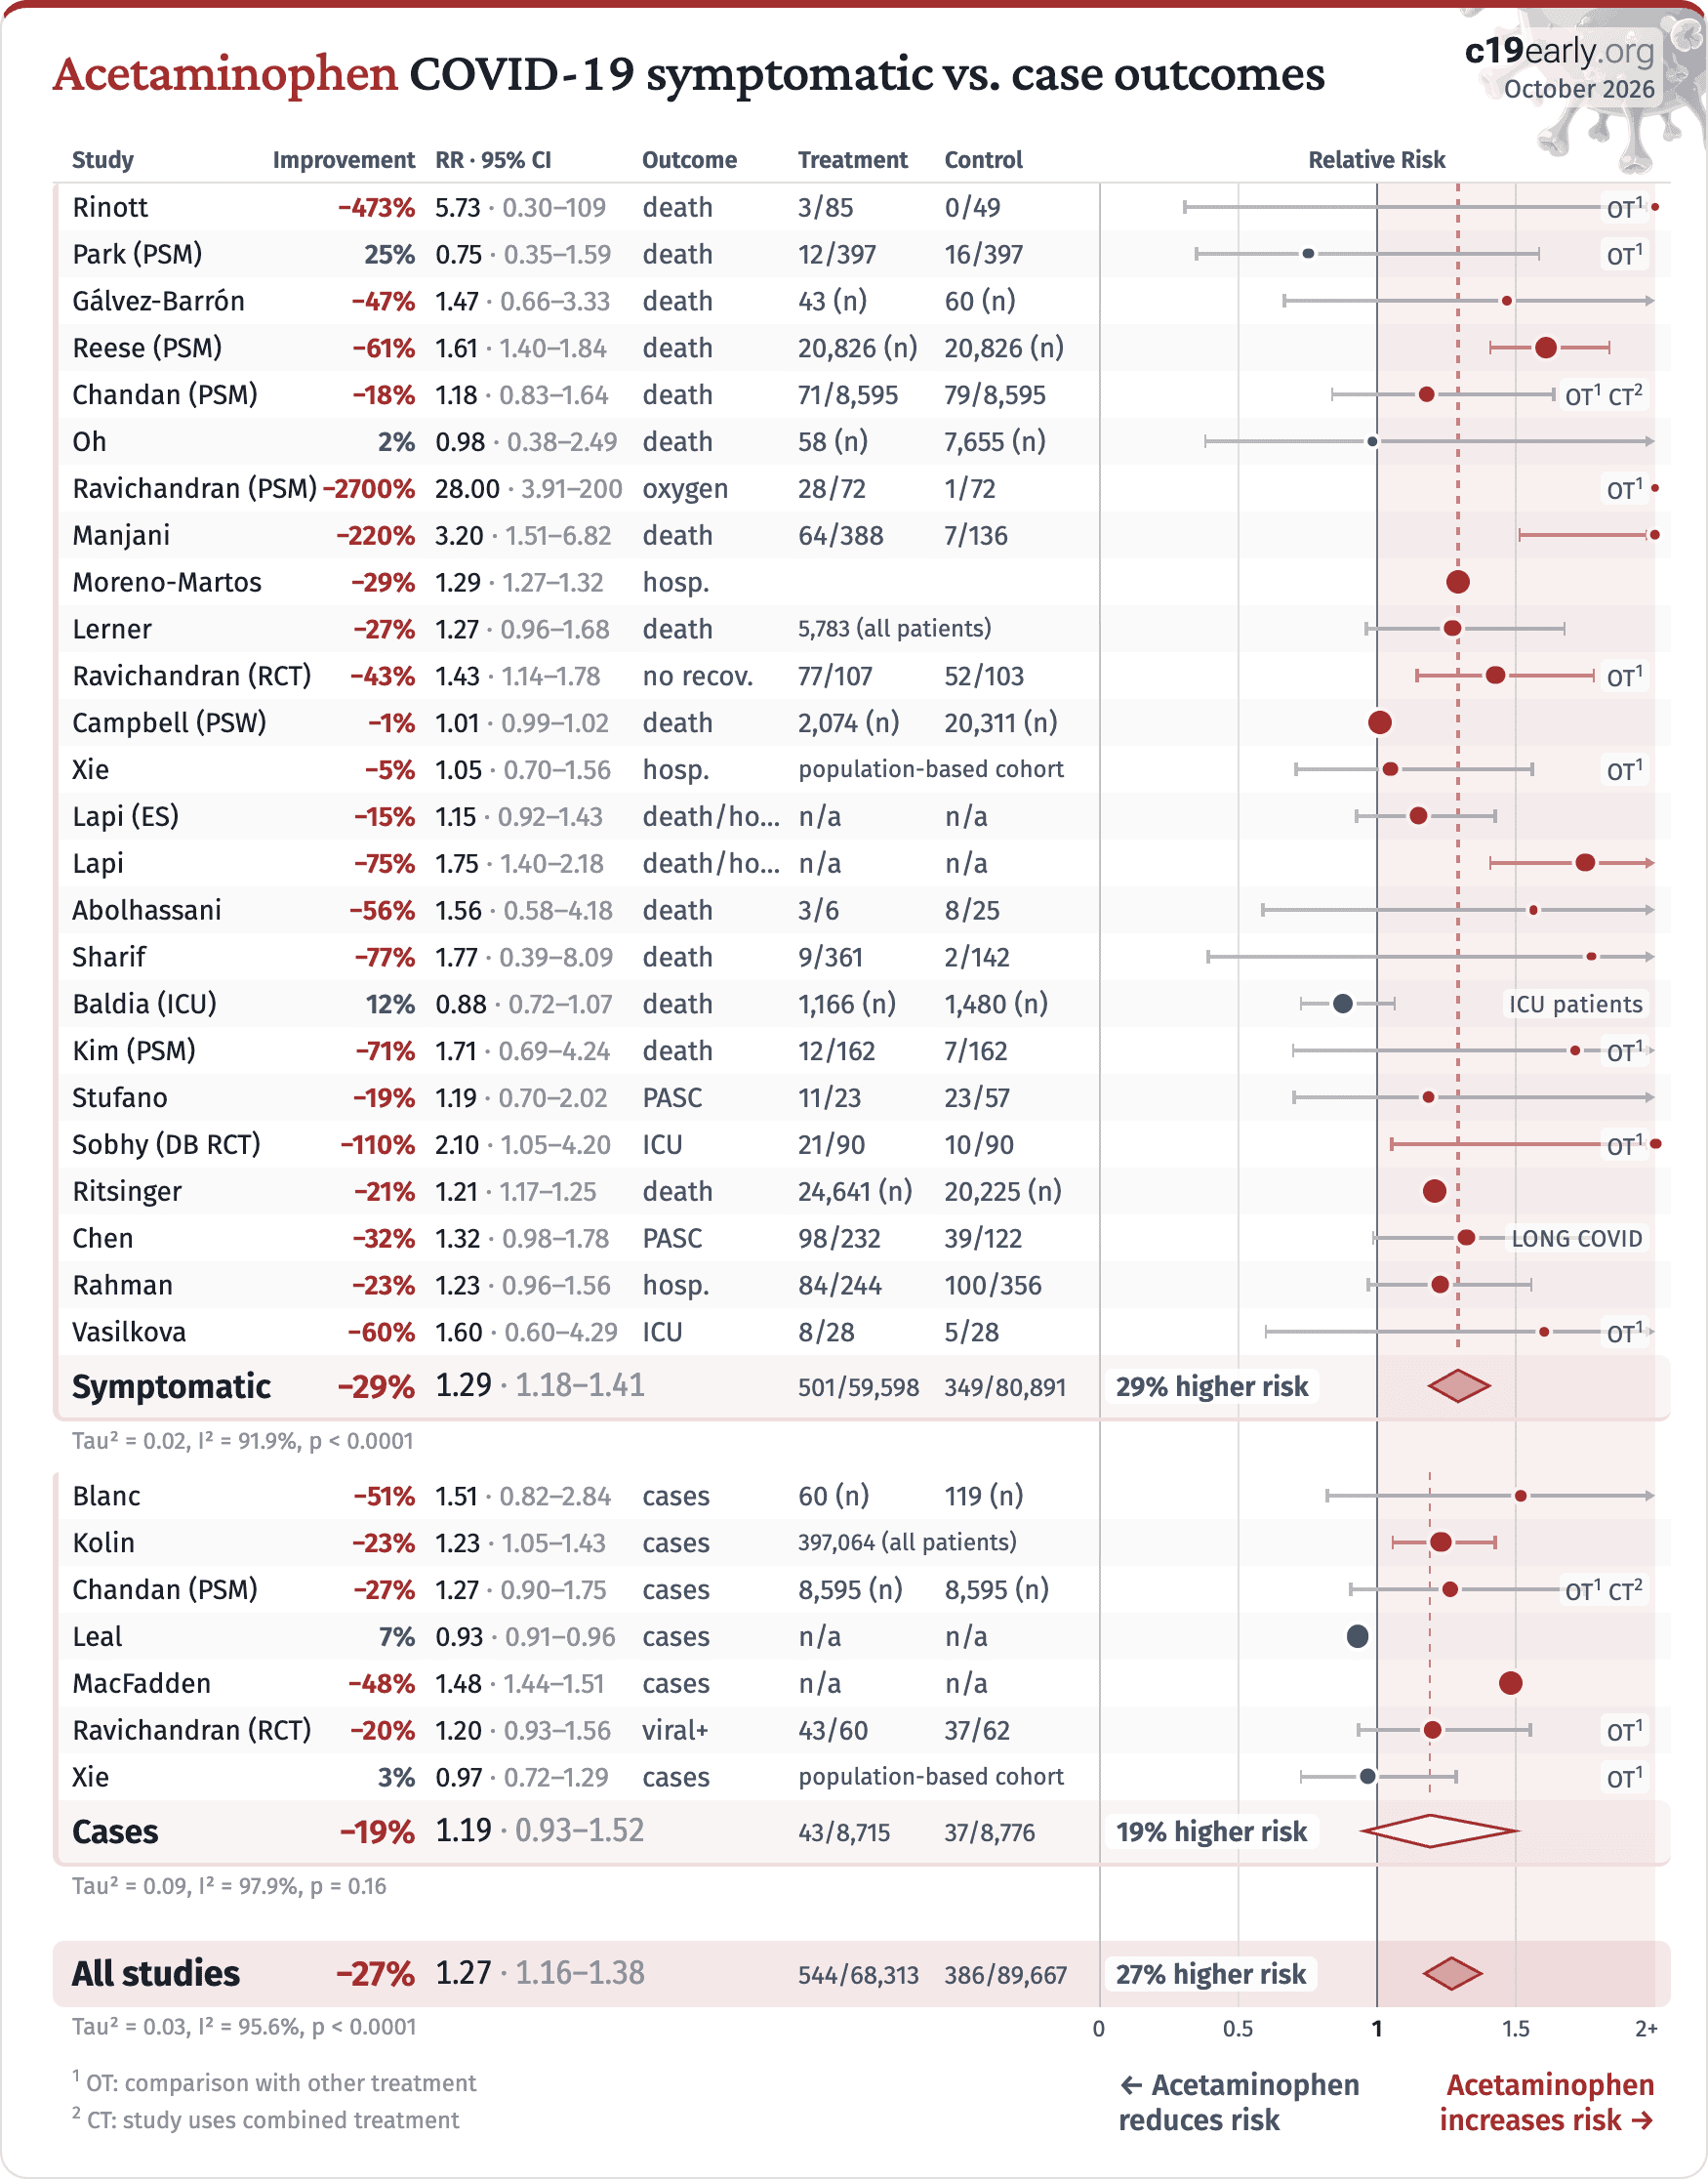
risk of death, 472.9% higher, RR 5.73, p = 0.30, treatment 3 of 85 (3.5%), control 0 of 49 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm).
|
|
risk of oxygen therapy, 534.1% higher, RR 6.34, p = 0.06, treatment 11 of 85 (12.9%), control 1 of 49 (2.0%).
|
|
Sharif, 11/26/2022, retrospective, Bangladesh, peer-reviewed, 14 authors, study period 13 December, 2020 - 4 February, 2021, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 77.0% higher, RR 1.77, p = 0.74, treatment 9 of 361 (2.5%), control 2 of 142 (1.4%), unadjusted, ACE.
|
|
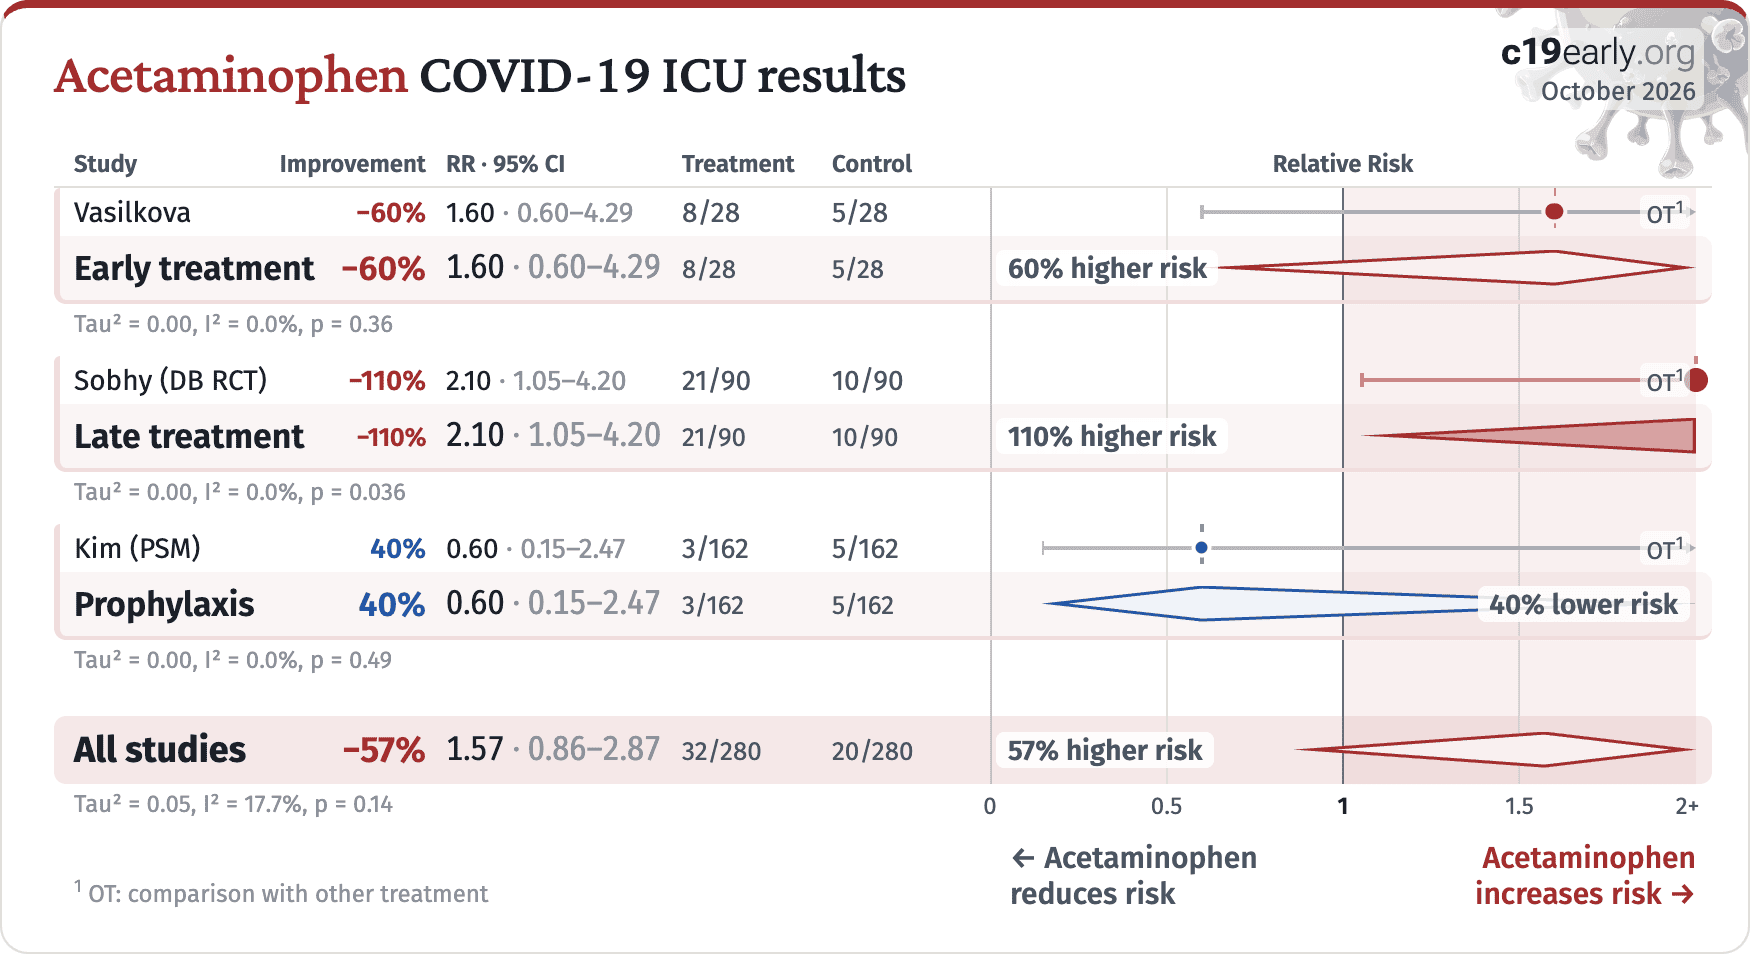
Vasilkova, 6/2/2026, retrospective, Russia, peer-reviewed, 2 authors, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of ICU admission, 60.0% higher, RR 1.60, p = 0.53, treatment 8 of 28 (28.6%), control 5 of 28 (17.9%).
|
|
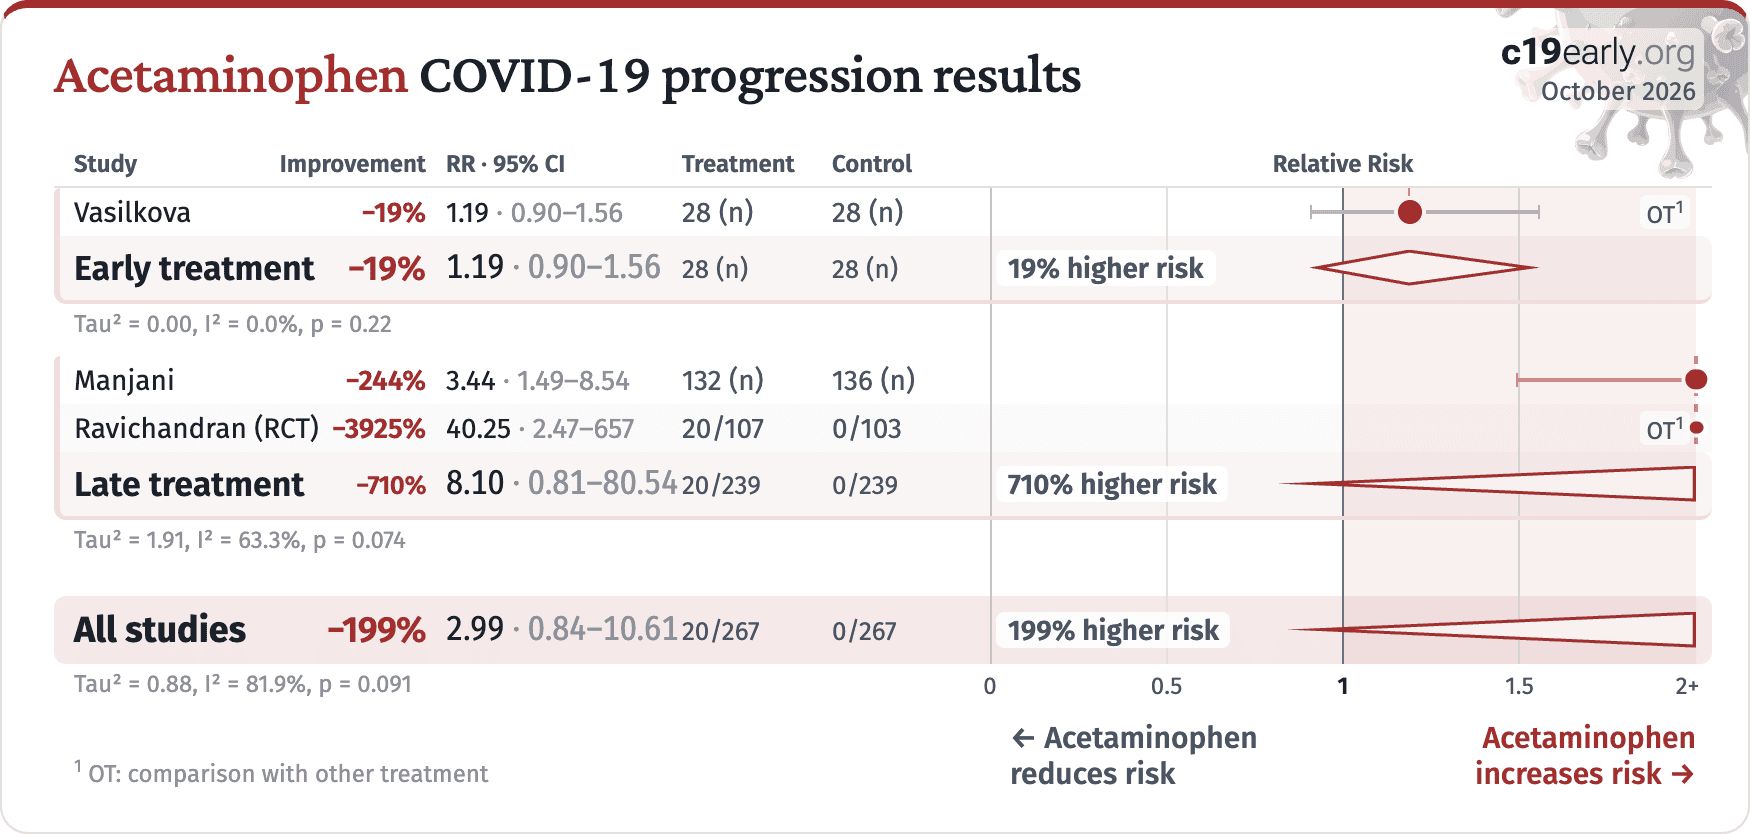
mean case severity score, 18.8% higher, relative time 1.19, p = 0.22, treatment mean 1.71 (±0.81) n=28, control mean 1.44 (±0.81) n=28.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Abolhassani, 9/13/2022, retrospective, Iran, peer-reviewed, 23 authors.
|
risk of death, 56.2% higher, RR 1.56, p = 0.64, treatment 3 of 6 (50.0%), control 8 of 25 (32.0%).
|
|
Baldia, 12/27/2022, prospective, multiple countries, peer-reviewed, median age 75.0, 26 authors, trial NCT04321265 (history).
|
risk of death, 12.0% lower, OR 0.88, p = 0.20, treatment 1,166, control 1,480, adjusted per study, multivariable, day 90, RR approximated with OR.
|
|
risk of death, 14.0% lower, OR 0.86, p = 0.20, treatment 1,166, control 1,480, adjusted per study, multivariable, day 30, RR approximated with OR.
|
|
Lapi, 7/30/2022, retrospective, Italy, peer-reviewed, 8 authors, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely.
|
risk of death/hospitalization, 75.0% higher, OR 1.75, p < 0.001, adjusted per study, late use, RR approximated with OR, late treatment result.
|
|
Lerner, 3/30/2022, retrospective, France, peer-reviewed, median age 69.2, 7 authors, study period 1 February, 2020 - 15 June, 2021.
|
risk of death, 26.9% higher, RR 1.27, p = 0.10, odds ratio converted to relative risk, weighted and trimmed, day 28, control prevalance approximated with overall prevalence.
|
|
Manjani, 10/31/2021, retrospective, USA, peer-reviewed, 6 authors, study period February 2020 - June 2020.
|
risk of death, 220.5% higher, RR 3.20, p = 0.001, treatment 64 of 388 (16.5%), control 7 of 136 (5.1%).
|
|
risk of mechanical ventilation, 434.5% higher, RR 5.34, p < 0.001, treatment 388, control 136.
|
|
risk of progression, 244.0% higher, OR 3.44, p < 0.005, treatment 132, control 136, triaged to higher level of care, high exposure, RR approximated with OR.
|
|
risk of progression, 201.0% higher, OR 3.01, p < 0.007, treatment 256, control 136, triaged to higher level of care, moderate exposure, RR approximated with OR.
|
|
hospitalization time, 100% higher, relative time 2.00, p < 0.001, treatment 388, control 136.
|
|
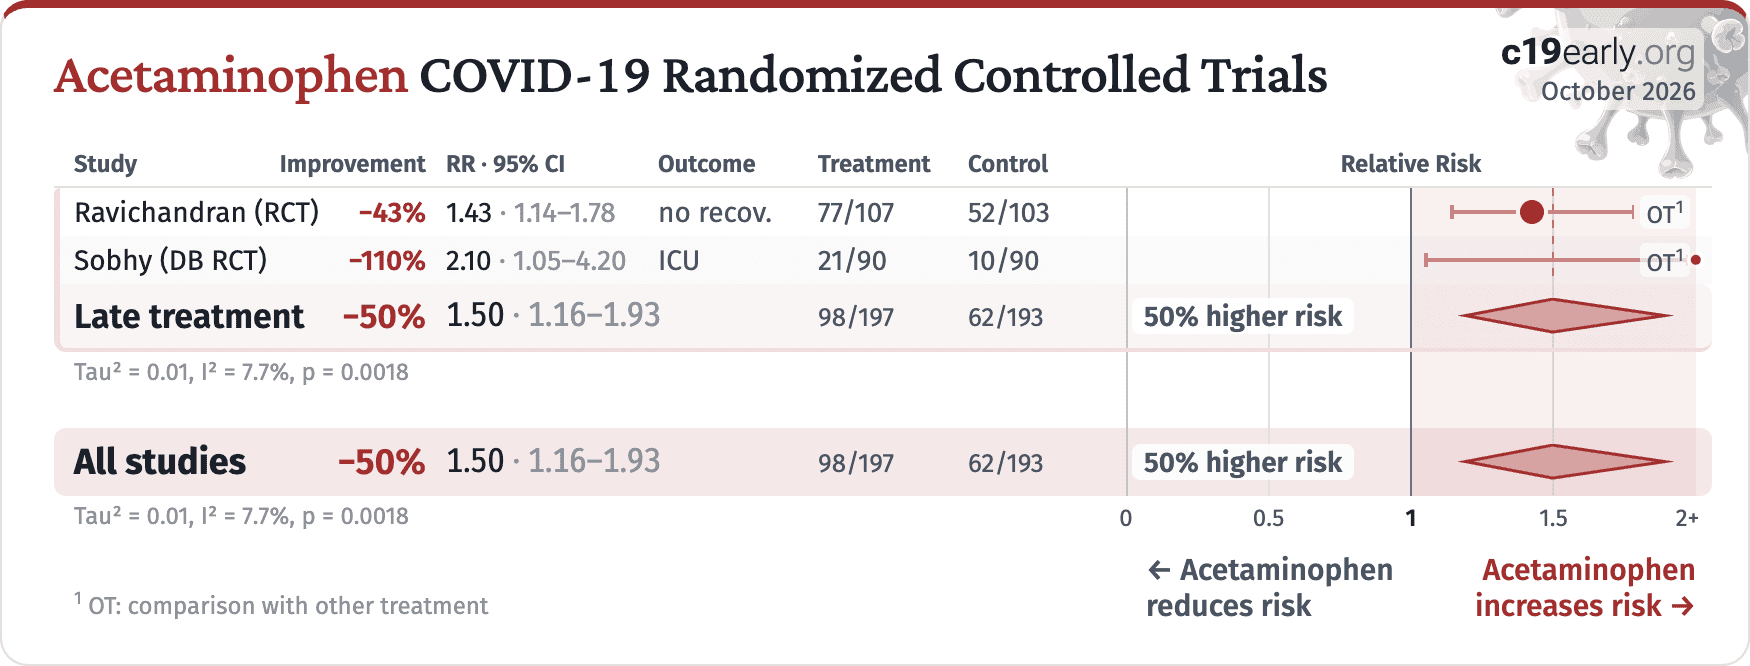
Ravichandran, 4/19/2022, Randomized Controlled Trial, India, peer-reviewed, 8 authors, this trial compares with another treatment - results may be better when compared to placebo, trial CTRI/2021/05/033544.
|
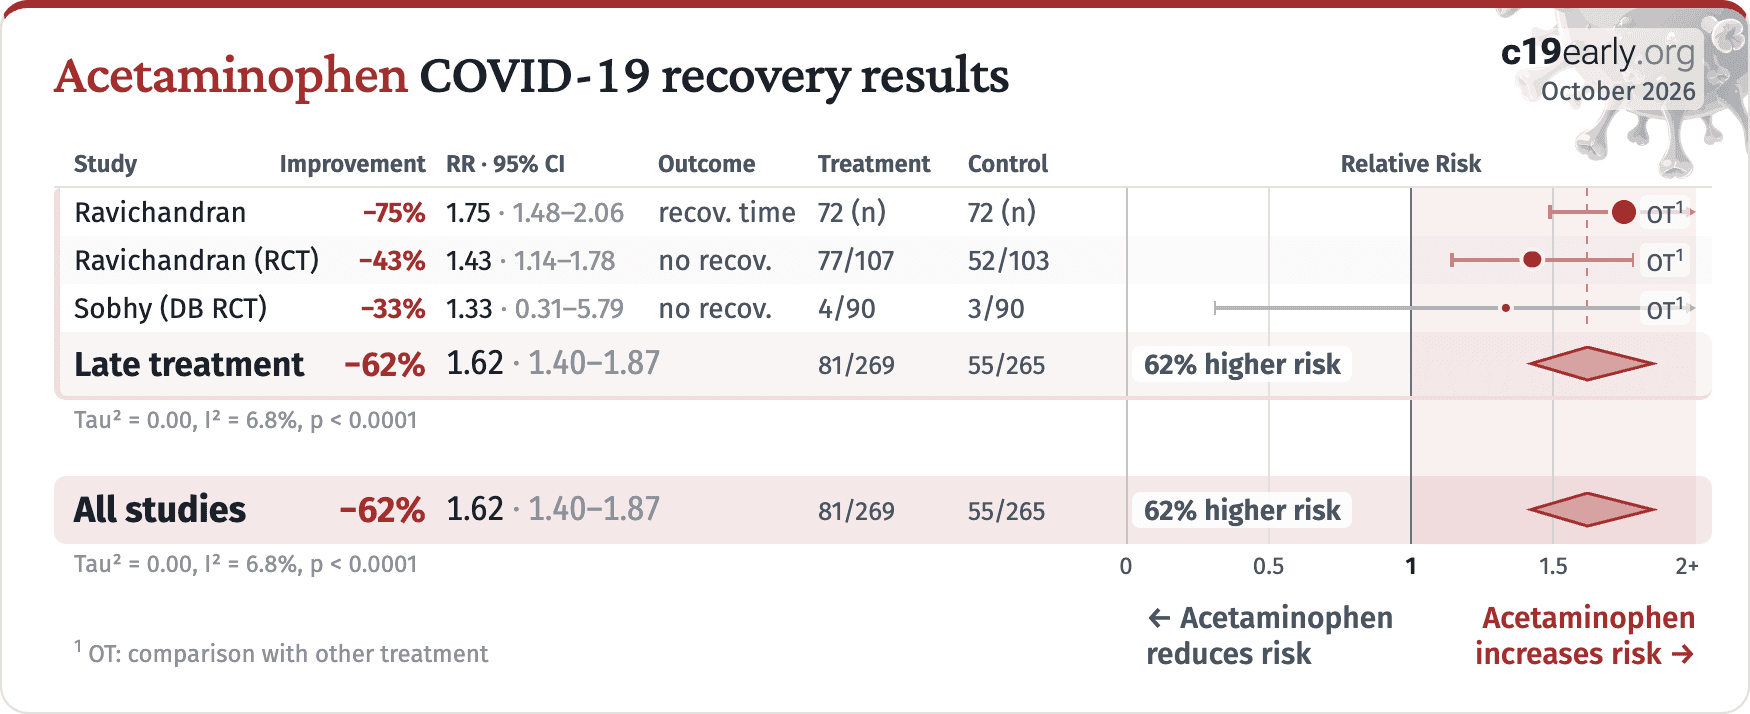
risk of no recovery, 42.5% higher, RR 1.43, p = 0.002, treatment 77 of 107 (72.0%), control 52 of 103 (50.5%), day 14.
|
|
risk of progression, 3925.2% higher, RR 40.25, p < 0.001, treatment 20 of 107 (18.7%), control 0 of 103 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), SpO2 ≤93.
|
|
recovery time, 133.3% higher, relative time 2.33, p < 0.001, treatment median 7.0 IQR 2.75 n=107, control median 3.0 IQR 1.0 n=103, fever.
|
|
recovery time, 75.0% higher, relative time 1.75, p < 0.001, treatment median 7.0 IQR 2.0 n=107, control median 4.0 IQR 2.0 n=103, myalgia.
|
|
recovery time, 75.0% higher, relative time 1.75, p < 0.001, treatment median 7.0 IQR 3.0 n=107, control median 4.0 IQR 1.0 n=103, cough.
|
|
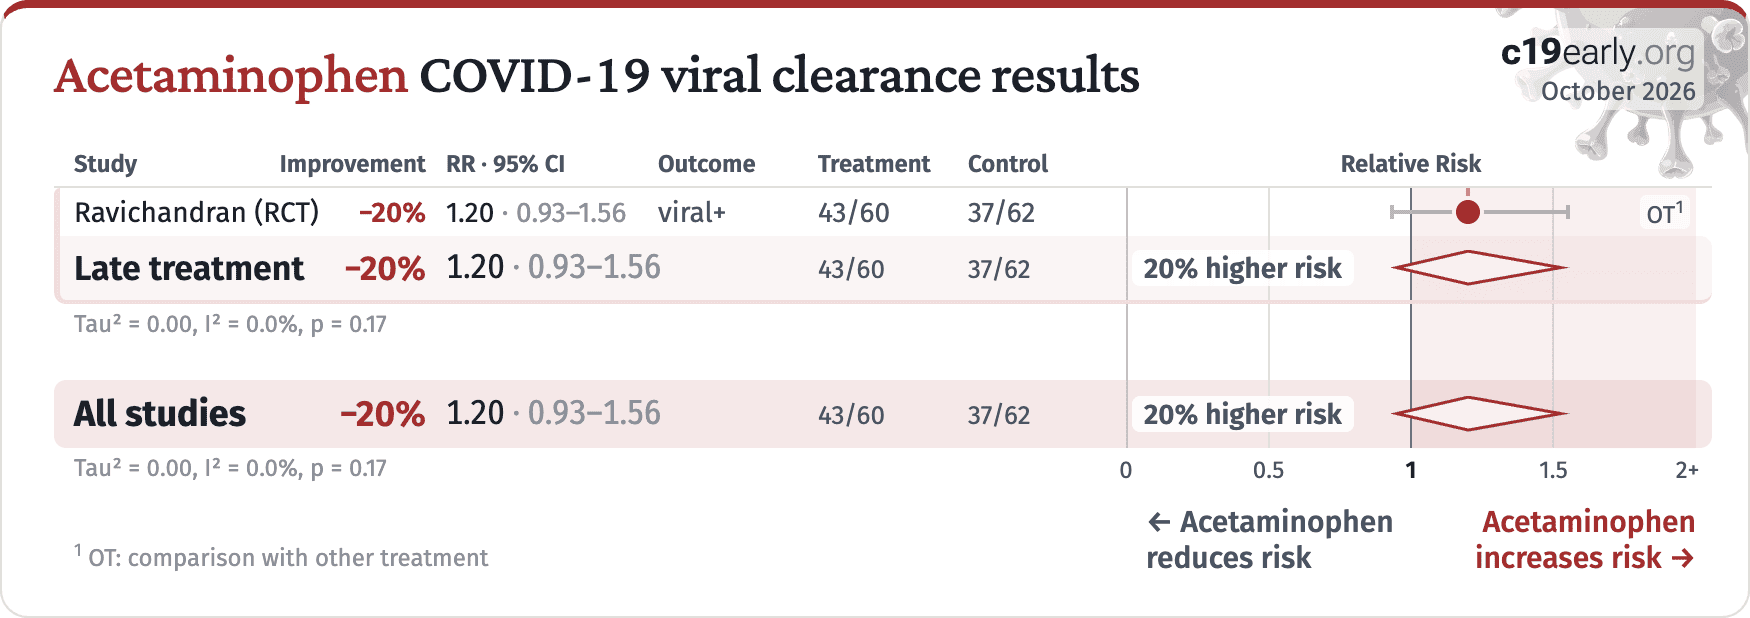
risk of no viral clearance, 20.1% higher, RR 1.20, p = 0.19, treatment 43 of 60 (71.7%), control 37 of 62 (59.7%), day 7.
|
|
Ravichandran (B), 7/31/2021, retrospective, India, peer-reviewed, 6 authors, this trial compares with another treatment - results may be better when compared to placebo, trial ISRCTN11970082.
|
risk of oxygen therapy, 2700.0% higher, RR 28.00, p < 0.001, treatment 28 of 72 (38.9%), control 1 of 72 (1.4%), propensity score matching.
|
|
recovery time, 75.0% higher, relative time 1.75, p < 0.001, treatment median 7.0 IQR 1.0 n=72, control median 4.0 IQR 1.0 n=72, fever.
|
|
recovery time, 116.7% higher, relative time 2.17, p < 0.001, treatment median 6.5 IQR 3.25 n=72, control median 3.0 IQR 2.0 n=72, myalgia.
|
|
recovery time, 166.7% higher, relative time 2.67, p < 0.001, treatment median 8.0 IQR 2.0 n=72, control median 3.0 IQR 2.0 n=72, cough.
|
|
Sobhy, 4/19/2023, Double Blind Randomized Controlled Trial, Egypt, peer-reviewed, 6 authors, study period January 2022 - May 2022, this trial compares with another treatment - results may be better when compared to placebo, trial PACTR202202880140319.
|
risk of ICU admission, 110.0% higher, RR 2.10, p = 0.047, treatment 21 of 90 (23.3%), control 10 of 90 (11.1%).
|
|
risk of oxygen therapy, 110.0% higher, RR 2.10, p = 0.047, treatment 21 of 90 (23.3%), control 10 of 90 (11.1%).
|
|
hospitalization time, 35.7% higher, relative time 1.36, p = 0.01, treatment 90, control 90.
|
|
risk of no recovery, 33.3% higher, RR 1.33, p = 1.00, treatment 4 of 90 (4.4%), control 3 of 90 (3.3%), day 4, dyspnea.
|
|
risk of no recovery, 75.0% higher, RR 1.75, p = 0.25, treatment 14 of 90 (15.6%), control 8 of 90 (8.9%), day 4, fever.
|
|
risk of no recovery, 92.3% higher, RR 1.92, p = 0.04, treatment 25 of 90 (27.8%), control 13 of 90 (14.4%), day 4, lymphopenia.
|
|
risk of no recovery, 70.0% higher, RR 1.70, p = 0.03, treatment 34 of 90 (37.8%), control 20 of 90 (22.2%), day 4, cough.
|
|
Stufano, 4/18/2023, retrospective, Italy, peer-reviewed, 7 authors.
|
risk of long COVID, 18.5% higher, RR 1.19, p = 0.62, treatment 11 of 23 (47.8%), control 23 of 57 (40.4%).
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
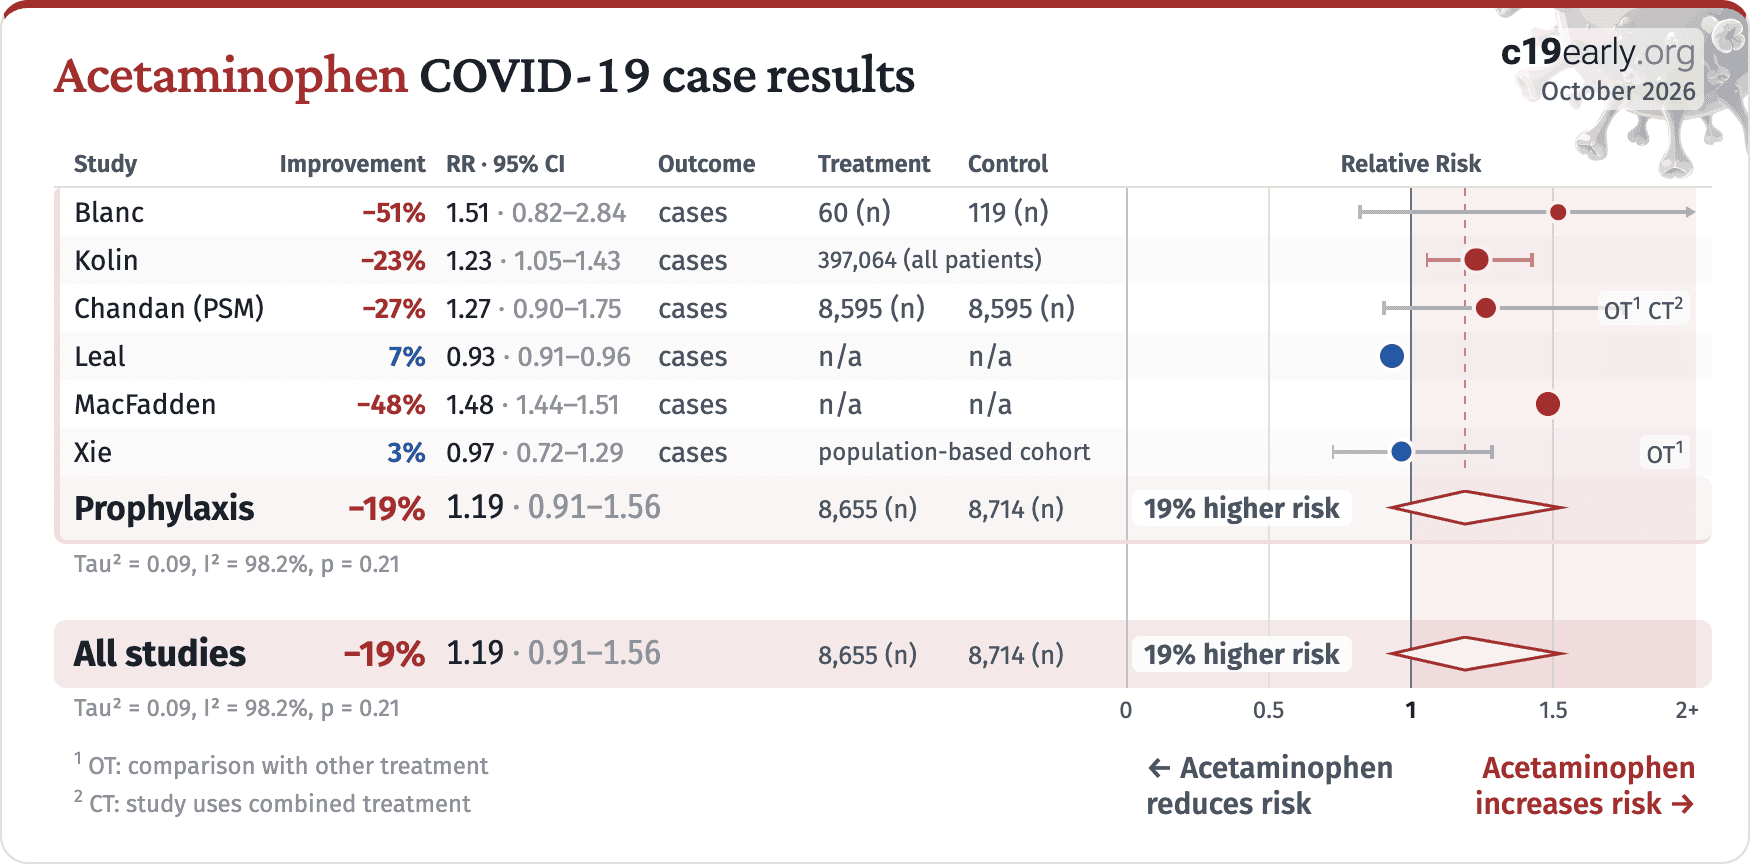
Blanc, 5/2/2020, retrospective, France, preprint, mean age 84.1, 22 authors, study period 2 March, 2020 - 8 April, 2020.
|
risk of case, 51.4% higher, OR 1.51, p = 0.19, treatment 60, control 119, RR approximated with OR.
|
|
Campbell, 5/5/2022, retrospective, USA, peer-reviewed, 4 authors, study period 2 March, 2020 - 14 December, 2020.
|
risk of death, 1.0% higher, OR 1.01, p = 0.43, treatment 2,074, control 20,311, adjusted per study, propensity score weighting, multivariable, day 60, RR approximated with OR.
|
|
risk of death, no change, OR 1.00, p = 0.86, treatment 2,074, control 20,311, adjusted per study, propensity score weighting, multivariable, day 30, RR approximated with OR.
|
|
Chandan, 4/29/2021, retrospective, United Kingdom, peer-reviewed, mean age 65.4, 24 authors, study period 30 January, 2020 - 31 July, 2020, this trial compares with another treatment - results may be better when compared to placebo, this trial uses multiple treatments in the treatment arm (combined with codeine or dihydrocodeine) - results of individual treatments may vary.
|
risk of death, 17.6% higher, HR 1.18, p = 0.35, treatment 71 of 8,595 (0.8%), control 79 of 8,595 (0.9%), adjusted per study, inverted to make HR<1 favor treatment, propensity score matching, multivariable.
|
|
risk of case, 26.6% higher, HR 1.27, p = 0.17, treatment 8,595, control 8,595, adjusted per study, inverted to make HR<1 favor treatment, propensity score matching, multivariable.
|
|
Gálvez-Barrón, 4/14/2021, retrospective, Spain, peer-reviewed, mean age 86.8, 13 authors, study period 12 March, 2020 - 2 May, 2020.
|
risk of death, 47.0% higher, OR 1.47, p = 0.42, treatment 43, control 60, RR approximated with OR.
|
|
risk of severe case, 23.0% lower, OR 0.77, p = 0.55, treatment 43, control 60, RR approximated with OR.
|
|
Kim, 2/21/2023, retrospective, South Korea, peer-reviewed, mean age 55.8, 4 authors, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 71.4% higher, RR 1.71, p = 0.34, treatment 12 of 162 (7.4%), control 7 of 162 (4.3%), propensity score matching.
|
|
risk of mechanical ventilation, 14.3% higher, RR 1.14, p = 1.00, treatment 8 of 162 (4.9%), control 7 of 162 (4.3%), propensity score matching.
|
|
risk of ICU admission, 40.0% lower, RR 0.60, p = 0.72, treatment 3 of 162 (1.9%), control 5 of 162 (3.1%), NNT 81, propensity score matching.
|
|
risk of oxygen therapy, 9.1% higher, RR 1.09, p = 0.87, treatment 24 of 162 (14.8%), control 22 of 162 (13.6%), propensity score matching.
|
|
Kolin, 11/17/2020, retrospective, United Kingdom, peer-reviewed, 4 authors.
|
risk of case, 23.0% higher, RR 1.23, p = 0.009.
|
|
Leal, 8/16/2021, retrospective, United Kingdom, peer-reviewed, 5 authors, study period 16 March, 2020 - 1 February, 2021.
|
risk of case, 7.0% lower, OR 0.93, p = 0.004, RR approximated with OR.
|
|
MacFadden, 3/29/2022, retrospective, Canada, peer-reviewed, 9 authors, study period 15 January, 2020 - 31 December, 2020.
|
risk of case, 48.0% higher, OR 1.48, p < 0.001, RR approximated with OR.
|
|
Moreno-Martos, 1/24/2022, retrospective, multiple countries, peer-reviewed, 24 authors, study period January 2020 - June 2020.
|
risk of hospitalization, 29.3% higher, RR 1.29, p < 0.001, treatment 10,367, control 89,523, meta analysis of all databases combined.
|
|
risk of hospitalization, 51.7% higher, RR 1.52, p < 0.001, treatment 103 of 178 (57.9%), control 196 of 514 (38.1%), US CU-AMC.
|
|
risk of hospitalization, 5.1% higher, RR 1.05, p = 0.57, treatment 87 of 144 (60.4%), control 360 of 626 (57.5%), US CUIMC.
|
|
risk of hospitalization, 21.8% lower, RR 0.78, p = 0.02, treatment 64 of 319 (20.1%), control 1,585 of 6,181 (25.6%), NNT 18, US HealthVerity.
|
|
risk of hospitalization, 16.5% higher, RR 1.16, p < 0.001, treatment 2,597 of 4,983 (52.1%), control 28,320 of 63,279 (44.8%), US IQVIA OpenClaims.
|
|
risk of hospitalization, 57.0% higher, RR 1.57, p < 0.001, treatment 1,090 of 1,868 (58.4%), control 3,414 of 9,188 (37.2%), US Optum EHR.
|
|
risk of hospitalization, 47.2% higher, RR 1.47, p < 0.001, treatment 1,397 of 2,875 (48.6%), control 3,214 of 9,735 (33.0%), US VA-OMOP.
|
|
Oh, 6/24/2021, retrospective, South Korea, peer-reviewed, 5 authors, study period 1 January, 2020 - 4 June, 2020.
|
risk of death, 1.9% lower, RR 0.98, p = 0.97, treatment 58, control 7,655, adjusted per study, odds ratio converted to relative risk, multivariable, control prevalance approximated with overall prevalence.
|
|
Park, 3/3/2021, retrospective, South Korea, peer-reviewed, 5 authors, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of death, 24.8% lower, HR 0.75, p = 0.46, treatment 12 of 397 (3.0%), control 16 of 397 (4.0%), NNT 99, inverted to make HR<1 favor treatment, propensity score matching.
|
|
risk of mechanical ventilation, 37.5% lower, HR 0.62, p = 0.42, treatment 5 of 397 (1.3%), control 8 of 397 (2.0%), NNT 132, inverted to make HR<1 favor treatment, propensity score matching.
|
|
Reese, 4/20/2021, retrospective, USA, preprint, 23 authors.
|
risk of death, 61.0% higher, HR 1.61, p < 0.001, treatment 20,826, control 20,826, propensity score matching, Cox proportional hazards, Table S58.
|
|
risk of severe case, 816.0% higher, OR 9.16, p < 0.001, treatment 20,826, control 20,826, propensity score matching, Table S50, RR approximated with OR.
|
|
Ritsinger, 4/28/2023, retrospective, Sweden, peer-reviewed, mean age 79.8, 8 authors, study period 1 January, 2020 - 9 September, 2021.
|
risk of death, 21.0% higher, HR 1.21, p < 0.001, treatment 24,641, control 20,225.
|
|
Xie (B), 7/13/2022, retrospective, USA, peer-reviewed, 9 authors, study period 1 February, 2020 - 31 October, 2020, this trial compares with another treatment - results may be better when compared to placebo.
|
risk of hospitalization, 4.8% higher, HR 1.05, p = 0.83, inverted to make HR<1 favor treatment, Open Claims, PharMetrics Plus, both periods combined.
|
|
risk of case, 3.5% lower, HR 0.97, p = 0.82, inverted to make HR<1 favor treatment, Open Claims, PharMetrics Plus, both periods combined.
|