October 2026
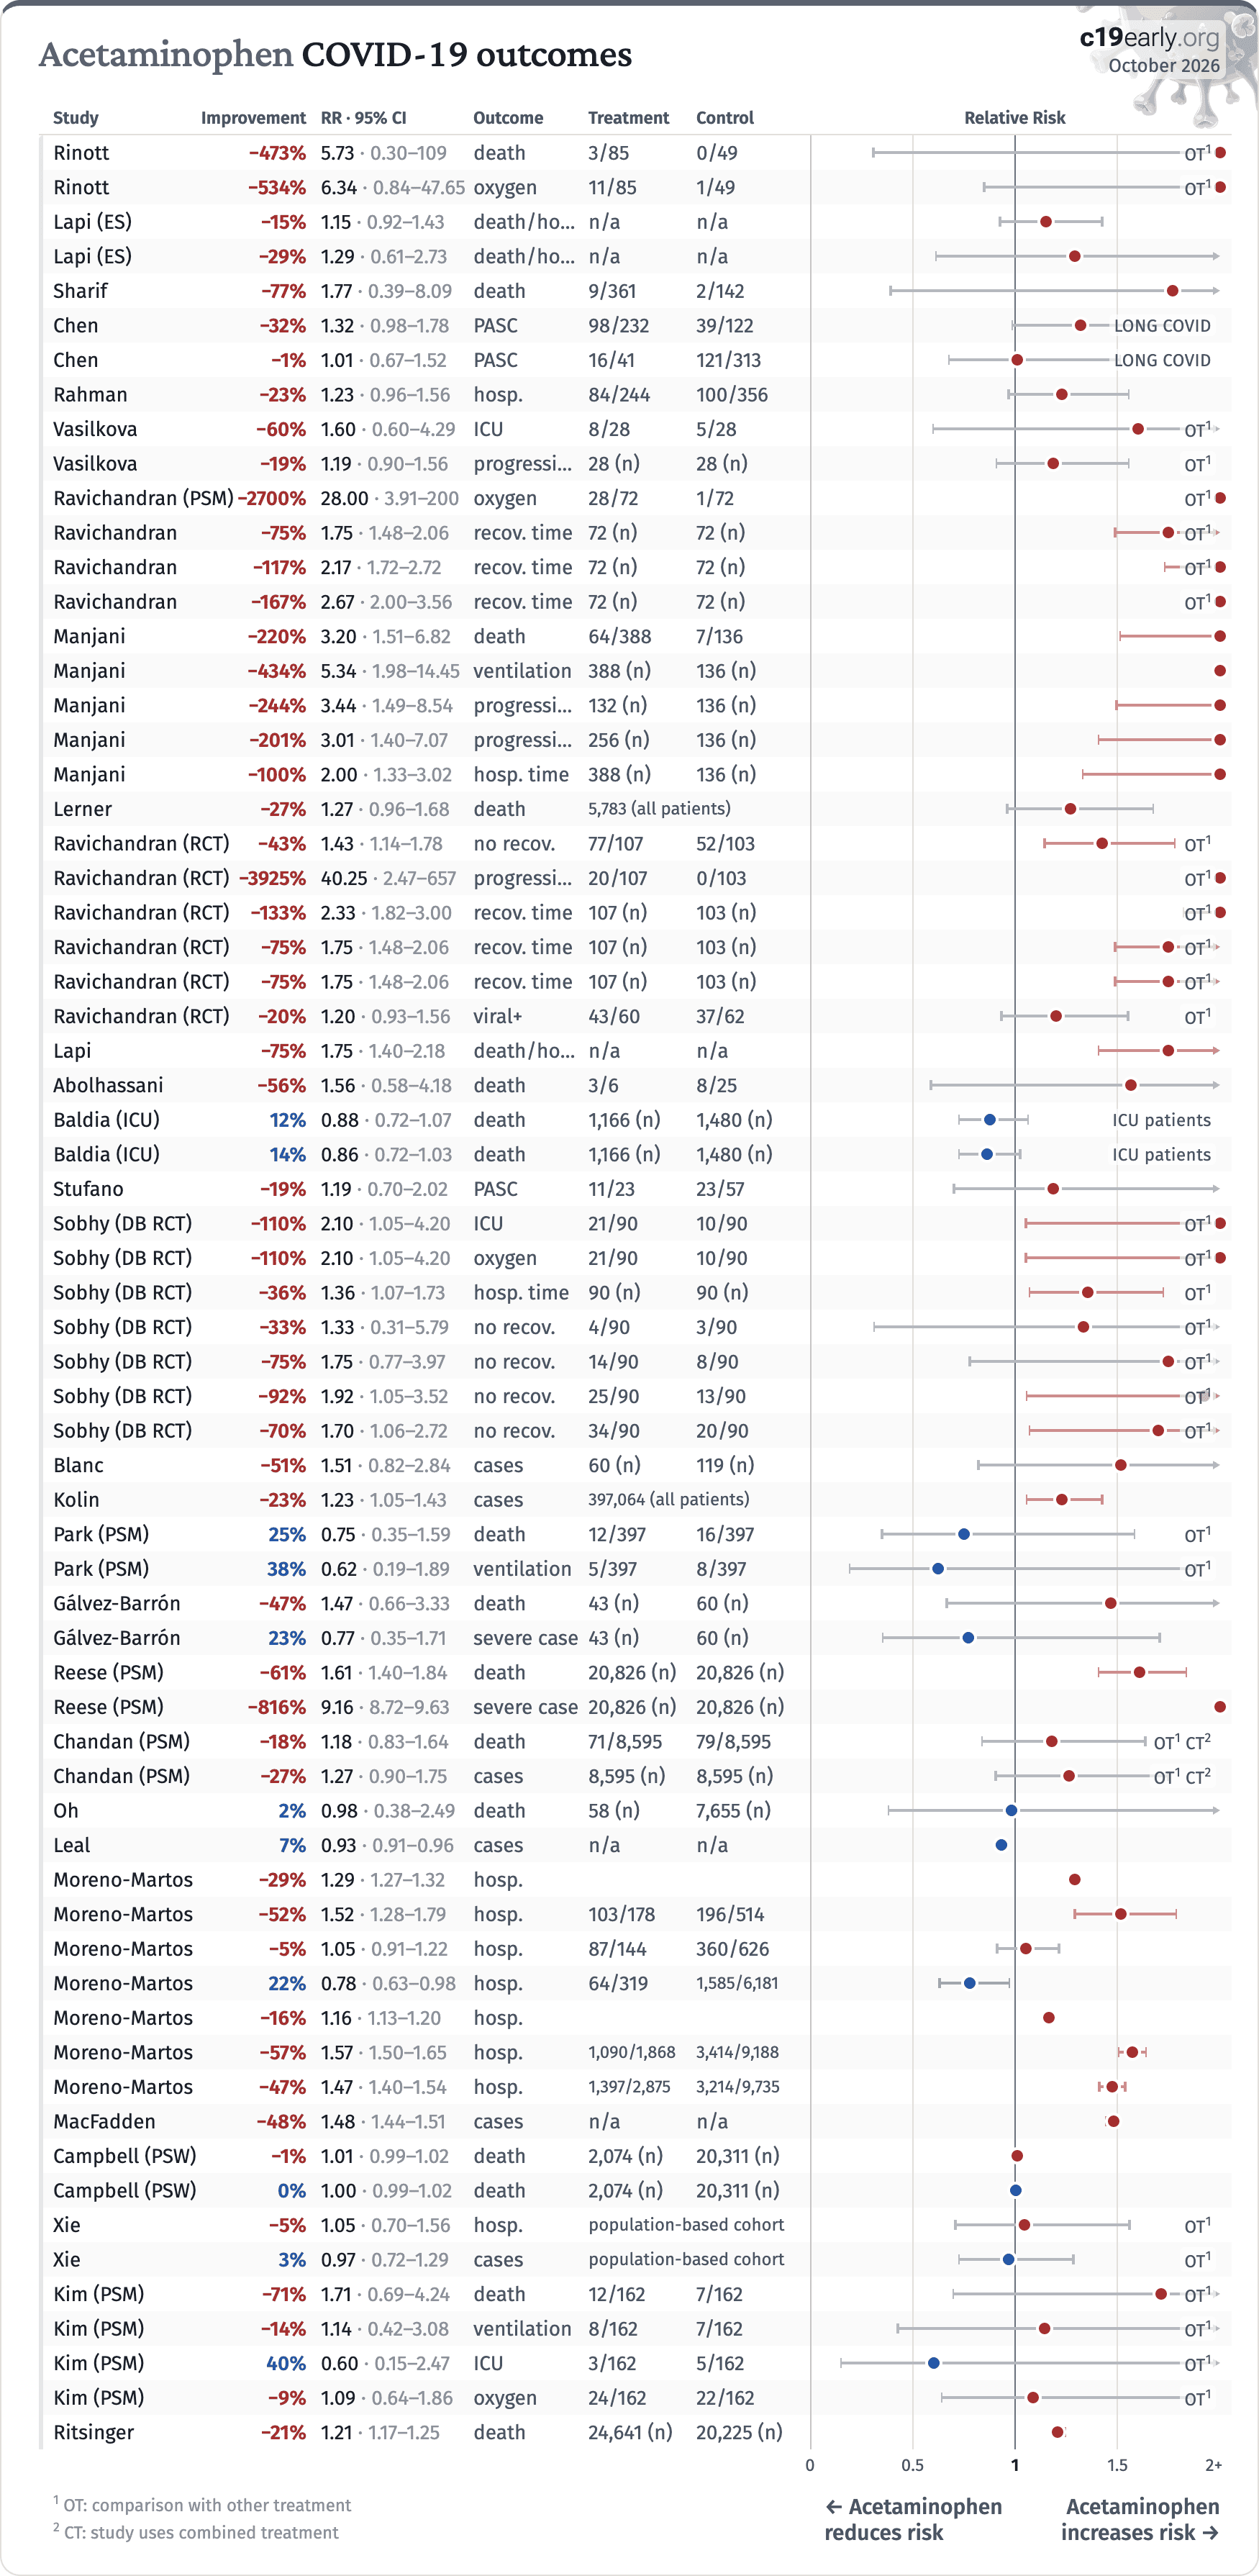
Acetaminophen COVID-19 outcomes
StudyImprovementRR · 95% CIOutcomeTreatmentControlRelative Risk
Rinott−473%5.73 · 0.30–109death3/850/49OT1
Rinott−534%6.34 · 0.84–47.65oxygen11/851/49OT1
Lapi (ES)−15%1.15 · 0.92–1.43death/hosp.n/an/a
Lapi (ES)−29%1.29 · 0.61–2.73death/hosp.n/an/a
Sharif−77%1.77 · 0.39–8.09death9/3612/142
Chen−32%1.32 · 0.98–1.78PASC98/23239/122LONG COVID
Chen−1%1.01 · 0.67–1.52PASC16/41121/313LONG COVID
Rahman−23%1.23 · 0.96–1.56hosp.84/244100/356
Vasilkova−60%1.60 · 0.60–4.29ICU8/285/28OT1
Vasilkova−19%1.19 · 0.90–1.56progression28 (n)28 (n)OT1
Ravichandran (PSM)−2700%28.00 · 3.91–200oxygen28/721/72OT1
Ravichandran−75%1.75 · 1.48–2.06recov. time72 (n)72 (n)OT1
Ravichandran−117%2.17 · 1.72–2.72recov. time72 (n)72 (n)OT1
Ravichandran−167%2.67 · 2.00–3.56recov. time72 (n)72 (n)OT1
Manjani−220%3.20 · 1.51–6.82death64/3887/136
Manjani−434%5.34 · 1.98–14.45ventilation388 (n)136 (n)
Manjani−244%3.44 · 1.49–8.54progression132 (n)136 (n)
Manjani−201%3.01 · 1.40–7.07progression256 (n)136 (n)
Manjani−100%2.00 · 1.33–3.02hosp. time388 (n)136 (n)
Lerner−27%1.27 · 0.96–1.68death5,783 (all patients)
Ravichandran (RCT)−43%1.43 · 1.14–1.78no recov.77/10752/103OT1
Ravichandran (RCT)−3925%40.25 · 2.47–657progression20/1070/103OT1
Ravichandran (RCT)−133%2.33 · 1.82–3.00recov. time107 (n)103 (n)OT1
Ravichandran (RCT)−75%1.75 · 1.48–2.06recov. time107 (n)103 (n)OT1
Ravichandran (RCT)−75%1.75 · 1.48–2.06recov. time107 (n)103 (n)OT1
Ravichandran (RCT)−20%1.20 · 0.93–1.56viral+43/6037/62OT1
Lapi−75%1.75 · 1.40–2.18death/hosp.n/an/a
Abolhassani−56%1.56 · 0.58–4.18death3/68/25
Baldia (ICU)12%0.88 · 0.72–1.07death1,166 (n)1,480 (n)ICU patients
Baldia (ICU)14%0.86 · 0.72–1.03death1,166 (n)1,480 (n)ICU patients
Stufano−19%1.19 · 0.70–2.02PASC11/2323/57
Sobhy (DB RCT)−110%2.10 · 1.05–4.20ICU21/9010/90OT1
Sobhy (DB RCT)−110%2.10 · 1.05–4.20oxygen21/9010/90OT1
Sobhy (DB RCT)−36%1.36 · 1.07–1.73hosp. time90 (n)90 (n)OT1
Sobhy (DB RCT)−33%1.33 · 0.31–5.79no recov.4/903/90OT1
Sobhy (DB RCT)−75%1.75 · 0.77–3.97no recov.14/908/90OT1
Sobhy (DB RCT)−92%1.92 · 1.05–3.52no recov.25/9013/90OT1
Sobhy (DB RCT)−70%1.70 · 1.06–2.72no recov.34/9020/90OT1
Blanc−51%1.51 · 0.82–2.84cases60 (n)119 (n)
Kolin−23%1.23 · 1.05–1.43cases397,064 (all patients)
Park (PSM)25%0.75 · 0.35–1.59death12/39716/397OT1
Park (PSM)38%0.62 · 0.19–1.89ventilation5/3978/397OT1
Gálvez-Barrón−47%1.47 · 0.66–3.33death43 (n)60 (n)
Gálvez-Barrón23%0.77 · 0.35–1.71severe case43 (n)60 (n)
Reese (PSM)−61%1.61 · 1.40–1.84death20,826 (n)20,826 (n)
Reese (PSM)−816%9.16 · 8.72–9.63severe case20,826 (n)20,826 (n)
Chandan (PSM)−18%1.18 · 0.83–1.64death71/8,59579/8,595OT1 CT2
Chandan (PSM)−27%1.27 · 0.90–1.75cases8,595 (n)8,595 (n)OT1 CT2
Oh2%0.98 · 0.38–2.49death58 (n)7,655 (n)
Leal7%0.93 · 0.91–0.96casesn/an/a
Moreno-Martos−29%1.29 · 1.27–1.32hosp.
Moreno-Martos−52%1.52 · 1.28–1.79hosp.103/178196/514
Moreno-Martos−5%1.05 · 0.91–1.22hosp.87/144360/626
Moreno-Martos22%0.78 · 0.63–0.98hosp.64/3191,585/6,181
Moreno-Martos−16%1.16 · 1.13–1.20hosp.
Moreno-Martos−57%1.57 · 1.50–1.65hosp.1,090/1,8683,414/9,188
Moreno-Martos−47%1.47 · 1.40–1.54hosp.1,397/2,8753,214/9,735
MacFadden−48%1.48 · 1.44–1.51casesn/an/a
Campbell (PSW)−1%1.01 · 0.99–1.02death2,074 (n)20,311 (n)
Campbell (PSW)0%1.00 · 0.99–1.02death2,074 (n)20,311 (n)
Xie−5%1.05 · 0.70–1.56hosp.population-based cohortOT1
Xie3%0.97 · 0.72–1.29casespopulation-based cohortOT1
Kim (PSM)−71%1.71 · 0.69–4.24death12/1627/162OT1
Kim (PSM)−14%1.14 · 0.42–3.08ventilation8/1627/162OT1
Kim (PSM)40%0.60 · 0.15–2.47ICU3/1625/162OT1
Kim (PSM)−9%1.09 · 0.64–1.86oxygen24/16222/162OT1
Ritsinger−21%1.21 · 1.17–1.25death24,641 (n)20,225 (n)
00.511.52+