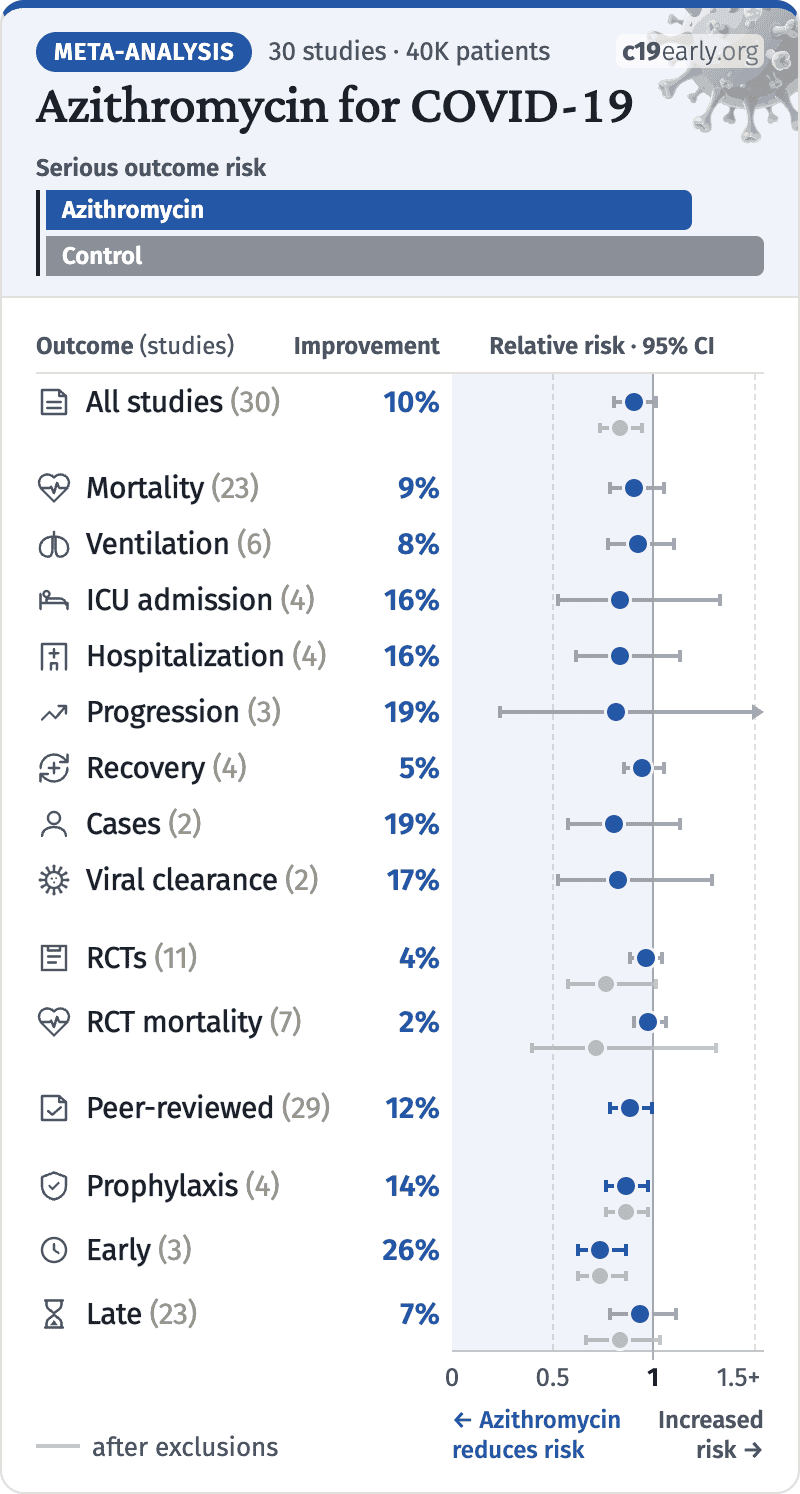
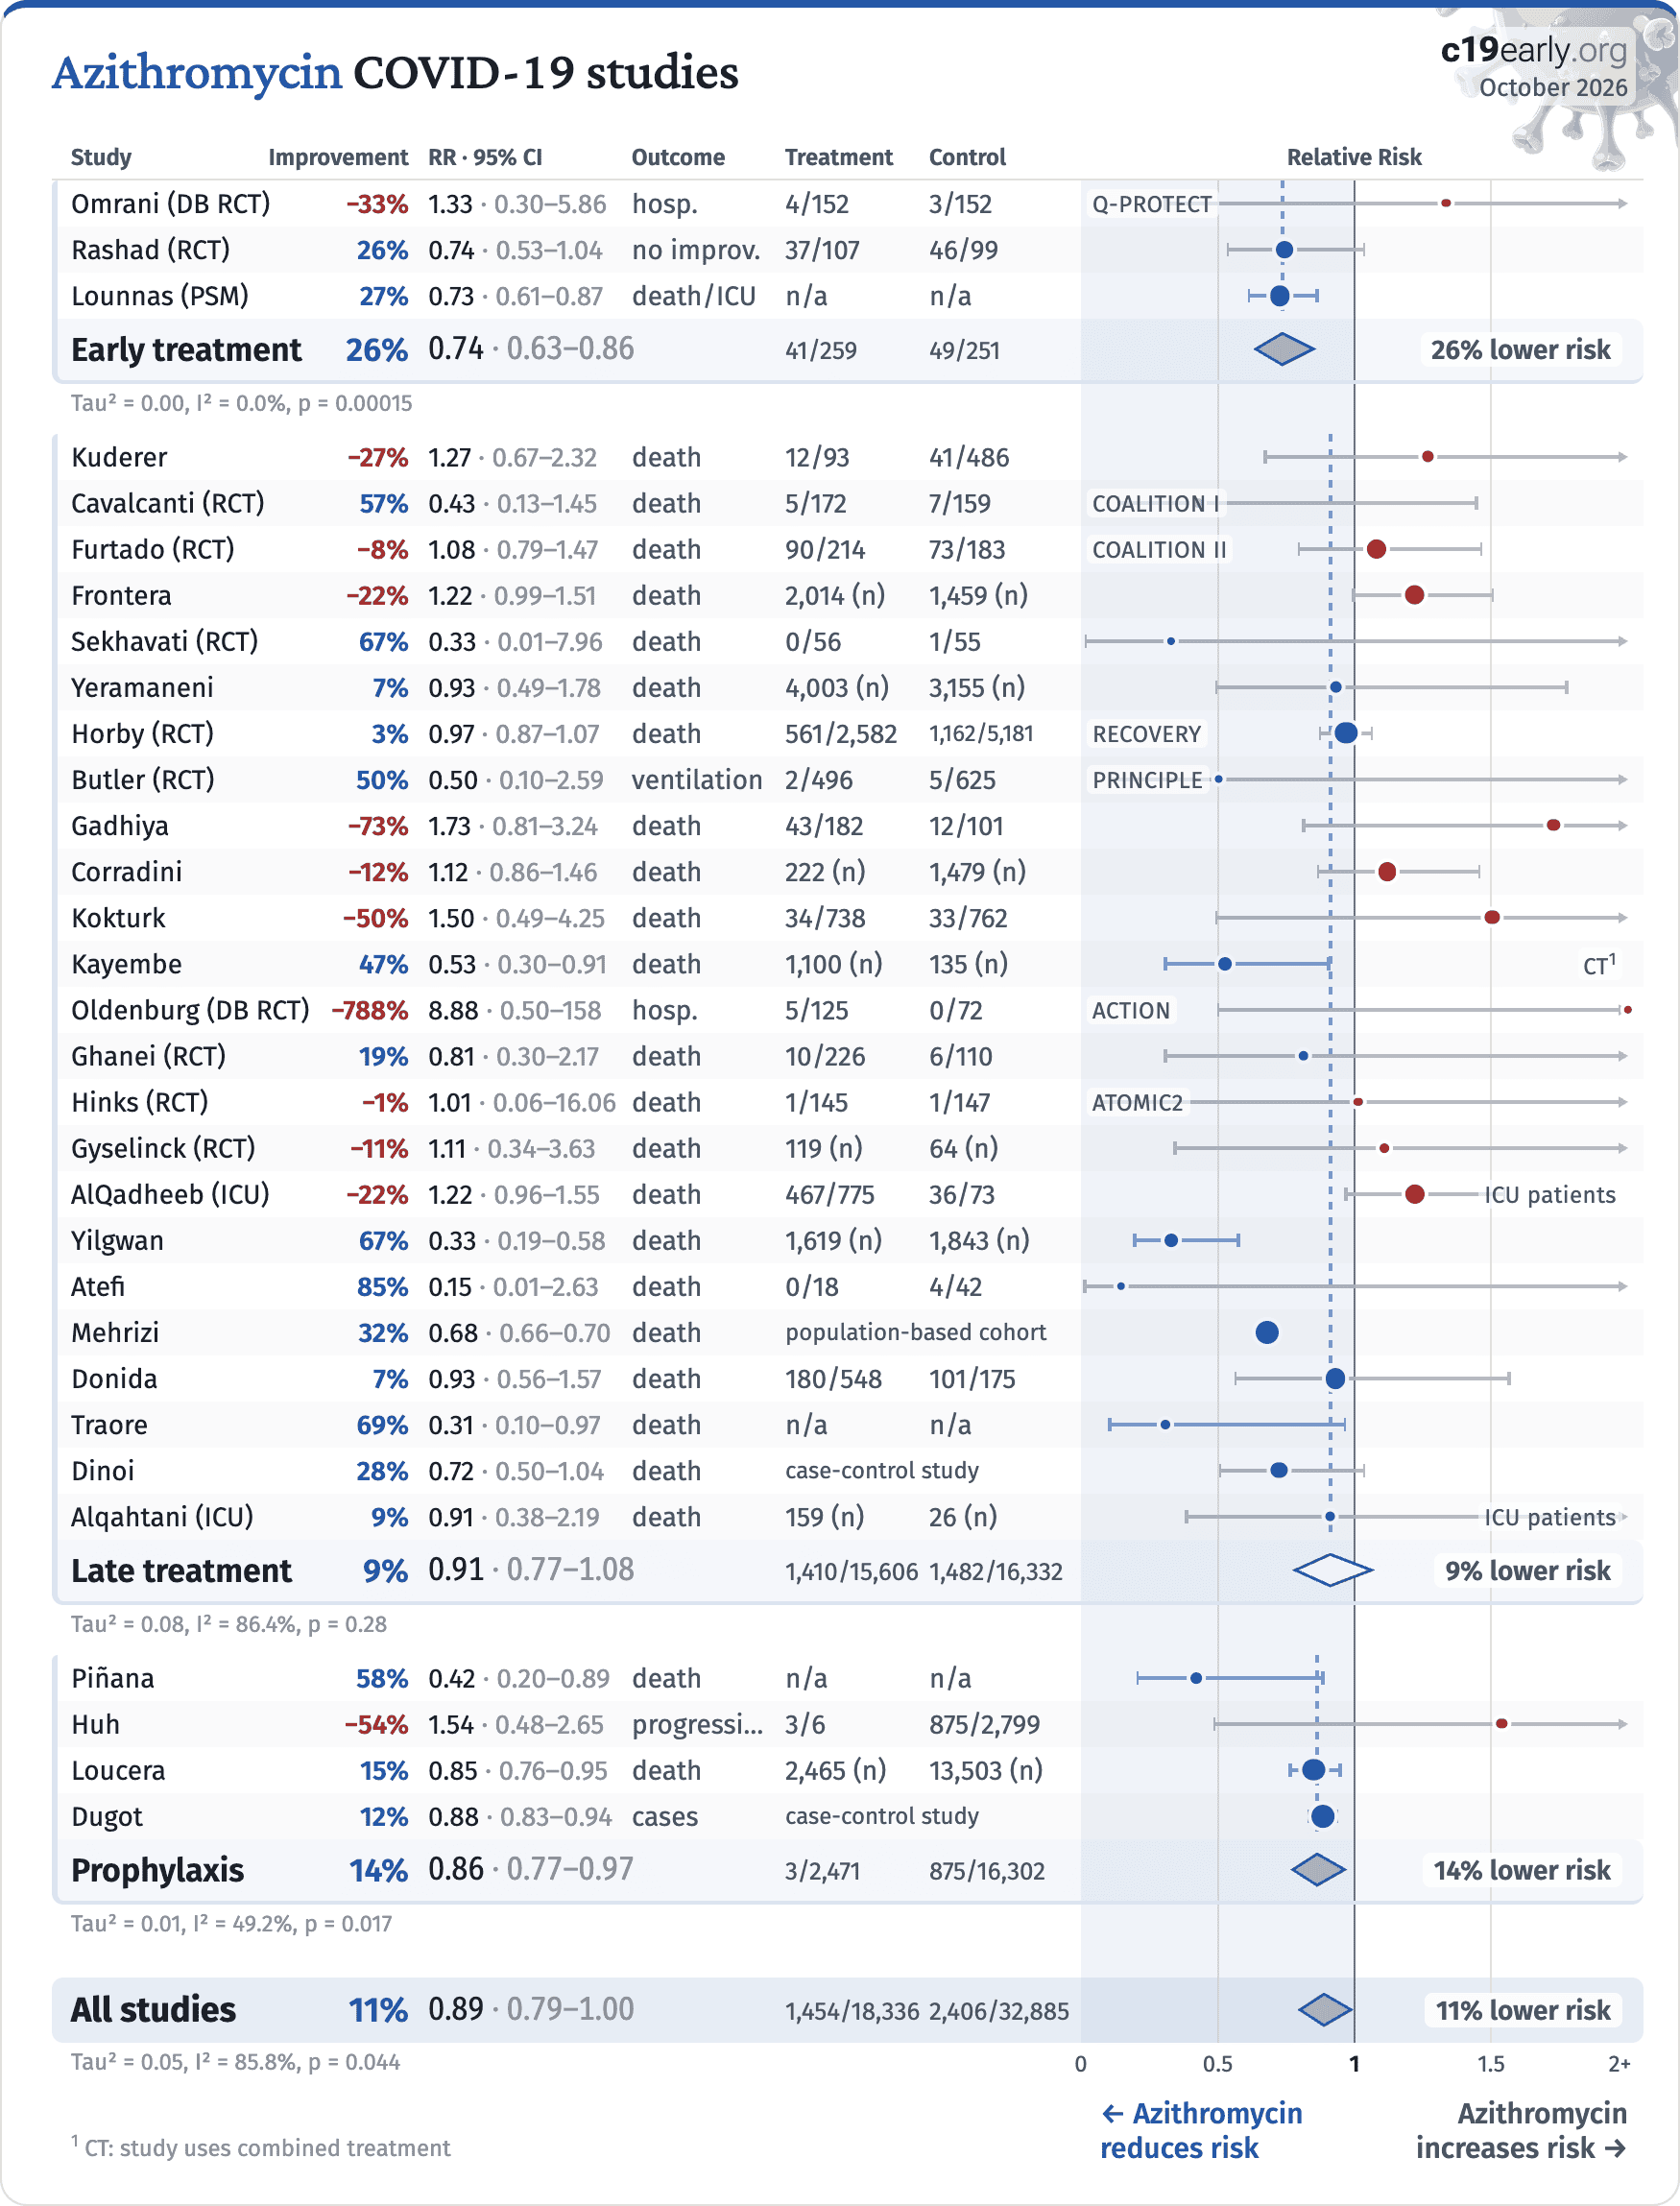
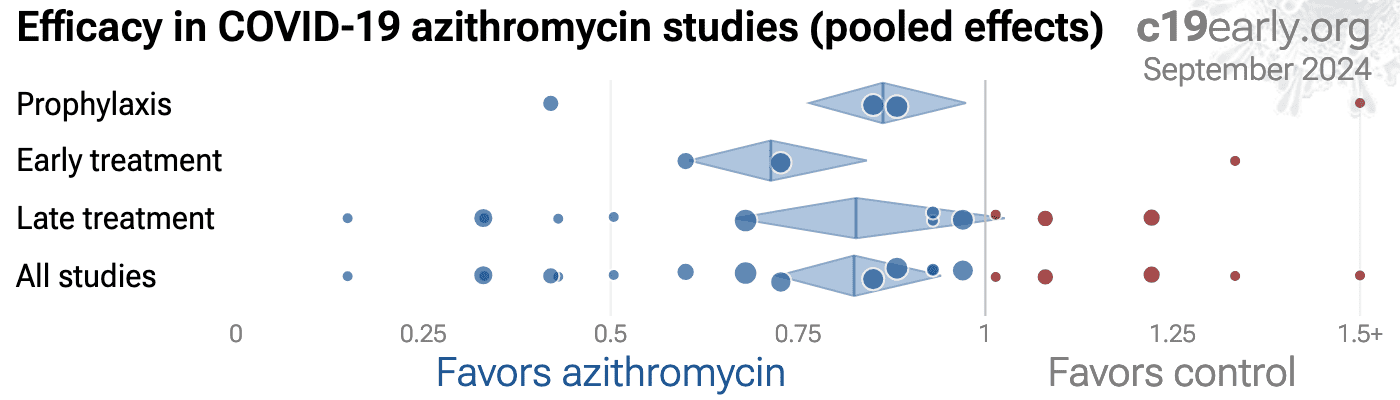
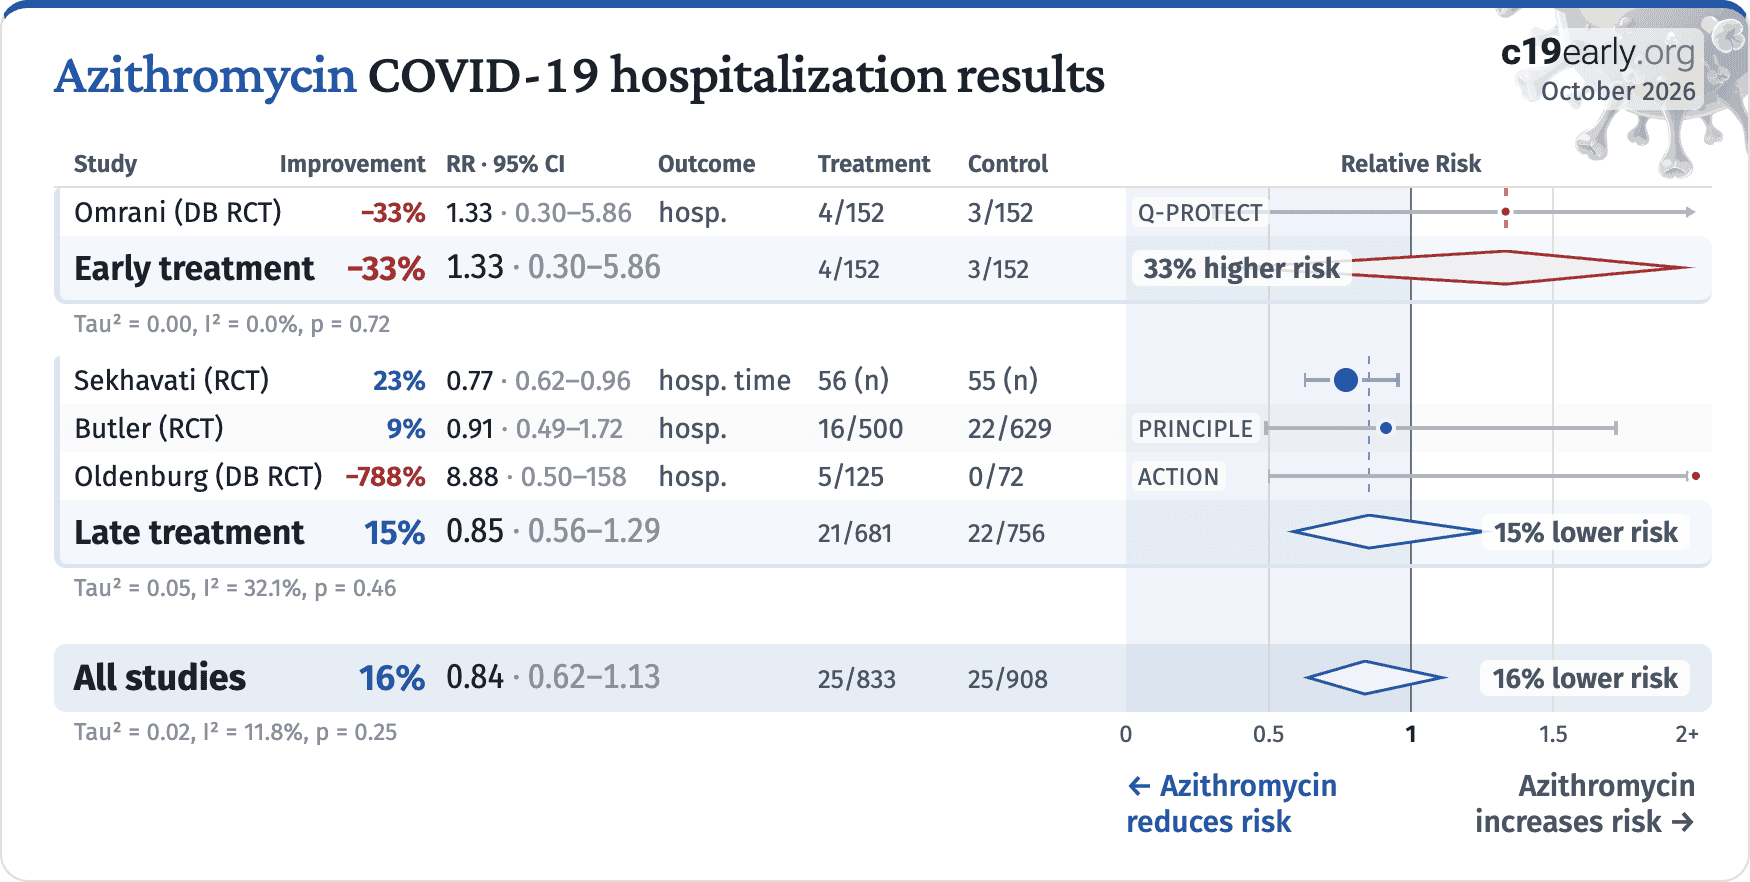
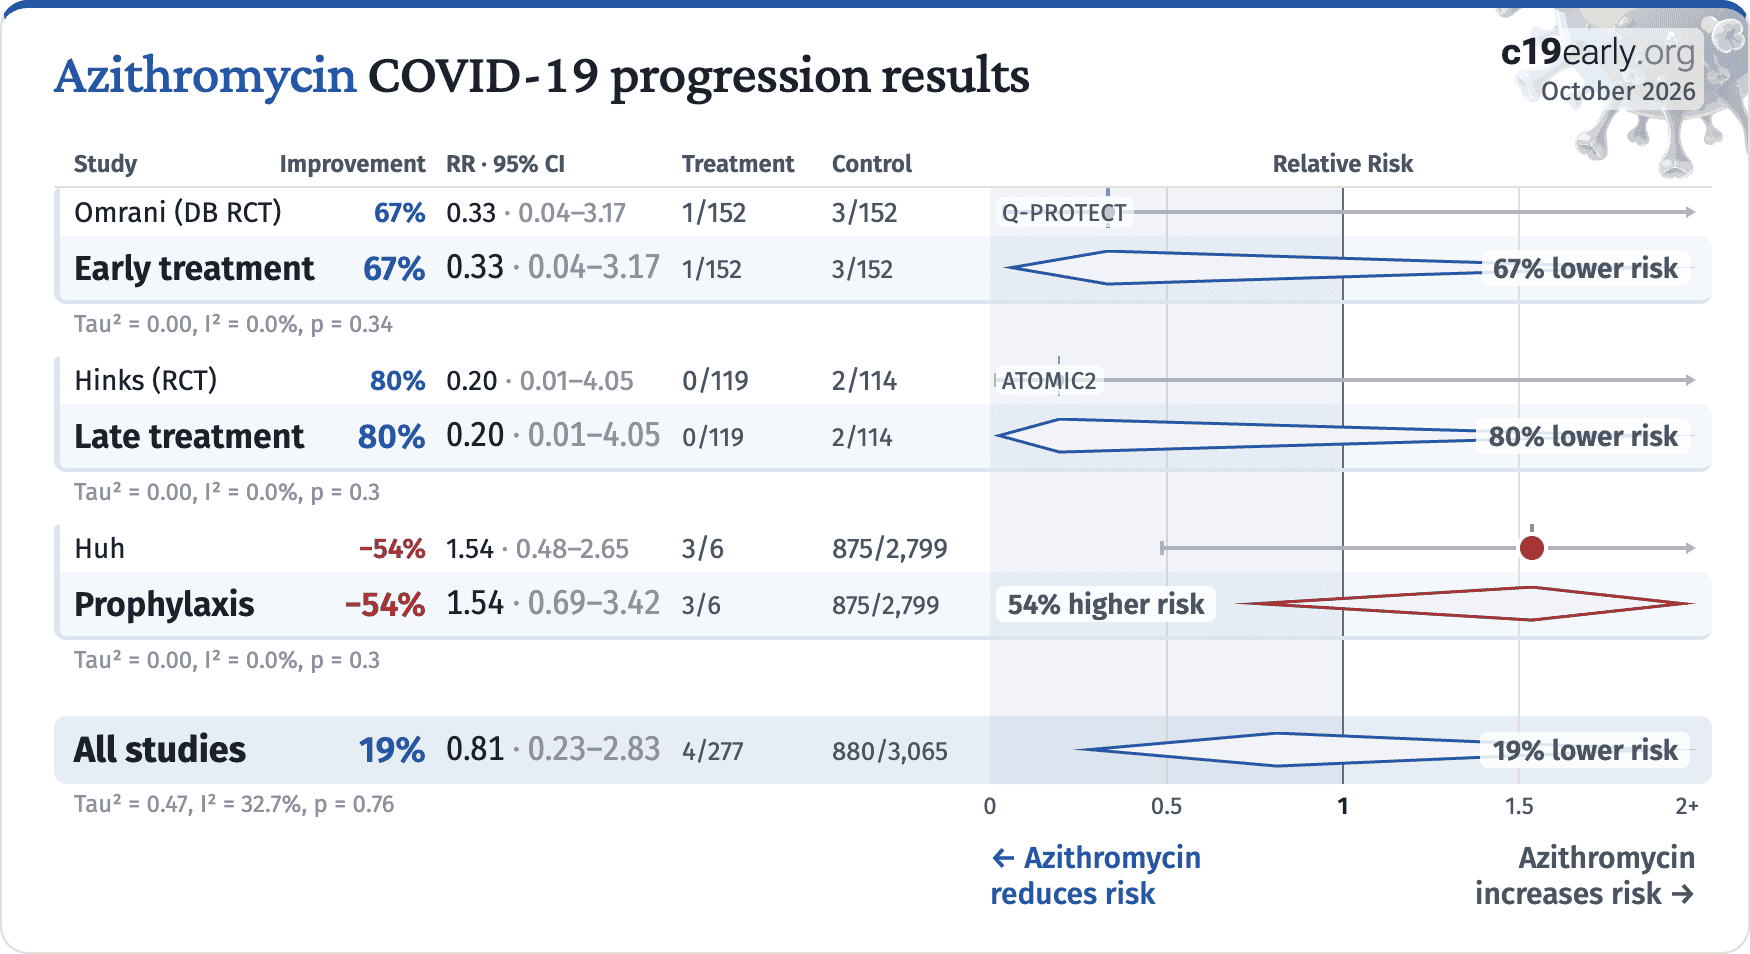
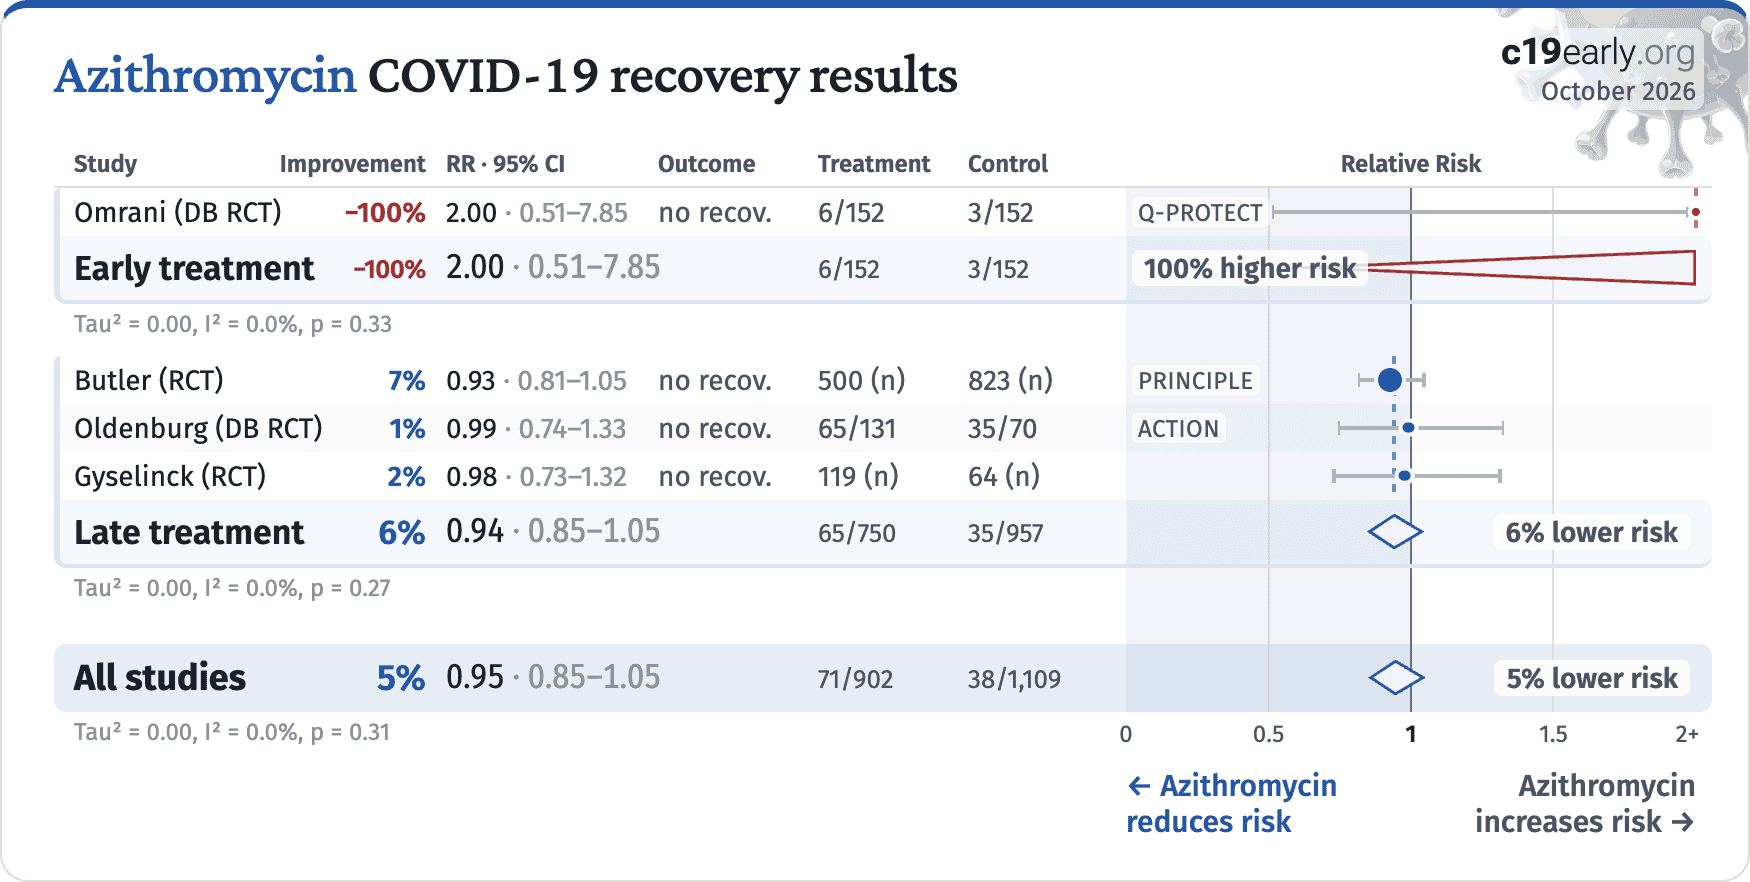
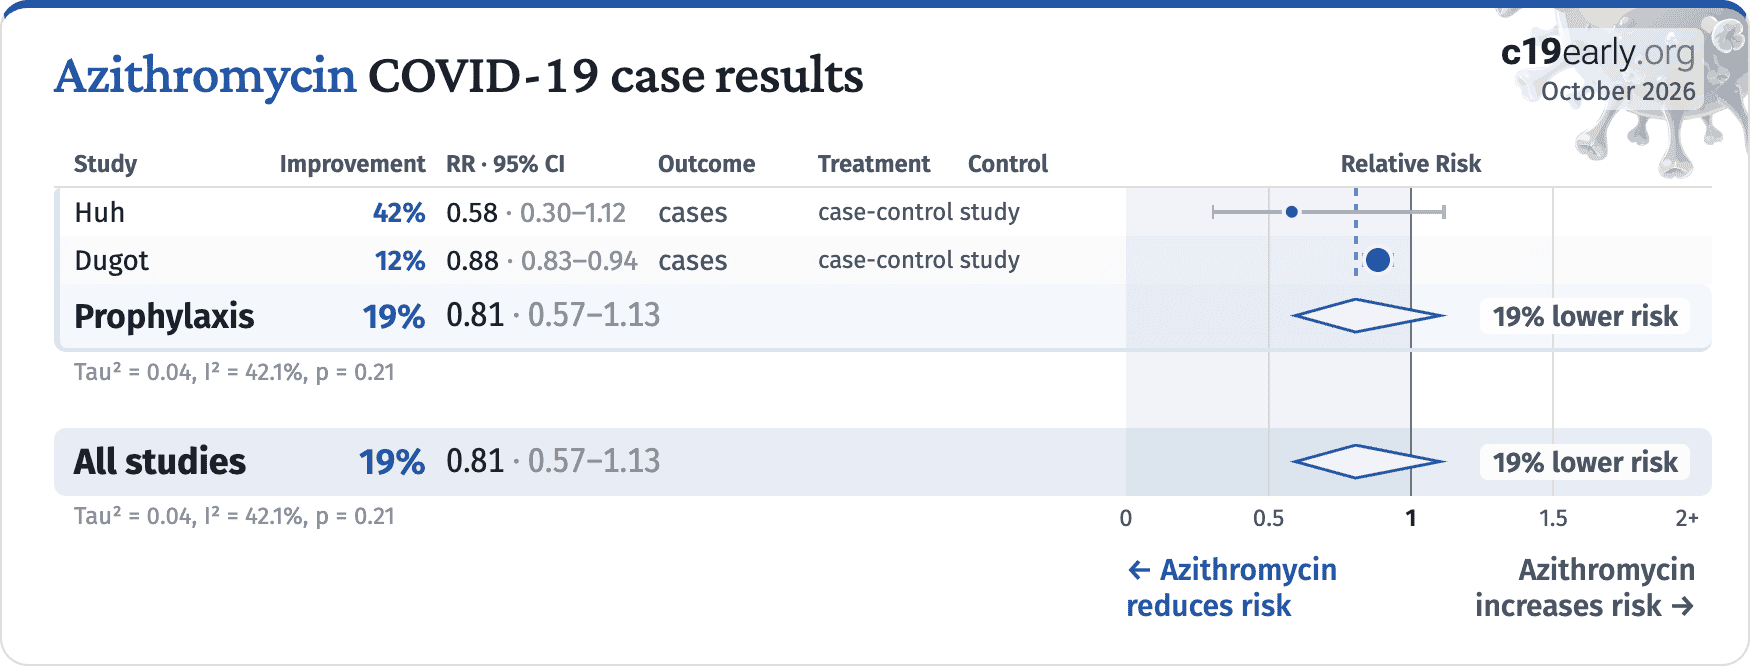
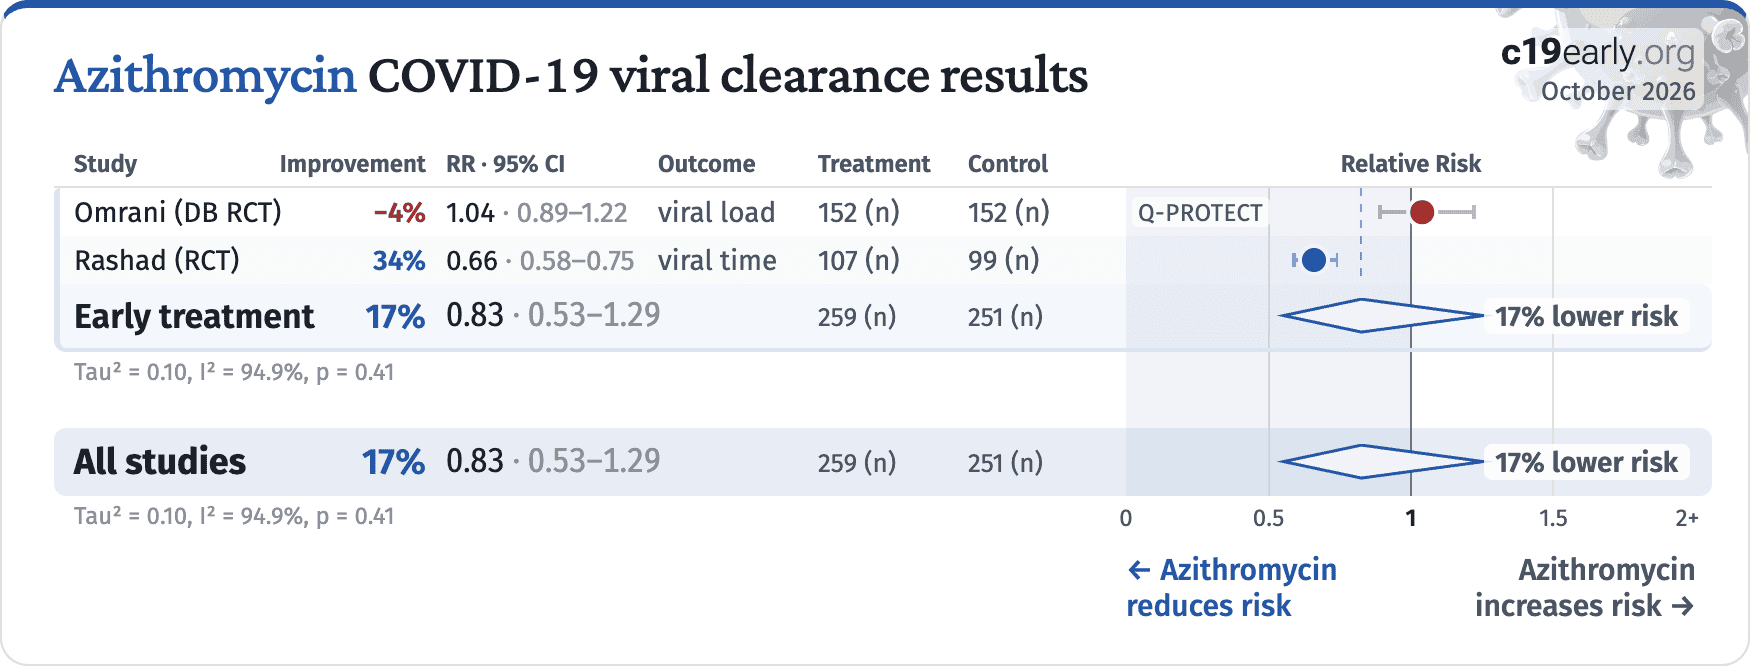
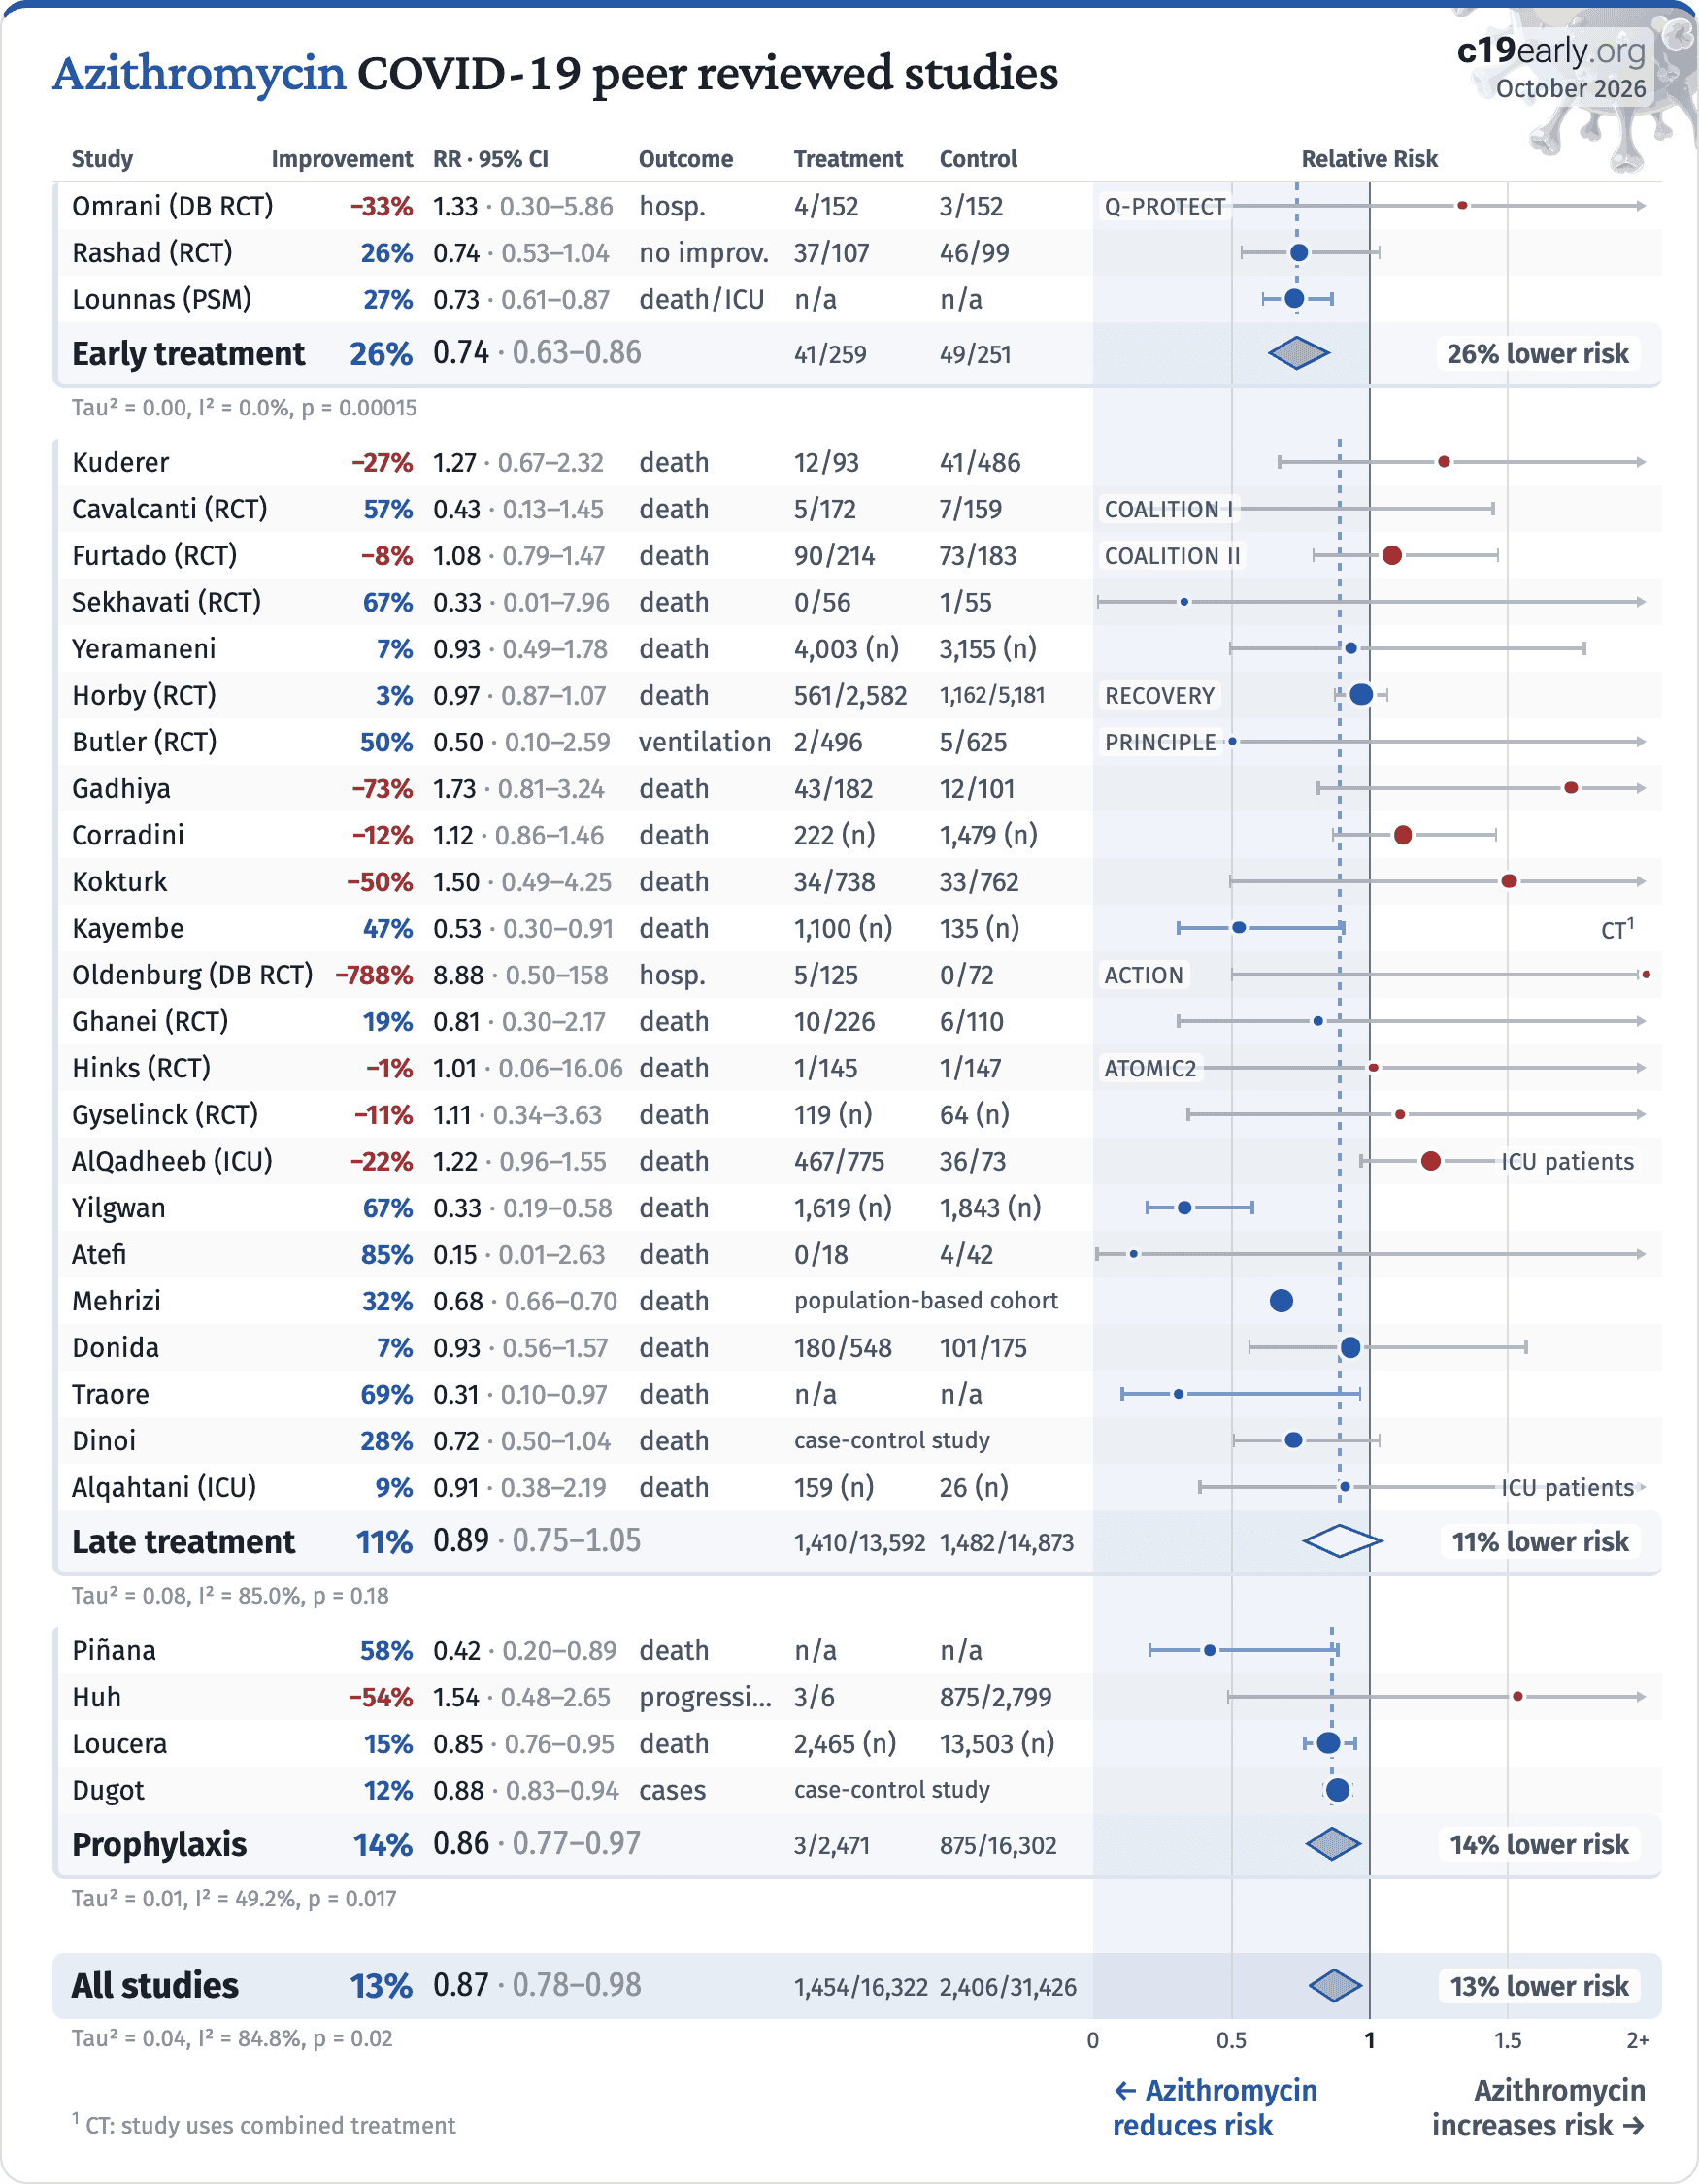
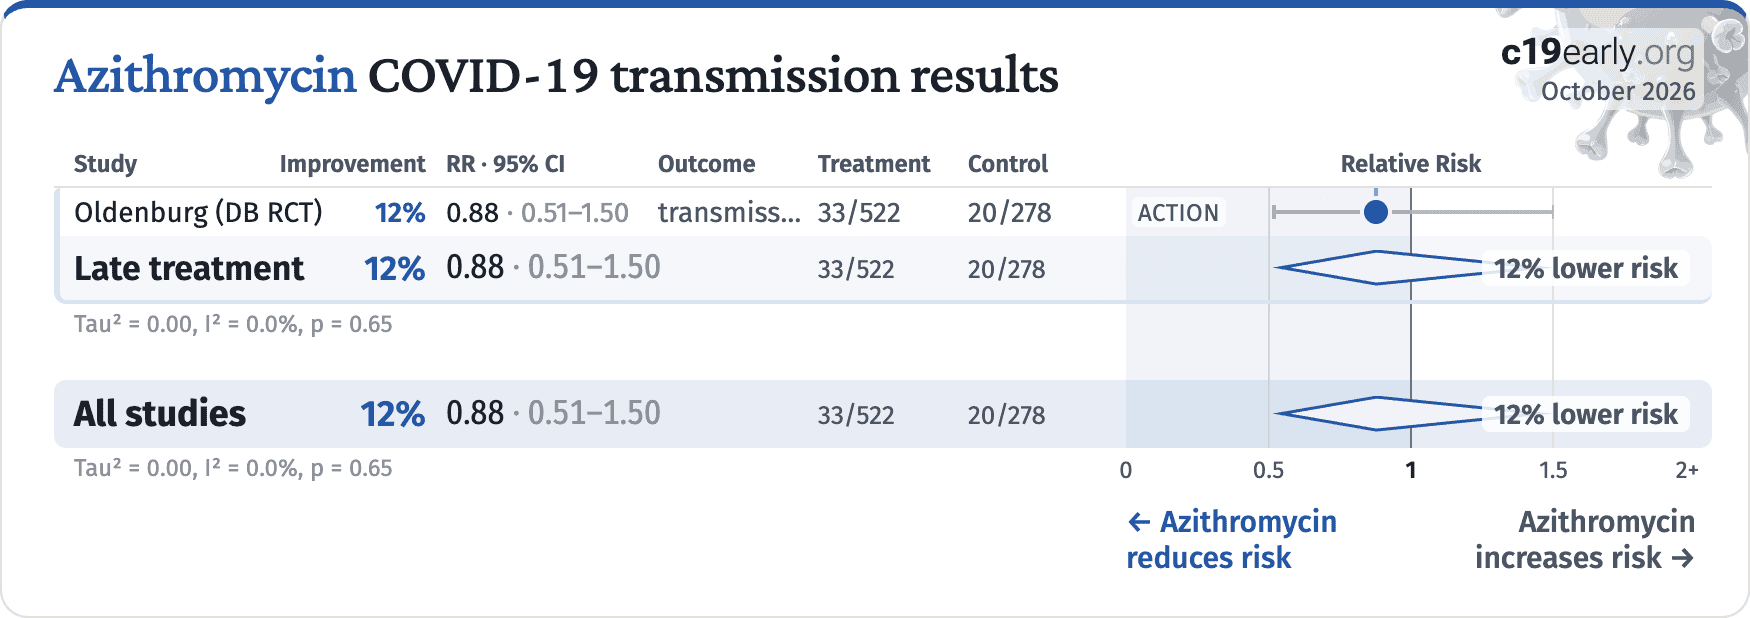
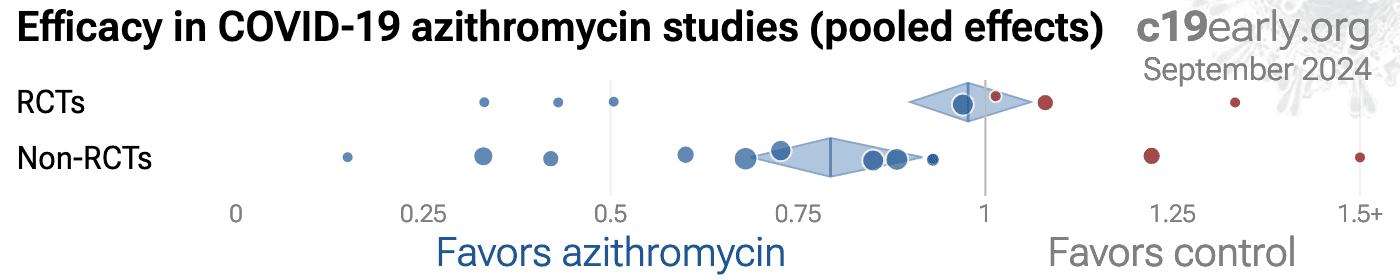
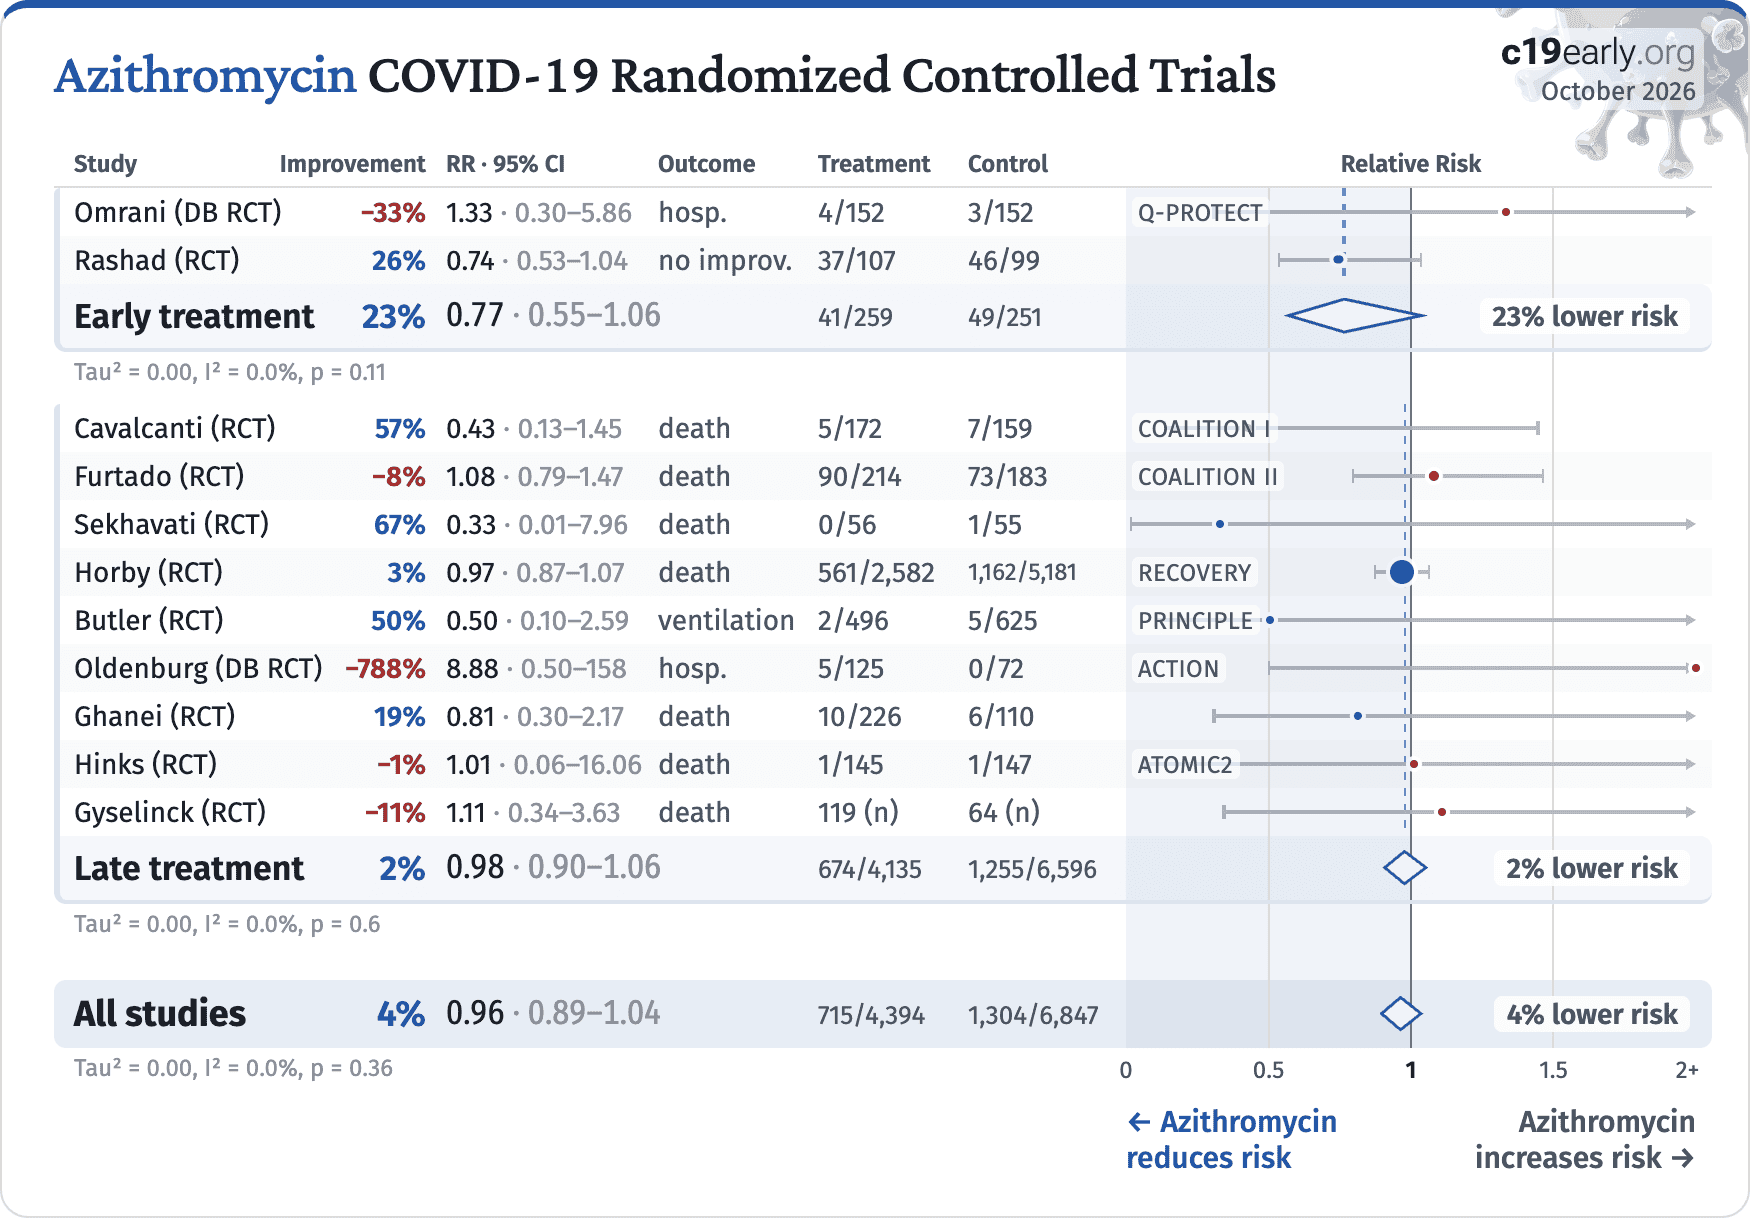
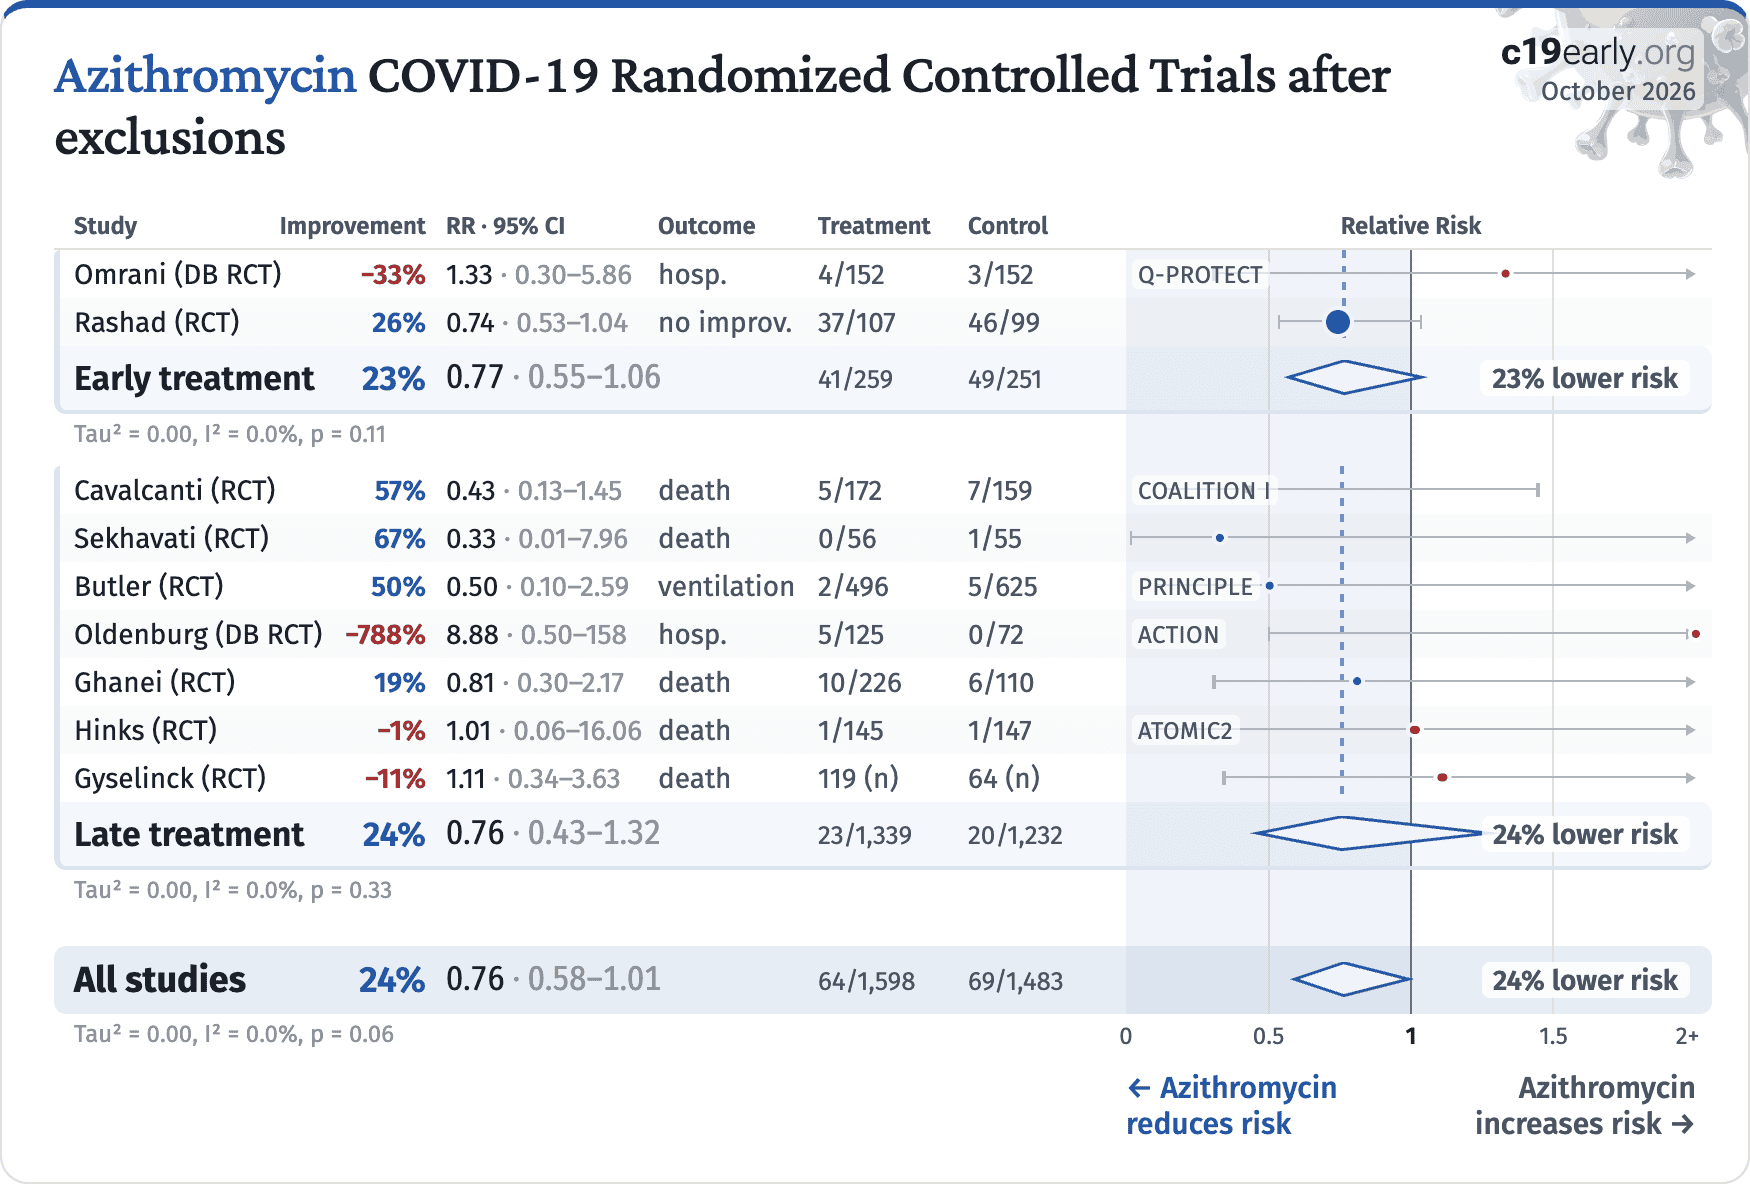
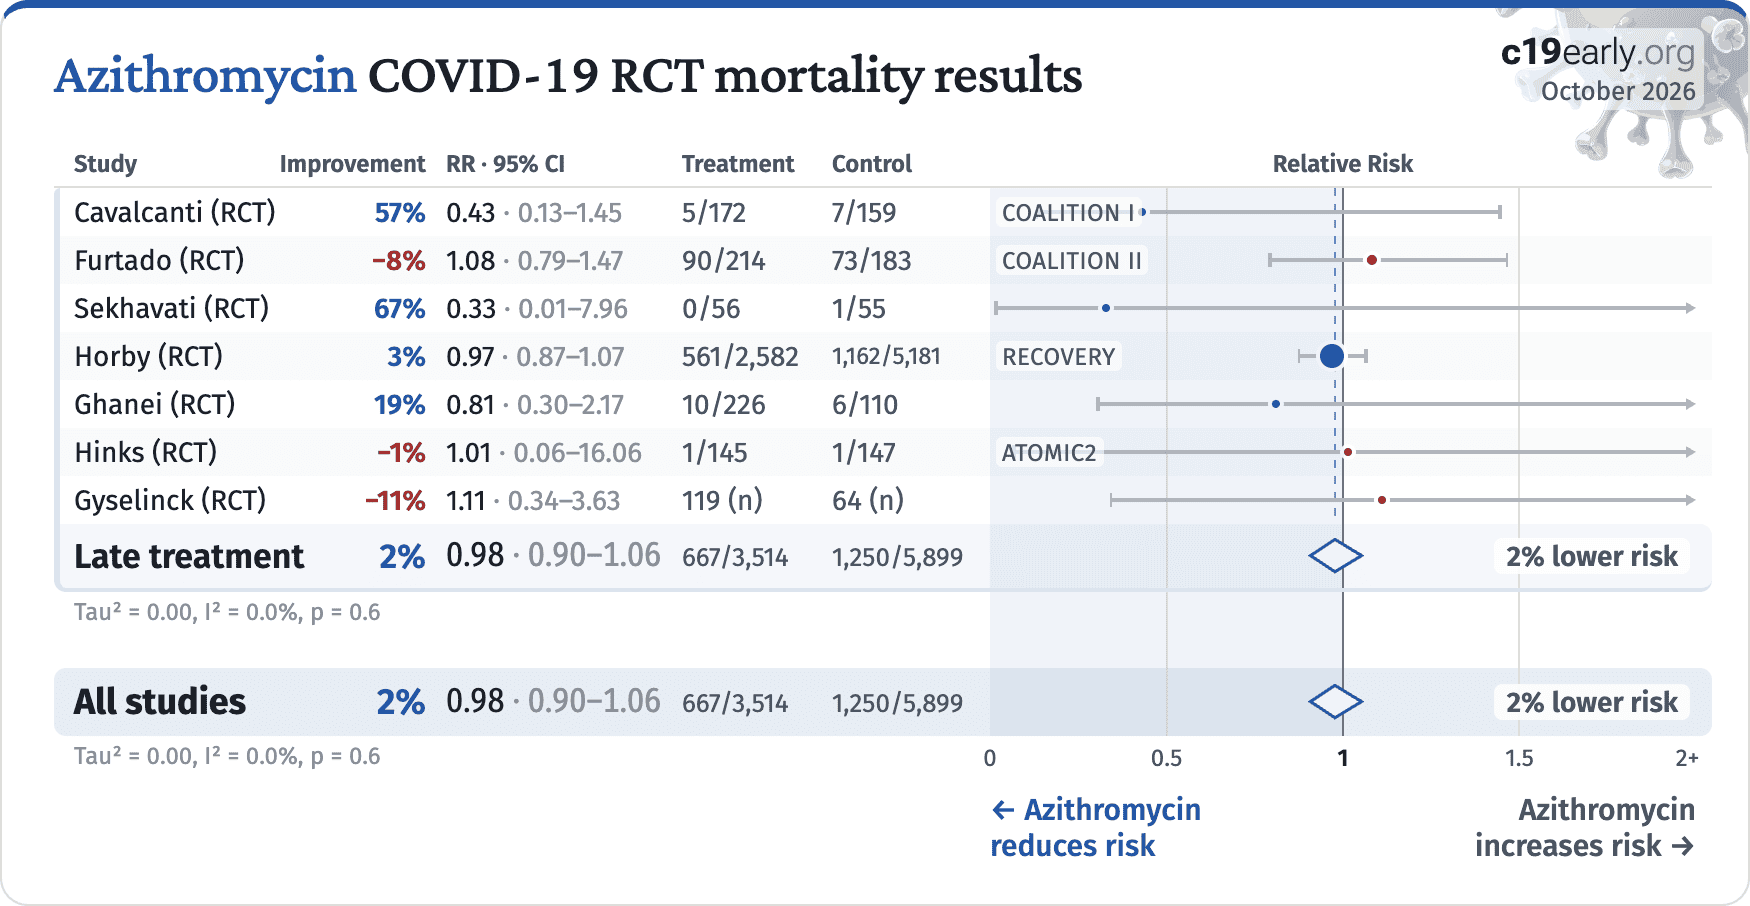
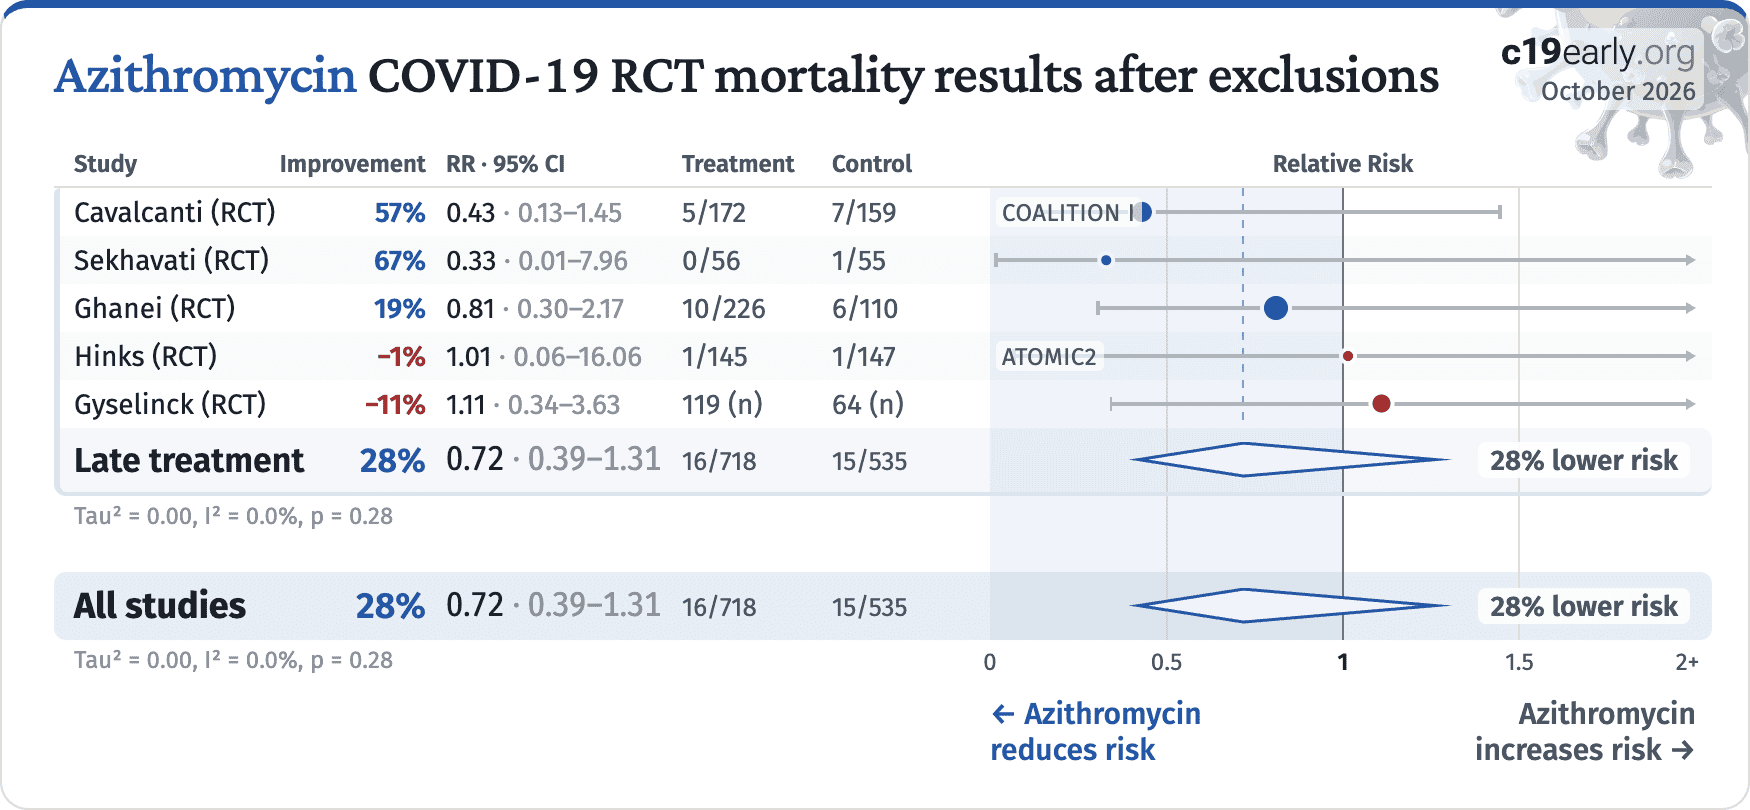
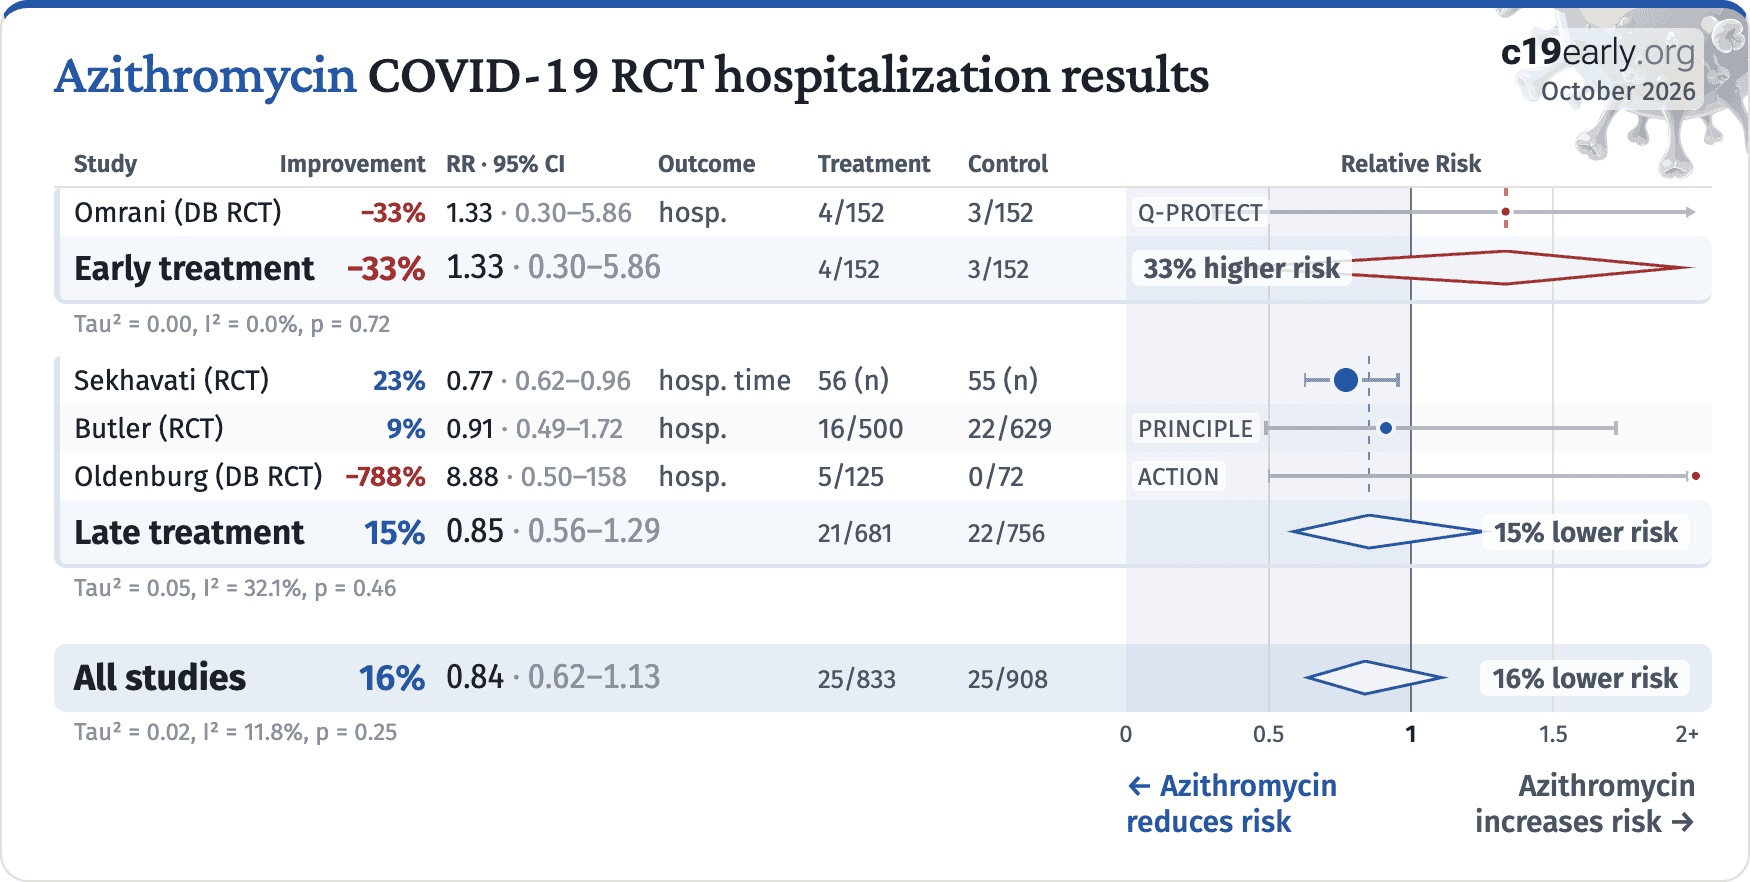
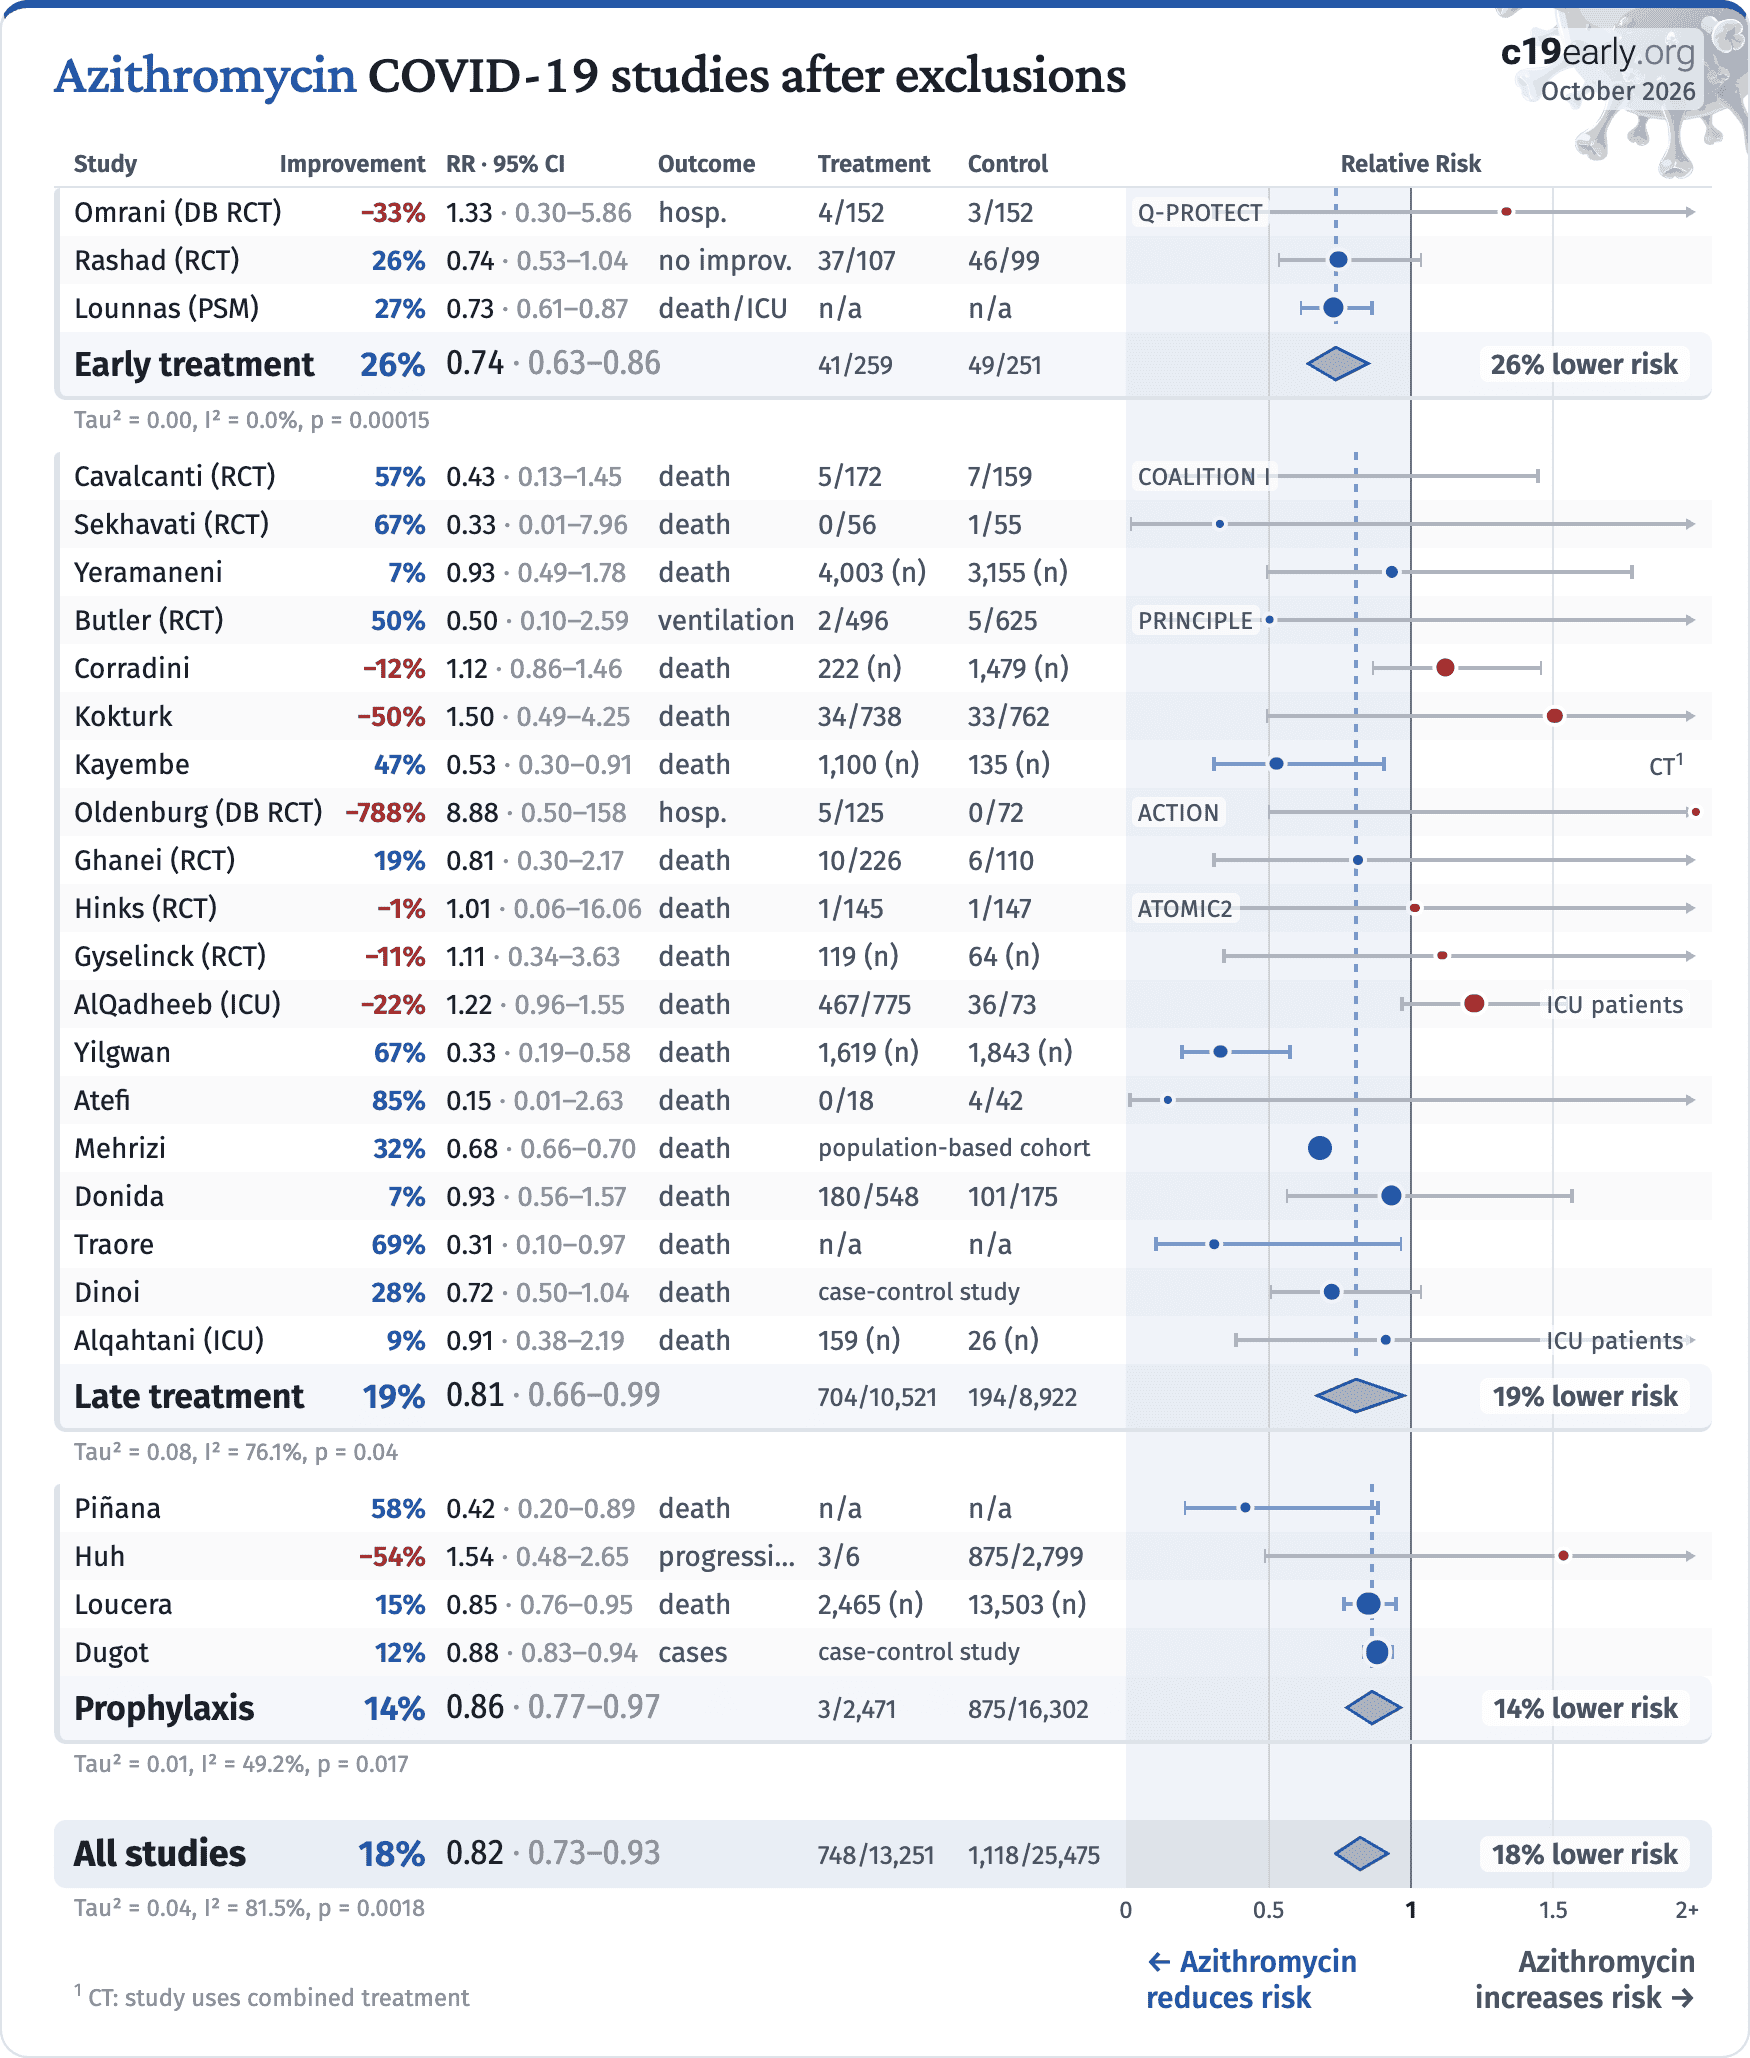
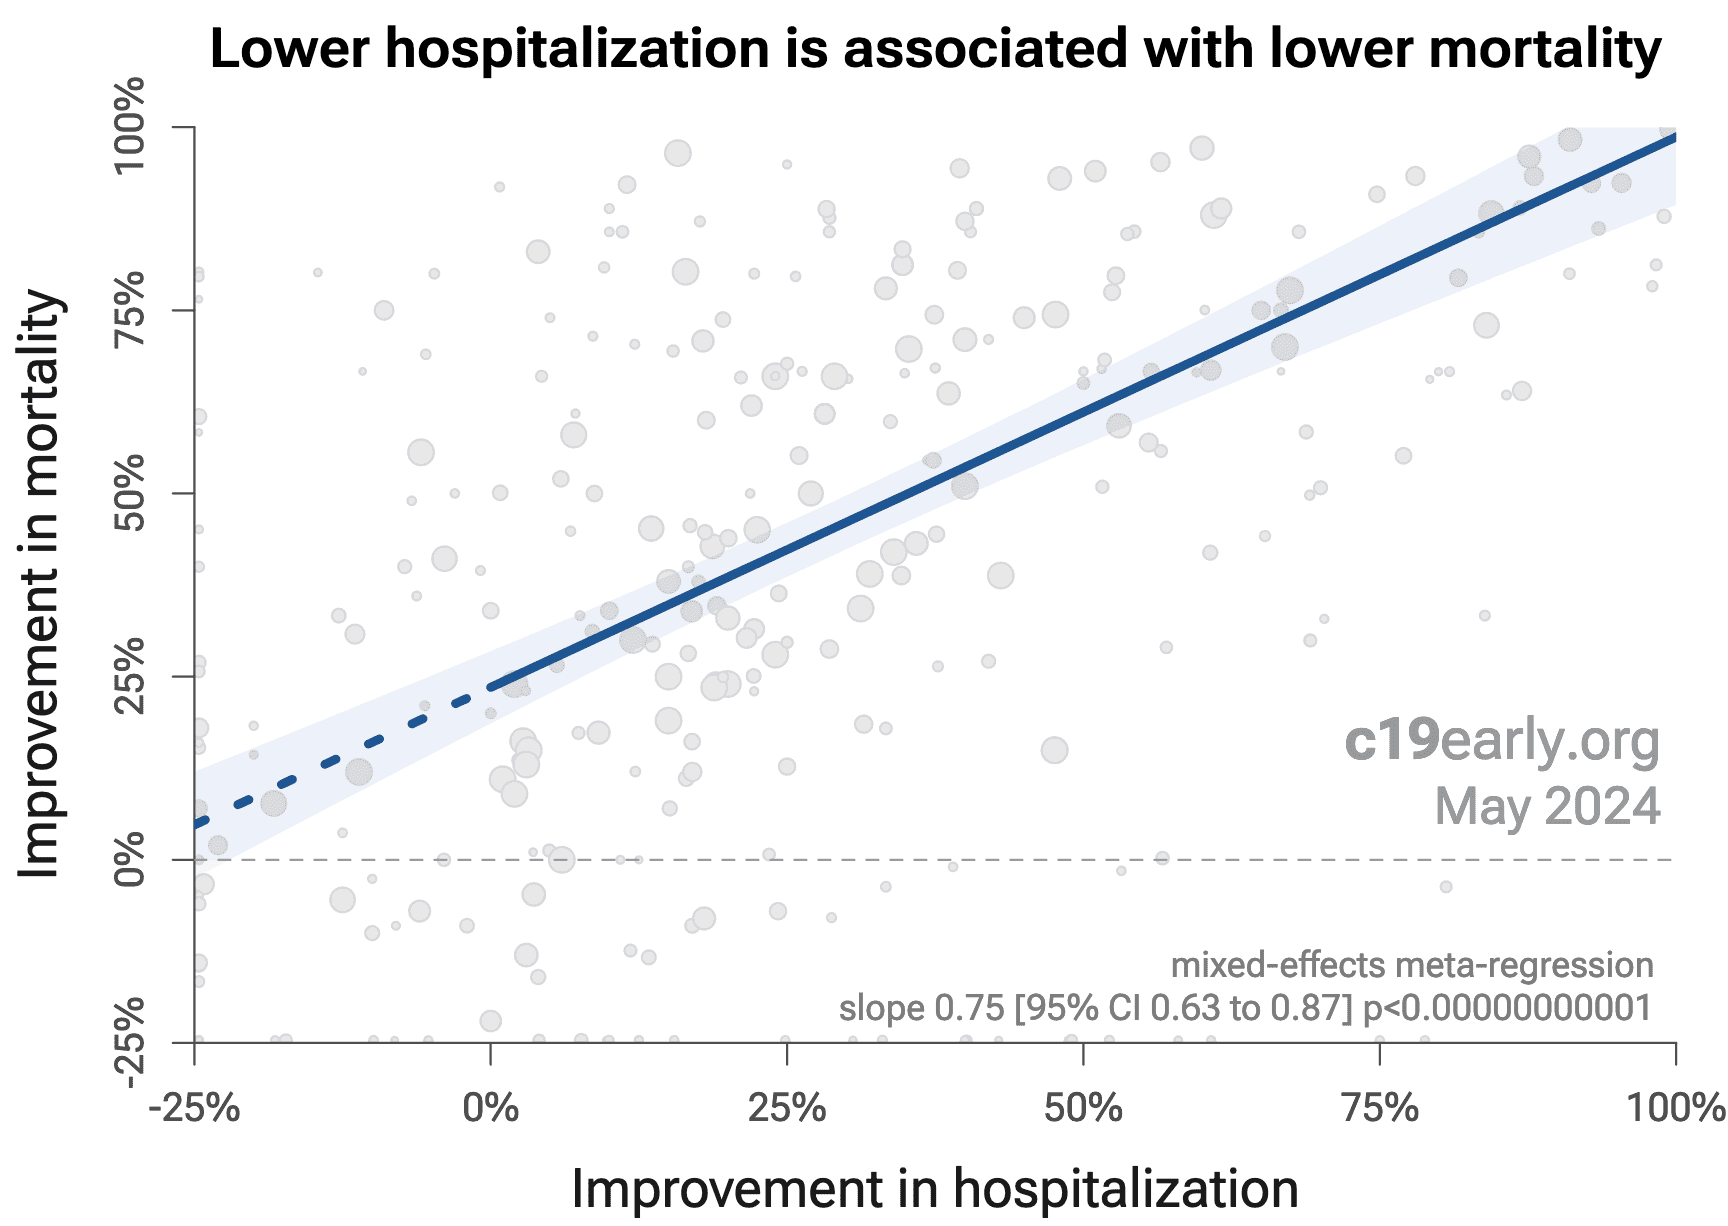
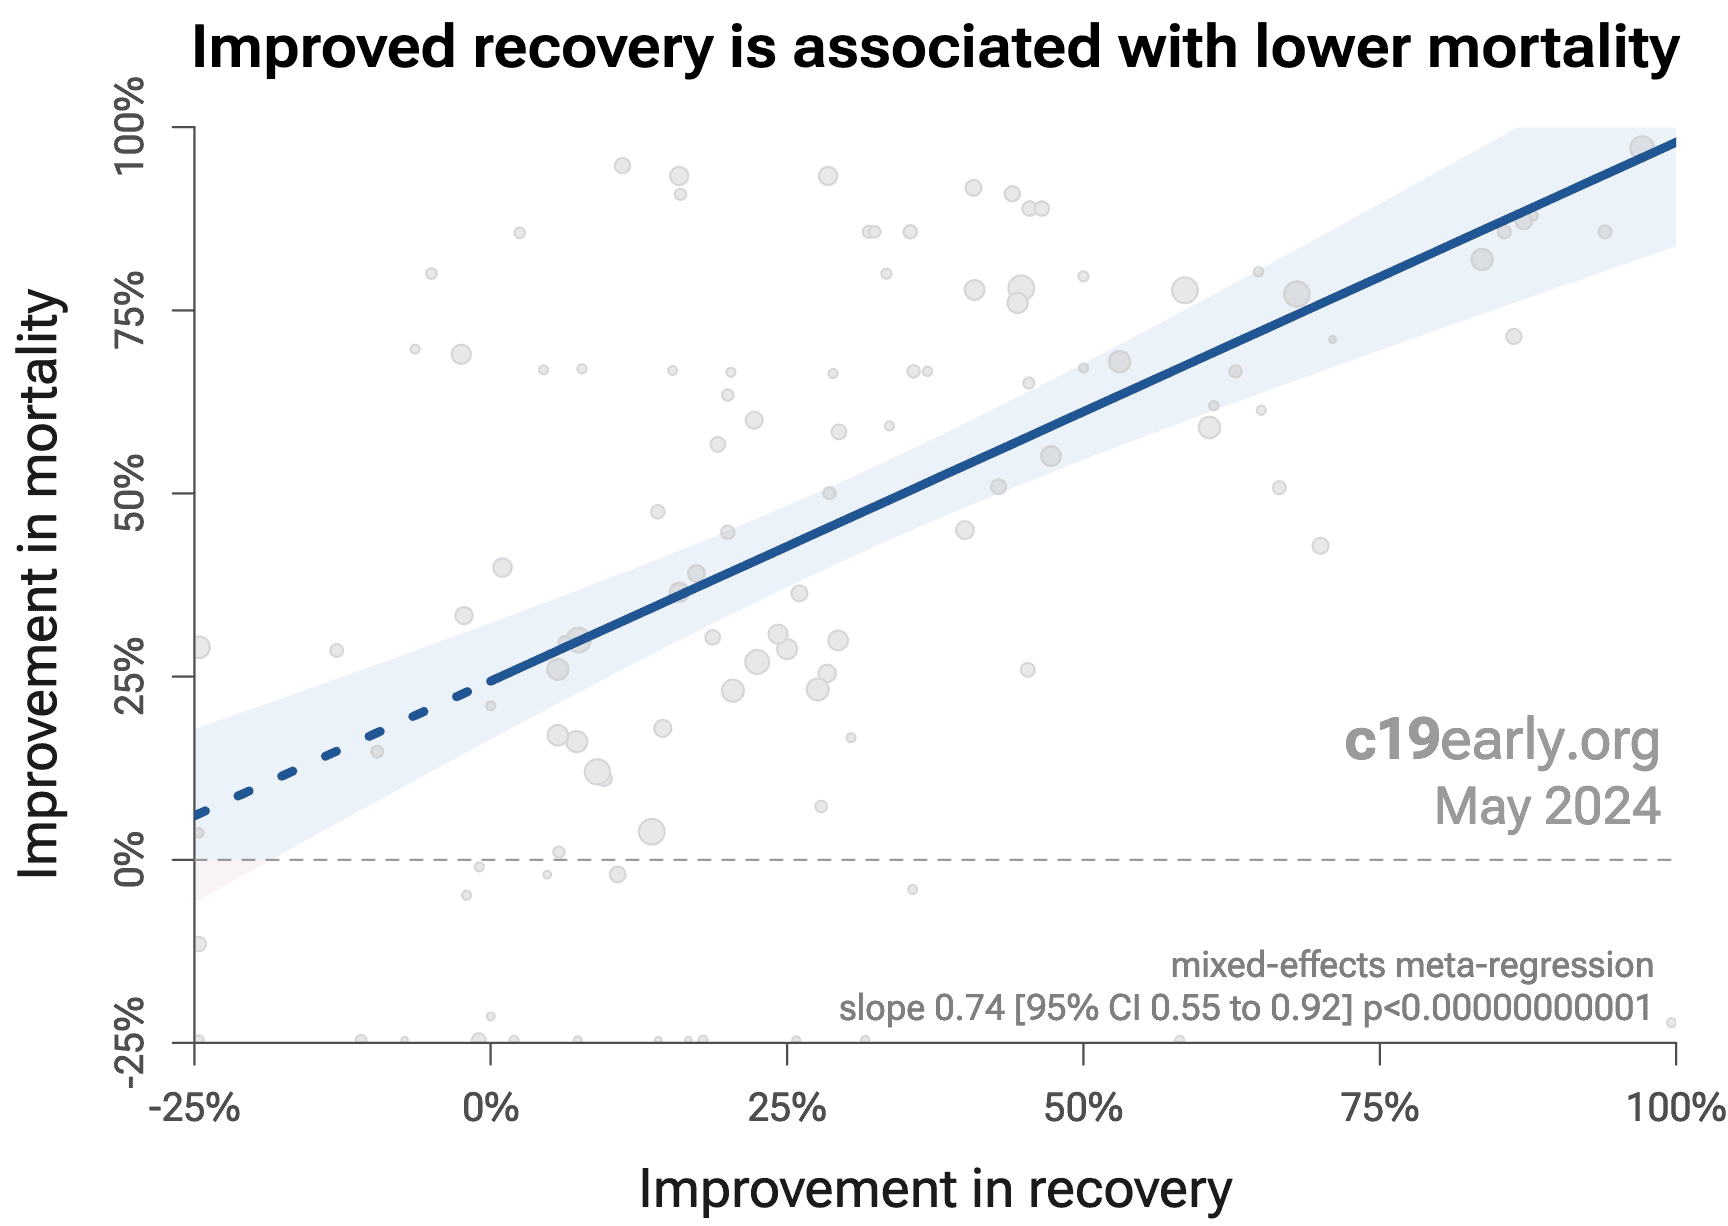
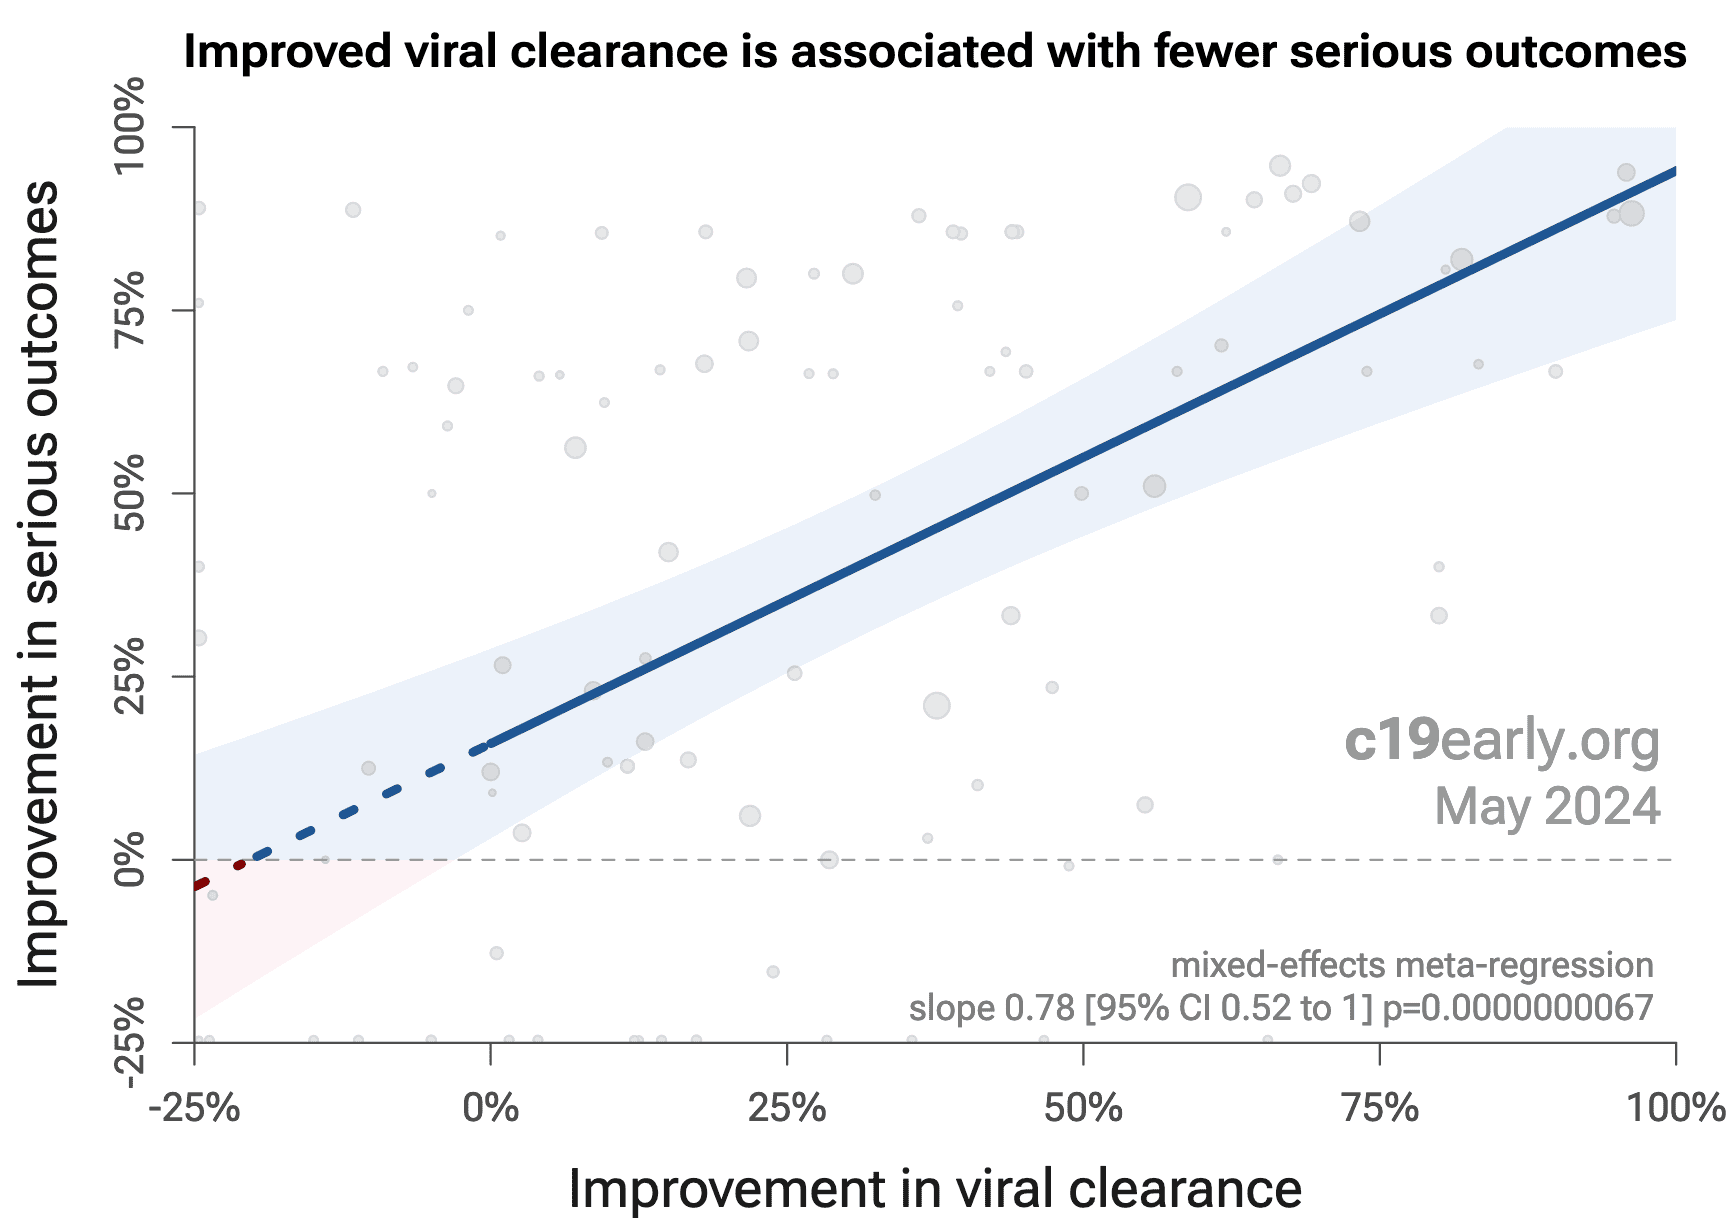
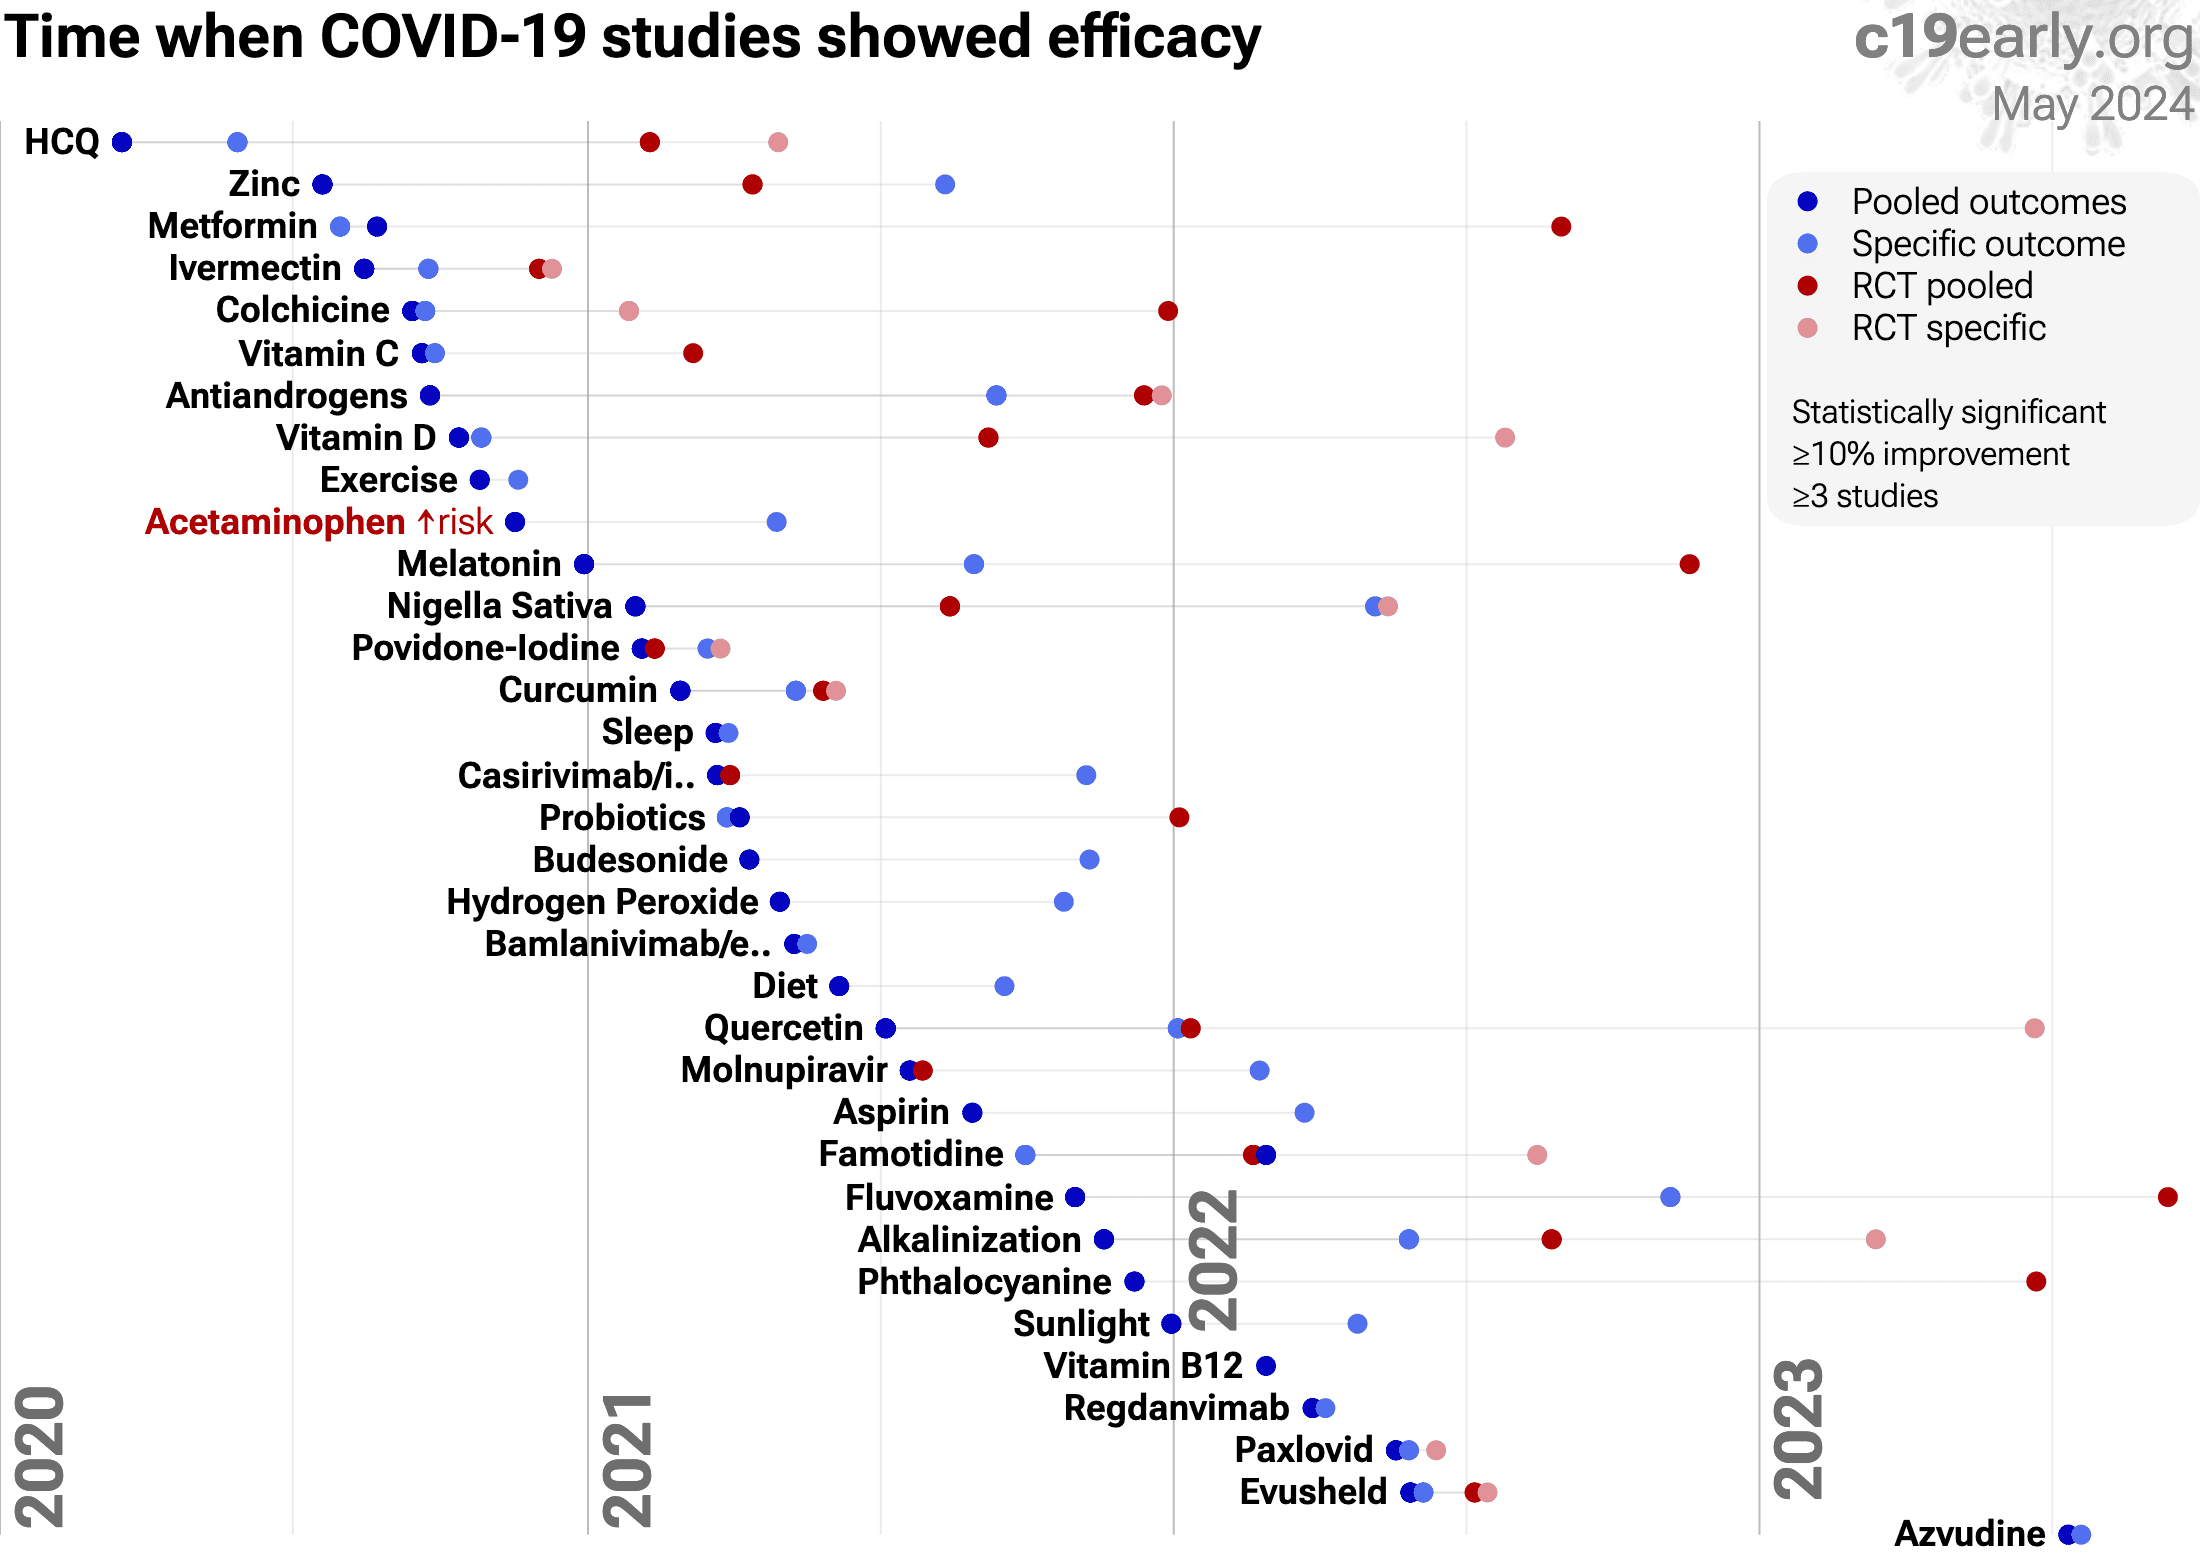
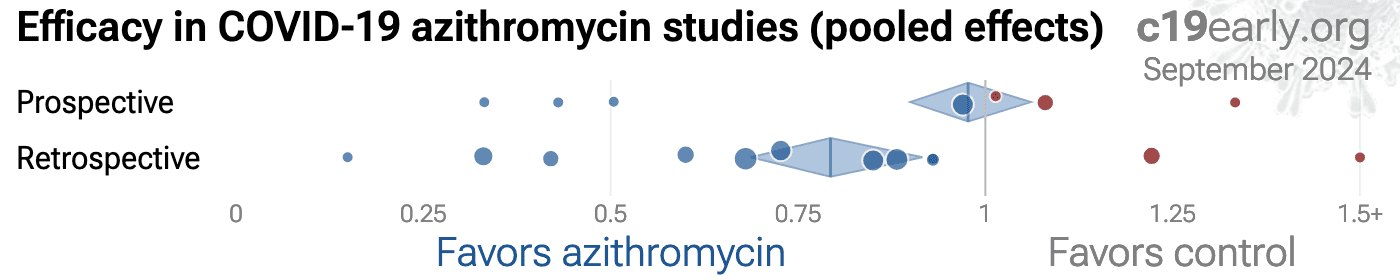
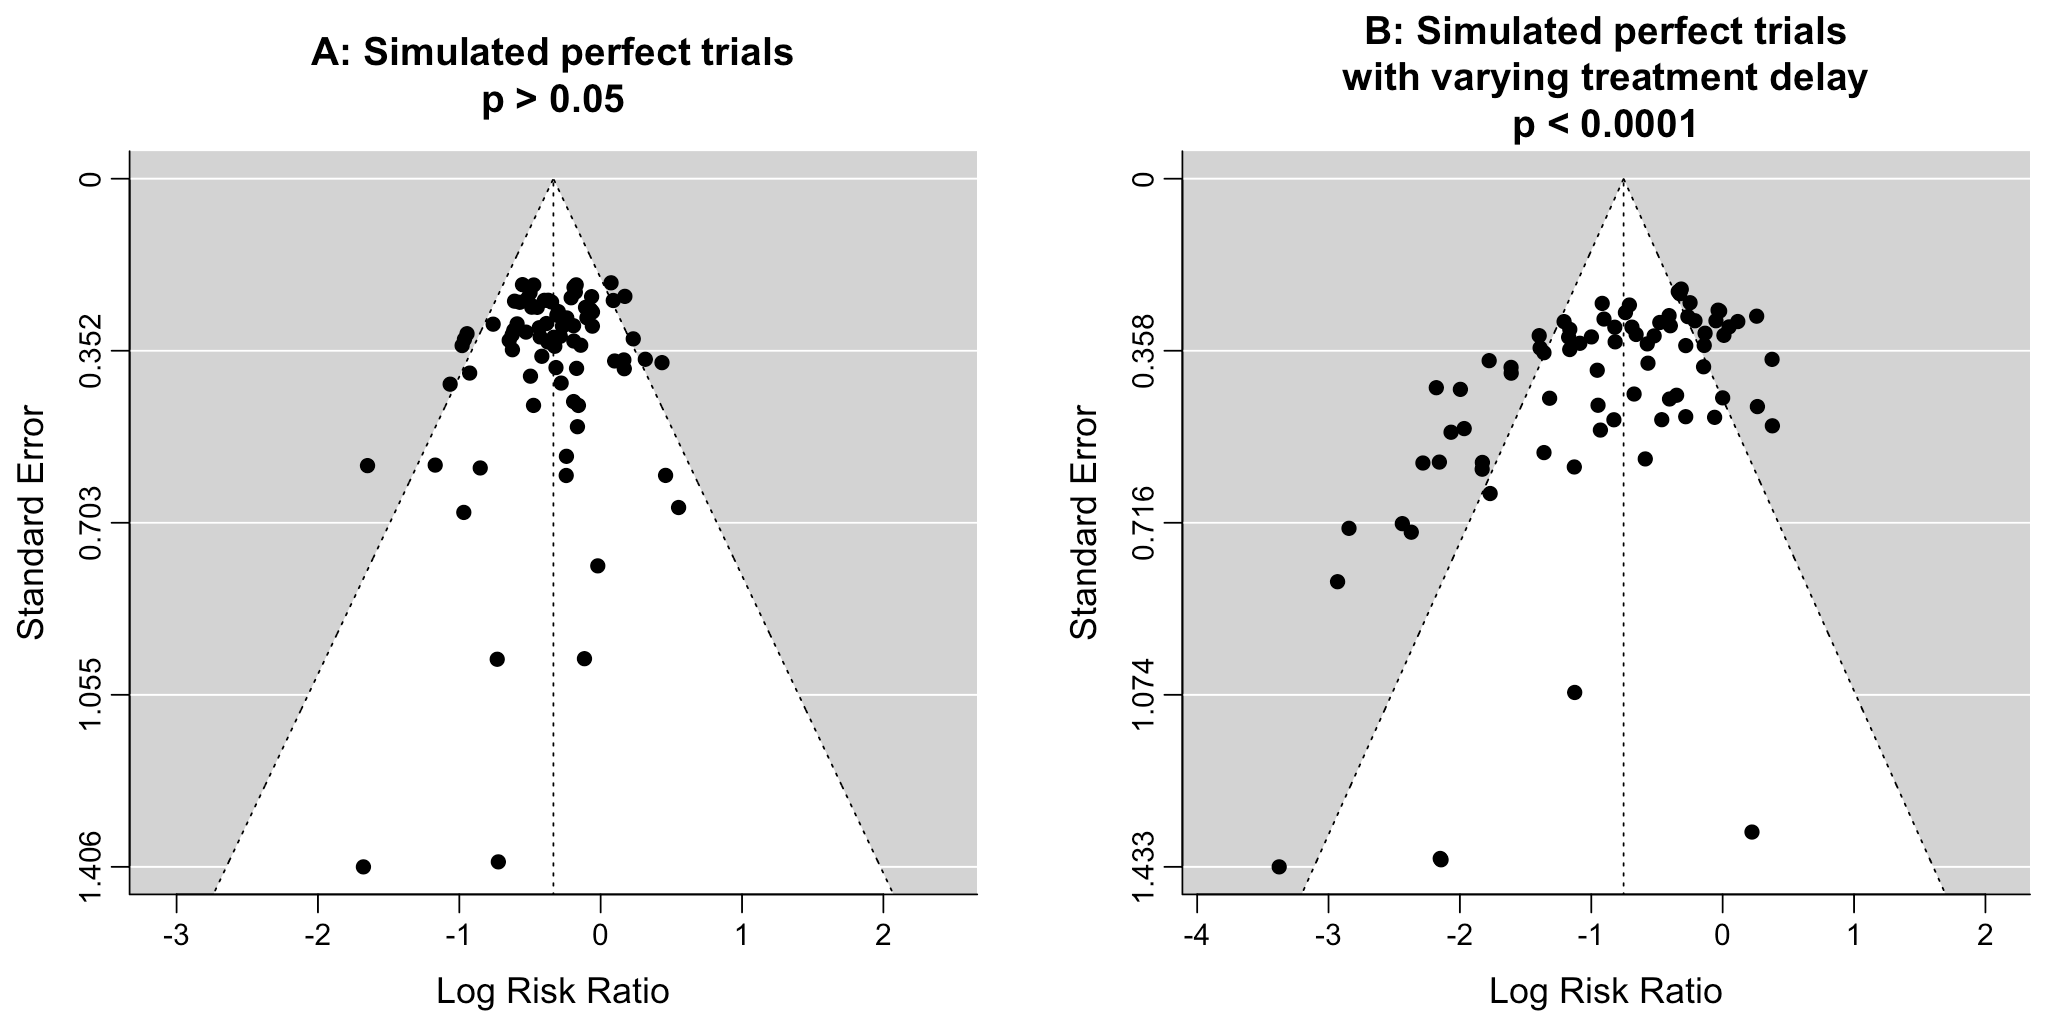
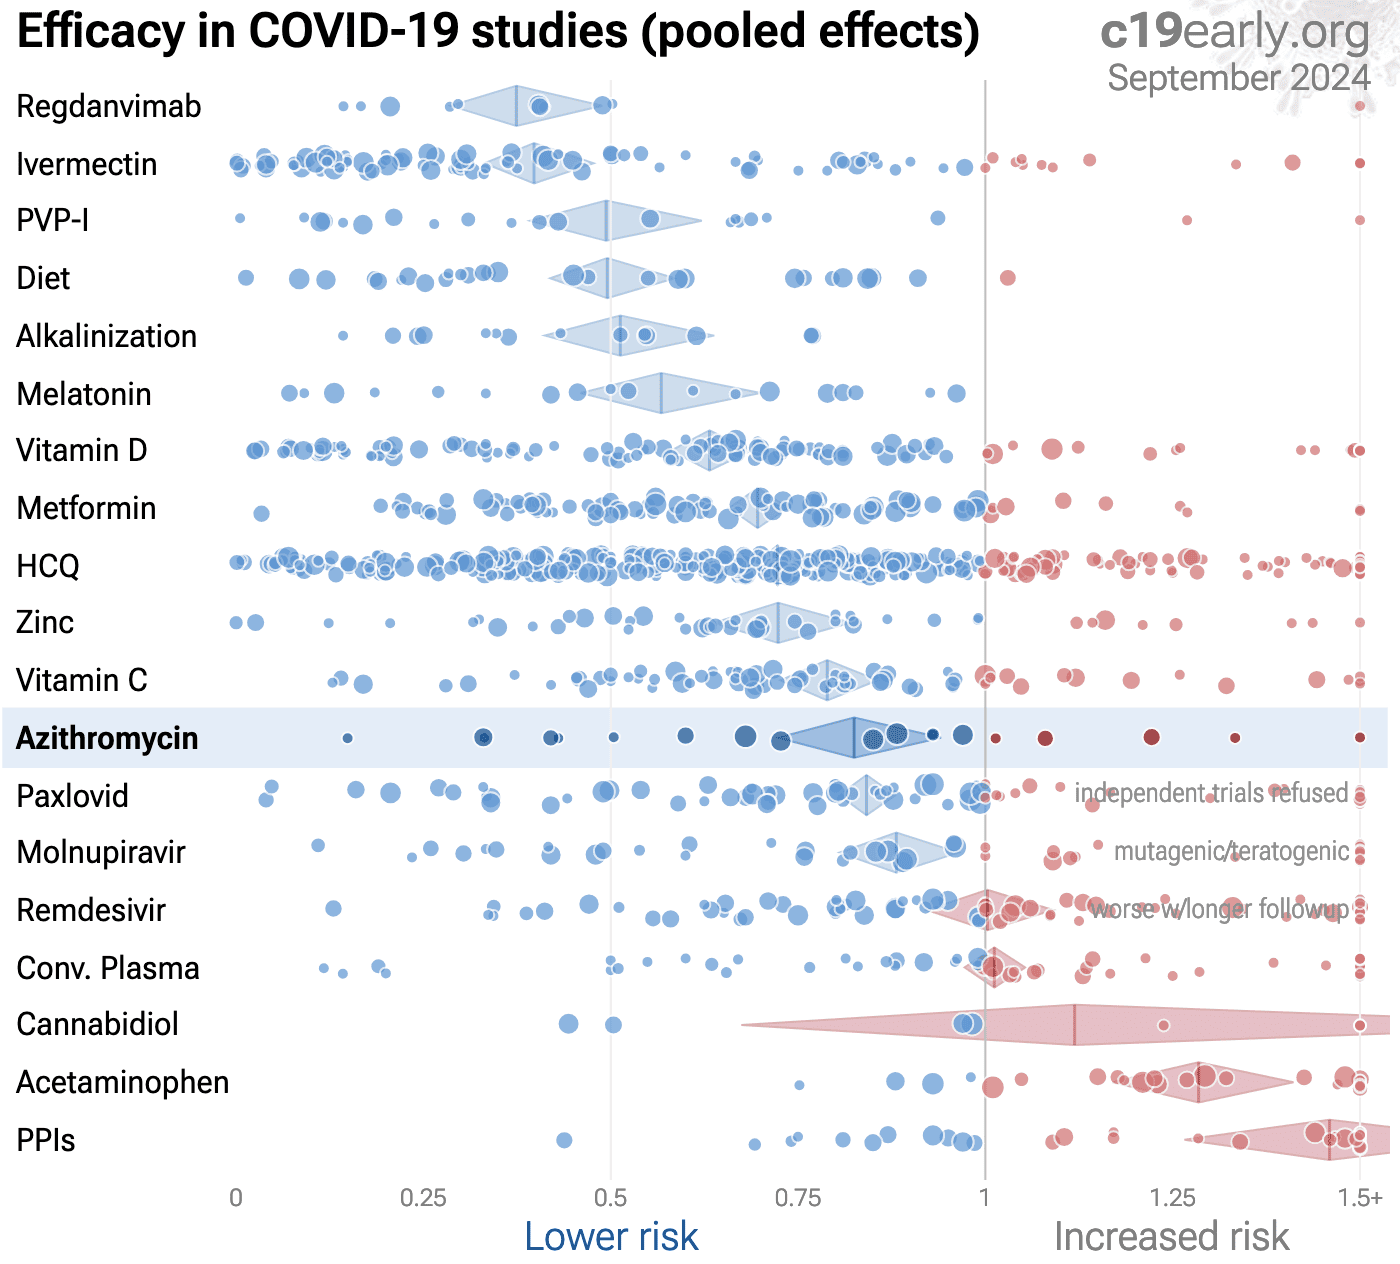
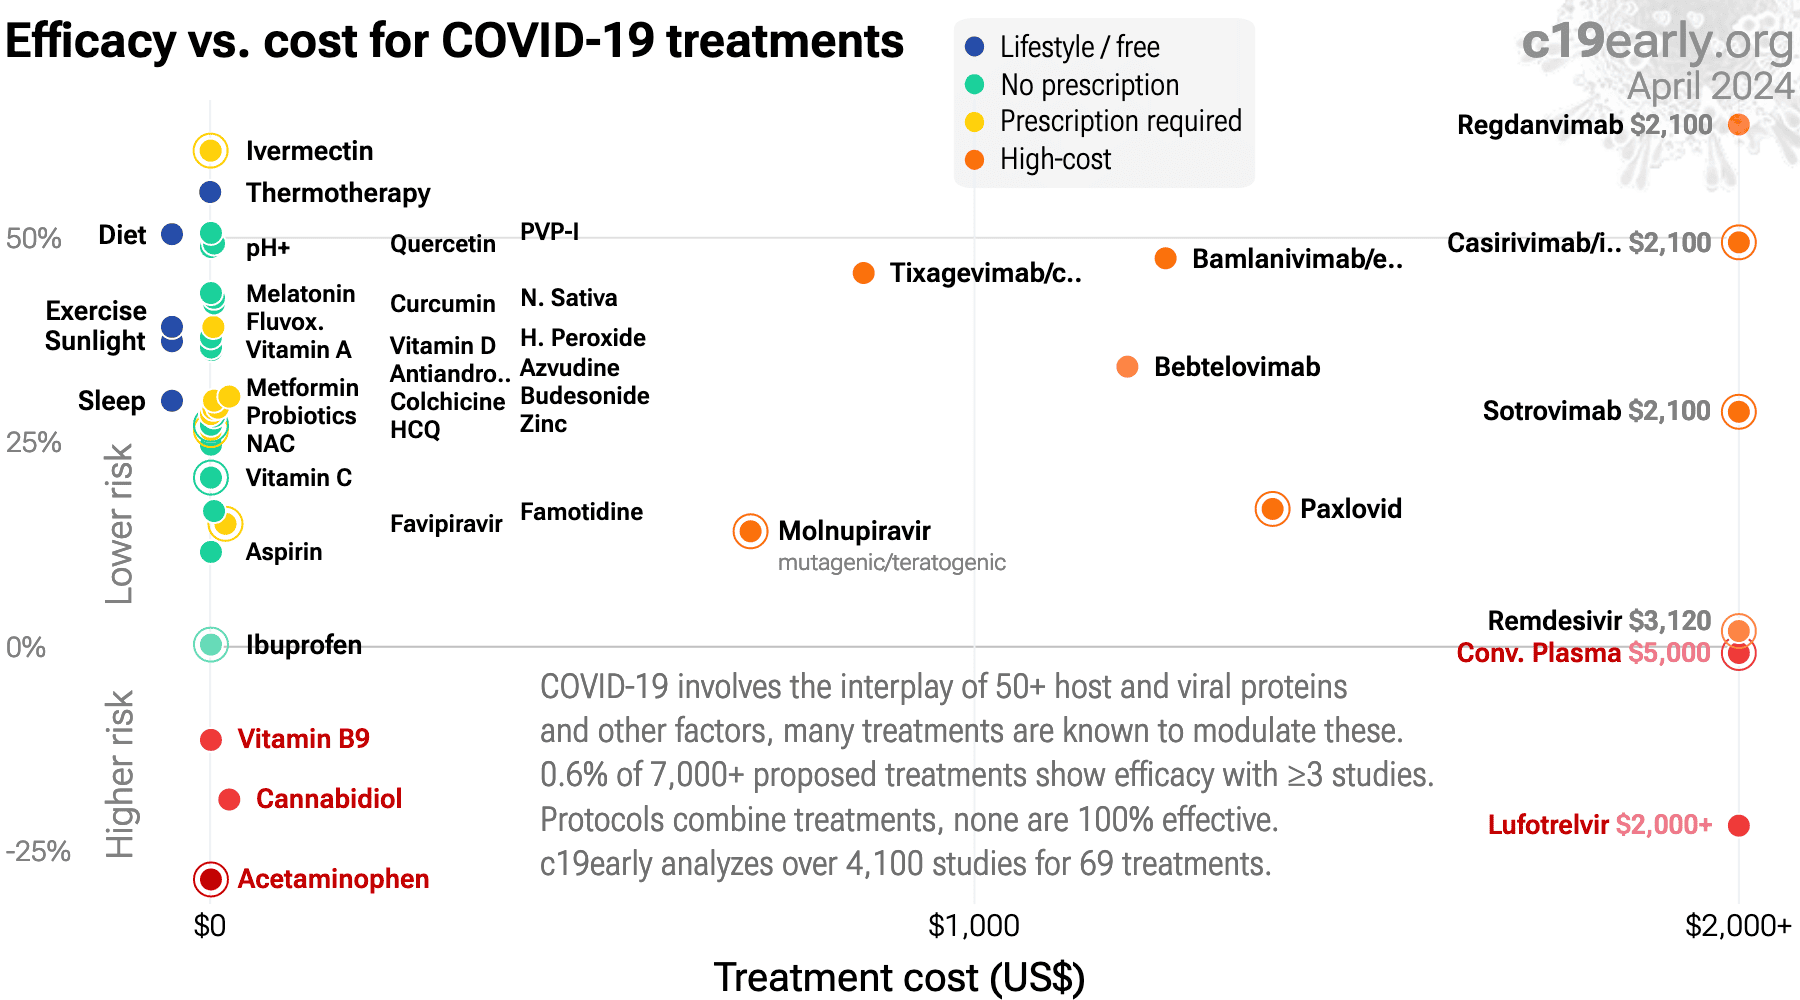
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/azmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
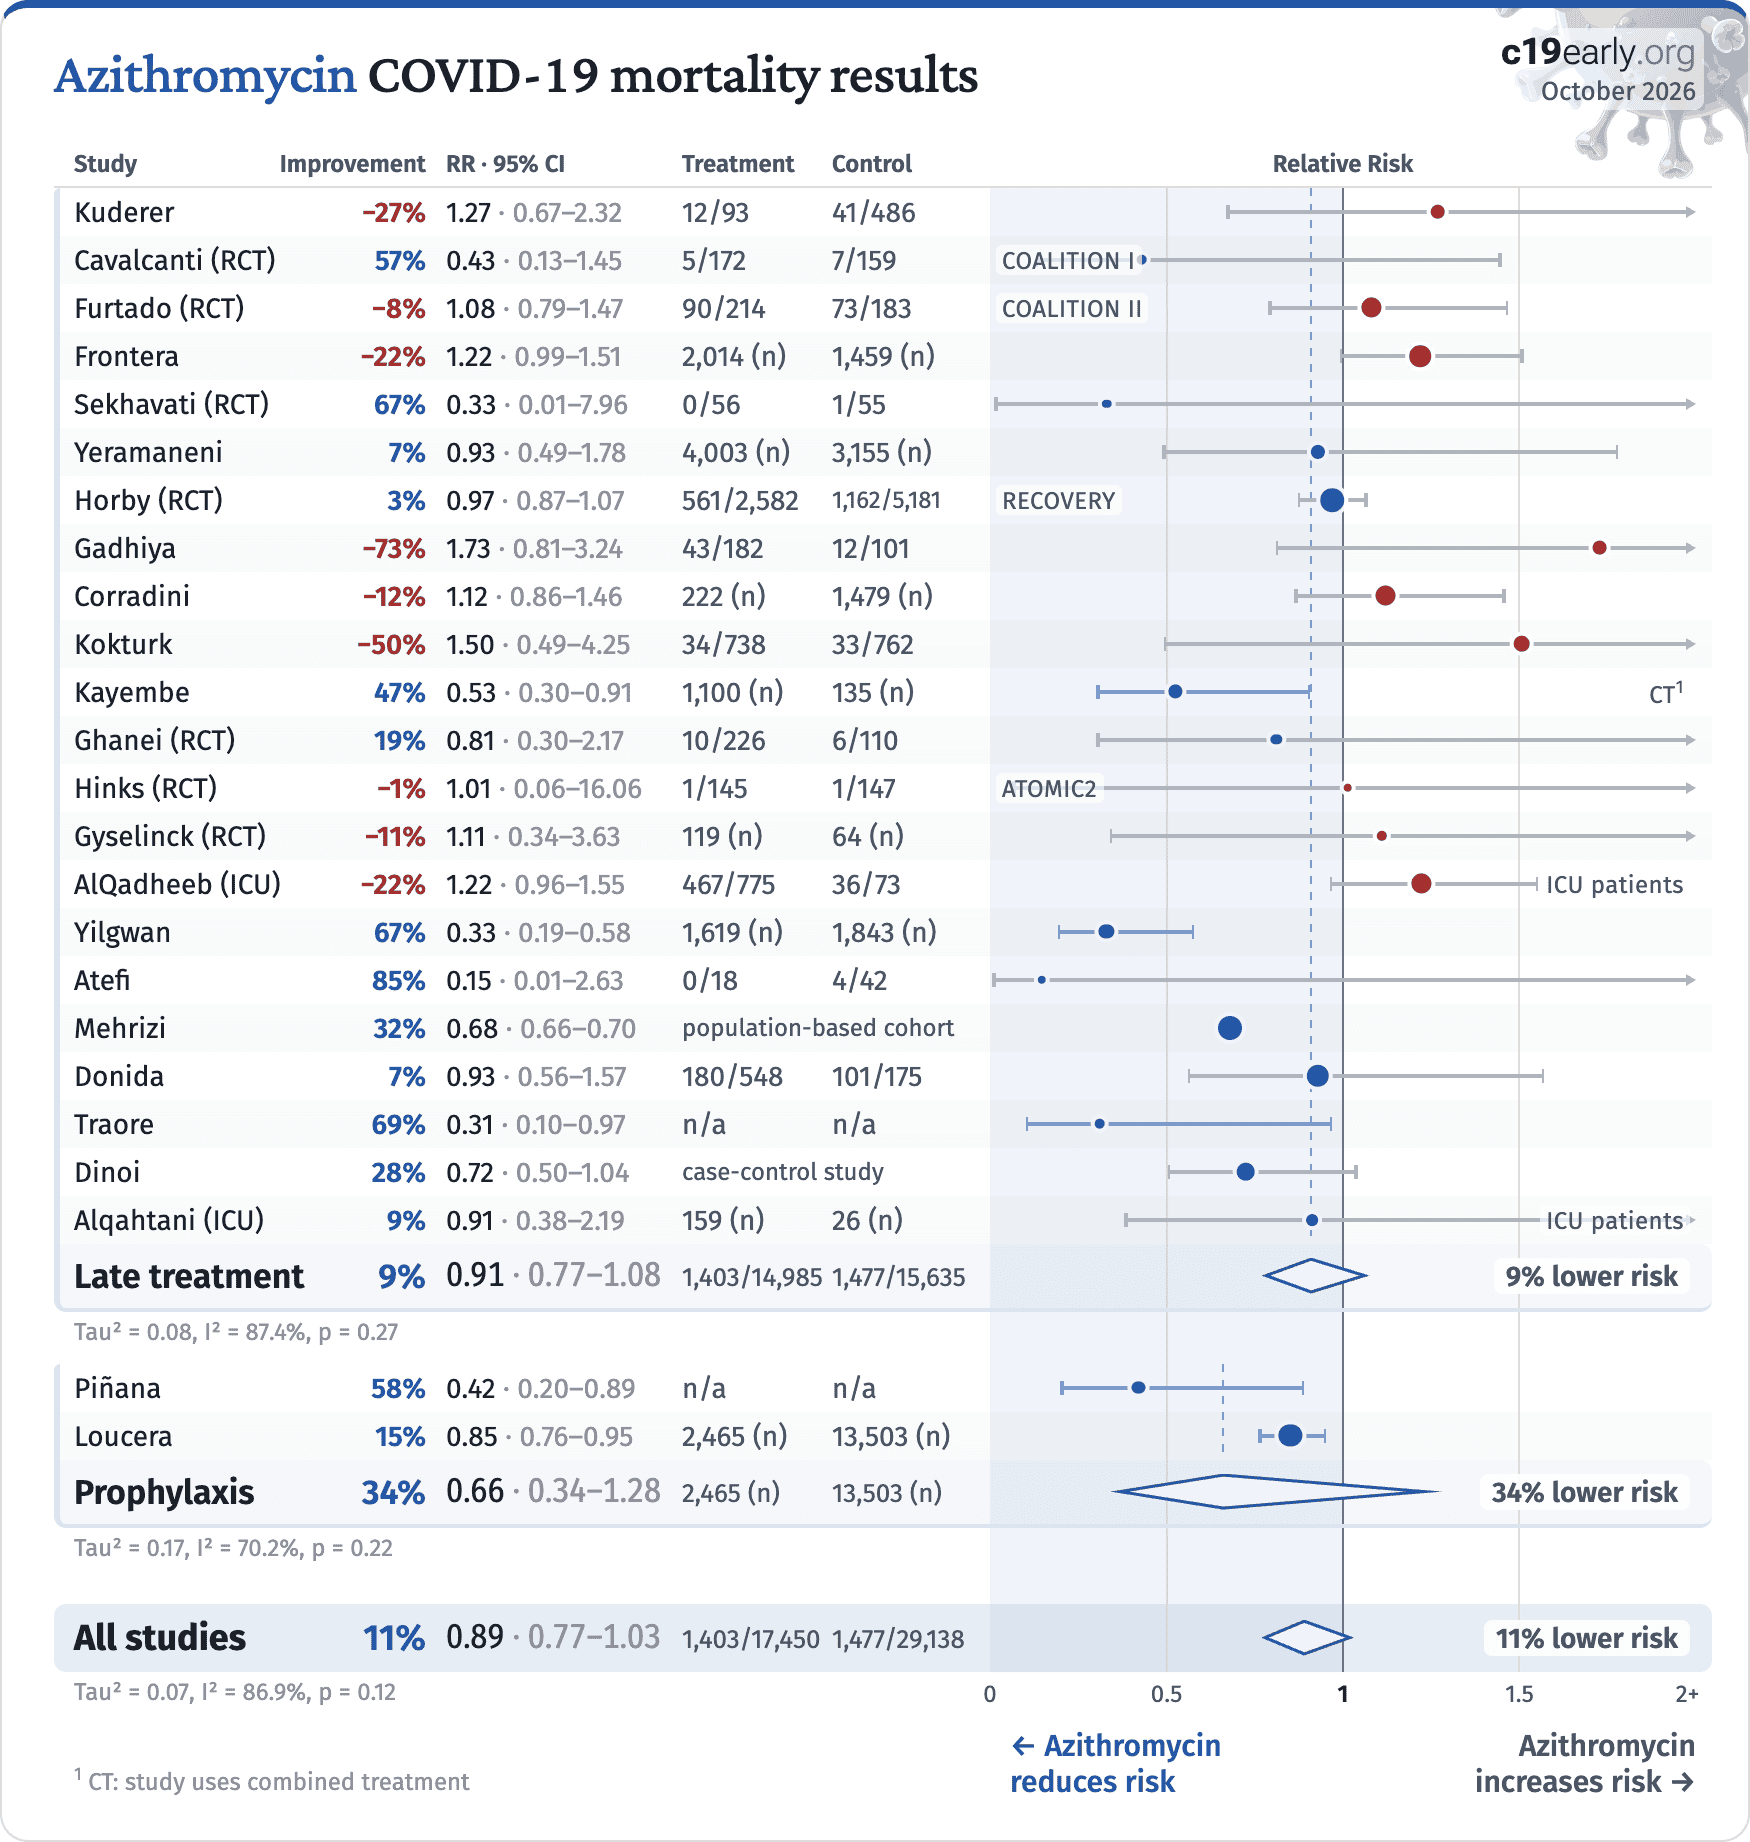
AlQadheeb, 5/10/2023, retrospective, Saudi Arabia, peer-reviewed, mean age 55.8, 9 authors, study period March 2020 - August 2021.
|
risk of death, 22.2% higher, RR 1.22, p = 0.08, treatment 467 of 775 (60.3%), control 36 of 73 (49.3%).
|
|
Alqahtani, 3/12/2025, retrospective, Saudi Arabia, peer-reviewed, mean age 56.7, 15 authors, study period 13 March, 2020 - 13 September, 2020.
|
risk of death, 9.0% lower, OR 0.91, p = 0.85, treatment 159, control 26, RR approximated with OR.
|
|
Atefi, 11/20/2023, retrospective, Iran, peer-reviewed, 10 authors, trial IRCT20200623047897N1.
|
risk of death, 85.1% lower, RR 0.15, p = 0.31, treatment 0 of 18 (0.0%), control 4 of 42 (9.5%), NNT 10, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Butler, 3/31/2021, Randomized Controlled Trial, United Kingdom, peer-reviewed, 18 authors, study period 22 May, 2020 - 30 November, 2020, average treatment delay 6.0 days, trial ISRCTN86534580 (PRINCIPLE).
|
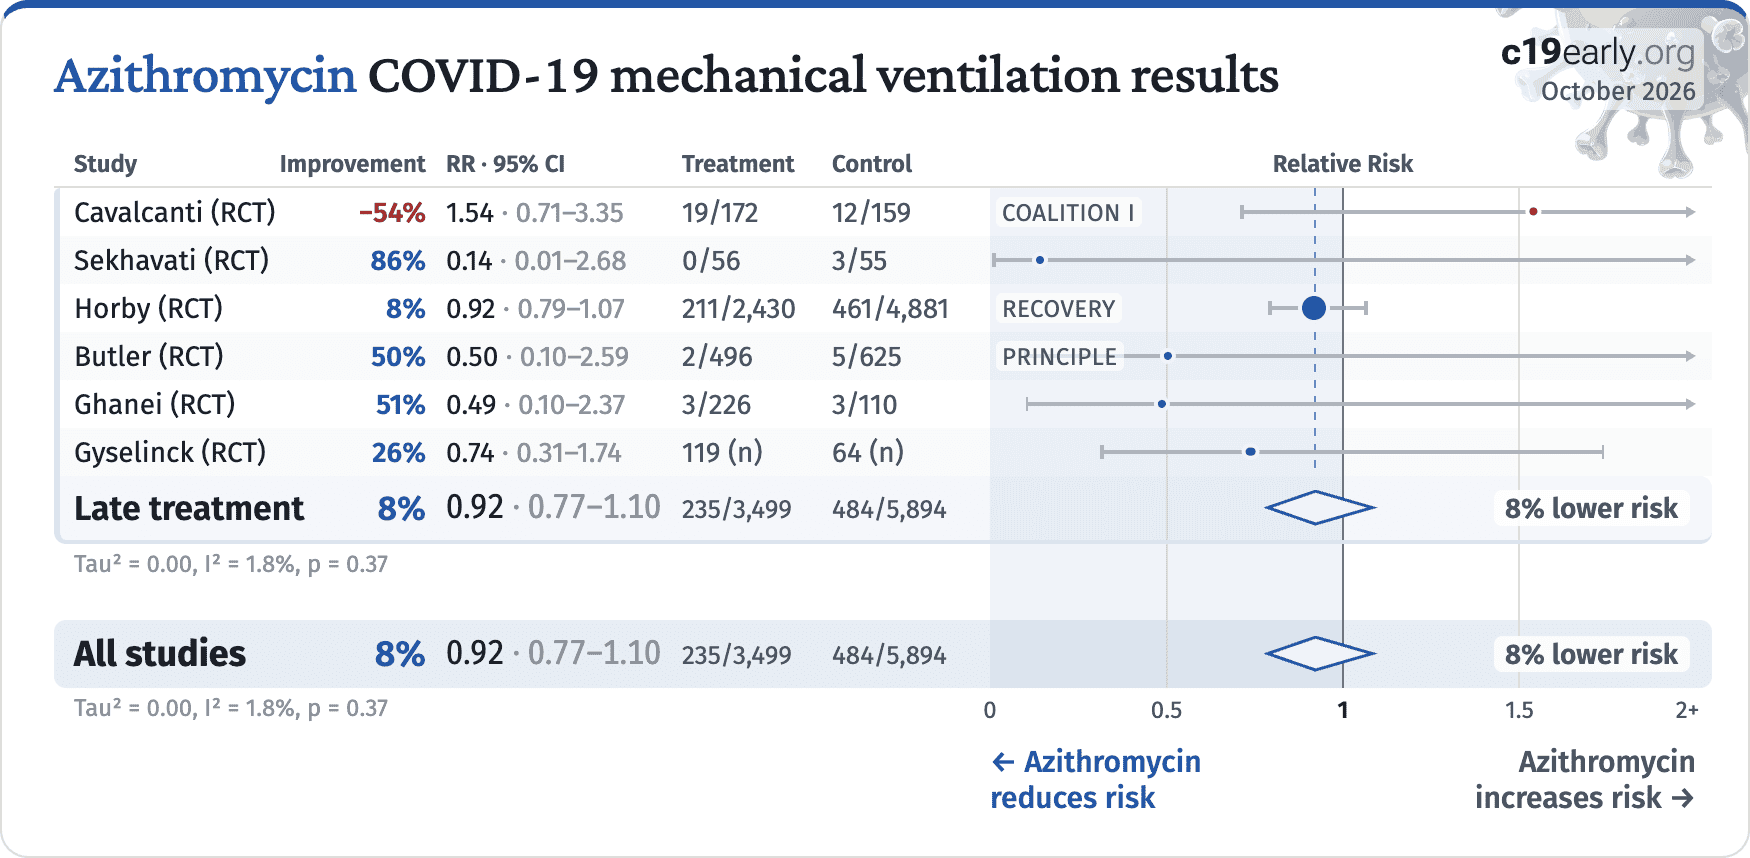
risk of mechanical ventilation, 49.6% lower, RR 0.50, p = 0.47, treatment 2 of 496 (0.4%), control 5 of 625 (0.8%), NNT 252.
|
|
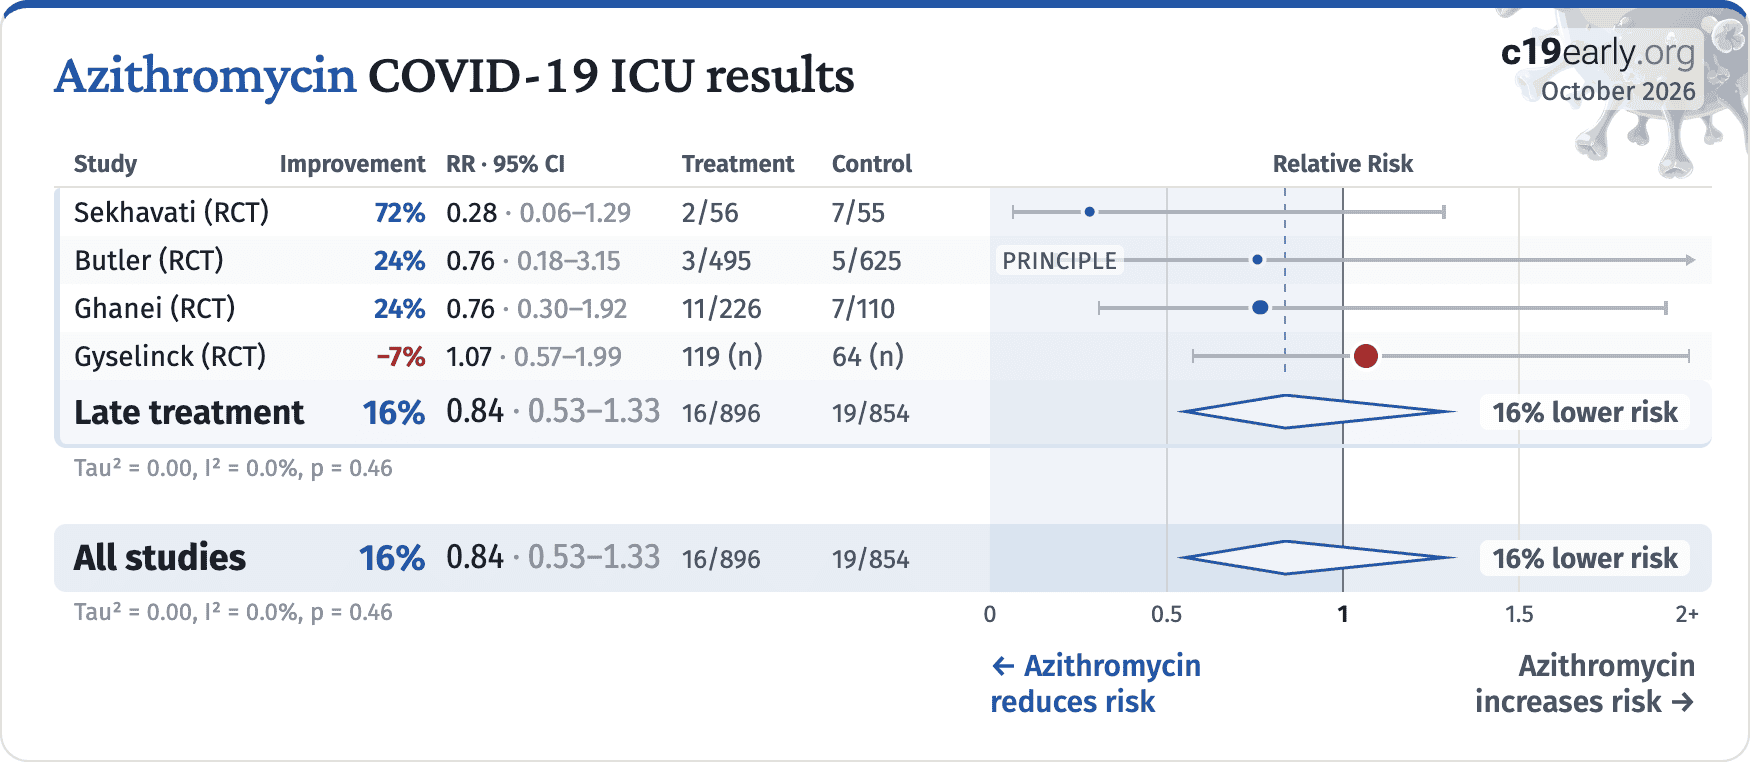
risk of ICU admission, 24.2% lower, RR 0.76, p = 1.00, treatment 3 of 495 (0.6%), control 5 of 625 (0.8%), NNT 516.
|
|
risk of oxygen therapy, 16.2% lower, RR 0.84, p = 0.69, treatment 10 of 497 (2.0%), control 15 of 625 (2.4%), NNT 258.
|
|
risk of hospitalization, 8.5% lower, RR 0.91, p = 0.87, treatment 16 of 500 (3.2%), control 22 of 629 (3.5%), NNT 336, concurrent randomization, day 28, Table S2.
|
|
risk of no recovery, 7.4% lower, HR 0.93, p = 0.23, treatment 500, control 823, inverted to make HR<1 favor treatment, first reported recovery.
|
|
Cavalcanti, 7/23/2020, Randomized Controlled Trial, Brazil, peer-reviewed, baseline oxygen required 41.8%, 35 authors, study period 29 March, 2020 - 18 May, 2020, trial NCT04322123 (history) (COALITION I).
|
risk of death, 57.0% lower, HR 0.43, p = 0.17, treatment 5 of 172 (2.9%), control 7 of 159 (4.4%), adjusted per study, HCQ+AZ vs. HCQ.
|
|
risk of death, 44.5% lower, RR 0.55, p = 0.49, treatment 3 of 172 (1.7%), control 5 of 159 (3.1%), NNT 71, HCQ+AZ vs. HCQ, day 15.
|
|
risk of mechanical ventilation, 54.0% higher, HR 1.54, p = 0.28, treatment 19 of 172 (11.0%), control 12 of 159 (7.5%), adjusted per study, HCQ+AZ vs. HCQ.
|
|
risk of 7-point scale, 18.0% lower, OR 0.82, p = 0.49, treatment 172, control 159, adjusted per study, HCQ+AZ vs. HCQ, RR approximated with OR.
|
|
Corradini, 4/24/2021, retrospective, Italy, peer-reviewed, 60 authors.
|
risk of death, 12.0% higher, OR 1.12, p = 0.38, treatment 222, control 1,479, adjusted per study, Table S6, all patients, multivariable, RR approximated with OR.
|
|
Dinoi, 2/20/2025, retrospective, Italy, peer-reviewed, 11 authors, study period 17 March, 2020 - 15 June, 2021.
|
risk of death, 27.7% lower, OR 0.72, p = 0.08, treatment 87 of 247 (35.2%) cases,
106 of 247 (42.9%) controls, NNT 12, case control OR.
|
|
Donida, 1/31/2024, retrospective, Italy, peer-reviewed, 4 authors, study period 21 February, 2020 - 31 May, 2020.
|
risk of death, 7.0% lower, HR 0.93, p = 0.79, treatment 180 of 548 (32.8%), control 101 of 175 (57.7%), NNT 4.0, adjusted per study, multivariable, Cox proportional hazards.
|
|
Frontera, 10/26/2020, retrospective, USA, preprint, median age 64.0, 14 authors, excluded in exclusion analyses:
substantial confounding by time likely due to declining usage over the early stages of the pandemic when overall treatment protocols improved dramatically.
|
risk of death, 22.0% higher, HR 1.22, p = 0.07, treatment 2,014, control 1,459, adjusted per study.
|
|
Furtado, 9/4/2020, Randomized Controlled Trial, Brazil, peer-reviewed, 33 authors, average treatment delay 8.0 days, trial NCT04321278 (history) (COALITION II), excluded in exclusion analyses:
very late stage patients.
|
risk of death, 8.0% higher, HR 1.08, p = 0.63, treatment 90 of 214 (42.1%), control 73 of 183 (39.9%), day 29.
|
|
risk of death, 2.6% higher, RR 1.03, p = 0.91, treatment 66 of 214 (30.8%), control 55 of 183 (30.1%), day 15.
|
|
6 point scale, 30.1% lower, OR 0.70, p = 0.08, treatment 214, control 183, inverted to make OR<1 favor treatment, day 29, RR approximated with OR.
|
|
6 point scale, 26.5% lower, OR 0.74, p = 0.10, treatment 214, control 183, inverted to make OR<1 favor treatment, day 15, primary outcome, RR approximated with OR.
|
|
Gadhiya, 4/8/2021, retrospective, USA, peer-reviewed, 4 authors, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely.
|
risk of death, 72.8% higher, RR 1.73, p = 0.15, treatment 43 of 182 (23.6%), control 12 of 101 (11.9%), adjusted per study, odds ratio converted to relative risk, multivariate logistic regression.
|
|
Ghanei, 9/15/2021, Randomized Controlled Trial, Iran, peer-reviewed, 18 authors, study period 13 April, 2020 - 9 August, 2020.
|
risk of death, 18.9% lower, RR 0.81, p = 0.79, treatment 10 of 226 (4.4%), control 6 of 110 (5.5%), NNT 97, azithromycin groups vs. lopinavir/ritonavir.
|
|
risk of mechanical ventilation, 51.3% lower, RR 0.49, p = 0.40, treatment 3 of 226 (1.3%), control 3 of 110 (2.7%), NNT 71, azithromycin groups vs. lopinavir/ritonavir.
|
|
risk of ICU admission, 23.5% lower, RR 0.76, p = 0.61, treatment 11 of 226 (4.9%), control 7 of 110 (6.4%), NNT 67, azithromycin groups vs. lopinavir/ritonavir.
|
|
Gyselinck, 1/27/2022, Randomized Controlled Trial, Belgium, peer-reviewed, mean age 62.0, 23 authors, study period 24 April, 2020 - 17 December, 2021, average treatment delay 7.0 days, trial EudraCT-2020-001614-38A.
|
risk of death, 10.9% higher, HR 1.11, p = 0.87, treatment 119, control 64, Kaplan-Meier.
|
|
risk of mechanical ventilation, 26.2% lower, HR 0.74, p = 0.50, treatment 119, control 64.
|
|
risk of ICU admission, 6.6% higher, HR 1.07, p = 0.85, treatment 119, control 64.
|
|
risk of no recovery, 2.2% lower, HR 0.98, p = 0.89, treatment 119, control 64, inverted to make HR<1 favor treatment.
|
|
Hinks, 10/31/2021, Randomized Controlled Trial, United Kingdom, peer-reviewed, mean age 45.0, 22 authors, study period 3 June, 2020 - 29 January, 2021, average treatment delay 6.02 days, trial NCT04381962 (history) (ATOMIC2).
|
risk of death, 1.4% higher, RR 1.01, p = 1.00, treatment 1 of 145 (0.7%), control 1 of 147 (0.7%).
|
|
risk of death/hospitalization, 1.0% lower, HR 0.99, p = 0.99, treatment 15 of 145 (10.3%), control 17 of 147 (11.6%), NNT 82, Cox proportional hazards, model 3.
|
|
risk of death/hospitalization, 8.0% lower, RR 0.92, p = 0.82, treatment 15 of 145 (10.3%), control 17 of 147 (11.6%), NNT 82, adjusted per study, odds ratio converted to relative risk, model 3.
|
|
progression to pneumonia, 80.3% lower, RR 0.20, p = 0.24, treatment 0 of 119 (0.0%), control 2 of 114 (1.8%), NNT 57, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Horby, 2/28/2021, Randomized Controlled Trial, United Kingdom, peer-reviewed, mean age 65.0, 34 authors, study period 7 April, 2020 - 27 November, 2020, average treatment delay 8.0 days, trial NCT04381936 (history) (RECOVERY), excluded in exclusion analyses:
very late stage patients.
|
risk of death, 3.0% lower, RR 0.97, p = 0.50, treatment 561 of 2,582 (21.7%), control 1,162 of 5,181 (22.4%), NNT 143, day 28, primary outcome.
|
|
risk of mechanical ventilation, 8.0% lower, RR 0.92, p = 0.29, treatment 211 of 2,430 (8.7%), control 461 of 4,881 (9.4%), NNT 131.
|
|
Kayembe, 5/7/2021, retrospective, Democratic Republic of Congo, peer-reviewed, 9 authors, study period 10 March, 2020 - 31 August, 2020, this trial uses multiple treatments in the treatment arm (combined with HCQ) - results of individual treatments may vary.
|
risk of death, 47.4% lower, HR 0.53, p = 0.03, treatment 1,100, control 135, inverted to make HR<1 favor treatment, 988 included for analysis, Cox proportional hazards, day 15.
|
|
Kokturk, 4/28/2021, retrospective, database analysis, Turkey, peer-reviewed, 68 authors.
|
risk of death, 50.5% higher, RR 1.50, p = 0.47, treatment 34 of 738 (4.6%), control 33 of 762 (4.3%), adjusted per study, odds ratio converted to relative risk.
|
|
Kuderer, 5/28/2020, retrospective, USA, peer-reviewed, 73 authors, excluded in exclusion analyses:
substantial unadjusted confounding by indication likely.
|
risk of death, 26.8% higher, RR 1.27, p = 0.46, treatment 12 of 93 (12.9%), control 41 of 486 (8.4%), odds ratio converted to relative risk, AZ.
|
|
risk of death, 152.0% higher, RR 2.52, p < 0.001, treatment 45 of 181 (24.9%), control 41 of 486 (8.4%), odds ratio converted to relative risk, HCQ+AZ.
|
|
Mehrizi, 12/18/2023, retrospective, Iran, peer-reviewed, 10 authors, study period 1 February, 2020 - 20 March, 2022.
|
risk of death, 32.0% lower, OR 0.68, p < 0.001, RR approximated with OR.
|
|
Oldenburg, 8/10/2021, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, median age 43.0, 15 authors, study period 22 May, 2020 - 16 March, 2021, average treatment delay 7.0 days, trial NCT04332107 (history) (ACTION).
|
risk of hospitalization, 788.0% higher, RR 8.88, p = 0.16, treatment 5 of 125 (4.0%), control 0 of 72 (0.0%), continuity correction due to zero event (with reciprocal of the contrasting arm), day 21.
|
|
ED visit, 418.4% higher, RR 5.18, p = 0.01, treatment 18 of 125 (14.4%), control 2 of 72 (2.8%), ED visit or urgent care, day 21.
|
|
risk of no recovery, 0.8% lower, RR 0.99, p = 1.00, treatment 65 of 131 (49.6%), control 35 of 70 (50.0%), NNT 262, day 21.
|
|
risk of transmission, 12.1% lower, RR 0.88, p = 0.66, treatment 33 of 522 (6.3%), control 20 of 278 (7.2%), NNT 115, day 21.
|
|
Sekhavati, 10/31/2020, Randomized Controlled Trial, Iran, peer-reviewed, 18 authors, study period 24 April, 2020 - 8 May, 2020.
|
risk of death, 66.9% lower, RR 0.33, p = 0.50, treatment 0 of 56 (0.0%), control 1 of 55 (1.8%), NNT 55, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of mechanical ventilation, 85.8% lower, RR 0.14, p = 0.12, treatment 0 of 56 (0.0%), control 3 of 55 (5.5%), NNT 18, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of ICU admission, 71.9% lower, RR 0.28, p = 0.09, treatment 2 of 56 (3.6%), control 7 of 55 (12.7%), NNT 11.
|
|
hospitalization time, 22.7% lower, relative time 0.77, p = 0.02, treatment 56, control 55.
|
|
Traore, 1/17/2025, retrospective, Mali, peer-reviewed, median age 43.0, 14 authors, study period 27 March, 2020 - 30 June, 2022.
|
risk of death, 69.0% lower, HR 0.31, p = 0.04, adjusted per study, multivariable.
|
|
Yeramaneni, 2/28/2021, retrospective, USA, peer-reviewed, 6 authors, study period 11 February, 2020 - 8 May, 2020.
|
risk of death, 7.0% lower, OR 0.93, p = 0.84, treatment 4,003, control 3,155, adjusted per study, multivariable, day 30, RR approximated with OR.
|
|
Yilgwan, 5/11/2023, retrospective, Nigeria, peer-reviewed, 12 authors, study period 25 February, 2020 - 30 August, 2021.
|
risk of death, 67.0% lower, OR 0.33, p < 0.001, treatment 1,619, control 1,843, RR approximated with OR.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.