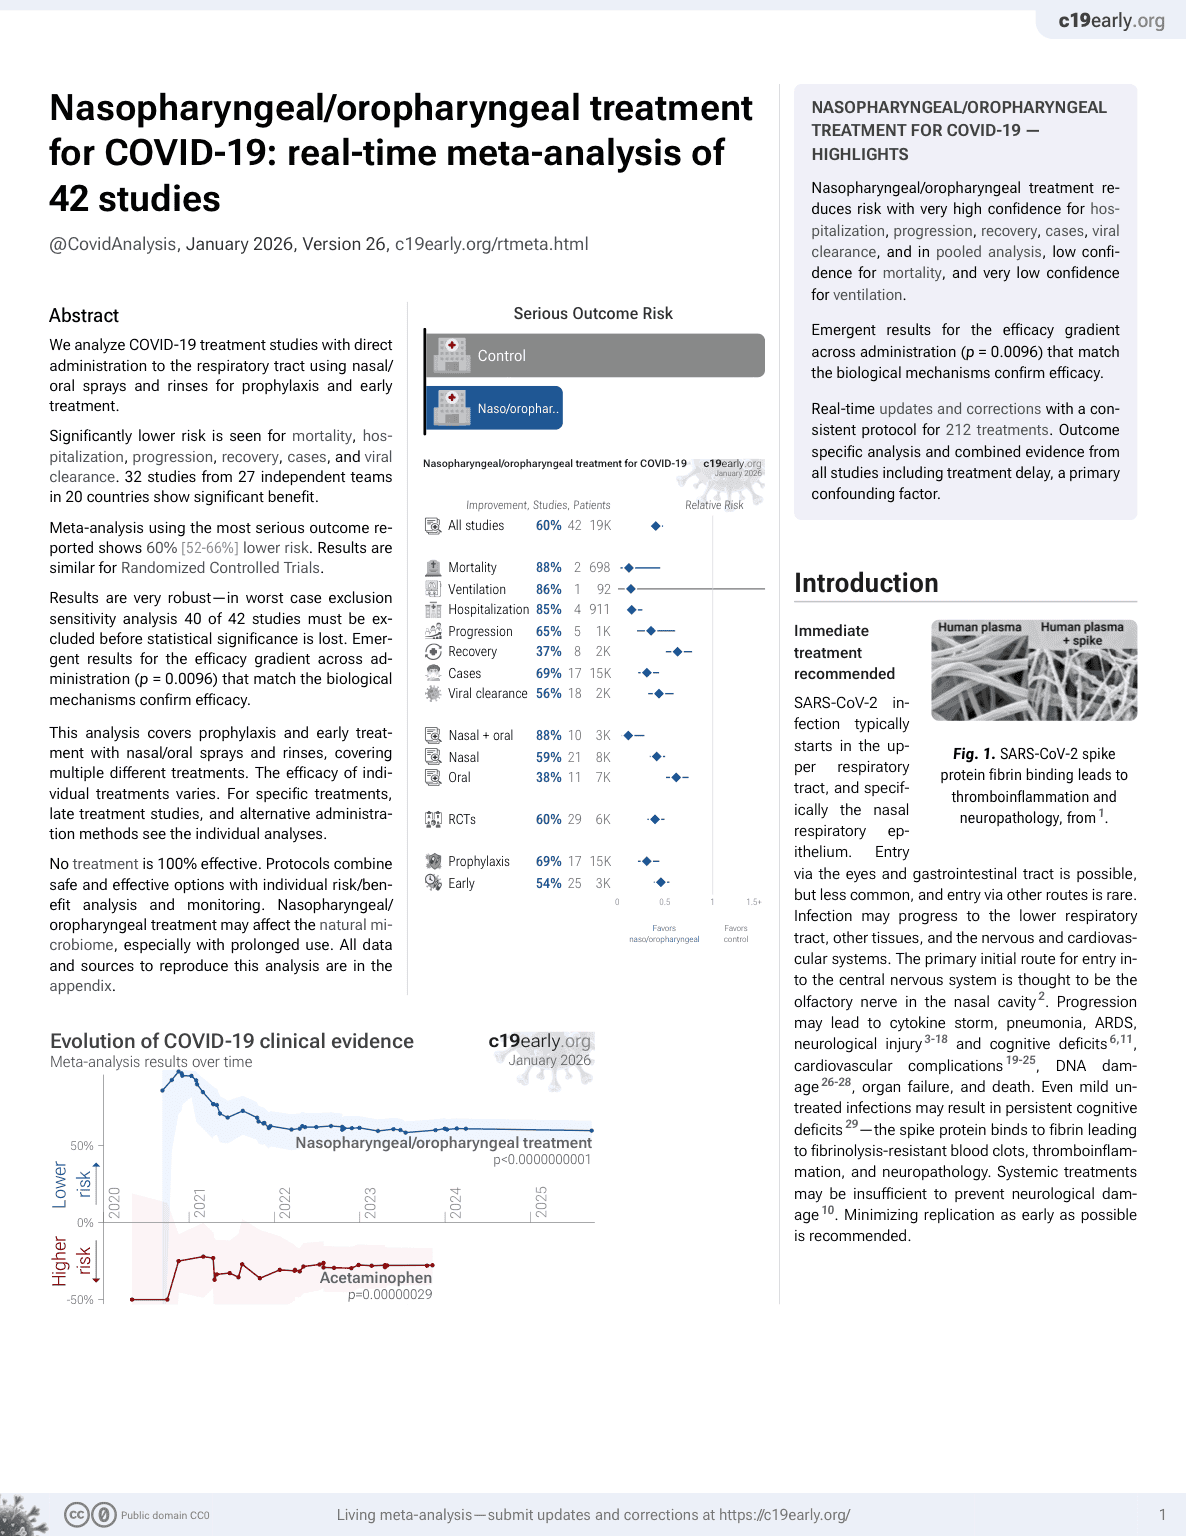
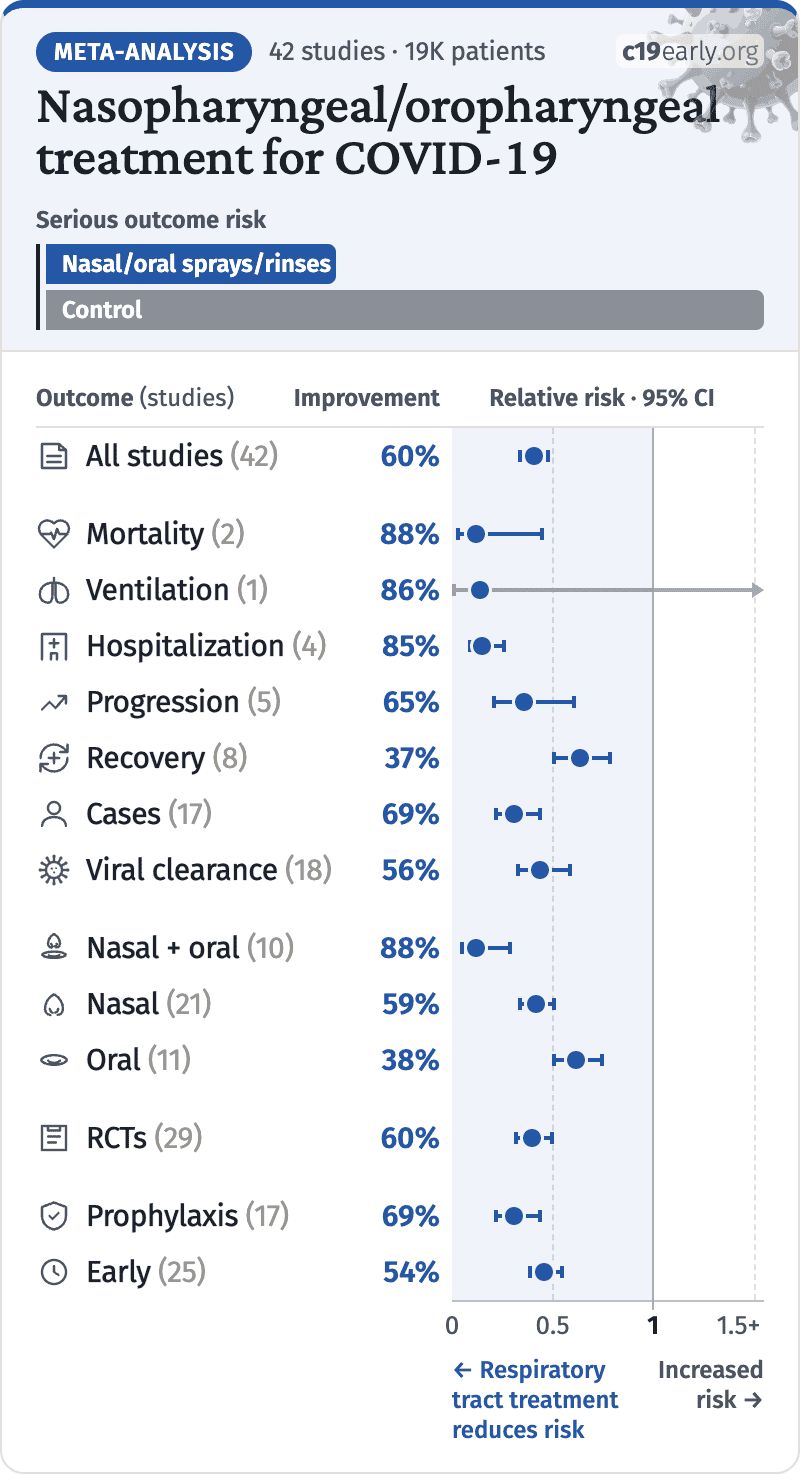
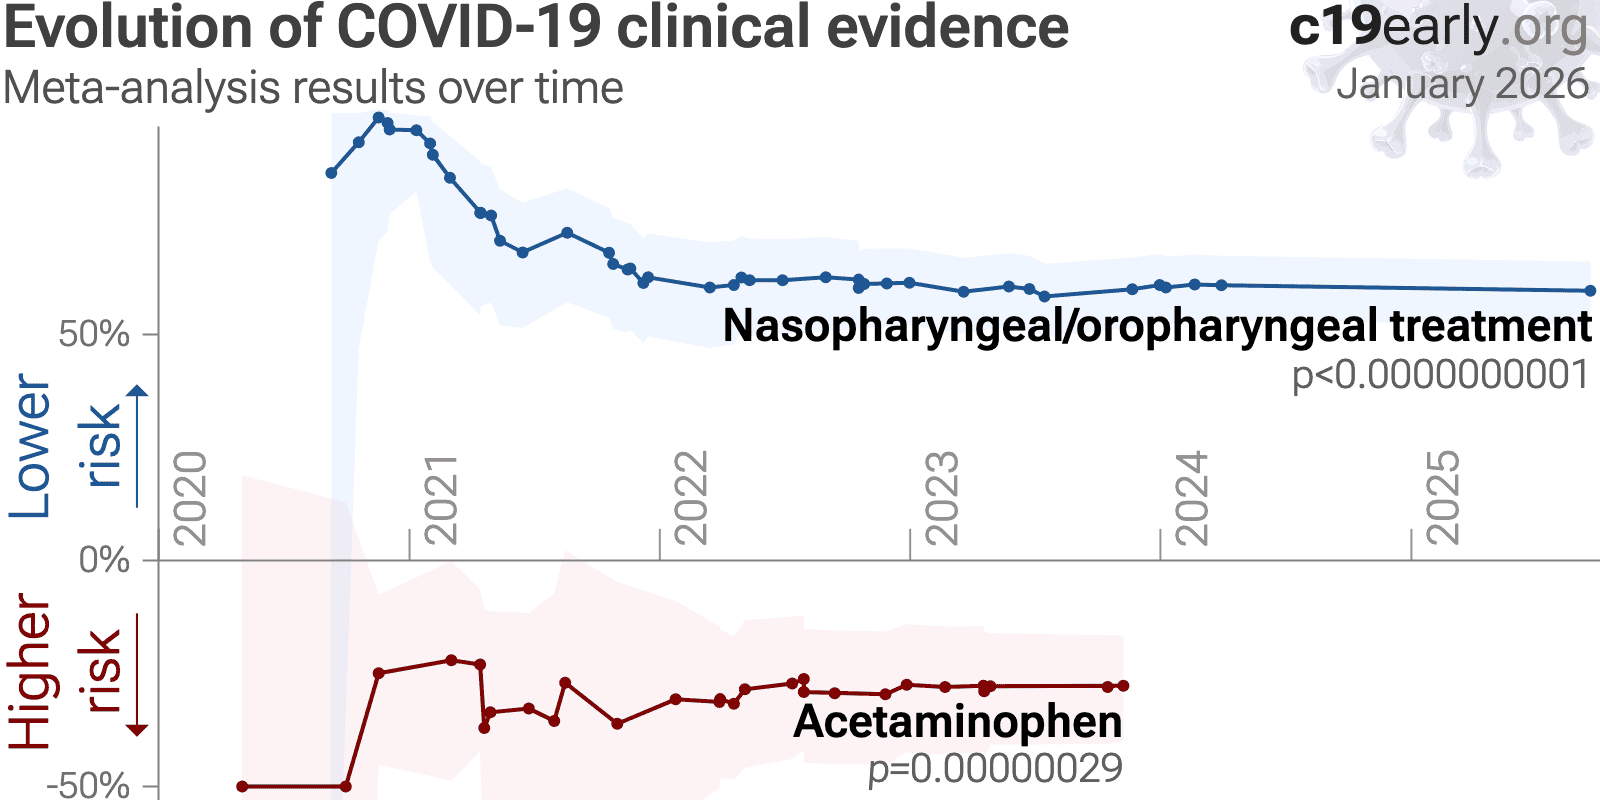
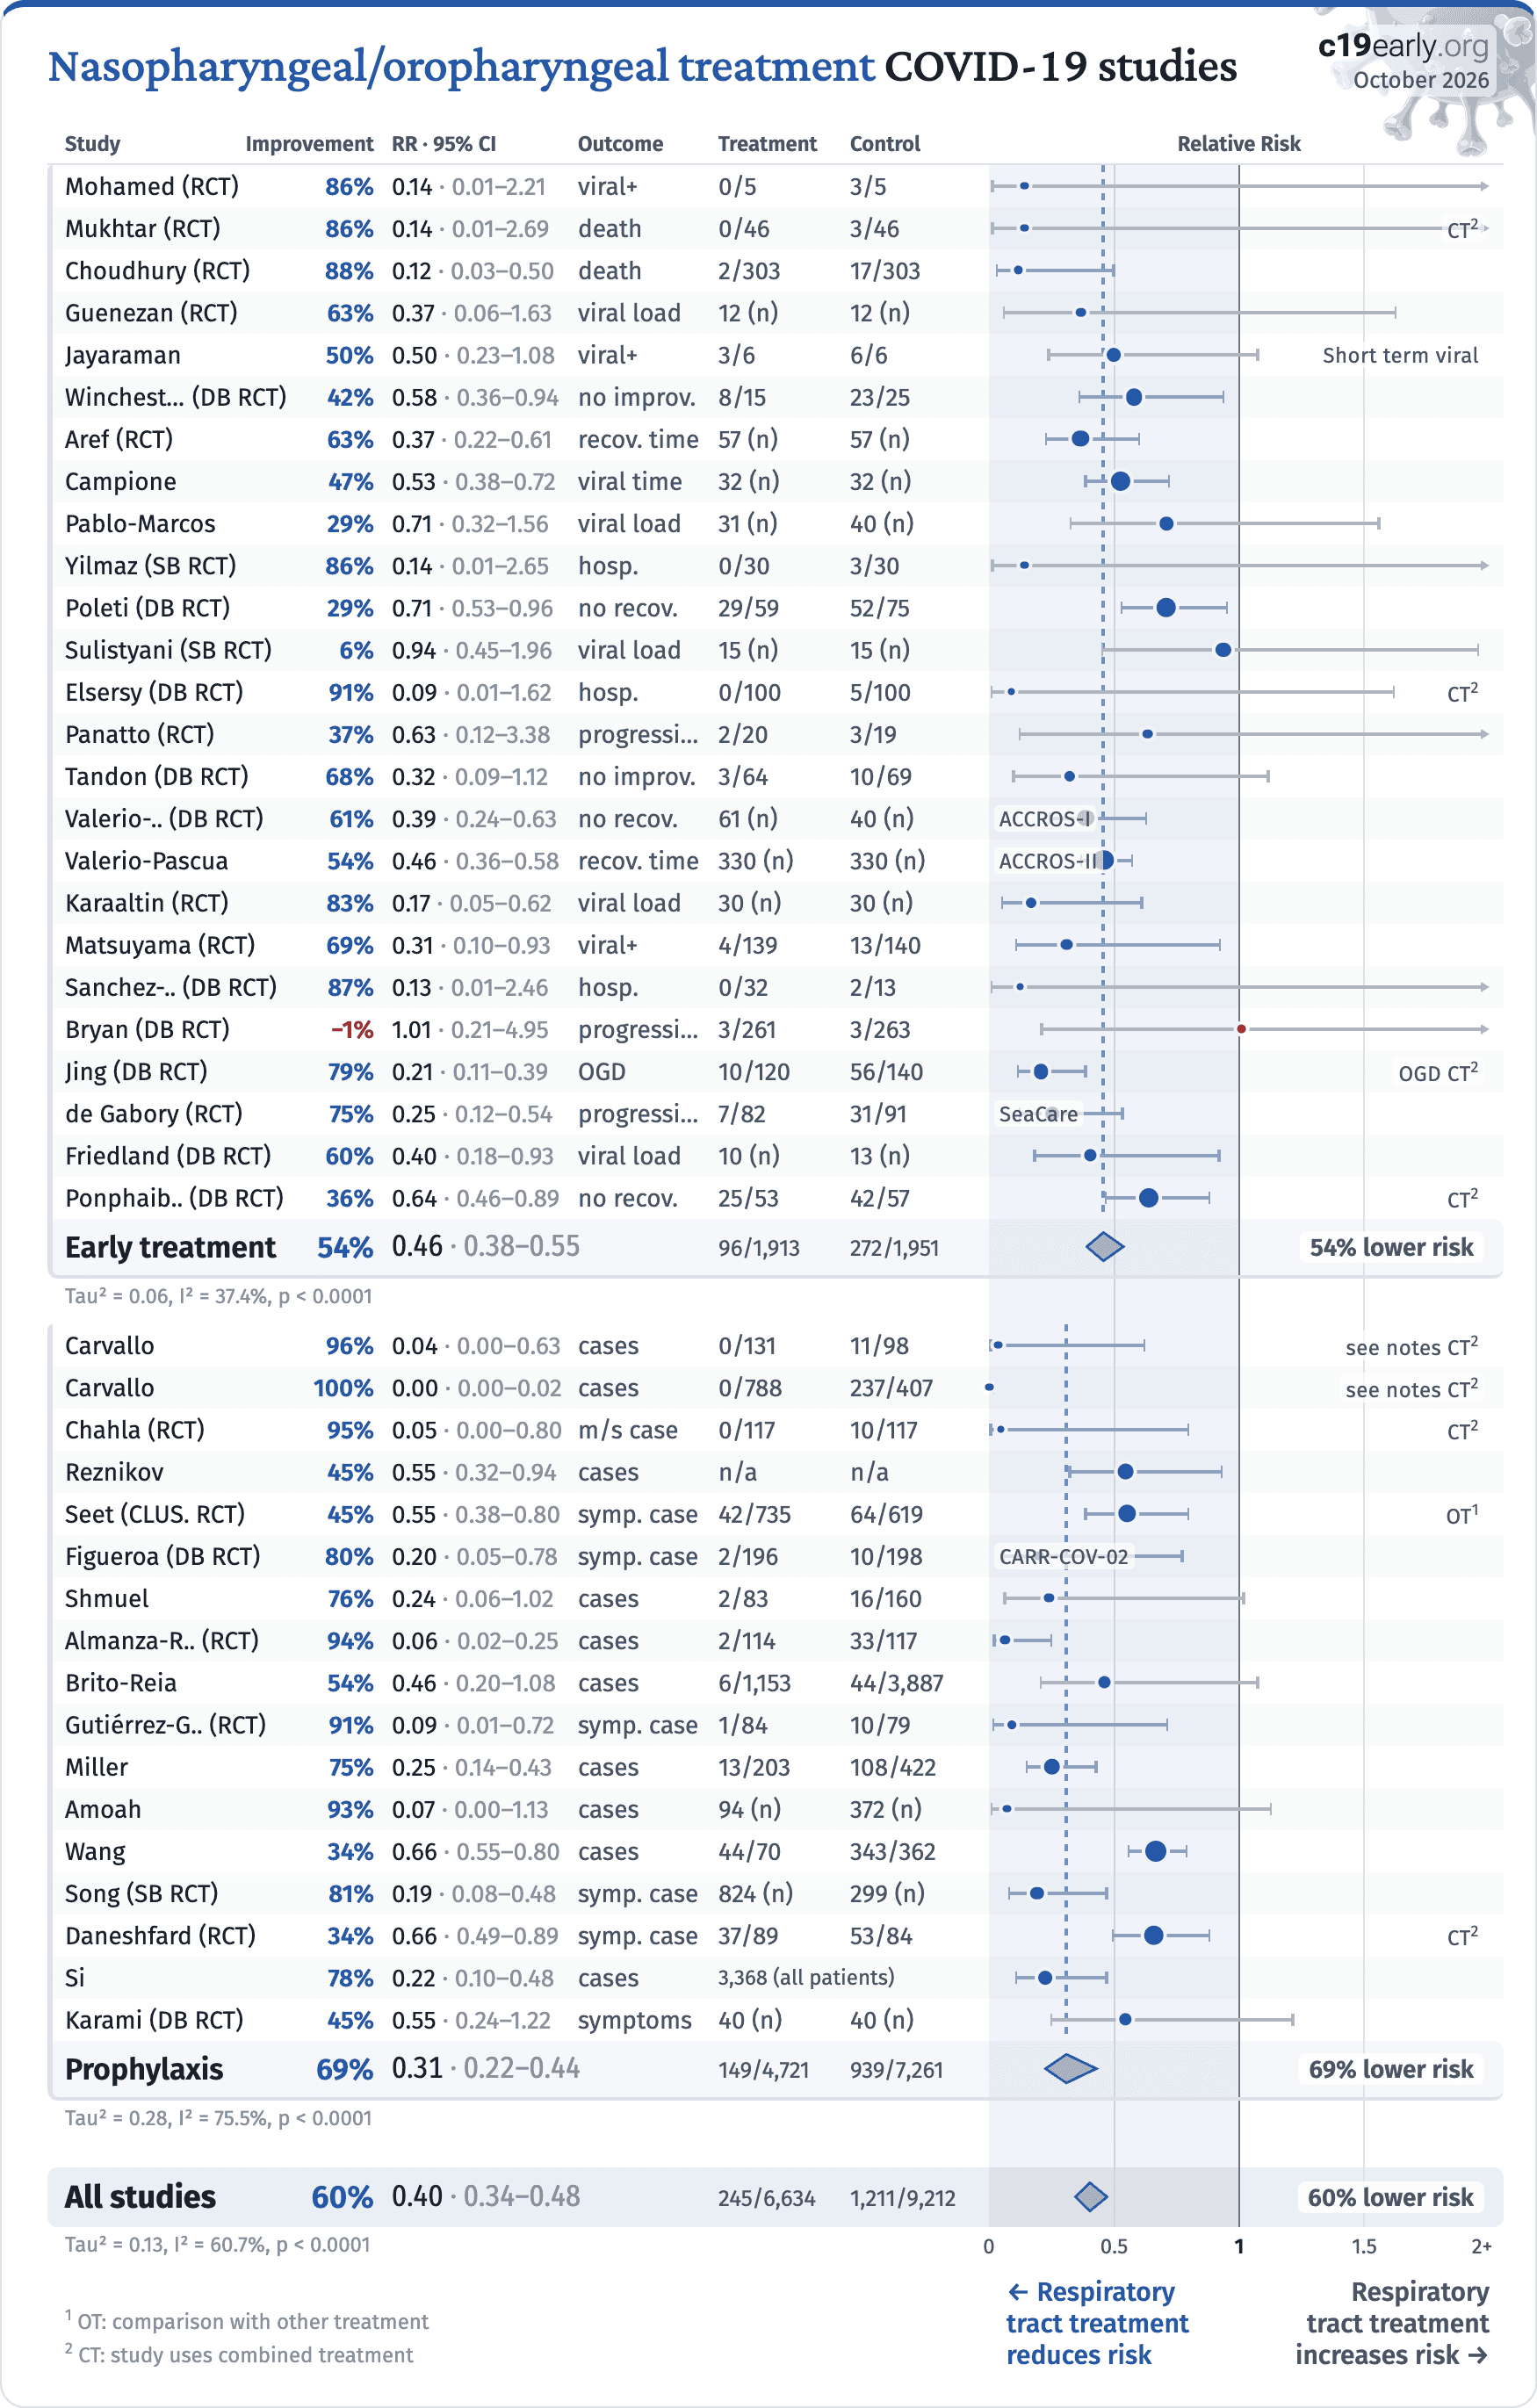
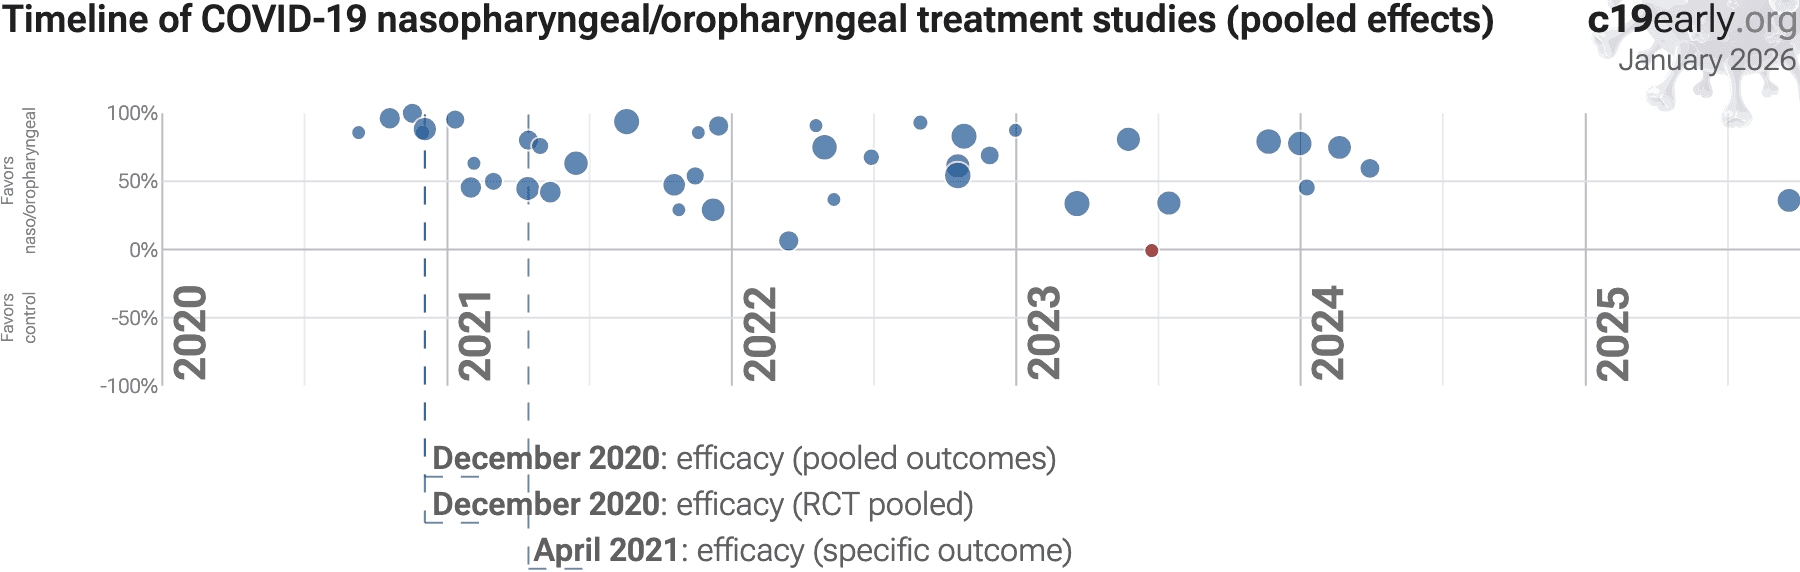
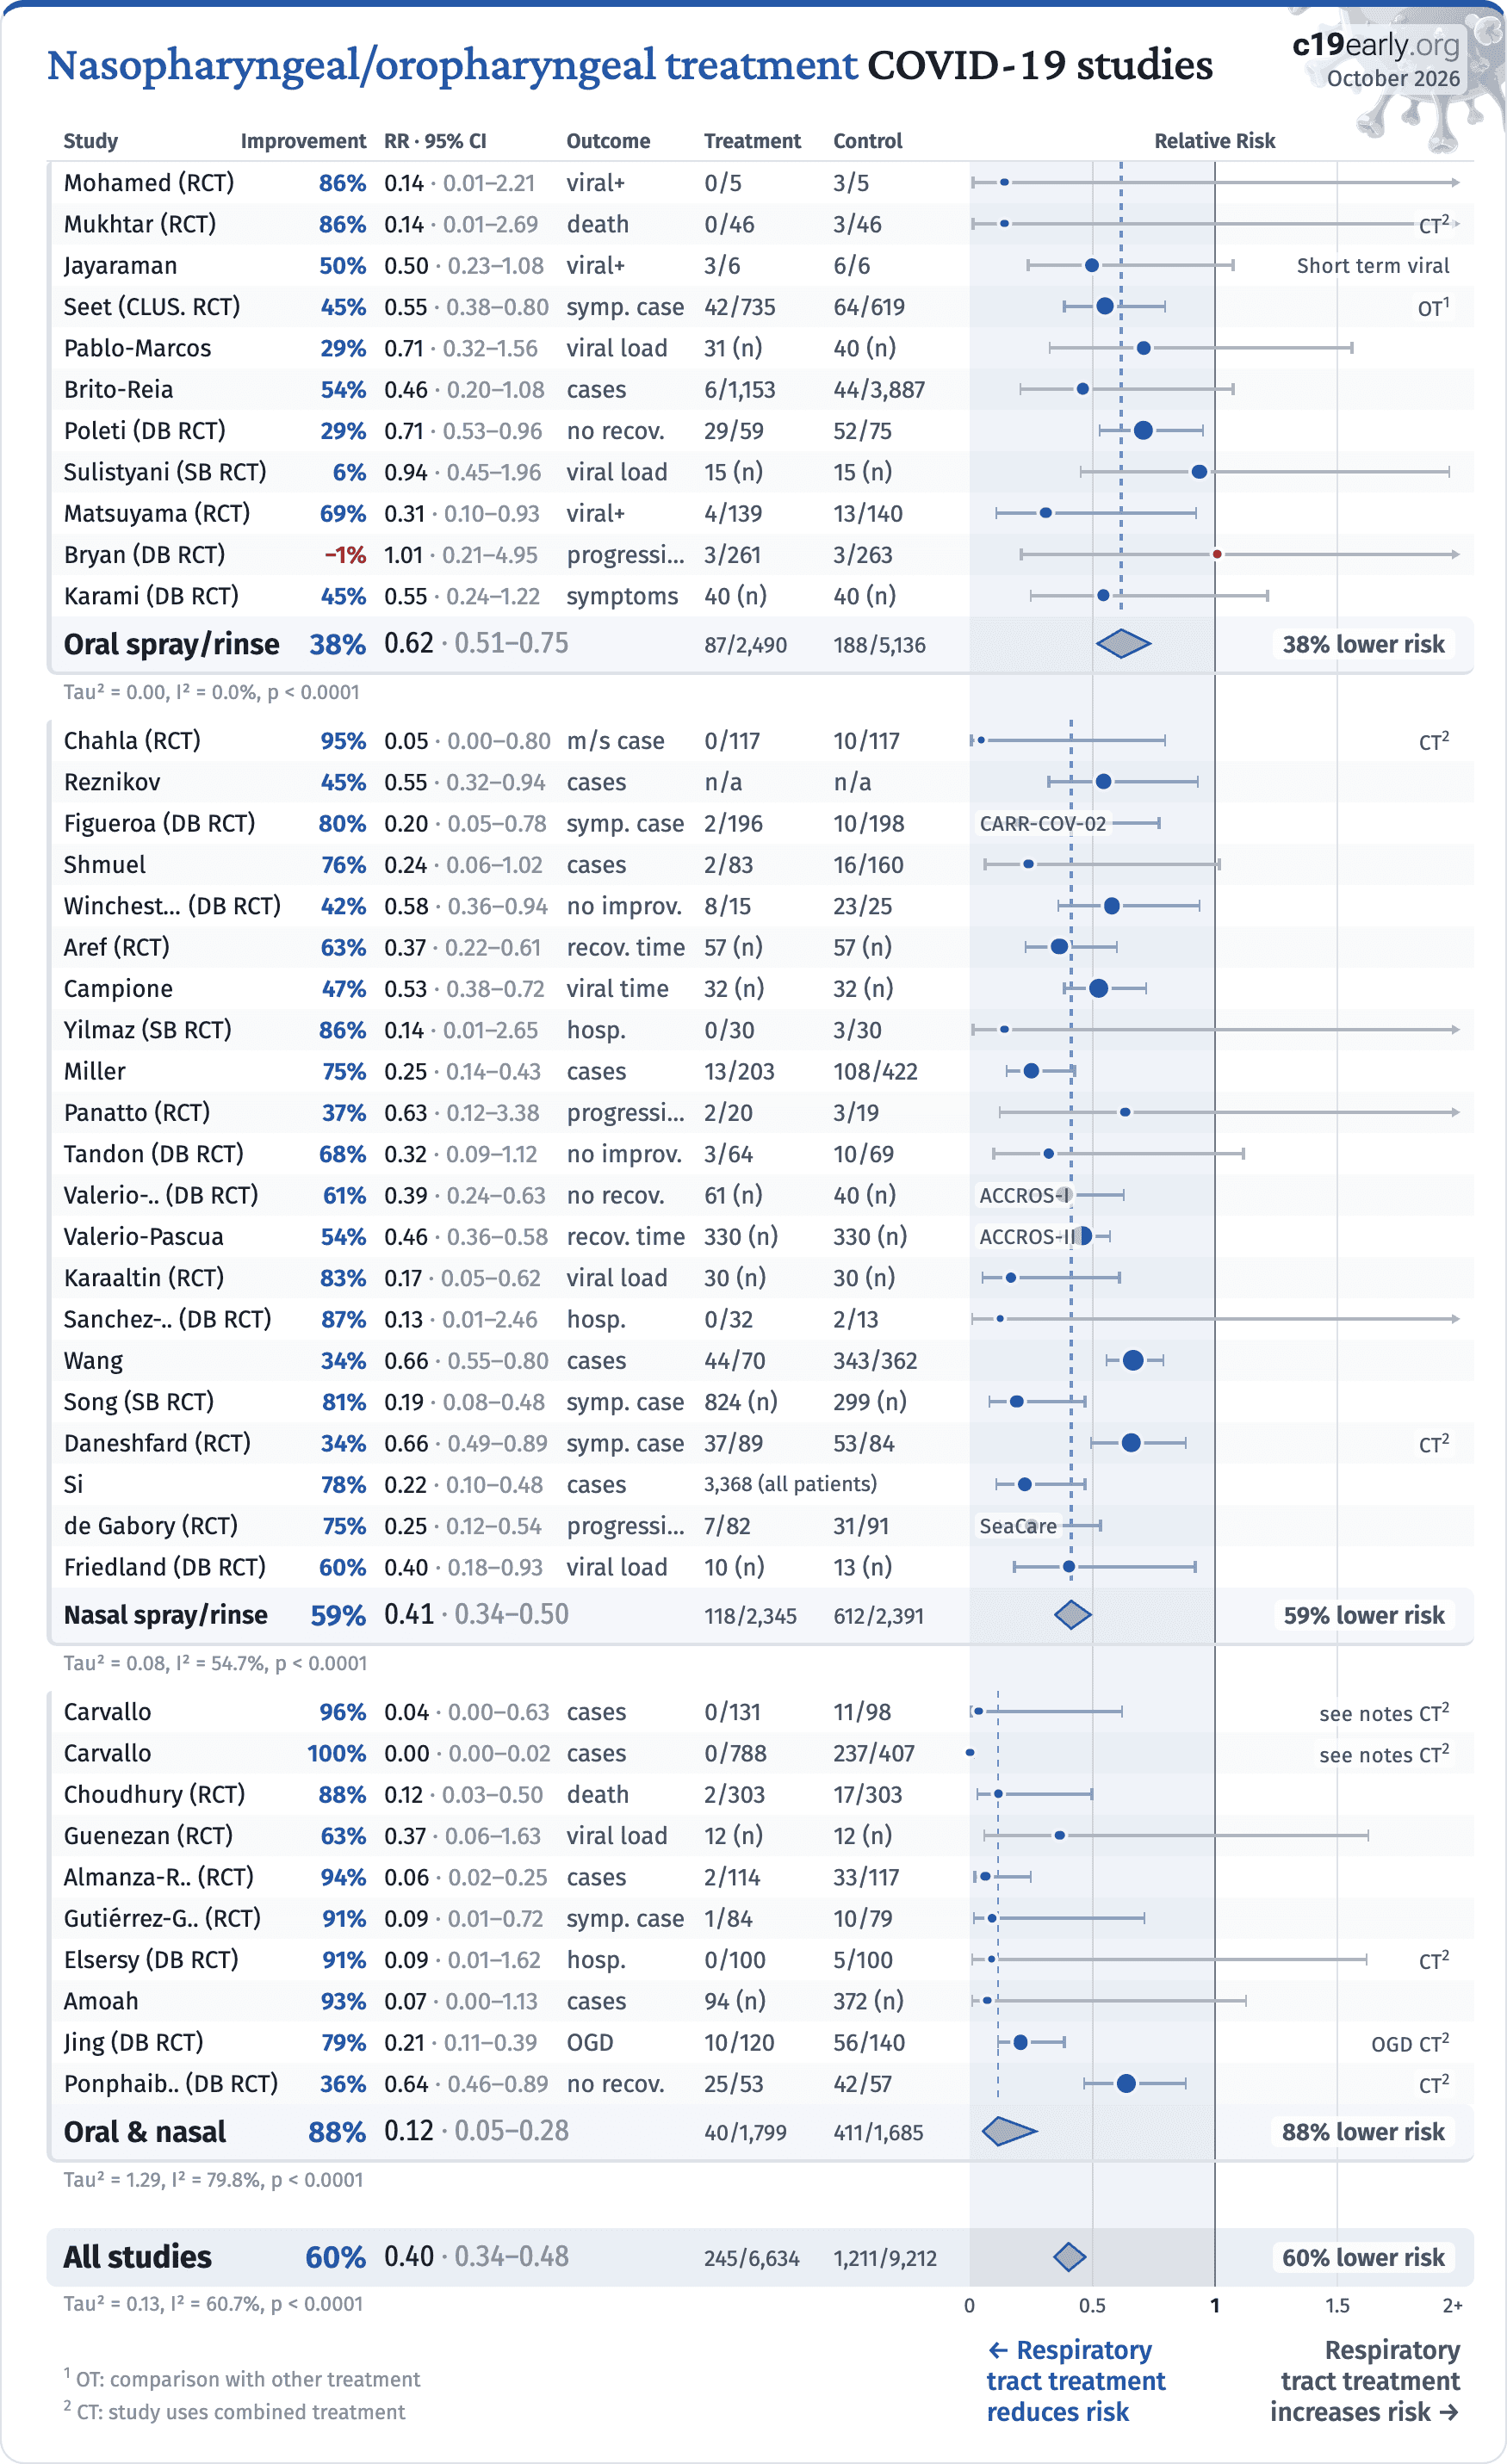
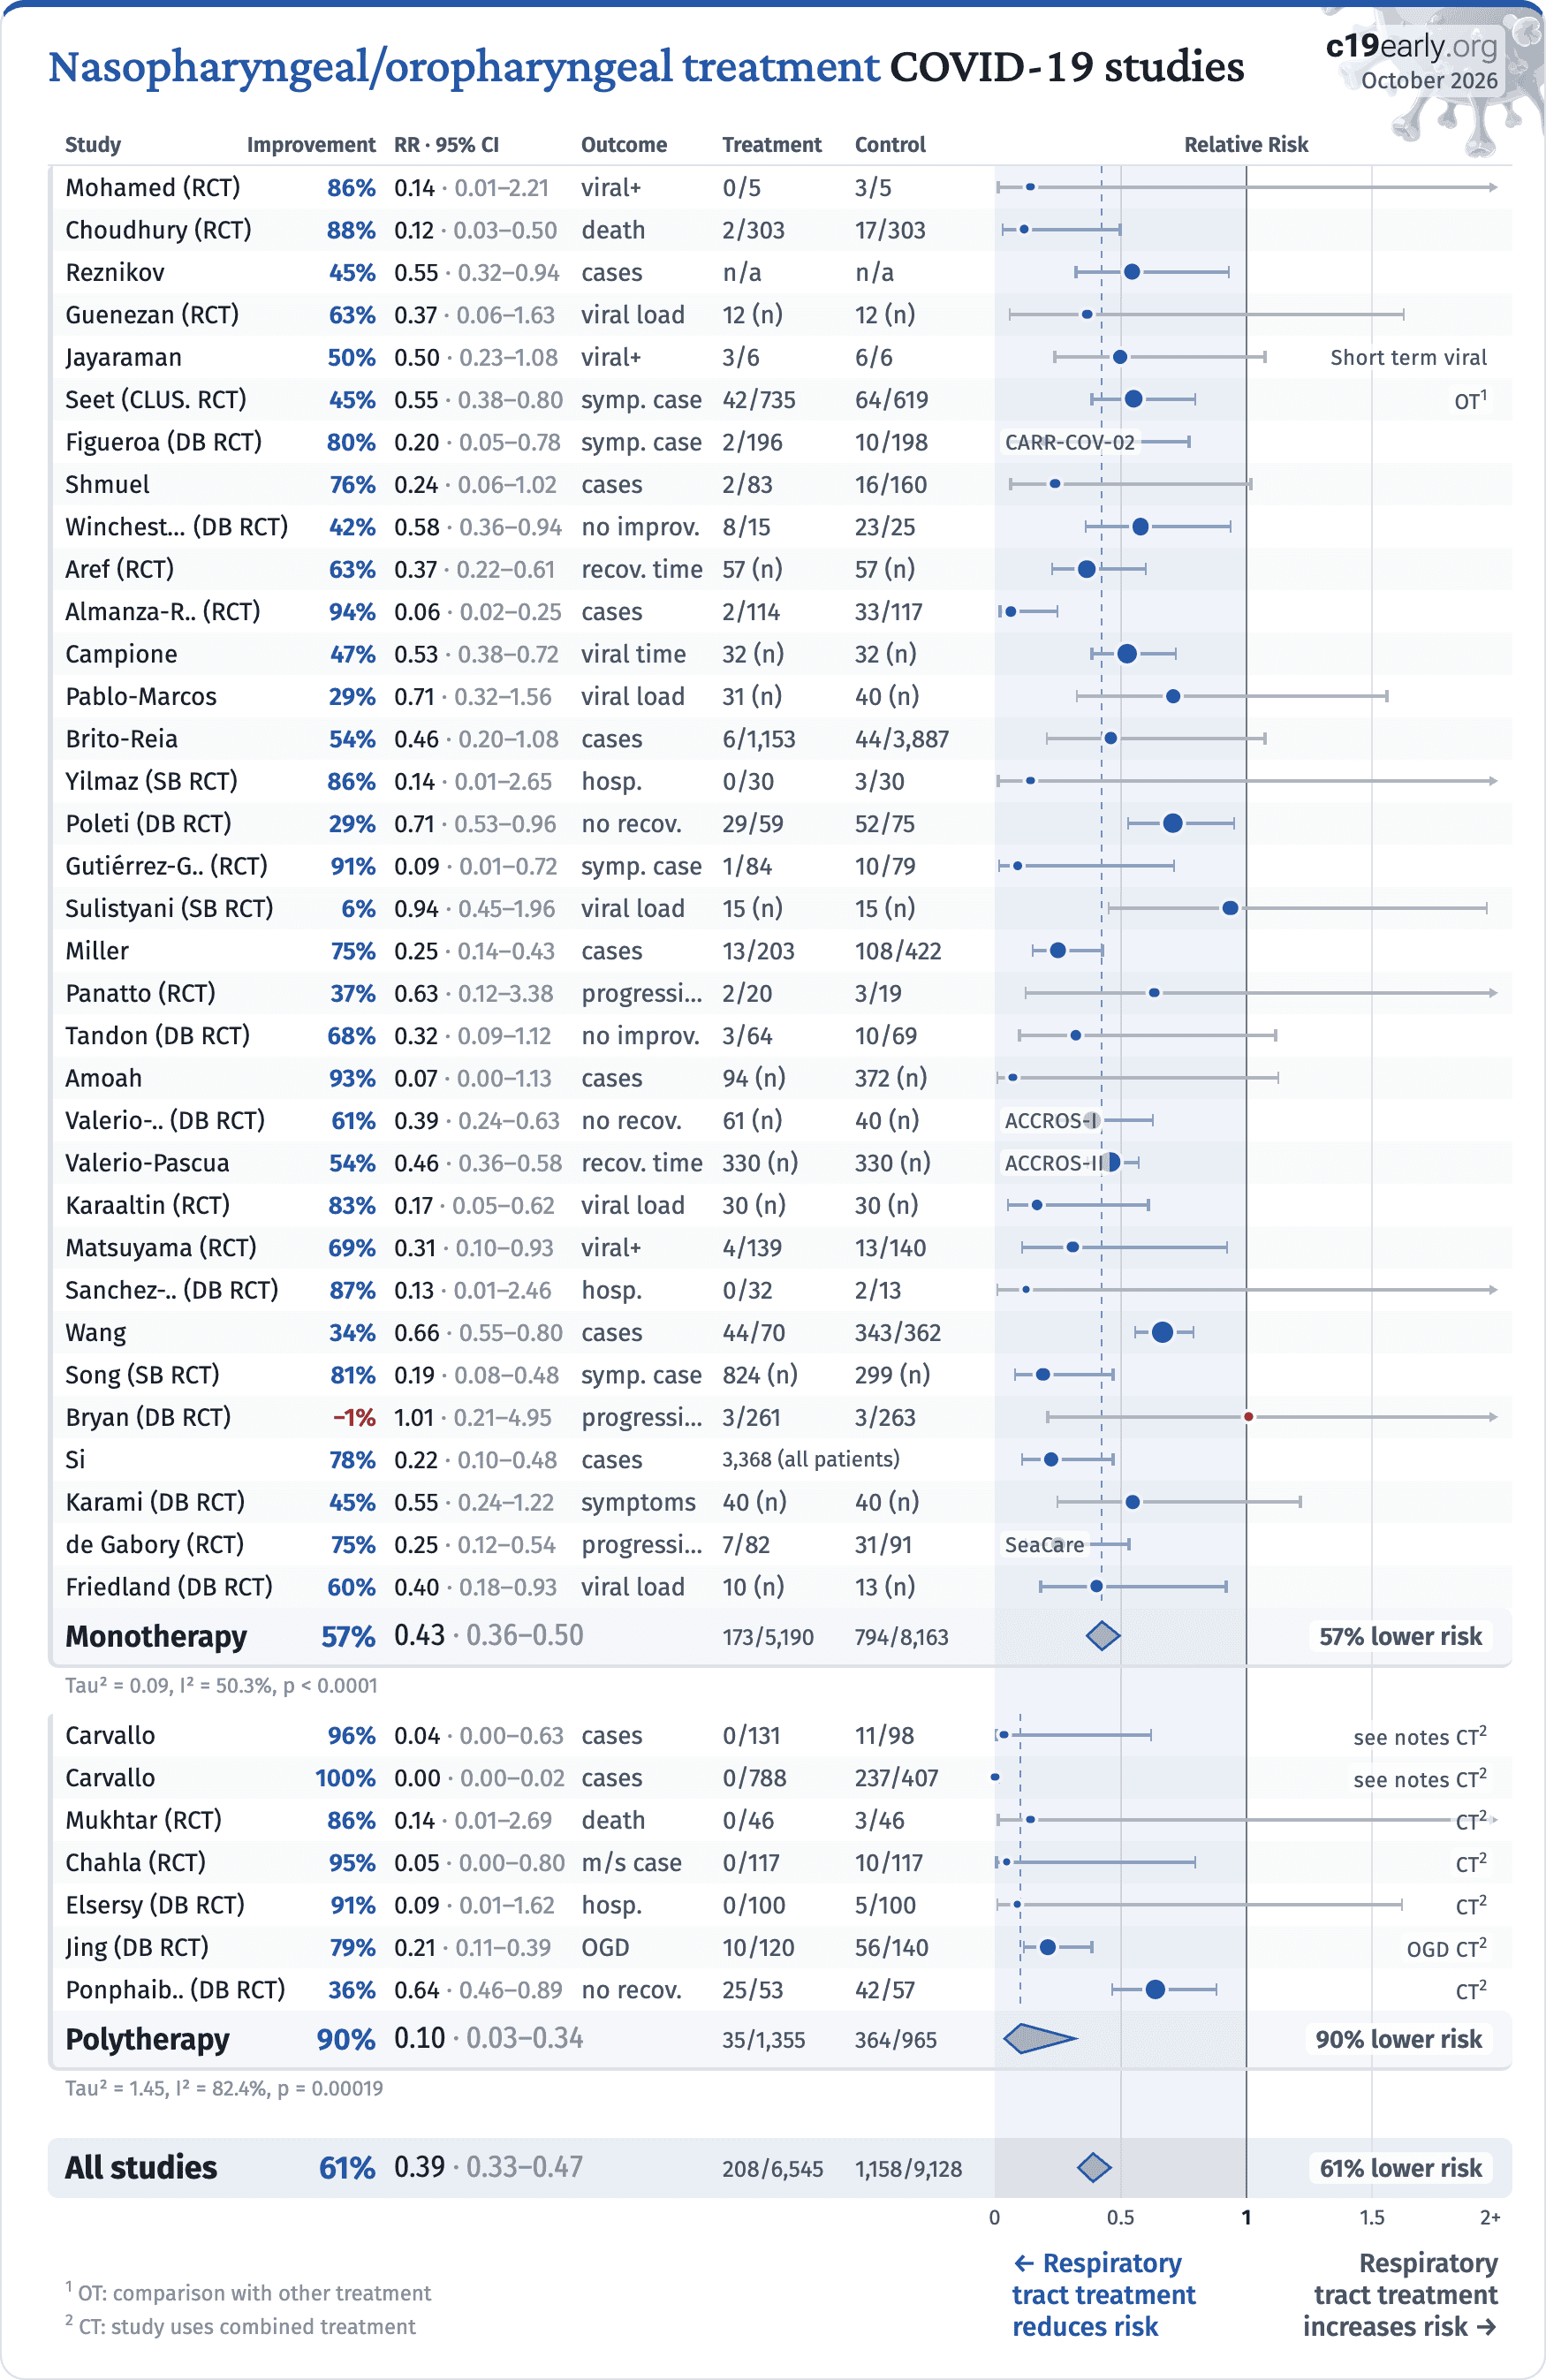
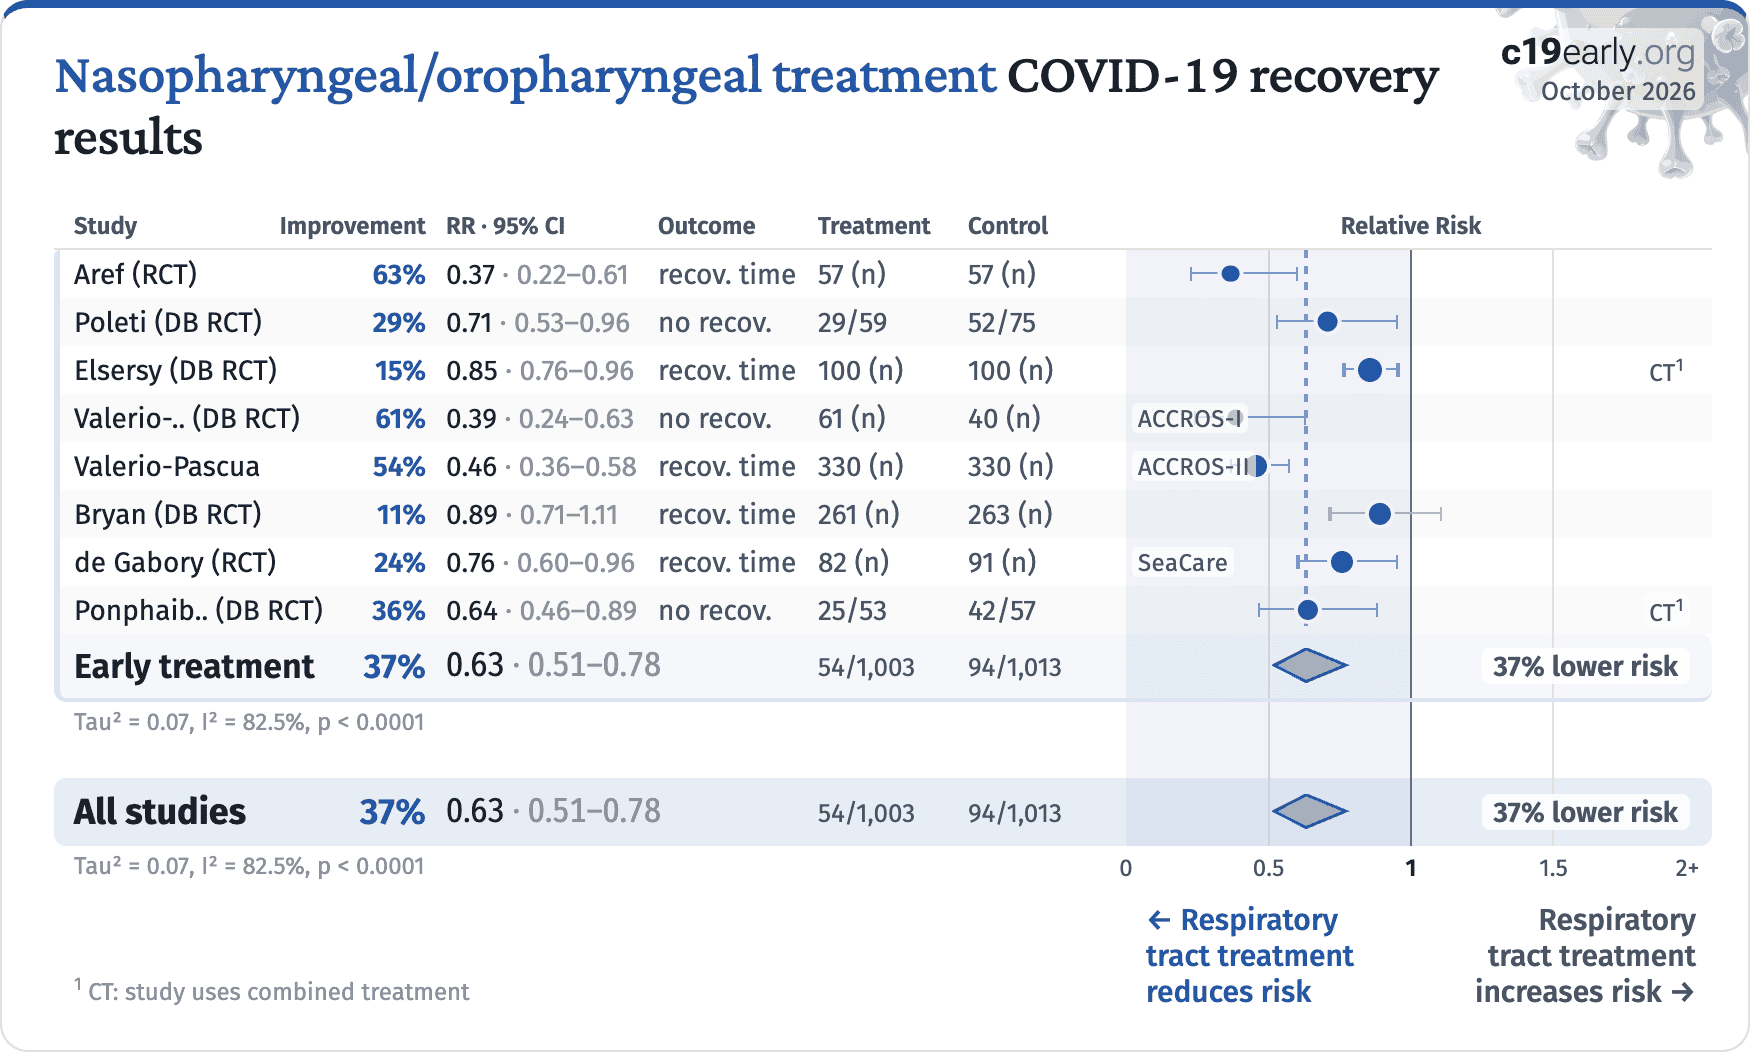
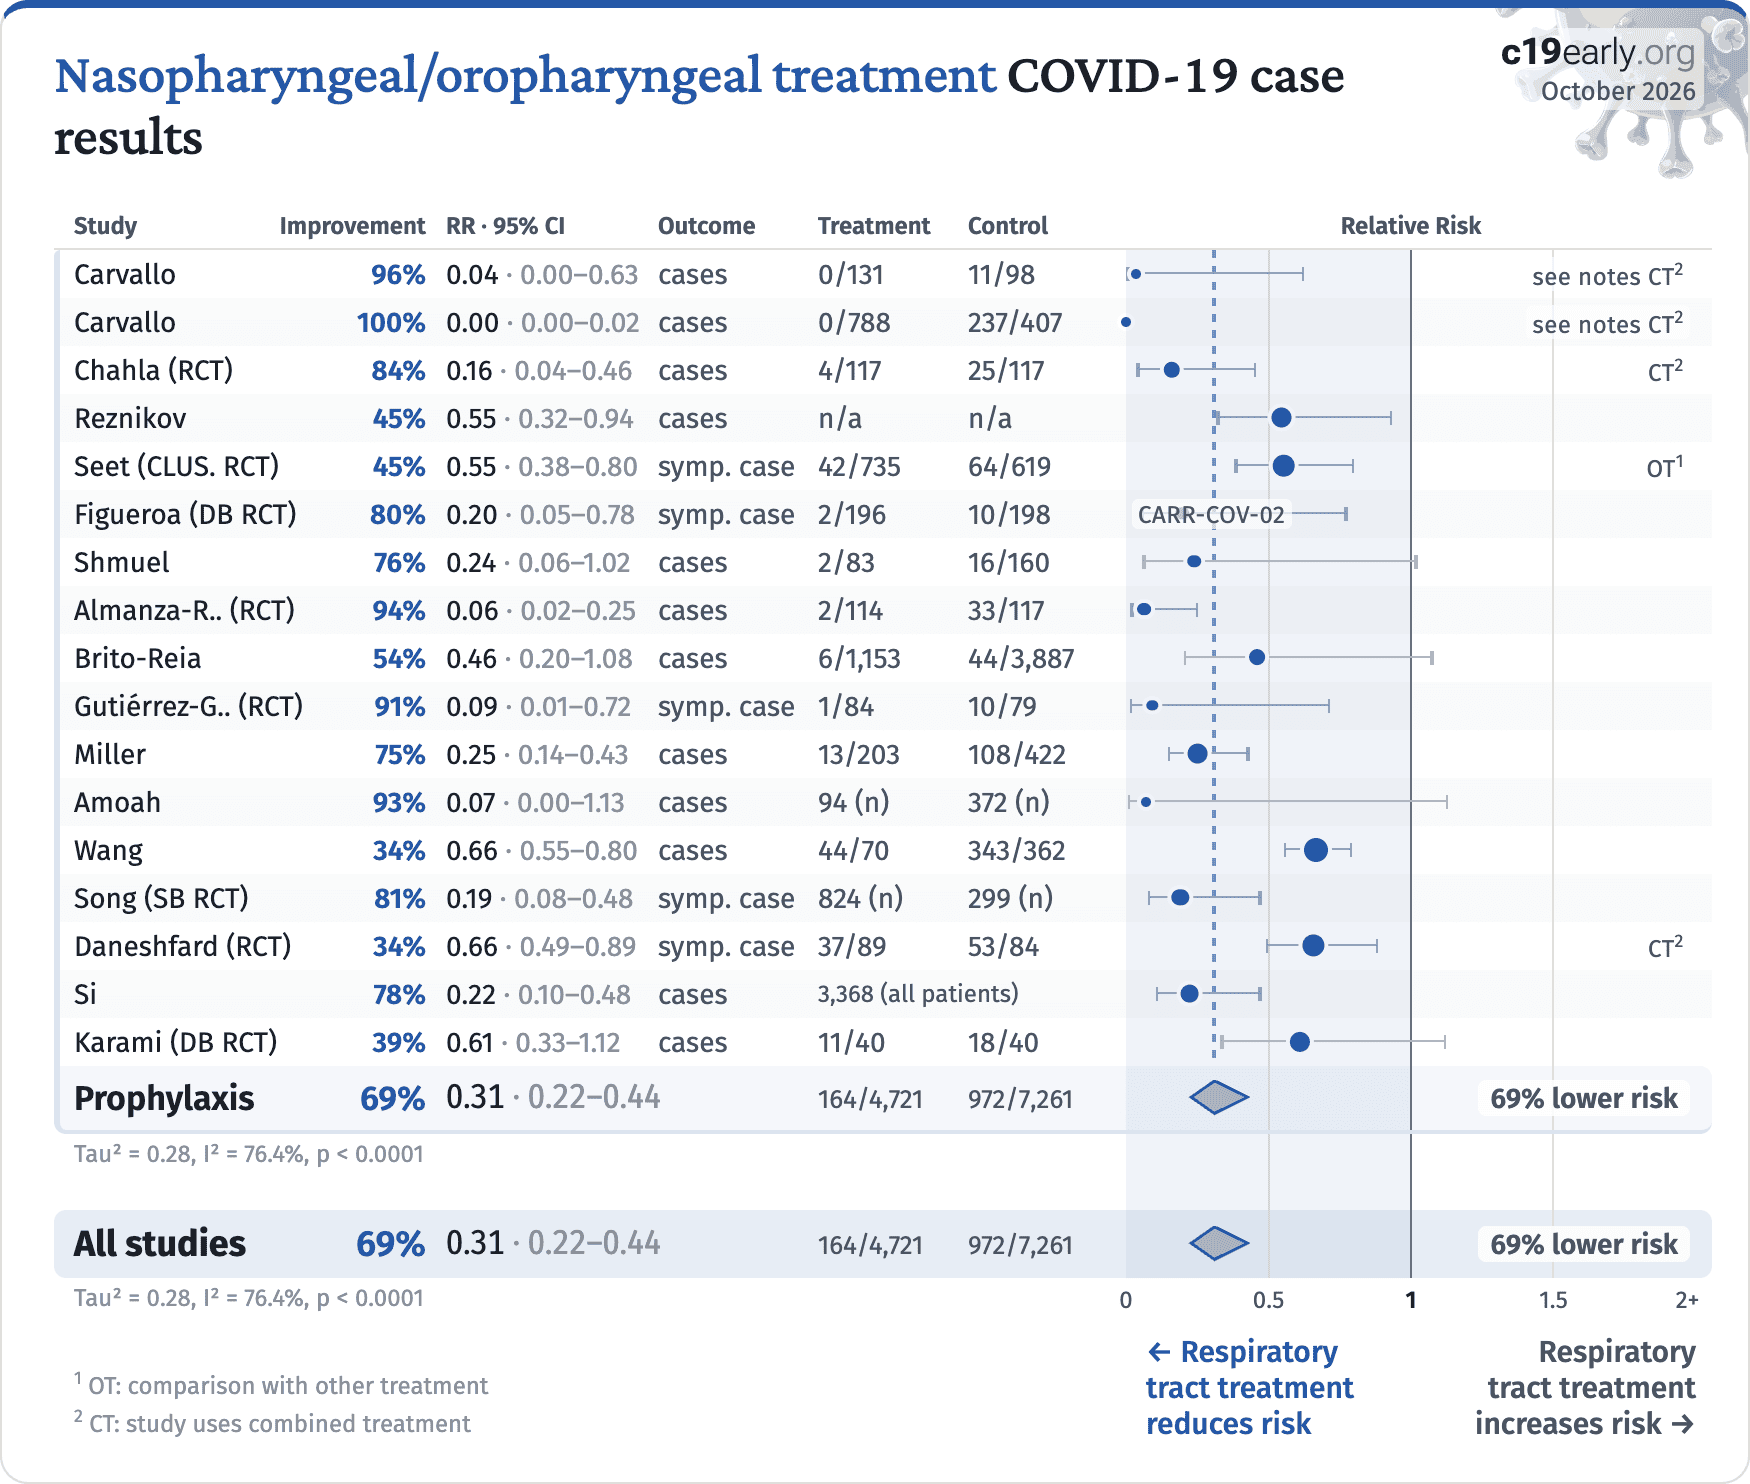
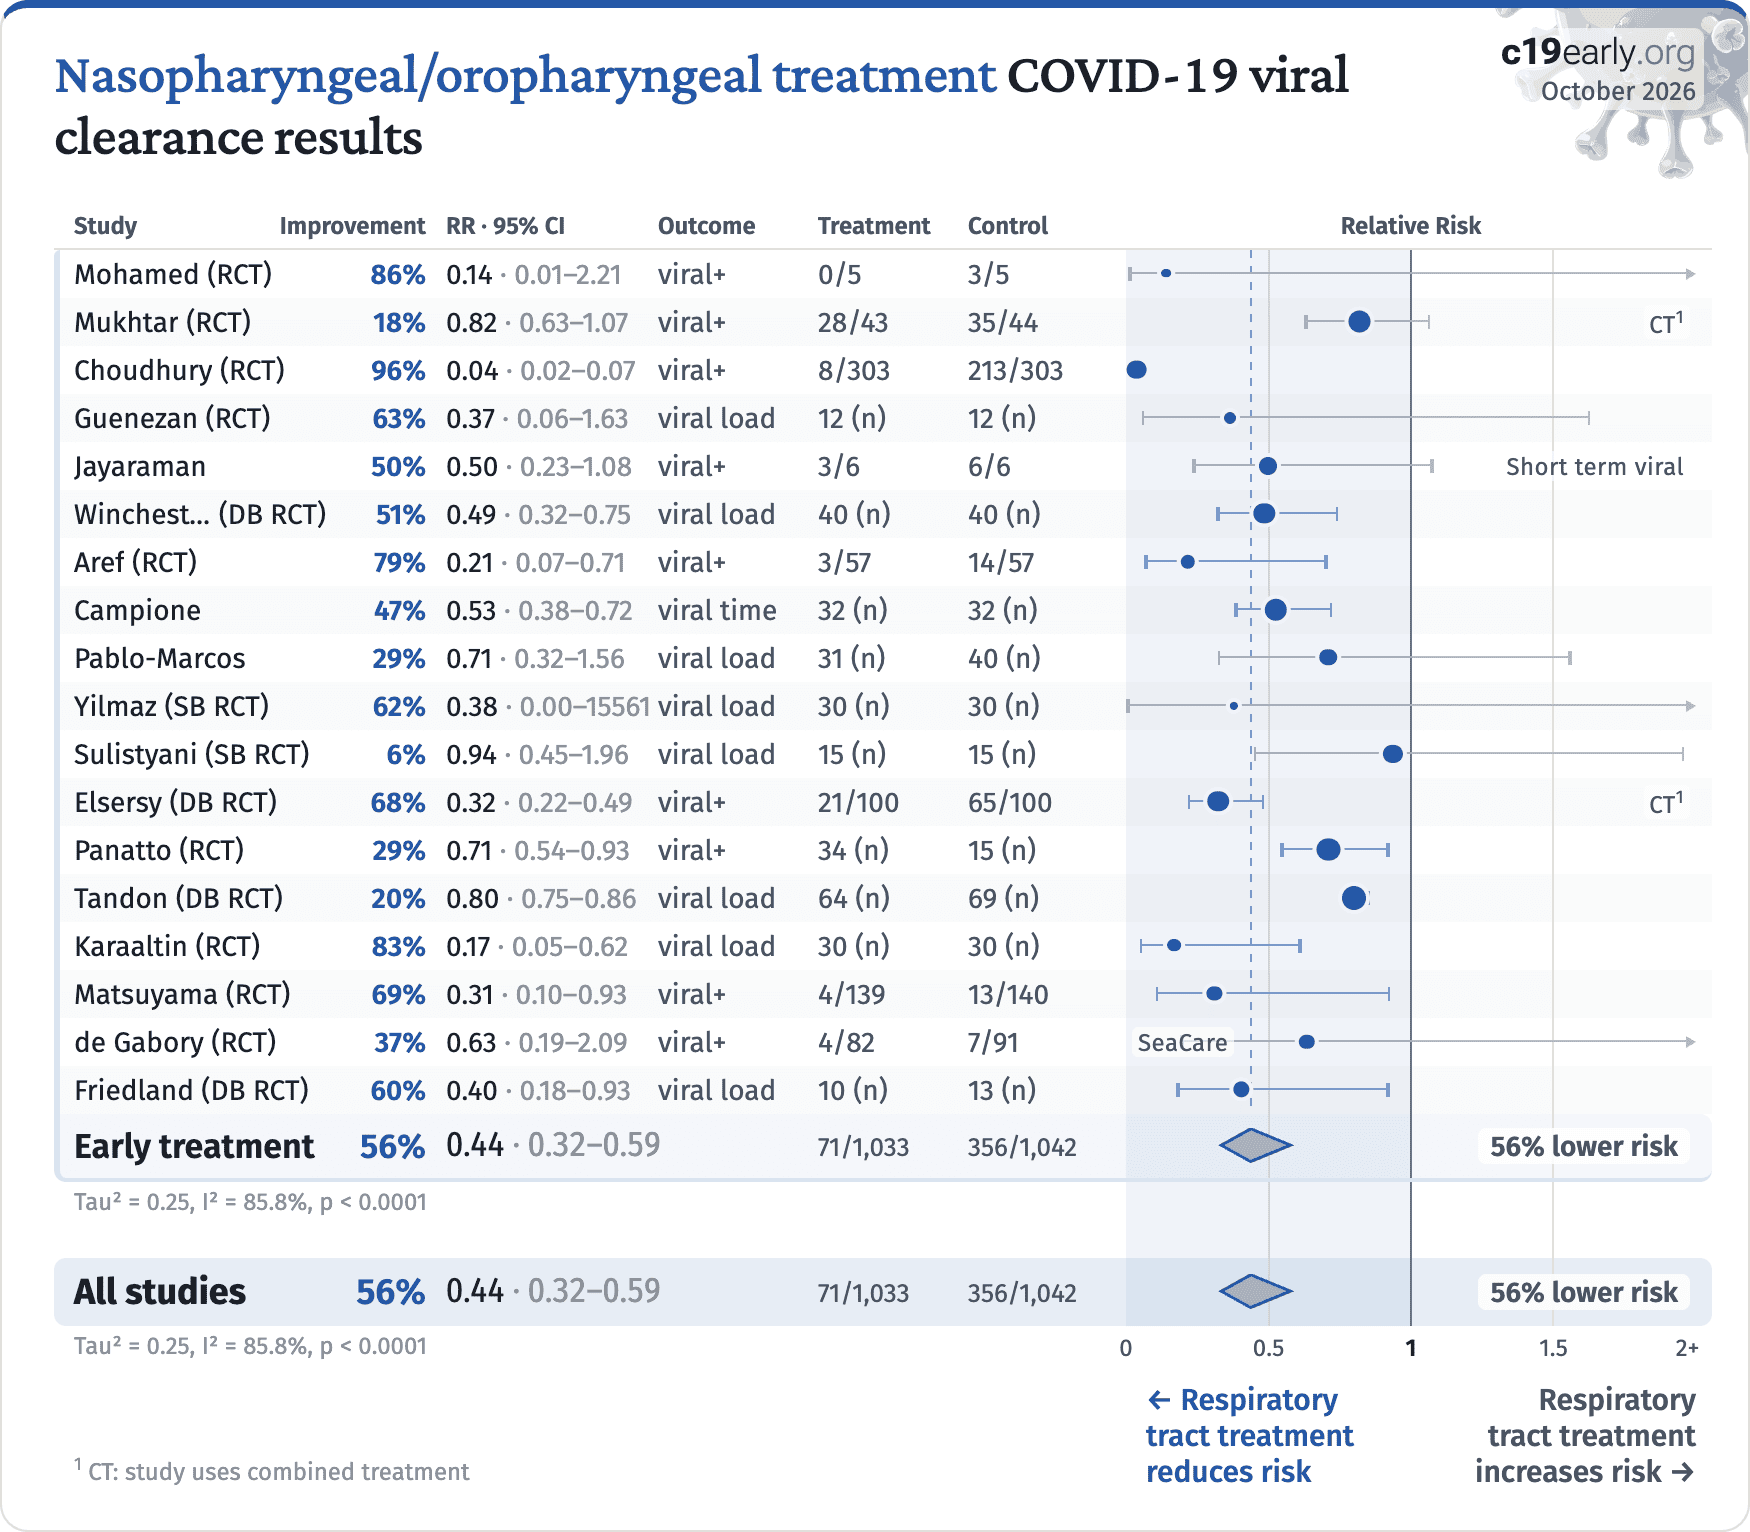
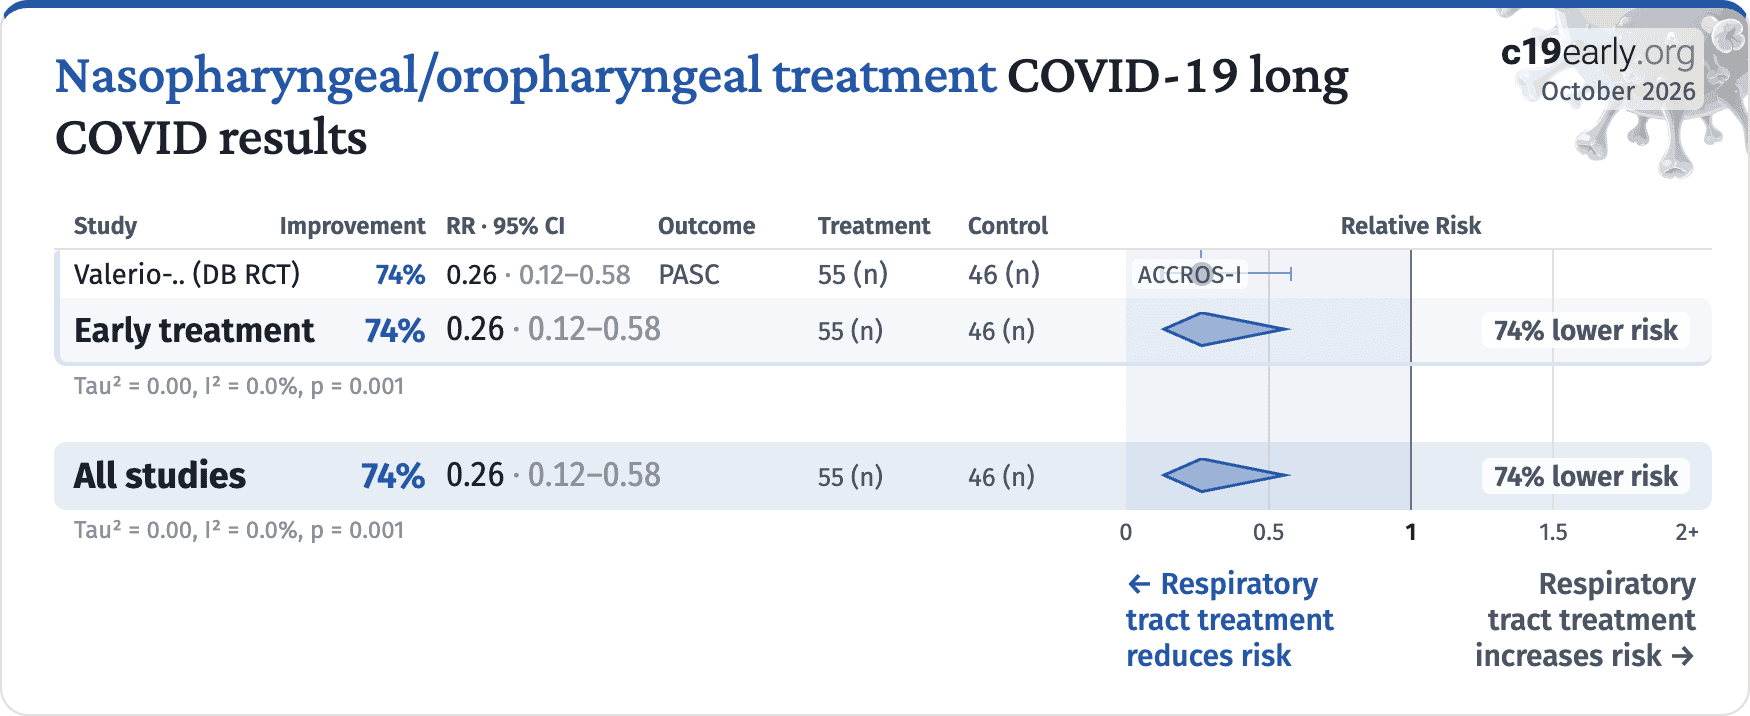
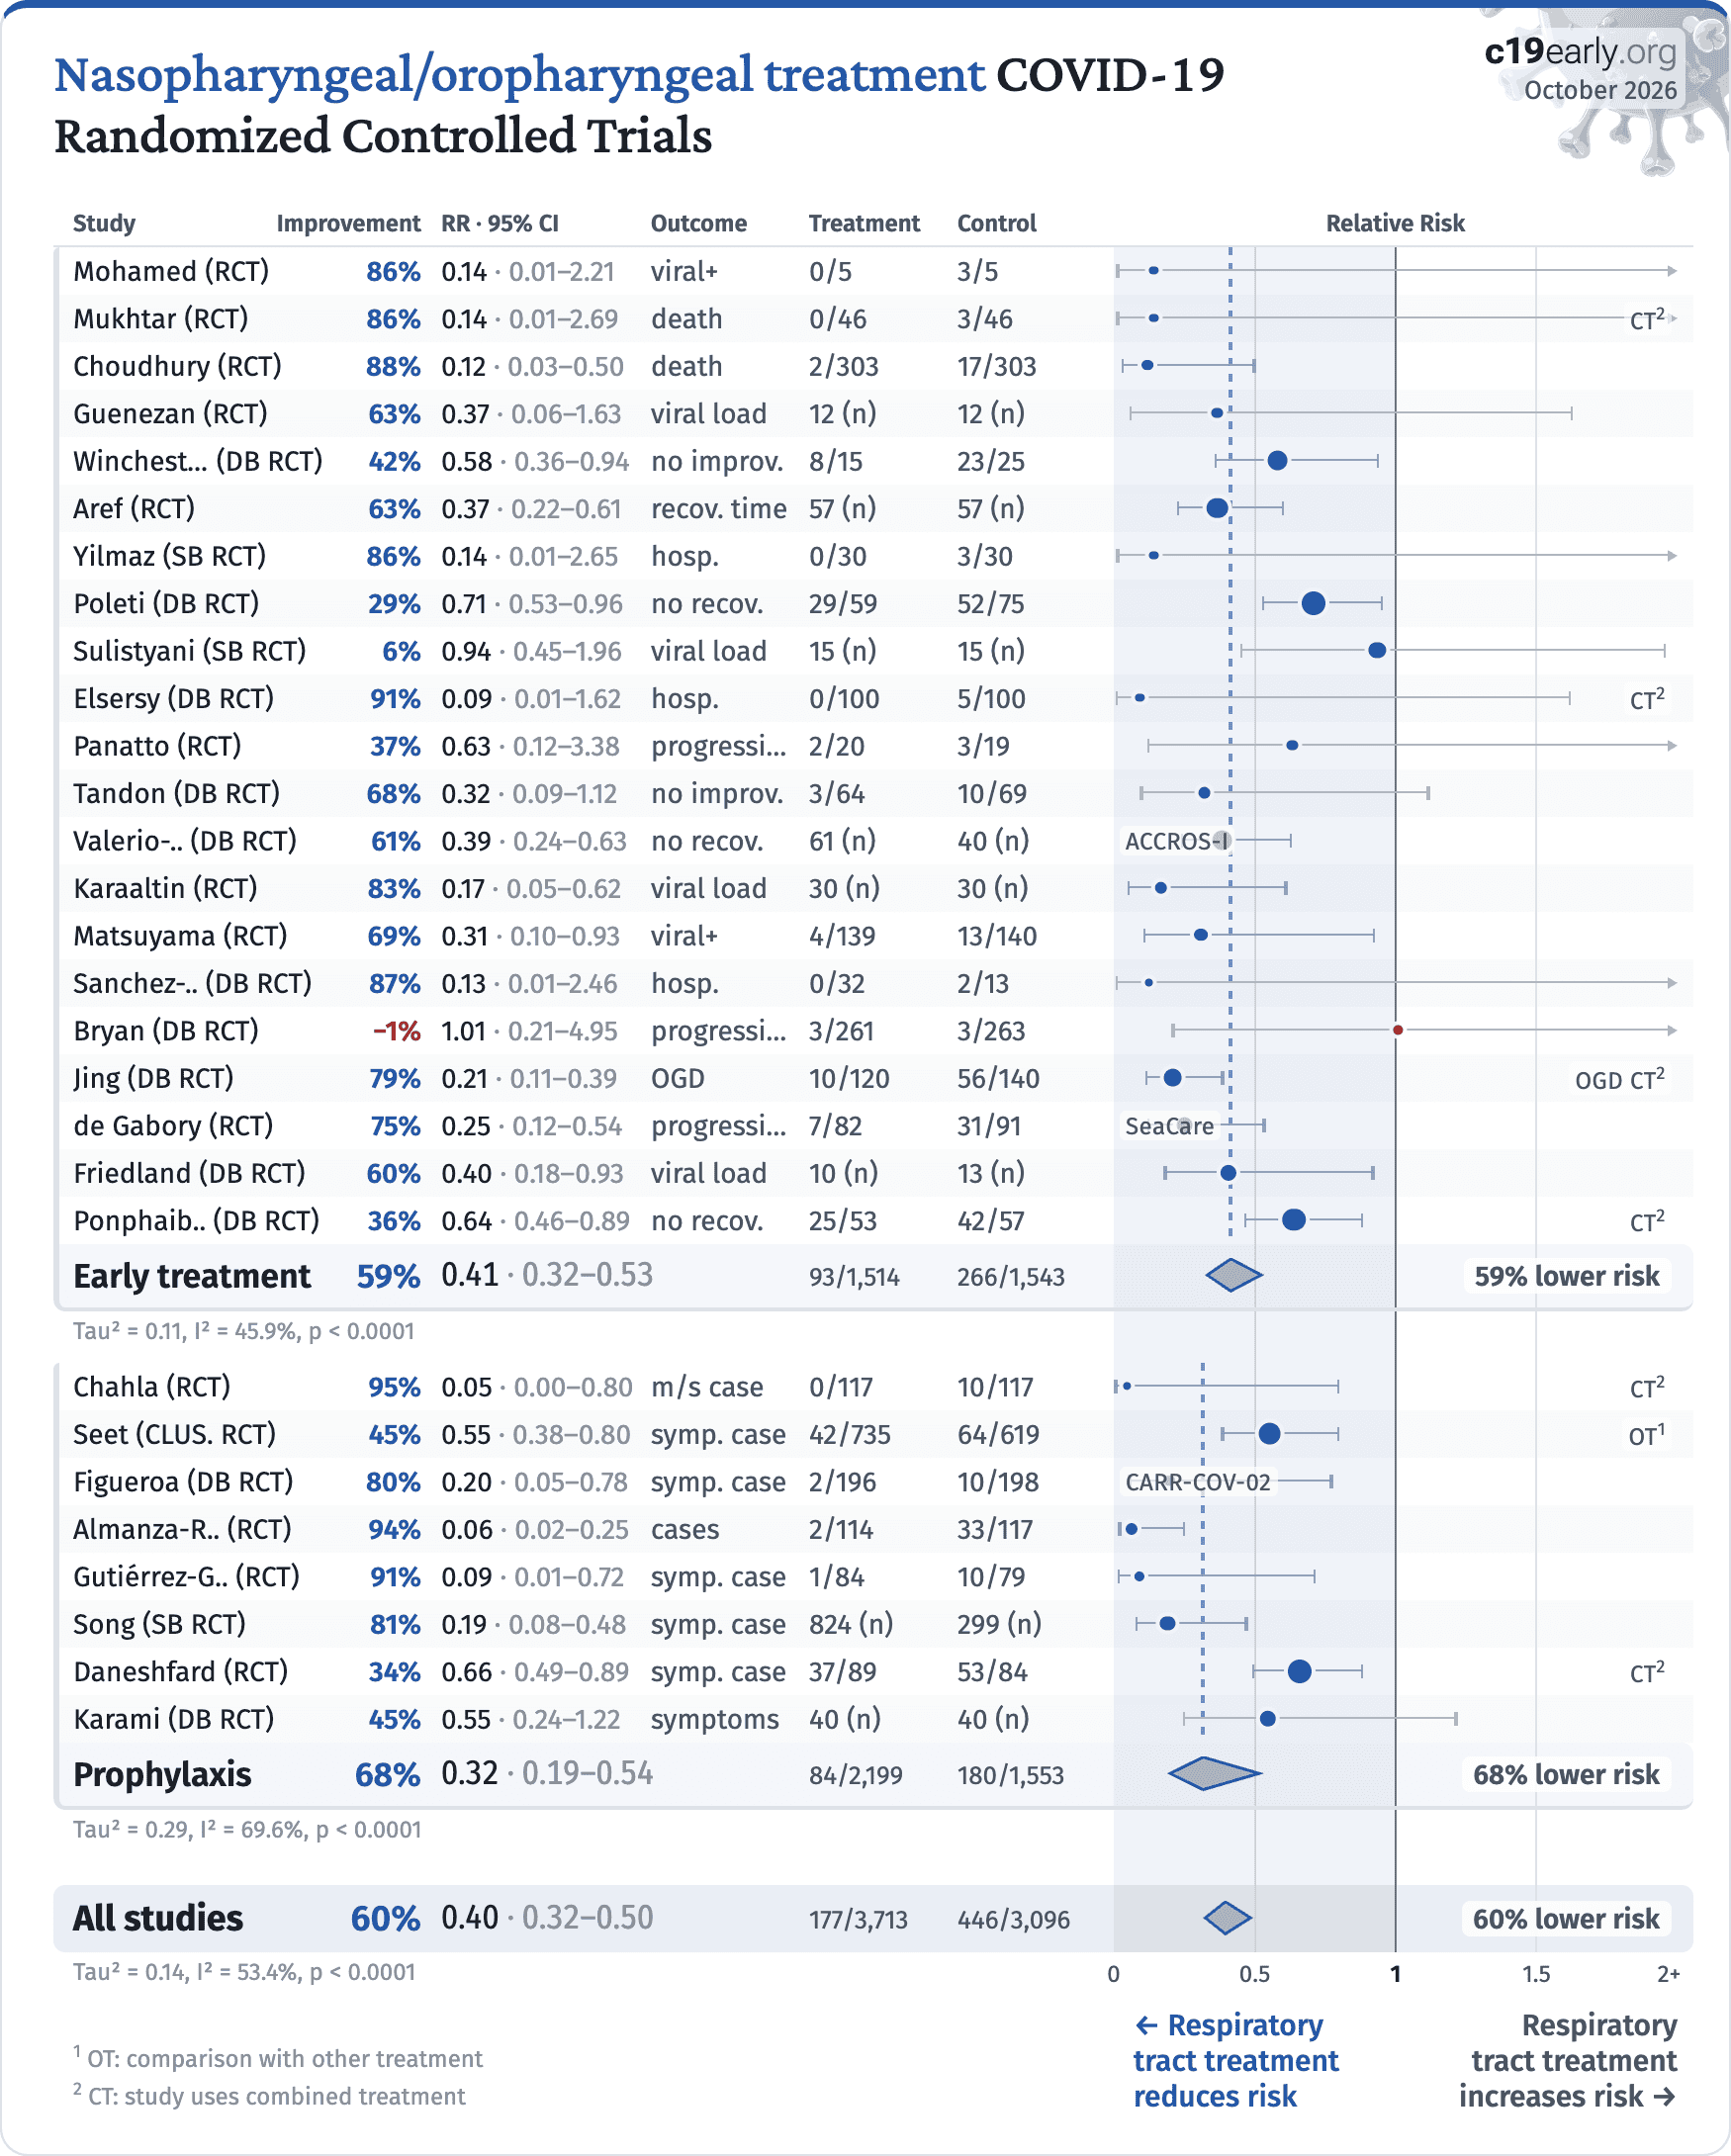
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/rtmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Aref, 6/15/2021, Randomized Controlled Trial, Egypt, peer-reviewed, 7 authors, study period February 2021 - March 2021, trial NCT04716569 (history).
|
relative duration of fever, 63.2% lower, relative time 0.37, p < 0.001, treatment 57, control 57, primary outcome.
|
|
relative duration of dyspnea, 56.4% lower, relative time 0.44, p < 0.001, treatment 57, control 57.
|
|
relative duration of anosmia, 68.8% lower, relative time 0.31, p < 0.001, treatment 57, control 57.
|
|
relative duration of cough, 64.3% lower, relative time 0.36, p < 0.001, treatment 57, control 57.
|
|
risk of no viral clearance, 78.6% lower, RR 0.21, p = 0.004, treatment 3 of 57 (5.3%), control 14 of 57 (24.6%), NNT 5.2.
|
|
time to viral-, 35.7% lower, relative time 0.64, p < 0.001, treatment 57, control 57.
|
|
Bryan, 6/24/2023, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, 3 authors, study period 1 November, 2020 - 30 November, 2022, trial NCT04601077 (history).
|
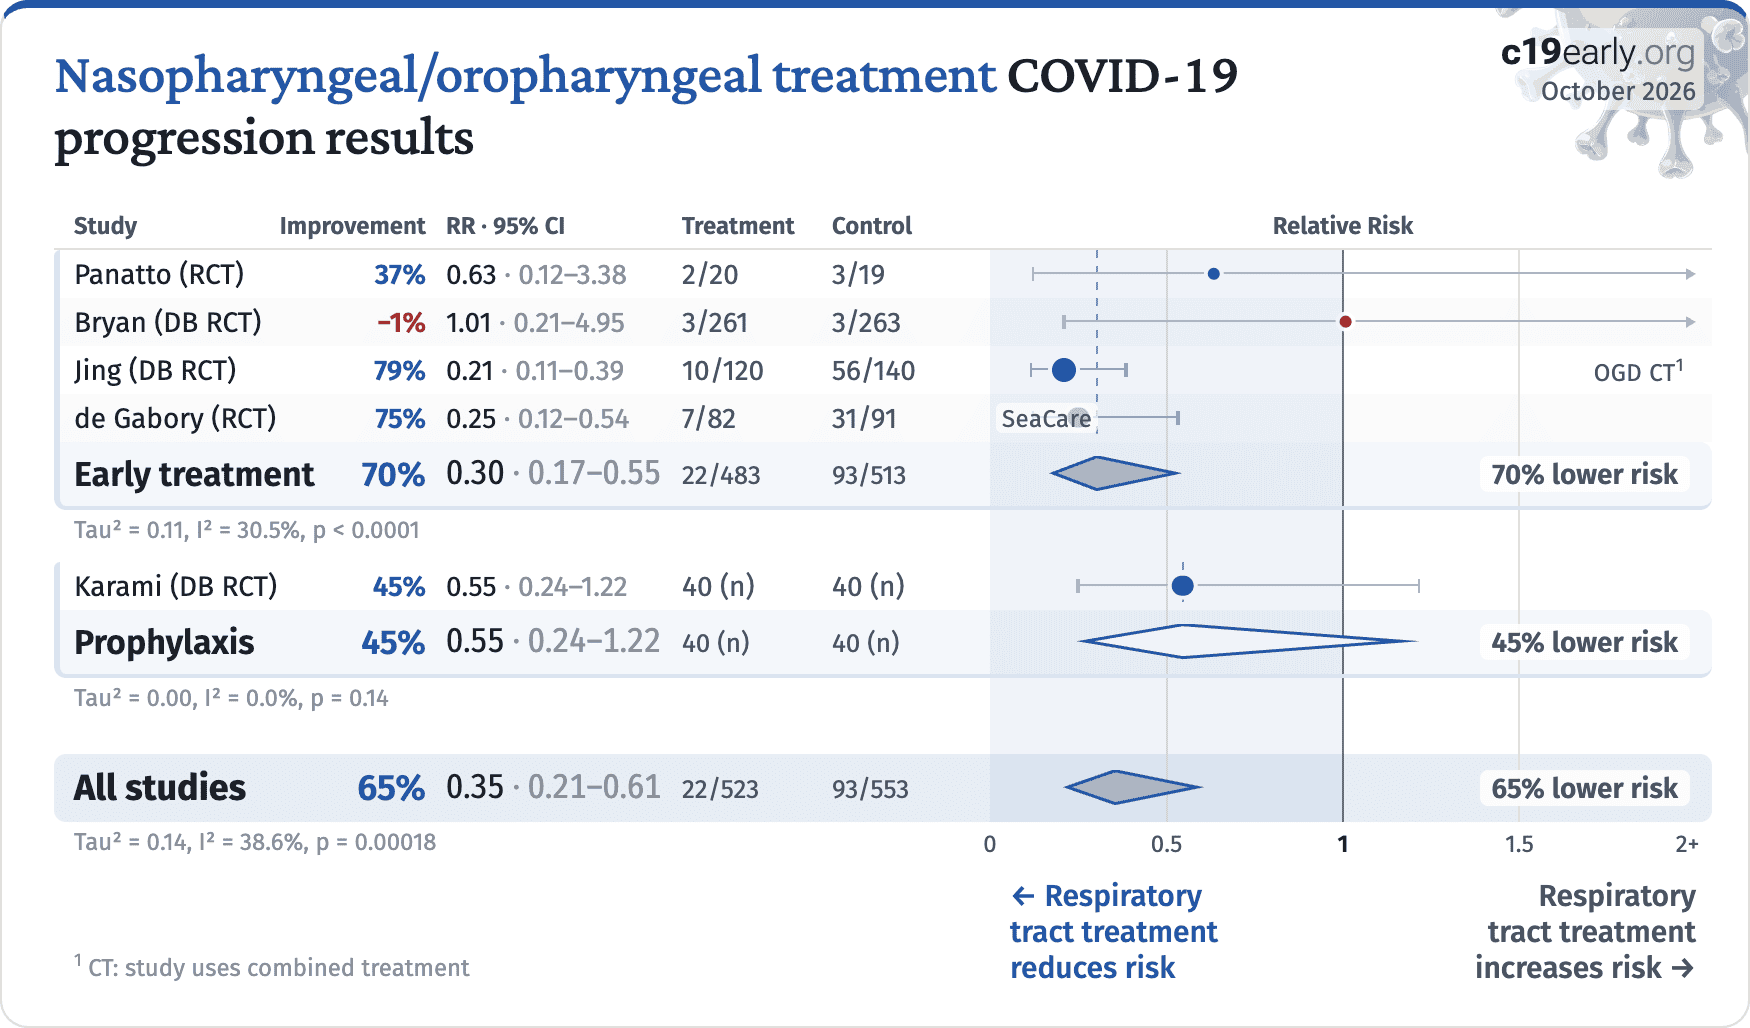
risk of progression, 0.8% higher, RR 1.01, p = 1.00, treatment 3 of 261 (1.1%), control 3 of 263 (1.1%), combined hospitalization, ICU admission, intubation, dialysis, and death.
|
|
recovery time, 11.2% lower, relative time 0.89, p = 0.30, treatment 261, control 263.
|
|
Campione, 10/19/2021, prospective, Italy, peer-reviewed, 32 authors.
|
time to viral-, 47.5% lower, relative time 0.53, p < 0.001, treatment 32, control 32, vs. SOC.
|
|
time to viral-, 56.3% lower, relative time 0.44, p < 0.001, treatment 32, control 28, vs. untreated.
|
|
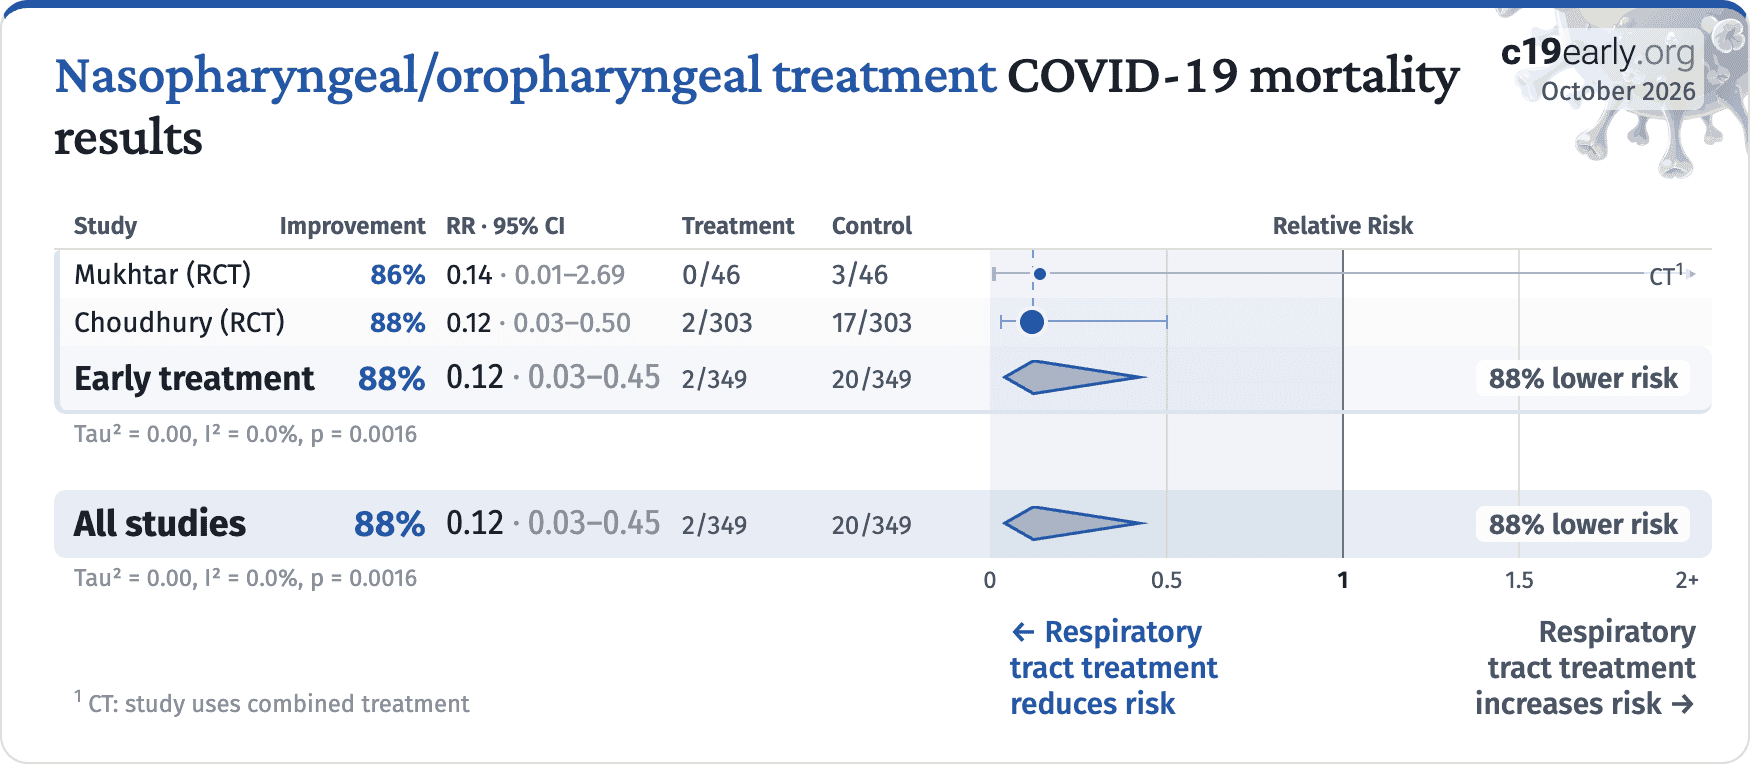
Choudhury, 12/3/2020, Randomized Controlled Trial, Bangladesh, peer-reviewed, 6 authors, study period 1 February, 2020 - 30 August, 2020.
|
risk of death, 88.2% lower, RR 0.12, p < 0.001, treatment 2 of 303 (0.7%), control 17 of 303 (5.6%), NNT 20.
|
|
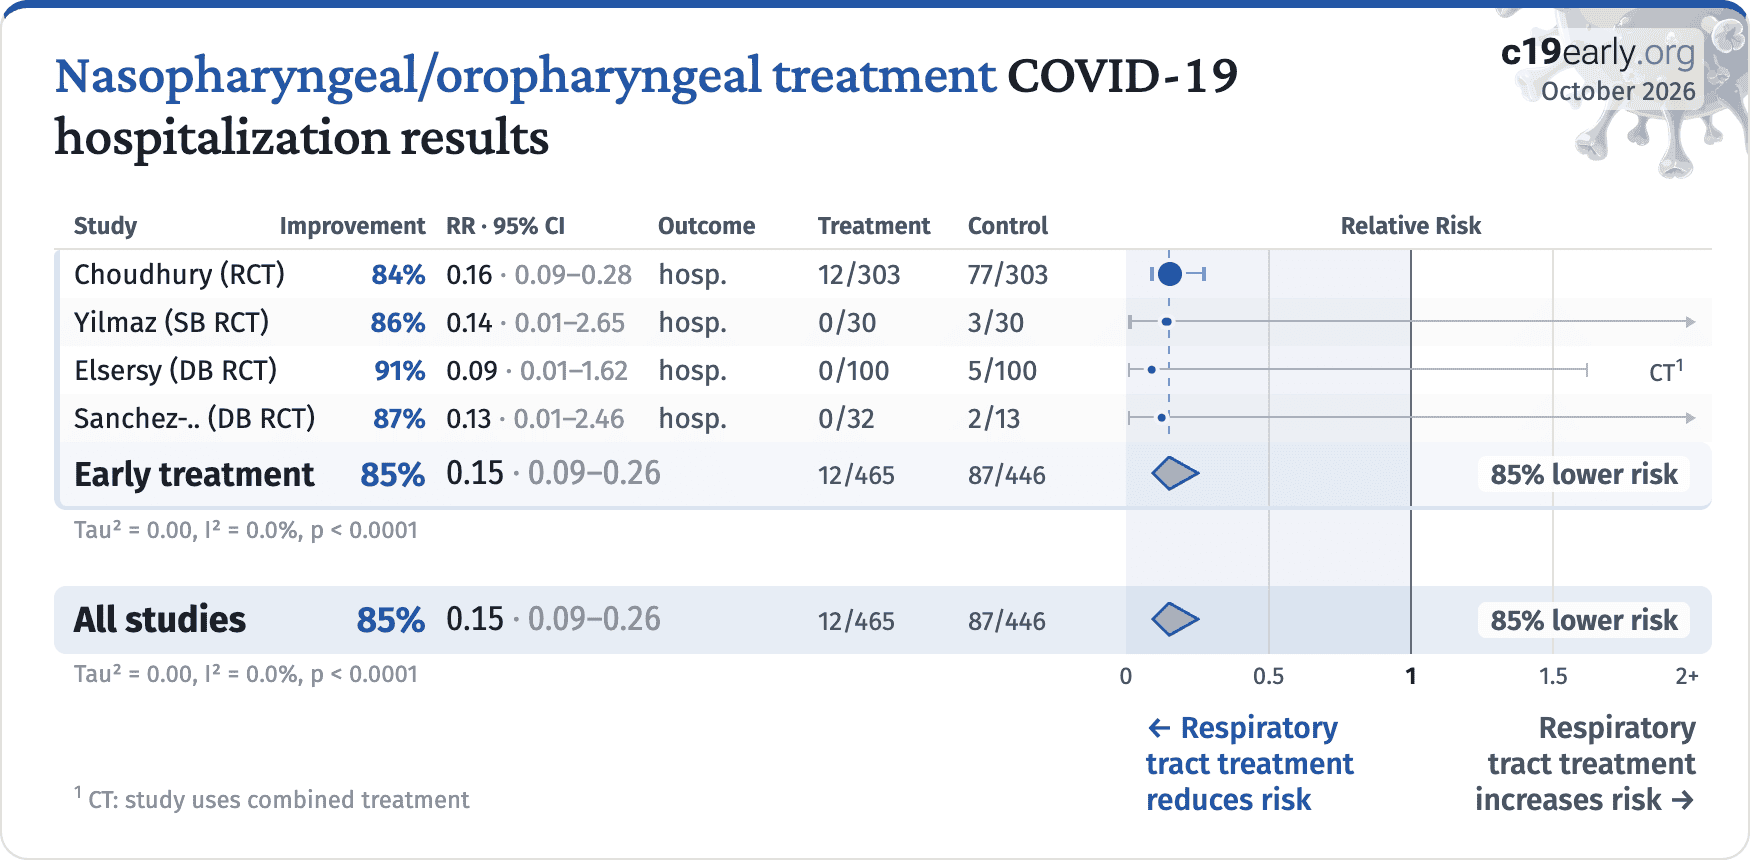
risk of hospitalization, 84.4% lower, RR 0.16, p < 0.001, treatment 12 of 303 (4.0%), control 77 of 303 (25.4%), NNT 4.7.
|
|
risk of no viral clearance, 96.2% lower, RR 0.04, p < 0.001, treatment 8 of 303 (2.6%), control 213 of 303 (70.3%), NNT 1.5, day 7.
|
|
de Gabory, 2/20/2024, Randomized Controlled Trial, France, peer-reviewed, 4 authors, study period July 2021 - March 2022, trial NCT04916639 (history) (SeaCare).
|
risk of progression, 74.9% lower, RR 0.25, p < 0.001, treatment 7 of 82 (8.5%), control 31 of 91 (34.1%), NNT 3.9, day 21.
|
|
risk of progression, 67.6% lower, RR 0.32, p = 0.003, treatment 7 of 82 (8.5%), control 24 of 91 (26.4%), NNT 5.6, day 14.
|
|
risk of progression, 35.3% lower, RR 0.65, p = 0.47, treatment 7 of 82 (8.5%), control 12 of 91 (13.2%), NNT 22, day 7.
|
|
recovery time, 24.2% lower, relative time 0.76, p = 0.02, treatment mean 5.0 (±4.1) n=82, control mean 6.6 (±4.8) n=91, time to resume daily activities.
|
|
recovery time, 17.0% lower, relative time 0.83, p < 0.001, treatment 82, control 91, all symptoms combined.
|
|
recovery time, 25.5% lower, relative time 0.74, p = 0.03, treatment mean 3.5 (±2.8) n=82, control mean 4.7 (±4.2) n=91, dyspnea.
|
|
recovery time, 29.5% lower, relative time 0.71, p < 0.001, treatment mean 6.7 (±5.2) n=82, control mean 9.5 (±5.7) n=91, loss of smell.
|
|
recovery time, 25.6% lower, relative time 0.74, p = 0.005, treatment mean 6.7 (±5.6) n=82, control mean 9.0 (±5.1) n=91, loss of taste.
|
|
recovery time, 13.8% lower, relative time 0.86, p = 0.22, treatment mean 5.6 (±5.0) n=82, control mean 6.5 (±4.6) n=91, post-nasal drip.
|
|
recovery time, 10.7% lower, relative time 0.89, p = 0.36, treatment mean 5.0 (±4.7) n=82, control mean 5.6 (±3.9) n=91, facial pain.
|
|
recovery time, 1.8% higher, relative time 1.02, p = 0.89, treatment mean 5.6 (±5.0) n=82, control mean 5.5 (±4.6) n=91, sore throat.
|
|
recovery time, 25.5% lower, relative time 0.75, p = 0.04, treatment mean 3.8 (±3.5) n=82, control mean 5.1 (±4.6) n=91, chest congestion.
|
|
recovery time, 3.3% lower, relative time 0.97, p = 0.78, treatment mean 5.8 (±5.0) n=82, control mean 6.0 (±4.5) n=91, headache.
|
|
recovery time, 14.0% lower, relative time 0.86, p = 0.20, treatment mean 4.9 (±3.8) n=82, control mean 5.7 (±4.4) n=91, loss of appetite.
|
|
risk of no viral clearance, 36.6% lower, RR 0.63, p = 0.54, treatment 4 of 82 (4.9%), control 7 of 91 (7.7%), NNT 36, day 21.
|
|
Elsersy, 4/19/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Egypt, peer-reviewed, 8 authors, study period March 2021 - July 2021, this trial uses multiple treatments in the treatment arm (combined with glycyrrhizic acid) - results of individual treatments may vary, trial PACTR202101875903773.
|
risk of hospitalization, 90.9% lower, RR 0.09, p = 0.06, treatment 0 of 100 (0.0%), control 5 of 100 (5.0%), NNT 20, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
recovery time, 14.6% lower, relative time 0.85, p = 0.008, treatment mean 7.6 (±2.0) n=100, control mean 8.9 (±2.0) n=100.
|
|
recovery time, 49.1% lower, relative time 0.51, p < 0.001, treatment mean 5.6 (±1.3) n=100, control mean 11.0 (±3.4) n=100, smell.
|
|
recovery time, 48.2% lower, relative time 0.52, p < 0.001, treatment mean 5.7 (±1.0) n=100, control mean 11.0 (±4.0) n=100, taste.
|
|
risk of no viral clearance, 67.7% lower, RR 0.32, p < 0.001, treatment 21 of 100 (21.0%), control 65 of 100 (65.0%), NNT 2.3, mid-recovery, day 7.
|
|
risk of no viral clearance, 90.0% lower, RR 0.10, p = 0.010, treatment 1 of 100 (1.0%), control 10 of 100 (10.0%), NNT 11, day 10.
|
|
risk of no viral clearance, 29.3% lower, RR 0.71, p < 0.001, treatment 70 of 100 (70.0%), control 99 of 100 (99.0%), NNT 3.4, day 4.
|
|
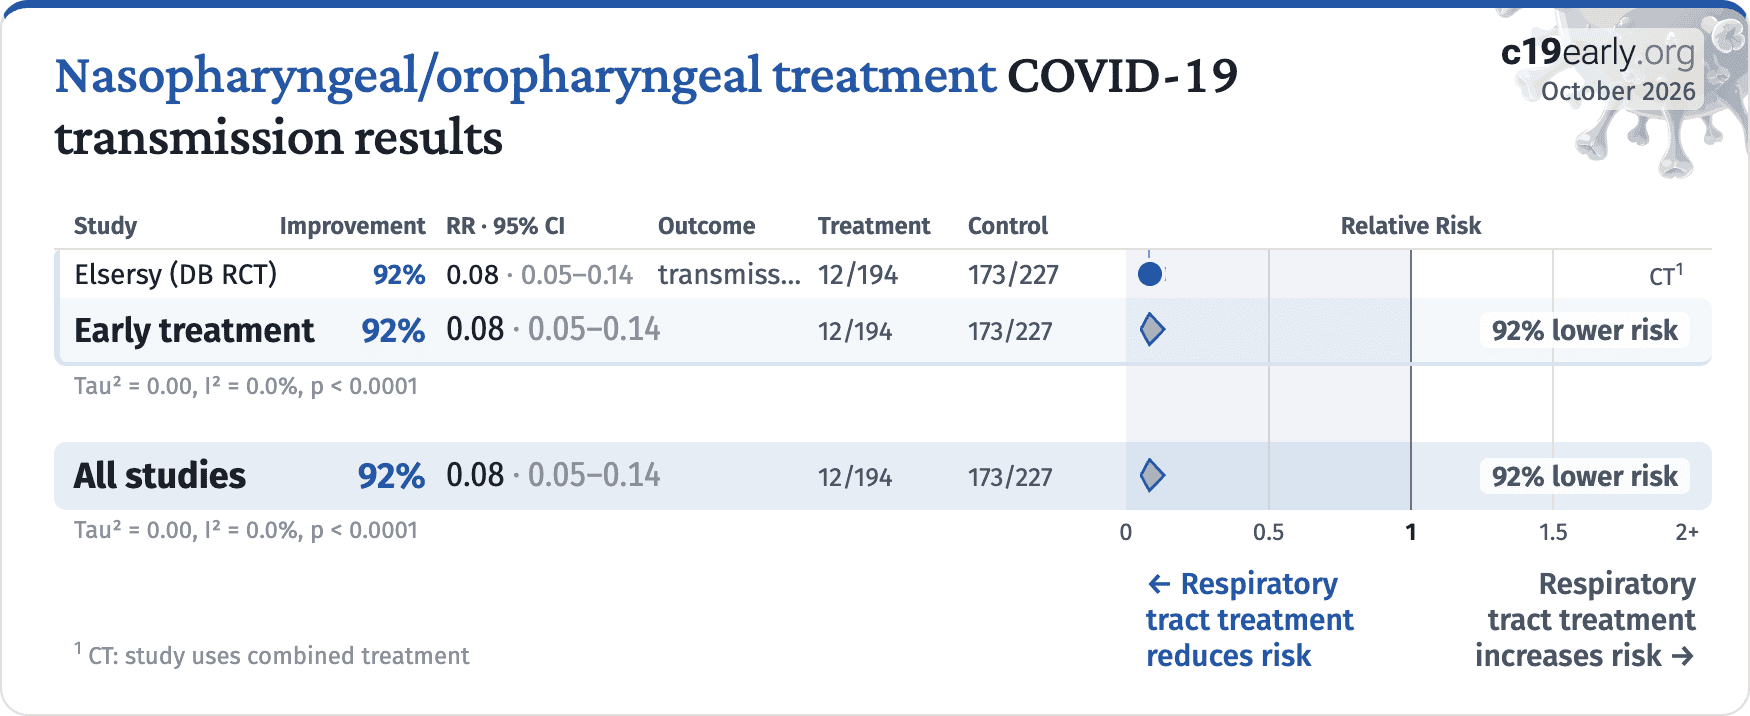
risk of transmission, 91.9% lower, RR 0.08, p < 0.001, treatment 12 of 194 (6.2%), control 173 of 227 (76.2%), NNT 1.4, symptomatic.
|
|
risk of transmission, 94.0% lower, RR 0.06, p < 0.001, treatment 8 of 194 (4.1%), control 157 of 227 (69.2%), NNT 1.5, PCR+.
|
|
Friedland, 3/30/2024, Double Blind Randomized Controlled Trial, placebo-controlled, South Africa, peer-reviewed, 2 authors, trial ACTRN12618001244291.
|
relative viral clearance rate, 59.5% better, RR 0.40, p = 0.03, treatment 10, control 13.
|
|
relative LSM log10TCID50 AUC2-4 reduction, 52.0% better, RR 0.48, p = 0.03, treatment 10, control 13.
|
|
Guenezan, 2/4/2021, Randomized Controlled Trial, France, peer-reviewed, 7 authors, study period 1 September, 2020 - 23 October, 2020, trial NCT04371965 (history).
|
relative improvement in viral titer reduction between baseline and day 1, 63.2% better, RR 0.37, p = 0.25, treatment 12, control 12.
|
|
Jayaraman, 3/1/2021, prospective, India, preprint, 12 authors.
|
risk of no viral clearance, 50.0% lower, RR 0.50, p = 0.18, treatment 3 of 6 (50.0%), control 6 of 6 (100.0%), NNT 2.0, antigen results.
|
|
Jing, 11/21/2023, Double Blind Randomized Controlled Trial, China, peer-reviewed, 7 authors, study period 5 May, 2022 - 16 June, 2022, this trial uses multiple treatments in the treatment arm (combined with budesonide and saline) - results of individual treatments may vary, trial ChiCTR2200059651.
|
olfactory or gustatory dysfunction, 79.2% lower, RR 0.21, p < 0.001, treatment 10 of 120 (8.3%), control 56 of 140 (40.0%), NNT 3.2, OGD.
|
|
VAS olfactory severe, 96.5% lower, RR 0.03, p < 0.001, treatment 0 of 120 (0.0%), control 15 of 140 (10.7%), NNT 9.3, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
VAS gustatory severe, 95.3% lower, RR 0.05, p = 0.001, treatment 0 of 120 (0.0%), control 11 of 140 (7.9%), NNT 13, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
TSS severe, 83.3% lower, RR 0.17, p = 0.07, treatment 1 of 120 (0.8%), control 7 of 140 (5.0%), NNT 24.
|
|
Karaaltin, 10/26/2022, Randomized Controlled Trial, Turkey, preprint, 16 authors, study period September 2021 - October 2021, average treatment delay 1.0 days.
|
viral load, 83.1% lower, relative load 0.17, p = 0.007, treatment 30, control 30, relative change in viral load, PVP-I vs. control, day 5.
|
|
viral load, 85.5% lower, relative load 0.14, p = 0.001, treatment 30, control 30, relative change in viral load, PVP-I + HANI vs. control, day 5.
|
|
viral load, 82.1% lower, relative load 0.18, p = 0.14, treatment 30, control 30, relative change in viral load, PVP-I vs. control, day 3.
|
|
viral load, 90.8% lower, relative load 0.09, p < 0.001, treatment 30, control 30, relative change in viral load, PVP-I + HANI vs. control, day 3.
|
|
Matsuyama, 11/28/2022, Randomized Controlled Trial, Japan, peer-reviewed, mean age 45.1, 4 authors, study period 30 November, 2020 - 17 March, 2021, trial jRCT1051200078.
|
viral infectivity, 69.0% lower, RR 0.31, p = 0.03, treatment 4 of 139 (2.9%), control 13 of 140 (9.3%), NNT 16, viral infectivity from culture, day 5.
|
|
risk of no viral clearance, 38.0% lower, HR 0.62, p = 0.01, treatment 139, control 140, inverted to make HR<1 favor treatment, day 5, primary outcome.
|
|
Mohamed, 9/9/2020, Randomized Controlled Trial, Malaysia, preprint, 16 authors, study period 22 June, 2020 - 29 June, 2020, trial NCT04410159 (history).
|
risk of no viral clearance, 85.7% lower, RR 0.14, p = 0.17, treatment 0 of 5 (0.0%), control 3 of 5 (60.0%), NNT 1.7, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), day 12.
|
|
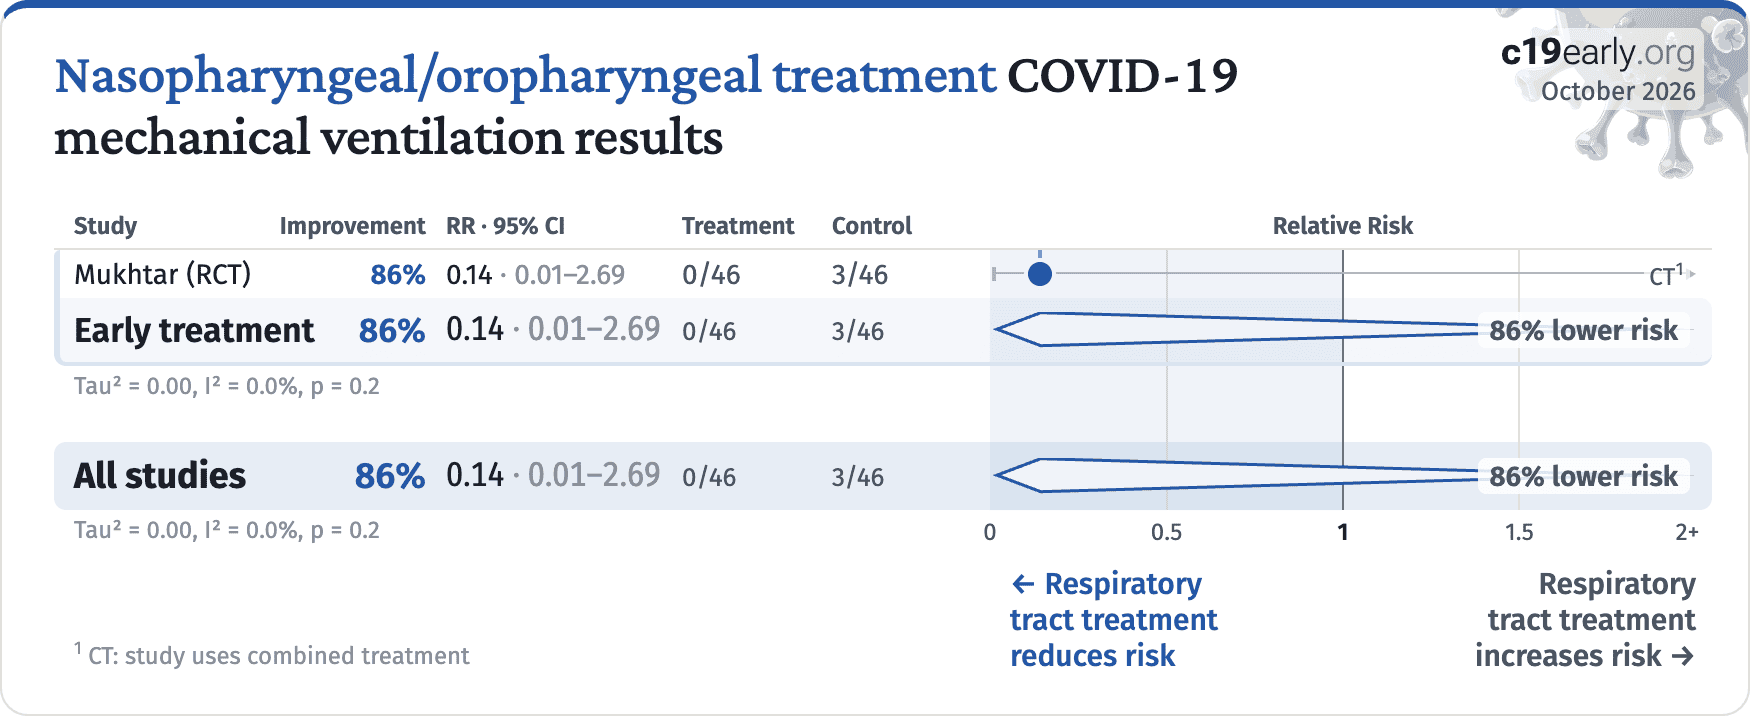
Mukhtar, 11/30/2020, Randomized Controlled Trial, Qatar, preprint, 16 authors, this trial uses multiple treatments in the treatment arm (combined with chlorhexidine) - results of individual treatments may vary, trial ISRCTN10197987.
|
risk of death, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 46 (0.0%), control 3 of 46 (6.5%), NNT 15, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), including third control death on day 54.
|
|
risk of mechanical ventilation, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 46 (0.0%), control 3 of 46 (6.5%), NNT 15, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
risk of no viral clearance, 18.1% lower, RR 0.82, p = 0.16, treatment 28 of 43 (65.1%), control 35 of 44 (79.5%), NNT 6.9, day 15.
|
|
risk of no viral clearance, 14.0% lower, RR 0.86, p = 0.01, treatment 37 of 43 (86.0%), control 44 of 44 (100.0%), NNT 7.2, day 5.
|
|
Pablo-Marcos, 10/25/2021, prospective, Spain, peer-reviewed, mean age 43.0, 6 authors, study period May 2020 - November 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
relative viral load, 12.5% better, RR 0.88, p = 0.67, treatment mean 2.1 (±2.5) n=17, control mean 2.4 (±2.4) n=40, 3rd PCR (mid-recovery).
|
|
relative viral load, 63.6% worse, RR 1.64, p = 0.16, treatment mean 1.8 (±2.5) n=31, control mean 1.1 (±1.6) n=40, 4th PCR (most patients recovered).
|
|
Pablo-Marcos (B), 10/25/2021, prospective, Spain, peer-reviewed, mean age 43.0, 6 authors, study period May 2020 - November 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
relative viral load, 29.2% better, RR 0.71, p = 0.40, treatment 31, control 40, 3rd PCR (mid-recovery).
|
|
relative viral load, 9.1% better, RR 0.91, p = 0.91, treatment 31, control 40, 4th PCR (most patients recovered).
|
|
Panatto, 5/12/2022, Randomized Controlled Trial, Italy, peer-reviewed, mean age 40.1, 10 authors, study period 20 May, 2021 - 9 November, 2021, trial NCT04909996 (history).
|
risk of progression, 36.7% lower, RR 0.63, p = 0.66, treatment 2 of 20 (10.0%), control 3 of 19 (15.8%), NNT 17, STX-5.
|
|
risk of progression, 85.4% lower, RR 0.15, p = 0.23, treatment 0 of 18 (0.0%), control 3 of 19 (15.8%), NNT 6.3, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), STX-3.
|
|
risk of progression, 66.7% lower, RR 0.33, p = 0.32, treatment 2 of 38 (5.3%), control 3 of 19 (15.8%), NNT 9.5, all patients.
|
|
risk of no viral clearance, 29.1% lower, RR 0.71, p = 0.01, treatment 34, control 15, inverted to make RR<1 favor treatment, Ct < 40, day 5.
|
|
risk of no viral clearance, 30.1% lower, RR 0.70, p = 0.002, treatment 34, control 15, inverted to make RR<1 favor treatment, Ct < 35, day 5.
|
|
Panatto (B), 5/12/2022, Randomized Controlled Trial, Italy, peer-reviewed, mean age 40.1, 10 authors, study period 20 May, 2021 - 9 November, 2021, trial NCT04909996 (history).
|
risk of progression, 36.7% lower, RR 0.63, p = 0.66, treatment 2 of 20 (10.0%), control 3 of 19 (15.8%), NNT 17, STX-5.
|
|
risk of progression, 85.4% lower, RR 0.15, p = 0.23, treatment 0 of 18 (0.0%), control 3 of 19 (15.8%), NNT 6.3, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), STX-3.
|
|
risk of progression, 66.7% lower, RR 0.33, p = 0.32, treatment 2 of 38 (5.3%), control 3 of 19 (15.8%), NNT 9.5, all patients.
|
|
risk of no viral clearance, 29.1% lower, RR 0.71, p = 0.01, treatment 34, control 15, inverted to make RR<1 favor treatment, Ct < 40, day 5.
|
|
risk of no viral clearance, 30.1% lower, RR 0.70, p = 0.002, treatment 34, control 15, inverted to make RR<1 favor treatment, Ct < 35, day 5.
|
|
Poleti, 12/8/2021, Double Blind Randomized Controlled Trial, Brazil, peer-reviewed, 10 authors, study period 6 November, 2020 - 19 November, 2020, trial RBR-8x8g36.
|
risk of no recovery, 29.1% lower, RR 0.71, p = 0.02, treatment 29 of 59 (49.2%), control 52 of 75 (69.3%), NNT 5.0, day 7.
|
|
risk of no recovery, 22.1% lower, RR 0.78, p = 0.02, treatment 38 of 59 (64.4%), control 62 of 75 (82.7%), NNT 5.5, day 3.
|
|
risk of no recovery, 45.5% lower, RR 0.54, p = 0.04, treatment 12 of 59 (20.3%), control 28 of 75 (37.3%), NNT 5.9, day 7, dyspnea.
|
|
risk of no recovery, 32.5% lower, RR 0.68, p = 0.11, treatment 17 of 59 (28.8%), control 32 of 75 (42.7%), NNT 7.2, day 3, dyspnea.
|
|
Ponphaiboon, 9/19/2025, Double Blind Randomized Controlled Trial, placebo-controlled, Thailand, preprint, 12 authors, study period 17 May, 2022 - 16 May, 2023, this trial uses multiple treatments in the treatment arm (combined with limonene and monolaurin) - results of individual treatments may vary, trial TCTR20240803002.
|
risk of no recovery, 36.0% lower, RR 0.64, p = 0.006, treatment 25 of 53 (47.2%), control 42 of 57 (73.7%), NNT 3.8, day 7, fever and headache.
|
|
risk of no recovery, 24.5% lower, RR 0.76, p < 0.001, treatment 43 of 59 (72.9%), control 55 of 57 (96.5%), NNT 4.2, day 7, sore throat.
|
|
risk of no recovery, 13.7% lower, RR 0.86, p = 0.02, treatment 50 of 59 (84.7%), control 56 of 57 (98.2%), NNT 7.4, day 7, cough and mucus.
|
|
risk of no recovery, 29.7% lower, RR 0.70, p < 0.001, treatment 40 of 59 (67.8%), control 55 of 57 (96.5%), NNT 3.5, day 7, runny nose and nasal congestion.
|
|
Sanchez-Gonzalez, 12/31/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, mean age 44.5, 5 authors.
|
risk of hospitalization, 87.4% lower, RR 0.13, p = 0.08, treatment 0 of 32 (0.0%), control 2 of 13 (15.4%), NNT 6.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Sanchez-Gonzalez (B), 12/31/2022, Double Blind Randomized Controlled Trial, placebo-controlled, USA, peer-reviewed, mean age 44.5, 5 authors.
|
risk of hospitalization, 87.4% lower, RR 0.13, p = 0.08, treatment 0 of 32 (0.0%), control 2 of 13 (15.4%), NNT 6.5, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Sulistyani, 3/15/2022, Single Blind Randomized Controlled Trial, Indonesia, peer-reviewed, 9 authors, study period July 2021 - September 2021.
|
relative improvement in Ct value, 6.3% better, RR 0.94, p = 0.74, treatment mean 12.9 (±5.96) n=15, control mean 12.09 (±7.38) n=15, 1% PVP-I vs. water, day 5.
|
|
relative improvement in Ct value, 11.3% better, RR 0.89, p = 0.54, treatment mean 13.63 (±6.28) n=15, control mean 12.09 (±7.38) n=15, 0.5% PVP-I vs. water, day 5.
|
|
Tandon, 6/29/2022, Double Blind Randomized Controlled Trial, placebo-controlled, India, peer-reviewed, 10 authors, study period 10 August, 2021 - 25 January, 2022, trial CTRI/2021/08.
|
risk of no improvement, 67.7% lower, RR 0.32, p = 0.08, treatment 3 of 64 (4.7%), control 10 of 69 (14.5%), NNT 10, mITT high risk, day 18.
|
|
risk of no improvement, 66.8% lower, RR 0.33, p = 0.04, treatment 4 of 64 (6.2%), control 13 of 69 (18.8%), NNT 7.9, mITT high risk, day 16.
|
|
risk of no improvement, 41.9% lower, RR 0.58, p = 0.06, treatment 14 of 64 (21.9%), control 26 of 69 (37.7%), NNT 6.3, mITT high risk, day 8.
|
|
risk of no improvement, 22.3% lower, RR 0.78, p = 0.63, treatment 8 of 105 (7.6%), control 10 of 102 (9.8%), NNT 46, day 18, modified intention-to-treat.
|
|
risk of no improvement, 17.8% lower, RR 0.82, p = 0.67, treatment 11 of 105 (10.5%), control 13 of 102 (12.7%), NNT 44, day 16, modified intention-to-treat.
|
|
risk of no improvement, 8.9% lower, RR 0.91, p = 0.76, treatment 30 of 105 (28.6%), control 32 of 102 (31.4%), NNT 36, day 8, modified intention-to-treat.
|
|
viral load, 19.8% lower, relative load 0.80, p < 0.001, treatment mean 2.62 (±0.14) n=64, control mean 2.1 (±0.14) n=69, mITT high risk, day 8.
|
|
viral load, 13.5% lower, relative load 0.86, p < 0.001, treatment mean 2.51 (±0.11) n=105, control mean 2.17 (±0.12) n=102, day 8, modified intention-to-treat.
|
|
time to viral-, 26.1% lower, relative time 0.74, p = 0.09, treatment 64, control 69, inverted to make RR<1 favor treatment, mITT high risk, Kaplan-Meier.
|
|
time to viral-, 6.5% lower, relative time 0.94, p = 0.66, treatment 105, control 102, inverted to make RR<1 favor treatment, Kaplan-Meier, modified intention-to-treat.
|
|
Valerio-Pascua (B), 10/18/2022, retrospective, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05520944 (history) (ACCROS-II).
|
recovery time, 54.3% lower, relative time 0.46, p < 0.001, treatment mean 4.97 (±3.32) n=330, control mean 10.88 (±6.64) n=330.
|
|
Valerio-Pascua (D), 10/18/2022, retrospective, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05520944 (history) (ACCROS-II).
|
recovery time, 54.3% lower, relative time 0.46, p < 0.001, treatment mean 4.97 (±3.32) n=330, control mean 10.88 (±6.64) n=330.
|
|
Valerio-Pascua, 10/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05449405 (history) (ACCROS-I).
|
risk of no recovery, 61.4% lower, RR 0.39, p < 0.001, treatment 61, control 40, all symptoms combined.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.15, treatment 3 of 61 (4.9%), control 6 of 40 (15.0%), NNT 9.9, day 7, anosmia.
|
|
risk of no recovery, 89.1% lower, RR 0.11, p = 0.01, treatment 1 of 61 (1.6%), control 6 of 40 (15.0%), NNT 7.5, day 7, ageusia.
|
|
risk of no recovery, 53.2% lower, RR 0.47, p = 0.05, treatment 10 of 61 (16.4%), control 14 of 40 (35.0%), NNT 5.4, day 7, cough.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.21, treatment 2 of 61 (3.3%), control 4 of 40 (10.0%), NNT 15, day 7, fatigue.
|
|
risk of no recovery, 59.0% lower, RR 0.41, p = 0.13, treatment 5 of 61 (8.2%), control 8 of 40 (20.0%), NNT 8.5, day 7, nasal congestion.
|
|
relative long COVID score, 73.5% better, RR 0.26, p < 0.001, treatment 55, control 46, relative average composite long COVID score.
|
|
Valerio-Pascua (E), 10/18/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Honduras, preprint, 16 authors, study period June 2021 - July 2022, trial NCT05449405 (history) (ACCROS-I).
|
risk of no recovery, 61.4% lower, RR 0.39, p < 0.001, treatment 61, control 40, all symptoms combined.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.15, treatment 3 of 61 (4.9%), control 6 of 40 (15.0%), NNT 9.9, day 7, anosmia.
|
|
risk of no recovery, 89.1% lower, RR 0.11, p = 0.01, treatment 1 of 61 (1.6%), control 6 of 40 (15.0%), NNT 7.5, day 7, ageusia.
|
|
risk of no recovery, 53.2% lower, RR 0.47, p = 0.05, treatment 10 of 61 (16.4%), control 14 of 40 (35.0%), NNT 5.4, day 7, cough.
|
|
risk of no recovery, 67.2% lower, RR 0.33, p = 0.21, treatment 2 of 61 (3.3%), control 4 of 40 (10.0%), NNT 15, day 7, fatigue.
|
|
risk of no recovery, 59.0% lower, RR 0.41, p = 0.13, treatment 5 of 61 (8.2%), control 8 of 40 (20.0%), NNT 8.5, day 7, nasal congestion.
|
|
relative long COVID score, 73.5% better, RR 0.26, p < 0.001, treatment 55, control 46, relative average composite long COVID score.
|
|
Winchester, 5/13/2021, Double Blind Randomized Controlled Trial, placebo-controlled, United Kingdom, peer-reviewed, 4 authors, study period 15 December, 2020 - 31 March, 2021.
|
risk of no improvement, 42.0% lower, RR 0.58, p = 0.008, treatment 8 of 15 (53.3%), control 23 of 25 (92.0%), NNT 2.6.
|
|
viral load, 51.3% lower, relative load 0.49, p = 0.001, treatment 40, control 40, AUC relative mean change.
|
|
Yilmaz, 11/19/2021, Single Blind Randomized Controlled Trial, Turkey, peer-reviewed, 8 authors, study period July 2020 - September 2020.
|
risk of hospitalization, 85.7% lower, RR 0.14, p = 0.24, treatment 0 of 30 (0.0%), control 3 of 30 (10.0%), NNT 10.0, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
relative viral load density, 62.0% better, RR 0.38, p = 0.87, treatment median 15.0 IQR 43.0 n=30, control median 39.51 IQR 1085.1 n=30, day 7.
|
|
relative viral load density, 42.9% better, RR 0.57, p = 0.95, treatment median 1747 IQR 5863.5 n=30, control median 3058 IQR 145568.9 n=30, day 3.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Almanza-Reyes, 8/19/2021, Randomized Controlled Trial, Mexico, peer-reviewed, mean age 34.0, 11 authors, study period 7 April, 2020 - 9 June, 2020.
|
risk of case, 93.8% lower, RR 0.06, p < 0.001, treatment 2 of 114 (1.8%), control 33 of 117 (28.2%), NNT 3.8.
|
|
risk of miscellaneous, 48.7% lower, RR 0.51, p = 0.003, treatment 21 of 114 (18.4%), control 42 of 117 (35.9%), NNT 5.7, RTI symptoms.
|
|
Amoah, 8/31/2022, retrospective, Ghana, peer-reviewed, 12 authors, study period May 2020 - December 2021.
|
risk of case, 93.0% lower, RR 0.07, p = 0.06, treatment 94, control 372, both periods combined.
|
|
risk of case, 92.6% lower, RR 0.07, p = 0.22, treatment 0 of 94 (0.0%), control 10 of 372 (2.7%), NNT 37, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), Jan - Mar 2021.
|
|
risk of case, 98.4% lower, RR 0.02, p = 0.60, treatment 0 of 8 (0.0%), control 62 of 458 (13.5%), NNT 7.4, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), May - Dec 2020.
|
|
Brito-Reia, 11/15/2021, prospective, Brazil, peer-reviewed, 7 authors, trial RBR-6c9xnw3.
|
risk of case, 54.0% lower, RR 0.46, p = 0.08, treatment 6 of 1,153 (0.5%), control 44 of 3,887 (1.1%), NNT 164.
|
|
Carvallo, 11/17/2020, prospective, Argentina, peer-reviewed, 4 authors, this trial uses multiple treatments in the treatment arm (combined with ivermectin) - results of individual treatments may vary, excluded:
combined treatment may significantly contribute to efficacy, concern about potential data issues.
|
risk of case, 99.9% lower, RR 0.001, p < 0.001, treatment 0 of 788 (0.0%), control 237 of 407 (58.2%), NNT 1.7, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Carvallo (B), 11/17/2020, prospective, Argentina, peer-reviewed, 4 authors, this trial uses multiple treatments in the treatment arm (combined with iota-carrageenan) - results of individual treatments may vary, see notes, excluded in exclusion analyses:
concern about potential data issues.
|
risk of case, 99.9% lower, RR 0.001, p < 0.001, treatment 0 of 788 (0.0%), control 237 of 407 (58.2%), NNT 1.7, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Carvallo (C), 10/19/2020, prospective, Argentina, preprint, 1 author, this trial uses multiple treatments in the treatment arm (combined with ivermectin) - results of individual treatments may vary, trial NCT04425850 (history), excluded:
combined treatment may significantly contribute to efficacy, concern about potential data issues.
|
risk of case, 96.3% lower, RR 0.04, p < 0.001, treatment 0 of 131 (0.0%), control 11 of 98 (11.2%), NNT 8.9, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Carvallo (D), 10/19/2020, prospective, Argentina, preprint, 1 author, this trial uses multiple treatments in the treatment arm (combined with iota-carrageenan) - results of individual treatments may vary, see notes, trial NCT04425850 (history), excluded in exclusion analyses:
concern about potential data issues.
|
risk of case, 96.3% lower, RR 0.04, p < 0.001, treatment 0 of 131 (0.0%), control 11 of 98 (11.2%), NNT 8.9, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm).
|
|
Chahla, 1/11/2021, Randomized Controlled Trial, Argentina, peer-reviewed, 11 authors, study period 15 October, 2020 - 31 December, 2020, this trial uses multiple treatments in the treatment arm (combined with iota-carrageenan) - results of individual treatments may vary, trial NCT04701710 (history).
|
risk of moderate/severe case, 95.2% lower, RR 0.05, p = 0.002, treatment 0 of 117 (0.0%), control 10 of 117 (8.5%), NNT 12, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), moderate/severe COVID-19.
|
|
risk of case, 84.0% lower, RR 0.16, p = 0.004, treatment 4 of 117 (3.4%), control 25 of 117 (21.4%), NNT 5.6, adjusted per study, odds ratio converted to relative risk, all cases, primary outcome.
|
|
Daneshfard, 7/16/2023, Randomized Controlled Trial, Iran, peer-reviewed, mean age 39.5 (treatment) 34.0 (control), 16 authors, study period 16 June, 2021 - 22 May, 2022, this trial uses multiple treatments in the treatment arm (combined with olea europaea oil) - results of individual treatments may vary, trial IRCT20210515051305N1.
|
risk of symptomatic case, 34.1% lower, RR 0.66, p = 0.006, treatment 37 of 89 (41.6%), control 53 of 84 (63.1%), NNT 4.6, any symptom.
|
|
risk of symptomatic case, 97.3% lower, RR 0.03, p < 0.001, treatment 1 of 89 (1.1%), control 35 of 84 (41.7%), NNT 2.5, fever.
|
|
risk of symptomatic case, 65.7% lower, RR 0.34, p = 0.06, treatment 4 of 89 (4.5%), control 11 of 84 (13.1%), NNT 12, chest pain.
|
|
risk of symptomatic case, 62.2% lower, RR 0.38, p = 0.10, treatment 4 of 89 (4.5%), control 10 of 84 (11.9%), NNT 13, loss of taste/smell.
|
|
risk of symptomatic case, 26.0% lower, RR 0.74, p = 0.16, treatment 29 of 89 (32.6%), control 37 of 84 (44.0%), NNT 8.7, muscle ache.
|
|
risk of symptomatic case, 6.2% higher, RR 1.06, p = 1.00, treatment 9 of 89 (10.1%), control 8 of 84 (9.5%), chills.
|
|
risk of symptomatic case, 79.0% lower, RR 0.21, p = 0.001, treatment 4 of 89 (4.5%), control 18 of 84 (21.4%), NNT 5.9, cough.
|
|
risk of symptomatic case, 76.4% lower, RR 0.24, p < 0.001, treatment 5 of 89 (5.6%), control 20 of 84 (23.8%), NNT 5.5, headache.
|
|
risk of symptomatic case, 98.1% lower, RR 0.02, p < 0.001, treatment 0 of 89 (0.0%), control 25 of 84 (29.8%), NNT 3.4, relative risk is not 0 because of continuity correction due to zero events (with reciprocal of the contrasting arm), vomiting.
|
|
Figueroa, 4/15/2021, Double Blind Randomized Controlled Trial, Argentina, peer-reviewed, 18 authors, study period 24 July, 2020 - 20 December, 2020, trial NCT04521322 (history) (CARR-COV-02).
|
risk of symptomatic case, 80.2% lower, RR 0.20, p = 0.03, treatment 2 of 196 (1.0%), control 10 of 198 (5.1%), NNT 25, odds ratio converted to relative risk.
|
|
Gutiérrez-García, 12/15/2021, Randomized Controlled Trial, Mexico, peer-reviewed, mean age 38.1, 6 authors, study period September 2020 - November 2020.
|
risk of symptomatic case, 90.6% lower, RR 0.09, p = 0.004, treatment 1 of 84 (1.2%), control 10 of 79 (12.7%), NNT 8.7.
|
|
Karami, 1/9/2024, Double Blind Randomized Controlled Trial, Iran, peer-reviewed, 4 authors, study period July 2022 - October 2022, trial IRCT20220328054364N1.
|
relative mean total symptoms, 61.0% better, RR 0.39, p = 0.04, treatment mean 1.8 (±3.67) n=36, control mean 4.62 (±7.37) n=40.
|
|
relative mean week 1 symptoms, 82.0% better, RR 0.18, p = 0.08, treatment mean 0.22 (±1.17) n=36, control mean 1.22 (±3.14) n=40.
|
|
relative mean week 2 symptoms, 56.0% better, RR 0.44, p = 0.13, treatment mean 0.66 (±2.05) n=36, control mean 1.5 (±2.63) n=40.
|
|
relative mean week 3 symptoms, 11.3% better, RR 0.89, p = 0.84, treatment mean 0.86 (±2.66) n=36, control mean 0.97 (±2.16) n=40.
|
|
relative mean week 4 symptoms, 94.6% better, RR 0.05, p = 0.048, treatment mean 0.05 (±0.23) n=36, control mean 0.92 (±2.58) n=40.
|
|
risk of case, 56.8% lower, RR 0.43, p = 0.03, treatment 7 of 36 (19.4%), control 18 of 40 (45.0%), NNT 3.9.
|
|
Karami (B), 1/9/2024, Double Blind Randomized Controlled Trial, Iran, peer-reviewed, 4 authors, study period July 2022 - October 2022, trial IRCT20220328054364N1.
|
relative mean total symptoms, 45.5% better, RR 0.55, p = 0.14, treatment mean 2.52 (±4.99) n=40, control mean 4.62 (±7.37) n=40.
|
|
relative mean week 1 symptoms, 42.6% better, RR 0.57, p = 0.39, treatment mean 0.7 (±1.84) n=36, control mean 1.22 (±3.14) n=40.
|
|
relative mean week 2 symptoms, 42.0% better, RR 0.58, p = 0.27, treatment mean 0.87 (±2.26) n=36, control mean 1.5 (±2.63) n=40.
|
|
relative mean week 3 symptoms, 79.4% better, RR 0.21, p = 0.045, treatment mean 0.2 (±0.72) n=36, control mean 0.97 (±2.16) n=40.
|
|
relative mean week 4 symptoms, 18.5% better, RR 0.82, p = 0.77, treatment mean 0.75 (±2.43) n=36, control mean 0.92 (±2.58) n=40.
|
|
risk of case, 38.9% lower, RR 0.61, p = 0.16, treatment 11 of 40 (27.5%), control 18 of 40 (45.0%), NNT 5.7.
|
|
Miller, 4/30/2022, retrospective, Thailand, peer-reviewed, 2 authors.
|
risk of case, 75.0% lower, RR 0.25, p < 0.001, treatment 13 of 203 (6.4%), control 108 of 422 (25.6%), NNT 5.2.
|
|
Reznikov, 1/31/2021, retrospective, USA, peer-reviewed, 9 authors.
|
risk of case, 45.5% lower, RR 0.55, p = 0.03, adjusted per study, age groups combined.
|
|
risk of case, 58.8% lower, OR 0.41, p < 0.001, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 61+, multivariable, RR approximated with OR.
|
|
risk of case, 28.6% lower, OR 0.71, p = 0.17, adjusted per study, inverted to make OR<1 favor treatment, azelastine, 31-60, multivariable, RR approximated with OR.
|
|
Seet, 4/14/2021, Cluster Randomized Controlled Trial, Singapore, peer-reviewed, 15 authors, study period 13 May, 2020 - 31 August, 2020, this trial compares with another treatment - results may be better when compared to placebo, trial NCT04446104 (history).
|
risk of symptomatic case, 44.7% lower, RR 0.55, p = 0.002, treatment 42 of 735 (5.7%), control 64 of 619 (10.3%), NNT 22.
|
|
risk of case, 31.1% lower, RR 0.69, p = 0.01, treatment 338 of 735 (46.0%), control 433 of 619 (70.0%), NNT 4.2, adjusted per study, odds ratio converted to relative risk, model 6.
|
|
Shmuel, 4/30/2021, prospective, Israel, peer-reviewed, 4 authors, study period 18 September, 2020 - 2 October, 2020.
|
risk of case, 75.9% lower, RR 0.24, p = 0.04, treatment 2 of 83 (2.4%), control 16 of 160 (10.0%), NNT 13.
|
|
Si, 12/31/2023, prospective, China, peer-reviewed, median age 34.0, 22 authors, study period 31 October, 2022 - 30 November, 2022, trial NCT05664919 (history).
|
risk of case, 77.7% lower, RR 0.22, p < 0.001, relative cases per person-day.
|
|
Song, 5/25/2023, Single Blind Randomized Controlled Trial, placebo-controlled, China, peer-reviewed, median age 46.0, 12 authors, study period 26 November, 2022 - 9 December, 2022, trial NCT05667714 (history).
|
risk of symptomatic case, 80.8% lower, RR 0.19, p < 0.001, treatment 824, control 299.
|
|
risk of case, 61.8% lower, RR 0.38, p < 0.001, treatment 824, control 299.
|
|
Wang (B), 3/20/2023, prospective, China, preprint, 15 authors, study period 9 November, 2022 - 24 November, 2022, trial NCT05667714 (history).
|
risk of case, 33.7% lower, RR 0.66, p < 0.001, treatment 44 of 70 (62.9%), control 343 of 362 (94.8%), NNT 3.1.
|