Authority review was extremely slow
and overlooked most research
Official treatment recommendations were often made based on a small fraction of
the evidence, with substantial bias in the selection of studies.
Just as 78% of experts polled regarding the origin of COVID-19 were not familiar with the
DEFUSE protocol4, experts on COVID-19 treatments were not familiar with
much of the key evidence.
In some cases, recommendations were made without reviewing any clinical evidence,
for example the US FDA recommended against ivermectin in an article that stated
"The FDA has not reviewed data to support use of ivermectin in COVID-19"5.
In cases where the people involved in recommendations are known, they were
often busy professionals that could not realistically have time to
carefully review all evidence6.
Analysis of NIH COVID-19 treatment guidelines. NIH added a second reference list with 21 extra ivermectin studies, but no summary, comments, or evidence that they were reviewed. The studies NIH selected are not higher quality—many of the lowest quality and most flawed studies are included.
Table 1. The NIH did not review most evidence for
low-cost treatments. The studies they did review include very low-quality studies.
With 500+ therapeutic targets and 12,000+ proposed
treatments, what is the probability that only 3 high-profit drugs from companies
with strong US lobbying are beneficial?
NIH reviews
NIH treatment reviews were done by a panel of 40+ external experts with
extensive conflicts of interest towards high-profit treatments6,7.
Out of 12,250 proposed treatments8,
they found only three high-profit drugs from top lobbying companies to be beneficial for
early treatment(a).
Most others received either "insufficient evidence" or no review at all,
despite extensive unreviewed evidence.
Across all low-cost treatments (within the 227
we cover), the NIH only referenced 2% of the
studies.
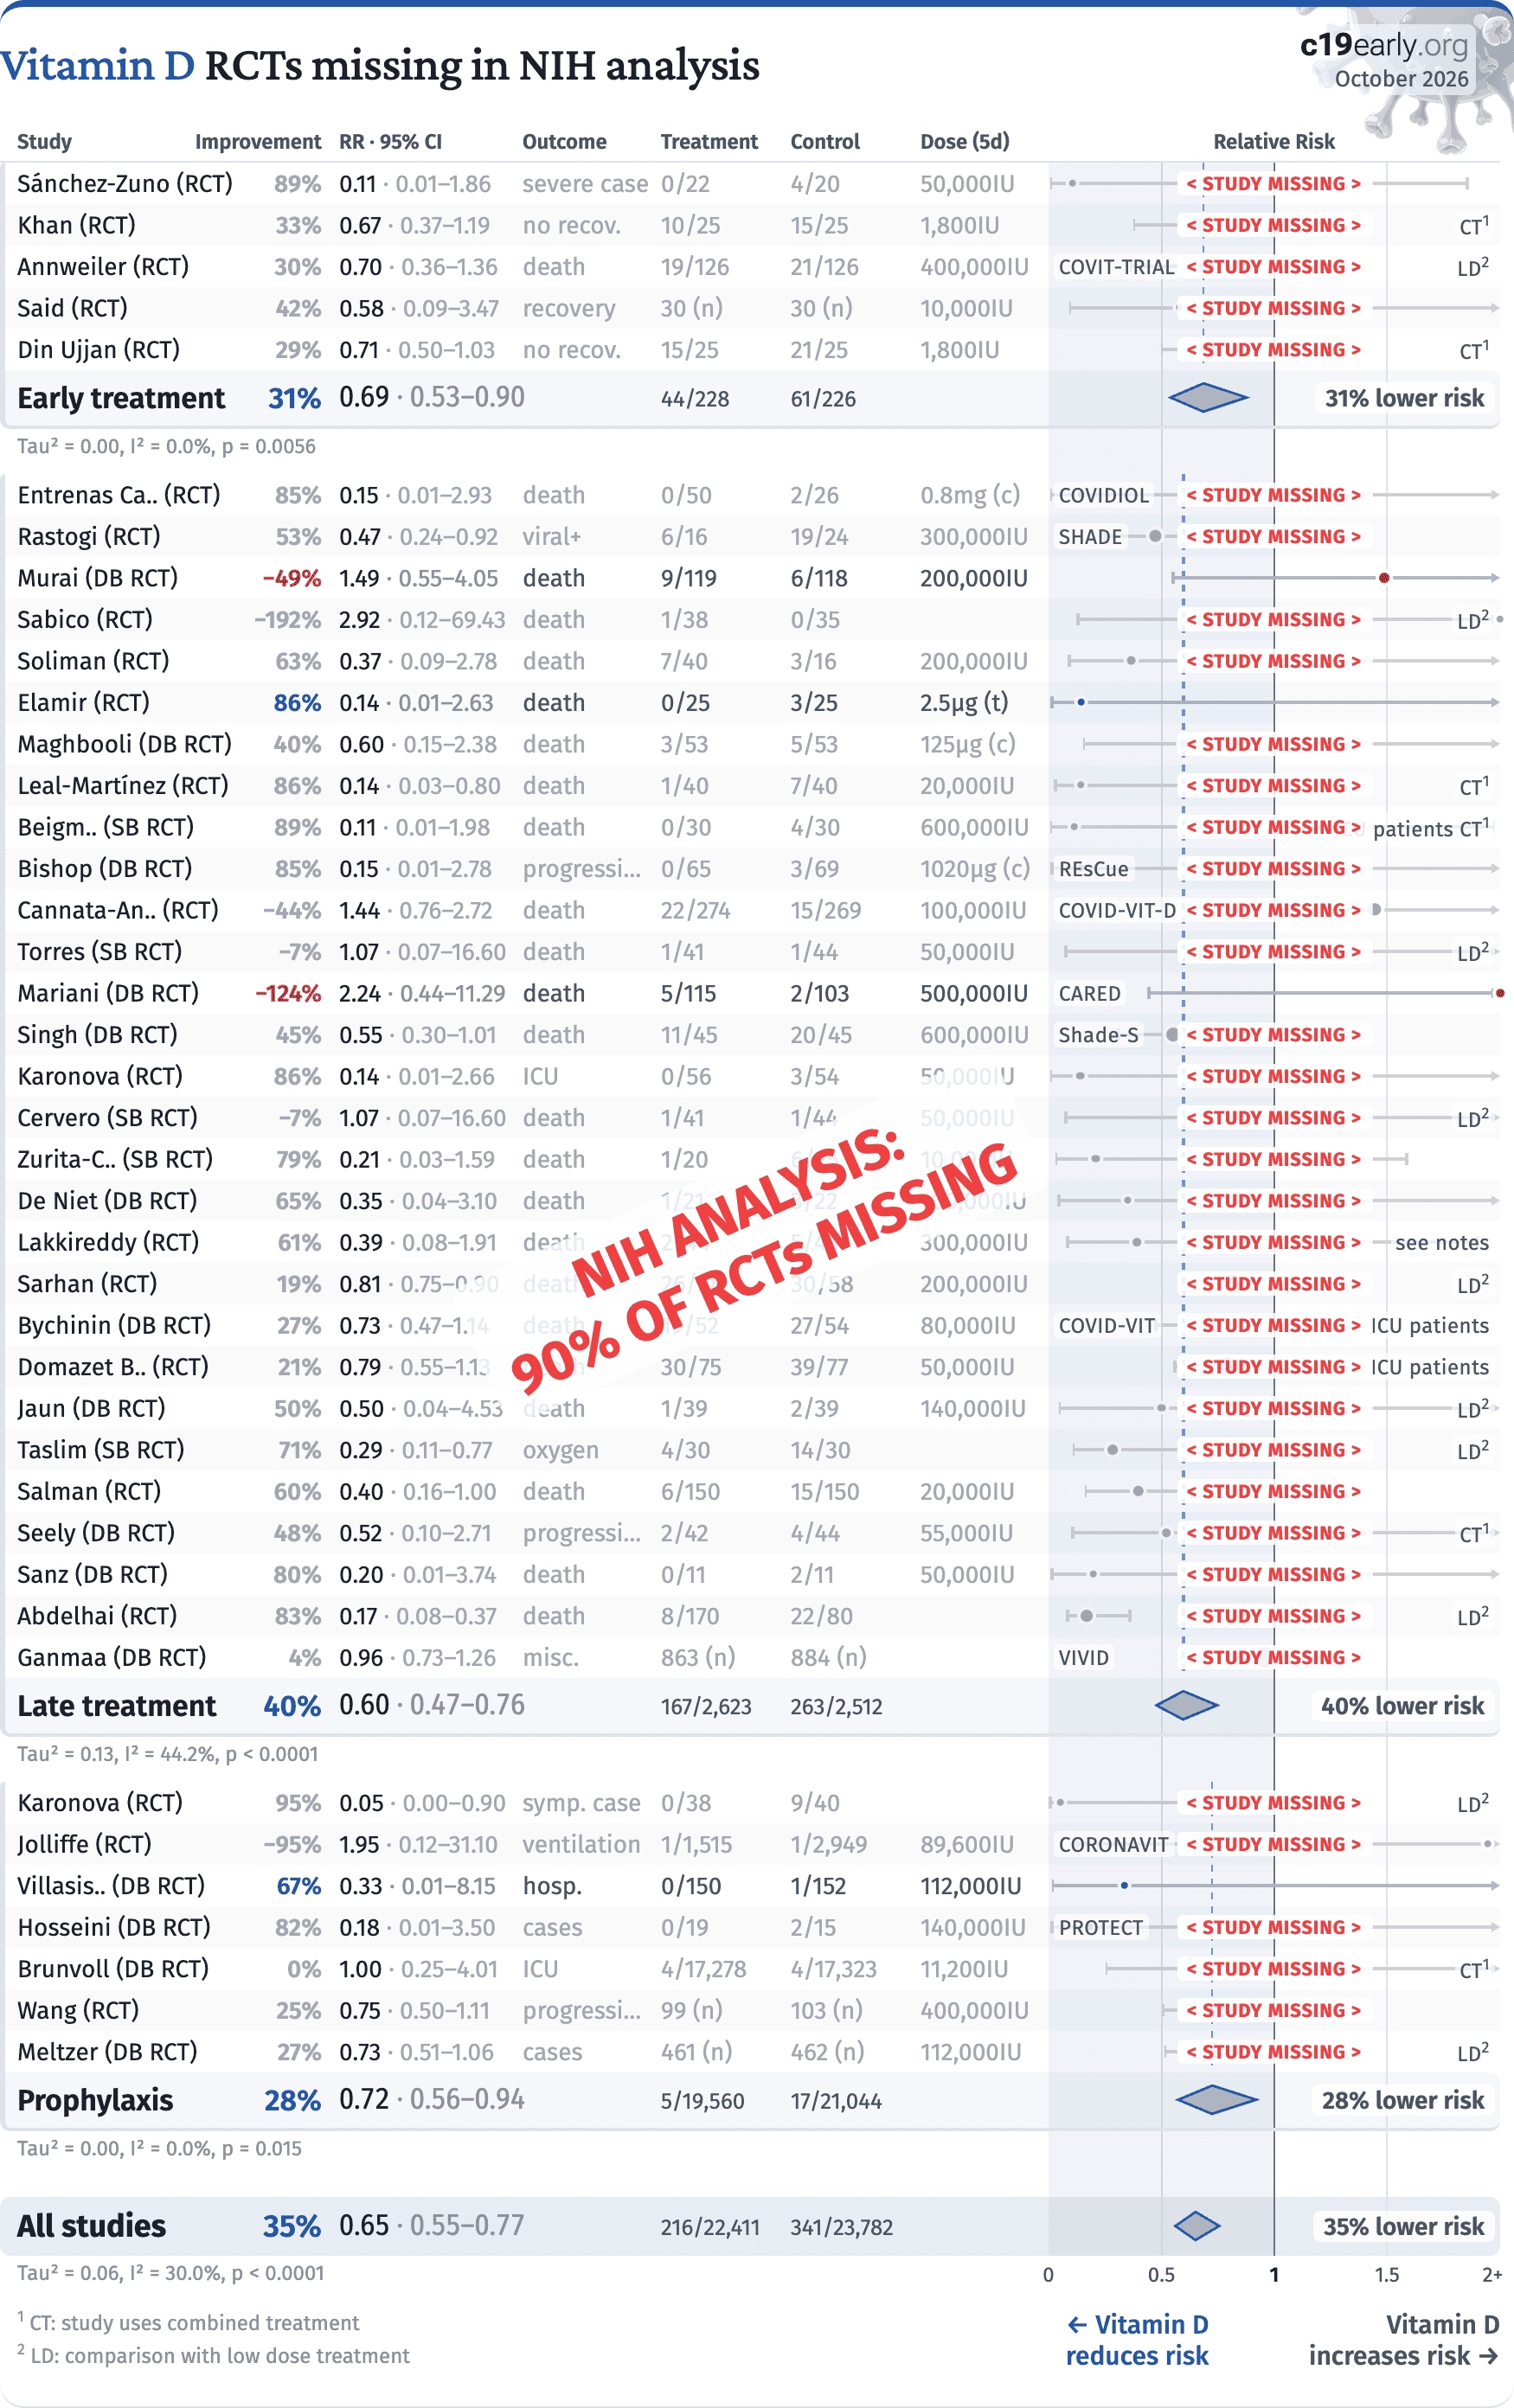
For vitamin D, the NIH claims "insufficient evidence ... to recommend either for or against"9.
No authors are listed, they provide only a brief narrative review, and they reference only 5 of the
138 controlled studies
(41 RCTs). The state is
similar or worse for other treatments (Table 1). The NIH provides no
quantitative analysis for any of the treatments listed.
Considering RCTs for vitamin D, the NIH references only
410-13 of 41 (Figure 114). The NIH selection does not have above average relevance or quality, for example
including two very late treatment studies using bolus doses of
cholecalciferol11,12—a trifecta of poor design and low relevance compared to recommended use:
early treatment is better, continuous dosing is more effective than bolus doses, and calcifediol,
calcitriol, or analogs avoid long delays in conversion.
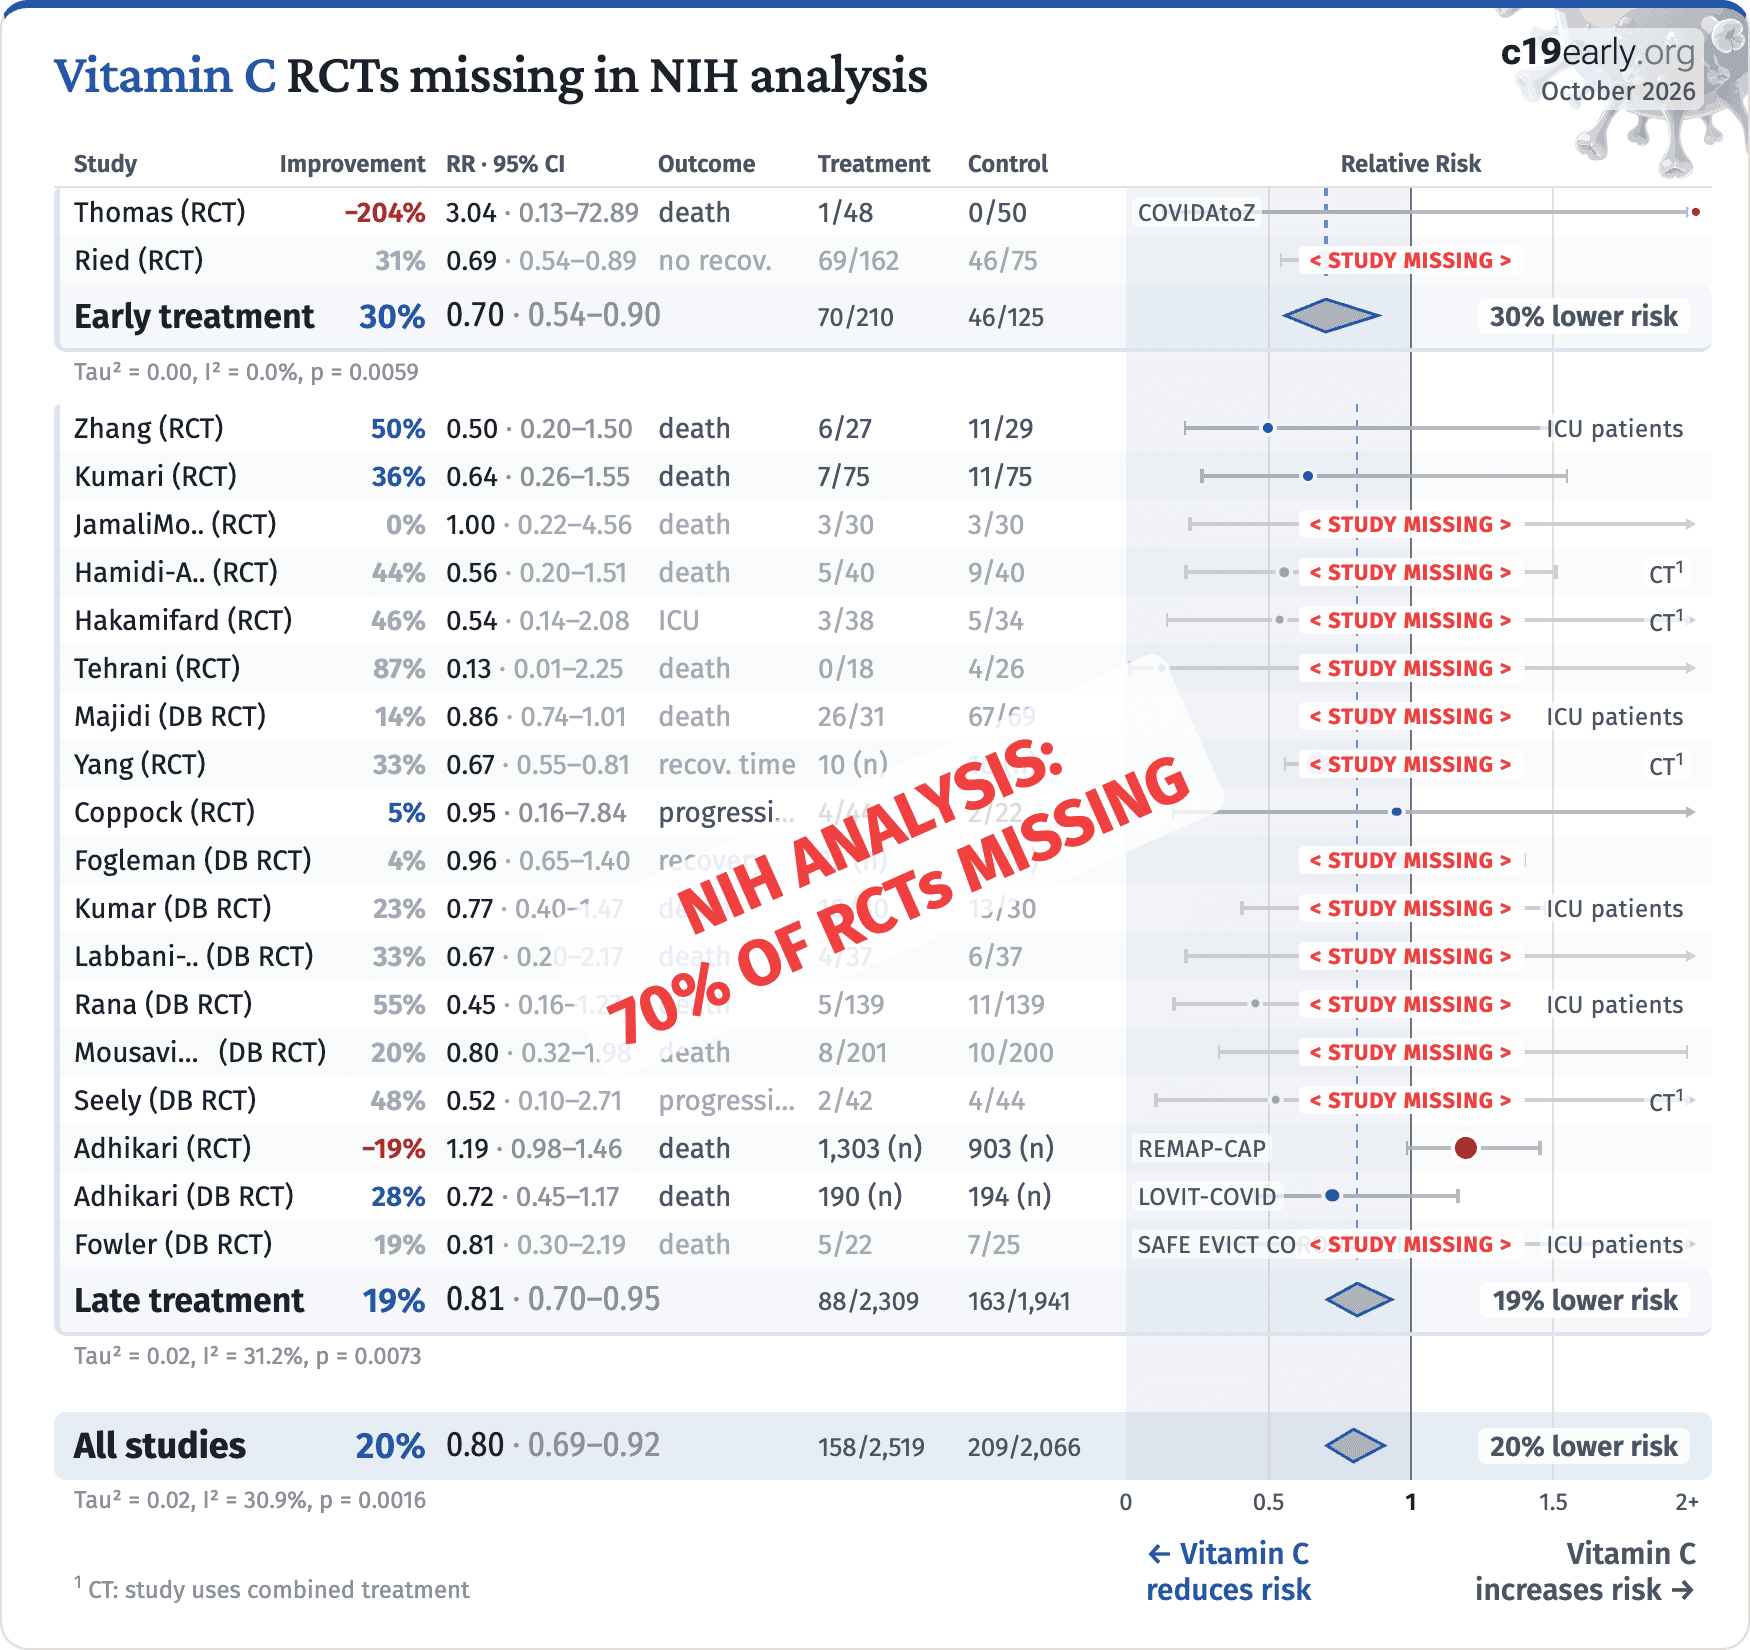
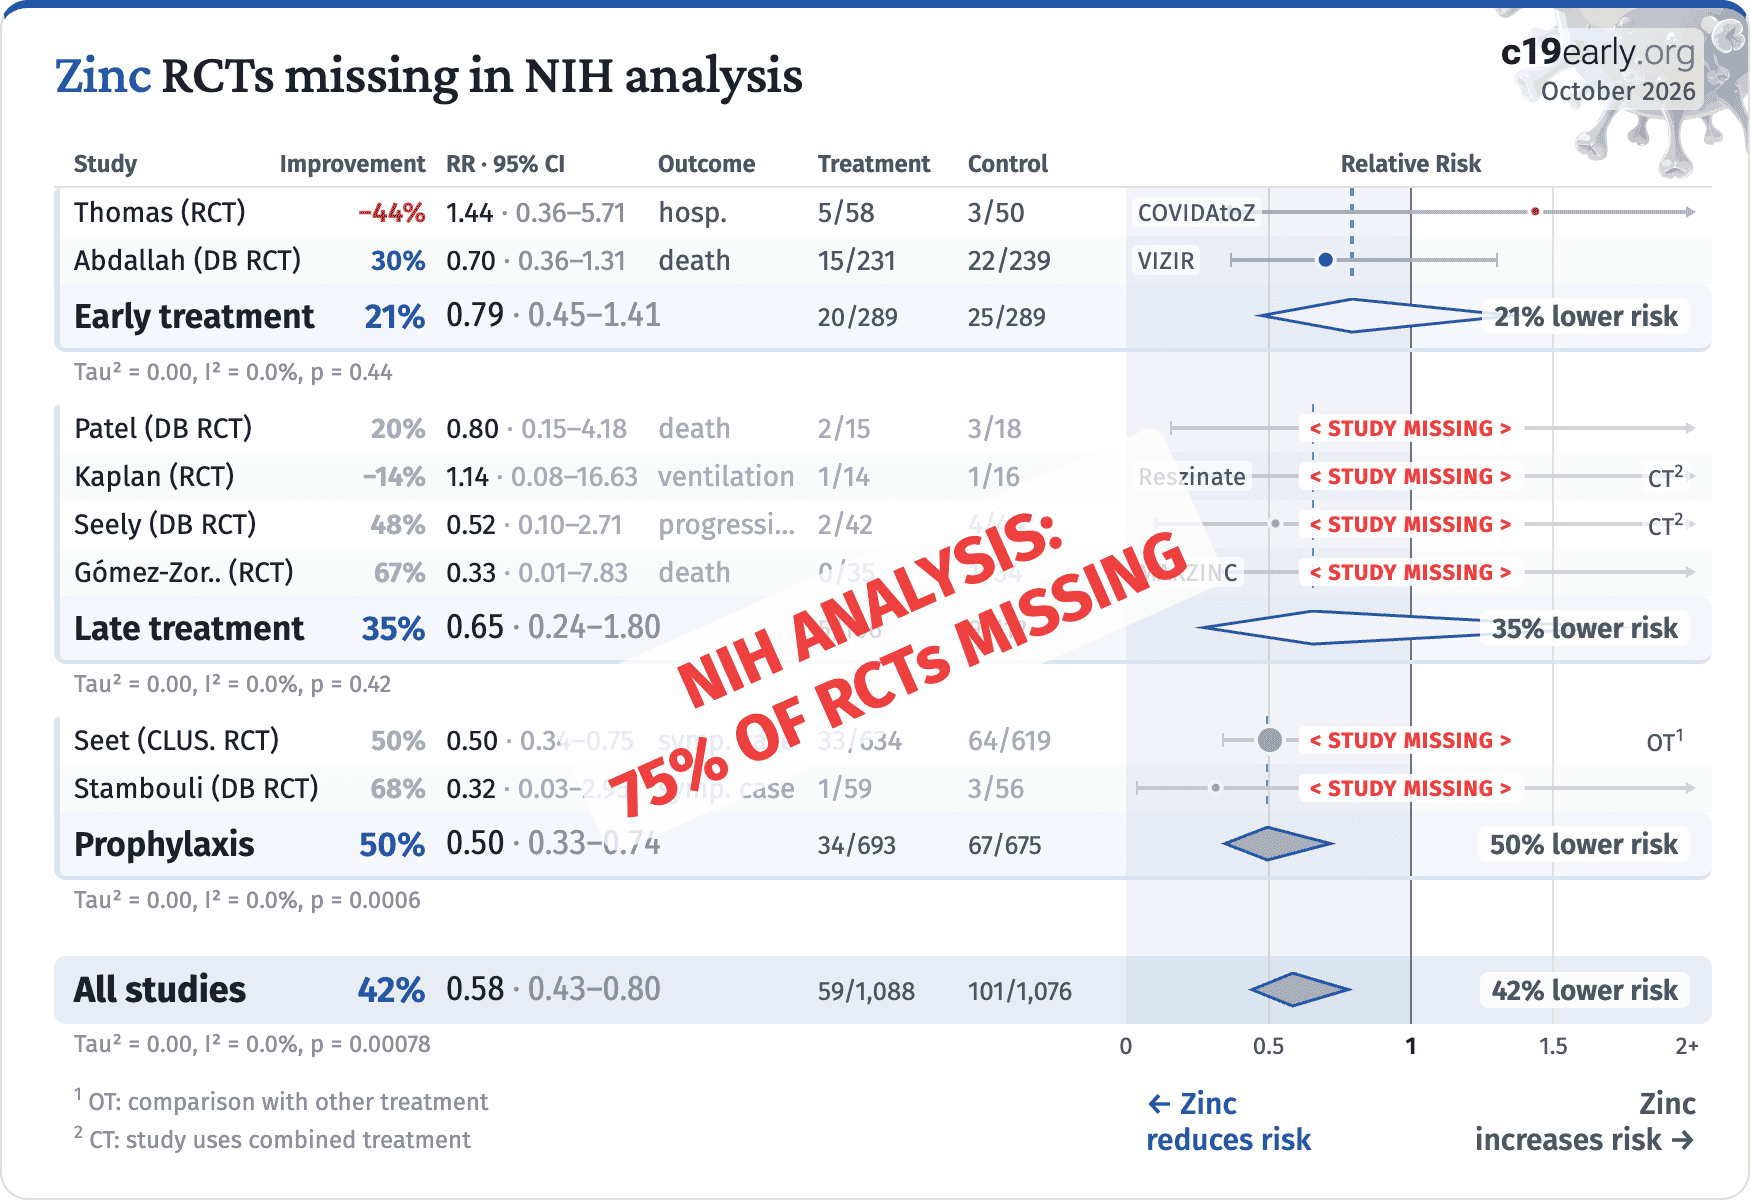
They include none of the early treatment RCTs. We provide similar analysis for vitamin
C15 and
zinc16.
Some NIH treatment guideline panel members have been revealed by FOIA
requests17-19. Many members have major conflicts of interest as summarized in the following table.
Conflicts of interest - NIH COVID-19 treatment guidelines
Gileadconsultant; institution received research funding. “Aadimora AA has received consulting fees from Viiv, and Gilead and her institution has received funding from Gilead for her research.”3
Gileadgrants. “Dr. Gandhi reports grants and personal fees from Gilead, personal fees from Merck, grants and personal fees from Theratechnologies, grants from ViiV, grants from Janssen.”7
Merckgrants; principal investigator of ACTG A5391, funded in part by Merck. “Roy M. Gulick, MD, MPH, has disclosed that he has received grants for clinical research from Abbott, Boehringer Ingelheim, Merck, Pfizer, Schering, and Tibotec, and has received grants for educational activities from Gilead and Monogram. Dr. Gulick has also disclosed that he has served as an ad-hoc advisor or consultant to Abbott, Boehringer Ingelheim, Bristol-Myers Squibb, Gilead, GlaxoSmithKline, Pfizer, Schering, and Tibotec.”10
Pfizergrants and ad-hoc advisor or consultant10(deleted from current version11)
Gileadgrants and ad-hoc advisor or consultant10(deleted from current version11)
GlaxoSmithKlinead-hoc advisor or consultant10(deleted from current version11)
Waiting for RCTs costs lives
While the NIH examined few of the RCTs, they dismissed almost all observational studies.
RCTs can provide significant advantages, however they show no benefit for COVID-19 and they introduce significantly delay.
For the 227 treatments analyzed, there is no difference in results
between RCTs and observational studies, RR 0.97 [0.91‑1.03]20 (Figure 4).
Observational studies do not systematically over- or underestimate
efficacy, as found in previous research21,22, and they
provided confirmation of efficacy 8+ months faster. RCTs aim to equalize study groups, but add
their own biases. For acute diseases with strong benefits for earlier treatment,
the typical increased treatment delay adds a major confounding factor.
Both RCTs and observational studies span the bias spectrum, from minimal to extreme.
Studies must be evaluated individually.
While observational studies require greater expertise to analyze, the advantages in
practicality, cost, time, and ethics are substantial.
← RCTs show higher efficacyRCTs show → lower efficacy
Figure 4. For COVID-19 there is no significant difference between the results of observational studies and RCTs20.
Waiting for specific outcomes costs
lives While patented treatments may be approved with a single
non-clinical
result23, authorities
often dismiss results for low-cost treatments where studies report different
outcomes.
To avoid delay and unnecessary mortality, we must use all available evidence.
Logically, minimizing viral replication will minimize serious outcomes. Singh
et al.24 confirm, showing improved viral clearance
significantly associated with lower hospitalization/death.
We confirm this across all 227 treatments—improved viral
clearance is strongly associated with lower serious outcomes, p = 0.00000000015 (see the appendix for
details).
Authorities may not pool any outcomes, e.g., separating studies reporting mortality
and studies reporting ICU admission, however data shows that—for COVID-19—it
is valid to combine outcomes from viral clearance to mortality.
85% of treatments showing significant efficacy/harm with pooled
effects have been confirmed without pooling, with a mean delay of
4.6 months.
Novel treatments are high risk,
existing treatments have a critical safety advantage Existing treatments
have a strong advantage with known pharmacokinetics and safety profiles. New
agents are more risky. Long-term risks cannot be known, and
known risks may not be acknowledged for some time. For example, molnupiravir's
potential risks include the creation of dangerous
variants25-29,
mutagenicity, carcinogenicity, teratogenicity, and
embryotoxicity30-44.
While the risk always exceeded the benefits within the context of
all treatments, and confirmation of harm continues to accumulate, the
treatment is still used in 2026 in some locations.
Novel treatments saw limited use during the pandemic45,46,
partly due to prescription requirements, limited availability, high cost, and,
for certain treatments, administration requirements and drug interactions.
Low-cost existing treatments
Can reduce risk
Known safety profile
More widely available
Available immediately
Can be distributed in advance for immediate treatment
High-profit novel treatments
Can reduce risk
Inherently risky—long-term and rare side effects unknown
We have received no funding or
compensation in any form, and do not accept donations. This is entirely volunteer work.
Conflicts of interest.
We have no conflicts of interest.
We have no affiliation with any pharmaceutical companies, supplement companies, governments, political parties, or advocacy organizations.
AI.
We use AI models (Gemini, Grok, Claude, and
ChatGPT) tasked with functioning as additional peer-reviewers to check for errors, suggest
improvements, and review spelling and grammar. Any corrections are manually verified. Our preference for em dashes is independent of AI.
Updates.
Our COVID-19 meta-analyses involve the extraction of over 229,000
datapoints from thousands of papers for 227 treatments. We thank the
thousands of scientists, physicians, and other contributors that have provided updates,
suggestions, feedback, and corrections. These are all welcome and can be submitted
below.
Dedication.
This work is dedicated to top
evidence-based physicians that worked tirelessly to analyze evidence and greatly reduce
mortality and morbidity during the pandemic. In alphabetical order:
Dr. Thomas J. Borody, Dr. Mary Talley Bowden, Dr. Flavio Cadegiani, Dr. Shankara Chetty,
Dr. Ryan Cole, Dr. George Fareed, Dr. Sabine Hazan, Dr. Pierre Kory, Dr. Tess Lawrie, Dr.
Robert Malone, Dr. Paul Marik, Dr. Peter McCullough, Dr. Didier Raoult, Dr. Harvey Risch,
Dr. Jackie Stone, Dr. Brian Tyson, Dr. Joseph Varon, and Dr. Vladimir Zelenko.
Public domain.
This is a public domain work
distributed in accordance with the Creative Commons CC0 1.0 Universal license, which
dedicates the work to the public domain by waiving all rights worldwide under copyright law.
You can distribute, remix, adapt, and build upon this work in any medium or format,
including for commercial purposes, without asking permission. Referenced material and
third-party images retain any original copyrights or restrictions.
See: https://creativecommons.org/publicdomain/zero/1.0/.
Monoclonal antibodies were also included in earlier versions. Other treatments such as dexamethasone, tocilizumab, and baricitinib were recommended for late stage hospitalized patients.