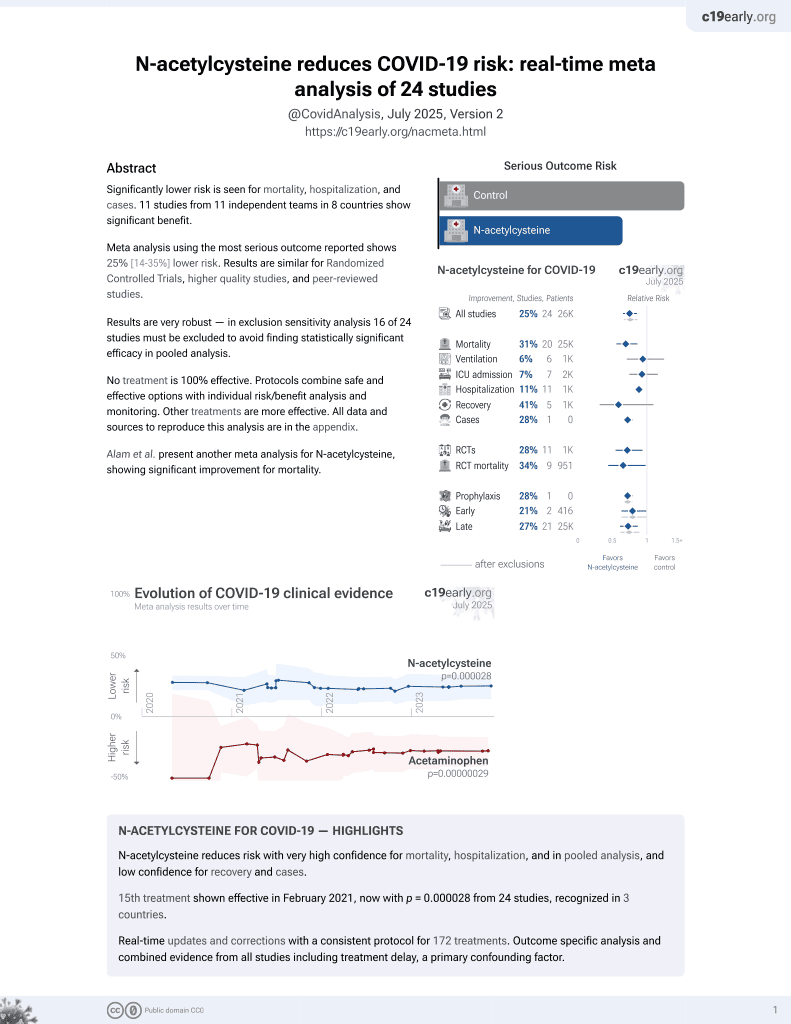
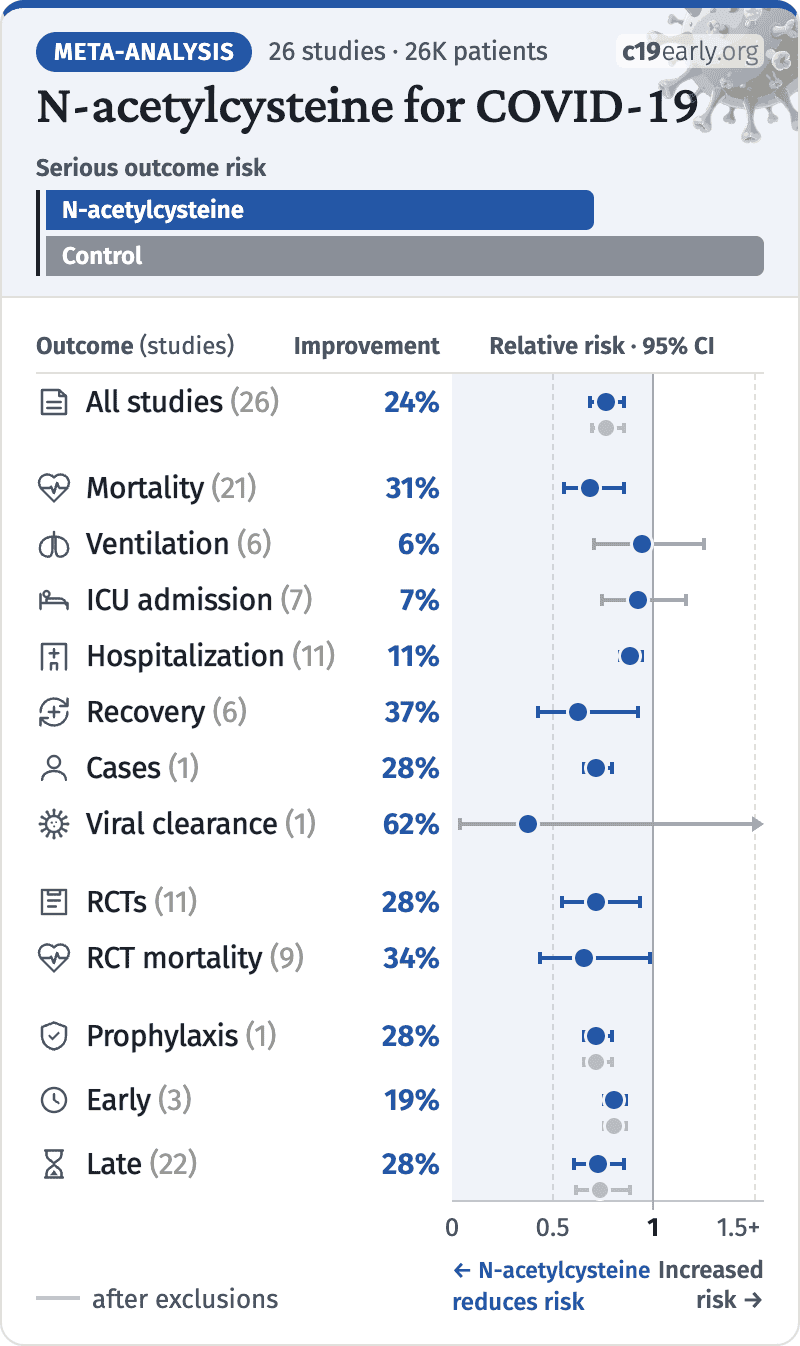
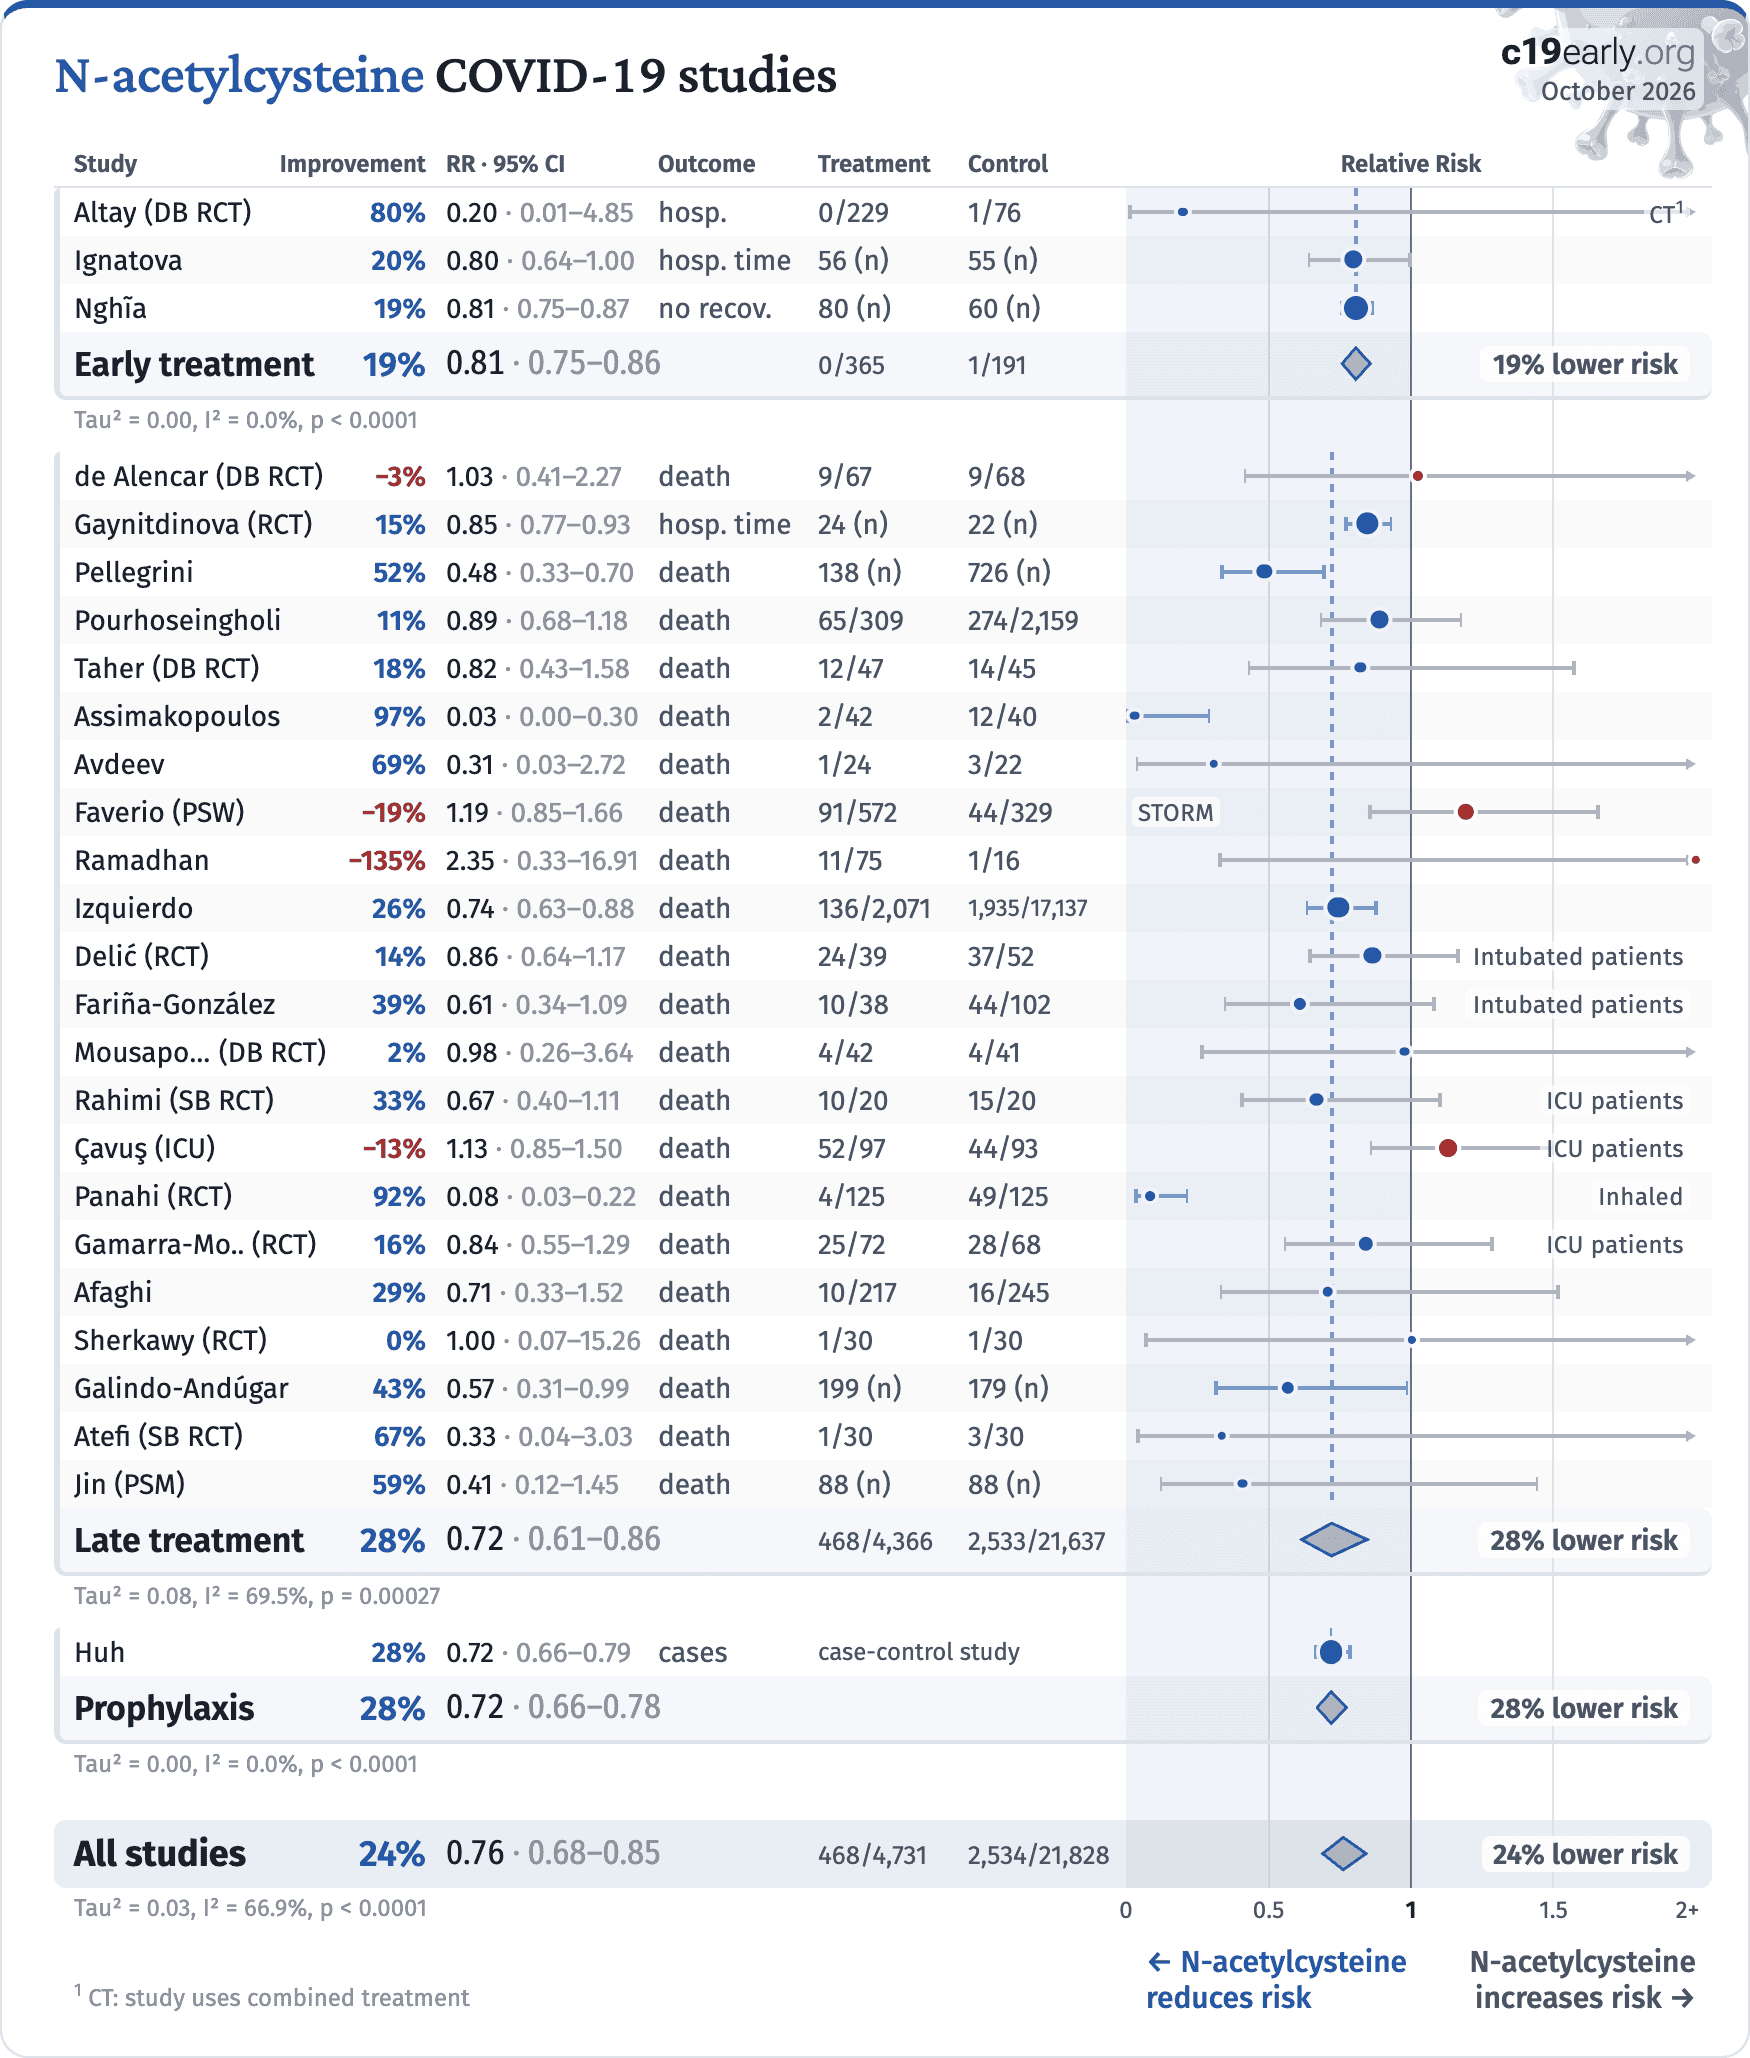
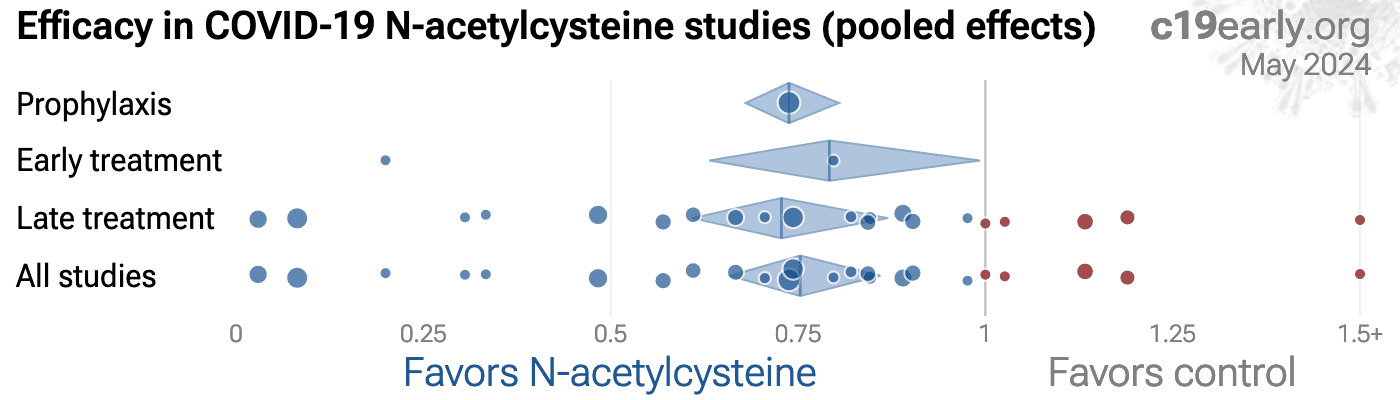
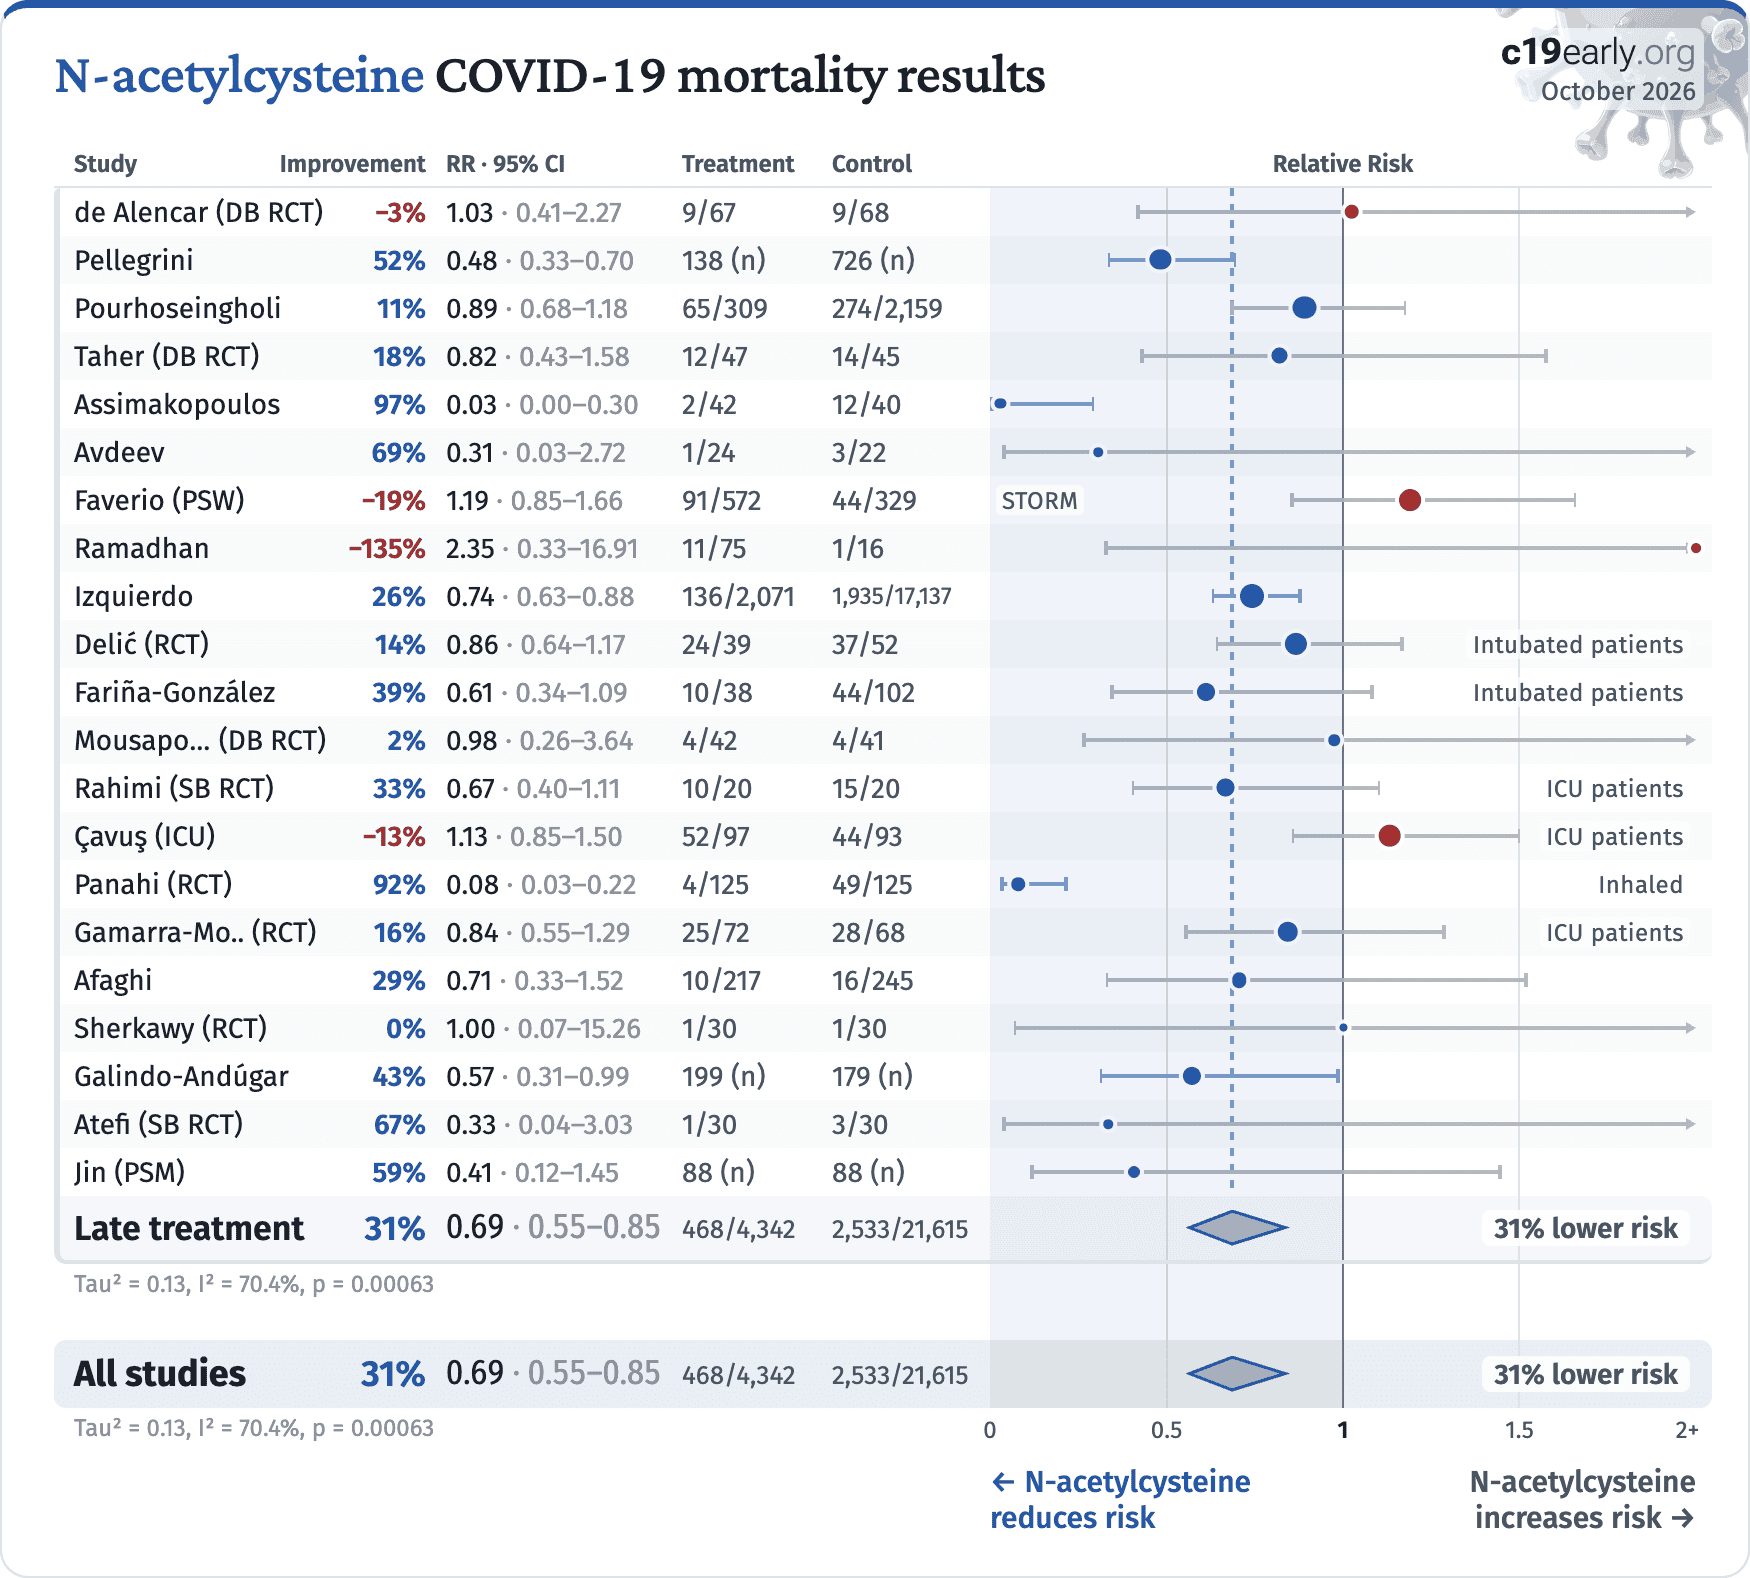
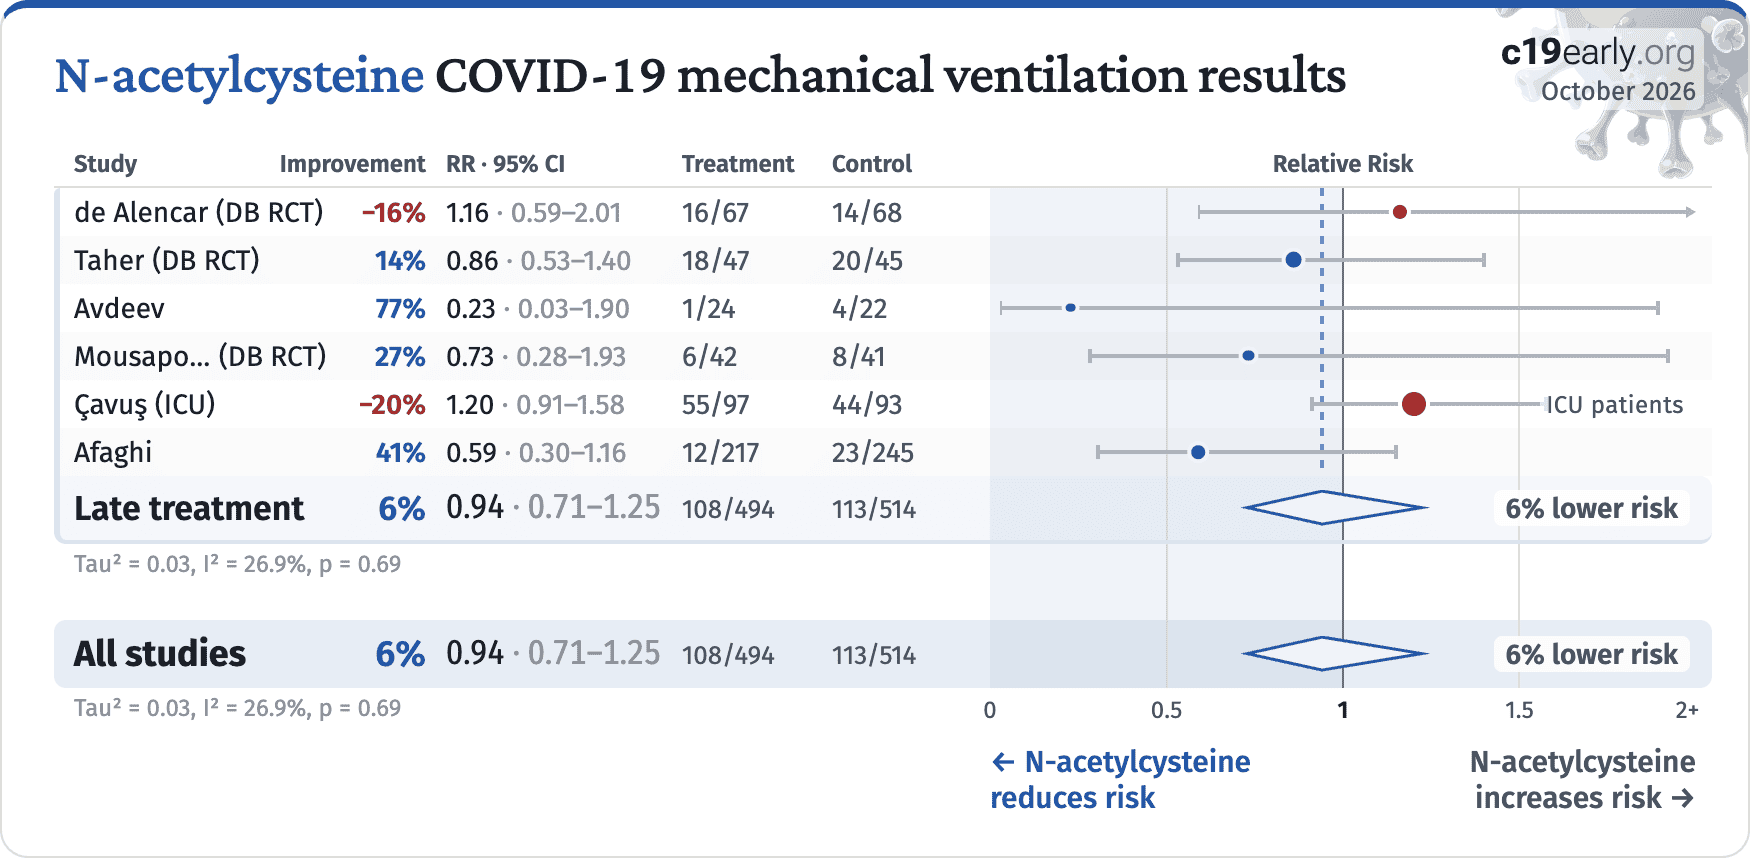
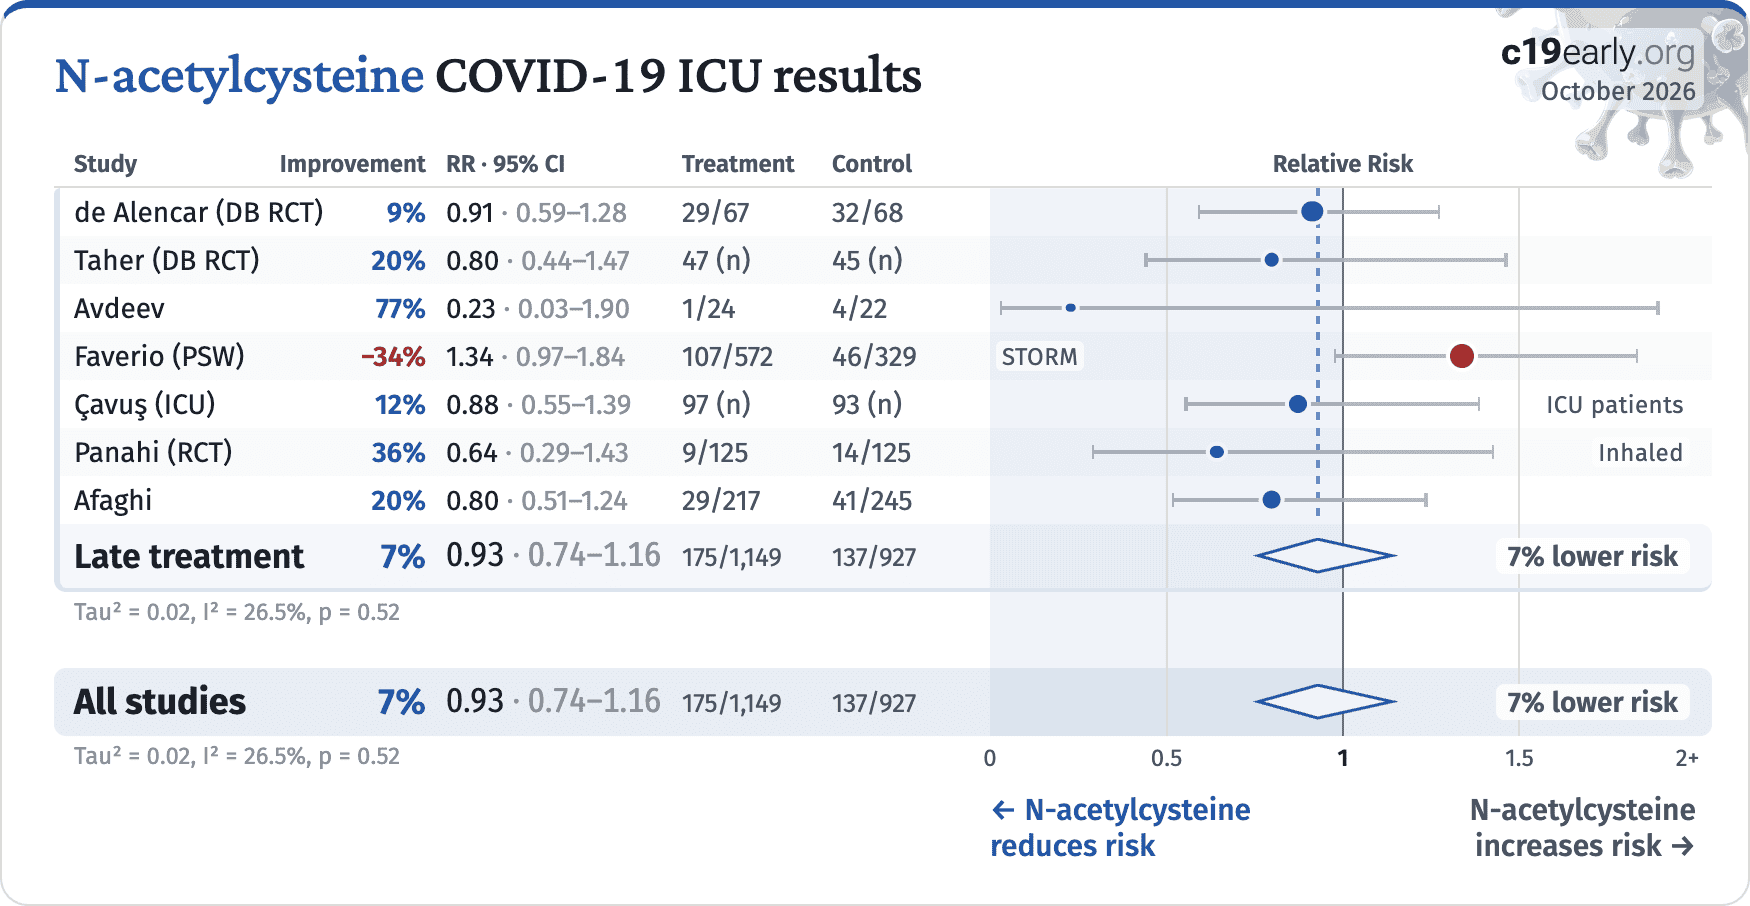
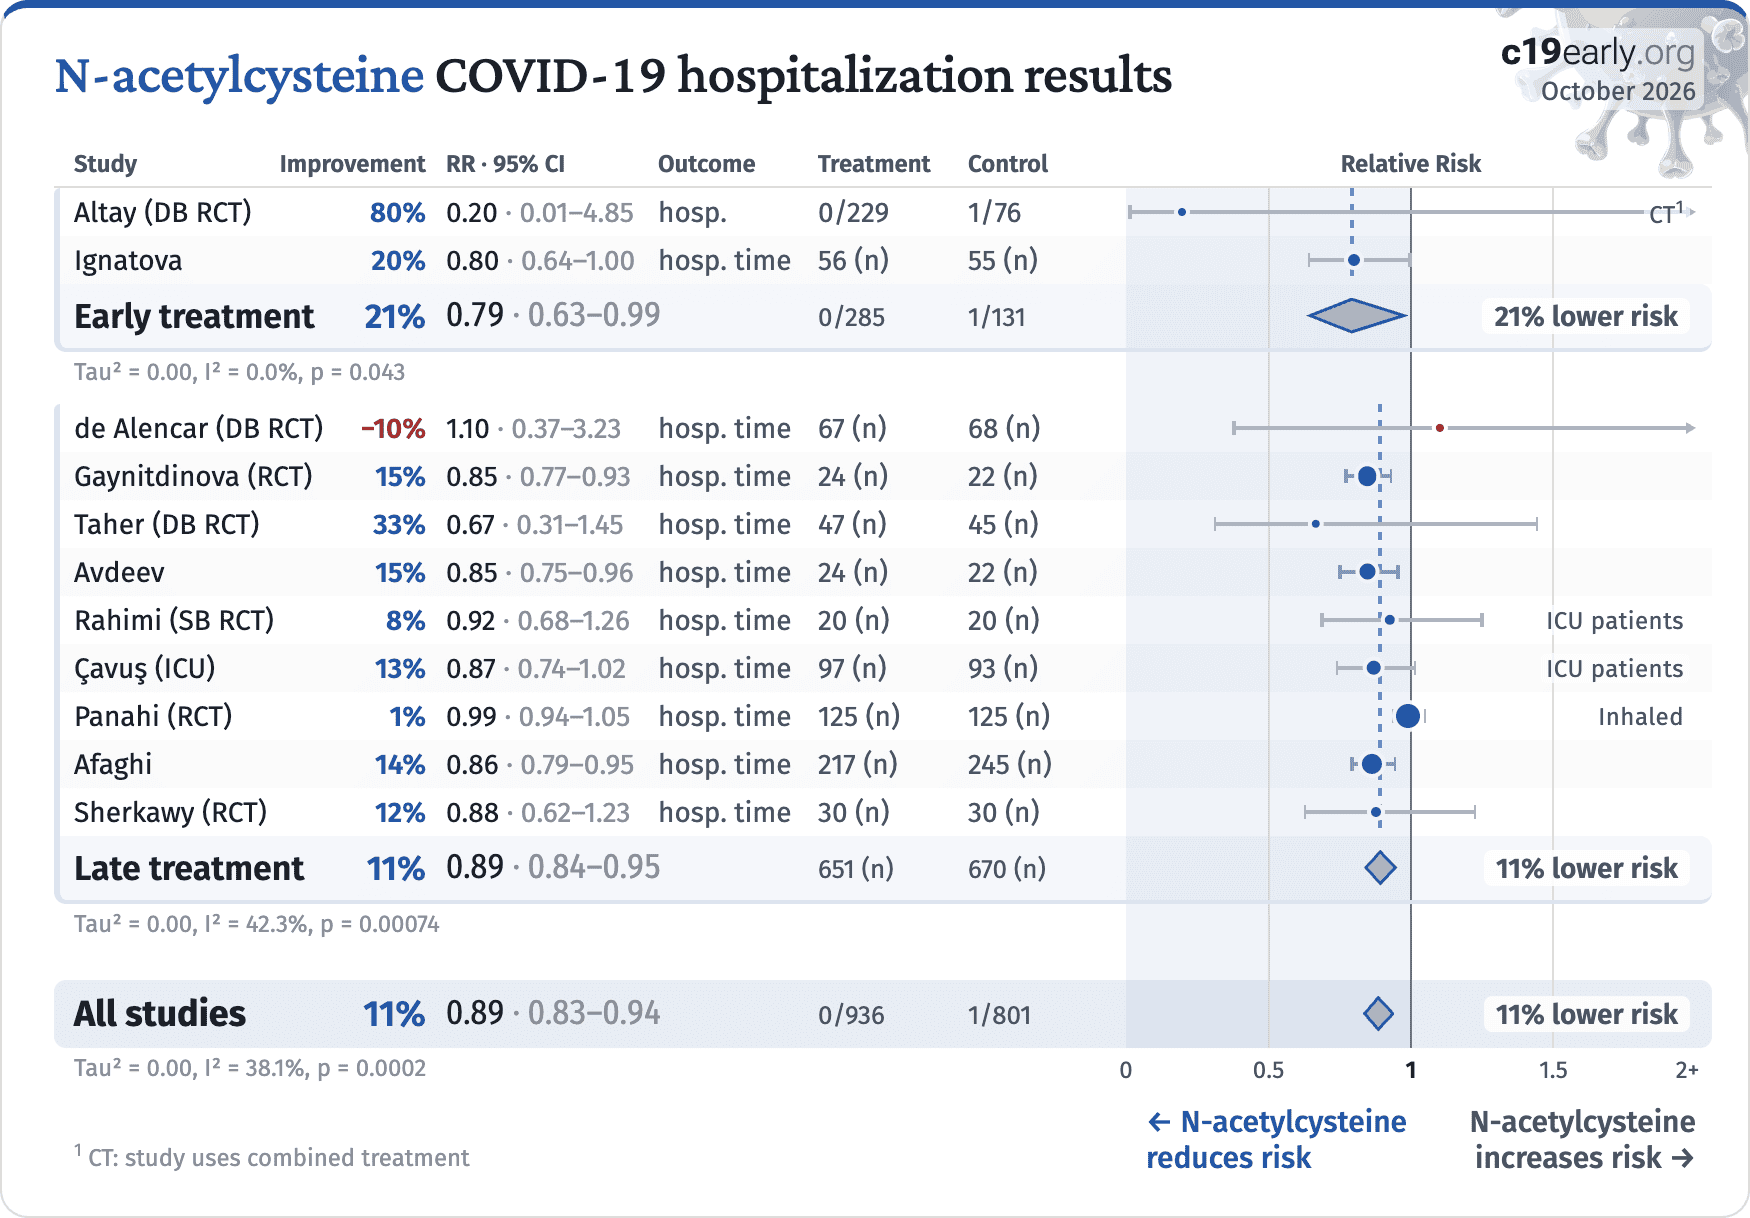
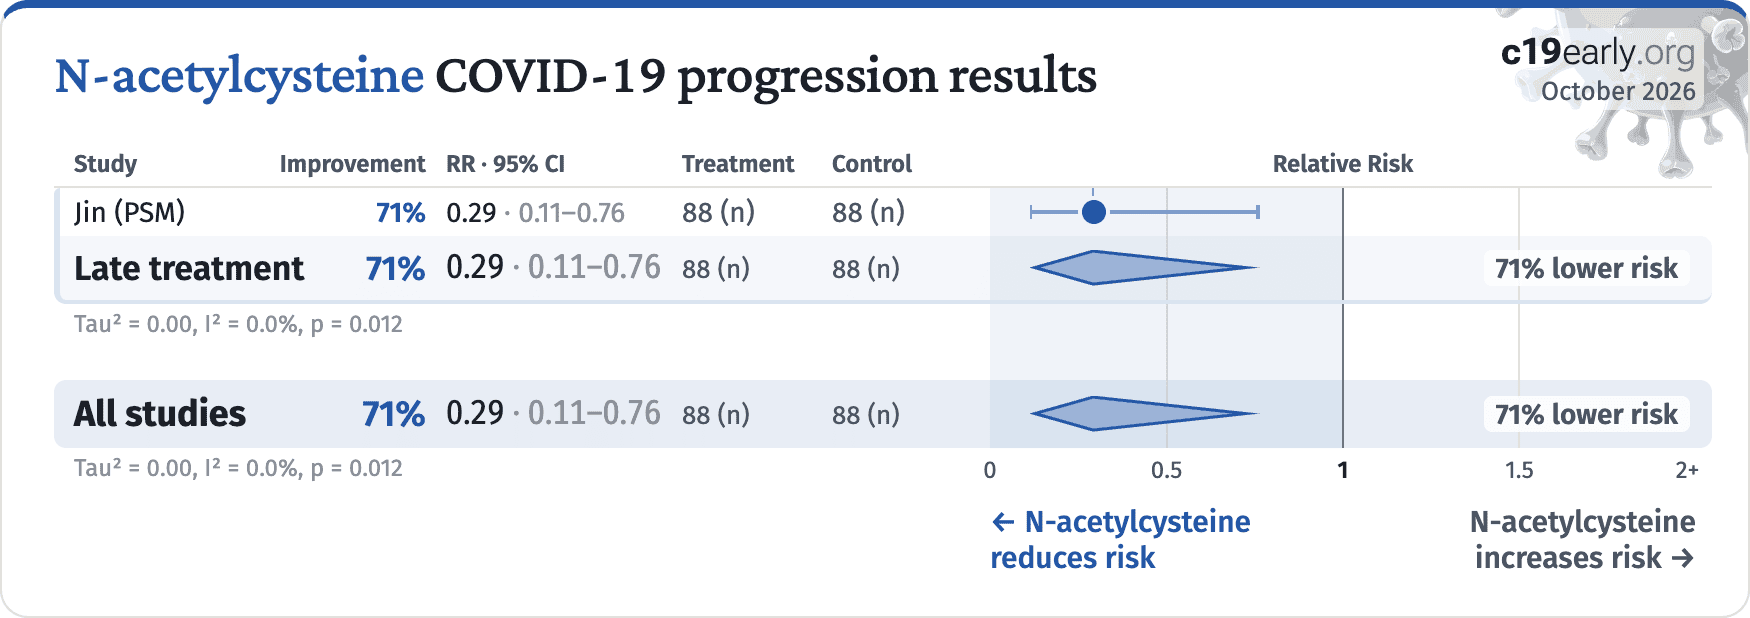
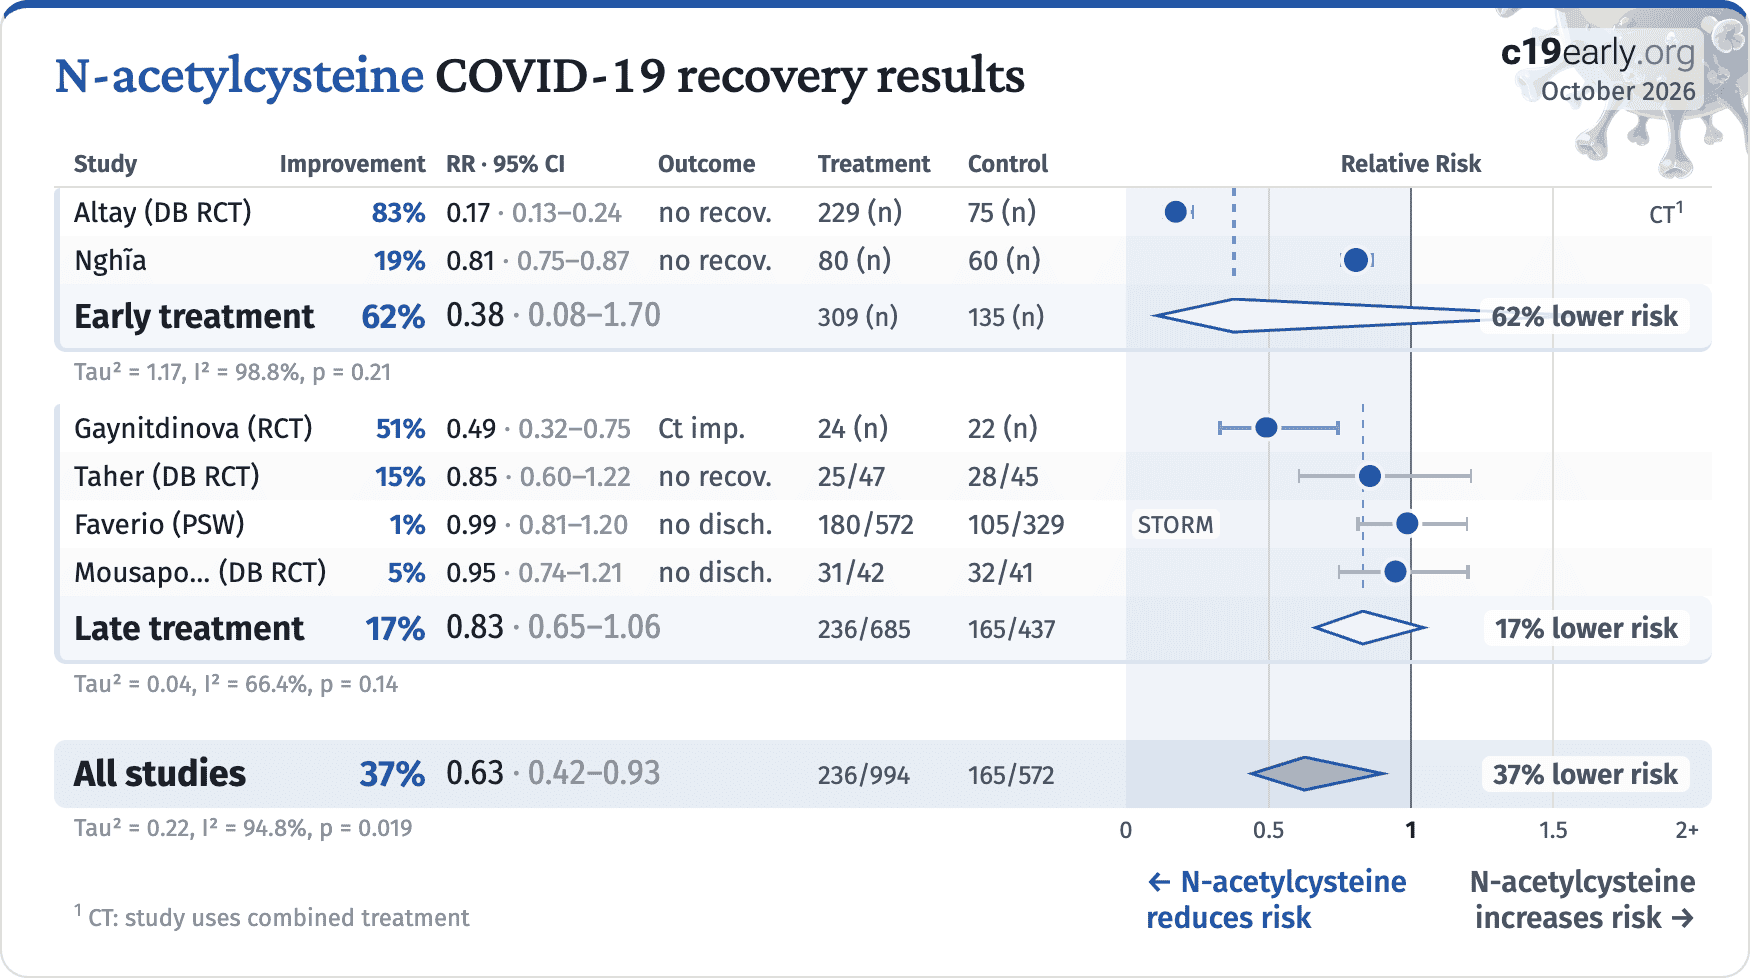
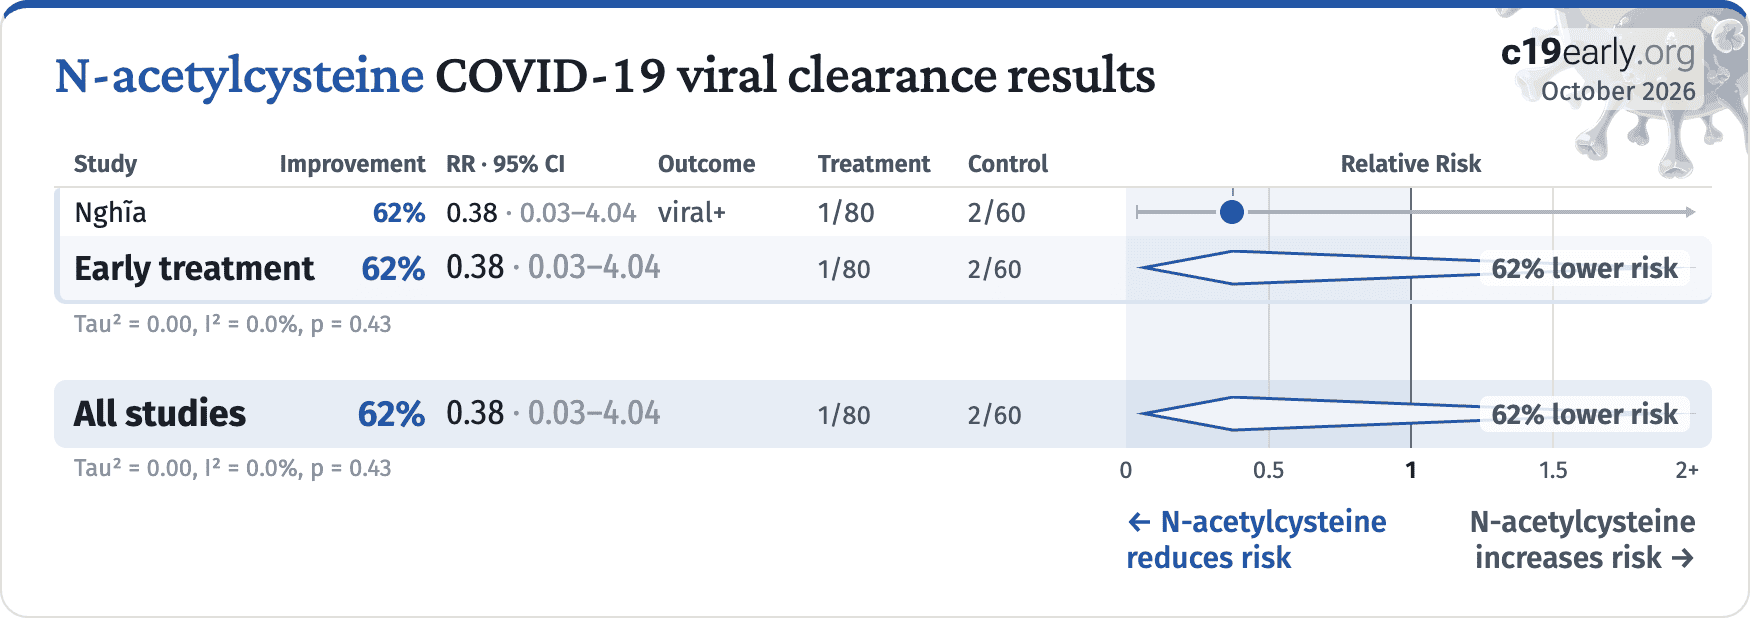
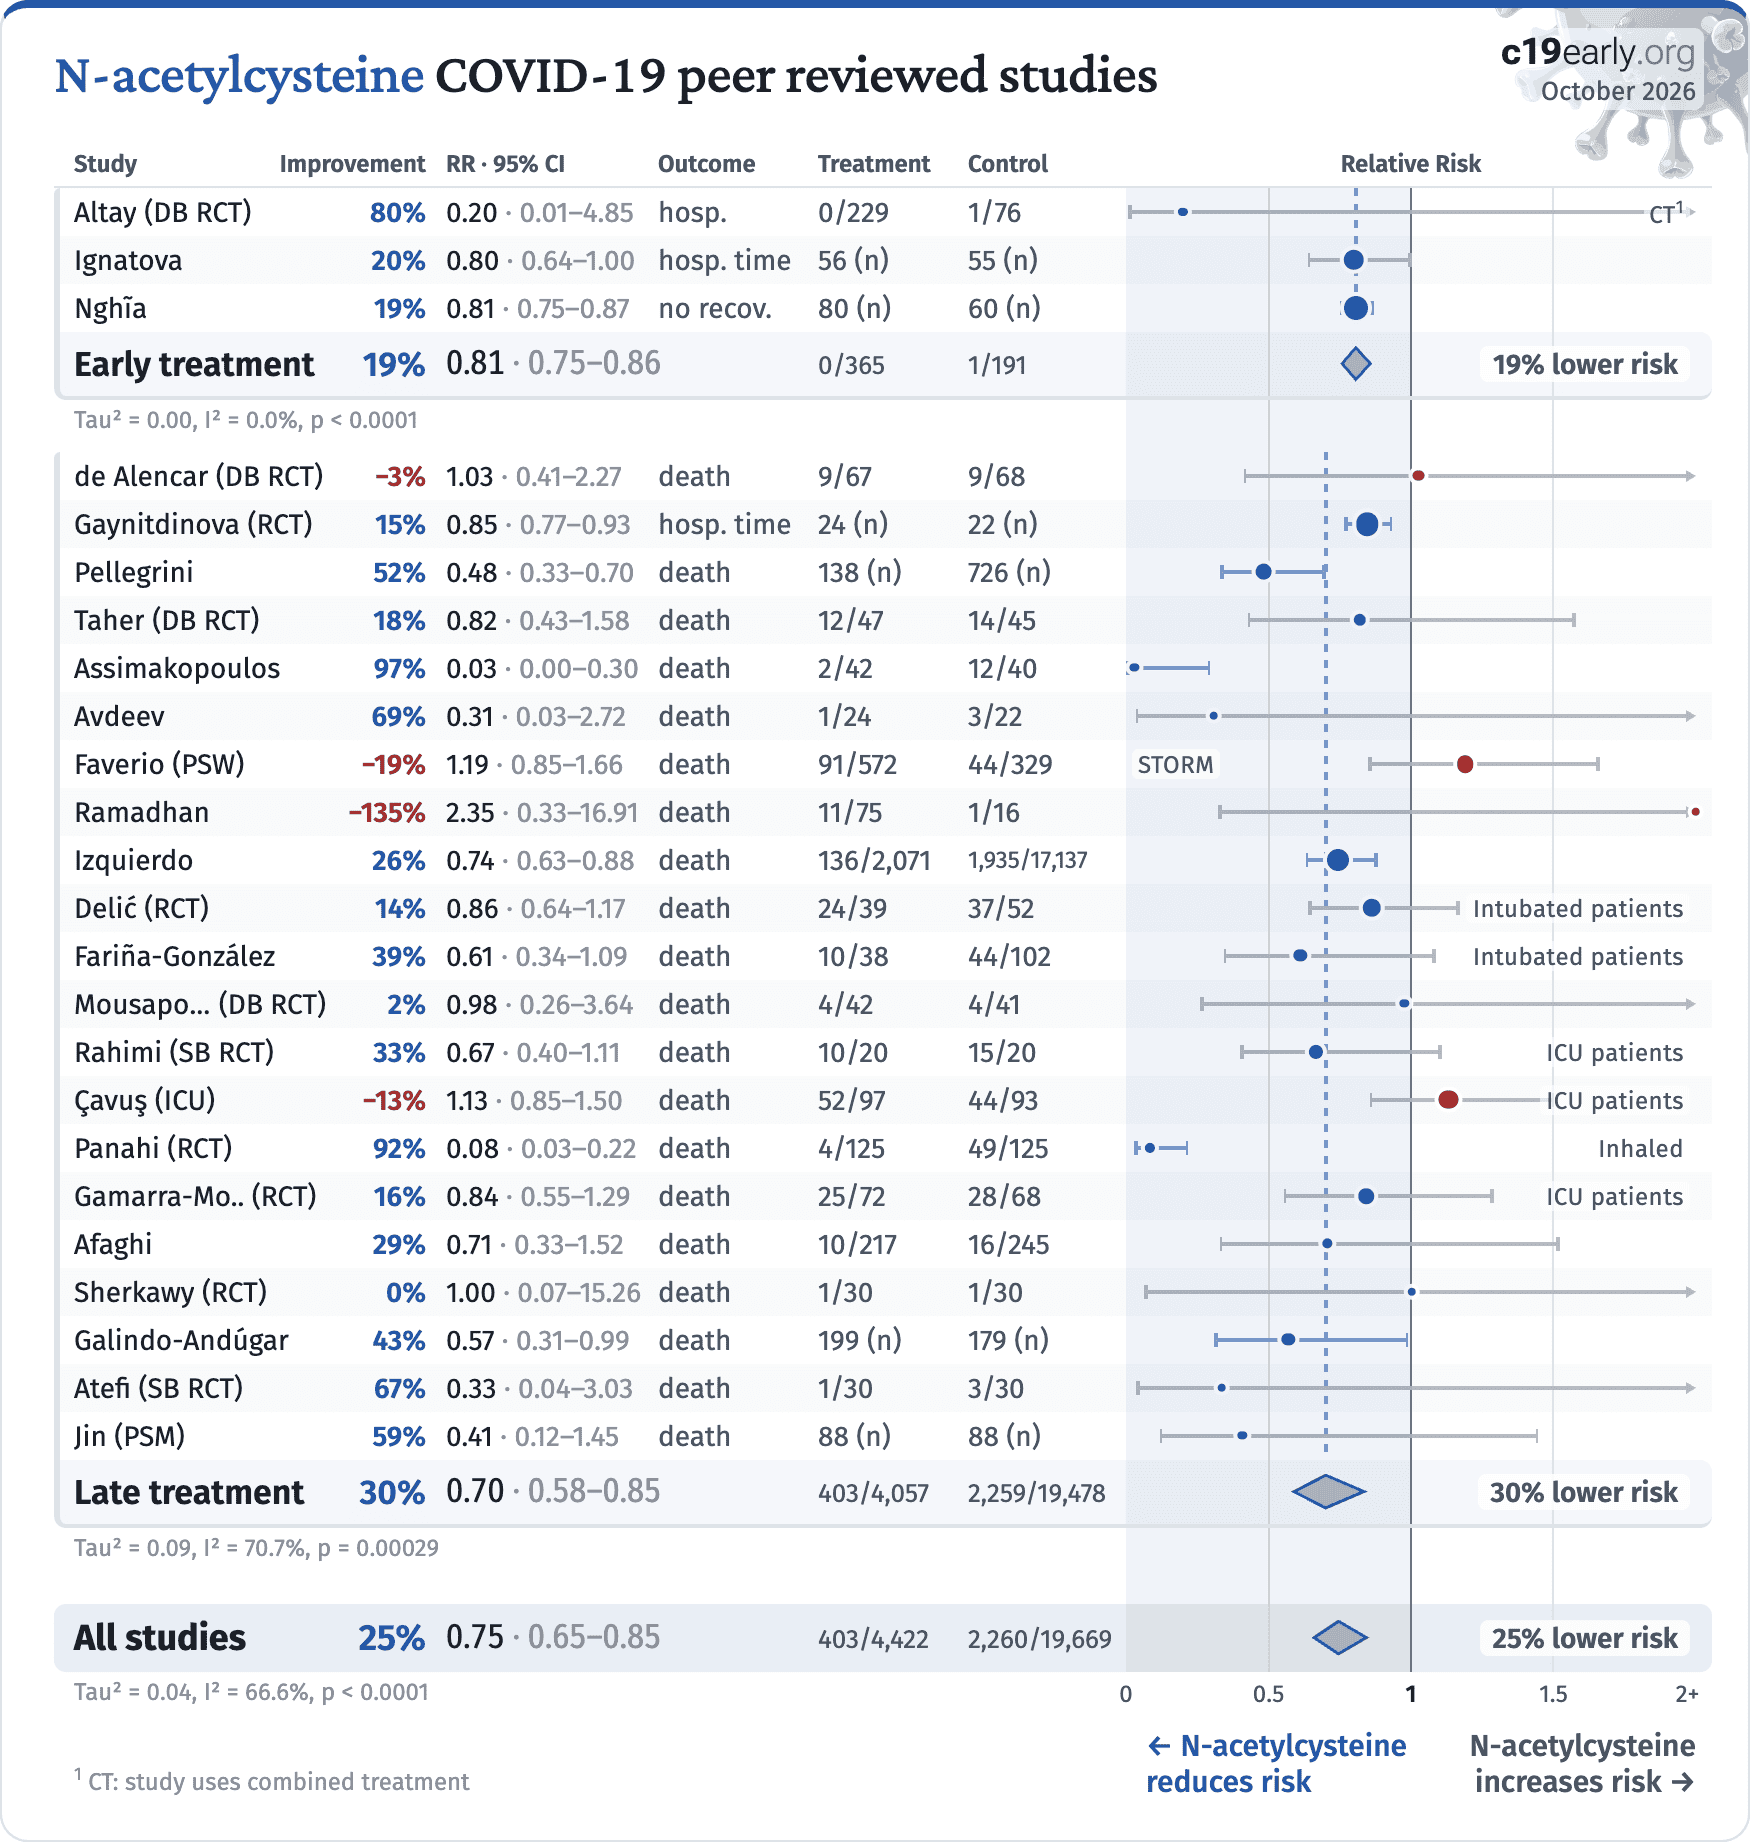
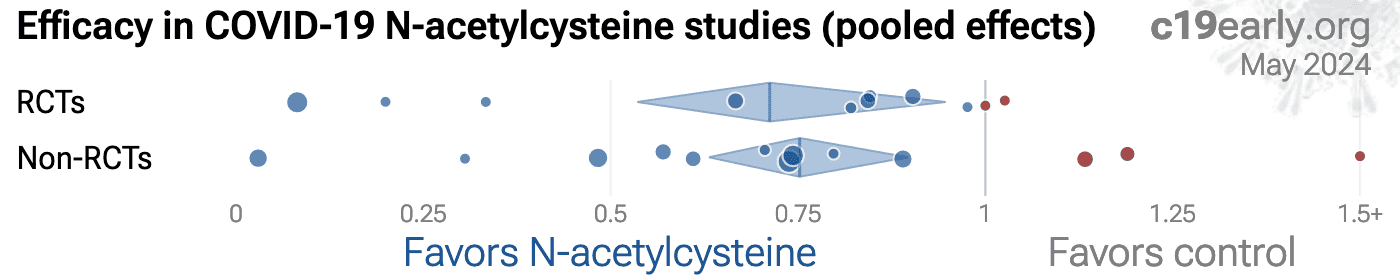
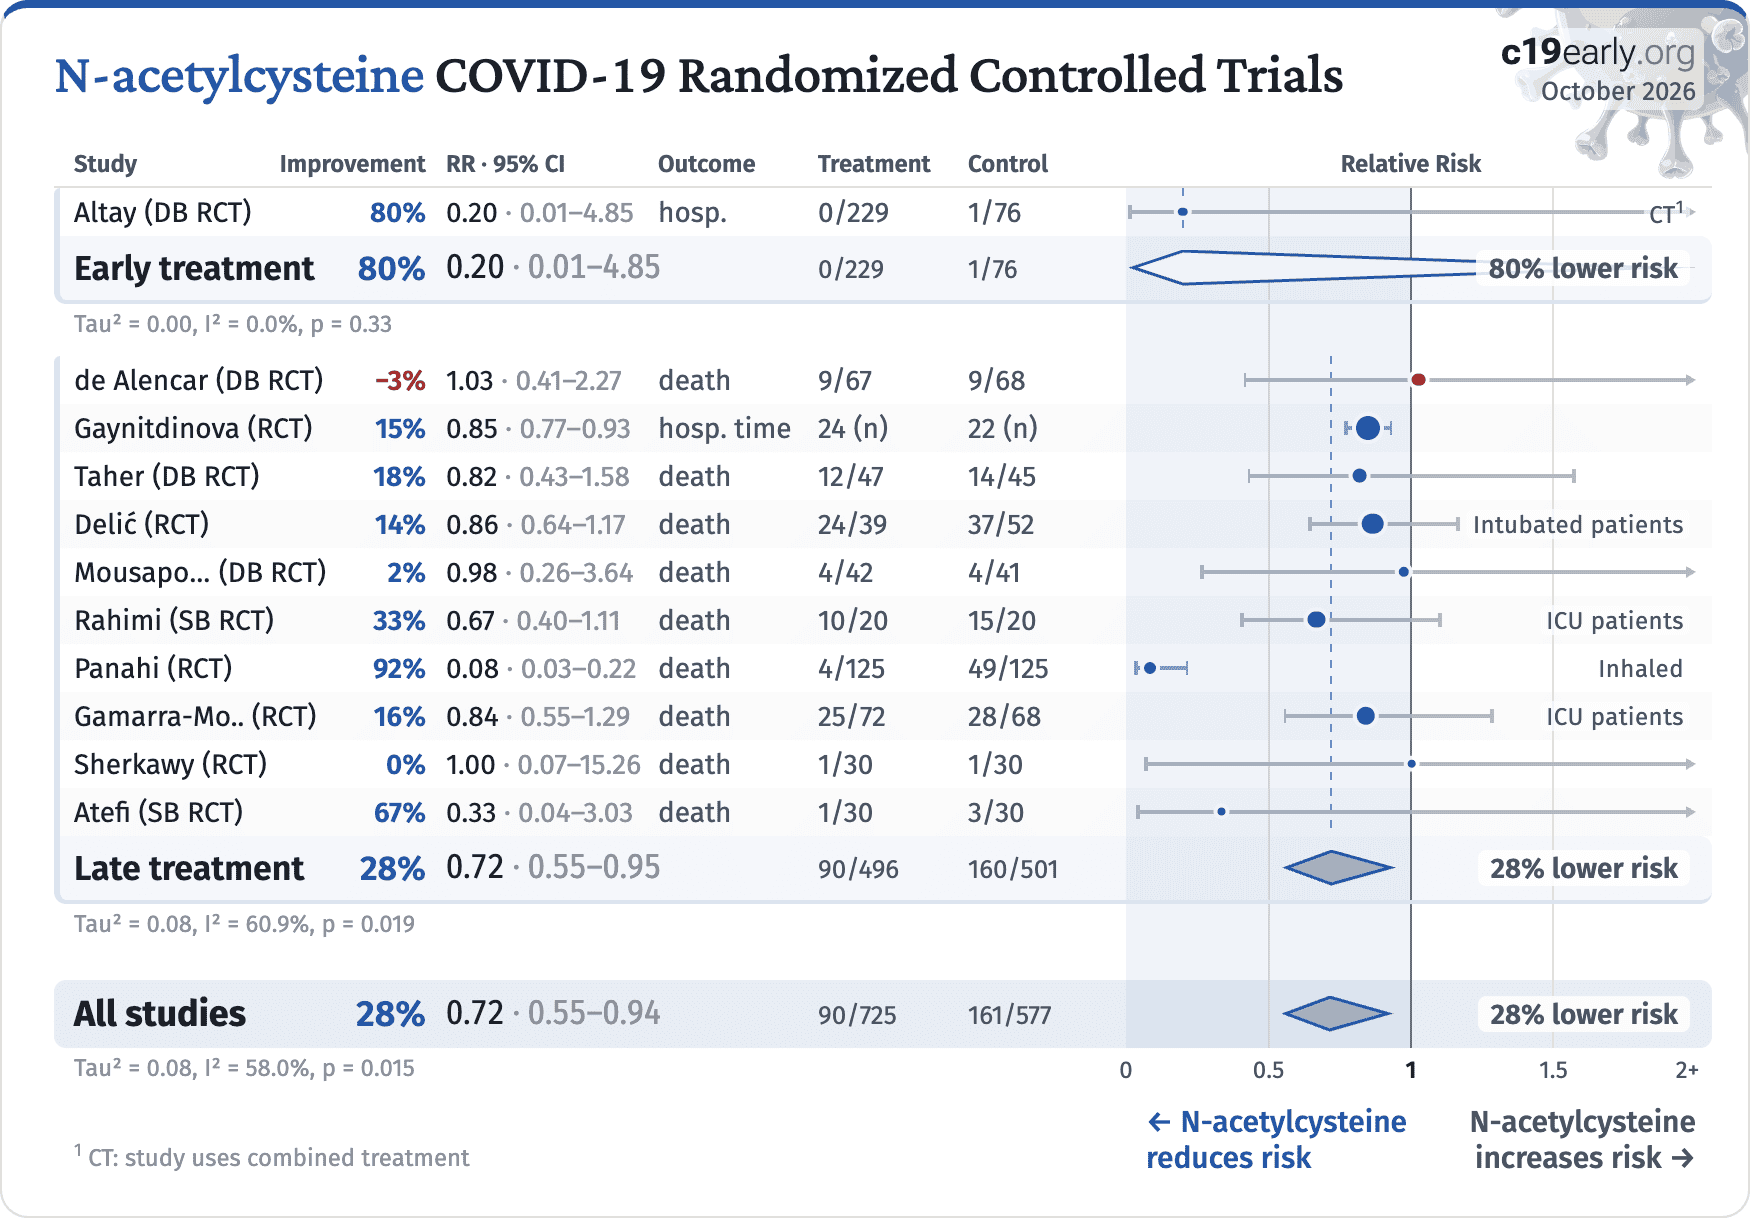
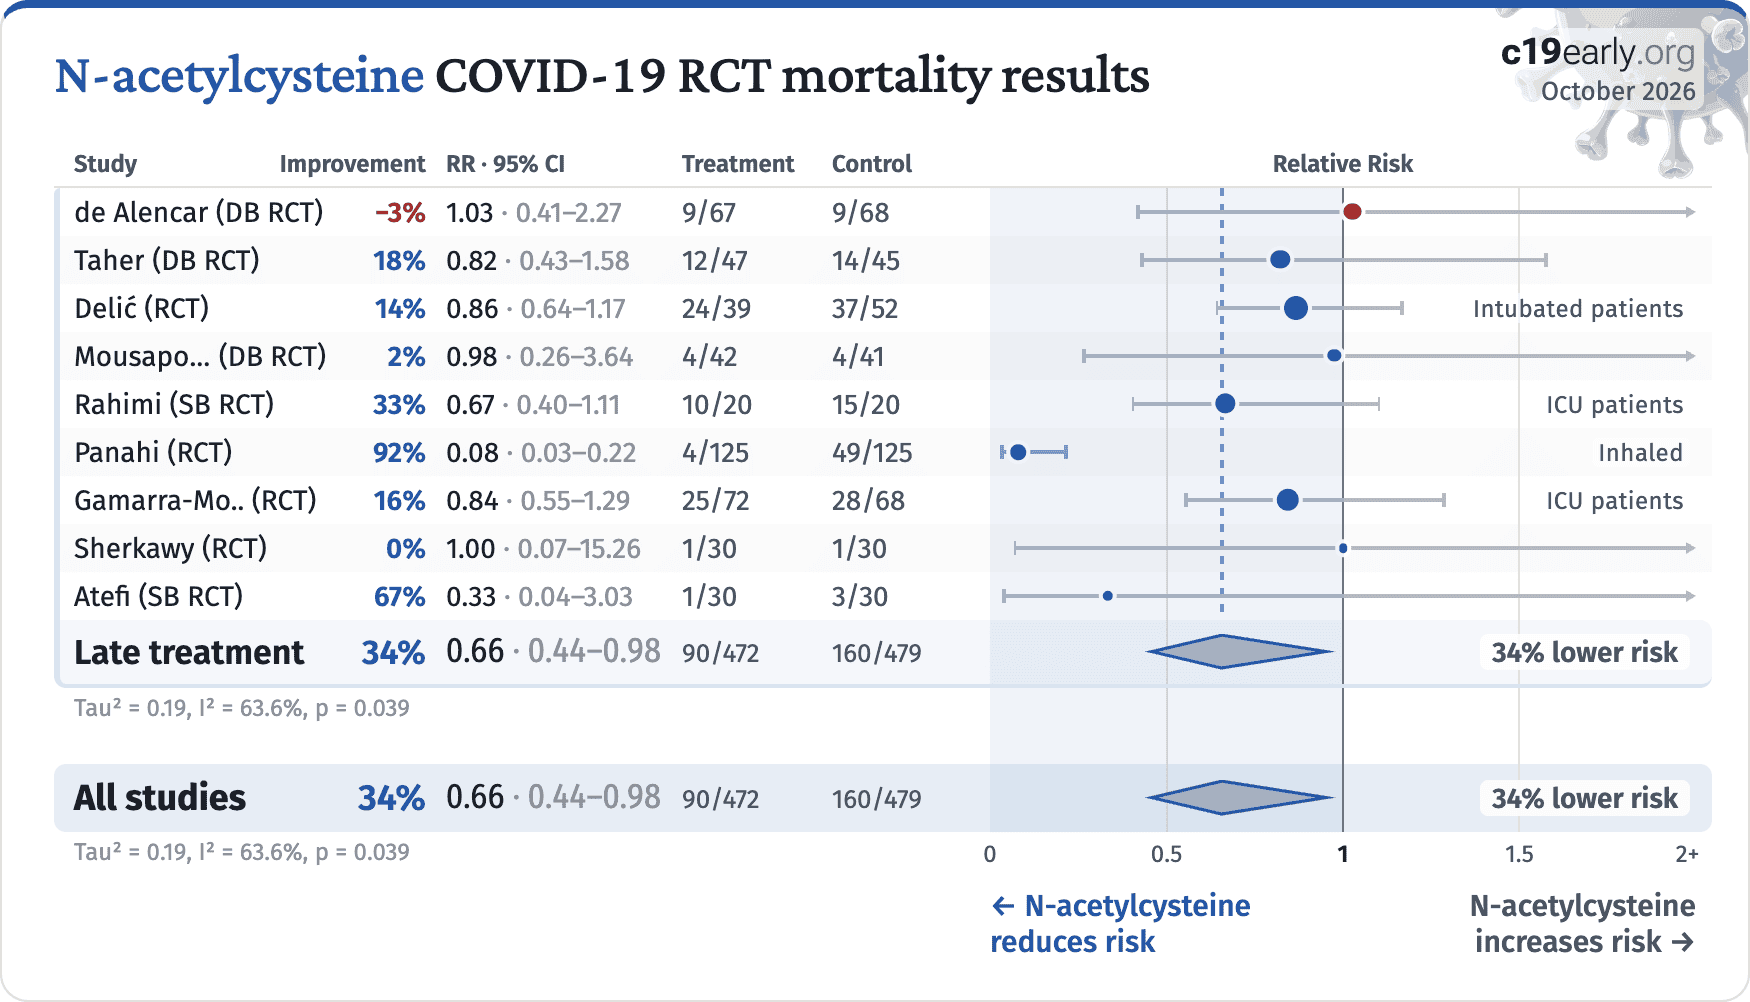
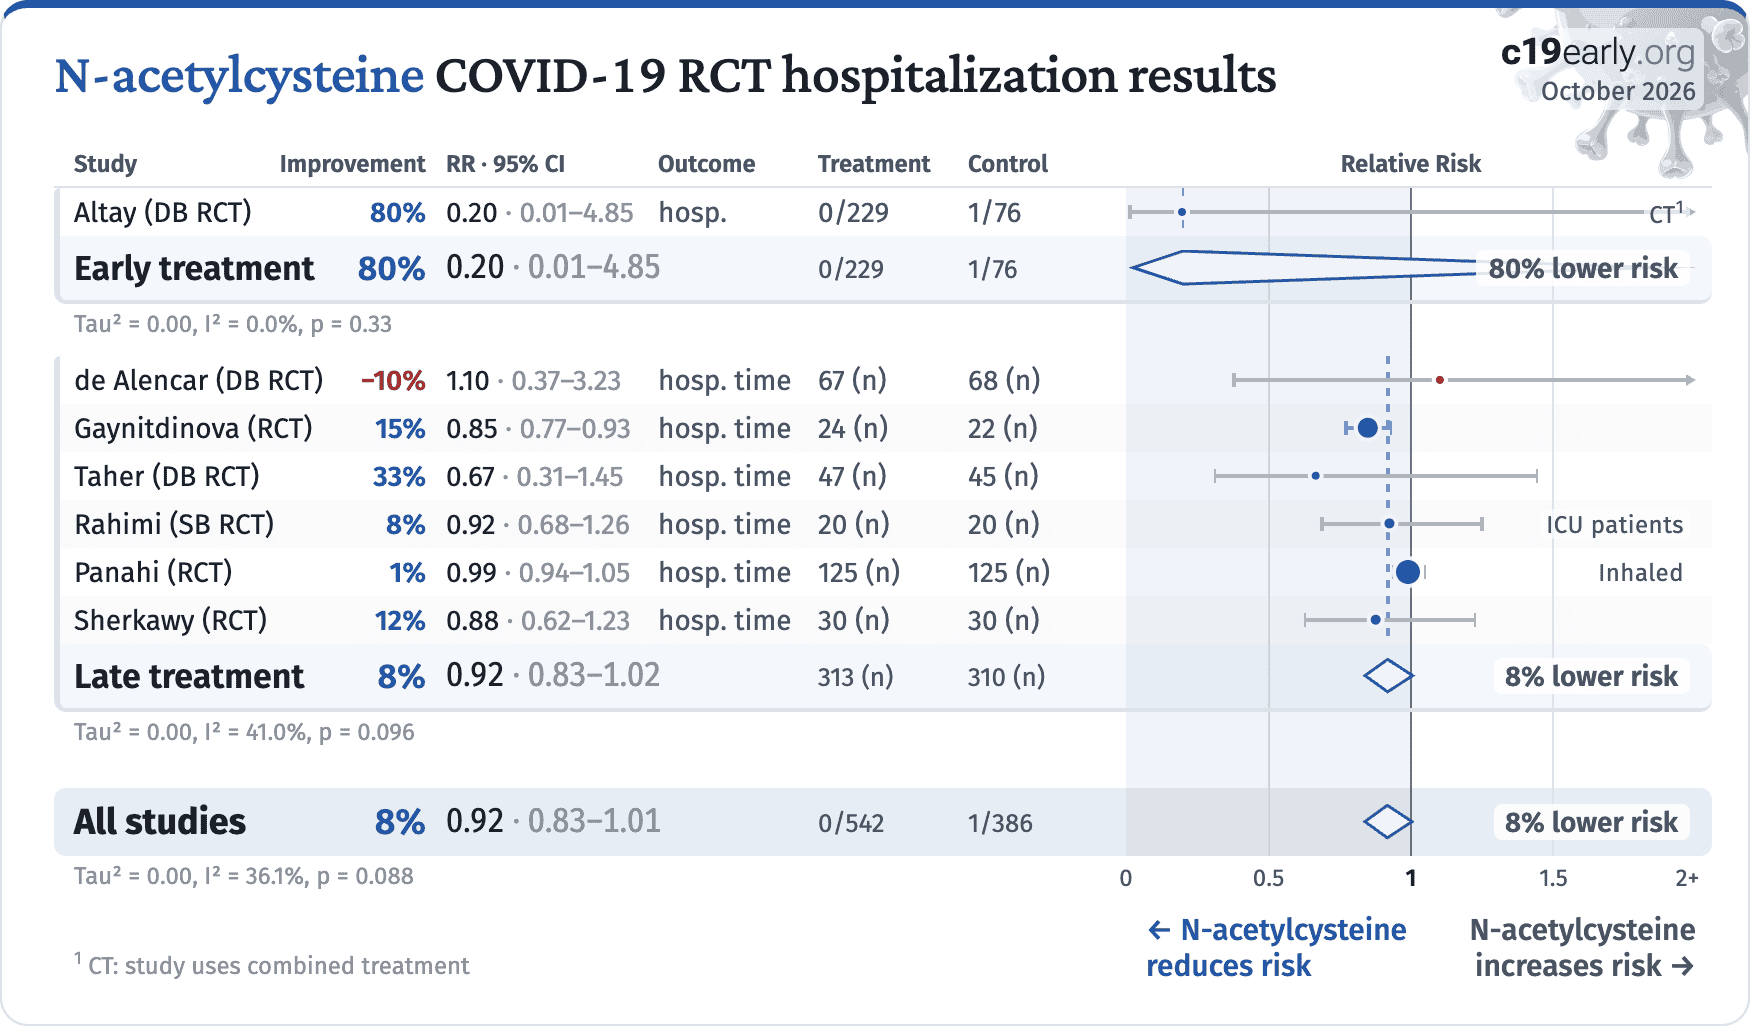
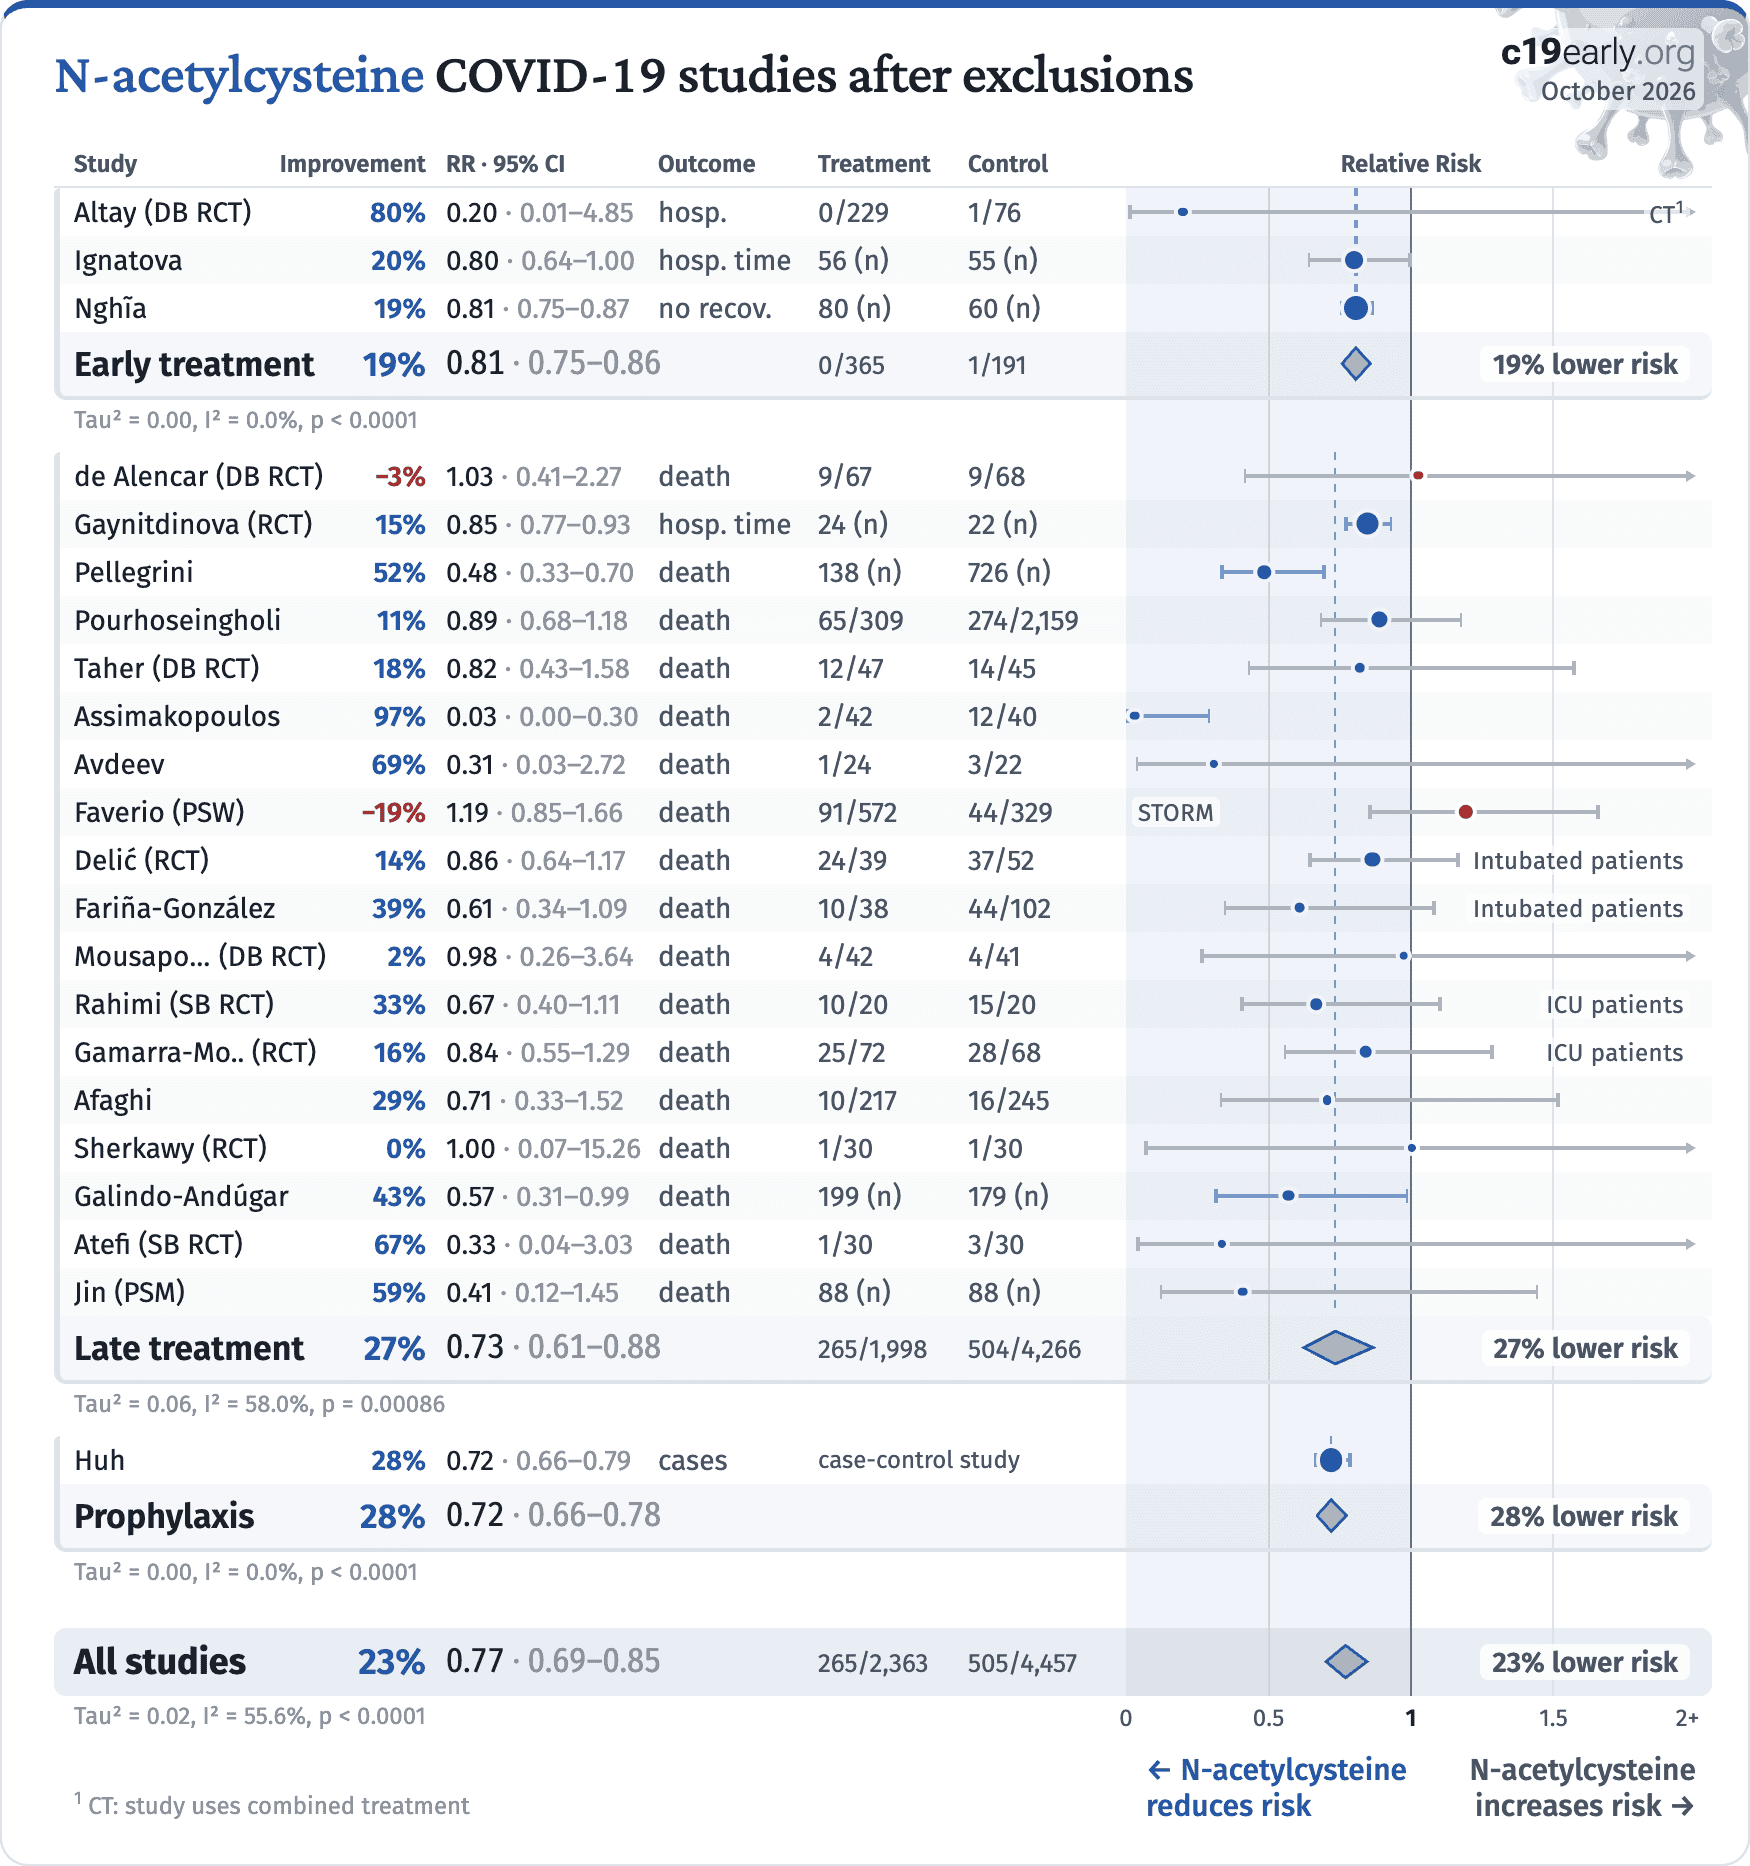
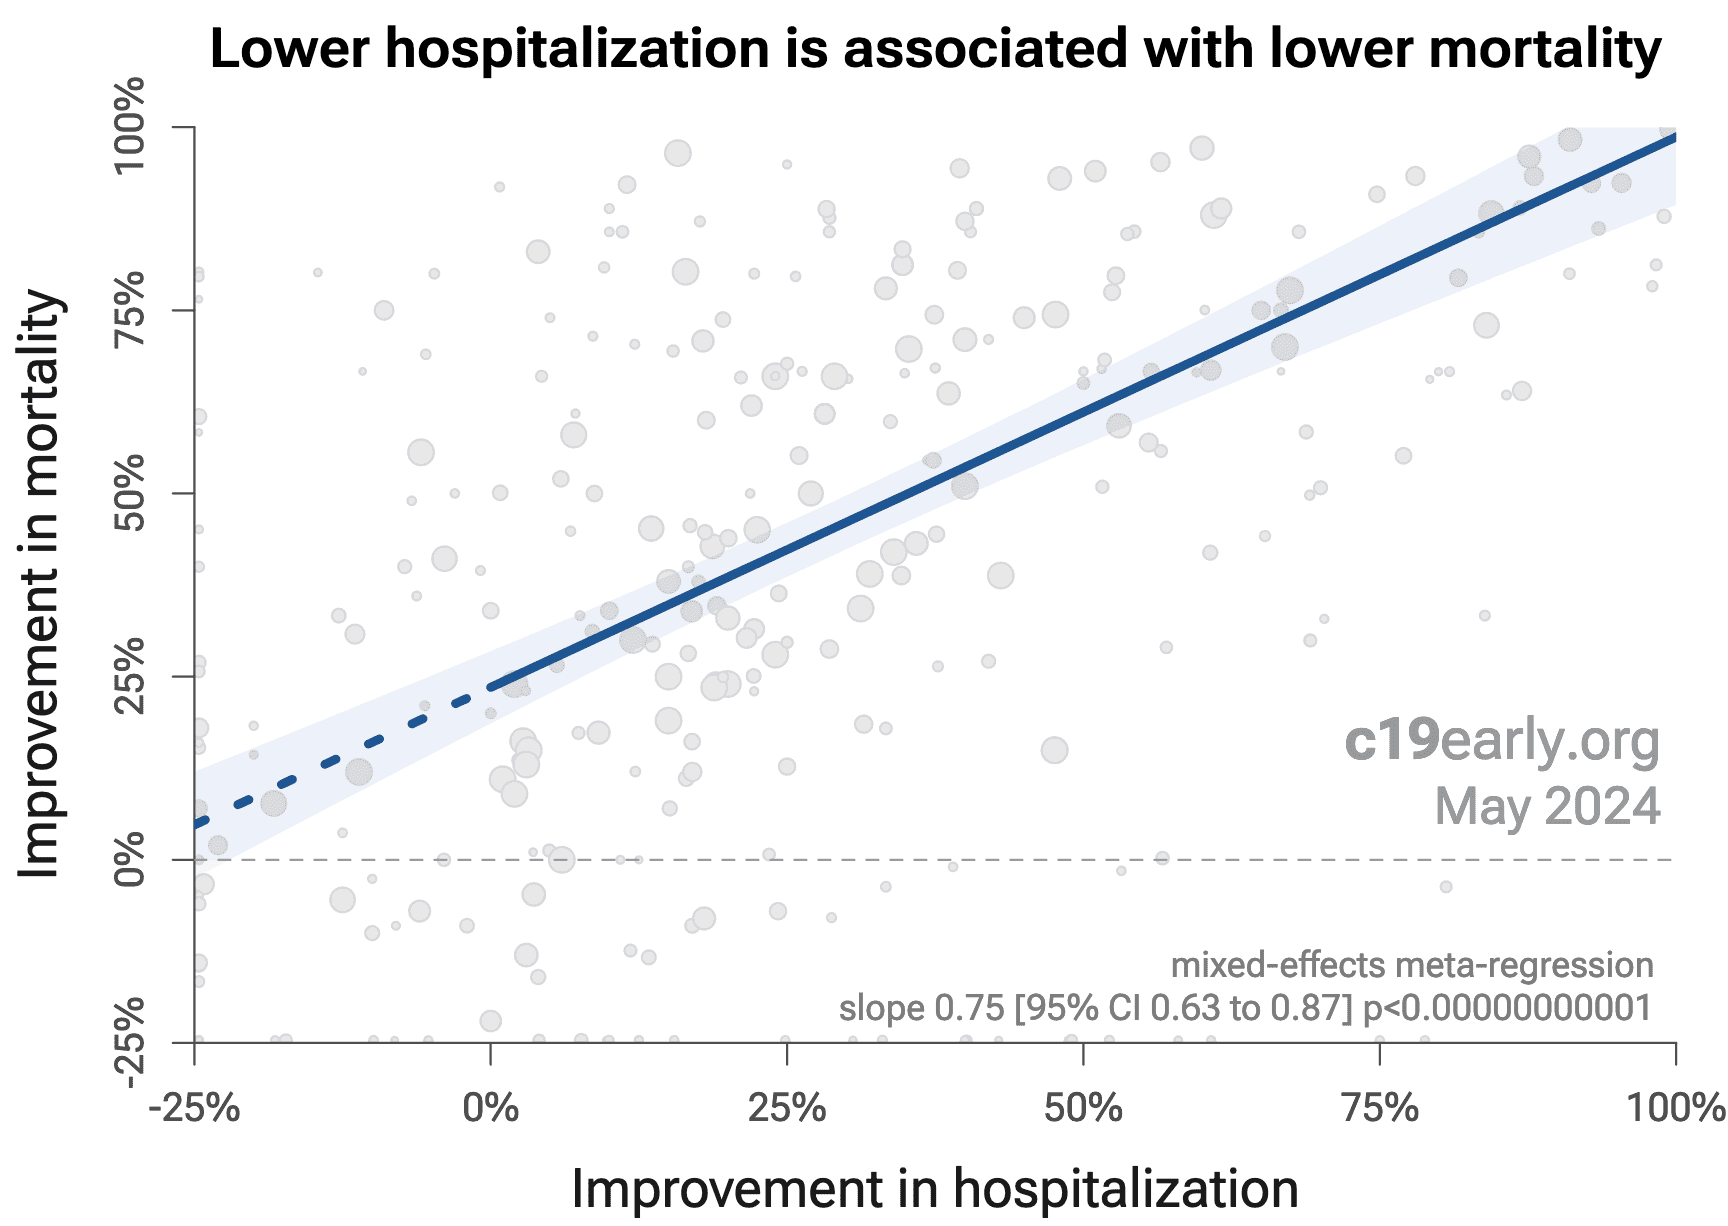
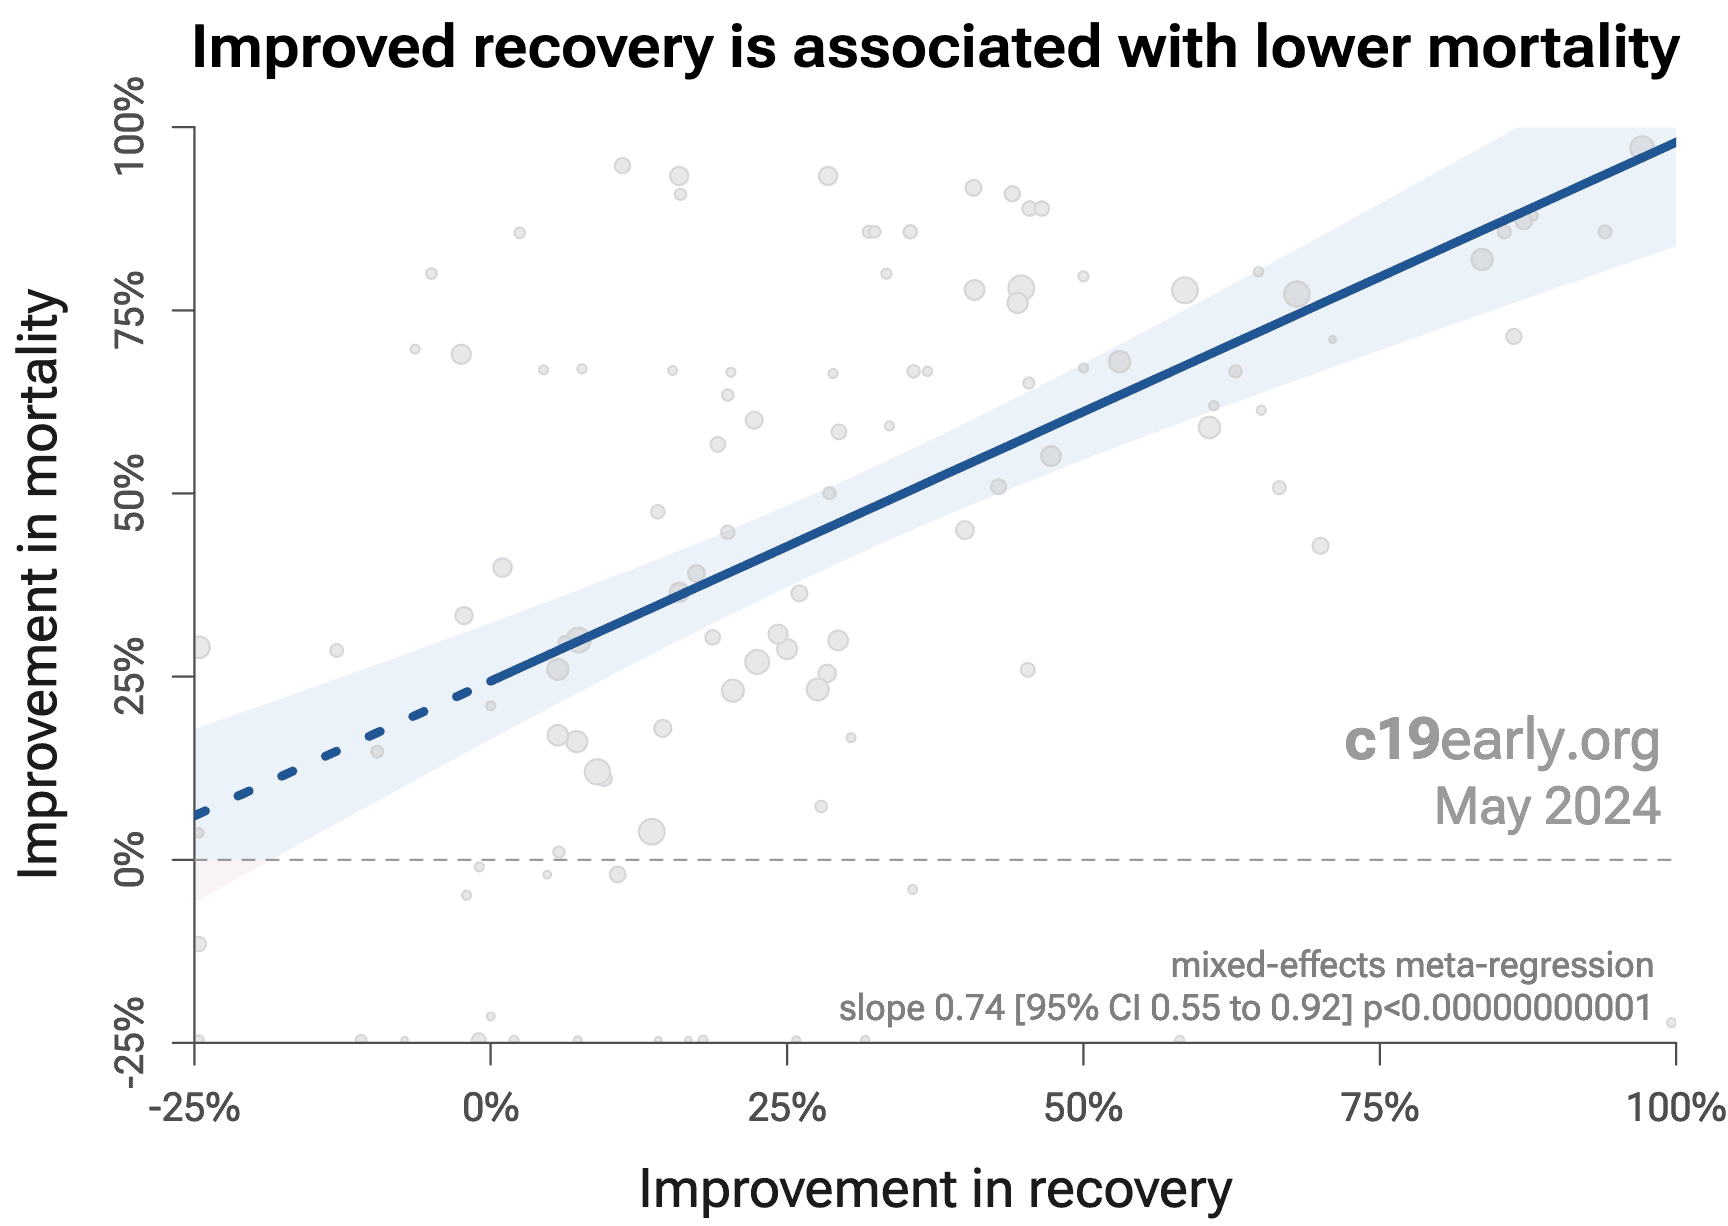
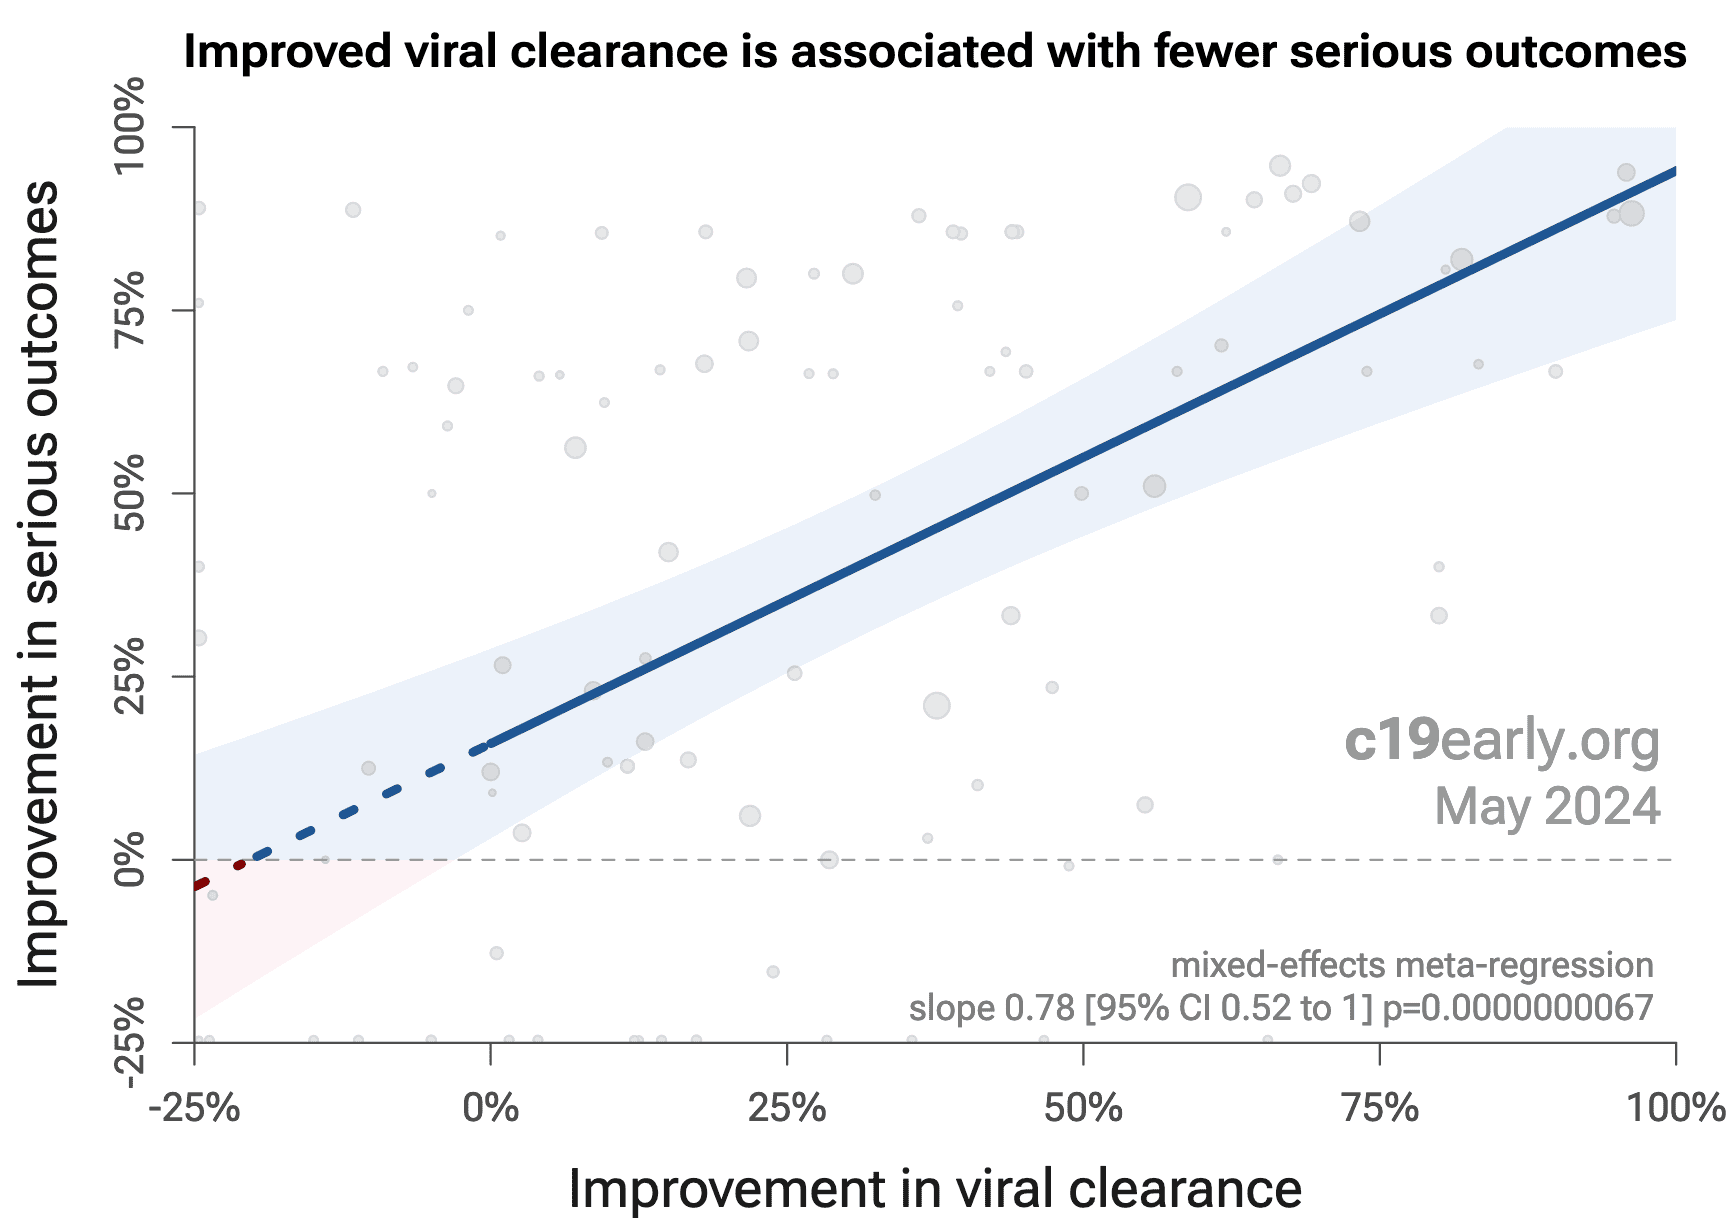
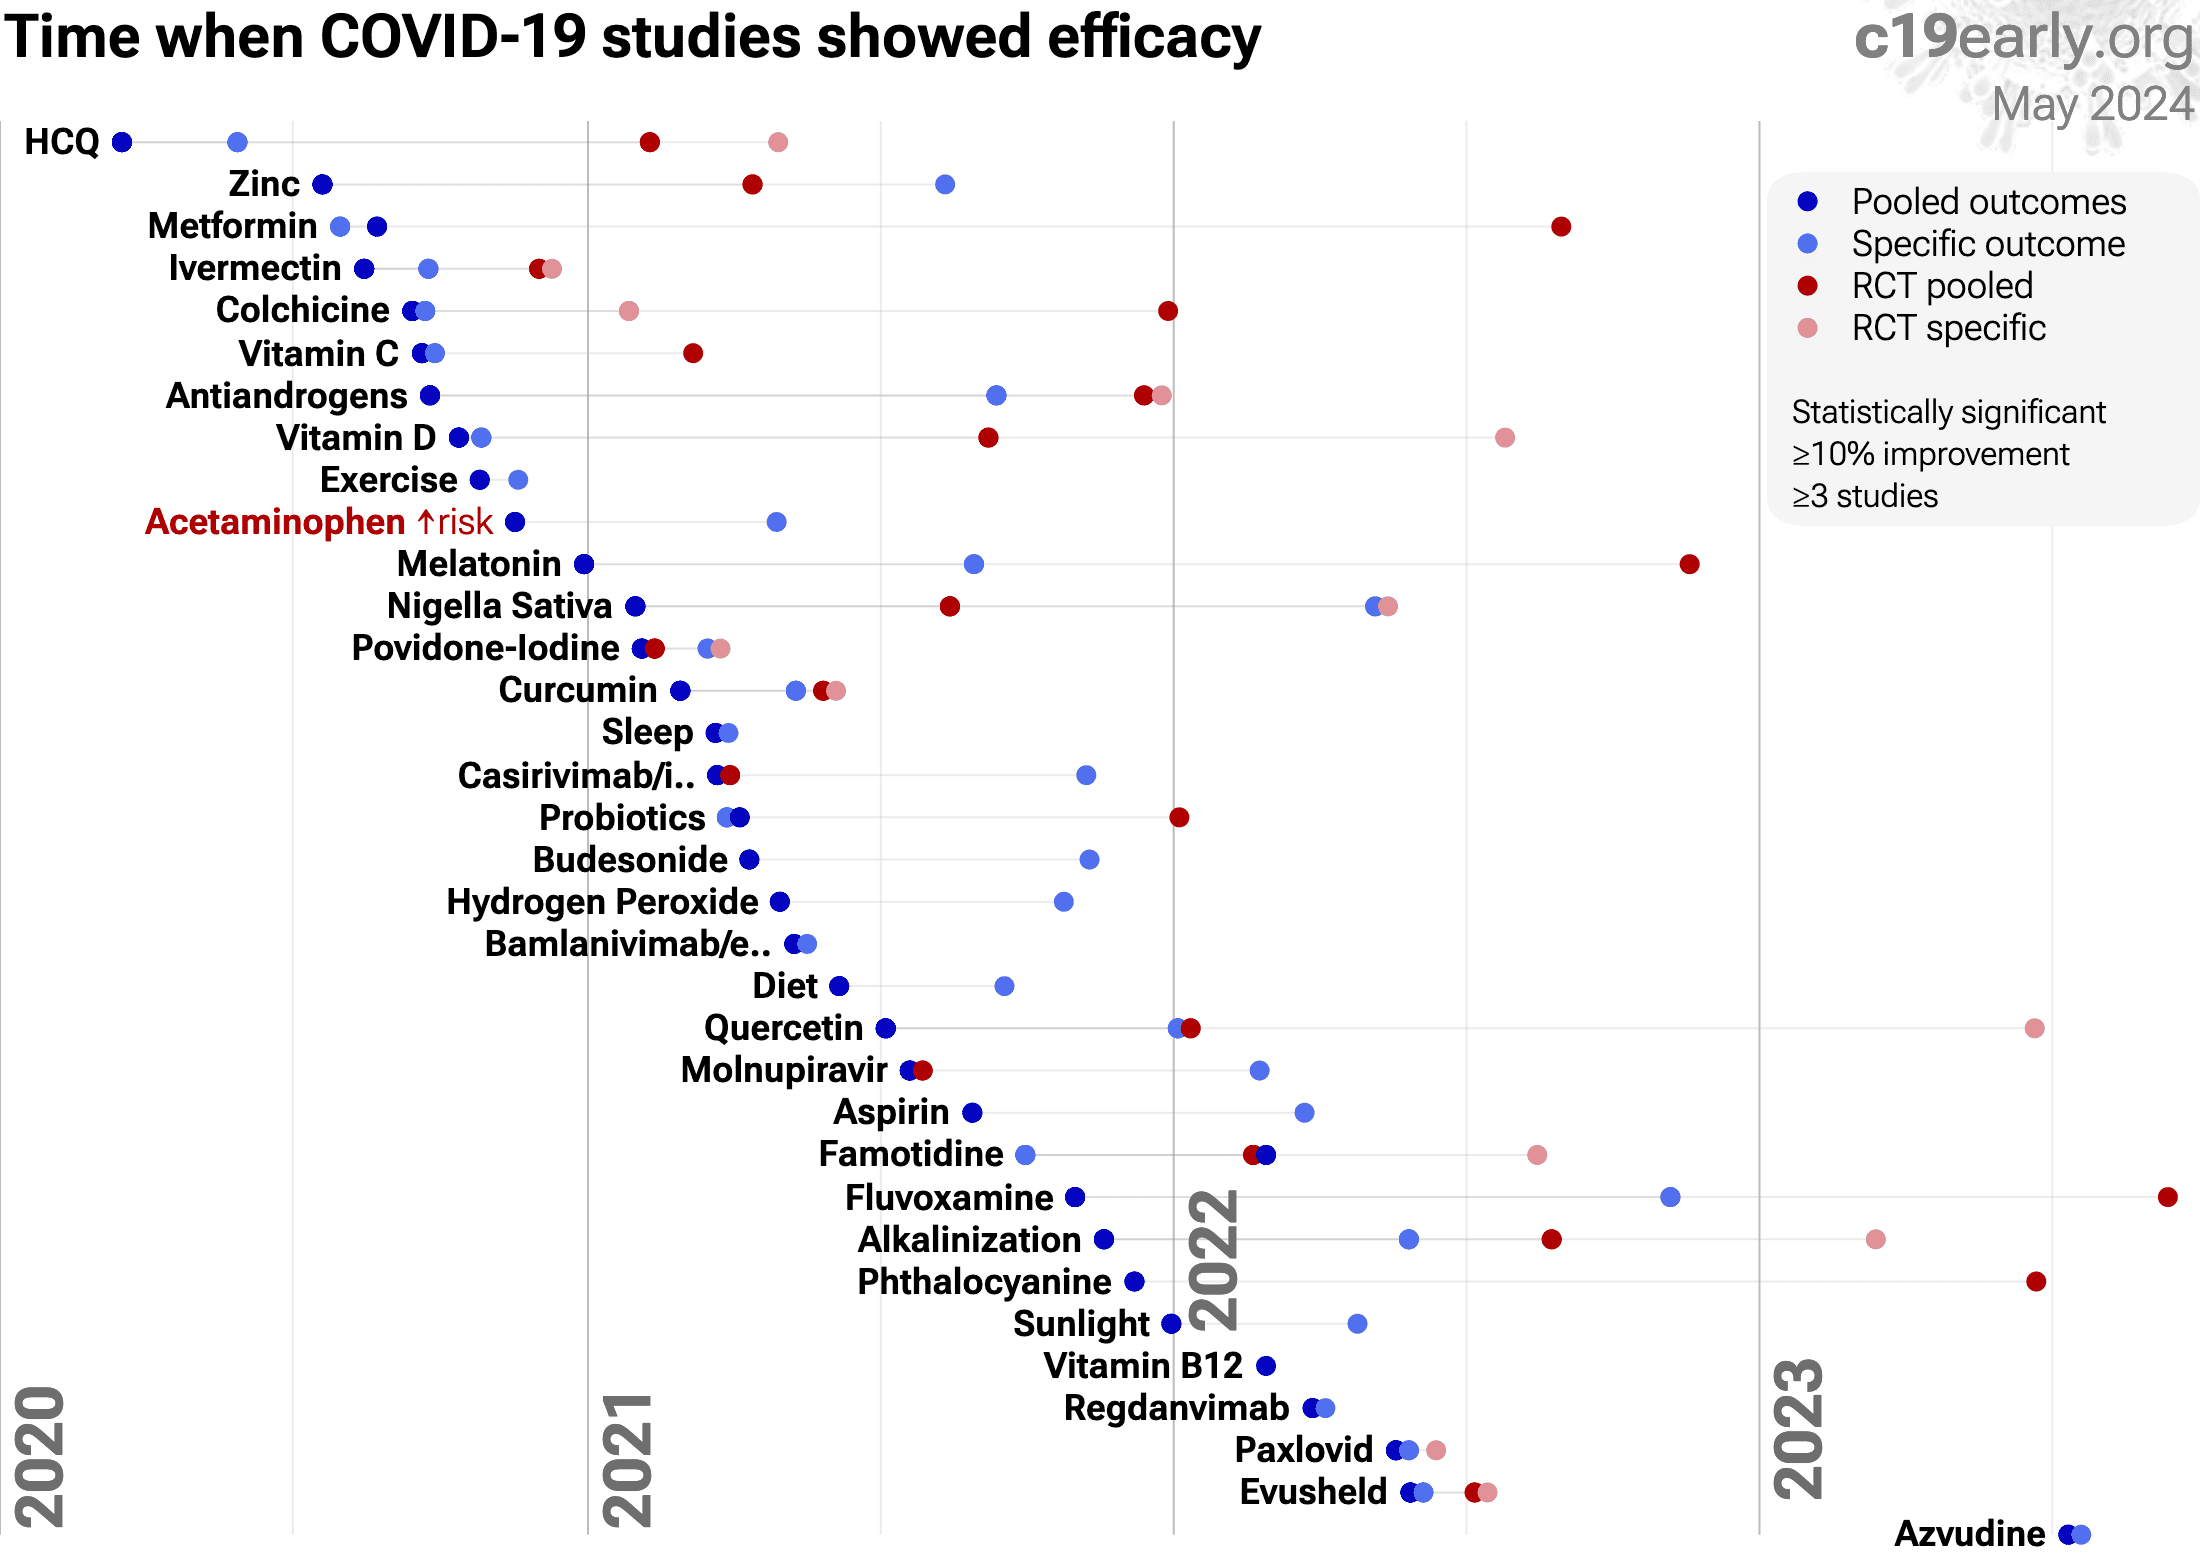
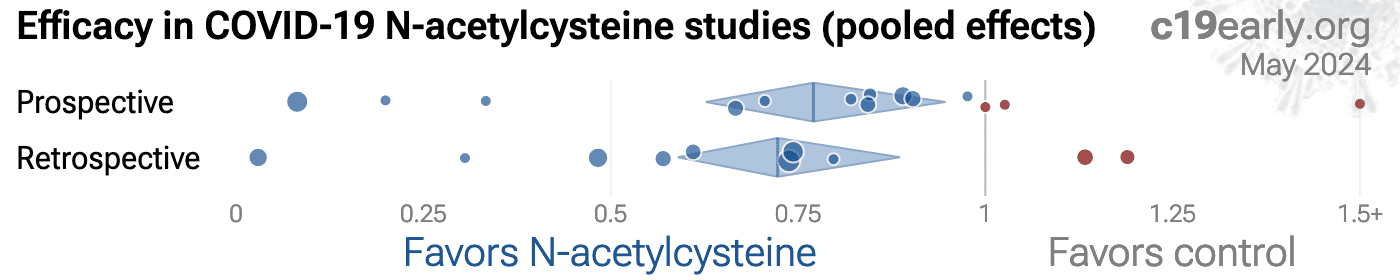
A summary of study results is below. Please submit
updates and corrections at the bottom of this page.
A summary of study results is below. Please submit
updates and corrections at https://c19early.org/nacmeta.html.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.
|
Afaghi, 6/1/2023, prospective, Iran, peer-reviewed, 10 authors, study period 1 June, 2020 - 13 March, 2021, average treatment delay 6.0 days.
|
risk of death, 29.4% lower, RR 0.71, p = 0.42, treatment 10 of 217 (4.6%), control 16 of 245 (6.5%), NNT 52.
|
|
risk of mechanical ventilation, 41.1% lower, RR 0.59, p = 0.16, treatment 12 of 217 (5.5%), control 23 of 245 (9.4%), NNT 26.
|
|
risk of ICU admission, 20.1% lower, RR 0.80, p = 0.36, treatment 29 of 217 (13.4%), control 41 of 245 (16.7%), NNT 30.
|
|
hospitalization time, 13.6% lower, relative time 0.86, p = 0.002, treatment 217, control 245.
|
|
Assimakopoulos, 6/29/2021, retrospective, Greece, peer-reviewed, 9 authors, study period 1 February, 2021 - 30 April, 2021.
|
risk of death, 97.1% lower, RR 0.03, p = 0.006, treatment 2 of 42 (4.8%), control 12 of 40 (30.0%), NNT 4.0, inverted to make RR<1 favor treatment, odds ratio converted to relative risk.
|
|
Atefi, 11/20/2023, Single Blind Randomized Controlled Trial, Iran, peer-reviewed, 10 authors, trial IRCT20200623047897N1.
|
risk of death, 66.7% lower, RR 0.33, p = 0.61, treatment 1 of 30 (3.3%), control 3 of 30 (10.0%), NNT 15.
|
|
Avdeev, 7/9/2021, retrospective, Russia, peer-reviewed, 4 authors, study period 12 April, 2020 - 20 June, 2020, average treatment delay 7.2 days.
|
risk of death, 69.4% lower, RR 0.31, p = 0.34, treatment 1 of 24 (4.2%), control 3 of 22 (13.6%), NNT 11.
|
|
risk of mechanical ventilation, 77.1% lower, RR 0.23, p = 0.18, treatment 1 of 24 (4.2%), control 4 of 22 (18.2%), NNT 7.1.
|
|
risk of ICU admission, 77.1% lower, RR 0.23, p = 0.18, treatment 1 of 24 (4.2%), control 4 of 22 (18.2%), NNT 7.1.
|
|
hospitalization time, 15.4% lower, relative time 0.85, p = 0.01, treatment 24, control 22.
|
|
de Alencar, 9/23/2020, Double Blind Randomized Controlled Trial, placebo-controlled, Brazil, peer-reviewed, median age 59.0, 65 authors, study period 10 April, 2020 - 25 May, 2020, average treatment delay 7.0 days.
|
risk of death, 2.6% higher, RR 1.03, p = 0.94, treatment 9 of 67 (13.4%), control 9 of 68 (13.2%), odds ratio converted to relative risk.
|
|
risk of mechanical ventilation, 16.0% higher, RR 1.16, p = 0.64, treatment 16 of 67 (23.9%), control 14 of 68 (20.6%), odds ratio converted to relative risk.
|
|
risk of ICU admission, 8.5% lower, RR 0.91, p = 0.65, treatment 29 of 67 (43.3%), control 32 of 68 (47.1%), NNT 26, odds ratio converted to relative risk.
|
|
ICU time, 12.5% higher, relative time 1.12, p = 0.56, treatment 67, control 68.
|
|
hospitalization time, 10.0% higher, relative time 1.10, p = 0.87, treatment 67, control 68.
|
|
Delić, 5/28/2022, Randomized Controlled Trial, Croatia, peer-reviewed, 12 authors, study period October 2020 - June 2021, trial NCT04755972 (history).
|
risk of death, 13.5% lower, RR 0.86, p = 0.37, treatment 24 of 39 (61.5%), control 37 of 52 (71.2%), NNT 10, ICU mortality.
|
|
risk of death, 9.7% lower, RR 0.90, p = 0.67, treatment 21 of 39 (53.8%), control 31 of 52 (59.6%), NNT 17, 28 day mortality.
|
|
Fariña-González, 5/31/2022, retrospective, Spain, peer-reviewed, 8 authors, study period 5 March, 2020 - 30 April, 2020.
|
risk of death, 39.0% lower, RR 0.61, p = 0.08, treatment 10 of 38 (26.3%), control 44 of 102 (43.1%), NNT 5.9.
|
|
Faverio, 12/2/2021, retrospective, Italy, peer-reviewed, 10 authors, study period February 2020 - April 2021, trial NCT04424992 (history) (STORM).
|
risk of death, 19.0% higher, RR 1.19, p = 0.33, treatment 91 of 572 (15.9%), control 44 of 329 (13.4%), propensity score weighting.
|
|
risk of ICU admission, 33.8% higher, RR 1.34, p = 0.08, treatment 107 of 572 (18.7%), control 46 of 329 (14.0%), propensity score weighting.
|
|
risk of no hospital discharge, 1.4% lower, RR 0.99, p = 0.94, treatment 180 of 572 (31.5%), control 105 of 329 (31.9%), NNT 224, propensity score weighting.
|
|
Galindo-Andúgar, 7/21/2023, retrospective, Spain, peer-reviewed, median age 73.3, 6 authors, study period March 2020 - April 2020.
|
risk of death, 43.0% lower, OR 0.57, p = 0.05, treatment 199, control 179, adjusted per study, multivariable, RR approximated with OR.
|
|
Gamarra-Morales, 5/8/2023, Randomized Controlled Trial, Spain, peer-reviewed, 8 authors, study period 1 March, 2020 - 1 June, 2020.
|
risk of death, 15.7% lower, RR 0.84, p = 0.49, treatment 25 of 72 (34.7%), control 28 of 68 (41.2%), NNT 15.
|
|
Gaynitdinova, 2/19/2021, Randomized Controlled Trial, Russia, peer-reviewed, 6 authors, average treatment delay 7.0 days.
|
hospitalization time, 15.4% lower, relative time 0.85, p < 0.001, treatment 24, control 22.
|
|
relative improvement in lung Ct, 50.7% better, RR 0.49, p < 0.001, treatment 24, control 22.
|
|
Izquierdo, 1/27/2022, retrospective, Spain, peer-reviewed, 7 authors, study period 1 March, 2020 - 24 January, 2021, excluded in exclusion analyses:
significant unadjusted confounding possible.
|
risk of death, 25.6% lower, RR 0.74, p < 0.001, treatment 136 of 2,071 (6.6%), control 1,935 of 17,137 (11.3%), adjusted per study, odds ratio converted to relative risk, multivariable.
|
|
Jin, 6/27/2026, retrospective, China, peer-reviewed, 3 authors, study period December 2022 - January 2023.
|
risk of death, 59.0% lower, HR 0.41, p = 0.17, treatment 88, control 88, propensity score matching, Cox proportional hazards, day 90.
|
|
risk of death, 54.7% lower, HR 0.45, p = 0.33, treatment 88, control 88, propensity score matching, Cox proportional hazards, day 28.
|
|
HFNC or mechanical ventilation, 12.1% lower, OR 0.88, p = 0.76, treatment 88, control 88, adjusted per study, propensity score matching, multivariable, RR approximated with OR.
|
|
risk of progression, 70.8% lower, OR 0.29, p = 0.01, treatment 88, control 88, adjusted per study, mortality or disease progression during hospitalization, propensity score matching, multivariable, RR approximated with OR.
|
|
Mousapour, 6/20/2022, Double Blind Randomized Controlled Trial, placebo-controlled, Iran, peer-reviewed, mean age 62.1, 5 authors, trial IRCT20210726051995N1.
|
risk of death, 2.4% lower, RR 0.98, p = 1.00, treatment 4 of 42 (9.5%), control 4 of 41 (9.8%), NNT 430, day 14.
|
|
risk of mechanical ventilation, 26.8% lower, RR 0.73, p = 0.57, treatment 6 of 42 (14.3%), control 8 of 41 (19.5%), NNT 19, day 14.
|
|
risk of no improvement, 6.1% lower, RR 0.94, p = 0.82, treatment 25 of 42 (59.5%), control 26 of 41 (63.4%), NNT 26, day 14.
|
|
risk of no hospital discharge, 5.4% lower, RR 0.95, p = 0.80, treatment 31 of 42 (73.8%), control 32 of 41 (78.0%), NNT 24, day 14.
|
|
Panahi, 12/19/2022, Randomized Controlled Trial, Iran, peer-reviewed, 7 authors, study period May 2021 - August 2021, trial IRCT20080901001165N55, excluded in exclusion analyses:
large difference in mortality vs. ICU results, significant baseline differences.
|
risk of death, 91.8% lower, RR 0.08, p < 0.001, treatment 4 of 125 (3.2%), control 49 of 125 (39.2%), NNT 2.8, Inhaled.
|
|
risk of ICU admission, 35.7% lower, RR 0.64, p = 0.38, treatment 9 of 125 (7.2%), control 14 of 125 (11.2%), NNT 25, Inhaled.
|
|
hospitalization time, 0.8% lower, relative time 0.99, p = 0.81, treatment 125, control 125, Inhaled.
|
|
Pellegrini, 5/23/2021, retrospective, USA, peer-reviewed, 10 authors, study period March 2020 - May 2020.
|
risk of death, 51.7% lower, OR 0.48, p < 0.001, treatment 138, control 726, adjusted per study, inverted to make OR<1 favor treatment, multivariable, RR approximated with OR.
|
|
Pourhoseingholi, 5/26/2021, prospective, Iran, preprint, mean age 57.9, 11 authors, study period 2 February, 2020 - 20 July, 2020, average treatment delay 7.4 days.
|
risk of death, 11.0% lower, HR 0.89, p = 0.43, treatment 65 of 309 (21.0%), control 274 of 2,159 (12.7%), adjusted per study, multivariable, Cox proportional hazards.
|
|
Rahimi, 10/8/2022, Single Blind Randomized Controlled Trial, Iran, peer-reviewed, 10 authors.
|
risk of death, 33.3% lower, RR 0.67, p = 0.19, treatment 10 of 20 (50.0%), control 15 of 20 (75.0%), NNT 4.0.
|
|
hospitalization time, 7.5% lower, relative time 0.92, p = 0.63, treatment 20, control 20.
|
|
Ramadhan, 12/27/2021, prospective, Indonesia, peer-reviewed, 6 authors, study period June 2020 - July 2021, excluded in exclusion analyses:
excessive unadjusted differences between groups.
|
risk of death, 134.7% higher, RR 2.35, p = 0.68, treatment 11 of 75 (14.7%), control 1 of 16 (6.2%), unadjusted.
|
|
Sherkawy, 6/1/2023, Randomized Controlled Trial, Egypt, peer-reviewed, 5 authors, study period March 2021 - April 2022, trial NCT04792021 (history).
|
risk of death, no change, RR 1.00, p = 1.00, treatment 1 of 30 (3.3%), control 1 of 30 (3.3%).
|
|
risk of oxygen therapy, 15.0% lower, RR 0.85, p = 0.60, treatment 17 of 30 (56.7%), control 20 of 30 (66.7%), NNT 10.
|
|
oxygen time, 33.3% lower, relative time 0.67, p = 0.005, treatment 30, control 30.
|
|
hospitalization time, 12.5% lower, relative time 0.88, p = 0.45, treatment 30, control 30.
|
|
Taher, 6/10/2021, Double Blind Randomized Controlled Trial, Iran, peer-reviewed, 6 authors, study period June 2020 - February 2021, average treatment delay 7.0 days.
|
risk of death, 17.9% lower, RR 0.82, p = 0.65, treatment 12 of 47 (25.5%), control 14 of 45 (31.1%), NNT 18.
|
|
risk of mechanical ventilation, 13.8% lower, RR 0.86, p = 0.67, treatment 18 of 47 (38.3%), control 20 of 45 (44.4%), NNT 16.
|
|
ICU time, 20.0% lower, relative time 0.80, p = 0.48, treatment 47, control 45.
|
|
hospitalization time, 33.3% lower, relative time 0.67, p = 0.31, treatment 47, control 45.
|
|
risk of no recovery, 14.5% lower, RR 0.85, p = 0.41, treatment 25 of 47 (53.2%), control 28 of 45 (62.2%), NNT 11.
|
|
Çavuş, 10/25/2022, retrospective, Turkey, peer-reviewed, 2 authors, study period April 2020 - September 2020, excluded in exclusion analyses:
unadjusted results with no group details.
|
risk of death, 13.3% higher, RR 1.13, p = 0.47, treatment 52 of 97 (53.6%), control 44 of 93 (47.3%).
|
|
risk of mechanical ventilation, 19.8% higher, RR 1.20, p = 0.25, treatment 55 of 97 (56.7%), control 44 of 93 (47.3%).
|
|
ICU time, 12.5% lower, relative time 0.88, p = 0.58, treatment 97, control 93.
|
|
hospitalization time, 13.3% lower, relative time 0.87, p = 0.09, treatment 97, control 93.
|
Effect extraction follows pre-specified rules as detailed above
and gives priority to more serious outcomes.
For pooled analyses, the first (most serious) outcome is used, which may
differ from the effect a paper focuses on.
Other outcomes are used in outcome specific analyses.