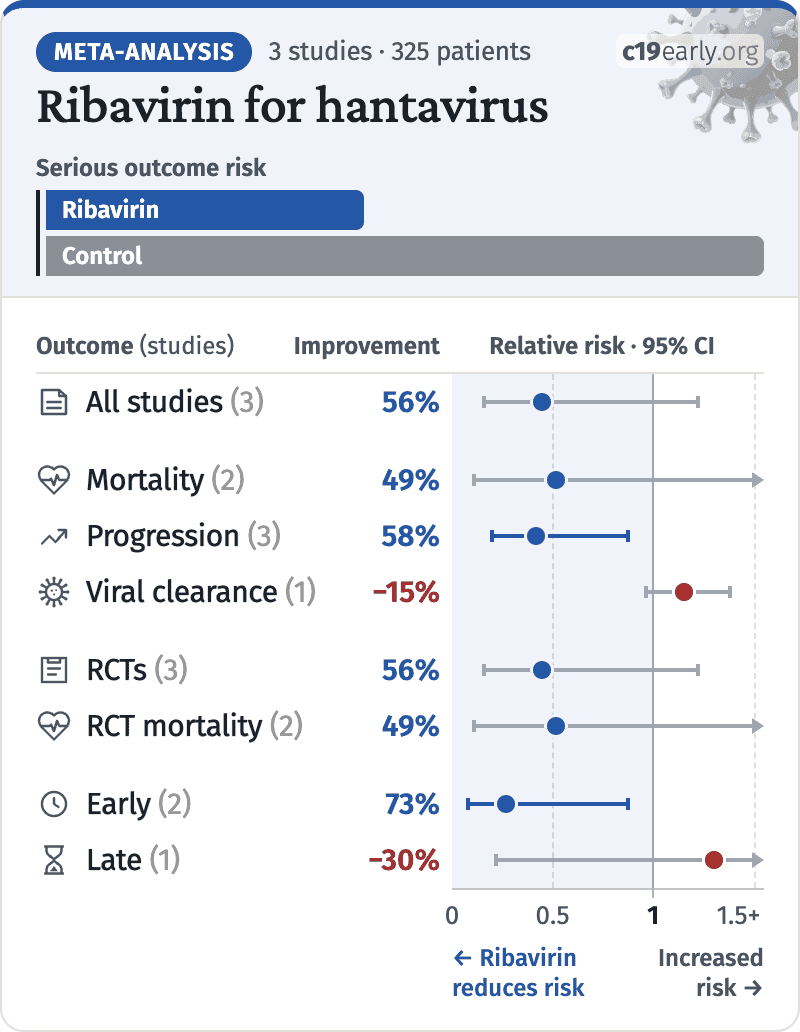
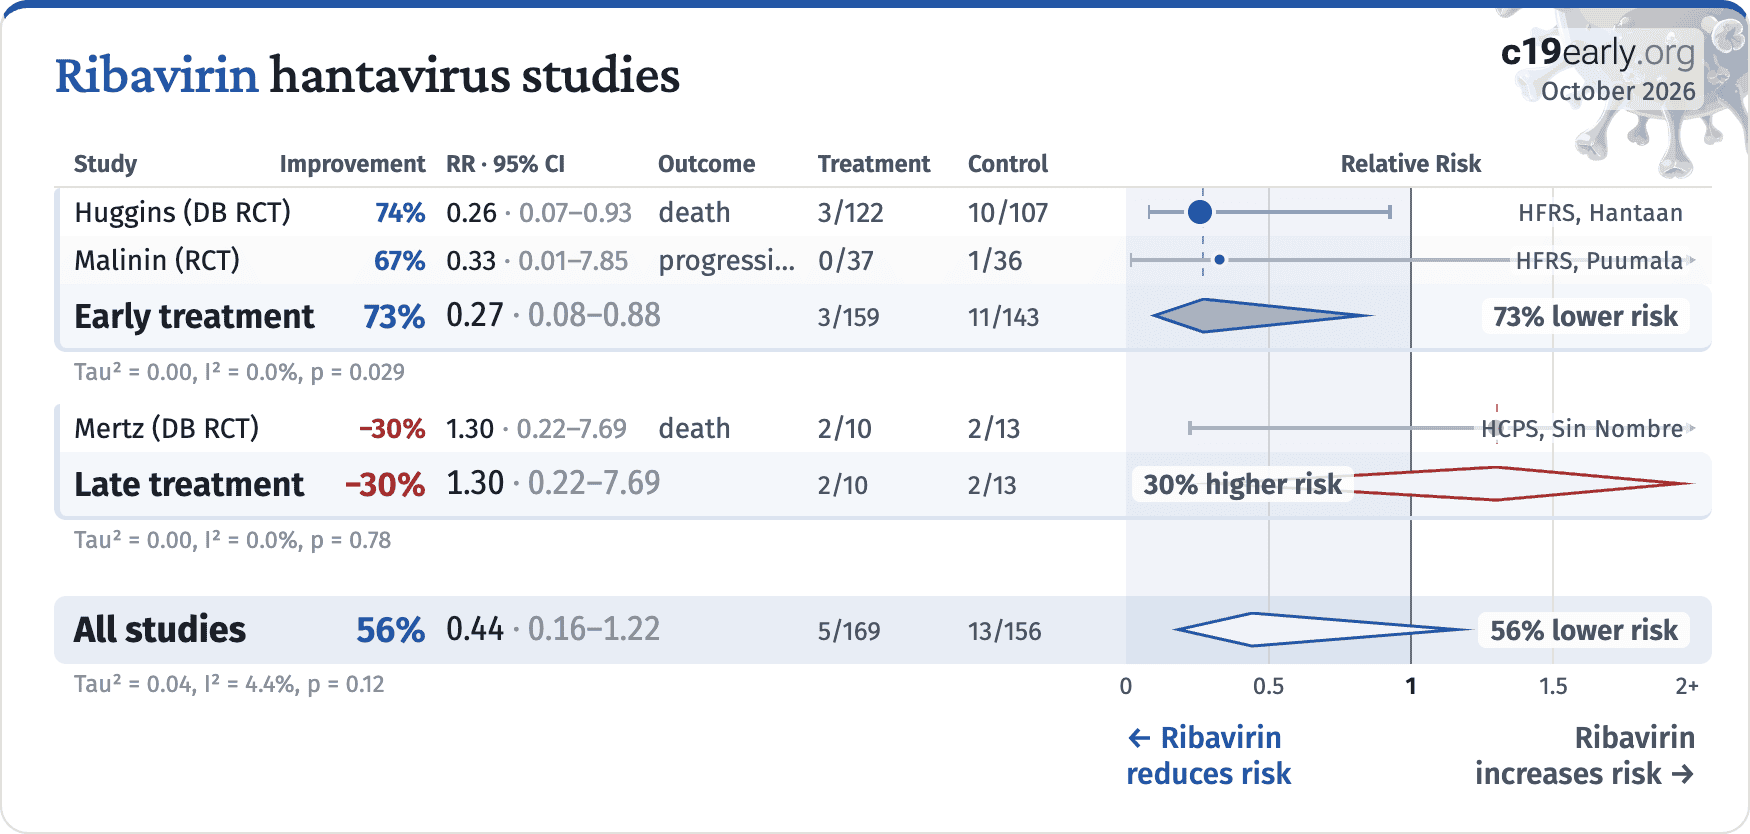
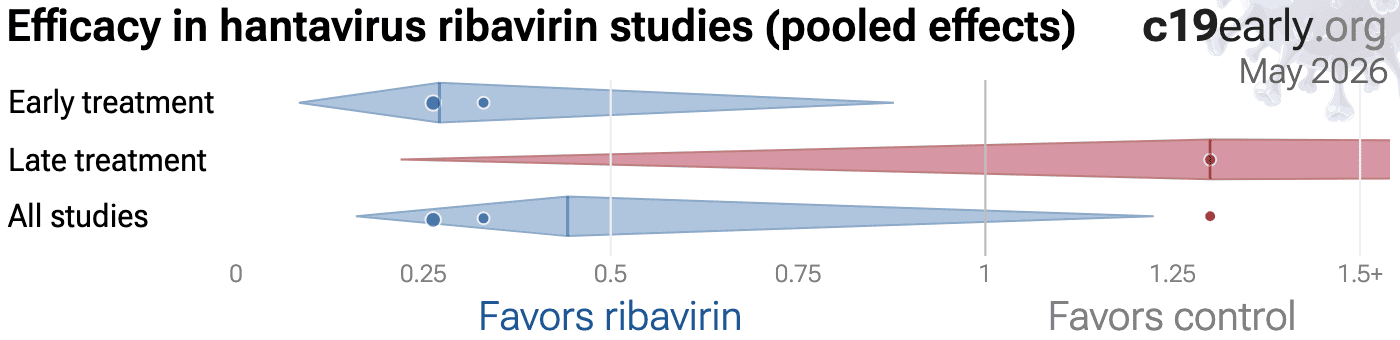
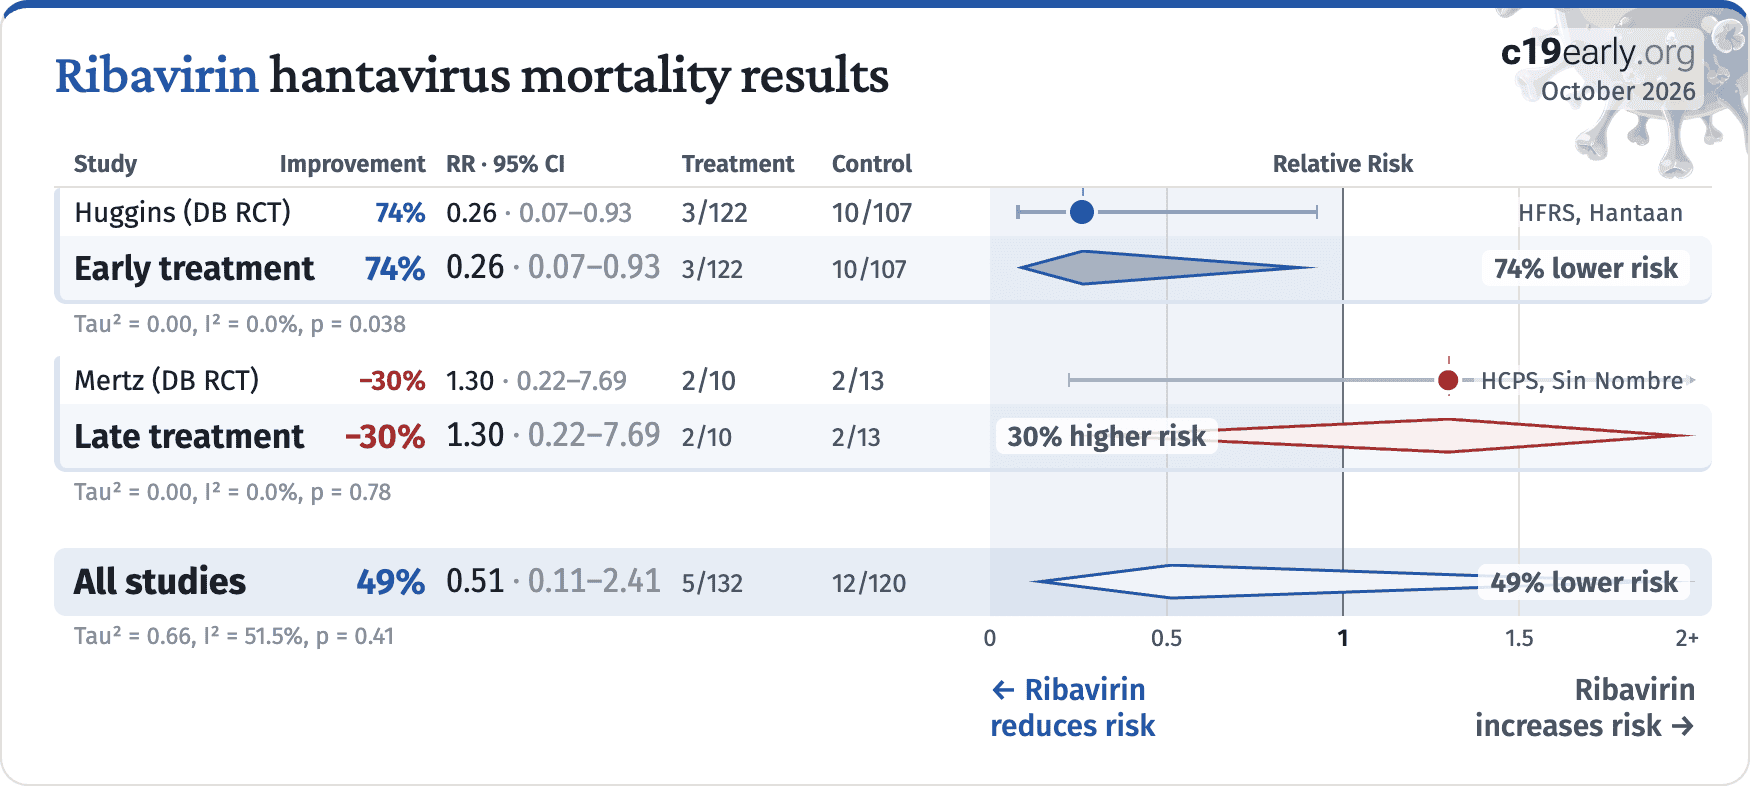
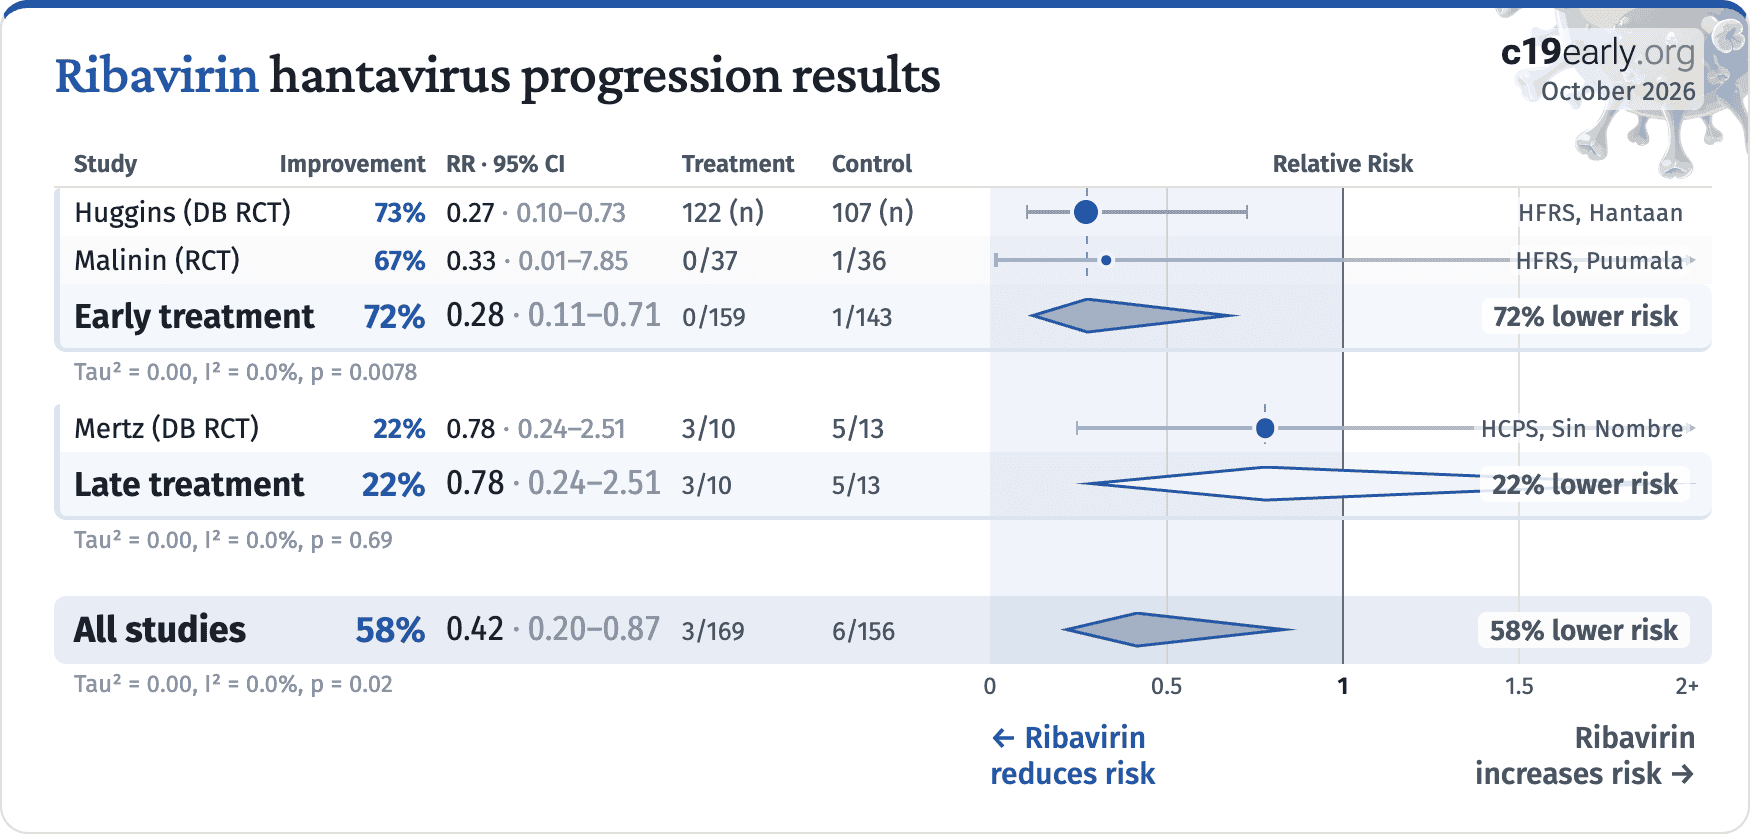
Huggins et al. shows efficacy of intravenous ribavirin for reducing
mortality and the incidence of oliguria when administered early in Hemorrhagic Fever with
Renal Syndrome (HFRS), however efficacy for Hantavirus Cardiopulmonary Syndrome (HCPS)
remains unknown.
Mechanistically, ribavirin inhibits the replication of both Old and New World
hantaviruses
in vitro, however, no clinical trial has evaluated early
(prodromal) treatment for HCPS.
Intravenous administration of ribavirin achieves therapeutic antiviral concentrations in
the lungs, however, ribavirin is a prodrug that may require days of continuous infusion to
reach steady-state, active intracellular levels. Therefore, rapid identification of cases
and earlier initiation of treatment may critical for HCPS.
For HFRS,
Huggins et al. note that
"early treatment (initiated on or before day 4
of illness) resulted in a more pronounced treatment effect".
Additionally, because ribavirin is primarily eliminated via the kidneys, it naturally
concentrates at much higher levels in renal tissue, potentially providing a therapeutic
advantage for HFRS that is not mirrored in the pulmonary-centric pathogenesis of HCPS.
Use of intravenous ribavirin is constrained by its substantial toxicity
profile, notably the induction of a pronounced, though generally reversible, hemolytic
anemia. Because the early, prodromal symptoms of severe hantavirus infections are
virtually indistinguishable from common, benign viral illnesses, empirical treatment
risks inflicting severe hematological toxicity on patients who do not actually
have the disease. Risk-benefit analysis recommends against the presumptive use of
high-dose intravenous ribavirin. Administration may only be recommended for cases where
the infection is definitively confirmed via diagnostics such as PCR, and where the patient
faces a significant risk that outweighs the drug's established adverse hematological
effects.
Summary statistics from
meta-analysis necessarily lose information. As with all meta-analyses, studies
are heterogeneous, with differences
in treatment delay, treatment regimen, patient demographics, variants,
conflicts of interest, standard of care, and other factors. We provide analyses for specific
outcomes and by treatment delay, and we aim to identify key characteristics in
the forest plots and summaries. Results should be viewed in the context of
study characteristics.
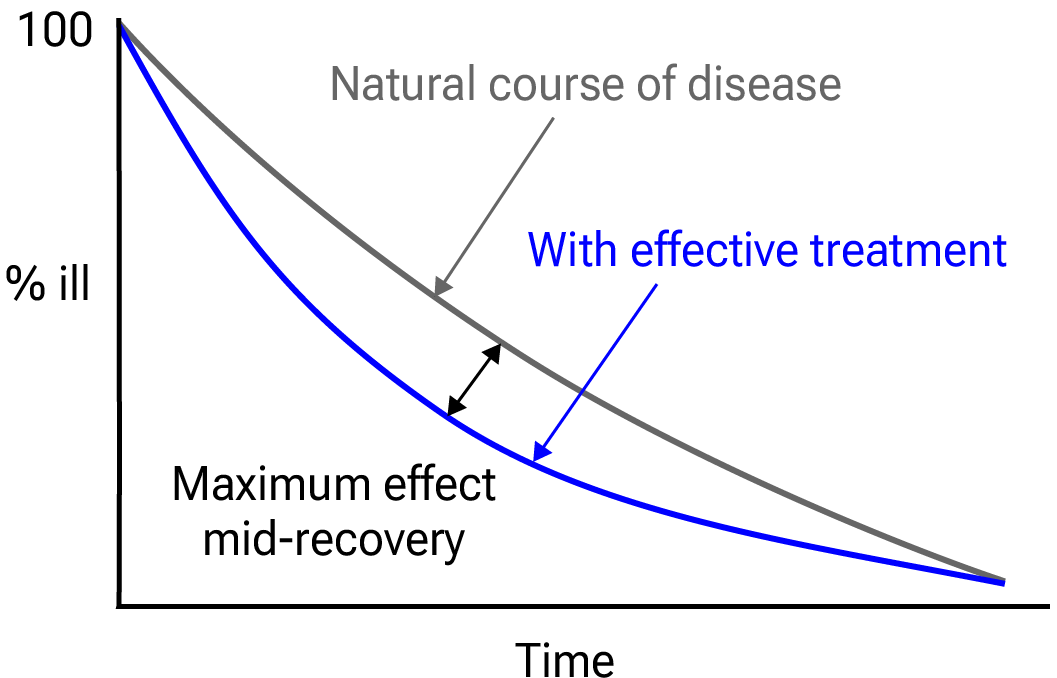
Details of treatment delay per patient is often not available.
For example, a study may treat 90% of patients relatively early, but the
events driving the outcome may come from 10% of patients treated very late.
Comparison across treatments is confounded by differences in
the studies performed, for example dose, variants, and conflicts of interest.
Trials with conflicts of interest may use designs better suited to the
preferred outcome.
In some cases, the most serious outcome has very few events,
resulting in lower confidence results being used in pooled analysis, however
the method is simpler and more transparent. This is less critical as the
number of studies increases. Restriction to outcomes with sufficient power may
be beneficial in pooled analysis and improve accuracy when there are few
studies, however we maintain our pre-specified method to avoid any
retrospective changes.
Studies show that combinations of treatments can be highly
synergistic and may result in many times greater efficacy than individual
treatments alone
2-26.
Therefore standard of care may be critical and benefits may diminish or
disappear if standard of care does not include certain treatments.
This real-time analysis is constantly updated based on
submissions. Accuracy benefits from widespread review and submission of
updates and corrections from reviewers. Less popular treatments may receive
fewer reviews.
No treatment or intervention is 100% available and
effective for all current and future variants. Efficacy may vary significantly
with different variants and within different populations. All treatments have
potential side effects. Propensity to experience side effects may be predicted
in advance by qualified physicians. We do not provide medical advice. Before
taking any medication, consult a qualified physician who can compare all
options, provide personalized advice, and provide details of risks and
benefits based on individual medical history and situations.