Molnupiravir Use and Severe Covid-19 Outcomes During the Omicron Surge

Arbel et al., Research Square, doi:10.21203/rs.3.rs-2115769/v1, Sep 2022
Early treatmentRetrospective ยท 19,868 patients ยท Israel ยท Jan โ€“ Mar 2022
Molnupiravir for COVID-19
Lower mortality and hospitalization
p = 0.0079 (mortality) and p = 0.014 (hospitalization)
Retrospective 19,868 patients eligible for molnupiravir treatment in Israel with 1,069 treated, showing lower mortality and hospitalization with treatment for the subgroup of patients โ‰ฅ65, and higher mortality for patients 40-64. Authors only provide subgroup results.
Confounding by treatment propensity. This study analyzes a population where only a fraction of eligible patients received the treatment. Patients receiving treatment may be more likely to follow other recommendations, more likely to receive additional care, and more likely to use additional treatments that are not tracked in the data (e.g., nasal/oral hygiene1,2, vitamin D3, etc.) — either because the physician recommending molnupiravir also recommended them, or because the patient seeking out molnupiravir is more likely to be familiar with the efficacy of additional treatments and more likely to take the time to use them. Therefore, these kind of studies may overestimate efficacy.
Potential risks of molnupiravir include the creation of dangerous variants, and mutagenicity, carcinogenicity, teratogenicity, and embryotoxicity4-18. Multiple analyses have identified variants potentially created by molnupiravir19-23. Studies show significantly increased risk of acute kidney injury24, cardiovascular toxocity25, and neurological symptoms24. Treatment may increase viral rebound26,27.
OutcomeImprovementEffect ยท pTreatmentControl
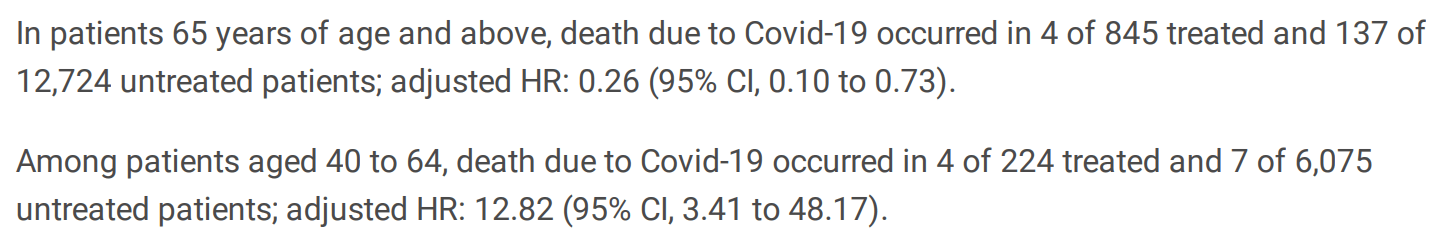
risk of death 74.0% lower ยท HR 0.26 ยท p = 0.008** 74.0% lowerHR 0.26p = 0.008** 4 of 845 (0.5%) 137 of 12,724 (1.1%) treatment 4 of 845 (0.5%), control 137 of 12,724 (1.1%)adjusted per studymultivariableCox proportional hazardsage 65+
risk of death 1182.0% higher ยท HR 12.82 ยท p < 0.001*** 1182.0% higherHR 12.82p < 0.001*** 4 of 224 (1.8%) 7 of 6,075 (0.1%) treatment 4 of 224 (1.8%), control 7 of 6,075 (0.1%)adjusted per studymultivariableCox proportional hazardsage 40-64
risk of hospitalization 45.0% lower ยท HR 0.55 ยท p = 0.01* 45.0% lowerHR 0.55p = 0.01* 18 of 845 (2.1%) 513 of 12,724 (4.0%) treatment 18 of 845 (2.1%), control 513 of 12,724 (4.0%)NNT 53adjusted per studymultivariableCox proportional hazardsage 65+
risk of hospitalization 80.0% higher ยท HR 1.80 ยท p = 0.12 80.0% higherHR 1.80p = 0.12 8 of 224 (3.6%) 97 of 6,075 (1.6%) treatment 8 of 224 (3.6%), control 97 of 6,075 (1.6%)adjusted per studymultivariableCox proportional hazardsage 40-64

Effect extraction follows pre-specified rules prioritizing more serious outcomes. Submit updates. * p < 0.05   ** p < 0.01   *** p < 0.001

Arbel et al., 29 Sep 2022, retrospective, Israel, preprint, 16 authors, study period 16 January, 2022 - 31 March, 2022. Contact: ronen.arbel@gmail.com.
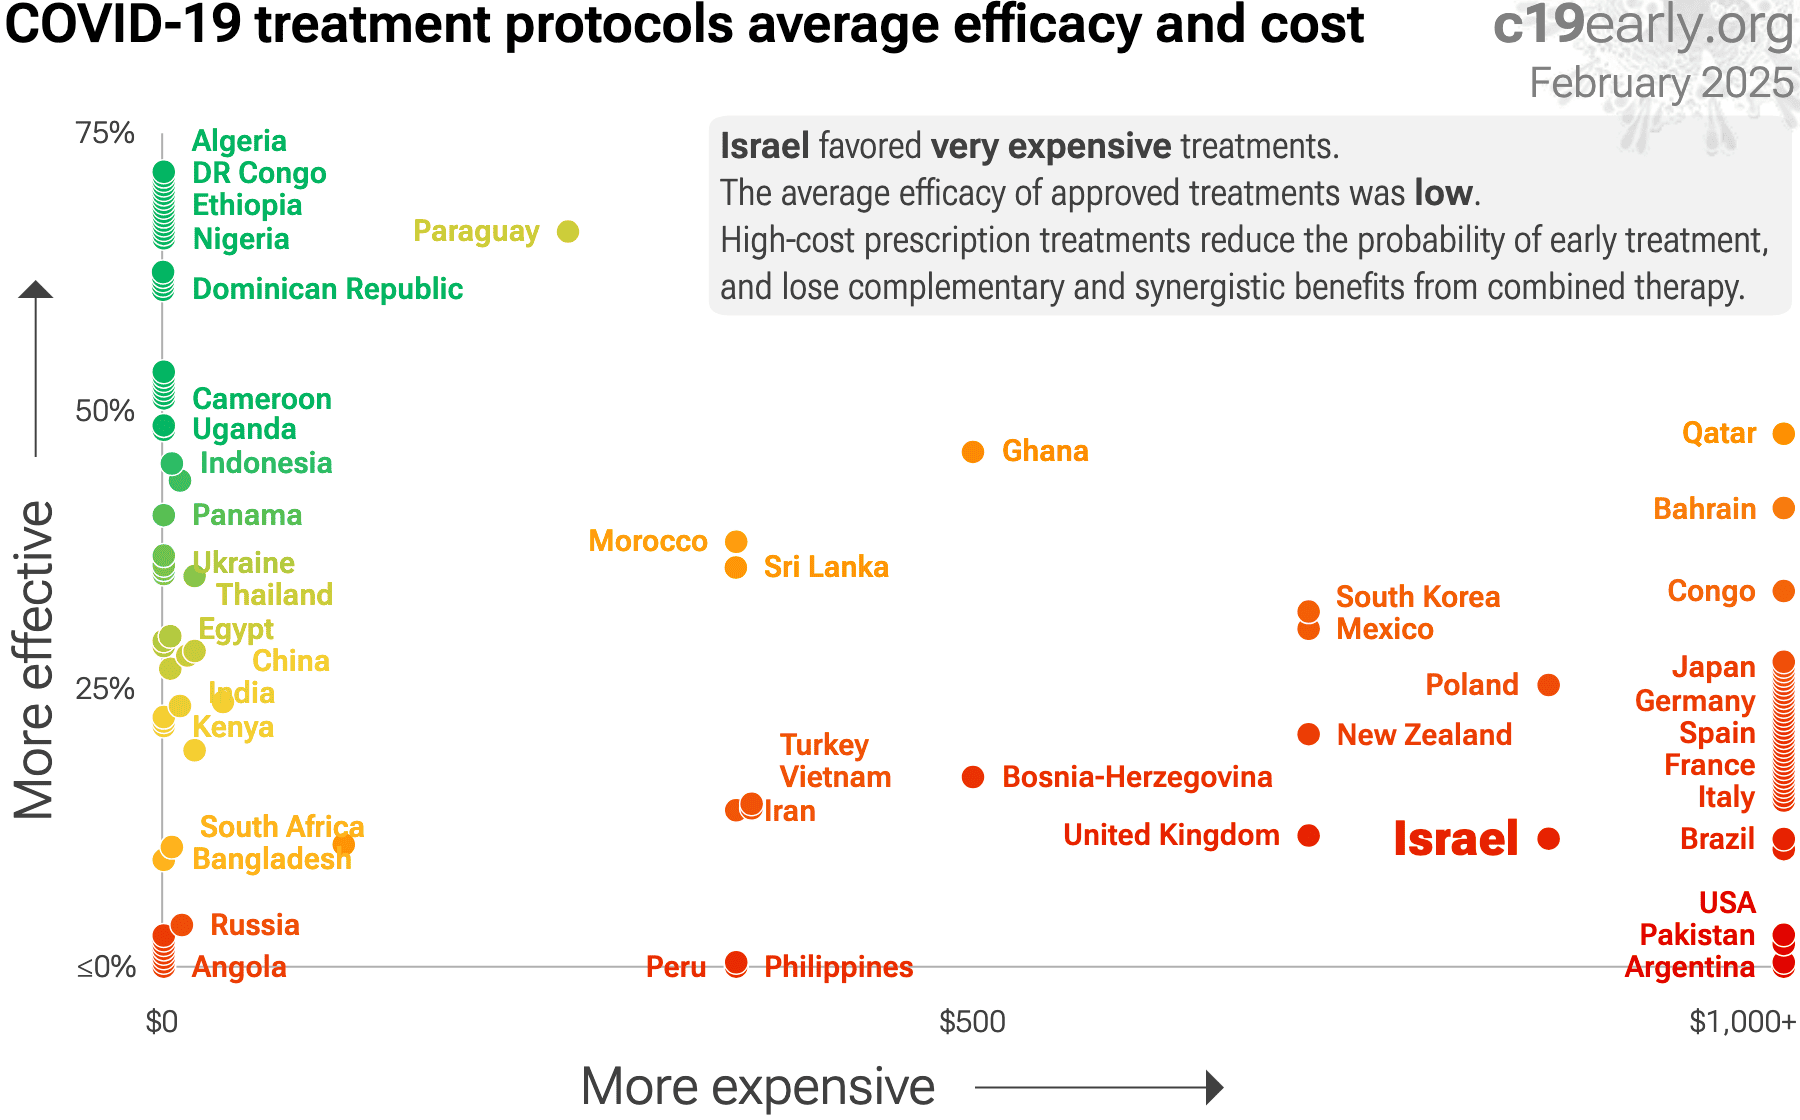
$0 $500 $1,000+ Efficacy vs. cost for COVID-19 treatment protocols c19early.org November 2026 Israel Angola Colombia Kenya Mozambique Myanmar South Africa Peru Philippines USA Brazil France Italy Canada Pakistan Spain Vietnam Japan Nepal Iran Bangladesh Ethiopia Ghana Germany Mexico South Korea United Kingdom Saudi Arabia Algeria Morocco Yemen Poland Uzbekistan India China Venezuela DR Congo Madagascar Thailand Uganda Egypt Nigeria Taiwan Fiji Zambia Bosnia-Herzegovina Dominican Republic Bolivia Cรดte d'Ivoire Eritrea Togo Bulgaria Greece Slovakia Iceland New Zealand Mongolia Czechia Belarus Haiti Hong Kong Qatar Panama Serbia Israel favored high-profit treatments.The average efficacy of treatments was moderate.High-cost protocols reduce early treatment, andforgo complementary/synergistic benefits. More effective More expensive 75% 50% 25% โ‰ค0%
$0 $500 $1,000+ Efficacy vs. cost for COVID-19treatment protocols worldwide c19early.org November 2026 Israel Angola Colombia Kenya Mozambique Myanmar South Africa Peru Philippines USA Brazil France Italy Canada Pakistan Spain Vietnam Japan Iran Bangladesh Ethiopia Ghana Germany Mexico South Korea United Kingdom Algeria Morocco Yemen Poland Uzbekistan India China Venezuela DR Congo Madagascar Thailand Uganda Egypt Taiwan Fiji Zambia Dominican Rep. Bolivia Cรดte d'Ivoire Eritrea Togo Sri Lanka Bulgaria Greece Slovakia New Zealand Czechia Belarus Qatar Panama Serbia Israel favored high-profit treatments.The average efficacy was moderate.High-cost protocols reduce early treatment,and forgo complementary/synergistic benefits. More effective More expensive 75% 50% 25% โ‰ค0%
Molnupiravir Use and Severe Covid-19 Outcomes During the Omicron Surge
Ronen Arbel, Yael Wolff Sagy, Erez Battat, Gil Lavie, Ruslan Sergienko, Michael Friger, Alon Peretz, Shlomit Yaron, Danielle Serby, Ariel Hammerman, Doron Netzer
doi:10.21203/rs.3.rs-2115769/v1
Background The oral antiviral molnupiravir is moderately effective in high-risk, unvaccinated non-hospitalized patients infected with early variants of SARS-CoV-2. Data regarding the effectiveness of molnupiravir against the B.1.1.529 (omicron) variant and in vaccinated populations are limited. Methods We obtained data for all members of Clalit Health Services, 40 years of age and older, eligible for molnupiravir therapy during the omicron surge. A Cox proportional-hazards regression model with timedependent covariates was used to estimate the association between molnupiravir treatment and hospitalizations and deaths due to Covid-19, with adjustment for sociodemographic factors, coexisting conditions, and prior Covid-19 immunity status. Results A total of 19,868 participants met the eligibility criteria, of whom 1,069 (5%) received molnupiravir during the study period. In patients 65 years and above, the rate of hospitalizations related to Covid-19 in treated compared to untreated patients was 74.6 versus 127.6 per 100,000 person-days; adjusted hazard ratio (HR) 0.55 (95% CI, 0.34 to 0.88). The adjusted HR for death due to Covid-19 was 0.26 (95% CI, 0.10 to 0.73). Among patients aged 40 to 64, the hospitalizations rate in treated compared to untreated patients was 125.8 versus 49.1 per 100,000 person-days; adjusted HR 1.80 (95% CI, 0.86 to 3.77). The adjusted HR for death was 12.8 (95% CI, 3.41 to 48.2). Conclusions In a cohort of non-hospitalized, omicron-infected high-risk patients, molnupiravir therapy was associated with a signi cant reduction in hospitalizations and mortality due to Covid-19 in patients 65 years and above. However, no evidence of bene t was found in younger adults.
This work did not receive any nancial or in-kind support. Con icts of Interest All authors report no Con icts of interest
References
Arbel, Sagy, Hoshen, Battat, Lavie et al., Nirmatrelvir Use and Severe Covid-19 Outcomes during the Omicron Surge, N Engl J Med, doi:10.1056/NEJMoa2204919
Bernal, Da Silva, Musungaie, Molnupiravir for Oral Treatment of Covid-19 in Non-hospitalized Patients, N Engl J Med
Li, Wang, Lavrijsen, SARS-CoV-2 Omicron variant is highly sensitive to molnupiravir, nirmatrelvir, and the combination, Cell Res, doi:10.1038/s41422-022-00618-w
Lรฉvesque, Hanley, Kezouh, Problem of immortal time bias in cohort studies: example using statins for preventing progression of diabetes, BMJ, doi:10.1136/bmj.b5087
Takashita, Kinoshita, Yamayoshi, E cacy of Antibodies and Antiviral Drugs against Covid-19 Omicron Variant, N Engl J Med, doi:10.1056/NEJMc2119407
Takashita, Kinoshita, Yamayoshi, E cacy of Antiviral Agents against the SARS-CoV-2 Omicron Subvariant BA.2, N Engl J Med, doi:10.1056/NEJMc2201933
Yip, Lui, Lai, Wong, Tse et al., Impact of the use of oral antiviral agents on the risk of hospitalization in community COVID-19 patients, Clin Infect Dis, doi:10.1093/cid/ciac687