COVIDOSE-2: A Multi-center, Randomized, Controlled Phase 2 Trial Comparing Early Administration of Low-dose Tocilizumab to Standard of Care in Hospitalized Patients With COVID-19 Pneumonitis Not Requiring Invasive Ventilation

Reid et al., NCT04479358, COVIDOSE-2, NCT04479358, Feb 2025
Late treatmentRCT · NCT04479358 · 85 patients · USA
Tocilizumab for COVID-19
COVIDOSE-2 Reid et al. NCT04479358 · February 2025
Trial underpowered for serious outcomes
RCT 85 patients in the USA showing no significant differences with tocilizumab treatment.
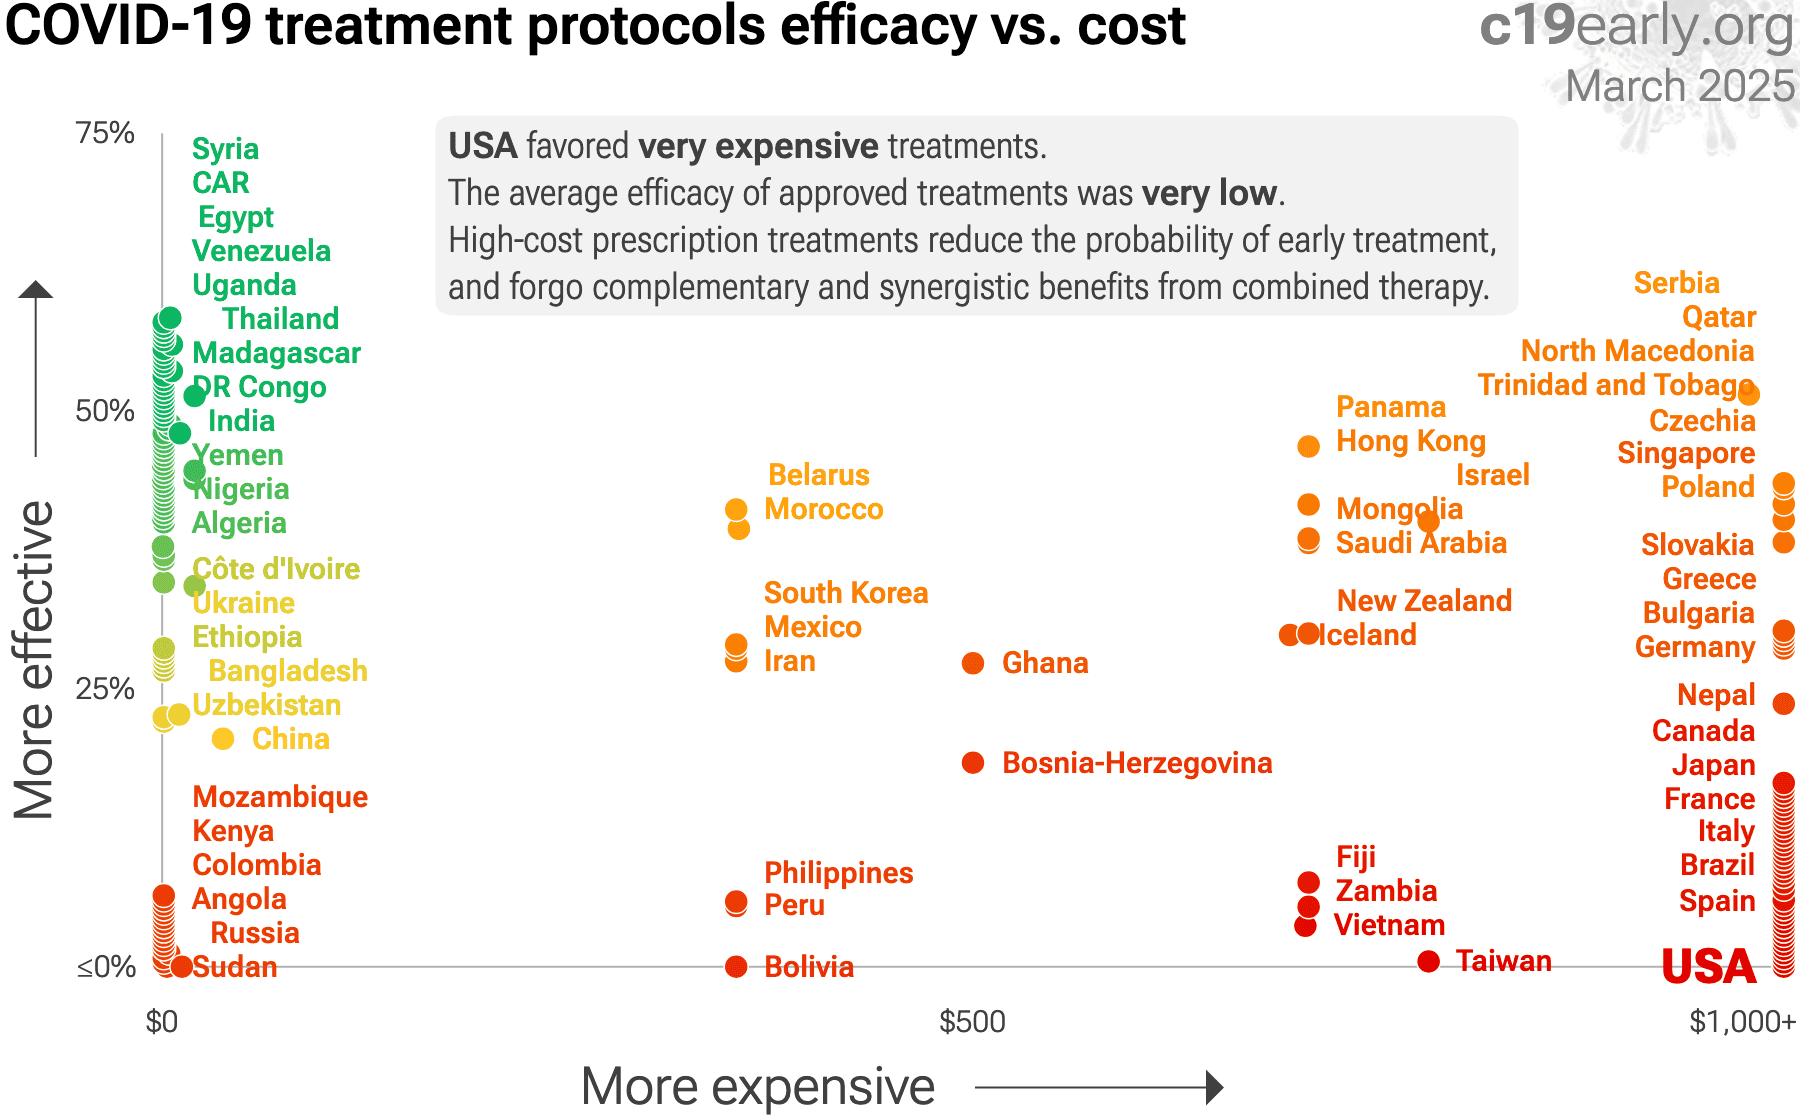
Standard of Care (SOC) for COVID-19 in the study country, the USA, is very poor with very low average efficacy for approved treatments1. Only expensive, high-profit treatments were approved for early treatment. Low-cost treatments were excluded, reducing the probability of early treatment due to access and cost barriers, and eliminating complementary and synergistic benefits seen with many low-cost treatments.
OutcomeImprovementEffect · pTreatmentControl
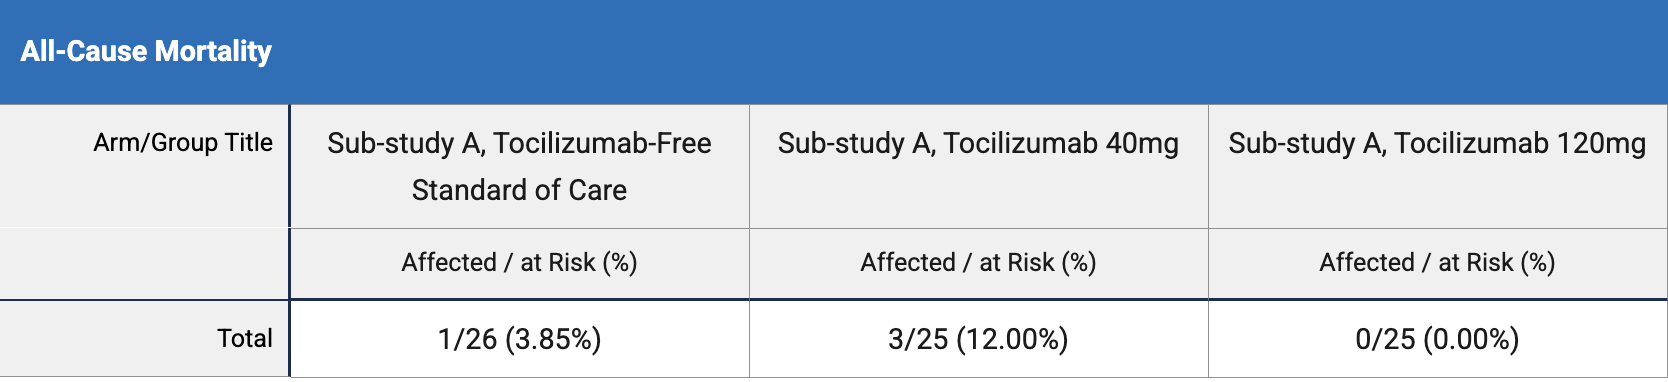
risk of death 56.0% higher · RR 1.56 · p = 1.00 56.0% higherRR 1.56p = 1.00 3 of 50 (6.0%) 1 of 26 (3.8%) treatment 3 of 50 (6.0%), control 1 of 26 (3.8%)all patients
risk of death 66.2% lower · RR 0.34 · p = 1.00 66.2% lowerRR 0.34p = 1.00 0 of 25 (0.0%) 1 of 26 (3.8%) treatment 0 of 25 (0.0%), control 1 of 26 (3.8%)120mgNNT 26continuity correction due to zero events
risk of death 212.0% higher · RR 3.12 · p = 0.35 212.0% higherRR 3.12p = 0.35 3 of 25 (12.0%) 1 of 26 (3.8%) treatment 3 of 25 (12.0%), control 1 of 26 (3.8%)40mg
recovery time 2.5% higher · relative time 1.02 · p = 0.94 2.5% higherrelative time 1.02p = 0.94 25 26 treatment 25, control 26all patients
recovery time 20.0% lower · relative time 0.80 · p = 0.09 20.0% lowerrelative time 0.80p = 0.09 4.0 [4.0-5.0] n=25 5.0 [4.0-6.0] n=26 treatment 4.0 [4.0-5.0] n=25, control 5.0 [4.0-6.0] n=26120mg
recovery time 40.0% higher · relative time 1.40 · p = 0.15 40.0% higherrelative time 1.40p = 0.15 7.0 [4.0-9.0] n=25 5.0 [4.0-6.0] n=26 treatment 7.0 [4.0-9.0] n=25, control 5.0 [4.0-6.0] n=2640mg
Effect extraction follows pre-specified rules prioritizing more serious outcomes. Submit updates.

Reid et al., 10 Feb 2025, Randomized Controlled Trial, USA, preprint, 1 author, trial NCT04479358 (history) (COVIDOSE-2). Contact: pankti.reid@bsd.uchicago.edu.
$0 $500 $1,000+ Efficacy vs. cost for COVID-19 treatment protocols c19early.org November 2026 USA Angola Colombia Kenya Mozambique Myanmar South Africa Peru Philippines Vietnam Japan Argentina Nepal Iran Bangladesh Ethiopia Ghana Germany Mexico South Korea United Kingdom Saudi Arabia Algeria Morocco Yemen Poland Uzbekistan India China Venezuela DR Congo Madagascar Thailand Uganda Egypt Nigeria Taiwan Fiji Zambia Bosnia-Herzegovina Jordan Georgia Switzerland Dominican Republic Bolivia Côte d'Ivoire Eritrea Togo Bulgaria Greece Slovakia Iceland New Zealand Trinidad and Tobago Mongolia Czechia Belarus Israel Haiti North Macedonia Hong Kong Qatar Panama Serbia USA favored high-profit treatments.The average efficacy of treatments was very low.High-cost protocols reduce early treatment, andforgo complementary/synergistic benefits. More effective More expensive 75% 50% 25% ≤0%
$0 $500 $1,000+ Efficacy vs. cost for COVID-19treatment protocols worldwide c19early.org November 2026 USA Angola Colombia Kenya Mozambique Myanmar South Africa Peru Philippines Vietnam Japan Argentina Nepal Iran Bangladesh Ethiopia Ghana Germany Mexico South Korea United Kingdom Saudi Arabia Algeria Morocco Yemen Poland Uzbekistan India China Venezuela DR Congo Madagascar Thailand Uganda Egypt Taiwan Fiji Zambia Jordan Georgia Switzerland Dominican Rep. Bolivia Côte d'Ivoire Eritrea Togo Sri Lanka Bulgaria Greece Slovakia New Zealand Trinidad and Tobago Mongolia Czechia Belarus Israel North Macedonia Hong Kong Qatar Panama Serbia USA favored high-profit treatments.The average efficacy was very low.High-cost protocols reduce early treatment,and forgo complementary/synergistic benefits. More effective More expensive 75% 50% 25% ≤0%
Late treatment
is less effective